


Product Monograph - Taro-Metronidazole Gel
SUMMARY PRODUCT INFORMATION
- For a complete listing see Dosage Forms, Composition and Packaging section.
INDICATIONS AND CLINICAL USE
Taro-Metronidazole Gel (metronidazole gel) is indicated for:
- topical application in the treatment of inflammatory papules, pustules, and erythema of rosacea.
Taro-Metronidazole Gel contains an antibacterial ingredient, metronidazole. To reduce the development of drug-resistant bacteria and maintain the effectiveness of metronidazole, Taro-Metronidazole Gel should only be used for the authorized indication and clinical use.
Geriatrics (≥ 65 years of age):
While specific clinical trials in the geriatric population have not been conducted, 66 patients aged 65 years and older treated with metronidazole gel 1% over 10 weeks showed comparable safety and efficacy as compared to the general study population.
Pediatrics:
Safety and effectiveness in pediatrics have not been established.
CONTRAINDICATIONS
Taro-Metronidazole Gel (metronidazole gel) is contraindicated:
- in individuals with a history of hypersensitivity to metronidazole, or other ingredients of the formulations. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
WARNINGS AND PRECAUTIONS
General
Because of the minimal absorption of metronidazole, and consequently its insignificant plasma concentration after topical administration, the systemic adverse reactions reported with the oral form of the drug should not be expected with Taro-Metronidazole Gel (metronidazole gel).
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients* |
|---|---|---|
| Topical | metronidazole gel / 0.75% (w/w), 1 % (w/w) | methylparaben, propylparaben, propylene glycol and phenoxyethanol (in 1% gel only). |
Physicians should consider the most appropriate formulation for their patients.
Although rosacea is a chronic disease, data on the long-term use of metronidazole gel in rosacea is not available. In controlled clinical trials, patients were treated for up to12 weeks (see DOSAGE AND ADMINISTRATION section).
Carcinogenesis and Mutagenesis
Information from preclinical studies indicates that metronidazole and its principal metabolite are mutagenic in bacteria and that tumours were observed in animal studies after oral administration of metronidazole (see TOXICOLOGY section). The relevance of these findings to the topical use of metronidazole in humans is unknown. The anaerobic or hypoxic conditions that might lead to the production of genotoxic compounds are unlikely to occur in topical use. There is no conclusive evidence after 30 years of clinical use of systemic metronidazole for either a genotoxic or carcinogenic potential.
Hematologic
Metronidazole is a nitroimidazole and should be used with care in patients with evidence of, or history of, blood dyscrasia.
Ophthalmologic
Avoid contact with the eyes. Topical metronidazole has been reported to cause tearing of the eyes. It should not be used in or close to the eye. If contact does occur, flush with water.
Conjunctivitis associated with topical use of metronidazole on the face has been reported.
Sensitivity/Resistance
Exposure to excessive sunlight, including sunlamps and tanning beds, should be avoided when using metronidazole gel, based on studies in hairless mice treated with intraperitoneal metronidazole (see TOXICOLOGY section).
Skin
If a reaction suggesting local irritation occurs, patients should be directed to use the medication less frequently, discontinue use temporarily, or discontinue use until further instructions.
There were no reports of contact dermatitis attributed to metronidazole gel during clinical trials. However, there have been reports of contact dermatitis/allergic reaction reported as post marketing adverse reactions (see ADVERSE REACTIONS section). Physicians should be aware of the possibility of skin sensitivity reactions and of cross-sensitization with other imidazole preparations, such as clotrimazole and tioconazole.
Special Populations
Pregnant Women:
There has been no experience to date with the use of metronidazole gel in pregnant patients. Metronidazole crosses the placental barrier and enters the fetal circulation rapidly. No fetotoxicity was observed after oral metronidazole in rats or mice. However, because animal reproduction studies are not always predictive of human response, this drug should only be used during pregnancy after careful assessment of the risk/benefit ratio.
Nursing Women:
Even though metronidazole blood levels are significantly lower after topical application than after oral administration a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother. After oral administration, metronidazole is secreted in breast milk in concentrations similar to those found in the plasma.
Susceptibility/Resistance
Development of Drug Resistant Bacteria:
Prescribing Taro-Metronidazole Gel in the absence of the authorized indications is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The safety profile of metronidazole gel 0.75% and 1% has been established in clinical trials. The results of the safety analyses indicate topical application of metronidazole is well tolerated.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Metronidazole Gel 1%
In a 10-week controlled clinical trial in patients with rosacea, 557 patients used metronidazole gel 1% and 189 patients used the gel vehicle once daily. Among the treatment groups, the adverse reactions considered related to treatment were low with comparable frequencies. The majority of the adverse reactions were mild or moderate in severity.
Adverse reactions considered related to once daily treatment with metronidazole gel 1% were reported at a frequency of <1% and are summarized in the table 1 below.
Table 1: Adverse Reactions Attributed to Metronidazole Gel 1% †
| SYSTEM ORGAN CLASS / ADVERSE REACTIONS | INCIDENCE (NO. OF PATIENTS) | SEVERITY (NO. OF PATIENTS) | FOLLOW-UP TREATMENT |
|---|---|---|---|
| Skin and subcutaneous tissue | |||
| disorders | |||
| Dry skin | 0.9% (5) | mild (2) | treatment required |
| mild | none required | ||
| mild | none required* | ||
| moderate | none required** | ||
| Erythema | 0.7% (4) | moderate (3) | none required* |
| severe | treatment required* | ||
| Pruritus | 0.5% (3) | mild | none required* |
| moderate | none required* | ||
| severe | treatment required* | ||
| Skin burning sensation | 0.2% (1) | mild | none required** |
| Skin irritation | 0.2% (1) | severe | treatment required* |
| Rash papular | 0.4% (2) | mild | none required |
| moderate | none required* | ||
| Skin desquamation | 0.2% (1) | moderate | none required* |
| Skin tightness | 0.4% (2) | mild | none required** |
| Facial oedema | 0.2% (1) | severe | treatment required* |
| Urticaria | 0.2% (1) | moderate | treatment required* |
Eye Disorders Conjunctivitis Eye irritation | 0.4% (2) 0.2% (1) | mild mild mild | treatment required treatment required* none required |
Gastrointestinal Disorders Dyspepsia | 0.2% (1) | mild | treatment required |
† MedDRA version 9.0 has been used for coding of adverse reactions.
- drug discontinued
** therapy interrupted/reduced
Metronidazole Gel 0.75%
The patient safety database included 114 evaluable patients that participated in controlled and uncontrolled metronidazole gel trials. Adverse reactions attributed to the use of metronidazole gel are summarized in the table 2 below.
Table 2: Adverse Reactions Attributed to Metronidazole Gel 0.75%
| SYSTEM ORGAN CLASS / ADVERSE REACTIONS | INCIDENCE (NO. OF PATIENTS) | SEVERITY | FOLLOW-UP TREATMENT |
|---|---|---|---|
| Skin and subcutaneous disorders | |||
| Skin irritation | 1.8% (2) | mild | none required |
| Dry skin | 1.8% (2) | mild | none required |
| Erythema | 1.8% (2) | mild | none required |
| Burning sensation | 0.9% (1) | mild | none required |
Eye disorders Lacrimation increased | 0.9% (1) | mild | none required |
Post-Market Adverse Drug Reactions
Since commercialization of metronidazole gel (0.75%, 1%), the following post marketing adverse reactions have been reported.
A causal relationship with topical metronidazole has not been unequivocally established for these adverse drug reactions.
Post Marketing Adverse Drug Reactions by System Organ Class, MedDRA preferred term for Metronidazole Gel:
Blood and lymphatic disorders: Leucopenia Eye disorders: Lacrimation increased Gastrointestinal disorders: Dysgeusia, nausea
General disorders and administration: Condition aggravated
Immune system disorders: Hypersensitivity
Nervous system disorders: Paraesthesia
Skin and subcutaneous tissue disorders: Dermatitis contact, dry skin, erythema, pruritis, rash pustular, dermatitis bullous, skin burning sensation, skin irritation, skin exfoliation, swelling face
DRUG INTERACTIONS
Drug-Drug Interactions
Table 3: Established or Potential Drug-Drug Interactions
| Metronidazole | Ref | Effect | Clinical comment |
|---|---|---|---|
| Metronidazole | Ref | Effect | Clinical comment |
| Coumarin and warfarin | C/CT | Potentiate the anticoagulant effect | Drug interactions are less likely with topical administration but should be kept in mind when metronidazole is prescribed for patients who are receiving anticoagulant treatment. Oral metronidazole has been reported to potentiate the anticoagulant effect of coumarin and warfarin resulting in a prolongation of prothrombin time. |
| Alcohol | T (topical) C (oral) | Disulfiram-like reaction. | Oral metronidazole also interacts with alcohol, producing a disulfiram-like reaction. Although this adverse reaction has not been reported with topical application of metronidazole, a drug interaction of metronidazole-alcohol is a possibility. |
| Other imidazole preparations such as clotrimazole and tioconazole | T | Skin sensitivity | Physicians should be aware of the possibility of skin sensitivity reactions and of cross-sensitization with other imidazole preparations. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Taro-Metronidazole Gel 1%: Apply and rub in a thin film once daily to entire affected area(s).
Taro-Metronidazole Gel 0.75%: Apply and rub in a thin film twice daily, morning and evening, to entire affected areas.
Significant therapeutic results should be noticed within three weeks. Clinical studies have demonstrated continuing improvement through nine weeks of therapy. The dosage required for long-term administration is uncertain (see WARNINGS section).
Administration
Areas to be treated should be cleansed before application of Taro-Metronidazole Gel. The face must be dry before applying medication.
Patients may use cosmetics after application of Taro-Metronidazole Gel. The medication should have absorbed into the skin (“dry”) before the cosmetics are applied.
OVERDOSAGE
There is no human experience with overdosage of metronidazole gel. Topically applied metronidazole can be absorbed in sufficient amount to produce systemic effects. Do not exceed the recommended dose and duration of treatment.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669)
Massive ingestion may produce vomiting and slight disorientation. There is no specific antidote. Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Metronidazole gel preparations are particularly effective against the inf1ammatory, papulopustular component of rosacea. The mechanisms by which topical metronidazole acts in reducing inflammatory lesions of rosacea are unknown, but may include an anti-bacterial and/or an anti-inflammatory effect (see DETAILED PHARMACOLOGY section).
Pharmacokinetics
Serum metronidazole levels have been shown to be below detection limits (<25 ng/mL) at the majority of time points after administration of topical metronidazole. At the time points that it could be detected, topical metronidazole produced blood levels (Cmax 40.6 ng/mL) that were approximately 80% less than a similar dose administered orally (Cmax 212 ng/mL). Therefore, with normal usage, topical metronidazole results in minimal blood levels of metronidazole.
STORAGE AND STABILITY
Taro-Metronidazole Gel 1%: Store at room temperature (15º to 30ºC). Protect from light. Store in original container.
Taro-Metronidazole Gel 0.75%: Store at 15º to 30ºC. Do not freeze. Protect from light. Store in original container.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Taro-Metronidazole Gel 1% is supplied as 55 g of gel, packaged in a 60 mL high-density polyethylene (HDPE) bottle with a 22 mm white polypropylene (PP) pump.
Taro-Metronidazole Gel 0.75% is supplied as 60 g of gel, packaged in a 60 g laminated tube with top seal and a white polypropylene (PP) screw-on cap.
Composition:
Taro-Metronidazole Gel (metronidazole gel 1%)
It is a clear to translucent, colourless to pale yellow gel containing metronidazole 1% (w/w).
Non- medicinal ingredients: beta-cyclodextrine (Kleptose), edetate disodium, hydroxyethyl cellulose (Natrosol 250 HHX Pharma), methylparaben, niacinamide, phenoxyethanol, propylene glycol, propylparaben, and purified water.
Taro-Metronidazole Gel (metronidazole gel 0.75%)
It is a colourless to pale yellow gel containing metronidazole 0.75% (w/w).
Non- medicinal ingredients: carbomer homopolymer type C (carbopol 980), propylene glycol, edetate disodium, methylparaben, propylparaben, sodium hydroxide, purified water.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: metronidazole
Chemical name: 2-Methyl-5-nitroimidazole-1-ethanol
Molecular formula and molecular mass: C6H9N3O3, 171.2 g/mol
Structural formula:
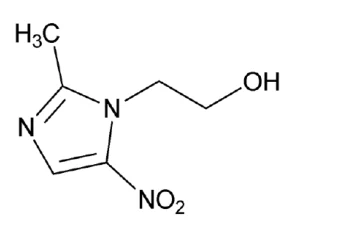
Physicochemical properties:
Description: Metronidazole is a white to pale yellow, crystalline powder.
Melting point: 159-163ºC
Solubility: It is slightly soluble in water, acetone, alcohol, methylene chloride.
pH: 5.5 – 7.5 (1% water)
CLINICAL TRIALS
Study Demographics and Trial Design
Metronidazole Gel 1%
Table 4: Summary of Patient Demographics for Clinical Trial in Rosacea for Metronidazole Gel 1%
| Study # | Trial design | Dosage, route of administration and duration | # Subjects by arm entered/ completed | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| 1 | Multicenter, randomized, investigator- blinded and vehicle-controlled, parallel comparison | Metronidazole gel 1%, topically to face, qd for 10 weeks Metronidazole gel vehicle, topically to face, qd for 10 weeks | 557/480 189/158 | 48.4 (18-92 yrs) 47.8 (22-81 yrs) | 149M/ 408F 48M/ 141F |
Safety and efficacy of metronidazole gel 1% have been demonstrated in a 10- week, randomized, vehicle-controlled trial in 746 patients with rosacea. Patients were treated once daily for ten weeks with metronidazole gel 1%, or with gel vehicle.
Patient demographics and disease history including age, sex, race, and duration of rosacea were not significantly different. The mean age was approximately 48 years and the percentage of patients over 65 years old was comparable in the treatment groups (10-12%). In each treatment group, more than 70% of patients were women and more than 86% were white. The mean disease duration for patients in the study was 7 to 8 years. Most patients had “moderate” rosacea at baseline.
Study Results
Metronidazole Gel 1%
Efficacy was determined by recording reduction in inflammatory lesion counts and success rate in the Investigator Global Assessment (percentage of subjects “clear” and “almost clear” of rosacea at the end of the study). The scale is based on the following definitions:
Investigator Global Assessment Scale
Score
Grade
Definition
0
Clear
No signs or symptoms present; at most, mild erythema
1
Almost Clear
Very mild erythema present. Very few small papules/pustules
2
Mild
Mild erythema. Several small papules/pustules
3
Moderate
Moderate erythema. Several small or large papules/pustules, and up to 2 nodules
4
Severe
Severe erythema. Numerous small and/or large papules/pustules, up to several nodules
The results are shown in the following table:
Table 5: Summary of clinical trial results for Metronidazole Gel 1%1
Inflammatory Lesion Counts and Global Scores in a Clinical Trial of Rosacea (ITT population)2
N
Metronidazole Gel 1%
Results (%)
N
Vehicle Results (%)
p-value4
Inflammatory lesion3
557
189
Baseline, mean count
18.3
18.4
Week-10, mean count
8.9
12.8
Reduction
Investigator Global Assessment5
557
9.4 (50.7)
189
5.6 (32.6)
<0.0001*
Subject clear or almost clear
214 (38.42)
52 (27.51)
0.0060*
Subject with no change
159 (28.5)
77 (40.7)
1Superiority of Metronidazole Ge, 1% over Metronidazole Gel Vehicle in the percent reduction in inflammatory lesion count for the Week 10 last observation carried forward (LOCF) analysis was also demonstrated for the PP (per protocol) populations (p<0.0001). For the Week 10 LOCF analysis, Metronidazole Gel 1% was also superior to the gel vehicle for the PP populations (p=0.0297).
2Intent to Treat Efficacy Population includes all patients randomized in the trial
3Papules + pustules + nodules
4Based on ANOVA for lesion analysis and Cochran-Mantel-Haenszel test for Investigator Global Assessment analysis
5Dichotomized success/failure where success = clear or almost clear and failure = mild, moderate or severe
- Statistically significant difference
Patients treated with metronidazole gel 1% experienced a mean reduction of 9.4 (50.7%) inflammatory lesions in the Week-10 last observation carried forward (LOCF) group, compared to a reduction of 5.6 (32.6%) for those treated with vehicle, or a difference in means of 3.8 lesions (p<0.0001).
Investigator Global Assessment of these same patients treated with metronidazole gel 1% showed 214 patients (38.4%) were clear or almost clear in the Week-10 LOCF group, in comparison with 52 (27.5%) who were clear or almost clear in the vehicle group (p=0.0060).
Safety Studies with Metronidazole Gel
Studies of cumulative irritation (n=35), contact sensitization-repeat insult patch test (n=230), phototoxicity (n=29), and photoallergy (n=30) of metronidazole gel 1% were conducted. No significant evidence of irritation, sensitization, phototoxicity or photoallergy was found in these studies.
Metronidazole Gel 0.75%
Two randomized, double-blind, placebo-controlled, split-face design clinical studies were conducted in the United States on patients with rosacea. Metronidazole gel 0.75% was applied to one side of the face and placebo gel to the other, twice daily for nine weeks. The results are summarized in the following table
Table 6: Clinical Trial Results for Metronidazole Gel 0.75%
| NUMBER OF PATIENTS EVALUATED | % OF PATIENTS WITH SUBSTANTIAL REDUCTION IN INFLAMMATORY LESIONS | % OF PATIENTS WITH IMPROVEMENT IN ERYTHEMA | ||
|---|---|---|---|---|
| Metronidazole Gel | Placebo | Metronidazole Gel | Placebo | |
| 39 (15M, 24F)a | 77% * | 28% | 56% | 28% |
| 47 (25M, 22F)b | 68% * | 28% | 74% | 55% |
- among metronidazole gel substantial responders, mean lesion reduction was 81% in Dr. Sober’s studya and 83% in Dr. Aronson’s studyb.
Statistically significant differences in inflammatory lesions, erythema and global assessments were seen at 3, 6 and 9 weeks post baseline in favour of the active treatment side. The telangiectatic component of the disease was not altered.
DETAILED PHARMACOLOGY
Clinical and experimental evidence suggests that rosacea presents through degenerative changes of the perivascular (and possibly vascular) collagen and elastic tissues. This dermal dystrophy leads to small vessel dilation resulting in telangiectasia, erythema, and flushing. Eventually this leads to small vessel incompetence with leakage of potentially inflammatory substances perivascularly which produce papules, pustules, and lupoid nodules. Alternatively, a number of antigens, including the mite Demodex folliculorum or light-altered collagen and nuclear components could generate an immune response leading to the inflammatory changes. Since metronidazole is particularly effective against the inflammatory papulopustular component of the disease, its mechanism of action may involve an anti-inflammatory effect. Evidence has been presented that metronidazole has a direct pharmacological effect on neutrophil cell function, inhibiting the generation of reactive oxygen species. Other investigators have provided evidence for an anti-inflammatory activity, modification of the granulocyte function, and selective effects on some aspects of the humoral and cell-mediated immunity.
Pharmacokinetics
Metronidazole is rapidly and nearly totally absorbed after oral administration. The drug is not significantly bound to serum proteins and distributes well to all body compartments with the lowest concentration found in fat. Metronidazole is excreted primarily in the urine as parent drug, oxidative metabolites, and conjugates.
Studies on the topical administration of 1 gram of metronidazole 0.75% gel to the face (7.5 mg of metronidazole) of 10 rosacea patients showed a maximum serum concentration of 66 nanograms per milliliter in one patient. This concentration is approximately 100 times less than concentrations afforded by a single 250 mg oral tablet. The serum metronidazole concentrations were below the detectable limits (< 25 ng/mL) of the assay at the majority of time points in all patients. Three of the patients had no detectable serum concentrations of metronidazole at any time point. The mean dose of gel applied during clinical studies was 600 mg, which represents 4.5 mg of metronidazole per application. Therefore, under normal usage levels, the formulation affords minimal serum concentrations of metronidazole.
A multiple-dose (7-day) pharmacokinetic study on the topical administration of a one gram dose of metronidazole 1% topical gel to the face of 13 patients with moderate to severe rosacea showed a maximum plasma level (Cmax) of 44.7 ng/mL. The mean ± SD Cmax of metronidazole was 32.1 ± 8.5 ng/mL, which is less than 1% of the value reported for a single 250 mg oral dose of metronidazole. The mean AUC (0-24) value for metronidazole was 595.43 ng/mL/hour and the mean AUC (0-48) was 827.65 ng/mL/hour. The time to maximum plasma concentration (Tmax) in the patients with detectable metronidazole was 6-10 hours after topical application.
Three in vitro and two in vivo pharmacokinetic studies have been performed on human skin to evaluate metronidazole bioavailability following cutaneous application of the three topical 0.75% metronidazole formulations (gel, cream, lotion). These were compared with systemic administration (oral metronidazole). The mean relative bioavailabilities of metronidazole gel, cream and lotion were 41.2%, 44.5%, and 47.4 % respectively for the in vivo study.
The results suggest that the in vitro experiments were only partially predictive of in vivo conditions. The amount of metronidazole recovered in the receptor fluid in vitro was significantly higher for the gel than for the cream and lotion, whereas no statistically significant differences were observed for the three formulations (gel, cream, lotion) in vivo in the serum. If percutaneous absorption in vitro is measured by the total amount of metronidazole recovered in the skin and in the receptor fluid, then it remains significantly higher for the gel than for the lotion. These discrepancies between the in vitro and in vivo data suggest that in vivo percutaneous metronidazole absorption is not mediated only via passive diffusion.
TOXICOLOGY
Acute Toxicity
The acute oral LD50 of metronidazole as a pure substance is in the range of 3 to 5 g/kg in mice and rats, respectively. Signs of toxicity following oral or intravenous administration were sedation, ataxia and death in mice, and sedation and death in rats. Metronidazole gel 0.75% was administered in one dose at 5 g/kg by oral gavage to ten (5M, 5F) young adult rats. No animal showed clinical signs of toxicity and no animal had visible lesions on gross necropsy. Therefore, it is concluded that the oral LD50 of 0.75% metronidazole gel, in male and female rats, is greater than 5 g/kg of body weight.
Subacute Toxicity
Metronidazole gel 0.75% was applied topically, 5 days per week, to young adult rabbits at three dose levels plus control (5M + 5F/dose level) for 13 weeks. The three dose levels employed were the human dose (per application) equivalent, and 10 and 100 times the human equivalent on a mg/kg basis.
There were no compound-related dermal observations for treated animals nor were there effects on the hematology or clinical chemistry data of treated rabbits when compared with those of controls. No effects were observed on terminal body weight or organ weights. In addition, there were no compound-related macroscopic or microscopic pathologic findings.
The no-observable-effect level for rabbits exposed cutaneously to 0.75% metronidazole is greater than 13.0 mg/kg.
Subchronic Toxicity
Two treatment groups containing five male and five female Sprague Dawley rats were treated with either the lotion or the gel formulation. A third, identical group left untreated served as a control. A treatment dose of 2 mL/kg/day (approximately 15 mg/kg/day metronidazole) was applied to about 10% of the total body surface once daily for 28 consecutive days (clipped mid- dorsal region, intact skin). In a satellite study, 24 Sprague Dawley rats were treated with a single cutaneous application (2 mL/kg) of either the lotion or the gel formulation (10 rats each, five males and five females), or with the vehicle alone (four rats). Blood samples for metronidazole determination in plasma were taken four hours following treatment.
No cutaneous signs of irritation were observed in any group (no erythema or edema in any animal). A variety of changes were observed in the clinical chemistries of animals treated with metronidazole lotion and gel 0.75% formulations. These changes are of no toxicological significance as the changes were small and metronidazole can interfere with certain types of determinations of serum chemistry values. A significant reduction in the white blood cell counts was noted in females treated with either the lotion or gel formulation (p=0.05 vs. control). No macroscopic abnormalities were detected on necropsy. Histopathology did not reveal any treatment-related changes.
Four hours following a single application of the lotion formulation (day 1), the mean metronidazole plasma levels were 207 ng/mL in males and 170 ng/mL in females. Higher metronidazole levels were observed following repeated applications, with mean levels of 736 and 922 ng/mL in males and females, respectively, four hours after the 28th application.
It is concluded that no cutaneous signs of irritation were seen in any of the treatment groups and that the minimal signs of systemic toxicity are of no toxicological significance for the topical use of metronidazole lotion, 0.75% in the treatment of rosacea.
Primary Dermal Irritation
Metronidazole gel, cream, or lotion were applied to one intact and one symmetrically abraded test site on the backs of New Zealand white rabbits and maintained under occlusion. Patches were removed 24 hours after application and the treated areas were individually examined and scored for erythema and edema using the Draize four-level skin scoring scale. Neither metronidazole gel, cream, nor lotion were judged primary skin irritants.
A dermal sensitisation study in Hartley albino guinea pigs, evaluated metronidazole gel 1% via a combination of intradermal and topical applications. Animals were divided into 4 groups: 12 test animals, 6 negative controls (vehicle – Sterile Water for Injection, USP:WFI), 6 positive controls (1-chloro-2,4-dinitrobenzene:DNCB) and six naïve positive controls. During the 9-day induction phase, the test formulation (diluted in a 25% v/v WFI) and the control solutions were administered by interdermal injection. At 7 days post-injection, the same animals were exposed to a topical application for 48 hours. A challenge phase 14 days later consisted of topical exposure to untreated sites on the animals. The dosing sites erythema scores ranged from 0 to 1 for the metronidazole test group and negative control. There were no edema reactions.
Metronidazole gel 1% was not a contact sensitizer and did not induce an allergic response.
Metronidazole gel 1% (0.5 mL) was administered at 2 sites, 1 intact and 1 abraded to the back of the New Zealand White rabbits (n=6) in a primary skin irritation study. Following removal of the gel at 24 hrs, Dermal Irritation scores and Cumulative Primary Dermal Irritation scores at 24 and 72 hours for intact and abraded sites were 0 for all animals. No irritation was observed throughout the duration of the study.
Primary Eye Irritation
Metronidazole gel (0.1 mL) was placed into the everted lower lid of one eye of each of three rabbits. The upper and lower lids were gently held together for one second to prevent loss of material and then released. The other eye served as the untreated control. The eyes were unflushed and examined for ocular irritation at 1, 24, 48 and 72 hours after treatment. At the 72 hour reading, sodium fluorescein was used to aid in revealing possible corneal injury. Irritation was graded and scored according to the Draize technique.
No pain response (vocalization) was elicited from any animal following instillation of the test material and no corneal or iridal irritation was exhibited by any animal during the study period. In addition, the sodium fluorescein examination at 72 hours was also negative for all animals. One animal at 1 hour had a clear discharge in an amount different from normal. It was concluded that this formulation does not produce irritation in the rabbit eye.
New Zealand White rabbits (n=6); were administered metronidazole gel 1% (0.1 mL) to the right eye in a primary eye irritation study. The right eye, and the left eye which served as a control, were rinsed with saline after 24 hrs. No irritation was observed in the eyes of the animals at 25, 48 and 72 hours following administration. Metronidazole gel was determined not to be an eye irritant.
Mutagenicity
The mutagenic potential of metronidazole has been extensively studied, either in vitro as an active ingredient, or in vivo following systemic administration.
In the Ames test, with several susceptible bacteria, and in growing and dividing cells of yeast and fungi, metronidazole demonstrated mutagenicity. Mutagenesis in this test only occurred under anaerobic conditions or when the nitroimidazoles were reduced by oxygen-insensitive nitroreductases. Since mutagenesis in the Ames test occurs only under conditions of low redox potential, which is unattainable in normal aerobic human cells, the relevance of this type of mutagenicity testing to potential human toxicity is questionable. The inherent antimicrobial properties of metronidazole further complicate the interpretation respecting genotoxicity to humans.
Metronidazole in in vitro non-mammalian systems using Drosophila showed no mutagenic activity in the sex-linked recessive lethal test, whereas it induced an increase in the frequency of mosaic light spots on the eyes.
In several in vitro and in vivo mammalian mutation-detecting assays, metronidazole and its two primary metabolites have produced negative results. The tests included: in vivo dominant lethal tests in rodents; the micronucleus test in rodents; sister chromatid exchange (SCE) in rodent cell lines, in vitro and in vivo, with and without S9 fractions; chromosomal aberration assays in human lymphocytes in vitro and in vivo; heritable translocation in mice; mutations at the TK locus in L5178Y mouse lymphoma cells; mutation at the HGPRT or Na+/ K+ ATPase locus in V79 cells and assays for DNA synthesis inhibition and unscheduled synthesis (repair) and damage.
Positive reports have included induction of chromosome aberrations in Chinese hamster V79 cells (only under anaerobic conditions); mutation of V79 “spheroids” (under partial hypoxic condition) and DNA single-strand breaks in rat hepatocytes as measured by alkaline elution. Other studies reported positive mutagenic effects including an increase in the percentage of abnormal anaphases in CHO cells, an increase in the percentage of micronuclei in human lymphocytes, a dose-related relationship in the frequency of micronuclei in mice, and a dose-related relationship in the increase of chromosomal aberrations in human lymphocytes.
In humans, no significant increases in the frequency of chromosomal aberrations or sister chromatid exchanges were observed in lymphocytes from patients treated with oral metronidazole for trichomoniasis. An increased chromosome aberration frequency in peripheral lymphocytes relative to controls was reported in a population of patients with Crohn's disease treated with oral metronidazole. No increased chromosome aberration frequency could be detected in the lymphocytes from patients treated with oral metronidazole for Crohn's disease in a double-blind cross-over study.
Carcinogenicity/Photocarcinogenicity
Long-term bioassays for carcinogenicity of systemic metronidazole have been carried out in three species of rodents: mouse, rat, and hamster, and one study also investigated the potential photocarcinogenic effects of intraperitoneally administered metronidazole.
Increased tumour incidences were reported from several studies in both rats and mice administered systemic metronidazole, but not in hamsters. Induction of lung adenomas and lymphatic lymphomas in male and female mice followed a relatively short, low dose exposure. A tendency towards an increase in the number of mammary tumours in female rats and in benign tumours of all cell types in both sexes of rat was observed. An enhanced response to UV induced skin tumours was reported for intraperitoneally administered metronidazole in hairless mice. No carcinogenicity studies have been performed by the topical route in animals. The relevance of these tumour findings in animals to the topical use of metronidazole in humans is unknown.
There is no conclusive evidence after 30 years of clinical use of systemic metronidazole for a carcinogenic potential.
In humans, three cases of carcinoma were reported in patients with Crohn's disease treated with large doses of oral metronidazole. Two of these patients developed breast carcinoma. One of them had received a total metronidazole dose of 720 g within a 3-year continuous treatment, the second one had received a total dose of approximately 340 g within two 4- to 5-month treatment periods. The third patient, who developed a cholangiocarcinoma, had received a total metronidazole dose of approximately 275 g over a 3-year period. The metronidazole doses involved are in excess from those used for the treatment of trichomoniasis, which usually consist of a total 8-g dose given over a 7 to 10-day period. No relationship other than chronological association could be established between these cases of cancers and the absorption of metronidazole.
One case of adrenal neuroblastoma was reported in a newborn male whose mother was treated with metronidazole during pregnancy. The dosage consisted of oral metronidazole 250 mg twice daily and intravaginal metronidazole 500 mg daily, both for 10 days. It was not possible to establish a causal relationship between adrenal neuroblastoma and metronidazole based on this report.
Epidemiological Studies
In view of these clinical reports and of the results obtained in animals, several epidemiologic studies were conducted to evaluate the incidence of cancers in patients treated with metronidazole.
In 771 women treated with metronidazole for vaginal trichomoniasis, no statistically significant increase in the incidence of cancers of all sites was observed when compared to the expected figures given by official statistics for a comparable standard population. Similar results were obtained in 237 untreated patients with the same pathology. In a subsequent study based on a 15 to 25-year follow-up of the same 771 patients, a slightly higher overall standardized morbidity ratio was observed in women prescribed metronidazole for trichomonal infection compared with age-specific expected rates calculated from several standard data bases. For site-specific cancers, only the standardized morbidity ratio for lung cancer was significantly increased (p < 0.05).
However, this observation was based on only 12 cases, 10 of whom were smokers. Smoking confounds any definitive association between metronidazole use and lung cancer.
In a screening analysis for carcinogenicity of commonly used drugs including metronidazole, 143,574 users of various medicinal drugs during the period 1969-1973 were followed through to 1976 for the development of cancer. For metronidazole, no statistically significant associations with cancer of any site or all sites combined were found.
In 2,460 persons who received at least one prescription of metronidazole between 1960 and 1973 and who were followed up through 1976, 45 cases of cancer were diagnosed whereas 33.3 cancer cases were expected. The excess was caused entirely by an excess occurrence of cancer of the uterine cervix, whose association with metronidazole-treated vaginitis can be explained by poor sexual hygiene. In an 11 to 15-year follow-up of the same subjects, the statistically significant increase in cervical cancer was still observed, but an increased risk for lung cancer or for all cancers combined could not be confirmed.
In 12,280 persons who received one or more prescriptions of metronidazole from 1977 to 1979, no increase in the incidence for the six cancers followed (endometrium, testis, thyroid, liver, breast and lung) was observed.
Information from the epidemiological studies did not demonstrate a significant increase in the incidence of tumours. However, since the data are limited, no definitive conclusion can be made at the present time.
REFERENCES
- 1. Bahr V, Ullmann U: The influence of Metronidazole and its Two Main Metabolites on Murine in vitro Lymphocyte Transformation. Eur. J. Clin. Microbial. 1983; 2:568-570.
- 2. Gnarpe H, Belsheim J, and Persson S: Influence of Nitroimidazole Derivatives on Leukocyte Migration. Scand. J. Infect. Dis. (Suppl). 1981: 26:68-71.
- 3. Grove DI, Makmoud M F, Warren KS: Suppression of Cell-Mediated Immunity by Metronidazole. Int. Archs Allergy Appl. Immunol. 1977; 54:422-427.
- 4. Lowe NJ, Henderson T, Millikan LE, Smith S, Turk K, Parker F: Topical metronidazole for severe and recalcitrant rosacea: A prospective open trial. Cutis 1989; 43:283.
- 5. Marks R: The Problem of Rosacea. Br. Med. J. (Clin. Res.) 1976; 1(6001):94-94.
- 6. Miyachi Y, Imamura S, Niwa Y: Anti-oxidant Action of Metronidazole: A Possible Mechanism of Action in Rosacea. Br. J. Dermatol 1986; 114:321-324.
- 7. Nunzi E, Rebora A, Hamerlinck F, Cormane RH: Immunopathological Studies on Rosacea. Br. J. Dermatol 1980; 103:543-551.
- 8. Saxena A, Shaski C, Vinayak VK: Modulation of Host Immune Responses by Metronidazole. Ind. J. Med. Res. 1985; 81:387-390.
- 9. Tanga MR, Antani JA, Kabade SS: Clinical Evaluation of Metronidazole as an Anti- Inflammatory Agent. Int. Surg. 1975; 60:75-76.
- 10. Taylor JAT: Pharmacodynamic Observations on Metronidazole Therapy. Side Effects in Endocrine, Metabolic and Auto-immune Disorders. III Anti-Ischemic and Anti-inflammatory Action in Peripheral Vascular Disorders. Proc. West Pharmacol. Soc. 1966; 9:37-39.
- 11. Ursing B, Kamme C: Metronidazole for Crohn's Disease. Lancet 1975: (i):775-777.
- 12. Kelly GE, Meikle WD, Moore DE: Enhancement of UV-induced skin carcinogenesis by azathioprine: role of photochemical sensitisation. Photochem. and Biol. 1989; 49: 59-65.
- 13. PrMETROGEL® metronidazole gel, 0.75% (w/w), 1% (w/w), control #209699, Product Monograph, Galderma Canada Inc., February 22, 2018.