


Product Monograph - Trulance
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, treatment of chronic idiopathic constipation (CIC) in adults. | DEC/2024 |
|---|
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................. 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics (<18 years of age) .................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................ 4
4 DOSAGE AND ADMINISTRATION .................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
- 4. 4 Administration .......................................................................................................... 5
- 4. 5 Missed Dose ............................................................................................................ 6
5 OVERDOSAGE ................................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................... 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations ................................................................................................. 7
7.1.1 Pregnant Women ................................................................................................. 7
7.1.2 Breast-feeding ..................................................................................................... 7
7.1.3 Pediatrics ............................................................................................................. 8
7.1.4 Geriatrics ............................................................................................................. 8
8 ADVERSE REACTIONS ................................................................................................... 8
8.1 Adverse Reaction Overview .................................................................................... 9
8.2 Clinical Trial Adverse Reactions .............................................................................. 9
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 12
8.5 Post-Market Adverse Reactions ............................................................................ 12
9 DRUG INTERACTIONS .................................................................................................. 12
9.2 Drug Interactions Overview…………………………………………………………....12
9.4 Drug-Drug Interactions .......................................................................................... 13
9.5 Drug-Food Interactions .......................................................................................... 13
9.6 Drug-Herb Interactions .......................................................................................... 13
9.7 Drug-Laboratory Test Interactions ......................................................................... 13
10 CLINICAL PHARMACOLOGY ....................................................................................... 13
10.1 Mechanism of Action ......................................................................................... 13
10.2 Pharmacodynamics ........................................................................................... 14
10.3 Pharmacokinetics .............................................................................................. 14
11 STORAGE, STABILITY AND DISPOSAL ...................................................................... 15
PART II: SCIENTIFIC INFORMATION ....................................................................................... 16
13 PHARMACEUTICAL INFORMATION ............................................................................ 16
14 CLINICAL TRIALS ......................................................................................................... 17
14.1 Clinical Trials by Indication………………………………………………………..……..17
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 24
PATIENT MEDICATION INFORMATION ........................................ Error! Bookmark not defined.
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TRULANCE (plecanatide) is indicated for:
- treatment of irritable bowel syndrome with constipation (IBS-C) in adults
- treatment of chronic idiopathic constipation (CIC) in adults
1.1 Pediatrics (<18 years of age)
TRULANCE is contraindicated in pediatric patients less than 6 years of age. Avoid use of TRULANCE in patients between 6 and 18 years of age as the safety and efficacy of TRULANCE in pediatric patients have not been established (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS, 10 CLINICAL PHARMACOLOGY, Special Populations).
1.2 Geriatrics
Geriatrics (>65 years of age)
Irritable Bowel Syndrome with Constipation (IBS-C)
Of 1456 patients in placebo-controlled clinical studies of TRULANCE, 114 (7.8%) were 65 years of age and over. Clinical studies of TRULANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from patients 18 years to less than 65 years of age.
Chronic Idiopathic Constipation (CIC)
Of 2,601 subjects in placebo-controlled clinical trials of TRULANCE, 273 (10%) were 65 years of age and over. Clinical studies of TRULANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from patients 18 years to less than 65 years of age.
2 CONTRAINDICATIONS
TRULANCE (plecanatide) is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- Patients less than 6 years of age due to the risk of serious dehydration (see 7 WARNINGS AND PRECAUTIONS, Special Populations).
- Patients with known or suspected mechanical gastrointestinal obstruction.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
No dose adjustments are required for patients with hepatic or renal impairment.
In some patients, TRULANCE taken with food led to looser stools and/or increased abdominal cramping. Patients experiencing gastrointestinal adverse events should avoid high-fat, high-calorie meals near the time of dosing. Some patients had an improvement in the number of bowel movements starting as early as 24 hours after taking TRULANCE.
4.2 Recommended Dose and Dosage Adjustment
The recommended dosage of TRULANCE for the treatment of IBS-C and CIC is 3 mg taken orally once daily with or without food.
Health Canada has not authorized an indication for pediatric use (see 1.1 INDICATIONS, Pediatrics).
- 4. 4 Administration
TRULANCE can be taken with or without food. The tablet should be swallowed whole.
For adult patients with swallowing difficulties, TRULANCE tablets can be crushed and administered orally either in applesauce or with water or administered with water via a nasogastric or gastric feeding tube. Mixing TRULANCE crushed tablets in other soft foods or in other liquids has not been tested.
Oral Administration in Applesauce
- 1. In a clean container, crush the TRULANCE tablet to a powder and mix with 1 teaspoonful of room temperature applesauce.
- 2. Consume the entire tablet-applesauce mixture immediately. Do not store the mixture for later use.
Oral Administration in Water
- 1. Place the TRULANCE tablet in a clean cup.
- 2. Pour approximately 30 mL of room temperature water into the cup.
- 3. Mix by gently swirling the tablet and water mixture for at least 10 seconds. The TRULANCE tablet will fall apart in the water.
- 4. Swallow the entire contents of the tablet water mixture immediately.
- 5. If any portion of the tablet is left in the cup, add another 30 mL of water to the cup, swirl for at least 10 seconds, and swallow immediately.
- 6. Do not store the tablet-water mixture for later use.
Administration via a Nasogastric or Gastric Feeding Tube (with water)
Serious Warnings and Precautions
- TRULANCE is contraindicated in patients less than 6 years of age.
- Avoid use of TRULANCE in patients between 6 years and 18 years of age.
(see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, Special Populations,
NON-CLINCIAL TOXICOLOGY, Reproductive and Developmental Toxicity)
- 1. Place the TRULANCE tablet in a clean cup with 30 mL of room temperature water.
- 2. Mix by gently swirling the tablet and water mixture for at least 15 seconds. The TRULANCE tablet will fall apart in the water.
- 3. Flush the nasogastric or gastric feeding tube with 30 mL of water using an appropriate syringe.
- 4. Draw up the mixture using the syringe and immediately administer via the nasogastric or gastric feeding tube. Do not reserve for future use.
- 5. If any portion of the tablet is left in the cup, add another 30 mL of water to the cup, swirl for at least 15 seconds, and using the same syringe, administer via the nasogastric or gastric feeding tube.
- 6.
Using the same or a fresh syringe, flush the nasogastric or gastric feeding tube with at least 10 mL of water.
- 4. 5 Missed Dose
If a dose is missed, the patient should skip the missed dose and take the next dose at the regular time. Two doses should not be taken at the same time.
5 OVERDOSAGE
No cases of overdose with plecanatide have been reported. In studies doses up to 48.6 mg of plecanatide were tolerated in healthy adults. Symptoms of overdose should be managed by supportive care, as appropriate, with attention to maintenance of fluid and electrolyte balance.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
Each tablet of TRULANCE contains 3 mg of plecanatide. The tablet is white to off-white, plain and round, debossed with “SP” on one side and “3” on the other side.
TRULANCE tablets are supplied in white HDPE bottles of 7-count and 30-count tablets and in aluminum foil unit dose blister pack of 7-count and 30-count tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
Risk of Serious Dehydration in Pediatric Patients
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet; 3mg | Microcrystalline Cellulose, Magnesium Stearate |
TRULANCE is contraindicated in patients less than 6 years of age. The safety and effectiveness of TRULANCE in patients less than 18 years of age have not been established. In young juvenile mice (human age equivalent of approximately 1 month to less than 2 years), plecanatide increased fluid-secretion into the intestines as a result of stimulation of guanylate cyclase-C (GC-C), resulting in mortality in some mice within the first 24 hours, apparently due to dehydration. Due to increased intestinal expression of GC-C, patients less than 6 years of age may be more likely than patients 6 years of age and older to develop severe diarrhea and its potentially serious consequences.
Avoid the use of TRULANCE in patients 6 years to less than 18 years of age. Although there were no deaths in older juvenile mice, given the deaths in younger mice and the lack of clinical safety and efficacy data in pediatric patients, avoid the use of TRULANCE in patients 6 years to less than 18 years of age (see Special Populations).
Diarrhea
Diarrhea was the most common adverse reaction in four placebo-controlled clinical trials, two in patients with IBS-C and two in patients with CIC. Severe diarrhea was reported in 0.6% of patients in two trials in patients with IBS-C and in 0.6% of patients in the two trials in patients with CIC (see 8 Adverse Reactions). If severe diarrhea occurs, suspend dosing and rehydrate the patient.
7.1 Special Populations
7.1.1 Pregnant Women
There is very limited experience in pregnancy during clinical trials.
Plecanatide and its active metabolite are negligibly absorbed systemically following oral administration and maternal use is not expected to result in fetal exposure to the drug.
The available data on TRULANCE use in pregnant women are not sufficient to inform any drug-associated risks for major birth defects and miscarriage. In animal developmental studies, no effects on embryo-fetal development were observed with oral administration of plecanatide in mice and rabbits during organogenesis at doses much higher than the recommended human dosage.
Animal Data
Pregnant mice and rabbits were administered plecanatide during the period of organogenesis. There was no evidence of harm to embryo-fetal development at oral doses up to 800 mg/kg/day in mice and 250 mg/kg/day in rabbits. Oral administration of up to 600 mg/kg/day in mice during organogenesis through lactation produced no developmental abnormalities or effects on growth, learning and memory, or fertility in the offspring through maturation.
The maximum recommended human dose is approximately 0.05 mg/kg/day, based on a 60-kg body weight. Limited systemic exposure to plecanatide was achieved in animals during organogenesis (area under the plasma concentration-time curve (AUCt) = 449 ng•h/mL in rabbits given 250 mg/kg/day). Plecanatide and its active metabolite are not measurable in human plasma following administration of the recommended clinical dosage. Therefore, animal and human doses should not be compared directly for evaluating relative exposure (see Non-Clinical Toxicology, Reproductive and Developmental Toxicology).
7.1.2 Breast-feeding
In a single dose lactation study with 3 mg plecanatide, of the 6 patients who participated, 1 patient had detectable plecanatide in breast milk 2 hours post dose administration. Plecanatide was below the level of quantification in all other patients, and at all other time points. Precaution should be used when prescribing plecanatide to breast-feeding patients because of the potential risks to pediatrics (see 2 CONTRAINDICATIONS, 7.1.3 Pediatrics).
7.1.3 Pediatrics
Pediatrics (< 18 years)
In nonclinical studies, deaths occurred within 24 hours in young juvenile mice (human age equivalent of approximately 1 month to less than 2 years) following oral administration of plecanatide, as described below in Juvenile Animal Toxicity Data. Because of increased intestinal expression of GC-C, patients less than 6 years of age may be more likely than patients 6 years of age and older to develop diarrhea and its potentially serious consequences. TRULANCE is contraindicated in patients less than 6 years of age. Given the deaths in young juvenile mice and the lack of clinical safety and efficacy data in pediatric patients, avoid the use of TRULANCE in patients between 6 and 18 years of age.
Juvenile Animal Toxicity Data
Single oral doses of plecanatide at 0.5 mg/kg and 10 mg/kg caused mortality in young juvenile mice on postnatal days 7 and 14, respectively (human age equivalent of approximately 1 month to less than 2 years). Treatment-related increases in the weight of intestinal contents were observed in juvenile mice following single doses of plecanatide on postnatal day 14 (human age equivalent of approximately less than 2 years), consistent with increased fluid in the intestinal lumen. Although the recommended human dose is approximately 0.05 mg/kg/day, based on a 60-kg body weight, plecanatide and its active metabolite are not measurable in adult human plasma, whereas systemic absorption was demonstrated in the juvenile animal toxicity studies.
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of TRULANCE in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 1 INDICATIONS, 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
7.1.4 Geriatrics
Irritable Bowel Syndrome with Constipation (IBS-C)
Of 1456 patients in the TRULANCE clinical trials, 7.8 % were 65 years of age and over. Clinical studies of TRULANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from patients 18 years to less than 65 years of age.
Chronic Idiopathic Constipation (CIC)
Of 2,601 subjects in placebo-controlled clinical trials of TRULANCE, 273 (10%) were 65 years of age and over, and 47 (2%) were 75 years and over. Clinical studies of TRULANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from patients 18 years to less than 65 years of age.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Irritable Bowel Syndrome with Constipation (IBS-C)
The safety of TRULANCE in IBS-C was evaluated in two placebo-controlled studies involving a total of 1879 patients (ITT-S, 1255 patients treated with TRULANCE and 624 treated with placebo). A total of 17 patients (0.8%) experienced 20 serious adverse events (SAEs), with the incidence being similar in the placebo (0.8%), 3 mg TRULANCE (0.8%) and 6 mg TRULANCE (0.7%) arms of the study. The transaminases increase was reported in 2 patients (0.1% for combined TRULANCE; 0% for placebo). All other SAE’s were reported as <0.1% in the combined TRULANCE group. No SAE in the placebo-controlled studies was considered related to study drug. There was no obvious pattern in the types of serious adverse events experienced in either the placebo or TRULANCE group.
The commonly reported AE (>1.0%) in the combined TRULANCE group was diarrhea (4.1%) compared to the placebo group (1.0%). Other AEs reported in at least 1% of either active treatment group included headache, nausea, influenza, nasopharyngitis, urinary tract infection, upper respiratory tract infection and dizziness. There were two deaths reported in the IBS-C clinical study, neither were related to TRULANCE. One patient did not receive TRULANCE and the second patient died of drowning. TRULANCE was generally well-tolerated with most AEs being mild to moderate in intensity.
Chronic Idiopathic Constipation (CIC)
The safety of TRULANCE in CIC was evaluated in two placebo-controlled studies involving a total of 2345 patients (ITT-S, 1557 patients treated with TRULANCE and 786 treated with placebo). A total of 30 patients (1.1%) reported 31 serious adverse events (SAEs), with the incidence being similar in the placebo (1.2%), 3 mg plecanatide (1.2%), and 6 mg plecanatide groups (0.9%) arms of the study. The aspartate aminotransferase increase was reported in 2 patients (0.1% each). All other SAE were reported in 1 plecanatide patient each. Two SAEs were considered related to study drug, which were acute diverticulitis of the sigmoid colon in a patient in the placebo group and liver function test abnormal in a patient in the 6 mg plecanatide group.
The most frequently reported AE (>1.0%) in the combined plecanatide group was diarrhea (4.8%) compared to the placebo group (1.3%). Other AEs reported in less than 0.5% of either active treatment group included rash (0.4%) and blood amylase increased (0.2%). There was one death reported in the CIC clinical study. Patient in the 6 mg plecanatide treatment group of long-term safety study died due to the SAE of myocardial infarction. Consequently, it was not related to study drug.
8.2 Clinical Trial Adverse Reactions
Irritable Bowel Syndrome with Constipation (IBS-C)
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 2 lists the incidence of treatment-emergent adverse events from the two double-blind, placebo-controlled phase 3 studies in adult patients with IBS-C that occurred in ≥ 1% of the patients treated with TRULANCE.
Table 2: Adverse Reactions Occurring in ≥1.0% of TRULANCE-Treated Patients and at an Incidence Greater than in Placebo-Treated Patients in Two Phase 3 Placebo-Controlled Trials in IBS-C
System Organ Class Preferred Term | Placebo n = 730 (%) | TRULANCE 3mg n = 726 (%) | TRULANCE 6mg n = 726 (%) | TRULANCE combined n = 1452 (%) | ||||
| Gastrointestinal Disorders | ||||||||
| Diarrhea* | 1.0 | 4.3 | 4.0 | 4.1 | ||||
| Nausea | 1.0 | 1.8 | 1.1 | 1.4 | ||||
| Infections and Infestations | ||||||||
| Nasopharyngitis | 1.2 | 1.5 | 0.8 | 1.2 | ||||
| Upper Respiratory Tract Infection | 0.8 | 1.2 | 0.4 | 0.8 | ||||
| Urinary Tract Infection | 0.7 | 1.0 | 1.5 | 1.2 | ||||
| Nervous System Disorders | ||||||||
| Dizziness | 0.4 | 1.0 | 0.3 | 0.6 | ||||
| Headache | 2.2 | 2.2 | 0.9 | 2.1 | ||||
* Reports of loose stools and increase in stool frequency were recorded as adverse reactions if they were also reported to be bothersome to the patient.
Chronic Idiopathic Constipation (CIC)
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 3 lists the incidence of treatment-emergent adverse events from the two double-blind, placebo-controlled phase 3 studies in adult patients with CIC that occurred in ≥0.50% of the patients treated with TRULANCE.
Table 3: Adverse Reactions Occurring in ≥0.5% of TRULANCE-Treated Patients and at an Incidence Greater than in Placebo-Treated Patients in Two Phase 3 Placebo-Controlled Trials in CIC.
System Organ Class Preferred Term | Placebo n = 924 (%) | TRULANCE 3mg n = 941 (%) | TRULANCE 6mg n = 926 (%) | TRULANCE combined n = 1867 (%) | ||||
| Gastrointestinal Disorders | ||||||||
| Abdominal distension | 0.3 | 1.1 | 0.9 | 1.0 | ||||
| Diarrhea | 1.3 | 4.6 | 5.1 | 4.8 | ||||
| Flatulence | 0.6 | 1.0 | 0.9 | 0.9 | ||||
| Vomitting | 0.4 | 0.6 | 0.4 | 0.5 | ||||
| General disorders and administration site conditions | ||||||||
| Pyrexia | 0.4 | 0.5 | 0.4 | 0.5 | ||||
| Infections and Infestations | ||||||||
| Bronchitis | 0.4 | 0.6 | 0.5 | 0.6 | ||||
| Sinusitis | 0.4 | 1.3 | 0.6 | 1.0 | ||||
| Upper Respiratory Tract Infection | 1.1 | 1.5 | 0.6 | 1.1 | ||||
| Urinary Tract Infection | 1.7 | 1.6 | 1.4 | 1.5 | ||||
| Nervous system disorders | ||||||||
| Headache | 1.9 | 1.8 | 1.7 | 1.8 | ||||
| Musculoskeletal and connective tissue disorders | ||||||||
| Arthralgia | 0.4 | 0.7 | 0.4 | 0.6 | ||||
Respiratory, thoracic and mediastinal disorders | ||||||||
| Cough | 0.4 | 1.0 | 0.5 | 0.7 | ||||
Adverse Events Leading to Discontinuation
Irritable Bowel Syndrome with Constipation (IBS-C)
Discontinuation due to AE occurred in 2.3% of TRULANCE treated patients with IBS-C compared to 0.4% in placebo. The frequently reported of AEs leading to discontinuation in the combined TRULANCE group was gastrointestinal disorders (1.8%) compared to placebo (0.1%). The most frequently reported AE leading to discontinuation in the combined TRULANCE group was diarrhea (1.3%), followed by abdominal pain, nausea, and increased transaminases (0.1% each). Although the incidence of diarrhea leading to discontinuation was low, it was higher in the combined TRULANCE group than in the placebo group (1.3% versus 0%), 1.2% in the 3 mg and 1.4% in the 6 mg group.
Chronic Idiopathic Constipation (CIC)
Discontinuation due to AE occurred in 5.3% of TRULANCE treated patients with CIC compared to 2.5% in placebo. The most frequently reported of AEs leading to discontinuation in the combined plecanatide group were diarrhea (119 patients, 2.7%), abdominal pain (12 patients, 0.3%), pregnancy (10 patients, 0.2%), abdominal distension (9 patients, 0.2%), fecal incontinence (4 patients, 0.1%), flatulence (4 patients, 0.1%), nausea (4 patients, 0.1%), and headache (4 patients, 0.1%). All other preferred terms were each reported by 3 or fewer plecanatide patients. Although the incidences of the most frequently reported events were low, the combined plecanatide group had a higher incidence than the placebo group of diarrhea (2.7% versus 0.4%), pregnancy (0.2% versus 0.1%), abdominal distension (0.2% versus 0.1%), fecal incontinence (0.1% versus 0), and flatulence (0.1% versus 0).
8.3 Less Common Clinical Trial Adverse Reactions
Other adverse reactions that were reported in less than 1% of IBS-C patients and less than 0.5% of CIC patients are listed below by body system:
Gastrointestinal disorders: abdominal distension, abdominal pain, gastrointestinal sounds abnormal, gastroesophageal reflux disease.
General disorders and administration site conditions: pyrexia.
Investigations: Transaminases increased; blood amylase increased.
Metabolism and nutrition disorders: decreased appetite.
Musculoskeletal and connective tissue disorders: Back pain.
Nervous system disorders: migraine, paresthesia, sciatica, syncope.
- 8. 5 Post-Market Adverse Reactions
Rare occurrences of the following adverse reactions have been observed in post-marketing studies.
Hypersensitivity Reactions: skin itching, hives, rash.
Gastrointestinal disorders: lower gastrointestinal hemorrhage, vomiting.
9 DRUG INTERACTION
9.2 Drug Interaction Overview
Neither plecanatide nor its active metabolite inhibited the cytochrome P450 (CYP) enzymes 2C9 and 3A4, and they did not induce CYP3A4 in vitro. Plecanatide and its active metabolite were neither substrates nor inhibitors of the transporters P-glycoprotein (P-gp) or breast cancer resistance protein (BCRP) in vitro.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been conducted. Concentration of plecanatide and its active metabolite in plasma are not measurable following administration of the recommended clinical doses; hence, no systemic drug-drug interactions or drug interactions mediated by plasma protein binding of plecanatide or its metabolite are expected. TRULANCE is neither an inhibitor nor an inducer of CYP3A nor an inhibitor of CYP2C9 based on results of in vitro studies. Plecanatide and its active metabolite are neither substrates nor inhibitors of the transporters P-glycoprotein (P-gp) or breast cancer resistance protein (BCRP) in vitro.
9.5 Drug-Food Interactions
TRULANCE can be taken with or without food.
In a crossover study, 24 healthy subjects were given a single dose of TRULANCE 9 mg (3 times the recommended dose) in 3 different states: fasted; following a low-fat, low-calorie meal (LF-LC; approximately 350 calories: 17% from fat, 66% from carbohydrate, and 17% from protein); and following a high-fat, high-calorie meal (HF-HC; approximately 1000 calories: 60% from fat, 25% from carbohydrate, and 15% from protein). Plecanatide was detected in 1 subject (fasted state) at 0.5 and 1-hour post dose. Plecanatide concentrations were below the limit of quantitation for all other time points and for all other subjects. The active metabolite was not detected in any subject.
In this study, there were no or minimal effects of food on bowel movement (BM) frequency, time to first BM, fecal urgency, and fecal incontinence. Potential food effects were observed in Bristol Stool Form Scale (BSFS) scores and abdominal cramping. There were slight increases in BSFS scores, which are associated with looser stools, in the LF-LC and HF-HC treatment periods, and there were increases in the incidence of mild, moderate and severe abdominal cramping following a HF-HC or LF-LC meal. Patients experiencing gastrointestinal adverse events should be advised to avoid high-fat, high-calorie meals near the time of dosing.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been evaluated.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been evaluated.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Plecanatide, a synthetic 16-amino acid peptide is a structural analog of the naturally occurring human uroguanylin peptide , and similarly to uroguanylin, is a potent and selective guanylate cyclase-C (GC-C) agonist with visceral analgesic and secretory activities. Plecanatide binds to GC-C receptors in a pH-dependent manner and is preferentially more active at slightly acidic pH levels. Both plecanatide and its active metabolite bind to GC-C and act locally on the luminal surface of the intestinal epithelium. Activation of GC-C results in an increase in both intracellular and extracellular concentrations of cyclic guanosine monophosphate (cGMP). Elevation of extracellular cGMP has been associated with a decrease in activity of pain-sensing nerves in animal models of visceral pain. Elevation of intracellular cGMP stimulates secretion of chloride and bicarbonate into the intestinal lumen, mainly through activation of the cystic fibrosis transmembrane conductance regulator (CFTR) ion channel, resulting in increased intestinal fluid and accelerated transit. In animal models, plecanatide has been shown to increase fluid secretion into the gastrointestinal (GI) tract, accelerate intestinal transit, and cause changes in stool consistency.
10.2 Pharmacodynamics
The pharmacologic effects of TRULANCE in humans have not been fully evaluated. In animal and clinical studies TRULANCE has been shown to accelerate colonic transit, soften stools and increase stool frequency.
10.3 Pharmacokinetics
Absorption
Plecanatide is minimally absorbed with negligible systemic availability following oral administration. Concentrations of plecanatide and its active metabolite in plasma are below the limit of quantitation after an oral TRULANCE dose of 3 mg. Therefore, standard pharmacokinetic parameters such as AUC, maximum concentration (Cmax), and half-life (t½) cannot be calculated.
Distribution
Given that plecanatide concentrations following clinically relevant oral doses are not measurable, plecanatide is expected to be minimally distributed in tissues. Oral plecanatide is localized to the GI tract where it exerts its effects as a GC-C agonist with negligible systemic exposure. Plecanatide exhibits little to no binding to human serum albumin or human α-1-acid glycoprotein.
Metabolism
Plecanatide is metabolized in the GI tract to an active metabolite by loss of the terminal leucine moiety. Both plecanatide and the metabolite are proteolytically degraded within the intestinal lumen to smaller peptides and naturally occurring amino acids.
Elimination
No excretion studies have been conducted in humans. Plecanatide and its active metabolite are not measurable in plasma following administration of the recommended clinical doses.
Special Populations
Pediatrics (<18 years of age)
Clinical studies to determine the impact of age on the clinical pharmacokinetics of plecanatide have not been conducted as plecanatide is not measurable in plasma following oral administration. TRULANCE is contraindicated in children under 6 years of age and is not recommended for use in children between 6 and18 years of age as the safety and efficacy of TRULANCE in pediatric patients have not been established [see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics and NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicity].
Geriatrics
Clinical studies to determine the impact of age on the pharmacokinetics of TRULANCE have not been conducted. (see WARNINGS AND PRECAUTIONS, Geriatrics) for information regarding patients aged 65 years and older.
Gender
Clinical studies to determine the impact of gender on the pharmacokinetics of TRULANCE have not been conducted. Gender is not expected to affect the pharmacokinetics of TRULANCE.
Hepatic Insufficiency
TRULANCE has not been specifically studied in patients who have hepatic impairment. Hepatic impairment is not expected to affect the metabolism or clearance of the parent drug or its metabolite because plecanatide has low systemic availability following oral administration and is metabolized within the gastrointestinal tract.
Renal Insufficiency
TRULANCE has not been specifically studied in patients who have renal impairment. Renal impairment is not expected to affect clearance of the parent drug or its metabolite because plecanatide has low systemic availability following oral administration and is metabolized within the gastrointestinal tract.
11 STORAGE, STABILITY AND DISPOSAL
TRULANCE bottles and blister packs should be stored at room temperature (15 to 30ºC). Do not remove desiccant from the bottle. Protect from moisture. Keep out of reach and sight of children.
As with any prescription medication, for proper disposal, unused and expired medications can be returned to any pharmacy in Canada any day of the year.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper/Common name: plecanatide
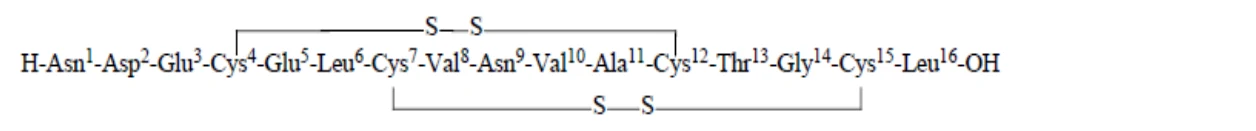
Chemical name: L-Leucine, L-asparaginyl-L-α-aspartyl-L-α-glutamyl-L-cysteinyl-L-αglutamyl-L-leucyl-L-cysteinyl-L-valyl-L-asparaginyl-L-valyl-L-alanyl-L-cysteinyl-L-threonylglycyl-Lcysteinyl-, cyclic (4→12),(7→15)-bis(disulfide)
Molecular formula: C65H104N18O26S4
Molecular mass: 1682 Daltons
Structural formula: Plecanatide is a 16-amino acid peptide with the following sequence:
Physicochemical properties
Description: White to off-white amorphous powder
Solubility: Plecanatide is soluble across the entire physiological pH range with dose solubility volumes of < 1 mL
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Irritable Bowel Syndrome with Constipation (IBS-C)
The efficacy of TRULANCE (plecanatide tablets) for the treatment of IBS-C was established in two double-blind, placebo-controlled, randomized, multicenter trials in adult patients: Study SP304203-04 (Study 04) and SP304203-05 (Study 05). In the Intention-to-Treat (ITT) population, a total of 699 patients (Study 04) and 754 patients (Study 05) received treatment with TRULANCE (3mg or 6mg) once daily and were evaluated for efficacy. In clinical studies, study medication was administered without regards to food intake. Demographics for these studies included an overall mean age of 44 years (range 18 to 83 years), 74% female, 73% white, and 22% black. A summary of trial designs and patient demographics is presented in Table 3 below.
Table 4 - Summary of Patient Demographics Supporting Efficacy of TRULANCE in the Treatment of IBS-C (Intention-to-Treat [ITT] Population)
| Trial # | Trial Design / Duration | Oral Dosage | Study Subjects (N) [Female/Male] | Mean Age (Range) | Mean Baseline Characteristics (Standard Deviation) | |||||||
| 04 | multicenter, randomized,12 weeks, double-blind, placebo-controlled study | Once daily dose Placebo 3 mg 6 mg | 354 (272/82) 351 (267/84) 349 (266/83) | 18-81 | CSBMs/week 0.2 ± 0.4 0.2 ± 0.5 0.3 ± 0.5 | Abdominal pain 6.1 ± 1.8 5.9 ± 1.7 6.0 ± 1.8 | ||||||
| 05 | multicenter, randomized, 12 weeks, double-blind, placebo-controlled study | Once daily dose Placebo 3mg 6mg | 379 (272/107) 377 (270/107) 379 (273/106) | 18-83 | 0.2 ± 0.5 0.3 ± 0.5 0.3 ± 0.5 | 6.4 ± 1.6 6.6 ± 1.6 6.5 ± 1.7 | ||||||
CSBM=Complete Spontaneous Bowel Movement Abdominal pain score based on 11-point numerical rating scale (NRS) (0=none, 10=very severe) | ||||||||||||
All patients met the Rome III criteria for IBS for the last 3 months prior to the screening visit, with symptom onset for at least 6 months prior to diagnosis. Diagnosis required recurrent abdominal pain or discomfort at least 3 days/month in the last 3 months associated with 2 or more of the following
- improvement with defecation.
- onset associated with a change in frequency of stool.
- onset associated with a change in form (appearance) of stool.
Patients also met the IBS-C differentiation criteria for constipation, characterized by a stool pattern in which ≥25% of defecations were hard or lumpy stools [Bristol Stool Form Scale (BSFS) score of 1 or 2] and ≤25% of reported SBMs (occurring without the use of laxatives) were loose or watery stools of (BSFS score of 6 or 7).
The efficacy of TRULANCE was assessed using an overall responder analysis based on abdominal pain intensity and a stool frequency responder [Complete Spontaneous Bowel Movement (CSBM) endpoint]. Efficacy was assessed using information provided by patients daily in an electronic diary using an interactive voice response system.
Primary Endpoints
The primary efficacy endpoint was the percentage of overall responders defined as patients who were abdominal pain intensity weekly responders and CSBM weekly responders in the same week for at least 6 out of the first 12 weeks of treatment.
- An abdominal pain intensity weekly responder was defined as a patient who experienced a decrease in the weekly average IBS-related daily abdominal pain severity score of at least 30% compared with baseline weekly average.
- A CSBM responder was defined as a patient who experienced an increase of at least 1 CSBM per week from baseline.
In the two placebo-controlled studies (Study 04 and 05), plecanatide treatment resulted in a significantly greater percentage of overall responders compared with placebo. The percentage of overall responders in Study 04 was 30.2% with plecanatide 3 mg and 17.8% with placebo (p<0.001 vs. placebo), and in Study 05 was 21.5% with 3 mg (p=0.009) and 14.2% with placebo.
In Studies 04 and 05, a third randomized treatment arm of TRULANCE 6 mg once daily did not demonstrate additional treatment benefit over the 3 mg dose. Therefore, TRULANCE 6 mg once daily is not recommended.
Table 5: Primary Efficacy of TRULANCE in IBS-C (ITT Population)
Secondary Endpoints
Three key secondary efficacy endpoints were assessed: sustained efficacy responder; change from baseline in stool consistency and change from baseline in severity of straining with bowel movements. Sustained efficacy responders were patients who were weekly responders i.e., met the criteria for abdominal pain intensity and CSBM responder in the same week for at least 6 of
| Study 04 | |||
|---|---|---|---|
Placebo N = 354 | TRULANCE 3 mg N = 351 | Treatment Difference [95% CI] | |
6/12-week Overall Responder (Abdominal Pain and CSBM Responder) | 17.8% | 30.2%a | 12.4% [6.1%, 18.6%] |
| Study 05 | |||
Placebo N = 379 | TRULANCE 3 mg N = 377 | Treatment Difference [95% CI] | |
| 6/12-week Overall Responder (Abdominal Pain and CSBM Responder) | 14.2% | 21.5%b | 7.2% [1.8%, 12.7%] |
a p<0.001, b p=0.009 CI= Confidence Interval, CSBM=Complete Spontaneous Bowel Movement Abdominal pain score based on 11-point numerical rating scale (NRS) (0=none, 10=very severe) | |||
the 12 treatment weeks and at least 2 of the 4 treatment weeks in month 3 of treatment.
In both studies, plecanatide treatment resulted in a significantly greater percentage of sustained efficacy responders. Plecanatide demonstrated significant improvements in stool consistency and straining scores compared with placebo in both studies. For each study, significant differences from placebo in mean change from baseline began at week 1 and continued throughout the treatment period (Table 5).
Table 6: Key Secondary Efficacy of TRULANCE in IBS-C ITT Population
| Study 04 | |||
|---|---|---|---|
Placebo N = 354 | TRULANCE 3 mg N = 351 | Treatment Difference [95% CI] | |
| Sustained Efficacy Responder (Abdominal pain and CSBM responder for 6/12 weeks and 2/4 weeks in month 3 of treatment) | 17.2% | 28.2%a | 10.9% [4.8%, 17.1%] |
| Change from baseline over 12-week period (LS mean): Stool consistency | 0.98 | 1.51a | 0.53 [0.33%, 0.72%] |
| Change from baseline over 12-week period (LS mean): Straining | -1.58 | -2.23a | -0.66 [-0.94%, -0.37%] |
| Study 05 | |||
Placebo N = 379 | TRULANCE 3 mg N = 377 | Treatment Difference [95% CI*] | |
| Sustained Efficacy Responder (Abdominal pain and CSBM responder for 6/12 weeks and 2/4 weeks in month 3 of treatment) | 14.0% | 20.7%b | 6.7% [1.3%, 12.1%] |
| Change from baseline over 12-week period (LS mean): Stool consistency | 0.84 | 1.36a | 0.52 [0.31%, 0.73%] |
| Change from baseline over 12-week period (LS mean): Straining | -1.28 | -1.85a | -0.57 [-0.86%, -0.27%] |
a p<0.001, b p=0.015 CI= Confidence Interval Stool consistency is measured using the 7-point BSFS (Bristol Stool Form Scale) Severity of straining is measured using 11-point scale (0-10 rating; 0=no straining; 10=worst straining) | |||
Additional secondary efficacy endpoints included abdominal pain responder and stool frequency responder for at least 6 of 12 treatment weeks. The change from baseline endpoints were the change from baseline in 12-week CSBM and abdominal symptoms (pain, bloating, cramping, discomfort, and fullness) and Patient Global Questionnaires (IBS Disease Severity, Patient Global Rating of Change - IBS Symptoms, Patient Global Rating of Change - IBS Abdominal Pain).
For the 6/12-week abdominal pain and stool frequency endpoints statistically significantly more patients receiving TRULANCE were responders versus placebo. The analyses from the combined studies (Study 04 and Study 05) are presented in Table 6.
Table 7: Additional Secondary Efficacy of TRULANCE in IBS-C; Study 04 and Study 05 (ITT-E Population)
| 6/12-week Responder Endpoint | Study 04 and Study 05 | ||
|---|---|---|---|
Placebo (N=733) | TRULANCE 3mg (N=728) | Treatment Difference [95% CI] | |
| Abdominal pain responders | 27.3% | 36.8%* | 9.6% [4.8, 14.3] |
| Stool frequency responders | 31.4% | 40.9%* | 9.6% [4.7, 14.5] |
* p <0.001, CI= Confidence Interval A stool frequency responder is a patient who has an increase in the weekly CSBM rate of 1 or more CSBMs per week compared with baseline | |||
For the change from baseline endpoints, patients who received TRULANCE demonstrated significantly greater improvements compared to patients receiving placebo in abdominal symptoms (bloating, cramping, discomfort, fullness, and pain) two weeks after treatment initiation and were maintained throughout the treatment period. In both studies, improvements in the frequency of CSBMs/week from baseline were observed in week 1, with improvement maintained through week 12. The difference between the 3 mg TRULANCE group and the placebo group in the mean change of CSBMs/week from baseline to week 12 was 0.48 CSBMs/week (p<0.001).
Table 8: Change from Baseline endpoints; Linear Mixed-effects Model, Study 04 and Study 05 (ITT-E Population)
| Change from baseline over 12- week period (LS mean) | Study 04 and Study 05 | ||||||||
|---|---|---|---|---|---|---|---|---|---|
Placebo (N=733) | TRULANCE 3mg (N=728) | LSMD [95% CI] | |||||||
| CSBM frequency rate | 0.74 | 1.22a | 0.48 [0.28, 0.69] | ||||||
Abdominal symptoms: pain (11-point NRS)* | -1.26 | -1.57a | -0.31 [-0.50, -0.13] | ||||||
Abdominal symptoms: bloating (11-point NRS)* | -1.19 | -1.51a | -0.31 [-0.49, -0.13] | ||||||
Abdominal symptoms: cramping (11-point NRS)* | -1.25 | -1.53b | -0.27 [-0.47, -0.08] | ||||||
Abdominal symptoms: discomfort (11-point NRS)* | -1.25 | -1.56a | -0.31 [-0.49, -0.13] | ||||||
Abdominal symptoms: fullness (11-point NRS)* | -1.22 | -1.53a | -0.31 [-0.49, -0.13] | ||||||
a p<0.001, b p=0.005 LSMD=Least Square Mean Difference, CSBM=Complete Spontaneous Bowel Movement CI= Confidence Interval, PGR=Patient Global Rating *11-point Numeric Rating Scale (NRS) from 0 (NO) to 10 (WORST POSSIBLE). The exact descriptors for each symptom rating will be appropriate for each symptom (e.g. for abdominal pain, 0 = no pain, 10 = worst possible pain). | |||||||||
A statistically significant improvement in SBMs within 24 hours of the first dose was seen in both Study 04 and Study 05 for plecanatide 3 mg compared to placebo. In Study 04, the responder rate for SBM within 24 hours after the first dose of study drug was 33.3% for placebo versus
47.9% for plecanatide 3 mg (p<0.001). In Study 05, the responder rate for SBM within 24 hours after the first dose of study drug was 31.4% for placebo versus 41.6% for Plecanatide 3 mg (p=0.003).
Patient Global Rating (PGR) Assessments
PGR - IBS disease severity was measured by asking patients to rate the severity of their IBS symptoms at their worst over the past 7 days, using a 5-point scale (1 -none, 5- very severe). Over a 12 week period, patients treated with TRULANCE had a significant change in IBS disease severity versus placebo (-1.0 (TRULANCE) vs -0.8 (Placebo); p<0.001). The LS mean difference between TRULANCE and placebo was -0.2; 95%CI (-0.3, -0.1). Reduction in PGR - IBS disease severity scores were observed after 1-2 weeks of treatment and at each subsequent treatment time point in patients who received TRULANCE compared with the placebo group.
PGR for change in IBS symptoms was also evaluated by asking patients how they would rate their Irritable Bowel Syndrome (IBS) signs and symptoms overall over the past 7 days, using a 5-point scale (-2 - significantly worse, 0 – unchanged, +2 significantly relieved). Over a 12 week period, patients treated with TRULANCE had a significant change in IBS symptoms versus placebo (+1.1 (TRULANCE) vs +0.9 (Placebo); p<0.001). The LS mean difference between TRULANCE and placebo was +0.2; 95%CI (0.1, 0.3).
Following completion of the study drug treatment period, patients continued to record data in the daily diary for a 2-week Post-Treatment Period. During this time, TRULANCE-treated patients generally returned to baseline but did not worsen below baseline for these study endpoints.
Chronic Idiopathic Constipation (CIC)
The efficacy of TRULANCE for the management of symptoms of CIC was established in two double-blind, placebo-controlled, randomized, multicenter clinical studies in adult patients: SP304203-00 (Study 00) and SP304203-03 (Study 03). In the Intention to- Treat (ITT) population, a total of 905 patients (Study 00) and 870 patients (Study 03) were randomized 1:1 to either placebo or TRULANCE 3 mg, once daily. In clinical studies, study medication was administered without respect to food intake. Demographics for these studies included an overall mean age of 45 years (range 18 to 80 years), 80% female, 72% white, and 24% black.
Table 9 - Summary of Patient Demographics Supporting Efficacy of TRULANCE in the Treatment of CIC (Intention-to-Treat [ITT] Population)
| Trial # | Trial Design / Duration | Oral Dosage | Study Subjects (N) [Female/Male] | Mean Age (Range) | Mean Baseline Characteristics (Standard Deviation) |
| 00 | Phase 3, randomized, DB, PBO-ctrl, repeat-dose study evaluating efficacy and safety of plecanatide | Once daily dose Placebo 3 mg 6 mg | 452 (357/95) 453 (368/85) 441 (362/79) | 18-80 | CSBMs/week 0.4 ± 0.6 0.3 ± 0.5 0.3 ± 0.5 |
| 03 | Phase 3, randomized, DB, PBO-ctrl, repeat-dose study evaluating efficacy and safety of plecanatide | Once daily dose Placebo 3mg 6mg | 445 (350/95) 443 (345/98) 449 (353/96) | 18-80 | 0.3 ± 0.5 0.3 ± 0.6 0.3 ± 0.4 |
| CSBM=Complete Spontaneous Bowel Movement | |||||
To be eligible for the studies, patients were required to meet modified Rome III criteria for at least 3 months prior to the screening visit, with symptom onset for at least 6 months prior to diagnosis. Rome III criteria were modified to require that patients report less than 3 defecations per week, rarely have a loose stool without the use of laxatives, not use manual maneuvers to facilitate defecations, and not meet criteria for IBS-C. In addition, patients were required to report at least two of the following symptoms:
- Straining during at least 25% of defections.
- Lumpy or hard stool in at least 25% of defecations.
- Sensation of incomplete evacuations for at least 25% of defecations.
- Sensation of anorectal obstruction/blockage for at least 25% of defecations.
Patients who met these criteria were also required to demonstrate the following during the last 2 weeks of the screening period:
- Less than 3 complete spontaneous bowel movements (CSBMs) (a CSBM is an SBM that is associated with a sense of complete evacuation) in each of the two weeks.
- Bristol Stool Form Scale (BSFS) of 6 or 7 in less than 25% of spontaneous bowel movements (SBMs) (an SBM is a bowel movement occurring in the absence of laxative use)
One out of the following three:
- BSFS of 1 or 2 in at least 25% of defecations.
- A straining value recorded on at least 25% of days when a BM was reported.
- At least 25% of BMs result in a sense of incomplete evacuation.
The efficacy of TRULANCE was assessed using a responder analysis and change-from-baseline in CSBM (Complete Spontaneous Bowel Movement) and SBM (Spontaneous Bowel Movement) endpoints. Efficacy was assessed using information provided by patients on a daily basis in an electronic diary.
Primary Endpoint
The primary endpoint was the proportion of patients who were durable overall CSBM responders over the 12-week treatment period. A CSBM weekly responder was defined as a patient who had ≥3 CSBMs per week and an increase from baseline of ≥1 CSBM for that week. An overall CSBM responder was defined as a patient who was a weekly responder for at least 9 of the 12 treatment weeks, and a durable overall CSBM responder was also a weekly responder in at least 3 of the last 4 weeks.
In the two placebo-controlled studies (Study 00 and 03), plecanatide treatment resulted in a significantly greater percentage of overall responders compared with placebo. The percentage of overall responders in Study 00 was 21% with plecanatide 3 mg and 10% with placebo and in Study 03 was 21% with 3 mg and 13% with placebo.
In Studies 00 and 03, a third randomized treatment arm of TRULANCE 6 mg once daily did not demonstrate additional treatment benefit over the 3 mg dose. Therefore, TRULANCE 6 mg once daily is not recommended.
Table10: Primary Efficacy of TRULANCE in CIC ITT Population
c = Primary endpoint defined as a patient who had a least 3 CSBMs in a given week and an increase of at least 1 CSBM from baseline in the same week for at least 9 weeks out of the 12-week treatment period and at least 3 of the last 4 weeks of the study.
Secondary Endpoint
The secondary endpoints included changes from baseline over the 12-week treatment period in weekly CSBM and SBM frequencies, and stool consistency as measured by BSFS (Bristol Stool Form Scale).
Table 11: Key Secondary Efficacy of TRULANCE in CIC (ITT Population)
| Study 00 | |||
|---|---|---|---|
Placebo N = 452 | TRULANCE 3 mg N = 453 | Treatment Difference [95% CI] | |
| CSBM frequency (across the 12-week treatment period) | 1.22 | 2.46 | 1.24 [0.87, 1.62] |
| SBM frequency (across the 12-week treatment period) | 1.27 | 3.19 | 1.92 [1.43, 2.42] |
| Stool consistency (BSFS; across the 12-week treatment period) | 0.77 | 1.53 | 0.76 [0.61, 0.90] |
| Straining score (across the 12-week treatment period) | -0.57 | -0.92 | -0.35 [-0.45, -0.25] |
| Study 03 | |||
| Study 00 | |||
|---|---|---|---|
Placebo N = 452 | TRULANCE 3 mg N = 453 | Treatment Differencea [95% CIb] | |
| Durable Overall CSBM Responderc | 10.2% | 21.0%a | 11% [6.1%, 15.4%] |
| Study 03 | |||
Placebo N = 440 | TRULANCE 3 mg N = 430 | Treatment Differencea [95% CIb ] | |
| Durable Overall CSBM Responderc | 12.8% | 20.1%a | 7% [2.6%, 12.4%] |
a p<0.005 bCI= Confidence Interval | |||
Placebo N = 445 | TRULANCE 3 mg N = 443 | Treatment Difference [95% CI*] | |||||||
| CSBM frequency (across the 12-week treatment period) | 1.37 | 2.27 | 0.90 [0.55, 1.24] | ||||||
| SBM frequency (across the 12-week treatment period) | 1.50 | 2.59 | 1.10 [0.69, 1.50] | ||||||
| Stool consistency (BSFS; across the 12-week treatment period) | 0.87 | 1.49 | 0.62 [0.47, 0.78] | ||||||
| Straining score (across the 12-week treatment period) | 0.61 | -0.89 | -0.27 [-0.38, -0.17] | ||||||
CI= Confidence Interval Stool consistency is measured using the 7-point BSFS (Bristol Stool Form Scale) Severity of straining is measured using 5-point scale (0-4 rating; 0=no straining; 4=worst straining) | |||||||||
A statistically significant improvement in CSBMs and SBMs within 24 hours of the first dose was seen in both Study 00 and Study 03 for plecanatide 3 mg compared to placebo. In Study 00, the responder rate for CSBMs within 24 hours after the first dose of study drug was 13.3% for placebo versus 28.7% for plecanatide 3 mg (p<0.001). The responder rate for SBMs within 24 hours after the first dose of study drug was 39.8% for placebo versus 59.2% for plecanatide 3 mg (p<0.001). In Study 03, the responder rate for CSBMs within 24 hours after the first dose of study drug was 12.1% for placebo versus 21.4% for plecanatide 3 mg (p<0.001). The responder rate for SBMs within 24 hours after the first dose of study drug was 36.4% for placebo versus 43.6% for plecanatide 3 mg (p=0.028).
16 NON-CLINICAL TOXICOLOGY
Single-dose Toxicity
In mice, plecanatide was detected in plasma when administered a single oral dose of 200 and 2000 mg/kg but not at the low dose of 20 mg/kg. There were no plecanatide-related effects observed on survival, body weight, food consumption, clinical observations, or macroscopic evaluations. The No-Observed-Adverse-Effect-Level (NOAEL) in mice was determined to be 2000 mg/kg.
In cynomolgus monkeys, oral administration of plecanatide at doses of 25, 250 and 2000 mg/kg resulted in diarrhea and change in color and/or odor of stools (loose and/or liquid feces). These clinical signs were dose related and lasted for 4 days in the 2000mg/kg group. A single oral dose of plecanatide up to 2000 mg/kg was well tolerated in cynomolgus monkeys. The NOAEL in monkeys was determined to 250 mg/kg.
There were no plecanatide-related effects observed on survival, body weight, food consumption, clinical observations, or macroscopic evaluations in rats and monkeys.
Repeat-dose Toxicity
Repeated-dose studies of orally administered plecanatide have been conducted in mice, rats and monkeys. In a 7-day oral dose range-finding study in mice there was no mortality or any plecanatide-related adverse clinical findings observed at doses up to 2000 mg/kg/day. The NOAEL for plecanatide in this study was determined to be 2000 mg/kg/day. In the 28-day repeat dose oral toxicity studies due to the poor tolerability (death and/or moribundity) at the 2000 mg/kg/day, the high dose was reduced to 1200 mg/kg/day and an additional dose of 1000 mg/kg/day was added to the 28-day study. The NOAEL for this study was 200 mg/kg/day due to the death of one mouse at 1000mg/kg/day which was plecanatide related.
In a 14-day repeated-dose oral toxicity study in rats and monkeys, the administration of plecanatide at dose levels up to 50 mg/kg/day in rats and up to 250 mg/kg/day in monkeys was associated with no notable clinical findings in rats and reversible changes in stool consistency in monkeys.
In a 13-week repeated-dose oral toxicity study rats were administered doses up to 300 mg/kg/day and monkeys up to 100mg/kg/day. In rats no plecanatide-related deaths or any notable clinical findings of toxicity were observed. In monkeys’ reversible changes in stool consistency which increased with dose were noted and is considered as a pharmacologically expected effect of plecanatide. The NOAEL for plecanatide in rats and monkeys is 300 mg/kg/day and 100 mg/kg/day respectively when administered orally for 13 weeks. During a 13-week repeated-dose oral toxicity study in mice, histological changes (synovial hyperplasia/hypertrophy), acute necrosis and hemorrhage of the pituitary was observed in the higher doses (200 and 800 mg/kg/day). The NOEL in mice was 20 mg/kg/day when administered orally once daily for 13 weeks.
In a 26-week repeated-dose oral toxicity study in mice dose levels up to 400 mg/kg/day was well-tolerated with no mortality or adverse findings of toxicity related to plecanatide. Hypertrophy and hyperplasia of synovial cells in the tibiofemoral joint observed in one mouse was considered a spontaneous event. The NOAEL was 400 mg/kg/day in mice administered plecanatide orally for 26 weeks.
In a 39-week study in monkeys dosed up to 100mg/kg/day, dose-related changes in stool consistency (loose and/or liquid stools) were noted in both sexes in all treated levels during the study. This was considered a pharmacologically expected effect of plecanatide and was not considered adverse because it was not associated with changes in body weight, chronic dehydration, or microscopic correlates in the GI tract. The NOAEL was 100 mg/kg/day in monkeys administered plecanatide orally for 39 weeks.
Carcinogenicity
The carcinogenic potential of plecanatide was assessed in 2-year carcinogenicity studies in mice and rats. Plecanatide was not tumorigenic in mice at oral doses up to 90 mg/kg/day or in rats at oral doses up to 100 mg/kg/day.
Genotoxicity
Plecanatide was not genotoxic in the in vitro bacterial reverse mutation (Ames) assay, in vitro mouse lymphoma mutation assay, or the in vivo mouse bone marrow micronucleus assay.
Reproductive and Developmental Toxicity
Plecanatide had no effect on fertility or reproductive function in male or female mice at oral doses of up to 600 mg/kg/day.
Studies in Juvenile Animals: In a dose-finding tolerability study, when administered orally for
14 days, plecanatide was tolerated at doses up to 300mg/kg/day for 14 days in juvenile mice when treatment was initiated on post-natal Day (PND) 21. Decreased motor activity followed by mortality was observed in juvenile mice treated with plecanatide on PND 14.
In a 14-week repeated-dose oral toxicity study in juvenile mice initiated on PND 14 through PND 111, there was an increase in mortality following the first dose of plecanatide on PND 14 in the group PND14-111 compared to PND 21-111 group. Except for the pups that died after the first dose of 10mg/kg/day, plecanatide was well tolerated at doses up to and including 300 mg/kg/day. No differences among the groups in the type or frequency of clinical signs, body weights and body weight changes, sexual maturation, or gross necropsy findings were attributed to plecanatide. The NOAELs for toxicity were 3 mg/kg/day in the pups given plecanatide on PNDs 14 through 111, and 300 mg/kg/day in the pups given plecanatide on PNDs 21 through 111.
The increased sensitivity of juvenile mice to plecanatide may be related to the increased expression of intestinal GC-C receptors in young animals or possibly other factors such as those related to an immature GI system (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION, Special Populations, CLINICAL PHARMACOLOGY).