


Product Monograph - Vistitan
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form/ Strength | All Nonmedicinal Ingredients |
| Ophthalmic | Ophthalmic Solution/ 0.03% w/v bimatoprost | Benzalkonium chloride 0.005% w/v as preservative, sodium chloride, sodium phosphate dibasic anhydrous, citric acid monohydrate, and purified water. Sodium hydroxide and/or hydrochloric acid may be added to adjust pH. |
INDICATIONS AND CLINICAL USE
Vistitan (bimatoprost ophthalmic solution 0.03% w/v) is indicated for:
- the reduction of elevated intraocular pressure in patients with open angle glaucoma or ocular hypertension
Geriatrics (> 65 years of age):
No overall clinical differences in safety or effectiveness have been observed between elderly and other adult patients. Use as for adult patients.
Pediatrics (<18 years of age):
Not recommended for pediatric use. Safety and effectiveness in pediatric patients have not been established.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
WARNINGS AND PRECAUTIONS
General
Bimatoprost ophthalmic solutions have been reported to cause changes to pigmented tissue. The changes include increased pigmentation and growth of eyelashes and increased pigmentation of the iris and periorbital tissue (eyelid). The increased iris pigmentation may be permanent.
Bimatoprost ophthalmic solution 0.03% w/v may gradually change eye color, increasing the amount of brown pigment in the iris by increasing the number of melanosomes (pigment granules) in melanocytes. The long-term effects on the melanocytes and the consequences of potential injury to the melanocytes and/or deposition of pigment granules to other area of the eye are currently unknown. The change in iris color occurs slowly and may not be noticeable for several months to years. Pigmentation is expected to increase as long as bimatoprost ophthalmic solution 0.03% w/v is administered. In clinical studies, noticeable darkening of the iris has been reported in 1.5% of patients treated for 12 months with bimatoprost ophthalmic solution 0.03% w/v at the proposed dose of one drop once daily in each affected eye (1.1% of patients treated for 6 months).
Patients should be informed of the possibility of iris color change. In addition, patients who are expected to receive treatment in only one eye should be informed about the potential for increased brown pigmentation of the iris, periorbital tissue, and eyelashes in the treated eye and thus, heterochromia between the eyes. They should be advised of the potential for a disparity between the eyes in length, thickness, and /or number of eyelashes.
Typically the brown pigmentation around the pupil is expected to spread concentrically towards the periphery in affected eyes, but the entire iris or parts of it may also become more brownish. Until more information about increased brown pigmentation is available, patients should be examined regularly and, depending on the clinical situation, treatment may be stopped if increased pigmentation ensues. The increase in brown iris pigment is not expected to progress further upon discontinuation of treatment, but the resultant color change may be permanent. Neither nevi nor freckles of the iris are expected to be affected by treatment.
There is the potential for hair growth to occur in areas where bimatoprost ophthalmic solution 0.03% w/v comes repeatedly in contact with the skin surface. Thus, it is important to apply Vistitan as instructed and to avoid it running onto the cheek or other skin areas.
There have been reports of bacterial keratitis associated with the use of multiple-dose containers of topical ophthalmic products. These containers had been inadvertently contaminated by patients who, in most cases, had a concurrent corneal disease or a disruption of the ocular epithelial surface. See Patient Medication Information.
Carcinogenesis and Mutagenesis
See Toxicology.
Hepatic/Biliary/Pancreatic
Bimatoprost ophthalmic solution 0.03% w/v has not been studied in patients with hepatic impairment and should therefore be used with caution in such patients.
Occupational Hazards
Based on the pharmacodynamic profile, bimatoprost is not expected to influence a patient’s ability to drive or operate machinery. As with any ocular medication, if transient blurred vision occurs at instillation, the patient should wait until the vision clears before driving or using machinery.
Ophthalmologic
Vistitan should be used with caution in patients with active intraocular inflammation (e.g. uveitis).
Macular edema, including cystoid macular edema, has been reported during treatment with bimatoprost ophthalmic solution 0.03% w/v for elevated intraocular pressure (IOP).
Vistitan should be used with caution in aphakic patients, in pseudophakic patients with a torn posterior lens capsule, or in patients with known risk factors for macular edema (e.g. intraocular surgery, retinal vein occlusions, ocular inflammatory disease and diabetic retinopathy).
Bimatoprost ophthalmic solution 0.03% w/v has not been studied in patients with inflammatory ocular conditions, neovascular, inflammatory, angle-closure glaucoma, congenital glaucoma or narrow-angle glaucoma.
There is a potential for the IOP-lowering effect of prostaglandin analogs to be reduced in patients with glaucoma or ocular hypertension when used with other prostaglandin analogs.
In bimatoprost ophthalmic solution 0.03% w/v studies in patients with glaucoma or ocular hypertension, it has been shown that more frequent exposure of the eye to more than one dose of bimatoprost daily may decrease the IOP-lowering effect. Patients using Vistitan with other prostaglandin analogs should be monitored for changes to their IOP.
The pivotal clinical studies included patients with pseudoexfoliative and pigmentary glaucoma, in numbers proportionate to the population. All of these patients responded positively to bimatoprost ophthalmic solution 0.03% w/v, however given the low absolute numbers of these patients enrolled no statistical significance can be concluded. None of these patients dropped out due to lack of efficacy or adverse experiences.
Vistitan (bimatoprost ophthalmic solution 0.03% w/v) contains the preservative benzalkonium chloride, which may be absorbed by and cause discoloration of soft contact lenses. Patients wearing soft (hydrophilic) contact lenses should be instructed to remove contact lenses prior to administration of Vistitan and wait at least 15 minutes following administration before reinserting soft contact lenses.
Cases of corneal calcification have been reported very rarely in association with the use of phosphate containing eye drops in some patients with significantly damaged corneas.
Renal
Bimatoprost ophthalmic solution 0.03% w/v has not been studied in patients with renal impairment and should therefore be used with caution in such patients.
Sexual Function/Reproduction
Bimatoprost did not impair fertility in male or female rats at doses of up to 0.6 mg/kg/day (approximately 103 times the human exposure based on blood area under the curve (AUC) levels).
Special Populations
Pregnant Women: In embryo/fetal developmental studies in pregnant mice and rats, abortion was observed at oral doses of bimatoprost which were at least 33 or 97 times, respectively, the intended human exposure as measured by area-under-the curve blood levels.
Maternal toxicity, evidenced by reduced gestation length, late resorptions, fetal death, postnatal mortality and reduced pup body weights were observed when female rats received oral doses which were at least 41 times the intended human exposure (based on blood AUC levels). Cohabitation times in the offspring were increased but neurobehavioural functions were not affected.
There are no adequate and well-controlled studies of bimatoprost ophthalmic solution 0.03% w/v administration in pregnant women. Because animal reproductive studies are not always predictive of human response, Vistitan should be administered during pregnancy only if the potential benefit justifies the potential risk to the fetus.
There has been no experience of pregnancy during clinical trials.
Nursing Women: It is not known whether bimatoprost is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Vistitan is administered to a nursing woman.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
In 12-month multi-center, double-blind, active-controlled clinical studies, most adverse events were ocular, mild to moderate, and not serious. The most frequently reported treatment related adverse event was conjunctival hyperemia (45% of patients treated with bimatoprost QD). Increased iris pigmentation was reported for 1.5 % of patients in the QD group.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The data presented below are taken from two randomized, multicentre, double-blind, parallel-group clinical studies, of 12 months duration, which were conducted on 1198 patients with glaucoma or ocular hypertension. Bimatoprost 0.03% w/v solution was administered once or twice daily and compared to timolol 0.5% w/v solution BID in a 2:2:1 ratio. Treatment-related adverse events reported from these studies (combined) are presented in Table 1. Adverse events were coded using the COSTART dictionary available at the time of the study, but are presented in Table 1 using MedDRA System Organ Class.
Table 1 - Number (%) of Patients in the 12 Month Phase 3 Studies with Treatment-Related Adverse Events Reported at an Incidence ≥ 1%
| Bimatoprost 0.03% w/v QD n=474 (%) | Bimatoprost 0.03% w/v BID n= 483(%) | Timolol 0.05% w/v BID n=241(%) | |
| Eye disorders | |||
| conjunctival hyperemia | 212 (44.7%) | 271 (56.1%) | 32 (13.3%) |
| growth of eyelashes | 202 (42.6%) | 259 (53.6%) | 12 (5.0%) |
| eye pruritus | 69 (14.6%) | 85 (17.6%) | 8 (3.3%) |
| eye dryness | 38 (8.0%) | 56 (11.6%) | 5 (2.1%) |
| burning sensation in eye | 33 (7.0%) | 32 (6.6%) | 25 (10.4%) |
| blepharal pigmentation | 26 (5.5%) | 55 (11.4%) | 1 (0.4%) |
| foreign body sensation | 26 (5.5%) | 48 (9.9%) | 5 (2.1%) |
| eye pain | 24 (5.1%) | 45 (9.3%) | 8 (3.3%) |
| visual disturbance | 24 (5.1%) | 37 (7.7%) | 11 (4.6%) |
| erythema eyelid | 18 (3.8%) | 19 (3.0%) | 2 (0.8%) |
| eyelash discoloration | 15 (3.2%) | 25 (5.2%) | 1 (0.4%) |
| eye discharge | 13 (2.7%) | 20 (4.1%) | 2 (0.8%) |
| irritation eye | 13 (2.7%) | 17 (3.5%) | 3 (1.2%) |
| blepharitis | 12 (2.5%) | 14 (2.9%) | 4 (1.7%) |
| superficial punctate keratitis | 12 (2.5%) | 11 (2.3%) | 6 (2.5%) |
| photophobia | 8 (1.7%) | 33 (6.8%) | 1 (0.4%) |
| allergic conjunctivitis | 7 (1.5%) | 7 (1.4%) | 0 (0.0%) |
| epiphora | 7 (1.5%) | 13 (2.7%) | 6 (2.5%) |
| iris pigmentation increased | 7 (1.5%) | 9 (1.9%) | 0 (0.0%) |
| visual acuity worsened | 7 (1.5%) | 7 (1.4%) | 2 (0.8%) |
| asthenopia | 6 (1.3%) | 15 (3.1%) | 1 (0.4%) |
| cataract NOS | 6 (1.3%) | 6 (1.2%) | 7 (2.9%) |
| conjunctival oedema | 6 (1.3%) | 9 (1.9%) | 3 (1.2%) |
| corneal erosion | 4 (0.8%) | 5 (1.0%) | 3 (1.2%) |
| stinging sensation eye | 4 (0.8%) | 10 (2.1%) | 4 (1.7%) |
| eyelid pruritus | 1 (0.2%) | 20 (4.1%) | 1 (0.4%) |
| General disorders and administration site conditions | |||
| asthenia | 6 (1.3%) | 7 (1.4%) | 2 (0.8%) |
| Infections and infestations | |||
| infection | 6 (1.3%) | 3 (0.6%) | 1 (0.4%) |
| Bimatoprost 0.03% w/v QD n=474 (%) | Bimatoprost 0.03% w/v BID n= 483(%) | Timolol 0.05% w/v BID n=241(%) | |
| Nervous system disorders | |||
| dizziness | 4 (0.8%) | 3 (0.6%) | 1 (1.2%) |
| headache | 16 (3.4%) | 15 (3.1%) | 9 (3.7%) |
| Psychiatric disorders | |||
| depression | 0 (0.0%) | 5 (1.0%) | 1 (0.4%) |
| Respiratory, thoracic and mediastinal disorders | |||
| rhinitis | 2 (0.4%) | 9 (1.9%) | 0 (0.0%) |
| Skin & subcutaneous tissue disorders | |||
| hirsutism | 5 (1.1%) | 7 (1.4%) | 0 (0.0%) |
| Vascular disorders | |||
| hypertension | 8 (1.7%) | 9 (1.9%) | 2 (0.8%) |
Treatment related adverse events resulted in the discontinuation of 5.7% of patients, principally for conjunctival hyperemia (3.4%). Only 1.1% of patients on bimatoprost ophthalmic solution 0.03% w/v QD were discontinued due to lack of efficacy.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Eye disorders: blepharospasm, conjunctiva (NOS), eyelid oedema, chalazion, eye oedema, hordeolum, conjunctival bleb, conjunctival folliculosis, eyelid (NOS), eyelid pain, iritis (ocular inflammation), keratitis, visual field defect, vitreous floaters, diplopia
Cardiac disorders: chest pain, palpitations
Gastrointestinal disorders: oral dryness, dyspepsia
General disorders and administration site conditions: liver function tests abnormal Immune system disorders: pruritus
Metabolism and nutrition disorders: peripheral oedema, hypercholesteremia Musculoskeletal and connective tissue disorders: arthritis
Nervous system disorders: somnolence, nervousness
Psychiatric disorders: anxiety, insomnia
Respiratory, thoracic and mediastinal disorders: bronchitis, cough increased, pharyngitis, sinusitis, dyspnea
Skin and subcutaneous tissue disorders: rash
Urogenital: cystitis, urine abnormality
Post-Market Adverse Drug Reactions
The following adverse reactions have been identified during postmarketing use of bimatoprost ophthalmic solution 0.03% w/v. Because postmarketing reporting is voluntary and from a population of uncertain size, it is not possible to reliably estimate the frequency of these reactions.
Eye disorders: eyelid oedema, macular oedema, deepened lid sulcus (enophthalmos), erythema (periorbital), ocular discomfort
Gastrointestinal disorders: nausea
Immune system disorders: hypersensitivity reaction including signs and symptoms of eye allergy and allergic dermatitis
Nervous System disorders: dizziness, headache
Respiratory, thoracic and mediastinal disorders: asthma, exacerbation of asthma Skin and subcutaneous tissue disorders: hair growth abnormal, skin discoloration Vascular disorders: hypertension
DRUG INTERACTIONS
Overview
No specific drug interaction studies have been conducted.
Drug-Drug Interactions
No drug-drug interactions are anticipated in humans since systemic drug concentrations of bimatoprost are extremely low (less than 0.2 ng/mL) following repeated ocular dosing and as metabolism and excretion involves multiple pathways.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
The recommended dosage is one drop in the affected eye(s) once daily in the evening. The dosage of Vistitan should not exceed once daily since it has been shown that more frequent administration may lessen the intraocular pressure (IOP) lowering effect, and increase the frequency and severity of adverse events (see WARNINGS and PRECAUTIONS, Ophthalmologic).
Missed Dose
Patients should be instructed to apply a single drop as soon as they remember, and then to return to their regular routine.
Administration
Patients should be instructed to avoid allowing the tip of the dispensing container to contact the eye or surrounding structures to avoid eye injury and contamination of the solution.
Vistitan may be used concomitantly with other topical ophthalmic drug products to lower IOP. If more than one topical ophthalmic drug is being used, the drugs should be administered at least five (5) minutes apart.
Contact lenses should be removed prior to instillation of Vistitan and may be reinserted 15 minutes following its administration (see WARNINGS and PRECAUTIONS, Ophthalmologic).
OVERDOSAGE
For management of a suspected drug overdose, including accidental ingestion, contact your regional Poison Control Centre.
No information is available on overdosage in humans. If overdose with Vistitan occurs, treatment should be symptomatic.
In oral (by gavage) mouse and rat studies, doses up to 100 mg/kg/day did not produce any toxicity. This dose, expressed as mg/m2, is at least 70 times higher than the amount of bimatoprost to which a 10 kg child would be exposed were it to accidentally ingest one 7.5 mL bottle of bimatoprost ophthalmic solution 0.03% w/v.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Bimatoprost is a synthetic prostamide analogue and is structurally related to prostaglandin F2α in that the carboxylic acid group is replaced with an electronically neutral substituent. Its mechanism of action resembles that of prostamide F2α, a naturally occurring substance. Bimatoprost exhibits no meaningful pharmacological activity at known prostaglandin receptors as well as no uterotonic or mitogenic activity. Studies suggest that it lowers IOP by increasing uveoscleral and trabecular meshwork outflow, with no significant effect on aqueous humor inflow. Pharmacodynamic studies in humans demonstrated a significant 30-35% decrease in outflow resistance compared to vehicle treated eyes based on tonographic data and calculated values of apparent outflow resistance. The ocular hypotensive effect does not involve a COX-dependent mechanism.
Pharmacodynamics
The effect of bimatoprost ophthalmic solution 0.03% w/v within the first 12 hours of dosing was evaluated in two studies. When dosed in the morning, bimatoprost began to take effect within 4 hours after initial instillation, and was followed by continued decreases in IOP through 12 hours. The effect of bimatoprost 0.03% w/v ophthalmic solution between 12 and 24 hours post-instillation also was evaluated. Mean IOP at 12 hours post-dosing was 17.7 mmHg and 16.9 mmHg 24 hours after the last dose. Based on this information, once-daily evening dosing is recommended so that the time of anticipated maximal efficacy of the drug coincides with the morning hours (08:00 to 11:00 AM) when untreated IOP is usually highest.
Pharmacokinetics
After one drop of bimatoprost ophthalmic solution 0.03% w/v was administered once daily to both eyes of 15 healthy subjects, blood bimatoprost concentrations peaked within 10 minutes
after dosing and were below the lower limit of detection (0.025 ng/mL) in most subjects within 1.5 hours after dosing.
Systemic exposure after repeated ocular application is low. Steady state was achieved after one week of once daily dosing with one drop of bimatoprost ophthalmic solution 0.03% w/v to both eyes, with mean Cmax values of 0.07 and 0.08 ng/mL on day 7 and 14, respectively, and mean AUC 0-24h of 0.074 and 0.096 ng•hr/mL on day 7 and 14, respectively.
In patients with glaucoma or ocular hypertension, bimatoprost blood concentrations were similar to those observed in normal healthy subjects.
There was no significant systemic drug accumulation over time with the once daily dosing regimen. Mean blood concentration was around 0.08 ng/mL after 12 months of QD or BID dosing. The once daily regimen corresponded to a total exposure of 6.13 mg (one 28 mcL drop in each eye once a day for 12 months) or 0.00028 mg/kg/day for a 60-kg individual over 12 months.
Absorption: Bimatoprost is rapidly absorbed across the human cornea and sclera, with scleral penetration being more efficient. Animal studies show that it is well distributed into ocular tissues following ocular administration, where only minimal metabolism occurs in humans.
Distribution: Bimatoprost is moderately distributed into body tissues with a steady-state volume of distribution of 0.67 L/kg. In human blood, bimatoprost resides mainly in the plasma. Approximately 12% of bimatoprost remains unbound in human plasma.
Metabolism: Bimatoprost is the major circulating species in the blood once it reaches the systemic circulation following ocular dosing. Bimatoprost then undergoes oxidation, N-deethylation and glucuronidation to form a diverse variety of metabolites. Studies using human liver microsomes and recombinant human P450 isozymes, identified CYP 3A4 as one of the enzymes involved in the metabolism of bimatoprost in humans. However, since multiple enzymes and pathways are involved in the biotransformation of bimatoprost, no significant drug-drug interactions are anticipated.
Bimatoprost is only minimally metabolized in ocular tissues in humans, and is active in its intact form, without metabolic modification.
Excretion: Following an intravenous dose of radiolabelled bimatoprost (3.12 mcg/kg) to six healthy subjects, the maximum blood concentration of unchanged drug was 12.2 ng/mL and decreased rapidly with an elimination half-life of approximately 45 minutes. The total blood clearance of bimatoprost was 1.5 L/hr/kg. Up to 67% of the administered dose was excreted in the urine while 25% of the dose was recovered in the feces. Both urinary and fecal routes are important pathways for elimination of the parent compound and its metabolites, following intravenous administration.
Special Populations and Conditions
Geriatrics: Elderly individuals (>65 years) exhibited higher systemic levels but this was not considered to be clinically relevant since bimatoprost had a similar efficacy and safety profile in
both the young and elderly that participated in the clinical trials.
STORAGE AND STABILITY
Vistitan (bimatoprost ophthalmic solution 0.03% w/v) should be stored in the original container at 2ºC - 25ºC. Discard unused solution at the end of treatment. Discard the unused portion 30 days after opening the bottle.
Keep in a safe place out of the reach of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Vistitan (bimatoprost ophthalmic solution 0.03% w/v) is supplied in the following size:
5 mL: 5 mL solution in 8 mL sterile white opaque plastic ophthalmic dispenser bottle closed with turquoise cap.
Vistitan is a clear, isotonic, buffered, preserved, colorless, sterile solution with a pH of 7.3 ± 0.5, and an osmolality of approximately 290 mOsmol/kg.
Each mL of Vistitan contains bimatoprost 0.3 mg with the following non-medicinal ingredients: benzalkonium chloride 0.05 mg as preservative, sodium chloride, sodium phosphate dibasic anhydrous, citric acid monohydrate, and purified water. Sodium hydroxide and/or hydrochloric acid may be added to adjust pH.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: bimatoprost
Chemical name: (Z)-7-[(1R,2R,3R,5S)-3,5-Dihydroxy-2-[1E,3S)-3-hydroxy-
5-phenyl-1-pentenyl]cyclopentyl]-5-N-ethylheptenamide
Molecular formula: C25H37NO4
Molecular mass: 415.58 g/mol
Structural formula:
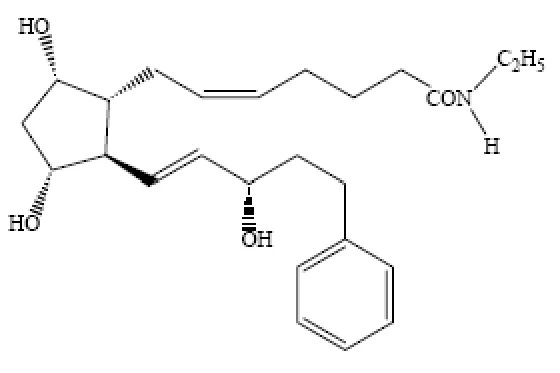
Physicochemical properties: Bimatoprost is a white to off-white powder, which is very soluble in ethyl alcohol and methyl alcohol and slightly soluble in water.
CLINICAL TRIALS
Study demographics and trial design
Table 2- Summary of patient demographics for clinical trials in specific indication
| Study # | Trial design | Dosage, route of administration and duration | Study Subjects (n=number) | Mean age (Range) | Gender |
| 008 | Randomized, multicentre, double- blind, parallel | Bimatoprost 0.03% w/v QD Bimatoprost 0.03% w/v BID Timolol 0.5% w/v BID Ophthalmic; one drop into each affected eye pet regimen above 12 months | Bim QD: 240 Bim BID: 240 Tim BID: 122 | 60.7 years (22 - 90) | M: 279 F: 323 |
| 009 | Bim QD: 234 Bim BID: 243 Tim BID: 119 | 62.4 years (26 - 92) | M: 262 F: 334 |
Two randomized, multicentre, double-blind, parallel-group clinical studies, of 12 months duration, were conducted on 1198 patients with glaucoma or ocular hypertension. Bimatoprost 0.03% w/v solution was administered once or twice daily and compared to timolol 0.5% w/v solution BID in a 2:2:1 ratio. The recommended dosage is one drop in the affected eye(s) once daily in the evening. The dosage of bimatoprost ophthalmic solution 0.03% w/v should not exceed once daily since it has been shown that more frequent administration may decrease the intraocular pressure lowering effect. The mean baseline IOP of these patients was 26 mmHg (range of 22 to 34 mmHg). Timolol dosed twice daily was the active control. During the 12 month treatment, mean decreases ranged from 7.92 to 8.75 mmHg with bimatoprost QD compared to decreases of 6.03 to 6.48 mmHg with timolol BID. The evening QD regimen maintained lowering of IOP throughout the 24-hour interval. The mean change in IOP from baseline was statistically significantly greater with bimatoprost than timolol at all of the assessment periods over the 12 month duration of the trial (See Table 3).
Study results
Table 3 - Results from Studies 008 and 009. Effect on Intraocular Pressure (IOP)
| Mean IOP | Mean Change from Baseline IOP | ||||
Timepoint Visit | Bimatoprost once daily (N = 474) | Timolol (N = 241) | Bimatoprost once Daily (N = 474) | Timolol (N = 241) | |
| 8 AM* | Baseline | 25.95 | 25.81 | --- | --- |
| Month 3 | 17.20a | 19.32 | -8.75b | -6.48 | |
| Mean IOP | Mean Change from Baseline IOP | ||||
Timepoint Visit | Bimatoprost once daily (N = 474) | Timolol (N = 241) | Bimatoprost once Daily (N = 474) | Timolol (N = 241) | |
| Month 6 | 17.67a | 19.34 | -8.28b | -6.48 | |
| Month 12 | 18.03 | 19.78 | -7.92b | -6.03 | |
10 AM 4 PM | Baseline | 24.67 | 24.06 | --- | --- |
| Month 3 | 16.38a | 18.24 | -8.29b | -5.82 | |
| Month 6 | 16.59 | 18.47 | -8.09b | -5.57 | |
| Month 12 | 17.03a | 18.77 | -7.64b | -5.29 | |
| Baseline | 23.80 | 23.23 | --- | --- | |
| Month 3 | 16.72a | 18.48 | -7.08b | -4.7 | |
| Month 6 | 16.81a | 18.68 | -7.01b | -4.53 | |
| Month 12 | 17.41a | 19.24 | -6.39b | -3.96 | |
| 8 PMc | Baseline | 22.08 | 22.42 | --- | --- |
| Month 3 | 16.42a | 18.23 | -5.66b | -4.18 | |
| Month 6 | 16.61a | 19.16 | -5.47b | -3.25 | |
| Month 12 | 16.99a | 19.72 | -5.08b | -2.69 | |
*8 AM is the 12 Hours post-dosing timepoint.
Note: Dosing occurred following the 8 AM and 8 PM examinations.
a bimatoprost superior to timolol (p ≤0.001)
b bimatoprost superior to timolol based on mean changes from baseline (Dunnett’s test p ≤ 0.050). c 8 PM measurements taken at selected sites only (N=189).
Over the 12 month study duration bimatoprost predictably lowered IOP in over 90% of patients to 22 mmHg or less, with approximately 50% of patients having IOPs of 17mmHg or less (See Table 4).
Table 4: Distribution of IOP Over 12 Month Study Duration
| Timepoint visit | IOP (mmHg) | Bimatoprost QD (N = 474) | Timolol (N = 241) |
| Week 2 | ≤ 13 | 8.5% (40) | 5.8% (14) |
| > 13 to ≤ 17 | 41.5% (194) | 22.8% (55) | |
| > 17 to ≤ 22 | 43.4% (203) | 47.3% (114) |
| Timepoint visit | IOP (mmHg) | Bimatoprost QD (N = 474) | Timolol (N = 241) |
| > 22 | 6.6% (31) | 24.1% (58) | |
| Week 6 | ≤ 13 | 9.8% (46) | 2.9% (7) |
| > 13 to ≤ 17 | 40.1% (189) | 27.4% (66) | |
| > 17 to ≤ 22 | 42.0% (198) | 49.0% (118) | |
| > 22 | 8.1% (38) | 20.7% (50) | |
| Month 3 | ≤ 13 | 9.9% (47) | 4.6% (11) |
| > 13 to ≤ 17 | 46.6% (221) | 27.4% (66) | |
| > 17 to ≤ 22 | 36.5% (173) | 49.0% (118) | |
| > 22 | 7.0% (33) | 19.1% (46) | |
| Month 6 | ≤ 13 | 7.6% (36) | 3.3% (8) |
| > 13 to ≤ 17 | 41.6% (197) | 24.1% (58) | |
| > 17 to ≤ 22 | 42.0% (199) | 56.4% (136) | |
| > 22 | 8.9% (42) | 16.2% (39) | |
| Month 12 | ≤ 13 | 6.3% (30) | 2.5% (6) |
| > 13 to ≤ 17 | 39.5% (187) | 22.4% (54) | |
| > 17 to ≤ 22 | 44.5% (211) | 55.2% (133) | |
| > 22 | 9.7% (46) | 19.9% (48) |
Over the 12 month study duration only 1.1% of the patients were discontinued due to lack of efficacy.
Extension study of the two 12 month efficacy trials (studies 008 and 009) were conducted to evaluate the long term safety and efficacy of bimatoprost ophthalmic solution 0.03% w/v compared with timolol 0.5% w/v ophthalmic solution for up to four years of dosing. The number of patients enrolled and completing each year of the extension are summarized in the table below:
Table 5: Number of Patients Entering and Completing the Long-Term Extension Periods
Long Term Extension Months 12 to 241 | Long Term Extension Months 24 to 362 | Long Term Extension Months 36 to 482 | |
| Number of Patients Entering | 379 | 183 | 152 |
| Number of Patients Completing | 284 | 162 | 141 |
1Patients were treated with bimatoprost ophthalmic solution 0.03% w/v QD, bimatoprost ophthalmic solution 0.03% w/v BID, or Timolol BID
2 Patients were treated with bimatoprost ophthalmic solution 0.03% w/v QD or Timolol BID
Increased iris pigmentation was reported in 16/957 (1.7%) of patients receiving any dose of bimatoprost (i.e., once daily or BID) and occurred during the first year of treatment. There were no additional reports or increases in severity after the first year in 3/16 patients with increased pigmentation who continued treatment for an additional 3 years of dosing (4 years total treatment). However, this may be due in part to the small number of patients followed up or to the low sensitivity / expected variability of the photographic methods assessing pigmentation, or both.
No patients discontinued treatment with bimatoprost due to increased iris pigmentation. IOP reduction was maintained throughout the four years and mean IOP reduction from baseline was consistently greater with bimatoprost than with timolol at all follow up time points (p< 0.01).
Twenty-seven patients who completed the 4 year extension study were enrolled in an open label follow-up for an additional year of treatment with bimatoprost ophthalmic solution 0.03% w/v; 20 of these 27 patients were previously treated with bimatoprost for 4 years. One patient experienced an increase in iris pigmentation during the first year of treatment with bimatoprost, but no intensification of pigmentation was noted in this patient in the 5th year extension as compared to the baseline photography.
DETAILED PHARMACOLOGY
Animal Pharmacology
Ocular Studies: Studies in ocular normotensive and laser-induced ocular hypertensive cynomolgus monkeys indicated that bimatoprost potently reduces intraocular pressure. Five-day studies in ocular normotensive monkeys and one day studies in ocular hypotensive monkeys demonstrated that a 0.001% w/v dose of bimatoprost could significantly lower intraocular pressure. Five day studies in ocular normotensive Beagle dogs confirmed bimatoprost as a potent ocular hypotensive over a dose range of 0.001% to 0.1% w/v when given either once daily or twice daily.
Bimatoprost did not alter pupil diameter in monkeys at the 0.1% dose. This is in contrast to Beagle dog studies, where 0.001% to 0.1% w/v doses produced miosis.
Metabolism and Pharmacokinetics
Ocular Pharmacokinetics: Following a single ocular instillation of 3H-bimatoprost to rabbits and single and multiple ocular instillations to monkeys, bimatoprost was absorbed rapidly and was well distributed in the eye. The absorbed radioactivity was found mainly in the anterior segment of the eye and the highest concentrations of radioactivity were found in the conjunctiva, cornea, sclera, iris, and ciliary body in both rabbit and monkey eyes. Maximal concentrations in these tissues were reached within 0.5 to 2 hours post-dose. Twenty-four hours after the last dose in monkeys, bimatoprost concentrations in the ciliary body (the purported site of action) were still over 5-fold higher than the in vitro EC50 value of 14 ng/mL required for pharmacological
effect.
Systemic Absorption Following Ocular and Oral Administration: Bimatoprost was systemically absorbed after ophthalmic administration to rabbits and monkeys. The Cmax in plasma was 3.23 ng-eq/mL in monkeys following twice-daily ocular administration of 0.1% bimatoprost for 10 days and 6.28 ng-eq/mL in rabbits following a single administration of 0.1%. The oral bioavailability of bimatoprost was 40%, 29% and 3% in mice, rats and monkeys, respectively. The low oral bioavailability in monkeys was attributed to extensive first-pass metabolism.
Systemic Disposition after Intravenous Administration: Following intravenous administration to mice, rats and monkeys bimatoprost had a moderate apparent volume of distribution at steady state ranging from 2.1 to 6.0 L/kg. Bimatoprost had a mean residence time of 0.28 hr in mice, 0.42 hr in rats and 0.93 hr in monkeys, indicating that bimatoprost was rapidly eliminated in all three species. The mean blood clearance was 12, 9.5 and 2.4 L/hr/kg, respectively. In mice and rats, total blood clearance appeared to be greater than liver blood flow, indicating the involvement of extrahepatic metabolism.
Systemic Tissue Distribution: The unbound fraction of bimatoprost in mouse, rat, rabbit and monkey plasma ranged from 28 to 37% in vitro. The in vitro binding of bimatoprost to synthetic melanin was not extensive at approximately 20%, and was reversible. Following intravenous administration of 3H-bimatoprost to rats, either as a single dose or after daily injections for 21 days, radioactivity was rapidly distributed to all tissues and organs examined. The highest concentrations of radioactivity were seen in the gastrointestinal tract, liver, kidney and urinary bladder. The blood-to-plasma ratio of radioactivity was 0.75, indicating that bimatoprost remained in the plasma portion of the blood. By 168 hours post-dose, all radioactivity in the body was accounted for by tritiated water, and not by bimatoprost or its metabolites. Following a single intravenous administration of 3H-bimatoprost to pregnant rats, there was a low, but quantifiable, amount of drug transfer into the placenta, amniotic fluid and fetus. Following intravenous administration of 3H-bimatoprost to lactating rats, the concentrations of radioactivity found in milk were similar to those seen in plasma. Therefore the amount of drug related material transferred into milk at the clinical dose level is expected to be extremely low.
Ocular Metabolism: After ophthalmic administration, bimatoprost was extensively metabolized in all of the ocular tissues in the rabbit eye. In contrast, bimatoprost, at exaggerated doses, was only minimally metabolized in the monkey eye following ophthalmic administration.
Systemic Metabolism: Following a single intravenous administration to rats and monkeys, bimatoprost was extensively metabolized by glucuronidation, hydroxylation, deamidation and N-deethylation, with glucuronidated metabolites accounting for the majority of the drug-related material in the blood, urine and faeces of both species. In pregnant rats, at least 22 metabolites were detected in the maternal tissues following a single intravenous administration of 3H-bimatoprost. The C1-acid metabolite of bimatoprost was the major species detected in the uterus and ovaries (about 45% of total radioactivity), while bimatoprost was the major species detected in the fetus (about 50% of total radioactivity). The C-1 acid is the major metabolite in rats and rabbits, but not in dogs, monkeys, or humans. Following one month of daily intravenous
administration to rats and monkeys, bimatoprost was found to have no clinically significant effect on any of the hepatic drug metabolizing enzymes tested. In studies using recombinant human P450 enzymes, CYP3A4/5 were identified as the most important Cytochrome P450 enzymes involved in the hydroxylation of bimatoprost.
Excretion: Both the urinary and fecal routes are important pathways for excretion of bimatoprost and its metabolites in rats and monkeys. Following a single intravenous administration of 3H-bimatoprost to rats, the urinary excretion of radioactivity was 42% of the dose in females and 27% in males, while the faecal excretion of radioactivity was 49% in females and 69% in males. Following a single intravenous administration of 3H-bimatoprost in monkeys, male and females excreted 58 and 64% of the dose into the urine and 24 and 31% into the faeces, respectively. The mean total recovery of radioactivity was >90% for both genders.
Human Pharmacology
Pharmacodynamics
Dosage Determination Studies for Treatment of Elevated IOP: Four Phase 2 dose-ranging studies were conducted in patients with open-angle glaucoma or ocular hypertension. A dose-response study in 60 patients with twice-daily dosing for 5 ± 2 days showed significant reductions from baseline IOP with bimatoprost 0.01% w/v and 0.03% w/v formulations as well as with timolol 0.5% w/v, compared to vehicle. Among the bimatoprost concentrations evaluated, 0.03% w/v had the best ratio of safety to efficacy, and the 24-hour post-dose results suggested the potential for efficacy with once-daily dosing.
The effects of 0.003%, 0.01% and 0.03% w/v bimatoprost (non-preserved formulations) and of twice-daily versus once-daily (evening) dosing were compared to timolol 0.5% w/v and vehicle in 100 patients treated for one month. Although 0.01% w/v and 0.03% w/v had similar safety profiles, 0.03% w/v had significantly better efficacy. There was no significant difference in efficacy between twice-daily and once-daily dosing.
A study in 106 patients evaluated once-daily evening dosing for 28 days with bimatoprost 0.03% w/v (preserved and non-preserved formulations), AGN 192151 0.06% w/v (a congener of bimatoprost), latanoprost 0.005% w/v, and vehicle. Although the sample size was small, bimatoprost and latanoprost appeared to exhibit comparable safety profiles. The profiles were similar with the preserved and non-preserved formulations of bimatoprost 0.03% w/v. The mean reduction in IOP are shown in Table 6.
Table 6: Mean Reduction in Intraocular Pressure (mmHg) from Baseline B Day 29
0.03% w/v Bimatoprost Non-preserved n=21 | 0.03% w/v Bimatoprost Preserved n=21 | Latanoprost n=22 | Vehicle Non-preserved n=21 |
| 8.9 ± 0.7 | 8.0 ± 0.9 | 7.6 ± 0.5 | 1.7 ± 1.2 |
A study in 32 patients evaluated once-daily morning dosing for 28 days with bimatoprost
0.03% w/v or vehicle. The ocular hypotensive effect of bimatoprost 0.03% w/v with once-daily morning dosing was similar to that observed with once-daily evening dosing.
In the Phase 2 dose-response studies, bimatoprost 0.03% w/v provided greater lowering of IOP than 0.003%, 0.01%, or 0.1% w/v, with similar number of treatment-related adverse events as the 0.01% w/v concentration. Thus the 0.03% w/v concentration was selected for evaluation in Phase 3 studies. Significant IOP-lowering effects were shown for this concentration with once-daily dosing.
The effect of bimatoprost 0.03% w/v within the first 12 hours of dosing was evaluated in two studies. When dosed in the morning, bimatoprost began to take effect within 4 hours after initial instillation, and was followed by continued decreases in IOP through 12 hours. The effect of bimatoprost 0.03% w/v between 12 and 24 hours post-instillation was evaluated. At baseline, the mean IOP of bimatoprost was approximately 26 mmHg. At 12 hours post-dosing it was 17.7 mmHg and at 24 hours post-dosing it was 16.9 mmHg.
Based on this information, once-daily evening dosing was selected for the Phase 3 studies so that the time of anticipated maximal efficacy of the drug coincided with the morning hours (08:00 to 11:00 AM) when untreated IOP is usually highest.
Pharmacokinetics
Absorption and Systemic Drug Exposure: Bimatoprost penetrates the human cornea and sclera well in vitro. The mean corneal permeability coefficient was 3.24 x 10⁻⁶ cm/sec. Bimatoprost penetrated human scleral tissue better than corneal tissue with a mean scleral permeability coefficient of 14.5 x 10⁻⁶ cm/sec.
After one drop of 0.03% w/v ophthalmic solution was administered once daily to both eyes of 15 healthy subjects for two weeks, blood bimatoprost concentrations were below the lower limit of detection (0.025 ng/mL) in most subjects within 1 to 1.5 hours after dosing. Mean bimatoprost Cmax values were similar on days 7 and 14 at 0.0721, and 0.0822 ng/mL, respectively. The mean AUC0-24hr values were also similar on days 7 and 14 at 0.0742, and 0.096 ng•hr/mL, respectively, indicating that a steady systemic exposure to bimatoprost had been reached during the first week of ocular dosing.
The blood concentrations of bimatoprost from patients with open angle glaucoma or ocular hypertension in two Phase 3 safety and efficacy studies were measured (N=88 on once-daily treatment and N=89 on twice-daily treatment). The samples were collected at approximately 5 minutes after the evening dose over a 3-month treatment period. Bimatoprost blood concentrations were similar to those observed in normal, healthy subjects and there was no significant systemic drug accumulation over time. The C-1 acid metabolite (AGN 191522) was typically not measurable in blood samples from these studies.
Therapeutic drug monitoring in the Phase 3 studies showed that in one study that the elderly group had a higher concentration in the blood; however, this was not observed in the second Phase 3 study.
There was no significant systemic accumulation of bimatoprost following twice-daily dosing for 7 days in either young (18-44 years, mean = 28.5) or elderly patients (65-80 years, mean = 71.0). Bimatoprost appeared rapidly in the blood in both age groups, and was below the LLOQ by 1.5 hours in most patients. Systemic exposure was higher in the elderly than the young following both single and multiple dosing (124% and 213%, respectively). The mean AUC0-24hr value of 0.0634 ng•hr/mL in elderly subjects was statistically significantly higher than that of 0.0218 ng•hr/mL in young subjects, suggesting the existence of an age effect. However, this finding is not considered clinically relevant as bimatoprost exhibits similar efficacy and safety profiles in both the young and elderly populations.
Distribution: Bimatoprost is moderately distributed into body tissues with a steady-state volume of distribution of 0.67 L/kg. In human blood, bimatoprost resides mainly in the plasma. Approximately 12% of bimatoprost remain unbound in human plasma. The in vitro binding of bimatoprost to synthetic melanin was ~20% at concentrations of 0.2 - 100 mcg/mL. The overall extent of melanin binding was not dependent on concentration, and the binding was reversible.
Metabolism: Bimatoprost is the major circulating species in the blood once it reaches the systemic circulation following ocular dosing. Bimatoprost then undergoes oxidation, N-deethylation and glucuronidation to form a diverse variety of metabolites.
Elimination: Following an intravenous dose of radiolabelled bimatoprost (3.12 mcg/kg) to six healthy subjects, the maximum blood concentration of unchanged bimatoprost was 12.2 ng/mL and declined rapidly with an elimination half-life of 0.771 hour (approximately 45 minutes). Blood concentrations of AGN 191522, the C-1 acid metabolite, were much lower than those of bimatoprost as peak concentration was 0.12 ng/mL. The total blood clearance (Clb) of unchanged bimatoprost was 1.50 L/hr/kg.
Sixty-seven percent of the administered dose of bimatoprost was excreted in the urine with only a small fraction excreted as unchanged drug. Twenty-five percent of the dose was recovered in feces of which 15-40% was eliminated as unchanged drug.
TOXICOLOGY
The acute toxicity of bimatoprost was evaluated in single intraperitoneal and intravenous (IV) dose studies in mice and rats. A dose of 96 mg/kg administered intraperitoneally to mice, and up to 3 mg/kg IV administered to rats produced no adverse effects.
Long-term Toxicity
No treatment-related ocular or systemic effects were produced in Dutch belted rabbits when 0.03% w/v or 0.1% w/v bimatoprost ophthalmic formulation was instilled to the eye once or twice daily for 6 months. The highest dose (0.1% twice daily) produced 53 times the systemic drug exposure seen in humans treated with 1 drop in each eye of 0.03% w/v bimatoprost once daily for 2 weeks. No treatment-related systemic effects were observed in cynomolgus monkeys
when 0.03% w/v or 0.1% w/v bimatoprost ophthalmic formulation was instilled to the eye once or twice daily for 1 year. An increase in iris pigmentation was noted in some animals in all treated groups. No associated increase in melanocyte number was observed with the pigmentation. It appears that the mechanism of increased iris pigmentation is due to increased stimulation of melanin production in melanocytes and not to an increase in melanocyte number. Reversible dose-related periocular effects characterized by a prominent upper and/or lower sulcus and widening of the palpebral fissure of the treated eye was also observed. No functional or microscopic change related to the periocular change was observed. The highest dose (0.1% twice daily) produced at least 65 times the systemic drug exposure seen in humans treated with 1 drop into each eye of 0.03% w/v bimatoprost once daily for 2 weeks. (Human dose calculated as 21 mcg in a 35 mcL drop dosed once daily in both eyes - not based on the 28 mcL drop size as used in the Phase III studies).
No effects were observed in mice given 4 mg/kg/day bimatoprost orally for 3 months. This dose achieved systemic exposure that was at least 149 times higher than that observed in humans treated with the intended clinical regimen. Female mice given oral doses of 8 mg/kg/day showed a reversible thymic lymphoid proliferation. This effect was observed only in mice and at a dose far exceeding the intended human exposure (460-fold higher).
Increased serum aminoglutamate oxaloacetate and glutamate pyruvate transaminase (2- to 5-fold in males) was observed in rats given 8 or 16 mg/kg/day orally for 13 weeks. These changes were reversible after 4 weeks without treatment and no microscopic correlate was observed. In addition, increased ovarian weight and increased number of prominent, vacuolated corpora lutea were observed with these doses and with the dose of 4 mg/kg/day. Ovarian changes were also reversible at 4 weeks. The effects on the ovaries could be related to the pharmacological effect of this class drug in rats since these changes were not observed in other species. A dose of 4 mg/kg/day achieved systemic exposure that was at least 1538 times higher than that observed in humans treated with 1 drop into each eye of 0.03% w/v bimatoprost once daily for 2 weeks.
A slight, reversible increase in alanine aminotransferase and aspartate aminotransferase was observed in rats given ≥ 0.1 mg/kg/day orally for 1 year. There were no associated microscopic liver findings. A dose-related, reversible cellular vacuolation of corpora lutea at ≥ 0.3 mg/kg/day in female rats was observed. The lowest effect dose of 0.1 mg/kg/day achieved systemic exposure (Cmax) that was 8 times higher than the intended human clinical dose. Hepatic and ovarian effects in rats were considered species-specific since these changes have not been observed in mice and monkeys at systemic exposures up to 2,800- to 14,000-fold higher, respectively, than those in humans given the intended clinical regimen of bimatoprost.
No treatment related systemic effects were produced when monkeys were intravenously administered from 0.01 to 1.0 mg/kg/day bimatoprost for 17 weeks. An increase in the prominence of the periocular sulci and widening of the palpebral fissure of both eyes were observed in all treated monkeys. This finding was reversible at 12 weeks after cessation of treatment. A dose of 0.01 mg/kg/day achieved systemic exposure that was 235 times greater than that observed in humans treated with 1 drop into each eye of 0.03% w/v bimatoprost once daily for 2 weeks.
Mutagenicity
Bimatoprost was not mutagenic or clastogenic in a series of in vitro and in vivo studies (Ames test, Mouse Lymphoma and Micronucleus tests).
Salmonella/Escherichia Coli Mutagenicity Assay: Bimatoprost was tested in the bacterial reverse mutation assay (Ames assay) using S. typhimurium tester strains TA98, TA100, TA 1535, and TA1537 and E. coli tester strains WP2 uvrA (pKM101) and WP2 (pKM101) in the presence and absence of Aroclor-induced rat liver S9. No positive response was observed in the mutagenicity assay at concentrations of up to 5000 mcg per plate.
Mouse Lymphoma Mutagenesis Assay: Bimatoprost was tested in the reduced volume L5178Y/TK+/- mouse lymphoma mutagenesis assay in the presence and absence of Aroclor-induced rat liver S9, and was negative when tested at concentrations up to 900 mcg/mL with or without S9.
In Vivo Mouse Micronucleus Assay: Bimatoprost was assayed for clastogenic activity and potential to disrupt the mitotic apparatus by evaluating micronuclei in polychromatic erythrocyte (PCE) cells in mouse bone marrow. Bimatoprost is considered negative in the mouse bone marrow micronucleus test following 20 mg/kg/day in mice. The high dose was based on the limit of solubility.
Carcinogenicity
Bimatoprost was not carcinogenic when administered once daily orally (by gavage) at doses of 0.3, 1.0 and 2.0 mg/kg/day to mice and 0.1, 0.3 and 1.0 mg/kg/day to rats (approximately 192 or 291 times the human exposure based on blood AUC levels) for 104 weeks.
Reproduction and Teratology
Impairment of Fertility: No impairment of fertility occurred in rats when males were treated for 70 days prior to cohabitation and females were treated for 15 days prior to mating. Treatment was continued in males until copulation was observed and in females through gestation day 7. The highest dose (0.6 mg/kg/day) achieved systemic exposure that was 103 times that observed in humans treated with 1 drop of 0.03% w/v bimatoprost in each eye once daily for 2 weeks.
Pregnancy/Teratogenic Effects: Bimatoprost given orally at doses up to 0.3 or 0.6 mg/kg/day to pregnant rats during gestation day 6 through 17 caused abortion but no drug-related developmental effects. This effect was also seen in mice receiving 0.3 mg/kg/day during gestation day 6 through 15. The maternal no-observable-adverse-effect level (NOAEL) of bimatoprost was 0.1 or 0.3 mg/kg/day for mice or rats, respectively. Abortion was expected as a rodent-specific pharmacological effect. The lowest effect dose of 0.3 mg/kg in mice and rats achieved systemic exposure (AUC) that was at least 33 or 97 times higher respectively, than that observed in humans treated with the intended clinical regimen.
Perinatal and Postnatal: Treatment of F0 female rats given 0.3 mg/kg/day (at systemic exposure estimated 41 times the intended clinical dose) or greater caused maternal toxicity as evidenced by reduced gestation length, increased late resorption, fetal death, and postnatal mortality and reduced pup body weight (a rodent-specific pharmacological effect). No effects on
postnatal development and mating performance of the F1 offspring were observed in groups treated with dosages as high as 0.1 mg/kg/day. Neurobehavioral function, Caesarean-sectioning parameters, and litter parameters in F1 rats were unaffected by doses as high as 0.3 mg/kg/day.
Animal Lactation
In animal studies, bimatoprost has been shown to be excreted in breast milk.
Special Toxicity Studies
Bimatoprost did not possess antigenic, cutaneous or systemic anaphylactic potential, or produce dermal contact hypersensitivity responses when administered topically, intradermally or systemically in rodents and guinea pigs.
REFERENCES
- 1.
Brubaker RF, Schoff EO, Nau CB, Carpenter SP, Chen K Vandenburgh AM. Effects of
AGN 192024, a new ocular hypotensive agent, on aqueous dynamics. Am J Ophthalmol 2001; 131(1):19-24.
- 2.
Dirks M, DuBiner H Cooke D et al. Efficacy and safety of the ocular hypotensive lipid AGN
192024 in patients with elevated IOP: A 30 day comparison with Latanoprost. Investigative Ophthalmol and Vis Sci1999;41(4)S514.
- 3.
VanDenburgh AM, Laibovitz RA and Felix C. A one month dose response study of AGN
192024, a novel antiglaucoma agent in patients with elevated intraocular pressure. Investigative Ophthalmol and Vis Sci 1999;40(4):S830.
- 4.
Woodward DF, Krauss AH-P, Chen J, Kedzie KM, Protzman CE, Shi L, Chen R, Krauss
HA, Bogardus HT, Dinh T, Wheeler LA, Andrews SW, Burk RM, Gac T, Roof MB, Garst ME, Kaplan LJ, Sachs G, Pierce KL, Regan JW, Ross RA, Chan MF. Replacement of the carboxylic acid group of prostaglandin F2α with a hydroxyl or methoxy substituent provides biologically unique compounds. Br J Pharmacol 2000; 130:1933-1943.
- 5. Woodward DF, Fairbairn CE, Krauss A H-P, Lawrence RA, Protzman CE. Radioligand binding analysis of receptor subtypes in two FP receptor preparations that exhibit different functional rank order of a potency in response to prostaglandins. J Pharmacol Exp Ther 1995; 273(1):285-291.
- 6. Allergan Inc. Product Monograph, LUMIGAN®. Control #219412, November 26, 2018.