


Product Monograph - AG-Olopatadine 0.2%
RECENT MAJOR LABEL CHANGES
None at the time of authorization.
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES .............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ...................................................................................................................... 4
1.2 Geriatrics ...................................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................... 4
4.1 Dosing Considerations ................................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ............................................................ 4
4.5 Missed Dose ................................................................................................................. 4
5 OVERDOSAGE ............................................................................................................... 4
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................... 5
7 WARNINGS AND PRECAUTIONS .................................................................................... 6
7.1 Special Populations ........................................................................................................ 6
7.1.1 Pregnant Women ...................................................................................................... 6
7.1.2 Breast-feeding ........................................................................................................... 7
7.1.3 Pediatrics ................................................................................................................... 7
7.1.4 Geriatrics: .................................................................................................................. 7
8 ADVERSE REACTIONS.................................................................................................... 7
8.1 Adverse Reaction Overview ......................................................................................... 7
8.2 Clinical Trial Adverse Reactions ................................................................................... 7
8.3 Less Common Clinical Trial Adverse Reactions ............................................................ 7
8.5 Post-Market Adverse Reactions ................................................................................... 8
9 DRUG INTERACTIONS ................................................................................................... 8
9.2 Drug Interactions Overview ......................................................................................... 8
10 CLINICAL PHARMACOLOGY ........................................................................................... 9
10.1 Mechanism of Action ................................................................................................. 9
10.2 Pharmacodynamics ..................................................................................................... 9
10.3 Pharmacokinetics ........................................................................................................ 9
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 11
PART II: SCIENTIFIC INFORMATION ........................................................................................ 12
13 PHARMACEUTICAL INFORMATION ............................................................................. 12
14 CLINICAL TRIALS ......................................................................................................... 13
14.1 Clinical Trials by Indication ...................................................................................... 13
16 NON-CLINICAL TOXICOLOGY ........................................................................................ 17
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 18
PATIENT MEDICATION INFORMATION .................................................................................... 19
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
AG-Olopatadine 0.2% (olopatadine hydrochloride ophthalmic solution) is indicated for:
- the treatment of ocular itching associated with seasonal allergic conjunctivitis.
1.1 Pediatrics
Pediatrics (<18 years): The effectiveness of olopatadine hydrochloride ophthalmic solution has not been established in pediatric patients <18 years of age. No overall difference in safety has been observed between pediatric and adult patients.
1.2 Geriatrics
Geriatrics: No overall differences in safety and effectiveness have been observed between elderly and other adult patients.
2 CONTRAINDICATIONS
Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the Product Monograph.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
No special dosage considerations are necessary for AG-Olopatadine 0.2%.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose is one drop in each affected eye once a day.
No dosage adjustment is required in hepatic or renal impairment.
4.5 Missed Dose
If a dose is missed, a single drop should be taken as soon as possible before reverting to regular routine. Do not use a double dose to make up for the one missed.
5 OVERDOSAGE
No data are available in humans regarding overdose by accidental or deliberate ingestion of olopatadine hydrochloride ophthalmic solution. No reports of overdose were received during the clinical studies of olopatadine hydrochloride ophthalmic solution.
If a topical overdose of AG-Olopatadine 0.2% occurs, the eye(s) may be flushed with tap water.
For the most recent information in the management of suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Topical Ophthalmic | Ophthalmic Solution / 0.2% w / v olopatadine (as olopatadine hydrochloride) | Preservative: Benzalkonium chloride Non-medicinal ingredients: Dibasic sodium phosphate, edetate disodium, hydrochloric acid and / or sodium hydroxide (to adjust pH), povidone, sodium chloride, water for injection. |
Description
Each mL of AG-Olopatadine 0.2% contains:
Medicinal ingredient: 2.22 mg olopatadine hydrochloride equivalent to 2 mg olopatadine.
Preservative: Benzalkonium chloride 0.01%.
Non-medicinal ingredients: See Table 1 for complete list.
AG-Olopatadine 0.2% has a pH of approximately 5.0 to 8.0 and an osmolality of approximately 260 to 340 mOsm / kg.
AG-Olopatadine 0.2% is supplied in a white, low density polyethylene bottle with natural LDPE nozzle and white HDPE screw-on cap.
Net contents are 2.5 mL in a 5 mL bottle.
7 WARNINGS AND PRECAUTIONS
General
For topical ocular use only. Not for injection or oral use.
Contamination
As with any eye drop, to prevent contamination of the dropper tip and solution, care should be taken not to touch the eyelids or surrounding areas with the dropper tip of the bottle. Keep bottle tightly closed when not in use.
Driving and Operating Machinery
Olopatadine is a non-sedating anti-histamine. Temporary blurred vision or other visual disturbances, after the use of AG-Olopatadine 0.2%, may affect the ability to drive or use machines. If blurred vision occurs after instillation, patients must wait until vision clears before driving or using machinery.
Ophthalmologic
Patients should be advised not to wear contact lenses if their eye(s) are red.
AG-Olopatadine 0.2% should not be used to treat contact lens related irritation. The preservative in AG-Olopatadine 0.2%, benzalkonium chloride, may cause eye irritation and is known to discolour soft contact lenses. Contact with soft contact lenses should be avoided. Patients must be instructed to remove contact lenses prior to application of AG-Olopatadine 0.2%, and wait at least 15 minutes before they insert their contact lenses.
If using other eye drops, patients should wait at least five minutes between putting in AG-Olopatadine 0.2% and the other drops. Eye ointments should be applied last.
Reproductive Health: Female and Male Potential
- Fertility
Studies have not been performed to evaluate the effect of topical ocular administration of olopatadine on human fertility.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well controlled studies in pregnant women. Studies in animals with olopatadine have shown reproductive toxicity following systemic administration considered sufficiently in excess of the maximum human exposure. Olopatadine was found not to be teratogenic in rats and rabbits at oral doses >90,000 and >60,000 times the maximum recommended ocular human use level, respectively (see 16 NON-CLINICAL
TOXICOLOGY, Reproductive and developmental Toxicology). Because animal studies are not always predictive of human responses, AG-Olopatadine 0.2% should be used in pregnant women only if the potential benefit to the mother justifies the potential risk to the embryo or fetus.
7.1.2 Breast-feeding
Olopatadine has been identified in the milk of nursing rats following oral administration. It is not known whether topical ocular administration could result in sufficient systemic absorption to produce detectable quantities in human breast milk. Nevertheless, caution should be exercised when AG-Olopatadine 0.2% is administered to a nursing mother.
7.1.3 Pediatrics
Pediatrics (<18 years): Effectiveness in pediatric patients has not been established. No overall difference in safety has been observed between pediatric and adult patients.
7.1.4 Geriatrics:
No overall differences in safety and effectiveness have been observed between elderly and other adult patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In clinical trials involving 1137 patients dosed with long-term ophthalmic topical therapy, olopatadine hydrochloride ophthalmic solution was administered once-daily for 4 to 12 weeks. The most frequently reported treatment-related undesirable effects were headache (0.8%), eye irritation (0.5%), dry eye (0.4%), and eyelid margin crusting (0.4%). No serious adverse drug reactions related to olopatadine hydrochloride ophthalmic solution were reported in the clinical trials.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
No treatment-related adverse drug reactions occurred at an incidence ≥ 1%.
8.3 Less Common Clinical Trial Adverse Reactions
The most frequently reported adverse drug reactions (>0.1%) are presented below.
Treatment-Related Adverse Drug Reactions >0.1% – Long-Term Exposure
Eye disorders: eye irritation, dry eye, eyelid margin crusting, and eye pruritus;
Gastrointestinal disorders: dry mouth;
Nervous system disorders: headache, dysgeusia;
Additional treatment-related adverse drug reactions that occurred at an incidence of 0.1% included the following:
Eye disorders: asthenopia, eye swelling, eyelid disorder, eyelids pruritus, ocular hyperaemia, and vision blurred;
Investigations: heart rate increased;
Respiratory, Thoracic, and Mediastinal disorders: nasal dryness;
8.5 Post-Market Adverse Reactions
Approximately 5.4 million units of olopatadine hydrochloride ophthalmic solution have been sold worldwide. The reporting rate of all reaction terms reported between 22 December 2004 and 31 August 2009 was 0.005%, and no single reaction term occurred with a reporting rate greater than 0.0007%. No post-market reports of serious adverse reactions have been received to date. The most frequent events reported being eye irritation, ocular hyperaemia, eye pain, and vision blurred. There were no new major findings bearing on the established overall safety profile of olopatadine hydrochloride ophthalmic solution. Other events include dizziness, eye discharge, punctate keratitis, keratitis, erythema of eyelid, dermatitis contact, fatigue, hypersensitivity, ocular discomfort, lacrimation increased and nausea.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No clinical interaction studies have been conducted with olopatadine hydrochloride ophthalmic solution. In vitro studies have shown that olopatadine does not inhibit metabolic reactions which involve cytochrome P-450 isoenzymes 1A2, 2C8, 2C9, 2C19, 2D6, 2E1, and 3A4. Olopatadine is moderately bound to plasma proteins (approximately 55%). These results indicate that olopatadine is unlikely to result in interactions with other concomitantly administered medications. Due to the low systemic exposure following topical ocular dosing, it is unlikely that AG-Olopatadine 0.2% would interfere with immediate hypersensitivity skin testing.
Interactions with other drugs, food, herbal products, or laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Olopatadine, a structural analog of doxepin, is a non-steroidal, non-sedating, topically effective anti-allergic molecule that exerts its effects through multiple distinct mechanisms of action. Olopatadine is a mast cell stabilizer and a potent, selective histamine H1 antagonist that inhibits the in vivo type 1 immediate hypersensitivity reaction. In vitro studies have demonstrated the ability of olopatadine to stabilize rodent basophils and human conjunctival mast cells and inhibit immunologically-stimulated release of histamine. In addition, Olopatadine inhibits the release of mast cell inflammatory mediators [i.e., histamine, tryptase, prostaglandin D2 and TNFα] as demonstrated in in vitro studies and confirmed in patients.
Olopatadine is a selective histamine H1 receptor antagonist in vitro and in vivo as demonstrated by its ability to inhibit histamine binding and histamine-stimulated vascular permeability in the conjunctiva following topical ocular administration. Olopatadine is also an inhibitor of pro-inflammatory cytokine secretion from human conjunctival epithelial cells. Decreased chemotaxis and inhibition of eosinophil activation has also been reported. Olopatadine is devoid of effects on alpha-adrenergic, dopamine, muscarinic type 1 and 2, and serotonin receptors.
10.2 Pharmacodynamics
Effects on cardiac repolarization (QTc):
Olopatadine had no observed effect on heart rate, cardiac conduction (PR and QRS interval duration), cardiac repolarization (QT duration) or wave form morphology relative to placebo in 2 double-masked, placebo controlled, 2-way crossover studies of 102 subjects given 5-mg oral doses of olopatadine every 12 hours for 2.5 days and 32 subjects given 20-mg oral doses twice- daily for 13.5 days. No clinically relevant or statistically significant changes in mean QTcF (determined to be the most appropriate heart correction formula for both study populations) at steady-state from baseline were observed in either study. A categorical analysis of QTc (< 30 ms, 30 ms-60 ms, or > 60 ms) showed no statistically significant differences between olopatadine and placebo in both studies. An analysis of the maximal change from baseline in QTcF showed the difference was higher for placebo than for olopatadine. In addition, no evidence of QT interval prolongation was observed, relative to placebo, in 429 perennial allergic rhinitis patients given olopatadine hydrochloride nasal spray, 665 micrograms twice daily for up to 1 year.
10.3 Pharmacokinetics
Systemic bioavailability data upon topical ocular administration of olopatadine hydrochloride ophthalmic solution are not available.
Absorption:
Following topical ocular administration in man, olopatadine was shown to have low systemic exposure. Two studies in healthy volunteers (totaling 24 subjects) dosed bilaterally with Olopatadine 0.15% ophthalmic solution once every 12 hours for 2 weeks demonstrated plasma concentrations to be generally below the quantitation limit of the assay (<0.5 ng/mL). Samples in which olopatadine was quantifiable were typically found within 2 hours of dosing and ranged from 0.5 to 1.3 ng/mL. These plasma concentrations were greater than 300 fold below those observed with a well-tolerated 20 mg oral multiple-dose regimen. In oral studies, olopatadine was found to be well absorbed.
In multiple oral dose studies, olopatadine plasma concentrations were shown to increase in proportion to the dose increment.
Metabolism:
Approximately 60-70% of the oral dose was recovered in the urine as parent drug. Peak plasma concentrations of the active metabolite, N-desmethyl olopatadine, and inactive N-oxide metabolite were low, less than 1% and 3% of parent, respectively. Two metabolites, the monodesmethyl and the N-oxide, were detected at low concentrations in the urine.
Elimination: The elimination half-life in plasma was 7-14 hours, and elimination was predominantly through renal excretion.
Special Populations and Conditions
- Pediatrics - Effectiveness in pediatric patients has not been established. No overall difference in safety has been observed between pediatric and adult patients.
- Geriatrics - No overall differences in safety and effectiveness have been observed between elderly and other adult patients.
- Sex - In multiple oral dose studies, plasma concentrations of olopatadine are higher in female subjects, however, the differences are small and not clinically meaningful.
- Ethnic Origin - No specific pharmacokinetic study examining the effect of race has been conducted.
- Hepatic Insufficiency - No specific pharmacokinetic study examining the effect of hepatic impairment was conducted. Since metabolism of olopatadine is a minor route of elimination, no adjustment of the dosing regimen of AG-Olopatadine 0.2% is warranted in patients with hepatic impairment
- Renal Insufficiency - The mean plasma Cmax values for olopatadine following single intranasal doses of olopatadine hydrochloride nasal spray 0.6% (665 mcg/spray) were not markedly different between healthy subjects (18.1 ng/mL) and patients with mild, moderate and severe renal impairment (range 15.5 to 21.6 ng/mL). Plasma AUC was 2.5-fold higher in patients with severe impairment (creatinine clearance <30 mL/min/1.73m2). Predicted peak steady-state plasma concentrations of olopatadine in patients with renal impairment following administration of olopatadine hydrochloride ophthalmic solution, 0.1% are at least 10-fold lower than those observed following administration of olopatadine nasal spray 0.6%, and approximately 300-fold lower than those observed following the safe and well-tolerated administration of 20 mg oral doses for 13.5 days. These findings indicate that no adjustment of the dosing regimen of AG-Olopatadine 0.2% is warranted in patients with renal impairment.
11 STORAGE, STABILITY AND DISPOSAL
- Store between 4-25°C. Discard the bottle at the end of treatment or 4 weeks after first opening, whichever comes first. Do not use if seal is damaged or missing.
- Keep out of reach and sight of children.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Olopatadine hydrochloride |
|---|---|
| Chemical name: | Dibenz[b,e]oxepin-2-acetic acid, 11-[3-(dimethylamino) propylidene]-6, 11-dihydro-,hydrochloride, (Z) |
| 11-[(Z)-3-(Dimethylamino)propylidene]-6,11 dihydrodibenz[b,e]oxepin-2-acetic acid, hydrochloride | |
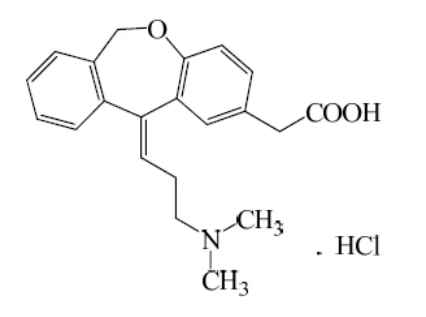
| Molecular formula: | C21H23NO3 • HCl |
| Molecular mass: | 373.87 g/mol |
| Structural formula: | |
| Description: | An off-white to white crystalline powder. |
| Solubility: | Very soluble in formic acid, sparingly soluble in water and very slightly soluble in dehydrated alcohol. |
| pH (1% aqueous solution): | Between 2.0 and 4.0 |
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Ocular itching associated with seasonal allergic conjunctivitis
A summary of the patient demographics for each of the 7 studies relevant to the evaluation of the efficacy of olopatadine hydrochloride ophthalmic solution is provided in Table 2. Overall, these demographics are representative of the population that would be expected to receive this medicinal product.
Table 2 - Summary of patient demographics for clinical trials
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| C-00-36 CAC | randomized, double-masked, placebo-controlled | Olopatadine hydrochloride ophthalmic solution or placebo, 1 drop each eye at each visit, dosed contra-laterally; visits on 3 non- consecutive days | n = 45 | 42.3 yrs (19 – 70) | 18 M 27 F |
| C-01-18 CAC | randomized, double-masked, placebo-controlled | Olopatadine hydrochloride ophthalmic solution, placebo, or Olopatadine hydrochloride ophthalmic solution and placebo dosed contra-laterally, 1 drop each eye at each visit, visits on 2 non-consecutive days | n = 36 | 38.1 yrs (20-58) | 16 M 20 F |
| C-01-100 CAC | randomized, double-masked, placebo-controlled | Olopatadine hydrochloride ophthalmic solution (OU), placebo (OU), Olopatadine hydrochloride ophthalmic solution (OS) and placebo (OD), or Olopatadine hydrochloride ophthalmic solution (OD) and placebo (OS), 1 drop each eye at each visit, visits on 2 nonconsecutive days | n = 92 | 39.2 yrs (20-67) | 38 M 54 F |
C-02-67 Environme ntal (grass) | randomized, double-masked, placebo-controlled parallel group | Olopatadine hydrochloride ophthalmic solution or placebo, 1 drop each eye once daily, 10 weeks | n = 260 | 36.4 yrs (11-75) | 123 M 137 F |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
 C-04-60 Environme ntal (grass) | randomized, double-masked, placebo-controlled parallel group | Olopatadine hydrochloride ophthalmic solution or placebo, 1 drop each eye once daily, 6 weeks | n = 287 | 36.4 yrs (10-81) | 127 M 160 F |
C-01-10 Environme ntal (ragweed) | randomized, double-masked, placebo-controlled, parallel group | olopatadine hydrochloride ophthalmic solution or placebo, 1 drop each eye once daily, 12 weeks | n = 240 | 37.3 (10-66) | 94 M 146 F |
C-01-90 Environme ntal (grass) | randomized, double-masked, placebo-controlled, parallel group | olopatadine hydrochloride ophthalmic solution or placebo, 1 drop each eye once daily, 12 weeks | n = 239 | 37.4 (10-73) | 94 M 145 F |
OU= both eyes, OD=right eye, OS=left eye
Conjunctival Allergen Challenge (CAC) Studies:
Three studies were conducted to assess the safety and efficacy of olopatadine hydrochloride ophthalmic solution versus placebo in the treatment of allergen-mediated conjunctivitis using the CAC model at 27 minutes (onset of- action), and either 16 hours or 24 hours or both (duration-of-action), after instillation. All three studies demonstrated that olopatadine hydrochloride ophthalmic solution dosed once daily was statistically superior to placebo in the treatment of ocular itching, has a rapid onset-of-action and a prolonged duration-of-action.
Table 3: CAC Itching Results from Contralateral Eye Analyses in Studies with olopatadine hydrochloride ophthalmic solution
| Onset-of-Action | 24Hr Duration-of-Action | 16Hr Duration-of-Action | ||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| time post-challenge | time post-challenge | time post-challenge | ||||||||||||||||||||||||
| 3 min | 5 min | 7 min | 10 min | 20 min | 3 min | 5 min | 7 min | 10 min | 20 min | 3 min | 5 min | 7 min | 10 min | 20 min | ||||||||||||
C-00-36 Olopatadine hydrochloride ophthalmic solution -Placebo | Mean Diff | -1.31 | -1.60 | -1.13 | -0.93 | -0.99 | -0.65 | -0.93 | -0.88 | -0.39 | ||||||||||||||||
P value | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | 0.014 | |||||||||||||||||
C-01-18 Olopatadine hydrochloride ophthalmic solution -Placebo | Mean Diff | -1.50 | -1.67 | -0.79 | -1.25 | -1.04 | -0.50 | |||||||||||||||||||
P value | 0.0002 | 0.0003 | 0.0180 | 0.0011 | 0.0044 | 0.0456 | ||||||||||||||||||||
C-01-100 Olopatadine hydrochloride ophthalmic solution -Placebo | Mean Diff | -1.56 | -1.66 | -1.53 | -0.98 | -1.07 | -1.07 | |||||||||||||||||||
P value | <0.0001 | <0.000 1 | <0.0001 | <0.0001 | <0.0001 | <0.0001 | ||||||||||||||||||||
Shaded areas indicate that ocular itching was not evaluated at these time-points; bold numbers indicate statistical significance.
Environmental Studies:
Four environmental studies were designed to assess the safety and efficacy of olopatadine hydrochloride ophthalmic solution in comparison with placebo in the treatment of the signs and symptoms of seasonal allergic conjunctivitis. All studies were randomized, double-masked, placebo-controlled, multi-centre, parallel group studies. Three studies (C-02-67, C-04-60, and C-01-90) enrolled patients with a history of seasonal allergic conjunctivitis, a positive diagnostic skin prick test for grass antigen within the past 2 years, and a positive response to grass in the Conjunctival Allergen Challenge model of the required magnitude. One study (C-01-10) enrolled patients with a positive skin prick test for ragweed antigen. Daily pollen counts were recorded for each study site.
Clinical Study C-02-67
Two hundred and sixty (260) patients were enrolled in this 10-week environmental study. The primary efficacy analysis was based on the subject self-evaluation of the frequency of ocular itching during the three days prior to each weekly assessment visit. The results showed that olopatadine hydrochloride ophthalmic solution statistically significantly reduced the effects of pollen on ocular itching relative to vehicle when dosed once a day (Figure 1).
Figure 1: Mean Scores for Itching Frequency by Visit Day (Intent-to-Treat) (C-02-67)
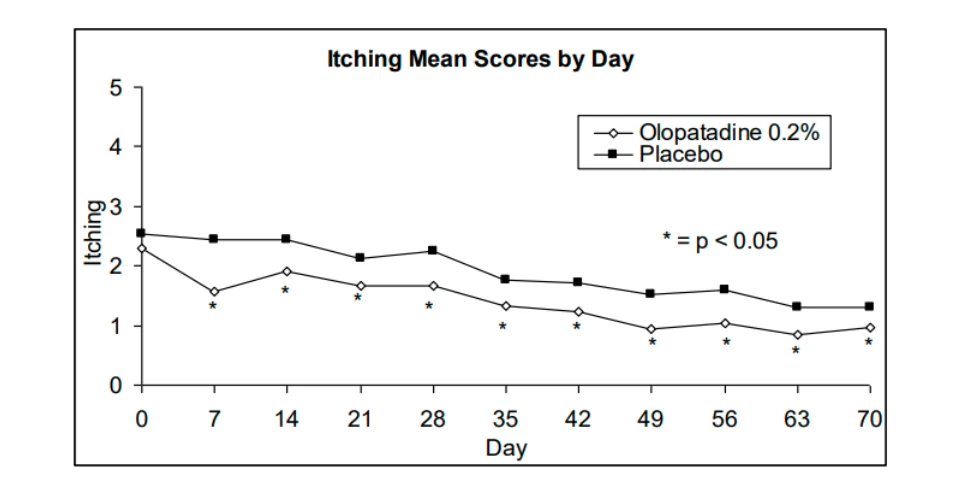
An analysis of the slopes of the lines measuring the effects of pollen on ocular itching also showed a statistically significant difference between olopatadine hydrochloride ophthalmic solution and placebo when pollen counts were taken into consideration.
The secondary analysis showed that olopatadine hydrochloride ophthalmic solution, dosed once a day, statistically significantly reduced the effects of pollen on daily itching severity when compared to vehicle (Table 4).
Table 4: Mean Itching Severity during 14 Consecutive Days of Peak Pollen (Intent-to-Treat) (C-02-67)
| ITCHING | |||
|---|---|---|---|
| Olopatadine Hydrochloride Ophthalmic Solution | Mean | 1.10 | |
| Std | 0.92 | ||
| N | 127 | ||
| PLACEBO | Mean | 1.48 | |
| Std | 1.04 | ||
| N | 129 | ||
| Difference from Vehicle | -0.38 | ||
| p-value (t-test) | 0.0023 | ||
Clinical Study C-04-60
Two hundred and eighty-seven (287) patients were enrolled in this 6-week environmental study. Severity scores for daily ocular itching, as recorded by patients three times per day in their diaries, were statistically significantly lower compared to placebo in the morning, mid-day, and evening when averaged over the 14 consecutive days of the peak pollen period. Additionally, the average diary itching scores are statistically significantly reduced in patients treated with olopatadine hydrochloride ophthalmic solution compared with placebo (Table 5).
Table 5: Average Diary Itching Over the Peak Pollen Period by Time (Intent-to-Treat) (C-04-60)
| Average Diary Itching | |||||
|---|---|---|---|---|---|
| Mean | Std | N | P-value | ||
| Morning | Olopatadine Hydrochloride Ophthalmic Solution | 0.55 | 0.60 | 144 | 0.0204 |
| Vehicle | 0.72 | 0.64 | 143 | ||
| Mid-Day | Olopatadine Hydrochloride Ophthalmic Solution | 0.50 | 0.61 | 144 | 0.0130 |
| Vehicle | 0.69 | 0.63 | 143 | ||
| Evening | Olopatadine Hydrochloride Ophthalmic Solution | 0.54 | 0.65 | 144 | 0.0084 |
| Vehicle | 0.74 | 0.67 | 143 | ||
Clinical Study C-01-10
A total of 240 patients were enrolled in this 12-week environmental study during ragweed season. The primary efficacy endpoint was subject self-evaluation of the frequency scores of ocular itching over a 12-week study period. The primary efficacy endpoint did not show any statistically significant difference between olopatadine hydrochloride ophthalmic solution and placebo in this study.
Clinical Study C-01-90
A total of 239 patients were enrolled in a 12-week environmental study during grass season. The primary efficacy endpoint was subject self-evaluation of the worst daily ocular itching averaged over a two-week, peak pollen period. The primary efficacy endpoint did not show any statistically significant difference between olopatadine hydrochloride ophthalmic solution and placebo in this study. The planned secondary efficacy analysis showed that olopatadine hydrochloride ophthalmic solution statistically significantly reduced the effects of pollen on ocular itching.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
The acute toxicity of olopatadine hydrochloride has been investigated in mice, rats and dogs. Mice and rats demonstrated that olopatadine hydrochloride was not an acute toxicity hazard with oral LD50 values greater than 1150 mg/kg and 3870 mg/kg for mice and rats, respectively.
Subchronic and chronic oral toxicity studies in rats and dogs demonstrated that the liver and kidney were target organs for olopatadine hydrochloride toxicity. In rats, ophthalmology and hematology parameters were unaffected following chronic administration of olopatadine hydrochloride. In chronic dog studies, ophthalmology, hematology, blood chemistry and organ weight parameters were unaffected by olopatadine hydrochloride administration.
A one-month topical ocular study was conducted with 0.1% QID or 0.2% olopatadine hydrochloride QID and HID ophthalmic solution in New Zealand White (NZW) rabbits. No signs of pharmacotoxicity were observed. Slit-lamp and indirect ocular evaluations and pachymetry revealed no treatment-related findings. Clinical pathology data and histopathology were unremarkable.
Two one-day topical ocular studies were conducted in NZW rabbits with 0.2% olopatadine hydrochloride formulations containing povidone. Each animal received two drops of the test article to one eye every 30 minutes for a total of ten doses. Slit lamp biomicroscopic examinations were conducted at 1, 2, 3 days following treatment. No significant ocular irritation was observed.
Reproductive and Developmental Toxicology:
Chronic topical ocular studies were conducted with olopatadine hydrochloride in rabbits and monkeys. Administration of olopatadine hydrochloride at concentrations of 0.1, 0.5 and 1.0% QID to NZW rabbits elicited no signs of pharmacotoxicity. No treatment-related findings were observed during slit-lamp and indirect ocular evaluations and pachymetry measurements. Clinical pathology data and histopathology were unremarkable. Similar findings were observed following six months of topical ocular administration of olopatadine hydrochloride at concentrations of 0.1, 0.2 and 0.5% QID to cynomolgus monkeys and following three months of topical ocular administration of formulations containing 0.2 and 0.4% of olopatadine hydrochloride with povidone TID to rabbits.
Juvenile Toxicity:
Olopatadine was found not to be teratogenic in rats and rabbits. However, rats treated at 600 mg/kg/day, or 150,000 times the MROHD and rabbits treated at 400 mg/kg/day, or approximately 100,000 times the MROHD, during organogenesis showed a decrease in live fetuses. In addition, rats treated with 600 mg/kg/day of olopatadine during organogenesis showed a decrease in fetal weight. Further, rats treated with 600 mg/kg/day of olopatadine during late gestation through the lactation period showed a decrease in neonatal survival and body weight.
Special Toxicology:
Antigenicity: Olopatadine hydrochloride was demonstrated to have a low potential for antigenicity when tested in mice and guinea pigs or in an in vitro passive hemagglutination test.Olopatadine was tested in a series of in vitro and in vivo mutagenesis studies. The results of these studies demonstrated that treatment with olopatadine did not induce genetic mutations or chromosomal aberrations. Long-term carcinogenicity studies in rats and mice also demonstrated that treatment with olopatadine did not increase the potential for cancer up to 500 mg/kg/day or over 200,000 fold greater than the maximum recommended daily dose.
17 SUPPORTING PRODUCT MONOGRAPHS
PrPATADAY® (Ophthalmic Solution, 0.2% w/v), submission control 266071, Product Monograph, Novartis Pharmaceuticals Canada Inc. (June 23, 2023)