


Product Monograph - AJ-Gemcitabine
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients* |
| Intravenous | Lyophilized powder / 200 mg/vial , 1 g vial, 2 g/vial | Mannitol, sodium acetate, hydrochloric acid and sodium hydroxide |
INDICATIONS AND CLINICAL USE
AJ-GEMCITABINE (Gemcitabine for Injection, USP) is indicated for the:
- Treatment of patients with locally advanced (nonresectable Stage II or Stage III) or metastatic (Stage IV) adenocarcinoma of the pancreas to achieve a Clinical Benefit Response (a composite measure of clinical improvement).
Treatment of patients with locally advanced or metastatic non-small cell lung cancer
(NSCLC) as either a single agent or in combination with cisplatin.
- Treatment of patients with Stage IV (locally advanced or metastatic) transitional cell carcinoma (TCC) of the bladder in combination with cisplatin.
- Treatment, in combination with paclitaxel, of patients with unresectable, locally recurrent or metastatic breast cancer, who have good performance status and have relapsed following adjuvant anthracycline-based chemotherapy.
AJ-GEMCITABINE should be used only under the supervision of a qualified healthcare professional who is experienced in the use of chemotherapeutic agents and in the management of patients with cancer. Appropriate management of therapy and complications is only possible when adequate diagnostic and treatment facilities are readily available.
Geriatrics (> 65 years of age):
Gemcitabine hydrochloride for Injection has been well tolerated in patients over the age of 65. Although clearance is affected by age (see ACTION AND CLINICAL PHARMACOLOGY section), there is no evidence that further dose adjustments, (i.e. other than those already recommended in the DOSAGE AND ADMINISTRATION section) are necessary in patients over the age of 65.
Pediatrics (< 17 years of age):
Safety and effectiveness in children have not been established.
CONTRAINDICATIONS
Gemcitabine hydrochloride is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
- AJ-GEMCITABINE is a cytotoxic drug and should be used only by physicians experienced with chemotherapeutic drugs. Patients should be informed of the risks associated with AJ-GEMCITABINE therapy.
- Prolongation of the infusion time beyond 60 minutes and more frequent than weekly dosing have been shown to increase toxicity (see DOSAGE AND ADMINISTRATION; and Part II: CLINICAL TRIALS sections).
- AJ-GEMCITABINE should be used with extreme caution in patients whose bone marrow reserve may have been compromised by prior irradiation or chemotherapy, or whose marrow function is recovering from previous chemotherapy.
- AJ-GEMCITABINE can suppress bone marrow function manifested by leucopenia, thrombocytopenia and anemia. Patients should be closely monitored prior to each dose for granulocyte and platelet counts. The dosage should be reduced, omitted, or the drug discontinued upon evidence of abnormal suppression of the bone marrow (see DOSAGE AND ADMINISTRATION section).
- Periodic physical examination and checks of renal and hepatic function should be made to detect non-hematologic toxicity. Doses may be reduced or withheld based upon the level of toxicity.
- Administration of AJ-GEMCITABINE in patients with concurrent liver metastases or a pre-existing medical history of hepatitis, alcoholism, or liver cirrhosis may lead to exacerbation of the underlying hepatic insufficiency (see DOSAGE AND ADMINISTRATION section).
- Acute shortness of breath with a temporal relationship to AJ-GEMCITABINE administration may occur (see ADVERSE REACTIONS; and DOSAGE AND ADMINISTRATION sections).
- This preparation is for intravenous administration only.
General
In all instances where the use of AJ-GEMCITABINE is considered for chemotherapy, the physician must evaluate the need and usefulness of the drug against the risk of adverse events. If severe adverse events occur, the drug should be reduced in dosage, omitted, or discontinued and appropriate corrective measures should be taken based on the clinical judgement of the physician (see DOSAGE AND ADMINISTRATION section).
Most drug-related adverse reactions observed with gemcitabine hydrochloride therapy are reversible (see ADVERSE REACTIONS section).
Cardiovascular
Heart failure has been reported very rarely (<0.01%). Arrhythmias, predominantly supraventricular in nature, have been reported signaling awareness of the possibility of cardiovascular events (see ADVERSE REACTIONS: Clinical Trial Adverse Drug Reactions and Post-Market Adverse Drug Reactions sections).
Carcinogenesis and Mutagenesis
Information available is based upon preclinical studies (see TOXICOLOGY section).
Fever and Flu-Like Symptoms
AJ-GEMCITABINE may cause fever, with or without flu-like symptoms, in the absence of clinical infection (see ADVERSE REACTIONS section). The administration of acetaminophen may provide symptomatic relief.
Hematologic
AJ-GEMCITABINE can suppress bone marrow function as manifested by leukopenia, thrombocytopenia and anemia. Blood counts should be taken prior to each dose (see DOSAGE AND ADMINISTRATION section for dose reduction guidelines).
Hepatic
Cases of serious hepatotoxicity including liver failure and death have been very rarely reported in patients receiving Gemcitabine hydrochloride for Injection alone or in combination with other potentially hepatotoxic drugs. A causal relationship between AJ-GEMCITABINE and severe hepatotoxicity including liver failure and death has not been established (see WARNINGS AND PRECAUTIONS: Special Populations; ADVERSE REACTIONS: Clinical Trial Adverse Drug Reactions and Post-Market Adverse Drug Reactions sections).
Radiosensitizing Effect
In a single trial where Gemcitabine hydrochloride for Injection at a dose of 1000 mg/m2 was administered once weekly for up to six (6) consecutive weeks concurrently with therapeutic thoracic radiation to patients with NSCLC, significant toxicity was observed in the form of severe, and potentially life-threatening mucositis, especially esophagitis and pneumonitis, particularly in patients receiving large volumes of radiotherapy [median treatment volumes 4,795 cm3
] (see DRUG INTERACTIONS section for more information). The optimum regimen for safe administration of AJ-GEMCITABINE with therapeutic doses of radiation has not yet been determined.
Renal
There have been cases of histologically confirmed Hemolytic Uremic Syndrome (HUS) reported in patients treated with gemcitabine hydrochloride. Renal failure leading to death or requiring dialysis despite discontinuation of therapy has been reported rarely. The majority of cases of renal failure leading to death were due to HUS (see WARNINGS AND PRECAUTIONS: Special Populations; ADVERSE REACTIONS: Clinical Trial Adverse Drug Reactions and Post-Market Adverse Drug Reactions sections).
AJ-GEMCITABINE should be discontinued at the first signs of any evidence of microangiopathic hemolytic anemia such as rapidly falling hemoglobin with concomitant thrombocytopenia, elevation of serum bilirubin, serum creatinine, blood urea nitrogen, or LDH. Renal failure may not be reversible even with discontinuation of therapy, and dialysis may be required.
Respiratory
Acute shortness of breath in association with AJ-GEMCITABINE administration may occur. Bronchodilators, corticosteriods, and/or oxygen produce symptomatic relief.
Pulmonary effects, sometimes severe (such as pulmonary edema, interstitial pneumonitis, or adult respiratory distress syndrome (ARDS)) have been reported rarely (<0.1%) in association with gemcitabine hydrochloride therapy, some of which may be attributed to capillary leak syndrome (see Vascular section below). If such effects develop, patients should discontinue therapy with AJ-GEMCITABINE and not be re-challenged with the drug. See ADVERSE REACTIONS: Pulmonary; and DOSAGE AND ADMINISTRATION sections.
Skin
Gemcitabine hydrochloride administration has been associated with rash (see ADVERSE REACTIONS). Topical corticosteroids may provide symptomatic relief.
Severe skin reactions, including desquamation and bullous skin eruptions such as toxic epidermal necrolysis (TEN) and Stevens Johnson syndrome (SJS), have been reported very rarely (<0.01%).
Vascular
Clinical signs of peripheral vasculitis and gangrene have been reported very rarely (<0.01%) in association with gemcitabine hydrochloride therapy.
Reports of capillary leak syndrome (CLS) with potentially severe consequences have been reported in patients receiving gemcitabine hydrochloride as single agent or in combination with other chemotherapeutic agents. Gemcitabine hydrochloride should be permanently discontinued and supportive measures implemented if CLS develops during therapy. CLS has been associated in the literature with adult respiratory distress syndrome (ARDS) (see ADVERSE DRUG REACTIONS: Post-Market Adverse Drug Reactions, Vascular section).
Special Populations
Gender: Gemcitabine hydrochloride clearance is affected by gender (see ACTION AND CLINICAL PHARMACOLOGY section). There is no evidence, however, that further dose adjustments (i.e. other than those already recommended in the DOSAGE AND ADMINISTRATION section) are necessary in women.
Renal and Hepatic Impairment: Gemcitabine hydrochloride should be used with caution in patients with pre-existing renal or hepatic insufficiency, as there is insufficient information from clinical studies to allow clear dose recommendations for this patient population. All combination studies involving gemcitabine hydrochloride and cisplatin have been performed in patients with creatinine clearance of ≥ 60 mL/minute.
Administration of gemcitabine hydrochloride in patients with compromised liver function due to liver metastasis or a pre-existing medical history of hepatitis, alcoholism, or liver cirrhosis may lead to exacerbation of the underlying hepatic insufficiency (see DOSAGE AND ADMINISTRATION sections).
Pregnant Women: The use of gemcitabine hydrochloride should be avoided in pregnant women because of the potential hazard to the fetus. Evaluation of experimental animal studies has shown reproductive toxicity, e.g. birth defects or other effects on the development of the embryo or fetus, the course of gestation or peri-and postnatal development.
Nursing Women: The use of gemcitabine hydrochloride should be avoided in nursing women because of the potential hazard to the infant.
Pediatrics (< 17 years of age): Safety and effectiveness in children have not been established.
Geriatrics (> 65 years of age): Gemcitabine hydrochloride has been well tolerated in patients over the age of 65. Although clearance is affected by age (see ACTION AND CLINICAL PHARMACOLOGY section), there is no evidence that further dose adjustments, (i.e. other than those recommended under Dosage and Administration) are necessary in patients over the age of
65.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Gemcitabine hydrochloride has been used, both as a single agent and in combination with other cytotoxic drugs.
Single-Agent Use: Data in Table 1 are based on 22 clinical studies (N=979) of gemcitabine hydrochloride administered as a single agent, using starting doses in the range of 800 to 1250 mg/m2 administered weekly as a 30-minute infusion for the treatment of a wide variety of malignancies. Of the 979 patients only 10.4% (102) were discontinued due to an adverse event regardless of causality. WHO grade 3 or 4 toxicity of non-laboratory events, was less than 1% for all parameters except nausea and vomiting, pulmonary toxicity, infection and pain.
All WHO-graded laboratory toxicities for a total of 979 patients are listed in Table 1, regardless of causality. Non-laboratory WHO-toxicities were available for 565 patients. They are listed in Table 1 (for parameters that occurred in ≥5% of patients), or discussed below. Edema, extravasation and flu-like symptoms were reported regardless of causality as treatment emergent signs and symptoms (TESS1; N=979).
Data are also shown (Table 1) for the subset of patients (N=360) with non-small cell lung cancer treated in 4 clinical studies (2 studies WHO laboratory toxicities; 2 studies non-laboratory WHO-toxicities) and the subset of patients (N=159) with pancreatic cancer treated in 5 clinical studies (WHO laboratory and non-laboratory toxicities). The frequency of all grades were generally similar for the overall safety database and the subsets of patients with non-small cell lung cancer and pancreatic cancer.
Table 1: WHO-Graded Toxicities occurring with a ≥ 5% frequency in Patients Receiving
Gemcitabine hydrochloride for injection
| WHO Grades (in % frequency) are rounded to the closest integer | ||||||||||
| All Patients | Non Small Cell Lung Cancer Patients | Pancreatic Cancer Patients | Disconti-nuations (%) | |||||||
All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | All Patients | |
| LABORATORY | (N=979) | (N=360) | (N=244) | (N=979) | ||||||
| Hematologic | ||||||||||
| Anemia | 68 | 7 | 1 | 65 | 5 | <1 | 73 | 8 | 3 | <1 |
| Neutropenia | 63 | 19 | 6 | 61 | 20 | 5 | 61 | 17 | 7 | |
| Leukopenia | 62 | 9 | <1 | 55 | 7 | <1 | 63 | 8 | 1 | <1 |
| Thrombocytopenia | 24 | 4 | 1 | 16 | 1 | 1 | 36 | 7 | <1 | <1 |
| Hepatic | ||||||||||
| ALT | 68 | 8 | 2 | 70 | 9 | 3 | 72 | 10 | 1 | <1 |
| AST | 67 | 7 | 2 | 67 | 5 | 1 | 78 | 12 | 5 | |
| Alkaline Phosphatase | 55 | 7 | 2 | 48 | 2 | 0 | 77 | 16 | 4 | |
| Bilirubin | 13 | 2 | <1 | 8 | <1 | <1 | 26 | 6 | 3 | |
| Renal | ||||||||||
| Proteinuria | 36 | <1 | 0 | 52 | <1 | 0 | 15 | <1 | 0 | |
| Hematuria | 31 | <1 | 0 | 43 | 2 | 0 | 14 | 0 | 0 | |
| BUN | 16 | 0 | 0 | 16 | 0 | 0 | 15 | 0 | 0 | <1 |
| Creatinine | 7 | <1 | 0 | 6 | <1 | 0 | 6 | 0 | 0 | |
NON- LABORATORY | (N=565) | (N=243) | (N=159) | (N=979) | ||||||
| Gastrointestinal Disorders | ||||||||||
| Nausea and Vomiting | 64 | 17 | 1 | 69 | 19 | <1 | 62 | 12 | 2 | <1 |
| Diarrhea | 12 | <1 | 0 | 6 | <1 | 0 | 24 | 2 | 0 | 0 |
| Constipation | 8 | <1 | 0 | 7 | <1 | 0 | 13 | 2 | 0 | 0 |
1 TESS: An event was considered treatment-emergent, if it occurred for the first time or worsened while receiving therapy following baseline evaluation. It is important to emphasize that although the events were reported during therapy, they were not necessarily caused by the therapy.
| Stomatitis | 8 | <1 | 0 | 7 | <1 | 0 | 10 | 0 | 0 | <1 |
| General Disorders and Administration Site Conditions | ||||||||||
| Fever | 37 | <1 | 0 | 46 | <1 | 0 | 28 | <1 | 0 | <1 |
| Pain | 16 | 1 | 0 | 16 | 1 | 0 | 12 | 2 | 0 | <1 |
| Infections | ||||||||||
| Infection | 9 | 1 | <1 | 10 | 0 | 0 | 8 | 1 | 0 | <1 |
| Nervous System Disorders | ||||||||||
State of Consciousness/ Somnolence | 9 | <1 | 0 | 6 | 0 | 0 | 10 | 3 | 0 | <1 |
| Respiratory Disorders | ||||||||||
| Dyspnea | 8 | 1 | <1 | 8 | 2 | 0 | 6 | 0 | 0 | <1 |
| Skin and Subcutaneous Tissue Disorders | ||||||||||
| Skin Rash | 25 | <1 | 0 | 30 | 0 | 0 | 22 | 0 | 0 | <1 |
| Alopecia | 14 | <1 | 0 | 14 | <1 | 0 | 14 | 0 | 0 | 0 |
Grade based on criteria from the World Health Organization (WHO)
Alopecia: Hair loss (alopecia), usually minimal, was reported for any WHO grade in only 13.7% of patients. No grade 4 toxicity (non-reversible alopecia) was reported, and only 0.4% of patients reported grade 3 toxicity (complete but reversible alopecia).
Cardiac Toxicity: Less than two percent of patients discontinued therapy with gemcitabine hydrochloride due to cardiovascular events such as myocardial infarction, arrhythmia, chest pain, heart failure, pulmonary edema and hypertension. Many of these patients had a prior history of cardiovascular disease.
Cutaneous Toxicity: A rash was seen in 24.8% of patients, was usually mild, not dose limiting and responded to local therapy (see WARNINGS AND PRECAUTIONS section). The rash was typically a macular or finely granular maculopapular pruritic eruption of mild to moderate severity involving the trunk and extremities.
Edema: The occurrence of Edema is reported regardless of causality, as a treatment emergent event (TESS). Edema (13%), peripheral edema (20%) and facial edema (<1%) were reported. Overall, edema was usually mild to moderate and reversible. Less than 1% of patients (N=979) discontinued due to edema.
Extravasation: Gemcitabine hydrochloride is well tolerated during the infusion with only a few cases (4%) of injection site reaction reported. Gemcitabine hydrochloride does not appear to be a vesicant (see DOSAGE AND ADMINISTRATION section). There have been no reports of injection site necrosis.
Fever and Infection: Fever of any severity was reported in 37.3% of patients. Fever was frequently associated with other flu-like symptoms and was usually mild and clinically manageable. Less than 1% of patients were discontinued for fever. The incidence of fever contrasts with the incidence of infection (8.7%) and indicates that gemcitabine hydrochloride may cause fever in the absence of clinical infection (see WARNINGS AND PRECAUTIONS section).
Flu-Like Symptoms: “Flu-syndrome” was reported regardless of causality (TESS) for 18.9% of patients (N=979). Individual symptoms of headache, anorexia, fever, chills, myalgia and asthenia were the most commonly reported symptoms. Cough, rhinitis, malaise, sweating and insomnia were also commonly reported. Less than 1% of patients discontinued due to flu-like symptoms.
Gastrointestinal: Mild or moderate nausea and vomiting (WHO toxicity grade 1 and 2) was reported in 64% of all patients. WHO grade 3 toxicity, defined as vomiting requiring therapy, was reported in 17.1% of patients. Any patient who received prophylactic antiemetics, was automatically graded >WHO grade 3, even if they only developed mild nausea. Diarrhea and stomatitis were usually mild and occurred in less than 13% of patients. WHO toxicity for constipation was mild (WHO grade 1) in the majority of cases and was reported for 7.8% of patients.
Hematologic: Myelosuppression is the major dose-limiting toxicity with gemcitabine hydrochloride; it was usually of short duration, reversible and not cumulative over time. Less than 1% of patients discontinued therapy for either anemia, leukopenia, or thrombocytopenia. Red blood cell transfusions were received by 19% of patients and less than 1% of patients received platelet transfusions. The incidence of major infection (WHO grade toxicity of 3) was only 1.1% and only one grade 4 toxicity for infection occurred.
Hepatic: Gemcitabine hydrochloride was associated with transient elevations of serum transaminases (predominantly WHO grades 1 and 2) in approximately two-thirds of patients, but there was no evidence of increasing hepatic toxicity with either longer duration of treatment with gemcitabine hydrochloride or with greater total cumulative dose.
Neurotoxicity: WHO grade 1 or 2 peripheral neurotoxicity2 was reported for 3.3% of patients. No patient reported WHO grade 3 or 4 toxicity.
State of consciousness toxicity was usually mild to moderate (WHO grades 1 and 2); somnolence was reported for 4.6% of patients.
Pulmonary and Allergic: Gemcitabine hydrochloride should not be administered to patients with a known hypersensitivity to this drug. One case of anaphylactoid reaction has been reported.
The administration of gemcitabine hydrochloride has been infrequently associated with shortness of breath (Dyspnea; See WARNINGS AND PRECAUTIONS section). Dyspnea when graded by WHO-toxicity criteria (Table 1) was reported in 8%, and severe dyspnea (WHO grades 3 and
- 4) was reported in 1.4% of patients.
Dyspnea, regardless of causality (TESS) was reported in 23% of patients and serious dyspnea was reported in 3% of patients. It should be noted that in both of these analyses, the occurrence
2 WHO grade 1 peripheral neurotoxicity is defined as paresthesia and/or decreased tendon reflexes and WHO grade 2 toxicity is defined as severe paresthesia and /or mild weakness.
of dyspnea may have been due to underlying disease such as lung cancer (40% of study population) or pulmonary manifestations of other malignancies. Dyspnea was occasionally accompanied by bronchospasm (<1% of patients).
Renal: Mild proteinuria and hematuria were commonly reported. Clinical findings consistent with the hemolytic uremic syndrome (HUS) were reported in 6 out of 2429 patients (0.25%) receiving gemcitabine hydrochloride in clinical trials (see WARNINGS AND PRECAUTIONS section). Renal failure associated with HUS, may not be reversible even with discontinuation of therapy and dialysis may be required.
Combination Use with Cisplatin in Non-Small Cell Lung Cancer: This section focuses on adverse events that were increased in frequency and/or severity with the addition of cisplatin to gemcitabine hydrochloride. Gemcitabine hydrochloride plus cisplatin was compared to single-agent cisplatin in a randomized trial, and safety data were collected using NCI Common Toxicity Criteria (CTC). In a second randomized trial, gemcitabine hydrochloride plus cisplatin was compared to the combination of cisplatin plus etoposide, and World Health Organization (WHO) criteria were used to grade adverse reactions. All CTC- and WHO-graded adverse events that occurred in ≥10% of patients are listed in Table 2. Toxicity grades for laboratory parameters are reported regardless of causality.
Table 2: CTC- and WHO-Graded Toxicities occurring with a ≥10% frequency in NSCLC
Patients Receiving Gemcitabine hydrochloride for injection plus Cisplatin
| CTC and WHO Grades (in % frequency) are rounded to the closest integer | |||||||
NCI COMMON TOXICITY CRITERIA | Gemcitabine hydrochloride plus Cisplatin (n=260)a vs. Cisplatin (n=262) (% incidence) | WORLD HEALTH ORGANIZATION CRITERIA | Gemcitabine hydrochloride plus Cisplatin (n=69)b vs. Cisplatin plus Etoposide (n=66) (% incidence) | ||||
All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | ||
| LABORATORYc | |||||||
| Hematologic | |||||||
| Anemia | 89 | 22 | 3 | Anemia | 88 | 22 | 0 |
| Thrombocytopenia | 85 | 25 | 25 | Thrombocytopenia | 81 | 39 | 16 |
| Leukopenia | 82 | 35 | 11 | Leukopenia | 86 | 26 | 3 |
| Neutropenia | 79 | 22 | 35 | Neutropenia | 88 | 36 | 28 |
| Lymphocytes | 75 | 25 | 18 | ||||
| Hepatic | |||||||
| Transaminase | 22 | 2 | 1 | ||||
| Alkaline Phosphatase | 19 | 1 | 0 | Alkaline Phosphatase | 16 | 0 | 0 |
| Renal | |||||||
| Creatinine | 38 | 4 | <1 | ||||
| Proteinuria | 23 | 0 | 0 | Proteinuria | 12 | 0 | 0 |
| Hematuria | 15 | 0 | 0 | Hematuria | 22 | 0 | 0 |
| Other Laboratory | |||||||
| Hypomagnesemia | 30 | 4 | 3 | ||||
| Hyperglycemia | 30 | 4 | 0 | ||||
| Hypocalcemia | 18 | 2 | 0 | ||||
| NON-LABORATORYd | |||||||
| CTC and WHO Grades (in % frequency) are rounded to the closest integer | |||||||
NCI COMMON TOXICITY CRITERIA | Gemcitabine hydrochloride plus Cisplatin (n=260)a vs. Cisplatin (n=262) (% incidence) | WORLD HEALTH ORGANIZATION CRITERIA | Gemcitabine hydrochloride plus Cisplatin (n=69)b vs. Cisplatin plus Etoposide (n=66) (% incidence) | ||||
All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | ||
| Blood | |||||||
| Hemorrhage | 14 | 1 | 0 | ||||
| Gastrointestinal Disorders | |||||||
| Nausea | 93 | 25 | 2 | Nausea and Vomiting | 96 | 35 | 4 |
| Vomiting | 78 | 11 | 12 | ||||
| Constipation | 28 | 3 | 0 | Constipation | 17 | 0 | 0 |
| Diarrhea | 24 | 2 | 2 | Diarrhea | 14 | 1 | 1 |
| Stomatitis | 14 | 1 | 0 | Stomatitis | 20 | 4 | 0 |
| General Disorders and Administration Site Conditions | |||||||
| Fever | 16 | 0 | 0 | ||||
| Local | 15 | 0 | 0 | ||||
| Infections | |||||||
| Infections | 18 | 3 | 2 | Infection | 28 | 3 | 1 |
| Nervous System Disorders | |||||||
| Neuro-Motor | 35 | 12 | 0 | Paresthesias | 38 | 0 | 0 |
| Neuro-Hearing | 25 | 6 | 0 | ||||
| Neuro-Sensory | 23 | 1 | 0 | ||||
| Neuro-Cortical | 16 | 3 | 1 | ||||
| Neuro-Mood | 16 | 1 | 0 | ||||
| Neuro-Headache | 14 | 0 | 0 | ||||
| Respiratory Disorders | |||||||
| Dyspnea | 12 | 4 | 3 | ||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Alopecia | 53 | 1 | 0 | Alopecia | 77 | 13 | 0 |
| Rash | 11 | 0 | 0 | Rash | 10 | 0 | 0 |
| Vascular Disorders | |||||||
| Hypotension | 12 | 1 | 0 | ||||
a
Gemcitabine hydrochloride plus cisplatin patients with laboratory or non-laboratory data, N=217-253. Gemcitabine hdyrochloride at 1000 mg/m2 on Days 1, 8, and 15, and cisplatin at 100 mg/m2 on Day 1 every 28 days.
bGemcitabine hdyrochloride plus cisplatin patients with laboratory or non-laboratory data, N=67-69. Gemcitabine hydrochloride at 1250 mg/m2 on Days 1 and 8, and cisplatin at 100 mg/m2 on Day 1 every 21 days. cRegardless of causality.
dNon-laboratory events were graded only if assessed to be possibly drug-related.
Alopecia: In comparison with single-agent gemcitabine hydrochloride for injection therapy, the incidence of alopecia with gemcitabine hydrochloride plus cisplatin combination therapy was increased; 14% with gemcitabine hydrochloride alone versus 53% and 77% with gemcitabine hydrochloride plus cisplatin. Hair loss was usually minimal (CTC/WHO Grade 1 or 2). However, 0.8% of patients that received gemcitabine hydrochloride plus cisplatin on the 4-week schedule experienced CTC Grade 3 alopecia, and 13% of patients who were on the 3-week schedule experienced WHO Grade 3 alopecia. No irreversible (i.e. Grade 4) hair loss was reported.
Fever and Infection:
The majority of patients that received gemcitabine hydrochloride plus cisplatin did not develop fever and only one patient (4-week cycle) experienced CTC Grade 3 fever. On the 4-week gemcitabine hydrochloride plus cisplatin schedule, CTC Grade 3 and 4 infection was seen in 2.8% and 1.6% of patients, respectively. On the 3-week schedule, WHO Grade 3 and 4 infection was seen in 2.9% and 1.4% of patients, respectively.
Gastrointestinal:
The incidence of nausea and vomiting was higher for combination therapy with gemcitabine hydrochloride plus cisplatin (~90%) than it was for single agent gemcitabine hydrochloride (50-70%). On the 4 week cycle, 23% of patients in the gemcitabine hydrochloride plus cisplatin arm experienced CTC Grade 3 or Grade 4 nausea and vomiting, and on the 3 week cycle, the incidence of WHO Grade 3 or 4 nausea and vomiting was 39.1% in the gemcitabine hydrochloride plus cisplatin arm, despite the use of antiemetics. Although nausea and vomiting were frequent, they were rarely dose-limiting and were seldom reasons for discontinuation from the study. Diarrhea, stomatitis and constipation were usually mild and occurred in 14-28% of patients that received gemcitabine hydrochloride plus cisplatin.
Hematologic:
As expected, myelosuppression occurred more frequently with gemcitabine hydrochloride plus cisplatin treatment (~90%) than with gemcitabine hydrochloride monotherapy (~60%), and gemcitabine hydrochloride dosage adjustments for hematologic toxicity were required more often with combination therapy. Although myelosuppression was common, early study discontinuation due to bone marrow suppression occurred in only 3.1% and 4.3% of patients receiving gemcitabine hydrochloride plus cisplatin in the two randomized trials. Platelet transfusions were required by 3% and 21% of patients that received gemcitabine hydrochloride plus cisplatin on a 3-week or 4-week cycle, respectively, and red blood cell transfusions were required by approximately 30-40% of patients. Less than 8% of patients treated with gemcitabine hydrochloride plus cisplatin were hospitalized for febrile neutropenia. Sepsis and severe hemorrhagic events were rare.
Neurotoxicity:
CTC Grade 3 neurohearing toxicity (hearing loss interfering with function but correctable with hearing aid) was experienced by 5.6% and 2.9% of gemcitabine hydrochloride plus cisplatin patients on 4-week and 3-week schedules, respectively. CTC Grade 3 neuromotor toxicity was experienced by 11.5% of gemcitabine hydrochloride plus cisplatin patients on the 4-week schedule, and 38% of patients on the 3-week schedule experienced peripheral neurotoxicity (WHO Grade 1 or 2 only).
Renal:
On the 4-week gemcitabine hydrochloride plus cisplatin schedule, CTC Grade 3 creatinine toxicity was observed in 4.4% of patients, and one patient experienced Grade 4 creatinine toxicity. On the 3-week schedule, no WHO Grade 2, 3 or 4 BUN or creatinine toxicity were observed.
Combination Use with Cisplatin in Bladder Cancer [Transitional Cell Carcinoma (TCC) of the Urothelium]: The following information presents adverse events seen with gemcitabine hydrochloride in combination with cisplatin for treatment of bladder cancer. Gemcitabine hydrochloride plus cisplatin (GC) was compared to MVAC in a pivotal, randomized trial.
Safety data were collected using the WHO toxicity criteria with the exception of Neuro Hearing event which was graded using the NCI Common Toxicity Criteria. All WHO- and CTC graded adverse events that occurred in ≥10% of patients are listed in Table 3.
Alopecia: Grade 3 and 4 alopecia occurred significantly less often in gemcitabine hydrochloride plus cisplatin patients than in MVAC patients (GC 10.5% vs. 55.2%).
Cardiac: Grade 3 and 4 cardiovascular events such as myocardial function, arrhythmia, chest pain, heart failure, pulmonary edema and hypertension were rare; Grade 3 events occurred in 4.1% of patients on gemcitabine hydrochloride plus cisplatin. There were no Grade 4 events. In the MVAC arm 2.2% of patients experienced Grade 3 events and 0.5% of patients experience Grade 4 events.
Gastrointestinal: The incidence of diarrhea was higher in the MVAC treatment arm than it was for the gemcitabine hydrochloride plus cisplatin. In the MVAC arm, 8% of patients experienced Grade 3 or 4 diarrhea compared to 3% of patients in the gemcitabine hydrochloride plus cisplatin arm. Nausea and vomiting occurred in similar frequencies among the gemcitabine hydrochloride plus cisplatin (22%) and the MVAC arms (21%).
Hematologic: Hematologic toxicity was the most frequent laboratory toxicity seen on both treatment arms in this pivotal trial. Grade 3 and 4 neutropenia occurred less often in gemcitabine hydrochloride plus cisplatin patients than in MVAC patients (GC 71% vs. MVAC 82%). Grade 3 and 4 anemia was more common on the gemcitabine hydrochloride plus cisplatin arm versus MVAC arm (27% vs. 18%). Grade 3 and 4 thrombocytopenia was more common on the gemcitabine hydrochloride plus cisplatin arm versus MVAC arm (GC 57% vs. MVAC 21%). In patients with Grade 3 or 4 thrombocytopenia there was no Grade 4 bleeding and only infrequent Grade 3 bleeding (<2%) on either arm. On the gemcitabine hydrochloride plus cisplatin arm, for every 100 cycles of chemotherapy, 13 patients received whole blood or red blood cell transfusion. On the MVAC arm, for every 100 cycles of chemotherapy, 13 patients received whole blood or red blood cell transfusion. On the gemcitabine hydrochloride plus cisplatin arm, for every 100 cycles of chemotherapy, 4 patients received platelet transfusion. On the MVAC arm, for every 100 cycles of chemotherapy, 2 patients received platelet transfusion.
Neurotoxicity: Of the 191 patients assessed in the gemcitabine hydrochloride plus cisplatin arm, CTC Grade 3 neurohearing toxicity occurred in 3 patients (2%). No patient experienced Grade 4 neurohearing toxicity. By comparison, out of 173 patients assessed in the MVAC arm, CTC Grade 3 neurohearing toxicity occurred in 3 patients. Grade 4 neurohearing toxicity occurred in 1 patient.
Pulmonary:
Grade 3 and 4 dyspnea occurred in 2.5% and 0.5% of patients on the gemcitabine hydrochloride plus cisplatin respectively, while compared to 2.6% Grade 3 and 3.1% Grade 4 dyspnea in the MVAC arm.
Renal: No patients on the gemcitabine hydrochloride plus cisplatin arm experienced Grade 3 or 4 renal toxicity, while Grade 3 renal toxicity was observed in 0.5% of patients in the MVAC arm. Renal toxicity was measured by serum creatinine levels.
Table 3: Selected WHO-Graded Adverse Events from Comparative Trial of Gemcitabine hydrochloride plus Cisplatin versus MVAC in TCC of the Bladder
| WHO Grades (% incidence) | ||||||
Gemcitabine hydrocloride plus Cisplatina | MVACb | |||||
| All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | |
| LABORATORYc | ||||||
| Hematologic | ||||||
| Anemia | 94 | 24 | 4 | 86 | 16 | 2 |
| Leukopenia | 92 | 44 | 7 | 93 | 46 | 18 |
| Neutropenia | 91 | 41 | 30 | 89 | 17 | 65 |
| Thrombocytopenia | 86 | 29 | 29 | 46 | 8 | 13 |
| Platelet Transfusionsd | 18 | 8 | ||||
| Hepatic | ||||||
| AST | 30 | 1 | 0 | 28 | 2 | 0 |
| ALT | 29 | 1 | 0 | 28 | 2 | 0 |
| Alkaline Phosphatase | 17 | 2 | 1 | 19 | 1 | 0 |
| Renal | ||||||
| BUN | 36 | 1 | 0 | 37 | 0 | 0 |
| Creatinine | 24 | 0 | 0 | 23 | 1 | 0 |
| Hematuria | 18 | 5 | 0 | 21 | 2 | 0 |
| Proteinuria | 9 | 0 | 0 | 14 | 1 | 0 |
| NON-LABORATORYe | ||||||
| Blood | ||||||
| Hemorrhage | 23 | 2 | 0 | 15 | 2 | 0 |
| Gastrointestinal Disorders | ||||||
| Nausea and Vomiting | 78 | 22 | 0 | 86 | 19 | 2 |
| Constipation | 38 | 2 | 0 | 39 | 3 | 1 |
| Diarrhea | 24 | 3 | 0 | 34 | 8 | 1 |
| Stomatitis | 20 | 1 | 0 | 66 | 18 | 4 |
| General Disorders and Administration Site Conditions | ||||||
| Fever | 21 | 0 | 0 | 30 | 3 | 0 |
| Infections | ||||||
| Infection | 24 | 2 | 1 | 47 | 10 | 5 |
| Nervous System Disorders | ||||||
| Paresthesias | 26 | 1 | 0 | 25 | 1 | 0 |
| Neuro-Hearingf | 19 | 2 | 0 | 14 | 2 | 1 |
| Somnolence | 17 | 1 | 0 | 30 | 3 | 1 |
| Respiratory Disorders | ||||||
| WHO Grades (% incidence) | ||||||
Gemcitabine hydrocloride plus Cisplatina | MVACb | |||||
| All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | |
| Dyspnea | 28 | 3 | 1 | 21 | 3 | 3 |
| Skin | ||||||
| Alopecia | 61 | 11 | 0 | 89 | 54 | 1 |
| Rash | 23 | 0 | 0 | 16 | 0 | 1 |
Grade based on criteria from the World Health Organization (WHO)
a N=191-200; all patients on gemcitabine hydrochloride for injection plus cisplatin with laboratory or non-laboratory data; Gemcitabine hydrochloride for injection 1000 mg/m2 on Days 1, 8, and 15, and cisplatin 70 mg/m2 on Day 2 of each 28-day cycle b N=186-194: all patients on MVAC with laboratory or non-laboratory data: methotrexate 30 mg/m2 on Days 1, 15, and 22,vinblastine 3 mg/m2 on Days 2, 15, and 22, doxorubicin 30 mg/m2 on Day 2, and cisplatin 70 mg/m2 on Day 2 of each 28-day cycle c Regardless of causality
d Percent of patients requiring transfusion
e Non-laboratory events were graded only if assessed to be possibly treatment-related
f Grade based on NCI Common Toxicity Criteria
Combination Use with Paclitaxel in Breast Cancer:
The following information presents adverse events seen with gemcitabine hydrochloride in combination with paclitaxel for the treatment of patients with unresectable, locally recurrent or metastatic breast cancer who have relapsed following anthracycline-based chemotherapy. Gemcitabine hydrochloride plus paclitaxel was compared to paclitaxel in Study JHQG, an unblinded, multicentre, randomized Phase 3 study.
In the gemcitabine hydrochloride plus paclitaxel arm, 7% of patients discontinued treatment because of an adverse event compared to 5% on the paclitaxel arm. In the gemcitabine hydrochloride plus paclitaxel arm, 7% of gemcitabine hydrochloride doses were omitted and 8% were reduced, and 0.9% of paclitaxel doses were omitted and 5% were reduced. In the paclitaxel alone arm, 0.1% of paclitaxel doses were omitted and 2% were reduced. There were 12 deaths in the gemcitabine hydrochloride plus paclitaxel arm, and 8 in the paclitaxel alone arm on study or within 30 days after study drug discontinuation. One death on each arm of the study was possibly drug-related, while the rest of the deaths were attributed to progressive disease and a single death attributed to a traffic accident.
The hospitalization of patients in the gemcitabine hydrochloride plus paclitaxel arm and in the paclitaxel alone arm were similar and not statistically significant (8.8 % and 7.3%, respectively). Median number of cycles given in the gemcitabine hydrochloride plus paclitaxel arm was 6, compared with 5 cycles given in the paclitaxel alone arm.
Table 4 presents a summary of Grade 3 and 4 toxicities reported in the pivotal clinical study JHQG.
Table 4. Percentages of Patients with Grade 3 and 4 Toxicities Reported in the Clinical
Study of Gemcitabine hydrochloride in Combination with Paclitaxel in Patients with Metastatic Breast Cancer
| CTC Grades (% incidence, rounded to the closest integer) a | ||||||
Gemcitabine hydrochloride plus Paclitaxel (N=262) | Paclitaxel alone (N=259) | |||||
| All Grades | Grade 3 | Grade 4 | All Grades | Grade 3 | Grade 4 | |
| LABORATORY b | ||||||
| Hematologic Events | ||||||
| Neutropenia | 69 | 31 | 17 | 31 | 4 | 7 |
| Anemia | 69 | 6 | 1 | 51 | 3 | <1 |
| Thrombocytopenia | 26 | 5 | <1 | 7 | <1 | <1 |
| Leukopenia | 21 | 10 | 1 | 12 | 2 | 0 |
| Liver Abnormalities | ||||||
| ALT | 18 | 5 | <1 | 6 | <1 | 0 |
| AST | 16 | 2 | 0 | 5 | <1 | 0 |
| Metabolic | ||||||
| Hyperglycemia | 6 | 3 | 0 | 5 | 3 | 0 |
| NON-LABORATORYC | ||||||
| Cardiac Disorders | ||||||
| Arrhythmia | <1 | <1 | 0 | 0 | 0 | 0 |
| Gastrointestinal Disorders | ||||||
| Nausea | 50 | 1 | 0 | 31 | 2 | 0 |
| Vomiting | 29 | 2 | 0 | 15 | 2 | 0 |
| Diarrhea | 20 | 3 | 0 | 13 | 2 | 0 |
| Stomatitis / Pharyngitis | 13 | 1 | <1 | 8 | <1 | 0 |
| General Disorders | ||||||
| Fatigue | 40 | 6 | <1 | 28 | 1 | <1 |
| Febrile neutropenia (drug-related) | 6 | 5 | <1 | 2 | 1 | 0 |
| Immune System Disorder | ||||||
| Allergic reaction / Hypersensitivity | 5 | 0 | 0 | 3 | <1 | 0 |
| Musculoskeletal and Connective tissue Disorders | ||||||
| Myalgia | 33 | 4 | 0 | 33 | 3 | <1 |
| Arthralgia | 24 | 3 | 0 | 22 | 2 | <1 |
| Peripheral Nervous System Disorders | ||||||
| Neuropathy – sensory | 64 | 5 | <1 | 58 | 3 | 0 |
| Neuropathy – motor | 15 | 2 | <1 | 10 | <1 | 0 |
| Respiratory Disorders | ||||||
| Dyspnea | 9 | 2 | <1 | 3 | 0 | 0 |
| Hypoxia | <1 | 0 | 0 | <1 | <1 | 0 |
| Skin | ||||||
| Alopecia | 90 | 14 | 4 | 92 | 19 | 3 |
a The toxicities above are as measured by the CTC scale, Version 2.0 (Study JHQG). b Regardless of causality.
c Non-laboratory events were graded only if assessed to be possibly drug-related. Abbreviations: N = number of patients; ALT = alanine aminotransferase; AST = aspartate aminotransferase
Hematologic:
In Study JHQG, more Grade 3 and 4 hematologic toxicities were reported with gemcitabine hydrochloride plus paclitaxel than paclitaxel alone. There was an increased incidence of red blood cell and/or whole blood transfusions (10% versus 4%), erythropoietin use (8% versus 3.5%), and granulocyte colony-stimulating factor use (7.6% versus 1.2%) in the gemcitabine hydrochloride plus paclitaxel arm than in the paclitaxel alone arm, respectively. There was a higher incidence of febrile neutropenia in the gemcitabine hydrochloride plus paclitaxel arm than in the paclitaxel alone arm (5% versus 1%; p<0.05); however, there was not an increased incidence of Grade 3 and 4 infections (<1%) or hemorrhagic events (0%). Of the patients experiencing febrile neutropenia (5%) in the gemcitabine hydrochloride plus paclitaxel arm, the majority of patients required hospitalization and dose adjustments.
Hepatic: Grade 3 and 4 liver enzyme elevation (ALT/AST) occurred in 8% of the patients treated with gemcitabine hydrochloride plus paclitaxel, and in 2% of the patients treated with paclitaxel alone.
Neurotoxicity: Eleven patients in the gemcitabine hydrochloride plus paclitaxel arm and 4 patients in the paclitaxel alone arm discontinued study due to neuropathy. In the gemcitabine hydrochloride plus paclitaxel arm, the majority of patients with neuropathy reported the onset after Cycle 2, while in the paclitaxel alone arm, most patients with neuropathy reported the onset after Cycle 4. Nearly half of the patients on each treatment arm reported Grade 3 or 4 neuropathy that lasted for more than one cycle.
Pulmonary: Grade 3 and 4 pulmonary toxicity characterized as dyspnea or hypoxia (2% versus <1%), were more common in the gemcitabine hydrochloride plus paclitaxel arm compared with the paclitaxel alone arm. Dyspnea was reported as worsening at the time of disease progression in patients who had this symptom reported at the time of study entry. All patients who reported dyspnea as Grade 3 or 4 toxicity and most who reported it as a serious adverse event had metastatic disease in the lungs and/or pleural effusion. No patients discontinued from the study because of grade 3 or 4 dyspnea.
Other Grade 3 or 4 Toxicities: Grade 3 and 4 non laboratory toxicities were more common in the gemcitabine hydrochloride plus paclitaxel arm.
The incidence of Grade 3 and 4 fatigue was 6% in the gemcitabine hydrochloride plus paclitaxel arm and 2% in the paclitaxel alone arm (p<0.05); however, there were no discontinuations due to Grade 3 or 4 fatigue. Grade 3 and 4 fatigue was reported for only one cycle in most patients on both treatment arms and was not associated with anemia.
Alopecia was common and was noted in both treatment arms (18% Grade 3/4 alopecia in the gemcitabine hydrochloride plus paclitaxel arm, and 22% Grade 3/4 alopecia in the paclitaxel alone arm).
Post-Market Adverse Drug Reactions
Cardiovascular:
Heart failure has been reported. Arrhythmias, predominantly supraventricular in nature, have been reported signaling awareness of the possibility of cardiovascular events.
Genito-Urinary System:
Clinical findings consistent with the hemolytic uremic syndrome (HUS) were reported in patients receiving gemcitabine hydrochloride. Gemcitabine hydrochloride should be discontinued at the first signs of any evidence of microangiopathic hemolytic anemia such as rapidly falling hemoglobin with concomitant thrombocytopenia, elevation of serum bilirubin, serum creatinine, blood urea nitrogen, or LDH. Renal failure may not be reversible even with discontinuation of therapy, and dialysis may be required.
Hepatobiliary:
Increased liver function tests including elevations in aspartate aminotransferase (AST), alanine aminotransferase (ALT), gamma-glutamyl transferase (GGT), alkaline phosphatase, and bilirubin levels have been reported. These increases were not all transient, mild or non-progressive (see WARNINGS and PRECAUTIONS: Hepatic section).
Injury, Poisoning, and Procedural Complications:
Radiation toxicity and radiation recall reactions have been reported (see DRUG INTERACTIONS section).
Respiratory:
Pulmonary effects, sometimes severe (such as pulmonary edema, interstitial pneumonitis, or adult respiratory distress syndrome (ARDS)) have been reported in association with gemcitabine hydrochloride therapy some of which may be attributed to capillary leak syndrome (see WARNINGS AND PRECAUTIONS: Vascular section, Post-Market Adverse Drug Reactions: Vascular section).
Skin and Appendages:
Severe skin reactions, including desquamation and bullous skin eruptions, have been reported.
Vascular:
Peripheral vasculitis, gangrene, and capillary leak syndrome have been reported (see WARNINGS AND PRECAUTIONS: Vascular section).
Several cases reported from clinical trials and post-market surveillance describe incidents of capillary leak syndrome (some fatal), which sometimes recurred upon subsequent gemcitabine injection.
There is some evidence to support a causal relationship between gemcitabine and CLS due to temporal relationship, recurrence upon subsequent gemcitabine injection, and biological plausibility.DRUG INTERACTIONS
Overview
The radiosensitizing effects of gemcitabine hydrochloride are reviewed below.
Drug-Drug Interactions
Interactions with other drugs have not been established.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
Drug-Radiation Interactions
Concurrent radiotherapy (given together or ≤ 7 days apart): Toxicity associated with this multimodality therapy is dependent on many different factors, including dose of gemcitabine hydrochloride, frequency of gemcitabine administration, dose of radiation, radiotherapy planning technique, the target tissue, and target volume. Pre-clinical and clinical studies have shown that gemcitabine has radiosensitizing activity. In a single trial where gemcitabine hydrochloride at a dose of 1000 mg/m2 was administered once weekly for up to six (6) consecutive weeks concurrently with therapeutic thoracic radiation to patients with NSCLC, significant toxicity was observed in the form of severe, and potentially life-threatening mucositis, especially esophagitis and pneumonitis, particularly in patients receiving large volumes of radiotherapy [median treatment volumes 4,795 cm3]. The optimum regimen for safe administration of gemcitabine hydrochloride with therapeutic doses of radiation has not yet been determined.
Radiation injury has been reported on targeted tissues (e.g. esophagitis, colitis, and pneumonitis) in association with both concurrent and non-concurrent use of gemcitabine hydrochloride. In addition, radiation recall has been seen with non-concurrent use.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- This preparation is for intravenous use only.
- AJ-GEMCITABINE should be administered by healthcare professionals experienced in the administration of chemotherapeutic drugs.
- Patients should be monitored prior to each dose for granulocyte and platelet counts.
- Periodic physical examination and checks of renal and hepatic function should be made to detect non-hematologic toxicity.
- Dosage escalation or reduction should be based upon the degree of toxicities experienced by the patient.
Treatment Discontinuation
Acute shortness of breath in association with AJ-GEMCITABINE administration may occur. Bronchodilators, corticosteroids and/or oxygen produce symptomatic relief. Some reports of parenchymal lung toxicity were consistent with drug induced pneumonitis in association with the use of gemcitabine hydrochloride (see ADVERSE REACTIONS section). The mechanism of this toxicity is not known. Patients suspected of experiencing drug-induced pneumonitis should be discontinued and not be re-challenged with the drug.
Recommended Dose
Dosage - Pancreatic Cancer:
AJ-GEMCITABINE should be used by IV infusion at a dose of 1,000 mg/m2 over 30 minutes once weekly for up to 7 weeks (or until toxicity necessitates reducing or holding a dose), followed by one week of rest from treatment. Subsequent cycles should consist of infusions once weekly for 3 consecutive weeks out of every 4 weeks.
For dose adjustment guidelines, see Dose Adjustment: Dose Modifications for Pancreatic Cancer, Non-Small Cell Lung Cancer, and TCC of the Bladder Patients section below.
Dosage - Non-Small Cell Lung Cancer: Single-agent AJ-GEMCITABINE should be administered by IV infusion at a dose of 1,000 mg/m2
over 30 minutes once weekly for three consecutive weeks, followed by a one week rest period. This 4 week cycle is repeated.
Gemcitabine hydrochloride has been given in combination with cisplatin on either a 4-week or a 3-week schedule. With the 4-week schedule, AJ-GEMCITABINE should be administered intravenously at 1000 mg/m2 over 30 minutes on days 1, 8, and 15 of each 28-day cycle. Cisplatin should be administered intravenously at 100 mg/m2on day 1 after the infusion of AJ-GEMCITABINE. With the 3-week schedule, AJ-GEMCITABINE should be administered intravenously at 1250 mg/m2 over 30 minutes on days 1 and 8 of each 21-day cycle. Cisplatin at a dose of 100 mg/m2 should be administered intravenously after the infusion of AJ-GEMCITABINE on day 1. See cisplatin prescribing information for administration and hydration guidelines.
For dose adjustment guidelines, see Dose Adjustment: Dose Modifications for Pancreatic Cancer, Non-Small Cell Lung Cancer, and TCC of the Bladder Patients section below.
Dosage - TCC of the Bladder: AJ-GEMCITABINE should be administered by IV infusion at a dose of 1,000 mg/m2 over 30 minutes on Days 1, 8 and 15 of each 28-day cycle. Cisplatin should be administered intravenously at 70 mg/m2 on Day 1 of each 28-day cycle. This 4-week schedule is then repeated. See cisplatin prescribing information for administration and hydration guidelines. A clinical trial showed more myelosuppression when cisplatin was used in doses of 100 mg/m2.
For dose adjustment guidelines, see Dose Adjustment: Dose Modifications for Pancreatic Cancer, Non-Small Cell Lung Cancer, and TCC of the Bladder Patients section below.
Dosage - Breast Cancer: Gemcitabine hydrochloride has been given in combination with paclitaxel. It is recommended to administer paclitaxel (175 mg/m2) on Day 1 over approximately 3 hours as an intravenous infusion, followed by AJ-GEMCITABINE (1250 mg/m2) as a 30-minute intravenous infusion on Days 1 and 8 of each 21-day cycle. Patients should have an absolute granulocyte count ≥1500 x 106 /L and a platelet count ≥100 000 x 106 /L prior to each cycle. See paclitaxel prescribing information for administration guidelines.
For dose adjustment guidelines, see Dose Adjustment: Dose Modifications for Breast Cancer Patients section below.
Dosage Adjustment
Dose Modifications for Pancreatic Cancer, Non-Small Cell Lung Cancer, and TCC of the Bladder Patients:
Patients receiving AJ-GEMCITABINE should be monitored prior to each dose for granulocyte and platelet counts and, if necessary, the dose of AJ-GEMCITABINE may be either reduced or withheld in the presence of hematological toxicity according to the guidelines in Table 5.
Table 5: Dose Adjustments Based on Granulocyte and Platelet Counts
Absolute granulocyte count (x 106/L) | Platelet count (x 106/L) | % of full dose | |
| > 1,000 | and | > 100,000 | 100 |
| 500 - 1000 | or | 50,000 – 100,000 | 75 |
| < 500 | or | < 50,000 | hold |
Periodic physical examination and checks of renal and hepatic function should be made to detect non-hematologic toxicity. Doses may be reduced or withheld based upon the level of toxicity.
Doses should be reduced or withheld until toxicity has resolved in the opinion of the physician.
Dose Modifications for Breast Cancer Patients:
Patients should be monitored prior to each dose with a complete blood count, including differential counts.
AJ-GEMCITABINE dosage adjustments for hematological toxicity is based on the granulocyte and platelet counts taken on Day 8 of therapy. If marrow suppression is detected, AJ-GEMCITABINE dosage should be modified according to the guidelines in Table 6.
Table 6: Day 8 Dosage Reduction Guidelines for AJ-GEMCITABINE in Combination with Paclitaxel.
| Absolute granulocyte count (x 106/L) | Platelet count (x 106/L) | % of full dose | |
| ≥ 1200 | and | > 75,000 | 100 |
| 1000 - 1199 | or | 50,000 - 75,000 | 75 |
| 700 - 999 | and | ≥ 50,000 | 50 |
| < 700 | or | < 50,000 | hold |
Periodic physical examination and checks of renal and hepatic function should be made to detect non-hematologic toxicity. Doses may be reduced or withheld based upon the level of toxicity.
Doses should be reduced or withheld until toxicity has resolved in the opinion of the physician.
For severe (Grade 3 or 4) non-hematological toxicity, therapy should be held or decreased by 50% depending on the judgement of the treating physician.
Administration
Gemcitabine hydrochloride for Injection is well tolerated during the infusion, with only a few cases of injection site reaction reported. There have been no reports of injection site necrosis. Gemcitabine hydrochloride for Injection also does not appear to act as a vesicant in a case of extravasation. AJ-GEMCITABINE may be administered on an outpatient basis.
As with other toxic compounds, caution should be exercised in handling and preparing solutions with AJ-GEMCITABINE. The use of gloves is recommended. If the solution of AJ-GEMCITABINE contacts the skin or mucosa, immediately wash the skin or mucosa thoroughly with soap and water or rinse the mucosa with copious amounts of water.
Reconstitution:
| Vial Size | Volume of Diluent to be Added to Vial | Approximate Available Volume | Nominal Concentration per mL |
| 200 mg | 5.0 mL of 0.9% NaCl Injection | 5 mL | 38 mg/mL |
| 1 g | 25 mL of 0.9% NaCl Injection | 25 mL | 38 mg/mL |
| 2 g | 50 mL of 0.9% NaCl Injection | 50 mL | 38 mg/mL |
To reconstitute, add at least 5 mL of 0.9% Sodium Chloride Injection to the 200 mg vial, at least 25 mL of 0.9% Sodium Chloride Injection to the 1 g vial or at least 50 mL of 0.9% to the 2 g vial. Invert to dissolve. These dilutions each yield a gemcitabine hydrochloride concentration of 38 mg/mL. The appropriate amount of drug may be administered as prepared or further diluted with 0.9% Sodium Chloride Injection to concentrations as low as 0.1 mg/mL.
Reconstitution of concentrations greater than 40 mg/mL may result in incomplete dissolution, and should not be attempted.
Sterile isotonic saline (0.9% sodium chloride injection) without added preservatives should be used as a diluent.
Parenteral drugs should be inspected visually for particulate matter and discoloration, prior to administration, whenever solution and container permit.
See STORAGE AND STABILITY section for more details.
OVERDOSAGE
There is no known antidote for overdoses of AJ-GEMCITABINE. Myelosuppression, and paresthesiae were the principal toxicities seen when a single dose as high as 5700 mg/m2 was administered by IV infusion over 30 minutes every 2 weeks to several patients in a Phase I study. In the event of a suspected overdose, the patient should be monitored with appropriate blood counts and should receive supportive therapy, as necessary.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Gemcitabine hydrochloride is a cell-cycle dependent oncolytic agent of the “antimetabolite” class. It is a deoxycytidine analog (difluoro-deoxycytidine; dFdC) that is metabolized intracellularly to the active diphosphate (dFdCDP) and triphosphate (dFdCTP) nucleosides. The cytotoxic effects of gemcitabine are exerted through dFdCDP-assisted incorporation of dFdCTP into DNA, resulting in inhibition of DNA synthesis and induction of apoptosis.
Pharmacokinetics
Gemcitabine disposition was studied in five patients who received a single 1000 mg/m2/30 minute infusion of radiolabeled drug. Within one (1) week, 92% to 98% of the dose was recovered, almost entirely in the urine. Gemcitabine (<10%) and the inactive uracil metabolite, 2’-deoxy-2’,2’-difluorouridine (dFdU), accounted for 99% of the excreted dose. The metabolite dFdU is also found in plasma. Gemcitabine plasma protein binding is negligible.
The pharmacokinetics of gemcitabine were examined in 353 patients, about 2/3 men, with various solid tumours. Pharmacokinetic parameters were derived using data from patients treated for varying durations of therapy given weekly with periodic rest weeks and using both short infusions (<70 minutes) and long infusions (70-285 minutes). The total gemcitabine dose varied from 500 to 3600 mg/m2.
Gemcitabine pharmacokinetics are linear and are described by a 2-compartment model. Population pharmacokinetic analyses of combined single and multiple dose studies showed that the volume of distribution of gemcitabine was significantly influenced by duration of infusion and gender. Clearance was affected by age and gender. Differences in either clearance or volume of distribution based on patient characteristics or the duration of infusion result in changes in half-life and plasma concentrations. Table 7 shows plasma clearance and half-life of gemcitabine following short infusions for typical patients by age and gender.
Table 7: Gemcitabine Clearance and Half-Life for the “Typical” Patient
| Age | Clearance Men (L/hr/m2) | Clearance Women (L/hr/m2) | Half-Lifea Men (min) | Half-Lifea Women (min) |
| 29 | 92.2 | 69.4 | 42 | 49 |
| 45 | 75.7 | 57.0 | 48 | 57 |
| 65 | 55.1 | 41.5 | 61 | 73 |
| 79 | 40.7 | 30.7 | 79 | 94 |
a
Half-life for patients receiving a short infusion (<70 min)
Gemcitabine half-life for short infusions ranged from 32 to 94 minutes, and the value for long infusions varied from 245 to 638 minutes, depending on age and gender, reflecting a greatly increased volume of distribution with longer infusions. The lower clearance in women and the elderly results in higher concentrations of gemcitabine for any given dose.
The volume of distribution was increased with infusion length. Volume of distribution of gemcitabine was 50 L/m2 following infusions lasting <70 minutes, indicating that gemcitabine, after short infusions, is not extensively distributed into tissues. For long infusions, the volume of distribution rose to 370 L/m2, reflecting slow equilibration of gemcitabine within the tissue compartment.
The maximum plasma concentrations of dFdU (inactive metabolite) were achieved up to 30 minutes after discontinuation of the infusions. The metabolite was excreted in urine without undergoing further biotransformation and did not accumulate with weekly dosing. Its elimination is dependent on renal excretion and the metabolite could accumulate with decreased renal function.
In patients with NSCLC or bladder cancer receiving combination therapy with gemcitabine plus cisplatin, the plasma concentrations of gemcitabine and its major metabolite, dFdU, did not differ significantly from those observed in patients receiving single-agent gemcitabine.
The effects of significant renal or hepatic insufficiency on the disposition of gemcitabine have not been assessed.
The active metabolite, gemcitabine triphosphate, can be extracted from peripheral blood mononuclear cells. The half-life of the terminal phase for gemcitabine triphosphate from mononuclear cells ranges from 1.7 to 19.4 hours.
STORAGE AND STABILITY
AJ-GEMCITABINE should be stored in glass vials, at 15°C to 30° C. Parenteral drugs should be inspected visually for particulate matter and discoloration, prior to administration, whenever solution and container permit. The reconstituted solution is stable for 24 hours at 15°C to 30° C. Any unused solution should be discarded. Solutions of reconstituted AJ-GEMCITABINE should not be refrigerated, as crystallization may occur.
Special Handling Instructions
Procedures for proper handling and disposal of anti-cancer drugs should be considered. Several guidelines on this subject have been published.
DOSAGE FORMS, COMPOSITION AND PACKAGING
AJ-GEMCITABINE is for intravenous use only.
Each 200 mg vial contains AJ-GEMCITABINE (gemcitabine) 200 mg (as the hydrochloride salt), mannitol 200 mg and sodium acetate 12.5 mg. Each 1 g vial contains gemcitabine 1 g (as the hydrochloride salt), mannitol 1 g, and sodium acetate 62.5 mg. Each 2 g vial contains gemcitabine 2 g (as the hydrochloride salt), mannitol 2 g, and sodium acetate 125 mg. Hydrochloric acid and/or sodium hydroxide may have been added for pH adjustment.
Each vial contains 200 mg, 1 g or 2 g sterile lyophilized gemcitabine (expressed as a free base), in a 10 mL-size, 50 mL size or 100 mL size vial, respectively.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: gemcitabine hydrochloride
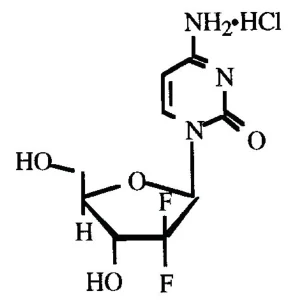
Chemical name: 2’-Deoxy-2’,2’-difluorocytidine monohydrochloride (ß-isomer)
Molecular formula and molecular mass: C9H11F2N3O4. HCl; (299.66 g/mol)
Structural formula:
Physicochemical properties:
- white to off-white solid
- soluble in water
- slightly soluble in methanol
- practically insoluble in ethanol and polar organic solvents
- the pH of a 1% aqueous solution is 2.5, and the pKa is 3.6
CLINICAL TRIALS
Pancreatic Cancer: Data from two clinical trials evaluated the use of gemcitabine hydrochloride in patients with locally advanced or metastatic pancreatic cancer. The first trial compared gemcitabine hydrochloride to 5-Fluorouracil (5-FU) in patients who had received no prior chemotherapy. A second trial studied the use of gemcitabine hydrochloride in pancreatic cancer patients previously treated with 5-FU or a 5-FU-containing regimen. In both studies, the first cycle of gemcitabine hydrochloride was administered intravenously at a dose of 1000 mg/m2 over 30 minutes once weekly for up to 7 weeks (or until toxicity necessitated holding a dose) followed by a week of rest from treatment with gemcitabine hydrochloride. Subsequent cycles consisted of injections once weekly for 3 consecutive weeks out of every 4 weeks.
The primary efficacy parameter in these studies was "clinical benefit response", which is a measure of clinical improvement based on analgesic consumption, pain intensity, performance status and weight change. Definitions for improvement in these variables were formulated prospectively during the design of the two trials. A patient was considered a clinical benefit responder if either:
- i)
the patient showed a ≥50% reduction in pain intensity (Memorial Pain Assessment Card)
or analgesic consumption, or a twenty point or greater improvement in performance status (Karnofsky Performance Scale) for a period of at least four consecutive weeks, without showing any sustained worsening in any of the other parameters. Sustained worsening was defined as four consecutive weeks with either any increase in pain intensity or analgesic consumption or a 20 point decrease in performance status occurring during the first 12 weeks of therapy.
OR:
ii) the patient was stable on all of the aforementioned parameters, and showed a marked, sustained weight gain (≥ 7% increase maintained for ≥ 4 weeks) not due to fluid accumulation.
The first study was a multicenter (17 sites in US and Canada), prospective, single-blinded, two-arm, randomized, comparison of gemcitabine hydrochloride and 5-FU in patients with locally advanced or metastatic pancreatic cancer who had received no prior treatment with chemotherapy. 5-FU was administered intravenously at a weekly dose of 600 mg/m2 for 30 minutes. The results from this randomized trial are shown in Table 8. Patients treated with gemcitabine hydrochloride had statistically significant increases in clinical benefit response, survival, and time to progressive disease compared to 5-FU. The Kaplan-Meier curve for survival is shown in Figure 1.
Table 8: Gemcitabine hydrochloride for injection Versus 5-FU in Pancreatic Cancer
| Gemcitabine hydrochloride | 5-FU | ||
| Number of patients | 63 | 63 | |
| Male | 34 | 34 | |
| Female | 29 | 29 | |
| Median age | 62 years | 61 years | |
| Range | 37 to 79 | 36 to 77 | |
| Stage IV disease | 71.4% | 76.2% | |
| Baseline KPSa ≤70 | 69.8% | 68.3% | |
| Clinical benefit response | 23.8% (Nc = 15) | 4.8% (N = 3) | p = 0.0022 |
| Survival | |||
| Median | 5.7 months | 4.2 months | p = 0.0009 |
| 6-month probabilityb | (N = 30) 46% | (N = 19) 29% | |
| 9-month probabilityb | (N = 14) 24% | (N = 4) 5% | |
| 1-year probabilityb | (N = 9) 18% | (N = 2) 2% | |
| Range | 0.2 to 18.6 months | 0.4 to 15.1+ months | |
| 95% C.I. of the median | 4.7 to 6.9 months | 3.1 to 5.1 months | |
| Time to Progressive Disease | |||
| Median | 2.3 months | 0.9 months | p = 0.0002 |
| Range | 0.1+ to 9.4 months | 0.1 to 12.0+ months | |
| 95% C.I. of the median | 1.9 to 3.4 months | 0.9 to 1.1 months | |
a Karnofsky Performance Status
b Kaplan-Meier estimates
c N = number of patients
+ No progression at last visit; remained alive.
The p-value for clinical benefit response was calculated using the 2-sided test for difference in binomial proportions. All other p-values were calculated using the Log Rank test for difference in overall time to an event.
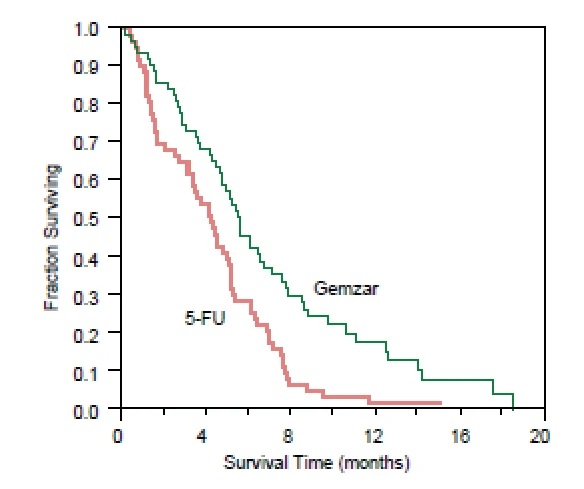
Figure 1: Kaplan-Meier Survival Curve - Gemcitabine hydrochloride for injection Versus 5-FU in Pancreatic Cancer
Clinical benefit response was achieved by 15 patients treated with gemcitabine hydrochloride and 3 patients treated with 5-FU. One patient on the gemcitabine hydrochloride arm showed improvement in all three primary parameters (pain intensity, analgesic consumption, and performance status). Twelve patients on the gemcitabine hydrochloride for injection arm and two patients on the 5-FU arm showed improvement in analgesic consumption and/or pain intensity with stable performance status. Two patients on the gemcitabine hydrochloride arm showed improvement in analgesic consumption or pain intensity with improvement in performance status. One patient on the 5-FU arm was stable with regard to pain intensity and analgesic consumption with improvement in performance status. No patient on either arm achieved a clinical benefit response based on weight gain.
The second trial was a multicenter (17 US and Canadian centers), open-label study of gemcitabine hydrochloride in 63 patients with advanced pancreatic cancer previously treated with 5-FU or a 5-FU-containing regimen. The study showed a clinical benefit response rate of 27% and median survival of 3.9 months.
Non-Small Cell Lung Cancer: Data from three randomized clinical studies (806 patients) support the use of gemcitabine hydrochloride, as a single agent or in combination with cisplatin, for the treatment of patients with locally advanced or metastatic NSCLC.
Gemcitabine hydrochloride for injection versus cisplatin plus etoposide: Single-agent gemcitabine hydrochloride was compared to the combination regimen of cisplatin plus etoposide in previously untreated patients with Stage IIIA, IIIB or IV NSCLC. Patients randomized to gemcitabine hydrochloride (n=72) received 1000 mg/m2 on days 1, 8, and 15 of a 28-day cycle. Patients randomized to cisplatin plus etoposide (n=75) received 100 mg/m2 of cisplatin on day 1 and 100 mg/m2 of etoposide intravenously on days 1, 2 and 3 of each 28-day cycle. The primary end point was objective tumour response rate. Single-agent gemcitabine hydrochloride was as effective as the standard combination regimen of cisplatin plus etoposide in the treatment of chemonaive NSCLC. The objective tumour response rate for gemcitabine hydrochloride was 17.9%, as compared to 15.3% for cisplatin plus etoposide, and there were no complete responses with either treatment. Median survival was estimated to be 6.6 months for gemcitabine hydrochloride patients and 7.6 months for cisplatin plus etoposide patients. The median time to progressive disease was 4.1 months in both treatment groups. Adverse events were less frequent with single-agent gemcitabine hydrochloride as compared to the combination regimen.
Gemcitabine hydrochloride for injection plus cisplatin versus cisplatin: This multicenter study enrolled 522 patients with inoperable Stage IIIA, IIIB, or IV NSCLC who had not received prior chemotherapy. Gemcitabine hydrochloride 1000 mg/m2 was administered on days 1, 8, and 15 of a twenty-eight day cycle with cisplatin 100 mg/m2 administered on day 1 of each cycle. Single-agent cisplatin 100 mg/m2 was administered on day 1 of each 28-day cycle. The primary end point was survival.
Efficacy data are summarized in Table 9, and the Kaplan-Meier survival curve is shown in Figure 2. Median survival time on the gemcitabine hydrochloride for injection plus cisplatin arm was 9.1 months compared to 7.6 months on the single-agent cisplatin arm (Logrank p=0.0040, two-sided). Median time to disease progression was 5.6 months on the gemcitabine 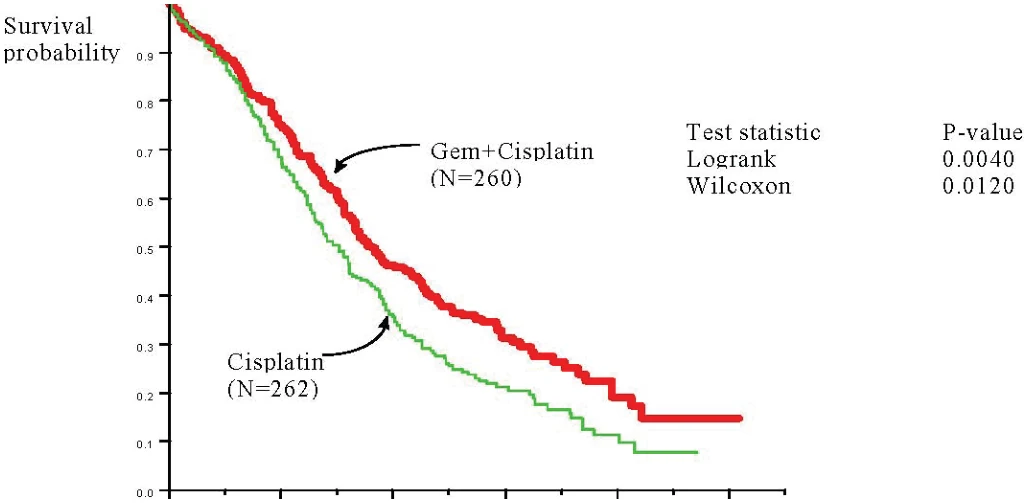
hydrochloride plus cisplatin arm compared to 3.7 months on the cisplatin arm (Logrank p=0.0013, two-sided). The objective response rate on the gemcitabine hydrochloride plus cisplatin arm was 30.4% compared to 11.1% with cisplatin (Fisher’s Exact p<0.0001, two-sided). No differences between treatment arms with regard to median time to tumour response and duration of response were observed.
Figure 2 Kaplan-Meier Survival Curves - Gemcitabine hydrochloride for injection plus
Cisplatin Versus Cisplatin in Non-Small Cell Lung Cancer
TABLE 9: Gemcitabine hydrochloride for injection plus Cisplatin in Non-Small Cell Lung Cancer
| Study JHEX | Study JHBR | ||||||||||||
| Efficacy Measure | Gemcitabine plus Cisplatin (N=260) | Cisplatin (N=262) | Significance | Gemcitabine plus Cisplatin (N=69) | Cisplatin plus Etoposide (N=64) | Significance | |||||||
Tumour Response CRb PR PRNM SD PD Not Evaluable Unknown | 30.4% | 11.1% | Fisher’s Exact Test a | 40.6% none 28 (40.6%) none 30 (43.5%) 6 (8.7%) 1 (1.4%) 4 (5.8%) | 21.9% none 14 (21.9%) none 28 (43.8%) 14 (21.9%) none 8 (12.5%) | Fisher’s Exact Test p=0.0253 | |||||||
| 3 (1.2%) | 1 (0.4%) | p<0.0001 | |||||||||||
| 76 (29.2%) | 28 (10.7%) | ||||||||||||
| 1 (0.4%) | 1 (0.4%) | ||||||||||||
| 97 (37.3%) | 111 (42.4%) | ||||||||||||
| 38 (14.6%) | 86 (32.8%) | ||||||||||||
| 20 (7.7%) | 17 (6.5%) | ||||||||||||
| 25 (9.6%) | 18 (6.9%) | ||||||||||||
Median Survival 6-month probability 9-month probability 1-year probability | 9.1 months | 7.6 months | Log-Rank p=0.0040 | 8.7 months 72% 46% 30% | 7.2 months 63% 42% 24% | ||||||||
| 69% | 61% | Wilcoxon p=0.0120 | |||||||||||
| 50% | 42% | ||||||||||||
| 39% | 28% | ||||||||||||
| Median Time to Progressive Diseasec | 5.6 months | 3.7 months | Log-Rank p=0.0013 | 6.9 months | 4.3 months | Log-Rank p=0.0503 Wilcoxon p=0.0110 | |||||||
| Wilcoxon p=0.0003 | |||||||||||||
| Median Time to Treatment Failured | 3.6 months | 2.6 months | Log-Rank p=0.0026 | 4.1 months | 3.1 months | Log-Rank p=0.2818 Wilcoxon p=0.0419 | |||||||
| Wilcoxon p=0.0040 | |||||||||||||
| Median Time to Tumour Responsee | 1.9 months | 1.8 months | 1.4 months | 1.5 months | |||||||||
| Duration of Tumour Responsef | 6.1 months | 6.7 months | 8.7 months | 6.5 months | |||||||||
a Where a statistically significant difference was observed between treatment arms, the statistical test and p-value have been noted.
b Abbreviations: CR, complete response; PR, partial response; PRNM, partial response non-measurable disease; SD, stable disease; PD, progressive disease.
c The time from randomization until the time that the patient was classified as having progressive disease.
d The time from randomization until the time that the patient discontinued from the study.
e The number of months from randomization until tumour response was observed.
f JHEX: the time from first objective status assessment of CR or PR to the first time of progression or death due to any cause. JHBR: for PRs, the time from randomization to the first time of progression or death due to any cause.
Gemcitabine hydrochloride for injection plus cisplatin versus etoposide plus cisplatin: A second, multicenter, study in Stage IIIB or IV NSCLC randomized 135 patients to gemcitabine hydrochloride 1250 mg/m2 on days 1 and 8, and cisplatin 100 mg/m2 on day 1 of a 21-day cycle or to etoposide 100 mg/m2 I.V. on days 1, 2, and 3 and cisplatin 100 mg/m2 on day 1 on a 21-day cycle (Table 9). The primary end point was objective tumour response rate.
The objective tumour response rate for gemcitabine hydrochloride plus cisplatin was significantly higher than that for cisplatin plus etoposide, 40.6% versus 21.9% (Fisher’s Exact p=0.0253, two-sided). Median time to disease progression for the gemcitabine hydrochloride plus cisplatin arm was 6.9 months compared to 4.3 months on the etoposide plus cisplatin arm (Logrank p=0.0338, two-sided). There was no significant difference in survival between the two treatment arms (Logrank p=0.18, two-sided). The median survival was 8.7 months for the gemcitabine hydrochloride plus cisplatin arm versus 7.2 months for the etoposide plus cisplatin arm.
Bladder Cancer [Transitional Cell Carcinoma (TCC) of the Urothelium]—Data from a randomized, multicenter, phase III clinical trial (405 patients with Stage IV TCC of the bladder) and two phase II trials support the use of gemcitabine hydrochloride in combination with cisplatin for the first-line treatment of patients with Stage IV (locally advanced or metastatic) TCC of the bladder.
The primary objective of the randomized, phase III trial was to compare survival of patients with Stage IV (locally advanced or metastatic) TCC of the bladder treated with either gemcitabine hydrochloride plus cisplatin or methotrexate, vinblastine, doxorubicin, and cisplatin (MVAC). Patients had not received any prior systemic chemotherapy. Patients were randomized to one of the following intravenous treatments:
- i)
Gemcitabine 1000 mg/m2 on Days 1, 8, and 15, and cisplatin 70 mg/m2 on Day 2 of each
28-day cycle,
OR:
ii) Methotrexate 30 mg/m2 on Days 1, 15, and 22, vinblastine 3 mg/m2 on Days 2, 15, and
22, doxorubicin 30 mg/m2 on Day 2, and cisplatin 70 mg/m2 on Day 2 of each 28-day cycle.
The secondary endpoints of this study were one-year survival probability, time to disease progression, response rates, duration of response, toxicity profile, and changes in quality of life. Patient demographics are shown in Table 10.
The Kaplan-Meier survival curve is shown in Figure 3 and efficacy data are summarized in Table 11. Median survival time on the gemcitabine hydrochloride plus cisplatin arm was 12.8 months compared to 14.8 months on the MVAC arm (Logrank p=0.55). Median time to disease progression was 7.4 months on the gemcitabine hydrochloride for injection plus cisplatin arm compared to 7.6 months on the MVAC arm (Logrank p=0.84). The overall response rate on the gemcitabine hydrochloride plus cisplatin arm was 49.4% compared to 45.7% on the MVAC arm (Chi-square p=0.51). Median duration of response was 9.6 months on the gemcitabine hydrochloride plus cisplatin arm compared to 10.7 months on the MVAC arm. Time to treatment
failure on the gemcitabine hydrochloride plus cisplatin arm was 5.8 months vs. 4.6 months on the MVAC arm (Logrank p=0.139). Significantly more patients on gemcitabine hydrochloride plus cisplatin had an increase in weight over baseline compared to MVAC patients (27% vs. 12% p=0.001).
Gemcitabine hydrochloride plus cisplatin was better tolerated than MVAC based on the indicators of tolerability discussed below and shown in Table 12. Gemcitabine hydrochloride plus cisplatin patients received a median of 6 cycles of treatment vs. a median of 4 cycles for MVAC patients. Gemcitabine hydrochloride plus cisplatin patients experienced significantly fewer episodes of neutropenic sepsis than MVAC patients (1% vs. 11.9%, p<0.001). Patients on gemcitabine hydrochloride plus cisplatin experienced fewer episodes of febrile neutropenia resulting in hospitalization than did those on MVAC [9 hospital admissions (33 days) vs. 49 hospital admissions (272 days)]. Fewer gemcitabine hydrochloride plus cisplatin patients required colony-stimulating factors than did MVAC patients (6% vs. 20%). Gemcitabine hydrochloride plus cisplatin patients experienced less Grade 3 and 4 alopecia than did MVAC patients (11% vs. 55%). Grade 3 and 4 nausea and vomiting occurred in approximately 20% of the patients in both treatment arms. Grade 3 and 4 mucositis occurred in 1% of gemcitabine hydrochloride plus cisplatin patients vs. 22% of MVAC patients (p= 0.001).
Table 10: Randomized Trial of Combination Therapy with Gemcitabine hydrochloride for injection plus Cisplatin vs. MVAC in TCC of the Bladder
| Treatment Arm | Gemcitabine hydrochloride for injection plus cisplatin | MVAC |
Number of patients (%) Male Female | N=203 160 (79) 43 (21) | N=202 160 (79) 42 (21) |
| Median age, years Range | 63 34 - 83 | 63 38 - 83 |
Baseline Disease (%) Stage IV T4b only Metastatic (M1) Visceral | 203 (100) 16 (8) 141 (69) 99 (49) | 202 (100) 19 (9) 127 (63) 93 (46) |
Baseline KPSa (%) 60 to 80 90 to 100 | 90 (45) 109 (55) | 92 (48) 101 (52) |
a Karnofsky Performance Scale
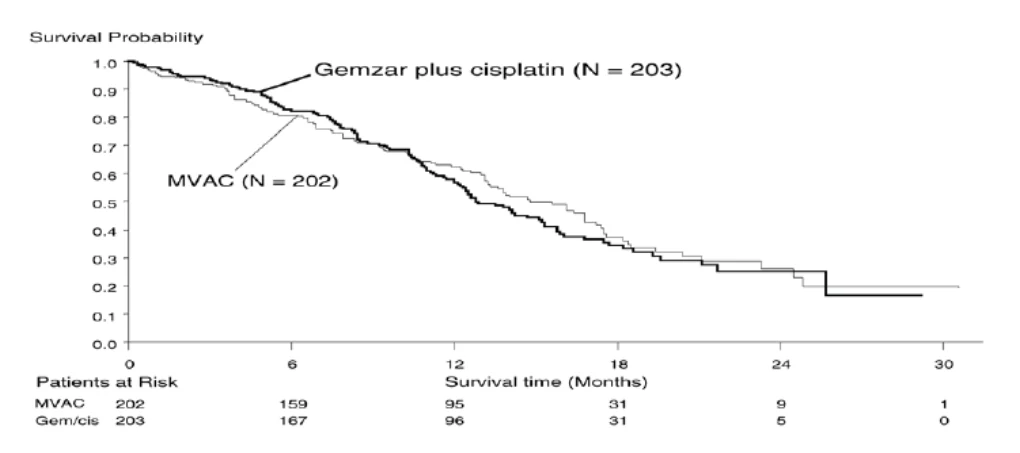
Figure 3: Kaplan-Meier Survival Curve in Gemcitabine hydrochloride for injection plus
Cisplatin versus MVAC Bladder Cancer Study (N=405)
Table 11: Efficacy Data from Pivotal Randomized Trial of Combination Therapy with
Gemcitabine hydrochloride for injection plus Cisplatin vs. MVAC in TCC of the Bladder
a p-value for tumour response was calculated using the 2-sided Pearson Chi-square test for difference in binomial proportions. All other p-values were calculated using the Log-rank test for difference in overall time to an event.
Table 12: Indicators of Tolerability from the Randomized Trial of Gemcitabine hydrochloride for injection plus Cisplatin versus MVAC
| Treatment Arm (N) | Gemcitabine hydrochloride for injection plus cisplatin (203) | MVAC (202) | |
| Median cycles of therapy | 6 | 4 | |
| Total cycles of therapy | 943 | 792 | |
| Neutropenia (%) | |||
| Grade 3 | 41 | 17 | |
| Treatment Arm | Gemcitabine hydrochloride for injection plus cisplatin | MVAC | |
Survival Median, months (95% C.I.) months 1 year survival probability (%) | N=203 12.8 12.0-15.3 56.9 | N=202 14.8 13.2-17.2 62.4 | p = 0.55 |
| Time to Disease Progression Median, months (95% C.I.) months | 7.4 6.0-8.1 | 7.6 6.7-9.1 | p = 0.84 |
| Tumour Response (%) Overall | N = 164 49.4 | N=151 45.7 | p = 0.51a |
| Duration of Response Median, months | 9.6 | 10.7 | p = 0.48 |
| Time to Treatment Failure Median, months | 5.8 | 4.6 | p = 0.14 |
| Treatment Arm (N) | Gemcitabine hydrochloride for injection plus cisplatin (203) | MVAC (202) | |
| Grade 4 | 30 | 65 | |
| Neutropenic sepsis (%) | 1 | 11.9 | p<0.001 |
| Febrile neutropenia | |||
| Hospitalizationsa | 9 | 49 | |
| Duration of stayb | 33 | 272 | |
| Colony-stimulating factors (%) | 6 | 20 | |
| Alopecia (%) | |||
| Grades 3 and 4 | 11 | 55 | |
| Mucositis (%) | |||
| Grades 3 and 4 | 1 | 22 | p= 0.001 |
| Nausea/Vomiting | |||
| Grades 3 and 4 | 22 | 21 | |
aPatient admissions due to febrile neutropenia.
bDays of hospitalization due to febrile neutropenia.
Quality of Life (QOL): QOL was measured using the EORTC QLQ-C30, which assessed physical and psychological functioning and symptoms related to cancer and its treatment. Both arms noted improvement in pain and emotional functioning. Fatigue worsened in the MVAC arm but did not change in the gemcitabine hydrochloride plus cisplatin arm. In all other scales, QOL was maintained in both treatment arms.
Additional Supporting Studies: A phase II nonrandomized trial using gemcitabine hydrochloride in combination with cisplatin in 46 patients with Stage IV (metastatic) TCC of the bladder who had not received treatment for metastatic disease supports the use of gemcitabine hydrochloride plus cisplatin as treatment for this disease. The regimen in this study was gemcitabine hydrochloride 1000 mg/m2
on Days 1, 8 and 15 and cisplatin 75 mg/m2 on Day 1 of each 28-day cycle. The first 11 patients received cisplatin 100 mg/m2 on Day 1; however, Grade 3/4 neutropenia (100%) and thrombocytopenia (73%) in the 11 patients resulted in a dose reduction to 75 mg/m2. In this study, the response rate was 41% and the median survival was 14.3 months. A second phase II [31 patients with Stage IV (locally advanced or metastatic) TCC of the bladder] trial used the same regimen as in the randomized trial. In this study the response rate was 57% and the median survival was 12.6 months. In both these trials, overall toxicities were similar to those seen in the randomized phase III trial.
Breast Cancer: Data from the pivotal study, JHQG (N=529), support the use of gemcitabine hydrochloride in combination with paclitaxel for the treatment of patients with unresectable, locally recurrent or metastatic breast cancer who have relapsed following adjuvant anthracycline based chemotherapy. In this multi centre, open-label, randomized Phase 3 study of metastatic breast cancer patients who have received prior adjuvant/neoadjuvant chemotherapy, 267 patients were randomly assigned to the gemcitabine hydrochloride plus paclitaxel arm and 262 patients were randomly assigned to the paclitaxel alone arm.
The study objectives were to compare overall survival, time to documented disease progression (TtDPD), progression-free survival (PFS), response rates, duration of response, and toxicities between patients treated with gemcitabine hydrochloride plus paclitaxel combination therapy and those treated with paclitaxel monotherapy.
The Kaplan-Meier plot of overall survival for randomized patients is shown in Figure 4, while the overall efficacy results of Study JHQG are summarized below and in Table 13:
- Survival analysis showed improvement in the gemcitabine hydrochloride plus paclitaxel arm compared with the paclitaxel alone arm, as demonstrated by a longer median survival (18.6 versus 15.8 months, with a hazard ratio of 0.817 (95% confidence interval [CI], 0.667 to 1.000, log-rank p=0.0489).
Median time to documented progression of disease (TtDPD) was 5.4 months (95% CI 4.6 to
6.1 months) for patients on the gemcitabine hydrochloride plus paclitaxel arm and 3.5 months (95% CI 2.9 to 4.0 months) for patients on the paclitaxel alone arm.
- The gemcitabine hydrochloride plus paclitaxel arm demonstrated statistically significant improved PFS (5.3 months versus 3.5 months, p=0.0021) and response rate (39% versus 26%, p=0.0007) over the paclitaxel alone arm. There was no statistical significant difference in duration of response between treatment arms.
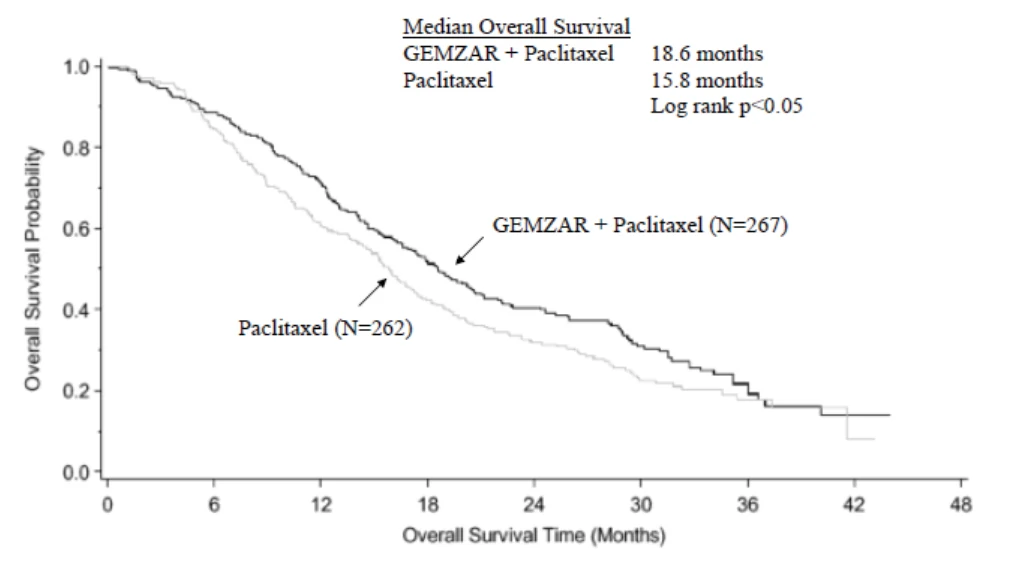
Figure 4: Kaplan-Meier Plot of Overall Survival in Randomized Patients, Study JHQG.
Table 13: Efficacy Results of Pivotal Trial Study JHQG Supporting Combination Therapy of Gemcitabine hydrochloride plus Paclitaxel in Patients with Metastatic Breast Cancer.
| Study JHQG | ||
| Efficacy Endpoint | Gemcitabine hydrochloride plus paclitaxel (N=267) | Paclitaxel alone (N=262) |
| Median Overall Survivala | 18.6 months | 15.8 months |
| 95% CI | 16.6 to 20.7 months | 14.4 to 17.4 months |
| log-rank test | p=0.0489 | |
| HR (95% CI); Wald Test | HR: 0.817 (0.667 to 1.000); p=0.495 | |
| Median TtDPDb | 5.4 months | 3.5 months |
| 95% CI | 4.6 to 6.1 months | 2.9 to 4.0 months |
| log-rank test | p=0.0013 | |
| HR (95% CI); Wald test | HR: 0.734 (0.607 to 0.889); p=0.0015 | |
| Median TtPD/PFSc | 5.3 months PFS | 3.5 months PFS |
| 95% CI | 4.4 to 5.9 months | 2.8 to 4.0 months |
| log-rank test | p=0.0021 | |
| HR (95% CI); Wald test | HR: 0.749 (0.621 to 0.903); p=0.0024 | |
| Response rate—investigator-assessed | 39% (105/267) | 26% (67/262) |
| 95% CI | 34% to 45% | 20% to 31% |
| number of patients with CR/PR/SD | 18 CR /87 PR /90 SD | 11 CR /56 PR /94 SD |
| z-test for normal approximation | p=0.0007 | |
| Response rate—independently reviewedd | 46% (90/198) | 26% (47/184) |
| 95% CI | 39% to 52% | 19% to 32% |
| number of patients with CR/PR/SD | 9 CR /81 PR /71 SD | 2 CR /45 PR /78 SD |
| z-test for normal approximation | p=0.00005 | |
aThe censoring rate for median overall survival was 31.6% for the gemcitabine hydrochloride for injection plus paclitaxel arm and 25.9% for the paclitaxel alone arm.
b
The censoring rate for TtDPD was 23% for gemcitabine hydrochloride for injection plus paclitaxel arm and 17% for the paclitaxel alone arm. c
The censoring rate for PFS was 18% for gemcitabine hydrochloride for injection plus paclitaxel arm and 14% for the paclitaxel alone arm. d
Overall best study response was determined by independent review for 382 patients (198 gemcitabine hydrochloride for injection plus paclitaxel arm, 184 paclitaxel alone arm).
Abbreviations: N = number of patients; TtDPD = time to documented progression of disease; CI = confidence interval; HR = hazard ratio; PFS = progression-free survival; CR = complete response; PR = partial response; SD = stable disease.
Other Clinical Studies
Dose-Range Studies: When gemcitabine hydrochloride was administered more frequently than once weekly or with infusions longer than 60 minutes, increased toxicity was observed. Results of a Phase 1 study of gemcitabine hydrochloride to assess the maximum tolerated dose (MTD) on a daily x 5 schedule showed that patients developed significant hypotension and severe flu-like symptoms that were intolerable at doses above 10 mg/m2. The incidence and severity of these events were dose-related. Other Phase 1 studies using a twice-weekly schedule reached MTDs of only 65 mg/m2 (30-minute infusion) and 150 mg/m2 (5-minute bolus). The dose-limiting toxicities were thrombocytopenia and flu-like symptoms, particularly asthenia. In a Phase 1 study to assess the maximum tolerated infusion time, clinically significant toxicity, defined as myelosuppression, was seen with weekly doses of 300 mg/m2 at or above a 270-minute infusion time. The half-life of gemcitabine is influenced by the length of the infusion (see ACTION AND CLINICAL PHARMACOLOGY section) and the toxicity appears to be increased if gemcitabine hydrochloride for injection is administered more frequently than once weekly or with infusions longer than 60 minutes (see WARNINGS AND PRECAUTIONS
section).
DETAILED PHARMACOLOGY
Cellular Metabolism and Mechanisms of Action: Gemcitabine exhibits cell phase specificity, primarily killing cells undergoing DNA synthesis (S-phase) and, under certain conditions, blocking the progression of cells through the G1/S-phase boundary. In vitro the cytotoxic action of gemcitabine is both concentration-dependent and time-dependent.
Gemcitabine (difluoro-deoxy-cytidine; dFdC) is metabolized intracellularly by nucleotide kinases to the active diphosphate (dFdCDP) and triphosphate (dFdCTP) nucleotides. The cytotoxic action of gemcitabine appears to be due to inhibition of DNA synthesis by two actions of dFdCDP and dFdCTP. First, dFdCDP inhibits ribonucleotide reductase which is uniquely responsible for catalyzing the reactions that generate the deoxynucleotide triphosphates for DNA synthesis. Inhibition of this enzyme by dFdCDP causes a reduction in the concentrations of deoxynucleotides in general, and especially in that of dCTP. Second, dFdCTP competes with dCTP for incorporation into DNA. Likewise, a small amount of gemcitabine may also be incorporated into RNA. Thus, the reduction in the intracellular concentration of dCTP potentiates the incorporation of dFdCTP into DNA. DNA polymerase epsilon is essentially unable to remove gemcitabine and repair the growing DNA strands. After gemcitabine is incorporated into DNA, one additional nucleotide is added to the growing DNA strands. After this addition there is essentially a complete inhibition in further DNA synthesis (masked chain termination). After incorporation into DNA, gemcitabine appears to induce the programmed cellular death process known as apoptosis.
Anti-Tumour Activity:
In vivo:
In animal tumour models, the anti-tumour activity of gemcitabine is schedule-dependent. When administered daily gemcitabine causes significant animal lethality with very little anti-tumour activity. However, when an every third or fourth day dosing schedule is used gemcitabine can be given at non-lethal doses that have an excellent anti-tumour activity against a broad range of murine tumours. For example, at non-toxic doses gemcitabine inhibits by 95-100% the growth of the following subcutaneously growing murine tumours: X5563 plasma cellmyeloma, 6C3HED lymphosarcoma, CA-755 mammary adenocarcinoma and M5 ovarian carcinoma. Gemcitabine inhibits the growth of subcutaneously growing B16 melanoma in the range of 60 - 80%. Gemcitabine produces significant increases in the life span of mice bearing the leukaemia models P388 and L1210 in the range of 50 - 200%. Gemcitabine also inhibits the growth of P 1534J and Friend Leukaemia in the order of 90%.
Gemcitabine has anti-tumour activity against a broad spectrum of human tumours grown as xenografts in immunologically deficient mice. As with murine tumours, optimum antitumour activity is seen when gemcitabine is given on a staggered dosing schedule. Several studies have shown that gemcitabine, at non-toxic doses, inhibits by 90-100% the growth of the following human carcinoma xenografts: non-small cell lung, mammary, colon, gastric, pancreatic, ovarian and head and neck.
Gemcitabine demonstrated dose-dependent synergistic activity with cisplatin in vitro, and no effect of cisplatin on gemcitabine triphosphate accumulation or DNA double-strand breaks was observed. In vivo, gemcitabine showed activity in combination with cisplatin against the LX-1 and CALU-6 human lung xenografts, but minimal activity was seen with the NCI-H460 or NCI-H520 xenografts. When tested against the CALU-6 human lung adenocarcinoma xenograft, gemcitabine plus cisplatin produced 80% tumour regression and 98% tumour growth inhibition, without toxicity, and was more effective than gemcitabine alone at preventing regrowth of this tumour. Gemcitabine was synergistic with cisplatin in the Lewis lung murine xenograft. Sequential exposure to gemcitabine 4 hours before cisplatin produced the greatest interaction.
TOXICOLOGY
Repeat Dose Toxicity Studies:
In repeat dose studies of up to 6 month in duration in mice and dogs, the principal finding was haematopoietic suppression. These effects were related to the cytotoxic properties of the drug and were reversible when treatment was withdrawn. The degree of the effect was schedule and dose-dependent.
Carcinogenicity, Mutagenicity, and Fertility Studies: Chromosomal damage, including chromatid breaks, has been produced by gemcitabine in in vitro studies. Gemcitabine caused a reversible, dose and schedule dependent hypospermatogenesis in male mice. Although animal studies have shown an effect of gemcitabine on male fertility, no effect has been seen on female fertility. Long-term animal studies have not been conducted to evaluate the carcinogenic potential of gemcitabine. Gemcitabine induced forward mutations in vitro in a mouse lymphoma (L5178Y) assay and was clastogenic in an in vivo mouse micronucleus assay. Gemcitabine was negative when tested using the Ames, in vivo sister chromatid exchange, and in vitro chromosomal aberration assays, and did not cause unscheduled DNA synthesis in vitro. Gemcitabine I.P. doses of 0.5 mg/kg/day (about 1/700 the human dose on a mg/m2 basis) in male mice had an effect on fertility with moderate to severe hypospermatogenesis, decreased fertility, and decreased implantations. In female mice fertility was not affected but, maternal toxicities were observed at 1.5 mg/kg/day I.V. (about 1/200 the human dose on a mg/m2 basis) and fetotoxicity or embryolethality was observed at 0.25 mg/kg/day I.V. (about 1/1300 the human dose on a mg/m2 basis).
The results of the toxicology studies involving gemcitabine are presented in Tables 14 to 17.
Table 14: Results of Acute Toxicity Studies With Gemcitabine Hydrochloride
| Species, Strain | No/Sex/ Group; Age | Doses (mg/kg/ day) | Route of Admini-stration | Duration of Observa- tion | Parameters Evaluated | Observations |
| Mouse, ICR | 5/sex; 4-5 wk | 0, 500 | IVa | 2 wk | Mortality, clin obs., body wt., gross pathology. | Poor grooming; ↓body wt. gain; leg weakness & clonic convulsion in control & treated mice; MLD›500 mg/kg. |
| Species, Strain | No/Sex/ Group; Age | Doses (mg/kg/ day) | Route of Admini-stration | Duration of Observa- tion | Parameters Evaluated | Observations |
Rat, Fischer 344 | 5 F; 8-9 wk | 0, 16, 33, 70, 160 | IVa | 2 wk | Mortality, clin obs., body wt., gross pathology. | Poor grooming, leg weakness; hypoactivity, diarrhea, ataxia, chromorhinorrhea, swollen face, chromadacryorrhea, emaciation, tremors, clonic convulsions, dark urine, pale eyes; MLD=64 mg/kg. |
| Mouse, ICR | 5/sex; 4-5 wk | 0, 500 | IVc | 2 wk | Mortality, clin obs., body wt., gross pathology. | Leg weakness, hair loss; MLD›500 mg/kg. |
Rat, Fischer | 5F; 8-9 wk | 0, 16, 33, 45, 70, 90, 160 | IVc | 2 wk | Mortality, clin. obs., body wt., gross pathology. | Poor grooming, leg weakness, hypoactivity, soft stool, diarrhea, excessive hair loss, emaciation, chromodacryorrhea, ptosis, pale eyes; MLD=236 mg/kg. |
Dog, Beagle | 1/sex; 8-10 mo | 3, 12, 18, 24 | IVc | 2 wk | Mortality, clin. obs., body wt., food consumption, hematology, clinical chem. | Soft or mucoid stools, reversible neutropenia; MLD›24 mg/kg. |
am-cresol/phenol diluent bMLD=Median Lethal Dose cSaline Diluent
Table 15: Results of Subchronic and Chronic Toxicity Studies With Gemcitabine Hydrochloride
| Species, Strain | No./Sex/ Group; Age | Doses (mg/kg) | Route of Admini-stration | Duration of Treat-ment | Parameters Evaluated | Observations |
| Subchronic Studies | ||||||
Dog, Beagle | 4/sex; 7-9 mo. | 0, 0.1 (daily) 1.5 (twice wkly) | IV | 3 mo | Survival; clin. obs.; physical & ophthalmic exams; body wt.; food consumption; hematol.; clinical chem.; urinalysis; organ wt.; pathology. | Abnormal stools; reversible mild to moderate ↓leucocytes & platelets in 1.5 mg/kg reversible minimal ↓erythrocyte count in 0.1 mg/kg group; hypoplasia of thymus & testes & ↓postmitomyeloid pool in bone marrow in 1.5 mg/kg group. |
Mouse, B6C3F1 | 15/sex; 5-6 wk | 0, 1 (daily); 5, 20 (2 X wkly) 40 (once weekly) | IP | 3 mo | Survival, clin. obs.; body wt.; hematology; clinical chem.; organ wt.; pathology. | ↓hemoglobin, PCV, erythrocyte & leukocyte counts in 1 mg/kg group; ↑spleen & ↓testes wt.; splenic erythropoiesis & spermatogenesis. |
| Chronic Studies | ||||||
Mouse, CD-1 | 30/sex; 5-6 wk | 0, 0.5 (daily); 5 (twice weekly); 40 (once weekly) | IP | 6 mo; 2 mo recovery | Survival; clin. obs.; body wt.; hematol.; clin. chem.; organ wt.; pathology. | Mortality (3), ↓body wt. & wt. gain; reversible ↓erythrocyte & lymphocyte counts, reversible ↑BUN & ↓total protein, ↓testes wt., ↑spleen wt., splenic erythropoiesis, & lymphoid hypoplasia in 0.5 mg/kg group; hypospermatogenesis in all treated males partially reversible. |
Mouse, CD-1 | 15/sex; 5-6 wk | 0, 0.006, 0.06 0.3 (daily) | IP | 6 mo; 6-wk recovery | Survival; clin. obs.; body wt.; food consumption; hematol.; clin. chem.; urinalysis; organ wt.; pathology. | Slight ↓body wt.; reversible ↓erythrocyte count, ↓testes wt.; ↑spleen wt.; hypospermatogenesis in 0.3 mg/kg group; spleen & testes changes partially reversible. |
Dog Beagle | 3-4/sex; 7-9 months | 0, 0.004, 0.04, 0.2 (daily); 0.3 (once weekly) | IV | 6 mo; 6-wk recovery | Survival; clin. obs.; body wt.; food consumption; ophthalmic & physical exams; ECG; hematol.; clin. chem.; urinalysis; organ wt.; pathology. | Reversible slight ↓erythrocyte count in 0.2 mg/kg group; slight ↓lymphocyte & neutrophil counts in 0.2 & 0.3 mg/kg groups. |
Table 16: Results of Reproduction Studies With Gemcitabine Hydrochloride
| Species, Strain | No./Sex/ Group; Age | Doses (mg/kg) | Route of adminis-tration | Duration of Treatment | Parameters Evaluated | Observations |
| Mouse, B6C3F1 | 20 M; 5 wk | 0, 0.05, 0.5 (daily); 3.5, 10 (weekly) | IP | 10 wk prior to mating, throughout mating | Survival; clin. obs.; body wt.; food cons.; mating performance; fertility; resorptions; fetal parameters; testes wt. & histopath. | ↓fertility, implantations (0.5 mg/kg daily) ↓testicular wt., hypospermatogenesis (0.5 mg/kg/day & 3.5 & 10 mg/kg/week). |
| Mouse, CD-1 | 25 F; 9 wk | 0, 0.5, 0.25, 1.5 (daily) | IV | 2 wk prior to mating, through Gestation Day 6 | Survival; clin. obs; body wt.; food cons; mating performance; fertility; resorptions; fetal parameters; hematology; organ wt. | ↓fetal viability;↓fetal wt.; ↑%fetal runts; slight ↑PCV; hemoglobin, MCV, MCH; ↑spleen wt. (1.5 mg/kg/day). |
| Mouse, CD-1 | 25 F (Teratology) 20F (Postnatal); adult, virgin | 0, 0.05, 0.25, 1.5 (daily) | IV | Gestation Days 6-15 | Survival; clin. obs.; body wt.; food cons.; reproduction (F0 & F1); fetal parameters; progeny measurements (F0 & F1); F0 preweaning & F1 postweaning behavior; hematology F0 pathology (F0 & F1 generations). | ↑vaginal discharge & abortions; ↓body wt., food cons.; (1.5 mg/kg/day). ↑spleen wt.; (0.05, 0.25 & 1.5 mg/kg/day). ↓liver wt.; ↑thymus wts.; ↓fetal wt.;↓fetal malformations (1.5 mg/kg). ↓liveborn progeny, ↓progenysurvival; ↓progeny wt. (1.5 mg/kg/day). ↓relative ovary wt. in all F1 groups. ↓startle reactivity in F1 males (0.05 & 1.5 mg/kg/day groups). ↑MCV, MCH (0.25 & 1.5 mg/kg/day). |
| Mouse, CD-1 | 25 F; adult, virgin | 0, 0.05, 0.1, 0.25, 1.5 (daily) | IV | Gestation Day 15-Postpartum Day 20 | Survival; clin. obs.; body wt.; food cons.; organ wts. (F0 & F1); reproduction & progeny measurements (F0 & F1); preweaning & postweaning behavior; hematology (F0); pathology (F0 & F1). | ↓fetal viability, ↓fetal wt.; ↑malformations & deviations (0.1 mg/kg/day), ↓erythrocytes, hemoglobin, PCV (0.1 mg/kg/day). |
Rabbit, New Zealand, White | 20 F; mated adult | 0, 0.0015, 0.005, 0.1 (daily) | IV | Gestation Days 6-18 | Survival; clin. obs.; body wt.; food cons.; hematology; fetal viability, fetal wt., morphology. | ↓fetal viability, ↓fetal wt., ↑malformations & deviations (0.1 mg/kg/day); ↓erythrocytes, hemoglobin, PCV (0.1 mg/kg/day). |
Table 17: Results Of Mutagenicity Studies With Gemcitabine Hydrochloride
| Type of Study | Species, Cells | Route of Administration | Doses/ Concentrations | Results |
| Ames | Salmonella typhimurium, Escherichia coli | Not applicable | 125 to 5000 µg/plate | Negative nonactivated & activated |
| Unscheduled DNA | Adult rat hepatocites | Not applicable | 0.5 to 1000 µg/ml | Negative |
| Forward mutation at thymidine kinase locus | L5178Y TK+/-mouse lymphoma | Not applicable | 0.001 to 0.06 µg/ml | Positive non activated & with metabolic activation |
| Sister chromatid exchange in bone marrow | Chinese hamster | Intraperitoneal | 3.125 to 50 mg/kg | Negative |
| Chromosome aberration | Chinese hamster ovary | Not applicable | 0.005 to 0.03 µg/ml, 0.04 to 0.1 µg/ml | Negative nonactivated; with metabolic activation |
| Micronucleus | Mouse, bone marrow | Intravenous | 0, 0.1875, 0.375, 0.75 mg/kg | Positive |
REFERENCES
- 1.
Abbruzzese JL. Grunewald R, Weeks EA, Gravel D, Adarns T, Nowak B, Mineishi S,
Tarassoff P, Satterlee W, Raber MN, Plunkett W. A phase I clinical, plasma, and cellular pharmacology study of gemcitabine. J Clin Oncol. 1991;9:491-498.
- 2. Advanced Ovarian Cancer Trialists Group. Chemotherapy in ovarian cancer: an overview of randomised clinical trials. Br Med J 1991; 303: 884 - 893.
- 3.
Aisner J, Weinberg V, Perloff M et al. Chemotherapy versus chemo-immunotherapy (CAF v
CAFVP v CMF each + MER) for metastatic carcinorna of the breast: a CALBG study. J Clin Oncol 1987; 5: 1523 -1533.
- 4.
Andersen JS. Burris HA, Casper E, Clayman M, Green M, Nelson RL, Portenoy R,
Rothenberg M, Tarassoff PG, Von Hoff DD. Development of a new system for assessing Clinical benefits for patients with advanced pancreatic cancer (meeting abstract). Proc Annu Meet Am Soc Clin Oncol. 1994; 13: A1600.
- 5.
Bajorin DF, Dodd PM, Mazumdar M, Fazzari M, McCaffrey JA, Scher HI et al. Long-Term
Survival in Metastatic Transitional-Cell Carcinoma and Prognostic Factors Predicting Outcome of therapy. J Clin Oncol 1999;17(10):3173-3181.
- 6.
Bishop JF, Dewar J, Toner C, et al. Initial paclitaxel improves outcome compared with
CMFP combination chemotherapy as front-line therapy in untreated metastatic breast cancer. J Clin Oncol 1999;17(8):2355-2364.
- 7. Carmichael J, Fink U, Russell RCG, Spittle MF, Harris AL, Spiessi G, Blatter J. Phase II study of gemcitabine in patients with advanced pancreatic cancer. British Journal of Cancer 1996; 73: 101-105.
- 8. Cartei G, Cartei F, Cantone A, Causarano D, Genco G, Tobaldin A et al. Cisplatin-cyclophosphamide-mitomycin combination chemotherapy with supportive care versus supportive care alone for the treatment of metastatic non-small cell lung cancer. J Natl Cancer Inst 1993; 85: 794 - 800.
- 9.
Casper ES, Green MR, Kelsen DP, Hellan RT, Brown TD, Flombaum CD, Trochanowski B,
Tarassoff PG. Phase II trial of gemcitabine (2,2’-difluorodeoxycytidine) in patients with adenocarcinoma of the pancreas. Invest New Drugs 1994; 12: 29-34.
- 10. Coates A, Gebski V, Bishop JF et al. Improving the quality of life during chemotherapy for advanced breast cancer. A comparison of intermittent and continuous treatment strategies. N Engl J Med 1987; 317: 1490 -1495.
- 11. Cormier Y, Bergeron D, Laforge J, et al. Benefit of polychemotherapy in advanced non-small cell lung bronchogenic carcinoma. Cancer 1982; 50: 845 - 849.
- 12. Cullen MH, Joshi R, Chetiyawardana AD, Woodroffe CM. Mitomycin, ifosfamide and cisplatin in non-small cell lung cancer: treatment good enough to compare. Br J Cancer 1988; 58: 359 -361.
- 13.
Cullen MH. The MIC regimen in non-small cell lung cancer. Lung Cancer 1993; 9 (suppl 2):
81- 89.
- 14. Cummings FJ, Gelman R, Horton J. Comparison of CAF versus CMFP in metastatic breast cancer analysis of prognostic factors. J Clin Oncol 1985; 3: 932 - 940.
- 15.
DeVita VT Jr, Hellman S, Rosenberg SA, eds. Cancer: Principles and Practice of Oncology.
Philadelphia, Pa: JB Lippincott Co; 1993;1:673.
- 16. Donnadieu N, Paesmans M, Sculier J-P. Chemotherapy of non-small cell lung cancer according to disease extent: a meta-analysis of the literature. Lung Cancer. 1991;7:243-252.
- 17. Evans WK. Management of metastatic non-small-cell lung cancer and a consideration of cost. Chest. 1993;103(1):68S-71S.
- 18.
Evans WK. Rationale for the treatment of non-small cell lung cancer. Lung Cancer.
1993;9(suppl. 2):S5-S14.
- 19.
Genot JY, Tubiana-Hulin M, Tubiana-Mathieu N, Piperno-Neumann S. Gemcitabine and
Paclitaxel in Metastatic Breast Cancer: a Phase 2 Study in the First Line Setting. Proc ASCO 2002. 21(Part 2):44b.
- 20.
Ginsberg RJ, Gris MG & Armstrong JG. in: Cancer: Principles and Practice of Oncology,
Fourth Edition. Ed: Vincent De Vita Jr, Samuel Hellmann, Steven A Rosenberg. Philadelphia, JB Lippincott Co 1993; 673 - 723.
- 21.
Green MR. Gemcitabine: We’ve reached the end of the beginning. Semin Oncol 1996; 23(5
SUPPL. 10): 99-100.
- 22.
Grindey G et al. Cytotoxicity and antitumor activity of 2',2' difluorodeoxycytidine
(gemcitabine). Cancer lnvest. 1990;8:313
- 23. Grunewald R, Abbruzzese JL, Tarassof P, Plunkett W. Saturation of 2',2'-difluorodeoxycytidine 5'-triphosphate accumulation by mononuclear cells during a phase I trial of gemcitabine. Cancer Chemother Pharmacol. 1991 ,27:258-262.
- 24.
Hanks GE, Myers CE, Scardino PT. Cancer of the Prostate. in: Cancer: Principles and
Practice of Oncology, Fourth Edition. Ed: Vincent De Vita Jr, Samuel Hellmann, Steven A Rosenberg. Philadelphia, JB Lippincott Co 1993; 1073 -1113.
- 25.
Hardy JR, Noble T, Smith IE. Symptom relief with moderate dose chemotherapy
(mitomycin-C, vinblastine and cisplatin) in advanced non-small cell lung cancer. Br J Cancer 1989; 60: 764 -766.
- 26. Heinemann V, Hertel LW, Grindey GB, et al. Comparison of the cellular pharmacokinetics and toxicity of 2',2'-difluorodeoxycytidine and l-~-D-Arabinofuranosylcytosine. Cancer Res. 1988;48:4024-403 l .
- 27.
Heinemann V, Wilke H, Possinger K, Mergenthaler K, Clemens M, Konig HJ, Illiger HJ,
Blatter J, Schallhorn A, Fink U. Gemcitabine and cisplatin: combination treatment for advanced and metastatic pancreatic carcinoma (Meeting abstract). Proc Annu Meet Am Soc Clin Oncol 1996; 15: A623.
- 28.
Ihde DC, Minna JD. Non small cell lung cancer. Part II. Treatment. In: Haskell CM, ed.
Current Problems in Cancer. St. Louis, MO: Mosby-Year Book Inc; 1991;109-153.
- 29. Ihde DC. Chemotherapy of lung cancer. N Engl J Med 1992; 327: 1434 -1441.
- 30.
Ihde DC, Pass Hl, and Glatstein EJ. Small Cell Lung Cancer. in: Cancer Principles and
Practice of Oncology, Fourth Edition. Ed: Vincent De Vita Jr, Samuel Hellmann, Steven A Rosenberg. Philadelphia, JB Lippincott Co 1993; 732 - 736.
- 31. Jaakkimainen L, Goodwin PJ, Pater J, Warde P, Murray N, Rapp E. Counting the costs of chemotherapy in a National Cancer Institute of Canada randomized trial in non-small cell lung cancer. J Clin Oncol. 1990;8:1301-1309.
- 32. Jensen OM, Esteve J, Moller H, Renard H. Cancer in the European community and its member states. Eur J Cancer. 1990;26:1167-1256.
- 33. Lawrence TS, Chang EY, Hahn TM, Jertel LW, Shewach DS. Radiosensitization of pancreatic cancer cells by 2’,2’-difluoro-2’-deoxycytidine. Int J Radiat Oncol Biol Phys 1996;34(4):867872.
- 34. Le Chevalier T, Scagliotti G, Natale R, et al. 2005. Efficacy of gemcitabine plus platinum chemotherapy compared with other platinum containing regimens in advanced non-smallcell lung cancer: a meta-analysis of survival outcomes. Lung Cancer 47:69-80
- 35.
Lenzi R, Fossella FV, Lee JS. Systemic treatment of non-small cell lung cancer. Comp. Ther.
1992;18:27-30.
- 36. Loehrer PJ Sr, Einhorn LH, Elson PJ, et al. 1992. A randomized comparison of cisplatin alone or in combination with methotrexate, vinblastine, and doxorubicin in patients with metastatic urothelial carcinoma: a cooperative study. J Clin Oncol 10(7): 1066-1073.
- 37.
Moore M. Activity of gemcitabine in patients with advanced pancreatic carcinoma: a review.
Cancer 1996; 78(3 SUPPL):633-638.
- 38.
Moore M, Andersen J, Burris H, Tarasoff P, Green M, Casper E, Portenoy R, Modiano M,
Cripps C, Nelson R. A randomized trial of gemcitabine (gem) versus 5FU as first-line therapy in advanced pancreatic cancer (meeting abstract). Proc Annu Meet Am Soc Clin Oncol 1995; 14:A473.
- 39. Nabholtz JM, Gelmon K, Bontenbal M, et al. Multicenter, randomized comparative study of two doses of paclitaxel in patients with metastatic breast cancer. J Clin Oncol 1996; 14(6):18581867.
- 40. Niyikiza C, Anderson JS Tarassoff PG, Rothenberg ML, Seitz DE, Nelson RL. Prognostic factors in a randomized trial of gemcitabine (GEM) versus 5-FU as first-line therapy in advanced pancreatic cancer and in pancreatic cancer patients failing 5-FU who receive gemcitabine (GEM) as a palliative therapy. Proc Am Soc Clin Oncol 1996; 15(32): A506.
- 41. Osoba D, Rusthoven JJ, Turnbull KA, Evans WK, Shepherd FA. Combination chemotherapy with bleomycin, etoposide, and cisplatin in metastatic non-small-cell lung cancer. J Clin Oncol. 1985;1 l: 1478-1485.
- 42. Paridaens R, Biganzoli L, Bruning P, et al. Paclitaxel versus doxorubicin as firstline single-agent chemotherapy for metastatic breast cancer: a European Organization for Research and Treatment of Cancer randomized study with cross-over. J Clin Oncol 2000;18(4):724-733.
- 43. Parkin DM, Pisani P, Ferlay J. 1999. Global cancer statistics. CA Cancer J Clin 49(1):33-64.
- 44.
Peters GJ, Bergman AM, Ruiz van Haperen VW, Veerman G, Kuiper CM, Braakhuis BJ.
1995. Interaction between cisplatin and gemcitabine in vitro and in vivo. Semin Oncol 22 (4 Suppl 11):72-79.
- 45.
Plunkett, et al. Increased cytotoxicity and therapeutic activity of 2',2' difluorodeoxycytidine
(dFdC) over cytosine arabinoside (araC) in L 1210 leukernia. Proc Am Assoc Cancer Res. 1988;29:352.
- 46. Poplin E, Thompson B, Whitacre M, Alsner J. Small cell carcinoma of the lung: influence of age on treatment outcome. Cancer Treat Reports. 1987;71:291-296.
- 47. Rapp E, Pater J, Willan A et al. Chemotherapy can prolong survival in patients with advanced non-small cell lung cancer: report of a Canadian multicenter randomized trial. J Clin Oncol 1988; 6: 633 - 641.
- 48. Rothenberg ML. New developments in chemoherapy for patients with advanced pancreatic cancer. Oncology 1996; 10(9 SUPPL.): 18-22.
- 49. Rothenberg ML, Abbruzzese JL, Moore M, Portenoy RK, Robertson JM, Wanebo HJ. A rationale for expanding the endpoints for clinical trials in advanced pancreatic carcinoma Cancer 1996; 78 (3SUPPL.) 627-632.
- 50.
Rothenberg ML, Moore MJ, Cripps MC, Anderseen JS, Portenoy RK, Burris HA, 3rd, Green
MR. Tarassoff PG, Brown TD, Casper ES, Storniolo A-M., Von Hoff DD. A phase II trial of gemcitabine in patients with 5-fu-refractory pancreas cancer. Ann Oncol 1996; 7(4): 347-353.
- 51. Ruckdeschel JC, Finkelstein DM, Ettinger DS et al. A randomised trial of the four most active regimens for metastatic non-small cell lung cancer. J Clin Oncol 1986; 4: 14 - 22.
- 52.
Sandler AB, Buzaid AC. Lung cancer: a review of current therapeutic modalities. Lung
1992; 170: 249 - 265.
- 53. Samet J, Hunt WC, Key C, Humble CG, Goodwin JS. Choice of cancer therapy varies with age of patient. JAAC. 1986; 255: 3385-3390.
- 54. Scagliotti GV, De Marinis F, Rinaldi M, et al. 2002. Phase III randomized trial comparing three platinum-based doublets in advanced non-small cell lung cancer. J Clin Oncol. 20: 4285-4291.
- 55.
Scher HI, Bahnson R, Cohen S, et al. 1998. NCCN urothelial cancer practice guidelines.
National Comprehensive Cancer Network. Oncology 12(7A):225-271.
- 56.
Schnall SF, Macdonald JS. Chemotherapy of adenocarcinoma of the pancreas. Semin Oncol.
1996; 23(2): 220-228.
- 57. Shewach DS, Lawrence TS. Radiosensitization of human solid tumor cell lines with gemcitabine. Semin Oncol 1996; 23 (5 SUPPL 10): 65-71.
- 58. Skarin A. Diagnosis in Oncology. Journal of Clinical Oncology 2000; 18(3):693-698.
- 59. Smith RE, Brown AM, Mamounas EP, et al. Randomized trial of 3-hour versus 24-hour infusion of high-dose paclitaxel in patients with metastatic or locally advanced breast cancer: NationalSurgical Adjuvant Breast and Bowel Project Protocol B-26. J Clin Oncol 1999;17(11):3403-3411.
- 60.
Sorensen JB. Prognosis and Prognostic Factors in Adenocarcinoma of the Lung. Kobenhavn:
Gemcitabine hydrochloride for injection Product Monograph Page 51 of 54 Laegeforeningens Forlag; 1992.
- 61.
Souhami RL and Law K. Longevity in small cell lung cancer. A report to the Lung Cancer
Subcommittee of the United Kingdom Coordinating Committee for Cancer Research. Br J Cancer 1990; 61: 584 - 589.
- 62.
Souquet PJ, Chauvin F, Boissel JP, Cellerino R, Cormier Y, Ganz PA, Kaasa S, Pater JL,
Quoix E, Rapp E, Tumarello D, Williams J, Woods BL, Bemard JP. Polychemotherapy in advanced non-small cell lung cancer: a meta-analysis. Lancet. 1993; 342: 19-21.
- 63.
Splinter TAW. Chemotherapy in advanced non-small cell lung cancer. Eur J Cancer 1990;
26: 1093 -1099.
- 64. Sternberg CN, Yagoda A, Scher HI, et al. 1989. Methotrexate, vinblastine, doxorubicin, and cisplatin for advanced transitional cell carcinoma of the urothelial: efficacy and patterns of response and relapse. Cancer 64(12):2448-2458.
- 65. Tempero M, Capadano M, Tarassoff P. Dose escalation of gemcitabine in previously untreated patients with pancreatic adenocarcinoma (meeting abstract). Proc Annu Meet Am Soc Clin Oncol 1994; 13: A660.
- 66.
Von Hoff DD. Gemcitabine: a case study for clinical benefit. Semin Oncol 1996; 23(5
SUPPL. 10): 1-2.
- 67.
Winer EP, Morrow M, Osborne CK, et al. Malignant tumours of the breast. In: DeVita VT Jr,
Hellman S, Rosenberg SA, editors. Cancer, principles & Practice of oncology. 6th ed. Philadelphia (PA): Lippincott Williams & Wilkins. 2001; P1651-1717.
- 68. World Health Organization. Handbook for reporting results of cancer treatment. WHO offset publications no. 48, Geneva 1979
- 69.
Product Monograph. GEMZAR (Gemcitabine Hydrochloride for Injection). Eli Lilly Canada.
Date of Revision: December 21, 2012; Control No.: 158714.