


Product Monograph - Cytarabine Injection BP
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intravenous infusion Subcutaneous injection Intrathecal injection | Solution for Injection 100mg / mL (100 mg / 1 mL, 500 mg / 5 mL, 1000 mg / 10 mL and 2000 mg / 20 mL) | Not applicable For a complete listing see DOSAGE FORMS, COMPOSITION and PACKAGING section. |
INDICATIONS AND CLINICAL USE
Cytarabine Injection BP (cytarabine) is indicated primarily for induction and maintenance of remission in acute leukemia in both adults and children.
It has been found useful in the treatment of acute myelocytic leukemia, chronic myelocytic leukemia (blast phase), acute lymphocytic leukemia and erythroleukemia. Cytarabine Injection BP may be used alone or in combination with other antineoplastic agents; the best results are obtained with combination therapy.
Children with non-Hodgkin's lymphoma have benefited from a combination drug program (LSA2L2) that included cytarabine.
Cytarabine has been used intrathecally in newly diagnosed children with acute lymphocytic leukemia as well as in the treatment of meningeal leukemia.
Cytarabine, in high dose 2-3 g/m2 as an IV infusion over 1-3 hours given every 12 hours for 2-6 days with or without additional cancer chemotherapeutic agents, has been shown to be effective in the treatment of poor-risk leukemia, refractory leukemia, and relapsed acute leukemia.
Remissions induced by cytarabine not followed by maintenance treatment have been brief.
CONTRAINDICATIONS
Cytarabine Injection BP is contraindicated in those patients who are hypersensitive to the drug.
Anaphylactic reactions have occurred with cytarabine treatment (see WARNINGS AND PRECAUTIONS, Sensitivity/Resistance).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
Cytarabine Injection BP should be prescribed only by physicians experienced with cancer therapy drugs. Patients should be monitored and blood counts as well as renal and hepatic function tests should be performed regularly (see WARNINGS AND PRECAUTIONS, Hematologic, Hepatic/Biliary/Pancreatic, Renal, Monitoring and Laboratory Tests and OVERDOSAGE).
Do not use a diluent that contains benzyl alcohol when giving to premature or low birth weight infants as benzyl alcohol has been associated with the “gasping syndrome” (see WARNINGS AND PRECAUTIONS, General and Special Populations, Pediatrics). Do not use a diluent that contains benzyl alcohol for high dose therapy or when using intrathecally (see ADVERSE REACTIONS, High Dose Therapy).
The following are clinically significant adverse events:
Cardiomyopathy with subsequent death (see WARNINGS AND PRECAUTIONS,
Cardiovascular and ADVERSE REACTIONS, High Dose Therapy).
GI toxicity, at times fatal (see WARNINGS AND PRECAUTIONS, Gastrointestinal and
ADVERSE REACTIONS, High Dose Therapy).
- Acute pancreatitis (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- CNS toxicity, severe neurological adverse reactions, paraplegia, necrotizing leukoencephalopathy and spinal cord toxicity. Patients with impaired hepatic or renal function may be at increased risk after high dose Cytarabine Injection BP (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Neurologic and Renal; ADVERSE REACTIONS, High Dose Therapy and Intrathecal Therapy; DRUG INTERACTIONS, Serious Interactions; DOSAGE AND ADMINISTRATION, Meningeal Leukemia – Intrathecal Use, OVERDOSAGE, and ACTION AND CLINICAL PHARMACOLOGY).
Infection (see WARNINGS AND PRECAUTIONS, Immune and ADVERSE
REACTIONS, Infections and Infestations).
Pulmonary toxicity, adult respiratory distress syndrome and pulmonary edema (see
WARNINGS AND PRECAUTIONS, Respiratory and ADVERSE REACTIONS, High Dose Therapy).
Myelosuppression (see WARNINGS AND PRECAUTIONS, Hematologic; ADVERSE
REACTIONS, Blood and Lymphatic System Disorders and OVERDOSAGE).
General
Before instituting a program of combined therapy, the physician should be familiar with the literature, adverse reactions, warnings and precautions, and contraindications applicable to all the
drugs in the program (see DOSAGE AND ADMINISTRATION, Combined Chemotherapy).
For induction therapy, patients should be treated in a facility with laboratory and supportive resources sufficient to monitor drug tolerance and protect and maintain a patient compromised by drug toxicity. The main toxic effect of Cytarabine Injection BP is bone marrow suppression with leukopenia, thrombocytopenia and anemia. Less serious toxicity includes nausea, vomiting, diarrhea and abdominal pain, oral ulceration, and hepatic dysfunction (see ADVERSE REACTIONS).
The physician must judge possible benefit to the patient against known toxic effects of this drug in considering the advisability of therapy with Cytarabine Injection BP. Before making this judgment or beginning treatment, the physician should be familiar with the following text.
When large intravenous doses are given quickly, patients are frequently nauseated and may vomit for several hours post injection. This problem tends to be less severe when the drug is infused.
High dose schedules: Do not further dilute Cytarabine Injection BP with diluents containing benzyl alcohol. Benzyl alcohol has been reported to be associated with a fatal "Gasping Syndrome" in pediatric patients. As premature and low birth weight infants may be at increased risk of developing this toxicity, they should not be given cytarabine when using a diluent containing benzyl alcohol (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
Carcinogenesis and Mutagenesis
Extensive chromosomal damage, including chromatoid breaks have been produced by cytarabine and malignant transformation of rodent cells in culture has been reported (see DETAILED PHARMACOLOGY).
Cardiovascular
High dose schedules: An increase in cardiomyopathy with subsequent death has been reported following experimental high dose cytarabine and cyclophosphamide therapy when used for bone marrow transplant preparation. This may be schedule dependent (see also DRUG INTERACTIONS).
Gastrointestinal
Abdominal tenderness (peritonitis) and typhlitis with concurrent neutropenia and thrombocytopenia have been reported in patients treated with conventional doses of cytarabine in combination with other drugs. Patients have responded to nonoperative medical management.
High dose schedule: Severe and at times fatal, GI toxicity (different from that seen with conventional therapy regimens of cytarabine) has been reported following high dose (2-3 g / m2) schedules of cytarabine). These reactions include severe gastrointestinal ulceration, including pneumatosis cystoides intestinalis, leading to peritonitis, bowel necrosis; and necrotizing colitis.
Genitourinary
Tumor Lysis Syndrome: Like other cytotoxic drugs, Cytarabine Injection BP may induce hyperuricemia secondary to rapid lysis of neoplastic cells. The clinician should monitor the patient's blood uric acid level and be prepared to use such supportive and pharmacologic measurements as might be necessary to control this problem.
Hematologic
Cytarabine Injection BP is a potent bone marrow suppressant; the severity depends on the dose of the drug and schedule of administration. Therapy should be started cautiously in patients with pre-existing drug-induced bone marrow suppression. Patients receiving this drug must be under close medical supervision and during induction therapy, should have leukocyte and platelet counts performed daily. Bone marrow examinations should be performed frequently after blasts have disappeared from the peripheral blood. Facilities should be available for management of complications (possibly fatal) of bone marrow suppression (infection resulting from granulocytopenia and other impaired body defenses, and hemorrhage secondary to thrombocytopenia). Periodic checks of bone marrow should be performed in patients receiving Cytarabine Injection BP.
Hepatic/Biliary/Pancreatic
The human liver may detoxify a substantial fraction of an administered cytarabine dose. In particular, patients with hepatic function impairment may have a higher likelihood of CNS toxicity after high dose treatment with Cytarabine Injection BP. Use the drug with caution and at reduced dose in patients whose liver function is poor.
Periodic checks of liver function should be performed in patients receiving Cytarabine Injection BP.
Pancreatitis: Acute pancreatitis has been reported to occur in patients being treated with cytarabine in combination with other drugs.
High dose schedules: Other reactions have been reported following high dose (2-3 g / m2) schedules of cytarabine and include sepsis and liver abscess, and liver damage with increased hyperbilirubinemia.
Immune
Immunosuppressant Effects/Increased Susceptibility to Infections: Administration of live or live-attenuated vaccines in patients immunocompromised by chemotherapeutic agents, including cytarabine, may result in serious or fatal infections. Vaccination with a live vaccine should be avoided in patients receiving cytarabine. Killed or inactivated vaccines may be administered; however, the response to such vaccines may be diminished.
Neurologic
High dose schedules: Severe and at times fatal, CNS toxicity (different from that seen with conventional therapy regimens of cytarabine) has been reported following high dose (2-3 g / m2) schedules of cytarabine. These reactions include cerebral and cerebellar dysfunction including personality changes, somnolence, convulsion and coma, usually reversible.
Delayed progressive ascending paralysis resulting in death has been reported in children with AML following intrathecal and intravenous cytarabine at conventional doses in combination with other drugs.
Cases of severe neurological adverse reactions that ranged from headache to paralysis, coma and stroke-like episodes have been reported mostly in pediatric patients given intravenous cytarabine in combination with intrathecal methotrexate.
Ophthalmologic
High dose schedules: The following reactions have been reported following high dose (2-3 g / m2) schedules of cytarabine: reversible corneal toxicity and hemorrhagic conjunctivitis, which may be prevented or diminished by prophylaxis with a local corticosteroid eye drop.
Renal
Patients with renal function impairment may have a higher likelihood of CNS toxicity after high dose treatment with Cytarabine Injection BP. Periodic checks of kidney function should be performed in patients receiving Cytarabine Injection BP.
Respiratory
High dose schedules: Severe and sometimes fatal pulmonary toxicity, adult respiratory distress syndrome and pulmonary edema have occurred following high dose schedules with cytarabine therapy. A syndrome of sudden respiratory distress, rapidly progressing to pulmonary edema and radiographically pronounced cardiomegaly has been reported following experimental high dose cytarabine therapy used for the treatment of relapsed leukemia.
Sensitivity/Resistance
Anaphylactic reactions have occurred with cytarabine treatment. Anaphylaxis that resulted in acute cardiopulmonary arrest and required resuscitation has been reported. This occurred immediately after the intravenous administration of cytarabine.
Sexual Function/Reproduction
Male Fertility: Cytarabine may present in the semen. Male patients who are not surgically sterile must agree to use effective contraception during treatment with Cytarabine Injection BP to prevent pregnancy in female partners (see WARNINGS AND PRECAUTIONS, Special Populations, Pregnant Women and TOXICOLOGY).
Skin
Palmar plantar erythrodysaesthesia: Palmar plantar erythrodysaesthesia (PPE) has occurred with cytarabine treatment in adults and children. Severe cytarabine associated PPE that resulted in treatment discontinuation has been reported.
High dose schedules: Rarely, severe skin rash, leading to desquamation has been reported. Complete alopecia is more commonly seen with high dose therapy than with standard cytarabine treatment programs.
Special Populations
Pregnant Women: Cytarabine is embryotoxic and teratogenic and produced peri- and postnatal toxicity in various species. Sperm head abnormalities were observed following cytarabine treatment in mice (see TOXICOLOGY).
There are no studies on the use of cytarabine in pregnant women. Use of this drug in women who are or who may become pregnant should be undertaken only after due consideration of potential benefit and potential hazard to both mother and child. Women of childbearing potential should be advised to avoid becoming pregnant (see also WARNINGS AND PRECAUTIONS, Sexual Function/Reproduction).
Normal infants have been born to mothers exposed to cytarabine during pregnancy (alone or in combination with other drugs); some of these infants were premature or of low birthweight. Some of the normal infants were followed up at ages ranging from six weeks to seven years following exposure, and showed no abnormalities. One apparently normal infant died at 80 days of gastroenteritis.
Congenital abnormalities have been reported, particularly when the fetus has been exposed to systemic therapy with cytarabine during the first trimester. These include upper and lower distal limb defects, and extremity and ear deformities.
Reports of pancytopenia, leucopenia, anemia, thrombocytopenia, electrolyte abnormalities, transient oesinophilia, increased IgM levels and hyperpyrexia, sepsis and death have occurred during the neonatal period to infants exposed to cytarabine in utero. Some of these infants were also premature.
Therapeutic abortions have been done in pregnant women on cytarabine. Normal fetuses have been reported while other reported fetal effects included enlarged spleen and Trisomy C chromosome abnormality in the chorionic tissue.
Because of the potential for abnormalities with cytotoxic therapy, particularly during the first trimester, a patient who is or who becomes pregnant while on Cytarabine Injection BP should be apprised of the potential risk to the fetus and the advisability of pregnancy continuation. There is a definite, but considerably reduced risk if therapy is initiated during the second or third trimester. Although normal infants have been delivered to patients treated in all three trimesters of pregnancy, follow-up of such infants would be advisable.
Do not further dilute Cytarabine Injection BP with diluents containing benzyl alcohol. Benzyl alcohol can cross the placenta (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
Nursing Women: It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants from cytarabine, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
Pediatrics: The safety of this drug for use in infants (under 1 year of age) is not established.
Gasping Syndrome: Cytarabine Injection BP should not be given to premature and low birth weight infants when using a diluent that contains benzyl alcohol. The preservative benzyl alcohol has been associated with serious adverse events, including the “gasping syndrome”, and death in pediatric patients. Symptoms of gasping syndrome may include metabolic acidosis, seizure, bradycardia, gasping respiration and cardiovascular collapse. Although normal therapeutic doses of this product ordinarily deliver amounts of benzyl alcohol that are substantially lower than those reported in association with the “gasping syndrome”, the minimum amount of benzyl alcohol at which toxicity may occur is not known. The risk of benzyl alcohol toxicity depends on the quantity administered and the hepatic capacity to detoxify the chemical. Premature and low-birth weight infants may be more likely to develop toxicity. If Cytarabine Injection BP is used in high dose or intrathecal therapy, do not further dilute with benzyl alcohol. The preservative-free 0.9% sodium chloride can be used for dilution (see also SERIOUS WARNINGS AND PRECAUTIONS).
See also WARNINGS AND PRECAUTIONS, Neurologic and Skin.
Monitoring and Laboratory Tests
Patients receiving Cytarabine Injection BP must be monitored closely. Frequent platelet and leukocyte counts and bone marrow examinations are mandatory. Consider suspending or modifying therapy when drug-induced marrow depression has resulted in a platelet count under 50,000 or a polymorphonuclear granulocyte count under 1000 / mm3. Counts of formed elements in the peripheral blood may continue to fall after the drug is stopped and reach lowest values after drug-free intervals of 12 of 24 days. When indicated, restart therapy when definite signs of marrow recovery appear (on successive bone marrow studies). Patients whose drug is withheld until "normal" peripheral blood values are attained, may escape from control.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The following listing is based on adverse events reported in clinical trials and/or spontaneous adverse event reports from post-marketing experience. When a frequency cannot be estimated from the available data it is classified as “not known”.
Blood and Lymphatic System Disorders
Because Cytarabine Injection BP is a bone marrow suppressant, anemia, leukopenia, thrombocytopenia, megaloblastosis, and reduced reticulocytes can be expected as a result of its administration. The severity of these reactions is dose and schedule dependent. Cellular changes in the morphology of bone marrows and peripheral smears can be expected.
Following 5-day constant infusions or acute injections of 50 mg / m2 to 600 mg / m2, white cell depression follows a biphasic course. Regardless of initial count, dosage level, or schedule, there is an initial fall starting the first 24 hours with a nadir at days 7 to 9. This is followed by a brief rise which peaks around the twelfth day. A second and deeper fall reaches nadir at days 15 to
- 24. Then there is a rapid rise to above baseline in the next 10 days. Platelet depression is noticeable at 5 days with a peak depression occurring between days 12 to 15. Thereupon, a rapid rise to above baseline occurs in the next 10 days.
Infections and Infestations
Viral, bacterial, fungal, parasitic, or saprophytic infections, in any location on the body, may be associated with the use of Cytarabine Injection BP alone or in combination with other immunosuppressive agents following immunosuppressive doses that affect cellular or humoral immunity. These infections may be mild, but can be severe and at times fatal.
Musculoskeletal and Connective Tissue Disorders
The Cytarabine Syndrome
A cytarabine syndrome has been described by Castleberry et al. 1981. It is characterized by fever, myalgia, bone pain, occasionally chest pain, maculopapular rash, conjunctivitis and malaise. It usually occurs 6 to 12 hours following drug administration. Corticosteroids have been shown to be beneficial in treating or preventing this syndrome. If the symptoms of the syndrome are deemed treatable, corticosteroids should be contemplated as well as continuation of therapy with Cytarabine Injection BP.
Other Adverse Reactions
Conventional Dose Therapy
Nausea and vomiting are most frequent following rapid intravenous injection.
Table 1 – Frequencies of Adverse Reactions with Cytarabine Conventional Dose Therapy
The reported adverse reactions are listed below by MedDRA System Organ Class and by frequency.
ADR frequencies are based on CIOMS convention: Very common (>10%), Common (>1%, ≤10%), Uncommon (>0.1%, ≤1%), Rare (>0.01%, ≤0.1%), and Frequency not known (cannot be estimated from available data).
| Blood and Lymphatic System Disorders: | |
| Very common | Bone marrow failure, thrombocytopenia, anaemia, anaemia megaloblastic, leukopenia, reticulocyte count decreased |
| Frequency not known | Bleeding (all sites) |
| Cardiac Disorders: | |
| Frequency not known | Pericarditis |
| Eye Disorders: | |
| Frequency not known | Conjunctivitisa |
| Gastrointestinal Disorders: | |
| Very common | Stomatitis, mouth ulceration, anal ulcer, anal inflammation, diarrhoea, vomiting, nausea, abdominal pain |
| Frequency not known | Bowel necrosis, Pancreatitis, oesophageal ulcer, oesophagitis |
| General Disorders and Administration Site Conditions: | |
| Very common | Pyrexia |
| Frequency not known | Chest pain, injection site reactionb |
| Hepatobiliary Disorders: | |
| Very common | Hepatic function abnormal |
| Frequency not known | Jaundice |
| Immune System Disorders: | |
| Frequency not known | Anaphylactic reaction, allergic oedema |
| Infections and Infestations: | |
| Very common | Sepsis, pneumonia, infectionc |
| Frequency not known | Injection site cellulitis |
| Investigations: | |
| Very common | Biopsy bone marrow abnormal, blood smear test abnormal |
| Metabolism and Nutrition Disorders: | |
| Frequency not known | Decreased appetite |
| Musculoskeletal, Connective Tissue and Bone Disorders: | |
| Very common | Cytarabine syndrome |
| Nervous System Disorders: | |
| Frequency not known | Neurotoxicity, neuritis, dizziness, headache |
| Renal and Urinary Disorders: | |
| Frequency not known | Renal impairment, urinary retention |
| Respiratory, Thoracic and Mediastinal Disorders: | |
| Frequency not known | Dyspnea, oropharyngeal pain |
| Skin and Subcutaneous Tissue Disorders: | |
| Very common | Alopecia, rash |
| Common | Skin ulcer |
| Frequency not known | Palmar-plantar erythrodysaesthesia syndrome, urticaria, pruritus, freckling |
| Vascular Disorders: | |
| Frequency not known | Thrombophlebitis |
a May occur with rash and may be hemorrhagic with high dose therapy.
b Pain and inflammation at subcutaneous injection site.
c May be mild, but can be severe and at times fatal.
High Dose Therapy
Severe and at times fatal CNS, GI and pulmonary toxicity (different from that seen with conventional therapy regimens of cytarabine) has been reported following high dose schedules (2.0 g to 3.0 g / m2 given every 12 hours for 12 doses).
Table 2 – Frequencies of Adverse Reactions with Cytarabine High Dose Therapy
The reported adverse reactions are listed below by MedDRA System Organ Class and by frequency.
ADR frequencies are based on CIOMS convention: Very common (>10%), Common (>1%, ≤10%), Uncommon (>0.1%, ≤1%), Rare (>0.01%, ≤0.1%), and Frequency not known (cannot be estimated from available data).
| Cardiac Disorders: | |
| Frequency not known | Cardiomyopathya |
| Eye Disorders: | |
| Very common | Corneal disorder |
| Frequency not known | hemorrhagic conjunctivitisb |
| Gastrointestinal Disorders: | |
| Common | Necrotising colitis |
| Frequency not known | Gastrointestinal necrosis, gastrointestinal ulcer, pneumatosis intestinalis, peritonitis |
| Hepatobiliary Disorders: | |
| Frequency not known | Liver injury, hyperbilirubinaemia |
| Infections and Infestations: | |
| Very common | Sepsis |
| Frequency not known | Liver abscess |
| Nervous System Disorders: | |
| Very common | Cerebral disorder, cerebellar disorder, somnolence |
| Frequency not known | Coma, convulsion, peripheral motor neuropathy, peripheral sensory neuropathy |
| Psychiatric Disorders: | |
| Frequency not known | Personality changec |
| Respiratory, Thoracic and Mediastinal Disorders: | |
| Very common | Acute respiratory distress syndrome, pulmonary oedema |
| Skin and Subcutaneous Tissue Disorders: | |
| Common | Skin exfoliation |
a With subsequent death.
b May be prevented or diminished by prophylaxis with a local corticosteroid eyedrop. c Personality change was reported in association with cerebral and cerebellar dysfunction.
Peripheral motor and sensory neuropathies after consolidation with high-dose cytarabine, daunorubicin, and asparaginase have occurred in adult patients with acute non lymphocytic leukemia. Patients treated with high-dose Cytarabine Injection BP should be observed for neuropathy since dose schedule alterations may be needed to avoid irreversible neurologic disorders.
Corneal toxicity consisting of ocular pain, tearing, foreign-body sensation, photophobia and blurred vision has been reported.
Rarely, severe skin rash, leading to desquamation has been reported. Complete alopecia is more commonly seen with high dose therapy than with standard cytarabine treatment programs.
Do not further dilute Cytarabine Injection BP with diluents containing benzyl alcohol.
Intermediate Dose Therapy
A diffuse interstitial pneumonitis without clear cause that may have been related to cytarabine was reported in patients treated with experimental intermediate doses of cytarabine (1 gm / m2)
with and without other chemotherapeutic agents (meta-AMSA, daunorubicin, VP-16).
Intrathecal Therapy
Cytarabine Injection BP given intrathecally may cause systemic toxicity and careful monitoring of the hemopoietic system is indicated. Modification of other anti-leukemia therapy may be necessary. Major toxicity is rare. The most frequently reported reactions after intrathecal administration were nausea, vomiting and fever; these reactions are mild and self-limiting. Paraplegia has been reported. Necrotizing leukoencephalopathy with or without convulsion has been reported; in some cases, patients had also been treated with intrathecal methotrexate and/or hydrocortisone, as well as by central nervous system radiation. Isolated neurotoxicity has been reported. Blindness occurred in two patients in remission whose treatment had consisted of combination systemic chemotherapy, prophylactic central nervous system radiation and intrathecal cytarabine. When Cytarabine Injection BP is administered both intrathecally and intravenously within a few days, there is an increased risk of spinal cord toxicity, however, in serious life-threatening disease, concurrent use of intravenous and intrathecal Cytarabine Injection BP is left to the discretion of the treating physician.
DRUG INTERACTIONS
Serious Drug Interactions
Methotrexate: Intravenous cytarabine given concomitantly with intrathecal methotrexate may increase the risk of severe neurological adverse reactions such as headache, paralysis, coma and stroke-like episodes.
Drug-Drug Interactions
Digoxin: Reversible decreases in steady-state plasma digoxin concentrations and renal glycoside excretion were observed in patients receiving beta-acetyldigoxin and chemotherapy regimens containing cyclophosphamide, vincristine and prednisone with or without cytarabine or procarbazine. Steady-state plasma digitoxin concentrations did not appear to change. Therefore, monitoring of plasma digoxin levels may be indicated in patients receiving similar combination chemotherapy regimens. The utilization of digitoxin for such patients may be considered as an alternative.
Gentamicin: An in vitro interaction study between gentamicin and cytarabine showed a cytarabine related antagonism for the susceptibility of K. pneumoniae strains. This study suggests that in patients on cytarabine being treated with gentamicin for a K. pneumoniae infection, the lack of a prompt therapeutic response may indicate the need for re-evaluation of antibacterial therapy.
Fluorocytosine: Clinical evidence showed possible inhibition of fluorocytosine efficacy therapy with cytarabine. This may be due to potential competitive inhibition of its uptake.
Experimental high dose cytarabine and cyclophosphamide therapy: An increase in cardiomyopathy with subsequent death has been reported when used for bone marrow transplant
preparation. This may be schedule dependent (see WARNINGS AND PRECAUTIONS, Cardiovascular).
Drug-Food Interaction
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal product have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Interactions associated with lifestyle have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Clinical experience accumulated to date suggests that success with cytarabine is dependent more on adeptness in modifying day-to-day dosage to obtain maximum leukemic cell kill with tolerable toxicity than on the basic treatment schedule chosen at the outset of therapy. Toxicity necessitating dosage alteration almost always occurs.
In many chemotherapeutic programs, Cytarabine Injection BP is used in combination with other cytotoxic drugs. The addition of these cytotoxic drugs has necessitated changes and dose alterations. The dosage schedules for combination therapy outlined below have been reported in the literature (see REFERENCES).
Recommended Dose and Dosage Adjustment
Acute myelocytic leukemia - induction remission: adults
Cytarabine Injection BP 200 mg / m2 daily by continuous infusion for 5 days (120 hours) - total dose 1000 mg / m2. This course is repeated approximately every 2 weeks. Modifications must be made based on hematologic response.
Acute myelocytic leukemia - maintenance: adults
Maintenance programs are modifications of induction programs and, in general, use similar schedules of drug therapy as were used during induction. Most programs have a greater time spacing between courses of therapy during remission maintenance.
Acute myelocytic leukemia - induction and maintenance in children
Numerous studies have shown that childhood AML responds better than adult AML given similar regimens. Where the adult dosage is stated in terms of body weight or surface area, the children's dosage may be calculated on the same basis. When specified amounts of a drug are indicated for the adult dosage, these should be adjusted for children on the basis of such factors as age, body weight or body surface area.
Acute myelocytic leukemia – adults and children
The following tables outline the results of treatment with cytarabine alone and in combination with other chemotherapeutic agents, in the treatment of acute myelocytic leukemia in adults and children.
The treatment regimens outlined in the tables should not be compared for efficacy. These were independent studies with a number of variables involved, such as patient population, duration of disease, and previous treatment.
The responsiveness and course of childhood acute myelocytic leukemia (AML) appear to be different from that in adults. Numerous studies show response rates to be higher in children than in adults with similar treatment schedules. Experience indicates that at least with induction and initial drug responsiveness, childhood AML appears to be more similar to childhood acute lymphocytic leukemia (ALL) than to its adult variant.
Patients with hepatic impairment: Cytarabine and dose adjustment has not been studied in individuals with hepatic impairment (see also WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Patients with renal impairment: Cytarabine and dose adjustment has not been studied in individuals with renal impairment (see also WARNINGS AND PRECAUTIONS, Renal).
Table I: Acute Myelocytic Leukemia - Remission Induction: Adults
| Drug Dosage Schedule* | No. of Patients Evaluated | Complete Remissions | Investigators | |
| Cytarabine Single-Dose Therapy | (Infusion) 10 mg / m2 12 hrs/day 30 mg / m2 12 hrs/day 10 mg / m2 24 hrs/day 30 mg / m2 24 hrs/day (Infusion) 200 mg / m2 24 hrs/5 days | 12 41 9 36 36 | 2 (17%) 10 (24%) 2 (22%) 2 (6%) 9 (25%) | Ellison (1968) Bodey (1969) |
| 10 mg / m2 IV injection initially, then infusions of 30 mg/m2 per 12 hrs or 60 mg/m2/day for 4 days | 49 | 21 (43%) | Goodell (1970) | |
(Infusion Therapy) 800 mg / m2 / 2 days 1000 mg / m2 / 5 days | 53 60 | 12 (23%) 24 (40%) | Southwest Oncology Group.(1974) | |
| 100 mg / m2 /day 1 hr infusion | 49 | 7 (14%) | Carey (1975) | |
| Drug Dosage Schedule* | No. of Patients Evaluated | Complete Remissions | Investigators | |
| 5-12.5 mg /kg / 12 hr infusion following IV synchronizing dose** | 5 | 5 (100%) | Lampkin (1976) | |
| Combined Therapy | Cytarabine – doxorubicin | 41 | 30 (73%) | Preisler (1979) |
Cytarabine - thioguanine daunorubicin | 28 | 22 (79%) | Gale (1977) | |
Cytarabine - doxorubicin vincristine – prednisolone | 35 | 23 (66%) | Weinstein (1980) | |
Cytarabine - daunorubicin thioguanine – prednisone vincristine | 139 | 84 (60%) | Glucksberg (1981) | |
| Cytarabine – daunorubicin | 21 | 14 (67%) | Cassileth (1977) | |
| High Dose Therapy | Cytarabine | 7 | 6 (86%) | Lister (1983) |
| Cytarabine | 21 | 12 (57%) | Herzig (1983) | |
| Cytarabine | 11 | 8 (73%) | Preisler (1983) | |
| Cytarabine - doxorubicin | 14 | 7 (50%) | Willemze (1982) | |
| Cytarabine - asparaginase | 13 | 9 (69%) | Capizzi (1983) | |
* Unless otherwise stated, all doses given until drug effect-modifications then based on hematologic reasons.
See references.
** Highly experimental - requires ability to study mitotic indices.
Table II: Acute Myelocytic Leukemia - Remission Induction: Children (21 and under)
| Drug Therapy | No. of Patients Evaluated | Complete Remissions | Investigator |
| Cytarabine (5-12.5 mg / kg following IV synchronizing dose**) | 16 | 12 (75%) | Lampkin (1976) |
| Cytarabine, vincristine, doxorubicin, prednisolone | 48 | 35 (73%) | Weinstein (1980) |
| Cytarabine, thioguanine, doxorubicin | 11 | 8 (72%) | Hagbin (1975) |
| Cytarabine, thioguanine | 47 | 20 (43%) | Pizzo (1976) |
| Cytarabine, cyclophosphamide | 12 | 7 (58%) | Pizzo (1976) |
** Highly experimental - requires ability to study mitotic indices.
Acute lymphocytic leukemia
In general, dosage schedules are similar to those used in acute myelocytic leukemia with some modification. Cytarabine has been used in the treatment of acute lymphocytic leukemia in both adults and children. When cytarabine was used with other antineoplastic agents as part of a total therapy program, results were equal to or better than reported with such programs which did not include cytarabine. Used singly, or in combination with other agents, cytarabine has also been effective in treating patients who had relapsed on other therapy. Table III and IV summarize the results obtained in previously treated patients. Since these are independent studies with such variables as patient population, duration of disease and previous treatment, results shown should not be used for comparing the efficacy of the outlined treatment programs.
Table III: Acute Lymphocytic Leukemia - Remission Induction Previously Treatment Patients Adults and Children
| Drug Therapy | No. of Patients Evaluated | Complete Remissions | Response | Investigator |
| Cytarabine 3-5 mg / kg / day (IV injection) | 43 | 2 (5%) | 15 (35%) | Howard (1968) |
| Cytarabine - asparaginase | 9 | 8 (89%) | 8 (89%) | McElwain (1969) |
| Cytarabine - cyclophosphamide | 11 | 7 (64%) | 9 (82%) | Bodey 1970 |
| Cytarabine - prednisone | 83 | - | (49%) | Nesbitt (1970) |
Cytarabine 150-200 mg / m2 / 5 days (infusion) | 34 | 1 (3%) | 4 (12%) | Wang (1970) |
| Cytarabine - L - asparaginase - prednisone - vincristine - doxorubicin | 91 | 72 (79%) | - | Klemperer (1978) |
| Cytarabine - L - asparaginase - prednisone - vincristine - doxorubicin | 55 | 42 (76%) | - | Klemperer (1978) |
| Cytarabine - asparaginase | 22 | 13 (59%) | 15 (68%) | Ortaga (1972) |
| Cytarabine - thioguanine | 19 | 9 (47%) | 9 (47%) | Bryan (1974) |
Table IV
| Drug Therapy | No. of Patients Evaluated | Complete Remissions | Investigator | |
| High Dose Therapy | Cytarabine | 8 | 3 (38%) | Rohatinar (1983) |
| Cytarabine - doxorubicin | 3 | 2 (67%) | Willemze (1982) | |
| Cytarabine - asparaginase | 10 | 3 (30%) | Capizzi (1983) | |
Non-Hodgkin's lymphoma in children
Cytarabine has been used as part of multi-drug program (LSA2L2) to treat non-Hodgkin's lymphoma in children. See Appendix A for complete dosage schedule.
High Dose Chemotherapy
Before instituting a program of high dose chemotherapy, the physician should be familiar with the literature, adverse reactions, precautions, contraindications, and warnings applicable to all the drugs involved in the program.
Cytarabine Injection BP
Cytarabine Injection BP: 2 g / m2 infused over 3 hours every 12 hours x 12 doses (Days 1-6).
Cytarabine Injection BP
Cytarabine Injection BP: 3 g / m2 infused over 1 hour every 12 hours x 12 doses (Days 1-6).
Cytarabine Injection BP
Cytarabine Injection BP: 3 g / m2 infused over 75 minutes every 12 hours x 12 doses (Days 1-6).
Cytarabine Injection BP - doxorubicin
Cytarabine Injection BP: 3 g / m2 infused over 2 hours every 12 hours x 12 doses (Days 1-6).
Doxorubicin: 30 mg / m2 IV on Days 6-7.
Cytarabine Injection BP - asparaginase
Cytarabine Injection BP: 3 g / m2 infused over 3 hours at 0 hours, 12 hours, 24 hours, and 36 hours. At 42 hours, 6000 units / m2 of asparaginase IM (Days 1-2); repeat same schedule Days 8-9.
Combined Chemotherapy
Before instituting a program of combined chemotherapy, the physician should be familiar with the literature, adverse reactions, precautions, contraindications, and warnings applicable to all the drugs involved in the program.
Cytarabine Injection BP, doxorubicin
Cytarabine Injection BP: 100 mg / m2 / day, continuous IV infusion (Days 1-10) Doxorubicin: 30 mg / m2 / day, IV infusion of 30 minutes (Days 1-3)
Additional (complete or modified) courses as necessary at 2-4 week intervals if leukemia is persistent.
Cytarabine Injection BP, thioguanine, daunorubicin
Cytarabine Injection BP: 100 mg / m2, IV infusion over 30 minutes every 12 hours (Days 1-7). Thioguanine: 100 mg / m2, orally every 12 hours (Days 1-7).
Daunorubicin: 60 mg / m2/day, IV infusion (Days 5-7).
Additional (complete or modified) courses as necessary at 2-4 week intervals if leukemia is persistent.
Cytarabine Injection BP, doxorubicin, vincristine, prednisone
Cytarabine Injection BP: 100 mg / m2 / day, continuous IV infusion (Days 1-7). Doxorubicin: 30 mg / m2 / day, IV infusion (Days 1-3).
Vincristine: 1.5 mg / m2 /day, IV infusion (Days 1, 5)
Prednisolone: 40 mg / m2 / day, IV infusion every 12 hours (Days 1-5).
Additional (complete or modified) courses as necessary at 2-4 week intervals if leukemia is persistent.
Cytarabine Injection BP, daunorubicin, thioguanine, prednisone, vincristine
Cytarabine Injection BP: 100 mg / m2 / day, IV infusion (Days 1-10). Daunorubicin: 70 mg / m2 / day, IV infusion (Days 1-3).
Thioguanine: 100 mg / m2, orally every 12 hours (Days 1-7).
Prednisone: 40 mg / m2 / day, orally (Days 1-7).
Vincristine: 1 mg / m2 / day, IV infusion (Days 1, 7)
Additional (complete or modified) courses as necessary at 2-4 week intervals if leukemia is persistent.
Cytarabine Injection BP, daunorubicin
Cytarabine Injection BP: 100 mg / m2 / day, continuous IV infusion (Days 1-7). Daunorubicin: 45 mg / m2 / day, IV. push (Days 1-3).
Additional (complete or modified) courses as necessary at 2-4 week intervals if leukemia is persistent.
Meningeal Leukemia - Intrathecal Use
Cytarabine has been used intrathecally in acute leukemia in doses ranging from 5 mg / m2 to 75 mg / m2 of body surface area. The frequency of administration varied from once a day for 4 days to once every 4 days. The most frequently used dose was 30 mg / m2 every 4 days until cerebrospinal fluid findings were normal, followed by one additional treatment. The dosage schedule is usually governed by the type and severity of central nervous system manifestations and the response to previous therapy.
Cytarabine has been used intrathecally with hydrocortisone sodium succinate and methotrexate, both as prophylaxis in newly diagnosed children with acute lymphocytic leukemia, as well as in the treatment of meningeal leukemia. Sullivan et al. has reported that prophylactic triple therapy has prevented late CNS disease and given overall cure and survival rates similar to those seen in patients in whom CNS radiation and intrathecal methotrexate was used as initial CNS prophylaxis. The dose of cytarabine was 30 mg / m2, hydrocortisone sodium succinate 15 mg / m2, and methotrexate 15 mg / m2 (an absolute maximum single dose of 15 mg of methotrexate). The physician should be aware of this regimen and note that methotrexate dosage in pediatric patients is otherwise based on age rather than body surface area. Prescribers should consult related Product Monographs for more information.
Prophylactic triple therapy following the successful treatment of the acute meningeal episode may be useful. The physician should familiarize himself with the current literature before instituting such a program.
Cytarabine Injection BP given intrathecally may cause systemic toxicity and careful monitoring of the hemopoietic system is indicated. Modification of the anti-leukemia therapy may be necessary. Major toxicity is rare. The most frequently reported reactions after intrathecal administration were nausea, vomiting and fever; these reactions are mild and self-limiting. Paraplegia has been reported. Necrotizing leukoencephalopathy occurred in 5 children; these patients had also been treated with intrathecal methotrexate and hydrocortisone, as well as by central nervous system radiation. Isolated neurotoxicity has been reported.
Blindness occurred in two patients in remission whose treatment had consisted of combination systemic chemotherapy, prophylactic central nervous system radiation and intrathecal cytarabine.
Focal leukemic involvement of the central nervous system may not respond to intrathecal Cytarabine Injection BP and may better be treated with radiotherapy.
If used intrathecally, dilute with preservative free saline and use immediately. Do not further dilute Cytarabine Injection BP with diluents containing benzyl alcohol.
Dosage Modification
The dosage of Cytarabine Injection BP must be modified or suspended when signs of serious hematologic depression appear. In general, consider discontinuing the drug if the patient has less than 50000 platelets or 1000 polymorphonuclear granulocytes/mm3 in his peripheral blood. These guidelines may be modified depending on signs of toxicity in other systems and on the rapidity of fall in formed blood elements. Restart the drug when there are signs of marrow recovery and the above platelet and granulocyte levels have been attained. Withholding therapy until the patient's blood values are normal may result in escape of the patient's disease from control by the drug.
Hepatic Insufficiency: Use cytarabine with caution or possibly at reduced doses in patients whose liver function is poor (see also WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Renal Insufficiency: Use cytarabine with caution or possibly at reduced doses in patients whose kidney function is poor (see also WARNINGS AND PRECAUTIONS, Renal).
Administration
Cytarabine is not active orally. The schedule and method of administration varies with the program of therapy to be used. Cytarabine Injection BP may be given by intravenous infusion, injection/subcutaneously or intrathecally. When preparing cytarabine for intravenous high dose therapy or intrathecal use, do not further dilute with benzyl alcohol (see SERIOUS WARNINGS AND PRECAUTIONS). It is recommended that Cytarabine Injection BP be diluted with preservative-free 0.9% sodium chloride for injection and used immediately.
Thrombophlebitis has occurred at the site of drug injection or infusion in some patients, and rarely patients have noted pain and inflammation at subcutaneous injection sites. In most instances, however, the drug has been well tolerated.
Patients can tolerate higher total doses when they receive the drug by rapid intravenous injection as compared with slow infusion. This phenomenon is related to the drug's rapid inactivation and brief exposure of susceptible normal and neoplastic cells to significant levels after rapid injection. Normal and neoplastic cells seem to respond to somewhat parallel fashion to these different modes of administration and no clear-cut clinical advantage has been demonstrated for either.
Relatively constant plasma levels can be achieved by continuous intravenous infusion.
FOR INTRATHECAL USE: DO NOT USE DILUENT CONTAINING BENZYL ALCOHOL. DILUTE WITH PRESERVATIVE-FREE 0.9% SODIUM CHLORIDE FOR INJECTION. USE IMMEDIATELY.
FOR HIGH DOSE USE: DO NOT FURTHER DILUTE CYTARABINE INJECTION BP WITH DILUENTS CONTAINING BENZYL ALCOHOL.
OVERDOSAGE
There is no antidote for Cytarabine Injection BP overdosage.
Discontinuation of the drug and supportive therapy are of course indicated. Transfusions of platelets should be given if there is any sign of hemorrhage. Patients should be carefully observed for intercurrent infection and if such appears they should be rapidly and rigorously treated with appropriate antibiotic therapy.
Chronic overdosage may cause serious bone marrow suppression. Daily hematological evaluation should be performed to prevent overdosage. Nausea and vomiting, although a general side effect of the drug, may be an additional warning of overdosage. Severe hemorrhage into the gastrointestinal tract may indicate overdosage as may severe generalized infections.
Doses exceeding recommended dosage schedules have been used clinically and have been tolerated. The major toxicity with the use of 3 g / m2 intravenous infusion over 1 hour every 12 hours for 12 doses and 3 g / m2 continuous infusion for 4 days, other than reversible bone marrow suppression has been reversible corneal, cerebral and cerebellar dysfunction. Doses of 4.5 g / m2 intravenous infusion over 1 hour every 12 hours for 12 doses has caused an unacceptable increase in irreversible CNS toxicity and death.
For management of a suspected drug overdose, contact your regional Poison Control Centre immediately.
ACTION AND CLINICAL PHARMACOLOGY
Pharmacodynamics
Cytarabine is capable of obliterating immune responses in man during administration. Suppression of antibody responses to E-coli-VI antigen and tetanus toxoid has been demonstrated. This suppression was obtained during both primary and secondary antibody responses.
Cytarabine also suppressed the development of cell-mediated immune responses such as delayed hypersensitivity skin reaction to dinitrochlorobenzene. However, it has no effect on already established delayed hypersensitivity reactions.
Following 5-day courses of intensive therapy with cytarabine the immune response was suppressed, as indicated by the following parameters: macrophage ingress into skin windows; circulating antibody response following primary antigenic stimulation; lymphocyte blastogenesis with phytohemagglutinin. A few days after termination of therapy there was a rapid return to normal.
Pharmacokinetics
Absorption:
Cytarabine is rapidly metabolized and is not effective orally; less than 20% of the orally administered dose is absorbed from the gastrointestinal tract.
After subcutaneous or intramuscular administration of cytarabine, peak plasma levels of radioactivity are achieved about 20 to 60 minutes after injection and are considerably lower than those after intravenous administration.
Distribution:
Cerebrospinal fluid levels of cytarabine are low in comparison to plasma levels after single intravenous injection. However, in one patient in whom cerebrospinal levels were examined after 2 hours of constant intravenous infusion, levels approached 40% of the steady state plasma level. With intrathecal administration, levels of cytarabine in the cerebrospinal fluid declined with a first order half-life of about 2 hours. Because cerebrospinal fluid levels of deaminase are low, little conversion to ara-U was observed.
Metabolism:
Cytarabine is metabolized by deoxycytidine kinase and other nucleotide kinases to the nucleotide triphosphate, an effective inhibitor of DNA polymerase; it is inactivated by pyrimidine nucleoside deaminase which converts it to the non-toxic uracil derivative. It appears that the balance of kinase and deaminase levels may be an important factor in determining sensitivity or resistance of the cell to cytarabine.
Excretion:
Following rapid intravenous injection of cytarabine, the disappearance from plasma is biphasic. There is an initial distributive phase with a half-life of about 10 minutes, followed by a second elimination phase with a half-life of about 1 to 3 hours. After the distributive phase, over 80% of plasma radioactivity can be accounted for by the inactive metabolite
1-β-D-arabinofuranosyluracid (ara-U). Within 24 hours about 80% of the administered radioactivity can be recovered in the urine, approximately 90% of which is excreted as ara-U.
Special Populations and Conditions
Hepatic Insufficiency: Use cytarabine with caution or possibly at reduced doses in patients whose liver function is poor (see WARNINGS AND PRECAUTIONS,
Hepatic/Biliary/Pancreatic and DOSAGE AND ADMINISTRATION).
Renal Insufficiency: Use cytarabine with caution or possibly at reduced doses in patients whose kidney function is poor (see WARNINGS AND PRECAUTIONS, Renal and DOSAGE AND ADMINISTRATION).
STORAGE AND STABILITY
Stability and Storage Recommendations
Store between 15°C and 25°C. Protect from light.
Chemical Stability and Compatibility
In-use Stability
Cytarabine Injection BP solution is stable after the vial has been punctured for 24 hours when stored at ambient temperature (15°C – 25°C) and for 48 hours when stored at refrigerated conditions (2°C - 8°C).
Stability in Infusion Solutions
Chemical and physical stability studies of Cytarabine Injection BP have demonstrated that cytarabine is stable for seven days at room temperature or at 2°C - 8°C when admixed at 0.1 mg / mL in plastic IV bags with: 5% Dextrose injection; 0.9% Sodium Chloride injection and Lactated Ringer’s Injection solutions.
Also when similarly admixed at 32.5 mg / mL in plastic IV bags, cytarabine is stable for seven days at room temperature or at 2°C - 8°C in 0.9% Sodium Chloride Injection Solution.
Drug Incompatibilities
Cytarabine has been known to be physically incompatible with heparin, insulin, 5-fluorouracil, penicillin G, and methylprednisolone sodium succinate.
AS WITH ALL INTRAVENOUS ADMIXTURES, DILUTION SHOULD BE MADE JUST PRIOR TO ADMINISTRATION AND THE RESULTING UNPRESERVED SOLUTION USED WITHIN 24 HOURS.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discoloration and leakage prior to administration whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discoloration or leakage should not be used.
SPECIAL HANDLING INSTRUCTIONS
CAUTION
The following precautionary measures are recommended in proceeding with the preparation and handling of cytotoxic agents such as Cytarabine Injection BP.
- 1.
The procedure should be carried out in a vertical laminar flow hood (Biological Safety
Cabinet - Class II).
- 2. Personnel should wear: PVC gloves, safety glasses, disposable gowns and masks.
- 3.
All needles, syringes, vials, and other materials which have come in contact with
Cytarabine Injection BP should be segregated and destroyed by incineration (sealed
containers may explode). If incineration is not available, neutralization should be carried out using 5% sodium hypochlorite, or 5% sodium thiosulfate.
- 4. Personnel regularly involved in the preparation and handling of Cytarabine Injection BP should have bi-annual haematologic examinations.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each mL of sterile unpreserved solution of Cytarabine Injection BP contains 100 mg of cytarabine in water for injection. Hydrochloric acid solution and/or sodium hydroxide solution is added to adjust the pH. pH of the solution is approximately 8.
Cytarabine Injection BP is supplied in single use vials of 100 mg / 1 mL (5 vials per box), 500 mg / 5 mL (5 vials per box), 1000 mg / 10 mL (1 vial per box) and 2000 mg / 20 mL (1 vial per box).
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: cytarabine
Chemical name: 4-amino-1-β- D-arabinofuranosyl-1H-pyrimidin-2-one
Molecular formula and molecular mass: C9H13N3O5 243.2 g / mol
Structural formula:
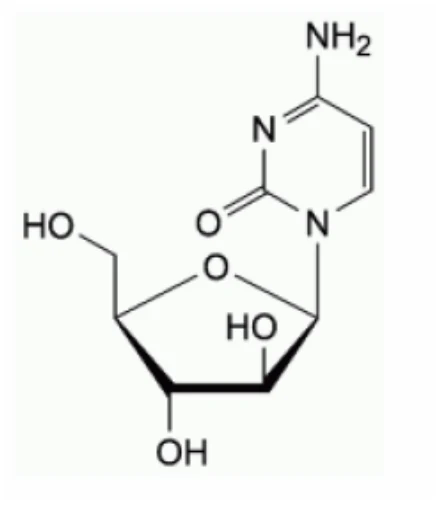
Description:
- white to almost white, crystalline powder
- melting point 215°C
Solubility:
- freely soluble in water
- slightly soluble in alcohol and methylene chloride
DETAILED PHARMACOLOGY
Cell Culture Studies
Cytarabine is cytotoxic to a wide variety of proliferating mammalian cells in culture. It exhibits cell phase specificity, primarily killing cells undergoing DNA synthesis (S-phase) and under certain conditions blocking the progression of cells from the G1 phase to S-phase. Although the mechanism of action is not completely understood, it appears that cytarabine acts through the inhibition of DNA polymerase. A limited, but significant, incorporation of cytarabine into both DNA and RNA has also been reported. Extensive chromosomal damage, including chromatoid breaks has been produced by cytarabine and malignant transformation of rodent cells in culture has been reported. Deoxycytidine prevents or delays (but does not reverse) the cytotoxic activity.
Animal Studies
In experimental studies with mouse tumors, cytarabine was most effective in those tumors with a high growth fraction. The effect was dependent on the treatment schedule; optimal effects were achieved when the schedule (multiple closely spaced doses or constant infusion) ensured contact of the drug with the tumor cells when the maximum number of cells was in the susceptible S-phase. The best results were obtained when courses of therapy were separated by intervals sufficient to permit adequate host recovery.
TOXICOLOGY
Animal Studies
Toxicity of cytarabine in experimental animals, as well as activity, is markedly influenced by the schedule of administration. For example, in mice, the LD10 for single intraperitoneal administration is greater than 6000 mg / m2. However, when administered in 8 doses, each separated by 3 hours, the LD10 is less than 750 mg / m2 total dose. Similarly, although a total dose of 1920 mg / m2 administered as 12 injections at 6-hour intervals was lethal to beagle dogs (severe bone marrow hypoplasia with evidence of liver and kidney damage), dogs receiving the same total dose administered as 8 injections (again at 6-hour intervals) over a 48-hour period survived with minimal signs of toxicity.
The most consistent observation in surviving dogs was elevated transaminase levels. In all experimental species the primary limiting toxic effect is marrow suppression with leukopenia. In addition, cytarabine causes abnormal cerebellar development in the neonatal hamster and is teratogenic to the rat fetus.
The major dose-limiting toxicity of cytarabine observed in all tested species is myelosuppression, manifested by megaloblastosis, retculocytopenia, leukopenia, and thrombocytopenia. Other target organs include liver, kidney, and brain. Extensive chromosomal damage, including chromatoid breaks have been produced by cytarabine and malignant transformation of rodent cells in culture has been reported. Cytarabine is embryotoxic and teratogenic and produced peri- and postnatal toxicity in various species. No formal fertility
studies have been reported however sperm head abnormalities were observed following cytarabine treatment in mice.
REFERENCES
- 1. Zaky DA, Betts RF, Douglas RG, et al. Varicella-Zoster virus and subcutaneous cytarabine: Correlation of in vitro sensitivities to blood levels. Antimicrob Agents Chemother 1975;7:229-32.
- 2. Davis CM, VanDersarl JV, Coltman CA Jr. Failure of cytarabine in varicella-zoster infections. JAMA 1973;224:122-3.
- 3. Betts RF, Zaky DA, Douglas RG, et al. Ineffectiveness of subcutaneous cytosine arabinoside in localized herpes zoster. Ann Intern Med 1975;82:778-83.
- 4. Dennis DT, Doberstyn EB, Awoke S, et al. Failure of cytosine arabinoside in treating smallpox, a double-blind study. Lancet 1974;2:377-9.
- 5. Gray GD. ARA-C and derivatives as examples of immunosuppressive nucleoside analogs. Ann NY Acad Sci 1975;255:372-9.
- 6. Mitchell MS, Wade ME, DaConti RC, et al. Immunosuppressive effects of cytosine arabinoside and methotrexate in man. Ann Intern Med 1969;70:525-47.
- 7. Frei E, Ho DHW, Body GP, et al. Pharmacologic and cytokinetic studies of arabinosyl cytosine. In unifying concepts of leukemia. Bibl Hematol No. 39 Karger, Base 1, 1973, p 1085-7.
- 8.
Woolner N, Burchenal JH, Lieberman PH, et al. Non-Hodgkin's lymphoma in children -
A comparative study of two modalities of therapy. Cancer 1976;37:123-34.
- 9. Woolner N, Exelby PR, Lieberman PH. Non-Hodgkin's lymphoma in children - A progress report on the original patients treated with the LSA2-L2 protocol. Cancer 1979;44:1990-99.
- 10. Sullivan MP, Pullen J, Moore T, et al: Pediatric oncology group trial of LSA2-L2 therapy in Non-Hodgkin's lymphoma. Abstracted, Proc AACR and ADCO 1981;22:C-180.
- 11. Ellison RR, Holland JF, Weil M, et al. Arabinosyl cytosine: A useful agent in the treatment of acute leukemia in adults. Blood 1968;32:507-23.
- 12. Bodey GP, Freireich EJ, Monto RW, et al. Cytosine arabinoside (NSC-63878) therapy for acute leukemia in adults. Cancer Chemother Rep 1969;53:59-66.
- 13. Goodell B, Leventhall B, Henderson E. Cytosine arabinoside in acute granulocytic leukemia. Clin Pharmacol Ther 1970;12:599-606.
- 14.
Southwest Oncology Group. Cytarabine for acute leukemia in adults. Arch Intern Med
1974;133:251-9.
- 15. Carey RW, Ribas-Mundo M, Ellison RR, et al. Comparative study of cytosine arabinoside therapy alone and combined with thioguanine, mercaptopurine or daunorubicin in acute myelocytic leukemia. Cancer 1975;36:1560-66.
- 16. Lampkin BC, McWilliams NB, Mauer AM, et al. Manipulation of the mitotic cycle in the treatment of acute myelogenous leukemia. Br J Haematol 1976;32:29-40.
- 17. Preisler H, Bjornsson S, Henderson ES, et al. Remission induction in acute non-lymphocytic leukemia - Comparison of a seven-day and ten-day infusion of cytosine arabinoside in combination with adriamycin. Med Pediatr Oncol 1979;7:269-75.
- 18.
Gale RP, Cline MJ. High remission - induction rate in acute myeloid leukemia. Lancet
1977;1:497-9.
- 19. Weinstein JH, Mayer RJ, Rosenthal DS, et al. Treatment of acute myelogenous leukemia in children and adults. N Engl J Med 1980;303:473-8.
- 20. Glucksberg H, Cheever MA, Farewell UT, et al. High-dose combination chemotherapy for acute non-lymphoblastic leukemia in adults. Cancer 1981;48:1073-81.
- 21. Cassileth PA, Katz ME. Chemotherapy for adult acute non-lymphocytic leukemia with daunorubicin and cytosine arabinoside. Cancer Treat Rep 1977;61:1441-5.
- 22. Hagbin M. Acute non-lymphoblastic leukemia: Clinical and morphological characterization. Mod Prob Pediatr 1975;16:39-58.
- 23. Pizzo PA, Henderson ES, Leventhal BG. Acute myelogenous leukemia in children. A preliminary report of combination chemotherapy. J Pediatr 1976;88:125-30.
- 24.
Report of the Medical Research Council's Working Party on Leukemia in Adults:
Treatment of acute myeloid leukemia with daunorubicin, cytosine arabinoside, mercaptopurine, L-asparaginase, prednisone and thioguanine: Results of treatment with five multiple-drug schedules. Br J Haematol 1974;27:373-89.
- 25. Ansari BM, Thompson EN, Whittaker JA. A comparative study of acute myeloblastic leukemia in children and adults. Br J Haematol 1975;31:269-77.
- 26. Gee TS, Haghbin M, Dowling MD Jr, et al. Acute lymphoblastic leukemia. In adults and children: Differences in response with similar therapeutic regimens. Cancer 1976;37:1256-64.
- 27. Spiers ASD, Roberts PD, Marsh GW, et al. Acute lymphoblastic leukemia: Cyclical chemotherapy with three combinations of four drugs (COAP-POMP-CART Regimen). Brit Med J 1975;4:614-7.
- 28. Howard JP, Albo V, Newton WA Jr. Cytosine arabinoside: Results of a cooperative study in acute childhood leukemia. Cancer 1968;21:341-5.
- 29. McElwain TJ, Hardisty RM. Remission induction with cytosine arabinoside and L-asparaginase in acute lymphoblastic leukemia. Brit Med J 1969;4:596-8.
- 30. Bodey GP, Rodriguez V, Hart J, et al. Therapy of acute leukemia with the combination of cytosine arabinoside (NSC-63878) and cyclophosphamide (NSC-26271). Cancer Chemother Rep 1970;54:255-62.
- 31. Nesbitt ME Jr, Hammond D. Cytosine arabinoside (ARAC) and prednisone therapy of previously treated acute lymphoblastic and undiffentiated leukemia (ALL/AUL) of childhood. Proc Am Assoc Cancer Res 1970;11:59.
- 32. Wang JJ, Selawry OS, Vietti TJ, et al. Prolonged infusion of arabinosyl cytosine in childhood leukemia. Cancer 1970;25:1-6.
- 33. Klemperer M, Coccia P, Albo V, et al. Reinduction of remission after first bone marrow relapse in childhood acute lymphoblastic leukemia.. Proc Am Assoc Cancer Res 1978;19:414.
- 34. Ortega JA, Finklestein JZ, Ertel I, et al. Effective combination treatment of advanced acute lymphocytic leukemia with cytosine arabinoside (NSC-63878) and L-asparaginase (NSC-109229). Cancer Chemother Rep 1972;56:363-8.
- 35. Bryan JH, Henderson ES, Leventhal BG. Cytosine arabinoside and 6-thioguanine in refractory acute lymphocytic leukemia. Cancer 1974;33:539-44.
- 36.
Proceedings of the chemotherapy conference on ARA-C: Development and application
(cytosine arabinoside hydrochloride - NSC 63878), Oct 10, 1969.
- 37. Lay HN, Colebatch JH, Ekert H. Experiences with cytosine arabinoside in childhood leukemia and lymphoma. Med J Aust 1971;2:187-92.
- 38. Halikowsli B, Cyklis R, Armata J, et al. Cytosine arabinoside administered intrathecally in cerebromeningeal leukemia. Acta Paediatr Scand 1970;59:164-8.
- 39.
Wang JJ, Pratt CG. Intrathecal arabinosyl cytosine in meningeal leukemia. Cancer
1970;25:531-4.
- 40. Band PR, Holland JF, Bernard J, et al. Treatment of central nervous system leukemia with intrathecal cytosine arabinoside. Cancer 1973;32:744-8.
- 41.
Sullivan MP, Dyment P, Hvizdala E, et al. Favourable Comparison of all out #2 with
"total" therapy in the treatment of childhood leukemia - The equivalence of intrathecal chemotherapy and radiotherapy as CNS prophylaxis. Abstracted, Proc of AACR and
ASCO 1981;22:675.
- 42.
Saiki JH, Thompson S, Smith F, et al. Paraplegia following intrathecal chemotherapy.
Cancer 1972;29:370-74.
- 43.
Rubinstein LJ, Herman MM, Long TF, et al. Disseminated necrotizing
leukoencephalopathy: A complication of treated central nervous system leukemia and lymphoma. Cancer 1975;35:291-305.
- 44.
Marmont AM, Damasio EE. Neurotoxicity of intrathecal chemotherapy for leukemia.
Brit Med J 1973;4:47.
- 45. Margileth DA, Poplack DG, Pizzo PA, et al. Blindness during remission in two patients with acute lymphoblastic leukemia. Cancer 1977;39:58-61.
- 46.
Hopen G, Mondino BJ, Johnson BL, et al. Corneal toxicity with systemic cytarabine.
Am J Opthalmol 1981;91:500-504.
- 47. Lazarus HM, Herzig RH, Herzig GP, et al. Central nervous system toxicity of high-dose systemic cytosine arabinoside. Cancer 1981;48(12):2577-82.
- 48. Slavin RE, Dias MA, Soral R. Cytosine arabinoside induced gastrointestinal toxic alterations in sequential chemotherapeutic protocols - A clinical pathologic study of 33 patients. Cancer 1978;42:1747-59.
- 49. Haupt HM, Hutchins GM, Moore GW. Ara-C lung: Noncardiogenic pulmonary edema complicating cytosine arabinoside therapy of leukemia. Am J Med 1981;70:256-61.
- 50.
Shafer AI. Teratogenic effects of antileukemic chemotherapy. Arch Intern Med
1981;141:514-5.
- 51.
Wagner VM, et al. Congenital abnormalities in baby born to cytarabine treated mother.
Lancet 1980;2:98-9.
- 52. Frei E III, Bickets JN, Hewlet JS, et al. Dose schedule and antitumor studies of arabinosyl cytosine (NSC 63878). Cancer Res 1969;29:1325-32.
- 53.
Bell WR, Whang JJ, Carbone PP, et al. Cytogenetic and morphologic abnormalities in human bone marrow cells during cytosine arabinoside therapy. J Hematol 1966;27:771-
81.
- 54. Burke PJ, Serpick AA, Carbone PP, et al. A clinical evaluation of dose and schedule of administration of cytosine arabinoside (NSC 63878). Cancer Res 1968;28:274-9.
- 55.
Castleberry RP, Crist WM, Holbrook T, et al. The cytosine arabinoside (Ara-C)
syndrome. Med Pediatr Oncol 1981;9:257-64.
- 56. Slevin ML, Piall EM, et al. The pharmacokinetics of subcutaneous cytosine arabinoside in patients with acute myelogenous leukemia. Br J Clin Pharmacol 1981;12:507-10.
- 57. Munson WJ, Kubiak EJ, Cohon MS. Cytosine arabinoside stability in intravenous admixtures with sodium bicarbonate and in plastic syringes. Drug Intell Clin Pharm 1982;16:765-7.
- 58. Athanikar N, Boyer B, Deamer R, et al. Visual Compatibility of 30 additives with a parenteral nutrient solution. Am J Hosp Pharm 1979;36:511-3.
- 59. Cradack JC, Kleinman LM, Rahman A. Evaluation of some pharmaceutical aspects of intrathecal methotrexate sodium, cytarabine and hydrocortisone sodium succinate. Am J Hosp Pharm 1978;35:402-406.
- 60. Keller JH, Ensminger WD. Stability of cancer chemotherapeutic agents in a totally implanted drug delivery system. Am J Hosp Pharm 1982;39:1321-3.
- 61. Benvenuto JA, Anderson RW, Kerkof K, et al. Stability and compatibility of antitumor agents in glass and plastic containers. Am J Hosp Pharm 1981;38:1914-8.
- 62. McRae MP, King JC. Compatibility of antineoplastic, antibiotic and corticosteroid drugs in intravenous admixtures. Am J Hosp Pharm 1976;33:1010-13.
- 63.
Ho D. Potential advances in the clinical use of arabinosylcytosine. Cancer Treat Rep
1977;61:717-22.
- 64. Piall E, et al. Cytosine arabinoside: Pharmacokinetics following different routes of administration. Biochem Soc Trans 1982;10:512-3.
- 65. Fulton DS, et al. Intrathecal cytosine arabinoside for the treatment of meningeal metastases from malignant brain tumors and systemic tumors. Cancer Chemother Pharmacol 1982;8:285-91.
- 66. Dahl S, et al. Therapeutic efficacy of preventive intrathecal (IT) chemotherapy for children with acute lymphocytic leukemia (ALL) who relapse after cessation of therapy. Abstracted, Proc of AACR and ASCO 1979;20:628.
- 67. Altman AJ, et al. Remission induction in acute non-lymphocytic leukemia (ANLL) with low-dose cytosine arabinoside (ARA-C). Abstract Pediatr Res 1982;16(4,Part 2):197A(714).
- 68.
Lister TA, Robatiner AZS. The treatment of acute myelogenous leukemia in adults.
Semin Haematol 1982;19:3,172-92.
- 69.
Mitrou PS for the AIO. Sequential combination therapy (COP-Bleo+AVP) in non-
Hodgkin's lymphomas (NHL) of high-grade malignancy stage III and IV. A phase II study. J Cancer Res Clin Oncol 1982;103 Suppl:A23.
- 70. Pichler E, et al. Results of LSA2-L2 therapy in 26 children with non-Hodgkin's lymphoma. Cancer 1982;50:2740-46.
- 71.
Preisler HD. High dose cytosine arabinoside therapy in acute non-lymphocytic leukemia.
Eur J Cancer Clin Oncol 1984;20(2):297-300.
- 72.
Rohatiner AZS, Slevin ML, Dhaliwal HS, et al. High dose cytosine arabinoside:
Response to therapy in acute leukemia and non-Hodgkin's lymphoma. Cancer Chemother Pharmacol 1983;12:90-93.
- 73. Herzig RH, Wolff SN, Larzaus HM, et al. High-dose cytosine arabinoside therapy for refractory leukemia. Blood 1983;62(2):361-9.
- 74. Preisler HD, Early AP, Raza A, et al. Therapy of secondary acute non-lymphocytic leukemia with cytarabine. N Eng J Med 1983;308(1):21-3.
- 75. Willemze R, Zwaan FE, Colpin G, et al. High dose cytosine arabinoside in the management of refractory acute leukemia. Scand J Haematol 1982;29:141-6.
- 76. Capizzi RL, Poole M, Cooper MR, et al. Treatment of poor risk acute leukemia with sequential high dose ARA-C and asparaginase. Blood 1984;63(3):694-700.
- 77.
Johnson H, Smith TJ, Desforges J. Cytosine arabinoside induced colitis and peritonitis:
Non-operative management. J Clin Oncol 1985;3(5):607-12.
- 78. Dunton SF, Ruprecht N, Spruce W, et al. Progressive ascending paralysis following administration of intrathecal and intravenous cytosine arabinoside. Cancer 1986;57:1083-8.
- 79.
Takvorian T, Anderson K, Ritz J. A fetal cardiomyopathy associated with high dosage
ARA-C (HIDAC) and cyclophosphamide (CTX) in bone marrow transplantation (BMTx). Abstract submitted for 1985 AACR meetings in Houston, Texas.
- 80. Anderson BS, Cogan B, Keating MJ, Estey EH, et al. Subacute pulmonary failure complicating therapy with high dose ARA-C in acute leukemia. Cancer 1985;56(9):2181-4.
- 81. Altman AJ, Dindorf P, Quinn JJ. Acute pancreatitis in association with cytosine arabinoside therapy. Cancer 1982;49:1384-6.
- 82. Powell BL, Capizzi RL, Lyerly EW, et al. Peripheral neuropathy after high-dose cytosine arabinoside, daunorubicin, and asparaginase consolidation for acute non-lymphocytic leukemia. J Clin Oncol 1986;4(1):95-7.
- 83. Peters WG, Willenze R, Coely LP. Results of induction and consolidation treatment with intermediate and high dose ARA-C and m-AMSA containing regimens in patients with primarily failed or relapsed acute leukemia and non-Hodgkin's lymphoma. Scand J Haematol 1986;36 Suppl 44:7-16.
- 84.
Marmont AM, Dimasio EE. Neurotoxicity of intrathecal chemotherapy for leukemia.
Brit Med J 1973;4:47.
- 85. Margileth DA, Peplack DG, Pizzo PA, et al. Blindness during remission in two patients with acute lymphoblastic leukemia. Cancer 1977;39:58-61.
- 86.
Trissel LA. Handbook on injectable drugs, 7th Ed. American Society of Hospital
Pharmacists 1992;267-71.
- 87.
Crampton JD, Cohon MS, Lummis WL, et al: Cytosine Arabinoside Stability in Three
Intravenous Infusion Solutions at Three Temperatures, Upjohn Technical Report, Code No. 7262/82/7262/037, December 10, 1982.
- 88.
Hassing, DH: 8-Day Stability of CYTOSAR in a Dextrose-NaC1-KC1 Infusion Solution,
Upjohn Interoffice Memo to J.R. Kline, April 7, 1978.
- 89.
Kuhlman J: Inhibition of Digoxin Absorption but not of Digitoxin During Cytostatic
Drug Therapy, Arzneim Forsch 32:698-704, 1982.
- 90.
Moody MR, Morris MJ, Yang VM, et al: Effect of Two Cancer Chemotherapeutic
Agents on the Antibacterial Activity of Three Antimicrobial Agents, Antimicrob. Agents Chemother., 14:737-742, 1978.
- 91.
Holt RJ: Clinical Problems with 5-fluorocytosine, Mykosen, 21(11):363-369, August,
1978.
- 92.
Polak A, Grenson M: Interference Between the Uptake of Pyrimidines and Purines in
Yeasts, Path. Microbiol., 39:37-38, 1973.
- 93.
Nand et al, Neurotoxicity Associated With Systemic High-Dose Cytosine Arabinoside, J
Clin Oncol 1986;4:571-5.
- 94.
Damon et al, The Association Between High-Dose Cytarabine Neurotoxicity and Renal
Insufficiency, J Clin Oncol 1989;7:1563-8.
- 95.
Reykdal S, Sham R, Kouides P: Cytarabine-Induced Pericarditis: A Case Report and
Review of the Literature of the Cardio-Pulmonary Complications of Cytarabine Therapy. Leukemia Research 1995; 19:141-144.
- 96.
Watterson J, Toogood I, Nieder M, et al: Excessive Spinal Cord Toxicity From Intensive
Central Nervous System-Directed Therapies. Cancer 1994; 74:3034-3041.
- 97.
Pharmascience Inc., Product Monograph PrCYTOSAR, Control No. 204769, Date of
Revision: May 17, 2017.
APPENDIX A
LSA2-L2 Protocol
Woolner N, Burchenal JH, Lieberman PH, et al: Non-Hodgkin's Lymphoma in Children - A Comparative Study of Two Modalities of Therapy. Cancer 1976;37:123-134.
Induction Phase
Day 1. Cyclophosphamide 1200 mg / m2 single push injection.
Day 3 to 31. Prednisone 60 mg / m2 PO divided into three daily doses. Day 3, 10, 17, 24. Vincristine 1.5 to 2.25 mg / m2 intravenously.
Day 5, 27, 30. Spinal tap and intrathecal injection of Methotrexate 6.25 mg/m2 Day 12, 13. Daunomycin 60 mg / m2 intravenously.
At the end of induction (last dose of intrathecal methotrexate) patient rests for 3-5 days before consolidation.
Consolidation Phase
Day 34 or 36, daily intravenous injections of cytosine arabinoside (Ara-C) 150 mg / m2 for a total of 15 injections are given. (Injections are given from Monday through Friday.) Thioguanine 75 mg / m2 is given orally, 8-12 hours after the injection of Ara-C. If the white blood count is 1500 or more and the platelet count 150000 or more on the 5th day of Ara-C, the patient continues to receive the same dosage of thioguanine over the weekend. However, both are discontinued temporarily when there is evidence of marrow depression; this usually occurs after the initial seventh to tenth doses of the combination and ordinarily recovers within 7-10 days. Hence, the patients may receive more than 15 doses of thioguanine orally, but receive only 15 doses of IV cytosine arabinoside (Ara-C). This first phase of the consolidation takes an average of 30-35 days. The second phase of the consolidation should be started immediately after completion of the 15 doses of Ara-C; it entails daily IV administration of L-asparaginase, 60000 U/m2 for a total of 12 injections, excluding weekends.
Two days after the last injection of the L-asparaginase, two more intrathecal (IT) injections of methotrexate are given 2 days apart. Three days after the last IT methotrexate, BCNU [1, 3-Bis (2 chloroethyl 1-1-nitrosourea)] 60 mg / m2 is given IV, which completes the consolidation. The average duration of the induction and consolidation is 85-100 days.
Maintenance Phase
The maintenance period consists of five cycles of 5 days each and is started 3-4 days after completion of consolidation.
Cycle I: Oral thioguanine 300 mg / m2 for 4 consecutive days: i.v. cyclophosphamide 600 mg / m2 on the 5th day.
Rest 7-10 days.
Cycle II: Oral hydroxyurea 2400 mg / m2 for 4 consecutive days: i.v. daunomycin 45 mg / m2 on the 5th day.
Rest 7-10 days.
Cycle III: Oral methotrexate 10 mg/m2 for 4 consecutive days: IV BCNU 60 mg / m2 on the 5th day.
Rest 7-10 days.
Cycle IV: I.V. Ara-C 150 mg / m2 for 4 consecutive days: i.v. vincristine 1.5 mg / m2 on day 5. Rest 7-10 days.
Cycle V: Two doses of IT methotrexate 6.25 mg / m2 2-3 days apart. Rest 7-10 days and restart with Cycle I.