


Product Monograph - Antithrombin III Immuno
INDICATIONS AND CLINICAL USE
ANTITHROMBIN Ill IMMUNO, Antithrombin III (human) is indicated for prophylaxis and treatment of thrombotic and thromboembolic disorders in patients with hereditary antithrombin III deficiency (antithrombin III activity below 70% of normal). Infusions of antithrombin III may be particularly valuable in surgical procedures or pregnancy and delivery in patients with congenital antithrombin III deficiency (8).
CONTRAINDICATIONS
None known.
WARNINGS
This product is prepared from pooled human plasma which may contain the causative agents of hepatitis and other viral diseases. Prescribed manufacturing procedures utilized at the plasma collection centres, plasma testing laboratories, and the fractionation facilities are designed to reduce the risk of transmitting viral infection. However, the risk of viral infectivity from this product cannot be totally eliminated.
Individuals who receive infusions of blood or plasma products may develop signs and/or symptoms of some viral infections, particularly non-A, non-B hepatitis.
PRECAUTIONS
General
Patients with ATIll deficiency who are undergoing treatment using a plasma-derived product, should be appropriately vaccinated.
Administer immediately after reconstitution.
Do not refrigerate after reconstitution.
Administer only by intravenous injection or infusion. Administration equipment and any unused reconstituted ATIII product should be appropriately discarded.
It is recommended that ATIII plasma levels be monitored during the treatment period.
Drug Interactions
The anticoagulant effect of heparin is enhanced by concurrent treatment with ANTITHROMBIN III IMMUNO, Antithrombin III (human). Thus, in order to avoid bleeding, reduced dosage of heparin is recommended during the treatment with ANTITHROMBIN III IMMUNO.
In patients with hemorrhagic diathesis the combined use of antithrombin III and heparin will increase the risk of bleeding.
When using antithrombin III in combination with heparin treatment, the enhancement of the anticoagulant effect must be taken into consideration when calculating the dose of heparin. In addition, attention is drawn to the fact that patients with thrombocytopenia may be deficient in platelet factor 4, which entails diminished neutralization of heparin and consequently may lead to an increased bleeding tendency.
As a rule, regular monitoring of APTT (activated partial thromboplastin time) and corresponding adjustment of the heparin dose is recommended for any combination therapy with heparin.
Pregnancy And Nursing Mothers
It is not known whether ANTITHROMBIN III lMMUNO, Antithrombin Ill (human) can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. ANTITHROMBIN III IMMUNO should be given to a pregnant or lactating woman only if clearly needed.
Use in children
Only a few children have so far been treated with ANTITHROMBIN III IMMUNO, Antithrombin III (human). Safety and effectiveness in children have not yet been established.
ADVERSE REACTIONS
As with any other infused plasma derivative, anaphylactoid or anaphylactic reactions may occur, although rarely. The occurrence of these reactions (e.g., fever, urticarial rashes, nausea, retching, dyspnoea, anaphylactic shock) necessitates the interruption of replacement therapy. Mild reactions can be managed with antihistamine; severe hypotonic reactions require immediate intervention using current principles of shock therapy.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
No symptoms of overdosage with ANTITHROMBIN III IMMUNO, Antithrombin III (human) are known.
DOSAGE AND ADMINISTRATION
The dosage of ANTITHROMBIN III IMMUNO, Antithrombin III (human) depends on the cause and the extent of the antithrombin III deficiency. Thus, the antithrombin III activity must be determined for accurate dosage calculation. The normal range of antithrombin III activity in human plasma is between 80% and 120%; a decrease in activity to below 70% of normal is associated with an increased risk of thrombosis. Individual doses should therefore be large enough to assure that an antithrombin III plasma level of at least 70% of normal is maintained between infusions.
As a rule, in patients with congenital antithrombin III deficiency, the biological half life is approximately 2.5 days. In cases of acute consumption of antithrombin III (DIC), the half life may be reduced to only a few hours.
The duration of treatment varies from case to case. In general, the administration of ANTITHROMBIN III IMMUNO may be discontinued after normalization of laboratory parameters and/or remission of clinical symptoms. Further monitoring of the antithrombin Ill plasma level at regular intervals may, however, be necessary for a prolonged period of time.
The measurement of antithrombin III biological activity, e.g., using chromogenic substrates (amidolytic method), is recommended for determination of the patient's plasma level of antithrombin III before and during treatment with ANTITHROMBIN Ill IMMUNO.
The functional antithrombin III activity is stated on the label of each vial in international units (IU) and was determined using a standard calibrated against the 2nd WHO ATIll reference standard.
Dosage Guidelines
- 1. Disseminated Intravascular Coagulation
Dosage of ANTITHROMBIN III IMMUNO, Antithrombin III (human) should be based on a determination of the patient's antithrombin III activity prior to therapy and thereafter at intervals of approximately 4-6 hours. The initial dose should be large enough to raise the plasma level to normal (80-120%). Additional doses are required whenever the antithrombin III activity has dropped to less than 70%.
In patients with an acute consumption of antithrombin III, the dosage calculations can be based on the formula:
Dose (in IU) = [desired ATIII activity (%) - baseline ATIII activity (%)] x body weight (in kg) divided by 1 %
Maintenance dosage is also calculated using the formula stated above, except that the 1% is substituted instead, with the actual increase in ATIII activity (in %) produced by 1 IU per kg of body weight, as determined by the measurement of ATIII activity following the administration of the initial dose.
When using ANTITHROMBIN III IMMUNO in combination with heparin, it must be taken into account that the anticoagulant effect of heparin is accelerated by antithrombin III (see also "PRECAUTIONS - Drug Interactions").
- 2. Other Antithrombin III Defects
As a guideline, an initial dose of 1500 IU and a maintenance dose of one half the initial dose given at 8 to 24 hour intervals is suggested for an average sized adult. However, the dosage should be adjusted to For management of a suspected drug overdose, contact your regional Poison Control Centre individual needs, which can only be estimated by determination of the patient's antithrombin III activity at regular intervals. In the absence of acute consumption of AT III, dosage calculations can be based on the formula:
Dose (in IU) = [desired ATIII activity (%) - baseline ATIII activity (%)] x body weight (in kg) divided by 2%
Maintenance dosage is also calculated using the formula stated above, except that the 2% is substituted instead, with the actual increase in ATIII activity (in %) produced by 1 IU per kg of body weight, as determined by the measurement of ATIII activity following the administration of the initial dose.
Reconstitution of Concentrate
ANTITHROMBIN III IMMUNO, Antithrombin III (human) is to be stored in its lyophilized condition and reconstituted immediately before application. Entered vials must not be reused. The product does not contain a preservative and must be handled with aseptic technique to prevent contamination.
For reconstitution, proceed as follows:
- 1.
Warm the unopened bottle containing Sterile Water for Injection (diluent) to room temperature
(not above 37°C, 98°F).
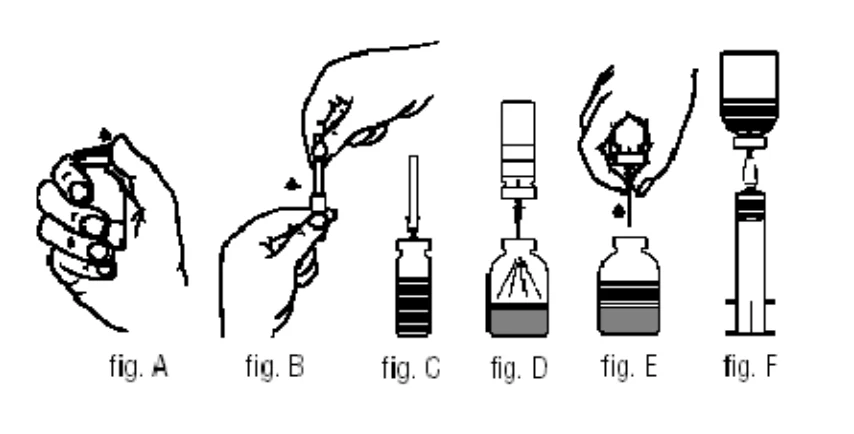
- 2. Remove caps from the concentrate and diluent bottles to expose central portions of the rubber stoppers (fig. A).
- 3. Cleanse exposed surface of the rubber stopper with germicidal solution and allow to dry.
- 4. Using aseptic technique, remove protective covering from one end of the double-ended needle and insert the exposed end through the diluent bottle stopper (fig. B and C).
- 5. Remove protective covering from the other end of the double-ended needle, taking care not to touch the exposed end. Invert diluent bottle over the concentrate bottle, then rapidly insert free end of the needle through the concentrate bottle stopper (fig. D). Diluent will be drawn into the concentrate bottle by vacuum.
- 6.
Disconnect the two bottles by removing the needle from the concentrate bottle stopper (fig. E).
Gently agitate or rotate the concentrate bottle until all material is dissolved.
- 7. Visually inspect the reconstituted product for particulate matter and discolouration prior to administration, whenever solution and container permit. Discard if particulate matter or discolouration exists.
Do not refrigerate after reconstitution.
Administration
The reconstituted solution must be given by intravenous injection or infusion immediately after preparation. The injection or infusion rate must not exceed 5 mL/minute.
For intravenous injection:
- 1. After reconstituting the concentrate as described under "Reconstitution of Concentrate", attach the enclosed filter needle to a sterile disposable syringe and insert needle through the bottle stopper (fig. F).
- 2. Inject air and withdraw solution into syringe.
- 3. Remove and discard filter needle. Attach a suitable intravenous needle or infusion set with winged adapter to the syringe and inject solution intravenously.
For intravenous infusion:
Prepare a solution of ANTITHROMBIN III IMMUNO as described under "Reconstitution of Concentrate". If not filtered during dissolution, a disposable infusion set with a filter (range between 149 micrometer and 5 micrometer) is to be used.
PHARMACEUTICAL INFORMATION
ANTITHROMBIN III IMMUNO, Antithrombin III (human) contains antithrombin III in a sterile, purified, concentrated and stabilized form. The antithrombin III content per mg total protein is between 1-2.5 IU1. The antithrombin III content per mg protein (excluding albumin) is not less than 3.0 IU1.
When reconstituted, ANTITHROMBIN III IMMUNO has a pH of 6.0-7.5, a heparin content of not more than 0.1 IU/IU1 antithrombin III, an albumin (human) content of 12 to 40 mg/mL, a sodium chloride content of 8-10 mg/mL, a glucose content of 9-11 mg/mL, a sodium citrate dihydrate content of 0.8-1.5 mg/mL, and a tris(hydroxymethyl)aminomethane content of 0.8-1.2 mg/mL. Each vial of ANTITHROMBIN III IMMUNO contains the labelled amount of antithrombin III in international units (IU1) per vial.
ANTITHROMBIN III IMMUNO contains no preservative.
To prevent the transmission of infective agents by the administration of ANTITHROMBIN III IMMUNO, measures are taken for donor and plasma selection, as well as virus removal and inactivation steps during manufacture. In addition to the required plasma screening tests, all individual plasma donations are subjected to an inventory hold for a possible look-back of plasma donations suspected of infection. Moreover, a plasma pool sample is tested for antibodies to HIV-1/HIV-2 and HBsAg; in addition to that, a test for viral genomic sequences of HIV-l/HIV-2, HBV, HAV, HCV and Parvo B19 is performed using the polymerase chain reaction (HIQ-PCR2).
The effectiveness of the steps as employed during the manufacture of ANTITHROMBIN III IMMUNO to remove and/or inactivate potential viral contamination (cryoprecipitation, adsorption on DEAE-Sephadex, heat treatment for 10 hrs. at 60°C; and filtration/filling and lyophilization) has been demonstrated in validation studies (9) using human immunodeficiency virus type 1 (HIV-1), hepatitis A virus (HAV) and human parvovirus B19 (B19V) as target viruses, tick-borne encephalitis virus (TBEV) and bovine viral diarrhea virus (BVDV) as models for hepatitis C virus (HCV), pseudorabies virus (PRV) as a general model for hepatitis B virus (HBV), and mice minute virus (MMV) as a model for B19V. It was demonstrated that the different steps investigated resulted in overall virus titer reductions3 by factors of >10.7 logs for HIV-1, >7.3 logs for HAV, >12.1 logs for HBV, >7.9 logs for HCV and 6.0 logs for B19V.
The risk of transfusion-transmitted viral infection in AT III recipients previously untreated with blood or blood products (PUP's) was followed in a prospective clinical study using the criteria established by the International Society for Thrombosis and Haemostasis (10). Data from 26 patients were evaluated for non-A, non-B hepatitis and 27 for hepatitis B transmission. In addition, 20 patients were evaluated for HCV seroconversion and 78 for HIV seroconversion. No case of product-related transmission of viral hepatitis or HIV was observed.
Shelf-Life and Storage
When stored between +2°C and +8°C (+35°F and +46°F), ANTITHROMBIN III IMMUNO, Antithrombin III (human) is stable until the date indicated on the label. Do not freeze.
ANTITHROMBIN III IMMUNO must not be used beyond the expiration date indicated on the label.
The reconstituted solution should be used immediately after preparation (contains no preservative), it should not be refrigerated and any unused portion of it should be discarded.
AVAILABILITY OF DOSAGE FORMS
ANTITHROMBIN III IMMUNO, Antithrombin III (human) is supplied in a single dose vial accompanied by a vial of Sterile Water for Injection, E.P. for diluent, a sterile double-ended needle and a sterile filter needle as follows:
ANTITHROMBIN III IMMUNO (IU1/vial) | Sterile Water for Injection, E.P. (mL) |
| 450-550 | 10 |
| 900-1100 | 20 |
| 1350-1650 | 30 |
The number of I.U.1 antithrombin III is stated on the label of each vial.
PHARMACOLOGY
- 1. Animals
Pharmacodynamics
Bahrami et al. in 1989 (11) investigated the protective effect of ANTlTHROMBIN III IMMUNO, Antithrombin III (human) against DIC induced death in rats previously treated with E. coli-toxin. In the untreated controls 70% of animals died of DIC whereas in the rats who had received 400 IU antithrombin III i.p. at 1h prior to the endotoxin, mortality was only 50%. The results of the study suggest that antithrombin III is effective in protecting against endotoxemia induced DIC.
In addition, the pharmacodynamic effect is routinely assessed in-vitro by determinations of antithrombin III activity during quality control of intermediates and the final container.
Pharmacokinetics
Animal pharmacokinetics studies with human protein do not appear relevant because due to species-specificity data obtained in animals cannot be extrapolated to humans.
- 2. Humans
Pharmacodynamics
In a controlled double blind randomized multicenter study by Baudo et al. in 1995 (12), the effect of AT III therapy on survival and multiple organ failure (MOF score) was evaluated in 119 patients with sepsis and/or post surgical complications (59 ATIll; 60 placebo). The mean MOF score showed significant improvements for all AT III-treated patients. AT III therapy also led to a reduction of fibrin (fibrinogen) degradation products and to a marked increase of the plasminogen level. At both day 7 and day 30, mortality was significantly reduced in patients with septic shock who received AT III replacement therapy as compared to placebo.
In a controlled, randomized open-label efficacy study by Blauhut et al in 1985 (13), 3 groups of shock patients with DIC (n=51) were treated either with AT III or heparin or with ATIII+heparin. In the two heparin groups a drop in platelet count was observed. Blood loss in traumatic shock was considerably higher in the AT III+heparin group. Duration of symptoms of DIC was considerably shortened in both AT III groups (DIC symptoms disappeared after 42±28.2 h in the AT III group, after 57.1±31.9 h in the AT llI/heparin group and after 110.6±48.4 h in patients with heparin alone.) These data suggest that AT III replacement in patients with shock and DIC is superior to the commonly used treatment with heparin. In addition, it was concluded that additional heparin does not improve the effect of AT III and is likely to be associated with thrombocytopenia and increased blood loss. Vinazzer et al. in 1986 (14) later presented data on 52 further patients with shock and DIC who were treated with various AT III concentrates, 15 of whom had received ANTITHROMBIN III IMMUNO. When the results of all patients admitted in shock phase IV were compared, there were 8 deaths out of 9 under heparin therapy, but only 7 out of 18 under AT III substitution. The authors conclude that this difference is of considerable clinical interest, although it does not permit statistical evaluation, since the two therapeutic regimens were given at different times.
In an open-label, prospective, controlled clinical study by Fagiano et al (1989) (15) the effect of AT III to reverse partial or complete failure to respond to heparin was investigated in three groups of patients (n=20 each) undergoing CABG surgery (group 1 - normal response – positive control, group 2 - reduced response -negative control, group 3 –r educed response and treatment with AT III IMMUNO). In the treatment group AT III replacement resulted in normalization of the response to heparin as well as of blood loss and the amount of blood transfused. The authors concluded from the results that treatment with AT III can achieve sufficient anticoagulation in patients with a decreased response to heparin to avoid the necessity of administering high doses of heparin and the resulting risk of bleeding complications.
Pharmacokinetics
Clinical evaluation of ANTITHROMBIN III IMMUNO for its in vivo recovery and half-life characteristics indicated that these parameters depend on the patient's clinical condition and coagulation status at the time of the infusion.
In normal individuals (1,2,3) and in asymptomatic patients with inherited AT III deficiency (4,5) the half-life of AT III is >2 days. During acute consumption coagulopathy (DIC), the half life may be reduced to only a few hours. For example, in two investigations of ANTITHROMBIN III IMMUNO (6,7), the mean 50% disappearance rate was found to be respectively 4.25 and 4.4 hours in patients with acute DIC vs. 20 and 25 hours in patients without DIC. Mean in vivo recovery was respectively 38% and 47% with acute DIC vs. 78% and 83% without acute DIC.
In these and other studies, in vivo recovery and half-life were investigated in a total number of 136 patients receiving ANTITHROMBIN III IMMUNO for treatment of different stages of shock. In these studies it was shown that in patients with disseminated intravascular cogulation (DIC), antithrombin III activity will rise by 1 % per unit ANTITHROMBIN III IMMUNO administered per kg body weight, whereas in antithrombin III-deficient patients without consumption coagulopathy the increase to be expected is 2%.
TOXICOLOGY
Humans
In the total of 365 patients in whom efficacy was evaluated either in clinical studies or case reports no product-related adverse drug events were reported.
In addition, pharomacoepidemiological surveillance shows that between the reporting period from January 1, 1990 to March 31, 1995, during which 269.2 million units ANTITHROMBIN III IMMUNO, Antithrombin III (human) were distributed world-wide, not a single product-related adverse event was reported to IMMUNO.
Viral safety was evaluated in a prospective, clinical study in which AT III recipients previously untreated with blood or blood products (PUP's) were followed up for transfusion-transmitted viral hepatitis using the criteria established by the International Society for Thrombosis and Haemostasis. 26 patients were evaluated for hepatitis non-A, non-B transmission and 27 for hepatitis B transmission. In addition 20 patients were evaluated for HCV seroconversion and 78 for HIV seroconversion. No case of product-related transmission of viral hepatitis or HIV was observed (10).
Animals
Single dose toxicity (16) was evaluated on 3 lots of ANTITHROMBlN III IMMUNO in NMRI mice using between 1250 and 5000 IU AT III per kg body weight. No animal died or showed toxic effects, even at the highest dose administered.
Abnormal toxicity is routinely tested on each batch of product in mice and guinea pigs within the framework of quality control.
Studies on subacute and chronic toxicity as well as studies on reproduction toxicity and mutagenic or tumorigenic potential were not performed since repeated administration of human antithrombin III would be likely to cause the formation of antibodies in the animals. Results obtained in the animal model would thus not allow extrapolation to humans.
ANTITHROMBIN III IMMUNO has not been reported to be associated with embryo-fetal toxicity, oncogenic or mutagenic potential.
Data on the efficacy of the steps during production to remove and/or inactivate viruses have been previously described in the chapter on "Clinical Pharmacology" (9).
REFERENCES
- 1. Carlsson T et al. (1985): In vivo behaviour of human radioiodinated antithrombin III: distribution among three physiologic pools. Blood 66/1, 13-19.
- 2. Collen D et al. (1977): Metabolism of antithrombin III (heparin cofactor) in man: effects of venous thrombosis and heparin administration. Eur. J. Clin. Invest. 7, 27-35.
- 3.
De Swart CAM et aI. (1984): Elimination of intravenously administered radiolabelled antithrombin
III and heparin in humans. Thromb. Haemostas. 52: 66-70.
- 4. Schwartz R et al. (1989): Clinical experience with antithrombin Ill concentrate in treatment of congenital and acquired deficiency of antithrombin. The American Journal of Medicine 87/88, 38-53S.
- 5. Menache D et al. (1990): Evaluation of the safety, recovery and half-life and clinical efficacy of antithrombin III (human) in patients with hereditary antithrombin III deficiency. Blood 75/1, 33-39.
- 6.
Blauhut B et aI. (1982): Substitution therapy with an antithrombin Ill concentrate in shock and
DIC. Thrombosis Research 27, 271-78.
- 7.
Vinazzer H (1983): Preliminary report on the recovery and on the biological half-of antithrombin
Ill. In: Wenzel E et al. (eds.): Antithrombin Ill - biochemistry, function, assay and clinical significance. Ann. Univ. Sarav. Med. Suppl. 3,185-87.
- 8. Blanco A et al. (1989): Prophylaxis during surgery in antithrombin III deficiency with low dose of concentrates. Thrombosis research 56; 497-499.
- 9. Data on File
- 10. Preiss D et al. (1991): Clinical results from safety studies with prothrombin complex concentrate and antithrombin III concentrate. Der Anästhesist 40/2.
- 11.
Bahrami S et al. (1989): Therapeutic modalities to ameliorate endotoxin-induced DIC in rats.
Second Vienna Shock Forum, 977-982.
- 12. Baudo F et al. (1995): Antithrombin III (ATIII) replacement therapy in patients with sepsis and/or post surgical complications requiring hemodynamic and/or respiratory support: a controlled, double blind, randomized, multicenter study. Abstract presented at XIlIth Meeting of the International Society of Haematology, 3-8 September 1995, Istanbul, Turkey.
- 13.
BIauhut B et al. (1985): Substitution therapy with an antithrombin III concentrate in shock and
DIC: a randomized study. Thrombosis Research 39,81-89.
- 14.
Vinazzer H et al. (1986): Further experience with ATIII substitution in shock and DIC. Thrombosis
Research. Suppl. VI. 131. 198.
- 15. Fagiano G et al. (1989). Prophylactic use of antithrombin III for protection of hemostatic balance in patients undergoing cardiopulmonary bypass. Abstract presented at the 4th annual meeting of the European Association of Cardiothoracic Anaesthesiology. Uppsala, Sweden, June 14-16, 1989.
- 16. Data on file
1 I.U. antithrombin III (as determined with a standard calibrated against the 2nd International Standard for ATIII (Human) in
Concentrates, Code 96/520) corresponds to the antithrombin III activity present in 1 mL of normal human plasma.
2 HIQ-PCR = Hyland Immuno Quality-Assured Polymerase Chain Reaction. With this method 500 genome equivalents/mL of the above viruses can be determined reliably, with the actual sensitivity of HIQ-PCR being below that. Therefore all pools which have been tested and evaluated as being positive lead to exclusion from further processing. No correlation has been demonstrated between infectivity and removal of pools containing these levels of genomic equivalents from further manufacturing.
3 Overall reduction factors were calculated as described in the EU CPMP Note for Guidance on Virus Validation Studies,
CPMP/BWF/268/95/Final