


Product Monograph - Heparin Sodium in 0.9% Sodium Chloride Injection
ACTION AND CLINICAL PHARMACOLOGY
Heparin inhibits reactions which lead to the clotting of blood and the formation of fibrin clots in vitro and in vivo. Heparin acts at multiple sites in the normal coagulation system. Small amounts of heparin, in combination with antithrombin III (heparin cofactor), can inhibit thrombosis by inactivating activated Factor X, and preventing the conversion of prothrombin to thrombin. Once active thrombosis has developed, larger amounts of heparin, in combination with antithrombin III, can inhibit further coagulation by inactivating thrombin and earlier clotting intermediates, thus preventing the conversion of fibrinogen to fibrin. Heparin also prevents the formation of stable fibrin clot by inhibiting the activation of the fibrin stabilizing factor.
Bleeding time is usually unaffected by heparin. Clotting time is usually not measurably affected by low doses, but is prolonged by full therapeutic doses of heparin.
Heparin is only active parenterally. In doses less than 5 000 units, heparin is primarily eliminated by hepatic metabolism. In larger doses, up to 50% is excreted unchanged in the urine.
The plasma half-life is approximately 1.5 hours; however, the half-life increases with increasing doses, ranging from approximately 1 hour with a dose of 100 units/kg to approximately 2.5 hours with a dose of 400 units/kg. The plasma half-life may be prolonged in patients with cirrhosis or severe renal impairment. Patients with pulmonary embolism may have a more rapid clearance of heparin.
Heparin is not removed by hemodialysis.
Heparin does not have fibrinolytic activity; therefore, it will not lyse existing clots.
INDICATIONS AND CLINICAL USE
HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION (2 USP Heparin Units/mL) is indicated as an anticoagulant in hemodialysis procedures.
CONTRAINDICATIONS
HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION should not be used in patients:
- With hypersensitivity to heparin or to any of the excipients or pork products (e.g. anaphylactoid reactions).
- With a history of heparin-induced thrombocytopenia or a history of thrombocytopenia with pentosane polysulfate;
- In whom suitable blood coagulation tests – e.g., the whole blood clotting time, partial thromboplastin time, etc., cannot be performed at appropriate intervals (this contraindication refers to full-dose heparin; there is usually no need to monitor coagulation parameters in patients receiving low-dose heparin);
- With an uncontrollable active bleeding state (see WARNINGS), except when this is due to disseminated intravascular coagulation.
WARNINGS
HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION is not intended for intramuscular use.
Hypersensitivity Patients with documented hypersensitivity to heparin should be given the drug only in clearly life-threatening situations.
Hemorrhage Hemorrhage can occur at virtually any site in patients receiving heparin. An unexplained drop in hematocrit, decrease in blood pressure or any other unexplained symptom should lead to serious consideration of hemorrhagic event.
Heparin should be used with extreme caution in disease states in which there is increased danger of hemorrhage. Some of the conditions in which increased danger of hemorrhage exists are:
- Cardiovascular: Subacute bacterial endocarditis, severe hypertension, arteriosclerosis.
- Surgical: During and immediately following (a) spinal tap or spinal anesthesia or (b) major surgery, especially involving the brain, spinal cord or eye.
- Hematologic: Conditions associated with increased bleeding tendencies, such as hemophilia, thrombocytopenia, and some vascular purpuras.
- Gastrointestinal: Ulcerative lesions and continuous tube drainage of the stomach or small intestine.
- Other: Menstruation, liver disease with impaired hemostasis.
Coagulation Testing When heparin is administered in therapeutic amounts, its dosage should be regulated by frequent blood coagulation tests. If the coagulation test is unduly prolonged or if hemorrhage occurs, heparin should be discontinued promptly (see SYMPTOMS AND TREATMENT OF OVERDOSAGE).
Thrombocytopenia Thrombocytopenia has been reported to occur in patients treated with heparin and may appear from 4-21 days after the start of treatment, although it may occur sooner if there is a history of heparin-induced thrombocytopenia; occurrence rates vary widely from 1 to 30%. Mild thrombocytopenia (count greater than 100 x 109/L) may remain stable or reverse even if heparin is continued. However, thrombocytopenia of any degree should be monitored closely. If the count falls below 100 x 109/L or if recurrent thrombosis develops (see PRECAUTIONS: White Clot Syndrome), heparin therapy should be discontinued.
Heparin-induced thrombocytopenia (HIT) may progress to the development of venous and arterial thromboses, a condition known as heparin-induced thrombocytopenia and thrombosis (HITT) the so-called “White-Clot Syndrome”. These serious thromboembolic events include deep vein thrombosis, pulmonary embolism, cerebral vein thrombosis, limb ischemia, stroke, myocardial infarction, renal arterial thrombosis, skin necrosis, gangrene of the extremities that may lead to amputation, and possibly death. Monitor thrombocytopenia of any degree closely.
It is therefore recommended that the platelet count be checked at the start of treatment with heparin and then monitored regularly until the end of treatment. Treatment should be discontinued and an alternative therapy should be initiated if the platelet count falls below 100,000/mm3, associated with positive or unknown in vitro platelet antibody test results in the presence of heparin or if recurrent thrombosis develop.
Delayed Onset of HIT and HITT
HIT and HITT can occur up to several weeks after the discontinuation of heparin therapy.
Epidural or Spinal Anesthesia
In patients undergoing epidural or spinal anesthesia, or lumbar puncture, the prophylactic use of heparin has been very rarely associated with epidural or spinal hematomas which may result in prolonged or permanent paralysis. The risk is increased by the use of epidural or spinal catheters for anesthesia, by concomitant use of drugs affecting coagulation such as nonsteroidal anti-inflammatory drugs (NSAIDs), platelet aggregation inhibitors and by traumatic or repeated punctures.
Hyperkalemia
Heparin can suppress adrenal secretion of aldosterone leading to hyperkalemia, in patients at risk of increased potassium levels such as patients with diabetes mellitus, renal insufficiency or taking drugs that may increase plasma potassium levels such as ACE inhibitors. The risk of hyperkalemia appears to increase with the duration of treatment, but is normally reversible.
Heparin Resistance
Resistance to heparin is encountered in patients with antithrombin III deficiency. Adjustment of heparin doses based on anti-Factor Xa levels may be warranted.
If continued heparin therapy is essential, administration of heparin from a different organ source can be reinstituted with caution.
Solutions containing sodium ions should be used with great care, if at all, in patients with congestive heart failure, severe renal insufficiency and in clinical states in which there exists edema with sodium retention.
The intravenous administration of these solutions can cause fluid and/or solute overloading, resulting in dilution of serum electrolyte concentrations, overhydration, congested states or pulmonary edema.
The risk of dilutional states is inversely proportional to the electrolyte concentration of administered parenteral solutions. The risk of solute overload causing congested states, with peripheral and pulmonary edema, is directly proportional to the electrolyte concentrations of such solutions.
In patients with diminished renal function, administration of solutions containing sodium ions may result in sodium retention.
Excessive administration of potassium-free solutions may result in significant hypokalemia.
As the dosage of HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION must be titrated to individual patient response, additive medications should not be delivered via this solution.
When heparin is used in conjunction with dialysis machines or where heparin is added to glucose or saline, it is most important that the pH is not less than 5 for heparin to act as an effective anticoagulant. At pH less than 5 and pH over 8.5, degradation occurs.
PRECAUTIONS
General
White Clot Syndrome It has been reported that patients on heparin may develop new thrombus formation in association with thrombocytopenia resulting from irreversible aggregation of platelets induced by heparin (“white clot syndrome”).
The process may lead to severe thromboembolic complications like skin necrosis, gangrene of the extremities that may lead to amputation, myocardial infarction, pulmonary embolism, stroke and possibly death. Therefore, heparin administration should be promptly discontinued if a patient develops new thrombosis in association with thrombocytopenia.
Heparin Resistance Increased resistance to heparin is frequently encountered in fever, thrombosis, thrombophlebitis, infections with thrombosing tendencies, myocardial infarction, cancer and in post-surgical patients.
Increased Risk in Older Women A higher incidence of bleeding has been reported in women over 60 years of age.
Use in Pregnancy Although heparin does not cross the placenta and is the anticoagulant of choice for use during pregnancy because it does not affect blood clotting mechanisms in the fetus, it should be administered with caution during pregnancy especially during the last trimester and withdrawn one or two days before the delivery date, due to the risk of fetal-maternal hemorrhage. Although heparin has not been reported to cause birth defects, use during pregnancy has been reported to increase the risk of stillbirth or prematurity. However, the underlying condition, rather than heparin itself, may have been responsible. Long-term usage of therapeutic doses of heparin during pregnancy may increase the risk of osteoporosis and vertebral fractures.
Careful monitoring of the patient and attention to dosage are recommended during pregnancy. Heparin requirements increase, because of expansion of the patient’s blood volume, as pregnancy progresses. Readjustment of heparin may be needed following delivery.
Use in Nursing Mothers Heparin is not excreted in human milk.
Drug Interactions
Drugs Increasing Effects of Heparin
Caution is recommended when heparin is administered concomitantly with other anticoagulant drugs, platelet aggregation inhibitors, systemic salicylates, glycoprotein IIb/IIIa antagonists, thienopyridines and dextrans. These drugs increase the pharmacological effect of heparin thereby increasing the risk of bleeding. Careful monitoring is advised if concomitant use cannot be avoided.
Concomitant use of thrombolytic agents such as alteplase, streptokinase may also increase the risk of hemorrhage.
Concomitant use of some contrast media may also affect the coagulation process and increase the risk of hemorrhage.
Heavy alcohol drinkers are at greater risk of major heparin associated bleeding than moderate or non-drinkers.
Drugs Antagonizing Effects of Heparin
Intravenous nitroglycerin administered to heparinized patients may result in a decrease of the partial thromboplastin time with subsequent rebound effect upon discontinuation of nitroglycerin. Careful monitoring of partial thromboplastin time and adjustment of heparin dosage are recommended during co-administration of heparin and intravenous nitroglycerin.
The concomitant use of heparin with andexanet alfa may reduce the effectiveness of heparin. Andexanet alfa, a recombinant modified human coagulation factor Xa used for reversal of anticoagulation with apixaban or rivaroxaban, has been shown to bind to heparin-bound antithrombin III (ATIII) and may reduce the anticoagulant effect of heparin. Unresponsiveness to unfractionated heparin leading to non-prolongation of activated clotting times and serious thrombotic events has occurred when unfractionated heparin was administered after use of andexanet alfa for the reversal of direct Factor Xa inhibitors (apixaban and rivaroxaban). Avoid use of heparin after use of andexanet alfa.
Diagnostic Interference Heparin may prolong the one-stage prothrombin time. Therefore, when heparin is given with dicumarol or warfarin sodium, a period of at least 5 hours after the last intravenous dose should elapse before blood is drawn, if a valid prothrombin time is to be obtained. Heparin may be used to prevent blood clotting during blood transfusions and in blood sampling for laboratory purposes. However, heparinized blood should not be used for isoagglutinin, complement, or for an erythrocyte fragility test, or for platelet counts. In addition, leukocyte counts should be performed within 2 hours after heparin is added to the blood sample.
Platelet Inhibitors Drugs such as acetylsalicylic acid, dextran, phenylbutazone, ibuprofen, indomethacin, dipyridamole, hydroxychloroquine and others that interfere with platelet-aggregation reactions (the main hemostatic defense of heparinized patients) may induce bleeding and should be used with caution in patients receiving heparin.
Effect of Heparin on Other Drugs
Heparin can increase the effect of oral antidiabetic agents such as sulfonylureas, as well as benzodiazepines (chlordiazepoxide, diazepam, oxazepam) and propranolol.
Other Interactions Digitalis, quinine, tetracyclines, nicotine, antihistamines, or intravenous (i.v.) nitroglycerin may partially counteract the anticoagulant action of heparin.
Drugs such as codeine phosphate, pethidine hydrochloride, streptomycin, erythromycin, kanamycin, neomycin, novobiocin, ampicillin, penicillins, glucocorticoids, polymyxin B, vancomycin, hydrocortisone sodium succinate, pentobarbitone, promazine hydrochloride, vitamin B complex and vitamin C may complex with heparin. This complex may be reversible (heparin rebound) and may result in excess bleeding at the surgical site. Extra protamine sulfate may then be indicated. Intravenously administered ethacrynic acid can cause gastrointestinal (G.I.) bleeding. However, a significantly higher incidence of G.I. bleeding has been attributed to the concurrent use of i.v. ethacrynic acid and heparin.
Drug/Laboratory Test Interactions
Hyperaminotransferasemia Significant elevations of aminotransferase (SGOT [S-AST] and SGPT [S-ALT]) levels have occurred in a high percentage of patients (and healthy subjects) who have received heparin. Since aminotransferase determinations are important in the differential diagnosis of myocardial infarction, liver disease, and pulmonary emboli, increased levels that might be caused by drugs (like heparin) should be interpreted with caution.
Laboratory Tests Periodic platelet counts, hematocrits and tests for occult blood in the stool are recommended during the entire course of heparin therapy.
Carcinogenesis, Mutagenesis, Impairment of Fertility No long-term studies in animals have been performed to evaluate the carcinogenic potential of heparin. Also, no reproduction studies in animals have been performed concerning mutagenesis or impairment of fertility.
ADVERSE REACTIONS
Hemorrhage Hemorrhage is the chief complication that may result from heparin therapy (see WARNINGS). An overly prolonged clotting time or minor bleeding during therapy can usually be controlled by withdrawing the drug (see SYMPTOMS AND TREATMENT OF OVERDOSAGE). It should be appreciated that gastrointestinal or urinary tract bleeding during anticoagulant therapy may indicate the presence of an underlying occult lesion. Bleeding can occur at any site but certain specific hemorrhagic complications may be difficult to detect:
- a) Adrenal hemorrhage, with resultant acute adrenal insufficiency, has occurred rarely during anticoagulant therapy. Therefore, such treatment should be discontinued in patients who develop signs and symptoms of acute adrenal hemorrhage and insufficiency. Initiation of corrective therapy should not depend on laboratory confirmation of the diagnosis, since any delay in an acute situation may result in the patient’s death.
- b) Ovarian (corpus luteum) hemorrhage developed in a number of women of reproductive age receiving short- or long-term anticoagulant therapy. This complication, if unrecognized, may be fatal.
- c) Retroperitoneal hemorrhage.
Local Irritation Local irritation, erythema, mild pain, hematoma or ulceration may follow deep subcutaneous (intrafat) injection of heparin. These complications are much more common after intramuscular use, and such use is not recommended.
Hypersensitivity Generalized hypersensitivity reactions have been reported, with chills, fever and urticaria as the most usual manifestations, and asthma, rhinitis, lacrimation, headache, nausea and vomiting, and anaphylactoid reactions, including shock, occurring more rarely. Itching and burning, especially on the plantar site of the feet, may occur.
Thrombocytopenia has been reported to occur in patients receiving heparin; occurrence rates vary widely from 1 to 30%. While often mild and of no obvious clinical significance, such thrombocytopenia can be accompanied by severe thromboembolic complications such as skin necrosis, gangrene of the extremities that may lead to amputation, myocardial infarction, pulmonary embolism, stroke, and possibly death (see WARNINGS and PRECAUTIONS).
Certain episodes of painful, ischemic and cyanosed limbs have, in the past, been attributed to allergic vasospastic reactions. Whether these are, in fact, identical to the thrombocytopenia-associated complications remains to be determined.
Miscellaneous Osteoporosis following long-term administration of high doses of heparin, cutaneous necrosis after systemic administration, suppression of aldosterone synthesis, delayed transient alopecia, priapism and hyperkalemia have occurred during therapy with heparin.
Rebound hyperlipemia may occur after administration of heparin is stopped.
Reactions which may occur because of heparin solution or the technique of administration include febrile response, infection at the site of injection, venous thrombosis or phlebitis extending from the site of injection, extravasation and hypervolemia, spinal hematoma and epidural hematoma.
If an adverse reaction does occur, discontinue the infusion, evaluate the patient, institute appropriate therapeutic countermeasures, and save the remainder of the fluid for examination, if deemed necessary.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms Bleeding is the chief sign of heparin overdosage. Nosebleeds, blood in the urine or tarry stools may be noted as the first sign of bleeding. Easy bruising or petechial formations may precede frank bleeding.
Treatment
Neutralization of Heparin Effect
When clinical circumstances (bleeding) require reversal of heparinization, protamine sulfate (1% solution), by slow infusion, will neutralize heparin. No more than 50 mg should be administered, very slowly, in any 10 minute period. Each mg of protamine sulfate neutralizes approximately 100 USP heparin units. The amount of protamine required decreases over time as heparin is metabolized. Although the metabolism of heparin is complex, it may, for the purpose of choosing a protamine dose, be assumed to have a half-life of about 1⁄2 hour after intravenous injection.
Administration of protamine sulfate can cause severe hypotensive and anaphylactoid reactions. Because fatal reactions often resembling anaphylaxis have been reported, the drug should be given only when resuscitation techniques and treatment of anaphylactoid shock are readily available.
In the event of overhydration or solute overload, re-evaluate the patient and institute appropriate corrective measures (see WARNINGS and PRECAUTIONS).
DOSAGE AND ADMINISTRATION
Heparin is not effective by oral administration and intravenous solutions with heparin should not be given orally. HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION should be administered by intravenous infusion, with the use of an infusion pump.
Heparinization of Hemodialysis Procedures Heparin administration procedures vary and are adjusted to the requirements of the individual patient by the attending physician, but a proper heparinization schedule must be initiated before and maintained throughout dialysis to prevent clotting and subsequent blood path obstruction.
Priming fluid should contain 2 000 USP heparin units/1 000 mL of 0.9% sodium chloride injection.
Note: Read dialyzer direction sheets and follow manufacturer’s directions for use. An infusion pump must be used to administer the medication.
INSTRUCTIONS FOR USE
To Open Tear outer wrap at notch and remove solution container.
Preparation for Administration (Use aseptic technique)
- 1. Close flow control clamp of administration set.
- 2. Remove cover from outlet port at bottom of container.
- 3. Insert piercing pin of administration set into port with a twisting motion until the set is firmly seated. Note: When using a vented administration set, replace bacterial retentive air filter with piercing pin cover. Insert piercing pin with twisting motion until shoulder of air filter housing rests against the outlet port flange.
- 4. Suspend container from hanger.
- 5. Squeeze and release drip chamber to establish proper fluid level in chamber.
- 6. Attach venipuncture device to set.
- 7. Open clamp to expel air from set and venipuncture device. Close clamp.
- 8. Perform venipuncture.
- 9. Regulate rate of administration with flow control clamp. Caution: Do not use flexible container in series connections. Use only if solution is clear and container undamaged. Additives should not be added to this solution. Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Heparin Sodium
Structural Formula:
Heparin Sodium (representative sub units)
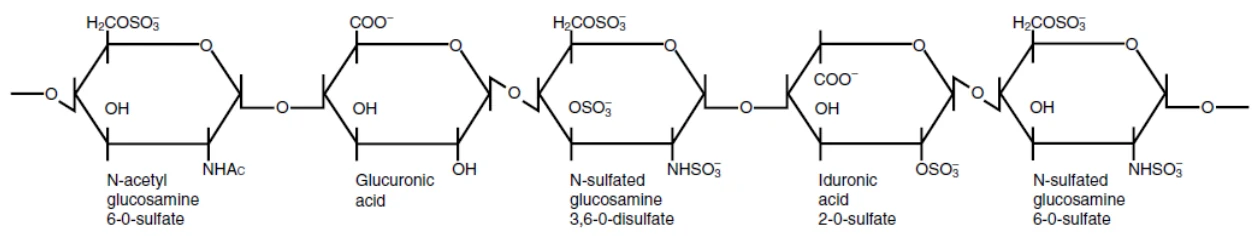
The antithrombin-binding structure of heparin
Description Heparin sodium is a white to greyish-brown amorphous powder that is odourless and hygroscopic. Heparin sodium is soluble in saline solution, alcohol and acetone; dissolves in water (1 g in 20 mL), but is practically insoluble in benzene, chloroform and ether.
Heparin Sodium is a heterogenous group of straight-chain anionic mucopolysaccharides, called glycosaminoglycans, having anticoagulant properties.
Heparin is strongly acidic because of its content of covalently linked sulfate and carboxylic acid groups. In heparin sodium, the acidic protons of the sulfate units are partially replaced by sodium ions. The potency is determined by a biological assay using a USP reference standard based on units of heparin activity per milligram.
Composition HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION is a sterile, nonpyrogenic solution of heparin sodium in flexible plastic containers. Each 100 mL contains heparin sodium 200 USP Heparin Units (porcine intestinal mucosa); sodium chloride 0.9 g, and, as buffers, citric acid monohydrate 40 mg and dibasic sodium phosphate heptahydrate 434 mg. Electrolytes mmol/L (mEq/L): Sodium 186.4 (186.4); phosphate 16.2 (32.4); citrate 1.9 (5.7) and chloride 154 (154). Osmolar concentration, 378 mOsm/L (calc.); pH 7.0 (approx.).
THIS FORMATION IS FOR INTRAVENOUS INFUSION ONLY.
Stability and Storage Recommendations Store between 20°C and 25°C. Protect from freezing.
AVAILABILITY OF DOSAGE FORMS
HEPARIN SODIUM IN 0.9% SODIUM CHLORIDE INJECTION is supplied in single-dose, flexible plastic containers as follows:
- 2 USP Heparin Units/mL in 500 mL (1000 USP Units/500 mL);
- 2 USP Heparin Units/mL in 1000 mL (2000 USP Units/1000 mL).
All primary packaging components are not made with natural rubber latex.
Last Revised: 2026-02-04