


Product Monograph - Apo-Emtricitabine-Tenofovir
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | Tablet Emtricitabine 200 mg/ Tenofovir Disoproxil Fumarate 300 mg | anhydrous lactose, colloidal silicon dioxide, crospovidone, FD&C Blue No. 2, magnesium stearate, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide. |
APO-EMTRICITABINE-TENOFOVIR tablets are a fixed-dose combination containing emtricitabine and tenofovir disoproxil fumarate.
INDICATIONS AND CLINICAL USE
Treatment of HIV-1 Infection
APO-EMTRICITABINE-TENOFOVIR is indicated in combination with other antiretroviral agents (such as non- nucleoside reverse transcriptase inhibitors or protease inhibitors) for the treatment of HIV-1 infection in adults.
Additional important information regarding the use of APO-EMTRICITABINE- TENOFOVIR for the treatment of HIV-1 infection:
- It is not recommended that APO-EMTRICITABINE-TENOFOVIR be used as a component of a triple nucleoside regimen.
APO-EMTRICITABINE-TENOFOVIR should not be coadministered with
EMTRIVA (emtricitabine), VIREAD (tenofovir disoproxil fumarate), ATRIPLA® (efavirenz/emtricitabine/tenofovir disoproxil fumarate), COMPLERA® (emtricitabine/rilpivirine/tenofovir disoproxil fumarate), STRIBILD® (elvitegravir/cobicistat/emtricitabine/tenofovir disoproxil fumarate) GENVOYA® (elvitegravir, cobicistat, emtricitabine, tenofovir alafenamide), DESCOVY® (emtricitabine and tenofovir alafenamide) , or lamivudine-containing products (see
WARNINGS AND PRECAUTIONS).
- In treatment-experienced patients, the use of APO-EMTRICITABINE- TENOFOVIR should be guided by laboratory testing and treatment history (see VIROLOGY).
Pre-Exposure Prophylaxis (PrEP) of HIV-1 Infection
APO-EMTRICITABINE-TENOFOVIR is indicated in combination with safer sex practices for PrEP to reduce the risk of sexually acquired HIV-1 infection in adults at high risk.
When considering APO-EMTRICITABINE-TENOFOVIR for PrEP, the following factors may help to identify individuals at high risk:
- has partner(s) known to be HIV-1 infected, or
engages in sexual activity within a high prevalence area or social network and one or more of the following:
- inconsistent or no condom use
- diagnosis of sexually transmitted infections
- exchange of sex for commodities (such as money, food, shelter, or drugs)
- use of illicit drugs or alcohol dependence
- incarceration
- partner(s) of unknown HIV-1 status with any of the factors listed above
When prescribing APO-EMTRICITABINE-TENOFOVIR for PrEP, healthcare providers must:
- prescribe APO-EMTRICITABINE-TENOFOVIR as part of a comprehensive prevention strategy because APO-EMTRICITABINE-TENOFOVIR is not always effective in preventing the acquisition of HIV-1 infection (see WARNINGS AND PRECAUTIONS);
counsel all uninfected individuals to strictly adhere to the recommended APO-
EMTRICITABINE-TENOFOVIR dosing schedule because the effectiveness of APO-EMTRICITABINE-TENOFOVIR in reducing the risk of acquiring HIV-1 was strongly correlated with adherence as demonstrated by measurable drug levels in clinical trials (see WARNINGS AND PRECAUTIONS);
confirm a negative HIV-1 test immediately prior to initiating APO-
EMTRICITABINE-TENOFOVIR for a PrEP indication. If clinical symptoms consistent with acute viral infection are present and recent (<1 month) exposures are suspected, delay starting PrEP for at least one month and reconfirm HIV-1 status or use a test approved by Health Canada as an aid in the diagnosis of HIV-1 infection, including acute or primary HIV-1 infection (see WARNINGS AND PRECAUTIONS); and
screen for HIV-1 infection at least once every 3 months while taking APO-
EMTRICITABINE-TENOFOVIR for PrEP.
This indication is based on clinical trials in men who have sex with men (MSM) at high risk for HIV-1 infection and in heterosexual serodiscordant couples (see CLINICAL TRIALS).
For more information on APO-EMTRICITABINE-TENOFOVIR for PrEP, log onto http://www.apotex.com/ca/en/.
Geriatrics (>65 years of age)
Clinical studies of emtricitabine or tenofovir disoproxil fumarate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
Pediatrics (<18 years of age)
Safety and effectiveness in pediatric patients have not been established.
CONTRAINDICATIONS
APO-EMTRICITABINE-TENOFOVIR is contraindicated in patients with previously demonstrated hypersensitivity to any of the components of the product. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
APO-EMTRICITABINE-TENOFOVIR is contraindicated for use as PrEP in individuals with unknown or positive HIV-1 status.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
- Lactic Acidosis and Severe Hepatomegaly with Steatosis
Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogs, including tenofovir disoproxil fumarate, a component of APO-EMTRICITABINE-TENOFOVIR, alone or in combination with other antiretrovirals (see WARNINGS AND PRECAUTIONS).
- Post-Treatment Exacerbation of Hepatitis B
APO-EMTRICITABINE-TENOFOVIR is not approved for the treatment of chronic hepatitis B virus (HBV) infection and the safety and efficacy of emtricitabine and tenofovir disoproxil fumarate have not been established in patients co-infected with HBV and HIV. Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with HBV and HIV and have discontinued emtricitabine and tenofovir disoproxil fumarate. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who are infected with HBV and discontinue APO-EMTRICITABINE-TENOFOVIR. If appropriate, initiation of anti-hepatitis B therapy may be warranted (see WARNINGS AND PRECAUTIONS).
- Nephrotoxicity
Renal impairment, including cases of acute renal failure and Fanconi syndrome (renal tubular injury with severe hypophosphatemia) has been reported with the use of emtricitabine/tenofovir disoproxil fumarate during clinical practice (see WARNINGS AND PRECAUTIONS).
Risk of Drug Resistance with Use of APO-EMTRICITABINE-TENOFOVIR for Pre-Exposure
Prophylaxis (PrEP) in Undiagnosed Early HIV-1 Infection
APO-EMTRICITABINE-TENOVOFIR used for a PrEP indication must only be prescribed to individuals confirmed to be HIV-negative immediately prior to initial use and periodically (at least every 3 months) during use. Drug-resistant HIV-1 variants have been identified with the use of emtricitabine/tenofovir disoproxil fumarate for a PrEP indication following undetected acute HIV-1 infection. Do not initiate APO-EMTRICITABINE-TENOFOVIR for a PrEP indication if signs or symptoms of acute HIV-1 infection are present unless negative infection status is confirmed (see WARNINGS AND PRECAUTIONS).
General
APO-EMTRICITABINE-TENOFOVIR should be used in the treatment of HIV-1 infected patients only in combination with other antiretroviral agents.
APO-EMTRICITABINE-TENOFOVIR is a fixed-dose combination of emtricitabine and tenofovir disoproxil fumarate. APO-EMTRICITABINE- TENOFOVIR should not be coadministered with other products containing tenofovir disoproxil fumarate or emtricitabine EMTRIVA (emtricitabine), VIREAD (tenofovir disoproxil fumarate), ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate), COMPLERA (emtricitabine/rilpivirine/tenofovir disoproxil fumarate) or STRIBILD (elvitegravir/cobicistat/emtricitabine/tenofovir disoproxil fumarate) or with medicinal products containing tenofovir alafenamide DESCOVY® (emtricitabine and tenofovir alafenamide) or GENVOYA® (elvitegravir, cobicistat, emtricitabine, tenofovir alafenamide). Due to similarities between emtricitabine and lamivudine, APO-EMTRICITABINE-TENOFOVIR should not be co-administered with other drugs containing lamivudine such as COMBIVIR® (lamivudine/zidovudine), 3TC® (lamivudine), HEPTOVIR® (lamivudine), KIVEXA® (abacavir sulfate and lamivudine), TRIUMEQ® (abacavir sulfate/dolutegravir sodium/lamivudine) or TRIZIVIR® (abacavir sulfate/lamivudine/zidovudine).
APO-EMTRICITABINE-TENOFOVIR should not be administered with HEPSERA® (adefovir dipivoxil).
Clinical studies in HIV-infected patients have demonstrated that certain regimens that only contain three nucleoside reverse transcriptase inhibitors (NRTI) are generally less effective than triple drug regimens containing two NRTIs in combination with either a non-nucleoside reverse transcriptase inhibitor or a HIV-1 protease inhibitor. In particular, early virological failure and high rates of resistance mutations have been reported. Triple nucleoside regimens should therefore be used with caution. Patients on a therapy utilizing a triple nucleoside-only regimen should be carefully monitored and considered for treatment modification.
Carcinogenesis, Mutagenesis, Impairment of Fertility
Emtricitabine: In long-term oral carcinogenicity studies of emtricitabine, no drug-related increase in tumor incidence was found in mice at doses up to 750 mg/kg/day (26 times the human systemic exposure at the therapeutic dose of 200 mg/day) or in rats at doses up to 600 mg/kg/day (31 times the human systemic exposure at the therapeutic dose).
Emtricitabine was not genotoxic in the reverse mutation bacterial test (Ames test), mouse
lymphoma or mouse micronucleus assays.
Emtricitabine did not affect fertility in male rats at approximately 140-fold or in male and female mice at approximately 60-fold higher exposures (AUC) than in humans given the recommended 200 mg daily dose. Fertility was normal in the offspring of mice exposed daily from before birth (in utero) through sexual maturity at daily exposures (AUC) of approximately 60-fold higher than human exposures at the recommended 200 mg daily dose.
Tenofovir disoproxil fumarate: Tenofovir disoproxil fumarate did not show any carcinogenic potential in a long-term oral carcinogenicity study in rats. A long-term oral carcinogenicity study in mice showed a low incidence of duodenal tumors, considered likely related to high local concentrations in the gastrointestinal tract at the high dose of 600 mg/kg/day. Liver adenomas were also seen at the high dose in female mice. The mechanism of tumor formation in mice and potential relevance for humans are uncertain.
Tenofovir disoproxil fumarate was mutagenic in the in vitro mouse lymphoma assay and negative in an in vitro bacterial mutagenicity test (Ames test). In an in vivo mouse micronucleus assay, tenofovir disoproxil fumarate was negative at doses up to 2000 mg/kg when administered orally to male mice.
There were no effects on fertility, mating performance or early embryonic development when tenofovir disoproxil fumarate was administered at 600 mg/kg/day to male rats for 28 days prior to mating and to female rats for 15 days prior to mating through day seven of gestation. There was, however, an alteration of the estrous cycle in female rats. A dose of 600 mg/kg/day is equivalent to 19 times the human dose based on body surface area comparisons.
Drug Interactions
Use with Certain HCV Regimens
Tenofovir exposure is increased when APO-EMTRICITABINE-TENOFOVIR is coadministered with HARVONI® (ledipasvir/sofosbuvir), EPCLUSA™ (sofosbuvir/velpatasvir), or VOSEVI™ (sofosbuvir/velpatasvir/voxilaprevir). Patients receiving APO-EMTRICITABINE-TENOFOVIR concomitantly with HARVONI (ledipasvir/sofosbuvir) or EPCLUSA™ (sofosbuvir/velpatasvir), particularly those at increased risk for renal dysfunction, should be monitored for tenofovir disoproxil fumarate-associated adverse reactions (see DRUG INTERACTIONS).
Use with Didanosine
Pharmacokinetic studies have shown that coadministration of didanosine and tenofovir disoproxil fumarate results in 40 to 60% increase in Cmax and AUC of didanosine (see Table 8). The mechanism of this interaction is unknown. Increases in didanosine concentrations of this magnitude could potentiate didanosine-associated adverse events, including pancreatitis, lactic acidosis, and neuropathy. In addition, suppression of CD4 counts has been observed in patients receiving tenofovir disoproxil fumarate with didanosine at a dose of 400 mg daily (see DRUG INTERACTIONS).
Endocrine and Metabolism
Serum Lipids and Blood Glucose
Serum lipid and blood glucose levels may increase during antiretroviral therapy. Disease control and life style changes may also be contributing factors. Consideration should be given to the measurement of serum lipids and blood glucose. Lipid disorders and blood glucose elevations should be managed as clinically appropriate.
Hepatic/Biliary/Pancreatic
Lactic Acidosis/Severe Hepatomegaly with Steatosis
Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of antiretroviral nucleoside analogs, including tenofovir disoproxil fumarate, a component of APO-EMTRICITABINE-TENOFOVIR, alone or in combination with other antiretrovirals in the treatment of HIV infection. A majority of these cases have been in women. Obesity and prolonged nucleoside exposure may be risk factors. Particular caution should be exercised when administering nucleoside analogs to any patient with known risk factors for liver disease; however, cases have also been reported in patients with no known risk factors. Treatment with APO-EMTRICITABINE-TENOFOVIR should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity (which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations).
Hepatic Impairment
Tenofovir and tenofovir disoproxil are not metabolized by liver enzymes. Clinically relevant pharmacokinetic changes in patients with hepatic impairment are not observed. Therefore, no dose adjustment is required in patients with hepatic impairment. Emtricitabine has not been evaluated in patients with hepatic impairment; however, emtricitabine has not been shown to be metabolized by liver enzymes, so the impact of liver impairment is likely to be limited. The safety and efficacy of emtricitabine/tenofovir disoproxil fumarate tablets has not been established or specifically studied in patients with underlying liver disorders.
Patients with chronic hepatitis B or C and treated with antiretroviral therapy are at increased risk for severe and potentially fatal hepatic adverse events. In case of concomitant antiviral therapy for hepatitis B or C, please refer also to the relevant product information for these medicinal products.
Hepatitis B Virus Infection
It is recommended that all patients be tested for the presence of hepatitis B virus (HBV) before initiating APO-EMTRICITABINE-TENOFOVIR. APO-EMTRICITABINE-TENOFOVIR is not approved for the treatment of chronic HBV infection and the safety and efficacy of emtricitabine/tenofovir disoproxil fumarate tablets have not been established in patients infected with HBV. Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with HBV and HIV after the discontinuation of emtricitabine/tenofovir disoproxil fumarate tablets. In some patients infected with HBV and treated with emtricitabine,
the exacerbations of hepatitis B were associated with liver decompensation and liver failure. Hepatic function should be closely monitored with both clinical and laboratory follow up for at least several months in patients who are infected with HBV and discontinue emtricitabine/tenofovir disoproxil fumarate tablets. If appropriate, initiation of anti-hepatitis B therapy may be warranted. In patients with advanced liver disease or cirrhosis, post-treatment exacerbation of hepatitis may lead to hepatic decompensation. Therefore, in these patients, discontinuation of treatment without initiation of alternative anti-hepatitis B therapy is not recommended.
Pancreatitis
Pancreatitis has occurred during therapy with combination regimens that included tenofovir disoproxil fumarate. Caution should be used when administering nucleoside analogues (including APO-EMTRICITABINE-TENOFOVIR) to patients with a history of pancreatitis or risk factors for the development of pancreatitis. Therapy should be suspended in patients with suspected pancreatitis.
Immune
Immune Reconstitution Inflammatory Syndrome
Immune reconstitution inflammatory syndrome has been reported in HIV-1 infected patients treated with combination antiretroviral therapy, including the components of APO-EMTRICITABINE-TENOFOVIR. During the initial phase of combination antiretroviral treatment, patients responding to antiretroviral therapy may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infections, cytomegalovirus, Pneumocystis jiroveci pneumonia (PCP), and tuberculosis), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves’ disease, polymyositis and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution; however, the reported time to onset is more variable, and these events can occur many months after initiation of treatment.
Musculoskeletal
Bone Effects
Bone Mineral Density
In a clinical trial in treatment-naive HIV-1 infected adults through 144 weeks, decreases from baseline in bone mineral density (BMD) were seen at the lumbar spine and hip in both tenofovir DF and stavudine treatment arms of the study; significantly greater decreases were seen in the lumbar spine measurement in the tenofovir DF group relative to the stavudine group. Clinically relevant fractures were reported in both treatment groups. Increases in biochemical markers of bone metabolism (serum bone-specific alkaline phosphatase, serum osteocalcin, serum C-telopeptide, and urinary N-telopeptide) were observed, suggesting increased bone turnover. Except for bone specific alkaline phosphatase, these changes resulted in values that remained within the normal range. These decreases in BMD and increases in biochemical markers of bone metabolism were also seen in the PrEP trials in HIV-1 uninfected
individuals. The effects of tenofovir DF-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk are unknown.
Assessment of BMD should be considered for patients who have a history of pathologic bone fracture or are at risk for osteopenia or osteoporosis. Although the effect of supplementation with calcium and vitamin D was not studied, such supplementation may be beneficial. If bone abnormalities are suspected then appropriate consultation should be obtained.
Mineralization Defects
Cases of hypophosphatemic osteomalacia associated with proximal renal tubulopathy, manifested as bone pain or pain in the extremities and which may contribute to fractures, have been reported in association with the use of tenofovir DF (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions). Arthralgias and muscle pain or weakness have also been reported in cases of proximal renal tubulopathy. Hypophosphatemia and osteomalacia secondary to proximal renal tubulopathy should be considered in patients at risk of renal dysfunction who present with persistent or worsening bone or muscle symptoms while receiving products containing tenofovir DF. Serum phosphate should be monitored in these patients.
Renal
Nephrotoxicity
Emtricitabine and tenofovir are principally eliminated by the kidney. Renal impairment, including cases of acute renal failure and Fanconi syndrome (renal tubular injury with severe hypophosphatemia) has been reported in association with the use of tenofovir DF in clinical practice. The majority of these cases occurred in patients with underlying systemic or renal disease, or in patients taking nephrotoxic agents; however, some cases occurred in patients without identified risk factors. Persistent or worsening bone pain, pain in extremities, fractures and/or muscular pain or weakness may be manifestations of proximal renal tubulopathy and should prompt an evaluation of renal function in at-risk patients. It is recommended that creatinine clearance be calculated in all patients prior to initiating therapy and as clinically appropriate during therapy with APO-EMTRICITABINE-TENOFOVIR. In patients at risk of renal dysfunction, including patients who have previously experienced renal events while receiving HEPSERA, it is recommended that calculated creatinine clearance, serum phosphorus, urine glucose, and urine protein be assessed prior to initiation of APO-EMTRICITABINE-TENOFOVIR, and periodically during APO-EMTRICITABINE-TENOFOVIR therapy (see ADVERSE REACTIONS, Post Market Adverse Drug Reactions and DRUG INTERACTIONS).
If serum phosphate is < 1.5 mg/dl (0.48 mmol/l) or creatinine clearance is decreased to < 50 ml/min in any patient receiving APO-EMTRICITABINE-TENOFOVIR, renal function should be re-evaluated within one week, including measurements of blood glucose, blood potassium and urine glucose concentrations. Consideration should also be given to interrupting treatment with APO-EMTRICITABINE-TENOFOVIR in patients with creatinine clearance decreased to < 50 ml/min or decreases in serum phosphate to < 1.0 mg/dl (0.32 mmol/l). Interrupting treatment with APO-EMTRICITABINE-TENOFOVIR should also be considered in case of progressive decline of renal function when no other cause has been identified (see ADVERSE
REACTIONS).
APO-EMTRICITABINE-TENOFOVIR should be avoided with concurrent or recent use of a nephrotoxic agent [eg, cidofovir, acyclovir, valacyclovir, ganciclovir, valganciclovir, aminoglycosides, high-dose or multiple non-steroidal anti-inflammatory drugs (NSAIDs)]. Cases of acute renal failure after initiation of high dose or multiple NSAIDs have been reported in HIV-1 infected patients with risk factors for renal dysfunction who appeared stable on tenofovir DF. Some patients required hospitalization and renal replacement therapy. Alternatives to NSAIDs should be considered, if needed, in patients at risk for renal dysfunction (see DRUG INTERACTIONS).
Renal Impairment
Treatment of HIV-1 infection
Dosing interval adjustment of APO-EMTRICITABINE-TENOFOVIR and close monitoring of renal function are recommended in all patients with creatinine clearance 30 to 49 mL/min. No safety and efficacy data are available in patients with renal dysfunction who received APO-EMTRICITABINE-TENOFOVIR using these guidelines, and so the potential benefit of APO-EMTRICITABINE-TENOFOVIR should be assessed against the potential risk of renal toxicity. APO-EMTRICITABINE-TENOFOVIR should not be administered to patients with creatinine clearance <30 mL/min or patients requiring hemodialysis (see DOSAGE AND ADMINISTRATION).
Pre-exposure Prophylaxis of HIV-1 infection
APO-EMTRICITABINE-TENOFOVIR for a PrEP indication should not be used in HIV-1 uninfected individuals with creatinine clearance below 60 mL/min.
If a decrease in creatinine clearance is observed in uninfected individuals while using APO-EMTRICITABINE-TENOFOVIR for PrEP, evaluate potential causes and re-assess potential risks and benefits of continued use (see DOSAGE AND ADMINISTRATION).
Special Populations
Pregnant Women
Antiretroviral Pregnancy Registry: To monitor fetal outcomes of pregnant women exposed to ART (antiretroviral therapy) including APO-EMTRICITABINE-TENOFOVIR, an Antiretroviral Pregnancy Registry has been established. Healthcare providers are encouraged to register patients by calling 800–258–4263.
Emtricitabine-tenofovir has been evaluated in a limited number of women during pregnancy and postpartum. Available human and animal data suggest that emtricitabine-tenofovir does not increase the risk of major birth defects overall compared to the background rate. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, APO-EMTRICITABINE-TENOFOVIR should be used in pregnant women only if the potential benefits outweigh the potential risks to the fetus. If an uninfected individual becomes pregnant while taking APO-
EMTRICITABINE-TENOFOVIR for a PrEP indication, careful consideration should be given to whether use of APO-EMTRICITABINE-TENOFOVIR should be continued, taking into account the potential increased risk of HIV-1 infection during pregnancy.
As of July 2015, the APR has received prospective reports of 1984 and 2608 exposures to emtricitabine- and tenofovir- containing regimens, respectively in the first trimester; and 949 and 1258 exposures, respectively, in second/third trimester, respectively. Birth defects occurred in 47 of 1984 (2.4%) live births for emtricitabine-containing regimens and 60 of 2608 (2.3%) live births for tenofovir-containing regimens (first trimester exposure); and 20 of 949 (2.1%) live births for emtricitabine-containing regimens and 26 of 1258 (2.1%) live births for tenofovir containing regimens (second/third trimester exposure). Among pregnant women in the U.S. reference population, the background rate of birth defects is 2.7%. There was no association between emtricitabine or tenofovir and overall birth defects observed in the APR.
Emtricitabine: The incidence of fetal variations and malformations was not increased in embryo-fetal toxicity studies performed with emtricitabine in mice at exposures (AUC) approximately 60-fold higher and in rabbits at approximately 120-fold higher than human exposures at the recommended daily dose.
Tenofovir disoproxil fumarate: Reproduction studies have been performed in rats and rabbits at doses up to 14 and 19 times the human dose based on body surface area comparisons and revealed no evidence of impaired fertility or harm to the fetus due to tenofovir. Reduced pup body weights, survival and delay in sexual maturation was observed in a peri- and postnatal toxicity study in rats at the maternally toxic doses of 450 and 600 mg/kg (approximately 14 and 19 times the human dose based on body surface area comparisons).
Nursing Women
HIV-infected mothers should not breastfeed their infants to avoid risking postnatal transmission of HIV to the infant.
In humans, samples of breast milk obtained from five HIV-1 infected mothers show that tenofovir is secreted in human milk at low levels (estimated neonatal concentrations 128 to 266 times lower than the tenofovir IC50). Tenofovir-associated risks, including the risk of developing viral resistance to tenofovir, in infants breastfed by mothers being treated with tenofovir disoproxil fumarate are unknown.
Samples of breast milk obtained from five HIV-1 infected mothers show that emtricitabine is secreted in human milk at estimated neonatal concentrations 3 to 12 times higher than the emtricitabine IC50 but 3 to 12 times lower than the Cmin achieved from oral administration of emtricitabine. Breast-feeding infants whose mothers are being treated with emtricitabine may be at risk for developing viral resistance to emtricitabine. Other emtricitabine-associated risks in infants breastfed by mothers being treated with emtricitabine are unknown.
Because of both the potential for HIV transmission and the potential for serious adverse reactions in nursing infants, mothers should be instructed not to breastfeed if they are receiving APO-EMTRICITABINE-TENOFOVIR, whether they are taking APO-
EMTRICITABINE-TENOFOVIR for treatment or to reduce the risk of acquiring HIV-1.
Pediatrics (<18 years of age)
Safety and effectiveness in pediatric patients have not been established.
Geriatrics (>65 years of age)
Clinical studies of emtricitabine or tenofovir disoproxil fumarate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently than younger subjects. In general, dose selection for the elderly patient should be cautious, keeping in mind the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
PrEP to Reduce the Risk of Acquiring HIV-1 Infection
Comprehensive HIV-1 Infection Prevention Strategy
Use APO-EMTRICITABINE-TENOFOVIR for PrEP only as part of a comprehensive prevention strategy that includes other prevention measures, such as safer sex practices, because APO-EMTRICITABINE-TENOFOVIR is not always effective in preventing the acquisition of HIV-1 (see CLINICAL TRIALS).
Counsel uninfected individuals about safer sex practices that include consistent and correct use of condoms, knowledge of their HIV-1 status and that of their partner(s), and regular testing for other sexually transmitted infections that can facilitate HIV-1 transmission (such as syphilis and gonorrhea).
- Inform uninfected individuals about and support their efforts in reducing sexual risk behavior.
Risk of Resistance
Use APO-EMTRICITABINE-TENOFOVIR to reduce the risk of acquiring HIV-1 only in individuals confirmed to be HIV-negative prior to initiating PrEP and re-confirmed routinely while taking PrEP. HIV-1 resistance substitutions may emerge in individuals with undetected HIV-1 infection who are taking only APO-EMTRICITABINE-TENOFOVIR, because APO-EMTRICITABINE-TENOFOVIR alone does not constitute a complete treatment regimen for HIV-1 treatment; therefore, care should be taken to minimize drug exposure in HIV-infected individuals (see VIROLOGY: Resistance).
Many HIV-1 tests, such as rapid tests, detect anti-HIV antibodies and may not identify
HIV-1 during the acute stage of infection. Prior to initiating APO-EMTRICITABINE-TENOFOVIR for a PrEP indication, evaluate seronegative individuals for current or recent signs or symptoms consistent with acute viral infections (e.g., fever, fatigue, myalgia, skin rash, etc.) and ask about potential exposure events (e.g., unprotected, or condom broke during sex with an HIV-1 infected partner) that may have occurred within the last month.
- If clinical symptoms consistent with acute viral infection are present and recent (<1
- While using APO-EMTRICITABINE-TENOFOVIR for a PrEP indication, HIV-1 screening tests should be repeated at least every 3 months. If symptoms consistent with acute HIV-1 infection develop following a potential exposure event, PrEP should be discontinued until negative infection status is confirmed using a test approved by Health Canada as an aid in the diagnosis of HIV-1, including acute or primary HIV-1 infection.
Counsel uninfected individuals to strictly adhere to the recommended APO-EMTRICITABINE-TENOFOVIR dosing schedule. The effectiveness of APO-EMTRICITABINE-TENOFOVIR in reducing the risk of acquiring HIV-1 is strongly correlated with adherence as demonstrated by measurable drug levels in clinical trials (see CLINICAL TRIALS). For more information on APO-EMTRICITABINE-TENOFOVIR for PrEP, log onto http://www.apotex.com/ca/en/.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Reactions from Clinical Trials Experience in HIV-1 Infected Subjects
Emtricitabine/tenofovir disoproxil fumarate tablets: Four hundred and forty-seven HIV-1 infected patients have received combination therapy with emtricitabine or tenofovir disosproxil fumarate with either a non-nucleoside reverse transcriptase inhibitor or protease inhibitor for 48 weeks in ongoing clinical studies. Study 934 - Treatment Emergent Adverse Events: Assessment of adverse reactions is based on data from Study 934 in which 511 antiretroviral-naïve patients received either emtricitabine + tenofovir disoproxil fumarate administered in combination with efavirenz (N=257) or Combivir®(lamivudine/zidovudine) administered in combination with efavirenz (N=254). Adverse events observed in this study were generally consistent with those seen in other studies in treatment experienced or treatment-naïve patients (Table 1).
Table 1. Selected Treatment-Emergent Adverse Events (Grades 2–4)
Reported in ≥3% in Any Treatment Group in Study 934 (0–48 Weeks)
Emtricitabine+Tenofovir
Disoproxil Fumarate+EFV
AZT/3TC+EFV
N=257 N=254
Blood and Lymphatic System Disorders
Anemia
<1%
5% Gastrointestinal Disorder
Diarrhea
Nausea
Vomiting
7%
8%
1%
4%
6%
4% General Disorders and Administration
Site Condition
Fatigue
7%
6% Infections and Infestations
Sinusitis
Upper respiratory tract infections
Nasopharyngitis
4%
3%
3%
2%
3%
1% Nervous System Disorders
Somnolence
Headache
Dizziness
3%
5%
8%
2%
4%
7% Psychiatric Disorders
Depression
Insomnia
Abnormal dreams
4%
4%
4%
7%
5%
3% Skin and Subcutaneous Tissue
Disorders
Rash 5% 4% Patients who received treatment up to 144 weeks in Study 934 reported adverse events similar in nature and severity to those reported in the first 48 weeks.
Through 48 weeks, 7 patients in the emtricitabine + tenofovir disoproxil fumarate group and 5 patients in the lamivudine/zidovudine group experienced a new CDC Class C event (10 and 6 patients, respectively, through 144 weeks). Renal safety assessed by laboratory abnormalities was similar in the two groups and no patient discontinued study drug due to renal events. At Weeks 48 and 144, total limb fat (as measured by dual-energy x-ray absorptiometry) was significantly less in a subgroup of patients in the lamivudine/zidovudine group compared to the tenofovir/emtricitabine subgroup (see Table 2).
Table 2. Study 934 Total Limb Fat at Week 48 and 144 (Dual-Energy
X-Ray Absorptiometry)
Emtricitabine + Tenofovir
Disoproxil Fumarate + EFV
AZT/3TC +EFV
Week 481 N=51 N=49 Total Limb Fat (kg)
(Mean ± S.D.)
8.9 ±5.4 6.9 ±3.9
Week 1442 N=145 N=124 Total Limb Fat (kg)
(Mean ± S.D.)
9.2 ±5.4 6.5 ±4.3
1P=0.03 for the comparison between arms
2P<0.001 for the comparison between arms
Laboratory Abnormalities: Laboratory Abnormalities observed in this study were generally consistent with those seen in other studies (Table 3).
Table 3. Grade 3/4 Laboratory Abnormalities Reported in ≥1% in Any
Treatment Group in Study 934 (0–48 Weeks)
Emtricitabine+Tenofovir
Disoproxil Fumarate+EFV
N=257
AZT/3TC+EFV
N=254
Any ≥ Grade 3 Laboratory
Abnormality 25% 22%
Fasting Cholesterol
(>240 mg/dL) 15% 17%
Creatine Kinase
(M: > 990 U/L)
(F: >845 U/L)
7%
6%
Serum Amylase (>175U/L) 7% 3% Alkaline Phosphatase (>550 U/L) 1% 0% AST
(M: >180 U/L)
(F: >170 U/L)
3%
2%
ALT
(M: >215 U/L)
(F: >170 U/L)
2%
2%
Hemoglobin (< 8.0 mg/dL) 0% 3% Hyperglycemia (> 250 mg/dl) 1% 1% Hematuria (>75 RBC/HPF) 2% 2% Neutrophil (>750/mm3) 3% 4% Fasting Triglycerides
(>750 mg/dL) 4% 2%
Laboratory abnormalities in patients who received treatment up to 144 weeks in Study 934 were consistent with those observed in the first 48 weeks of treatment.
In addition to the events described above for Study 934, other adverse events that occurred in at least 3 to 5% of patients receiving emtricitabine or tenofovir disoproxil fumarate with other antiretroviral agents in clinical trials include: anorexia, anxiety, arthralgia, asthenia, increased cough, depressive disorders, dyspepsia, fever, flatulence, myalgia, pain, abdominal pain, back pain, chest pain, paresthesia, peripheral neuropathy (including peripheral neuritis and neuropathy), pneumonia, rhinitis and rash event (including rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, pustular rash and allergic reaction), sweating and weight loss.
Skin discoloration has been reported with higher frequency among emtricitabine treated patients. Skin discoloration, mainly manifested by hyperpigmentation on the palms and/or soles was generally mild and asymptomatic and of little clinical significance. The mechanism is unknown.
In addition to the laboratory abnormalities described above for Study 934, Grade 3/4 elevations of bilirubin (>2.5 x ULN), pancreatic amylase (>2.0 x ULN), serum glucose (<40 or >250 mg/dL), serum lipase (>2.0 x ULN), and urine glucose (≥3+) occurred in up to 3% of patients treated with emtricitabine or tenofovir disoproxil fumarate with other antiretroviral agents in clinical trials.
For more information, please consult the emtricitabine and tenofovir disoproxil fumarate Product Monographs.
In Study 903 through 144 weeks, decreases from baseline in bone mineral density (BMD) were seen at the lumbar spine and hip in both arms of the study. At Week 144, there was a significantly greater mean percentage decrease from baseline in BMD at the lumbar spine in patients in the tenofovir disoproxil fumarate group compared with patients in the stavudine group (see Table 4). In both groups, the majority of the reduction in BMD occurred in the first 24 to 48 weeks of the study and this reduction was sustained through Week 144. Twenty-eight percent of tenofovir disoproxil fumarate-treated patients vs. 21% of the stavudine-treated patients lost at least 5% of BMD at the spine or 7% of BMD at the hip. Clinically relevant fractures (excluding fingers and toes) were reported in 4 patients in the tenofovir disoproxil fumarate group and 6 patients in the stavudine group. In addition, there were significant increases in biochemical markers of bone metabolism (serum bone-specific alkaline phosphatase, serum osteocalcin, serum C-telopeptide, and urinary N-telopeptide) in the tenofovir disoproxil fumarate group relative to the stavudine group, suggesting increased bone turnover. Serum parathyroid hormone levels and 1,25 Vitamin D levels were also higher in the tenofovir disoproxil fumarate group. Except for bone specific alkaline phosphatase, these changes resulted in values that remained within the normal range. The effects of tenofovir disoproxil fumarate- associated changes in BMD and biochemical markers on long-term bone health and future fracture risk are unknown.
Table 4 Changes in Bone Mineral Density Study 903
Mean Percent Change (±SD) to Week 144 in BMD
Tenofovir Disoproxil
Fumarate + 3TC+ EFV
d4T + 3TC +EFV
Lumbar Spine –2.2% ± 3.9 –1.0% ± 4.6 Hip –2.8% ± 3.5 –2.4% ± 4.5
Adverse Reactions from Clinical Trials Experience in HIV-1 Uninfected Adult Subjects (PrEP)
No new adverse reactions to emtricitabine/tenofovir disoproxil fumarate were identified from two randomized placebo-controlled clinical trials (iPrEx, Partners PrEP) in which 2830 HIV-1 uninfected adults received emtricitabine/tenofovir disoproxil fumarate tablets once daily for pre-exposure prophylaxis. Subjects were followed for a median of 71 weeks and 87 weeks, respectively. These trials enrolled HIV-negative individuals ranging in age from 18 to 67 years. The iPrEx trial enrolled only men or transgender women of Hispanic/Latino (72%), White (18%), Black (9%) and Asian (5%) race. The Partners PrEP trial enrolled both men (61 to 64% across treatment groups) and women in Kenya and Uganda. Table 5 provides a list of all adverse events that occurred ≥2% of subjects in any treatment group in the iPrEx and Partners PrEP trials.
Table 5 Selected Adverse Events (All Grades) Reported in ≥2% of
Uninfected individuals in Any Treatment Group in the iPrEx Trial and Partners PrEP Trial
| iPrEx Trial | Partners PrEP Trial | |||
| FTC/TDF N=1251 | Placebo N=1248 | FTC/TDF N=1579 | Placebo N=1584 | |
| Gastrointestinal Disorder | ||||
| Diarrhea | 7% | 8% | 2% | 3% |
| Abdominal pain | 4% | 2% | -a | - |
| Infections and Infestations | ||||
| Pharyngitis | 13% | 16% | - | - |
| Urethritis | 5% | 7% | - | - |
| Urinary tract infection | 2% | 2% | 5% | 7% |
| Syphilis | 6% | 5% | - | - |
| Secondary syphilis | 6% | 4% | - | - |
| Anogenital warts | 2% | 3% | - | - |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Back pain | 5% | 5% | - | - |
| Nervous System Disorders | ||||
| Headache | 7% | 6% | - | - |
| Psychiatric Disorders | ||||
| Depression | 6% | 7% | - | - |
| Anxiety | 3% | 3% | - | - |
| Reproductive System and Breast Disorders | ||||
| Genital ulceration | 2% | 2% | 2% | 2% |
| Investigations | ||||
| Weight decreased | 3% | 2% | - | - |
a. Not reported or reported below 2%.
Laboratory Abnormalities: Table 6 provides a list of laboratory abnormalities observed in both PrEP trials. Six subjects in the TDF-containing arms of the Partners PrEP trial discontinued participation in the study due to an increase in blood creatinine compared with no discontinuations in the placebo group. One subject in the emtricitabine/tenofovir disoproxil fumarate arm of the iPrEx trial discontinued from the study due to an increase in blood creatinine and another due to low phosphorus.
Table 6 Laboratory Abnormalities (Highest Toxicity Grade) Reported for
Each Subject in the iPrEx Trial and Partners PrEP Trial
| Gradeb | iPrEx Trial | Partners PrEP Trial | |||
| FTC/ TDF N=1251 | Placebo N=1248 | FTC/ TDF N=1579 | Placebo N=1584 | ||
| Creatinine | 1 (1.1-1.3 X ULN) | 27 (2%) | 21 (2%) | 18 (1%) | 12 (<1%) |
| 2-4 (> 1.4 x ULN) | 5 (<1%) | 3 (<1%) | 2 (<1%) | 1 (<1%) | |
| Phosphorus | 1 (2.5 - <LLN mg/dL) | 81 (7%) | 110 (9%) | NRa | NRa |
| 2-4 (<2.0 mg/dL) | 123 (10%) | 101 (8%) | 140 (9%) | 136 (9%) | |
| AST | 1 (1.25-<2.5 x ULN) | 175 (14%) | 175 (14%) | 20 (1%) | 25 (2%) |
| 2-4 (> 2.6 x ULN) | 57 (5%) | 61 (5%) | 10 (<1%) | 4 (<1%) | |
| ALT | 1 (1.25-<2.5 x ULN) | 178 (14%) | 194 (16%) | 21 (1%) | 13 (<1%) |
| 2-4 (> 2.6 x ULN) | 84 (7%) | 82 (7%) | 4 (<1%) | 6 (<1%) | |
| Hemoglobin | 1 (8.5 - 10 mg/dL) | 49 (4%) | 62 (5%) | 56 (4%) | 39 (2%) |
| 2-4 (<9.4 mg/dL) | 13 (1%) | 19 (2%) | 28 (2%) | 39 (2%) | |
| Neutrophils | 1 (1000-1300/mm3) | 23 (2%) | 25 (2%) | 208 (13%) | 163 (10%) |
| 2-4 (<750/mm3) | 7 (<1%) | 7 (<1%) | 73 (5%) | 56 (3%) | |
a. Grade 1 phosphorus was not reported for the Partners PrEP trial. b. Grading is per DAIDS criteria.
In addition to the laboratory abnormalities described above, Grade 1 proteinuria (1+) occurred in 6% of subjects receiving emtricitabine/tenofovir disoproxil fumarate in the iPrEx trial. Grade 2-3 proteinuria (2-4+) and glycosuria (3+) occurred in less than 1% of subjects treated with emtricitabine/tenofovir disoproxil fumarate in the iPrEx trial and Partners PrEP trial.
In clinical trials of HIV-1 uninfected individuals, decreases in BMD were observed. In the iPrEx trial, a substudy of 503 subjects found mean changes from baseline in BMD ranging from -0.4% to -1.0% across total hip, spine, femoral neck, and trochanter in the emtricitabine/tenofovir disoproxil fumarate group compared with the placebo group, which returned toward baseline after discontinuation of treatment. Thirteen percent of subjects receiving emtricitabine/tenofovir disoproxil fumarate vs. 6% of subjects receiving placebo lost at least 5% of BMD at the spine during treatment. Bone fractures were reported in 1.7% of the emtricitabine/tenofovir disoproxil fumarate group compared with 1.4% in the placebo group. No correlation between BMD and fractures was noted. The Partners PrEP trial found similar fracture rates between treatment and placebo groups (0.8% and 0.6%, respectively). No BMD evaluations were conducted during this trial (see CLINICAL TRIALS).
Post Market Adverse Drug Reactions
Emtricitabine: The following adverse experiences have been reported in post-marketing experience without regard to causality. Because these events are voluntarily reported from a population of unknown size, estimates of frequency cannot be made. These events have been considered possible adverse reactions due to a combination of their seriousness, frequency of reporting or potential causal relationship with treatment.
Blood and lymphatic system disorders: Thrombocytopenia
Gastrointestinal disorders: Pancreatitis
General disorders and administrative site Pyrexia
conditions:
Metabolism and nutrition disorders: Lactic acidosis
Tenofovir disoproxil fumarate: The following adverse reactions have been identified during post-approval use of tenofovir disoproxil fumarate. Because these events have been reported voluntarily from a population of unknown size, estimates of frequency cannot be made. These events have been considered possible adverse reactions due to a combination of their seriousness, frequency of reporting or potential causal relationship with tenofovir disoproxil fumarate.
Immune system disorders: Allergic reaction (including angioedema)
Metabolism and nutrition disorders: Lactic acidosis, hypokalemia, hypophosphatemia,
Respiratory, thoracic and mediastinal disorders: Dyspnea
Gastrointestinal disorders: Pancreatitis, increased amylase, abdominal pain
Blood and lymphatic system disorders: Thrombocytopenia
Hepatobiliary disorders: Hepatic steatosis, hepatitis, increased liver enzymes (most commonly AST, ALT, GGT)
Skin and Subcutaneous Tissue Disorders: Rash
Musculoskeletal and Connective Tissue
Disorders:
Rhabdomyolysis, osteomalacia (manifested as bone pain and infrequently contributing to fractures), muscular weakness, myopathy
Renal and urinary disorders: Acute renal failure, renal failure, acute tubular necrosis, Fanconi syndrome, proximal renal tubulopathy, interstitial nephritis (including acute cases), nephrogenic diabetes insipidus, renal insufficiency, increased creatinine, proteinuria, polyuria
General Disorders and Administration Site
Conditions
Asthenia
The following adverse reactions, listed under the body system headings above, may occur as a consequence of proximal renal tubulopathy: rhabdomyolysis, osteomalacia (manifested as bone pain and infrequently contributing to fractures), hypokalemia, muscular weakness, myopathy, hypophosphatemia.
There have been three post marketing reports of acute renal failure in patients on concomitant NSAIDS therapy where a relationship to tenofovir disoproxil fumarate could not be excluded. These events mostly occurred in medically complex patients, where underlying disease processes confound interpretation.
Emtricitabine and Tenofovir Disoproxil Fumarate: In HIV-infected patients with severe immune deficiency at the time of initiation of antiretroviral therapy an inflammatory reaction to infectious pathogens (active or inactive) may arise (see WARNINGS AND PRECAUTIONS).
In HIV infected patients coinfected with HBV, clinical and laboratory evidence of exacerbations of hepatitis has occurred after discontinuation of treatment (see WARNINGS AND PRECAUTIONS).
DRUG INTERACTIONS
Overview
No drug interaction studies have been conducted using emtricitabine/tenofovir disoproxil fumarate tablets. Drug interaction trials have been conducted with emtricitabine and tenofovir disoproxil fumarate, the components of APO-EMTRICITABINE-TENOFOVIR tablets.
The steady state pharmacokinetics of emtricitabine and tenofovir were unaffected when emtricitabine and tenofovir disoproxil fumarate were administered together versus each agent dosed alone (see Table 9 and Table10).
In vitro and clinical pharmacokinetic drug-drug interaction studies have shown that the potential for CYP450 mediated interactions involving emtricitabine and tenofovir with other medicinal products is low.
Drug-Drug Interactions
Established and Other Potentially Significant Drug Interactions
The drug interactions described are based on studies conducted with the individual agents of APO-EMTRICITABINE-TENOFOVIR and/or in combination, or are potential drug interactions that may occur with APO-EMTRICITABINE-TENOFOVIR.
Table 7. Established and Other Potentially Significanta Drug Interactions
Concomitant Drug
Class: Drug Name
Effect on Concentrationb
Clinical Comment
Antiretroviral Agents:
Didanosine ↑ didanosine Pharmacokinetic studies have shown that coadministration of didanosine and tenofovir disoproxil fumarate results in 40 to 60% increase in Cmax and AUC of didanosine (see Table 8). The mechanism of this interaction is unknown. Increases in didanosine concentrations of this magnitude could potentiate didanosine-associated adverse events, including pancreatitis, lactic acidosis, and neuropathy.
In addition, suppression of CD4 counts has been observed in patients receiving tenofovir disoproxil fumarate with didanosine at a dose of 400 mg daily.
A reduced dose of Videx EC® (ddl-EC) is recommended when coadministered with APO-EMTRICITABINE-TENOFOVIR. When coadministered with APO-EMTRICITABINE-TENOFOVIR, the Videx EC® (didanosine) Product Monograph recommends a reduced dose
of 250 mg ddI-EC for HIV infected adults with body weight ≥60 kg and creatinine clearance ≥60 mL/min. For patients with body weight <60 kg, and creatinine clearance ≥60 mL/min, the recommended dose of ddI-EC is 200 mg. Data are not available to recommend a dose adjustment for patients with creatinine clearance <60mL/min or for the buffered tablet formulation of didanosine (Videx®).
Caution should be used when coadministering reduced-dose didanosine, tenofovir, and an NNRTI in treatment-naïve patients with high viral loads at baseline since such use has been associated with reports of a high rate of virologic failure and emergence of resistance at an early stage. All patients receiving tenofovir disoproxil fumarate and didanosine
concomitantly should be closely monitored for didanosine-related adverse events and clinical response.
Atazanavir/ritonavir
Darunavir/ritonavir
Lopinavir/ritonavir
↑ tenofovir Atazanavir/ritonavir, darunavir/ritonavir and lopinavir/ritonavir have been shown to increase tenofovir concentrations (see Table 11). The mechanism of this interaction is unknown. Higher tenofovir concentrations could potentiate tenofovir-associated adverse events, including renal disorders. Patients receiving atazanavir/ritonavir, darunavir/ritonavir or lopinavir/ritonavir and APO-EMTRICITABINE-TENOFOVIR should be monitored for APO-EMTRICITABINE-TENOFOVIR-associated adverse events.
Atazanavir ↓ atazanavir Tenofovir decreases atazanavir concentrations (see
Table 12). Although safety and efficacy data are limited, it is recommended that atazanavir, without ritonavir, should not be coadministered with APO-EMTRICITABINE-TENOFOVIR. The recommended regimen is atazanavir 300 mg given with ritonavir 100 mg when used in combination with APO-EMTRICITABINE-TENOFOVIR (all as a single daily dose with food).
Hepatitis C Virus Antiviral Agents:
Ledipasvir/sofosbuvir
Sofosbuvir/velpatasvir
Sofosbuvir/velpatasvir/
voxilaprevir
↑ tenofovir Coadministration of tenofovir disoproxil fumarate and HARVONI (ledipasvir/sofosbuvir), EPCLUSA (sofosbuvir/velpatasvir), or VOSEVI (sofosbuvir/velpatasvir/voxilaprevir) has been shown to increase tenofovir exposure (see Table 11). Patients receiving a regimen containing tenofovir disoproxil fumarate concomitantly with HARVONI (ledipasvir/sofosbuvir), EPCLUSA (sofosbuvir/velpatasvir), or VOSEVI (sofosbuvir/velpatasvir/voxilaprevir) should be monitored for adverse reactions associated with tenofovir disoproxil fumarate (see WARNINGS AND PRECAUTIONS, Drug Interactions).
a This table is not all inclusive.
b ↑= increase, ↓= decrease
Drugs Affecting Renal Function
Emtricitabine and tenofovir are primarily excreted by the kidneys by a combination of glomerular filtration and active tubular secretion. No drug-drug interactions due to competition for renal excretion have been observed. Since emtricitabine and tenofovir are primarily eliminated by the kidneys, coadministration of APO-EMTRICITABINE-TENOFOVIR with drugs that reduce renal function or compete for active tubular secretion may increase serum concentrations of emtricitabine, tenofovir, and/or other renally eliminated drugs. Some examples include, but are not limited to cidofovir, acyclovir, valacyclovir, ganciclovir, valganciclovir, aminoglycosides and high-dose or multiple NSAIDs.
APO-EMTRICITABINE-TENOFOVIR should not be administered with HEPSERA (adefovir dipivoxil) (see WARNINGS AND PRECAUTIONS, General).
Drugs without Clinically Significant Interactions with APO-EMTRICITABINE-TENOFOVIR
No clinically significant drug interactions have been observed between emtricitabine and famciclovir, indinavir, zidovudine, stavudine, and tenofovir disoproxil fumarate, sofosobuvir, ledipasvir/sofosbuvir, sofosbuvir/velpatasvir, and sofosbuvir/velpatasvir/voxilaprevir (see Table 9 and Table10). Similarly, no clinically significant drug interactions have been observed between tenofovir disoproxil fumarate and abacavir, efavirenz, emtricitabine, entecavir, indinavir, lamivudine, methadone, nelfinavir, oral contraceptives, ribavirin, saquinavir/ ritonavir, sofosbuvir and tacrolimus in studies conducted in healthy volunteers (see Table 11 and Table12).
Assessment of Drug Interactions
Drug-drug interaction studies were conducted with APO-EMTRICITABINE-TENOFOVIR or the components of APO-EMTRICITABINE-TENOFOVIR (emtricitabine or tenofovir disoproxil fumarate) as individual agents and/or in combination.
The effects of didanosine in the presence of tenofovir are shown in Table 8.
The effects of coadministered drugs on the exposure of emtricitabine are shown in Table 9. The effects of emtricitabine on the exposure of coadministered drugs are shown in Table 10.
The effects of coadministered drugs on the exposure of tenofovir disoproxil fumarate are shown in Table 11.
The effects of tenofovir disoproxil fumarate on the exposure of coadministered drugs are shown in Table 12.
Table 8 Drug Interactions: Pharmacokinetic Parameters for Didanosine in the Presence of Tenofovir
Didanosine1 Dose
(mg)/ Method of
Administration2
Tenofovir Method of Administration2 | N |
% Difference (90% CI) vs. Didanosine
400 mg Alone, Fasted3
| Cmax |
AUC
Buffered tablets
400 once daily4 x 7 days
Fasted 1 hour after didanosine | 14 | ↑ 27 ( ↑ 8 to ↑ 46) |
↑ 43
(↑ 30 to ↑ 57) Enteric coated capsules
400 once,
fasted
With food, 2 hr after didanosine | 26 | ↑ 48 ( ↑ 25 to ↑ 76) |
↑ 48
( ↑ 31 to ↑ 67)
400 once, with food
Simultaneously with didanosine | 26 | ↑ 64 (↑ 41 to ↑ 89) |
↑ 60
(↑ 44 to ↑ 79) 250 once, fasted
With food, 2 hr after didanosine | 28 | ↓ 10 (↓ 22 to ↑ 3) |
0
(↓ 11 to ↑ 12)
250 once, fasted
Simultaneously with didanosine | 28 | ↓8 (↓ 19 to ↑ 5) |
↑ 14
(0 to ↑ 31)
250 once, with food
Simultaneously with didanosine | 28 | ↓ 29 (↓ 39 to ↓ 18) |
↓ 11
(↓ 23 to ↑ 2)
- 1. See PRECAUTIONS regarding use of didanosine with tenofovir disoproxil fumarate.
- 2. Administration with food was with a light meal (~373 kcal, 20% fat).
- 3. Increase =↑; Decrease = ↓
- 4. Includes 4 subjects weighing <60 kg receiving ddI 250 mg.
Table 9 Drug Interactions: Changes in Pharmacokinetic Parameters for Emtricitabine in the Presence of the Coadministered Drug1
Coadministered
Drug
Dose of Coadministered Drug (mg) | Emtricitabine Dose (mg) | N |
% Change of Emtricitabine Pharmacokinetic
Parameters2 (90% CI)
| Cmax | AUC |
Cmin
Tenofovir DF
300 once daily x 7 days | 200 once daily x 7 days | 17 | ↓ 4 (↓ 13 to ↑6) | ↑ 7 ( 0 to ↑ 4) |
↑ 20
(↑ 12 to ↑ 29)
Zidovudine
300 twice daily x7 days | 200 once daily x 7 days | 27 | ↓ 3 | ↓ 3 |
↓ 4
| (↓ 10 to ↑4) | (↓ 7 to ↑ 1) |
(↓ 12 to ↑ 4)
Indinavir
| 800 x 1 | 200 x 1 | 12 | ↓ 8 (↓ 18 to ↑4) | ↑ 1 (↓ 6 to ↑ 9) |
NC
Famciclovir
| 500 x 1 | 200 x 1 | 12 | ↓ 10 (↓ 20 to ↑1) | ↓ 8 (↓ 14 to ↓ 1) |
NC
Stavudine
| 40 x 1 | 200 x 1 | 6 | ↑ 4 (↓ 6 to ↑ 16) | ↑ 2 (↓ 6 to ↑ 11) |
NC
- 1. All interaction studies conducted in healthy volunteers.
- 2. ↑ = Increase; ↓ = Decrease; NC = Not Calculated
Table 10 Drug Interactions: Changes in Pharmacokinetic Parameters for
Coadministered Drug in the Presence of Emtricitabine1.
Coadministered
Drug
Dose of Coadministered Drug (mg) | Emtricitabine Dose (mg) | N |
% Change of Coadministered
Drug Pharmacokinetic Parameters2 (90% CI)
| Cmax | AUC |
Cmin
Tenofovir DF
| 300 once daily x 7 days | 200 once daily x 7 days | 17 | ↑ 3 (↓ 5 to ↑ 11) | 0 (↓ 8 to ↑ 9) |
↑ 2
(↓ 8 to ↑13)
Zidovudine
300 twice daily x 7 days | 200 once daily x 7 days | 27 | ↑ 17 ( 0 to ↑ 38) | ↑ 13 (↑ 5 to ↑ 20) |
↓ 2
(↓ 11 to ↑ 9) Indinavir
| 800 x 1 | 200 x 1 | 12 | ↓ 2 (↓ 16 to ↑ 13) | ↑ 2 (↓ 11 to ↑ 17) |
NC
Famciclovir
| 500 x 1 | 200 x 1 | 12 | ↓ 7 (↓ 22 to ↑ 11) | ↓ 9 (↓ 17 to ↓ 1) |
NC
Stavudine
| 40 x 1 | 200 x 1 | 6 | ↑ 5 (↓ 5 to ↑ 16) | ↑ 9 (↓ 17 to ↑ 44) |
NC
- 1. All interaction studies conducted in healthy volunteers.
2 ↑ = Increase; ↓ = Decrease; NC = Not Calculated
Table 11 Drug Interactions: Changes in Pharmacokinetic Parameters for Tenofovir1 in the Presence of the Coadministered Drug
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Tenofovir Pharmacokinetic
Parameters2
(90% CI)
| Cmax | AUC |
Cmin
Abacavir
| 300 once | 8 | ↓ 8 (↓ 24 to ↑ 12) | ↑ 4 (↓ 14 to ↑ 26) |
NC
Atazanavir3
400 once daily x 14 days | 33 | ↑ 14 (↑ 8 to↑ 20) | ↑ 24 (↑ 21 to ↑ 28) |
↑ 22
(↑ 15 to ↑ 30) Atazanavir/ Ritonavir3
| 300/100 once daily | 12 | ↑ 34 (↑ 20 to↑ 51) | ↑ 37 (↑ 30 to↑ 45) |
↑ 29
(↑ 21 to↑ 36) Darunavir/ Ritonavir4
300/100 twice daily | 12 | ↑ 24 ( ↑ 8 to↑ 42) | ↑ 22 ( ↑ 10 to↑ 35) |
↑ 37
(↑ 19 to↑ 57)
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Tenofovir Pharmacokinetic
Parameters2
(90% CI)
| Cmax | AUC |
Cmin
Didanosine (enteric- coated)
| 400 once | 25 | ↓ 2 (↓ 7 to ↑ 4) | ↑ 2 (↓ 2 to ↑ 5) |
NC
Didanosine (buffered)
| 250 or 400 once daily x7 days5 | 14 | ↑ 1 (↓ 12 to ↑ 14) | ↓ 5 (↓ 14 to ↑ 4) |
↓ 22
(↓ 36 to ↓ 7)
Efavirenz
600 once daily x 14 days | 29 | ↑ 7 (↓ 4 to ↑ 17) | ↓ 2 (↓ 8 to ↑ 3) |
↑ 2
(↓ 9 to ↑ 12)
Emtricitabine
200 once daily x 7 days | 17 | ↑ 3 (↓ 5 to ↑ 11) | 0 (↓ 8 to ↑ 9) |
↑ 2
(↓ 8 to ↑ 13)
Entecavir
1 mg once daily x 10 days | 28 | NA | NA |
NA
Indinavir
| 800 three times daily x 7 days | 13 | ↑ 14 (↓ 3 to ↑ 31) | ↑ 7 (↓ 5 to ↑ 19) |
↑ 8
(↓ 7 to ↑ 22)
Lamivudine
150 twice daily x 7 days | 15 | ↑ 2 (↓ 4 to ↑ 9) | ↓ 3 (↓ 15 to ↑ 10) |
↓ 8
(↓ 33 to ↑ 18)
Ledipasvir/ Sofosbuvir6, 7
90/400 once daily x10 days | 24 | ↑ 47 (↑ 37 to ↑ 58) | ↑ 35 (↑ 29 to ↑ 42) |
↑ 47
(↑ 38 to ↑ 57)
Ledipasvir/ Sofosbuvir6, 8
| 23 | ↑ 64 (↑ 54 to ↑ 74) | ↑ 50 (↑ 42 to ↑ 59) |
↑ 59
(↑ 49 to ↑ 70)
Ledipasvir/ Sofosbuvir9
| 15 | ↑ 79 (↑ 56 to ↑ 104) | ↑ 98 (↑ 77 to ↑ 123) |
↑ 163
(↑ 132 to ↑ 197)
Ledipasvir/ Sofosbuvir10
| 14 | ↑ 32 (↑ 25 to ↑ 39) | ↑ 40 (↑ 31 to ↑ 50) |
↑ 91
(↑ 74 to ↑ 110)
Ledipasvir/ Sofosbuvir11
| 29 | ↑ 61 (↑ 51 to ↑ 72) | ↑ 65 (↑ 59 to ↑ 71) |
↑ 115
(↑ 105 to ↑ 126)
Lopinavir/ Ritonavir
400/100 twice daily x 14 days | 24 | ↓ 33 (↓ 17 to ↑ 49) | ↑ 32 (↑ 25 to ↑ 40) |
↑ 28
(↑ 7 to ↑ 49)
Nelfinavir
1250 twice daily x 14 days | 29 | ↓ 2 (↓ 9 to ↑ 5) | ↑ 1 (↓ 5 to ↑ 7) |
↑ 9
(↑ 2 to ↑17) Saquinavir/Ritonavir
| 1000/100 twice daily x 14 days | 35 | ↑ 15 (↑ 7 to ↑ 22) | ↑ 14 (↑ 9 to ↑ 19) |
↑ 23
(↑ 16 to ↑ 30) Sofosbuvir12
| 400 single dose | 16 | ↑ 25 (↑ 8 to ↑ 45) | ↓ 2 (↓ 9 to ↑ 5) |
↓ 1
(↓ 9 to ↑ 7) Sofosbuvir/ Velpatasvir13
400/100 once daily
| 24 | ↑ 55 (↑43 to ↑68) | ↑30 (↑24 to ↑ 36) |
↑39
(↑ 31 to ↑48) Sofosbuvir/ Velpatasvir14
| 29 | ↑ 55 (↑ 45 to ↑66) | ↑ 39 (↑ 33 to ↑44) |
↑ 52
(↑ 45 to ↑ 59) Sofosbuvir/ Velpatasvir15
| 15 | ↑ 77 (↑ 53 to ↑104) | ↑ 81 (↑ 68 to ↑ 94) |
↑ 121
(↑ 100 to ↑ 143) Sofosbuvir/ Velpatasvir16
| 24 | ↑ 44 (↑ 33 to ↑ 55) | ↑ 40 (↑ 34 to ↑ 46) |
↑ 84
(↑ 76 to ↑ 92)
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Tenofovir Pharmacokinetic
Parameters2
(90% CI)
| Cmax | AUC |
Cmin
Sofosbuvir/ Velpatasvir17
| 24 | ↑ 36 (↑ 25 to ↑ 47) | ↑ 35 (↑ 29 to ↑ 42) |
↑ 45
(↑ 39 to ↑ 51) Sofosbuvir/ Velpatasvir18
| 30 | ↑ 46 (↑ 39 to ↑ 54) | ↑ 40 (↑ 34 to ↑ 45) |
↑ 70
(↑ 61 to ↑79) Sofosbuvir/ Velpatasvir/ Voxilaprevir19
400/100/100 + 100 voxilaprevir20 once daily | 29 | ↑ 48 (↑ 36 to ↑ 61) | ↑ 39 (↑ 32 to ↑ 46) |
↑ 47
(↑ 38 to ↑ 56)
Tacrolimus
| 0.05 mg/kg twice daily x 7 days | 21 | ↑13 (↑ 1 to ↑ 27) | ↑ 6 (↓ 1 to ↑ 13) |
↑ 11
(↑ 4 to ↑ 18) Tipranavir/Ritonavir19
500/100 twice daily | 22 | ↓ 23 (↓ 32 to ↓ 13) | ↓ 2 (↓ 9 to ↑ 5) |
↑ 7
(↓ 2 to ↑ 17)
| 750/200 twice daily (23 doses) | 20 | ↓ 38 (↓ 46 to ↓ 29) | ↑ 2 (↓ 6 to ↑ 10) |
↑ 14
(↑ 1 to ↑ 27)
- 1. Patients received tenofovir disoproxil fumarate 300 mg once daily.
- 2. Increase = ↑; Decrease = ↓; NC = Not Calculated; NA = Not Available
- 3. REYATAZ® (Atazanavir sulfate) Prescribing Information (Bristol-Myers Squibb)
- 4. Prezista (darunavir) Prescribing Information
- 5. weight <60kg: 250 mg, ≥60 kg more: 400 mg
- 6. Data generated from simultaneous dosing with HARVONI (ledipasvir/sofosbuvir). Staggered administration (12 hours apart) provided similar results.
- 7. Comparison based on exposures when administered as atazanavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with HARVONI (ledipasvir/sofosbuvir).
- 8. Comparison based on exposures when administered as darunavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with HARVONI (ledipasvir/sofosbuvir).
- 9.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate) coadministered with HARVONI
(ledipasvir/sofosbuvir).
- 10.
Study conducted with COMPLERA (erntricitabine/rilpivirine/tenofovir disoproxil fumarate) coadministered with
HARVONI (ledipasvir/sofosbuvir).
- 11.
Study conducted with APO-EMTRICITABINE-TENOFOVIR + dolutegravir coadministered with HARVONI
(ledipasvir/sofosbuvir).
- 12.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate) coadrninistered with
SOYALDI® (sofosbuvir).
- 13. Comparison based on exposures when administered as atazanavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with EPCLUSA (sofosbuvir/velpatasvir).
- 14. Comparison based on exposures when administered as darunavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with EPCLUSA (sofosbuvir/velpatasvir).
- 15.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir DF) coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 16.
Study conducted with COMPLERA (emtricitabine/rilpivirine/tenofovir DF) coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 17.
Study conducted with STRIBILD (elvitegravir/cobicistat/emtricitabine/tenofovir DF) coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 18.
Administered as raltegravir + APO-EMTRICITABINE-TENOFOVIR coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 19. Comparison based on exposures when administered as darunavir + ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with sofosbuvir/velpatasvir/voxilaprevir.
- 20.
Study conducted with additional voxilaprevir 100 mg to achieve voxilaprevir exposures expected in HCV-infected
patients.
- 21. Aptivus® (tipranavir) Prescribing Information.
Table 12 Drug Interactions: Changes in Pharmacokinetic Parameters for
Coadministered Drug in the Presence of Tenofovir
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Coadministered Drug Pharmacokinetic
Parameters1
(90% CI)
| Cmax | AUC |
Cmin
Abacavir2
| 300 single dose | 8 | ↑ 12 (↓ 1 to ↑ 26) | ↑ 11 (↑ 4 to↑ 19) |
NC
Atazanavir3
400 once daily x 14 days | 34 | ↓ 21 (↓ 27 to ↓ 14) | ↓ 25 (↓ 30 to ↓ 19) |
↓ 40
(↓ 48 to ↓ 32)
Atazanavir3
Atazanavir/Ritonavir 300/100 once daily x 42 days | 10 | ↓ 28 (↓ 50 to ↑ 5) | ↓ 257 (↓ 42 to ↓ 3) |
↓ 237
(↓ 46 to ↑ 10)
Darunavir4
| Darunavir/Ritonavir 300/100 once daily | 12 | ↑ 16 (↓ 6 to ↑42) | ↑ 21 (↓ 5 to ↑54) |
↑ 24
(↓10 to ↑69)
Didanosine2 (enteric-coated)
250 once, simultaneously with tenofovir DF and a light meal4 | 33 | ↓ 296 (↓ 39 to ↓ 18) | ↓ 11 (↓ 23 to ↑ 2) 6 |
NC
Efavirenz2
600 once daily x 14 days | 30 | ↓ 4 (↓ 9 to↑ 1) | ↓3 (↓ 7 to 0) |
↓ 7
(↓ 13 to ↓ 1)
Emtricitabine2
200 once daily x 7 days | 17 | ↓ 4 (↓ 13 to ↑ 6) | ↑ 7 (0 to ↑ 4) |
↑ 20
(↑ 12 to ↑ 29
Entecavir2
1 mg once daily x 10 days | 28 | NA | ↑ 13 (↑ 11 to ↑ 15) |
NA
Indinavir2
800 three times daily x 7 days | 12 | ↓ 6 (↓ 23 to ↑ 10) | ↓2 (↓ 12 to ↑ 8) |
↑ 43
(↓ 45 to ↑ 130)
Lamivudine2
150 twice daily x 7 days | 15 | ↓ 29 (↓ 39 to ↓ 19) | ↓ 10 (↓ 17 to ↓ 3) |
↑ 17
(↑ 3 to ↑ 32)
Lopinavir2
Lopinavir/Ritonavir 400/100 twice daily x 14 days | 24 | ↓14 (↓ 23 to ↓ 4) | ↓ 12 (↓ 20 to ↓ 5) |
↓ 11
(↓ 22 to ↑1)
Ritonavir
↓ 24 (↓ 46 to ↓ 3) | ↓ 22 (↓ 34 to ↓ 9) |
↓ 15
(↓ 32 to ↑ 2)
Ledipasvir
| Ledipasvir/Sofosbuvir 90/400 once daily13,14 | 24 | ↑ 68 (↑ 54 to ↑ 84) | ↑ 96 (↑ 74 to ↑ 121) |
↑ 118
(↑ 91 to ↑ 150)
Sofosbuvir
↑ 1 (↓12 to ↑ 15) | ↑ 11 (↑ 2 to ↑ 21) |
NC
GS-33100712
↑ 17 (↑ 12 to ↑ 23) | ↑ 31 (↑ 25 to ↑ 36) |
↑ 42
(↑ 34 to ↑ 49)
Ledipasvir
| Ledipasvir/Sofosbuvir 90/400 once daily13,15 | 23 | ↑ 11 (↓ 1 to ↑ 24) | ↑ 12 (0 to ↑ 25) |
↑ 17
(↑ 4 to ↑ 31)
Sofosbuvir
↓ 37 (↓ 48 to ↓ 25) | ↓ 27 (↓ 35 to ↓ 18) |
NC
GS-33100712
| ↑ 10 | ↑ 20 |
↑ 26
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Coadministered Drug Pharmacokinetic
Parameters1
(90% CI)
| Cmax | AUC |
Cmin
| (↑ 4 to ↑ 16) | (↑ 16 to ↑ 24) |
(↑ 20 to ↑ 32)
Ledipasvir
| Ledipasvir/Sofosbuvir 90/400 once daily16 | 15 | ↓ 34 (↓ 41 to ↓ 25) | ↓ 34 (↓ 41 to ↓ 25) |
↓ 34
(↓ 43 to ↓24)
Sofosbuvir
↑ 3 (↓ 13 to ↑ 23) | ↓ 6 (↓ 19 to ↑ 10) |
NC
GS-33100712
↓ 14 (↓ 24 to ↓ 4) | ↓ 10 (↓ 17 to ↓ 3) |
↑ 7
(↑ 2 to ↑ 13)
Ledipasvir
| Ledipasvir/ Sofosbuvir 90/400 once daily17 | 14 | ↑ 1 (↓ 5 to ↑ 7) | ↑ 8 (↑ 2 to ↑ 15) |
↑ 16
(↑ 8 to ↑ 25)
Sofosbuvir
↑ 5 (↓ 7 to ↑ 20) | ↑ 10 (↑ 1 to ↑ 21) |
NC
GS-33100712
↑ 6 (↑ 1 to ↑ 11) | ↑ 15 (↑ 11 to ↑ 19) |
↑ 18
(↑ 13 to ↑ 23) Sofosbuvir
| Sofosbuvir/ Velpatasvir 400/100 once daily18 | 24 | ↑ 12 (↓ 3 to ↑ 29) | ↑ 22 (↑ 12 to ↑ 33) |
NC
GS-33100712
↑ 21 (↑ 12 to ↑ 29) | ↑ 32 (↑ 27 to ↑ 36) |
↑ 42
(↑ 37 to ↑ 49) Velpatasvir
↑ 55 (↑ 41 to ↑ 71) | ↑ 142 (↑ 123 to ↑ 164) |
↑ 301
(↑ 257 to ↑ 350) Sofosbuvir
| Sofosbuvir/ Velpatasvir 400/100 once daily19 | 29 | ↓ 38 (↓ 46 to 29) | ↓ 28 (↓ 34 to ↓ 20) |
NC
GS-33100712
↑ 4 (↓ 1 to ↑ 8) | ↑ 13 (↑ 8 to ↑ 18) |
↑ 13
(↑ 6 to ↑ 19) Velpatasvir
↓ 24 (↓ 35 to ↓ 11) | ↓ 16 (↓ 28 to ↓ 2) |
↑ 1
(↓ 13 to ↑ 18) Sofosbuvir
| Sofosbuvir/ Velpatasvir 400/100 once daily20 | 14 | ↑ 38 (↑ 14 to ↑ 67) | ↓ 3 (↓ 17 to ↑ 14) |
NC
GS-33100712
↓ 14 (↓ 20 to ↓ 7) | ↓ 10 (↓ 15 to ↓ 4) |
↑ 1
(↓ 5 to ↑ 7) Velpatasvir
↓ 47 (↓ 57 to ↓ 36) | ↓ 53 (↓ 61 to ↓ 43) |
↓ 57
(↓ 64 to ↓ 48) Sofosbuvir
| Sofosbuvir/ Velpatasvir 400/100 once daily21 | 24 | ↑ 9 (↓ 5 to ↑ 25) | ↑ 16 (↑ 9 to ↑ 24) |
NC
GS-33100712
↓ 4 (↓ 10 to ↑ 1) | ↑ 4 (0 to ↑ 7) |
↑ 12
(↑ 7 to ↑ 17) Velpatasvir
↓ 4 (↓ 15 to ↑ 10) | ↓ 1 (↓ 12 to ↑ 11) |
↑ 2
(↓ 9 to ↑ 15) Sofosbuvir
| Sofosbuvir/ Velpatasvir 400/100 once daily22 | 24 | ↑ 1 (↓ 15 to ↑ 19) | ↑ 24 (↑ 13 to ↑ 37) |
NC
GS-33100712
↑ 13 (↑ 7 to ↑ 18) | ↑ 35 (↑ 30 to ↑ 40 |
↑ 45
(↑ 38 to ↑ 52) Velpatasvir
↑ 5 (↓ 7 to ↑ 19) | ↑ 19 (↑ 7 to ↑ 34) |
↑ 37
(↑ 22 to ↑ 54) Sofosbuvir
| Sofosbuvir/ Velpatasvir | 30 | ↑ 9 | ↑ 16 |
NC
Coadministered
Drug
Dose of Coadministered Drug (mg) | N |
% Change of Coadministered Drug Pharmacokinetic
Parameters1
(90% CI)
| Cmax | AUC |
Cmin
| 400/100 once daily23 | (↓ 3to ↑ 23) | (↑ 7 to ↑ 25) |
GS-33100712
↓ 5 ↓ 9 to ↓ 2 | ↑ 3 0 to ↑ 6 |
↑ 8
↑ 4 to ↑ 13 Velpatasvir
↓ 3 (↓ 13 to ↑ 8) | ↓ 2 (↓ 12 to ↑ 10) |
↓ 3
(↓ 13 to ↑ 7) Sofosbuvir
400/100/100 + 100 voxilaprevir24 once daily | 29 | ↓ 3025 (↓ 38 to ↓ 22) | ↓ 2225 (↓ 27 to ↓17) |
NA
GS-33100712
↓ 625 (↑ 1 to ↑ 10) | ↑ 1525 (↑ 12 to ↑ 19) |
NA
Velpatasvir
↓ 2225 (↓ 27 to ↓ 16) | ↓ 524 (↓ 12 to ↑ 2) |
↑ 1625 (↑ 7 to ↑ 26) Voxilaprevir
↓ 7225 (↓ 51 to ↑ 97) | ↓ 14325 (↓ 115 to ↑ 175) |
↓ 30025
(↓ 244 to ↑ 365)
Methadone 8
40-110 once daily x 14 days9 | 13 | ↑ 5 (↓ 3 to ↑ 14) | ↑ 5 (↓ 2 to ↑ 13) |
↑ 6
(↓ 3 to ↑ 15)
Nelfinavir2
1250 twice daily x 14 days | 29 | ↓ 8 (↓ 15 to ↓ 1) | ↓ 7 (↓ 15 to ↑ 2) |
↑ 1
(↓ 15 to ↑ 19)
M8 metabolite
↓ 8 (↓ 16 to 0) | ↓ 7 (↓ 17 to ↑5 ) |
↓ 2
(↓ 16 to ↑ 15)
Norgestimate
Ethinyl Estradiol/ Norgestimate (Ortho- Tricyclen®) Once daily x 7 days | 20 | ↓ 6 (↓ 13 to ↑ 1) | ↓ 5 (↓ 9 to ↓ 1) |
↓ 4
(↓ 8 to ↑ 1)
Ethinyl estradiol10
↓ 6 (↓ 12 to 0) | ↓ 4 (↓ 9 to ↑1) |
↓ 2
(↓9 to ↑ 6)
Ribavirin
| 600 once | 22 | ↓ 5 (↓ 11 to ↑ 1) | ↓ 12 (↑ 6 to ↑ 17) |
NC
Saquinavir
1000/100 twice daily x 14 days | 32 | ↑ 22 (↑ 6 to ↑ 41) | ↑ 2911 (↑ 12 to ↑ 48) |
↑ 4711
(↑ 23 to ↑ 76)
Ritonavir
↑ 10 (↓ 5 to ↑ 28) | ↑ 11 (0 to ↑ 22) |
↑ 23
(↑ 3 to ↑ 46)
Sofosbuvir
| Sofosbuvir 400 once26 | 16 | ↓ 19 (↓ 40 to ↑ 10) | ↓ 6 (↓ 24 to ↑ 16) |
NC
GS-33100712
↓ 23 (↓ 30 to ↓16) | ↓ 16 (↓ 24 to ↓ 8) |
NC
Tacrolimus
0.05 mg/kg twice daily x 7 days | 21 | ↑ 3 (↓ 3 to ↑ 9) | ↑ 4 (↓ 3 to ↑ 11) |
↑ 10
(↑ 2 to ↑ 17)
Tipranavir27
| Tipranavir/Ritonavir 500/100 twice daily | 22 | ↓ 17 (↓ 26 to ↓ 6) | ↓ 18 (↓ 25 to ↓ 9) |
↓ 21
(↓ 30 to ↓ 10)
Tipranavir/Ritonavir 750/200 twice daily (23 doses) | 20 | ↓ 11 (↓16 to ↓ 4) | ↓9 (↓ 15 to ↓ 3) |
↓12 (↓ 22 to 0)
- 1. Increase = ↑; Decrease = ↓; NC = Not Calculated; NA = Not Available
- 2. Study conducted with VIREAD (tenofovir DF).
- 3. REYATAZ (atazanavir sulfate) Prescribing Information (Bristol-Myers Squibb)
- 4. Prezista (darunavir) Prescribing Information.
- 5. 373 kcal, 8.2 g fat
- 6. Compared with didanosine (enteric-coated) 400 mg administered alone under fasting conditions.
- 7.
In HIV-infected patients, addition of tenofovir disoproxil fumarate to atazanavir 300 mg plus ritonavir 100 mg, resulted in
AUC and Cmin values of atazanavir that were 2.3 and 4-fold higher than the respective values observed for atazanavir 400 mg when given alone.
- 8. R-(active), S-and total methadone exposures were equivalent when dosed alone or with VIREAD (tenofovir).
- 9. Individual subjects were maintained on their stable methadone dose. No pharmacodynamic alterations (opiate toxicity or withdrawal signs or symptoms) were reported.
10.Ethinyl estradiol and 17-deacetyl norgestimate (pharmacologically active metabolite) exposures were equivalent when dosed alone or with VIREAD (tenofovir).
- 11. Increases in AUC and Cmin are not expected to be clinically relevant; hence no dose adjustments are required when tenofovir DF and ritonavir-boosted saquinavir are coadministered.
- 12. The predominant circulating nucleoside metabolite of sofosbuvir.
- 13. Data generated from simultaneous dosing with HARVONI (ledipasvir/sofosbuvir). Staggered administration (12 hours apart) provided similar results.
- 14. Comparison based on exposures when administered as atazanavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with HARVONI (ledipasvir/sofosbuvir).
- 15. Comparison based on exposures when administered as darunavir/ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with HARVONI (ledipasvir/sofosbuvir).
- 16.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate) coadministered with
HARVONI (ledipasvir/sofosbuvir).
- 17.
Study conducted with COMPLERA (emtricitabine/rilpivirine/tenofovir) coadministered with HARVONI
(ledipasvir/sofosbuvir).
18 Comparison based on exposures when administered as atazanavir/ritonavir + APO-EMTRICITABINE-
TENOFOVIR coadministered with EPCLUSA (sofosbuvir/velpatasvir).
- 19.
Comparison based on exposures when administered as darunavir/ritonavir + APO-EMTRICITABINE-
TENOFOVIR coadministered with EPCLUSA (sofosbuvir/velpatasvir).
- 20.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir DF) coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 21.
Study conducted with COMPLERA (emtricitabine/rilpivirine/tenofovir DF) coadministered with EPCLUSA
(sofosbuvir/velpatasvir).
- 22.
Study conducted with STRIBILD (elvitegravir/cobicistat/emtricitabine/tenofovir DF) coadministered with
EPCLUSA (sofosbuvir/velpatasvir).
- 23. Comparison based on exposures when administered as raltegravir + APO-EMTRICITABINE-TENOFOVIR coadministered with EPCLUSA (sofosbuvir/velpatasvir).
- 24.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate) coadministered with SOVALDI
(sofosbuvir).
- 25. Comparison based on exposures when administered as darunavir + ritonavir + APO-EMTRICITABINE-TENOFOVIR coadministered with VOSEVI (sofosbuvir/velpatasvir/voxilaprevir).
- 26.
Study conducted with ATRIPLA (efavirenz/emtricitabine/tenofovir disoproxil fumarate) coadministered with SOVALDI
(sofosbuvir).
- 27. Aptivus (tipranavir) Prescribing Information
Drug-Food Interactions
APO-EMTRICITABINE-TENOFOVIR can be taken with or without food. Compared to fasted administration, dosing of emtricitabine/tenofovir disoproxil fumarate following a either a high fat meal or a light meal increased the mean AUC and Cmax of tenofovir by 35% and 15%, respectively, without affecting emtricitabine exposures (see ACTIONS AND CLINICAL PHARMACOLOGY, Effect of Food on Absorption).
Drug-Herb Interactions
Interactions of emtricitabine/tenofovir disoproxil fumarate tablets with herbs have not been established.
Drug-Laboratory Interactions
Interactions of emtricitabine/tenofovir disoproxil fumarate tablets with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Recommended Dose
Treatment of HIV-1 Infection
The dose of APO-EMTRICITABINE-TENOFOVIR is one tablet (containing 200 mg of emtricitabine and 300 mg of tenofovir disoproxil fumarate) once daily taken orally with or without food.
Pre-exposure Prophylaxis of HIV-1 Infection
The dose of APO-EMTRICITABINE-TENOFOVIR is one tablet (200 mg of emtricitabine and 300 mg of tenofovir disoproxil fumarate) once daily taken orally with or without food.
Special Populations
Dose Adjustment for Renal Impairment
Treatment of HIV-1 Infection
Significantly increased drug exposures occurred when emtricitabine or tenofovir disoproxil fumarate were administered to patients with moderate to severe renal impairment (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency). Therefore, the dosing interval of APO-EMTRICITABINE-TENOFOVIR should be adjusted in HIV-1 infected adult patients with baseline creatinine clearance 30 to 49 mL/min using the recommendations in Table 13. These dosing interval recommendations are based on modeling of single-dose pharmacokinetic data in non-HIV infected subjects with varying degrees of renal impairment, including end-stage renal disease requiring hemodialysis. The safety and effectiveness of these dosing interval adjustment recommendations have not been clinically evaluated in moderate to severe renal impairment, therefore, clinical response to treatment and renal function should be closely monitored in these patients.
No dose adjustment of APO-EMTRICITABINE-TENOFOVIR tablets is necessary with mild renal impairment patients (creatinine clearance 50 to 80 mL/min). Routine monitoring of calculated creatinine clearance, serum phosphorus, urine glucose, and urine protein should be performed for patients with mild renal impairment (creatinine clearance 50 to 80 mL/min). (see WARNINGS AND PRECAUTIONS).
Table 13 Dosage Adjustment for HIV-1 Infected Adult Patients with Altered
Creatinine Clearance Creatinine Clearance (mL/min)1
| ≥50 | 30–49 |
<30
(Including Patients Requiring
Hemodialysis)
Recommended Dosing Interval
| Every 24 hours | Every 48 hours |
APO-EMTRICITABINE-TENOFOVIR should not be administered.
- 1. Calculated using ideal (lean) body weight.
Pre-exposure Prophylaxis of HIV-1 Infection
Do not use APO-EMTRICITABINE-TENOFOVIR for PrEP in HIV-1 uninfected individuals with creatinine clearance below 60 mL/min (see WARNINGS AND PRECAUTIONS).
No dose adjustment of APO-EMTRICITABINE-TENOFOVIR tablets is necessary with mild renal impairment patients (creatinine clearance 50 to 80 mL/min). Routine monitoring of calculated creatinine clearance, serum phosphorus, urine glucose and urine protein should be performed in all individuals with mild renal impairment. If a decrease in calculated creatinine clearance is observed in uninfected individuals while using APO-EMTRICITABINE-TENOFOVIR for PrEP, evaluate potential causes and re- assess potential risks and benefits of continued use (see WARNINGS AND PRECAUTIONS).
Hepatic Impairment
No dose adjustment is required in patients with hepatic impairment (see WARNINGS AND PRECAUTIONS).
Geriatrics (>65 years of age)
Clinical studies of emtricitabine or tenofovir disoproxil fumarate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently than younger subjects. In general, dose selection for the elderly patient should be cautious, keeping in mind the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Missed Dose
If a patient misses a dose within 12 hours of the regularly scheduled time, but then remembers it that same day, the patient should take the missed dose with food as soon as possible and resume their normal dosing schedule. If a patient misses a dose of APO-EMTRICITABINE-TENOFOVIR by more than 12 hours and it is almost time for their next dose, the patient should not take the missed dose and simply resume the usual dosing schedule. The patient should not take more than 1 dose of APO-EMTRICITABINE-TENOFOVIR in a day, and should not take 2 doses of APO-EMTRICITABINE-TENOFOVIR at the same time to make up for missing a dose.
Uninfected individuals who miss doses are at greater risk of acquiring HIV-1 than those who do not miss doses (see WARNINGS AND PRECAUTIONS).
OVERDOSAGE
For management of a suspected drug overdose, please contact your regional Poison Control Centre.
If overdose occurs the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary.
Emtricitabine: Limited clinical experience is available at doses higher than the therapeutic dose of emtricitabine. In one clinical pharmacology study single doses of emtricitabine 1200 mg were administered to 11 patients. No severe adverse reactions were reported. The effects of higher doses are not known.
Hemodialysis treatment removes approximately 30% of the emtricitabine dose over a 3-hour dialysis period starting within 1.5 hours of emtricitabine dosing (blood flow rate of 400 mL/min and a dialysate flow rate of 600 mL/min); however, a single treatment does not significantly affect emtricitabine Cmax or AUC. It is not known whether emtricitabine can be removed by peritoneal dialysis.
Tenofovir disoproxil fumarate: Limited clinical experience at doses higher than the therapeutic dose of tenofovir disoproxil fumarate 300 mg is available. In one study, 600 mg tenofovir disoproxil fumarate was administered to 8 patients orally for 28 days. No severe adverse reactions were reported. The effects of higher doses are not known.
Tenofovir is efficiently removed by hemodialysis with an extraction coefficient of approximately 54%. Following a single 300 mg dose of tenofovir disoproxil fumarate, a four-hour hemodialysis session removed approximately 10% of the administered tenofovir dose.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
APO-EMTRICITABINE-TENOFOVIR is a fixed-dose combination of antiviral drugs, emtricitabine and tenofovir disoproxil fumarate (see VIROLOGY).
Pharmacokinetics
Emtricitabine/tenofovir disoproxil fumarate tablets: One emtricitabine/tenofovir disoproxil fumarate tablet was bioequivalent to one emtricitabine capsule (200 mg) plus one tenofovir disoproxil fumarate tablet (300 mg) following single-dose administration to fasting healthy subjects (N=39).
Emtricitabine: The pharmacokinetic properties of emtricitabine are summarized in Table 14. Following oral administration of emtricitabine, emtricitabine is rapidly absorbed with peak plasma concentrations occurring at 1 to 2 hours post-dose. In vitro binding of emtricitabine to human plasma proteins is <4% and is independent of concentration over the range of 0.02 to 200 mcg/mL. Following administration of radiolabelled emtricitabine, approximately 86% is recovered in the urine and 13% is recovered as metabolites. The metabolites of emtricitabine include 3′-sulfoxide diastereomers and their glucuronic acid conjugate. Emtricitabine is eliminated by a combination of glomerular filtration and active tubular secretion. Following a single oral dose of emtricitabine, the plasma emtricitabine half-life is approximately 10 hours.
Tenofovir disoproxil fumarate: The pharmacokinetic properties of tenofovir disoproxil fumarate are summarized in Table 14. Following oral administration of tenofovir disoproxil fumarate, maximum tenofovir serum concentrations are achieved in 1.0 ± 0.4 hour. In vitro binding of tenofovir to human plasma proteins is <0.7% and is independent of concentration over the range of 0.01 to 25 mcg/mL. Approximately 70 to 80% of the intravenous dose of tenofovir is recovered as unchanged drug in the urine. Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion. Following a single oral dose of tenofovir disoproxil fumarate, the terminal elimination half-life of tenofovir is approximately 17 hours.
Table 14 Single Dose Pharmacokinetic Parameters for Emtricitabine and
Tenofovir in Adults
Emtricitabine Tenofovir
Fasted Oral Bioavailability2 (%) 92 (83.1–106.4) 25 (NC–45.0)1
Plasma Terminal Elimination
Half-Life2 (hr) 10 (7.4–18.0) 17 (12.0–25.7)
Cmax3 (mcg/mL) 1.8 ± 0.724 0.30 ± 0.09 AUC3 (mcg·hr/mL) 10.0 ± 3.124 2.29 ± 0.69 CL/F3 (mL/min) 302 ± 94 1043 ± 115 CLrenal3 (mL/min)
213 ± 89 243 ± 33
- 1. NC = Not calculated
- 2. Median (range)
- 3. Mean ± SD
- 4. Data presented as steady state values.
Effects of Food on Oral Absorption
APO-EMTRICITABINE-TENOFOVIR may be administered with or without food. Administration of emtricitabine/tenofovir disoproxil fumarate following a high fat meal (784 kcal; 49 grams of fat) or a light meal (373 kcal; 8 grams of fat) delayed the time of tenofovir Cmax by approximately 0.75 hour. The mean increases in tenofovir AUC and Cmax were approximately 35% and 15%, respectively, when administered with a high fat or light meal, compared to administration in the fasted state. In previous safety and efficacy studies, tenofovir was taken under fed conditions. Emtricitabine systemic exposures (AUC and Cmax) were unaffected when emtricitabine/tenofovir disoproxil fumarate was
administered with either a high fat or a light meal.
Special Populations and Conditions
Pediatrics and Geriatrics
Pharmacokinetics of emtricitabine and tenofovir have not been fully evaluated in children (<18 years) or in the elderly (>65 years).
Race
Emtricitabine: No pharmacokinetic differences due to race have been identified following the administration of emtricitabine.
Tenofovir disoproxil fumarate: There were insufficient numbers from racial and ethnic groups other than Caucasian to adequately determine potential pharmacokinetic differences among these populations.
Gender
Emtricitabine and tenofovir disoproxil fumarate: Emtricitabine and tenofovir pharmacokinetics are similar in male and female patients.
Hepatic Insufficiency
The pharmacokinetics of tenofovir following a 300 mg single dose of tenofovir disoproxil fumarate have been studied in non-HIV infected subjects with moderate to severe hepatic impairment. There were no substantial alterations in tenofovir pharmacokinetics in subjects with hepatic impairment compared with unimpaired subjects. The pharmacokinetics of emtricitabine/tenofovir disoproxil fumarate tablets or emtricitabine have not been studied in patients with hepatic impairment; however, emtricitabine has not been shown to be significantly metabolized by liver enzymes, so the impact of liver impairment is likely to be limited.
Renal Insufficiency
The pharmacokinetics of emtricitabine and tenofovir are altered in patients with renal insufficiency. In patients with creatinine clearance <50 mL/min, Cmax and AUC0-∞ of emtricitabine and tenofovir were increased (see WARNINGS, Nephrotoxicity).
It is recommended that the dosing interval for APO-EMTRICITABINE-TENOFOVIR be modified in HIV-1 infected patients with creatinine clearance 30 to 49 mL/min. APO-EMTRICITABINE-TENOFOVIR should not be used in HIV-1 infected patients with creatinine clearance <30 mL/min and in patients with end-stage renal disease requiring dialysis (see DOSAGE AND ADMINISTRATION).
APO-EMTRCITABINE-TENOFOVIR for PrEP has not been studied and should not be used in HIV-1 uninfected individuals with creatinine clearance below 60 mL/min. (see
DOSAGE AND ADMINISTRATION).
STORAGE AND STABILITY
Store at controlled room temperature 15°C to 30°C, protect from moisture.
- Keep container tightly closed
- Dispense only in original container
- Do not use if seal over bottle opening is broken or missing.
SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
DOSAGE FORMS, COMPOSITION AND PACKAGING
APO-EMTRICITABINE-TENOFOVIR is available as tablets. Each tablet contains 200 mg of emtricitabine and 300 mg of tenofovir disoproxil fumarate (which is equivalent to 245 mg of tenofovir disoproxil), as active ingredients. The tablets also include the following inactive ingredients: anhydrous lactose, colloidal silicon dioxide, crospovidone, FD&C Blue No. 2, magnesium stearate, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
APO-EMTRICITABINE-TENOFOVIR 200/300 mg are blue, capsule-shaped, biconvex, film-coated tablets. Engraved “APO” on one side, “E-T” on the other side. Available in bottles of 30 and 100 tablets with desiccants and blister pack of 100 tablets.
PART II. SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Emtricitabine:
Common Name: emtricitabine
Chemical Name: 5-fluoro-1-(2R,5S)-[2-(hydroxymethyl)-1,3-oxathiolan-5- yl]cytosine
Molecular Formula: C8H10FN3O3S
Molecular Weight: 247.25 g/mol
Structural Formula:
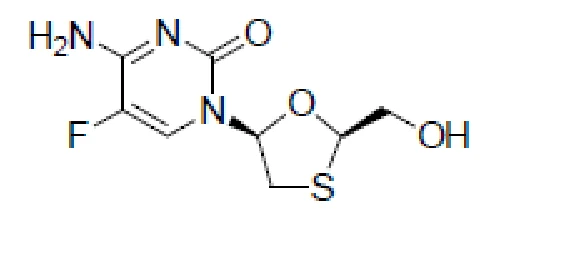
Physicochemical Properties:
Physical Description: Emtricitabine is a white to off-white powder.
Solubility: The solubility of emtricitabine is approximately 112 mg/mL in water at 25 oC. Freely soluble in methanol and practically insoluble in methylene chloride. The partition coefficient (log p) for emtricitabine is –0.43 and the pKa is 2.65.
Tenofovir disoproxil fumarate:
Common Name: tenofovir disoproxil fumarate
Chemical Name: 9-[(R)-2-[[bis[[(isopropoxycarbonyl)oxy]methoxy]phosphinyl]- methoxy]propyl]adenine fumarate (1:1)
Molecular Formula: C19H30N5O10P • C4H4O4
Molecular Weight: 635.51 g/mol
Structural Formula:
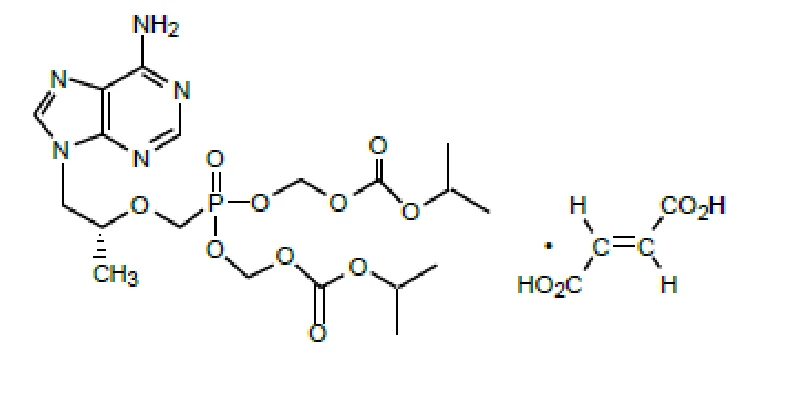
Physicochemical Properties:
Physical Description: Tenofovir disoproxil fumarate is a white to off-white powder.
Solubility: Soluble in methanol and dimethylformamide. The partition coefficient (log p) for tenofovir disoproxil is 1.25 and the pKa is 3.75.
CLINICAL TRIALS
Comparative Bioavailability Studies
A randomized, single dose, double-blinded, 2-way crossover comparative bioavailability study, conducted under fasting conditions, was performed on healthy male volunteers. The results obtained from 22 volunteers who completed the study are summarized in the following tables. The rate and extent of absorption of emtricitabine and tenofovir were measured and compared following a single oral dose (1 x 200/300 mg tablet) of Apo-Emtricitabine and Tenofovir Disoproxil Fumarate (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablet (Apotex Inc.) and Truvada® (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablet (Gilead Sciences Canada, Inc.).
Emtricitabine 1 x 200 mg of Emtricitabine /300 mg of Tenofovir Disoproxil Fumarate From Measured Data Geometric Mean# Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
| AUCt (ng•h/mL) | 10883.5 11152.6 (21) | 10900.3 10982.21 (16) | 99.8 | 94.9 – 105.1 |
| AUCinf (ng•h/mL) | 11251.1 11490.09 (19) | 11212.9 11288.49 (15) | 100.3 | 95.7 – 105.2 |
| Cmax (ng/mL) | 2054.7 2180.3 (33) | 1990.0 2023.4 (20) | 103.3 | 93.6 – 113.9 |
| Tmax§ (h) | 1.09 (26) | 1.48 (40) | ||
| Thalf§ (h) | 9.74 (38) | 9.15 (29) | ||
* Apo-Emtricitabine and Tenofovir Disoproxil Fumarate (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablets (Apotex Inc.) † Truvada® (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablets (Gilead Sciences Canada, Inc.) was purchased in Canada. # For balanced treatment sequence, results are based on Geometric means. For unbalanced treatment sequence, results are based on Least Squares Means (LSM). § Expressed as arithmetic means (CV%) only. | ||||
Tenofovir 1 x 200 mg of Emtricitabine /300 mg of Tenofovir Disoproxil Fumarate From Measured Data Geometric Mean# Arithmetic Mean (CV%) | ||||
| Parameter | Test* | Reference† | ||
Ratio of Geometric
Means (%)
| 90% Confidence Interval (%) |
AUCt (ng•h/mL) 3245.80
3362.32 (24)
3122.09
3180.70 (18)
| 104.0 |
95.9 – 112.8
| AUCinf (ng•h/mL) | 3410.60 3545.28 (25) | 3273.02 3338.38 (19) | 104.2 | 95.9 – 113.2 |
| Cmax (ng/mL) | 422.64 438.97 (25) | 365.88 378.07 (23) | 115.5 | 103.3 – 129.2 |
| Tmax§ (h) | 0.86 (23) | 1.26 (42) | ||
| Thalf§ (h) | 17.51 (19) | 17.23 (15) | ||
* Apo-Emtricitabine and Tenofovir Disoproxil Fumarate (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablets (Apotex Inc.) † Truvada® (Emtricitabine and Tenofovir Disoproxil Fumarate) 200/300 mg tablets (Gilead Sciences Canada, Inc.) was purchased in Canada. # For balanced treatment sequence, results are based on Geometric means. For unbalanced treatment sequence, results are based on Least Squares Means (LSM). § Expressed as arithmetic means (CV%) only. | ||||
Clinical Studies in Patients with HIV-1 Infection
Study Demographics and Trial Design
Description of Clinical Studies
For safety and efficacy studies using emtricitabine or tenofovir disoproxil fumarate in combination with other antiretroviral agents, also consult the Product Monograph for these products.
Clinical Study 934 supports the use of emtricitabine/tenofovir disoproxil fumarate tablets for the treatment of HIV-1 infection. Additional data in support of the use of emtricitabine/tenofovir disoproxil fumarate tablets are derived from Study 903, in which lamivudine and tenofovir disoproxil fumarate were used in combination in treatment-naïve adults, and clinical Study 303 in which emtricitabine and lamivudine demonstrated comparable efficacy, safety and resistance patterns as part of multidrug regimens (see Table 19 and Table 20).
Table 15 Study 934 Emtricitabine + Tenofovir Disoproxil Fumarate (DF) + Efavirenz
Compared with Lamivudine/Zidovudine +Efavirenz
Study
Number
| Trial Design | Dosage, Route of Administration and Duration | Study Subjects (N=511) | Mean Age |
Gender GS-01-934
Randomized, open- label, parallel, multicenter, active controlled study. Arm 1: | Arm 11: efavirenz 600 mg once daily for oral administration, emtricitabine 200 mg once and tenofovir DF 300 mg | Antiretroviral naïve patients (HIV-1 RNA > 10,000 copies/mL) | Mean 38 years (18–80) |
Male : 86%
Female: 14%
emtricitabine+ tenofovir DF+ efavirenz Arm 2: lamivudine/ zidovudine + efavirenz | once daily Arm 2: efavirenz 600 mg once daily for oral administration and Combivir (lamivudine/ zidovudine) 150/300 mg twice daily. 144 weeks | (N=511) |
1From weeks 96 to 144 of the study, patients received emtricitabine and tenofovir DF with efavirenz in place of emtricitabine + tenofovir DF
Data through 144 weeks are reported for Study 934, a randomized, open-label, active controlled multicenter study comparing emtricitabine + tenofovir disoproxil fumarate administered in combination with efavirenz versus lamivudine/zidovudine administered in combination with efavirenz in 511 antiretroviral-naïve patients. From weeks 96 to 144 of the study, patients randomized to emtricitabine + tenofovir disoproxil fumarate received emtricitabine tablets and tenofovir disoproxil fumarate tablets with efavirenz in place of emtricitabine/tenofovir disoproxil fumarate combination tablets. Patients had a mean age of 38 years (range 18 to 80), 86% were male, 59% were Caucasian and 23% were Black. The mean baseline CD4 cell count was 245 cells/mm3 (range 2 to 1191) and median baseline plasma HIV-1RNA was 5.01 log10 copies/mL (range 3.56 to 6.54). Patients were stratified by baseline CD4 count (< or ≥200 cells/mm3); 41% had CD4 cell counts <200 cells/mm3 and 51% of patients had baseline viral loads >100,000 copies/mL.
Emtricitabine:
Table 16 Study 303: Emtricitabine QD + Stable Background Therapy
(SBT) Compared to Lamivudine BID + SBT
Study
No.
| Trial Design | Dosage, Route of Administration and Duration | Study Subjects (N=440) | Mean Age (Range) |
Gender
FTC-303
Randomized (2:1), open-label, active- controlled switch study. Arm 1: emtricitabine + (d4T or ZDV + PI or NNRTI) Arm 2: lamivudine + (d4T or ZDV + PI or NNRTI) | Arm 1: emtricitabine 200 mg capsules orally, QD + (d4T or ZDV + PI or NNRTI) for 48 weeks Arm 2: lamivudine 150 mg tablet orally, BID + (d4T or ZDV + PI or NNRTI) for 48 weeks | Stable treatment- experienced (HIV-1 RNA <400 copies/mL) (N=440) | 42 years (22–80) |
Male:
86%
Female: 14%
Study 303 was a 48-week, open-label, active-controlled multicenter study comparing
emtricitabine (200 mg QD) to lamivudine, in combination with stavudine or zidovudine and a protease inhibitor or NNRTI in 440 patients who were on a lamivudine-containing triple- antiretroviral drug regimen for at least 12 weeks prior to study entry and had HIV-1 RNA ≤400 copies/mL.
Patients were randomized 1:2 to continue therapy with lamivudine (150 mg BID) or to switch to emtricitabine (200 mg QD). All patients were maintained on their stable background regimen. Patients had a mean age of 42 years (range 22 to 80), 86% were male, 64% Caucasian, 21% African-American and 13% Hispanic. Patients had a mean baseline CD4 cell count of 527 cells/mm3 (range 37 to 1909), and a median baseline plasma HIV RNA of 1.7 log10 copies/mL (range 1.7 to 4.0). The median duration of prior antiretroviral therapy was 27.6 months.
Tenofovir Disoproxil Fumarate:
Table 17 Study 903: Tenofovir Disoproxil Fumarate (DF) + Lamivudine + Efavirenz Compared with Stavudine + Lamivudine + Efavirenz
Study
No.
| Trial Design | Dosage, Route of Administration and Duration | Study Subjects (N=600) | Mean Age (Range) |
Gender
GS-99- 903
Randomized (1:1), double-blind, active- controlled, equivalence study. Arm 1: tenofovir DF + lamivudine + efavirenz Arm 2: stavudine + lamivudine + efavirenz | Arm 1: tenofovir DF 300 mg tablets QD, stavudine placebo capsules BID, lamivudine 150 mg tablets BID, efavirenz 600 mg QD Arm 2: tenofovir DF placebo tablets QD, stavudine1 capsules 40/30 mg BID, lamivudine 150 mg tablets BID, efavirenz 600 mg QD All for oral (PO) administration for 144 weeks double-blind phase followed by 192-week open-label phase. (Nevirapine 200 mg BID could replace efavirenz in the event of efavirenz- associated central nervous system toxicity or rash.) | Treatment-naive (HIV-1 RNA >5,000 copies/mL) (N=600) | 36 years (18–64) |
Male:
74%
Female: 26%
- 1. Stavudine/placebo capsules 20/15 mg BID as need for dose reduction.
Study 903 is a double-blind, active-controlled multicenter study comparing tenofovir disoproxil fumarate (300 mg QD) administered in combination with lamivudine and efavirenz
versus stavudine, lamivudine, and efavirenz in 600 antiretroviral-naïve patients. Patients had a mean age of 36 years (range 18 to 64), 74% were male, 64% were Caucasian and 20% were Black. The mean baseline CD4 cell count was 279 cells/mm3 (range 3 to 956) and median baseline plasma HIV-1 RNA was 77,600 copies/mL (range 417 to 5,130,000). Patients were stratified by baseline HIV-1 RNA and CD4 count. Forty-three percent of patients had baseline viral loads >100,000 copies/mL and 39% had CD4 cell counts <200 cells/mm3.
Study Results
Emtricitabine and Tenofovir Disoproxil Fumarate
Study 934: Emtricitabine + Tenofovir Disoproxil Fumarate (DF) + Efavirenz Compared with Lamivudine/Zidovudine + Efavirenz
Treatment outcomes through 48 and 144 weeks for those patients who did not have efavirenz resistance at baseline are presented in Table 18.
Table 18 Outcomes of Randomized Treatment at Weeks 48 and 144 (Study
934)
Outcome
| At Week 48 |
At Week 1441
Emtricitabine + Tenofovir DF +EFV | 3TC+AZT +EFV | Emtricitabine + Tenofovir DF + EFV |
3TC/AZT
+EFV
| (N=244) | (N=243) | (N=227) |
(N=229)
Responder2
| 84% | 73% | 71% |
58% Virologic failure3
Rebound
Never suppressed
Change in antiretroviral regimen
| 2% | 4% | 3% |
6%
| 1% | 3% | 2% |
5%
| 0% | 0% | 0% |
0%
| 1% | 1% | 1% |
1%
Death
| <1% | 1% | 1% |
1% Discontinued due to adverse event
| 4% | 9% | 5% |
12% Discontinued for other reasons4
| 10% | 14% | 20% |
22%
- 1. Patients who were responders at Week 48 or Week 96 but did not consent to continue study after Week 48 or Week 96 were excluded from analysis.
- 2. Patients achieved and maintained confirmed HIV-1 RNA <400 copies/mL through Week 48.
- 3. Includes confirmed viral rebound and failure to achieve confirmed <400 copies/mL through Week 48.
- 4. Includes lost to follow-up, patient withdrawal, non-compliance, protocol violation and other reasons.
In this study, emtricitabine + tenofovir disoproxil fumarate in combination with efavirenz demonstrated statistically significant superiority to lamivudine/zidovudine in combination with efavirenz in achieving and maintaining HIV-1 RNA <400 copies/mL through 48 weeks and 144 weeks (Table 18). The difference in the percentages of responders, stratified by baseline CD4 cell count (< or ≥200 cells/mm3), between the emtricitabine + tenofovir disoproxil fumarate group and the lamivudine/zidovudine group was 11.4%, and the 95% CI was 4.3% to 18.6% (p=0.002) at Week 48 and was 13% at Week 144, 95% CI = 4% to 22% (p=0.004).
Through 48 weeks of therapy, 80% and 70% of patients in the emtricitabine + tenofovir DF and the lamivudine/zidovudine arms, respectively, achieved and maintained HIV-1 RNA <50 copies/mL (64% and 56%, respectively, through Week 144). The difference in the percentages of responders stratified by baseline CD4 cell count (< or ≥200 cells/mm3) between the emtricitabine + tenofovir disoproxil fumarate group and the lamivudine/zidovudine group was 9.1%, and the 95% CI was 1.6% to 16.6% (p=0.021) at Week 48 and was 8% at Week 144, 95% CI = -1% to 17% (p=0.082). The mean increase from baseline in CD4 cell count was 190 cells/mm3for the emtricitabine + tenofovir disoproxil fumarate + efavirenz arm, and 158 cells/mm3 for the lamivudine/zidovudine + efavirenz arm (p=0.002) at Week 48 (312 and 271 cells/mm3, respectively, at Week 144, p=0.089).
The difference in the proportion of patients who achieved and maintained HIV-1 RNA <400 copies/mL through 48 weeks largely results from the higher number of discontinuations due to adverse events and other reasons in the zidovudine/lamivudine group in this open label study.
Emtricitabine:
Study 303: Emtricitabine QD + Stable Background Therapy (SBT) Compared to Lamivudine BID + SBT
Treatment outcomes through 48 weeks are presented in Table 19.
Table 19 Outcomes of Randomized Treatment at Week 48 (Study 303)
Outcome at Week 48
Emtricitabine + ZDV/d4T + NNRTI/PI
(N=294)
Lamivudine + ZDV/d4T + NNRTI/PI
(N=146)
Responder1 77% (67%) 82% (72%) Virologic Failure2 7% 8% Death 0% < 1% Study Discontinuation Due to Adverse Event 4% 0% Study Discontinuation For Other Reasons3 12% 10%
- 1. Patients achieved and maintained confirmed HIV RNA <400 copies/mL (<50 copies/mL) through Week 48.
- 2. Includes patients who failed to achieve virologic suppression or rebounded after achieving virologic suppression.
- 3. Includes lost to follow-up, patient withdrawal, non-compliance, protocol violation and other reasons.
The mean increase from baseline in CD4 cell count was 29 cells/mm3 for the emtricitabine arm and 61 cells/mm3 for the lamivudine arm. Through 48 weeks, in the emtricitabine group 2 patients (0.7%) experienced a new CDC Class C event, compared to 2 patients (1.4%) in the lamivudine group.
Tenofovir Disoproxil Fumarate:
Study 903: Tenofovir Disoproxil Fumarate (DF) + Lamivudine + Efavirenz Compared with Stavudine + Lamivudine + Efavirenz
Treatment outcomes at Week 48 and Week 144 are presented in Table 20 below.
Table 20 Outcomes of Randomized Treatment (Study 903)
Outcomes
| At Week 48 |
At Week 144
Tenofovir DF + 3TC + EFV (N=299) | Stavudine + 3TC + EFV (N=301) | Tenofovir DF + 3TC + EFV (N=299) |
Stavudine +
3TC + EFV (N=301)
| % | % | % |
%
Responder1
| 79% (76%) | 82% (79%) | 68% (62%) |
62% (58%) Virologic failure2
| 6% | 4% | 10% |
8% Rebound
| 5% | 3% | 8% |
7% Never suppressed
| 0% | 1% | 0% |
0% Added an antiretroviral agent
| 1% | 1% | 2% |
1% Death
| <1% | 1% | <1% |
2% Discontinued due to adverse event
| 6% | 6% | 8% |
13% Discontinued for other reasons3
| 8% | 7% | 14% |
15%
- 1. Patients achieved and maintained confirmed HIV-1 RNA <400 copies/mL (<50 copies/mL) at Weeks 48 and 144.
- 2. Includes confirmed viral rebound and failure to achieve confirmed <400 copies/mL through Week 48 and 144.
- 3. Includes lost to follow-up, patient’s withdrawal, noncompliance, protocol violation and other reasons.
Through 48 weeks, the mean increase from baseline in CD4 cell count was 169 cells/mm3 for the tenofovir disoproxil fumarate arm and 167 cells/mm3 for the stavudine arm. Eight patients in the tenofovir disoproxil fumarate group and six patients in the stavudine group experienced a new CDC Class C event.
Through 144 weeks, the mean increase from baseline in CD4 cell count was 263 cells/mm3 for the tenofovir disoproxil fumarate arm and 283 cells/mm3 for the stavudine arm. Eleven patients in the tenofovir disoproxil fumarate group and nine patients in the stavudine group experienced a new CDC Class C event.
Clinical Studies in HIV-1 Uninfected Subjects
The iPrEx study and Partners PrEP study support the use of emtricitabine/tenofovir disoproxil fumarate to help reduce the risk of acquiring HIV-1.
iPrEx Trial
The study demographics and trial design for the iPrEx Trial are summarized in Table 21.
Table 21 Study Demographics and Trial Design of iPrEx Trial
Study
No.
| Trial Design | Dosage, Route of Administration and Duration | Study Subjects (N=2499) | Mean Age (Range) |
Gender
CO-US- 104-0288 (iPrEx)
Randomized, double-blind, placebo- controlled multinational study in men and transgender women who have sex with men and with evidence of high risk behavior for HIV-1 infection Arm 1: emtricitabine/ tenofovir disoproxil fumaarate Arm 2: placebo | Arm 1: emtricitabine/tenofovir disoproxil fumarate tablet taken orally QD Arm 2: Placebo tablet taken orally QD Duration of treatment was variable. Subjects remained on treatment until the target number of seroconversion events was identified and the last enrolled study subject completed 48 weeks of treatment. Subjects were followed for at least 8 weeks follow up. HBsAg reactive subjects were followed for hepatic flares for 24 weeks after study drug discontinuation. Subjects who HIV-1 seroconverted during study were followed through at least 24 weeks after the last dose of study drugs | Randomized: 1251 – Emtricitabine/ tenofovir disoproxil fumarate 1248 –placebo Race: Asian – 5% Black – 9% White – 18% Hispanic/Latino
| 27 (18 to 67 years) |
Male:
100% subjects born male
29 (1%) report current identity as female
Evidence of high risk behavior included any one of the following reported to have occurred up to six months prior to study screening: no condom use during anal intercourse with an HIV-1 positive partner or a partner of unknown HIV-1 status; anal intercourse with more than 3 sex partners; exchange of money, gifts, shelter or drugs for anal sex; sex with male partner and diagnosis of sexually transmitted infection; no consistent use of condoms with sex partner known to be HIV-1 positive.
All subjects received monthly HIV-1 testing, risk-reduction counseling, condoms and management of sexually transmitted infections.
Partners PrEP Study
The demographics and trial design for the Partners PrEP study are summarized in Table 22.
Table 22 Study Demographics and Trial Design of Partners PrEP Trial
Study
No.
| Trial Design | Dosage, Route of Administration and Duration | Study Subjects (N=4758) | Mean Age (Range) |
Gender
CO-US- 104-0380 (Partners PrEP)
Randomized, double-blind, placebo- controlled 3-arm trial conducted in serodiscordant heterosexual couples in Kenya and Uganda | Arm 1: tenofovir disoproxil fumarate tablet taken orally QD Arm 2: emtricitabine/tenofovir disproxil fumarate tablet taken orally QD Arm 3: Matched Placebo tablets, taken orally QD. Duration of study drug treatment was variable. Subjects received the assigned study drugs once daily for a minimum of 24 months up to a maximum of 36 months. | Randomized: 1589 –TDF 1583 – Emtricitabine/ tenofovir disproxil fumarate 1586 – placebo | 33−34 |
Female: 38%
Male
62%
All subjects received monthly HIV-1 testing, evaluation of adherence, assessment of sexual behavior, and safety evaluations. Women were also tested monthly for pregnancy. Women who became pregnant during the trial had study drug interrupted for the duration of the pregnancy and while breastfeeding. The uninfected partner subjects were predominantly male (61 to 64% across study drug groups).
Study Results
iPrEx Study
Subjects were followed for 4237 person-years. The primary outcome measure for the study was the incidence of documented HIV-1 seroconversion. The results of the iPrEx study are summarized below in Table 23.
Table 23 iPrEx Study: Relative Risk Reduction Through End-of-
Treatment Cutoff (Primary Analysis; mITT Analysisa)
| Placebo | Emtricitabine/ Tenofovir disoproxil fumarate |
P-valueb
End of Treatmentc
mITT Analysis
| N=1217 | N=1224 |
0.002 Person-Years follow-upd
| 2113 | 2124 |
Number of HIV-1 Infections (Seroconversions)
| 83 | 48 |
Relative Risk Reduction (2-sided 95% CI) 42% (18%, 60%) Abbreviation: CI = confidence interval
a Modified Intent-to-Treat (mITT) analysis excludes subjects who do not have follow-up HIV test and who were infected at enrollment
b p-values by log rank test
c End of treatment is defined as the next post-treatment visit after this date (approximately one month).
This analysis excludes post-treatment stop seroconversions.
d Time to first evidence of seroconversion for those with event
Risk reduction was found to be higher (53%; 95% CI: 34% to 72%) among subjects who reported previous unprotected anal intercourse (URAI) at screening (732 and 753 subjects reported URAI within the last 12 weeks at screening in the emtricitabine/tenofovir disoproxil fumarate and placebo groups, respectively). In a post-hoc case control study of plasma and intracellular drug levels in about 10% of study subjects, risk reduction appeared to be the greatest in subjects with detectable intracellular tenofovir. Efficacy was therefore strongly correlated with adherence.
Partners PrEP Study
The efficacy analyses results of the Partner’s PrEP study are summarized in Table 24 below.
Table 24 Partners PrEP Study: Relative Risk Reduction and HIV-1
Seroincidence for Partner Subjects (Primary Analysis; mITT Analysisa)
| Emtricitabine /Tenofovir disoproxil fumarate | Tenofovir disoproxil fumarate | Placebo |
Total mITT Analysis
| N=1576 | N=1579 | N=1578 |
N=4733
Person-years of follow-upb
| 2616 | 2604 | 2607 |
7827
Number of HIV-1 Infections (Seroconversions)
| 13 | 17 | 52 |
82
HIV-1 incidence, per 100 person-years
| 0.50 | 0.65 | 1.99 |
1.05
Relative Risk Reduction (2-sided 95% CI)
| 75% (55-87%) | 67% (44-81%) |
p-valuec
| <0.0001 | <0.0001 |
a Modified Intent-to-Treat (mITT) analysis excludes subjects who were infected at enrollment b Time to first evidence of seroconversion for those with event
c p-values using Cox’s proportional hazards model for the active study drug relative to placebo
Two of the 13 seroconversions in the emtricitabine/tenofovir disoproxil fumarate arm and 3 of the 52 seroconversions in the placebo arm occurred in women during treatment interruptions for pregnancy. In a post-hoc case control study of plasma drug levels in about 10% of study subjects, risk reduction was most pronounced in subjects with detectable plasma tenofovir. Efficacy was therefore strongly correlated with adherence.
VIROLOGY (MICROBIOLOGY)
Mechanism of Action
Emtricitabine: Emtricitabine, a synthetic nucleoside analog of cytidine, is phosphorylated by cellular enzymes to form emtricitabine 5'-triphosphate. Emtricitabine 5'-triphosphate inhibits the activity of the HIV-1 reverse transcriptase (RT) by competing with the natural substrate deoxycytidine 5'-triphosphate and by being incorporated into nascent viral DNA which results in chain termination. Emtricitabine 5′-triphosphate is a weak inhibitor of mammalian DNA polymerases α, β, ε and mitochondrial DNA polymerase γ.
Tenofovir disoproxil fumarate: Tenofovir disoproxil fumarate is an acyclic nucleoside phosphonate diester analog of adenosine monophosphate. Tenofovir disoproxil fumarate requires initial diester hydrolysis for conversion to tenofovir and subsequent phosphorylations by cellular enzymes to form tenofovir diphosphate. Tenofovir diphosphate inhibits the activity of HIV-1 RT by competing with the natural substrate deoxyadenosine 5′-triphosphate and, after incorporation into DNA, by DNA chain termination. Tenofovir diphosphate is a weak inhibitor of mammalian DNA polymerases α, β, and mitochondrial DNA polymerase γ.
Antiviral Activity
Emtricitabine and tenofovir disoproxil fumarate: In combination studies evaluating the in vitro antiviral activity of emtricitabine and tenofovir together, synergistic antiviral effects were observed. Additive to synergistic effects were observed in combination studies with protease inhibitors, integrase strand transfer inhibitors, and with nucleoside and non- nucleoside analogue inhibitors of HIV-1 reverse transcriptase.
Emtricitabine: The in vitro antiviral activity of emtricitabine against laboratory and clinical isolates of HIV was assessed in lymphoblastoid cell lines, the MAGI-CCR5 cell line, and peripheral blood mononuclear cells. The IC50 values for emtricitabine were in the range of 0.0013 to 0.64 mcM (0.0003 to 0.158 mcg/mL). In drug combination studies of emtricitabine with nucleoside reverse transcriptase inhibitors (abacavir, lamivudine, stavudine, zalcitabine, or zidovudine), non-nucleoside reverse transcriptase inhibitors (delavirdine, efavirenz, or nevirapine), protease inhibitors (amprenavir, nelfinavir, ritonavir, or saquinavir), and with integrase strand transfer inhibitors, additive to synergistic effects were observed. Most of these drug combinations have not been studied in humans. Emtricitabine displayed antiviral activity in vitro against HIV-1 clades A, B, C, D, E, F, and G (IC50 values ranged from 0.007 to 0.075 mcM) and showed strain specific activity against HIV-2 (IC50 values ranged from 0.007 to 1.5 mcM).
Tenofovir disoproxil fumarate: The in vitro antiviral activity of tenofovir against laboratory and clinical isolates of HIV-1 was assessed in lymphoblastoid cell lines, primary monocyte/macrophage cells and peripheral blood lymphocytes. The IC50 (50% inhibitory concentration) values for tenofovir were in the range of 0.04 to 8.5 mcM. In drug combination studies of tenofovir with integrase strand transfer inhibitors, nucleoside reverse transcriptase inhibitors (abacavir, didanosine, lamivudine, stavudine, zalcitabine, or zidovudine), non-nucleoside reverse transcriptase inhibitors (delavirdine, efavirenz, or
nevirapine), and protease inhibitors (amprenavir, indinavir, nelfinavir, ritonavir, or saquinavir), additive to synergistic effects were observed. Most of these drug combinations have not been studied in humans. Tenofovir displayed antiviral activity in vitro against HIV-1 clades A, B, C, D, E, F, G, and O (IC50 values ranged from 0.5 to 2.2 mcM).
Prophylactic Activity in a Nonhuman Primate Model of HIV Transmission
Emtricitabine and tenofovir disoproxil fumarate: The prophylactic activity of the combination of daily oral emtricitabine and tenofovir disoproxil fumarate was evaluated in a controlled study of macaques inoculated once weekly for 14 weeks with SIV/HIV-1 chimeric virus (SHIV) applied to the rectal surface. Of the 18 control animals, 17 became infected after a median of 2 weeks. In contrast, 4 of the 6 animals treated daily with oral emtricitabine and tenofovir disoproxil fumarate remained uninfected and the two infections that did occur were significantly delayed until 9 and 12 weeks and exhibited reduced viremia. An M184I-expressing FTC-resistant variant emerged in 1 of the 2 macaques after 3 weeks of continued drug exposure.
Resistance
Emtricitabine and tenofovir disoproxil fumarate: HIV-1 isolates with reduced susceptibility to the combination of emtricitabine and tenofovir have been selected in vitro. Genotypic analysis of these isolates identified the M184V/I and/or K65R amino acid substitutions in the viral RT. In addition, a K70E substitution in HIV-1 reverse transcriptase has been selected by tenofovir and results in reduced susceptibility to tenofovir.
In Study 934 (emtricitabine + tenofovir disoproxil fumarate + efavirenz compared with lamivudine/zidovudine + efavirenz), resistance analysis was performed on HIV isolates from all patients with >400 copies/mL of HIV-1 RNA at Week 144 or early discontinuation. Genotypic resistance to efavirenz, predominantly the K103N mutation, was the most common form of resistance that developed. Resistance to efavirenz occurred in 13/19 (68%) analyzed patients in the emtricitabine + tenofovir disoproxil fumarate group and in 21/29 (72%) analyzed patients in the lamivudine/zidovudine group. The M184V mutation, associated with resistance to emtricitabine and lamivudine, was observed in 2/19 (11%) analyzed patients in the emtricitabine + tenofovir disoproxil fumarate group and in 10/29 (34%) analyzed patients in the lamivudine/zidovudine group.
In treatment-naïve patients treated with emtricitabine + tenofovir disoproxil fumarate + efavirenz, none of the HIV isolates from 19 patients analyzed for resistance showed reduced susceptibility to tenofovir or the presence of the K65R or K70E mutation.
Emtricitabine: Emtricitabine-resistant isolates of HIV have been selected in vitro. Genotypic analysis of these isolates showed that the reduced susceptibility to emtricitabine was associated with a mutation in the HIV RT gene at codon 184 which resulted in an amino acid substitution of methionine by valine or isoleucine (M184V/I).
Emtricitabine-resistant isolates of HIV have been recovered from some patients treated with emtricitabine alone or in combination with other antiretroviral agents. In a clinical study, viral isolates from 6/16 (37.5%) treatment-naïve patients with virologic failure showed >20-
fold reduced susceptibility to emtricitabine. Genotypic analysis of these isolates showed that the resistance was due to M184V/I mutations in the HIV RT gene.
Tenofovir disoproxil fumarate: The K65R and K70E substitutions selected by tenofovir are also selected in some HIV-1-infected patients treated with abacavir or didanosine. HIV-1 isolates with the K65R and K70E substitutions also showed reduced susceptibility to emtricitabine and lamivudine. Therefore, cross-resistance among these NRTIs may occur in patients whose virus harbors the K65R or K70E substitutions. HIV-1 isolates with reduced susceptibility to tenofovir have been selected in vitro. These viruses expressed a K65R mutation in RT and showed a 2–4 fold reduction in susceptibility to tenofovir.
Tenofovir-resistant isolates of HIV-1 have also been recovered from some patients treated with tenofovir disoproxil fumarate in combination with certain antiretroviral agents. In treatment-naive patients, 7/29 (24%) isolates from patients failing tenofovir disoproxil fumarate + lamivudine + efavirenz at 48 weeks showed >1.4 fold (median 3.4) reduced susceptibility in vitro to tenofovir.
In treatment-experienced patients, 14/304 (4.6%, studies 902 and 907) isolates from patients failing tenofovir disoproxil fumarate at 96 weeks showed >1.4 fold (median 2.7) reduced susceptibility to tenofovir. Genotypic analysis of the resistant isolates showed a mutation in the HIV-1 RT gene resulting in the K65R amino acid substitution.
iPrEx Trial: In a clinical study of HIV-1 seronegative subjects (iPrEx Trial, see CLINICAL TRIALS), no mutations associated with resistance to emtricitabine or tenofovir were detected at the time of seroconversion among 48 subjects in the emtricitabine/tenofovir disoproxil fumarate group and 83 subjects in the placebo group who became infected with HIV-1 during the trial. Ten subjects were observed to be HIV-1 infected at time of enrollment. The M184V/I substitutions associated with resistance to emtricitabine were observed in 3 of the 10 subjects (2 of 2 in the emtricitabine/tenofovir disoproxil fumarate group and 1 of 8 in the placebo group). One of the two subjects in the emtricitabine/tenofovir disoproxil fumarate group harbored wild type virus at enrollment and developed the M184V substitution 4 weeks after enrollment. The other subject had indeterminate resistance at enrollment but was found to have the M184I substitution 4 weeks after enrollment.
Partners PrEP Trial: In a clinical study of HIV-1 seronegative subjects (Partners PrEP Trial, see CLINICAL TRIALS), no variants expressing amino acid substitutions associated with resistance to emtricitabine or tenofovir were detected at the time of seroconversion among 12 subjects in the emtricitabine/tenofovir disoproxil fumarate group, 15 subjects in the tenofovir disoproxil fumarate group, and 51 subjects in the placebo group. Fourteen subjects were observed to be HIV-1 infected at the time of enrollment (3 in the emtricitabine/tenofovir disoproxil fumarate group, 5 in the tenofovir disoproxil fumarate group, and 6 in the placebo group). One of the three subjects in the emtricitabine/tenofovir disoproxil fumarate group who was infected with wild type virus at enrollment selected an M184V expressing virus by week
- 12. Two of the five subjects in the tenofovir disoproxil fumarate group had tenofovir-resistant viruses at the time of seroconversion; one subject infected with wild type virus at enrollment developed a K65R substitution by week 16, while the second subject had virus expressing the combination of D67N and K70R substitutions upon seroconversion at week 60, although baseline virus was not genotyped and it is unclear if the resistance emerged or was
transmitted. Following enrollment, 4 subjects (2 in the tenofovir disoproxil fumarate group, 1 in the emtricitabine/tenofovir disoproxil fumarate group, and 1 in the placebo group) had virus expressing K103N or V106A substitutions, which confer high-level resistance to NNRTIs but have not been associated with tenofovir or emtricitabine and may have been present in the infecting virus.
Cross-resistance
Emtricitabine and tenofovir disoproxil fumarate: Cross-resistance among certain nucleoside reverse transcriptase inhibitors (NRTIs) has been recognized. The M184V/I and/or K65Ror K70E substitutions selected in vitro by the combination of emtricitabine and tenofovir are also observed in some HIV-1 isolates from subjects failing treatment with tenofovir in combination with either lamivudine or emtricitabine, and either abacavir or didanosine. Therefore, cross-resistance among these drugs may occur in patients whose virus harbors either or both of these amino acid substitutions.
Emtricitabine: Emtricitabine-resistant isolates (M184V/I) were cross-resistant to lamivudine and zalcitabine but retained susceptibility in vitro to didanosine, stavudine, tenofovir, zidovudine, and NNRTIs (delavirdine, efavirenz, and nevirapine). Isolates from heavily treatment-experienced patients containing the M184V/I amino acid substitution in the context of other NRTI resistance-associated substitutions may retain susceptibility to tenofovir. HIV-1 isolates containing the K65R substitution, selected in vivo by abacavir, didanosine, tenofovir, and zalcitabine, demonstrated reduced susceptibility to inhibition by emtricitabine. Viruses harboring mutations conferring reduced susceptibility to stavudine and zidovudine (M41L, D67N, K70R, L210W, T215Y/F, K219Q/E) or didanosine (L74V) remained sensitive to emtricitabine. HIV-1 containing the K103N substitution associated with resistance to NNRTIs was susceptible to emtricitabine.
Tenofovir disoproxil fumarate: HIV-1 isolates from patients (N=20) whose HIV-1 expressed a mean of 3 zidovudine-associated RT amino acid substitutions (M41L, D67N, K70R, L210W, T215Y/F, or K219Q/E/N) showed a 3.1-fold decrease in the susceptibility to tenofovir. Multinucleoside resistant HIV-1 with a T69S double insertion mutation in the RT showed reduced susceptibility to tenofovir.
NON-CLINICAL TOXICOLOGY
Toxicology
Tenofovir and tenofovir disoproxil fumarate administered in toxicology studies to rats, dogs and monkeys at exposures (based on AUCs) greater than or equal to 6-fold those observed in humans caused bone toxicity. In monkeys the bone toxicity was diagnosed as osteomalacia. Osteomalacia observed in monkeys appeared to be reversible upon dose reduction or discontinuation of tenofovir. In rats and dogs, the bone toxicity manifested as reduced bone mineral density. The mechanism(s) underlying bone toxicity is unknown.
Evidence of renal toxicity was noted in 4 animal species. Increases in serum creatinine, BUN, glycosuria, proteinuria, phosphaturia, and/or calciuria and decreases in serum
phosphate were observed to varying degrees in these animals. These toxicities were noted at exposures (based on AUCs) 2–20 times higher than those observed in humans. The relationship of the renal abnormalities, particularly the phosphaturia, to the bone toxicity is not known.
Carcinogenesis
Emtricitabine: In long-term oral carcinogenicity studies of emtricitabine, no drug-related increase in tumor incidence was found in mice at doses up to 750 mg/kg/day (26 times the human systemic exposure at the therapeutic dose of 200 mg/day) or in rats at doses up to 600 mg/kg/day (31 times the human systemic exposure at the therapeutic dose).
Tenofovir disoproxil fumarate: Long-term oral carcinogenicity studies were conducted in mice and rats receiving tenofovir disoproxil fumarate. At the high dose in female mice, liver adenomas were increased at exposures 16 times that in humans. In the mouse study, (60/sex/group), one male and two female mice in the 600 mg/kg/day group (15 times the human systemic exposure at the recommended human dose of 300 mg/day) developed duodenal tumors. The mechanism underlying this effect is uncertain but may relate to high local drug concentrations in the gastrointestinal tract. No treatment-related tumors were seen in mice in the 100 or 300 mg/kg/day groups. In the rat study (60/sex/group) at doses of 30, 100, and 300 mg/kg/day (approximately 5 times human exposure), no treatment-related increase in tumor incidence was observed.
Mutagenesis
Emtricitabine: Emtricitabine was not genotoxic in the reverse mutation bacterial test (Ames test), mouse lymphoma or mouse micronucleus assays.
Tenofovir disoproxil fumarate: Tenofovir disoproxil fumarate was negative in the in vitro bacterial mutation (Ames) assay (Salmonella-Eschericia coli/Mammalian-Microsome Reverse Mutation Assay) but positive in the in vitro mouse lymphoma assay (L5178Y TK +/- Forward Mutation Assay), with and without metabolic activation. Tenofovir disoproxil fumarate was negative in the in vivo mouse micronucleus assay at plasma exposure levels of more than 10x the human exposure.
Impairment of Fertility
Emtricitabine: Emtricitabine did not affect fertility in male rats at approximately 140-fold or in male and female mice at approximately 60-fold higher exposures (AUC) than in humans given the recommended 200 mg daily dose. Fertility was normal in the offspring of mice exposed daily from before birth (in utero) through sexual maturity at daily exposures (AUC) of approximately 60-fold higher than human exposures at the recommended 200 mg daily dose.
Tenofovir disoproxil fumarate: Reproductive toxicity was evaluated in rats and rabbits. Tenofovir disoproxil fumarate had no adverse effects on fertility or general reproductive performance in rats at doses up to 600 mg/kg/day. Tenofovir disoproxil fumarate had no adverse effects on embryo-fetal development in rats at doses 450 mg/kg/day and in rabbits at
doses up to 300 mg/kg/day. In a study of effects on peri- and postnatal development in rats, effects considered due to maternal toxicity (450 to 600 mg/kg/day) were reduced survival and a slight delay in sexual maturation in the F1 generation. There were no adverse effects on growth, development, behavior, or reproductive parameters at non-maternally toxic doses (150 mg/kg/day).
Pregnancy
Emtricitabine: The incidence of fetal variations and malformations was not increased in embryofetal toxicity studies performed with emtricitabine in mice at exposures (AUC) approximately 60-fold higher and in rabbits at approximately 120-fold higher than human exposures at the recommended daily dose.
Tenofovir disoproxil fumarate: Reproduction studies have been performed in rats and rabbits at doses up to 14 and 19 times the human dose based on body surface area comparisons and revealed no evidence of impaired fertility or harm to the fetus due to tenofovir. Reduced pup body weights, survival and delay in sexual maturation was observed in a peri- and postnatal toxicity study in rats at the maternally toxic doses of 450 and 600 mg/kg (approximately 14 and 19 times the human dose based on body surface area comparisons).
Antiretroviral Pregnancy Registry
To monitor fetal outcomes of pregnant women exposed to ART (antiretroviral therapy) including APO-EMTRICITABINE-TENOFOVIR, an Antiretroviral Pregnancy Registry has been established. Healthcare providers are encouraged to register patients by calling 800–258–4263.
REFERENCES
- 1.
Deeks SG, Barditch-Crovo P, Lietman PS, Hwang F, Cundy KC, Rooney JF, et al.
Safety, pharmacokinetics, and antiretroviral activity of intravenous 9-[2-(R)- (phosphonomethoxy)propyl]adenine, a novel anti-human immunodeficiency virus (HIV) therapy, in HIV-infected adults. Antimicrob Agents Chemother 1998 Sep;42 (9):2380-4.
- 2.
Barditch-Crovo P, Deeks SG, Collier A, Safrin S, Coakley DF, Miller M, et al. Phase
I/II trial of the pharmacokinetics, safety, and antiretroviral activity of tenofovir disoproxil fumarate in HIV-1 infected adults. Antimicrob Agents Chemother 2001 Oct;45 (10):2733-9.
- 3.
Schooley RT, Ruane P, Myers RA, Beall G, Lampiris H, Berger D, et al. Tenofovir
DF in antiretroviral-experienced patients: results from a 48-week, randomized, double-blind study. AIDS 2002 Jun 14;16 (9):1257-63.
- 4.
Margot NA, Isaacson E, McGowan I, Cheng AK, Schooley RT, Miller MD.
Genotypic and phenotypic analyses of HIV-1 in antiretroviral-experienced patients treated with tenofovir DF. AIDS 2002 Jun 14;16 (9):1227-35.
- 5. Gallant, J.E., DeJesus, E., Arribas, J.R., Pozniak, A.L., Gazzard, B., Campo, R.E. et al. Tenofovir DF, Emtricitabine and Efavirenz versus Zidovudine, Lamivudine and Efavirenz for HIV. New Engl. J. Med. 2006 (354): 251-260.
- 6. EMEA Public Statement, Efficacy and safety concerns regarding the co- administration of tenofovir disoproxil fumarate (TDF, Viread) and didanosine (ddI, Videx), 2005. http://www.emea.eu.int/pdfs/human/press/pus/6233105en.pdf
- 7.
Podzamczer D, Ferrer E, Gatell JM, Niubo J, Dalmau D, Leon A, Knobel H, Polo C,
Iniguez D, Ruiz I. Early virological failure with a combination of tenofovir, didanosine and efavirenz. Antiviral Therapy 2005; 10: 171-177
- 8.
Benaboud, S., et al. 2011. Concentrations of Tenofovir and Emtricitabine in Breast
Milk of HIV-1 Infected Women in Abidjan, Côte d’Ivoire, in the ANRS 12109 TEmAA Study, Step 2. Antimicrob. Agents Chemother. 55: 1315-1317.
- 9. Baeten J, Donnell D, Ndase P, Mugo N, Campbell J, Wangisi J, et al. Antiretroviral prophylaxis for HIV prevention in heterosexual men and women. N Engl J Med 2012;367 (5):399-410.
- 10.
Grant RM, Lama JR, Anderson PL, McMahan V, Liu AY, Vargas L, et al. Preexposure
Chemoprophylaxis for HIV Prevention in Men Who Have Sex with Men. N Engl J Med 2010;363 (27):2587-99.
- 11.
Product Monograph - TRUVADA® (emtricitabine/tenofovir disoproxil fumarate)
Tablets, 200 mg/300 mg. Gilead Sciences Inc., Submission Control No.:215258, Date of Revision: July 5, 2018.
| IMPORTANT: PLEASE READ |
PART III. CONSUMER INFORMATION
PrAPO-EMTRICITABINE-TENOFOVIR
Emtricitabine and Tenofovir Tablets
Apotex Standard
This leaflet is Part III of a three part “Product Monograph” published when APO-EMTRICITABINE-TENOFOVIR was approved for sale in Canada and is designed specifically for consumers. This leaflet is a summary and will not tell you everything about APO-EMTRICITABINE-TENOFOVIR. Contact your healthcare professional if you have any questions about the drug.
ABOUT THIS MEDICATION
What the medication is used for:
APO-EMTRICITABINE-TENOFOVIR is a type of medicine called an HIV (human immunodeficiency virus) nucleoside analog reverse transcriptase inhibitor (NRTI). APO-EMTRICITABINE-TENOFOVIR contains 2 medicines, emtricitabine and tenofovir disoproxil fumarate, combined in one pill.
APO-EMTRICITABINE-TENOFOVIR is used:
To treat HIV-1 Infection when used with other anti-HIV
medicines in adults.
OR
To help reduce the risk of getting HIV-1 infection when
used with safer sex practices in:
O HIV-1 negative men who have sex with men, who
are at high risk of getting infected with HIV-1 through sex.
O Male-female sex partners when one partner has HIV-1infection and the other does not.
This is sometimes called Pre-Exposure Prophylaxis or PrEP. For more information on APO-EMTRICITABINE-TENOFOVIR for PrEP, log onto
http://www.apotex.com/ca/en/.
APO-EMTRICITABINE-TENOFOVIR is for adults age 18
and older. Emtricitabine and tenofovir disoproxil fumarate is not indicated in children under age 18 or adults over age
65.
What it does:
Use of APO-EMTRICITABINE-TENOFOVIR to treat
HIV-1 infection:
When used with other HIV-1 medicines to treat HIV-1 infection, APO-EMTRICITABINE-TENOFOVIR helps block HIV reverse transcriptase, a chemical in your body (enzyme) that is needed for HIV to multiply. APO-EMTRICITABINE-TENOFOVIR lowers the amount of HIV in the blood (viral load). Lowering the amount of HIV in the blood lowers the chance of
infections that happen when your immune system is weak (opportunistic infections).
HIV infection destroys CD4+ (T) cells, which are important to the immune system. The immune system helps fight infection. After a large number of T cells are destroyed, acquired immune deficiency syndrome (AIDS) develops. APO-EMTRICITABINE-TENOFOVIR may also help to increase the number of T cells (CD4+ cells).
APO-EMTRICITABINE-TENOFOVIR does not cure HIV-1 infection or AIDS. If you have HIV-1 infection, you must stay on continuous HIV therapy to control HIV infection and decrease HIV-related illnesses. People taking APO-EMTRICITABINE-TENOFOVIR may still get opportunistic infections or other conditions that happen with HIV infection. Opportunistic infections are infections that develop because the immune system is weak. Some of these conditions are pneumonia, herpes virus infections, and Mycobacterium avium complex (MAC) infections.
- Use of APO-EMTRICITABINE-TENOFOVIR to reduce the risk of HIV-1 infection (PrEP indication):
When used with safer sex practices, APO-
EMTRICITABINE-TENOFOVIR may help to reduce the risk of getting HIV-1 infection:
- APO-EMTRICITABINE-TENOFOVIR works better to reduce the risk of getting HIV-1 when the medicines are in your bloodstream before you are exposed to HIV-1.
It is very important that you see your healthcare professional regularly while taking APO-EMTRICITABINE-TENOFOVIR.
Considerations when APO-EMTRICITABINE-TENOFOVIR is used for PrEP:
- Together with your healthcare professional, you need to decide whether APO-EMTRICITABINE-TENOFOVIR is right for you.
- APO-EMTRICITABINE-TENOFOVIR can only help reduce your risk of getting HIV-1 before you are infected.
Do not take APO-EMTRICITABINE-TENOFOVIR to help reduce your risk of getting
HIV-1 if:
you already have HIV-1 infection. If you are
HIV-1 positive, you need to take other medicines with APO-EMTRICITABINE-TENOFOVIR to treat HIV-1. APO-EMTRICITABINE-TENOFOVIR by itself is not a complete treatment for HIV-1.
you do not know your HIV-1 infection status. You may already be HIV-1 positive. You need to take other HIV-1 medicines with APO-
EMTRICITABINE-TENOFOVIR to treat HIV-1.
- Your healthcare professional will run tests to determine that you are HIV- negative before starting PrEP treatment.
| IMPORTANT: PLEASE READ |
When it should not be used:
Do not use APO-EMTRICITABINE-TENOFOVIR if:
You are allergic (hypersensitive) to any of the ingredients in this
formulation ( see: What the medicinal ingredients are; What the important nonmedicinal ingredients are)
Do not use APO-EMTRICITABINE-TENOFOVIR to
reduce the risk of getting HIV if you already have HIV or do not know your HIV status.
What the medicinal ingredients are:
- emtricitabine
- tenofovir disoproxil fumarate
What the important nonmedicinal ingredients are: anhydrous lactose, colloidal silicon dioxide, crospovidone, FD&C Blue No. 2, magnesium stearate, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
What dosage forms it comes in:
APO-EMTRICITABINE-TENOFOVIR is available as tablets. Each tablet contains 200 mg of emtricitabine and 300 mg of tenofovir disoproxil fumarate (which is equivalent to 245 mg of tenofovir disoproxil), as active ingredients. The tablets are blue, capsule-shaped, biconvex, film-coated, engraved with “APO” on one side, “E-T” on the other side. Available in bottles of 30 and 100 tablets with desiccants and blister pack of 100 tablets.
| WARNINGS AND PRECAUTIONS |
Serious Warnings and Precautions
The most serious possible side effect is harm to the
kidneys, including damage to kidney cells, kidney tissue inflammation and kidney failure. Your healthcare professional may monitor your kidney function before beginning and while receiving APO-EMTRICITABINE-TENOFOVIR. Some patients treated with tenofovir disoproxil fumarate (a component of APO-EMTRICITABINE-
TENOFOVIR) have had kidney problems. Your healthcare professional may need to perform additional blood tests if you have had kidney problems in the past or need to take another drug that can cause kidney problems.
If you are also infected with the Hepatitis B Virus,
“flare-ups” of Hepatitis B Virus infection, in which the disease suddenly returns in a worse way than before, can occur if you stop taking APO-EMTRICITABINE-TENOFOVIR. Do not stop taking APO-EMTRICITABINE-TENOFOVIR without your healthcare professional’s advice. If you stop taking APO-EMTRICITABINE-TENOFOVIR, tell your healthcare professional immediately about any new,
unusual or worsening symptoms that you notice after stopping treatment. After you stop taking APO-EMTRICITABINE-TENOFOVIR, your healthcare professional will still need to check your health and take blood tests to check your liver for several months. APO-EMTRICITABINE-TENOFOVIR is not approved for the treatment of Hepatitis B Virus infection.
The class of medicines to which APO-
EMTRICITABINE-TENOFOVIR belong (NRTIs) can cause a condition called lactic acidosis, together with an enlarged liver. Non-specific symptoms such as nausea, vomiting and stomach pain might indicate the development of lactic acidosis. This rare but serious side effect has occasionally been fatal. Lactic acidosis occurs more often in women, particularly if they are very overweight. You should consult your healthcare professional immediately if such symptoms occur while you are receiving APO-EMTRICITABINE-TENOFOVIR. The symptoms that may indicate lactic acidosis include: feeling very weak, tired or uncomfortable; unusual or unexpected stomach discomfort; feeling cold; feeling dizzy or lightheaded; suddenly developing a slow or irregular heartbeat. If you notice these symptoms, stop taking APO-EMTRICITABINE-TENOFOVIR and consult a healthcare professional immediately.
- Tenofovir disoproxil fumarate caused harm to the bones of animals. Tenofovir disoproxil fumarate reduced bone density in humans. If you notice bone pain, suffer a bone fracture, or other bone problem, consult your healthcare professional. If you have bone problems, you may wish to discuss calcium and/or vitamin D supplements with your healthcare professionals.
- APO-EMTRICITABINE-TENOFOVIR should only be used for the PrEP indication if you are HIV-negative before and during treatment. Discuss with your healthcare professional if you have had a recent flu-like illness. Your healthcare professional will run tests to confirm that you are HIV negative before and during APO-EMTRICITABINE-TENOFOVIR treatment.
Do NOT take APO-EMTRICITABINE-TENOFOVIR if:
- you are on other medications that may affect your kidneys and have not discussed this with your healthcare professional.
- you have or are at known risk for any type of bone disease or bone related problems and have not discussed this with your healthcare professional.
- you are allergic to APO-EMTRICITABINE-TENOFOVIR or any of its ingredients. The medicinal ingredients are emtricitabine and tenofovir DF (see What the important
| IMPORTANT: PLEASE READ |
nonmedicinal ingredients in APO-EMTRICITABINE-TENOFOVIR are).
you are already taking 3TC® (lamivudine), ATRIPLA®
(efavirenz/emtricitabine/tenofovir disoproxil fumarate), Combivir® (lamivudine/zidovudine), COMPLERA®
(emtricitabine/rilpivirine/tenofovir disoproxil fumarate), DESCOVY® (emtricitabine and tenofovir alafenamide), EMTRIVA® (emtricitabine), GENVOYA® (elvitegravir, cobicistat, emtricitabine, tenofovir alafenamide), Heptovir®
(lamivudine), Kivexa® (abacavir sulfate and lamivudine), STRIBILD® (elvitegravir/cobicistat/emtricitabine/tenofovir disoproxil fumarate), Triumeq® (abacavir sulfate/dolutegravir sodium/lamivudine), Trizivir® (abacavir
sulfate/lamivudine/zidovudine), or VIREAD® (tenofovir disoproxil fumarate) because these medicines contain the same or similar active ingredients
you are also taking HEPSERA® (adefovir dipivoxil) to treat
your HBV infection.
Changes in your immune system (Immune Reconstitution Inflammatory Syndrome) can happen when an HIV-1 infected person starts taking HIV medicines. Your immune system may get stronger and begin to fight infections that have been hidden in your body for a long time, or you could develop an autoimmune disease in which your immune system reacts against your own body (e.g. Grave's disease (which affects the thyroid gland), Guillain-Barrésyndrome (which affects the nervous system) or polymyositis (which affects the muscles)) and it may develop at any time, sometimes months later after the start of HIV therapy. Sometimes symptoms can be severe, so if you develop high temperature (fever), joint or muscle pain, redness, rash, swelling or fatigue, or any new symptoms, contact your healthcare professional right away.
Before taking APO-EMTRICITABINE-TENOFOVIR to reduce your risk of getting HIV-1 infection (PrEP indication):
You must get tested to be sure you are HIV-negative. It is
important that you also get tested at least every 3 months as recommended by your healthcare provider while taking APO-EMTRCITABINE-TENOFOVIR. Do not take APO-EMTRICITABINE-TENOFOVIR to reduce the risk of getting HIV (PrEP) unless you are confirmed to be HIV-negative.
Tell your healthcare provider if you have any of the
following symptoms within the last month before you start taking APO-EMTRICITABINE-TENOFOVIR or at any time while taking APO-EMTRICITABINE-TENOFOVIR:
- tiredness
- fever
- sweating a lot (especially at night)
- rash
- vomiting or diarrhea
- joint or muscle aches
headache
- sore throat
- enlarged lymph nodes in the neck or groin
These may be signs of HIV infection and you may need to have a different kind of test to diagnose HIV. If you are already taking APO-EMTRICITABINE-TENOFOVIR to prevent HIV-1 infection (PrEP), your healthcare provider may tell you to stop taking APO-EMTRICITABINE-TENOFOVIR until an HIV test confirms that you do not have HIV-1 infection. For more information on APO-EMTRICITABINE-TENOFOVIR for PrEP, log onto http://www.apotex.com/ca/en/.
Just taking APO-EMTRICITABINE-TENOFOVIR may not keep you from getting HIV.
You must still practice safer sex at all times. Do not have any kind of sex without protection. Always practice safer sex by using a latex or polyurethane condom to lower the chance of sexual contact with semen, vaginal secretions, or blood.
You must also use other prevention methods to keep from getting HIV.
- Know your HIV-1 status and the HIV-1 status of your partners. •While taking APO-EMTRICITABINE-TENOFOVIR, get tested at least every 3 months for HIV, as recommended by your healthcare provider. Ask your partners to get tested.
- If you think you were exposed to HIV-1, tell your healthcare provider right away. They may want to do more tests to be sure you are still HIV-negative.
- Get tested for other sexually transmitted infections such as syphilis and gonorrhea. These infections make it easier for HIV to infect you.
- Get information and support to help reduce risky sexual behavior.
- Have fewer sex partners.
- Do not miss any doses of APO-EMTRICITABINE-TENOFOVIR. Missing doses may increase your risk of getting HIV-1 infection.
BEFORE you use APO-EMTRICITABINE-TENOFOVIR (emtricitabine / tenofovir disoproxil fumarate) talk to your healthcare professional:
If you are pregnant or planning to become pregnant: Pregnant mothers should not take APO-EMTRICITABINE-TENOFOVIR unless specifically directed by the healthcare professional.
If you are a female who is taking APO-EMTRICITABINE-TENOFOVIR to prevent HIV infection (PrEP) and you become pregnant while taking APO-EMTRICITABINE-TENOFOVIR, talk to your healthcare provider about whether you should continue taking APO-EMTRICITABINE-TENOFOVIR.
Pregnancy Registry.There is a pregnancy registry for women who take antiviral medicines during pregnancy. The purpose of this
| IMPORTANT: PLEASE READ |
registry is to collect information about the health of you and your baby. Talk to your healthcare provider about how you can take part in this Antiretroviral Pregnancy Registry.
If you are breastfeeding or planning to breastfeed: Do not breast-feed if you are taking APO-EMTRICITABINE-TENOFOVIR or have HIV. Emtricitabine and tenofovir disoproxil fumarate, the two components of APO-EMTRICITABINE-TENOFOVIR, pass to your baby in your breast milk. You should not breastfeed because of the risk of passing HIV to your baby. Talk to your healthcare professional about the best way to feed your baby.
If you have other medical conditions: Let your healthcare professional know if you have other medical conditions, especially liver, bone and kidney problems.
If you are taking other medicines: Some medicines can interact when taken together, including prescription and non-prescription medicines and dietary supplements (see INTERACTIONS WITH THIS MEDICATION).
If you are taking didanosine: Taking didanosine and APO-EMTRICITABINE-TENOFOVIR may cause serious reactions including lactic acidosis (too much acid in the blood), pancreatitis (inflamed pancreas) and nerve damage (neuropathy) (see INTERACTIONS WITH THIS MEDICATION and SIDE EFFECTS AND WHAT TO DO ABOUT THEM).
APO-EMTRICITABINE-TENOFOVIR should not be used with or soon after cidofovir, acyclovir, valacyclovir, ganciclovir, valganciclovir, aminoglycosides, or nonsteroidal anti-inflammatory drugs (NSAIDS), due to potential harm to the kidneys.
It is a good idea to keep a complete list of all the medicines that you take. Make a new list when medicines are added or stopped. Give copies of this list to all of your healthcare providers every time you visit your healthcare professional or fill a prescription.
Other Special Warnings:
Your blood sugar levels (glucose) or levels of fats (lipids) in your blood may increase with HIV treatment. Your doctor may order blood tests for you.
INTERACTIONS WITH THIS MEDICATION
Let your healthcare professional know if you are taking these or any other medications:
Drugs that contain didanosine (Videx®, Videx EC®).
Tenofovir disoproxil fumarate (a component of APO-EMTRICITABINE-TENOFOVIR) may increase the amount of didanosine in your blood. You may need to be followed more carefully if you are taking APO-EMTRICITABINE-TENOFOVIR and didanosine together. Also, the dose of didanosine may need to be reduced.
Reyataz® (atazanavir sulfate), Kaletra (lopinavir/ritonavir)
Prezista® (darunavir), HARVONI® (ledipasvir/sofosbuvir), EPCLUSA™ (sofosbuvir/velpatasvir), or VOSEVI™ (sofosbuvir/velpatasvir/voxilaprevir). These medicines may increase the amount of tenofovir disoproxil fumarate (a component of APO-EMTRICITABINE-TENOFOVIR) in your blood, which could result in more side effects. You may need to be followed more carefully if you are taking APO-EMTRICITABINE-TENOFOVIR together with Reyataz® (atazanavir sulfate), Kaletra® (lopinavir/ritonavir) , Prezista® (darunavir), HARVONI® (ledipasvir/sofosbuvir), EPCLUSATM (sofosbuvir/velpatasvir), VOSEVI™ (sofosbuvir/velpatasvir/voxilaprevir). APO-
EMTRICITABINE-TENOFOVIR may decrease the amount of atazanavir sulfate in your blood. If you are taking APO-EMTRICITABINE-TENOFOVIR and Reyataz (atazanavir sulfate) together, you should also be taking Norvir® (ritonavir).
- Non-steroidal anti-inflammatory drugs.
PROPER USE OF THIS MEDICATION
Stay under a healthcare professional’s care when taking APO-EMTRICITABINE-TENOFOVIR. Do not change your treatment or stop treatment without first talking with your healthcare professional.
Take APO-EMTRICITABINE-TENOFOVIR exactly as your healthcare professional prescribed it. Follow the directions from your healthcare professional, exactly as written on the label. Set up a dosing schedule and follow it carefully.
When used to treat HIV-1 infection, APO-EMTRICITABINE-TENOFOVIR is always used with other HIV-1 medicines.
If you take APO-EMTRICITABINE-TENOFOVIR to reduce your risk of getting HIV-1:
- you must also use other methods to reduce your risk of getting HIV.
- take APO-EMTRICITABINE-TENOFOVIR every day, not just when you think you have been exposed to HIV-1.
Avoid doing things that can increase your risk of getting HIV infection or spreading HIV infection to other people:
- Do not re-use or share needles or other injection equipment.
- Do not share personal items that can have blood or body fluids on them, like toothbrushes and razor blades.
- Do not have any kind of sex without protection. Always practice safer sex by using a latex or polyurethane condom to lower the chance of sexual contact with semen, vagina secretions, or blood.
Ask your healthcare provider if you have any questions on how
| IMPORTANT: PLEASE READ |
to prevent getting HIV infection or spreading HIV infection to other people.
When your APO-EMTRICITABINE-TENOFOVIR supply starts to run low, get more from your healthcare professional. This is very important because the amount of virus in your blood may increase if the medicine is stopped for even a short time. The virus may develop resistance to APO-EMTRICITABINE-TENOFOVIR and become harder to treat.
Only take medicine that has been prescribed specifically for you. Do not give APO-EMTRICITABINE-TENOFOVIR to others or take medicine prescribed for someone else.
Do not use if seal over bottle opening is broken or missing.
Usual Adult Dose:
For the treatment of HIV-1 infection:
The usual dose of APO-EMTRICITABINE-TENOFOVIR is
one tablet orally (by mouth) once a day, in combination with other anti-HIV medicines.
APO-EMTRICITABINE-TENOFOVIR may be taken with
or without a meal.
For prevention of HIV-1 infection (PrEP):
The usual dose of APO-EMTRICITABINE-TENOFOVIR is
one tablet orally (by mouth) once a day.
APO-EMTRICITABINE-TENOFOVIR may be taken with or
without a meal.
Overdosage:
In case of drug overdose, contact your healthcare professional, hospital emergency department or Regional Poison Control Centre, even if there are no symptoms.
Missed Dose:
It is important that you do not miss any doses. If you miss a dose of APO-EMTRICITABINE-TENOFOVIR and it is less than 12 hours from the time you usually take APO-EMTRICITABINE-TENOFOVIR, then take the dose. If more than 12 hours has passed from the time you usually take APO-EMTRICITABINE-TENOFOVIR, then wait until the next scheduled daily dose. Do not take more than 1 dose of APO-EMTRICITABINE-TENOFOVIR in a day. Do not take 2 doses at the same time. Call your healthcare professional if you are not sure what to do.
| SIDE EFFECTS AND WHAT TO DO ABOUT THEM |
The most common side effects of emtricitabine and tenofovir disoproxil fumarate are:
- Diarrhea
- Nausea
Vomiting
- Dizziness
- Headache
Other side effects include:
- Stomach pain
- Indigestion
- Inflammation of the pancreas
- Sleeping problems
- Abnormal dreams
- Weakness
- Pain
- Shortness of breath
- Allergic reaction (including swelling of the face, lips, tongue or throat)
- Rash
- Flatulence (intestinal gas)
- Skin discoloration (small spots or freckles) may also happen with APO-EMTRICITABINE-TENOFOVIR
| SERIOUS SIDE EFFECTS, HOW OFTEN THEY HAPPEN AND | ||||||
| WHAT TO DO ABOUT THEM | ||||||
| Symptom / effect | Talk with your healthcare professional | Stop taking drug and call your healthcare professional | ||||
| Only if severe | In all cases | |||||
| Rare | Effect: Kidney problems Symptoms
| |||||
| Rare | ||||||
Effect: Lactic acidosis
Symptoms
- Feeling very weak or tired
- Unusual muscle pain
| IMPORTANT: PLEASE READ |
| SERIOUS SIDE EFFECTS, HOW OFTEN THEY HAPPEN AND | ||||||
| WHAT TO DO ABOUT THEM | ||||||
| Symptom / effect | Talk with your healthcare professional | Stop taking drug and call your healthcare professional | ||||
Only if severe | In all cases | |||||
| ||||||
| Very Rare | Effect: Hepatotoxicity (severe liver problems) with hepatomegaly (liver enlargement) and steatosis (fat in the liver) Symptoms | |||||
| ||||||
| SERIOUS SIDE EFFECTS, HOW OFTEN THEY HAPPEN AND | ||||||
| WHAT TO DO ABOUT THEM | ||||||
| Symptom / effect | Talk with your healthcare professional | Stop taking drug and call your healthcare professional | ||||
Only if severe | In all cases | |||||
| Very Rare | Effect: Flare-ups of hepatitis B virus infection following drug discontinuation Symptoms
| |||||
| ||||||
Lactic acidosis is a medical emergency and must be treated in the hospital. You may be more likely to get lactic acidosis or serious liver problems if you are very overweight (obese) or have been taking nucleoside analog medicines, like APO-
EMTRICITABINE-TENOFOVIR, for a long time.
Muscle pain, muscle weakness, bone pain and softening of the bone (infrequently contributing to fractures) have also been reported.
There have been other side effects in patients taking emtricitabine or tenofovir disoproxil fumarate. This is not a complete list of side effects. If you have questions about side effects, ask your healthcare professional. You should report any new or continuing symptoms to your healthcare professional right away. Your healthcare professional may be able to help you manage these side
| IMPORTANT: PLEASE READ |
effects.
HOW TO STORE IT
- Keep APO-EMTRICITABINE-TENOFOVIR and all other medications out of reach and sight of children.
- APO-EMTRICITABINE-TENOFOVIR should be stored at controlled room temperature 15°C to 30°C, protect from moisture. It should remain stable until the expiration date printed on the label.
- Do not keep your medicine in places that are too hot or cold.
- Do not keep medicine that is out of date or that you no longer need. If you throw any medicines away, make sure that children will not find them.
- Keep APO-EMTRICITABINE-TENOFOVIR in its original container and keep the container tightly closed.
Reporting Side Effects
You can report any suspected side effects associated with the use of health products to Health Canada by:
Visiting the Web page on Adverse Reaction Reporting
(https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/adverse-reaction-reporting.html) for information on how to report online, by mail or by fax; or
- Calling toll-free at 1-866-234-2345
NOTE: Contact your health professional if you need information about how to manage your side effects. The Canada Vigilance Program does not provide medical advice.
| MORE INFORMATION |
If you want more information about APO-EMTRICITABINE-TENOFOVIR:
- Talk to your healthcare professional
- Find the full product monograph that is prepared for healthcare professionals and includes this patient medication information by visiting the Health Canada website (https://www.canada.ca/en/health-canada/services/drugs-health-products/drug-products/drug-product-database.html); the manufacturer’s website http://www.apotex.ca/products, or by calling 1-800-667-4708.
Last revised: October 25, 2018