


Product Monograph - Bacitracin USP
ACTION AND CLINICAL PHARMACOLOGY
Bacitracin, an antibiotic substance derived from cultures of Bacillus subtilis (Tracey), exerts pronounced antibacterial action in vitro against a variety of gram-positive and a few gram-negative organisms.
However, among systemic diseases, only staphylococcal infections qualify for consideration of bacitracin therapy. Bacitracin is assayed against a standard and its activity is expressed in units, 1 mg, having a potency of not less than 50 units.
Susceptibility plate testing: If the Kirby-Bauer method of disc susceptibility is used, a 10-unit bacitracin disc should give a zone over 13 mm when tested against a bacitracin-susceptible strain of Staphylococcus aureus. Absorption of bacitracin following intramuscular injection is rapid and complete. A dose of 200 or 300 units/kg every six hours gives serum levels of 0.2 to 2 mcg/mL in individuals with normal renal function. The drug is excreted slowly by glomerular filtration. It is widely distributed in all body organs and is demonstrable in ascitic and pleural fluids after intramuscular injection.
INDICATIONS AND CLINICAL USE
The use of intramuscular bacitracin is indicated in the treatment of infants with pneumonia and empyema caused by staphylococci shown to be susceptible to the drug.
Bacitracin solutions, applied locally in the form of compresses or instillations, may be used once or twice daily in secondarily infected wounds, ulcers, pyodermas and other superficial skin infections and in superficial infections of the eye caused by bacitracin-susceptible organisms. Bacitracin solutions may be instilled into the nasal cavities or administered by inhalation as an aerosol in the treatment of bacitracin-susceptible infections of the upper and lower respiratory tract. In severe or extensive infections, appropriate antibacterial therapy should be given in addition to local treatment with bacitracin.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Bacitracin USP and other antibacterial drugs, Bacitracin USP should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
Bacitracin is contraindicated in patients who are hypersensitive to this drug or any ingredient in the formulation or component of the container.
Bacitracin is contraindicated in patients with impaired renal function, including those taking nephrotoxic drugs.
SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
There have been reports of nephrotoxicity, including renal failure in patients exposed to BACITRACIN (see WARNINGS, Renal).
Serious hypersensitivity and/or anaphylactic reactions have been reported in patients exposed to BACITRACIN (see WARNINGS: Hypersensitivity).
WARNINGS
General
Nephrotoxicity, hypersensitivity, and/or anaphylactic reactions have been reported in patients treated with Bacitracin administered intramuscularly and through local exposure (see INDICATIONS AND CLINICAL USE).
Bacitracin is not indicated as an irrigation solution for intraoperative prophylaxis nor for pre-soaking of medical devices or implants prior to surgery. Anaphylactic reactions and nephrotoxicity can occur when Bacitracin is used in this manner.
Hypersensitivity
There have been reports of serious hypersensitivity, including anaphylaxis and/or allergic contact dermatitis, in patients exposed to Bacitracin following intramuscular and local administration. These reactions may occur following the first dose.
Monitoring and Laboratory Tests
Close monitoring of renal function is recommended in patients treated with Bacitracin. Glomerular and tubular kidney function must be evaluated and checked before commencement of therapy, as well as during and after treatment.
Renal
Nephrotoxicity
There have been reports of nephrotoxicity in patients exposed to Bacitracin via intramuscular and non-intramuscular routes. Bacitracin may cause renal failure due to tubular and glomerular necrosis due to high systemic absorption. Intramuscular use should be restricted to infants with Staphylococcal pneumonia and empyema due to organisms shown to be susceptible to Bacitracin.
Renal function should be carefully determined prior to, and daily during therapy. Bacitracin should be used only where adequate laboratory facilities are available and when constant supervision of the patient is possible. The recommended daily dose should not be exceeded and fluid intake and urinary output maintained at proper levels to avoid kidney toxicity. If renal toxicity occurs, the drug should be discontinued. Concurrent use of other nephrotoxic drugs should be avoided.
Susceptibility/Resistance
Development of Drug Resistant Bacteria
Prescribing Bacitracin USP in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
PRECAUTIONS
See Warnings for precautions in regard to kidney toxicity associated with intramuscular use of bacitracin.
Adequate fluid intake should be maintained orally, or if necessary, by parenteral method.
As with other antibiotics, use of this drug may result in overgrowth of non-susceptible organisms, including fungi. If superinfection occurs, appropriate therapy should be instituted.
ADVERSE REACTIONS
Nephrotoxic reactions: Albuminuria, Cylindruria Azotemia. Rising blood levels without any increase in dosage.
Other reactions: Nausea and vomiting. Pain at site of injection. Skin rashes.
DOSAGE AND ADMINISTRATION
TO BE ADMINISTERED INTRAMUSCULARLY.
Infant dose:
For infants under 2500 grams - 900 units/kg/24 hours in 2 or 3 divided doses. For infants over 2500 grams - 1,000 units/kg/24 hours, in 2 or 3 divided doses. Intramuscular injections of the solution should be given in the upper outer quadrant of the buttocks, alternating right and left and avoiding multiple injections in the same region because of the transient pain following injection.
Preparation of Solutions:
Should be dissolved in Sodium Chloride Injection containing 2 percent procaine hydrochloride. The concentration of the antibiotic in the solution should not be less than 5,000 units per mL nor more than 10,000 units per mL.
Diluents containing parabens should not be used to reconstitute bacitracin; cloudy solutions and precipitate formation have occurred. Reconstitution of the 50,000 unit vial with 9.8 mL of diluent will result in a concentration of 5,000 units per mL.
TO BE ADMINISTERED TOPICALLY.
Preparation of Solution:
| Skin | 500 units per mL |
| Ophthalmic Solutions | 500 to 1,000 units per mL |
| Intranasal Therapy | 250 units per mL |
| Aerosol | 500 to 1,000 units per mL |
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Bacitracin USP
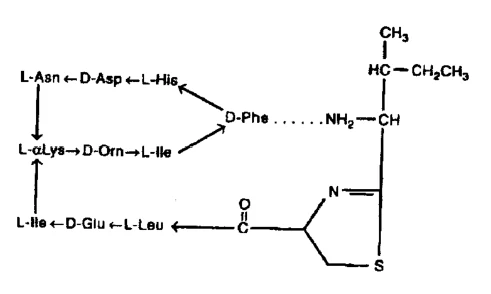
Chemical structure: C66H103N17O16S
Structural Formula:
DESCRIPTION:
Bacitracin is a white to pale buff, hygroscopic powder, odorless or having a slight odor. It is freely soluble in water; insoluble in acetone, chloroform, and ether. While soluble in alcohol, methanol, and glacial acetic acid, there is some insoluble residue. It is precipitated from its solutions and inactivated by many of the heavy metals.
STABILITY AND STORAGE RECOMMENDATIONS:
Store unreconstituted Bacitracin in a refrigerator 2ºC to 8°C. Solutions are rapidly inactivated at room temperature but are stable for one week when stored in a refrigerator 2°C to 8°C.
Availability of Dosage Forms:
Bacitracin USP is available in a vial containing 50,000 unit, packaged in cartons of 5’s.