


Product Monograph - Fosfomycin Powder for Oral Solution
INDICATIONS AND CLINICAL USE
Fosfomycin powder for oral solution (fosfomycin tromethamine) is indicated in the treatment of acute uncomplicated lower urinary tract infections (acute cystitis) in women of 18 years of age and older caused by the following susceptible pathogens: Escherichia coli, Enterococcus faecalis.
Fosfomycin powder for oral solution is not indicated for the treatment of pyelonephritis or perinephric abscess.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Fosfomycin powder for oral solution and other antibacterial drugs, Fosfomycin powder for oral solution should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
Fosfomycin powder for oral solution (fosfomycin tromethamine) is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container.
PRECAUTIONS
General:
A single dose only of Fosfomycin powder for oral solution (fosfomycin tromethamine) should be used to treat an episode of acute cystitis. Repeated daily doses of Fosfomycin powder for oral solution did not improve the clinical success or microbiological eradication rates compared to single dose therapy, but did increase the incidence of adverse events.
Hypersensitivity reactions, including anaphylaxis and anaphylactic shock, which can be life-threatening, have been reported during Fosfomycin powder for oral solution treatment. If such reaction occurs, adequate medical treatment is required and Fosfomycin powder for oral solution should never be re-administrated (see CONTRAINDICATIONS and ADVERSE REACTIONS).
Fosfomycin powder for oral solution contains sucrose. Its use is not recommended in patients with hereditary problems of fructose intolerance, glucose-galactose malabsorption or sucrase-isomaltase insufficiency.
Before the administration of Fosfomycin powder for oral solution to patients with severe renal impairment (creatinine clearance < 30 mL/min) or patients undergoing hemodialysis, the physician should evaluate if the potential benefits of the drug outweigh the potential risks to the patient, as Fosfomycin powder for oral solution is principally excreted by the kidney (see ACTION AND CLINICAL PHARMACOLOGY and PHARMACOLOGY).
Clostridium difficile-associated disease
Clostridium difficile‐associated disease (CDAD) has been reported with the use of many antibacterial agents, including fosfomycin tromethamine. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and many permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against C. difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against C. difficile. Drugs that inhibit peristalsis may delay clearance of C. difficile and its toxins, and therefore should not be used in the treatment of CDAD. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Susceptibility/Resistance
Development of Drug Resistant Bacteria
Prescribing Fosfomycin powder for oral solution in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Pediatric Use:
Safety and effectiveness have not been established in children under 18 years of age.
Use in Pregnancy and Nursing Mothers:
Fosfomycin crosses the placental barrier and its safety in the treatment of infections during pregnancy has not been established. Fosfomycin powder for oral solution should not be used during pregnancy unless clearly needed and after taking into account the benefits to the mother and potential risks to the fetus.
As Fosfomycin powder for oral solution may be excreted in human milk, a decision should be made whether to discontinue nursing or to not administer Fosfomycin powder for oral solution, taking into account the benefits to the mother and potential risks to the neonate.
Drug Interactions:
Metoclopramide: When co‐administered with Fosfomycin powder for oral solution, metoclopramide, a drug which increases gastrointestinal motility, lowers the serum concentration and urinary excretion of fosfomycin. Other drugs that increase gastrointestinal motility may produce similar effects.
Probenecid should not be co‐prescribed with Fosfomycin powder for oral solution, as it has been shown to significantly decrease renal clearance and excretion of fosfomycin.
Probenecid when administered to healthy volunteers given an infusion of disodium fosfomycin significantly decreased renal clearance, probably by inhibiting tubular secretion, leading to lower urinary concentrations.
No therapeutic assessments of the effect of either metoclopramide or probenecid on urinary levels of fosfomycin have been carried out following their administration with fosfomycin tromethamine to women with acute urinary tract infection. Based on the information from healthy volunteers, urinary levels of fosfomycin may not exceed bactericidal levels for long enough to result in microbiological cure. Neither of these drugs should be co‐prescribed with Fosfomycin powder for oral solution.
Cimetidine: Cimetidine does not affect the pharmacokinetics or the urinary concentrations of fosfomycin when co‐administered with Fosfomycin powder for oral solution.
Effect of food: Food delays the absorption of Fosfomycin powder for oral solution, resulting in a decrease in peak plasma levels and urinary concentrations. It is therefore recommended to take the medicine on an empty stomach or at least 2-3 hours after a meal (see ACTION AND CLINICAL PHARMACOLOGY and PHARMACOLOGY).
Effects on Ability to Drive and Use Machines
Although no studies have been conducted on the effects on the ability to drive and use machines, dizziness has been reported from patients taking fosfomycin tromethamine. This may influence some patients’ ability to drive and operate machinery (see ADVERSE REACTIONS).
ADVERSE REACTIONS
In three US trials, 1233 patients were treated with (fosfomycin tromethamine). The most frequently reported adverse events occurring in >1% of the study population regardless of drug relationship were: diarrhea (10.4%), headache (10.3%), vaginitis (7.6%), nausea (5.2%), rhinitis (4.5%), back pain (3.0%), dysmenorrhea (2.6%), pharyngitis (2.5%), dizziness (2.3%), abdominal pain (2.2%), pain (2.2%), dyspepsia (1.8%), asthenia (1.7%) and rash (1.4%).
In addition, adverse events occurring in clinical trials at a rate of less than 1%, regardless of drug relationship were: abnormal stools, anorexia, constipation, dry mouth, dysuria, ear disorder, fever, flatulence, flu syndrome, hematuria, infection, insomnia, lymphadenopathy, menstrual disorder, migraine, myalgia, nervousness, paraesthesia, pruritus, skin disorder and vomiting.
In the US study population, statistically significant laboratory changes reported without regard to causal relationship included: increased eosinophil count, increased or decreased WBC count, increased bilirubin, increased SGPT, increased SGOT, increased alkaline phosphatase, decreased hematocrit, decreased hemoglobin, increased and decreased platelet count. The changes were generally transient, not clinically significant and occurred in less than 1% patients.
In the same study population, adverse events which were considered to be drug related by the investigators and reported in greater than 1% of the fosfomycin‐treated patients were diarrhea (9.0%), vaginitis (5.5%), nausea (4.1 %), headache (3.9%), dizziness (1.3%), asthenia (1.1 %) and dyspepsia (1.1 %). The most frequently observed symptom, diarrhea, was considered mild and self-limiting.
A single case of unilateral optic neuritis was reported and considered possibly related to fosfomycin tromethamine therapy.
Post-marketing experience with fosfomycin tromethamine has resulted in reports of vulvovaginitis, tachycardia, impaired hearing, urticaria and anaphylactic reactions including anaphylactic shock and hypersensitivity. Cases of angioedema, aplastic anemia, asthma (exacerbation), cholestatic jaundice, general decline in taste perception, hepatic necrosis, metallic taste and vestibular loss have also been reported. A single case of toxic megacolon was reported and found to be not related to fosfomycin tromethamine.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
For management of suspected drug overdose, contact your Regional Poison Control Centre.
Experience regarding the overdose of oral fosfomycin is limited.
Hypotonia, somnolence, electrolytes disturbances, thrombocytopenia and hypoprothrombinemia have been reported in cases of overdose with parenteral use of fosfomycin.
In the event of overdosage, treatment should be symptomatic and supportive. Urinary elimination of fosfomycin should be encouraged by adequate administration of oral fluids.
DOSAGE AND ADMINISTRATION
The recommended dosage for women over 18 years with acute uncomplicated urinary tract infections (acute cystitis) is one sachet containing the equivalent of 3 grams of fosfomycin. The contents of the single dose sachet should be added to about 125 mL (½ cup) of cold water, stirred to dissolve and immediately taken orally. It is recommended that Fosfomycin powder for oral solution (fosfomycin tromethamine) be taken on an empty stomach or at least 2-3 hours after a meal. As for other medications, Fosfomycin powder for oral solution should not be co‐ administered, if possible, with other drugs.
PHARMACEUTICAL INFORMATION
Drug Substance:
Fosfomycin tromethamine is the mono-acid salt of fosfomycin with tromethamine.
- 1. NAMES
Established Name: Fosfomycin trometamol (international non-proprietary name [INN])
USAN: Fosfomycin tromethamine
Chemical Name: 1. Mono(2-ammonium-2-hydroxymethyl-1 ,3-propanediol )(2R- cis)-3(methyloxiranyl) phosphonate
Therapeutic Class: Antibiotic
Pharmacological
Class: Antibacterial
- 2. PHYSICAL AND CHEMICAL CHARACTERISTICS
Appearance: White to near white crystalline powder.
Solubility: Very soluble in water. Slightly soluble in 95% methanol and ethanol. Insoluble in acetone, ether and chlorinated solvents
Melting point: 116-122°C
Structural formula:
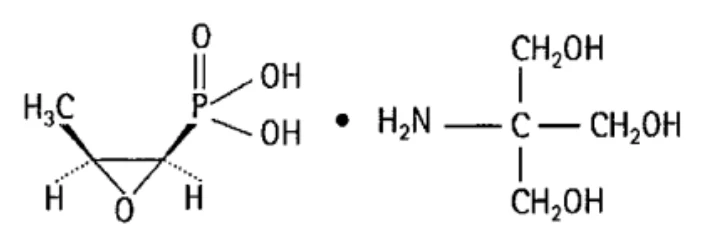
Molecular weight: 259.2 [Acid: 138.0]
Molecular formula: C7H18NO7P
pH: 4.0 to 5.0 (5% w/v aqueous solution)
Composition: Each sachet of Fosfomycin powder for oral solution contains: 5.631 g of fosfomycin tromethamine (equivalent to 3 g of fosfomycin) plus mandarin and orange flavouring, saccharin and sucrose.
Storage Conditions: Store at controlled room temperature 15° to 30°C.
AVAILABILITY OF DOSAGE FORMS
Fosfomycin powder for oral solution (fosfomycin tromethamine) is available as a single-dose sachet containing the equivalent of 3 grams of fosfomycin.
MICROBIOLOGY
Fosfomycin is bactericidal by inhibiting the cytoplasmic enzyme, enolpyruvyl transferase, which serves as a catalyst to create the basic monomer (uridine diphosphate‐N‐acetylmuramic acid) needed for the first step of the bacterial cell wall (peptidoglycan) synthesis.
Fosfomycin (the active component of fosfomycin tromethamine) has in vitro activity against a range of gram‐positive and gram‐negative aerobic microorganisms, some of which are associated with uncomplicated urinary tract infections. The antibacterial activity of fosfomycin, using agar dilution test, is shown in Table 1.
TABLE 1: ANTIBACTERIAL ACTIVITY OF FOSFOMYCIN IN VITRO (AGAR DILUTION TEST)
Microorganism (No. Tested) | Minimal Inhibitory Concentration (mcg/mL) Agar Dilution | ||
| 50% | 90% | Range | |
| Escherichia coli (51) | 1.0 | 4.0 | ≤0.5 – 32 |
| Citobacter species (30) | 2.0 | 4.0 | 2.0 – 8.0 |
| Klebsiella species (30) | 16 | 32 |
|
| Enterobacter species (45) | 16 | 32 |
|
| Serratia marcescens (20) | 8.0 | 16 | 4.0 – 32 |
| Morganella morganii (10) | 128 | >256 | 32 – >256 |
| Providencia species (25) | 16 | 128 |
|
| Pseudomonas species (35) | 128 | 256 | ≤ 0.5 – 512 |
| Acinetobacter calcoaceticus subsp. anitratus (10) | 128 | 128 | 64 – 128 |
| Enterococcus species (41) | 32 | 64 | 16 – >256 |
| Staphylococcus saprophyticus (30) | 128 | 512 | 64 – >256 |
(Reference: Barry and Fuchs, 1991)
The in vitro activity of fosfomycin against urinary tract pathogens, isolated from 1233 patients in US clinical studies is presented in the following Table 2, which shows MIC (mcg/mL) distribution among the six most common uropathogens:
TABLE 2: DISTRIBUTION OF FOSFOMYCIN MICs AGAINST UROPATHOGENS IN US CLINICAL TRIALS
| Number of Isolates with MIC 90(mcg/mL) of | ||||||||||||
| Microorganism | ≤2 | 4 | 8 | 16 | 32 | 64 | 128 | ≥256 | ||||
| Escherichia coli | 566 | 10 | 5 | 3 | 1 | 2 | 0 | 0 | ||||
| Enterobacter aerogenes | 0 | 0 | 3 | 3 | 0 | 0 | 0 | 0 | ||||
| Klebsiella pneumoniae | 1 | 5 | 11 | 6 | 2 | 1 | 3 | 0 | ||||
| Proteus mirabillis | 20 | 4 | 1 | 1 | 0 | 0 | 1 | 1 | ||||
| Enterococcus faecalis | 0 | 0 | 0 | 1 | 5 | 4 | 0 | 0 | ||||
| Staphylococcus saprophyticus | 2 | 0 | 0 | 0 | 1 | 9 | 1 | 8 | ||||
| All | 589 | 19 | 20 | 14 | 9 | 16 | 5 | 9 | ||||
Resistance to fosfomycin can develop either through chromosomal or plasmid mediated mechanisms. Chromosomally mediated mutations result in reduced uptake of fosfomycin by the L‐α‐glycerophosphate (primary) or the hexose phosphate (alternative) transport system. Catalytic conjugation between glutathione and fosfomycin which gives an inactive entity is the mechanism for plasmid mediated resistance. Surveys of developing resistance patterns in Europe have not revealed either any major development of chromosomal mutants or plasmid mediated resistance with fosfomycin. Also, there appears to be little cross‐resistance between fosfomycin and other antibacterial agents, likely due to the fact that its chemical structure and mode of action differ from those of other agents.
In healthy volunteers, a single dose of fosfomycin tromethamine (equivalent to 3 g fosfomycin) decreased the coliform count in six of eight volunteers, the count returning to normal by Day 7 in seven of eight of the volunteers. While there was an increase in fosfomycin‐resistant coliforms isolated on Days 2 to 3 in three volunteers, these had disappeared by Day 7 to 14. The total number of fecal anaerobes was often slightly increased, largely due to an elevation of Bacteroides species. There was no rise in the proportion of fosfomycin resistant anaerobes.
Neither C. difficile nor its toxin were detected in any sample nor was there colonization with pseudomonas or yeasts.
IN VITRO SUSCEPTIBILITY TESTING
SUSCEPTIBILITY TESTS
Dilution Techniques:
Quantitative methods are used to determine minimum inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure uses a standardized agar dilution method (NCCLS M7-A4) or equivalent with standardized inoculum concentrations and standardized concentrations of fosfomycin tromethamine (in terms of fosfomycin base content) powder supplemented with 25 mcg/mL of glucose-6-phosphate. BROTH DILUTION METHOD SHOULD NOT BE USED TO TEST SUSCEPTIBILITY OF FOSFOMYCIN. The MIC values obtained should be interpreted according to the following criteria:
MIC (mcg/mL) Interpretation
≤64 Susceptible (S)
128 Intermediate (I)
≥256 Resistant (R)
A report of "Susceptible" indicates that the pathogen is likely to be inhibited by generally achievable concentrations of the antimicrobial compound in urine. A report of "Intermediate" indicates that the results should be considered equivocal and if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category provides a "buffer zone" that prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of "Resistant" indicates that usually achievable concentrations of the antimicrobial compound in the urine are unlikely to be inhibitory and that other therapy should be selected.
Standardized susceptibility test procedures require the use of laboratory control microorganisms. Standard fosfomycin tromethamine should provide the following MIC values for agar dilution testing in media containing 25 mcg/mL of glucose-6-phosphate. (Broth dilution testing should not be performed):
Microorganism MIC (mcg/mL)
Enterococcus faecalis 32 - 128
ATCC 29212
Escherichia coli 0.5 - 2
ATCC 25922
Pseudomonas aeruginosa 2 - 8
ATCC 27853
Staphylococcus aureus 0.5 - 4
ATCC 29213
Diffusion Techniques:
Qualitative methods that require measurement of zone diameters also provide reproducible estimate of the susceptibility of bacteria to antimicrobial agents. One such standardized procedure (NCCLS M2-A5) requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 200 mcg fosfomycin and 50 mcg of glucose-6-phosphate to test the susceptibility of microorganism to fosfomycin.
Laboratory results utilizing the standard single-disk susceptibility test should be interpreted according to the following criteria:
Zone Diameter (mm) Interpretation
≥16 Susceptible (S)
13 - 15 Intermediate (I)
≤12 Resistant (R)
Interpretation should be stated as above for results using dilution techniques. Interpretation involves correlation of the diameter obtained in the disk test with the MIC for fosfomycin.
As with standard dilution techniques, diffusion methods require the use of laboratory control microorganisms that are used to control the technical aspects of the laboratory procedures. For the diffusion technique, the 200 mcg fosfomycin disk with 50 mcg/mL of glucose-6-phosphate should provide the following zone diameters in these laboratory quality control strains:
Microorganism Zone Diameter (mm)
Escherichia coli 22 - 30
ATCC 25922
Staphylococcus aureus 25 - 33
ATCC 25923
PHARMACOLOGY
Animal:
Five studies in two species of rodent and dog demonstrated that fosfomycin tromethamine is well absorbed, distributed to highly perfused organs and predominantly excreted as unchanged drug in the urine. The results are shown in Table 3.
TABLE 3: PLASMA AND URINE CONCENTRATIONS OF FOSFOMYCIN IN ANIMALS
| Species | Route | Dose mg/kg | Plasma | Urine recovery% | |||||||||||||||
Cmax (mcg/mL) | Tmax (mins.) | 6-8 hrs. | 24 hrs. | 48 hrs. | |||||||||||||||
| Mouse | Oral | 30 | 8.65 | 15 | 27.8 | 55.8 | - | ||||||||||||
| Rat | Oral | 50 | 16.6 | 60 | 36.5 | 49.2 | - | ||||||||||||
| Rat | Oral | 50 | 14.3 | - | - | - | 88.5 | ||||||||||||
| Dog | Oral | 50 | 39.6 | 120 | 52.2 | 62.0 | - | ||||||||||||
| Dog | Oral | 500 | 91.3 | 120 | 22.9 | 41.6 | - | ||||||||||||
In rats administered 50 mg/kg fosfomycin tromethamine (mean oral dose 11.3±0.6 mg) mean recovery (% of total dose) over 48 hours was 8.7±6.9% in feces, 88.5±3.9% in urine and 97.3±5.1% in urine and feces combined. Peak plasma concentrations of 14.3±3.5 mcg/mL occurred 1 hour after drug intake. Peak concentrations in all organs examined, also occurred at 1 hour and levels in the kidney exceeded those in plasma by approximately 5 fold (mean 74.9±23.3 mcg/g).
Human:
Healthy Volunteers
Pharmacokinetic parameters following administration of a single dose of fosfomycin tromethamine (equivalent to 3 g of fosfomycin) to young healthy volunteers, with and without a high fat meal, were compared to those following a 3 g iv dose of fosfomycin (disodium fosfomycin) in the same subjects. The results covering an 84 hour period are shown in Table 4. Corresponding urine concentrations measured at time intervals up to 84 hours are shown in Table 5.
TABLE 4: SUMMARY OF PHARMACOKINETIC DATA (±SD)
| Route and Dose | # of Subject s | Cmax (mcg/mL ) | Tmax (hr.) | AUC (mcg-hr/mL) | t½ (hr.) | Urinary Excretion (% dose) | Feces Excretion (% dose) |
Oral fosfomycin tromethamine (equivalent to 3 g fosfomycin) without food | 24 12F, 12M | 26.1 (±9.1) | 2.1 (±0.42) | 184.0 (±33.6) | 5.7 (±2.8) | 38.0 (±7.9) | 18.0 (±1 0.6) |
Oral fosfomycin tromethamine (equivalent to 3 g fosfomycin) with food | 24 12F, 12M | 17.6 (±4.4) | 4.0 (±0.55) | 154.0 (±34.2) | 5.8 (±1.9) | 37.3 (±6.7) | 19.0 ±13.0) |
intravenous disodium fosfomycin (equivalent to 3 g fosfomycin) Without food | 24 12F, 12M | - | - | 504.0 (±87.6) | 2.7 (±0.6) | 89.6 (±13.5) | - |
TABLE 5: MEAN (±SD) FOSFOMYCIN URINE CONCENTRATIONS (mcg/mL) FOLLOWING A SINGLE 3G DOSE
| Time Interval (hours) | Oral (fasted) | Oral (fed) | Intravenous (fasted) |
| 0.0 - 2.0 | 649.2 (±442.1) | 209.6 (±127.2) | 6353.2 (±3653.4) |
| 2.0 - 4.0 | 706.5 (±466.4) | 428.1 (±153.5) | 1810.5 (±1608.5) |
| 4.0 - 6.0 | 594.2 (±267.5) | 531.5 (±187.2) | 829.9 (±362.4) |
| 6.0 - 8.0 | 549.9 (±302.4) | 537.7 (±251.8) | 954.7 (±603.8) |
| 8.0 - 10.0 | 478.5 (±176.2) | 404.4 (±221.3) | 498.0 (±221.1) |
| 10.0 - 12.0 | 492.9 (±212.2) | 351.8 (±179.4) | 403.5 (±269.1) |
| 12.0 - 16.0 | 265.0 (±143.3) | 250.0 (±123.9) | 195.2 (±141.9) |
| 16.0 - 24.0 | 168.1 (±108.9) | 163.5 (±99.3) | 82.3 (±64.2) |
| 24.0 - 36.0 | 62.2 (±29.8) | 62.8 (±30.2) | 14.4 (±16.1) |
| 36.0 - 48.0 | 54.2 (±45.5) | 54.1 (±30. 7) | 3.3 (±2.8) |
| 48.0 - 60.0 | 30.6 (±21.2) | 29.3 (±23.3) | - |
| 60.0 - 72.0 | 21.6 (±17.7) | 17.4 (±17.2) | - |
| 72.0 - 84.0 | 10.8 (±11.4) | 10.6 (±10.7) | - |
Other Pharmacokinetics Considerations:
Food: While food produces some decrease in the rate and extent of absorption of fosfomycin following oral administration of (fosfomycin tromethamine), urine concentrations remain above the MICs for most uropathogens for a similar time, whether administered with food or fasting.
Administration with calcium-containing products: In comparative studies of the bioavailability of fosfomycin tromethamine and fosfomycin calcium, the rate and extent of absorption of fosfomycin from fosfomycin tromethamine were approximately 6 times greater than from fosfomycin calcium during the first two hours post dose and approximately 3-4 times greater during the 12 hour post dose period. In vitro studies indicate that addition of a solution of antacid tablet (containing 750 mg calcium) to a solution of fosfomycin tromethamine in simulated gastric fluid does not result in complexation of calcium with fosfomycin. There is, therefore, no need to avoid fosfomycin tromethamine intake with antacids or calcium.
Elderly population: In seven (7) elderly women of average age 77 yrs and mean serum creatinine of 121 µmol/L and mean estimated creatine clearance of 40 mL/min., mean urinary concentrations over 84 hours following a single oral dose of fosfomycin tromethamine (equivalent to 3 g fosfomycin) are shown in Table 6.
TABLE 6: URINARY CONCENTRATIONS OF FOSFOMYCIN IN ELDERLY WOMEN
| Sample | Mean Urinary Concentration mcg/mL; (±SD) |
| 0 - 12 hr | 1,383 (±1,354) |
| 12 - 24 hr | 508 (±487) |
| 24 - 36 hr | 510 (±794) |
| 36 - 48 hr | 165 (±116) |
| 48 - 60 hr | 222 (±386) |
| 60 - 72 hr | 78 (±63) |
| 72 - 84 hr | 143 (±239) |
(Reference: Janknegt et al., 1994)
The total percentage of the administered dose recovered at 84 hours in the urine was 37 ± 15%, which was comparable to that reported in young healthy volunteers. In the U.S. trials, there was no difference in drug efficacy or tolerance for patients older than 65 years compared with patients younger than 65 years. There is, therefore, no need to adjust the dose in the elderly with age-dependent renal impairment.
Renal Impairment: In another trial, the pharmacokinetic parameters and urinary excretion were compared in healthy subjects and patients with varying degrees of renal impairment. The results are shown in Table 7.
TABLE 7: FOSFOMYCIN PHARMACOKINETIC PARAMETERS (±SD) IN HEALTHY SUBJECTS AND IN PATIENTS WITH VARYING DEGREES OF RENAL IMPAIRMENT
| Parameters | Healthy Subjects (n=5) | Group I (n=7) CrCl > 30 mL/min | Group II (n=6) 10 < CrCl < 30 mL/min | Group Ill (n=5) CrCl < 10 mL/min | Group IV (n=5) anuric |
Creatinine clearance (mL/min) | 127.0 (±19.9) | 54.2 (±24.2) | 16.4 (±5.4) | 7.3 (±1.9) | 0 |
Dose (25mg/kg; total mg) | 2032 (±444) | 1792 (±410) | 1667 (±368) | 1811 (±58) | 1836 (±240) |
Cmax (mcg/mL) | 18.5 (±10.3) | 26.0 (±10.0) | 35.7 (±10.4) | 27.4 (±8.4) | 37.9 (±7.9) |
Tmax (hr) | 1.6 (±0.2) | 2.4 (±1.4) | 4.6 (±1.2) | 5.1 (±1.3) | 7.9 (±3.8) |
AUC (mcg-hr/mL) | 102.8 (±42.1) | 388.5 (±184.7) | 1266.8 (±457.4) | 2108.6 (±824.0) | 2367.0 (±855.8) |
| t½ serum (hr) | 5.4 (±2.6) | 10.8 (±4.5) | 24.5 (±11.7) | 50.3 (±12.9) | 39.6 (±19.7) |
| Urinary elimination 24 hr (% of dose) | 57.7 (±30.2) | 31.6 (±10.5) | 24.0 (±17.3) | 11.0 (±4.6) | - |
| Age (yr) | 29.0 (±2.7) | 43.7 (±22.9) | 56.8 (±11.9) | 55.8 (±5.0) | 56.4 (±6.0) |
CrCl: Creatinine clearance (Reference: Fillastre et al., 1988)
Although renal excretion of fosfomycin decreased in association with the impairment in renal function, the urinary concentration of fosfomycin remained greater than 100mcg/mL at 48 hours post-dose even in the group with the lowest creatinine clearance. In contrast, in normal subjects, the urinary concentration at 36 - 48 hours was 54 mcg/mL. While renal impairment significantly prolongs the elimination of fosfomycin, and since fosfomycin tromethamine is intended to be administered as a single dose therapy only, continued drug accumulation is not expected. Renal impairment significantly decreases the excretion of fosfomycin (see PRECAUTIONS).
No clinical trials in renally impaired patients or in patients undergoing hemodialysis were conducted to clearly determine the efficacy and safety of fosfomycin tromethamine.
TOXICOLOGY
Acute Toxicity
The acute toxicity of fosfomycin tromethamine was established in mice, rats, rabbits and dogs at doses 100 fold higher than human doses. The LD50 values are shown in Table 8.
TABLE 8: LD50 VALUES
| Animal | Route | LD50 (mg/kg) Male | LD50 (mg/kg) Female |
| Mouse | po ip | >5000 4441 | >5000 4344 |
| Rat | po ip | >5000 4539 | >5000 4342 |
| Rabbit | po | >2000 | >2000 |
| Dog | po | >2000 | >2000 |
No deaths occurred in the acute oral studies listed above. The only unusual findings noted were anorexia and diarrhea in the dog. In the intraperitoneal studies, the observations noted one hour after dosing were piloerection, blepharoptosis and diarrhea. These symptoms are mainly attributable to the peritoneal inflammation due to the hypertonicity of the injected solution. No changes were noted in behaviour, body weight or food consumption during the 14 day observation period, in any species.
By the intraperitoneal route, deaths occurred at doses above 4000 mg/kg, in rodents. These were mainly on the first day of treatment and no animal died after day 4.
Sub-acute Toxicity
4- Week Rat Study:
Fosfomycin tromethamine was administered once daily by oral gavage to 3 groups of Sprague Dawley rats (15 male, 15 female per group) at doses of 200, 800 and 3200 mg/kg/day for 4 weeks. An additional group acted as control.
Physical examinations, body weights, food consumption, ophthalmoscopic examinations, hematology values, urinalysis values, and gross or histopathological observations did not reveal any drug-related effects.
A dose-related increase in cholesterol was noted in the treated animals; differences from control values were most significant in the high-dose group. Statistically significant increases in serum glutamic pyruvic transaminase and slight increases in serum glutamic oxaloacetic transaminase values were also noted in the 3200 mg/kg/day group.
These changes were suggestive of an effect on liver function. Statistically significant increases in absolute and relative liver weights were noted in the high-dose animals; absolute kidney weights were also slightly increased in the high-dose males.
Based on the increased cholesterol in the 800 and 3200 mg/kg/day groups and on the increased liver weights in the high-dose animals, the no-effect level in this study was determined to be 200 mg/kg/day of fosfomycin tromethamine.
12-Week Rat Study:
In another rat study, fosfomycin tromethamine was given daily by oral gavage for 12 weeks, with 4 weeks recovery. Male and female rats, eighteen per dosing group, respectively received doses 250, 1000 and 4000 mg/kg. The no-effect level was seen at the 1000 mg/kg dose level. The males and females in the 4000 mg/kg group had areas of mucosal inflammation in the terminal ileum and colon. Also, liver weight and kidney weight increases were evident at the high doses for the male and female rats. In the females, kidney weight increases were also noted at 250 and 1000 mg/kg respectively. There was no drug-related mortality. Treatment effects did not persist during the 4 week recovery period.
4-Week Dog Study:
In another study, fosfomycin tromethamine was administered once daily by oral gavage to three groups of Beagle dogs for 4 weeks at doses of 100, 300 and 1000 mg/kg/day. Each group consisted of 4 male and 4 female dogs and an additional group acted as control.
Survival, physical and ophthalmoscopic examinations, hematology values, urinalysis data, and gross or histopathological evaluations did not reveal any drug-related effects.
The body weights of the high-dose males were about 10% lower than control males during the first three weeks and 8% lower than at study termination. The body weights in the 300 mg/kg/day females were 8 to 10% lower than controls and in the 1000 mg/kg/day females 11 to 14% lower. The body weight effects were generally more pronounced during the early part of the study and appeared to become less marked over time.
A statistically significant increase in aspartate aminotransferase as compared to control values was observed in the high-dose males at study termination.
The absolute and relative testes weights of the high-dose males were slightly or statistically significantly lower than controls, respectively. Based on the body weight effects seen in females given 300 mg/kg/day, the no adverse effect level for this study was determined to be 100 mg/kg/day of fosfomycin tromethamine.
Chronic Toxicity
26-Week Dog Study:
Fosfomycin tromethamine was administered daily, by oral gavage, to dogs at doses of 100, 300 and 1000 mg/kg for 26 weeks, with a 6 week recovery period.
Diarrhea was observed in the animals in the high-dose group during the first four weeks of treatment, but this returned to normal as the study progressed. There were no deaths.
At all dose levels, the external appearance of the animals, food consumption, hematology, blood chemistry, urinalysis, and ECG results revealed no changes attributable to either of the drugs tested. Gross autopsy and histopathological examinations did not reveal any differences between the control and treatment groups.
Reproduction
Fertility Study:
In a fertility study, Sprague Dawley rats received fosfomycin tromethamine by oral gavage at doses of 0, 250, 500 and 1000 mg/kg/day. Treatment groups consisted of 24 males per dose and 24 females per dose. Dosing in males was once daily beginning at puberty for 63 days before mating and throughout cohabitation. The females were dosed daily for at least 14 days before mating, throughout 14 days of cohabitation and until day 7 post-coitum.
The only side effects observed were diarrhea in the males during the first four weeks of treatment and a reduction in food intake in the males given 500 and 1000 mg/kg/day during the first four days of treatment. Treatment did not adversely affect spermatogenesis or the reproductive capacity of the male rats nor adversely affect oogenesis, the regularity of the estrus cycle, or fertility and gestation in the female rats.
Teratology Studies
Rat Study:
In a teratogenicity study, fosfomycin tromethamine was administered by oral gavage to 4 groups of female Sprague Dawley rats at doses of 0, 250, 500 and 1000 mg/kg/day. The dosing was done from gestation day 6 through gestation day 15. Litter viability, sizes, and weights in the treated groups were comparable with those in the control group, except for one litter in the 250 mg/kg/day group in which scarcely viable and underweight fetuses were observed.
At high doses of 1000 mg/kg/day, comparable to approximately 20 times the normal human dose, treatments did not produce teratogenic effects and the litters of dams left to deliver at term developed normally during the period of lactation. The maternal and the fetal no-observed-adverse-effect-level (NOAEL) was 1000 mg/kg/day.
Rabbit Study:
In the rabbit teratogenicity study, fosfomycin tromethamine was administered by oral gavage to four groups at doses of 100, 200 and 400 mg/kg/day. These rabbits were divided after mating into four groups of 14-15 rabbits who were dosed from gestation days 6 to 16 and sacrificed on gestation day 28. Six female rabbits died in the course of gestation: two (1 at 100 mg/kg, 1 at 400 mg/kg) as a result of faulty gavage procedure, and four (1 control, 1 at 100 mg/kg and 2 at 400 mg/kg) died after a few days of anorexia; the cause of death was not evident during necropsy. Diarrhea was observed in all groups and melena occurred in one animal and mucoid stools in another in the 400 mg/kg/day group.
Treatment did not adversely affect the normal course of gestation except in one 100 mg/kg/day female that aborted on gestation day 28 and expelled dead fetuses in various stages of resorption. Treatment did not adversely affect the development of the viable fetuses and the external, visceral and skeletal examinations of the fetuses did not reveal any drug-related major malformations or minor anomalies. There was a possible increase in resorptions at the mid and high doses. These toxicities were considered to be due to the well recognized sensitivity of the rabbit to changes in the intestinal microflora resulting from antibiotic administration.
Peri-postnatal Study
Fosfomycin tromethamine was administered by oral gavage once daily to groups of 20 pregnant dams at doses of 250, 500 and 1000 mg/kg/day, respectively. The dosing was on day 6 of gestation through day 21 of lactation. Observation of the F1 generation showed normal morphological and psychomotor development in all groups. The fertility gestation and parturition in the F1 generation were also normal in all groups. The survival rate and postnatal body growth in all groups of the F2 generation were normal for the colony of rats used in this study. The maternal and fetal fetal no-observed-adverse-effect-level (NOAEL) was 1000 mg/kg/day.
Placenta Transfer Study
In a placenta transfer study, rats (dams) were dosed by oral gavage 50 mg/kg/day on either gestation day (GD) 14 or 19. Samples collected at 2, 4, 6 and 24 hours included liver, kidney, plasma and placenta for the dams, embryonic tissue, pooled embryos and amniotic fluid for the fetuses. Study results showed fosfomycin concentration in maternal plasma and tissue below limits of quantification on GD 14 at 24 hours. Detectable levels were observed in plasma, the kidney and placenta in dams dosed on GD 19. For the fetuses, maximum accumulation of fosfomycin in amniotic fluid occurs between 4 to 6 hours post dose and at GD 19 fosfomycin was detected only in the amniotic fluid. Conclusive results demonstrated fosfomycin readily crosses the placenta and that the fetal kidney was the major site of fosfomycin accumulation. The fetal-maternal ratio is 0.65.
Mutagenicity
A standard Ames in vitro test was conducted using fosfomycin tromethamine in a Salmonella typhimurium system (strains TA-98, TA-100, TA-1535, TA-1537 and TA-1538). The results showed fosfomycin tromethamine did not cause an increase in the number of reversions in the Salmonella strains.
Also, in the in vitro bacterial reversion test, fosfomycin tromethamine was not mutagenic. No genotoxicity was demonstrated in the in vitro tests using cultured human lymphocytes, the Chinese hamster V79 cells or with in vivo mouse micronucleus assay.
Carcinogenicity
Long term carcinogenicity studies in rodents have not been conducted because fosfomycin tromethamine is to be administered as a single dose treatment in humans.
BIBLIOGRAPHY
- 1. Andrews JM, Baquero F, Beltran JM, Canton E, Crokaert F, Gobernado M, et al. International collaborative study on standardization of bacterial sensitivity of fosfomycin. J Antimicrob Chemother. 1983;12(4):357-61.
- 2. Arca P, Reguera G, Hardisson C. Plasmid-encoded fosfomycin resistance in bacteria isolated from the urinary tract in a multicentre survey. J Antimicrob Chemother. 1997;40(3):393-9
- 3. Barry AL, Fuchs PC. In vitro susceptibility testing procedures for fosfomycin tromethamine. Antimicrob Agents Chemother. 1991;35(6):1235-8.
- 4. Barry AL, Pfaller MA, Fuchs PC, Tenover FC, Reller LB, Allen SO, et al. Interpretive criteria and quality control parameters for determining bacterial susceptibility to fosfomycin tromethamine. Eur J Clin Microbial Infect Dis. 1993;12(5):352-6.
- 5. Barry AL, Brow SD. Antibacterial spectrum of fosfomycin trometamol. J Antimicrob Chemother. 1995;35(1 ):228-30.
- 6. Bergan T. Degree of absorption, pharmacokinetics of fosfomycin trometamol and duration of antibacterial activity. Infection. 1990;18 Suppl 2:65-9.
- 7. Bergan T, Thorsteinsson SB, Albini E. Pharmacokinetic profile of fosfomycin trometamol. Chemotherapy. 1993;39: 297-301.
- 8. Bergan T. Pharmacokinetics of fosfomycin and influence of cimetidine and metoclopramide on the bioavailability of fosfomycin trometamol. Neu HC, Williams JD, editors. New trends in urinary tract infections: The single-dose therapy. Basel: Karger; 1988. p. 157-66.
- 9. Bergogne-Berezin E, Muller-Serieys C, Joly-Guillou ML, Dronne N. Trometamol fosfomycin (MONURIL) bioavailability and food-drug interaction. Eur Urol. 1987;13 Suppl 1:64-8.
- 10. Borgia M, Longo A, Lodola E. Relative bioavailability of fosfomycin and of trometamol after administration of single dose by oral route of fosfomycin trometamol in fasting conditions and after a meal. Int J Clin Pharm Ther Tox. 1989;(27):411-7.
- 11. Briggs GG, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation: A Reference Guide to Fetal and Neonatal Risk. 7th ed. Lippincott Williams and Wilkins; 2005. p. 700-702.
- 12. De Cecco L, Ragni N. Urinary tract infections in pregnancy: MONURIL single-dose treatment versus traditional therapy. Eur Urol. 1987;13 Suppl 1:108-13.
- 13. Ferreres L, Paz M, Martin G, Gobernado M. New studies on placental transfer of fosfomycin. Chemotherapy. 1977;23 Suppl 1:175-9.
- 14. Fillastre JP, Leroy A, Humbert G, Borsa F, Josse S. Comparative pharmacokinetics study of fosfomycin trometamol versus calcium fosfomycin in healthy elderly subjects and uremic patients. Neu HC, Williams JD, editors. New trends in urinary tract infections. Int. Symp, Karger, Basel; 1988. p.143-156.
- 15. Greenwood D, Jones A, Eley A. Factors influencing the activity of the trometamol salt of fosfomycin. Eur J Clin Microbial. 1986;5(1):29-34.
- 16. Janknegt R, Hooymans PM, Fabius GT, Nohlmans-Paulssen MK, Machielsen C, Boogaard-van den Born J, et al. Urinary concentrations of fosfomycin after a single 3 g dose of fosfomycin to elderly nursing-home patients. Pharm World Sci. 1994;16(3):149-53.
- 17. Kahan FM, Kahan JS, Cassidy PJ, Kropp H. The mechanism of action of fosfomycin (phosphonomycin). Ann NY Acad Sci. 1974; 235:364-86.
- 18. National Committee for Clinical Laboratory Standards (NCCLS). Performance standard for antimicrobial disk susceptibility tests. 5th ed. ANSI/NCCLS M2-A5. Villanova, PA: NCCLS, 1993.
- 19. National Committee for Clinical Laboratory Standards (NCCLS). Methods for dilution antimicrobial susceptibility tests for bacteria that grow aerobically. 3rd ed. ANSI/NCCLS M7-A4. Villanova, PA: NCCLS, 1993
- 20. Patel SS, Balfone JA, Bryson HM. Fosfomycin tromethamine. A review of its antibacterial activity, pharmacokinetic properties and therapeutic efficacy as a single-dose oral treatment for acute uncomplicated lower urinary tract infections. Drugs. 1997;53(4):637-56.
- 21. Pfaller MA, Barry AL, Fuchs PC. Evaluation of disk susceptibility testing of fosfomycin tromethamine. Diagn Microbiol lnfect Dis. 1993;17(1):67-70.
- 22. Pinasi C, Albini E, Marca G. Correlation between bactericidal activity of fosfomycin trometamol in an in vitro model of the urinary bladder and susceptibility testing. Eur Urol. 1987;13 Suppl 1:80-5.
- 23. Potel G, Meignier M, Baron D, Reynaud A, Touze MD, Courtieu AI. Pharmacokinetics of fosfomycin in normal and burn patients. Effect of probenecid. Drugs Exp Clin Res. 1989;15(4):177-84.
- 24. Ragni N. Urinary tract infections in pregnancy: Fosfomycin trometamol single-dose treatment vs. conventional therapy with pipemidic acid. Neu HC, Williams JD, editors. New trends in urinary tract infections: The single-dose therapy. Basel: Karger; 1988. p. 197-206.
- 25. Reeves DS, Holt HA, Bywater MJ, Ley D. Effect of fosfomycin trometamol of the faecal flora of eight healthy volunteers. Neu HC, Williams JD, editors. New trends in urinary tract infections: The single-dose therapy. Basel: Karger; 1988. p. 292-98.
- 26. Schito GC, Ghezzi C, Nicoletti G, Moreddu M, Arcangeletti MC, Stefani S, et al. Susceptibility of frequent urinary pathogens to fosfomycin trometamol and eight other antibiotics: results of an Italian multicenter survey. Infection. 1992;20 Suppl 4:S291-5.