


Product Monograph - Daptomycin for Injection (Juno Pharmaceuticals)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Intravenous | Lyophilized Powder for Solution, 500 mg / vial | Sodium hydroxide |
INDICATIONS AND CLINICAL USE
Daptomycin for Injection is indicated for the following infections in adults:
Complicated skin and skin structure infections (cSSSI) caused by susceptible strains of the following Gram-positive microorganisms: Staphylococcus aureus (including methicillin- resistant strains), Streptococcus pyogenes and Streptococcus agalactiae.
Combination therapy may be clinically indicated if the documented or presumed pathogens include Gram-negative and/or anaerobic organisms. Skin and soft tissues infections are considered complicated when they involve deeper skin structures, such as fascia or muscle layers, require significant surgical intervention or arise in the presence of significant co- morbidity.
Staphylococcus aureus bloodstream infections (bacteremia) including those with right-sided Staphylococcus aureus infective endocarditis (native valve) caused by methicillin-susceptible and methicillin-resistant strains.
Patients with prosthetic valves, meningitis, known osteomyelitis, polymicrobial bloodstream infections or with intravascular foreign material not planned for removal within 4 days of dosing (except vascular stents in place for > 6 months or permanent pacemakers) were not enrolled in clinical trials.
The efficacy of daptomycin for injection in patients with left-sided infective endocarditis due to Staphylococcus aureus has not been demonstrated. The clinical trial of daptomycin in patients with Staphylococcus aureus bloodstream infections included limited data from patients with left-sided infective endocarditis; outcomes in these patients were poor.
Combination therapy may be clinically indicated if the documented or presumed pathogens include Gram-negative and/or anaerobic organisms.
Daptomycin for Injection is not indicated for the treatment of pneumonia.
Patients with persisting or relapsing Staphylococcus aureus infection or poor clinical response should have repeat blood cultures. Appropriate surgical intervention (e.g., debridement, removal of prosthetic devices, valve replacement surgery) and/or consideration of a change in antibiotic regimen may be required.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Daptomycin for Injection and other antibacterial drugs, Daptomycin for Injection should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Pediatrics (<18 years of age):
Daptomycin for Injection is indicated for the following infections in pediatric patients (aged 1 to 17 years):
Complicated skin and skin structure infections (cSSSI) caused by susceptible strains of the following Gram-positive microorganisms: Staphylococcus aureus (including methicillin-resistant strains), Streptococcus pyogenes and Streptococcus agalactiae.
Staphylococcus aureus bloodstream infections (bacteremia) caused by methicillin-susceptible and methicillin-resistant strains.
The safety and effectiveness of daptomycin for injection in the treatment of cSSSI and S. aureus bloodstream infections (bacteremia) have been established in the age groups 1 to 17 years of age. Use of daptomycin for injection in these age groups is supported by evidence from adequate and well-controlled studies in adults, with additional data from pharmacokinetic (PK) studies in pediatric patients, and from safety, efficacy and PK studies in pediatric patients with cSSSI and S. aureus bloodstream infections.
Safety and effectiveness in pediatric patients below the age of one year have not been established. Daptomycin for Injection is not recommended in pediatric patients younger than one year of age due to the risk of potential effects on muscular, neuromuscular, and/or nervous systems (either peripheral and/or central) observed in neonatal dogs.
The dosage regimen for daptomycin for injection in pediatric patients with renal impairment has not been established.
Daptomycin for injection has not been studied in pediatric patients with other bacterial infections.
CONTRAINDICATIONS
Daptomycin for Injection is contraindicated in patients with known hypersensitivity to daptomycin.
WARNINGS AND PRECAUTIONS
General
Daptomycin for Injection should be reconstituted with 0.9% sodium chloride for injection, USP (see Reconstitution).
Daptomycin for Injection should not be used in conjunction with ReadyMED® elastomeric infusion pumps. Stability studies of daptomycin for injection solutions stored in ReadyMED® elastomeric infusion pumps identified an impurity (2-mercaptobenzothiazole) leaching from this pump system into the daptomycin for injection solution (see Reconstitution).
Daptomycin for injection is inactive against Gram-negative bacteria.
Because daptomycin activity is inhibited in the presence of pulmonary surfactant,
Daptomycin for Injection is not indicated for use in pneumonia.
The safety and efficacy of daptomycin for injection has not been established in patients with co-morbidities of meningitis, musculopathies, neuropathies or severe renal impairment.
Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) and Tubulointerstitial
Nephritis (TIN)
DRESS and TIN have been reported in post-marketing experience with daptomycin. Patients who develop fever, skin rash, peripheral eosinophilia and/or new or worsening renal impairment or other organ impairment while receiving Daptomycin for Injection should undergo medical evaluation. If DRESS and/or TIN are suspected, Daptomycin for Injection should be discontinued promptly and appropriate treatment instituted (see Renal).
Immune System
Hypersensitivity
Anaphylaxis and hypersensitivity reactions (including angioedema, drug rash with eosinophilia and systemic symptoms (DRESS), pruritus, hives, shortness of breath, difficulty swallowing, truncal erythema and pulmonary eosinophilia) have been reported with daptomycin for injection use. If an allergic reaction occurs, administration of Daptomycin for Injection should be discontinued and appropriate therapy should be initiated.
Persisting or Relapsing Staphylococcus aureus Infection
Patients with persisting or relapsing Staphylococcus aureus infection or poor clinical response should have repeat blood cultures. If a culture is positive for Staphylococcus aureus, MIC susceptibility testing of the isolate should be performed using a standardized procedure, as well as diagnostic evaluation to rule out sequestered foci of infection. Appropriate surgical intervention (e.g., debridement, removal of prosthetic devices, valve replacement surgery) and/or consideration of a change in antibiotic regimen may be required.
In the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, failure of treatment due to persisting or relapsing Staphylococcus aureus infections was assessed in 19/120 (15.8%) daptomycin for injection-treated patients [12 with methicillin-resistant Staphylococcus aureus (MRSA) and 7 with methicillin-susceptible Staphylococcus aureus (MSSA)] and 11/115 (9.6%) comparator-treated patients (9 with MRSA treated with vancomycin and 2 with MSSA treated with anti-staphylococcal semi-synthetic penicillin). Among all failures, 6 daptomycin for injection-treated patients and 1 vancomycin-treated patient developed increasing MICs (reduced susceptibility) on or following therapy. Most patients who failed due to persisting or relapsing Staphylococcus aureus infection had deep-seated infection and did not receive necessary surgical intervention.
Musculoskeletal
Myopathy and Creatine Phosphokinase (CPK)
Myopathy [muscular pains, weakness, and/or rhabdomyolysis (with or without acute renal failure)] associated with creatine phosphokinase (CPK) elevations has been observed with the use of daptomycin in human and animal studies and during post-marketing use (see ADVERSE REACTIONS, DETAILED PHARMACOLOGY and TOXICOLOGY).
Therefore, in patients receiving Daptomycin for Injection it is recommended that:
- Patients should be monitored regularly for any signs and symptoms that might represent myopathy including muscle pain or weakness, particularly in the distal extremities.
- Any patient who develops unexplained muscle pain, tenderness, weakness or cramps should have CPK levels monitored every 2 days.
- Plasma CPK levels should be measured at baseline and at least once weekly during therapy in all patients.
- Patients who develop unexplained elevations in CPK should be monitored more frequently than once weekly.
- Consideration should be given prior to initiation of Daptomycin for Injection therapy in patients with increased baseline CPK as these patients may be at increased risk of further increases of CPK during Daptomycin for Injection therapy. If Daptomycin for Injection is given, these patients should be monitored more frequently than once weekly.
- CPK should be measured more frequently than once weekly in patients who are at higher risk of developing myopathy. These patients include but are not limited to those with renal impairment, and those who recently received or are currently taking other medications known to be associated with myopathy (e.g., HMG-CoA reductase inhibitors).
Daptomycin for Injection should be discontinued in patients with unexplained signs and symptoms of myopathy in conjunction with CPK elevation > 1000 U/L (approximately 5 times ULN), or in patients without reported symptoms who have marked elevations in CPK (≥ 10 times ULN). In addition, consideration should be given to temporarily suspending agents associated with rhabdomyolysis, such as HMG-CoA reductase inhibitors, in patients receiving Daptomycin for Injection.
In adult Phase 3 complicated skin and skin structure infection trials (cSSSI) of daptomycin for injection, at a dose of 4 mg/kg, elevations in serum CPK were reported as clinical adverse events in 15/534 (2.8%) daptomycin for injection-treated patients, compared to 10/558 (1.8%) comparator-treated patients.
In the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, at a dose of 6 mg/kg, elevations in CPK were reported as clinical adverse events in 8/120 (6.7%) of daptomycin for injection-treated patients, compared to 1/116 (< 1%) of the comparator-treated patients. There were a total of 11 patients who experienced CPK elevations to above 500 U/L (2.5 times ULN). Of these 11 patients, 5 had recent prior or concomitant treatment with an HMG-CoA reductase inhibitor. Three (2.6%) daptomycin for injection-treated patients, including 1 with trauma associated with heroin overdose, 1 with spinal cord compression and 1 with concomitant HMG-CoA reductase inhibitor, had an elevation in CPK > 500 U/L with associated musculoskeletal symptoms. None of the patients in the comparator group had an elevation of CPK > 500 U/L with associated musculoskeletal symptoms.
In a Phase 1 study in adult healthy volunteers examining doses up to 12 mg/kg q24h of daptomycin for injection for 14 days, no skeletal muscle effects or CPK elevations were observed.
Skeletal muscle effects associated with daptomycin for injection were observed in animals (see DETAILED PHARMACOLOGY, Animal Pharmacology and TOXICOLOGY).
Neurologic
Neuropathy
Cases of peripheral neuropathy have been reported during post-marketing therapy with daptomycin for injection (see ADVERSE REACTIONS).
Patients should be monitored for signs and symptoms of neuropathy during therapy with daptomycin for injection.
Direct effects on the central nervous system have not been investigated.
In a small number of patients in adult Phase 1 and Phase 2 studies at doses up to 6 mg/kg, administration of daptomycin for injection was associated with decreases in nerve conduction velocity and with adverse events (e.g., paresthesias, Bell’s palsy) possibly reflective of peripheral or cranial neuropathy. In the Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, a total of 11/120 (9.2%) daptomycin for injection-treated patients had treatment-emergent adverse events related to the peripheral nervous system. All of the events were classified as mild to moderate in severity; most were of short duration and resolved during continued treatment with daptomycin for injection or were likely due to an alternative etiology.
In a Phase 1 study in adult healthy volunteers examining doses up to 12 mg/kg q24h of daptomycin for injection for 14 days, no evidence of peripheral nerve conduction deficits or symptoms of peripheral neuropathy were observed.
In adult animals, effects of daptomycin for injection on peripheral nerve were observed. In juvenile dogs, peripheral and spinal cord nerve effects were noted.
Pediatric patients younger than 12 months should not be given daptomycin for injection due to the risk of potential effects on muscular, neuromuscular, and/or nervous systems (either peripheral and/or central) that were observed in neonatal dogs (see INDICATIONS AND CLINICAL USE, Pediatrics, DETAILED PHARMACOLOGY, Animal Pharmacology and TOXICOLOGY).
Renal
The safety and efficacy of daptomycin for injection in patients with severe renal impairment (creatinine clearance < 30 mL/min) have not been established. Daptomycin for Injection should only be considered for use in patients with severe renal impairment when the expected clinical benefit outweighs the potential risk and there are no further available therapeutic options. In these patients, a dose adjustment is required (see DOSAGE AND ADMINISTRATION, Patients with Renal Impairment). Response to treatment, renal function and creatine phosphokinase (CPK) should be closely monitored.
No dose adjustment is required in adult patients with mild to moderate renal impairment (creatinine clearance ≥30 mL/min). However, due to limited clinical experience, response to treatment, renal function and creatine phosphokinase (CPK) should be closely monitored in all patients with some degree of renal impairment (creatinine clearance < 80 mL/min).
Consideration should be given to monitoring renal function in adult patients treated with Daptomycin for Injection. Renal impairment has been reported during treatment with daptomycin for injection although the relationship to daptomycin remains unclear (see ADVERSE REACTIONS).
Caution is advised prior to commencing therapy with Daptomycin for Injection in adult patients who already have some degree of renal impairment (creatinine clearance < 80 mL/min).
Regular monitoring of renal function is advised during the concomitant administration of potentially nephrotoxic agents, regardless of the patient’s underlying renal function.
In the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, at a dose of daptomycin for injection 6 mg/kg/day, a lower clinical success rate and an increase in serious adverse events were seen in patients with moderately impaired renal function (creatinine clearance 30 to < 50 mL/min).
The dosage regimen for daptomycin for injection in pediatric patients with renal impairment has not been established.
If DRESS and/or TIN are suspected, Daptomycin for Injection should be discontinued promptly and appropriate treatment instituted.
Carcinogenesis and Mutagenesis
Long-term carcinogenicity studies in animals have not been conducted to evaluate the carcinogenic potential of daptomycin. However, neither mutagenic nor clastogenic potential was found in a battery of genotoxicity tests (see TOXICOLOGY).
Gastrointestinal
Clostridium difficile-Associated Disease
Clostridium difficile-associated disease (CDAD) has been reported with the use of many antibacterial agents, including daptomycin for injection. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Respiratory
Community-Acquired Pneumonia
In adult Phase 3 studies of community-acquired pneumonia, the death rate and rates of serious cardiorespiratory adverse events were higher in daptomycin for injection-treated patients than in comparator- treated patients. These differences were due to lack of therapeutic effectiveness of daptomycin for injection in the treatment of community-acquired pneumonia in patients experiencing these adverse events (see INDICATIONS AND CLINICAL USE). Daptomycin’s activity in vitro is inhibited by the presence of pulmonary surfactant.
Eosinophilic Pneumonia
Eosinophilic pneumonia has been reported in patients receiving daptomycin for injection. In reported cases associated with daptomycin for injection, patients developed fever, dyspnea with hypoxic respiratory insufficiency, and diffuse pulmonary infiltrates or organizing pneumonia. In general, patients developed eosinophilic pneumonia 2 to 4 weeks after starting daptomycin for injection and improved when daptomycin for injection was discontinued and steroid therapy was initiated. Recurrence of eosinophilic pneumonia upon re-exposure has been reported. Patients who develop these signs and symptoms while receiving Daptomycin for Injection should undergo prompt medical evaluation, and Daptomycin for Injection should be discontinued immediately. Treatment with systemic steroids is recommended.
Susceptibility/Resistance
Development of Drug-Resistant Bacteria
The use of antibiotics may promote the overgrowth of non-susceptible organisms. Should superinfection occur during therapy, appropriate measures should be taken.
Prescribing Daptomycin for Injection in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Special Populations
Pregnant Women: No clinical studies have been performed in pregnant women. Daptomycin for Injection should not be used during pregnancy unless clearly necessary and the benefits to the mother outweigh the potential risks to the fetus. Animal studies have not demonstrated harmful effects with respect to pregnancy, embryonal/fetal development, parturition or postnatal development.
Nursing Women: Data from a single case indicated that daptomycin is present in human milk. Daptomycin is poorly bioavailable orally. Due to limited data, breastfeeding should be discontinued during treatment with Daptomycin for Injection.
Pediatrics (<18 years of age): The safety and effectiveness of daptomycin for injection in the treatment of cSSSI and S. aureus bloodstream infections (bacteremia) have been established in the age groups 1 to 17 years of age. Use of daptomycin for injection in these age groups is supported by evidence from adequate and well-controlled studies in adults, with additional data from pharmacokinetic (PK) studies in pediatric patients, and from safety, efficacy and PK studies in pediatric patients with cSSSI and S. aureus bloodstream infections.
Pediatric patients younger than 12 months should not be given daptomycin for injection due to the risk of potential effects on muscular, neuromuscular, and/or nervous systems (either peripheral and/or central) that were observed in neonatal dogs (see INDICATIONS AND CLINICAL USE, Pediatrics, ACTION AND CLINICAL PHARMACOLOGY, Special
Populations and Conditions, Pediatrics, DETAILED PHARMACOLOGY, Animal Pharmacology, and TOXICOLOGY).
Geriatrics (≥ 65 years of age): In the adult Phase 3 clinical studies, lower clinical success rates were seen in patients ≥ 65 years of age compared to those < 65 years of age. In addition, treatment-emergent adverse events were more common in patients ≥ 65 years old than in patients
< 65 years of age. Of the 534 patients treated with daptomycin for injection in Phase 3 controlled clinical trials of complicated skin and skin structure infection (cSSSI), 27.0% were 65 years of age or older and 12.4% were 75 years or older. Of the 120 patients treated with daptomycin for injection in the Phase 3 Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) controlled clinical trial, 25.0% were 65 years of age or older and 15.8% were 75 years or older.
Monitoring and Laboratory Tests
Creatine Phosphokinase (CPK)
Patients should be monitored regularly for any signs and symptoms that might represent myopathy including muscle pain or weakness, particularly in the distal extremities. Any patient who develops unexplained muscle pain, tenderness, weakness or cramps should have CPK levels monitored every 2 days.
Plasma CPK levels should be measured at baseline and at least once weekly during Daptomycin for Injection therapy in all patients. Patients who develop unexplained elevations in CPK should be monitored more frequently than once weekly. Consideration should be given prior to initiation of Daptomycin for Injection therapy in patients with increased baseline CPK as these patients may be at increased risk of further increases of CPK during Daptomycin for Injection therapy. If Daptomycin for Injection is given, these patients should be monitored more frequently than once weekly.
CPK should be measured more frequently than once weekly in patients who are at higher risk of developing myopathy. These patients include but are not limited to those with renal impairment, and those who recently received or are currently taking other medications known to be associated with myopathy (e.g., HMG-CoA reductase inhibitors) [see WARNINGS AND PRECAUTIONS, Musculoskeletal, Myopathy and Creatine Phosphokinase (CPK)].
Renal
Consideration should be given to monitoring renal function in patients treated with
Daptomycin for Injection.
In patients with renal impairment (creatinine clearance < 80 mL/min) response to treatment, renal function and creatine phosphokinase (CPK) should be closely monitored.
The safety and efficacy of daptomycin for injection in patients with severe renal impairment (creatinine clearance < 30 mL/min) have not been established.
The dosage regimen for daptomycin for injection in pediatric patients with renal impairment has not been established.
Neuropathy
Patients should be monitored for signs and symptoms of neuropathy during therapy with
Daptomycin for Injection.
Warfarin
As experience with the concomitant administration of daptomycin for injection and warfarin is limited, anticoagulant activity in patients receiving Daptomycin for Injection and warfarin should be monitored for the first several days after initiating therapy with Daptomycin for Injection.
ADVERSE REACTIONS
Adverse Drug Reaction Overview Adults
Clinical studies enrolled 1,667 patients treated with daptomycin for injection and 1,319 treated with comparator.
Overall, at least one adverse event was reported by 51.3% of daptomycin for injection -treated subjects and by 52.5% of comparator-treated subjects in two adult Phase 3, double-blind, controlled complicated skin and skin structure infection (cSSSI) trials. In the randomized, comparative, open-label adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, the majority of patients experienced at least one treatment emergent adverse event during the study, including 95.8% and 94.8% of patients in the daptomycin for injection and comparator groups, respectively. The majority of adverse events reported in the adult Phase 1, 2 and 3 clinical studies were described as mild or moderate in intensity.
In the adult cSSSI trials, daptomycin for injection was discontinued in 15/534 (2.8%) patients due to an adverse event while comparator was discontinued in 17/558 (3.0%) patients. In the adult SAB/SAIE trial, daptomycin for injection was discontinued in 20/120 (16.7%) patients due to an adverse event while comparator was discontinued in 21/116 (18.1%) patients.
The most frequent adverse events observed in the adult cSSSI trials were: constipation, nausea, injection site reactions, headache and diarrhea. In the SAB/SAIE trial, the most frequent adverse events were: diarrhea, vomiting, constipation and nausea.
The safety data for the administration of daptomycin via 2-minute intravenous injection are derived from two pharmacokinetic studies in adult healthy volunteers. Based on these study results, both methods of daptomycin administration, the 2-minute intravenous injection and the 30-minute intravenous infusion, had a similar safety and tolerability profile. There was no relevant difference in local tolerability or in the nature and frequency of adverse reactions.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Complicated Skin and Skin Structure Infection (cSSSI) Trials in Adults
Most Common Clinical Trial Adverse Drug Reactions in Two Adult Phase 3 cSSSI Studies
The rates of the most common treatment emergent adverse events irrespective of causality, organized by body system, observed in the cSSSI clinical trials are displayed in Table 1.
Table 1. Incidence (%) of Treatment Emergent Adverse Events Irrespective of Causality that Occurred in ≥ 2% of Patients in Either Daptomycin or Comparator Treatment Groups in the Adult Phase 3 cSSSI Studies1 (Population: Safety2)
| Adverse Event | Daptomycin 4 mg/kg (N=534) | Comparator3 (N=558) |
| Gastrointestinal Disorders | ||
| Constipation | 6.2% | 6.8% |
| Nausea | 5.8% | 9.5% |
| Diarrhea | 5.2% | 4.3% |
| Vomiting | 3.2% | 3.8% |
| Dyspepsia | 0.9% | 2.5% |
| General Disorders | ||
| Injection site reactions | 5.8% | 7.7% |
| Fever | 1.9% | 2.5% |
| Nervous System Disorders | ||
| Headache | 5.4% | 5.4% |
| Insomnia | 4.5% | 5.4% |
| Dizziness | 2.2% | 2.0% |
| Skin/Subcutaneous Disorders | ||
| Rash | 4.3% | 3.8% |
| Pruritus | 2.8% | 3.8% |
| Diagnostic Investigations | ||
| Abnormal liver function tests | 3.0% | 1.6% |
| Elevated CPK | 2.8% | 1.8% |
| Infections | ||
| Fungal infections | 2.6% | 3.2% |
| Urinary tract infections | 2.4% | 0.5% |
| Vascular Disorders | ||
| Hypotension | 2.4% | 1.4% |
| Hypertension | 1.1% | 2.0% |
| Renal/Urinary Disorders | ||
| Renal failure | 2.2% | 2.7% |
| Blood/Lymphatic Disorders | ||
| Anemia | 2.1% | 2.3% |
| Respiratory Disorders | ||
| Dyspnea | 2.1% | 1.6% |
| Musculoskeletal Disorders | ||
| Limb pain | 1.5% | 2.0% |
| Arthralgia | 0.9% | 2.2% |
1 This table includes Adverse Events from both cSSSI Phase 3 trials. The first trial was conducted in the U.S. and South Africa, the second in Europe, South Africa, Australia and Israel
2 Safety population includes all subjects who received at least one dose of daptomycin or comparator according to treatment actually received during the trials
3 Comparators included vancomycin (1 g IV q12h), which was used in patients with known or suspected penicillin allergy or with methicillin- resistant Staphylococcus aureus infection, and anti-staphylococcal semi-synthetic penicillin (i.e. nafcillin, oxacillin, cloxacillin, flucloxacillin 4- 12 g/day IV), which were selected based on the standard therapy in each country.
Additional adverse events that occurred in < 1 to 2% of patients in either daptomycin for injection (4 mg/kg) or comparator treatment groups in the adult cSSSI studies are as follows: edema, cellulitis, hypoglycemia, elevated alkaline phosphatase, cough, back pain, abdominal pain, hypokalemia, hyperglycemia, decreased appetite, anxiety, chest pain, sore throat, cardiac failure, confusion and Candida infections. These events occurred at rates ranging from 0.2 to 1.7% in daptomycin for injection-treated patients and at rates of 0.4 to 1.8% in comparator-treated patients.
The most common possibly or probably drug-related treatment emergent adverse events organized by body system, observed in the adult cSSSI trials are displayed in Table 2.
Table 2. Incidence (%) of Possibly or Probably Drug-Related Treatment Emergent Adverse Events Occurring in ≥ 1% of Patients in Either Daptomycin or Comparator Treatment Groups in the Adult Phase 3 cSSSI Studies (Population: Safety)
| Adverse Event | Daptomycin 4 mg/kg (N=534) | Comparator (N=558) |
| Gastrointestinal Disorders | ||
| Nausea | 2.2% | 3.4% |
| Investigations | ||
| Blood creatine phosphokinase increased | 2.1% | 1.4% |
Less Common Clinical Trial Adverse Drug Reactions (<1%) in Two Adult Phase 3 cSSSI Studies
Additional drug-related adverse events (possibly or probably related) that occurred in < 1% of patients receiving daptomycin for injection in the complicated skin and skin structure infection (cSSSI) trials are as follows:
Body as a Whole: fatigue, weakness, rigors, discomfort, tremor, flushing, hypersensitivity Blood/Lymphatic System: leukocytosis, thrombocytopenia, thrombocytosis, eosinophilia, increased international normalized ratio (INR)
Cardiovascular System: supraventricular arrhythmia
Dermatologic System: eczema
Digestive System: abdominal distension, flatulence, stomatitis, jaundice, increased serum lactate dehydrogenase
Metabolic/Nutritional System: hypomagnesemia, increased serum bicarbonate, electrolyte disturbance
Musculoskeletal System: myalgia, muscle cramps, muscle weakness, osteomyelitis
Nervous System: vertigo, mental status change, paraesthesia Special Senses: taste disturbance, eye irritation Reproductive System and Breast Disorders: vaginitis
Abnormal Hematologic and Clinical Chemistry Findings in Two Adult Phase 3 cSSSI Studies
In the two adult Phase 3 comparator-controlled complicated skin and skin structure (cSSSI) studies, there was no clinically or statistically significant difference (p<0.05) in the incidence of creatine phosphokinase (CPK) elevations between patients treated with daptomycin for injection and those treated with comparator. CPK elevations in both groups were generally related to medical conditions, for example, skin and skin structure infection, surgical procedures, or intramuscular injections; and were not associated with muscle symptoms.
Table 3 summarizes the CPK shifts from Baseline through End of Treatment in the adult cSSSI trials.
Table 3. Incidence (%) of Creatine Phosphokinase (CPK) Elevations From Baseline Through End of Treatment in either Daptomycin or Comparator Treatment Groups in Adult Phase 3 cSSSI Studies
| Change | All Patients | Patients with Normal CPK at Baseline | ||||||
| Daptomycin (N=430) | Comparator (N=459) | Daptomycin (N=374) | Comparator (N=392) | |||||
| % | N | % | N | % | N | % | N | |
| No Increase | 90.7% | 390 | 91.1% | 418 | 91.2% | 341 | 91.1% | 357 |
Maximum Value >1x ULN* | 9.3% | 40 | 8.9% | 41 | 8.8% | 33 | 8.9% | 35 |
| >2x ULN | 4.9% | 21 | 4.8% | 22 | 3.7% | 14 | 3.1% | 12 |
| >4x ULN | 1.4% | 6 | 1.5% | 7 | 1.1% | 4 | 1.0% | 4 |
| >5x ULN | 1.4% | 6 | 0.4% | 2 | 1.1% | 4 | 0.0% | 0 |
| >10x ULN | 0.5% | 2 | 0.2% | 1 | 0.2% | 1 | 0.0% | 0 |
* ULN (Upper Limit of Normal) is defined as 200 U/L.
In the adult cSSSI studies, 0.2% of patients treated with daptomycin for injection had symptoms of muscle pain or weakness associated with CPK elevations to greater than 4 times the upper limit of normal. The symptoms resolved within 3 days and CPK returned to normal within 7 to 10 days after discontinuing treatment [see WARNINGS AND PRECAUTIONS, Musculoskeletal, Myopathy and Creatine Phosphokinase (CPK)].
Staphylococcus aureus Bacteremia/Staphylococcus aureus Infective Endocarditis (SAB/SAIE) Trial in Adults
Most Common Clinical Trial Adverse Drug Reactions in the Adult SAB/SAIE Trial
The rates of the most common treatment emergent adverse events irrespective of causality and organized by body system observed in the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial are displayed in Table 4.
Table 4. Incidence (%) of Treatment Emergent Adverse Events Irrespective of Causality that Occurred in ≥ 5% of Patients in Daptomycin or Comparator Treatment Groups in the Adult SAB/SAIE Study (Population: Safetya)
| Adverse Events | Daptomycin 6 mg/kg (N=120) | Comparatorb (N=116) |
| Infections and Infestations | 54.2% | 48.3% |
| Urinary tract infection NOSc | 6.7% | 9.5% |
| Osteomyelitis NOS | 5.8% | 6.0% |
| Sepsis NOS | 5.0% | 2.6% |
| Bacteremia | 5.0% | 0% |
| Pneumonia NOS | 3.3% | 7.8% |
| Gastrointestinal Disorders | 50.0% | 58.6% |
| Diarrhea NOS | 11.7% | 18.1% |
| Vomiting NOS | 11.7% | 12.9% |
| Constipation | 10.8% | 12.1% |
| Nausea | 10.0% | 19.8% |
| Abdominal pain NOS | 5.8% | 3.4% |
| Dyspepsia | 4.2% | 6.9% |
| Loose stools | 4.2% | 5.2% |
| Gastrointestinal hemorrhage NOS | 1.7% | 5.2% |
| General Disorders and Administration Site Conditions | 44.2% | 59.5% |
| Edema peripheral | 6.7% | 13.8% |
| Pyrexia | 6.7% | 8.6% |
| Chest pain | 6.7% | 6.0% |
| Edema NOS | 6.7% | 4.3% |
| Asthenia | 5.0% | 5.2% |
| Injection site erythema | 2.5% | 6.0% |
| Respiratory, Thoracic and Mediastinal Disorders | 31.7% | 37.1% |
| Pharyngolaryngeal pain | 8.3% | 1.7% |
| Pleural effusion | 5.8% | 6.9% |
| Cough | 3.3% | 6.0% |
| Dyspnea | 3.3% | 5.2% |
| Skin and Subcutaneous Tissue Disorders | 30.0% | 34.5% |
| Rash NOS | 6.7% | 8.6% |
| Pruritus | 5.8% | 5.2% |
| Erythema | 5.0% | 5.2% |
| Sweating increased | 5.0% | 0% |
| Musculoskeletal and Connective Tissue Disorders | 29.2% | 36.2% |
| Pain in extremity | 9.2% | 9.5% |
| Back pain | 6.7% | 8.6% |
| Arthralgia | 3.3% | 11.2% |
| Psychiatric Disorders | 29.2% | 24.1% |
| Insomnia | 9.2% | 6.9% |
| Anxiety | 5.0% | 5.2% |
| Nervous System Disorders | 26.7% | 27.6% |
| Headache | 6.7% | 10.3% |
| Dizziness | 5.8% | 6.0% |
| Investigations | 25.0% | 28.4% |
| Blood creatine phosphokinase increased | 6.7% | <1% |
| Blood and Lymphatic System Disorders | 24.2% | 20.7% |
| Anemia NOS | 12.5% | 15.5% |
| Metabolism and Nutrition Disorders | 21.7% | 32.8% |
| Hypokalemia | 9.2% | 12.9% |
| Hyperkalemia | 5.0% | 8.6% |
| Vascular Disorders | 17.5% | 17.2% |
| Hypertension NOS | 5.8% | 2.6% |
| Hypotension NOS | 5.0% | 7.8% |
Injury, Poisoning and Procedural Complications | 15.8% | 15.5% |
| Renal and Urinary Disorders | 15.0% | 22.4% |
| Renal failure NOS | 3.3% | 9.5% |
| Renal failure acute | 3.3% | 6.0% |
| Cardiac Disorders | 11.7% | 15.5% |
| Reproductive System and Breast Disorders | 5.0% | 6.9% |
| Eye Disorders | 4.2% | 8.6% |
a Safety population includes all subjects who received at least one dose of daptomycin or comparator according to treatment actually received during the trials
b Comparator: vancomycin (1 g IV q12h), which was used in patients with known or suspected penicillin allergy or with methicillin- resistant Staphylococcus aureus, or anti-staphylococcal semi-synthetic penicillins (i.e., nafcillin, oxacillin, cloxacillin, flucloxacillin; 2 g IV q4h), which were selected based on the standard therapy in each country, each with initial synergistic gentamicin.
c NOS: Not Otherwise Specified
Note: p-values by body system were as follows: infections p=0.435; gastrointestinal p=0.194; general and administration site p=0.020; respiratory, thoracic, mediastinal p=0.412; skin and subcutaneous tissue p=0.488; musculoskeletal and connective tissue p=0.269; psychiatric p=0.462; nervous system p=0.885; investigations p=0.560; blood and lymphatic system p=0.537; metabolism and nutrition p=0.059; vascular p>0.999; injury, poisoning p>0.999; renal and urinary p=0.181; cardiac disorders p=0.449; reproductive system p=0.591; eye disorders p=0.189
The most common possibly or probably drug-related treatment emergent adverse events, organized by body system, observed in the adult SAB/SAIE trial are displayed in Table 5.
Table 5. Incidence (%) of Possibly or Probably Drug-Related Treatment Emergent Adverse Events Occurring in ≥ 1% of Patients in Either Daptomycin or Comparator Treatment Groups in the Adult Phase 3 SAB/SAIE Study (Population: Safety)
| Adverse Events | Daptomycin 6 mg/kg (N=120) | Comparator (N=116) |
| Investigations | ||
| Blood creatine phosphokinase (CPK) increased | 5.0% | 0% |
| Blood phosphorus increased | 2.5% | <1% |
| Blood alkaline phosphatase increased | 1.7% | 0% |
| International normalized ratio increased | 1.7% | 0% |
| Liver function test abnormal | 1.7% | <1% |
| Blood creatinine increased | 0% | 2.6% |
| Gastrointestinal Disorders | ||
| Loose stools | 3.3% | 1.7% |
| Dyspepsia | 2.5% | <1% |
| Diarrhea NOS | 1.7% | 9.5% |
| Nausea | 1.7% | 5.2% |
| Vomiting | <1% | 1.7% |
| Skin and Subcutaneous Tissue Disorders | ||
| Rash NOS | 2.5% | 2.6% |
| Renal and Urinary Disorders | ||
| Renal failure NOS | 1.7% | 6.0% |
| Renal impairment NOS | <1% | 1.7% |
| Renal failure acute | 0% | 2.6% |
| Infections and Infestations | ||
| Candidal infection NOS | 1.7% | 0% |
| Vaginal candidiasis | 1.7% | 0% |
| General Disorders and Administration Site Conditions | ||
| Chest pain | 1.7% | 0% |
| Pyrexia | 0% | 2.6% |
| Blood and Lymphatic System Disorders | ||
| Eosinophilia | 1.7% | 0% |
| Nervous System Disorders | ||
| Dysgeusia | 0% | 2.6% |
| Vascular Disorders | ||
| Hypotension NOS | 0% | 2.6% |
| Musculoskeletal and Connective Tissue Disorders | ||
| Arthralgia | 0% | 1.7% |
| Weakness in extremity | 1.7% | 0% |
Less Common Clinical Trial Adverse Drug Reactions in the Adult SAB/SAIE Trial (< 1%)
The following events, not included above in Table 5, were reported as possibly or probably drug- related in the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) daptomycin for injection-treated group:
Blood and Lymphatic System Disorders: lymphadenopathy, thrombocythemia, thrombocytopenia
Cardiac Disorders: atrial fibrillation, atrial flutter, cardiac arrest
Ear and Labyrinth Disorders: tinnitus
Eye Disorders: vision blurred
Gastrointestinal Disorders: dry mouth, epigastric discomfort, gingival pain, hypoesthesia oral Infections and Infestations: fungemia, oral candidiasis, urinary tract infection fungal Investigations: alanine aminotransferase increased, aspartate aminotransferase increased, prothrombin time prolonged
Metabolism and Nutrition Disorders: appetite decreased NOS Musculoskeletal and Connective Tissue Disorders: myalgia Nervous System Disorders: dyskinesia, paresthesia Psychiatric Disorders: hallucination NOS
Renal and Urinary Disorders: proteinuria, renal impairment NOS
Skin and Subcutaneous Tissue Disorders: heat rash, pruritus generalized, rash vesicular Abnormal Hematologic and Clinical Chemistry Findings in the Adult SAB/SAIE Trial
In the adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) trial, a total of 11 daptomycin for injection patients (9.2%) had treatment-emergent elevations in creatine phosphokinase (CPK) to > 500 U/L, including 4 patients with elevations > 10X ULN. Three of these 11 patients had CPK levels return to the normal range during continued daptomycin for injection treatment, 6 had values return to the normal range during follow-up, 1 had values returning toward baseline at the last assessment, and 1 did not have follow-up values reported. Six of the 11 patients with treatment-emergent CPK elevations > 500 U/L had medical or surgical reasons for the elevated CPK. Three patients discontinued daptomycin for injection due to CPK elevation. Table 6 presents the incidence of CPK elevations from baseline in all patients and in patients with normal CPK levels through the end of treatment with daptomycin for injection and comparator in the adult SAB/SAIE trial.
Table 6. Incidence (%) of Creatine Phosphokinase (CPK) Elevations from Baseline through End of Treatment in either Daptomycin or Comparator Treatment Groups in the Adult SAB/SAIE Study
| Change | All Patients | Patients with Normal CPK at Baseline | ||||||
Daptomycin (N=116) % N | Comparator (N=111) % N | Daptomycin (N=92) % N | Comparator (N=96) % N | |||||
| No Increase | 75.9 | 88 | 87.4 | 97 | 75.0 | 69 | 87.5 | 84 |
| Maximum Value > 1X ULN* | 24.1 | 28 | 12.6 | 14 | 25.0 | 23 | 12.5 | 12 |
| > 2X ULN | 13.8 | 16 | 6.3 | 7 | 12.0 | 11 | 5.2 | 5 |
| > 4X ULN | 8.6 | 10 | 0.9 | 1 | 7.6 | 7 | 0.0 | 0 |
| > 5X ULN | 6.9 | 8 | 0.9 | 1 | 5.4 | 5 | 0.0 | 0 |
| > 10X ULN | 3.4 | 4 | 0.9 | 1 | 2.2 | 2 | 0.0 | 0 |
- * ULN (Upper Limit of Normal) is laboratory specific.
Note: CPK evaluations through 3 days post-treatment are included in the analysis.
There was more renal dysfunction in comparator-treated patients than in daptomycin for injection-treated patients. The incidence of decreased renal function, defined as the proportion of patients with a creatinine clearance level < 50 mL/min if baseline clearance was ≥ 50 mL/min or with a decrease of ≥ 10 mL/min if baseline clearance was < 50 mL/min, is shown in Table 7.
Table 7. Incidence of Decreased Renal Function Based on Creatinine Clearance Levels
| Study Interval | Daptomycin 6 mg/kg (N=120) n/N (%) | Comparatora (N=116) n/N (%) |
| Days 2 to 4 | 2/96 (2.1%) | 6/90 (6.7%) |
| Days 2 to 7 | 6/115 (5.2%) | 16/113 (14.2%) |
| Days 2 to End of Study | 13/118 (11.0%) | 30/114 (26.3%) |
a Comparator: vancomycin (1 g IV q12h) or anti-staphylococcal semi-synthetic penicillin (i.e. nafcillin, oxacillin, cloxacillin, flucloxacillin; 2 g IV q4h), each with initial low-dose gentamicin.
Complicated Skin and Skin Structure Infection (cSSSI) Trial in Pediatric Patients
The safety of daptomycin for injection was evaluated in one cSSSI clinical trial which included 256 pediatric patients (1 to 17 years of age) treated with intravenous daptomycin for injection and 133 patients treated with comparator agents. Patients were given age-dependent doses once daily for a treatment period of up to 14 days (median treatment period was 3 days). The doses given by age group were as follows: 10 mg/kg for 1 to <2 years, 9 mg/kg for 2 to 6 years, 7 mg/kg for 7 to 11 years and 5 mg/kg for 12 to 17 years of age. Patients treated with daptomycin for injection were 51% male, 49% female and 46% Caucasian and 32% Asian.
In the pediatric cSSSI study, daptomycin for injection was discontinued in 7/256 (2.7%) patients due to an adverse reaction, while comparator was discontinued in 7/133 (5.3%) patients.
Most Common Clinical Trial Adverse Drug Reactions in the Pediatric cSSSI Trial
The rates of the most common adverse events, organized by body system, observed in pediatric patients with cSSSI are displayed in Table 8.
Table 8. Incidence (%) of Adverse Events that Occurred in ≥2% of Pediatric Patients in the Daptomycin Treatment-Arm and Greater Than or Equal to the Comparator Treatment-Arm in the Pediatric cSSSI Trial
| Adverse Events | Daptomycin (N=256) | Comparator* (N=133) |
| Gastrointestinal Disorders | ||
| Diarrhea | 7.0% | 5.3% |
| Vomiting | 2.7% | 0.8% |
| Abdominal Pain | 2.0% | 0% |
| General Disorders and Administration Site Conditions | ||
| Pyrexia | 3.9% | 3.0% |
| Investigations | ||
| Blood creatine phosphokinase (CPK) increased | 5.5% | 5.3% |
| Nervous System Disorders | ||
| Headache | 2.7% | 2.3% |
| Skin and Subcutaneous Tissue Disorders | ||
| Pruritus | 3.1% | 1.5% |
*Comparators included intravenous therapy with either vancomycin, clindamycin, or an anti-staphylococcal semi-synthetic penicillin (nafcillin, oxacillin, or cloxacillin)
The safety profile in the clinical trial of cSSSI pediatric patients was similar to that observed in the cSSSI adult trials.
Staphylococcus aureus Bacteremia Trial in Pediatric Patients
The safety of daptomycin for injection was evaluated in one S. aureus bacteremia clinical trial which treated 55 pediatric patients with intravenous daptomycin for injection and 26 patients with comparator agents. Patients were given age-dependent doses once daily for a treatment period of up to 42 days (mean duration of IV treatment was 12 days). The doses by age group were as follows: 12 mg/kg for 1 to <6 years, 9 mg/kg for 7 to 11 years and 7 mg/kg for 12 to 17 years of age. Patients treated with daptomycin for injection were 69% male and 31% female. No patients 1 to <2 years of age were enrolled.
In the bacteremia study, daptomycin for injection was discontinued in 3/55 (5.5%) patients due to an adverse reaction, while comparator was discontinued in 2/26 (7.7%) patients.
Most Common Clinical Trial Adverse Drug Reactions in the Pediatric Bacteremia Trial
The rates of the most common adverse events, organized by body system, observed in pediatric patients with bacteremia are displayed in Table 9.
Table 9. Incidence (%) of Adverse Events that Occurred in ≥5% of Pediatric Patients in the Daptomycin Treatment-Arm and Greater Than or Equal to the Comparator Treatment-Arm in the Pediatric Bacteremia Trial
| Adverse Events | Daptomycin (N=55) | Comparator* (N=26) |
| Gastrointestinal Disorders | ||
| Vomiting | 10.9% | 7.7% |
| Investigations | ||
| Blood creatine phosphokinase (CPK) increased | 7.3% | 0% |
*Comparators included intravenous therapy with either vancomycin, cefazolin, or an anti-staphylococcal semi-synthetic penicillin (nafcillin, oxacillin, or cloxacillin)
Post-Market Adverse Drug Reactions
The following adverse reactions have been reported with daptomycin for injection in worldwide post- marketing experience. Because these events are reported voluntarily from a population of unknown size, estimates of frequency cannot be made and causal relationship cannot be precisely established.
Immune System Disorders: anaphylaxis; hypersensitivity reactions, including angioedema, drug reaction with eosinophilia and systemic symptoms (DRESS), pruritus, hives, shortness of breath, difficulty swallowing, truncal erythema and pulmonary eosinophilia.
Infections and Infestations: Clostridium difficile-associated diarrhea.
Investigations: platelet count decreased.
Musculoskeletal Disorders: myoglobin increased; rhabdomyolysis (some reports involved patients treated concurrently with daptomycin for injection and HMG-CoA reductase inhibitors).
Neurologic Disorders: one case of coma post-anaesthesia/surgery; peripheral neuropathy.
Renal and Urinary Disorders: acute kidney injury; renal failure; renal insufficiency; tubulointerstitial nephritis (TIN) Respiratory, Thoracic, and Mediastinal Disorders: cough; eosinophilic pneumonia (see WARNINGS AND PRECAUTIONS, Respiratory, Eosinophilic Pneumonia); organizing pneumonia.
Skin and Subcutaneous Tissue Disorders: acute generalized exanthematous pustulosis;
serious skin reactions, including Stevens-Johnson syndrome and vesiculobullous rash (with or without mucous membrane involvement).
DRUG INTERACTIONS
Overview
There is limited experience regarding concomitant administration of daptomycin for injection with other medicinal products that may trigger myopathy (e.g., HMG-CoA reductase inhibitors). However, some cases of marked rises in creatine phosphokinase (CPK) levels and cases of rhabdomyolysis occurred in adult patients taking one of these medications at the same time as daptomycin for injection. It is recommended that other medications associated with myopathy should, if possible, be temporarily discontinued during treatment with Daptomycin for Injection unless the benefits of concomitant administration outweigh the risk. If co-administration cannot be avoided, CPK levels should be measured more frequently than once weekly and patients should be closely monitored for any signs or symptoms that might represent myopathy.
Daptomycin is primarily cleared by renal filtration and, therefore, plasma levels may be increased during co-administration with medicinal products that reduce renal filtration (e.g., NSAIDs and COX-2 inhibitors). In addition, there is a potential for a pharmacodynamic interaction to occur during co-administration due to additive renal effects. Therefore, caution is advised when Daptomycin for Injection is co-administered with any other medicinal product known to reduce renal filtration.
Drug-Drug Interactions
Drug-drug interaction studies were performed in adults with daptomycin for injection and other drugs that are likely to either be co-administered or associated with overlapping toxicity as shown in Table 10.
Table 10. Established or Potential Drug-Drug Interactions with daptomycin for injection
| Drug Name | Ref | Effect | Clinical comment |
|---|---|---|---|
| Aztreonam | CT | In a study in which 15 healthy adult subjects received a single dose of daptomycin for injection 6 mg/kg IV and a combination dose of daptomycin for injection 6 mg/kg IV and aztreonam 1 g IV, the Cmax and AUC0-∞ of daptomycin were not significantly altered by aztreonam. | No dosage adjustment of daptomycin for injection is warranted when daptomycin for injection is co- administered with aztreonam. |
| Drug Name | Ref | Effect | Clinical comment |
|---|---|---|---|
HMG-CoA Reductase Inhibitors | CT | In 20 healthy adult subjects on a stable daily dose of oral simvastatin 40 mg, administration of daptomycin for injection 4 mg/kg IV q24h for 14 days (N=10) was not associated with a higher incidence of adverse events than subjects receiving placebo once daily (N=10). | Inhibitors of HMG-CoA reductase may cause myopathy, which is manifested as muscle pain or weakness associated with elevated levels of CPK. Experience with co-administration of HMG-CoA reductase inhibitors and daptomycin for injection in patients is limited, therefore, consideration should be given to temporarily suspending use of HMG-CoA reductase inhibitors in patients receiving daptomycin for injection (see WARNINGS AND PRECAUTIONS, Musculoskeletal). |
| Probenecid | CT | Concomitant administration of oral probenecid (500 mg four times daily) and a single dose of daptomycin for injection 4 mg/kg IV did not significantly alter the Cmax and AUC0-∞ of daptomycin. | No dosage adjustment of daptomycin for injection is warranted when daptomycin for injection is co-administered with probenecid. |
| Tobramycin | CT Non- clinical | In a study in which 6 healthy adult males received a single dose of daptomycin for injection 2 mg/kg IV, tobramycin 1 mg/kg IV, and both in combination, the mean Cmax and AUC0-∞ of daptomycin increased 12.7% and 8.7%, respectively, when administered with tobramycin. The mean Cmax and AUC0-∞ of tobramycin decreased 10.7% and 6.6%, respectively, when administered with daptomycin for injection. These differences were not statistically significant. In rats, mild skeletal muscle degeneration and/or regeneration was observed with 20 mg/kg IV daptomycin for injection when administered alone. During concurrent administration with tobramycin 10 mg/kg SC b.i.d., mild skeletal muscle changes were observed with 5 mg/kg IV daptomycin for injection. Tobramycin may have a weak potentiating effect on muscle damage caused by daptomycin for injection. | The interaction between daptomycin for injection and tobramycin with a clinical dose of daptomycin for injection is unknown. Caution is warranted when daptomycin for injection is co-administered with tobramycin. |
| Warfarin | CT | In 16 healthy adult subjects, concomitant administration of daptomycin for injection 6 mg/kg IV q24h for 5 days followed by a single oral dose of warfarin (25 mg) had no significant effect on the pharmacokinetics of either drug and did not significantly alter the INR (International Normalized Ratio). | As experience with the concomitant administration of daptomycin for injection and warfarin is limited, anticoagulant activity in patients receiving daptomycin for injection and warfarin should be monitored for the first several days after initiating therapy with daptomycin for injection. |
| Drug Name | Ref | Effect | Clinical comment |
|---|---|---|---|
| Gentamicin | Non- Clinical | An increase in nephrotoxicity was apparent upon combination treatment with daptomycin 30 mg/kg/day IV and a high dose of gentamicin (30 mg/kg/day IM) in dogs. No meaningful difference in nephrotoxicity was observed in animals receiving daptomycin in combination with a more clinically relevant dose of gentamicin (9 mg/kg/day IM). | Concurrent administration of daptomycin and clinical levels of gentamicin is unlikely to alter the nephrotoxic potential of gentamicin in humans. However, caution should be used when administering the combination to renally impaired patients. |
CT: Clinical Trial
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Clinically relevant plasma levels of daptomycin have been observed to cause a significant concentration-dependent false prolongation of prothrombin time (PT) and elevation of International Normalized Ratio (INR) when certain recombinant thromboplastin reagents are utilized for the assay. The possibility of an erroneously elevated PT/INR result due to interaction with a recombinant thromboplastin reagent may be minimized by drawing specimens for PT or INR testing near the time of trough plasma concentrations of daptomycin. However, sufficient daptomycin levels may be present at trough to cause interaction.
If confronted with an abnormally high PT/INR result in a patient being treated with Daptomycin for Injection, it is recommended that clinicians:
- 1. Repeat the assessment of PT/INR, requesting that the specimen be drawn just prior to the next Daptomycin for Injection dose (i.e., at trough concentration). If the PT/INR value drawn at trough remains substantially elevated over what would otherwise be expected, consider evaluating PT/INR utilizing an alternative method.
- 2. Evaluate for other causes of abnormally elevated PT/INR results.
DOSAGE AND ADMINISTRATION
Adults
Complicated Skin and Skin Structure Infections: Daptomycin for Injection 4 mg/kg should be administered intravenously once every 24 hours for 7 to 14 days, either by injection over a 2-minute period or by infusion over a 30-minute period.
Staphylococcus aureus Bloodstream Infections (Bacteremia) including those with Right- Sided Staphylococcus aureus Infective Endocarditis (Native Valve): Daptomycin for Injection
6 mg/kg should be administered intravenously once every 24 hours, either by injection over a 2-minute period or by infusion over a 30-minute period. Duration of treatment should be based on the treating physician’s working diagnosis. In the clinical trial, duration ranged from 10 days to 42 days with an option for an additional 14 days.
There are limited safety data for the use of daptomycin for injection for more than 28 days.
Clinical studies in adult patients employed infusion of daptomycin over 30 minutes. There is no clinical experience in patients with the administration of daptomycin as an injection over 2 minutes. This mode of administration was only studied in healthy subjects. However, when compared with the same doses given as intravenous infusions over 30 minutes, there were no clinically important differences in the pharmacokinetics and safety profile of daptomycin (see also ADVERSE REACTIONS, Adverse Drug Reaction Overview and ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Dosing and Administration Considerations
General
- Daptomycin for Injection should not be dosed more frequently than once a day. In Phase 1 and 2 clinical studies with daptomycin for injection, creatine phosphokinase (CPK) elevations appeared to be more frequent when daptomycin for injection was dosed more frequently than once daily.
- Clinical studies with daptomycin for injection have shown that dosing adjustments based on age alone, gender, race or obesity are not required (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
- Daptomycin for Injection should be reconstituted with a 21 gauge or smaller needle to prevent contamination of broken rubber in the reconstituted solution.
The recommended dosing schedule for adult patients including those with creatinine clearance
≥30 mL/min is presented in Table 11.
Table 11. Recommended Dosage of Daptomycin for Injection in Adult Patients including those with Creatinine Clearance ≥ 30 mL/min
| Creatinine Clearance | Indication | Dosage Regimen | Duration | |||||
| ≥ 30 mL/min | Complicated Skin and Skin Structure Infections | 4 mg/kg once every 24 hours | 7 to 14 days | |||||
Staphylococcus aureus Bloodstream Infections (Bacteremia) including those with Right-Sided Staphylococcus aureus Infective Endocarditis (Native Valve) | 6 mg/kg once every 24 hours | 10 to 42 days with an option for an additional 14 days | ||||||
Patients with Renal Impairment
Daptomycin is eliminated primarily by the kidney.
No dose adjustment is required in patients whose creatinine clearance is ≥30 mL/min (see Table
11).
Patients with Creatinine Clearance < 30 mL/min
Daptomycin for Injection should only be used in patients whose creatinine clearance is < 30 mL/min when it is considered that the expected clinical benefit outweighs the potential risk and for whom there are no further therapeutic options.
Clinical efficacy and safety of daptomycin for injection have not been established in patients with severe renal impairment (creatinine clearance < 30 mL/min).
The dose interval adjustment guidance presented below in Table 12 is based on pharmacokinetic modeling data.
Response to treatment, renal function and creatine phosphokinase (CPK) should be closely monitored in these patients.
Whenever possible, Daptomycin for Injection should be administered following the completion of dialysis on dialysis days. The use of high-flux dialysis membranes during 4 hours of hemodialysis may increase the percentage of dose removed compared with low-flux membranes.
Table 12. Dosage Adjustment of Daptomycin for Injection in Adult* Patients with Severe Renal Impairment (creatinine clearance < 30 mL/min)
| Creatinine Clearance | Indication | Dosage Regimen | Duration |
| < 30 mL/min | Complicated Skin and Skin Structure Infections | 4 mg/kg once every 48 hours | 7 to 14 days |
Staphylococcus aureus Bloodstream Infections (Bacteremia) including those with Right-Sided Staphylococcus aureus Infective Endocarditis (Native Valve) | 6 mg/kg once every 48 hours | 10 to 42 days with an option for an additional 14 days | |
*The dosage regimen for daptomycin for injection in pediatric patients with renal impairment has not been established
Patients with Hepatic Insufficiency
No dose adjustment is necessary when administering Daptomycin for Injection to patients with mild or moderate hepatic insufficiency (Child-Pugh Class B). No data are available in patients with severe hepatic insufficiency (Child-Pugh Class C).
Pediatrics
Complicated Skin and Skin Structure Infections:
Table 13. Recommended Dosage of Daptomycin for Injection in Pediatric Patients (aged 1 to 17 years) with cSSSI, based on Age
| Age Group | Dosage* |
| Duration of Therapy | |
| 12 to 17 years | 5 mg/kg once every 24 hours infused over 30 minutes |
| Up to 14 days | |
| 7 to 11 years | 7 mg/kg once every 24 hours infused over 30 minutes |
| 2 to 6 years | 9 mg/kg once every 24 hours infused over 60 minutes |
| 1 to less than 2 years | 10 mg/kg once every 24 hours infused over 60 minutes |
*Recommended dosage is for pediatric patients (1 to 17 years of age) with normal renal function. Dosage adjustment for pediatric patients with renal impairment has not been established.
Staphylococcus aureus Bloodstream Infections (Bacteremia):
Table 14: Recommended Dosage of Daptomycin for Injection in Pediatric Patients (aged 1 to 17 years) with S. aureus Bacteremia based on Age
| Age Group | Dosage* | Duration of Therapy |
| 12 to 17 years | 7 mg/kg once every 24 hours infused over 30 minutes | Up to 42 days |
| 7 to 11 years | 9 mg/kg once every 24 hours infused over 30 minutes | |
| 1 to 6 years | 12 mg/kg once every 24 hours infused over 60 minutes | |
*Recommended dosage is for pediatric patients (1 to 17 years of age) with normal renal function. Dosage adjustment for pediatric patients with renal impairment has not been established.
Dosing and Administration Considerations
- Unlike in adults, do NOT administer Daptomycin for Injection by injection over a two (2) minute period to pediatric patients.
Administer Daptomycin for Injection to pediatric patients intravenously by infusion over a 30- or 60-minute period, based on age:
- Pediatric Patients 7 to 17 years of age: Administer Daptomycin for Injection intravenously by infusion over a 30-min period. The appropriate volume of reconstituted Daptomycin for Injection (concentration of 50 mg/mL) should be further diluted into a 50 mL intravenous infusion bag containing 0.9% sodium chloride injection. The infusion rate should be maintained at 1.67 mL/minute over the 30-minute period.
Pediatric Patients 1 to 6 years of age: Administer Daptomycin for Injection
intravenously by infusion over a 60-minute period. The appropriate volume of reconstituted Daptomycin for Injection (concentration of 50 mg/mL) should be further diluted into an intravenous infusion bag containing 25 mL of 0.9% sodium chloride injection. The infusion rate should be maintained at 0.42 mL/minute over the 60-minute period.
Reconstitution
Daptomycin for Injection should be reconstituted with 0.9% sodium chloride for injection, USP
(see Reconstitution).
Daptomycin for Injection is supplied in single-dose vials containing 500 mg daptomycin as a sterile, lyophilized powder. The contents of a Daptomycin for Injection 500 mg vial should be reconstituted with 10 mL of 0.9% sodium chloride for injection to 50 mg/mL. Since no preservative or bacteriostatic agent is present in the product, aseptic technique must be used in preparation of the product.
Procedure:
- 1. Prior to reconstitution, remove the Daptomycin for Injection vials from refrigeration and allow the product to sit at room temperature for a few minutes. Daptomycin for Injection vials do not need to be warmed to room temperature prior to reconstitution.
- 2. Remove the aluminium flip-off cap from the Daptomycin for Injection vial to expose the central portions of the rubber stoppers. Gently tap vial twice on counter to settle/loosen the lyophilized powder cake.
- 3. Using a syringe, slowly transfer the diluent through the center of the rubber stopper into the Daptomycin for Injection vial, pointing the transfer needle toward the wall of the vial to prevent excessive foaming. Ensure that the complete daptomycin product is wetted by gently rotating the vial.
- 4. Allow the product to sit undisturbed for approximately 10 minutes at room temperature.
- 5. Gently swirl the Daptomycin for Injection vial until a clear, fully reconstituted solution is obtained. This typically takes from 5 to 15 minutes.
- 6. AVOID VIGOROUS SHAKING TO PREVENT FOAMING OF THE PRODUCT DURING RECONSTITUTION.
The reconstituted solution should be checked carefully to ensure that the product is in solution and visually inspected for the absence of particulates prior to use. Freshly reconstituted solutions of Daptomycin for Injection range in colour from pale yellow to light brown.
For IV injection over a period of 2 minutes:
Reconstitute Daptomycin for Injection, as directed above, to a concentration of 50 mg/mL with 0.9% sodium chloride for injection.
For IV infusion over a period of 30 minutes:
Reconstitute Daptomycin for Injection, as directed above, to a concentration of 50 mg/mL with 0.9% sodium chloride for injection. Further dilute using aseptic technique with additional 0.9% sodium chloride for injection to a final concentration in the range of 2.5 to 20 mg/mL (typically 10 mg/mL).
| Vial Size | Nominal Concentration of Reconstituted Solution | Approximate Available Volume of Reconstituted Solution | Volume of Additional Diluent | Total Volume of Solution for Infusion | Nominal Concentration of Solution for Infusion |
| 500 mg | 50 mg/mL | 10 mL | 15 mL | 25 mL | 20 mg/mL |
| 500 mg | 50 mg/mL | 10 mL | 40 mL | 50 mL | 10 mg/mL |
| 500 mg | 50 mg/mL | 10 mL | 190 mL | 200 mL | 2.5 mg/mL |
Because Daptomycin for Injection does not contain any preservative or bacteriostatic agent, aseptic technique must be used during preparation for administration and the product should be used promptly. If reconstituted Daptomycin for Injection within the vial or infusion bag is not used immediately, it must be refrigerated at 2 to 8°C. It is recommended that the solution be used within 72 hours due to the possibility of microbial contamination during reconstitution (see also STORAGE AND STABILITY).
Daptomycin for Injection should not be used in conjunction with ReadyMED® elastomeric infusion pumps. Stability studies of daptomycin for injection solutions stored in ReadyMED® elastomeric infusion pumps identified an impurity (2-mercaptobenzothiazole) leaching from this pump system into the daptomycin for injection solution.
Daptomycin for Injection vials are for single-use only.
Compatible Intravenous Solutions
Daptomycin for Injection is compatible with 0.9% sodium chloride injection and lactated Ringer’s injection. The following are compatible at room temperature when co-administered with Daptomycin for Injection in 0.9% sodium chloride through the same IV line from separate infusion bags: aztreonam, ceftazidime, ceftriaxone, gentamicin, fluconazole, levofloxacin, dopamine, heparin, and lidocaine.
Daptomycin for Injection is NOT compatible with glucose (dextrose) containing diluents. Other than the nine drugs listed above, additives and other medications should not be infused simultaneously with Daptomycin for Injection through the same IV line because only limited data are available on compatibility. If the same IV line is used for sequential infusion of several different drugs, the line should be flushed with a compatible infusion solution before and after infusion with Daptomycin for Injection. No other product than the approved diluent should be added to the Daptomycin for Injection vial or infusion bag.
OVERDOSAGE
In the event of overdosage, supportive care is advised with maintenance of glomerular filtration. Daptomycin is slowly cleared from the body by hemodialysis (approximately 15% recovered over 4 hours) or peritoneal dialysis (approximately 11% recovered over 48 hours). The use of high-flux membranes during 4 hours of hemodialysis may increase the percentage of dose removed, as evidenced by the larger decrease in the pre- to post-dose concentrations (41%) compared with low-flux membranes (5 to 7%).
A 58-year old male with a history of multiple sclerosis, diabetes and hypertension was administered an accidental single dose of daptomycin for injection 3 g (43 mg/kg). Twenty-four hours later symptoms of orofacial movements, lip smacking and shoulder shrugging were observed and diagnosed as dyskinesia. Daptomycin for injection was discontinued and the patient was treated with benztropine and lorazepam. The events resolved and therapy was restarted without further incident.
ACTION AND CLINICAL PHARMACOLOGY
For management of a suspected drug overdose, contact your regional Poison Control Centre immediately.
Mechanism of Action
Daptomycin is a cyclic lipopeptide antibacterial agent. Daptomycin binds to Gram-positive bacterial membranes in a calcium-dependant manner and causes a rapid depolarization of membrane potential. This loss of membrane potential causes inhibition of protein, DNA, and RNA synthesis, which results in bacterial cell death. Activity of daptomycin is dependant on the presence of physiological levels of free calcium ions (50 μg/mL) (see MICROBIOLOGY).
Resistance
Cases of daptomycin resistance have been reported in staphylococci in clinical trials and during post-marketing use.
Pharmacokinetics
The mean pharmacokinetic parameters of daptomycin at steady-state following IV administration of daptomycin for injection over a 30-minute period at 4 to 12 mg/kg q24h to healthy young adults are summarized in Table 15.
Table 15. Mean Daptomycin Pharmacokinetic Parameters in Healthy Adult Volunteers at Steady-State
| Doseb (mg/kg) | N | Pharmacokinetic Parametersa Mean (Standard Deviation) | ||||||||||||
cAUC0-24 (µg*h/mL) | t1/2 (h) | Vss (L/kg) | CLT (mL/h/kg) | cCmax (µg/mL) | cCmin (µg/mL) | |||||||||
| 4 | 6 | 494 (75) | 8.1 (1.0) | 0.096 (0.009) | 8.3 (1.3) | 57.8 (3.0) | 5.9 (1.6) | |||||||
| 6 | 6 | 632 (78) | 7.9 (1.0) | 0.101 (0.007) | 9.1 (1.5) | 93.9 (6.0) | 6.7 (1.6) | |||||||
| 8 | 6 | 858 (213) | 8.3 (2.2) | 0.101 (0.013) | 9.0 (3.0) | 123.3 (16.0) | 10.3 (5.5) | |||||||
| 10 | 9 | 1039 (178) | 7.9 (0.6) | 0.098 (0.017) | 8.8 (2.2) | 141.1 (24.0) | 12.9 (2.9) | |||||||
| 12 | 9 | 1277 (253) | 7.7 (1.1) | 0.097 (0.018) | 9.0 (2.8) | 183.7 (25.0) | 13.7 (5.2) | |||||||
a AUC0-24: area under the concentration-time curve from 0 to 24 hours; t½: terminal elimination half-life ; Vss: volume of distribution at steady- state; CLT: plasma clearance; Cmax: maximum plasma concentration (total drug)
b Doses of daptomycin for injection in excess of 6 mg/kg have not been approved
c Values relate to total drug in plasma (free + protein bound)
Absorption: Daptomycin pharmacokinetics were generally linear and time-independent at doses of 4 to 12 mg/kg q24h. Steady-state trough concentrations were achieved by the third daily dose. The mean (standard deviation) steady-state trough concentrations attained following administration of 4, 6, 8, 10 and 12 mg/kg q24h were 5.9 (1.6), 6.7 (1.6), 10.3 (5.5), 12.9 (2.9) and 13.7 (5.2) μg/mL, respectively. The mean AUC and Cmin (minimum plasma concentration) of daptomycin during once-daily dosing with 6, 8, 10 and 12 mg/kg were dose proportional; however, the mean Cmax (maximum plasma concentration) was slightly less than dose proportional. Total clearance was unchanged across 4 to 12 mg/kg q24h.
Daptomycin administered as a 2-minute intravenous injection also exhibited dose proportional pharmacokinetics in the approved therapeutic dose range of 4 to 6 mg/kg. Comparable exposure (AUC and Cmax) was demonstrated in healthy adult subjects following administration of daptomycin as a 30-minute intravenous infusion or as a 2-minute intravenous injection.
Following IV administration of daptomycin for injection to healthy adult volunteers over a 2-minute period at doses of 4 and 6 mg/kg, the mean (SD) daptomycin steady-state AUC0-tau values were 475 (71) and 701 (82) µg*h/mL, respectively. The mean (SD) steady-state Cmax values were 63 (11) and 92 (18) µg/mL, respectively.
Distribution: Daptomycin is reversibly bound to human plasma proteins, primarily to serum albumin, in a concentration-independent manner. The overall mean binding at doses from 4 to 12 mg/kg ranged from 90 to 93%. The apparent volume of distribution (Vd) of daptomycin at steady-state in healthy adult subjects was low, approximately 0.1 L/kg at doses of 4 to 12 mg/kg, consistent with distribution primarily within the extracellular space.
Daptomycin penetrates into skin blister fluid and reaches a mean Cmax of 27.6 μg/mL (mean t½=
17.3 hrs).
In clinical studies, mean serum protein binding in adult subjects with creatinine clearance (CLCR)
≥ 30 mL/min was comparable to that observed in healthy adult subjects with normal renal function. However, there was a trend toward decreasing serum protein binding among subjects with CLCR < 30 mL/min (87.6%), including hemodialysis patients (85.9%) and continuous ambulatory peritoneal dialysis patients (83.5%). The protein binding of daptomycin in subjects with moderate hepatic impairment (Child-Pugh B) was similar to healthy adult subjects.
Metabolism: In vitro studies with human hepatocytes indicate that daptomycin does not inhibit or induce the activities of the following human cytochrome P450 (CYP) isoforms: 1A2, 2A6, 2C9, 2C19, 2D6, 2E1, and 3A4. In in vitro studies, daptomycin was not detectably metabolized by human liver microsomes. It is unlikely that daptomycin will inhibit or induce the metabolism of drugs metabolized by the CYP system.
In a separate study, no metabolites were observed in plasma on Day 1 following administration of daptomycin at 6 mg/kg to healthy adult subjects. Inactive metabolites have been detected in urine, as determined by the difference in total radioactivity concentrations and microbiologically active concentrations. Minor amounts of 3 oxidative metabolites and one unidentified compound were detected in urine. The site of metabolism has not been identified.
Excretion: Daptomycin is excreted primarily by the kidney. In a mass balance study of 5 healthy adult subjects using radiolabelled daptomycin, approximately 78% of the administered dose was recovered from urine based on total radioactivity (approximately 52% of the dose based on microbiologically active concentrations) and 5.7% of the dose was recovered from feces (collected for up to nine days) based on total radioactivity.
Due to limited clinical experience, response to treatment, renal function and creatine phosphokinase (CPK) should be closely monitored in all patients with some degree of renal impairment (CLCR < 80 mL/min) (see DOSAGE AND ADMINISTRATION).
Special Populations and Conditions
Pediatrics: The pharmacokinetics of daptomycin in pediatric subjects was evaluated in 3 single- dose pharmacokinetic studies. In general, body weight-normalized total body clearance in pediatric patients was higher than in adults and increased with a decrease of age, whereas elimination half-life tends to decrease with a decrease of age. Body weight-normalized total body clearance and elimination half-life of daptomycin in children 2 to 6 years of age were similar at different doses.
A study was conducted to assess safety, efficacy, and pharmacokinetics of daptomycin in pediatric patients (1 to 17 years old, inclusive) with cSSSI caused by Gram-positive pathogens. Patients were enrolled into 4 age groups and intravenous daptomycin for injection doses of 5 to 10 mg/kg once daily were administered. Following administration of multiple doses, daptomycin exposure (AUCss and Cmax,ss) was similar across different age groups after dose adjustment based on body weight and age (Table 16).
Table 16. Mean (SD) Daptomycin Population Pharmacokinetic Parameters in cSSSI Pediatric Populations
| Age | Pharmacokinetic Parameters | ||||||
| Dose (mg/kg | Infusion Duration (min) | AUCss (µg·h/mL) | t1/2 (h) | Vss (mL) | CLT (mL/h/kg) | Cmax,ss (µg/mL) | |
12 to 17 years (N=6) | 5 | 30 | 434 (67.9) | 7.1 (0.9) | 8200 (3250) | 11.8 (2.15) | 76.4 (6.75) |
7 to 11 years (N=2) | 7 | 30 | 543* | 6.8* | 4470* | 13.2* | 92.4* |
2 to 6 years (N=7) | 9 | 60 | 452 (93.1) | 4.6 (0.8) | 2750 (832) | 20.8 (4.29) | 90.3 (14.0) |
1 to <2 years (N=27) | 10 | 60 | 462 (138) | 4.8 (0.6) | 1670 (446) | 23.1 (5.43) | 81.6 (20.7) |
AUCss: area under the concentration-time curve at steady-state; t½: terminal elimination half-life ; Vss: volume of distribution at steady-state; CLT: plasma clearance; Cmax: maximum plasma concentration at steady-state (total drug).
*Mean is calculated from N=2
A study was conducted to assess the safety, efficacy and pharmacokinetics of daptomycin in pediatric patients with S. aureus bacteremia. Patients were enrolled into 3 age groups and intravenous doses of 7 to 12 mg/kg once daily were administered. Following administration of multiple doses, daptomycin exposure (AUCss and Cmax,ss) was similar across different age groups after dose adjustment based on body weight and age (Table 17).
Table 17. Mean (SD) of Daptomycin Pharmacokinetics in Bacteremia Pediatric Patients
| Age | Pharmacokinetic Parameters | ||||||
| Dose (mg/kg | Infusion Duration (min) | AUCss (µg·h/mL) | t1/2 (h) | Vss (mL) | CLT (mL/h/kg) | Cmax,ss (µg/mL) | |
12 to 17 years (N=13) | 7 | 30 | 656 (334) | 7.5 (2.3) | 6420 (1980) | 12.4 (3.9) | 104 (35.5) |
7 to 11 years (N=19) | 9 | 30 | 579 (116) | 6.0 (0.8) | 4510 (1470) | 15.9 (2.8) | 104 (14.5) |
| 2 to 6 years | 620 | 5.1 | 2200 | 19.9 | 106 | ||
| 12 | 60 | (N=19) | (109) | (0.6) | (570) | (3.4) | (12.8) |
AUCss: area under the concentration-time curve at steady-state; t½: terminal elimination half-life ; Vss: volume of distribution at steady-state; CLT: plasma clearance; Cmax: maximum plasma concentration at steady-state (total drug).
No patients 1 to <2 years of age were enrolled in the study. Simulation using a population pharmacokinetic model demonstrated that the AUCss of daptomycin in pediatric patients 1 to <2 years of age receiving daptomycin 12 mg/kg once daily would be comparable to adult patients receiving 6 mg/kg once daily.
Geriatrics: The pharmacokinetics of daptomycin were evaluated in 12 healthy elderly subjects (≥ 75 years of age) and 11 healthy young matched controls (18 to 30 years of age). Following administration of a single 4 mg/kg IV dose of daptomycin for injection, the mean total clearance of daptomycin was reduced approximately 35% and the mean AUC0-∞ increased approximately 58% in elderly subjects compared to young healthy subjects. There were no differences in Cmax. No dosage adjustment is warranted for elderly patients with normal renal function based on age alone.
Gender: No clinically significant gender-related differences in daptomycin pharmacokinetics have been observed. No dosage adjustment is warranted based on gender when administering Daptomycin for Injection.
Hepatic Insufficiency: The pharmacokinetics of daptomycin were evaluated in 10 adult subjects with moderate hepatic impairment (Child-Pugh Class B) and compared with healthy adult volunteers (N=9) matched for gender, age, and weight. The pharmacokinetics of daptomycin were not altered in subjects with moderate hepatic impairment. No dosage adjustment is warranted when administering Daptomycin for Injection to patients with mild to moderate hepatic impairment. The pharmacokinetics of daptomycin for injection in patients with severe hepatic insufficiency have not been evaluated.
Renal Impairment in Adult Complicated Skin and Skin Structure Infections (cSSSI): Population derived pharmacokinetic parameters were determined for adult patients with cSSSI and healthy non-infected adult subjects with varying degrees of renal function (N=282).
Following the administration of a single 4 mg/kg IV dose of daptomycin for injection, the plasma clearance (CLT) was reduced and the systemic exposure (AUC0-∞) was increased with decreasing renal function (see Table 18. The mean AUC0-∞ was not markedly different for subjects and patients with creatinine clearance (CLCR) 30-80 mL/min as compared to those with normal renal function (CLCR > 80 mL/min). The mean AUC0-∞ for subjects and patients with CLCR < 30 mL/min was approximately 2-times higher than that observed in individuals with normal renal function. For subjects on hemodialysis (dosed post-dialysis)/continuous ambulatory peritoneal dialysis, the mean AUC0-∞ was 3-times higher than that observed in individuals with normal renal function. The mean Cmax ranged from 59.6 to 69.6 µg/mL in subjects with CLCR ≥ 30 mL/min, while those with CLCR < 30 mL/min ranged from 41.1 to 57.7 µg/mL. In non-infected adult subjects undergoing dialysis, approximately 15% and 11% of the administered dose was removed by 4 hours of hemodialysis and 48 hours of continuous ambulatory peritoneal dialysis, respectively. In patients with renal impairment, both renal function and creatine phosphokinase (CPK) should be monitored more frequently. Daptomycin for Injection should be administered following the completion of hemodialysis on hemodialysis days (see DOSAGE AND ADMINISTRATION).
Table 18. Daptomycin Population Pharmacokinetic Parameters Following a Single 30- Minute IV Infusion of 4 mg/kg of Daptomycin to Adult Patients with Complicated Skin and Skin Structure Infections (cSSSI) and Healthy Volunteers with Varying Degrees of Renal Function
| Renal Function | N | Pharmacokinetic Parameters Mean (Standard Deviation) | ||||||||
AUC0-∞ (µg*h/mL) | t1/2 (h) | Vss (L/kg) | CLT (mL/h/kg) | |||||||
Normal (CLCR>80 mL/min) | 165 | 417 (155) | 9.39 (4.74) | 0.13 (0.05) | 10.9 (4.0) | |||||
Mild Renal Impairment (CLCR 50-80 mL/min) | 64 | 466 (177) | 10.75 (8.36) | 0.12 (0.05) | 9.9 (4.0) | |||||
| Moderate Renal Impairment (CLCR 30-<50 mL/min) | 24 | 560 (258) | 14.70 (10.50) | 0.15 (0.06) | 8.5 (3.4) | |||||
| Severe Renal Impairment (CLCR <30 mL/min) | 8 | 925 (467) | 27.83 (14.85) | 0.20 (0.15) | 5.9 (3.9) | |||||
| Hemodialysis and CAPD | 21 | 1244 (374) | 29.81 (6.13) | 0.15 (0.04) | 3.7 (1.9) | |||||
CLCR: creatinine clearance estimated using the Cockcroft-Gault equation with actual body weight; Vss: volume of distribution at steady-state; CAPD: continuous ambulatory peritoneal dialysis
Renal Impairment in the Adult Staphylococcus aureus bacteremia/Staphylococcus aureus infective endocarditis (SAB/SAIE) Trial: A second population analysis was conducted to determine pharmacokinetic parameters at steady-state in adult SAB/SAIE patients (Table 19). Patients (N=108) received 6 mg/kg q24h of daptomycin for injection and were stratified by varying degrees of renal function. Plasma clearance (CLT) decreased with decreasing renal function, whereas AUC and Cmin increased with decreasing renal function. Mean AUC increased 1.6-fold while mean Cmin increased 2.8-fold in patients with moderate renal impairment compared to those with CLCR > 80 mL/min. In the two patients with CLCR < 30 mL/min, pharmacokinetic parameters were similar to those with moderate renal impairment. Mean Cmax values ranged from 80 to 114 μg/mL in patients with moderate to mild renal impairment and were similar to those of normal subjects. In SAB/SAIE patients, the overall mean volume of distribution at steady-state (Vss) was 0.16 L/kg and was greater than that in non-infected subjects (0.1 L/kg), but similar to cSSSI patients. In non-infected adult subjects undergoing dialysis, approximately 15% and 11% of the administered dose was removed by 4 hours of hemodialysis (N=6) and 48 hours of continuous ambulatory peritoneal dialysis [CAPD (N=5)], respectively. In patients with renal impairment, both renal function and CPK should be monitored more frequently. Daptomycin for Injection should be administered following the completion of hemodialysis on hemodialysis days (see DOSAGE AND ADMINISTRATION).
Table 19. Daptomycin Population Pharmacokinetic Parameters at Steady-State in Adult SAB/SAIE Patients Dosed with 6 mg/kg of Daptomycin with Varying Degrees of Renal Function
| Renal Function | N | Pharmacokinetic Parameters Mean (Standard Deviation)1 | |||||||||
AUC0-24 [μg*h/mL] | t1/2 [h] | Vss [L/kg] | CLT [mL/h/kg] | Cmax [μg/mL] | Cmin [μg/mL] | ||||||
Normal CL 2 >80 L/min CR | 62 | 545 (296) | 9.0 (2.86) | 0.15 (0.07) | 13.2 (5.0) | 108 (143) | 6.9 (3.5) | ||||
Mild Impairment CLCR 50-80 mL/min | 29 | 637 (215) | 12.0 (2.26) | 0.17 (0.04) | 10.5 (3.5) | 80 (41) | 12.4 (5.6) | ||||
| Moderate Impairment CLCR 30-<50 mL/min | 15 | 868 (349) | 16.1 (3.62) | 0.17 (0.05) | 8.2 (3.6) | 114 (124) | 19.0 (9.0) |
Severe Impairment CLCR <30 mL/min | 2 | 1050, 892 | 25.8, 16.0 | 0.20, 0.15 | 5.7, 6.7 | 97, 83 | 25.4, 21.4 |
1 Mean (SD) values are presented except Severe Impairment where N=2;
2 Creatinine clearance was estimated using the Cockcroft-Gault equation with actual body weight.
A 41% reduction in daptomycin plasma concentration was achieved using high-flux dialysis membranes, and a 5 to 7% reduction was achieved using low-flux dialysis membranes.
Obesity: The pharmacokinetics of daptomycin were evaluated in 6 moderately obese [Body Mass Index (BMI) 25 to 39.9 kg/m2] and 6 extremely obese (BMI ≥ 40 kg/m2) adult subjects and controls matched for age, sex, and renal function. Following administration of a single 4 mg/kg IV dose of daptomycin for injection based on total body weight, the plasma clearance of daptomycin normalized to total body weight was approximately 15% lower in moderately obese adult subjects and 23% lower in extremely obese adult subjects compared with non-obese controls. The AUC0-∞ of daptomycin increased approximately 30% in moderately obese and 31% in extremely obese adult subjects compared with non-obese controls. In the adult complicated skin and skin structure infection trials (cSSSI), 8 adult patients > 150 kg received daptomycin 4 mg/kg. The highest total dose exposure occurred in one patient weighing 238.6 kg (total exposure 20 900 mg daptomycin over 21 days). No dosage adjustment of Daptomycin for Injection is warranted in obese patients based solely on weight.
STORAGE AND STABILITY
Store vials containing lyophilized powder at 2 to 8ºC.
Chemical and physical in-use stability of the reconstituted solution in the vial, or infusion solutions, has been demonstrated for 12 hours at 25°C and up to 10 days if stored under refrigeration (2 to 8°C), under normal lighting conditions. However, because Daptomycin for Injection does not contain any preservative or bacteriostatic agent, aseptic technique must be used during preparation for administration and the product should be used promptly. If the reconstituted product is not used immediately, it must be refrigerated at 2 to 8°C. It is recommended that the solution be used within 72 hours due to the possibility of microbial contamination during reconstitution. Avoid excessive heat.
The combined time (vial and infusion bag) at room temperature, up to 25°C, should not exceed 12 hours. The combined time (vial and infusion bag) at 2-8°C should not exceed 10 days.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Daptomycin for Injection is supplied as a pale yellow to light brown lyophilized cake or powder, free from foreign material in 15 mL tubular vial (500 mg / 15 mL) with a rubber stopper and sealed
with an aluminium flip off seal. Available in packages of 10 vials. Daptomycin for Injection may also contain sodium hydroxide used to adjust pH in trace amounts.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: daptomycin
Chemical name: N-decanoyl-L-tryptophyl-D-asparaginyl-L-aspartyl-L-threonylglycyl-L- ornithyl-L-aspartyl-D-alanyl-L-aspartylglycyl-D-seryl-threo-3-methyl- L-glutamyl-3- anthraniloyl-L-alanine ε1-lactone
Molecular formula: C72H101N17O26
Molecular mass: 1620.67 g/mol
Structural formula:
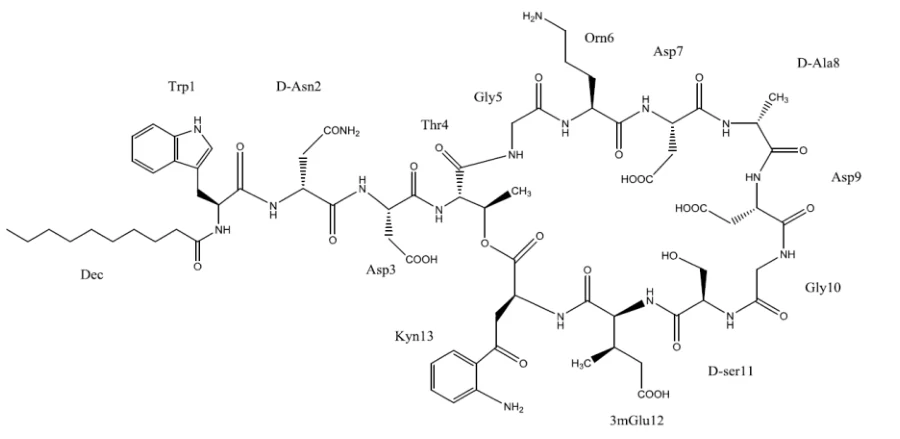
Table 20. Physicochemical properties
| Attribute | Description |
| Appearance | A homogeneous solid that is readily constituted into solution with 10mL of sodium chloride, and dispersion is completed with gentle agitation. |
Solubility (at 25°C) Water Acetonitrile Methanol Ethanol (95%) Acetone | 1000.81 mg/mL 0.105 mg/mL 35.164 mg/mL 0.944 mg/mL 0.099 mg/mL |
Partition Coefficient 1-octanol/water 1-octanol/tris-buffer, pH 7.4 | -1.32 -3.26 |
| pKa (aqueous) | 2.9, 3.5, 4.3, 4.7, 10.5 |
| Melting point | 215°C |
Specific Rotation (at 25°C) Water Methanol | +17.8° +11.2° |
CLINICAL TRIALS
Complicated Skin and Skin Structure Infections (cSSSI) in Adults
Study demographics and trial design
The patient demographics and basic trial design for the two pivotal adult cSSSI studies are summarized in Table 22. Adult patients were included for skin and skin structure infections complicated by factors implicating deeper soft tissue, significant surgical intervention, co- morbidities, hospitalization and/or other factors. The main diagnoses were wound infections, major abscesses and ulcer infections, 57% of which were considered severe in accordance with the SIRS rating scale. Children, pregnant or lactating women and, among others, patients such as those with bacteremia, pneumonia, osteomyelitis, primary muscle disorders or CPK > 50% Upper Limit Normal, third degree burns, shock/hypotension, and severe renal impairment (calculated creatinine clearance < 30 mL/min) were excluded. In the majority of patients with Gram-positive cSSSI, the infections were polymicrobial either due to Gram-positive bacteria, Gram-negative bacteria or anaerobes and 30% of patients received adjunctive surgery.
Microbiological analyses were restricted to Gram-positive organisms.
For purposes of the comparator arm, overall analyses, and the grouping of clinically similar patients, all patients were pre-randomized to either vancomycin or anti-staphylococcal semi- synthetic penicillins. Vancomycin was chosen in cases of known or suspected MRSA or patient intolerance to penicillins. The anti-staphylococcal semi-synthetic penicillin chosen was dependent upon availability and standard of care in the study country. All patients were then randomized 1:1 to either daptomycin or the comparator arm. Patients could be switched to oral therapies after a minimum of four days of IV treatment if clinical improvement was demonstrated and if a switch was required for other relevant reasons. Patients initially treated with penicillins could be switched to vancomycin if MRSA was cultured after randomization had occurred. Aztreonam and metronidazole could be concurrently administered for the treatment of Gram-negative and anaerobic bacteria respectively.
Overall, the daptomycin and comparator arms were comparable. In study 9801 the large majority of patients were from the US whereas in study 9901 the majority was from South Africa. In the former relative to the latter, study patients tended to be slightly older and included slightly more Caucasians, diabetics, surgical interventions, and vancomycin usage.
Table 21. Summary of Trial Design and Demographics
| Study Number (location) | Basic Design | Primary Efficacy Parameter | Antibiotic Treatments Compared (dose and duration) | Number of Patients Treated (ITT)* | Mean Age in Years (range) | Gender (%M/F) | Race (% caucasian/ black/other) |
|---|---|---|---|---|---|---|---|
DAP-SST-9801 (US and South Africa) | Multicentre,r andomized, parallel group, investigator blinded | Clinical outcome in MITT* and CE* patient populations with cSSSI 7-12 days after treatment cessation | Daptomycin (4mg/kg/q24h IV x 7-14 days) versus Comparator: vancomycin (1g q12h IV x 7- 14 days) or semi- synthetic | 264 266 | 55.2 (18-91) 55.5 (19-94) | 54.2/45.8 55.6/44.4 | 67.0/18.9/14.4 62.8/22.6/14.9 |
| Study Number (location) | Basic Design | Primary Efficacy Parameter | Antibiotic Treatments Compared (dose and duration) | Number of Patients Treated (ITT)* | Mean Age in Years (range) | Gender (%M/F) | Race (% caucasian/ black/other) |
|---|---|---|---|---|---|---|---|
| penicillins** (4-12 g/d IV in divided doses x 7-14 days) | |||||||
| DAP-SST- | Multicentre, | Clinical | Daptomycin | 270 | 47.9 | 55.6/44.4 | 50.4/35.2/14.4 |
| 9901 | randomized, parallel | outcome in MITT* and | (4mg/kg/q24h iv x7-14days) | (18-87) | |||
(South Africa, | group, investigator | CE* patient | versus | ||||
| Europe, Australia and Israel) | blinded | populations with cSSSI 7-12 days after treatment cessation | Comparator: vancomycin (1g q12h iv x 7- 14days) or semi- | 292 | 48.6 (17-85) | 54.8/45.2 | 50.0/31.2/18.8 |
| synthetic | |||||||
| penicillins*** | |||||||
| (4-12 g/d iv in | |||||||
| divided doses x | |||||||
| 7-14 days) | |||||||
* analytical subpopulations included: ITT: intent to treat population (patients with cSSSI who received at least one dose); MITT: modified intent to treat population (ITT patients with proved Gram-positive bacterial cSSSI at baseline); CE: clinically evaluable population (all ITT patients in whom clinical outcome could be inferred to reflect the effect of the study drug, met clinical criteria for study infection, received correct study drug as randomized for appropriate duration and intensity, had required clinical evaluations and did not receive confounding non-study medications); ME: microbiologically evaluable population (CE patients with a Gram-positive bacterium at baseline); about 82% of ITT patients met MITT criteria and 81% of ITT patients met CE criteria; 84% of CE patients met ME criteria for microbiological evaluability at Test of Cure visit
** anti-staphylococcal semi-synthetic penicillin: nafcicillin, cloxacillin or oxacillin
*** anti-staphylococcal penicillin: flucloxacillin, cloxacillin or oxacillin
Study results
Overall clinical efficacy results are provided in Tables 22 and 23 in terms of the sponsor-defined primary clinical efficacy parameters at the Test Of Cure visit (7-12 days after cessation of antibiotic treatment) for MITT and CE populations.
Table 22. Clinical efficacy outcome (MITT population)
| Clinical Response | DAP-SST-9801 | DAP-SST-9901 | Pooled Results | ||||||||||||
Daptomycin (N=215) n (%) | Comparatora (N=216) n (%) | Daptomycin (N=213) n (%) | Comparatora (N=255) n (%) | Daptomycin (N=428) n (%) | Comparatora (N=471) n (%) | ||||||||||
| Clinical Success | 140 (65.1) | 140 (64.8) | 179 (84.0) | 212 (83.1) | 319 (74.5) | 352 (74.7) | |||||||||
| Cure | 90 (41.9) | 84 (38.9) | 82 (38.5) | 109 (42.7) | 172 (40.2) | 193 (41.0) | |||||||||
| Clinical Improvement | 50 (23.3) | 56 (25.9) | 97 (45.5) | 103 (40.4) | 147 (34.3) | 159 (33.8) | |||||||||
| Clinical Failure | 75 (34.9) | 76 (35.2) | 34 (16.0) | 43 (16.9) | 109 (25.5) | 119 (25.3) | |||||||||
a Vancomycin or anti-staphylococcal semi-synthetic penicillins
Table 23. Clinical efficacy outcome (CE population)
| Clinical Response | DAP-SST-9801 | DAP-SST-9901 | Pooled Results | ||||||||||
| Daptomycin (N=208) n (%) | Comparatora (N=206) n (%) | Daptomycin (N=238) n (%) | Comparatora (N=250) n (%) | Daptomycin (N=446) n (%) | Comparatora (N=456) n (%) | ||||||||
| Clinical Success | 158 (76.0) | 158 (76.7) | 214 (89.9) | 226 (90.4) | 372 (83.4) | 384 (84.2) | |||||||
| Cure | 105 (50.5) | 96 (46.6) | 103 (43.3) | 117 (46.8) | 208 (46.6) | 213 (46.7) | |||||||
Clinical Improvement | 53 (25.5) | 62 (30.1) | 111(46.6) | 109 (43.6) | 164(36.8) | 171 (37.5) |
| Clinical Failure | 50 (24.0) | 48 (23.3) | 24 (10.1) | 24 (9.6) | 74 (16.6) | 72 (15.8) |
a Vancomycin or anti-staphylococcal semi-synthetic penicillins
The pooled clinical efficacy results, based on sponsor-defined clinical efficacy outcome parameters for the MITT population in studies DAP-SST-9801 and DAP-SST 9901, are provided in Table 24 in terms of infecting bacteria and patient pre-randomization to either anti- staphylococcal semi-synthetic penicillins or vancomycin. These two clinical groupings were based upon the likelihood of patients having MRSA or penicillin intolerance and the patients of both groupings received either daptomycin for injection or the appropriate comparator drug (vancomycin or an anti-staphylococcal semi-synthetic penicillin).
Table 24. Pooled clinical success rates by infecting pathogen and patient pre- randomization (MITT population)
| Pathogen | Pre-randomized to Semi-synthetic Penicillins | Pre-randomized to Vancomycin | |||||||||||||
| Drug Received | Drug Received | ||||||||||||||
Daptomycin n/N(%) | Semi-synthetic Penicillins n/N (%) | Daptomycin n/N (%) | Vancomycin n/N (%) | ||||||||||||
Staphylococcus aureus (MSSA) | 130/161 (80.7) | 128/160 (80.0) | 38/50 (76.0) | 56/79 (70.9) | |||||||||||
Staphylococcus aureus (MRSA) | 3/7 (42.9) | 6/9 (66.7) | 15/29 (51.7) | 20/38 (52.6) | |||||||||||
| Streptococcus pyogenes | 70/79 (88.6) | 74/88 (84.1) | 9/9 (100.0) | 8/15 (53.3) | |||||||||||
| Streptococcus agalactiae | 13/15 (86.7) | 15/27 (55.6) | 7/9 (77.8) | 7/14 (50.0) | |||||||||||
Similarly, the pooled microbiological efficacy results (eradication or presumed eradication in the ME population) for studies DAP–SST-9801 and DAP-SST 9901, are provided in Table 25.
Table 25. Pooled microbiological success rates (eradication or presumed eradication) by infecting pathogen and patient pre-randomization (ME population)
| Pathogen | Pre-randomization to Semi-synthetic Penicillins | Pre-randomization to Vancomycin | |||||||||||||
| Drug Received | Drug Received | ||||||||||||||
Daptomycin n/N (%) | Semi-synthetic penicillins n/N (%) | Daptomycin n/N (%) | Vancomycin n/N (%) | ||||||||||||
Staphylococcus aureus (MSSA) | 108/144 (75.0) | 108/139 (77.7) | 31/41 (75.6) | 49/68 (72.1) | |||||||||||
Staphylococcus aureus (MRSA) | 2/4 (50.0) | 3/6 (50.0) | 12/21 (57.1) | 18/30 (60.0) | |||||||||||
| Streptococcus pyogenes | 66/72 (91.7) | 65/79 (82.3) | 9/9 (100.0) | 7/9 (77.8) | |||||||||||
| Streptococcus agalactiae | 12/14 (85.7) | 12/18 (66.7) | 6/7 (85.7) | 7/11 (63.6) | |||||||||||
Complicated Skin and Skin Structure Infections (cSSSI) in Pediatric Patients (1 to 17 years of Age)
The cSSSI pediatric trial was a single prospective multi-center, randomized, comparative trial. A total of 396 pediatric patients aged 1 to 17 years with cSSSI caused by Gram-positive pathogens were enrolled into the study. Patients known to have bacteremia, osteomyelitis, endocarditis, and pneumonia at baseline were excluded. Patients were enrolled in a stepwise approach into four age groups and given age-dependent doses of daptomycin for injection once daily for up to 14 days. The different age groups and doses evaluated were as follows: Adolescents (12 to 17 years) treated with 5 mg/kg of daptomycin for injection (n=113), Children (7 to 11 years) treated with 7 mg/kg of daptomycin for injection (n=113), Children (2 to 6 years) treated with 9 mg/kg of daptomycin for injection (n=125) and Infants (1 to <2) treated with 10 mg/kg of daptomycin for injection (n=45).
Patients were randomized 2:1 to receive daptomycin for injection or a standard of care (SOC) comparator, which included intravenous therapy with either vancomycin, clindamycin, or an anti- staphylococcal semi-synthetic penicillin (nafcillin, oxacillin, or cloxacillin). Patients could switch to oral therapy after clinical improvement was demonstrated (no minimum IV dosing was required).
The primary objective of this study was to evaluate the safety of daptomycin for injection. The clinical outcome was determined by resolution or improvement of symptoms at the End-of-Treatment (EOT), 3 days after the last dose, and at Test-of-Cure (TOC), 7 – 14 days after the last dose. Investigator observed outcomes were verified in blinded fashion. Of the 396 subjects randomized in the study, 389 subjects were treated with daptomycin for injection or comparator and included in the ITT population. Of these, 257 subjects were randomized to the daptomycin for injection group and 132 subjects were randomized to the comparator group. Approximately 95% of subjects switched to oral therapy. The mean day of switch was day 4, and ranged from day 1 to day 14. The clinical success rates determined at 7 – 14 days after last dose of therapy (IV and oral) (TOC visit) were 88% (227/257) for daptomycin for injection and 86% (114/132) for comparator.
Staphylococcus aureus Bacteremia/Staphylococcus aureus Infective Endocarditis (SAB/SAIE) Trial in Adults
Study Demographics and Trial Design
The trial design and patient demographics for the adult Staphylococcus aureus bacteremia/ Staphylococcus aureus infective endocarditis (SAB/SAIE) trial are summarized in Table 27 and Table 28.
Adult patients ≥ 18 years of age with clinically documented Staphylococcus aureus bacteremia determined by at least one positive blood culture for Staphylococcus aureus obtained within 2 calendar days prior to the first dose of study drug and irrespective of source were enrolled. The major exclusion criteria were patients with a prosthetic heart valve, cardiac decompensation and/or valve damage, shock or hypotension, severe renal disease, increased AST or ALT, severe neutropenia, or known osteomyelitis. Patients who developed osteomyelitis during treatment were permitted to remain on study. In addition, patients with meningitis, pneumonia, polymicrobial bloodstream infections or with intravascular foreign material not planned for removal within 4 days of dosing (except vascular stents in place > 6 months or permanent pacemakers) were not to be enrolled.
Baseline characteristics in the Intent-to-Treat (ITT) population were well balanced between the two treatment arms. Patients were generally seriously ill and included the elderly, those with systemic inflammatory response syndrome (SIRS), diabetes mellitus, injection drug use, extravascular foreign materials, intravascular foreign materials, percutaneous intravascular devices, presence of a catheter at first positive culture, prior endocarditis, pre-existing valvular heart disease, abnormal chest x-ray, HIV positive, prior endocarditis and surgery, infection and/or trauma within 30 days of onset of the Staphylococcus aureus bacteremia. Eighty-nine patients (38%) had bacteremia caused by methicillin-resistant Staphylococcus aureus (MRSA).
Vancomycin was used if the patient had methicillin-resistant Staphylococcus aureus. Vancomycin was used unless or until susceptibility results proved to be methicillin-susceptible whereupon therapy was changed to an anti-staphylococcal semi-synthetic penicillin (SSP) unless contraindicated. The choice of anti-staphylococcal semi-synthetic penicillin was based on the standard therapy in each country.
Table 26. Trial design in the pivotal SAB/SAIE Study
| Study Number/ Country | Design | Primary Efficacy Parameter | Treatment Regimen | Number of Patients Treated |
DAP-IE-01-02 United States (40 sites) Europe (8 sites) | Multi-centre, randomized, open- label, comparative (non-inferiority) | Co-primary composite efficacy endpoint was clinical and microbiological success at test-of- cure visit (6 weeks after last treatment dose), based on an Independent External Adjudication Committee outcome, in the ITT and PP populations* | Dose Daptomycin (6 mg/kg IV q24h) versus vancomycin† (1 g IV q12h) or semi-synthetic penicillin** (2 g IV q4h) Gentamicin† (1 mg/kg IV q8h): given to all patients in comparator group and those with left-sided infective endocarditis in daptomycin group for the first 4 days (or until blood cultures were negative for 48 hours) Duration 10-42 days with an option to extend for 14 days. The duration of treatment was to be based on the patient’s diagnosis as determined by the Investigator and the susceptibility of the S. aureus isolate. | 120 115 |
* ITT population included all patients who were randomized and received at least one dose of study medication; PP population included those in the ITT population with documented adherence to the protocol
** Anti-staphylococcal semi-synthetic penicillins included nafcillin, oxacillin, cloxacillin or flucloxacillin based on standard therapy in each country
† Vancomycin and gentamicin were to be adjusted based on renal function and plasma level according to Investigator’s standard practice and manufacturer’s guidelines
Table 27. Summary of Demographic Characteristics for the SAB/SAIE Study (ITT Population)
| Characteristic | Daptomycin (N=120) | Comparator (N=115) | Total (N=235) |
| Median Age (years) (range) | 50.5 (21, 87) | 55.0 (25, 91) | 53.0 (21, 91) |
Age, years [N (%)] ≥65 ≥75a | 30 (25.0%) 19 (15.8%) | 37 (32.2%) 15 (13.0%) | 67 (28.5%) 34 (14.5%) |
| Gender, N (%) Male | 70 (58.3%) | 71 (61.7%) | 141 (60.0%) |
| Female | 50 (41.7%) | 44 (38.3%) | 94 (40.0%) |
| Race, N (%) Caucasian | 75 (62.5%) | 81 (70.4%) | 156 (66.4%) |
| BMI, kg/m2 Median (range) | 26.90 (17.6, 49.7) | 25.67 (17.0, 44.0) | 26.47 (17.0, 49.7) |
| CLcr, mL/minb, Median (range) | 86.44 (28.0, 246.9) | 83.61 (17.9, 277.0) | 84.56 (17.9, 277.0) |
| CLcr, N (%) <50 mL/minb | 19 (15.8%) | 22 (19.1%) | 41 (17.4%) |
a Age category ≥75 years is a subset of the category ≥65 years.
b Calculated by the Sponsor using the Cockcroft-Gault equation.
Upon entry, adult patients were classified for likelihood of endocarditis using the modified Duke criteria (Possible, Definite, or Not Endocarditis). Echocardiography, including transesophageal echocardiogram (TEE), was performed within 5 days following study enrollment. Final diagnoses and outcome assessments at Test of Cure were made by a treatment-blinded Independent External Adjudication Committee (IEAC), using protocol-specified clinical definitions.
Of the 37 patients with an entry diagnosis of Definite Endocarditis, all (100%) had a final diagnosis of infective endocarditis; of the 144 patients with an entry diagnosis of Possible Endocarditis, 15 (10%) had a final diagnosis of infective endocarditis; and, of the 54 patients with an entry diagnosis of Not Endocarditis, 1 (2%) had a final diagnosis of infective endocarditis. There were 182 patients with bacteremia including 121 with complicated and 61 with uncomplicated Staphylococcus aureus bacteremia; and, there were 53 patients with infective endocarditis, including 35 with right-sided and 18 with left-sided endocarditis.
A summary of the entry and final diagnostic subgroups (defined below) in the ITT population are presented in Table 28.
Complicated bacteremia was defined as Staphylococcus aureus isolated from blood cultures obtained on at least 2 different calendar days, and/or metastatic foci of infection (deep tissue involvement), and classification of the patient as not having endocarditis according to the modified Duke criteria.
Uncomplicated bacteremia was defined as Staphylococcus aureus isolated from blood culture(s) obtained on a single calendar day, no metastatic foci of infection, no infection of prosthetic material, and classification of the patient as not having endocarditis according to the modified Duke criteria.
Right-sided infective endocarditis (RIE) was definite or possible endocarditis according to the modified Duke criteria and no echocardiographic evidence of predisposing pathology or active involvement of either the mitral or aortic valve. Patients with a final diagnosis of RIE based on these criteria were further classified as either complicated or uncomplicated RIE as described below:
Complicated RIE included patients who met any of the following criteria: were not intravenous drug users; had a positive blood culture for MRSA; had a serum creatinine ≥2.5 mg/dL; or had evidence of extrapulmonary sites of infection.
Uncomplicated RIE included patients who met all of the following criteria: were intravenous drug users; had a positive blood culture for MSSA; had a serum creatinine <2.5 mg/dL; and were without evidence of extrapulmonary sites of infection.
Left-sided infective endocarditis (LIE) was definite or possible endocarditis according to modified Duke criteria and echocardiographic evidence of involvement or predisposing pathology of the mitral or aortic valve.
Table 28. Summary of Entry and Final Diagnostic Subgroups in the SAB/SAIE Trial (ITT Population)
| Diagnostic Subgroup | Daptomycin (N=120) | Comparator (N=115) | Total (N=235) |
IEAC Entry Diagnostic Subgroup [N (%)] N Definite IE Possible IE Not IE | 120 17 (14.2%) 73 (60.8%) 30 (25.0%) | 115 20 (17.4%) 71 (61.7%) 24 (20.9%) | 235 37 (15.7%) 144 (61.3%) 54 (23.0%) |
IEAC Final Diagnostic Subgroup [N (%)] N Complicated RIE Uncomplicated RIE Complicated bacteremia Uncomplicated bacteremia LIE | 120 13 (10.8%) 6 (5.0%) 60 (50.0%) 32 (26.7%) 9 (7.5%) | 115 12 (10.4%) 4 (3.5%) 61 (53.0%) 29 (25.2%) 9 (7.8%) | 235 25 (10.6%) 10 (4.3%) 121 (51.5%) 61 (26.0%) 18 (7.7%) |
Study Results
The overall success rates at Test of Cure in the ITT population were 44.2% (53/120) in patients treated with daptomycin for injection and 41.7% (48/115) in patients treated with comparator [95% CI 2.4% (-10.2, 15.1)]. The success rates at Test of Cure in the Per Protocol Population were 54.4% (43/79) in patients treated with daptomycin for injection and 53.3% (32/60) with comparator [95% CI 1.1% (-15.6, 17.8)].
The success rates in the ITT population are shown in Table 29.
Table 29. Success Rates* at Test of Cure in the pivotal SAB/SAIE Trial (ITT Population)
| Population | Daptomycin 6 mg/kg n/N (%) | Comparatora n/N (%) | Difference: Daptomycin − Comparator (Confidence Interval) |
| Overall | 53/120 (44.2%) | 48/115 (41.7%) | 2.4% (−10.2, 15.1)c |
Baseline Pathogen MSSA MRSA | 33/74 (44.6%) 20/45 (44.4%) | 34/70 (48.6%) 14/44 (31.8%) | −4.0% (−22.6, 14.6)d 12.6% (−10.2, 35.5) d |
Entry Diagnosisb Definite or Possible Infective Endocarditis Not Infective Endocarditis | 41/90 (45.6%) 12/30 (40.0%) | 37/91 (40.7%) 11/24 (45.8%) | 4.9% (−11.6, 21.4) d −5.8% (−36.2, 24.5)d |
Final Diagnosisf Complicated Bacteremia Uncomplicated Bacteremia Right-Sided Infective Endocarditis (RIE) Complicated RIE Uncomplicated RIE Left-Sided Infective Endocarditis | 26/60 (43.3%) 18/32 (56.3%) 8/19 (42.1%) 5/13 (38.5%) 3/6 (50.0%) 1/9 (11.1%) | 23/61 (37.7%) 16/29 (55.2%) 7/16 (43.8%) 6/12 (50.0%) 1/4 (25.0%) 2/9 (22.2%) | 5.6% (−17.3, 28.6) e 1.1% (−31.7, 33.9)e −1.6% (−44.9, 41.6) e −11.5% (−62.4, 39.4) e 25.0% (−51.6, 100.0) e −11.1% (−55.9, 33.6) e |
* Success: if patient was judged as cured or improved by IEAC, had a negative blood culture, did not receive potentially effective non-study antibiotic that could have altered outcome, and received at least the minimum amount of study medication
a Comparator: vancomycin (1 g IV q12h) or anti-staphylococcal semi-synthetic penicillin (i.e., nafcillin, oxacillin, cloxacillin, flucloxacillin; 2 g IV q4h), each with initial low-dose gentamicin According to the modified Duke criteria
b According to the modified Duke criteria
c 95% Confidence Interval
d 97.5% Confidence Interval (adjusted for multiplicity)
e 99% Confidence Interval (adjusted for multiplicity)
f See definitions above.
Table 30 presents a summary of success rates at Test of Cure by duration of study treatment in the ITT population. Across all patients in the ITT population, success rates increased with increasing duration of treatment in both the daptomycin for injection and comparator groups.
Table 30. Summary of Success Rates at Test of Cure in the SAB/SAIE Trial by Duration of Treatment and Final Diagnosis (ITT Population)
| Group | Daptomycin 6 mg/kg q24h n/N (%) | Comparator n/N (%) | ||||||||||||||
1-14 days | 15-28 days | 29-42 days | >42 days | 1-14 days | 15-28 days | 29-42 days | >42 days | |||||||||
| Overall ITT | 29/77 (37.7%) | 15/29 (51.7%) | 7/11 (63.6%) | 2/3 (66.7%) | 14/52 (26.9%) | 21/41 (51.2%) | 11/18 (61.1%) | 2/4 (50.0%) | ||||||||
| Complicated bacteremia | 14/36 (38.9%) | 6/14 (42.9%) | 4/7 (57.1%) | 2/3 (66.7%) | 5/30 (16.7%) | 10/18 (55.6%) | 7/11 (63.6%) | 1/2 (50.0%) | ||||||||
Uncomplicated bacteremia | 12/25 (48.0%) | 6/7 (85.7%) | 0/0 (0%) | 0/0 (0%) | 9/16 (56.2%) | 5/11 (45.5%) | 1/1 (100%) | 1/1 (100%) |
Right-sided endocarditis | 3/9 (33.3%) | 3/7 (42.9%) | 2/3 (66.7%) | 0/0 (0%) | 0/4 (0%) | 4/6 (66.7%) | 3/5 (60.0%) | 0/1 (0%) |
| Left-sided endocarditis | 0/7 (0%) | 0/1 (0%) | 1/1 (100%) | 0/0 (0%) | 0/2 (0%) | 2/6 (33.3%) | 0/1 (0%) | 0/0 (0%) |
Note: anti-staphylococcal semi-synthetic penicillin (SSP) included nafcillin, oxacillin, cloxacillin, and flucloxacillin.
In the overall ITT population, there was no statistically significant difference in time to clearance of Staphylococcus aureus bacteremia between daptomycin for injection and comparator. The median time to clearance in patients with MSSA was 4 days and in patients with MRSA was 8 days.
Failure of treatment due to persisting or relapsing Staphylococcus aureus infections was assessed in 19/120 (15.8%) adult daptomycin for injection-treated patients (12 with MRSA and 7 with MSSA) and 11/115 (9.6%) comparator-treated patients (9 with MRSA treated with vancomycin and 2 with MSSA treated with anti-staphylococcal semi-synthetic penicillin). Among all failures, 6 daptomycin for injection-treated patients and 1 vancomycin-treated patient developed increasing MICs (reduced susceptibility on or following therapy). Most patients who failed due to persisting or relapsing Staphylococcus aureus infection had deep-seated infection and did not receive necessary surgical intervention (see WARNINGS AND PRECAUTIONS).
Staphylococcus aureus Bacteremia (SAB) Trial in Pediatric Patients (1 to 17 years of Age)
The pediatric S. aureus bacteremia study was designed as a prospective multi-center, randomized comparative trial to treat pediatric patients aged 1 to 17 years with bacteremia. Patients known to have endocarditis or pneumonia at baseline were excluded. Patients were enrolled in a stepwise approach into three age groups and given age-dependent doses of daptomycin for injection once daily for up to 42 days. The different age groups and doses evaluated were as follows: Adolescents (12 to 17 years) treated with daptomycin for injection dosed at 7 mg/kg (n=14) once daily, Children (7 to 11 years) treated with daptomycin for injection dosed at 9 mg/kg once daily (n=19) and Children (2 to 6 years) treated with daptomycin for injection dosed at 12 mg/kg once daily (n=22). No patients 1 to <2 years were enrolled.
Patients were randomized 2 :1 to receive daptomycin for injection or a standard of care comparator, which included intravenous therapy with vancomycin, semi-synthetic penicillin, first generation cephalosporin or clindamycin. Patients could switch to oral therapy after clinical improvement was demonstrated (no minimum IV dosing was required).
The primary objective of this study was to assess the safety of daptomycin for injection. The clinical outcome was determined by resolution or improvement of symptoms at the Test-of-Cure (TOC) visit, 7 to 14 days after the last dose, which was assessed by the site level Blinded Evaluator.
Of the 82 subjects randomized in the study, 81 subjects were treated with daptomycin for injection or comparator and included in the safety population, and 73 had a proven S. aureus bacteremia at Baseline. Of these, 51 subjects were randomized to the daptomycin for injection group and 22 subjects were randomized to the comparator group. The mean duration of IV therapy was 12 days, with a range of 1 to 44 days. Forty-eight subjects switched to oral therapy, and the mean duration of oral therapy was 21 days. The clinical success rates determined at 7 to
14 days after last dose of therapy (IV and oral) (TOC visit) were 88% (45/51) for daptomycin for injection and 77% (17/22) for comparator.
DETAILED PHARMACOLOGY
Animal Pharmacology
Adult Animals
In animals, daptomycin administration has been associated with effects on skeletal muscle with no changes in cardiac or smooth muscle. Skeletal muscle effects were characterized by degenerative/regenerative changes and variable elevations in creatine phosphokinase (CPK). No fibrosis or rhabdomyolysis was evident in repeat dose studies up to the highest doses tested in rats (150 mg/kg/day IV) and dogs (100 mg/kg/day IV). The degree of skeletal myopathy showed no increase when treatment was extended from 1 month to up to 6 months. Severity was dose dependent. All muscle effects, including microscopic changes, were fully reversible within 30 days following cessation of dosing.
In adult animals, effects on peripheral nerve (characterized by axonal degeneration and frequently accompanied by significant losses of patellar reflex, gag reflex and pain perception) were observed at doses higher than those associated with skeletal myopathy. Deficits in the dogs' patellar reflexes were seen within 2 weeks of the start of treatment at 40 mg/kg IV (9 times the human Cmax at the 6 mg/kg IV q24h dose), with some clinical improvement noted within 2 weeks of the cessation of dosing. However, at 75 mg/kg/day IV for 1 month, 7/8 dogs failed to regain full patellar reflex responses within the duration of a 3-month recovery period. In a separate study in dogs receiving doses of 75 and 100 mg/kg/day IV for 2 weeks, minimal residual histological changes were noted at 6 months after cessation of dosing. However, recovery of peripheral nerve function was evident.
Acute IV administration of daptomycin to male mice was associated with dose-related effects on the central nervous system that were minimal at dose levels below 100 mg/kg but significant at 200 mg/kg. These effects included decreased motor activity, leg weakness, tremors, grasping loss, decreased abdominal tone, piloerection, decreased frequency of acetic acid-induced writhing, and increased hexobarbital-induced sleep time. Animal model studies have demonstrated that there is an increased penetration of daptomycin into the cerebrospinal fluid through inflamed meninges.
Daptomycin has been shown to penetrate into rabbit meninges (non-inflamed, 2%; inflamed 6%).
In another study of general pharmacological properties at doses up to 150 mg/kg IV, daptomycin caused no changes in gross behavior of rats at 15 mg/kg. Slight hypoactivity and abnormal posture were observed at 50 mg/kg. At 150 mg/kg, changes included hypoactivity, abnormal posture and gait, ptosis, decreased limb tone, increased defecation, and decreased food consumption and body weight. Most effects were transient and reversed within 24 hours post- dose. After pre-treatment at this dose, daptomycin also potentiated thiopental-Na anesthesia by 4 to 8-fold and inhibited motor coordination.
Tissue distribution studies in rats have shown that daptomycin is retained in the kidney.
The effect of concurrent administration of daptomycin and simvastatin on skeletal muscle was studied in a repeat dose study in CD rats. A total of four groups of male rats (15 rats per group) were treated as follows: Group 1: vehicle, days 0-27; Group 2: daptomycin 20 mg/kg/day IV, days 14-27; Group 3: Simvastatin 10 mg/kg/day Oral, days 0-27; and Group 4: Simvastatin 10 mg/kg/day Oral, days 0-27 and daptomycin 20mg/kg/day IV, days 14-27. Blood for serum chemistry was obtained on days 13 (prior to the initiation of daptomycin treatment) and 27.
Following 14 days of treatment with 10 mg/kg/day of simvastatin in combination with 20 mg/kg/day of daptomycin, a slight, statistically significant increase was detected in the levels of aspartate aminotransferase but not creatine phosphokinase (Table 32). However, it is noteworthy that following thirteen days of treatment with simvastatin alone (prior to the administration of daptomycin), slight, statistically significant elevations in mean serum levels of creatine phosphokinase and aspartate aminotransferase were detected in Group 4 animals as compared to Group 3 animals (see Table 32). Because the magnitude of the difference in CPK and AST between Group 4 and Group 3 (10/20 and 10/0 mg/kg/day simvastatin/daptomycin, respectively) on day 27 (1.4 and 1.4-fold respectively) was comparable to that noted on day 13, the difference is most likely related to the pre-existing (day 13) elevation and not due to the addition of daptomycin administration to simvastatin.
The microscopic examination of skeletal muscle at the end of study revealed minimal degenerative and/or regenerative changes in animals from all groups. Although the incidence was slightly higher for daptomycin (with or without simvastatin) as compared to vehicle or simvastatin alone treated groups, there was no increase in the incidence or severity of muscle effects in the daptomycin alone group as compared to daptomycin in combination with simvastatin.
Together, these data support the conclusion that no effect of drug interaction on skeletal muscle was observed upon co-administration of daptomycin and simvastatin to rats at clinically relevant doses.
Table 31. Summary of Creatine Phosphokinase (CPK) and Aspartate Aminotransferase (AST) Levels in Rats Following Administration of Oral Simvastatin With and Without Intravenous Daptomycin
| Daily Dosea | Control Vehicle + Vehicle Group 1 | Daptomycin 20mg/kg/day + Vehicle Group 2 | Simvastatin 10 mg/kg/day +Vehicle Group 3 | Simvastatin 10mg/kg/day + Daptomycin 20 mg/kg/day Group 4 |
CPK (IU/L) Day 13b | 331.4 | 435.7 | 352.5 | 590.2c |
| Day 27 | 509.1(54%)e | 568.5 (30%)e | 777.0 (121%)e | 1083 (84%)e |
AST (U/L) Day 13 b | 99.2 | 99.3 | 97.7 | 121.7d |
| Day 27 | 104.5 (5%)e | 107.1 (8%)e | 121.3 (24%)e | 169.5d (39%)e |
a Dose administration of simvastatin was initiated 14 days prior to addition of daptomycin treatment. Simvastatin was administered from Treatment Days 0 to 27; Daptomycin was administered from Treatment Days 14-27.
b Values for Day 13 preceded initiation of daptomycin treatment.
c Significantly different from Groups 1 and 3 but not Group 2 by Duncan’s test (p<0.05)
d Significantly different from Groups 1, 2 and 3 by Duncan’s test (p<0.05)
e Numbers in parentheses represent the percentage increase in CPK or AST values from Day 13 to 27
The effect of concurrent administration of daptomycin and tobramycin with respect to nephrotoxicity and neuromuscular toxicity was studied in rats. Daptomycin dose levels were 1, 5, and 20 mg/kg IV q24h. The tobramycin dose was 10 mg/kg SC b.i.d. Tobramycin treatment alone was associated with mild nephropathy. In comparison to the control group, absolute and relative kidney weights were increased in all groups receiving tobramycin. In addition, an increased incidence and severity of cortical tubular regeneration was observed in all tobramycin- treated groups. Concurrent administration of daptomycin had no effect on the tobramycin- induced nephropathy. Mild skeletal muscle degeneration and/or regeneration were observed in the high dose daptomycin group when given alone. When daptomycin was administered concurrently with tobramycin, skeletal muscle degeneration and/or regeneration were observed at dose levels of daptomycin ≥ 5 mg/kg. An increase in the incidence of the muscle damage in relation to tobramycin dose suggests that daptomycin-induced myopathy may be potentiated by co-administration of tobramycin. This increase is most likely related to the nephrotoxic effects of tobramycin, which may have resulted in reduced renal clearance of daptomycin and higher systemic exposure. No microscopic damage to the sciatic nerve was apparent.
The effect of concurrent administration of daptomycin and gentamicin with respect to nephrotoxicity was investigated in dogs. Gentamicin dose levels were 9 or 30 mg/kg/day IM (3 or 10 mg/kg q8h). The daptomycin dose was 30 mg/kg/day IV (10 mg/kg.q8h). When daptomycin was administered with high dose gentamicin, blood urea nitrogen and creatinine levels were 2-fold greater and potassium levels were slightly decreased (approximately 17%) as compared to the values observed with gentamicin alone. High dose gentamicin alone produced slight to minimal renal tubular necrosis and tubular epithelial regeneration. In animals receiving high dose gentamicin in combination with daptomycin, the severity of these lesions was graded as minimal to moderate. Thus, when a high dose of gentamicin was given in combination with daptomycin, the severity of the nephrotoxic lesions was increased and changes in clinical chemistry parameters indicative of renal effects were observed. In contrast, the administration of daptomycin with a low dose of gentamicin did not produce a functionally meaningful difference in the severity of nephrotoxicity. Daptomycin, given alone at 30 mg/kg/day did not induce nephrotoxicity.
Juvenile Animals
Target organs of daptomycin-related effects in 7-week-old juvenile dogs were skeletal muscle and nerve, the same target organs as in adult dogs. In juvenile dogs, nerve effects were noted at lower daptomycin blood concentrations than in adult dogs following 28 days of dosing. In contrast to adult dogs, juvenile dogs showed evidence of effects in nerves of the spinal cord as well as peripheral nerves after 28 days of dosing. No nerve effects were noted in juvenile dogs following 14 days of dosing at doses up to 75 mg/kg/day.
Administration of daptomycin to 7-week-old juvenile dogs for 28 days at doses of 50 mg/kg/day produced minimal degenerative effects on the peripheral nerve and spinal cord in several animals. A dose of 150 mg/kg/day for 28 days produced minimal degeneration in the peripheral nerve and spinal cord as well as minimal to mild degeneration of the skeletal muscle in a majority of animals, accompanied by slight to severe muscle weakness evident in most dogs. Following a 28-day recovery phase, microscopic examination revealed apparent recovery of the skeletal muscle and the ulnar nerve effects, but nerve degeneration in the sciatic nerve and spinal cord was still observed in all 150 mg/kg/day dogs (see TOXICOLOGY).
Following once-daily administration of daptomycin to juvenile dogs for 28 days, microscopic effects in nerve tissue were noted at a Cmax value of 417 µg/mL, which is approximately 3-fold less than the Cmax value associated with nerve effects in adult dogs treated once daily with daptomycin for 28 days (1308 µg/mL).
Neonatal Animals
Administration of daptomycin to postnatal day (PND) 4 neonatal dogs at 50 and 75 mg/kg/day
(Cmax and AUCinf values of ≥321 μg/mL and ≥1470 μg•h/mL, respectively) produced marked clinical signs of twitching, muscle rigidity in the limbs, impaired use of limbs, and a decrease in body weights and overall body condition necessitating early discontinuation by PND 19. A dose of 25 mg/kg/day from PND 4 to PND 31 (Cmax and AUCinf values of 147 μg/mL and 717 μg•h/mL, respectively) produced mild reversible clinical signs of twitching and one incidence of muscle rigidity with no effects on body weight. No histopathological effect related to daptomycin was observed (including peripheral and central nervous system and skeletal muscle) at any dose. No effects were observed in dogs administered daptomycin at 10 mg/kg/day, the NOAEL, following 28 days of treatment with associated Cmax and AUCinf values of 62 μg/mL and 247 μg•h/mL, respectively.
Human Pharmacology
Pharmacodynamics
In a placebo-controlled study in healthy adult volunteers, there was no evidence that exposure to daptomycin for injection at 6 mg/kg IV q24h x 14d caused any meaningful changes in cardiac repolarization as measured by QTcB. In nerve motor function studies in adults, daptomycin for injection administration did not cause any significant changes in the set of objective measures indicative of neuropathy or myopathy. Daptomycin for injection administration was associated with a significant increase in the number of affirmative responses to the neurological questionnaire designed to assess symptoms and deficits associated with small fiber sensory function. During the 14-day follow-up period more subjects in the daptomycin for injection group (8) compared to the normal saline group (5) reported symptoms of tingling, numbness and weakness.
In an ascending dose study in adults, daptomycin for injection was well-tolerated at doses up to 12 mg/kg for up to 14 days. No significant adverse effects, including effects on skeletal muscle and peripheral nerves, were observed during the study period in any dose group.
Pharmacokinetics
The pharmacokinetic profile of daptomycin for injection in humans is highly predictable following intravenous administration. Single and multiple doses of daptomycin for injection, up to 12 mg/kg/day for up to 14 consecutive days have been studied in healthy adult subjects (see Table 16, ACTION AND CLINICAL PHARMACOLOGY).
The pharmacokinetics and concentrations of daptomycin in cantharides-induced skin blisters and in plasma were determined over a 24-hour period following a single IV infusion of 4 mg/kg of daptomycin for injection in healthy adult volunteers. Daptomycin penetrated the inflammatory exudate moderately rapidly, with mean 1- and 2- hour concentrations of 9.4 µg/mL and 14.5 µg/mL, respectively. Tmax in the inflammatory fluid occurred approximately 3 hours later than in plasma (3.7 hours vs. 0.5 hours) with a Cmax of 27.6 µg/mL. The mean Cmax in the plasma was 77.5 µg/mL. The elimination half-life of daptomycin from the inflammatory exudate was highly variable, ranging from 6.3 hours to 30.9 hours, with a mean of 17.3 hours. The mean AUC0-24h in the inflammatory exudate was 318.2 µg⋅hr/mL. Mean plasma elimination half-life was 7.74 hours with mean plasma AUC0-24h of 468.0 µg⋅hr/mL, representing approximately 88% of the mean AUC0-∞ (529.7 µg⋅hr/mL). The penetration of daptomycin into inflammatory exudate, calculated as AUC0-24h exudate/AUC0-24h plasma, was 68.4%.
A study was conducted to evaluate the pharmacokinetics of daptomycin over a period of 3 weeks in adult subjects with End Stage Renal Disease (ESRD) on hemodialysis three times weekly using both high-flux (Baxter CT190G) and low-flux (Fresenius F8) dialysis membranes.
daptomycin for injection was administered as an 8 mg/kg loading dose followed by 6 mg/kg 3 times per week.
The AUC values on Day 17 appear higher in the low-flux group at 2586 μg x h/mL compared with the high-flux group at 1716 μg x h/mL (Table 33). However, examination of the individual AUC’s of the 4 adult subjects in the low-flux group and 3 adult subjects in the high-flux group indicated that the low flux cohort’s AUCs were consistently higher across all time points than those of the subjects in the high-flux cohort. Thus, there was little evidence of excessive accumulation in the low flux group compared with the high flux group.
Due to high variability in daptomycin pharmacokinetics between adult subjects under hemodialysis using low-flux and high-flux membranes, no statistically significant differences were detectable. However, the pre- to post-dialysis decrease in daptomycin levels was greater on the high-flux membrane (41%) compared to the low-flux membrane (5 to 7%).
Table 32. Pharmacokinetic Parameters of Daptomycin Following Single (Day 1) and Repeat (3 times/week) Dosing of Daptomycin in Adult Subjects with ESRD
| Mem- brane Type | Day | N | Pharmacokinetic Parameters Mean (CV%) | |||||||||||
| Cmax (μg/mL) | Cmin (μg/mL) | AUCa (μg x h/mL) | T1/2 (h) | CL (mL/h/kg) | Vss L/kg | |||||||||
| Low- Flux | 1 | 6 | 91 (31) | -- | 1697 (33) | 38.5 (21.3) | 2.8 (40.7) | 0.14 (17.8) | ||||||
| 8 | 5 | 86 (33) | 17 (9) | 1916 (45) | 42.3 (26.9) | 3.5 (54.4) | 0.18 (28.3) | |||||||
| 17 | 4 | 103 (26) | 29 (11) | 2586 (35) | 55.9 (36.1) | 2.2 (35.4) | 0.16 (21.0) | |||||||
| High - Flux | 1 | 7 | 107 (39) | -- | 1945 (34) | 35.7 (11.3) | 2.8 (51.6) | 0.14 (54.2) | ||||||
| 8 | 6 | 81 (38) | 14 (6) | 1672 (36) | 38.1 (16.6) | 3.7 (50.0) | 0.19 (54.6) | |||||||
| 17 | 3 | 94 (17) | 22 (3) | 1716 (27) | 45.3 (37.8) | 3.6 (44.1) | 0.27 (85.1) | |||||||
Subjects received 8 mg/kg on Day 1, followed by 6 mg/kg 3 times per week.
a AUC (0-t): Area under the concentration versus time curve from 0 to end of dosing interval
MICROBIOLOGY
Daptomycin has clinical utility in the treatment of infections caused by aerobic Gram-positive bacteria only. Daptomycin inserts directly into the cytoplasmic membrane of both growing and stationary phase Gram-positive bacteria resulting in dissipation of the membrane potential and efflux of potassium ions, which causes inhibition of protein, DNA and RNA synthesis and bacterial cell death with negligible lysis. The antibacterial activity of daptomycin requires the presence of free calcium, therefore, the determination of in vitro susceptibility of bacteria to daptomycin requires that broth media be supplemented with physiological levels of free (ionized) calcium at a concentration of 50 μg/mL. Daptomycin retains activity against Gram-positive bacteria including methicillin-resistant Staphylococcus aureus (see INDICATIONS AND CLINICAL USE). Daptomycin is not active against Gram-negative bacteria.
Daptomycin exhibits rapid, concentration-dependent bactericidal activity against Gram-positive organisms in vitro. This has been demonstrated both by time-kill curves and by MBC/MIC ratios (minimum bactericidal concentration/minimum inhibitory concentration) using broth dilution methodology.
Daptomycin’s activity in vitro is inhibited in the presence of pulmonary surfactant. In mouse and hamster models of broncho-alveolar pneumonia (BAP), daptomycin lacked efficacy.
In vitro studies have investigated daptomycin interactions with other antibiotics. Antagonism, as determined by kill curve studies, has not been observed. In vitro synergistic interactions of daptomycin occurred with aminoglycosides, β-lactam antibiotics and rifampin against some isolates of staphylococci including some methicillin-resistant isolates.
Daptomycin has been shown to be active against most isolates of the following bacteria both in vitro and in clinical infections.
Table 33. Daptomycin MIC50 and MIC90 for Susceptible Aerobic and Facultative Gram- Positive Bacteria in vitro and in Clinical Infections
| Microorganism | # of clinical isolates | MIC (μg/mL) | ||
| MIC50 | MIC90 | Range | ||
| Staphylococcus aureus (including methicillin-resistant strains) | 3848 | 0.25 | 0.5 | <0.06 – 2 |
| Streptococcus agalactiae | 187 | 0.12 | 0.25 | <0.06 - 0.5 |
| Streptococcus pyogenes | 170 | <0.06 | <0.06 | <0.06 - 0.12 |
The following in vitro data are available (Table 34), but their clinical significance is unknown. Greater than 90% of the following microorganisms demonstrate an in vitro MIC less than or equal to the susceptible breakpoint for daptomycin versus the bacterial genus. The efficacy of daptomycin in treating clinical infections due to these bacteria has not been established in adequate and well-controlled clinical trials.
Table 34. Daptomycin MIC50 and MIC90 for Susceptible Aerobic and Facultative Gram- Positive Microorganisms in vitro
| Microorganism | # of clinical isolates | MIC (μg/mL) | ||
| MIC50 | MIC90 | Range | ||
| Corynebacterium jeikeium | 68 | 0.25 | 0.5 | 0.06 – 1 |
Enterococcus faecalis (vancomycin-resistant strains) | 34 | 0.5 | 2 | 0.25 – 2 |
Enterococcus faecalis (vancomycin-susceptible strains) | 917 | 0.5 | 1 | <0.06 - 4 |
| Enterococcus faecium (including vancomycin-resistant strains) | 398 | 2 | 4 | 0.25 - 4 |
| Staphylococcus epidermidis (including methicillin-resistant strains) | 164 | 0.5 | 0.5 | 0.12 - 1 |
| Staphylococcus haemolyticus | 102 | 0.25 | 0.5 | 0.03 - 1 |
| Streptococcus dysgalactiae subsp. equisimilis | 102 | <0.03 | 0.06 | <0.03 - 0.12 |
Resistance
At this time, no mechanism of resistance to daptomycin has been identified. There have been reports of Staphylococcus aureus isolates exhibiting decreased or intermediate vancomycin susceptibility demonstrating decreased daptomycin susceptibility.
Non-susceptible isolates of Staphylococcus aureus have been recovered from patients in clinical trials. These include one patient enrolled in a Phase 2 study, one who received daptomycin for injection in a compassionate use study, and seven from the SAB/SAIE trial.
Cases of daptomycin resistance have been reported in staphylococci during post-marketing.
Susceptibility Testing Methods
Susceptibility testing by dilution methods requires the use of daptomycin susceptibility powder. The testing also requires the presence of physiological levels of free calcium ions (50 μg/mL of calcium, using calcium chloride) in Mueller-Hinton broth.
Dilution Technique
Quantitative methods are used to determine antimicrobial MICs. These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure based on a broth dilution method or equivalent using standardized inoculum and concentrations of daptomycin. The use of the agar dilution method is not recommended with daptomycin. The MICs should be interpreted according to the criteria in Table 35.
Table 35. Susceptibility Interpretive Criteria for Daptomycin
| Pathogen | Broth Dilution MIC (μg/mL)a | ||
| S | I | R | |
Staphylococcus aureus (methicillin-susceptible and methicillin-resistant) | ≤ 1 | (b) | (b) |
| Streptococcus pyogenes and Streptococcus agalactiae | ≤ 1 | (b) | (b) |
a The MIC interpretive criteria for S. aureus are applicable only to tests performed by broth dilution using Mueller-Hinton broth adjusted to a calcium content of 50 μg/mL; the MIC interpretive criteria for Streptococcus spp. other than S. pneumoniae are applicable only to tests performed by broth dilution using Mueller-Hinton broth adjusted to a calcium content of 50 μg/mL, supplemented with 2 to 5% lysed horse blood, inoculated with a direct colony suspension and incubated in ambient air at 35ºC for 20 to 24 hours.
b Limited data on daptomycin resistant strains precludes defining any categories other than “Susceptible”. Strains yielding test results suggestive of a “Non-Susceptible” category should be retested, and if the result is confirmed, the isolate should be submitted to a reference laboratory for confirmation of results using CLSI reference broth microdilution method.
A report of “Susceptible” indicates that the pathogen is likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable.
Diffusion Technique
Quantitative methods that require measurements of zone diameters have not been shown to provide reproducible estimates of the susceptibility of bacteria to daptomycin. The use of a disk diffusion method is not recommended with daptomycin.
Quality Control
Standardized susceptibility test procedures require the use of quality control microorganisms to control the technical aspects of the procedures. Standard daptomycin powder should provide the range of values noted in Table 37. Quality control microorganisms are specific strains of organisms with intrinsic biological properties relating to resistance mechanisms and their genetic expression within bacteria; the specific strains used for microbiological quality control are not clinically significant.
Table 36. Acceptable Quality Control Ranges for Daptomycin to be used in Validation of Susceptibility Test Results
| QC Strain | Acceptable Quality Control Ranges |
| Broth Dilution MIC (μg/mL)a | |
| Staphylococcus aureus ATCC 29213 | 0.12-1 |
| Streptococcus pneumoniae ATCC 49619b | 0.06-0.5 |
a The quality control ranges for S. aureus are applicable only to tests performed by broth dilution using Mueller-Hinton broth adjusted to a calcium content of 50 μg/mL; the quality control ranges for S. pneumoniae are applicable only to tests performed by broth dilution using Mueller- Hinton broth adjusted to a calcium content of 50 μg/mL, supplemented with 2 to 5% lysed horse blood, inoculated with a direct colony suspension and incubated in ambient air at 35ºC for 20 to 24 hours.
b This organism may be used for validation of susceptibility test results when testing Streptococcus spp. other than S. pneumoniae.
TOXICOLOGY
Single-Dose Toxicity Studies
Acute toxicity testing identified the neuromuscular system (nervous system and/or skeletal muscle) as the target organ of daptomycin toxicity, and uncovered potential differences in sensitivity among the species tested (i.e., mouse, rat, dog, and monkey). Studies performed are listed in Table 37 below.
Table 37. Results of Single-Dose Toxicity Studies
| Species/ Strains | Route | Dose Levels (mg/kg) | Max. Non-Lethal Dose (mg/kg) | Noteworthy Findings |
|---|---|---|---|---|
| Mouse/ ICR | IV | 0, 700, 900, 1100, 1400 | <700 | 0: Transient generalized leg weakness 700: 1M and 5F died ≥700: Generalized leg weakness, hypoactivity, ataxia, tremors, ptosis, and death |
| Rat/ Fischer | IV | 0, 110, 140, 180, 225 | 110 | 0: Transient generalized leg weakness 110: Transient generalized leg weakness, hypoactivity 140: 4M and 1F died ≥140: Leg weakness, ataxia, hindlimb paralysis, tremors, clonic convulsions, and death |
| Dog/ Beagle | IV | 25, 200 | 200 | ≥25: Slight (2-3X) increases in serum creatine phosphokinase (CPK) within 24 h post-dose and generally returned to normal within 48 h after dosing 200: 10% decrease in body weight in 1 of 4 dogs, and slight reduction in appetite in 2 of 4 dogs |
| Species/ Strains | Route | Dose Levels (mg/kg) | Max. Non-Lethal Dose (mg/kg) | Noteworthy Findings |
|---|---|---|---|---|
| Monkey/ Rhesus | IV | 25, 200 | 25 | 25: Slight, transient lethargy and paleness of the facial skin in 2 of 4 animals; CPK increased >10-fold at 3 h post-dose and returned to normal within 48 h 200: 1M and 2F died. Death preceded by extreme lethargy, ataxia, and severe muscle weakness; slight axonal degeneration of the sciatic nerve in one of the deaths; CPK increased >10-fold at 3 h post-dose and did not return to normal until Day 7 after dosing |
| Rat/ Fischer | SC | 0, 350, 700 | 700 | 0: Transient generalized leg weakness ≥ 350: Transient generalized leg weakness; sores/scabs at injection sites |
IV: intravenous; SC: subcutaneous; M: male; F: female; h: hour.
Repeat-Dose Toxicity Studies
The results of repeat-dose and investigative studies consistently demonstrated daptomycin’s primary target organ to be skeletal muscle in adult rats and dogs, with effects observed in peripheral nerve at higher dose levels in both species (Table 39). Skeletal myopathy was usually accompanied by serum creatine phosphokinase (CPK) elevations in adult dogs, which preceded clinical effects and correlated with the severity of microscopic lesions. Nephrotoxicity and gastrointestinal effects observed in rats appear to be species-specific because these effects were not evident in either dogs or monkeys up to the highest doses tested (75 mg/kg/day and 10 mg/kg/day in dogs and monkeys, respectively). Recovery from skeletal myopathy was more rapid than recovery from daptomycin-related peripheral neuropathy. Recovery of peripheral nerve function was evident within 3 to 6 months post-dosing, although very minimal histological changes were observed 6 months after dosing cessation.
In contrast to adult dogs, juvenile dogs showed evidence of effects in nerves of the spinal cord as well as peripheral nerves after 28 days of dosing (Table 38 and see DETAILED PHARMACOLOGY, Animal Pharmacology, Juvenile Animals). The effects were noted at lower daptomycin doses and at lower daptomycin blood concentrations than in adult dogs. The data suggests that as compared to adult populations, juvenile populations may be more sensitive to daptomycin-related nerve effects.
Table 38. Summary of Findings on Repeat-Dose Toxicity and Investigative Studies*
| Species / Strain | Study Duration | Dose Range (mg/kg/day) | Noteworthy Findings (Dose levels affected) |
|---|---|---|---|
| Rat/ Fischer | 2 weeks; 1, 3, and 6 months | 1 to 150 |
|
| Species / Strain | Study Duration | Dose Range (mg/kg/day) | Noteworthy Findings (Dose levels affected) |
|---|---|---|---|
| Dog/ Beagle | 2 weeks; 1, 3, and 6 months | 1 to 100 |
|
Juvenile Dog/ Beagle | 2 weeks and 1 month | 1 to 150 |
|
Monkey/ Rhesus | 1 month | 1 to 10 | No effects were observed up to 10 mg/kg, the highest dose tested. |
* Daptomycin was administered by bolus IV injection in all studies; one study also investigated administration via 30-minute IV infusion. For most studies, daptomycin was administered once daily (q24h), except for select investigative studies in which it was also administered on a three times daily (q8h) regimen.
GI: gastrointestinal; CPK: creatine phosphokinase; ALT: alanine aminotransferase; AST: aspartate aminotransferase; AUC: area under the curve; Cmax: maximum serum concentration following dosing.
Genotoxicity
Daptomycin was not mutagenic or clastogenic in a battery of genotoxicity tests, including the Ames assay, a mammalian cell gene mutation assay, a test for chromosomal aberrations in Chinese hamster ovary cells, an in vivo micronucleus assay, an in vitro DNA repair assay, and an in vivo sister chromatid exchange assay in Chinese hamsters.
Carcinogenicity
Carcinogenicity studies have not been conducted.
Reproduction and Development Toxicity
Reproductive and developmental toxicity studies of daptomycin were conducted in rats (up to 150 mg/kg) and rabbits (up to 75 mg/kg) by once-daily bolus IV injection. Studies were conducted at daptomycin dose levels up to and including those that caused parental toxicity (see Repeat-Dose Toxicity Studies).
Daptomycin administration to the F0 generation was not associated with any reproductive toxicity, such as adverse effects on mating, fertility, parturition, and lactation. Further, there were no findings to suggest that daptomycin treatment of the F0 generation resulted in any developmental toxicities in the F1 generation. No test article-related mortality, teratogenic potential, alterations in growth, or functional toxicities was noted in any of the studies. Effects on progeny were limited to a slight (~10%), transient decrease in body weight at a dose level of 150 mg/kg in rats; this effect was reversible within 14 days postpartum. No other effects on the growth, behavior, or reproductive performance of the offspring were noted.
REFERENCES
- 1. Clinical and Laboratory Standards Institute (CLSI). Methods for Dilution Antimicrobial Susceptibility Tests for Bacteria that Grow Aerobically; Approved Standard - Tenth Edition. CLSI document M07-A10, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2015.
- 2. Clinical and Laboratory Standards Institute (CLSI). Performance Standards for Antimicrobial Susceptibility Testing; Twenty-seventh Informational Supplement, CLSI document M100-S27, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2017.
- 3. Clinical and Laboratory Standards Institute (CLSI). Performance Standards for Antimicrobial Disk Diffusion Susceptibility Tests; Approved Standard – Twelfth Edition. CLSI document M02-A12, Clinical and Laboratory Standards Institute, 950 West Valley Road, Suite 2500, Wayne, Pennsylvania 19087, USA, 2015.
- 4. Product Monograph for Pr CUBICIN®/CUBICIN® RF (Daptomycin for Injection) 500 mg /vial, Cubist Pharmaceuticals LLC, Lucerne, Switzerland. Submission Control No. 235553 , Date of Revision: May 15, 2020.
READ THIS FOR SAFE AND EFFECTIVE USE OF YOUR MEDICINE PATIENT MEDICATION INFORMATION
PrDaptomycin for Injection
Read this carefully before you start taking Daptomycin for Injection and each time you get a refill. This leaflet is a summary and will not tell you everything about this drug. Talk to your healthcare professional about your medical condition and treatment and ask if there is any new information about Daptomycin for Injection.
What is Daptomycin for Injection used for? Daptomycin for Injection is used to treat bacterial infections:
- of the skin and soft tissues (patients 1 year and older)
- in the blood (patients 1 year and older)
- certain heart valve infections (patients 18 years and older)
Antibacterial drugs like Daptomycin for Injection treat only infections caused by bacteria. They do not treat viral infections. Although you may feel better early in treatment, Daptomycin for Injection should be used exactly as directed. Misuse or overuse of Daptomycin for Injection could lead to growth of bacteria that will not be killed by Daptomycin for Injection (resistance). This means that Daptomycin for Injection may not work for you in the future.
How does Daptomycin for Injection work?
Daptomycin for Injection is an antibiotic. It works by killing certain bacteria that cause your infection.
What are the ingredients in Daptomycin for Injection?
Medicinal ingredients: Daptomycin
Non-medicinal ingredients: Sodium hydroxide
Daptomycin for Injection comes in the following dosage form:
Lyophilized powder for solution available as 500 mg/15 mL vial
Do not use Daptomycin for Injection if:
- you are allergic to daptomycin.
To help avoid side effects and ensure proper use, talk to your healthcare professional before you take Daptomycin for Injection. Talk about any health conditions or problems you may have, including if you:
- have kidney or severe liver problems.
- have high blood levels of creatine phosphokinase (CPK).
- are pregnant, or planning on becoming pregnant.
are breastfeeding or plan to breastfeed. Breastfeeding should be stopped during treatment
with Daptomycin for Injection.
- are allergic to any antibiotics or other drugs.
- are taking other medications (see The following may interact with Daptomycin for Injection).
- have any questions about your treatment, both before and during treatment.
Other warnings you should know about:
Stop taking Daptomycin for Injection and contact your doctor right away if you:
have severe or lasting diarrhea (bloody or watery) with or without
- fever.
- stomach pain or tenderness.
You may have Clostridium difficile colitis (bowel inflammation).
Tell your healthcare professional about all the medicines you take, including any drugs, vitamins, minerals, natural supplements or alternative medicines.
The following may interact with Daptomycin for Injection:
- Drugs that lower cholesterol (HMG-CoA reductase inhibitors also known as “statins” such as atorvastatin, fluvastatin, lovastatin, pravastatin, rosuvastatin, and simvastatin)
- Tobramycin (another antibiotic)
- Blood thinners (warfarin)
How to take Daptomycin for Injection:
Daptomycin for Injection will be given intravenously (injected into a vein) by a doctor or nurse in a hospital or clinical setting.
Usual dose:
Adults:
Serious skin infections: The usual adult dose is 4 mg for every kg of body weight. Your dose will be given either as an injection over a 2-minute period or by infusion over a 30-minute period every 24 hours for 7 to 14 days.
Bacterial infections in the blood, including certain heart valve infections: The usual adult dose is 6 mg for every kg of body weight. Your dose will be given either as an injection over a 2-minute period or by infusion over a 30-minute period every 24 hours for 10 to 56 days.
Children:
Your doctor will decide how much Daptomycin for Injection to give your child based on their age, weight and type of infection.
Serious skin infections:
| Age Group | Dosage* |
| Duration of Therapy | |
| 12 to 17 years | 5 mg/kg once every 24 hours infused over 30 minutes |
| Up to 14 days | |
| 7 to 11 years | 7 mg/kg once every 24 hours infused over 30 minutes |
| 2 to 6 years | 9 mg/kg once every 24 hours infused over 60 minutes |
| 1 to less than 2 years | 10 mg/kg once every 24 hours infused over 60 minutes |
Bacterial infections in the blood:
| Age Group | Dosage | Duration of Therapy |
| 12 to 17 years | 7 mg/kg once every 24 hours infused over 30 minutes | Up to 42 days |
| 7 to 11 years | 9 mg/kg once every 24 hours infused over 30 minutes | |
| 1 to 6 years | 12 mg/kg once every 24 hours infused over 60 minutes | |
Overdose:
What are possible side effects from using Daptomycin for Injection?
These are not all the possible side effects you may feel when taking Daptomycin for Injection. If you experience any side effects not listed here, contact your healthcare professional.
Common side effects may include:
- headache or dizziness.
- diarrhea or constipation.
- nausea or vomiting.
- rash or itching.
- difficulty sleeping.
| Serious side effects and what to do about them | ||
| Symptom / effect | Talk to your healthcare professional | Stop taking drug and get immediate medical help |
| Only if severe | In all cases | |
UNCOMMON A serious allergic reaction with symptoms such as:
| ||
| X | ||
If you think you have taken too much Daptomycin for Injection, contact your healthcare professional, hospital emergency department or regional poison control centre immediately, even if there are no symptoms.
Pain in the hands and feet with symptoms such as:
| X | ||
| Irregular heartbeat | X | ||
Kidney problems with symptoms such as:
| X | ||
VERY RARE Respiratory problems with symptoms such as:
| X |
If you have a troublesome symptom or side effect that is not listed here or becomes bad enough to interfere with your daily activities, talk to your healthcare professional.
Storage:
Daptomycin for Injection vials containing lyophilized powder should be stored at 2ºC to 8ºC.
Reconstituted solutions are to be used immediately or refrigerated (2ºC to 8ºC) and used within 72 hours, then discarded. Health Care professionals should refer to the Product Monograph for more details.
Reporting Side Effects
You can report any suspected side effects associated with the use of health products to Health Canada by:
- Visiting the Web page on Adverse Reaction Reporting (https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/adverse-reaction-reporting.html) for information on how to report online, by mail or by fax; or
- Calling toll-free at 1-866-234-2345.
NOTE: Contact your health professional if you need information about how to manage your side effects. The Canada Vigilance Program does not provide medical advice.
Keep out of reach and sight of children.
If you want more information about Daptomycin for Injection:
- Talk to your healthcare professional
- Find the full Product Monograph that is prepared for healthcare professionals and includes this Patient Medication Information by visiting the Health Canada website (https://health-products.canada.ca/dpd-bdpp/index-eng.jsp); or by contacting the manufacturer, Juno Pharmaceuticals Corp.: 1-855-819-0505.
Juno Pharmaceuticals Corp.
402-2233 Argentia Road, Mississauga, Ontario, L5N 2X7
Last Revised: January 28, 2021