


Product Monograph - Derma Smoothe/Fs Liq 0.01%
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Topical | Topical Oil / 0.01% w/v | Refined Peanut Oil NF, Mineral Oil Light, Oleth-2, Isopropyl Myristate, Isopropyl Alcohol, Cream Fragrance, Balsam Pine Fragrance. For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Derma-Smoothe/FS® Topical Oil (fluocinolone acetonide 0.01% w/v) is a low to medium potency corticosteroid indicated for:
- Treatment of atopic eczema in adults.
- Treatment of moderate to severe atopic dermatitis in children 3 months to 12 years. It may be used for a maximum duration of 4 weeks on the body. It is not indicated for use on the face or in the diaper or anogenital areas. Derma-Smoothe/FS® topical oil should not be used on infants under the age of 3 months.
Geriatrics (>65 years of age)
Clinical studies have not been conducted in populations >65 years of age.
Pediatrics
Safety and efficacy data are available for a very limited number of patients under the age of one year. Derma-Smoothe/FS® topical oil should be used on children between the ages of 3 months and one year only if the potential benefit justifies the potential risks. See also Endocrine and Metabolism, Special Populations - Pediatrics, Clinical trial Adverse Drug Reactions and Clinical Trials.
CONTRAINDICATIONS
- Derma-Smoothe/FS® Topical Oil is contraindicated in those patients with a history of hypersensitivity to any of the components of the preparation. This product contains refined peanut oil NF (see WARNINGS AND PRECAUTIONS section). For a complete listing see Dosage Forms, Composition and Packaging section.
- Patients who are hypersensitive to other corticosteroids.
- Patients with viral (e.g. herpes or varicella) lesions of the skin, bacterial or fungal skin infections, parasitic infections, skin manifestations relating to tuberculosis or syphilis, eruptions following vaccinations.
- Topical application to the eye is contraindicated, especially in the presence of ophthalmologic infections.
WARNINGS AND PRECAUTIONS
General
Derma-Smoothe/FS® is formulated with 48% refined peanut oil NF. Physicians should use caution in prescribing Derma-Smoothe/FS® for peanut-sensitive individuals. In clinical trials, one peanut-sensitive child experienced a flare of his atopic dermatitis after 5 days of twice daily treatment with Derma-Smoothe/FS®. There have also been post-market reports of reactions to Derma-Smoothe/FS® topical oil attributed to peanut allergy. See Post-Market Adverse Drug Reactions and CLINICAL TRIALS.
Derma-Smoothe/FS® should not be used in intertriginous areas or under occlusion. When used under occlusive dressing over extensive areas or on the face, scalp, axillae or scrotum, sufficient absorption may occur to result in adrenal suppression and other systemic effects (see Endocrine and Metabolism).
Carcinogenesis and Mutagenesis
Long term animal studies have not been performed to evaluate the carcinogenic potential or the effect on fertility of Derma-Smoothe/FS® Topical Oil.
Studies have not been performed to evaluate the mutagenic potential of fluocinolone acetonide, the active ingredient in Derma-Smoothe/FS®. Some corticosteroids have been found to be genotoxic in various genotoxicity tests (i.e. the in vitro human peripheral blood lymphocyte chromosome aberration assay with metabolic activation, the in vivo mouse bone marrow micronucleus assay, the Chinese hamster micronucleus test and the in vitro mouse lymphoma gene mutation assay).
Cardiovascular
Suitable precautions should be taken when using topical corticosteroids in patients with stasis dermatitis and other skin diseases with impaired circulation.
Endocrine and Metabolism
Systemic absorption of topical corticosteroids can produce reversible hypothalamic-pituitary-adrenal (HPA) axis suppression and the potential for adrenal insufficiency after sudden withdrawal of treatment. Manifestations of Cushing's syndrome, hyperglycemia, and glycosuria can also be produced in some patients by systemic absorption of topical corticosteroids while on treatment.
Conditions which augment systemic absorption include the application of topical corticosteroids over large body surface areas, prolonged use, or the addition of occlusive dressings. If patients must be treated over large body surface areas, they should be evaluated periodically for evidence of HPA axis suppression (see Monitoring and Laboratory Tests). If HPA axis suppression is noted, an attempt should be made to withdraw the drug, to reduce the frequency of application, or to substitute a less potent steroid.
Recovery of HPA axis function is generally prompt and complete upon discontinuation of topical corticosteroids. Infrequently, signs and symptoms of glucocorticosteroid insufficiency may occur requiring supplemental systemic corticosteroids. For information on systemic corticosteroid supplementation, see prescribing information for those products.
Pediatric patients may be more susceptible to systemic toxicity from equivalent doses because of their larger skin surface to body mass ratios (See Special Populations-Pediatrics). As well, there is some evidence in the literature to suggest that the barrier function and water-handling properties of the stratum corneum become adult-like only after the first year of life.16 As such, infants in the first year of life may be more susceptible to percutaneous absorption of drugs and consequent systemic effects than older individuals. Derma-Smoothe/FS® topical oil should be used on children between the ages of 3 months and one year only if the potential benefit justifies the potential risks.
The effect of Derma-Smoothe/FS® topical oil on HPA axis function was investigated in 30 pediatric patients aged 3 months to 2 years. In this study, subjects with moderate to severe atopic dermatitis covering at least 20% body surface area were treated with Derma-Smoothe/FS® topical oil twice daily for 4 weeks. A normal functioning HPA axis was defined as a baseline morning cortisol level exceeding 5mcg/100mL, followed by a cortisol level exceeding 18 mcg/100mL with an increment of at least 7mcg/100mL above the basal level 30 minutes after stimulation with 0.125mg of cosyntropin. Of the 29 subjects with cortisol results available at the end of the study, four had abnormal post-treatment results following 28 days of treatment with Derma-Smoothe/FS® topical oil. Three subjects ranging in age from 5 months to 9 months, all with moderate disease covering 50-75% body surface area, had post-treatment basal cortisol levels less than 5 mcg/100mL, but the values were within the normal range for children age 2 months to 13 years based on the standard used by the reference laboratory. All three subjects had normal responses to cosyntropin stimulation. The fourth subject was a 12-month old with atopic dermatitis covering 50-75% of body surface area who had an incremental increase in cortisol of less than 7mcg/100mL but a normal cortisol level greater than 18mcg/100mL following cosyntropin stimulation. The clinical significance of these four abnormal results is not known, as all 29 subjects had a normal post-treatment, post-stimulation cortisol level greater than 18mcg/100mL. See Clinical Trial Adverse Drug Reactions.
Glucocorticoids decrease the hypoglycemic activity of insulin and oral hypoglycemics, so that a change in dose of the antidiabetic drugs may be necessitated. In high doses, glucocorticoids also decrease the response to somatotropin.
The usual doses of mineralocorticoids and large doses of some glucocorticoids cause hypokalemia and may exaggerate the hypokalemic effects of thiazides and high-ceiling diuretics. In combination with amphotericin-B, they also may cause hypokalemia.
Glucocorticoids appear to enhance the ulcerogenic effects of non-steroidal anti-inflammatory drugs.
They decrease the plasma levels of salicylates, and salicylism may occur on discontinuing steroids.
Glucocorticoids may increase or decrease the effects of prothrombopenic anticoagulants.
Estrogens, phenobarbital, phenytoin and rifampin increase the metabolic clearance of adrenal steroids and hence necessitate dose adjustments.
Immune
Cortisol and the synthetic analogs of cortisol have the capacity to prevent or suppress the development of the local heat, redness, swelling, and tenderness by which inflammation is recognized. At the microscopic level, they inhibit not only the early phenomena of the inflammatory process (edema, fibrin deposition, capillary dilation, migration of leukocytes into the inflamed area, and phagocytic activity) but also the later manifestations (capillary proliferation, fibroblast proliferation, deposition of collagen, and, still later, cicatrization).
Topical corticosteroids may increase the risk of infections including aggravation of cutaneous infection, masked infection and secondary infections. If concomitant skin infections develop, Derma-Smoothe/FS® topical oil should be discontinued until the infection has been adequately controlled.
Ophthalmologic
Topical corticosteroids should be used with caution on lesions close to the eye because systemic absorption may cause increased intraocular pressure, glaucoma or cataracts.
Avoid contact with the eyes. In case of contact, wash eyes liberally with water.
Sensitivity/Resistance
Allergic contact dermatitis with corticosteroids is usually diagnosed by observing a failure to heal rather than noticing a clinical exacerbation. Such an observation should be corroborated with appropriate diagnostic patch testing.
Skin
If significant irritation develops, Derma-Smoothe/FS® Topical Oil should be discontinued and appropriate therapy instituted.
The following local adverse reactions have been reported infrequently with topical corticosteroids, including fluocinolone acetonide. They may occur more frequently with the use of occlusive dressing, especially with higher potency corticosteroids and with prolonged use. The reactions are listed in approximate decreasing order of occurrence: burning, itching, irritation, dryness, folliculitis, acneiform eruptions, hypopigmentation, perioral dermatitis, allergic contact dermatitis, secondary infection, skin atrophy, striae and miliaria.
Topical corticosteroids should be used with caution on lesions of the face, groin and axillae as these areas are more prone to atrophic changes than other areas of the body. Frequent observation is important if these areas are to be treated. If skin atrophy is observed, treatment should be discontinued.
Special Populations
Pregnant Women:
Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at relatively low dosage levels. Some corticosteroids have been shown to be teratogenic after dermal application in laboratory animals. No studies have been done on Derma-Smoothe/FS® Topical Oil to show teratologic effects on animals.
There are no adequate and well-controlled studies in pregnant women on teratogenic effects from Derma-Smoothe/FS®. Therefore, Derma-Smoothe/FS® should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Nursing Women:
Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. It is not known whether topical administration of corticosteroids could result in sufficient systemic absorption to produce detectable quantities in human milk. Because many drugs are secreted in human milk, caution should be exercised when Derma-Smoothe/FS® Topical Oil is administered to a nursing woman.
Pediatrics:
Derma-Smoothe/FS® topical oil should not be used on infants under the age of 3 months.
Safety data are available for a very limited number of patients under the age of one year. See Clinical Trial Adverse Drug Reactions and Clinical Trials. Long term safety (over 28 days) in the paediatric population (children aged 3 months to 12 years) has not been established.
Derma-Smoothe/FS® is not indicated for use on the face or in the diaper or anogenital areas.
Application to intertriginous areas should be avoided due to the increased possibility of local adverse events such as striae, atrophy, and telangiectasia, which may be irreversible. Administration of topical corticosteroids to children should be limited to the least amount and for the shortest duration compatible with an effective therapeutic regimen.
Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of HPA axis suppression and Cushing's syndrome when they are treated with topical corticosteroids. They are therefore also at greater risk of adrenal insufficiency during and/or after withdrawal of treatment. As well, there is some evidence in the literature to suggest that the barrier function and water-handling properties of the stratum corneum become adult-like only after the first year of life.16 As such, infants in the first year of life may be more susceptible to percutaneous absorption of drugs and consequent systemic effects than older individuals. Derma-Smoothe/FS® Topical Oil should be used on children between the ages of 3 months and one year only if the potential benefit justifies the potential risks. See also Endocrine and Metabolism.
Adverse effects including striae have been reported with use of topical corticosteroids in infants and children. HPA axis suppression, Cushing’s syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in children receiving topical
corticosteroids. Manifestations of adrenal suppression in children include low plasma cortisol levels and an absence of response to ACTH stimulation. Manifestations of intracranial hypertension include bulging fontanelles, headache, and bilateral papilledema. Chronic corticosteroid therapy may interfere with the growth and development of children.
Derma-Smoothe/FS® is formulated with 48% refined peanut oil NF. The peanut oil used in Derma-Smoothe/FS® is tested for residual protein through amino acid analysis; the acceptance criterion for total protein is no more than 0.5 parts per million. Physicians should use caution in prescribing Derma-Smoothe/FS® for peanut-sensitive children.
Geriatrics:
Clinical studies have not been conducted in populations >65 years of age. In general, topical corticosteroids should be used cautiously in elderly patients, reflecting their increased skin fragility and greater frequency of hepatic, renal, or cardiac dysfunction, and of concomitant disease or other drug therapy.
Monitoring and Laboratory Tests
The following tests may be helpful in evaluating patients for HPA axis suppression: ACTH stimulation test
A.M. plasma cortisol test
Urinary free cortisol test
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The following local adverse reactions have been reported with topical corticosteroids and may occur more frequently with use of occlusive dressings. These reactions are listed in an approximate decreasing order of occurrence: burning, itching, irritation, dryness, folliculitis, hypertrichosis, acneiform eruptions, hypopigmentation, perioral dermatitis, allergic contact dermatitis, secondary infection, skin atrophy, striae and miliaria.
In clinical trials, one peanut sensitive child experienced a flare of his atopic dermatitis after 5 days of twice daily treatment with Derma-Smoothe/FS®. There have also been post-market reports of reactions to Derma-Smoothe/FS® topical oil attributed to peanut allergy. See Post-Market Adverse Drug Reactions and CLINICAL TRIALS.
Deaths and other Serious Adverse Events
No deaths or serious adverse events were reported in any of the studies.
Withdrawals Due to Adverse Events
One subject was withdrawn from the primary safety study in pediatric patients 3 months to 2 years of age with atopic dermatitis due to an adverse event (abscess of right antecubital area), considered not likely to be related to the study product. There were 7 withdrawals from the primary efficacy studies in pediatric patients (2 years to 12 years) with atopic dermatitis. Six (6) withdrawals were due to adverse events (disease exacerbation), 4 from the placebo group and 2 from the active treatment group. One patient from the active treatment group was removed due to a protocol violation.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions, the adverse drug reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Atopic Dermatitis Studies
Study HD-038-PED
Safety in patients with atopic dermatitis aged 3 months to 2 years was investigated in an open-label, Phase 4 study (n=30) in which subjects were treated with Derma-Smoothe/FS® Topical Oil twice daily for 4 weeks. In this study, patients had moderate-severe atopic dermatitis affecting as least 20% of body surface area. Safety evaluation included assessment of hypothalamic-pituitary-adrenal (HPA) axis function 4 weeks after treatment (on Day 29) and local occurrences of adverse events. Fifteen subjects (50%) were 3 months to 1 year of age and 15 subjects were one year of age and over (up to 2.7 years of age). Seven of the 30 subjects (23.3%) were less than 6 months of age. One subject was omitted from the HPA axis assessment due to study withdrawal related to an adverse event (abscess right antecubital area).
In this study, a normal functioning HPA axis was defined as a baseline morning cortisol level exceeding 5 mcg/100 mL, followed by a cortisol level exceeding 18 mcg/100 mL with an increment of at least 7 mcg/100 mL above the basal level 30 minutes after stimulation with 0.125 mg of cosyntropin. Of the 29 subjects with cortisol results available at the end of the study, four had abnormal post-treatment results following 28 days of treatment with Derma-Smoothe/FS® topical oil. Three subjects ranging in age from 5 months to 9 months, all with moderate disease covering 50-75% body surface area, had post-treatment basal cortisol levels less than 5 mcg/100mL, but the values were within the normal range for children age 2 months to 13 years based on the standard used by the reference laboratory. All three subjects had normal responses to cosyntropin stimulation. The fourth subject was a 12-month old with atopic dermatitis covering 50-75% of body surface area who had an incremental increase in cortisol of less than 7mcg/100mL but a normal cortisol level greater than 18mcg/100mL following cosyntropin stimulation. The clinical significance of these four abnormal results is not known, as all 29 subjects had a normal post-treatment, post-stimulation cortisol level greater than 18mcg/100mL.
See Table below for list of adverse events from pediatric study HD-038-PED.
Table 1: Study HD-038-PED Adverse Events Report by Incidence
| Body System | MedDRA Preferred Term | Incidence (N=30) |
| Number of subjects with at least one AE | 17 (56.7%) | |
| Gastrointestinal disorder | 2 (6.7%) | |
| Diarrhea | 1 (3.3%) | |
| Vomiting | 1 (3.3%) | |
| General disorder and administration site conditions | 3 (10.0%) |
| Body System | MedDRA Preferred Term | Incidence (N=30) |
| Pyrexia | 3 (10.0%) | |
| Infections and infestations | 7 (23.3%) | |
| Nasopharyngitis | 2 (6.7%) | |
| Abscess | 1 (3.3%) | |
| Bite, insect | 1 (3.3%) | |
| Molluscum | 1 (3.3%) | |
| Otitis media | 1 (3.3%) | |
| URI | 1 (3.3%) | |
| Respiratory, thoracic and mediastinal disorder | 8 (26.6%) | |
| Cough | 6 (20%) | |
| Rhinorrhea | 4 (13.3%) | |
| Skin and subcutaneous tissue disorder | 5 (16.7%) | |
| Atopic dermatitis | 1 (3.3%) | |
| Eczema | 1 (3.3%) | |
| Hyperpigmentation | 1 (3.3%) | |
| Hypopigmentation | 2 (6.7%) | |
| Rash | 1 (3.3%) |
Study 25
Study 25 was a double-blind safety and efficacy study of Derma-Smoothe/FS® versus the Derma-Smoothe/FS® vehicle in the treatment of atopic dermatitis in children 2 years and older. Derma-Smoothe/FS® was applied twice daily for 28 days. Only one adverse event was noted in Study 25. This adverse event was slight hypopigmentation, noted at the final evaluation, 2 weeks after stopping treatment with Derma-Smoothe/FS®. In Study 25, a total of 84 patients completed the study.
Study 25-S
Study 25-S was an open-label safety study of Derma-Smoothe/FS® for the treatment of atopic dermatitis. Derma-Smoothe/FS® was applied twice daily for 28 days. No adverse events were observed in Study 25-S California. Four patients in Study 25-S Chicago, Cleveland, and Miami had at least one adverse event. All patients with reported adverse events were at the Chicago site: two patients had severe papules, pustules, burning, itching, and irritation at the final visit (2 weeks after stopping study medication), and two patients had mild papules and pustules at the 4th week of treatment (the last week of treatment with study medication), and moderate erythema, papules, pustules, burning, itching, and irritation at the final visit (2 weeks after stopping study medication). All adverse events had resolved soon after the end of the study, as determined by an informal follow-up by the sponsor to each investigator after termination of the study. Seven placebo treated patients had exacerbation of the disease. In Study 25-S, a total of 25 subjects completed the study.
Study 26
Study 26 was a post-marketing (open label) safety study to evaluate the effects of Derma-Smoothe/FS® on HPA axis suppression. A total of 15 subjects were enrolled in the safety study. One subject withdrew before week two evaluations and one subject was eliminated for a lack of cortisol levels at week four. No local adverse events were reported during Study 26. In Study 26 a total of 13 subjects completed the study.
Table 2: Study 25 and Study 25-S
Derma-Smoothe/FS® N = 76 * (%) | Derma-Smoothe/FS® Vehicle N = 52 (%) | |
Integumentary Hypopigmentation Erythema Papules Pustules Burning Itching Irritation | 1 (1.3) 2 (2.6) 6 (7.9) 6 (7.9) 4 (5.3) 4 (5.3) 4 (5.3) | 0 0 0 0 0 0 0 |
* Combined Study 25 and Study 25-S (Open-label)
Post-Market Adverse Drug Reactions
The following post-market adverse drug reactions have been reported. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
-allergic reaction, reaction attributed to peanut allergy, rash, hives -alopecia, skin irritation, itching, bumps, erythema, flaking/crusting/scaling/scabbing, blisters/sores in scalp, burning of skin and scalp
-transient corneal irritation due to accidental exposure, eye swollen, blood shot eye, burning/redness/tearing of eyes
-nausea, vomiting, diarrhea
-headache, vertigo, pain, paralysis-like episode, muscle spasms -diabetic incident (elevated glucose)
-attempted suicide by ingestion of product
-concerned for child sucking a treated thumb
Study HD-038-PED
See Clinical trial adverse drug reactions section, above.
Study 26
See Clinical trial adverse drug reactions section, above.
Peanut Hypersensitivity Safety Study
Chicago Peanut Allergy Study
A phase 4, controlled, open label clinical study was conducted to assess the safety of Derma-Smoothe/FS®, which contains refined peanut oil NF, on subjects with known peanut allergies. The study enrolled 13 patients with atopic dermatitis, 6 to 17 years of age. Of the 13 patients, 9 were Radioallergosorbent Test (RAST) positive to peanuts and 4 had no peanut sensitivity (controls). One of the 9 peanut-sensitive patients experienced an exacerbation of atopic dermatitis after 5 days of treatment with Derma-Smoothe/FS®
(see CLINICAL TRIALS section). In the Chicago Peanut Allergy Study, a total of 12 patients completed the study.
DRUG INTERACTIONS
Overview
There are no known genetic differences in response to Derma-Smoothe/FS® Topical Oil for treatment of atopic dermatitis, and there are no known clinically relevant interactions with other medicinal products. There were insufficient numbers of patients in the clinical trials of Derma-Smoothe/FS® Topical Oil to examine potential drug-drug, drug-demographic, or drug-disease interactions.
Drug-Drug Interactions
There have been no clinical studies conducted to assess the safety of Derma-Smoothe/FS® Topical Oil used in combination therapy. It is recommended that Derma-Smoothe/FS® Topical Oil be used without the use of other medications. (see WARNINGS AND PRECAUTIONS, Endocrine and Metabolism for possible drug interactions with glucocorticoids in general)
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Patients/caregivers should be instructed to use Derma-Smoothe/FS® Topical Oil for the minimum amount of time necessary to achieve the desired results because of the potential for corticosteroids to suppress the hypothalamic-pituitary-adrenal (HPA) axis and cause skin atrophy (See Warnings and Precautions).
- Apply the least amount of Derma-Smoothe/FS® Topical Oil needed to cover the affected areas.
- Paediatrics: Due to their higher ratio of skin surface area to body mass, children are at greater risk than adults of HPA axis suppression when they are treated with topical corticosteroids. Derma-Smoothe/FS® should not be used on infants under the age of 3 months. Parents of paediatric patients should be advised not to use Derma-Smoothe/FS® Topical Oil in the treatment of facial or diaper dermatitis. Derma-Smoothe/FS® Topical Oil is not indicated for use on the face or anogenital areas. Derma-Smoothe/FS® Topical Oil is not indicated for use in the diaper area as diapers or plastic pants may constitute occlusive dressing. Parents of paediatric patients should be advised that use of Derma-Smoothe/FS® Topical Oil is for topical use only, not for oral, ophthalmic, or intravaginal use.
Geriatrics: Clinical studies have not been conducted in population ages >65 years of age.
Derma-Smoothe/FS® Topical Oil should be used with caution in patients >65 years of
age who may be more susceptible to percutaneous absorption and the potential effects of systemic absorption.
Recommended Dose and Dosage Adjustment
Atopic Eczema in Adults: Wet or dampen the affected area and apply a thin film of
Derma-Smoothe/FS® Topical Oil two to three times daily, massaging in gently. For use on the scalp: Wet hair and scalp, then apply thin film of oil to entire scalp. Massage scalp and cover with supplied shower cap overnight (4 hours minimum).
Atopic Dermatitis in Children 3 months to 12 years: Moisten skin and apply a thin film of
Derma-Smoothe/FS® Topical Oil over the affected areas, massaging in gently twice daily for up to a maximum of 4 weeks. If no improvement is seen within 2 weeks, contact the physician.
Missed Dose
If a dose of this medication is missed, it is not necessary to make up the missed dose. Skip the missed dose and continue with the next scheduled dose.
Administration
- Avoid contact with the eyes. In case of contact, wash eyes liberally with water.
- Derma-Smoothe/FS® Topical Oil should not be used with occlusive dressings.
OVERDOSAGE
- Topically applied corticosteroids can be absorbed in sufficient amounts to produce systemic effects. Excessive prolonged use may suppress hypothalamic-pituitary-adrenal (HPA) axis function, resulting in secondary adrenal insufficiency, which is usually reversible. If toxic effects occur, treatment should be discontinued and symptomatic therapy administered. (See WARNINGS and PRECAUTIONS).
- If an overdose should occur, the area should be washed thoroughly with water. There is no antidote for overdose of this product.
For management of a suspected drug overdose contact your regional Poison Control Center.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Like other topical corticosteroids, fluocinolone acetonide has anti-inflammatory, antipruritic, and vasoconstrictive properties. The mechanism of the anti-inflammatory activity of the topical steroids is unclear. However, corticosteroids are thought to act by the induction of phospholipase A2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation, such as prostaglandins and leukotrienes by inhibiting the release of their common precursor arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A2.
Pharmacodynamics
The pathways by which topical steroids improve atopic dermatitis are not clearly understood. No studies involving the pharmacodynamics of the active fluocinolone acetonide or the drug product Derma-Smoothe/FS® Topical Oil have been performed.
Pharmacokinetics
No studies in pharmacokinetics, absorption, distribution, excretion, or metabolism involving the active fluocinolone acetonide or the drug product Derma-Smoothe/FS® Topical Oil have been performed. Pharmacokinetic properties of the drug class of topically applied corticosteroids remain incompletely understood.
Absorption:
Topically applied corticosteroids may be absorbed percutaneously; percutaneous absorption of topical steroids is determined by many factors including the vehicle, thickness of the stratum corneum, presence of skin disease, skin hydration, and integrity of the epidermal barrier. Topical corticosteroids can be absorbed through normal skin.
Distribution:
Dermally applied corticosteroids are distributed throughout the skin, although the distribution in the skin depends on their percutaneous absorption. Percutaneously absorbed corticosteroids can also be distributed throughout the body, entering the systemic circulation via the dermal microcirculation.
Metabolism:
The viable epidermis is known to be metabolically active and contains many of the enzymes also found in the liver, including a cytochrome P450 system which may be inducible. Steroids may undergo hydrolysis within the epidermis; sulphate conjugation also occurs. The importance of dermal metabolism of steroids to their mechanism of action is unknown.
Systemically, 90% or more of glucocorticoids is reversibly bound to protein under normal circumstances. Corticosteroid-binding globulin and albumin account for most of the plasma steroid-binding capacity. Topically applied corticosteroids undoubtedly undergo further systemic metabolic processes. All of the biologically active adrenocortical steroids and their synthetic congeners have a double bond in the 4,5 position and a ketone group at C3. Reduction of the 4,5 double bond occurs at both hepatic and extrahepatic sites, yielding inactive compounds. Reduction of the 3-ketone constituent occurs only in the liver.
Excretion:
Systemically distributed steroids are excreted in the urine as water-soluble esters and glucuronides. Neither biliary nor fecal excretion is of quantitative importance in humans. Topical steroids may also remain on the surface of the skin and may be eliminated by washing them off the skin.
STORAGE AND STABILITY
Recommended storage condition for Derma-Smoothe/FS® Topical Oil is at controlled room temperature of approximately 25o C excursions permitted to 15°-30°C (59°-86°F). Derma-Smoothe/FS® Topical Oil has a full shelf life of 18 months under the required storage conditions.
Keep out of reach of children and pets. Unused medication should not be disposed of down the drain or in household garbage.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Forms: Topical Oil
Composition:
Medicinal: Fluocinolone acetonide, 0.01% w/v
Non-medicinal:
Balsam Pine Fragrance # 5124
Cream Fragrance # 362411
Isopropyl Alcohol USP
Isopropyl Myristate NF
Mineral Oil Light NF
Oleth-2
Peanut Oil Refined NF
Packaging:
Derma-Smoothe/FS® Topical Oil is provided in two packaging configurations. The composition of both packaging configurations are identical:
- Derma-Smoothe/FS® Topical Oil, Topical Use – for the Body only, is supplied in bottles containing 118.28ml (4 fl. oz.).
- Derma-Smoothe/FS® Topical Oil, Topical Use – for the Scalp only, is supplied in
bottles containing 118.28ml (4 fl. oz.) with shower cap included. 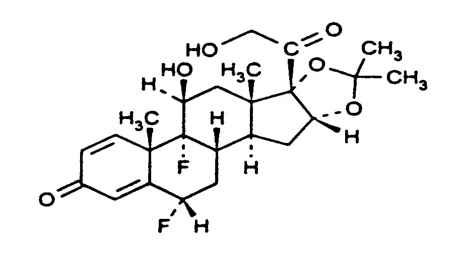
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Fluocinolone acetonide
Chemical Name: 6α,9α-Difluoro-11β,16α,17,21-tetrahydroxypregna-1,4-diene-3,20-dione cyclic 16,17-acetal with acetone
Molecular Formula and Molecular Mass: C24H30F2O6 , 452.50
Structural Formula:
Physicochemical Properties:
Physical Form: White, crystalline powder that is odorless; stable in light. Solubility: Fluocinolone acetonide is soluble in alcohol, acetone and methanol; slightly soluble in chloroform; insoluble in water.
Melting Point: Melts at about 270°C, with decomposition.
Storage: Store in well-closed containers, protected from light, at temperatures not exceeding 25°C
CLINICAL TRIALS
Study Demographics and Trial Design
Study HD-038-PED An Open-label Safety Study of Derma-Smoothe/FS® Topical Oil in Pediatric Patients, 3 months to 2 years of age, with Atopic Dermatitis
The primary objective of this study was to evaluate the potential of Derma-Smoothe/FS® Topical Oil to suppress the hypothalamic-pituitary-adrenal (HPA) axis. The study was an open-label, Phase 4 trial with pediatric patients, 3 months to 2 years of age, with moderate-severe atopic dermatitis covering at least 20% body surface area. Derma-Smoothe/FS® Topical Oil was applied as a thin film on all affected areas and massaged gently into moistened skin, twice daily for a period of 4 weeks (28 days). Efficacy parameters were incorporated as secondary objectives into the study design to ensure the doses applied to the test areas were therapeutically effective. The investigator evaluated individual signs and symptoms (pruritus, prurigo, eczematous lesions and lichenification), global severity and global response at each visit, including one week after discontinuation of treatment (Day 35). Each subject's parents were also asked to assess the child's pruritus and global improvement in the disease.
Of the 30 patients in the intent-to-treat (ITT), population, 29/30 (97%) completed the study; one patient did not complete the study due to an adverse event (abscess on the right antecubital area). Fifteen subjects (50%) were 3 months to 1 year of age and 15 subjects were one year of age and over (up to 2.7 years of age). Seven of the 30 subjects (23.3%) were less than 6 months of age.
Table 1: Reasons for Patient-Withdrawal from the Study
| N | |
| Number of subjects enrolled | 32 |
| Number of subjects who did not complete study: | 4 |
| Baseline pre-stimulation cortisol level < 5 mcg/dL † | 1 |
| Did not return for baseline cortisol evaluation † | 1 |
| Did not return for final F/U visit | 1 |
| Discontinued for Adverse Event at Day 14 | 1 |
| ITT Population | 30 |
† These subjects did not receive study drug and were not included in the ITT population
Table 2: Summary of ITT Population Demographics
| Gender: | Male | 15 (50%) |
| Female | 15 (50%) | |
| Race: | Caucasian | 7 (23.3%) |
| African American | 10 (33.3%) | |
| Asian | 6 (20.0%) | |
| Other | 7 (23.3%) | |
| Age (yrs): | Mean | 1.1 |
| SD | 0.7 | |
| Min-Max | 0.3-2.7 |
Study Results
See Clinical trial adverse drug reactions section for HPA axis (safety) results.
No hypothesis testing was planned in the study protocol. For ITT efficacy analysis population, the missing values were replaced using the last observation carried forward (LOCF) technique.
All efficacy parameters exhibited improvements from baseline at Day 14 and Day 29, suggesting that the dose of the study drug administered was in the therapeutic range.
Table 3: Investigator Evaluations of Signs and Symptoms at Baseline, Day 14 and Day 29
(mean scores)
| Parameter | Baseline Score (N=30) | Day 14 (N=30) | Day 29 (N=30) |
| Pruritus | 2.07 | 0.77 | 0.40 |
| Prurigo | 0.70 | 0.33 | 0.17 |
| Lichenification | 1.37 | 0.70 | 0.40 |
| Eczema | 2.10 | 1.17 | 0.63 |
Scale: O=None, 1=Mild, 2=Moderate, 3=Severe
Table 4: Distribution of Global Improvement Ratings at Day 14 and Day 29 compared to baseline
| Time | N | Number of Patients with a Rating of: | ||||||
Complete Clearing (100% improvement) | Excellent Response (75%-99% improvement) | Good Response (50%-74% improvement) | Fair Response (25%-49% improvement) | Slight Response (<25% improvement) | No Change | Exacerbated | ||
| Day 14* | 29 | 1 (3%) | 10 (35%) | 13 (45%) | 2 (7%) | 2 (7%) | 1(3%) | 0 |
| Day 29 | 30 | 12 (40%) | 7 (23%) | 10 (33%) | 1 (3%) | 0 | 0 | 0 |
* One subject did not have Day 14 values
Table 5: Distribution of Global Severity Assessments at Baseline, Day 14 and Day 29
| Time | N | Number of Patients with a Rating of: | |||
| None | Mild | Moderate | Severe | ||
| Baseline | 30 | 0 | 0 | 27 (90%) | 3 (10%) |
| Day 14 | 30 | 1 (3%) | 23 (77%) | 6 (20%) | 0 |
| Day 29 | 30 | 12 (40%) | 16 (54%) | 2 (7%) | 0 |
Table 6: Investigator Evaluation of Disease Status at Follow-up Visit (Day 35)
| Disease Status | Number of Subjects (N=28) |
| Patient is totally clear of atopic dermatitis signs and/or symptoms. | 5 |
| Patient has residual signs and/or symptoms that do not require further treatment. | 7 |
| Although signs/symptoms were gone at the last visit, patient now requires further treatment for atopic dermatitis. | 13 |
| Patient was not cleared at any point during the study and requires further treatment for atopic dermatitis. | 3 |
Parent assessments of pruritus also indicated improvement over the duration of the study. The parents assessed approximately 44% of the subjects were clear to almost clear of disease at Day
14, and 76% were clear or almost clear by Day 29. The parent assessment demonstrated all subjects had shown marked or better improvement by Day 29.
Study 25 Double-Blind Comparative Efficacy and Safety Study Comparing Derma-Smoothe/FS® Topical to its Vehicle in the Treatment of Atopic Dermatitis in Pediatric Patients
A phase 3 double-blind clinical study was conducted to assess the efficacy and safety of Derma-Smoothe/FS® Topical Oil in the treatment of Atopic Dermatitis in children 2 years and older. Of the 102 subjects who were enrolled in the study, 4 did not return after the 2-week washout (and did not receive the study drug) and one did not return after the baseline visit. Six subjects suffered disease exacerbation during the study and were terminated because of protocol violations (required disallowed medications). Of the subjects included in the Intend-To-Treat (ITT) population, 46/49 (94%) of the active subjects completed the study, as did 41/45 (91%) of the vehicle-treated subjects. All seven subjects who did not complete the study did so because of disease exacerbation, which required treatment with disallowed medication. Derma-Smoothe/FS® Topical Oil was applied to the affected areas twice daily for 28 days.
| Table 7: Demographic and Baseline Information | |||||||
| Parameter | Treatment Group | Miami | Atlanta | p-value | Chicago | St. Louis | p-value |
Age (yrs) ( M ± SE) | Active | 6.14 ± 3.05 | 5.53 ± 2.50 | 0.530a | 6.57 ± 1.83 | 3.50 ± 2.26 | 0.024a |
| Vehicle | 6.76 ± 3.58 | 6.27 ± 4.03 | 0.714a | 4.71 ± 1.98 | 3.50 ± 1.38 | 0.233a | |
| Sex | Active Male Female | 8 13 | 6 9 | 0.908b | 2 5 | 5 1 | 0.048b |
Active Male Female | 10 7 | 8 7 | 0.755b | 2 5 | 4 2 | 0.170b | |
| Race | Active White Hispanic | 6 14 1 | 2 13 0 | 0.351b | 3 1 2 | 2 4 0 | 0.135b |
Active White Hispanic | 2 13 2 | 1 14 0 | 0.324b | 3 3 1 | 1 5 0 | 0.296b | |
at-test bchi square test
| Table 8: Subjects Enrolled in Study 25. | |||||||
| Subject Status | Treatment Group | Miami | Atlanta | Chicago | St. Louis | East | West |
| Enrolled | Active | 21 | 15 | 7 | 7 | 36 | 14 |
| Vehicle | 22 | 15 | 8 | 7 | 37 | 15 | |
| Did not return after washout | Active | 0 | 0 | 0 | 1 | 0 | 1 |
| Vehicle | 2 | 0 | 1 | 0 | 2 | 1 | |
| Did not return after baseline | Active | 0 | 0 | 0 | 0 | 0 | 0 |
| Vehicle | 0 | 0 | 0 | 1 | 0 | 10 | |
| No evaluations after baseline | Active | 0 | 0 | 0 | 0 | 0 | 0 |
| Vehicle | 3 | 0 | 0 | 0 | 3 | 0 | |
| ITT analysis population | Active | 21 | 15 | 7 | 6 | 36 | 13 |
| Vehicle | 17 | 15 | 7 | 6 | 32 | 13 | |
| Did not complete studya | Active | 1 | 0 | 1 | 1 | 1 | 2 |
| Vehicle | 0 | 0 | 4 | 0 | 0 | 4 | |
Completed Study | Active | 20 | 15 | 6 | 5 | 35 | 11 |
| Vehicle | 17 | 15 | 3 | 6 | 32 | 9 | |
a subjects experienced disease exacerbation and required disallowed medications
Study Results
After one week of treatment (week 1 visit), there were statistically significant differences between the active (Derma-Smoothe/FS®) and vehicle groups for all four parameters, all in favour of the active group: erythema (p=0.0062); scaling (p=0.0021); lichenification (p=0.0027); and pruritus (p=0.0009).
| Table 9: East Study: Summary of Efficacy Parameter Scores at Baseline, Week 1, and Week 2a | |||||||
| Parameter | Treatment Group | Baseline | Week 1 (mean ± SD) (median) | Week 2 (mean ± SD) (median) | |||
| Erythema | Active (N=36) | 1.11 ± 0.91 1.00 | p = 0.76 | 0.29 ± 0.50 0.00 | pb = 0.0062 | 0.09 ± 0.25 0.00 | pb = 0.0274 |
| Vehicle (N=32) | 1.06 ± 0.84 1.00 | 0.73 ± 0.68 0.87 | 0.50 ± 0.56 0.25 | ||||
| Scaling | Active (N=36) | 1.80 ± 0.51 2.00 | p = 0.608 | 0.92 ± 0.58 1.00 | p = 0.0021 | 0.46 ± 0.49 0.33 | p = 0.0012 |
| Vehicle (N=32) | 1.92 ± 0.72 2.00 | 1.55 ± 0.89 1.87 | 1.06 ± 0.77 1.00 | ||||
| Lichenification | Active (N=36) | 1.92 ± 0.54 2.00 | p = 0.084 | 1.28 ± 0.73 1.00 | p = 0.0027 | 0.84 ± 0.54 1.00 | p = <0.0001 |
| Vehicle (N=32) | 2.23 ± 0.68 2.00 | 1.89 ± 0.79 2.00 | 1.65 ± 0.80 2.00 | ||||
| Pruritus | Active (N=36) | 1.62 ± 0.87 2.00 | p = 0.406 | 0.53 ± 0.64 0.29 | p = 0.0009 | 0.19 ± 0.32 0.00 | p = 0.0001 |
| Vehicle (N=32) | 1.85 ± 0.85 2.00 | 1.23 ± 0.91 1.00 | 0.87 ± 0.86 1.00 | ||||
a Difference in mean values tested by Mann Whitney U test b p-value based on testing differences from baseline.
Except for the parameter erythema, the between group differences at week 1 were significantly in favour of the active group: scaling (p=0.0136); lichenification (p= 0.0057); and pruritus (p=0.0382). These differences remained statistically in favor of the active group at week 2: scaling (p=0.0079); lichenification (p= 0.0085); and pruritus (p=0.0324). The between group differences for erythema at both week 1 and week 2 were numerically in favor of the active group, but were not statistically significant. The lack of significance may be due to the small number of subjects in the analysis.
| Table 10: West Study: Summary of Efficacy Parameter Scores at Baseline, Week 1, and Week 2 | |||||||
| Parameter | Treatment Group | Baseline | Week 1 (mean ± SD) (median) | Week 2 (mean ± SD) (median) | |||
| Erythema | Active (N=36) | 1.46 ± 0.60 1.50 | p = 0.7373 | 1.09 ± 0.61 1.00 | P = 0.1137 | 0.91 ± 0.74 0.75 | p = 0.1578 |
Vehicle (N=32) | 1.49 ± 0.65 1.67 | 1.46 ±0.69 1.33 | 1.37 ± 0.88 1.33 | ||||
| Scaling | Active (N=36) | 1.60 ± 0.61 1.75 | p = 0.7952 | 1.11 ± 0.69 1.00 | P = 0.0136 | 0.93 ± 0.71 0.75 | P = 0.0079 |
Vehicle (N=32) | 1.73 ± 0.42 1.83 | 1.73 ± 0.50 2.00 | 1.68 ± 0.63 2.00 | ||||
| Lichenification | Active (N=36) | 1.34 ± 0.84 1.50 | p = 0.6601 | 1.03 ± 0.55 1.13 | P = 0.0057 | 0.84 ± 0.62 0.75 | P = 0.0085 |
Vehicle (N=32) | 1.63 ± 0.38 1.67 | 1.62 ± 0.39 1.67 | 1.51 ± 0.61 1.75 | ||||
| Pruritus | Active (N=36) | 1.82 ± 0.64 2.00 | p = 0.4195 | 1.05 ± 0.68 1.00 | P = 0.0382 | 0.82 ± 0.71 0.80 | P = 0.0324 |
Vehicle (N=32) | 1.63 ±0.86 1.83 | 1.56 ± 0.73 2.00 | 1.54 ± 0.86 1.83 | ||||
The Global Assessment at Week 1 and Week 2 indicate a statistically significant differences between the active (Derma-Smoothe/FS®) and vehicle groups for disease clearing, in favour of the active group: Week 1 (p=<0. 001) and Week 2 (p=0.003).
| Table 11 East Study: Global Assessment at Week 1 and Week 2 | ||||||||
Treatment Group | Cleared (1) | Excellent (2) | Good (3) | Fair (4) | Slight (5) | No Change (6) | Exacerbation (7) | p-valuea |
| Week 1b | ||||||||
| Active (N=36) | 0 | 10 | 11 | 8 | 5 | 0 | 0 | <0.001 |
| Vehicle (N=32) | 0 | 0 | 5 | 6 | 12 | 5 | 3 | |
| Week 2 b | ||||||||
| Active (N=36) | 4 | 15 | 11 | 1 | 3 | 0 | 1 | 0.003 |
| Vehicle (n=32) | 1 | 3 | 10 | 4 | 13 | 1 | 0 | |
a the p-values represented are those obtained from the chi-square analysis the above matrices, which contain empty cells. A second analysis was performed after coalescing the cleared-excellent-good cells and the slight-no change-exacerbation cells for the above matrices. The p-values were <0.0001 and 0.0014, respectively. bWeek 1: 2 active and 1 vehicle subject had no assessment
Week 2: 1 active subject had no assessment
| Table 12: West Study: Global Assessment at Week 1 and Week 2 | ||||||||
Treatment Group | Cleared (1) | Excellent (2) | Good (3) | Fair (4) | Slight (5) | No Change (6) | Exacerbation (7) | p-valuea |
| Week 1b | ||||||||
| Active (N=13) | 1 | 1 | 6 | 3 | 0 | 0 | 1 | 0.0156 |
| Vehicle (N=13) | 0 | 1 | 0 | 1 | 1 | 4 | 5 | |
| Week 2 b | ||||||||
| Active (N=13) | 1 | 5 | 4 | 0 | 0 | 0 | 1 | 0.065 |
| Vehicle (n=13) | 0 | 1 | 1 | 0 | 1 | 3 | 3 | |
a the p-values represented are those obtained from the chi-square analysis the above matrices, which contain empty cells. A second analysis was performed after coalescing the cleared-excellent-good cells and the slight-no change-exacerbation cells for the above matrices. The p-values were 0.0001 and 0.0018, respectively. bWeek 1: 1 active and 1 vehicle subject had no assessment
Week 2: 2 active and 4 vehicle subjects had no assessment
Study 25-S Open-Label Safety Study on Derma-Smoothe/FS® Topical Oil on Pediatric Patients with Atopic Dermatitis
Study 25-S assessed suppression of the hypothalamic-pituitary-adrenal (HPA) axis in the paediatric population with atopic dermatitis. Twenty-six patients were exposed to Derma-Smoothe/FS® only as part of the open-label study design. Patients were to apply Derma-Smoothe/FS® twice daily for a total of 4 weeks; at the end of 4 weeks cortisol testing was conducted to evaluate HPA axis suppression. Of the 26 subjects who were enrolled, 25 subjects completed the study. Of the 25 who completed the study, only 21 subjects had evaluable cortisol
results. No evidence of suppression of the HPA axis was observed in pediatric patients following treatment with Derma-Smoothe/FS® Topical Oil twice daily for 4 weeks.
Table 13: Cortisol Concentrations (ug/dL) Before and After Adrenal Stimulation: Start of Study and After 4 Weeks of Treatment with Derma-Smoothe/FS® Study 25-S California | |||
At Start of Study (N=11) | After 4 Weeks of Treatment (N=11) | Week 0 vs. Week 4c p valuea | |
| Cortisol Concentration at Baseline (SD)b | 12.09 (3.87) | 10.73 (1.96) | 0.185 |
| Cortisol Concentration Following Stimulation (SD) | 25.30 (3.60) | 24.51 (1.93) | 0.408 |
| Increase in Cortisol After Stimulation | 13.21 (5.00) | 13.78 (2.25) | 0.742 |
a p-value from paired t-test
b Baseline value is value prior to stimulation c Day 28: 7 day post-treatment evaluation
Table 14: Cortisol Concentrations (ug/dL) Before and After Adrenal Stimulation: Start of Study and After 4 Weeks of Treatment with Derma-Smoothe/FS® Study 25-S Chicago, Cleveland, and Miami | |||
At Start of Study (N=10) | After 4 Weeks of Treatment (N=10) | Week 0 vs. Week 4c p valuea | |
| Cortisol Concentration at Baseline (SD)b | 11.00 (3.95) | 11.76 (3.28) | 0.444 |
| Cortisol Concentration Following Stimulation (SD) | 28.84 (6.74) | 26.07 (5.20) | 0.056 |
| Increase in Cortisol After Stimulation | 17.84 (9.67) | 14.28 (5.60) | 0.091 |
a p-value from paired t-test
b Baseline value is value prior to stimulation c Day 28: 7 day post-treatment evaluation
Study 26 HPA Axis Open-Label Safety Study on Derma-Smoothe/FS® on Pediatric Patients with Atopic Dermatitis (2 to 5 years)
A phase 4, open label clinical study was conducted to assess the safety of Derma-Smoothe/FS® Topical Oil used twice daily for 28 days in children 2 years and older with atopic dermatitis. Fifteen subjects between the ages of 2 and 5 were enrolled in Study 26. Of the 15 enrolled, 13 completed the study. No HPA axis suppression was observed following treatment of Derma-Smoothe/FS® Topical Oil.
Table 15: Cortisol Concentrations (ug/dL) Before and After Adrenal Stimulation: Start of Study and After 4 Weeks of Treatment with Derma-Smoothe/FS® Study 26 | |||
At Start of Study (N=13) | After 4 Weeks of Treatment (N=13) | Week 0 vs. Week 4 p valuea | |
| Cortisol Concentration at Baseline (SD)b | 10.73 (5.01) | 9.35 (3.82) | 0.376 |
| Cortisol Concentration Following Stimulation (SD) | 26.12 (2.97) | 24.20 (3.79) | 0.153 |
| Increase in Cortisol After Stimulation | 15.39 (4.81) | 14.85 (3.10) | 0.647 |
a p-value from paired t-test
b Baseline value is value prior to stimulation
Hypersensitivity Safety Study
Chicago Peanut Allergy Study
A phase 4 controlled, open label clinical study was conducted to assess the safety of Derma-Smoothe/FS®, which contains refined peanut oil NF, on subjects with known allergies. The study enrolled 13 patients with atopic dermatitis, 6 to 17 years of age. Of the 13 patients, 9 were Radioallergosorbent Test (RAST) positive to peanuts and 4 had no peanut sensitivity (controls). The study evaluated the responses to both prick test and patch test utilizing refined peanut oil NF, Derma-Smoothe/FS® and histamine/saline controls, on the 13 individuals. These subjects were also treated with Derma-Smoothe/FS® twice daily for 7 days.
Prick test and patch test results for all 13 patients were negative to Derma-Smoothe/FS® and the refined peanut oil NF. One of the 9 peanut-sensitive patients experienced an exacerbation of atopic dermatitis after 5 days of Derma-Smoothe/FS®. Importantly, the bulk peanut oil NF, used in Derma-Smoothe/FS® is heated at 475°F for at least 15 minutes, which should provide for adequate decomposition of allergenic proteins. The peanut oil used in Derma-Smoothe/FS® is tested for residual protein through amino acid analysis; the acceptance criterion for total protein is no more than 0.5 parts per million.
DETAILED PHARMACOLOGY
Like other topical corticosteroids, fluocinolone acetonide has anti-inflammatory, antipruritic, and vasoconstrictive properties. The mechanism of the anti-inflammatory activity of the topical steroids in general is unclear. One factor may be the ability of the glucocorticoids to
inhibit the recruitment of neutrophils and monocyte-macrophages into the affected area. Glucocorticoid also decreases the adherence of neutrophils to nylon fibers, indicating decreased tendency of neutrophils to adhere to capillary endothelial cells in areas of inflammation. Although steroids do not affect the production of macrophage migratory inhibitory factor (MIF), it blocks the effect of MIF on macrophages so that the movements of these cells are no longer restricted hence they do not accumulate locally. Evidence also show that glucocorticoids induce the production of a protein that inhibits phospholipase A2, reducing the release of arachidonic acid from phospholipids, in turn decreasing the formation of prostaglandins, leukotrienes, endoperoxides and thromboxane which plays an important role in chemotaxis and inflammation.
MICROBIOLOGY
Investigative studies showing pharmacokinetic, toxicology and microbiological aspects have not been carried out for Derma-Smoothe/FS®.
TOXICOLOGY
No nonclinical studies were performed to assess the toxicology, genotoxicity, carcinogenicity, reproductive or developmental toxicity, or local tolerance of fluocinolone acetonide or Derma-Smoothe/FS® Topical Oil. However, some corticosteroids are associated with several toxic effects; they are summarized below.
Genotoxicity
Some corticosteroids have been found to be genotoxic in various genotoxicity tests (e.g., the in vitro human peripheral blood lymphocyte chromosome aberration assay with metabolic activation, the in vivo mouse bone marrow micronucleus assay, the Chinese hamster micronucleus test, and the in vitro mouse lymphoma gene mutation assay).
Reproductive and Developmental Toxicity
Corticosteroids have been shown to be teratogenic in laboratory animals when administered systemically at relatively low dosage levels. Some corticosteroids have been shown to be teratogenic after dermal application in laboratory animals. The relationship between corticosteroid use and teratogenicity in humans is unclear.
Local Tolerance
Skin thinning (atrophy) has been shown after fluocinolone acetonide administration on mouse tail epidermis and on the dorsal skin of hairless dogs. This activity may correlate with the activity of fluocinolone acetonide in treating atopic dermatitis.
REFERENCES
- 1. Balow JE. Glucocorticoid suppression of macrophage migration inhibitory factor. J. Exp. Med. 1973; 137(4): 1031-41
- 2. Blackwell GJ. Macrocortin: a polypeptide causing the anti-phospholipase effect of glucocorticoids. Nature 1980; 287(5778):147-9.
- 3. Carmichael SL, Shaw GM. Maternal corticosteroid use and risk of selected congenital anomalies. Am J Med Genet 1999; 86:242-4.
- 4.
Fauci AS. Immunosupressive and anti-inflammatory effects of glucocorticoids.
Monographs on Endocrinology 1979; 12:449-65.
- 5. Goa KL. Clinical pharmacology and pharmacokinetic properties of topically applied corticosteroids. A review. Drugs 1988; 36:51-61.
- 6. Hirata F. A phospholipase A2 inhibitory protein in rabbit neutrophils induced by glucocorticoids. Proc Natl Acad Sci USA 1980; 77(5): 2533-6.
- 7. Kimura T, Doi K. Dorsal skin reactions of hairless dogs to topical treatment with corticosteroids. Toxicol Pathol 1999; 27:528-35.
- 8. McKenzie AW, Stoughton RB. Method for comparing percutaneous absorption of steroids. Arch Dermatol 1962; 86:608-10.
- 9. Schimmer BP, Parker KL. Adrenocorticotropic hormone; adrenocortical steroids and their synthetic analogs; inhibitors of the synthesis and actions of adrenocortical hormones. In Goodman & Gilman’s the pharmacological basis of therapeutics. New York: The Mc Graw-Hill Companies; 2001. p. 1649-77.
- 10.
Spearman RIC, Jarrett A. Bio-assay of corticosteroids for topical application.
Br J Dermatol 1975; 92:581-4.
- 11.
Stoughton RB. Vasoconstrictor assay-specific applications. In: Maibach HI,
Surber C (eds). Topical corticosteroids. Basel: S Karger AG; 1992. p. 42-52.
- 12. Wester RC, Bucks DAW, Maibach HI. In vivo percutaneous absorption of hydrocortisone in psoriatic patients and normal volunteers. J Amer Acad Dermatol 1983; 8:645-7.
- 13. Wester RC, Maibach HI. Cutaneous pharmacokinetics: 10 steps to percutaneous absorption. Drug Metab Rev 1983; 14:169-205.
- 14.
Gilman AG, Goodman LS, Rall TW, Murad F (eds). Pharmacological Basis of
Therapeutics. 7th ed. New York: Macmillan Publishing Company; 1985.
- 15.
Maibach HI, Surber C (eds). Topical corticosteroids. Basel: S Karger AG;
1992.
- 16. Nikolovski J, Stamatas GN, Kollias N, Wiegand BC. Barrier function and water-holding and transport properties of infant statum corneum are different from adult and continue to develop through the first year of life. J InvestDermatol 2008;128:1728-1736.