


Product Monograph - Synalar (Bausch Health, Canada, 0.01 %)
ADVERSE REACTIONS
The following adverse skin reactions have been reported with the use of topical steroids: dryness, burning itching, local irritation, striae, skin atrophy, atrophy of subcutaneous tissues, telangiectasia, hypertrichosis change in pigmentation and secondary infection.
Adrenal suppression has also been reported following topical corticosteroid therapy. Posterior subcapsular cataracts have been reported following systemic use of corticosteroids.
TREATMENT OF OVERDOSAGE
There is no specific antidote, but gastric lavage should be performed. In case of hypercorticism and/ or adrenal suppression, discontinue therapy.
DOSAGE AND ADMINISTRATION
SYNALAR ointments are suitable when an emollient effect is desired.
A small amount of SYNALAR ointments 0.025% should be applied gently on the affected skin area, 2 or 3 times daily, as needed.
SYNALAR topical solution, 0.01% should be applied to the affected area as thin skin, from 2 to 4 times daily, depending on the severity of the condition. On hairy sites, the hair should be parted to allow direct contact with the lesion.
It is recommended that SYNALAR ointment or solution not be used under occlusive conditions.
AVAILABILITY
SYNALAR ointment 0.025% is available in 60g collapsible tubes.
SYNALAR topical solution 0.01% is available in 60 ml plastic squeeze bottles.
Store at room temperature, 15°C - 30°C.
CHEMISTRY
Chemical name: 6a, 9a-difluoro-16-hydroxyprednisolone-16, 17-acetonide.
Structural formula:
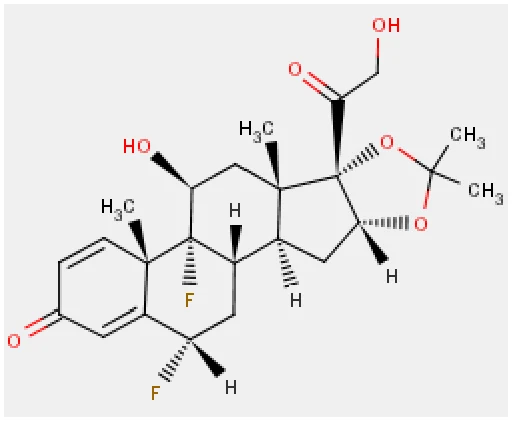
Molecular formula: C24 H30 F2 O6
Molecular weight: 452.48 g/mol
Physicochemical Properties
Description: Fluocinolone acetonide, the active ingredient in SYNALAR, is a chemical modification of prednisolone and occurs as a white to creamy-white crystalline powder. It is odorless and stable in air.
Melting Point: Melting range between 268°C - 280°C.
PHARMACOLOGY
SYNALAR (fluocinolone acetonide) is a chemical modification of prednisolone which possesses greater anti-inflammatory and gluconeogenic properties than the parent compound when compared on an equivalent basis.
Fluocinolone acetonide has been reported to posses 263 times the glucocorticoid activity of cortisol (hydrocortisone) as measured by the thymolitic activity assay in the rat; 446 times assay in the rat; 446 times that of cortisol in the antigranuloma activity assay in the rat; and also in the same animal 138 times that of cortisol in the liver glycogen deposition assay.
In similar test in rats, data indicated that fluocinolone acetonide has 500 times the glucocorticoid activity of cortisol (hydrocortisone) as measured by the thymolitic and antigranuloma activity assays. Fluocinolone acetonide showed minimal effects on sodium and potassium excretion as studied in the adrenalectomized rat.
CLINICAL PHARMACOLOGY
The vasoconstrictor activity assay has been used to estimate the anti-inflammatory potential of topical corticosteroids in humans. In this assay fluocinolone acetonide showed 100 times the activity of hydrocortisone acetate.
It was shown by Holden & Adams (1959) and by Ruhman & Berliner (1965) that corticosteroids inhibit fibroblast growth and by Dougherty & Berliner that fibroblasts are directly involved in the inflammatory process. In the fibroblast inhibitory effect on fibroblast multiplication in a tissue culture system, fluocinolone acetonide was 440 times more potent than cortisol (hydrocortisone).
Corticosteroids stabilize lysosomal membranes, thus preventing the liberation of digestive and lytic enzymes which are released in response to certain noxious stimuli. It has been suggested that this protective effect of corticoids may be a basis for their therapeutic action.
Orally, as measured by the oesinopenic assay in man, fluocinolone acetonide is equipotent to prednisolone. Administered intravenously, it is more potent than prednisolone on a mg/mg basis.
The effect of oral fluocinolone acetonide in the suppression of the standard croton oil inflammatory insult assay was assessed in human volunteers. In 5 subjects, triamcinolone was consistently more potent than fluocinolone acetonide. In 4 of 6 subjects, fluocinolone acetonide did have an anti-inflammatory effect exceeding that of a control placebo, but in 2 of 6 subjects it was equal to the control. Utilizing stable strontium as a tracer for studying calcium metabolism in man, it was found that fluocinolone acetonide had a negligible effect. In human subjects 20mg of fluocinolone acetonide per os per day 18-24 days produced a negative nitrogen balance and parallel weight loss. At this dose level there was no effect on calcium balance nor on the excretion of 17-hydroxycorticosteroids or 17-ketosteroids.
Pharmacokinetics
The extent of percutaneous absorption of topical corticosteroids is determined by many factors including the vehicle, and the integrity of the epidermal barrier.
Topical corticosteroids can be absorbed from normal intact skin. Inflammation and/ or other disease processes in the skin increase percutaneous absorption.
Once absorbed through the skin, topical corticosteroids are handled through pharmacokinetic pathways similar to systemically administered corticosteroids. Corticosteroids are bound to plasma proteins in varying degrees. They are metabolized primarily in the liver and are then excreted by the kidneys. Some of the topical corticosteroids and their metabolites are also excreted into the bile.
Human systemic absorption studies have been conducted by various researchers. McNall and Melby (data on file) have studied the effect of applying large amounts of fluocinolone acetonide cream 30-60g /day (7.5 to 15mg of active material) to the skin of normal subjects and one patient with severe exfoliative dermatitis. In the normal patients, urine volume, sodium and potassium excretions were also measured in addition to the 17-ketosteroids and 17-hydroxycorticosteroids.
No abnormal values were reported. In a similar study, Myerson (1964) reported that there were no appreciable changes in these parameters which could be attributed to absorption of fluocinolone acetonide.
Absorption studies utilizing fluocinolone acetonide cream 0.2% in quantities of 2 to 3 g per day with occlusion (4 to 6 mg of active material) have failed to show any evidence of corticosteroid effect. Additional studies utilizing fluocinolone acetonide cream 0.2% in quantities of 10 g per day without occlusion have also shown no evidence of corticosteroid effect.
Transient suppression of adrenal activity has been noted after application of corticosteroids to moderately large body areas under occlusive therapy. The adrenal suppression depends on several factors: percentage of body surface treated, concentration of the corticosteroid in the topical preparation, and most important, the integrity of the skin barrier. The adrenals apparently revert to normal function within 48 hours after cessation of therapy.
Administered orally, clinical evaluation of fluocinolone acetonide resulted in a surprisingly variable response in patients with corticosteroid responsive disease. Most investigators found it to be effective and about equipotent to prednisolone but in at least one group of patients with rheumatic disease previously shown to be corticoid responsive there was negligible benefit in 11 of 18 subjects from administered doses of up to 8 mg per day.
SYNALAR (fluocinolone acetonide) used topically has been shown to be an effective agent in the treatment of inflammatory and pruritic dermatoses. It is significantly more effective than hydrocortisone, and in many instances, was effective when other available topical corticosteroids gave inadequate therapeutic responses.
CLINICAL STUDIES
The efficacy of fluocinolone acetonide, the active ingredient in SYNALAR, is well documented in over 4,000 patients for the indications listed below. Table I summarizes some of the representative accumulated clinical data.
Table I
No. of publications | No. of patients | Significant Improvement** | |||||||
| contact dermatitis | 27 | 750 | 713 | ||||||
| eczematous dermatitis | 21 | 472 | 409 | ||||||
| seborrheic dermatitis | 18 | 442 | 426 | ||||||
| atopic dermatitis | 24 | 460 | 426 | ||||||
| psoriasis | 36 | 1699 | 1510 | ||||||
| neurodermatitis | 18 | 351 | 324 | ||||||
| TOTAL | 144 | 4174 | 3808 | ||||||
**Expressed by authors as excellent, very good, good, improved, complete remission of inflammation, etc.
TOXICOLOGY
Acute toxicity studies with fluocinolone acetonide, the active ingredient in SYNALAR, have been done in rats, cats, and dogs. In rats, the LD50 intraperitoneal dose ranged from 79 mg/kg to 126 mg/kg. Administered orally, the LD50 dose was 1000 mg/kg. Administered orally, the LD50 in cats and dogs is greater than 1 g/kg. Subacute toxicity studies with fluocinolone acetonide have been done in monkeys. Six months of oral administration of fluocinolone acetonide to monkeys resulted in no significant deviation from control observations except for weight loss at the high dosages. The dosage was 0.5 mg/kg for 14 weeks with an increase to 2 mg/kg for the remainder of the six months.
Fluocinolone acetonide applied topically in rabbits at a dose of 2 g/kg body weight over a 13-week period produced weight loss and slight decrease in the size of adrenals. Ten human adult males received per os 4 mg of fluocinolone acetonide daily for 90 days. Complete blood counts, urinalysis, liver function tests, serum sodium, potassium, calcium and stool examinations were done during the control period, at 45 and 90 days. No significant alterations of these parameters from control levels were noted.
No significant eye irritation was observed in rabbits during a 15-day period in which 0.1ml of either the vehicle of fluocinolone acetonide ophthalmic solution with antibiotics or the vehicle without antibiotics was instilled twice daily into eyes of rabbits. Daily doses of fluocinolone acetonide ranging from 0.062 to 0.083 mg/kg/day delivered by nasal spray to rabbits for 24 consecutive days produced no significant gross pathology of the respiratory tract.
BIBLIOGRAPHY
- 1. Berliner, D.L. and Rhumann, A. G. (1967) Influence of steroids on fibroblasts. I. An in vitro fibroblast assay for corticosteroids. J. Invest. Derm. 49: 117-122
- 2. Chann, M.M. and Levy, E.J. (1961) Fluocinolone acetonide, a new topical corticosteroid: clinical and pharmacologic evaluation. J. New Drugs 1:262-267
- 3. Dougherty, T.F. and Berliner D. Film: A new view of corticosteroid action in inflammatory dermatoses produced by Syntex Labs, Inc. - Palo Alto, CA
- 4. Deumling, W.W. (1965) The effects of propylene glycol solution of fluocinolone acetonide cream. Clin.Med.72: 1167-1171
- 5. Holden, M. and Adams, L.B. (1957) Inhibitory effects of cortisone acetate and hydrocortisone on growth of fibroblasts. Kanee, B. (1963)
- 6. Clinical studies with topical fluocinolone acetonide in the treatment of various dermatoses. Can. Med. Assn. J. 88: 999-1003
- 7. Lerner, L.J., et al (1964) Anti-inflammatory steroids: potency, duration and modification of activities. Ann. N.Y. Acad. Sci. 116: 1071-1077
- 8. London, D.R. (1968) The corticosteroids. Practitioner 200: 113-120
- 9. March, C., et al (1965) Adrenal function after topical steroid therapy. Clin. Pharmacol. Ther. 6: 43-49
- 10. McKenzie, A.W. (1962) Percutaneous absorption of steroids. Arch. Derm. 86:611-614
- 11. Meenan, F.O. (1963) The treatment of infantile eczema with fluocinolone acetonide cream. J. Irish Med.Assn.52: 75-76
- 12. Myerson, R.M. (1984) The effect of topical fluocinolone acetonide and nearly total body occlusive dressings on the urinary excretion of nitrogen, sodium, potassium, 17-ketosteroids and 17- hydroxysteroids. Amer. J. Med. Sci. 248: 441-444
- 13. Robinson, H.M., et al (1962) Topical therapy with fluocinolone acetonide. Bull. Sch. Med. Univ. of Maryland, 47: 21-24
- 14. Rhumann, A.G. and Berliner, D.L. (1965) Effect of steroids on growth of mouse fibroblasts in vitro. Endocrinology 76: 916-927
- 15. Sawyer, W.C. (1962) Treatment of resistant eczematous dermatoses with a new compound, fluocinolone acetonide. Ann. Allergy 20: 330-331
- 16. Scher, R.K. (1961) Treatment of refractory dermatoses with fluocinolone acetonide. Curr. Ther. Res. 3: 461-464
- 17. Scholtz, J.R. (1961) A new corticosteroid for topical therapy - fluocinolone acetonide. Calif. Med. 95: 224-226
- 18. Scholtz, J.R. and Nelson, D.H. (1965) Some quantitative factors in topical corticosteroid therapy. Clin. Pharmacol. Ther. 6: 498-509
- 19. Scoggins, R.B. and Kliman, B. (1965) Percutaneous absorption of corticosteroids. New Eng. J. Med. 273: 831-840