


Product Monograph - Prevex B
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Topical Use | Cream,0.1% w/w | For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING section. |
INDICATIONS AND CLINICAL USE
PREVEX® B (betamethasone valerate USP) Cream is a potent topical corticosteroid indicated for the relief of the inflammatory and pruritic manifestations of steroid responsive dermatoses for a maximum duration of 4 weeks in patients 1 year of age and older.
Geriatrics (> 65 years of age): Safety and effectiveness of PREVEX® B Cream in geriatric patients over 65 years of age have not been established. Some published studies of 0.1% betamethasone valerate creams have reported that clinical outcomes in geriatric patients over 65 years of age were consistent with those of the general adult population (see WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics (> 65 years of age)).
Pediatrics (<18 years of age): PREVEX® B Cream should not be used in pediatric patients less than 1 year of age (see CONTRAINDICATIONS). Safety and effectiveness of PREVEX® B Cream in pediatric patients less than 18 years of age have not been established. Some published studies of 0.1% betamethasone valerate creams have reported that clinical outcomes in pediatric patients more than 1 year and less than 18 years of age were consistent with those of the general adult population (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics (<18 years of age)).
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the PRESCRIBING INFORMATION.
- Patients who are hypersensitive to other corticosteroids.
- Dermatoses in infants under one year of age, including dermatitis.
- Patients with viral (e.g. herpes or varicella) lesions of the skin, bacterial or fungal skin infections, parasitic infections, skin manifestations relating to tuberculosis or syphilis, eruptions following vaccinations.
- Patients with rosacea.
- Patients with acne vulgaris.
- Patients with pruritus without inflammation.
- Patients with perianal and genital pruritus.
- Patients with perioral dermatitis.
- Topical application to the eye.
WARNINGS AND PRECAUTIONS
General
Patients should be advised to inform subsequent physicians of the prior use of corticosteroids.
PREVEX® B Cream should not be used under occlusion due to increased risk of systemic exposure and infection. When used under occlusive dressing, over extensive areas, or on the face, scalp, axillae, or scrotum, sufficient absorption may occur to result in adrenal suppression and other systemic effects (see WARNINGS AND PRECAUTIONS – Endocrine and Metabolism, Immune and Ophthalmologic).
Cardiovascular
Suitable precautions should be taken when using topical corticosteroids in patients with stasis dermatitis and other skin diseases with impaired circulation.
Use of corticosteroids around chronic leg ulcers may be associated with a higher occurrence of local hypersensitivity reactions and an increased risk of local infection.
Endocrine and Metabolism
Systemic absorption of topical corticosteroids has produced reversible hypothalamic-pituitary-adrenal (HPA) axis suppression, manifestations of Cushing’s syndrome, hyperglycemia, and glucosuria in some patients.
Conditions which augment systemic absorption include the formulation and potency of the topical corticosteroid, the application of topical corticosteroids over large body surface areas, application to intertriginous areas (such as the axillae), frequency of application, prolonged use, or the addition of occlusive dressings. Other risk factors for increased systemic effects include increasing hydration of the stratum corneum, use on thin skin areas (such as the face), and use on broken skin or in conditions where the skin barrier may be impaired.
If patients must be treated over large body surface areas, they should be evaluated periodically for evidence of HPA axis suppression (see WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests). If HPA axis suppression is noted, an attempt should be made to withdraw the drug by reducing the frequency of application. Abrupt withdrawal of treatment may result in glucocorticosteroid insufficiency (see OVERDOSAGE).
Recovery of HPA axis function is generally prompt upon discontinuation of topical corticosteroids. Infrequently, signs and symptoms of glucocorticosteroid insufficiency may occur requiring supplemental systemic corticosteroids. For information on systemic corticosteroid supplementation, see the prescribing information for those products.
Pediatric patients may absorb larger amounts of topical corticosteroids and thus be more susceptible to systemic toxicity from equivalent doses because of their larger skin surface to body mass ratios as compared with adult patients (see WARNINGS AND PRECAUTIONS – Special Populations, Pediatrics).
Immune
Topical corticosteroids may increase the risk of infections including aggravation of cutaneous infection, masked infection and secondary infections. In particular, bacterial infection is encouraged by the warm, moist conditions within skin-fold areas, or caused by occlusive dressings. If concomitant skin infections develop PREVEX® B Cream should be discontinued and antimicrobial therapy should be administered.
Ophthalmologic
Topical corticosteroids should be used with caution on lesions close to the eye because systemic absorption may cause increased intraocular pressure, glaucoma, or cataracts.
Sensitivity
Local hypersensitivity reactions (see ADVERSE REACTIONS) may resemble symptoms of the condition under treatment. If hypersensitivity reactions occur, the drug should be discontinued and appropriate therapy should be initiated.
Allergic contact dermatitis with corticosteroids is usually diagnosed by observing a failure to heal rather than noticing a clinical exacerbation. Such an observation should be corroborated with appropriate diagnostic patch testing.
Skin
Topical corticosteroids should be used with caution in psoriasis as rebound relapses, development of tolerances, risk of generalised pustular psoriasis, and development of local or systemic toxicity due to impaired barrier function of the skin have been reported in some cases. If used in psoriasis careful patient supervision is important.
If significant irritation develops, PREVEX® B Cream should be discontinued and appropriate therapy should be instituted.
Prolonged use of topical corticosteroid preparations may produce striae or atrophy of the skin or subcutaneous tissue. Topical corticosteroids should be used with caution on lesions of the face, groin, and axillae as these areas are more prone to atrophic changes than other areas of the body. Frequent observation is important if these areas are to be treated. If skin atrophy is observed, treatment should be discontinued.
Special Populations
Pregnant Women: There are limited data for the use of betamethasone valerate in pregnant women.
Topical administration of corticosteroids to pregnant animals can cause abnormalities of fetal development (see TOXICOLOGY). Subcutaneous administration of betamethasone valerate to mice or rats at doses of ≥0.1 mg/kg/day, or to rabbits at doses of ≥12 micrograms/kg/day during pregnancy produced fetal abnormalities including cleft palate. The relevance of this finding to humans has not been established.
There are no adequate and well-controlled studies of PREVEX® B Cream in pregnant women. Administration of PREVEX® B Cream during pregnancy should only be considered if the expected benefit to the mother outweighs the potential risk to the fetus. The minimum quantity should be used for the minimum duration.
Fertility: There are no data in humans to evaluate the effect of topical corticosteroids on fertility.
Nursing Women: The safe use of topical corticosteroids during lactation has not been established.
Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects.It is not known whether topical administration of corticosteroids could result in sufficient systemic absorption to produce detectable quantities in human breast milk.
Because many drugs are excreted in human milk, caution should be exercised when PREVEX® B Cream is administered to a nursing woman. Administration of PREVEX®
B Cream during lactation should only be considered if the expected benefit to the mother outweighs the risk to the infant.
If used during lactation, PREVEX® B Cream should not be applied to the breasts to avoid accidental ingestion by the infant.
Pediatrics (< 18 years of age): The safety of PREVEX® B Cream has not been studied in pediatric patients. PREVEX® B Cream should not be used in patients less than 1 year of age (see CONTRAINDICATIONS).
Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of HPA axis suppression and Cushing’s syndrome when they are treated with topical corticosteroids. They are therefore also at greater risk of adrenal insufficiency during and/or after withdrawal of treatment.
Adverse effects including striae have been reported with the use of topical corticosteroids in infants and children. HPA axis suppression, Cushing’s syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in children receiving topical corticosteroids. Manifestations of adrenal suppression in children include low plasma cortisol levels and an absence of response to ACTH stimulation. Manifestations of intracranial hypertension include bulging fontanelles, headaches, and bilateral papilledema. Chronic corticosteroid therapy may interfere with the growth and development of children.
There are no adequate and well-controlled studies of PREVEX® B Cream in pediatric patients. Some published studies of 0.1% betamethasone valerate creams have reported that clinical outcomes in pediatric patients more than 1 year and less than 18 years of age were consistent with those of the general adult population.1, 2, 3, 4, 5 Administration of topical corticosteroids to children under 18 years of age should be limited to the least amount and for the shortest duration compatible with an effective therapeutic regimen (see DOSAGE AND ADMINISTRATION).
Geriatrics (> 65 years of age): The safety of PREVEX® B Cream has not been studied in geriatric patients.
In general, topical corticosteroids should be used cautiously in elderly patients, reflecting their increased skin fragility and greater frequency of hepatic, renal, or cardiac dysfunction, and of concomitant disease or other drug therapy. The greater frequency of decreased hepatic or renal function in the elderly may delay elimination if systemic absorption occurs.
There are no adequate and well-controlled studies of PREVEX® B Cream in geriatric patients. Some published studies of 0.1% betamethasone valerate creams have reported that clinical outcomes in geriatric patients over 65 years of age were consistent with those of the general adult population.1, 2, 4 For geriatric patients over 65 years of age, the minimum quantity should be used for the minimum duration (see DOSAGE AND ADMINISTRATION).
Patients with renal / hepatic impairment: The safety of PREVEX® B Cream has not been studied in patients with renal or hepatic impairment.
In case of systemic absorption, metabolism and elimination may be delayed leading to increased risk of systemic toxicity.
There are no adequate and well controlled studies of PREVEX® B Cream in patients with renal or hepatic impairment. For patients with renal or hepatic impairment, the minimum quantity should be used for the minimum duration (see DOSAGE AND ADMINISTRATION).
Monitoring and Laboratory Test
The cosyntropin (ACTH 1-24) stimulation test may be helpful in evaluating patients for HPA axis suppression.
ADVERSE REACTIONS
Post-Marketing Adverse Drug Reactions
The following adverse reactions have been identified during post-approval use of PREVEX® B Cream. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Endocrine Disorders: Hypothalamic-pituitary adrenal (HPA) axis suppression, cushingoid features (e.g. moon face, central obesity), delayed weight gain/growth retardation in children, osteoporosis, hyperglycemia/glucosuria, hypertension, increased weight/obesity, and decreased endogenous cortisol levels.
Eye Disorders: Glaucoma, cataract.
General Disorders and Administration Site Conditions: Application site irritation/pain.
Immune System Disorders: Local hypersensitivity.
Infections and Infestations: Opportunistic infection.
Skin and Subcutaneous Tissue Disorders: Pruritus, local skin burning /skin pain, allergic contact dermatitis/dermatitis, erythema, rash, urticaria, pustular psoriasis, skin thinning*/skin atrophy*, skin wrinkling*, skin dryness*, striae*, telangiectasias*, pigmentation changes*, hypertrichosis, exacerbation of underlying symptoms, alopecia, and trichorrhexis.
*Skin features secondary to local and/or systemic effects of hypothalamic-pituitary adrenal (HPA) axis suppression.
DRUG INTERACTIONS
Overview
No clinical trials were specifically designed to assess potential drug-drug, drug-food, drug-herb, or drug-laboratory interactions with PREVEX® B Cream.
Co-administered drugs that can inhibit CYP3A4 (e.g. ritonavir, itraconazole) have been shown to inhibit the metabolism of corticosteroids leading to increased systemic exposure. The extent to which this interaction is clinically relevant depends on the dose and route of administration of the corticosteroids and the potency of the CYP3A4 inhibitor.
Drug-Drug Interactions
Interactions with other drugs have not been established.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Patients/caregivers should be instructed to use the minimum quantity of PREVEX® B Cream for the shortest duration of time necessary to achieve the desired therapeutic benefit because of the potential for corticosteroids to suppress the HPA axis and cause skin atrophy (see WARNINGS AND PRECAUTIONS).
- If the condition worsens or does not improve within 2-4 weeks, treatment and diagnosis should be re-evaluated.
- PREVEX® B Cream is for topical use only and not for ophthalmic use.
- PREVEX® B Cream is contraindicated in children under one year of age (see CONTRAINDICATIONS). Pediatric patients are more likely to develop local and systemic toxicity from equivalent doses of topical corticosteroids because of their larger skin surface to body weight ratios and, in general, require shorter courses of treatment and less potent agents than adults.
- Geriatric patients may be more susceptible to percutaneous absorption and the potential effects of systemic absorption. The greater frequency of decreased hepatic or renal function in the elderly may delay elimination if systemic absorption occurs.
Recommended Dose and Dosage Adjustment
Apply thinly and gently rub in using only enough to cover the affected area once or twice daily for a maximum of 4 weeks. If the condition worsens or does not improve within 2-4 weeks, treatment and diagnosis should be re-evaluated. Allow adequate time for absorption after each application before applying an emollient.
Avoid abrupt discontinuation of PREVEX® B therapy once control is achieved as rebound of pre-existing dermatoses can occur. Continue an emollient as maintenance therapy.
Pediatrics (< 18 years of age): PREVEX® B Cream is contraindicated in children under one year of age. In older children, care should be taken when using PREVEX® B Cream. The minimum quantity should be used for the shortest duration to achieve the desired therapeutic benefit (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS — Special Populations, Pediatrics (< 18 years of age)).
Geriatrics (> 65 years of age): PREVEX® B Cream should be used with caution in geriatric patients due to increased risk of renal or hepatic impairment in this population. The minimum quantity should be used for the shortest duration to achieve the desired therapeutic benefit (see WARNINGS AND PRECAUTIONS — Special Populations, Geriatrics (> 65 years of age)).
Renal/Hepatic Impairment: In patients with renal or hepatic impairment, the minimum quantity should be used for the shortest duration to achieve the desired therapeutic benefit (see WARNINGS AND PRECAUTIONS — Special Populations, Patients with renal / hepatic impairment).
Missed Dose
In the event of a missed dose, PREVEX® B Cream should be applied as soon as possible after the missed dose is remembered. If this is close to the scheduled application time or the next dose, the patient should wait and apply the next scheduled dose. The usual schedule should be resumed thereafter.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
Topically applied corticosteroids can be absorbed in sufficient amounts to produce systemic effects (see WARNINGS and PRECAUTIONS). In the event of overdose or misuse, the features of hypercortisolism may occur (see ADVERSE REACTIONS).
Excessive prolonged use or misuses may suppress hypothalamic-pituitary-adrenal (HPA) axis function, resulting in secondary adrenal insufficiency. If symptoms of HPA axis suppression occur, betamethasone valerate should be withdrawn gradually by reducing the frequency of application, or by substituting a less potent corticosteroid because of the risk of glucocorticosteroid insufficiency. Further management should be as clinically indicated. If toxic effects occur, PREVEX® B Cream should be discontinued and symptomatic therapy should be administered.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
PREVEX® B Cream belongs to a class of topical drugs called topical corticosteroids. It is considered to be a potent corticosteroid. Topical corticosteroids share anti-inflammatory, antipruritic and vasoconstrictive actions. The mechanism of anti-inflammatory activity of topical corticosteroids is unclear. However, corticosteroids are thought to act by the induction of phospholipase A2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation such as prostagladins and leukotrienes by inhibiting the release of their common precursor arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A2.
Pharmacodynamics
The pharmacodynamics of PREVEX® B Cream have not been specifically investigated in any clinical studies. Topical corticosteroids have anti-inflammatory, antipruritic, and vasoconstrictive properties.
Pharmacokinetics
The pharmacokinetics of PREVEX® B Cream (absorption, distribution, excretion, and metabolism) have not been specifically investigated in any clinical studies. Pharmacokinetic properties of the drug class of topically applied corticosteroids remain incompletely understood.
Absorption: Topical corticosteroids can be systemically absorbed from intact healthy skin. The extent of percutaneous absorption of topical corticosteroids is determined by many factors, including the product formulation, potency, vehicle, frequency and duration of application, as well as the integrity of the epidermal barrier, skin thickness, application to intertriginous areas (such as the axillae) and to large skin surface areas. Occlusion, hydration of the stratum corneum, inflammation and/or other disease processes in the skin may also increase percutaneous absorption.
Distribution: The use of pharmacodynamic endpoints for assessing the systemic exposure of topical corticosteroids is necessary because circulating levels are well below the level of detection.
Metabolism: Once absorbed through the skin, topical corticosteroids are handled through pharmacokinetic pathways similar to systemically administered corticosteroids. They are primarily metabolised in the liver.
Excretion: Topical corticosteroids are excreted by the kidneys. In addition, some corticosteroids and their metabolites are also excreted in the bile.
STORAGE AND STABILITY
Store between 15-25 C. Do not freeze. Keep out of the reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each gram of PREVEX® B Cream contains 1.22 mg betamethasone valerate USP as the medicinal ingredient, equivalent to 1 mg (0.1% w/w) betamethasone and the following non-medicinal ingredients: petrolatum, dimethicone, trisiloxane, and microcrystalline wax.
PREVEX® B 0.1% Cream is available in 2 g sample tubes or 30 g trade tubes.
REFERENCES
- 1. Almeyda J, Burt BW. Double blind controlled study of treatment of atopic eczema with a preparation of hydrocortisone in a new drug delivery system versus betamethasone 17-valerate. Br J Dermatol. 1974; 91(5):579-83.
- 2. Ashton RE, Catterall M, Morley N, Fairris G, Joesph DN. A double-blind comparison of 0.25% and 0.05% desoxymethasone, 0.1% betamethasone valerate and 1% hydrocortisone creams in the treatment of eczema. J Int Med Res. 1987; 15(3):160-6.
- 3. Khan SA, Williamson DM. A double-blind comparison of 1% hydrocortisone plus 10% urea ('Alphaderm') and 0.1% betamethasone 17-valerate in the treatment of non-infective inflammatory dermatoses. Curr Med Res Opin. 1978;5(4):354-8.
- 4. Singapore Lichen Planus Study Group. A randomized controlled trial to compare calcipotriol with betamethasone valerate for the treatment of cutaneous lichen planus. J Dermatolog Treat. 2004;15(3):141-5.
- 5. Thomas KS, Armstrong S, Avery A, Li Wan Po A, O’Neill C, Young S, et al. Randomised controlled trial of short bursts of a potent topical corticosteroid versus prolonged use of a mild preparation for children with mild or moderate atopic eczema. BMJ. 2002;324(7340):768.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Betamethasone valerate
Chemical name: 9-fluoro-11ß,17, 21-trihydroxy-16ß-methylpregna-1, 4-diene-3, 20-dione 17-valerate
Molecular formula and molecular mass: C27H37FO6
Molecular mass: 476.58
Structural formula: 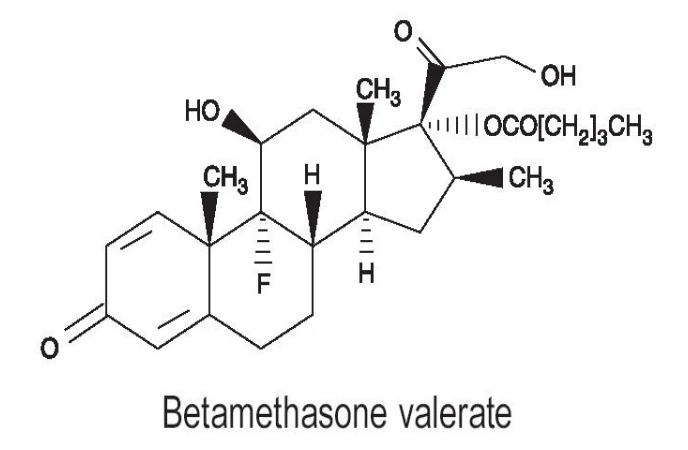
Physicochemical properties: Betamethasone valerate is a white to practically white, odourless crystalline powder, and is practically insoluble in water, freely soluble in acetone and in chloroform, soluble in alcohol, and slightly soluble in benzene and in ether.
TOXICOLOGY
Carcinogenesis
Long-term animal studies have not been performed to evaluate the carcinogenic potential of betamethasone valerate.
Genotoxicity
No specific studies have been conducted to investigate the genotoxic potential of betamethasone valerate.
Fertility
The effect on fertility of betamethasone valerate has not been evaluated in animals.
Pregnancy
Subcutaneous administration of betamethasone valerate to mice or rats at doses of ≥0.1 mg/kg/day, or to rabbits at doses of ≥12 micrograms/kg/day during pregnancy produced fetal abnormalities including cleft palate.