


Product Monograph - Dilaudid (Purdue Pharma, 250 mg, 20 mg, 50 mg)
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Intramuscular, Intravenous, Subcutaneous | Sterile Solution for Injection / 10 mg/mL | Citric acid, sodium citrate in water for injection |
| Sterile Solution for Injection / 20 mg/mL | Citric acid, sodium citrate in water for injection | |
| Sterile Solution for Injection / 50 mg/mL | Citric acid, sodium citrate in water for injection | |
| Sterile Powder for Injection / 250 mg/vial | Diluted in sterile water for injection, 0.9% sodium chloride or 5% dextrose |
INDICATIONS AND CLINICAL USE
Adults:
DILAUDID-HP®, DILAUDID-HP-PLUS®, DILAUDID-XP® and Reconstituted DILAUDID®
Sterile Powder (HYDROmorphone hydrochloride) are indicated exclusively for the relief of severe pain in patients who require subcutaneously, intravenously or intramuscularly administered opioids in doses or concentrations higher than those usually needed. Because HYDROmorphone is highly soluble, a smaller injection volume can be used and discomfort associated with the intramuscular or subcutaneous injection of larger volumes of solution can be minimized.
DILAUDID® STERILE POWDER Prescribing Information
Geriatrics (> 65 years of age):
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION).
Pediatrics (< 18 years of age):
The safety and efficacy of DILAUDID has not been studied in the pediatric population. Therefore the use of DILAUDID is not recommended in patients under 18 years of age.
CONTRAINDICATIONS
High concentration DILAUDID® preparations (HYDROmorphone hydrochloride) are contraindicated in:
- Patients who are not already receiving high doses or high concentrations of opioids.
Patients who are hypersensitive to the active substances (HYDROmorphone) or other opioid analgesics or to any ingredient in the formulation. For a complete listing, see the DOSAGE
FORMS, COMPOSITION AND PACKAGING section of the Prescribing Information.
- In patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction, strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type).
- Patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis).
- Patients with mild pain that can be managed with other pain medications.
- Patients with acute asthma or other obstructive airway, and status asthmaticus.
- Patients with acute respiratory depression, elevated carbon dioxide levels in the blood and cor pulmonale.
- Patients with acute alcoholism, delirium tremens, and convulsive disorders.
- Patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury.
- Patients taking concomitant monoamine oxidase (MAO) inhibitors (or within 14 days of such therapy).
DILAUDID® STERILE POWDER Prescribing Information
- Women who are breast-feeding, pregnant, or during labour and delivery.
WARNINGS AND PRECAUTIONS
General
Where high concentration HYDROmorphone preparations are indicated; the patient is presumed to be receiving an opioid to which tolerance has developed and the initial dose of HYDROmorphone selected, should therefore be estimated on the basis of the relative potency of HYDROmorphone and the opioid previously used by the patient (See DOSAGE AND ADMINISTRATION).
In diseases, such as malignant cancers, where pain control is the primary focus opioid administration at very high doses is associated with seizures and myoclonus.
Hyperalgesia that will not respond to a further dose increase of HYDROmorphone may very rarely occur in particular in high doses. A HYDROmorphone dose reduction or change in opioid may be required.
DILAUDID-HP®, DILAUDID-HP-PLUS®, DILAUDID-XP® and Reconstituted DILAUDID®
Sterile Powder are highly concentrated solutions of HYDROmorphone hydrochloride. They should be used only in opioid tolerant patients requiring high doses or high concentrations of opioid agonists. Do not confuse DILAUDID-HP®, DILAUDID-HP-PLUS®, DILAUDID-
XP® and Reconstituted DILAUDID® Sterile Powder with the lower concentration of the
DILAUDID® 2 mg/mL Sterile Solution for Injection since overdosage and death could result.
When used at high concentrations, the delivery of precise lower doses of DILAUDID®
(HYDROmorphone hydrochloride) may be difficult. Therefore, high concentration
HYDROmorphone preparations should be used only if the amount of HYDROmorphone required can be delivered accurately.
DILAUDID® STERILE POWDER Prescribing Information
Abuse of Opioid Formulations
Abuse can lead to overdose and death. This risk is increased if DILAUDID is taken with alcohol or other CNS depressants.
Cardiovascular
Hypotensive Effect: Opioid analgesics, including HYDROmorphone, may cause severe hypotension in individuals whose ability to maintain normal blood pressure has already been compromised by depleted blood volume, or the concurrent administration of drugs such as phenothiazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics (see also DRUG
INTERACTIONS). HYDROmorphone may produce orthostatic hypotension in ambulatory patients.
HYDROmorphone should be administered with caution to patients in circulatory shock, since vasodilation produced by the drug may further reduce cardiac output and blood pressure.
Rapid intravenous injection of opioid analgesics increases the possibility of hypotension and respiratory depression and should be avoided (see DOSAGE AND ADMINISTRATION).
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of HYDROmorphone and there is a potential for development of psychological dependence.
DILAUDID should therefore be prescribed and handled with the degree of caution appropriate to the use of a drug with abuse potential.
Abuse and addiction are separate and distinct from physical dependence and tolerance. In addition, abuse of opioids can occur in the absence of true addiction and is characterized by misuse for non-medical purposes, often in combination with other psychoactive substances.
DILAUDID® STERILE POWDER Prescribing Information
Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Concerns about abuse, addiction, and diversion should not prevent the proper management of pain.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse. Addiction is not usually a problem in patients with pain in whom opioid analgesics are appropriately indicated. However, data are not available to establish the true incidence of addiction in chronic pain patients.
Opioids, such as HYDROmorphone, should be used with particular care in patients with a history of alcohol and drug abuse.
Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist.
Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control.
Infants born to mothers physically dependent on HYDROmorphone will also be physically dependent and may exhibit respiratory difficulties and withdrawal symptoms.
Use in Drug and Alcohol Addiction
DILAUDID is an opioid with no approved use in the management of addictive disorders. Its proper usage in individuals with drug or alcohol dependence, either active or in remission, is for the management of pain requiring opioid analgesia.
DILAUDID® STERILE POWDER Prescribing Information
Gastrointestinal
Acute Abdominal Conditions: HYDROmorphone has been shown to decrease bowel motility.
The administration of opioid analgesics including HYDROmorphone may obscure the diagnosis or clinical course in patients with acute abdominal conditions.
Neurologic
Head Injury: The respiratory depressant effects of HYDROmorphone with carbon dioxide retention and secondary elevation of cerebrospinal fluid pressure may be markedly exaggerated in the presence of head injury, other intracranial lesions, or pre-existing increase in intracranial pressure. Opioid analgesics, including HYDROmorphone may produce effects which can obscure the clinical course and neurologic signs of further increase in intracranial pressure in patients with head injuries. In such patients, HYDROmorphone should not be used.
Peri-operative considerations
DILAUDID injections should be used with caution pre- and intra-operatively and within the first 24 hours post-operatively. Severe pain antagonizes the subjective and respiratory depressant actions of
HYDROmorphone. However, should pain suddenly subside, these effects may rapidly become manifest. Patients who are scheduled for cordotomy or other interruptions of pain transmission pathways should not receive HYDROmorphone within 24 hours of the procedure. Thereafter, if
DILAUDID is to be continued after the patient recovers from the post-operative period, a new dosage should be administered in accordance with the changed need for pain relief. The risk of withdrawal in opioid-tolerant patients should be addressed as clinically indicated.
The administration of analgesics in the peri-operative period should be managed by healthcare providers with adequate training and experience (e.g., by an anesthesiologist).
DILAUDID® STERILE POWDER Prescribing Information
Psychomotor Impairment
HYDROmorphone may impair the mental and/or physical abilities needed for certain potentially hazardous activities such as driving a car or operating machinery. Patients should be cautioned accordingly. Patients should also be cautioned about the combined effects of HYDROmorphone with other CNS depressants, including other opioids, phenothiazine, sedative/hypnotics and alcohol.
Respiratory
Respiratory Depression: Respiratory depression is the chief hazard of HYDROmorphone. It occurs most frequently in overdose, the elderly, in the debilitated, and in those suffering from conditions accompanied by hypoxia or hypercapnia, when even moderate therapeutic doses may dangerously decrease pulmonary ventilation. This effect may be lessened by careful dose titration as severe pain can antagonize the respiratory depressant action of HYDROmorphone.
HYDROmorphone should not be used in patients with substantially decreased respiratory reserve, pre-existing respiratory depression, hypoxia or hypercapnia. Such patients are often less sensitive to the stimulatory effects of carbon dioxide (CO2) on the respiratory centre and the respiratory depressant effects of HYDROmorphone may reduce respiratory drive to the point of apnea.
Patient Counselling Information:
A patient information sheet should be provided when DILAUDID is dispensed to the patient.
Patients receiving DILAUDID and/or their caregivers should be given the following instructions by the physician:
- 1. Patients should be informed that accidental use or administration by individuals (including children) other than the patient for whom it was originally prescribed, may lead to severe, even fatal consequences. DILAUDID should be kept under lock and out of sight and out of reach of children.
- 2. Patients should be advised that DILAUDID contains HYDROmorphone, an opioid pain medicine.
DILAUDID® STERILE POWDER Prescribing Information
- 3.
Patients should be advised that DILAUDID should only be taken as directed. The dose of
DILAUDID should not be adjusted without consulting with a physician.
- 4. Patients should be advised that high concentration DILAUDID preparations should only be used by patients who are already receiving high doses or high concentrations of opioids.
- 5. Patients should not combine DILAUDID with alcohol or other central nervous system depressants (sleep aids, tranquilizers) because dangerous additive effects may occur, resulting in serious injury or death.
- 6. Patients should be advised to consult their physician or pharmacist if other medications are being used or will be used with DILAUDID.
- 7. Patients should be advised that if they have been receiving treatment with DILAUDID and cessation of therapy is indicated, do not abruptly stop without consulting their physician.
- 8. Patients should be advised of the most common adverse reactions that may occur while taking DILAUDID: constipation, dizziness, light-headedness, nausea, sedation, sweating and vomiting. If symptoms worsen, seek immediate medical attention.
- 9.
Patients should be advised that DILAUDID may cause drowsiness, dizziness or light-headedness and may impair mental and/or physical ability required for the performance of potentially hazardous tasks (e.g., driving, operating machinery). Patients started on
DILAUDID or patients whose dose has been adjusted should be advised not to drive a car or operate machinery unless they are tolerant to the effects of DILAUDID.
- 10. Patients should be advised that DILAUDID is a potential drug of abuse. They should protect it from theft or misuse.
- 11. Patients should be advised that DILAUDID should never be given to anyone other than the individual for whom it was prescribed.
- 12.
Women of childbearing potential who become or are planning to become pregnant should be advised to consult a physician prior to initiating or continuing therapy with DILAUDID.
Women who are breastfeeding or pregnant should not use DILAUDID.
DILAUDID® STERILE POWDER Prescribing Information
Special Populations
Special Risk Groups:
In general, opioids should be given with caution and the initial dose should be reduced for the elderly or debilitated, and those with severe impairment of hepatic, pulmonary or renal function;
myxedema or hypothyroidism; adrenocortical insufficiency (i.e. Addison's disease); CNS depression or coma; elevated intracranial pressure; toxic psychosis; prostatic hypertrophy or urethral stricture;
gallbladder disease; acute alcoholism; delirium tremens; pancreatitis; or kyphoscoliosis.
The administration of opioid analgesics, including HYDROmorphone, may obscure the diagnosis or clinical course in patients with acute abdominal conditions.
Opioid analgesics including HYDROmorphone should also be used with caution in patients about to undergo surgery of the biliary tract, since it may cause spasm of the sphincter of Oddi.
Pregnant women:
DILAUDID is contraindicated in patients who are pregnant. Animal studies with both morphine and HYDROmorphone have indicated the possibility of teratogenic effects. In humans, it has not conclusively been established whether HYDROmorphone can cause fetal harm when administered during pregnancy or can affect reproductive capacity, therefore DILAUDID is contraindicated in patients who are pregnant.
Labour, Delivery and Nursing Women:
High concentration HYDROmorphone preparations are contraindicated in labour, delivery and nursing mothers (see CONTRAINDICATIONS). In view of the potential for opioids to cross the placental barrier and to be excreted in breast milk, HYDROmorphone should not be used during labour or in nursing mothers. Respiratory depression may occur in the infant if opioids are administered during labour.
DILAUDID® STERILE POWDER Prescribing Information
Pediatrics (< 18 years of age):
The safety and efficacy of DILAUDID has not been studied in the pediatric population. Therefore the use of DILAUDID is not recommended in patients under 18 years of age.
Geriatrics (> 65 years of age):
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The adverse effects of DILAUDID® (HYDROmorphone hydrochloride) are similar to those of other opioid analgesics and represent an extension of pharmacological effects of the drug class. The major hazards include respiratory depression, central nervous system depression and apnea. To a lesser degree, circulatory depression, respiratory arrest, shock and cardiac arrest have occurred.
The most frequently observed adverse effects are constipation, light-headedness, dizziness, sedation, nausea, vomiting, and sweating.
Sedation: Some degree of sedation is experienced by most patients upon initiation of therapy. This may be at least partly because patients often recuperate from prolonged fatigue after the relief of persistent pain. Most patients develop tolerance to the sedative effects of opioids within three to five days and, if the sedation is not severe, will not require any treatment except reassurance. If excessive sedation persists beyond a few days, the dose of the opioid should be reduced and alternate causes investigated. Some of these are: concurrent CNS depressant medication, hepatic or renal dysfunction, brain metastases, hypercalcemia and respiratory failure. If it is necessary to reduce the dose, it can be carefully increased again after three or four days if it is obvious that the pain is not DILAUDID® STERILE POWDER Prescribing Information being well controlled. Dizziness and unsteadiness may be caused by postural hypotension particularly in elderly or debilitated patients and may be alleviated if the patient lies down.
Nausea and Vomiting: Nausea is a common side effect on initiation of therapy with opioid analgesics and is thought to occur by activation of the chemoreceptor trigger zone, stimulation of the vestibular apparatus and through delayed gastric emptying. The prevalence of nausea declines following continued treatment with opioid analgesics. When instituting prolonged therapy with an opioid for chronic pain, the routine prescription of an antiemetic should be considered. In the cancer patient, investigation of nausea should include such causes as constipation, bowel obstruction, uremia, hypercalcemia, hepatomegaly, tumor invasion of celiac plexus and concurrent use of drugs with emetogenic properties. Persistent nausea which does not respond to dosage reduction may be caused by opioid-induced gastric stasis and may be accompanied by other symptoms including anorexia, early satiety, vomiting and abdominal fullness. These symptoms respond to chronic treatment with gastrointestinal prokinetic agents.
Constipation: Practically all patients become constipated while taking opioids on a persistent basis.
In some patients, particularly the elderly or bedridden, fecal impaction may result. It is essential to caution the patients in this regard and to institute an appropriate regimen of bowel management at the start of prolonged opioid analgesic therapy. Stool softeners, stimulant laxatives and other appropriate measures should be used as required.
The following adverse effects occur less frequently with opioid analgesics and include those reported in DILAUDID clinical trials, whether related or not to HYDROmorphone.
General and CNS: Agitation, anxiety, apprehension, asthenic conditions, blurred vision, confusion, convulsions, depression, diplopia, disorientation, drug dependence, drug tolerance, drug withdrawal syndrome, dyskinesia, dysphoria, euphoria, hallucinations, headache, hyperalgesia, increased intracranial pressure, insomnia, miosis, muscle rigidity, muscle tremor, DILAUDID® STERILE POWDER Prescribing Information nightmares, nystagmus, other alterations of mood (nervousness, floating feelings, dreams), paresthesia, peripheral edema, somnolence, tremor, uncoordinated muscle movements, visual disturbances and weakness may occur.
Cardiovascular: Bradycardia, chills, faintness, flushing of the face, hypertension, hypotension, palpitation, syncope, and tachycardia have been reported.
Respiratory: Bronchospasm, dyspnea and laryngospasm have been known to occur.
Gastrointestinal: Abdominal pain, anorexia, biliary colic, biliary tract spasm, cramps, diarrhea, dry mouth, hepatic enzymes increased, ileus and taste alterations have been reported.
Genitourinary: Antidiuretic effects, hesitancy and urinary retention have been reported.
Dermatologic: Diaphoresis, other skin rashes, pruritus, urticaria and wheal and flare over the vein with intravenous injection have been reported with opioid analgesics.
Immune: Anaphylactic reactions and hypersensitivity reactions (including oropharyngeal swelling) have been reported.
Reproductive: Erectile dysfunction has been known to occur.
DILAUDID® STERILE POWDER Prescribing Information
Withdrawal (Abstinence) Syndrome: Physical dependence with or without psychological dependence tends to occur with chronic administration. An abstinence syndrome may be precipitated when opioid administration is discontinued or opioid antagonists administered. The following withdrawal symptoms may be observed after opioids are discontinued: body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, unexplained fever, weakness and yawning. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal from the drug, these symptoms are usually mild.
DRUG INTERACTIONS
Overview
Interaction with Central Nervous System (CNS) Depressants: DILAUDID® (HYDROmorphone hydrochloride) should be dosed with caution in patients who are currently taking other CNS depressants or other drugs that may cause respiratory depression, hypotension, profound sedation, or may potentially result in coma. Such agents include alcohol, antihistamines, antipsychotics, anxiolytics, barbiturates, benzodiazepines, centrally acting anti-emetics, chloral hydrate, clonidine and related substances, general anaesthetics, some heart medications (e.g. beta-blockers), neuroleptics, other opioid derivatives (analgesic and antitussive), phenothiazines and sedatives or hypnotics. When such combined therapy is contemplated, a substantial reduction in the dose of one or both agents should be considered and patients carefully monitored. Patients should also be warned that these combinations increase central nervous system depression and can make driving vehicles and operating machinery hazardous (see WARNINGS AND PRECAUTIONS, Psychomotor
Impairment).
DILAUDID® STERILE POWDER Prescribing Information
Drug-Drug Interactions
Administration with Mixed Activity Agonist/Antagonist Opioids: Mixed agonist/antagonist opioid analgesics (i.e., pentazocine, nalbuphine, butorphanol, and buprenorphine) should be administered with caution to a patient who has received or is receiving a course of therapy with a pure opioid agonist analgesic such as HYDROmorphone. In this situation, mixed agonist/antagonist analgesics may reduce the analgesic effect of HYDROmorphone and/or may precipitate withdrawal symptoms in these patients.
MAO Inhibitors: MAO inhibitors intensify the effects of opioid drugs which can cause anxiety, confusion and decreased respiration. DILAUDID is contraindicated in patients receiving MAO inhibitors or who have used them within the previous 14 days (see CONTRAINDICATIONS).
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DILAUDID® STERILE POWDER Prescribing Information
DOSAGE AND ADMINISTRATION
Dosing Considerations
DILAUDID-HP®, DILAUDID-HP-PLUS®, DILAUDID-XP® and Reconstituted DILAUDID®
Sterile Powder are highly concentrated solutions of HYDROmorphone hydrochloride. They should be used only in opioid tolerant patients requiring high doses or high concentrations of opioid agonists. Do not confuse DILAUDID-HP®, DILAUDID-HP-PLUS®, DILAUDID-XP® and Reconstituted DILAUDID® Sterile Powder with the lower concentration of the DILAUDID®
2 mg/mL Sterile Solution for Injection since overdosage and death could result.
Recommended Dose and Dosage Adjustment
High concentration HYDROmorphone preparations are indicated for relief of severe pain in opioid tolerant patients. Thus, these patients will already have received opioid analgesics. If the patient is being changed from one injectable form of HYDROmorphone to higher concentration
HYDROmorphone preparations, similar doses should be used, depending on the patient's clinical response to the drug. If high concentration HYDROmorphone preparations are substituted for a different opioid analgesic, Table 1 is provided as a guide to determine the approximate equivalent dose of HYDROmorphone. Further dose reductions should be considered due to incomplete cross-tolerance between opioids.
Dose Titration: Dose titration is the key to success with opioid analgesic therapy. Proper optimization of doses scaled to the relief of the individual’s pain should aim at the administration of the lowest dose which will achieve the overall treatment goal of satisfactory pain relief with acceptable side effects.
Dosage adjustments should be based on the patient’s clinical response.
DILAUDID® STERILE POWDER Prescribing Information
Opioid analgesics may only be partially effective in relieving dysesthetic pain, postherpetic neuralgia, stabbing pains, activity-related pain and some forms of headache. That is not to say that patients with advanced cancer suffering from some of these forms of pain should not be given an adequate trial of opioid analgesics, but it may be necessary to refer such patients at an early time to other forms of pain therapy.
DILAUDID® STERILE POWDER Prescribing Information
TABLE 1
OPIOID ANALGESICS: APPROXIMATE ANALGESIC EQUIVALENCES1
Drug Equivalent Dose (mg)2
(compared to morphine 10 mg IM)
Duration of Action (hours)
Parenteral Oral
Strong Opioid Agonists:
Morphine
Oxycodone
HYDROmorphone
Anileridine
Levorphanol
Meperidine6
Oxymorphone
Methadone7
Heroin
10
15
1.5
25
2
75
1.5
-
5-8
603 304 7.55 75
4
300 5 (rectal)
-
10-15
3-4
2-4
2-4
2-3
4-8
1-3
3-4
-
3-4
Weak Opioid Agonists:
Codeine
Propoxyphene
120
50
200 100
3-4
2-4
Mixed Agonist-Antagonists8:
Pentazocine6
Nalbuphine
Butorphanol
60
10
2
180
-
-
3-4
3-6
3-4
Footnotes:
1 References:
Expert Advisory Committee on the Management of Severe Chronic Pain in Cancer Patients, Health and Welfare Canada. Cancer pain: A monograph on the management of cancer pain. Ministry of Supplies and Services Canada, 1987. Cat. No. H42-2/5-1984E.
Foley KM. The treatment of cancer pain. N Engl J Med 1985;313(2):84-95.
Aronoff GM, Evans WO. Pharmacological management of chronic pain: A review. In: Aronoff GM, editor. Evaluation and treatment of chronic pain. 2nd ed. Baltimore (MD): Williams and Wilkins; 1992. p. 359-68. Cherny NI, Portenoy RK. Practical issues in the management of cancer pain. In: Wall PD, Melzack R, editors. Textbook of pain. 3rd ed. New York: Churchill Livingstone; 1994. p. 1437-67.
2 Most of this data was derived from single-dose, acute pain studies and should be considered an approximation for selection of doses when treating chronic pain. As analgesic conversion factors are approximate and patient response may vary, dosing should be individualized according to relief of pain and side effects. Because of incomplete cross-tolerance, dose reductions of 25-50% of the equianalgesic dose may be appropriate in some patients when converting from one opioid to another, particularly at high doses.† Upward titration may be required to reach appropriate maintenance doses.
† Levy MH. Pharmacologic treatment of cancer pain. N Engl J Med 1996;335:1124-1132
3 For acute pain, the oral or rectal dose of morphine is six times the injectable dose. However, for chronic dosing, clinical experience indicates that this ratio is 2 - 3: 1 (i.e., 20-30 mg of oral or rectal morphine is equivalent to 10 mg of parenteral morphine).
4 Based on single entity oral oxycodone in acute pain.
5 Clinical experience indicates that during chronic dosing the oral morphine/oral HYDROmorphone dose ratio is 5 - 7.5:1. 6 Not recommended for the management of chronic pain.
7 Extremely variable equianalgesic dose. Patients should undergo individualized titration starting at an equivalent to 1/10 of the morphine dose.
8 Mixed agonist-antagonists can precipitate withdrawal in patients on pure opioid agonists.
DILAUDID® STERILE POWDER Prescribing Information
In open clinical trials with HYDROmorphone in patients with terminal cancer, both subcutaneous and intramuscular injections of HYDROmorphone were well-tolerated, with minimal pain and/or burning at the injection site. Mild erythema was rarely noted after intramuscular injection.
Subcutaneous injections of HYDROmorphone were particularly well tolerated when administered with a short, 30 gauge needle. In addition, continuous subcutaneous infusions of HYDROmorphone have been shown to be well tolerated. The most common adverse reaction is local tissue redness which can be relieved with more frequent site changes. Experience with administration of
HYDROmorphone by the intravenous route is limited. Should intravenous administration be necessary, the injection should be given slowly, over at least 2 to 3 minutes. Rapid intravenous injection of opioid analgesics increases the possibility of hypotension and respiratory depression.
The intravenous route is usually painless.
A gradual increase in dose may be required if analgesia is inadequate, tolerance occurs, or if pain severity increases. The first sign of tolerance is usually a reduced duration of effect.
OVERDOSAGE
For management of a suspected drug overdose, contact your Regional Poison Control Centre.
Symptoms
Serious overdosage with DILAUDID® (HYDROmorphone hydrochloride) is characterized by respiratory depression (a decrease in respiratory rate and/or tidal volume, Cheyne-Stokes respiration, cyanosis), dizziness, confusion, extreme somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils and sometimes bradycardia and hypotension. In severe overdosage, particularly following intravenous injection, apnea, circulatory collapse, cardiac arrest and death may occur.
DILAUDID® STERILE POWDER Prescribing Information
Treatment
In the treatment of overdosage, primary attention should be given to the re-establishment of adequate respiratory exchange through provision of a patent airway and institution of assisted or controlled ventilation. It should be borne in mind that for individuals who are physically dependent on opioids and are receiving large doses of these drugs, the administration of the usual dose of opioid antagonist will precipitate an acute withdrawal syndrome. The severity will depend on the degree of physical dependence and the dose of the antagonist administered. Use of an opioid antagonist in such persons should be avoided. If necessary to treat serious respiratory depression in the physically dependent patient, the antagonist should be administered with extreme care and by titration, commencing with
10 to 20% of the usual recommended initial dose.
Respiratory depression which may result from overdosage, or unusual sensitivity to
HYDROmorphone in a non-opioid-tolerant patient, can be managed with the opioid antagonist naloxone. A dose of naloxone (usually 0.4 to 2.0 mg) should be administered intravenously, if possible, simultaneously with respiratory resuscitation. The dose can be repeated in 3 minutes.
Naloxone should not be administered in the absence of clinically significant respiratory or cardiovascular depression. Naloxone should be administered cautiously to persons who are known or suspected to be physically dependent on HYDROmorphone. In such cases, an abrupt or complete reversal of opioid effects may precipitate an acute abstinence syndrome.
Since the duration of action of HYDROmorphone may exceed that of the antagonist, the patient should be kept under continued surveillance; repeated doses of the antagonist may be required to maintain adequate respiration. Other supportive measures should be applied when indicated.
Supportive measures, including oxygen and vasopressors, should be employed in the management of circulatory shock and pulmonary edema accompanying overdose, as indicated. Cardiac arrest or arrhythmias may require cardiac massage or defibrillation.
DILAUDID® STERILE POWDER Prescribing Information
ACTION AND CLINICAL PHARMACOLOGY
DILAUDID® (HYDROmorphone hydrochloride) is a hydrogenated ketone of morphine. It is an opioid analgesic with many of the effects common to the class of drugs.
Opioid analgesics have multiple actions but exert their primary effects on the central nervous system and organs containing smooth muscle. The principal actions of therapeutic value are analgesia and sedation. Opioid analgesics also suppress the cough reflex and cause respiratory depression, mood changes, mental clouding, euphoria, dysphoria, nausea, vomiting, increased cerebrospinal fluid pressure, pinpoint constriction of the pupils, increased biliary tract pressure, increased parasympathetic activity and transient hyperglycemia.
The precise mode of analgesic action of opioid analgesics is unknown. However, specific CNS opiate receptors have been identified. Opioids are believed to express their pharmacological effects by combining with these receptors.
The relationship between plasma concentration of HYDROmorphone and analgesic effect has not been well established. In patients with chronic pain, HYDROmorphone should be titrated to the dose required to adequately relieve pain without unmanageable side effects. There is no intrinsic limit to the analgesic effect of HYDROmorphone; adequate doses will relieve even the most severe pain. Clinically, however, dosage limitations are imposed by the adverse effects, primarily respiratory depression; nausea and vomiting which can result from high doses.
Pharmacokinetics
In normal human volunteers HYDROmorphone is metabolized primarily in the liver. It is excreted predominantly as the glucuronidated conjugate, with small amounts of parent drug and minor amounts of 6-hydroxy reduction metabolites.
DILAUDID® STERILE POWDER Prescribing Information
Following intravenous administration of HYDROmorphone to normal volunteers, the mean t2 of elimination was 2.65 +/- 0.88 hours. The mean volume of distribution was 91.5 liters, suggesting extensive tissue uptake. HYDROmorphone is rapidly removed from the bloodstream and distributed to skeletal muscle, kidneys, liver, intestinal tract, lungs, spleen and brain. It also crosses the placental membranes.
Estimates of the relative analgesic potency of parenterally administered HYDROmorphone to morphine in acute pain studies in man range from approximately 7:1 to 11:1. After intramuscular administration, HYDROmorphone has a slightly more rapid onset and slightly shorter duration of action than morphine. The duration of analgesia in the non-tolerant patient with usual doses may be up to 4 to 5 hours. However, in opioid tolerant subjects, duration of analgesia will vary substantially depending on tolerance and dose. Dose should be adjusted so that 3 to 4 hours of pain relief may be achieved.
STORAGE AND STABILITY
Store between 15˚ and 25°C. Protect from light. Do not use beyond the expiry date indicated on the label.
DILAUDID® STERILE POWDER Prescribing Information
Reconstitution Information
DILAUDID Sterile Powder is provided sterile as 250 mg of HYDROmorphone HCl in a 30 mL vial.
It can be reconstituted to desired concentration with sterile water for injection, 0.9% sodium chloride, or 5% dextrose. The table below provides information on the amount of diluent to be added in order to prepare a variety of concentrations.
| Volume of Diluent to be added to Vial | Resulting Volume | Nominal Concentration per mL |
| 24.8 mL | 25.0 mL | 10 mg/mL |
| 12.4 mL | 12.5 mL | 20 mg/mL |
| 4.9 mL | 5.0 mL | 50 mg/mL |
| 2.4 mL | 2.5 mL | 100 mg/mL |
| 1.6 mL | 1.67 mL | 150 mg/mL |
| 1.1 mL | 1.25 mL | 200 mg/mL |
| 0.9 mL | 1.0 mL | 250 mg/mL |
The information provided below is only for physical compatibility and chemical stability of the reconstituted solutions. Continued sterility of the reconstituted solution is dependent on the procedures and equipment used during the preparation of the solution. Each pharmacist must address these factors in determining the duration of use of the solution prepared. The usual recommendation for reconstituted solutions is 24 hours at room temperature or 72 hours under refrigeration.
DILAUDID® STERILE POWDER Prescribing Information
DILAUDID Sterile Powder is physically compatible and chemically stable in the following diluents and containers:
| DILUENT | FINAL CONCENTRATION HYDROMORPHONE HCl (mg/mL) | STORAGE CONDITION | TYPE OF CONTAINER | *PHYSICAL AND CHEMICAL STABILITY (IN DAYS) |
| Sterile Water for Injection | 10, 100, 250 | Room Temperature | Amber Glass | 42 |
| Refrigerated (Fridge) | Amber Glass | 42 | ||
| Sterile Water for Injection | 10, 100, 250 | Room Temperature | Pharmacia Cassettes | 42 |
| Refrigerated (Fridge) | Pharmacia Cassettes | 42 | ||
| Sterile Water for Injection | 10, 100, 250 | 37oC dry heat incubator (after storage in Fridge) | Pharmacia Cassettes | 10 days after 42 days storage in fridge |
| 0.9% Sodium Chloride Solution | 10, 100 | Room Temperature | Amber Glass | 28 |
| 5% Dextrose Solution | 10, 100 | Room Temperature | Amber Glass | 28 |
| * This information does not address sterility. Please see the previous paragraph for further comments. | ||||
Solutions made from DILAUDID Sterile Powder (as well as DILAUDID-HP,
DILAUDID-HP-PLUS and DILAUDID-XP) can be administered by intravenous, intramuscular or subcutaneous routes including intravenous and subcutaneous continuous infusion.
SPECIAL HANDLING INSTRUCTIONS
Not applicable.
DILAUDID® STERILE POWDER Prescribing Information
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage Forms and Composition
DILAUDID-HP®: Each 1 mL of sterile solution contains 10.0 mg of HYDROmorphone hydrochloride, 2.0 mg of citric acid, 2.0 mg of sodium citrate in water for injection; no added preservative.
DILAUDID-HP-PLUS®: Each 1 mL of sterile solution contains 20.0 mg of HYDROmorphone hydrochloride, 2.0 mg of citric acid, 2.0 mg of sodium citrate in water for injection; no added preservative.
DILAUDID-XP®: Each 1 mL of sterile solution contains 50.0 mg of HYDROmorphone hydrochloride, 2.0 mg of citric acid, 2.0 mg of sodium citrate in water for injection; no added preservative.
DILAUDID® Sterile Powder: Each vial contains 250 mg of sterile lyophilized HYDROmorphone hydrochloride, no added preservatives.
Packaging
DILAUDID-HP® (10 mg/mL) ampoules are amber in colour. DILAUDID-HP single-use vials are amber and have a white flip-off cap. 1 mL and 5 mL ampoules - boxes of 10. 50 mL single-use vials - boxes of 2.
DILAUDID-HP-PLUS® (20 mg/mL) single-use vials are amber in colour and have a brown flip-off cap - 50 mL single-use vials, boxes of 2.
DILAUDID-XP® (50 mg/mL) single-use vials are amber in colour and have a yellow flip-off cap -
50 mL single-use vials, boxes of 2.
DILAUDID® STERILE POWDER Prescribing Information
DILAUDID® Sterile Powder (250 mg/vial) vials are amber in colour and have a black flip-off cap - boxes of 4.
NOTE: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. A slight yellowish discoloration may develop in HYDROmorphone solutions. This yellowish colouration is proportional to HYDROmorphone concentration and has a tendency to increase over time. The colouration is of an aesthetic nature and not a result of chemical degradation. No loss of potency has been demonstrated. Also, note that DILAUDID® does not contain any preservatives; therefore, unused portions of the remaining drug in the vial should be discarded.
DILAUDID® STERILE POWDER Prescribing Information
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
HYDROmorphone is a semisynthetic congener of morphine, differing structurally from morphine in the substitution of an oxygen for the 6-hydroxyl group and hydrogenation of the 7-8 double bond of the morphine molecule.
Proper Name: HYDROmorphone hydrochloride
Chemical Name: 4,5α-Epoxy-3-hydroxy-17-methylmorphinan-6-one hydrochloride
Molecular formula and molecular mass: C17H19NO3·HCl 321.8
Structural Formula:
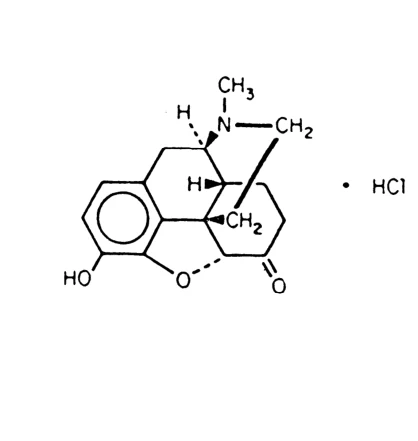
Physicochemical properties: HYDROmorphone hydrochloride is a hydrogenated ketone of morphine.
DILAUDID® STERILE POWDER Prescribing Information
Appearance: Fine, white, or practically white, crystalline powder.
Solubility: Soluble 1:3 in water and 1:100 in alcohol (90%); practically insoluble in chloroform and ether.
Melting Point: Decomposes at 305˚ to 315EC.
pH: 1.0 mg/mL solution in water has a pH between 4.5 - 6.5.
10.0 mg/mL solution in water has a pH between 3.5 - 5.5.
100.0 mg/mL solution in water has a pH between 3.5 - 5.5.
250.0 mg/mL solution in water has a pH between 3.0 - 5.0.
pKa: 8.2 (20EC)
DILAUDID® STERILE POWDER Prescribing Information
REFERENCES
- 1. Brown CR Jr., Forrest WH, Hayden J, James KE. Respiratory effects of hydromorphone in man. Clin Pharmacol Ther 1973;14(3):331-7.
- 2.
Bruera E, Brenneis C, Michaud M, Bacovsky R, Chadwick S, Emeno A, MacDonald N. Use of the subcutaneous route for the administration of narcotics in patients with cancer pain.
Cancer 1988;62(2):407-11.
- 3. Cone EJ, Phelps BA, Gorodetzky CW. Urinary excretion of hydromorphone and metabolites in humans, rats, dogs, guinea pigs and rabbits. J Pharm Sci 1977;66(12):1709-13.
- 4.
Cone EJ, Darwin WD. Simultaneous determination of hydromorphone, hydrocodone and their
6 and 6β hydroxy metabolites in urine using selected ion recording with methane chemical ionization. Biomed Mass Spectrom 1978;5(4):291-5.
- 5.
Dickson PH, Lind A, Studts P, Nipper HC, Makoid M, Makoid M, et al. The routine analysis of breast milk for drugs of abuse in a clinical toxicology laboratory. J Forensic Sci
1994;39(1):207-14.
- 6.
Expert Advisory Committee on the Management of Severe Chronic Pain in Cancer Patients,
Health and Welfare Canada. Cancer pain: a monograph on the management of cancer pain.
Ministry of Supplies and Services Canada, 1987. Cat. No. H42-2/5-1984E.
- 7. Ferris FD, Kerr IG, De Angelis C, Sone M, Hume S. Inpatient narcotic infusions for patients with cancer pain. J Palliat Care 1990;6(2):51-9.
- 8. Hanks GW, Justins DM. Cancer pain: management. Lancet 1992;339(8800):1031-6.
DILAUDID® STERILE POWDER Prescribing Information
- 9.
Hill HF, Coda BA, Tanaka A, Schaffer R. Multiple-dose evaluation of intravenous hydromorphone pharmacokinetics in normal human subjects. Anesth Analg 1991;72(3): 330-
6.
- 10. Houde RW. Clinical analgesic studies of hydromorphone. In: Foley KM, Inturrisi CE, editors. Advances in pain research and therapy. Vol. 8. Opioid analgesics in the management of clinical pain. New York: Raven Press; 1986. p. 129-41.
- 11.
Keeri-Szanto M. Anaesthesia time/dose curves IX: the use of hydromorphone in surgical anaesthesia and postoperative pain relief in comparison to morphine. Can Anaesth Soc J
1976;23(6):587-95.
- 12. Mahler DL, Forrest WH Jr. Relative analgesic potencies of morphine and hydromorphone in postoperative pain. Anesthesiology 1975;42(5):602-7.
- 13.
Moulin DE, Johnson NG, Murray-Parsons N, Geoghegan MF, Goodwin VA, Chester MA.
Subcutaneous narcotic infusions for cancer pain: treatment outcome and guidelines for use.
CMAJ 1992;146(6):891-7.
- 14. Portenoy RK, Coyle N. Controversies in the long-term management of analgesic therapy in patients with advanced cancer. J Pain Symptom Manage 1990;5(5):307-19.
- 15.
Portenoy RK. Chronic opioid therapy in non-malignant pain. J Pain Symptom Manage 1990;5
(Suppl 1):S46-S62.
- 16.
Principles of analgesic use in the treatment of acute pain and cancer pain. 6th ed. Glenview
(IL): American Pain Society;2008.
DILAUDID® STERILE POWDER Prescribing Information
- 17.
Reidenberg MM, Goodman H, Erle H, Gray G, Lorenzo B, Leipzig RM, Meyer BR, Drayer
DE. Hydromorphone levels and pain control in patients with severe chronic pain. Clin
Pharmacol Ther 1988;49(4):376-82.
- 18.
Steinberg SK, Kornijenko M. The role of hydromorphone in the treatment of cancer pain. Can
Pharm J 1988;121(3):182-6.
- 19. Vallner JJ, Stewart JT, Kotzan JA, Kirsten EB, Honigberg IL. Pharmacokinetics and bioavailability of hydromorphone following intravenous and oral administration to human subjects. J Clin Pharmacol 1981;21(4):152-6.