


Product Monograph - Emerade
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
Intramuscular injection to be injected into anterolateral aspect of the thigh. Do not inject into the buttock. | The pre-filled pen contains 0.5 mL of 1 mg/mL epinephrine solution. EMERADE 0.15 mg auto-injector delivers a single dose of 0.15 mL containing 0.15 mg of epinephrine (as hydrogen tartrate). EMERADE 0.3 mg auto-injector delivers a single dose of 0.3 mL containing 0.3 mg of epinephrine (as hydrogen tartrate). EMERADE 0.5 mg auto-injector delivers a single dose of 0.5 mL containing 0.5 mg of epinephrine (as hydrogen tartrate). | Sodium chloride, Sodium meta-bisulfite, Disodium edetate, Hydrochloric acid (for adjustment of pH), Water for injection |
INDICATIONS AND CLINICAL USE
EMERADE is indicated for the emergency treatment of anaphylactic reactions in patients who are determined to be at increased risk for anaphylaxis, including individuals with a history of anaphylactic reactions. Selection of the appropriate dosage strength is determined according to patient body weight and age (see DOSAGE AND ADMINISTRATION section).
EMERADE is intended for immediate self-administration for the emergency treatment of severe allergic reactions (Type I), including anaphylaxis associated with:
- Foods (e.g., peanuts, tree nuts, shellfish, fish, milk, eggs, and wheat)
- Stinging insects (e.g., Order Hymenoptera, including bees, wasps, hornets, yellow jackets, and fire ants) and biting insects (e.g., mosquitoes and black flies)
- Medications
- Latex
- Idiopathic anaphylaxis
- Exercise-induced anaphylaxis
- Other allergens
Epinephrine (adrenaline) is the drug of choice for the emergency treatment of severe allergic reactions. The strong vasoconstrictor action of epinephrine, through its effect on alpha adrenergic receptors, quickly counteracts vasodilation and increased vascular permeability which can lead to loss of intravascular fluid volume and hypotension during anaphylactic reactions.
EMERADE is designed as emergency supportive therapy only and not as a replacement or substitute for subsequent medical or hospital care, nor are they intended to supplant insect venom hyposensitization.
Clinical Signs and Symptoms of Anaphylaxis
Anaphylaxis is a serious, acute, allergic reaction that may cause death. It has a sudden onset and generally lasts less than 24 hours. Because anaphylaxis is a generalized reaction, a wide variety of clinical signs and symptoms may be observed.
1% to 2% of the general population is estimated to be at risk for anaphylaxis from food allergies and insect stings, with a lower reported prevalence for drugs and latex. People with asthma (especially poorly controlled asthma) are at particular risk.
Symptoms of anaphylaxis may include:
Oral: pruritus of lips, tongue, and palate, edema of lips and tongue; metallic taste in the mouth.
Cutaneous: flushing, pruritus, urticaria, angioedema, morbilliform rash, and pilor erecti.
Gastrointestinal: nausea, abdominal pain, vomiting, and diarrhea.
Respiratory:
Laryngeal: pruritus and “tightness” in the throat, dysphagia, dysphonia, hoarseness, wheezing, and cough.
Nasal: nasal pruritus, congestion, rhinorrhea, sneezing, and sensation of itching in the external auditory canals.
Cardiovascular: feeling of faintness, syncope, chest pain, dysrhythmia, and hypotension. Note: Hypotension is a sign of anaphylaxis. Patients should be treated in the early stages of anaphylaxis to prevent hypotension from developing.
Other: periorbital pruritus, erythema and edema, conjunctival erythema, and tearing; lower back pain and uterine contractions in women; aura of “doom.”
The severity of previous anaphylactic reactions does not determine the severity of future reactions, and subsequent reactions could be the same, better, or worse. The severity may depend on the degree of sensitivity, the dose of allergen, and other factors.
Research shows that fatalities from anaphylaxis are often associated with failure to use epinephrine or a delay in the use of epinephrine treatment.
Epinephrine should be administered as early as possible after the onset of symptoms of a severe allergic response. Patients requiring epinephrine will not always have predictable reactions. Adequate warning signs are not always present before serious reactions occur.
It is recommended that epinephrine be given at the start of any reaction associated with a known or suspected allergen contact. In patients with a history of severe cardiovascular collapse on exposure to an allergen, the physician may advise that epinephrine be administered immediately after exposure to that allergen, and before any reaction has begun.
Epinephrine may prove to be lifesaving when used as directed immediately following exposure to an allergen.
All individuals receiving emergency epinephrine must be immediately transported to hospital, ideally by ambulance, for evaluation and observation. Repeat attacks have occurred hours later without additional exposure to the offending allergen. Therefore, it is recommended that a patient suffering from an anaphylactic reaction be observed in an emergency facility for an appropriate period because of the possibility of either a “biphasic” reaction (a second reaction) or a prolonged reaction. At least a four-hour period of observation is advised, although this time may vary. The attending physician will take into consideration such factors as the severity of the reaction, the patient’s response and history and the distance from the hospital to the patient’s home.
Anaphylactic reactions typically follow a uniphasic course; however, 20% will be biphasic in nature. The second phase usually occurs after an asymptomatic period of 1 to 8 hours but may occur up to 38 hours (mean 10 hours) after the initial reaction. About one third of the second phase reactions are more severe, one third are as severe, and one third are less severe. The second-phase reactions can occur even following administration of corticosteroids.
Following treatment of anaphylaxis, the patient must stay within close proximity to a hospital or where he or she can call 911 for the next 48 hours.
Protracted anaphylaxis, which is frequently associated with profound hypotension and sometimes lasts longer than 24 hours, is minimally responsive to aggressive therapy, and has a poor prognosis.
CONTRAINDICATIONS
There are no absolute contraindications to the use of epinephrine in a life-threatening allergic situation.
WARNINGS AND PRECAUTIONS
Emergency Treatment
EMERADE is intended for immediate administration as emergency supportive therapy and is not intended as a substitute for immediate medical care. In conjunction with the administration of epinephrine, the patient should seek immediate medical or hospital care. More than two sequential doses of epinephrine should only be administered under direct medical supervision.
General
All patients who are prescribed EMERADE should be thoroughly instructed to understand the indications for use and the correct method of administration. It is strongly advised also to educate the patient's immediate associates (e.g., parents, caregivers, teachers) for the correct usage of EMERADE in case support is needed in the emergency situation.
Patients with a history of anaphylaxis are at risk for subsequent episodes and even death. EMERADE should be used in emergency situations as life-sustaining treatment. All patients who have had one or more episodes of anaphylaxis should have injectable epinephrine with them or with their parent or caregiver at all times and should wear some form of medical identification bracelet or necklace.
Following the resolution of an anaphylactic episode and discharge from hospital, the patient should immediately obtain and fill a new EMERADE auto-injector prescription.
EMERADE injection is not intended as a substitute for medical attention or hospitable care. In conjunction with the administration of epinephrine, the patient should seek appropriate medical care. More than two sequential doses of epinephrine should only be administered under direct medical supervision (See DOSAGE AND ADMINISTRATION section).
The patient/carer should be informed about the possibility of biphasic anaphylaxis which is characterised by initial resolution followed by recurrence of symptoms some hours later.
In patients with a thick subcutaneous fat layer, there is risk for epinephrine not reaching the muscle tissue resulting in a suboptimal effect.
Antihistamines and asthma medications must not be used as the first line treatment for an anaphylactic reaction.
There is also a risk for adverse reactions after the administration of epinephrine to patients with
hyperthyroidism, pheochromocytoma, severe renal impairment, prostate adenoma, hypercalcaemia, hypokalemia, and in elderly patients and pregnant women.
Injection-Related Complications
EMERADE is designed to minimize the risk of unintentional injection.
EMERADE should ONLY be injected into the anterolateral aspect of the thigh (see DOSAGE AND ADMINISTRATION - Dosing Considerations).
Do not inject intravenously
Large doses or accidental intravenous injection of epinephrine may result in cerebral hemorrhage due to sharp rise in blood pressure. Rapidly acting vasodilators can counteract the marked pressor effects of epinephrine if there is such inadvertent administration.
Do not inject into buttock
Patients should be advised that EMERADE is not intended for injection into the buttock. Injection into the buttock may not provide effective treatment of anaphylaxis; advise the patient to go immediately to the nearest emergency room for further treatment of anaphylaxis. Additionally, injection into the buttock has been associated with Clostridial infections (gas gangrene).
Do not inject into digits, hands or feet
Since epinephrine is a strong vasoconstrictor, accidental injection into the hands or feet may result in loss of blood flow to the affected areas and should be avoided. If there is an accidental injection into these areas, the patient must go immediately to the nearest emergency room for treatment.
Hold leg firmly during injection
Lacerations, bent needles, and embedded needles have been reported when EMERADE has been injected into the thigh of young children who are uncooperative and kick or move during an injection. To minimize the risk of injection related injury when administering EMERADE to young children, instruct caregivers to hold the child’s leg firmly in place and limit movement prior to and during injection.
Serious Infections at the Injection Site
Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Clostridium spores can be present on the skin and introduced into the deep tissue with subcutaneous or intramuscular injection. While cleansing with alcohol may reduce presence of bacteria on the skin, alcohol cleansing does not kill Clostridium spores. To decrease the risk of Clostridium infection, do not inject EMERADE into the buttock. Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site.
The presence of a condition listed below is not a contraindication to epinephrine administration in an acute, life-threatening situation. Therefore, patients with these conditions, or any other person who might be in a position to administer epinephrine to a patient with these conditions experiencing anaphylaxis, should be instructed about the circumstances under which epinephrine should be used.
Cardiovascular
Epinephrine use should be avoided in patients with cardiogenic, traumatic, or hemorrhagic shock; cardiac dilation; and/or cerebral arteriosclerosis.
Epinephrine should be used with caution in patients with cardiac arrhythmias, coronary artery or organic heart disease, hypertension, or in patients who are on medications that may sensitize the heart to arrhythmias, e.g., digitalis, diuretics, or anti-arrhythmics. In such patients, epinephrine may precipitate or aggravate angina pectoris as well as produce ventricular arrhythmias.
Patients with hypertension or hyperthyroidism are prone to more severe or persistent effects.
Endocrine and Metabolism
Patients with diabetes may develop increased blood glucose levels following epinephrine administration.
Neurologic
Epinephrine use should be avoided in patients with organic brain damage.
Patients with Parkinson’s disease may notice a temporary worsening of symptoms after treatment with epinephrine.
Ophthalmologic
Epinephrine use should be avoided with narrow-angle glaucoma.
Respiratory
There is a significantly increased risk of respiratory symptoms in patients with concomitant asthma, especially if poorly controlled. These patients are at increased risk of death from anaphylaxis. Fatalities may occur from pulmonary edema resulting from peripheral constriction and cardiac stimulation.
Sensitivity
This product contains sodium metabisulfite, a substance which may cause allergic -type reactions including anaphylactic symptoms or mild to severe asthmatic episodes in certain susceptible persons.
Nevertheless, epinephrine is the drug of choice of serious allergic reactions and the presence of sulfite in this product should not deter administration of the drug treatment of serious allergic or other emergency situations, even if the patient is sulfite-sensitive.
Reproduction
There are no studies available to determine epinephrine’s potential effect on fertility.
Special Populations
Geriatrics (> 65 years of age)
Elderly patients with hypertension, coronary artery disease or cardiac arrhythmias are particularly at risk for epinephrine overdose. More careful monitoring and avoidance of epinephrine overdose is recommended for these patients.
Pediatrics (patients 15-30 kg)
There are no data to suggest a difference in safety or effectiveness of epinephrine between adults and children in this weight group.
See DOSAGE AND ADMINISTRATION section for dosage requirements based on weight.
Pregnancy
There are no adequate or well-controlled studies of epinephrine during pregnancy. Epinephrine should be used in pregnancy only if the potential benefit to the mother outweighs the possible risk to the fetus.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Adverse reactions of epinephrine include transient, moderate anxiety; feelings of over stimulation; apprehensiveness; restlessness; tremor; weakness; shakiness; dizziness; sweating; tachycardia; palpitations; pallor; nausea and vomiting; headache; and/or respiratory difficulties. Ventricular arrhythmias may follow administration of epinephrine. While these symptoms occur in some patients treated with epinephrine, they are likely to be more pronounced in patients with hypertension or hyperthyroidism. These signs and symptoms usually subside rapidly, especially with bed rest.
Some patients may be at greater risk of developing adverse reactions after epinephrine administration. These include patients with asthma, elderly individuals, pregnant women, and patients with diabetes. Patients with coronary artery disease are prone to more severe or persistent effects and may experience angina. Cases of takotsubo (stress) cardiomyopathy have been reported in patients treated with epinephrine. Patients with epinephrine-triggered takotsubo cardiomyopathy are predominantly women and are younger than the typical takotsubo cardiomyopathy patient. These events are characterized by rapid onset of symptoms after epinephrine administration and high complication rates, mostly in the form of cardiogenic shock and acute pulmonary edema. The prognosis is however good with complete recovery in most cases.
Excessive doses cause acute hypertension. Rapid rises in blood pressure have produced cerebral hemorrhage, particularly in elderly patients with cardiovascular disease.
Arrhythmias, including fatal ventricular fibrillation, have been reported, particularly in patients with underlying cardiac disease or those receiving certain drugs (see DRUG INTERACTIONS).
Lacerations, bent needles, and embedded needles have been reported when EMERADE® has been injected into the thigh of young children who are uncooperative and kick or move during the injection (see WARNING AND PRECAUTIONS section).
Injection into the buttock has resulted in cases of gas gangrene.
Accidental injections can lead to injury at the injection site resulting in bruising, bleeding, discoloration, erythema or skeletal injury.
Serious Infections at the Injection Site
Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection in the thigh. Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site (see WARNING AND PRECAUTIONS section).
The potential for epinephrine to produce these types of adverse reactions does not contraindicate its use in an acute life-threatening allergic reaction.
DRUG INTERACTIONS
Overview
There are no known contraindications to the use of epinephrine in life-threatening allergic reactions.
Drug-Drug Interactions
Epinephrine should be used with caution in patients who are on medications that may sensitize the heart to arrhythmias, e.g., digitalis, diuretics, or anti-arrhythmics. In such patients, epinephrine may precipitate or aggravate angina pectoris as well as produce ventricular arrhythmias.
Caution is advised in patients receiving cardiac glycosides or diuretics, since these agents may sensitize the myocardium to beta-adrenergic stimulation and make cardiac arrhythmias more likely.
The effects of epinephrine may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, sodium levothyroxine, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine.
The cardiostimulating and bronchodilating effects of epinephrine are antagonized by beta-adrenergic blocking drugs, such as propranolol. Anaphylaxis may be made worse by beta blockers because these drugs decrease the effectiveness of epinephrine.
The vasoconstricting and hypertensive effects of epinephrine are antagonized by alpha-adrenergic blocking drugs, such as phentolamine.
Phenothiazines may also reverse the pressor effects of epinephrine.
Deaths have been reported in asthmatic patients treated with epinephrine following the use of isoproterenol, orciprenaline, salbutamol, and long-acting beta agonists.
Drug-Lifestyle Interactions
Cocaine sensitizes the heart to catecholamines (as does uncontrolled hyperthyroidism), and epinephrine use in these patients should be cautious.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Dosage in any specific patient should be based on body weight. A physician who prescribes EMERADE should take appropriate steps to ensure that the patient thoroughly understands the indications and use of the device. The physician should review with the patient, in detail, the PATIENT MEDICATION INFORMATION section and operation of the auto-injector.
Recommended Dose and Dosage Adjustment
The effective dose is usually in the range 0.005-0.01 mg/kg bodyweight
Pediatric Population
Use in children: EMERADE 0.5 mg is not recommended for use in children.
- Children between 15 kg and 30 kg bodyweight: The usual dose is 0.15 mg.
- Children over 30 kg bodyweight: The usual dose is 0.3 mg.
- Adolescent patients over 30 kg bodyweight: The dosage recommendations for adult patients should be followed.
Adults
- Individuals under 60 kg bodyweight: The recommended dose is 0.3 mg.
- Individuals over 60 kg bodyweight: The recommended dose is 0.3 to 0.5 mg depending on clinical judgement.
Administration
An initial dose should be administered as soon as symptoms of anaphylaxis are recognised. In the absence of clinical improvement or if deterioration occurs, a second injection with an additional EMERADE may be administered 5 – 15 minutes after the first injection. More than two sequential doses of epinephrine should only be administered under direct medical supervision (see WARNINGS AND PRECAUTIONS section). It is recommended that the patients are prescribed two EMERADE auto-injectors which they should carry at all times.
All individuals receiving emergency epinephrine must be immediately transported to hospital, ideally by ambulance, for evaluation and observation even if symptoms appear to be improving.
The patient/carer should be informed that following each use of EMERADE auto-injector:
- As EMERADE auto-injector is designed as emergency treatment only, the patient should be advised to always seek medical help immediately.
- Conscious patients should preferably lie flat with feet elevated but sit up if they have breathing difficulties. Unconscious patients should be placed on their side in the recovery position.
- The patient should if possible remain with another person until medical assistance arrives.
EMERADE is intended for intramuscular use in the anterolateral aspect of the thigh, through clothing if necessary. Do not inject into the buttock.
Instruct caregivers to hold the leg of young children firmly in place and limit movement prior to and during injection (see WARNINGS AND PRECAUTIONS section).
Patients with a history of severe allergic reactions should be instructed about the circumstances under which epinephrine should be used (see INDICATIONS AND CLINICAL USE section). 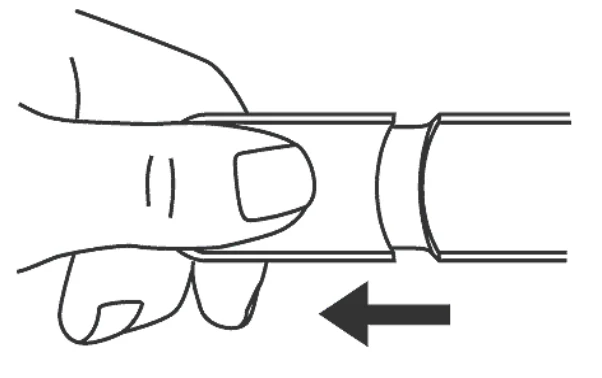
A physician who prescribes EMERADE should take appropriate steps to ensure that the patient thoroughly understands the indications and use of the device.
The patient’s physician or pharmacist should review the package insert in detail with the patient or caregiver to ensure that he/she understands the indications and use of EMERADE. The physician should review with the patient, in detail, the PATIENT MEDICATION INFORMATION section and operation of the auto-injector.
Actual demonstration of the injection technique by a physician or a pharmacist is recommended. The instructions for use must be carefully followed in order to avoid accidental injection. EMERADE should only be used for injection in the outer thigh.
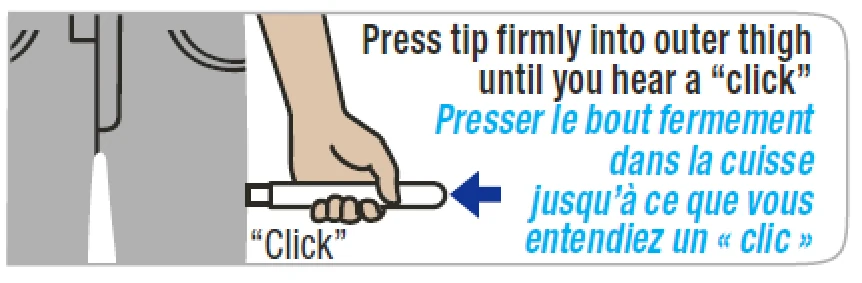
The injection occurs when EMERADE is pressed gently into the thigh.
Instructions for use:
EMERADE should be used for intramuscular injection only on the outer thigh (see WARNINGS AND PRECAUTIONS). The injection occurs when the triggering cylinder is gently pressed into the thigh. This can be done through clothing due to the 25 mm needle length.
- 1. Remove the needle cap.
EMERADE is easy to use. EMERADE has an obvious opening at the needle end; and none at the opposite end. Therefore, there is no risk that the patient turns EMERADE backwards and injects incorrectly.
- 2. Place EMERADE against the outer side of the thigh at a 90⁰ angle and press firmly so the needle cover is depressed. You will hear a click when the device has activated and the needle has penetrated the thigh.
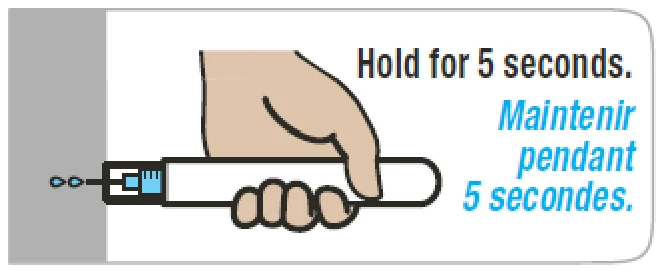

- 3. Hold EMERADE against the thigh for about 5 seconds. Lightly massage the injection site afterwards.
- 4. Seek immediate medical help.
The needle in EMERADE is protected before, during and after the injection.
When the injection is completed the plunger is visible in the inspection window by lifting the label.
Some liquid may remain in the auto-injector after the injection. The auto-injector cannot be re-used. Talk to your pharmacist or physician about how to properly dispose of your expired EMERADE.
EMERADE is intended only for emergency treatment.
You must always contact your doctor or go to the nearest hospital for further treatment. Inform your doctor that you have taken an injection of epinephrine. Take the used auto-injector with you.
OVERDOSAGE
Epinephrine is rapidly inactivated in the body, and treatment following overdose with epinephrine is primarily supportive. If necessary, pressor effects may be counteracted by rapidly acting vasodilators or alpha-adrenergic blocking drugs. If prolonged hypotension follows such measures, it may be necessary to administer another pressor drug.
Overdosage of epinephrine may produce extremely elevated arterial pressure, which may result in cerebrovascular hemorrhage, particularly in elderly patients. Overdosage sometimes also results in extreme pallor and coldness of the skin, metabolic acidosis, and kidney failure.
Suitable corrective measures must be taken in such situations. Epinephrine overdosage can also cause transient bradycardia followed by tachycardia, and these may be accompanied by potentially fatal cardiac arrhythmias. Treatment of arrhythmias consists of administration of a beta-adrenergic blocking drug such as propranolol.
If an epinephrine overdose induces pulmonary edema that interferes with respiration, treatment consists of a rapidly acting alpha-adrenergic blocking drug and/or intermittent positive-pressure respiration.
Premature ventricular contractions may appear within 1 minute after injection and may be followed by multifocal ventricular tachycardia (prefibrillation rhythm).
Subsidence of the ventricular effects may be followed by atrial tachycardia and occasionally by atrioventricular block.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Epinephrine acts on both alpha- and beta-adrenergic receptors. Through its action on alpha adrenergic receptors, epinephrine counters the vasodilation and high vascular permeability that occurs during an anaphylactic reaction that can lead to loss of intravascular fluid volume and hypotension. Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation that helps alleviate bronchospasm, wheezing, and dyspnea that may occur during anaphylaxis.
Epinephrine also helps to alleviate pruritus, urticaria, and angioedema, and may be effective in relieving gastrointestinal and genitourinary symptoms of anaphylaxis because of its relaxant effects on the smooth muscle of the stomach, intestine, and urinary bladder. Epinephrine contracts the smooth muscle of the uterus.
Epinephrine, when given intramuscularly or subcutaneously, has a rapid onset and short duration of action.
Pharmacodynamics
Epinephrine is the natural active sympathomimetic hormone from the adrenal medulla. It stimulates both the α- and β-adrenergic receptors. Epinephrine is the first choice for emergency treatment of severe allergic reactions and idiopathic or exercised-induced anaphylaxis. Epinephrine has a potent vasoconstrictive effect through its α-adrenergic stimulation. This effect counteracts the vasodilatation and increases vascular perfusion, leading to low intravascular flow and hypotension, which are the main pharmacotoxicological effects in the anaphylactic shock.
By stimulating of β-receptors in the lungs, epinephrine produces a potent bronchodilator effect with relief of wheezing and dyspnea. Epinephrine also relieves pruritus, urticaria and angioedema associated to anaphylaxis.
Pharmacokinetics
The oral bioavailability of epinephrine is poor, owing to its rapid and extensive metabolism in the gut and liver. Epinephrine is, however, well absorbed systemically when administered by intramuscular (IM) or subcutaneous (SQ) routes. Epinephrine is distributed throughout the body. Epinephrine crosses the placenta but does not penetrate the blood-brain barrier to a great extent.
Epinephrine will distribute into breast milk.
Epinephrine, when given intramuscularly, has a rapid onset and short duration of action. However, when epinephrine is injected subcutaneous or intramuscularly the absorption is retarded by local vasoconstriction and thus the effects can last longer than as predicted by half-life. Massage around the injection site is advised to accelerate absorption.
Subcutaneous administration of epinephrine is no longer the route of choice for patients in shock, because absorption and achievement of therapeutic plasma concentrations can be significantly delayed.
Circulating epinephrine is metabolized in the liver and other tissues by the enzymes COMT and MAO. Inactive metabolites are excreted in the urine.
STORAGE AND STABILITY
Shelf-life
0.15 mg: 18 months
0.3 mg and 0.5 mg: 24 months
Store at room temperature (15°C to 25°C). Do not freeze.
EMERADE should always be carried if at risk for anaphylaxis.
Protect from light. Keep out of reach and sight of children.
Keep in the original package a durable case to protect the auto-injector and the labelling.
The solution can be examined through the inspection window at any time by lifting the label. Discard and replace EMERADE if the solution is discolored or contains particles. The expiry date is indicated on the label; EMERADE should not be used after this date. Replace and discard the auto-injector after expiry date.
DOSAGE FORMS, COMPOSITION AND PACKAGING
EMERADE consists of a pre-filled syringe made of glass with a polyisoprene rubber plunger in an auto-injector. The pre-filled syringe contains 0.5 mL of 1 mg/mL epinephrine sterile solution.
EMERADE is available in three fixed doses:
EMERADE 0.15 mg single use pre-filled auto-injector delivers a single dose of 0.15 mL containing 0.15 mg of epinephrine (as epinephrine hydrogen tartrate).
EMERADE 0.3 mg single use pre-filled auto-injector delivers a single dose of 0.3 mL containing 0.3 mg of epinephrine (as epinephrine hydrogen tartrate).
EMERADE 0.5 mg single use pre-filled auto-injector delivers a single dose of 0.5 mL containing 0.5 mg of epinephrine (as epinephrine hydrogen tartrate).
Needle
The syringe in EMERADE has a 25 mm needle. In EMERADE 0.15 mg, the needle protrudes 16 mm at the injection. In EMERADE 0.3 mg and EMERADE 0.5 mg, the needle protrudes 23 mm for the injection.
Package
EMERADE has a durable, plastic outer case to protect the auto-injector and labelling.
Each dosage is differentiated by an appropriate labelling with different colors:
- EMERADE 0.15 mg pre-filled auto-injector is identified in green.
- EMERADE 0.3 mg pre-filled auto-injector is identified in blue.
- EMERADE 0.5 mg pre-filled auto-injector is identified in red.
EMERADE is available in pack sizes of one or 2 pre-filled auto-injectors.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
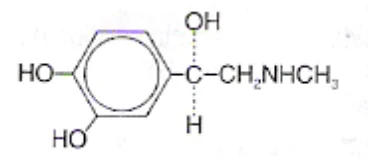
Proper name: Epinephrine hydrogen tartrate or Adrenaline tartrate
Chemical name: 1-(3,4-dihydroxyphenyl)-2-(methylamino)ethanol
Molecular formula: C13H19NO9
Molecular mass: 333.29 g/mol
Structural formula:
Physicochemical properties
Description: White or greyish-white crystalline powder.
Solubility: Freely soluble in water, slightly soluble in ethanol.
REPRODUCTION
Teratogenic Effects
Pregnancy Category C
Epinephrine has been shown to have adverse developmental effects in rabbits at a subcutaneous dose of 1.2 mg/kg (approximately 30 times the maximum recommended daily subcutaneous or intramuscular dose on a mg/m2 basis), in mice at a subcutaneous dose of 1 mg/kg (approximately 7 times the maximum recommended daily subcutaneous or intramuscular dose on a mg/m2 basis), and in hamsters at a subcutaneous dose of 0.5 mg/kg (approximately 5 times the maximum recommended daily subcutaneous or intramuscular dose on a mg/m2 basis).
These effects were not seen in mice at a subcutaneous dose of 0.5 mg/kg (approximately 3 times the maximum recommended daily subcutaneous or intramuscular dose on a mg/m2 basis).
REFERENCES
- 1.
Sampson H. et al. Second Symposium on the Definition and Management of
Anaphylaxis: Summary Report – Second National Institute of Allergy and Infectious Disease/Food Allergy and Anaphylaxis Network Symposium. Journal of Allergy and Clinical Immunology 2006: 117(2) 391-397.
- 2.
Stark BJ, Sullivan TJ. Biphasic and protracted anaphylaxis. Journal of Allergy and
Clinical Immunology 1986; 78:76-83.
- 3.
Lieberman P. Biphasic Anaphylaxis (Review) Allergy and Clinical Immunology
International – Journal of the World Allergy Organization 2004;16:241-248.
- 4. Sampson HA. Anaphylaxis and Emergency Treatment. Pediatrics 2003;111;1601-1608
- 5.
Allen, M. et al. (2005) Anaphylaxis in Schools and Other Settings, Hamilton, Ontario:
Canadian Society of Allergy and Clinical Immunology.
- 6.
Simons, F., et al., World Allergy Organization anaphylaxis guidelines: Summary. J
Allergy Clin Immunol, 2011. 127(3): p. 587-593.e22.
- 7.
Muraro, A., et al., Anaphylaxis: guidelines from the European Academy of Allergy and
Clinical Immunology. Allergy, 2014. 69(8): p. 1026-45.
- 8. Simons, F.E., S. Peterson, and C.D. Black, Epinephrine dispensing for the out-of-hospital treatment of anaphylaxis in infants and children: a population-based study. Ann Allergy Asthma Immunol, 2001. 86(6): p. 622-6.
- 9. Simons, F., Anaphylaxis. J Allergy Clin Immunol, 2010. 125(2 Suppl 2): p. S161-81.
- 10. Tsai, G., et al., Auto-injector needle length may be inadequate to deliver epinephrine intramuscularly in women with confirmed food allergy. Allergy, Asthma & Clinical Immunology, 2014. 10(1): p. 39.