


Product Monograph - Estradot 37.5
Recent Major Label Changes
| 7 Warnings and Precautions, Carcinogenesis and Mutagenesis, Breast Cancer | 2025-12 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................................ 2
Table of Contents ................................................................................................................................. 2
Part 1: Healthcare Professional Information ......................................................................................... 5
1 Indications ............................................................................................................................... 5
1.1 Pediatrics ............................................................................................................................ 5
1.2 Geriatrics ............................................................................................................................. 5
2 Contraindications .................................................................................................................... 5
3 Serious Warnings and Precautions Box .................................................................................... 6
4 Dosage and Administration ..................................................................................................... 6
4.1 Dosing Considerations ........................................................................................................ 6
4.2 Recommended Dose and Dosage Adjustment ................................................................... 7
4.4 Administration .................................................................................................................... 8
4.5 Missed Dose ........................................................................................................................ 8
5 Overdose ................................................................................................................................. 9
6 Dosage Forms, Strengths, Composition, and Packaging ............................................................ 9
7 Warnings and Precautions ..................................................................................................... 10
Carcinogenesis and Mutagenesis ................................................................................................... 10
Cardiovascular ................................................................................................................................ 12
Ear/Nose/Throat ............................................................................................................................ 13
Endocrine and Metabolism ............................................................................................................ 13
Genitourinary ................................................................................................................................. 13
Hematologic ................................................................................................................................... 14
ESTRADOT® Page 3 of 46
Hepatic/ Biliary/ Pancreatic ........................................................................................................... 14
Immune .......................................................................................................................................... 15
Monitoring and Laboratory Tests .................................................................................................. 15
Neurologic ...................................................................................................................................... 16
Renal .............................................................................................................................................. 17
Skin ................................................................................................................................................ 17
7.1 Special Populations ........................................................................................................... 17
7.1.1 Pregnancy ......................................................................................................................... 17
7.1.2 Breastfeeding .................................................................................................................... 17
7.1.3 Pediatrics .......................................................................................................................... 17
7.1.4 Geriatrics ........................................................................................................................... 17
8 Adverse Reactions ................................................................................................................. 17
8.1 Adverse Reaction Overview .............................................................................................. 17
8.2 Clinical Trial Adverse Reactions ........................................................................................ 19
8.3 Less Common Clinical Trial Adverse Reactions ................................................................. 20
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data .......................................................................................................................................... 20
8.5 Post-Market Adverse Reactions ........................................................................................ 21
9 Drug Interactions ................................................................................................................... 22
9.2 Drug Interactions Overview .............................................................................................. 22
9.3 Drug-Behaviour Interactions ............................................................................................. 22
9.4 Drug-Drug Interactions ..................................................................................................... 22
9.5 Drug-Food Interactions ..................................................................................................... 24
9.6 Drug-Herb Interactions ..................................................................................................... 24
9.7 Drug-Laboratory Tests Interactions .................................................................................. 24
10 Clinical Pharmacology ............................................................................................................ 25
10.1 Mechanism of Action ........................................................................................................ 25
10.2 Pharmacodynamics ........................................................................................................... 25
10.3 Pharmacokinetics .............................................................................................................. 25
11 Storage, Stability, and Disposal .............................................................................................. 27
12 Special Handling Instructions ................................................................................................. 27
ESTRADOT® Page 4 of 46
Part 2: Scientific Information ............................................................................................................. 28
13 Pharmaceutical Information .................................................................................................. 28
14 Clinical Trials ......................................................................................................................... 28
14.1 Trial Design and Study Demographic ................................................................................ 28
14.2 Study results ..................................................................................................................... 30
14.3 Comparative Bioavailability Studies ................................................................................. 31
15 Microbiology ......................................................................................................................... 31
16 Non-Clinical Toxicology .......................................................................................................... 32
Patient Medication Information ......................................................................................................... 33
ESTRADOT® Page 5 of 46
Part 1: Healthcare Professional Information
1 Indications
ESTRADOT® (estradiol-17ß) is indicated for:
- the relief of menopausal and postmenopausal symptoms occurring in naturally or surgically induced estrogen deficiency states.
- the prevention of osteoporosis in naturally occurring or surgically induced estrogen-deficiency states in addition to other important therapeutic measures such as adequate diet, calcium and vitamin D intake, cessation of smoking and regular weight-bearing exercise. In postmenopausal women already diagnosed as having osteoporosis and vertebral fractures, treatment with ESTRADOT may retard further bone loss. ESTRADOT is to be considered in the light of other available therapies for osteoporosis prevention and therapy should only be continued as long as the benefits outweigh the risks for the individual (see 3 Serious Warnings and Precautions Box).
In women with intact uteri, ESTRADOT should always be supplemented by sequential administration of a progestin whose role is to prevent endometrial hyperplasia/carcinoma.
1.1 Pediatrics
ESTRADOT is not indicated for use in children.
1.2 Geriatrics
No clinical studies were conducted to evaluate the effect of ESTRADOT on women more than 65 years old.
2 Contraindications
- Known or suspected hypersensitivity to this drug or to any ingredient in the formulation or to any component of the patch. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging section.
- Known or suspected estrogen-dependent malignant neoplasia such as endometrial cancer.
- Endometrial hyperplasia
- Known, suspected or past history of breast cancer
- Known or suspected pregnancy
- Active or past history of confirmed venous thromboembolism (such as deep venous thrombosis or pulmonary embolism) or active thrombophlebitis
- Known thrombophilic disorders
- Liver dysfunction or disease as long as liver function tests have failed to return to normal.
- Undiagnosed abnormal genital bleeding
- Active or past history of arterial thromboembolic disease (e.g. stroke, myocardial infarction, coronary heart disease)
- Porphyria
- Partial or complete loss of vision from ophthalmic vascular disease
- Classical Migraine
ESTRADOT® Page 6 of 46
- Breast feeding
3 Serious Warnings and Precautions Box
The Women’s Health Initiative (WHI) trial examined the health benefits and risks of oral combined estrogen plus progestin therapy (n=16,608) and oral estrogen-alone therapy (n=10,739) in postmenopausal women aged 50 to 79 years.
The estrogen plus progestin arm of the WHI trial (mean age 63.3 years) indicated an increased risk of myocardial infarction (MI), stroke, invasive breast cancer, pulmonary emboli and deep vein thrombosis in postmenopausal women receiving treatment with combined conjugated equine estrogens (CEE, 0.625 mg/day) and medroxyprogesterone acetate (MPA, 2.5 mg/day) for 5.2 years compared to those receiving placebo.
The estrogen-alone arm of the WHI trial (mean age 63.6 years) indicated an increased risk of stroke and deep vein thrombosis in hysterectomized women treated with CEE-alone (0.625 mg/day) for 6.8 years compared to those receiving placebo.
Therefore, the following should be given serious consideration at the time of prescribing:
- Estrogens with or without progestins should not be prescribed for primary or secondary prevention of cardiovascular diseases.
- Estrogens with or without progestins should be prescribed at the lowest effective dose for the approved indication.
- For the prevention of osteoporosis, ESTRADOT should be considered in light of other available therapies.
- Estrogens with or without progestins should be prescribed for the shortest period possible for the approved indication.
4 Dosage and Administration
4.1 Dosing Considerations
- For all therapeutic indications, the lowest effective dose should be used for maintenance therapy (see Coadministration of Progestins).
- Hormone replacement therapy (HRT) involving either estrogen alone or estrogen-progestogen combined therapy should only be continued as long as the benefits outweigh the risks for the individual.
- In women who are not currently taking oral estrogens, treatment with ESTRADOT (estradiol-17ß) can be initiated at once. In women who are currently taking oral estrogens, treatment with ESTRADOT can be initiated on reappearance of menopausal symptoms, following discontinuation of oral therapy.
ESTRADOT® Page 7 of 46
- ESTRADOT is administered as continuous therapy (uninterrupted application). ESTRADOT should be applied twice weekly i.e., the patch should be changed once every 3-4 days.
- In women with intact uteri, a progestin should be sequentially coadministered for 12 to 14 days per cycle to avoid overstimulation of the endometrium. The addition of sufficient progestin to induce secretory transformation of the endometrium during estrogen replacement therapy is mandatory.
- Abnormal vaginal bleeding, due to its prolongation, irregularity or heaviness, in any patient receiving hormone replacement therapy requires institution of prompt diagnostic measures like endometrial biopsy or curettage to rule out the possibility of uterine malignancy.
- The short term effects of progestin coadministration may include vaginal bleeding during or after progestin treatment, breast tenderness, and mood and weight changes. The long-term effects generally depend on the dosage and type of progestin used. The lowest effective dose of estrogen and progestin should be prescribed (see Coadministration of Progestins).
- ESTRADOT should be prescribed with an appropriate dosage of a progestin for women with intact uteri in order to prevent endometrial hyperplasia/carcinoma. Progestin therapy is not required as part of hormone replacement therapy in women who have had a previous hysterectomy.
See 7 Warnings and Precautions section on the examination of the patient before ESTRADOT administration.
4.2 Recommended Dose and Dosage Adjustment
- 1. Menopausal symptoms
Treatment of menopausal symptoms is usually initiated with a patch that releases 50 mcg estradiol-17ß per day i.e. ESTRADOT 50. Thereafter the dosage should be adapted to the needs of the individual.
Breast discomfort, breakthrough or heavy vaginal bleeding, water retention, bloating or nausea (if persisting for more than six weeks), are generally signs that the estrogen dose is too high and needs to be lowered. If on the other hand, the selected dose fails to eliminate the signs and symptoms of estrogen deficiency, a higher dose may be considered.
For maintenance therapy one should always use the lowest dose that still proves effective. The requirement for hormone replacement therapy for menopausal symptoms should be reassessed periodically. Attempts to taper or discontinue the medication should be made at 3 to 6 month intervals.
- 2. Prevention of post-menopausal osteoporosis
For optimal prevention of postmenopausal bone loss in women for whom the drug is indicated, therapy should be initiated as soon as possible after diagnosis of menopause. The dosage of estradiol-17ß may require adjustment according to the patient's clinical status, the plasma estradiol-17ß levels and the results of bone mineral density studies. Ideally, plasma estradiol-17ß levels should be maintained at 183 pM/L (50 picogram/mL).
Discontinuation of hormone replacement therapy may reestablish the natural rate of bone loss.
ESTRADOT® Page 8 of 46
Special Populations
Patients with renal and / or hepatic impairment
No studies were performed in the patients with renal and hepatic impairment.
All estrogen preparations are contraindicated in the patients with severe hepatic impairment.
Pediatric population
ESTRADOT is not indicated for use in children.
4.4 Administration
Patch Application
The physician should discuss the most appropriate placement of the patch with the patient. Immediately after removal of a patch from the pouch and removal of the protective liner, the adhesive side of the ESTRADOT patch should be placed on a clean, dry area of intact skin. The area selected should not be oily, damaged or irritated, and not exposed to the sun. The site selected should also be one at which little wrinkling of the skin occurs during movement of the body, preferably the buttocks, lower abdomen or hip. The patch may also be placed on the side or lower back. The patch should be placed consistently on the same area of the body with each application (i.e., either the buttocks, lower abdomen, hip, side or lower back). Experience to date has shown that less irritation of the skin occurs on the buttocks than on other sites of application. Therefore, it is advisable to apply ESTRADOT to the buttocks. The waistline should be avoided, since tight clothing may dislodge the patch. The patch should be pressed firmly in place with the palm of the hand, making sure there is good contact, especially around the edges. In the event that a patch should fall off, it can be reapplied. If it fails to adhere then a new patch may be applied. In either case, the original treatment schedule should be continued. Patches should not be applied to the same skin site twice in succession.
ESTRADOT must not never be applied to, or near, the breasts to avoid potentially harmful effects on the breast tissue.
Coadministration of Progestins
Studies have reported that the addition of a progestin for 10 or more days of a cycle of estrogen administration greatly lowers the incidence of endometrial hyperplasia, and thereby irregular bleeding and endometrial carcinoma, compared to estrogen treatment alone. This applies to women with intact uteri and not to those who have had hysterectomies.
4.5 Missed Dose
Patients who miss applying a patch of ESTRADOT, should apply a new patch as soon as possible. The subsequent patch should be applied according to the original treatment schedule. The interruption of treatment might increase the likelihood of recurrence of symptoms.
ESTRADOT® Page 9 of 46
5 Overdose
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
Symptoms of overdose
Numerous reports of ingestion of large doses of estrogen products and estrogen-containing oral contraceptives by young children have not revealed acute serious ill effects. Overdosage with estrogen may cause nausea, breast discomfort, fluid retention, bloating or vaginal bleeding in women.
Treatment of overdose
Owing to the mode of administration (transdermal), plasma levels of estradiol-17ß can be rapidly reduced by removal of the patch. Symptomatic treatment should be given.
6 Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
| Transdermal | Patch 25, 37.5, 50, 75 and 100 mcg | Cellulose compounds, ethanol, ethylene-vinyl acetate copolymer, light mineral oil, polyester and polyisobutylene. |
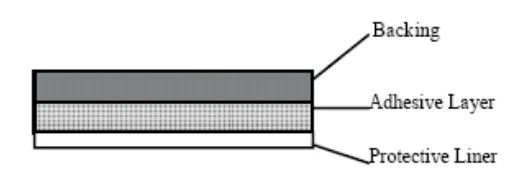
The ESTRADOT patch is thin, rounded rectangular, multilayer, transparent transdermal therapeutic system, i.e., an adhesive patch, containing estradiol 17ß that is designed for application to an area of intact skin.
Proceeding from the visible surface toward the surface attached to the skin, the ESTRADOT patch is comprised of three layers:
- 1. a translucent polyolefin film
- 2. an adhesive formulation containing estradiol, acrylic adhesive, silicone adhesive, oleyl alcohol, povidone and dipropylene glycol
- 3. a polyester release liner which is attached to the adhesive surface and must be removed before the system can be used.
The active component of the patches is estradiol 17ß.
ESTRADOT® Page 10 of 46
The matrix provides a source for continuous delivery of drug for up to 4 days. ESTRADOT is available in 5 strengths; the composition per unit area in each strength is identical (see 4 Dosage and Administration section).
ESTRADOT (estradiol-17ß) is available in the following strengths in patient packs containing 8 patches:
| ESTRADOT 25 | ESTRADOT 37.5 | ESTRADOT 50 | ESTRADOT 75 | ESTRADOT 100 | |
| Estradiol-17ß Dosage nominal in vivo delivery | 25 mcg/day | 37.5 mcg/day | 50 mcg/day | 75 mcg/day | 100 mcg/day |
| Total Estradiol-17ß content | 0.39 mg | 0.585 mg | 0.78 mg | 1.17 mg | 1.56 |
| Drug-Releasing Area | 2.5 cm2 | 3.75 cm2 | 5 cm2 | 7.5 cm2 | 10 cm2 |
| Shape of Patch | Rounded rectangle | Rounded rectangle | Rounded rectangle | Rounded rectangle | Rounded rectangle |
7 Warnings and Precautions
Carcinogenesis and Mutagenesis
Breast Cancer
Epidemiological data/meta-analysis: A large meta-analysis of prospective cohort studies based on 108, 647 postmenopausal women who developed breast cancer at mean age of 65 years old, also reported an increased risk of developing breast cancer in women treated with estrogen plus progestin therapy or estrogen alone therapy. Not only the risk of breast cancer increases with the duration of use, but also the risk could last up to >10 years after discontinuation of treatment. Observational studies also suggest that the risk of breast cancer was greater, and became apparent earlier, with estrogen plus progestin therapy as compared to estrogen-alone therapy. These studies have not generally found significant variation in the risk of breast cancer among different estrogen plus progestin combinations, doses, or routes of administration.
Available epidemiological data indicate that the use of combined estrogen plus progestin by postmenopausal women is associated with an increased risk of invasive breast cancer.
In the estrogen plus progestin arm of the WHI trial, among 10,000 women over a one-year period, there were:
- 8 more cases of invasive breast cancer (38 on combined HRT versus 30 on placebo).
The WHI study also reported that the invasive breast cancers diagnosed in the estrogen plus progestin group were similar in histology but were larger (mean (SD), 1.7 cm (1.1) vs. 1.5 cm (0.9), respectively; P=0.04) and were at a more advanced stage compared with those diagnosed in the placebo group. The percentage of women with abnormal mammograms (recommendations for short-interval follow-up, a
ESTRADOT® Page 11 of 46
suspicious abnormality, or highly suggestive of malignancy) was significantly higher in the estrogen plus progestin group versus the placebo group. This difference appeared at year one and persisted in each year thereafter.
In the estrogen-alone arm of the WHI trial, there was no statistically significant difference in the rate of invasive breast cancer in hysterectomized women treated with conjugated equine estrogens versus women treated with placebo.
It is recommended that estrogens not be given to women with existing breast cancer or those with a previous history of the disease (see 2 Contraindications).
There is a need for caution in prescribing estrogens for women with known risk factors associated with the development of breast cancer, such as strong family history of breast cancer (first degree relative) or who present a breast condition with an increased risk (breast nodules, fibrocystic disease of the breast, abnormal mammograms and/or atypical hyperplasia at breast biopsy).
Other known risk factors for the development of breast cancer such as nulliparity, obesity, early menarche, late age at first full term pregnancy and at menopause should also be evaluated.
It is recommended that women undergo mammography prior to the start of HRT treatment and at regular intervals during treatment, as deemed appropriate by the treating physician and according to the perceived risks for each patient.
The overall benefits and possible risks of hormone replacement therapy should be fully considered and discussed with patients. It is important that the modest increased risk of being diagnosed with breast cancer after 4 years of treatment with combined estrogen plus progestin HRT (as reported in the results of WHI-trial) be discussed with the patient and weighed against its known benefits.
Instructions for regular self-examination of the breasts should be included in this counseling.
Endometrial Hyperplasia & Endometrial Carcinoma
Estrogen should be prescribed with an appropriate dosage of a progestin for women with intact uteri in order to prevent endometrial hyperplasia/carcinoma.
Estrogen-only hormonal therapy in postmenopause is recommended for women without uteri only to avoid unnecessary exposure to progestins. The focus of the clinical program with VIVELLE®/ESTRADOT was the demonstration of efficacy in the treatment of postmenopausal symptoms and in the prevention of postmenopausal osteoporosis. Some clinical trials included non-hysterectomized patients who were treated with concomitant progestogen therapy according to the best medical practice at the time, with different dosages, regimens and types of progestin. In addition, endometrial sampling after treatment was not consistently performed and in most cases no baseline data were available to assess the relationship and the effects of the progestogen treatment on the endometrium.
The risk of endometrial hyperplasia/carcinoma in users of unopposed estrogens who have intact uteri is greater than in non-users and appears to depend on the duration of treatment and the estrogen dose. The greatest risk appears to be associated with prolonged use. It has been shown that adequate concomitant progestogen therapy lowers the incidence of endometrial hyperplasia and therefore the potential risk of endometrial carcinoma associated with prolonged use of estrogen therapy (see Coadministration of Progestins).
ESTRADOT® Page 12 of 46
Ovarian Cancer
Some recent epidemiologic studies have found that the use of hormone replacement therapy (estrogen-alone and estrogen plus progestin therapies), in particular for five or more years, has been associated with an increased risk of ovarian cancer. Epidemiologic evidence from a meta-analysis suggests that while the risk of ovarian cancer diminishes over time after discontinuation, the risk is still significantly increased more than five years (median time of 10 years since last use) after stopping long duration hormone therapy (median duration of treatment of nine years) for serous or endometrioid tumours.
Hepatocellular Carcinomas
Hepatocellular carcinoma has also been reported in women taking estrogen-containing oral contraceptives. The causal relationship of this malignancy to these drugs is not known.
Cardiovascular
The results of the Heart and Estrogen/progestin Replacement Studies (HERS and HERS II) and the Women’s Health Initiative (WHI) trial indicate that the use of estrogen plus progestin is associated with an increased risk of coronary heart disease (CHD) in postmenopausal women. The results of the WHI trial indicate that the use of estrogen-alone and estrogen plus progestin is associated with an increased risk of stroke in postmenopausal women.
WHI trial findings
In the combined estrogen plus progestin arm of the WHI trial, among 10,000 women over a one-year period, there were:
- 8 more cases of stroke (29 on combined HRT versus 21 on placebo)
- 7 more cases of CHD (37 on combined HRT versus 30 on placebo).
In the estrogen-alone arm of the WHI trial of women with prior hysterectomy, among 10,000 women over a one-year period, there were/was:
- 12 more cases of stroke (44 on estrogen-alone therapy versus 32 on placebo)
- no statistically significant difference in the rate of CHD.
HERS and HERS II findings
In the Heart and Estrogen/progestin Replacement Study (HERS) of postmenopausal women with documented heart disease (n=2763, average age 66.7 years), a randomized placebo-controlled clinical trial of secondary prevention of coronary heart disease (CHD), treatment with 0.625 mg/day oral conjugated equine estrogen (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) demonstrated no cardiovascular benefit. Specifically, during an average follow-up of 4.1 years, treatment with CEE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established coronary heart disease. There were more CHD events in the hormone-treated group than in the placebo group in year 1, but not during the subsequent years.
From the original HERS trial, 2321 women consented to participate in an open label extension of HERS, known as HERS II. Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years
ESTRADOT® Page 13 of 46
overall. After 6.8 years, hormone therapy did not reduce the risk of cardiovascular events in women with CHD.
Blood pressure
Women using hormone replacement therapy sometimes experience increased blood pressure. Blood pressure should be monitored with HRT use. Elevation of blood pressure in previously normotensive or hypertensive patients should be investigated and HRT may have to be discontinued.
Ear/Nose/Throat
Otosclerosis
Estrogens should be used with caution in patients with otosclerosis.
Endocrine and Metabolism
Glucose and lipid metabolism
A worsening of glucose tolerance and lipid metabolism have been observed in a significant percentage of peri- and post-menopausal patients. Therefore, diabetic patients or those with a predisposition to diabetes should be observed closely to detect any alterations in carbohydrate or lipid metabolism, especially in triglyceride blood levels.
Women with familial hyperlipidemias or porphyria need special surveillance. Lipid-lowering measures are recommended additionally, before treatment is started.
Calcium and phosphorus metabolism
Because the prolonged use of estrogens influences the metabolism of calcium and phosphorus, estrogens should be used with caution in patients with metabolic and malignant bone diseases associated with hypercalcemia and in patients with renal insufficiency.
Hypothyroidism
Patients who require thyroid hormone replacement therapy and who are also taking estrogen should have their thyroid function monitored regularly to assure that thyroid hormone levels remain in an acceptable range (see 9.7 Drug-Laboratory Tests Interactions).
Genitourinary
Vaginal bleeding
Abnormal vaginal bleeding, due to its prolongation, irregularity or heaviness, occurring during therapy should prompt appropriate diagnostic measures to rule out the possibility of uterine malignancy and the treatment should be re-evaluated.
Uterine leiomyomata
Pre-existing uterine leiomyomata may increase in size during estrogen use. Growth, pain or tenderness of uterine leiomyomata requires discontinuation of medication and appropriate investigation.
ESTRADOT® Page 14 of 46
Endometriosis
Symptoms and physical findings associated with a previous diagnosis of endometriosis may reappear or become aggravated with estrogen use.
Hematologic
Venous Thromboembolism
Available epidemiological data indicate that the use of estrogen with or without progestin by postmenopausal women is associated with an increased risk of developing venous thromboembolism (VTE).
In the estrogen plus progestin arm of the WHI trial, among 10,000 women on combined HRT over a one-year period, there were 18 more cases of venous thromboembolism, including 8 more cases of pulmonary embolism.
In the estrogen-alone arm of the WHI trial, among 10,000 women on estrogen therapy over a one-year period, there were 7 more cases of venous thromboembolism, although there was no statistically significant difference in the rate of pulmonary embolism.
Generally recognized risk factors for VTE include a personal history, a family history (the occurrence of VTE in a direct relative at a relatively early age may indicate genetic predisposition), severe obesity (body mass index > 30 kg/m2) and systemic lupus erythematosus. The risk of VTE also increases with age and smoking.
A history of recurrent spontaneous abortions should be investigated to exclude thrombophilic predisposition. In patients in whom thrombophilia is confirmed, the use of ESTRADOT is viewed as contraindicated.
The risk of VTE may be temporarily increased with prolonged immobilization, major surgery or trauma. In women on HRT, attention should be given to prophylactic measures to prevent VTE following surgery. Also, patients with varicose veins should be closely supervised. The physician should be alert to the earliest manifestations of thrombotic disorders (thrombophlebitis, retinal thrombosis, cerebral embolism and pulmonary embolism). If these occur or are suspected, hormone therapy should be discontinued immediately given the risks of long-term disability or fatality.
If feasible, estrogens should be discontinued at least 4 weeks before major surgery which may be associated with an increased risk of thromboembolism, or during periods of prolonged immobilization. The treatment should not be restarted until the woman is completely mobile.
Hepatic/ Biliary/ Pancreatic
Benign Hepatic Adenomas
Benign hepatic adenomas have been associated with the use of combined estrogen and progestin oral contraceptives. Although benign and rare, these tumours may rupture and cause death from intra-abdominal hemorrhage. Such lesions have not yet been reported in association with other estrogen or progestin preparations, but they should be considered if abdominal pain and tenderness, abdominal mass, or hypovolemic shock occurs in patients receiving estrogen.
ESTRADOT® Page 15 of 46
Gallbladder Diseases
A 2- to 4-fold increase in the risk of gallbladder disease requiring surgery in women receiving postmenopausal estrogens has been reported.
Hepatic hemangiomas
Particular caution is indicated in women with hepatic hemangiomas, as estrogen may cause an exacerbation of this condition.
Jaundice
Caution is advised in patients with a history of liver and/or biliary disorders. If cholestatic jaundice develops during treatment, the treatment should be discontinued and appropriate investigations carried out.
Liver function tests
Liver function tests should be done periodically in subjects who are suspected of having hepatic disease. For information on endocrine and liver function tests, see the section under Monitoring and Laboratory Tests.
Immune
Severe anaphylactic/anaphylactoid reactions and angioedema
Cases of anaphylactic/anaphylactoid reactions, which developed anytime during the course of estradiol treatment and required emergency medical management, have been reported in the post marketing setting. Involvement of skin (urticaria, pruritus, swelling of the face, throat, lips, tongue, skin and periorbital edema) and either respiratory tract (respiratory compromise) or gastrointestinal tract (abdominal pain, vomiting) has been noted.
Estrogens may induce or exacerbate symptoms of angioedema, in particular in women with hereditary angioedema. Angioedema requiring medical intervention involving eye/eyelid, face, larynx, pharynx, tongue and extremity (hands, legs, ankles, and fingers) with or without urticaria has occurred in the post marketing experience of using estradiol. If angioedema involves the tongue, glottis, or larynx, airway obstruction may occur. Patients who develop angioedema after treatment with estradiol should not receive ESTRADOT again.
Systemic lupus erythematosus
Particular caution is indicated in women with systemic lupus erythematosus.
Monitoring and Laboratory Tests
Before ESTRADOT (estradiol-17ß) is administered, the patient should have a complete physical examination including a blood pressure determination. Breasts and pelvic organs should be appropriately examined and a Papanicolaou smear should be performed. Endometrial biopsy should be done only when indicated. Baseline tests should include mammography, measurements of blood glucose, calcium, triglycerides and cholesterol, and liver function tests.
ESTRADOT® Page 16 of 46
The first follow-up examination should be done within 3-6 months after initiation of treatment to assess response to treatment. Thereafter, examinations should be made at intervals at least once a year. Appropriate investigations should be arranged at regular intervals as determined by the physician.
The importance of regular self-examination of the breasts should be discussed with the patient.
Women should be advised that changes in their breasts should be reported to their doctor or nurse.
Neurologic
Cerebrovascular insufficiency
Patients who develop visual disturbances, classical migraine, transient aphasia, paralysis or loss of consciousness should discontinue medication.
Patients with a previous history of classical migraine and who develop a recurrence or worsening of migraine symptoms should be reevaluated.
Dementia
Available epidemiological data indicate that the use of combined estrogen plus progestin in women age 65 and over may increase the risk of developing probable dementia.
The Women’s Health Initiative Memory Study (WHIMS), a clinical sub-study of the WHI, was designed to assess whether postmenopausal hormone replacement therapy (oral estrogen plus progestin or oral estrogen-alone) reduces the risk of dementia in women aged 65 and over (age range 65-79 years) and free of dementia at baseline.
In the estrogen plus progestin arm of the WHIMS (n=4532), women with intact uteri were treated with daily 0.625 mg conjugated equine estrogens (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) or placebo for an average of 4.05 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 23 more cases of probable dementia (45 on combined HRT versus 22 on placebo).
In the estrogen-alone arm of the WHIMS (n=2947), women with prior hysterectomy were treated with daily 0.625 mg CEE or placebo for an average of 5.21 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 12 more cases of probable dementia (37 on estrogen-alone versus 25 on placebo), although this difference did not reach statistical significance.
When data from the estrogen plus progestin arm of the WHIMS and the estrogen alone arm of the WHIMS were combined, as per the original WHIMS protocol, in 10,000 women over a one-year period, there were:
- 18 more cases of probable dementia (41 on estrogen plus progestin or estrogen-alone versus 23 on placebo).
For transdermal estrogen-only or estrogen-progestogen combined products, no large randomized clinical trials have assessed the HRT-associated risk of probable dementia to date. Therefore there are no data to support the conclusion that the frequency of probable dementia is different with ESTRADOT.
ESTRADOT® Page 17 of 46
Epilepsy
Particular caution is indicated in women with epilepsy, as estrogen, with or without progestins, may cause an exacerbation of this condition.
Renal
Fluid retention
Estrogens may cause fluid retention. Therefore, particular caution is indicated in cardiac or renal dysfunction or asthma. If, in any of the above-mentioned conditions, a worsening of the underlying disease is diagnosed or suspected during treatment, the benefits and risks of treatment should be reassessed based on the individual case.
Skin
Contact Sensitization
Contact sensitization is known to occur with topical applications. Although it is extremely rare, patients who develop contact sensitization to any component of the patch should be warned that a severe hypersensitivity reaction may occur with continuing exposure to the causative agent.
7.1 Special Populations
7.1.1 Pregnancy
ESTRADOT must not be used during pregnancy. Both estrogens and progestogens may cause fetal harm when administered to a pregnant woman (see 2 Contraindications).
7.1.2 Breastfeeding
ESTRADOT must not be used while breastfeeding (see 2 Contraindications).
7.1.3 Pediatrics
ESTRADOT is not indicated for use in children.
7.1.4 Geriatrics
No clinical studies were conducted to evaluate the effect of ESTRADOT on women more than 65 years old.
8 Adverse Reactions
8.1 Adverse Reaction Overview
See 7 Warnings and Precautions regarding potential induction of malignant neoplasms and adverse effects similar to those of oral contraceptives.
The following adverse reactions have been reported with estrogen/progestin combinations in general.
ESTRADOT® Page 18 of 46
Blood and lymphatic system disorders
Altered coagulation tests (see 7 Warnings and Precautions and 9 Drug Interactions, 9.7 Drug-Laboratory Tests Interactions)
Cardiac disorders
Palpitations; increase in blood pressure (see 7 Warnings and Precautions), coronary thrombosis.
Endocrine disorders
Increased blood sugar levels; decreased glucose tolerance.
Eye disorders
Neuro-ocular lesions (e.g., retinal thrombosis, optic neuritis), visual disturbances; steepening of the corneal curvature; intolerance to contact lenses, (dry eyes and tear film compositions changes).
Gastrointestinal disorders
Nausea; vomiting; abdominal discomfort (cramps, pressure, pain; bloating).
General disorders and administration site conditions
Fatigue; changes in appetite; changes in body weight; change in libido.
Hepatobiliary disorders
Gallbladder disorder; asymptomatic impaired liver function; cholestatic jaundice.
Musculoskeletal and connective tissue disorders
Musculoskeletal pain including leg pain not related to thromboembolic disease (usually transient, lasting 3-6 weeks) may occur.
Nervous system disorders
Aggravation of migraine episodes; headaches; dizziness; neuritis.
Psychiatric disorders
Mental depression; nervousness; irritability.
Renal and urinary disorders
Cystitis; dysuria; sodium retention; edema.
Reproductive system and breast disorders
Breakthrough bleeding; spotting; change in menstrual flow; dysmenorrhea; vaginal itching/discharge; dyspareunia ; endometrial hyperplasia; pre-menstrual-like syndrome; reactivation of endometriosis; changes in cervical erosion and amount of cervical secretion; breast swelling and tenderness.
ESTRADOT® Page 19 of 46
Skin and subcutaneous tissue disorders
Loss of scalp hair; chloasma or melasma, which may persist when drug is discontinued; erythema nodosum; erythema multiforme; hemorrhagic skin eruptions; hirsutism, acne.
Vascular disorders
Isolated cases of thrombophlebitis; thromboembolic disorders and cerebrovascular accident.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following adverse reactions have been reported with estrogen/progestin combinations in general.
The most commonly reported adverse reaction to VIVELLE® (estradiol-17ß), another matrix patch, in clinical trials in patients treated for post-menopausal symptoms was redness and irritation at the application site. This caused approximately 0.8% of patients to discontinue therapy. In a comparative clinical trial, ESTRADOT was found to be less irritating than VIVELLE®.
In a 2-year controlled trial in patients with post-menopausal osteoporosis, back pain was reported in 13% of patients treated with the VIVELLE® patch and 4.5% of patients treated with placebo. Local application site reactions (patch site erythema, itching, rash, burning, irritation) were reported in approximately 9% of patients treated with active patch and 10% of patients treated with placebo. In most cases the local application site reactions were considered mild; none was considered severe. Two patients out of 259 were discontinued from the trial due to local application site reactions.
Frequency estimate: very common ≥10%, common ≥ 1% to < 10%; uncommon ≥ 0.1% to < 1%; rare ≥ 0.01% to < 0.1%; very rare < 0.01%; with unknown frequency.
Table 2 – Most Common Adverse Drug Reactions (≥1%)
Psychiatric disorders
Common:
Depression
Nervous system disorders
Common:
Headache, Migraine, Dizziness
Gastrointestinal disorders
Common:
Nausea, Abdominal pain, Abdominal distension
Reproductive system and breast disorders
Very common:
Breast tenderness
Common:
Menstrual disorders, Metrorrhagia, Cervical discharge, Breast enlargement
General disorders and administration site conditions
Very common:
Application site reaction*
Common:
Weight fluctuation, Oedema, Pruritus and rash
*Application site reactions include localized bleeding, bruising, burning, discomfort, dryness, eczema, edema, erythema, inflammation, irritation, pain, papules, paraesthesia, pruritus, rash, skin discolouration, skin pigmentation, swelling, urticaria, and vesicles.
ESTRADOT® Page 20 of 46
8.3 Less Common Clinical Trial Adverse Reactions
Gastrointestinal disorders:
Uncommon: Vomiting
General disorders and administration site conditions:
Uncommon: Libido increased or decreased
Neoplasms benign, malignant and unspecified (including cysts and polyps):
Uncommon: Breast cancer
Reproductive system and breast disorders:
Uncommon: Genital candidiasis, Uterine leiomyoma
Skin and subcutaneous tissue disorders:
Uncommon: Alopecia, Hirsutism
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Table 3 – Abnormal hematologic and clinical chemistry
| Laboratory parameters | Effect |
|---|---|
| Antithrombin III | ↓ |
| Coagulation factors VII, VIII, IX, X | ↑ |
| Corticosteroid binding globulin (CBG) | CBG ↑ in serum ➔ increased circulating corticosteroids. free or biologically active hormone concentrations are unchanged |
| Fibrinogen and fibrinogen activity | ↑ levels |
| Folate | ↓ serum concentration |
| T3 | ↓ Resin uptake , reflecting the elevated TBG |
| Free T4 | concentration unaltered |
| Glucose | impaired glucose tolerance |
| METOPIRONE test | Reduced response |
| Norepinephrine-induced platelet aggregability | ↑ |
| Partial tromboplastin time | ↓ |
Sex-hormone binding globulin (SHBG) | SHBG↑ in serum due to increased circulating estrogen |
ESTRADOT® Page 21 of 46
| Laboratory parameters | Effect |
|---|---|
| Sulfobromophthalein | ↑ retention |
| Triglyceride and Phospholipid | ↑ serum concentration |
| Thyroxin-binding globulin (TBG) | ↑ ➔ increased circulating total thyroid hormone (T4) as measured by column or radioimmunoassay |
If adverse symptoms persist, the prescription of HRT should be re-considered.
8.5 Post-Market Adverse Reactions
Adverse Drug Reactions with unknown frequency
Cardiac disorders:
Embolism, hypertension
Gastrointestinal disorders:
Cholelithiasis, liver function tests abnormal, diarrhoea
Immune system disorders:
Anaphylactic reaction, anaphylactoid reaction, hypersensitivity
Musculoskeletal and connective tissue disorder
Back pain, pain in extremities
Reproductive system and breast disorders:
Endometrial hyperplasia, breast discomfort, breast pain, dysmenorrhea, fibrocystic breast disease, breast discharge
Skin and subcutaneous tissue disorders:
Angioedema, erythema nodosum, erythema multiforme, rash generalised, pruritus generalized, urticaria, contact dermatitis, chloasma.
Hypersensitivity, including allergic contact dermatitis and isolated cases of anaphylactoid reactions (some of the patients had a history of previous allergy or allergic disorders).
Reversible post-inflammatory pigmentation and precipitation or aggravation of porphyria cutanea tarda in predisposed individuals
Nervous system disorders
chorea.
Psychiatric disorders
Nervousness, affect liability
Vascular disorders
varicose veins
ESTRADOT® Page 22 of 46
9 Drug Interactions
9.2 Drug Interactions Overview
- Estrogens may diminish the effectiveness of anticoagulant, antidiabetic and antihypertensive agents.
- Preparations inducing liver enzymes (e.g. barbiturates, hydantoins, carbamazepine, meprobamates, phenylbutazone rifampicin, rifabutin, nevirapine and efavirenz) may interfere with the activity of orally administered estrogens.
- Estradiol is predominantly metabolized by CYP3A4; concomitant administration of inhibitors of CYP3A4 such as ketoconazole, erythromycin or ritonavir may therefore result in an increase of approximately 50% in estradiol exposure.
9.3 Drug-Behaviour Interactions
Specific drug-behavioural interaction studies have not been conducted with ESTRADOT.
Acute alcohol ingestion during HRT may lead to elevations in circulating estradiol levels.
9.4 Drug-Drug Interactions
The following section contains information on drug interactions with ethinyl estradiol-containing products (specifically, oral contraceptives) that have been reported in the public literature. It is unknown whether such interactions occur with drug products containing other types of estrogens.
Table 4 – Established or Potential Drug-Drug Interactions
| Drug | Ref | Effect | Clinical comment |
Anticonvulsants (phenobarbital, phenytoin, carbamazepin) | T | ↑ metabolism of ethinyl estradiol | ↓ plasma concentration of estradiol |
| Acetaminophen | T | ↑ AUC and/or plasma concentration of ethinyl estradiol ↓ plasma concentration of acetaminophen | Therapeutic monitoring is recommended |
| Acid ascorbic | T | ↑ AUC and/or plasma concentration of ethinyl estradiol | Therapeutic monitoring is recommended |
| Aminoglutethimide with medroxyprogesterone acetate (MPA) | T | ↓ bioavailability of MPA | Therapeutic monitoring is recommended |
ESTRADOT® Page 23 of 46
| Drug | Ref | Effect | Clinical comment |
| Atorvastatin | T | ↑ AUC values for ethinyl estradiol by 20 % | Therapeutic monitoring is recommended |
| Clofibric acid | ↑ clearance of clofibric acid | Therapeutic monitoring is recommended | |
| Cyclosporin | T | ↑ plasma concentration of cyclosporine. | Therapeutic monitoring is recommended |
| Lamotrigine | T | ↓ plasma concentration of lamotrigrine | Although the potential interaction between hormone replacement therapy and lamotrigine has not been studied, concomitant administration of lamotrigine with estradiol has been shown to significantly decrease plasma concentrations of lamotrigine when co-administered due to induction of lamotrigine glucuronidation. This may lead to a reduction in seizure control among women taking both medicinal products together. |
| Morphine | T | ↑ clearance of morphine | Therapeutic monitoring is recommended |
| Prednisolone | T | ↑ plasma concentration of prednisolone | Therapeutic monitoring is recommended |
| Rifampicinª | T | ↑ metabolism of ethinyl estradiol | ↓ plasma concentration of estradiol |
| Salicylic acid | T | ↑ clearance of salicylic acid | Therapeutic monitoring is recommended |
| Temazepam | T | ↑ clearance of temazepam | Therapeutic monitoring is recommended |
ESTRADOT® Page 24 of 46
| Drug | Ref | Effect | Clinical comment |
| Theophylline | T | ↑ plasma concentration of theophylline | Therapeutic monitoring is recommended |
| Troglitazone | T | ↓ plasma concentrations of ethinyl estradiol by 30 % | Therapeutic monitoring is recommended |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
ª Clinical pharmacokinetics studies have not demonstrated any consistent effect of antibiotics (other than rifampicin) on plasma concentrations of synthetic steroids.
9.5 Drug-Food Interactions
The interaction of ESTRADOT with food has not been studied.
9.6 Drug-Herb Interactions
It was found that some herbal products (e.g., St. John’s wort) which are available as over-the-counter (OTC) products might interfere with steroid metabolism, and therefore, alter the efficacy and safety of estrogen/progestin products.
Physicians and other health care providers should be made aware of other non-prescription products concomitantly used by the patient, including herbal and natural products obtained from the widely spread health stores.
9.7 Drug-Laboratory Tests Interactions
The results of certain endocrine and liver function tests may be affected by estrogen-containing products:
- decreased partial thromboplastin time; increased levels of fibrinogen and fibrinogen activity; increased coagulation factors VII, VIII, IX, X; increased norepinephrine-induced platelet aggregability; decreased antithrombin III;
- increased thyroxine-binding globulin (TBG), leading to increased circulating total thyroid hormone (T4) as measured by column or radioimmunoassay; T3 resin uptake is decreased, reflecting the elevated TBG; free T4 concentration is unaltered;
- other binding proteins may be elevated in serum i.e., corticosteroid binding globulin (CBG), sex-hormone binding globulin (SHBG), leading to increased circulating corticosteroids and sex steroids respectively; free or biologically active hormone concentrations are unchanged;
- impaired glucose tolerance;
- increased serum triglyceride and phospholipid concentration.
(See also Table 3 in 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data section)
ESTRADOT® Page 25 of 46
With ESTRADOT, no effect on fibrinogen, antithrombin III, TBG, CBG or SHBG and decreases in serum triglycerides have been observed.
The results of the above laboratory tests should not be considered reliable unless therapy has been discontinued for two to four weeks. The pathologist should be informed that the patient is receiving estrogen therapy when relevant specimens are submitted.
10 Clinical Pharmacology
10.1 Mechanism of Action
ESTRADOT is designed to deliver daily estradiol-17ß, a physiologic hormone, transdermally into the systemic circulation. Due to the transdermal route of administration, the estradiol-17ß does not undergo first-pass liver metabolism. Resultant estradiol-17ß plasma levels are comparable to those seen in premenopausal women in the early follicular phase of the menstrual cycle. Estradiol-17ß stimulates target tissues such as the uterus, breast and vagina (see 10 Clinical Pharmacology).
ESTRADOT delivers estradiol-17ß via the skin, which metabolizes estradiol only to a small extent. In comparison, orally administered estrogens are rapidly metabolized by the liver to estrone and its conjugates, giving rise to higher circulating levels of estrogens than transdermal estradiol. Therefore, transdermal administration of estradiol produces therapeutic plasma levels with lower circulating levels of estrone conjugates and requires smaller total doses than does oral therapy.
10.2 Pharmacodynamics
Estradiol
The active substance in ESTRADOT, 17beta-estradiol, is chemically and biologically identical to the endogenous human 17beta-estradiol and is classified as a natural estrogen. It compensates for the decreasing estrogen production in menopausal women and alleviates menopausal symptoms. Estradiol prevents bone loss after the menopause or after an ovariectomy.
Hormone Replacement Therapy
ESTRADOT (estradiol-17ß) provide continuous, controlled transdermal delivery of estradiol-17ß such that estradiol-17ß levels as well as the E2/E1 ratio in postmenopausal women are restored to those seen in the earlier follicular phase of the premenopausal range (see 10.3 Pharmacokinetics). ESTRADOT thus alleviate the symptoms of estradiol-17ß deficiency in menopausal women.
10.3 Pharmacokinetics
Absorption
Studies in postmenopausal women using other estradiol-17ß matrix patches (VIVELLE®) which provide 37.5, 50, 75 and 100 mcg of exogenous estradiol-17ß per day, showed increased blood levels within 4 hours. These levels were linearly proportional to the size of the dose and maintained respective mean serum estradiol-17ß levels of 92, 173, 217 and 308 pM/L (25, 47, 59 and 84 picogram/mL) above baseline (typically 37 pM/L). At the same time, increases in estrone serum concentration averaged only 44, 111, 81 and 207 pM/L (12, 30, 22 and 56 picogram/mL) above baseline, respectively, providing an average E2/E1 ratio between 1.6 and 2.7, well within the premenopausal range. Serum concentrations of estradiol-17ß and estrone returned to pre-application levels within 24 hours after removal of the patch.
ESTRADOT® Page 26 of 46
Distribution
Mean plasma clearance rates of estradiol-17ß and estrone in women have been estimated to be 735 L/day per m2 and 1213 L/day per m2, respectively. Hence, based on studies with VIVELLE®, for women with a body surface area of 1.4-1.9 m2, (weight, 48-86 kg; average height 157 cm) VIVELLE® patches which provide 37.5, 50, 75 and 100 mcg/day should maintain mean steady state serum concentrations as follows:
| Patch | Estradiol Dosage (mcg per day) | Expected Increase in Serum Levels of Estradiol (pM/L) Above Baseline (typically 37 pM/L) |
VIVELLE 37.5 VIVELLE 50 VIVELLE 75 VIVELLE 100 | 37.5 50 75 100 | 66-106 88-147 132-228 176-312 |
Estradiol-17ß delivered by the transdermal route results in an E2/E1 ratio of approximately 1. By comparison, typical E2/E1 ratios following oral estrogen therapy are 0.1 to 0.3 because estrone levels increase to a greater extent than estradiol-17ß levels. The extensive first-pass liver metabolism leads to supraphysiological plasma concentrations of estrone and, in patients on prolonged treatment, to accumulation of estrone and estrone sulphate. Only 2% is free and biologically active.
Metabolism
Metabolism and plasma levels of estradiol-17ß delivered transdermally are similar to those of endogenous hormone in premenopausal women. Estradiol-17ß is metabolised primarily in the liver to estrone, then later to estriol, epiestriol and catechol estrogens, which are then conjugated to sulphates and glucuronides, which are far less active than estradiol-17ß. Cytochrome 450 isoforms CYP1A2 and CYP3A4 catalyze the hydroxylation of estradiol-17ß forming estriol. Estriol is glucuronidated by UGT1A1 and UGT2B7 in humans. Estrogen metabolites are excreted by the kidneys but are also subject to enterohepatic circulation. The skin metabolizes estradiol-17ß only to a small extent.
Elimination
The daily urinary output of estradiol-17ß conjugates increased 3 to 10 times the baseline values and returned to near baseline values within 2 days after removal of the patch. Multiple-application studies yielded similar results, with urinary output of estradiol-17ß conjugates returning to baseline within 3 days of patch removal.
The plasma elimination half-life of estradiol-17ß is approximately 1 hour. The short half-life and rapid clearance of estradiol-17ß permit a rapid cessation of estrogen therapy when cycling is desirable. The bulk of the metabolites is excreted in the urine as glucuronides and sulphates.
Special populations and conditions
- Pediatrics: ESTRADOT is not indicated for use in children
- Geriatrics: No clinical studies were conducted to evaluate the effect of estradiol on women more
ESTRADOT® Page 27 of 46
- than 65 years old.
- Sex: ESTRADOT should be used in women only.
Estrogen pharmacology
Estradiol-17ß is the major estrogenic hormone secreted by the human ovary. Among numerous effects, estradiol-17ß is largely responsible for the development and maintenance of the female reproductive system and of secondary sexual characteristics. It promotes growth and development of the vagina, uterus, fallopian tubes, and breasts. Estradiol-17ß contributes to the shaping of the skeleton, to the maintenance of tone and elasticity of urogenital structures, to changes in the epiphyses of the long bones that allow for the pubertal growth spurt and its termination, to the growth of axillary and pubic hair, and to the pigmentation of the nipples and genitals. Estradiol-17ß also affects the release of pituitary gonadotropins.
After menopause, when the ovaries have ceased to function, only small amounts of estradiol-17ß are still produced, i.e., from the aromatization of androstenedione to estrone and to a lesser extent, testosterone to estradiol-17ß. Estrone is transformed to estradiol-17ß by the enzyme 17ß-hydroxysteroid-dehydrogenase. Both enzymes prevail in fat, liver and muscle tissue.
In premenopausal women, the ratio of estradiol-17ß (E2) to estrone (E1) (i.e., E2/E1 ratio) in the plasma is in the range of 0.5 to 2, depending on the phase of the menstrual cycle. The E2/E1 ratio for untreated postmenopausal women is below 0.5.
Loss of the ovarian estradiol-17ß production after menopause can result in the following: instability of thermoregulation causing hot flushes associated with sleep disturbance and excessive sweating; accelerated loss of bone matrix and mineral; alterations in lipid metabolism; urogenital atrophy, causing dyspareunia and urinary incontinence.
The protection against endometrial hyperplasia in women with intact uteri is necessary during long-term therapy. Published data suggest that 12 to 14 days of sequential progestin treatment during estrogen replacement therapy reduces the occurrence of endometrial hyperplasia, and thereby irregular bleeding and endometrial carcinoma, compared to estrogen treatment alone.
11 Storage, Stability, and Disposal
Store ESTRADOT patches between 2°C-30°C. Do not freeze.
Each patch is individually sealed in a separate pouch. Do not store out of the pouch. Apply immediately upon removal from the protective pouch. Patches should be applied in whole.
Keep ESTRADOT out of the reach and sight of children and pets both before use and when disposing of used patches.
Do not use any ESTRADOT pack that is damaged or shows signs of tampering.
12 Special Handling Instructions
See 4 Dosage and Administration, 4.4 Administration, Patch Application section.
ESTRADOT® Page 28 of 46
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Proper name:
Estradiol-17β
Chemical name:
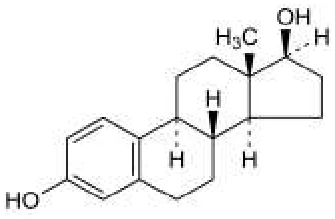
estra-1,3,5 (10)-triene-3,17ß-diol
Molecular formula and molecular mass:
C18H2402 ; 290.4 g/Mol
Structural formula:
Physicochemical properties:
Estradiol is a white crystalline powder. Estradiol is practically insoluble in water; soluble 1 in 28 of alcohol and soluble 1 in 17 of acetone.
14 Clinical Trials
14.1 Trial Design and Study Demographic
Relief of menopausal symptoms
Efficacy and safety of another estradiol-17ß matrix patch (VIVELLE®) in the relief of menopausal and postmenopausal symptoms have been studied in two multicenter, double-blind, placebo-controlled pivotal studies. A total of 356 healthy menopausal women aged 30-65 years (mean 50.5 years) with moderate to severe vasomotor symptoms, a minimum of 6 hot flushes/day, plasma estradiol levels ≤20 picogram/mL and plasma FSH levels ≥50 mU/mL were enrolled in the studies. A total of 266 women were randomized to VIVELLE® patches (37.5, 50, 75 or 100 mcg/day) and 90 were randomized to placebo patches. Over 3 months (3 cycles), the patches were applied to a clear, non-oily area of the abdomen below the waist and were changed twice a week. The evaluable groups consisted of 239 active and 80 placebo patients.
ESTRADOT® Page 29 of 46
Table 5 – Summary of patient demographics for clinical trials in Relief of menopausal symptoms
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=356) | Mean age (Range) | Sex |
| Studies 1003-A and 1003-B combined | two multicenter, double-blind, placebo-controlled pivotal safety and efficacy trials | -patch 37.5 mcg/day (n=79), twice a week for 3 months
| ESTRADOT: 266 women randomised to VIVELLE® patches (37.5,50,75 or 100 mcg/day) | 30-65 years (mean 50.5 years) | Women |
| Patch placebo (n=80), twice a week for 3 months | Placebo: 80 women randomized to placebo patches | ||||
Prevention of osteoporosis
Efficacy and safety of another estradiol-17ß matrix patch (VIVELLE®) in the prevention of postmenopausal osteoporosis have been studied in a 2-year double-blind, randomized, placebo-controlled, parallel group study. A total of 261 hysterectomized (161) and non-hysterectomized (100), surgically or naturally menopausal women (within 5 years of menopause), with no evidence of osteoporosis (lumbar spine bone mineral density within 2 standard deviation of average peak bone mass, i.e., ≥0.827 g/cm2) were enrolled in this study; 194 patients were randomized to one of the four doses of VIVELLE® (100, 50, 37.5 or 25 mcg/day) and 67 patients to placebo. Over 2 years, study systems were applied to the buttock or the abdomen twice a week. Non-hysterectomized women received oral medroxy progesterone acetate (2.5 mg/day) throughout the study.
The study population comprised naturally (82%) or surgically (18%) menopausal, hysterectomized (61%) or nonhysterectomized (39%) women with a mean age of 52.0 years (range 27 to 62 years; the mean duration of menopause was 31.7 months (range 2 to 72 months). Two hundred thirty nine (92%) of randomized subjects (178 on active drug, 61 on placebo) contributed data to the analysis of percent change from baseline in bone mineral density (BMD) of the AP lumbar spine, the primary efficacy variable.
ESTRADOT® Page 30 of 46
Table 6 – Summary of patient demographics for clinical trials in Prevention of osteoporosis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=261) | Mean age (Range) | Sex |
| 035 | 2-year double-blind, randomized, placebo-controlled, parallel group study | -patch 25 mcg/day twice a week for 2 years
| ESTRADOT: 194 patients were randomized to one of the four doses of VIVELLE® (100, 50, 37.5 or 25 mcg/day) | 27-62 years (mean 52.0 years) | Women |
| Patch placebo twice a week for 2 years | Placebo: 67 women randomized to placebo patches | ||||
14.2 Study results
Relief of menopausal symptoms
The primary efficacy variable for both studies was the change in the number of hot flushes at the end of the third treatment cycle compared to baseline values. VIVELLE® was found to be statistically and clinically superior to placebo at all four doses (Table 6). In addition, VIVELLE® significantly reduced the severity of hot flushes, sweating and insomnia compared to placebo.
Table 7 – Mean reduction in number of hot flushes - Studies 1003-A and 1003-B combined
| Treatment | N | Baseline | N | Cycle 3 |
| 37.5 mcg/day | 79 | 10.3 | 77 | -7.1* |
| 50 mcg/day | 44 | 12.5 | 43 | -7.6* |
| 75 mcg/day | 40 | 13.0 | 37 | -9.1* |
| 100 mcg/day | 76 | 11.2 | 68 | -9.0* |
| Placebo | 80 | 10.8 | 72 | -3.0 |
*p<0.0001
ESTRADOT® Page 31 of 46
Prevention of osteoporosis
There was an increase in BMD of the AP lumbar spine in all VIVELLE® dose groups; in contrast to this a decrease in AP lumbar spine BMD was observed in placebo patients. All VIVELLE® doses were significantly superior to placebo (p<0.05) at all time points with the exception of VIVELLE® 50 mcg/day at 6 months, implying bone preservation for all treatment groups, as opposed to bone loss for placebo.
Analysis of percent change from baseline in femoral neck BMD also showed similar results; all doses of VIVELLE® were significantly superior to placebo (p<0.05) at 24 months.
Serum osteocalcin (a marker of bone formation) and urinary excretion of cross-link N-telopeptides of type 1 collagen (a marker of bone resorption) generally decreased in active treatment groups, suggesting a decrease in bone turnover. However, the differences were not statistically significant.
14.3 Comparative Bioavailability Studies
A comparative, multiple dose, cross-over pharmacokinetic study in 30 healthy postmenopausal women demonstrated that the ESTRADOT 5 cm2 (50 mcg/day) and the VIVELLE® 14.5 cm2 (50 mcg/day) patches produced comparable serum concentrations of estradiol at steady state. Each patch was administered for four 84-hour dosing periods with a 7-day washout period between treatments. Statistical analyses also demonstrated equivalence between the two patches for estradiol pharmacokinetic parameters.
Table 8 – Mean Observed Pharmacokinetic Parameters for Estradiol (E2) Obtained After Treatments with Two Different Transdermal Estradiol Systems (n=30)
| Parameter | ESTRADOT 5.0 cm2 patch Mean (SD) | VIVELLE® 14.5 cm2 patch Mean (SD) |
| Cmax (pg/mL) | 56.7 (30.7) | 52.7 (20.0) |
| Tmax (h) | 30.7 (15.6) | 22.0 (13.5) |
| Ctrough (pg/mL) | 28.1 (19.5) | 29.4 (12.3) |
| % Fluctuation | 158.0 (190.8) | 89.2 (59.4) |
| AUC0-84 (pg·h/mL) | 3088 (1721) | 2886 (1147) |
| AUC0-96 (pg·h/mL) | 3268 (1865) | 3051 (1191) |
| ke (h-1) | 0.138 (0.079) | 0.132 (0.056) |
| t½ (h) | 7.7 (7.1) | 6.3 (2.7) |
15 Microbiology
No microbiological information is required for this drug product.
ESTRADOT® Page 32 of 46
16 Non-Clinical Toxicology
Preclinical safety data
The toxicity profile of estradiol is well established in the literature. Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis and liver.
At low physiological doses of estradiol (similar to those delivered by ESTRADOT), neoplastic potential is negligible in experimental animals. Most of the documented effects of exogenously administered estradiol in animal studies have been consequences of the administration of supraphysiological doses and are consistent with an exaggerated pharmacological response (most notably the promotion of tumours in oestrogen-responsive tissues). However, long-term unopposed treatment with physiological doses of estradiol may lead to hyperplastic changes in oestrogen-dependent reproductive organs like the uterus.
In local tolerability studies in rabbits, some skin irritation was observed.