


Product Monograph - Oesclim
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Transdermal | Transdermal patch 25, 37.5, 50, 75, 100 mcg/24 hrs | For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
OESCLIM® (Estradiol-17β) is indicated for the relief of menopausal and post menopausal symptoms occurring in naturally or surgically induced estrogen deficiency states.
OESCLIM® (Estradiol-17β) should be prescribed with an appropriate dosage of a progestin for women with intact uteri in order to prevent endometrial hyperplasia/carcinoma.
CONTRAINDICATIONS
Estrogen and estrogen/progestin combinations are contraindicated in patients with any of the following conditions/disorders:
- Hypersensitivity to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the product monograph.
- Active hepatic dysfunction or disease, especially of the obstructive type.
- Personal history of known or suspected estrogen-dependent malignant neoplasia (e.g. breast or endometrium).
- Endometrial hyperplasia.
- Undiagnosed abnormal genital bleeding.
- Known or suspected pregnancy.
- Lactation
- Active or past history of arterial thromboembolic disease (e.g. stroke, myocardial infarction, coronary heart disease).
- Classical migraine.
- Active or past history of confirmed venous thromboembolism (such as deep vein thrombosis or pulmonary embolism) or active thrombophlebitis.
- Partial or complete loss of vision due to ophthalmic vascular disease.
- Porphyria
WARNINGS AND PRECAUTIONS
General
- Abnormal vaginal bleeding, due to its prolongation, irregularity or heaviness, occurring during therapy should prompt diagnostic measures like hysteroscopy, endometrial biopsy or curettage to rule out the possibility of uterine malignancy and the treatment should be re-evaluated.
- Pre-existing uterine leiomyoma may increase in size during estrogen use. Growth, pain or tenderness of uterine leiomyoma requires discontinuation of medication and appropriate investigation.
- Symptoms and physical findings associated with a previous diagnosis of endometriosis may reappear or become aggravated with estrogen use.
- Caution is advised in patients with a history of liver and/or biliary disorders. If cholestatic jaundice develops during treatment, the treatment should be discontinued and appropriate investigations carried out.
Serious Warnings and Precautions
The Women’s Health Initiative (WHI) trial examined the health benefits and risks of combined estrogen plus progestin therapy (n=16,608) and estrogen-alone therapy (n=10,739) in postmenopausal women aged 50 to 79 years.3, 30, 31
The estrogen plus progestin arm of the WHI trial (mean age 63.3 years) indicated an increased risk of myocardial infarction (MI), stroke, invasive breast cancer, pulmonary emboli and deep vein thrombosis in postmenopausal women receiving treatment with combined conjugated equine estrogens (CEE, 0.625 mg/day) and medroxyprogesterone acetate (MPA, 2.5 mg/day) for 5.2 years compared to those receiving placebo.31
The estrogen-alone arm of the WHI trial (mean age 63.6 years) indicated an increased risk of stroke and deep vein thrombosis in hysterectomized women treated with CEE-alone (0.625 mg/day) for 6.8 years compared to those receiving placebo.30
Therefore, the following should be given serious consideration at the time of prescribing:
- Estrogens with or without progestins should not be prescribed for primary or secondary prevention of cardiovascular diseases.
- Estrogens with or without progestins should be prescribed at the lowest effective dose for the approved indication.
- Estrogens with or without progestins should be prescribed for the shortest period possible for the approved indication.
- Patients who develop visual disturbances, classical migraine, transient aphasia, paralysis or loss of consciousness should discontinue medication.
- If feasible, estrogens should be discontinued at least 4 weeks before major surgery which may be associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
- Estrogens may cause fluid retention. Therefore, particular caution is indicated in cardiac or renal dysfunction, epilepsy or asthma. Treatment should be stopped if there is an increase in epileptic seizures. If, in any of the above-mentioned conditions, a worsening of the underlying disease is diagnosed or suspected during treatment, the benefits and risks of treatment should be reassessed based on the individual case.
- Because the prolonged use of estrogens influences the metabolism of calcium and phosphorus, estrogens should be used with caution in patients with metabolic and malignant bone diseases associated with hypercalcemia and in patients with renal insufficiency.
- A worsening of glucose tolerance and lipid metabolism have been observed in a significant percentage of peri- and post-menopausal patients. Therefore, diabetic patients or those with a predisposition to diabetes should be observed closely to detect any alterations in carbohydrate or lipid metabolism, especially in triglyceride blood levels.
- Women with familial hyperlipidemias need special surveillance. Lipid-lowering measures are recommended additionally, before treatment is started.
- Liver function tests should be done periodically in subjects who are suspected of having hepatic disease. For information on endocrine and liver function tests, see the section under Laboratory Tests.
Carcinogenesis and Mutagenesis
Breast Cancer
Available epidemiological data indicate that the use of combined estrogen plus progestin by postmenopausal women is associated with an increased risk of invasive breast cancer.
In the estrogen plus progestin arm of the WHI trial, among 10,000 women over a one-year period, there were:
- 8 more cases of invasive breast cancer (38 on combined HRT versus 30 on placebo).31
The WHI study also reported that the invasive breast cancers diagnosed in the estrogen plus progestin group were similar in histology but were larger (mean [SD], 1.7 cm [1.1] vs. 1.5 cm [0.9], respectively; P=0.04) and were at a more advanced stage compared with those diagnosed in the placebo group. The percentage of women with abnormal mammograms (recommendations for short-interval follow-up, a suspicious abnormality, or highly suggestive of malignancy) was significantly higher in the estrogen plus progestin group versus the placebo group. This difference appeared at year one and persisted in each year thereafter.3
In the estrogen-alone arm of the WHI trial, there was no statistically significant difference in the rate of invasive breast cancer in hysterectomized women treated with conjugated equine estrogens versus women treated with placebo.30
It is recommended that estrogens not be given to women with existing breast cancer or those with a previous history of the disease (see Contraindications).
There is a need for caution in prescribing estrogens for women with known risk factors associated with the development of breast cancer, such as strong family history of breast cancer (first degree relative) or who present a breast condition with an increased risk (abnormal mammograms and/or atypical hyperplasia at breast biopsy).
Other known risk factors for the development of breast cancer such as nulliparity, obesity, early menarche, late age at first full term pregnancy and at menopause should also be evaluated.
It is recommended that women undergo mammography prior to the start of HRT treatment and at regular intervals during treatment, as deemed appropriate by the treating physician and according to the perceived risks for each patient.
The overall benefits and possible risks of hormone replacement therapy should be fully considered and discussed with patients. It is important that the modest increased risk of being diagnosed with breast cancer after 4 years of treatment with combined estrogen plus progestin HRT (as reported in the results of the WHI trial) be discussed with the patient and weighed against its known benefits.
Instructions for regular self-examination of the breasts should be included in this counselling.
Endometrial Hyperplasia & Endometrial Carcinoma
Estrogen-only HRT increases the risk of endometrial hyperplasia (if taken by women with intact uteri).
The incidence of endometrial hyperplasia is lowered with sequential co-administration of a progestin (see administration of progestins under DOSAGE AND ADMINISTRATION). One case of endometrial hyperplasia (0.45%) among 222 patients in the OESCLIM® 50-treated group was reported in an uncontrolled clinical trial conducted to evaluate the tolerability of OESCLIM® over a twelve-month period. Time of onset was between 271-360 days into the treatment phase in a patient treated continuously with OESCLIM® 50. The patient was withdrawn 343 days after the inclusion visit (Vi), after 329 days of exposure to the transdermal systems.
Estrogen should be prescribed with an appropriate dosage of a progestin for women with intact uteri in order to prevent endometrial hyperplasia/carcinoma.
Ovarian cancer
Some recent epidemiologic studies have found that the use of hormone replacement therapy (estrogen-alone and estrogen plus progestin therapies), in particular for five or more years, has been associated with an increased risk of ovarian cancer.
Cardiovascular
The results of the Heart and Estrogen/progestin Replacement Studies (HERS and HERS II) and the Women's Health Initiative (WHI) trial indicate that the use of estrogen plus progestin is associated with an increased risk of coronary heart disease (CHD) in postmenopausal women.6,9,31 The results of the WHI trial indicate that the use of estrogen-alone and estrogen plus progestin is associated with an increased risk of stroke in postmenopausal women.30,31
WHI trial findings
In the combined estrogen plus progestin arm of the WHI trial, among 10,000 women over a one-year period, there were:
- 8 more cases of stroke (29 on combined HRT versus 21 on placebo).
- 7 more cases of CHD (37 on combined HRT versus 30 on placebo).31
In the estrogen-alone arm of the WHI trial of women with prior hysterectomy, among 10,000 women over a one-year period, there were/was:
- 12 more cases of stroke (44 on estrogen-alone therapy versus 32 on placebo)
- no statistically significant difference in the rate of CHD.30
HERS and HERS II findings
In the Heart and Estrogen/progestin Replacement Study (HERS) of postmenopausal women with documented heart disease (n=2763, average age 66.7 years), a randomized placebo-controlled clinical trial of secondary prevention of coronary heart disease (CHD), treatment with 0.625 mg/day oral conjugated equine estrogen (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) demonstrated no cardiovascular benefit. Specifically, during an average follow-up of 4.1 years, treatment with CEE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established coronary heart disease. There were more CHD events in the hormone-treated group than in the placebo group in year 1, but not during the subsequent years.9
From the original HERS trial, 2321 women consented to participate in an open label extension of HERS known as HERS II. Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall. After 6.8 years, hormone therapy did not reduce the risk of cardiovascular events in women with CHD.6
Blood Pressure
Women using hormonal replacement therapy (HRT) sometimes experience increased blood pressure. Blood pressure should be monitored with HRT use. Elevation of blood pressure in previously normotensive or hypertensive patients should be investigated and HRT therapy may have to be discontinued.
Endocrine and Metabolism
Glucose and lipid metabolism
A worsening of glucose tolerance and lipid metabolism have been observed in a significant percentage of peri- and post-menopausal patients. Therefore, diabetic patients or those with a predisposition to diabetes should be observed closely to detect any alterations in carbohydrate or lipid metabolism, especially in triglyceride blood levels.
Women with familial hyperlipidemias or porphyria need special surveillance. Lipid-lowering measures are recommended additionally, before treatment is started.
Calcium and phosphorus metabolism
Because the prolonged use of estrogens influences the metabolism of calcium and phosphorus, estrogens should be used with caution in patients with metabolic and malignant bone diseases associated with hypercalcemia and in patients with renal insufficiency.
Hypothyroidism
Patients who require thyroid hormone replacement therapy and who are also taking estrogen should have their thyroid function monitored regularly to assure that thyroid hormone levels remain in an acceptable range (see Drug-Laboratory Test Interactions).
Genitourinary
Vaginal bleeding
Abnormal vaginal bleeding, due to its prolongation, irregularity or heaviness, occurring during therapy should prompt appropriate diagnostic measures to rule out the possibility of uterine malignancy and the treatment should be re-evaluated.
Uterine leiomyomata
Pre-existing uterine leiomyomata may increase in size during estrogen use. Growth, pain or tenderness of uterine leiomyomata requires discontinuation of medication and appropriate investigation.
Endometriosis
Symptoms and physical findings associated with a previous diagnosis of endometriosis may reappear or become aggravated with estrogen use.
Hematologic
Venous Thromboembolism
Available epidemiological data indicate that use of estrogen with or without progestin by postmenopausal women is associated with an increased risk of developing venous thromboembolism (VTE).
In the estrogen plus progestin arm of the WHI trial, among 10,000 women on combined HRT over a one-year period, there were 18 more cases of venous thromboembolism, including 8 more cases of pulmonary embolism.31
In the estrogen-alone arm of the WHI trial, among 10,000 women on estrogen therapy over a one-year period, there were 7 more cases of venous thromboembolism, although there was no statistically significant difference in the rate of pulmonary embolism.30
Generally recognized risk factors for VTE include a personal history, a family history (the occurrence of VTE in a direct relative at a relatively early age may indicate genetic predisposition) and severe obesity (body mass index > 30 kg/m2) and systemic lupus erythematosus. The risk of VTE also increases with age and smoking.
The risk of VTE may be temporarily increased with prolonged immobilization, major surgery or trauma. In women on HRT, attention should be given to prophylactic measures to prevent VTE following surgery. Also, patients with varicose veins should be closely supervised. The physician should be alert to the earliest manifestations of thrombotic disorders (thrombophlebitis, retinal thrombosis, cerebral embolism and pulmonary embolism). If these occur or are suspected, hormone therapy should be discontinued immediately, given the risks of long-term disability or fatality.
If feasible, estrogens should be discontinued at least 4 weeks before major surgery, which may be associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
Hepatic/Biliary/Pancreatic
Gallbladder Disease
A 2- to 4-fold increase in gallbladder disease requiring surgery in women receiving postmenopausal estrogens has been reported.
Jaundice
Caution is advised in patients with a history of liver and/or biliary disorders. If cholestatic jaundice develops during treatment, the treatment should be discontinued and appropriate investigations carried out.
Liver function tests
Liver function tests should be done periodically in subjects who are suspected of having hepatic disease. For information on endocrine and liver function tests, see the section under Monitoring and Laboratory Tests.
Hepatic
Benign hepatic adenomas have been associated with the use of combined estrogen and progestagen oral contraceptives. Although benign and rare, these tumours may rupture and cause death from intra-abdominal hemorrhage. Such lesions have not yet been reported in association with other estrogen or progestagen preparations, but they should be considered if abdominal pain and tenderness, abdominal mass, or hypovolemic shock occurs in patients receiving estrogen.
Hepatocellular carcinoma has also been reported in women taking estrogen-containing oral contraceptives. The causal relationship of this malignancy to these drugs is not known.
Neurologic
Cerebrovascular insufficiency
Patients who develop visual disturbances, classical migraine, transient aphasia, paralysis or loss of consciousness should discontinue medication. Patients with a previous history of classical migraine and who develop a recurrence or worsening of migraine symptoms should be reevaluated.
Dementia
Available epidemiological data indicate that the use of combined estrogen plus progestin in women age 65 and over may increase the risk of developing probable dementia.
The Women’s Health Initiative Memory Study (WHIMS), a clinical substudy of the WHI, was designed to assess whether postmenopausal hormone replacement therapy (estrogen plus progestin or estrogen-alone) reduces the risk of dementia in women aged 65 and over and free of dementia at baseline.26,27
In the estrogen plus progestin arm of the WHIMS (n=4532), women with an intact uterus were treated with daily 0.625 mg conjugated equine estrogens (CEE) plus 2.5 mg medroxyprogesterone acetate (MPA) or placebo for an average of 4.05 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 23 more cases of probable dementia (45 on combined HRT versus 22 on placebo).27
In the estrogen-alone arm of the WHIMS (n=2947), women with prior hysterectomy were treated with daily 0.625 mg CEE or placebo for an average of 5.21 years. The results, when extrapolated to 10,000 women treated over a one-year period showed:
- 12 more cases of probable dementia (37 on estrogen-alone versus 25 on placebo), although this difference did not reach statistical significance.26
When data from the estrogen plus progestin arm of the WHIMS and the estrogen-alone arm of the WHIMS were combined, as per the original WHIMS protocol, in 10,000 women over a one-year period, there were:
- 18 more cases of probable dementia (41 on estrogen plus progestin or estrogen-alone versus 23 on placebo).26
Renal
Fluid retention
Estrogens with or without progestins may cause fluid retention. Therefore, particular caution is indicated in cardiac or renal dysfunction, epilepsy or asthma. If, in any of the above-mentioned conditions, a worsening of the underlying disease is diagnosed or suspected during treatment, the benefits and risks of treatment should be reassessed based on the individual case.
Skin
Dermatologic Hypersensitivity
Contact sensitization is known to occur with topical applications. Although it is extremely rare, patients who develop contact sensitization to any component of the patch should be warned that a severe hypersensitivity reaction may occur with continuing exposure to the causative agent.
Monitoring and Laboratory Tests
Before OESCLIM® is administered, the patient should have a complete physical
- examination including a blood pressure determination. Breasts and pelvic organs should be appropriately examined and a Papanicolaou smear should be performed. An endometrial biopsy should be done when indicated. Baseline tests should include mammography, measurements of blood glucose, calcium, triglycerides and cholesterol, and liver function tests.
- The first follow-up examination should be done within 3-6 months after initiation of treatment to assess response to treatment. Thereafter, examinations should be made at intervals at least once a year. Appropriate investigations should be arranged at regular intervals as determined by the physician. It is important that patients are encouraged to practice frequent self-examination of the breasts.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
See Warnings and Precautions regarding potential induction of malignant neoplasms and adverse effects similar to those of oral contraceptives.
The following adverse reactions have been reported with the use of estrogen/progestin combination in general.
Blood and lymphatic system disorders
Altered coagulation tests (see Warnings and Precautions, Drug-Laboratory Tests Interactions).
Cardiac disorders
Palpitations; increase in blood pressure (see Warnings and Precautions); coronary thrombosis.
Endocrine disorders
Increased blood sugar levels; decreased glucose tolerance.
Eyes disorders
Neuro-ocular lesions (e.g. retinal thrombosis, optic neuritis); visual disturbances; steepening of the corneal curvature; intolerance to contact lenses.
Gastrointestinal disorders
Nausea; vomiting; abdominal discomfort (cramps, pain, pressure); bloating.
General disorders and administration site conditions
Fatigue; changes in appetite; changes in body weight; change in libido.
Hepatobiliary disorders
Gallbladder disorder, asymptomatic impaired liver function; cholestatic jaundice.
Musculoskeletal and connective tissue disorders
Musculoskeletal pain including leg pain not related to thromboembolic disease (usually transient, lasting 3-6 weeks) may occur.
Nervous System disorders
Aggravation of migraine episodes; headaches; dizziness; neuritis.
Psychiatric disorders
Mental depression; nervousness; irritability.
Renal and urinary disorders
Cystitis; dysuria; sodium retention; edema.
Reproductive system and breast disorders
Breakthrough bleeding, spotting; change in menstrual flow, dysmenorrhea; vaginal itching/discharge, dyspareunia, endometrial hyperplasia, pre-menstrual-like syndrome; reactivation of endometriosis; changes in cervical erosion and amount of cervical secretion, breast swelling and tenderness.
Skin and subcutaneous tissue disorders
Cloasma or melasma, which may persist when drug is discontinued; erythema multiforme; hemorrhagic eruption; loss of scalp hair; hirsutism and acne.
Vascular disorders
Isolated cases of: thrombophlebitis, thromboembolic disorders.
If adverse symptoms persist, the prescription of HRT should be reconsidered.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The most commonly reported adverse reaction to OESCLIM® in clinical trials was application site reaction. 9 patients (28.1 %) in Study # 1, 85 patients (38.3 %) in Study #2 and 37 patients (25.9 %) in Study #3 presented at least one local skin reaction. In all three clinical trials, 4.2% of all applications caused local skin reactions, which included redness, itching, spots, burning and swelling. Of the 22,239 applications in the three clinical trials, 1,017 (4.6%) patches became detached. The second most frequent adverse reactions were symptoms of specific estrogen therapy intolerance reported by a total of 193 patients (48.6 %) treated with OESCLIM® in the 3 clinical trials: 119 (30%) presented signs of hyperestrogenism including mastodynia (38.8 % to 53.8 % of the cases of hyperestrogenism), 116 (38.5 %) non-hysterectomised patients presented metrorrhagia and spotting.
DRUG INTERACTIONS
Overview
Estrogens may diminish the effectiveness of anticoagulant, antidiabetic and antihypertensive agents.
Preparations inducing liver enzymes, (e.g., barbiturates, hydantoins, carbamazepine, meprobamate, phenylbutazone or rifampicin) may interfere with the activity of orally administered estrogens.
Drug-Drug Interactions
The extent of interference with transdermally administered estradiol-17β is not known. Given that the first-pass effect in the liver is avoided by transdermal administration, transdermally applied estrogens may be less affected by enzyme inducers than oral estrogen preparations.
Clinical pharmacokinetic studies have not demonstrated any consistent effect of antibiotics (other than rifampin) on plasma concentrations of synthetic steroids.
Drug-Herb Interactions
It was found that some herbal products (e.g. St. John’s wort), which are available as over-the-counter (OTC) products, may affect metabolism, and therefore, efficacy and safety of estrogen/progestin products.
Physicians and other healthcare providers should be aware of other non-prescription products concomitantly used by the patient, including herbal and natural products, widely available in health food stores.
Drug-Laboratory Interactions
The results of certain endocrine and liver function tests may be affected by estrogen-containing products:
- increased prothrombin time and partial thromboplastin time; increased levels of fibrinogen and fibrinogen activity; increased coagulation factors VII, VIII, IX, X; increased norepinephrine-induced platelet aggregability; decreased antithrombin III;
- increased thyroxine-binding globulin (TBG), leading to increased circulating total thyroid hormone (T4) as measured by column or radioimmunoassay; free T3 resin uptake is decreased, reflecting the elevated TBG; free T4 concentration is unaltered;
- other binding proteins may be elevated in serum i.e., corticosteroid binding globulin (CBG), sex-hormone binding globulin (SHBG), leading to increased circulating corticosteroids and sex steroids respectively; free or biologically active hormone concentrations are unchanged.
- impaired glucose tolerance;
- reduced serum folate concentration;
- increased serum triglycerides and phospholipids concentration.
In clinical trials with transdermal estradiol-17β, no effect on fibrinogen, antithrombin III, TBG, CBG or SHBG and decreases in serum triglycerides were seen.2
The results of the above laboratory tests should not be considered reliable unless therapy has been discontinued for 2 to 4 weeks. The pathologist should be informed that the patient is receiving estrogen therapy when relevant specimens are submitted.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The treatment is generally initiated with OESCLIM® 25, 37.5 or 50. The initial selection of the dose of estradiol can be based on the type and severity of the patient’s symptomatology. Depending on the clinical response to treatment, the dosage must then be adjusted to the individual’s needs. If the chosen dose does not correct the symptoms of estrogen deficiency, the dose may be increased. Breast tenderness and/or metrorrhagia in general indicates that the dose is too high and needs to be lowered.
Two therapeutic schedules can be used with OESCLIM®:
discontinuous (cyclic): 24–28 days treatment followed by a two to seven day treatment-free period;
continuous (noncyclic): no treatment-free period.
Continuous, noncyclic therapy may be indicated in hysterectomized women or in cases where the signs and symptoms of estrogen deficiency become problematic during the treatment-free interval.
In women with an intact uterus, sequential treatment with sufficient progestogen to inhibit endometrial hyperplasia and to induce secretory transformation of the endometrium is mandatory. The progestogen may be administered according to one of the two following regimens:
- If OESCLIM® is administered on a discontinuous schedule, the progestogen should be administered for at least the last 12 days of the estradiol treatment; thus there is no hormone administration during the treatment-free period of each cycle.
- If OESCLIM® is administered on a continuous schedule, the progestogen is recommended for at least 12 sequential days per month.
In both cases breakthrough bleeding may occur after the progestogen is stopped. Unexpected or abnormal bleeding in such patients is an indication for prompt diagnostic measures.
The lowest clinically effective dose of each hormone should be used.
Recommended Dose and Dosage Adjustment
Apply OESCLIM® twice a week, i.e. apply one patch for a three day application period and the next for a four day application period.
Administration
Remove the OESCLIM® transdermal system from its pouch only just before using. Once the protective liner has been removed, OESCLIM® must be applied immediately onto the buttock, the torso (iliac fossa, abdomen) or the upper part of the arm or thigh at a site free of major folds and away from areas where the system can be rubbed off by tight clothing.
The skin must be dry and free from any irritation and not treated with oily or greasy products.
Do not apply OESCLIM® to the abdomen, if a dose of OESCLIM® has been previously adjusted with the patch applied to other sites of the body, as this might change the amount of hormone delivered.
OESCLIM® must not be applied to the breasts. When a patch is removed, the next patch should not be applied to the same site.
It is possible to shower or take a bath while wearing an OESCLIM® transdermal system. In the exceptional circumstance that a transdermal system should fall off (hyperperspiration, abnormal rubbing by clothing), it is recommended that the same system be reapplied on dry skin. If this is not possible, use a new transdermal patch which will be removed on the anticipated date. Thereafter the cycle of changing of the patch will continue according to the original schedule.
OVERDOSAGE
Symptoms
Numerous reports of ingestion of large doses of estrogen products and estrogen-containing oral contraceptives by young children have not revealed acute serious ill effects. Overdosage with estrogen may cause nausea, breast discomfort, fluid retention, bloating or vaginal bleeding in women.
Treatment
Owing to the mode of administration (transdermal), plasma levels of estradiol-17β can be rapidly reduced by removal of the patch. Symptomatic treatment should be given.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
OESCLIM® delivers estradiol-17β, a physiologic hormone, transdermally into the systemic circulation. Consequently, the estradiol-17β does not undergo first-pass liver and intestinal metabolism and estradiol-17β serum levels are comparable to those seen in premenopausal women in the early follicular phase of the menstrual cycle. Estradiol-17β stimulates target tissues such as the uterus, breast and vagina.
OESCLIM® contains estradiol-17β in an adhesive transdermal therapeutic system designed for application to an area of intact skin. It is designed to release controlled amounts of estradiol-17β continuously through the skin at a rate sufficient to raise circulating estradiol to premenopausal blood levels. Thus, OESCLIM® provides a replacement for physiological estradiol.
Pharmacodynamics
- Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol at the receptor level.
The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle. After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone by peripheral tissues. Thus, estrone and the sulfate conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women.
Estrogens act through binding to nuclear receptors in estrogen-responsive tissues. To date two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH) and follicle-stimulating hormone (FSH) through a negative feedback mechanism and estrogen replacement therapy acts to reduce the elevated levels of these hormones seen in postmenopausal women.
Pharmacokinetics
The pharmacokinetics of transdermally administered estradiol using OESCLIM® have been evaluated in a total of 138 healthy postmenopausal women in nine clinical and biopharmaceutic studies.
Absorption:
Approximately twenty-four hours after the application, the mean values of estradiol maximal concentrations (Cmax) are 25, 81 and 108 pg/mL respectively with OESCLIM® 25, 50 and 100, and estimated Cmax values are 38 and 75 pg/mL for OESCLIM® 37.5 and 75 respectively. Serum levels then remain practically constant throughout the application period (3-4 days). Seventy-two hours (3 days) after application, estradiol serum levels are practically the same as the mean values measured throughout the application period, i.e. 18, 46 and 64 pg/mL, respectively for OESCLIM® 25, 50 and 100, and the estimated average serum estradiol concentrations over 72 hours are 31 and 52 pg/mL for OESCLIM® 37.5 and 75 respectively.
Repeated applications over three weeks do not lead to accumulation of estradiol.
Distribution:
The distribution of exogenous estrogens is similar to that of endogenous estrogens. Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estradiol and other naturally occurring estrogens are bound mainly to sex hormone binding globulin (SHBG), and to lesser degree to albumin.
Metabolism:
Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. These transformations take place mainly in the liver. Estradiol is converted reversibly to estrone, and both can be converted to estriol, which is the major urinary metabolite. Estrogens also undergo enterohepatic recirculation via sulfate and glucuronide conjugation in the liver, biliary secretion of conjugates into the intestine, and hydrolysis in the gut followed by reabsorption. In postmenopausal women, a significant portion of the circulating estrogens exist as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens.
Since transdermally absorbed estradiol is not subject to first-pass liver metabolism, the ratio of serum concentrations of estradiol to either of its major metabolites, estrone or estrone sulfate, is closer to those observed in premenopausal women than when administered by the oral route of administration.
Mean ratios for E2/E1 (estradiol/estrone) serum concentrations during OESCLIM® patch application are similar to those observed in women before menopause, approximately equal to one.
Excretion:
Estradiol, estrone and estriol are excreted in the urine along with glucuronide and sulfate conjugates. Estradiol serum concentrations return to baseline values within eight hours after patch removal.
STORAGE AND STABILITY
Store at room temperature (15–25°C). Avoid freezing. Do not store unpouched. Apply immediately upon removal from the protective pouch. Keep out of the reach of children both before and after use. After removal of the patch fold it in half, with the adhesive side inwards, before discarding.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Dosage forms / Packaging
Description: Rectangular transdermal system (11, 16.5, 22, 33 or 44 cm2), with rounded corners, consisting of a transparent adhesive layer laminated onto a beige foam backing. The adhesive is protected by a transparent peelable release liner. Each system is contained in a heat-sealed paper/aluminium sachet.
Composition: Ethylene/vinyl acetate copolymer, dipropylene glycol, octyl dodecanol, ethylcellulose.
OESCLIM® 25: Each rectangular (11 cm2) transdermal system contains estradiol hemihydrate corresponding to 5 mg estradiol for delivery of estradiol 25 mcg/24 hrs. Patient pack of 8 systems.
OESCLIM® 37.5: Each rectangular (16.5 cm2) transdermal system contains estradiol hemihydrate corresponding to 7.5 mg estradiol for delivery of estradiol 37.5 mcg/24 hrs. Patient pack of 8 systems.
OESCLIM® 50: Each rectangular (22 cm2) transdermal system contains estradiol hemihydrate corresponding to 10 mg estradiol for delivery of estradiol 50 mcg/24 hrs. Patient pack of 8 systems.
OESCLIM® 75: Each rectangular (33 cm2) transdermal system contains estradiol hemihydrate corresponding to 15 mg estradiol for delivery of estradiol 75 mcg/24 hrs. Patient pack of 8 systems.
OESCLIM® 100: Each rectangular (44 cm2) transdermal system contains estradiol hemihydrate corresponding to 20 mg estradiol for delivery of estradiol 100 mcg/24 hrs. Patient pack of 8 systems.
Composition
Oesclim transdermal system has the following composition:
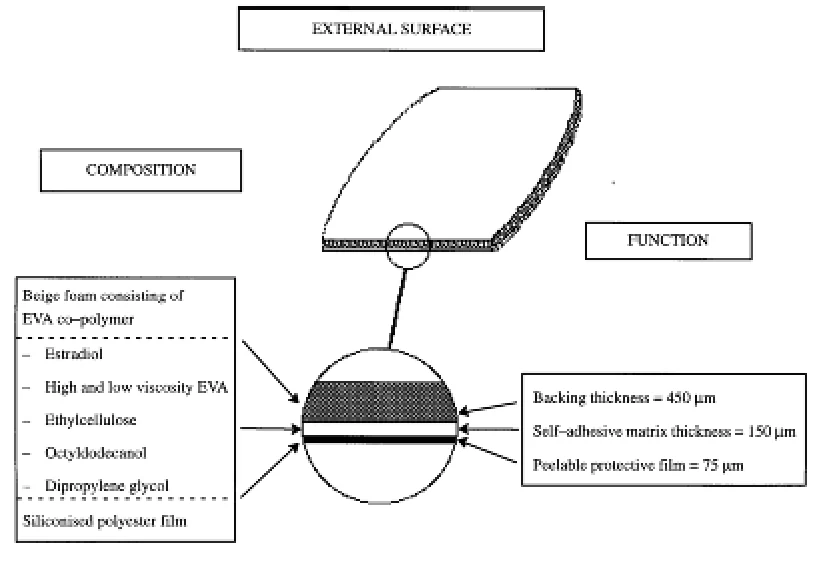
OESCLIM® patches are made up of a self-adhesive polymer matrix, which contains the estradiol, backed onto a rectangular foam mounting with rounded corners. The adhesive surface is covered by a transparent silicone-treated protective film which must be removed before use. This system provides excellent local tolerability and adhesion.
The active component of the system is estradiol-17β. The drug matrix provides a source for continuous delivery of drug for at least 4 days. The composition of each of the systems per unit area is identical.
The mean dose of estradiol-17β absorbed per 24 hours is about 25 mcg for OESCLIM® 25, 50 mcg for OESCLIM® 50 and 100 mcg for OESCLIM® 100. Physiological serum concentrations of estradiol, proportional to the quantity administered, are reached four hours after application of the patch.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Estradiol hemihydrate (INN)
Chemical name: (17β)-Estra-1,3,5(10)-triene-3,17-diol hemihydrate
Structural formula:
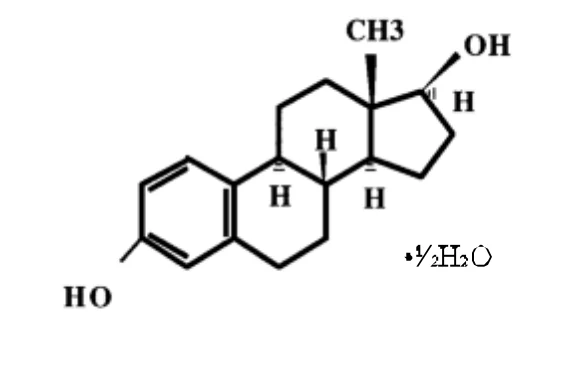
Molecular formula: C18H24O2, ½H2O
Molecular weight: 281.4
Description: White or almost white crystalline powder or colourless crystals
Melting point: 175°C to 180°C
Solubility: Practically insoluble in water, soluble in acetone, sparingly soluble in alcohol, slightly soluble in ether and in methylene chloride
CLINICAL TRIALS
Three clinical trials have been performed in order to evaluate the efficacy and safety of OESCLIM® in menopausal patients.
The aim of these studies was to evaluate the local skin tolerability of OESCLIM® in short- and long-term studies and to document its efficacy in comparison with placebo and with a reference oestrogen replacement therapy patch, ESTRADERM TTS® 50.
- The first clinical study (study #1) was a randomized, placebo-controlled, double-blind study evaluating the efficacy of OESCLIM® in highly symptomatic patients (>5 vasomotor symptoms per day) treated for 12 to 13 weeks.
- The second clinical study (study #2) was an open-label, uncontrolled study evaluating the long-term local skin, specific and general tolerability of OESCLIM® in different types of menopausal patients (natural or surgical menopause) and using different therapeutic schedules (24 or 28-day discontinuous treatment regimen or continuous treatment regimen). Planned duration of treatment in this trial was 12 months.
- The third clinical study (study #3) was a randomized, controlled study comparing the local skin tolerability, specific and general tolerability and efficacy of OESCLIM® 50 and ESTRADERM TTS® 50 in symptomatic menopausal patients treated for 16 weeks.
The studies #1 and #3 are regarded as pivotal for the evaluation of efficacy; study #2 confirmed the maintenance of efficacy during a 1-year long-term treatment. The studies #2 and #3 are regarded as major for the evaluation of safety.
The following table summarizes the most critical design features of the three main clinical trials.
| Study identification | Design | Primary aim | Secondary aims | Population | Evaluated patients | Treatment features |
|---|---|---|---|---|---|---|
| Study #1 | Randomized Double-blind 2 parallel groups Placebo-control Multicentre | Efficacy on vasomotor symptoms at 12 weeks | Evaluate:
| Symptomatic naturally menopausal women with ≥ 5 hot flushes per day 4/7 days and ≥ 1 night sweat per 24 hours 4/7 nights during 7-day self-assessment | 61 OESCLIM® 50: 32 Placebo: 29 | Continuous No progestogen Fixed dose: OESCLIM® 50 or placebo 2 systems per week 12 to 13 weeks of treatment |
| Study identification | Design | Primary aim | Secondary aims | Population | Evaluated patients | Treatment features |
|---|---|---|---|---|---|---|
| Study #2 | Uncontrolled Open-label Multicentre | Local skin tolerability over one year | Evaluate specific tolerability to Hormone Replacement Therapy; general safety and efficacy. | Female patients showing signs of estrogen deficiency related to the menopause or patients treated with other hormone replacement therapy for menopausal symptoms and having undergone a one-month wash-out period Natural or surgical menopause | 222 | 24 or 28-day discontinuous or continuous Fixed dose for 3 months: OESCLIM® 50, flexible after 3 months: OESCLIM® 25, 50 or 100 Total of 12 months of treatment with concomitant progestogen treatment given in sequential fashion during the last 12 to 16 days of cycles |
| Study #3 | Randomized Open-label Multicentre 2 parallel groups Comparison of OESCLIM® 50 and Estraderm TTS® 50 | Local skin tolerability after 16 weeks of treatment. | Compare OESCLIM® 50 and Estraderm TTS® 50 in terms of efficacy, general tolerability, specific tolerability to estrogen treatment. | Symptomatic menopausal patients with ≥ 1 hot flush and ≥ 1 night sweat during the 7-day self-assessment | 281 OESCLIM® 50: 143 Estraderm TTS® 50: 138 | 24-day discontinuous Treatment with OESCLIM® 50 or Estraderm TTS® 50 during 4 cycles of 28 days per cycle (16 weeks) with concomitant progestogen treatment given in sequential fashion during the last 12 days of estrogen therapy |
Discussion of Clinical Results
The efficacy of OESCLIM® 50 in alleviating subjective vasomotor symptoms was documented in the 2 controlled studies, the placebo-controlled study (study # 1) and the study comparing OESCLIM® 50 and ESTRADERM TTS® 50 (study # 3). Supportive efficacy data over 1 year of treatment were also obtained in the long-term, uncontrolled study (study # 2). Study results showed that in highly symptomatic patients (β5 vasomotor symptoms per day, i.e. hot flushes and night sweats), OESCLIM® 50 provided a near maximum effect (i.e. maximum decrease in the number of vasomotor symptoms, from the inclusion visit (Vi) to the end of study visit (Vf)) after 4 weeks (V1) of treatment with mean percent decreases from baseline values (i.e. hot flushes and night sweats measured before treatment) of 71% to 89%, and percentages of patients with complete relief (i.e. no vasomotor symptoms reported) of 30% to 43%, in Studies 3 and 1 respectively. In Study 2, OESCLIM® 50 provided the maximum effect after 2 months (V1) of treatment with a mean percent decrease from baseline value of 91%, and percentage of patients with complete relief of 75%. After 12 to 16 weeks of treatment, in the same populations, OESCLIM® 50 provided mean percent decreases from baseline values of 92% to 97%, and percentages of patients with complete relief of 72% to 86%, depending on the study (see tables below for detailed study results).
| Mean number of vasomotor symptoms (hot flushes and night sweats) per day at each visit in all patients who were evaluated for efficacy. | ||||||||||
| Inclusion Visit | Study Visits | |||||||||
Study # 1 Mean + SD Difference | Baseline (Vi) 9.31 + 4.24 | After 4 weeks (V1) 1.15 + 2.14 89.2% | After 8 weeks (V2) 0.32 + 1.11 97.6% | After 12 weeks (Vf) 0.26 + 0.76 97.5% | ||||||
Study # 3 Mean + SD Difference | Baseline (Vi) 9.95 + 6.29 | After 4 weeks (V1) 2.54 + 2.94 71.0% | After 8 weeks (V2) 0.98 + 2.04 86.6% | After 12 weeks (V3) 1.11 + 3.21 86.3% | After 16 weeks (Vf) 0.60 + 1.61 91.6% | |||||
| Mean number of vasomotor symptoms (hot flushes and night sweats) per day at each visit in all patients who were evaluated for efficacy. | |||||||
| Inclusion Visit | Study Visits | ||||||
Study # 2 Mean + SD Difference | Baseline (Vi) 5.35 + 4.80 | After 2 months (V1) 0.47 + 1.32 91.2% | After 6 months (V2) 0.21 + 0.54 96.1% | After 11 months (V3) 0.42 + 1.28 92.1% | After 12 months (Vf) --- --- | ||
| Number of patients obtaining complete relief from vasomotor symptoms (hot flushes and night sweats) at each visit of all patients evaluated for efficacy. | ||||
Study # 1 Oesclim 50 (n=28) | After 4 weeks (V1) 12 (42.9%) | After 8 weeks (V2) 20 (71.4%) | After 12 weeks (Vf) 24 (85.7%) | |
Study # 3 Oesclim 50 (n=50) | After 4 weeks (V1) 15 (30.0%) | After 8 weeks (V2) 29 (58.0%) | After 12 weeks (V3) 33 (66.0%) | After 16 weeks (Vf) 36 (72.0%) |
| Number of patients obtaining complete relief from vasomotor symptoms (hot flushes and night sweats) at each visit of all patients evaluated for efficacy. | |||
Study # 2 Oesclim 50 (n=142) | After 2 months (V1) (n=136) 102 (75.0%) | After 6 months (V2) (n=100) 79 (79.0%) | After 11 months (V3) (n=83) 63 (75.9%) |
Discussion of tolerability
Three aspects of tolerability were studied:
- local skin tolerability;
- drug specific tolerability, including the signs described by the investigators as due to hyperestrogenism or directly due to treatment with HRT;
- general tolerability, covering all other adverse events.
Results on local skin tolerability
The number of OESCLIM®-treated patients presenting at least one local skin reaction were 9, 85, and 37 in Studies #1, #2, and #3 respectively. The percentages were lowest in the studies of short duration (28.13% after 12 weeks for study #1 and 25.9% after 16 weeks for study # 3), and higher in the 1-year treatment study #2 (38.32%).
In all three trials, approximately 4.2% of all applications caused a local skin reaction (i.e. number of application site reaction/total number of applications), irrespective of the duration of exposure.
For all 3 trials, the most frequent types of application site reactions with OESCLIM® were erythema, 2.7%, and pruritus, 3.0%.
Of the 397 OESCLIM®-treated patients (32 in Study #1; 222 in Study #2; 143 in Study #3) evaluated for local skin tolerability across the clinical trials, 7 (1.8%) patients withdrew due to application site reactions from the trials; 0 patients in Study #1, 6 patients (2.7%) in Study #2 and 1 patient (0.7%) in Study #3.
Results on specific hormone replacement therapy tolerability
Symptoms of specific estrogen therapy intolerance were reported by 197 patients treated with OESCLIM® among 397 patients in the 3 clinical studies: 17 (53.1%) in Study #1, 138 (62.2%) in Study #2, and 52 (36.4%) in Study #3. 119 OESCLIM®-treated patients presented signs of hyperestrogenism: 14 (43.7%) in Study #1, 76 (34.2%) in Study #2, and 26 (18.2%) in Study #3. 116 non-hysterectomized patients presented metrorrhagia or spotting: 8 (25.0%) in Study #1, 76 (36.9%) in Study #2, and 29 (20.3%) in Study #3.
The most frequent sign of hyperestrogenism was mastodynia (breast pain): 7 (21.9%) in Study #1, 66 (29.5%) in Study #2 and 18 (12.6%) in Study #3.
During the course of the 3 clinical trials, 23 patients (5.8%) treated with active OESCLIM® withdrew due to signs of hyperestrogenism and/or metrorrhagia: 1 patient (3.1%) in Study #1, 17 patients (7.7%) in Study #2 and 5 patients (3.5%) in Study #3. Four (1.0%) of these patients withdrew for metrorrhagia alone: 1 in Study #1, 3 in Study #2 and 0 in Study #3. Nine (2.3%) patients withdrew for adverse events related to the treatment that were not considered signs of hyperestrogenism: 0 in Study #1, 8 in Study #2 and 1 in Study #3.
Results on general tolerability
General tolerability includes all adverse events described by the investigators which were neither signs of hyperestrogenism, nor metrorrhagia, nor symptoms attributed to the study treatment, nor application site reactions.
A total of 150 patients presented at least one adverse event not related to OESCLIM® during the course of the 3 studies: 7 patients (21.9%) in Study #1, 106 patients (47.3%) in Study #2 and 37 patients (25.9%) in Study #3. In general, these events resolved spontaneously. Forty two (10.6%) patients withdrew from the trials due to general adverse events: 1 patient in Study #1, 34 patients in Study #2 and 7 patients in Study #3.
DETAILED PHARMACOLOGY
Estrogens (naturally occurring, their derivatives or synthetic estrogens) are the basis of post-menopausal Hormonal Replacement Therapy (HRT). Mashchak et al.16 compared the metabolic effects of different estrogens given orally and reported that the physiological hormone estradiol induced the least metabolic disturbances.
It has been clearly demonstrated that estradiol is metabolised to a lesser extent when administered by the transdermal route than by the oral route. The transdermal route, by avoiding “first-pass” metabolism, allows a considerable reduction in the quantity of estradiol administered. Treatment with a patch that delivers 100 μg of estradiol per day results in mean serum levels of estradiol comparable to those obtained with 2 mg/day of micronised estradiol given orally. Moreover, oral estradiol administration results in serum concentrations of estrone, estrone glucuronide and estrone sulphate that are 3, 13 and 4 fold higher respectively, than after transdermal administration. Thus, after transdermal estradiol administration, the estradiol/estrone ratio in the serum is close to 1, the normal value present before menopause (this ratio is approximately 0.2 when estradiol is administered orally).21
Similarly, serum levels of estradiol glucuronides and sulphates, as well as oestriol glucuronides and sulphates, are 11, 5, 7 and 10 fold higher, respectively, after oral treatment than after transdermal treatment.25
The transdermal administration of estradiol provides dose levels of estradiol and estradiol metabolites that more closely approach the physiological than the oral route.
The significant difference in estradiol metabolism between the oral and transdermal routes is also evident in the results of urinary elimination. The concentration of estradiol and estrone conjugates in the urine is in fact 56 μg/g and 183 μg/g of creatinine, respectively, after 3 days of treatment with 2 mg/day of oral estradiol. After a 3-day application of a patch which delivers 100 μg/day, the urinary conjugates of estradiol and estrone did not exceed 4.2 μg/g and 11.3 μg/g of creatinine, respectively.4
A similar situation exists for estradiol distribution studies. Estrogens in the blood stream are bound to albumin, sex hormone-binding globulin (SHBG), cortisol-binding globulin and alpha-1 glycoproteins. It has been shown that three months treatment with 0.1 mg/day of estradiol by the transdermal route does not significantly modify estradiol or estrone binding to plasma transport proteins.10
Moreover, the transdermal route avoids unwanted metabolic effects following oral administration, such as an increase in angiotensinogen or a decrease in antithrombin III.10,11
TOXICOLOGY
Excess estradiol is one of the pre-disposing factors in the development of certain tumours, principally in the uterus, mammary and pituitary glands. These effects have been studied after long-term administration in rodents. Exposure in dogs and in primates has not been sufficiently long to reveal this type of activity. However, hyperplasia of the endometrium and the mammary glands, and increased secretory activity of the pituitary suggest that effects occurred at these sites in the above species.
In hamsters, tumour-inducing effects of mesenchymatous origin were observed in the kidneys. No such effects occur in rats, mice or humans. Hepatocarcinomas have been reported in rats after 9 and 12 months treatment with synthetic estrogens such as ethynyl estradiol and mestranol. Such effects have not been reported for estradiol-17β. Furthermore, estradiol administered by the transdermal route does not undergo “first pass” effect through the liver and thus avoids deleterious metabolic effects.
Estradiol is devoid of any mutagenic and/or clastogenic potential. Aneuploidy effects have been observed in vitro.
The carcinogenic potential (uterus, mammary glands and pituitary) of estradiol has been clearly established in animals. Its pre-neoplastic effects on the endometrium are reduced if a progestogen is associated with the estradiol.
No relationship has been established between the risk of pituitary tumours and estrogen treatment in postmenopausal women. Estradiol is contra-indicated in women presenting with tumours of the breast or the pituitary.
The OESCLIM® transdermal system was tested in the rabbit and the guinea-pig to evaluate its irritative and sensitizing potential. Three duplicate studies, two acute and two sub-acute local tolerability studies in rabbits and two sensitization studies in guinea-pigs, were performed. The patch was found to be only slightly irritating and had no sensitizing potential.
REFERENCES
- 1. Baulieu EE. Steroid receptors and hormone receptivity: new approaches in pharmacology and therapeutics. Ed by Inserm. In Hormones and Breast Cancer, 1975, 55, 15-28.
- 2. Chetowski RJ, Meldrum DR, Steingold KA, et al. Biologic effects of transdermal estradiol. N Engl J Med, 1986, 314, 1615-1620.
- 3. Chlebowski RT, Hendrix SL, Langer RD, et al. The Women’s Health Initiative randomized trial. Influence of estrogen plus progestin on breast cancer and mammography in healthy postmenopausal women. JAMA. 2003; 289(24):3243-3253.
- 4. Erenus M, Kutlay K, Kutlay L, Pekin S. Comparison of the impact of oral versus transdermal estrogen on serum lipoproteins. Fertil Steril, 1994, 61, 300-2.
- 5. Gangar KF, Vyas S, Whitehead M, Groor D, Meire H, et al. Pulsatility index in internal carotid artery in relation to transdermal oestradiol and time since menopause. Lancet, 1991, 338, 839-42.
- 6. Grady S, Herrington D, Bittner V, et al for the HERS Research Group. Cardiovascular disease outcomes during 6.8 years of hormone therapy. Heart and Estrogen/progestin Replacement Study follow-up (HERS II). JAMA. 2002; 288(1):49-57.
- 7. Grodstein F, Coditz GA, Stampfer MJ. Postmenopausal hormone use and cholecystectomy in a large prospective study. Obstet Gynecol, 1994, 83, 5-11.
- 8. Helgason S. Estrogen replacement therapy after the menopause. Estrogenicity and metabolic effects. Acta Obstet Gynecol Scand Suppl. 1982, 107, 1-29.
- 9. Hulley S, Grady D, Bush T, et al for the Heart and Estrogen/progestin Replacement Study (HERS) Research Group. Randomized trial of estrogen plus progestin for secondary prevention of coronary heart disease in postmenopausal women. JAMA. 1998; 280(7):605-613.
- 10. Jasonni VM, Bulletti C, Naldi S, et al. Biological and endocrine aspects of transdermal 17∃-oestradiol administration on post-menopausal women. Maturitas, 1988, 10, 263-270
- 11. Jensen J, Christiansen C. Effects of smoking on serum lipoproteins and bone mineral content during postmenopausal hormone replacement therapy. Am J Obstet Gynecol, 1988, 159, 820-5.
- 12. Kroon UB, SilfverStolpe G, Tengborn L. The effects of transdermal estradiol and oral conjugated estrogens on haemostasis variables. Trombosis haemostas, 1994, 71, 420-3.
- 13. Kuhnz W, Gansau C, Mahlel M. Pharmacokinetics of estradiol, free and total estrone, in young women following single intravenous and oral administration of 17∃ estradiol. Arzneim - Forsch Drug Res, 1993, 43, 966-73.
- 14. La Santé en France, faits majeurs et grandes tendances. Les principales pathologies, les maladies cardiovasculaires. La documentation française, Paris, 1989, pp 31-39.
- 15. Limouzin-Lamothe MA, Mairon N, Joyce CRB, Le Gal M. Quality of life after menopause: influence of hormonal replacement therapy. Am J Obstet Gynecol, 1994, 170, 618-24.
- 16. Mashchak CA, Lobo RA, Dozono-Takano R, et al. Comparison of pharmacodynamic properties of various estrogen formulations. Am J Obstet Gynecol, 1982, 144, 5, 511-518.
- 17. Means AR, O’Malley BW. Mechanism of estrogen action: early transcriptional and translational events. Metabolism, 1972, 21(4), 357-370.
- 18. Mueller GC. Estrogen action: a study of the influence of steroid hormones on genetic expression. Biochem Soc Symp. 1971, 32, 1-29.
- 19. Mueller GC, Cowan RA. Current Molecular insights into the mechanism of estrogen action. Adv Biosci. 1975, 15, 55-76.
- 20. Murad F, Gilman AG. Estrogens and progestins. Ed by Goodman AG, Rall TW, Nies AS Taylor P. In: The Pharmacological Basis of Therapeutic, 1980, 8, 1423-1434.
- 21. Padwick ML, Endacott J, Whitehead MI. Efficacy, acceptability and metabolic effects of transdermal estradiol in the management of postmenopausal women. Am J Obstet Gynecol, 1985, 152, 1085-1091.
- 22. Posthuma WFM, Westendorp RGJ, Vandenbroucke JP. Cardioprotective effect of hormonal replacement therapy in post menopausal women: is the evidence biased? BMJ, 1994, 308, 1268-9.
- 23. Powers MS, Shenkel L, Darkey PE, et al. Pharmacokinetics and pharmacodynamics of transdermal dosage forms of 17∃-estradiol: comparison with conventional oral estrogens used for hormone replacement. Am J Obstet Gynecol, 1985, 152, 8, 1099-1106.
- 24. Ryan KJ, Engell LL. The interconversion of estrone and estradiol by human tissue slices. Endoc, 1953, 52, 287-291.
- 25. Selby PI, McGarrigle HHG, Peacock M. Comparison of the effects of oral and transdermal oestradiol administration on oestrogen metabolism, protein synthesis, gonadotrophin release, bone turnover and climacteric symptoms in postmenopausal women. Clin Endocrinol, 1989, 30, 241-249.
- 26. Shumaker SA, Legault C, Kuller L, et al. Conjugated Equine Estrogens and Incidence of Probable Dementia and Mild Cognitive Impairment in Postmenopausal Women. Women’s Health Initiative Memory Study. JAMA. 2004; 291(24):2947-2958.
- 27. Shumaker SA, Legault C, Rapp SR, et al. Estrogen plus progestin and the incidence of dementia and mild cognitive impairment in postmenopausal women. The Women’s Health Initiative Memory Study: A randomized controlled trial. JAMA. 2003; 289(20):2651-2662.
- 28. Stevenson JC, Crook D, Godsland IF, Lees B, Whitehead MI. Oral versus transdermal hormone replacement therapy. Int J Fertil, 1993, 38 52, 30 - S.
- 29. Wagner JD, Clarkson TB, St Clair W, Schenke DC, Shively CA, et al. Estrogen and progesterone replacement therapy reduces low density lipoprotein accumulation in the coronary arteries of surgically postmenopausal cynomolgus monkeys. Clin Invest, 1991, 88, 1995-2002.
- 30. The Women’s Health Initiative Steering Committee. Effects of conjugated equine estrogen in postmenopausal women with hysterectomy. The Women’s Health Initiative randomized controlled trial. JAMA. 2004; 29(14):1701 – 1712.
- 31. Writing Group for the Women’s Health Initiative Investigators. Risks and benefits of estrogen plus progestin in healthy postmenopausal women. Principal results from the Women’s Health Initiative randomized controlled trial. JAMA. 2002; 288(3):321-333.
- 32. Wren BG, Routeledge DA. Blood pressure changes oestrogens in climacteric women. Med J Aust, 1981, 2, 528-31.
- 33. Data on file.