


Product Monograph - Kamrab
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.1 Pediatrics | 01/2025 |
|---|---|
| 4 DOSAGE AND ADMINISTATION, 4.4 Administration | 01/2025 |
| 7 WARNINGS AND PRECAUTIONS | 01/2025 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | 01/2025 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics | 01/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.1 Dosing Considerations ............................................................................................ 4
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.3 Reconstitution ........................................................................................................ 5
4.4 Administration ........................................................................................................ 5
4.5 Missed Dose ........................................................................................................... 5
5 OVERDOSAGE .............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations................................................................................................. 8
7.1.1 Pregnant Women ............................................................................................. 8
7.1.2 Breast-feeding .................................................................................................. 8
7.1.3 Pediatrics .......................................................................................................... 8
7.1.4 Geriatrics .......................................................................................................... 8
8 ADVERSE REACTIONS .................................................................................................. 8
8.1 Adverse Reaction Overview .................................................................................... 8
8.2 Clinical Trial Adverse Reactions .............................................................................. 8
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ..................................................... 9
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 10
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ............................ 10
9 DRUG INTERACTIONS ................................................................................................ 10
9.2 Drug Interactions Overview .................................................................................. 10
9.3 Drug-Behavioural Interactions .............................................................................. 10
9.4 Drug-Drug Interactions ......................................................................................... 11
9.5 Drug-Food Interactions ......................................................................................... 11
9.6 Drug-Herb Interactions ......................................................................................... 11
9.7 Drug-Laboratory Test Interactions ........................................................................ 11
10 CLINICAL PHARMACOLOGY ....................................................................................... 11
10.1 Mechanism of Action ...................................................................................... 11
10.2 Pharmacodynamics ........................................................................................ 11
10.3 Pharmacokinetics ........................................................................................... 11
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 12
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 12
PART II: SCIENTIFIC INFORMATION ....................................................................................... 12
13 PHARMACEUTICAL INFORMATION ............................................................................ 12
14 CLINICAL TRIALS ........................................................................................................ 14
14.1 Trial Design and Study Demographics ............................................................ 14
14.2 Study Results .................................................................................................. 15
14.3 Comparative Bioavailability Studies ................................................................ 15
15 MICROBIOLOGY ........................................................................................................ 17
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 17
PATIENT MEDICATION INFORMATION .................................................................................. 18
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
KamRAB is a human rabies immunoglobulin (HRIG) indicated for passive, transient post-exposure prophylaxis (PEP) of rabies infection, when given immediately after contact with a rabid or possibly rabid animal. KamRAB should be administered concurrently with a full course of rabies vaccine.
- Do not administer additional (repeat) doses of KamRAB once vaccine treatment has been initiated, since this may interfere with the immune response to the rabies vaccine.
- Do not administer KamRAB to patients with a history of a complete pre-exposure or post-exposure vaccination regimen and confirmed adequate rabies antibody titer.
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of KamRAB in the pediatric population have been evaluated in a clinical trial including pediatric patients aged from 0.5 to 14.9 years. Please refer to Section 14.2 Study Results.
1.2 Geriatrics
Geriatrics (> 65 years of age): Clinical studies of KamRAB did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Clinical experience with HRIG products has not identified differences in effectiveness between elderly and younger patients.
2 CONTRAINDICATIONS
None.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- For wound infiltration and intramuscular use. Do not administer intravenously.
Local Treatment of Wounds prior to KamRAB Administration
The World Health Organization (WHO) and National Advisory Committee on Immunization (NACI) have outlined recommendations for passive and active immunization after exposure to an animal suspected of having rabies. Immediate and thorough cleansing of all bite wounds and scratches with soap and water is an important component of post-exposure prophylaxis (PEP). A virucidal agent (e.g., povidone-iodine solution) should be used to irrigate the wounds.
Tetanus prophylaxis and measures to control bacterial infection should be given if medically indicated.
4.2 Recommended Dose and Dosage Adjustment
Post-exposure prophylaxis consists of a single dose of KamRAB and a full course of rabies vaccine. The recommended dose of KamRAB is 20 IU/kg body weight, given at the time of the first vaccine dose. KamRAB and the first dose of rabies vaccine should be given as soon as possible after exposure, as delays are potentially lethal. However, should a delay occur, KamRAB should be administered at any time up to and including seven days after the first dose of vaccine. The rabies vaccine should be given according to the manufacturer’s instructions.
No more than the recommended dose of KamRAB should be given because KamRAB partially suppresses active antibody production following vaccination. For the same reason, additional doses of KamRAB should not be given, even if the antibody response to vaccination is delayed.
4.3 Reconstitution
Reconstitution is not required. KamRAB is supplied in single-use vials containing ready-to-use solution.
4.4 Administration
When the bite site is known and infiltration at the bite site is feasible:
- Infiltrate as much of the dose as possible into and around any detectable bite wounds. Inject any remaining volume intramuscularly into the upper arm deltoid region or, in small children, into the anterolateral aspect of the thigh. Administer the remaining KamRAB at site(s) distant from the site of the rabies vaccine.
- When the bite site is unknown or indeterminate (undetectable) or if infiltration is difficult at the bite site (e.g., lips, fingers, knee), administer the full KamRAB dose by the intramuscular route at a site distant from the site of rabies vaccination.
- If a large intramuscular volume is required (>2 mL for children or >5 mL for adults), administer the total volume in divided doses at different sites.
- If intramuscular administration is contraindicated (e.g., in patients with uncorrectable bleeding disorders), administer KamRAB subcutaneously. However, note that there are no clinical efficacy data to support administration of KamRAB by the subcutaneous route.
- Do not mix with the rabies vaccine or administer in the same syringe with the rabies vaccine.
- Do not administer into the same anatomical site(s) as rabies vaccine.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. If either of these conditions exists, DO NOT use KamRAB; discard the vial.
Further Information on Rabies Post-Exposure Prophylaxis:
Consult public health officials if questions arise about the need for rabies prophylaxis.
4.5 Missed Dose
Not applicable.
5 OVERDOSAGE
Rabies Immunoglobulin (Human) may partially suppress active production of antibody in response to the rabies vaccine, do not give more than the recommended dose of rabies immunoglobulin (human).
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1– Dosage Forms, Strengths, Composition and Packaging
KamRAB is a sterile, non-pyrogenic aqueous solution of anti-rabies immunoglobulin (≥95% protein as IgG). The product is stabilized with 0.3 M glycine and has a pH of 5.5 ± 0.5. It does not contain preservatives and the vial stopper is not made with natural rubber latex. KamRAB is a clear to opalescent liquid.
7 WARNINGS AND PRECAUTIONS
This product is prepared from large pools of human plasma. Thus, there is a possibility it may contain causative agents of viral or other undetermined diseases.
General
Transmissible Infectious Agents
KamRAB is derived from human plasma; therefore, the potential exists that KamRAB administration may transmit infectious agents such as viruses, the variant Creutzfeldt-Jakob disease (vCJD) agent, and theoretically, the Creutzfeldt-Jakob disease (CJD) agent.
The risk of transmitting an infectious agent has been minimized by:
- Screening plasma donors for prior exposure to certain viruses;
- Testing for certain viral infections;
- Inactivating and removing certain viruses during the manufacturing process [see Pharmaceutical Information].
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intramuscular | Single-use vials containing 2 mL or 10 mL of ready-to-use human rabies immunoglobulin (HRIG) solution with a potency of 150 IU/mL | Glycine, Water for Injection, Sodium Hydroxide |
Despite these measures, KamRAB administration can still potentially transmit infectious diseases. There is also the possibility that unknown infectious agents may be present in KamRAB.
Hematologic
As with all preparations administered by the intramuscular route, bleeding complications may be encountered in patients with thrombocytopenia or other bleeding disorders. If intramuscular administration is contraindicated (e.g., in patients with uncorrectable bleeding disorders), administer KamRAB subcutaneously. However, note that there are no clinical efficacy data to support administration of KamRAB by the subcutaneous route.
Immune
Previous Rabies Vaccination
Patients who can document previous complete rabies pre-exposure prophylaxis or complete post-exposure prophylaxis should only receive a booster rabies vaccine without KamRAB, because KamRAB may interfere with the anamnestic response to the vaccine.
Live Attenuated Virus Vaccines
KAMRAB administration may interfere with the development of an immune response to live attenuated virus vaccines.
- Avoid immunization with measles vaccine within 4 months after KamRAB administration.
- Avoid immunization with other live attenuated virus vaccines within 3 months after KamRAB administration.
Monitoring and Laboratory Tests
KAMRAB may interfere with serologic testing. Please refer to 9.4 Drug-Laboratory Test Interactions.
Sensitivity/Resistance
Hypersensitivity
Hypersensitivity reactions, including anaphylaxis, may occur with KamRAB. History of prior systemic allergic reactions to human immunoglobulin preparations places patients at greater risk. Have epinephrine available for treatment of acute allergic symptoms. Patients with isolated immunoglobulin A (IgA) deficiency may develop severe hypersensitivity reactions to KamRAB or, subsequently, to the administration of blood products that contain IgA.
Skin
Injection site pain was observed in some patients administered KamRAB [see 8 ADVERSE REACTIONS].
7.1 Special Populations
7.1.1 Pregnant Women
KamRAB has not been studied in pregnant women. Therefore, the risk of major birth defects and miscarriage in pregnant women who are exposed to KamRAB is unknown. Animal developmental or reproduction toxicity studies have not been conducted with KamRAB. It is not known whether KamRAB can cause harm to the fetus when administered to a pregnant woman or whether KamRAB can affect reproductive capacity.
7.1.2 Breast-feeding
There is no information regarding the presence of KamRAB in human milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for KamRAB and any potential adverse effects on the breastfed infant from KamRAB or from the underlying maternal condition.
7.1.3 Pediatrics
Pediatrics (<18 years): The safety and effectiveness of KamRAB in the pediatric population have been evaluated in a clinical trial including pediatric patients aged from 0.5 to 14.9 years. Please refer to Section 14.2 Study Results.
7.1.4 Geriatrics
Clinical studies of KamRAB did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Clinical experience with HRIG products has not identified differences in effectiveness between elderly and younger patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most frequent adverse events in the KamRAB group (>6%) in clinical trials were injection site pain, headache, muscle pain, and upper respiratory tract infection.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
KamRAB was evaluated in three single-center, controlled clinical trials conducted in adults (≥ 18 years of age). Subjects in the clinical studies of KamRAB were healthy adults, primarily white and ranged in age from 18 to 72 years. A total of 160 subjects were treated in these three studies, including 91 subjects who received single intramuscular doses of KamRAB (20 IU/kg) with or without rabies vaccine.
The table below summarizes adverse events (assessed by the investigator as related or unrelated to study treatment) occurring in >3% of subjects in the clinical trials of KamRAB.
Table 2: Adverse Events Occurring in >3% of Subjects in All Studies in Adults (≥18 years of age) Combined
KamRAB N = 91 | Comparator HRIG N = 84 | Saline Placebo + Vaccine N = 8 | |
|---|---|---|---|
| Injection site pain | 30 (33) | 26 (31) | 2 (25) |
| Headache | 14 (15) | 11 (13) | 3 (38) |
| Muscle pain | 8 (9) | 6 (7) | 0 (0) |
| Upper respiratory tract infection | 8 (9) | 8 (10) | 0 (0) |
| Joint pain | 5 (6) | 0 (0) | 1 (13) |
| Dizziness | 5 (6) | 3 (4) | 0 (0) |
| Fatigue | 5 (6) | 2 (2) | 0 (0) |
| Abdominal pain | 4 (4) | 1 (1) | 0 (0) |
| Blood in urine | 4 (4) | 2 (2) | 0 (0) |
| Nausea | 4 (4) | 3 (4) | 0 (0) |
| Feeling faint | 4 (4) | 1 (1) | 0 (0) |
| Bruising | 3 (3) | 1 (1) | 0 (0) |
| Sunburn | 3 (3) | 0 (0) | 0 (0) |
| White blood cells in urine | 3 (3) | 4 (5) | 0 (0) |
Data are presented as number of subjects (% of subjects)
8.2.1 Clinical Trial Adverse Reactions – Pediatrics (≤18 years of age)
KamRAB was also evaluated in a two-center, open-label clinical trial in 30 pediatric patients exposed or possibly exposed to rabies virus. They ranged in age from 0.5 to 14.9 years. Study treatment included a single dose of KamRAB (20 IU/kg) and active rabies vaccine on Days 0, 3, 7 and 14 administered as per ACIP recommendations for rabies post-exposure prophylaxis.
Twelve pediatric patients (40%) experienced adverse reactions within 14 days of receipt of KamRAB and first dose of rabies vaccine. There were no serious adverse reactions. Table 1 summarizes the adverse reactions that occurred in >5% of patients in the pediatric clinical trial within 14 days of receipt of KamRAB and the first dose of the rabies vaccine.
Table 1: Adverse Reactions Occurring in >5% of Pediatric Patients within 14 Days of Post-exposure Prophylaxis with KamRAB and Active Rabies Vaccine
KamRAB + Rabies Vaccine N = 30 | |
|---|---|
| Injection site pain | 8 (27%) |
| Headache | 4 (13%) |
| Fever (Pyrexia) | 4 (13%) |
| Pain in extremity | 3 (10%) |
| Bruising (hematoma) | 2 (7%) |
| Fatigue | 2 (7%) |
| Vomiting | 2 (7%) |
N = Safety population: all subjects who received any amount of KamRAB
Data are presented as number of patients (% of patients).
8.3 Less Common Clinical Trial Adverse Reactions
Less common adverse events in adult population were joint pain, dizziness, fatigue, abdominal pain, blood in urine, nausea, feeling faint, bruising, sunburn, and white blood cells in urine.
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
Less common adverse reactions (≤5%) in pediatric patients were injection site redness (erythema), injection site swelling (edema), muscle pain, oral pain, and wound complication.
Insomnia was reported as a less common adverse reactions (<5%) in pediatric patients occurring after 14 days of administration.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Concomitant Vaccine Administration
- Do not administer additional (repeat) doses of KamRAB once vaccination has been initiated, since additional doses of KamRAB may interfere with the immune response to the vaccine.
- Do not administer KamRAB into the same anatomical site(s) as rabies vaccine.
KamRAB contains other antibodies that may interfere with the response to live vaccines such as measles, mumps, polio or rubella. Avoid immunization with live virus vaccines within 3 months after KamRAB administration, or in the case of measles vaccine, within 4 months after KamRAB administration.
9.3 Drug-Behavioural Interactions
Interactions with behaviour have not been established.
9.4 Drug-Drug Interactions
KamRAB may interfere with the anamnestic response to a previous rabies vaccination. KAMRAB administration may also interfere with the development of an immune response to live attenuated virus vaccines Please see Section 7 WARNINGS AND PRECAUTIONS, Immune.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
- A transient rise of the various passively transferred antibodies in the patient’s blood may result in misleading positive results of serologic tests after KamRAB administration.
- Passive transmission of antibodies to erythrocyte antigens, e.g., A, B, and D, may interfere with serologic tests for red cell antibodies such as the antiglobulin test (Coombs’ test).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Rabies is a zoonotic disease caused by RNA viruses in the family Rhabdoviridae, genus Lyssavirus. Virus is typically present in the saliva of rabid mammals and is transmitted primarily through a bite. KamRAB is infiltrated into the inoculation site (i.e., at the beginning of anti-rabies PEP) to previously unvaccinated persons, to provide immediate passive rabies virus neutralizing antibody protection until the patient’s immune system responds to vaccination by actively producing antibodies.
10.2 Pharmacodynamics
A protective threshold for rabies virus neutralizing activity (RVNA) has never been established. However, the WHO has generally accepted a RVNA of at least 0.5 IU/mL measured 14 days after initiation of PEP as protective. By comparison, the ACIP recommends complete neutralization of rabies virus at a 1:5 serum dilution by a rapid fluorescent focus inhibition test (RFFIT) from 1 to 2 weeks after prophylaxis; this corresponds to RVNA ~0.1-0.2 IU/mL. In support of these recommendations, there has been almost no documented clinical disease when the current rabies PEP regimen is administered appropriately.
KamRAB has the potential to attenuate the patient’s immune response to rabies vaccine. This was evaluated in a double-blind, randomized study where 16 healthy subjects were administered either KamRAB (20 IU/kg IM) or saline placebo followed by three doses of a rabies vaccine. Lower RVNA levels were seen in the KamRAB + vaccine group compared to the placebo + vaccine group at all time-points beginning on Day 14, confirming that KamRAB interferes with the host immune response to rabies vaccine.
10.3 Pharmacokinetics
A randomized, single-dose, two-period, two-treatment, two-sequence, double-blind, crossover study assessed the pharmacokinetics of KamRAB. Twenty-six healthy adult volunteer subjects were randomized to receive a single IM injection of 20 IU/kg HRIG on two separate occasions (KamRAB or Comparator HRIG). Subjects received the second treatment (A or B) following the 42-day test period and a 21-day washout period. Single dose IM injection of KamRAB resulted in maximum plasma RVNA levels of 0.25 IU/mL. The median Tmax was 7 days (range: 3 – 14 days). The elimination half-life was approximately 17.9 days.
No pharmacokinetics studies in pediatrics have been conducted to facilitate comparisons between children and adult pharmacokinetic profiles.
Duration of Effect
KAMRAB administration may interfere with the development of an immune response to live attenuated virus vaccines [see 7 WARNINGS AND PRECAUTIONS, Immune].
11 STORAGE, STABILITY AND DISPOSAL
- Store KamRAB at 2-8 °C (36-46 °F). Do not freeze.
- Keep vial in carton until use.
- KamRAB may be stored at room temperatures not exceeding 25 °C (77 °F) for up to one month.
- Use within one month after removal from refrigeration, Do not return to refrigeration.
- Do not use after the expiration date printed on the label.
12 SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Rabies Immunoglobulin (Human)
Chemical name: Rabies Immunoglobulin (Human)
Product Characteristics:
KamRAB Rabies Immunoglobulin (Human) is a sterile solution containing anti-rabies immunoglobulins (≥95% protein as IgG) for intramuscular injection with a nominal potency of 150 IU/mL.
KamRAB is prepared from human plasma from donors hyper-immunized with rabies vaccine. Individual plasma units are tested using FDA-licensed serologic assays for hepatitis B surface antigen (HBsAg) and for antibodies to hepatitis C virus (HCV) and human immunodeficiency virus types 1 and 2 (HIV-1/2), as well as by FDA-licensed Nucleic Acid Testing (NAT) for hepatitis B virus (HBV), HCV and HIV-1. Each plasma unit must be non-reactive (negative) in all tests. Plasma is also tested by in-process NAT procedures for HAV and parvovirus B19. Each plasma unit must be non-reactive to HAV, while the limit in the manufacturing pool is set not to exceed 104 IU per mL for parvovirus B19.
Viral Inactivation
To reduce the risk of viral transmission further, the manufacturing process for KamRAB includes three steps specifically designed to remove or inactivate viruses. The first of these is solvent/detergent (S/D) treatment with a mixture of tri-(n-butyl) phosphate (TnBP) and Octynoxol 9, which inactivates enveloped viral agents such as HIV, HBV and HCV. The second and third are heat-treatment (pasteurization) steps, which can inactivate both enveloped and non–enveloped viruses, and a nanofiltration (NF) step which removes viruses on the basis of size. The effectiveness of the S/D treatment, pasteurization and nanofiltration procedures for reducing viral content has been assessed using a series of viruses with a range of physico-chemical characteristics. The results of the viral challenge studies are summarized in the following table.
Table 4: Log10 Virus Reduction during Manufacture of KamRAB
| Process Step | Enveloped Viruses | Non-enveloped Viruses | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| HIV-1 | BVDV | PRV | WNV | EMCV | PPV | ||||||||||
| S/D treatment | >4.99 | >5.70 | >4.38 | >5.46 | Not tested | Not tested | |||||||||
| Heat treatment | >6.21 | >5.67 | Not tested | >6.33 | 3.30 | Not tested | |||||||||
| Nanofiltration | Not tested | Not tested | >6.58 | Not tested | >7.66 | 3.41 | |||||||||
| Global Log10 Reduction Factor | >11.20 | >11.37 | >10.96 | >11.79 | >10.96 | 3.41 | |||||||||
Abbreviations: BVDV: bovine viral diarrhea virus; EMCV: encephalomyocarditis virus; HIV-1: human immunodeficiency virus 1; HRIG: human rabies immunoglobulin; PPV: Porcine parvovirus; PRV: Pseudorabies virus; S/D: solvent/detergent; WNV: West Nile Virus
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Table 5 - Summary of patient demographics for clinical trials in [specific indication]
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| 003 | Prospective, randomized, double-blind, non-inferiority, pharmacokinetic, safety and effectiveness study of simulated post-exposure prophylaxis | 20 IU/kg KamRAB or comparator HRIG at a dose of 20 IU/kg on Day 0, and rabies vaccine on Days 0, 3, 7, 14 and 28 | 118 subjects (59 per treatment group) | KamRAB 43.3 (18-69) Comparator 46.3 (20-72) | M & F |
| 004 | Prospective, open-label study | Single dose (20 IU/kg) on day 0 IM injection Rabies vaccine On days 0, 3, 7 and 14 | 30 pediatric subjects | 7.45 ± 4.3 (0.5-14.9) | M & F |
The efficacy of KamRAB administered concurrently with rabies vaccine was studied in a single-center, randomized, comparator HRIG-controlled clinical study (Study 003). Study subjects were healthy adults 18 to 72 years of age who were without significant acute or chronic illness. A total of 118 subjects (59 per treatment group) received intramuscular KamRAB or comparator HRIG at a dose of 20 IU/kg on Day 0, and rabies vaccine on Days 0, 3, 7, 14 and 28. The mean age of study subjects was 45 years; subjects were, predominantly white (93%), and 64% were women. The efficacy variable was RVNA, as assessed by RFFIT, on Day 14. Efficacy analyses were performed on the As-Treated Population, which comprised the 116 study subjects who received KamRAB or comparator HRIG and at least 3 of the 5 doses of rabies vaccine before Day 14.
A study conducted in pediatric subjects, Study 004, was evaluated in a two-center, open-label clinical trial in 30 pediatric patients exposed or possibly exposed to rabies virus for whom post-exposure prophylaxis was indicated. The patients were treated with KamRAB at a dose of 20 IU/kg on Day 0 and active rabies vaccine on Days 0, 3, 7, and 14 as per ACIP recommendations for rabies post-exposure prophylaxis. The patients ranged in age from 0.5 to 14.9 years, 46.7% were females, 6.7% were Asian, 23.3% were Black and 70% were White, 10% were Latino. The efficacy variables were RVNA as assessed by RFFIT on Day 14 and occurrence of rabies disease through Day 84 after administration of KamRAB. Efficacy analyses were performed on the As-Treated Population, which comprised all 30 study patients.
14.2 Study Results
In study 003, efficacy, considered when RVNA titer is 0.5 IU/mL or higher on Day 14 (as established by the WHO), was met by 56/57 subjects (98.2%) in the KamRAB group and 59/59 subjects in the comparator HRIG group. The lower limit of the 90% CI was greater than the pre-specified non-inferiority margin of -10%; thus, KamRAB was non-inferior to comparator HRIG.
Table 6: Subjects with Geometric Mean RVNA ≥0.5 IU/mL on Day 14 (As-Treated Population)
KamRAB with Rabies Vaccine (N=57) | Comparator HRIG with Rabies Vaccine (N=59) | |||||||
|---|---|---|---|---|---|---|---|---|
| Rabies virus neutralizing antibody titer ≥0.5 IU/mL, n (%) | 56 (98.2) | 59 (100) | ||||||
| Exact 95% CI for proportion (%) | (90.6, 100) | (93.9, 100) | ||||||
| Difference (Pa-Pb)a (%) | -1.8 | |||||||
| Exact 90% CI for differenceb (%) | (-8.1, 3.0) | |||||||
a 'Pa' and 'Pb' are the proportion of participants with IgG antibody titer ≥0.5 IU/mL on Day 14 in Groups A and B, respectively. Group A = KamRAB +Rabies Vaccine, Group B = Control HyperRAB®+Rabies Vaccine.
b based on Farrington-Manning score statistic.
Abbreviations: CI: confidence interval; HRIG: human rabies immunoglobulin; IU: international units; mL: milliliter
Additional efficacy analyses included pharmacokinetics [see 10 Clinical Pharmacology, 10.3 Pharmacokinetics; 14.3 Comparative Bioavailability Studies].
In Pediatric Study 004, in the As-Treated Population, the geometric mean (SD) Day-14 RVNA titer was 18.89 (31.61) IU/mL and the median Day-14 RVNA titer was 8.81 (range 0.21 – 153.62) IU/mL. Of the 30 treated pediatric patients, 28 patients (93.3%) had a Day-14 RVNA titer ≥ 0.5 IU/mL, the WHO recommended level. None of the 28/30 patients who were followed for the duration of the study developed rabies infection through day 84.
14.3 Comparative Bioavailability Studies
A prospective, randomized, double-blind, non-inferiority, study evaluated the pharmacokinetics, safety and effectiveness of simulated post-exposure prophylaxis with KamRAB with co-administration of active rabies vaccine in 118 healthy adult subjects. Subjects were randomized into two treatment groups (59 per treatment group) to receive intramuscular KamRAB or comparator HRIG at a dose of 20 IU/kg on Day 0, and rabies vaccine on Days 0, 3, 7, 14 and 28. The geometric mean of the peak plasma RVNA was 39.9 IU/mL and 36.2 IU/mL for KamRAB and comparator HRIG respectively. For both treatment groups, the median Tmax was 14 days (range: 14 – 49 days). The half-lives were 48.6 hours and 52.7 hours for KamRAB and comparator HRIG respectively (Error! Reference source not found.7).
A plot of plasma rabies virus neutralizing antibody titer concentration versus time (Figure 1) demonstrated that, in both treatment groups, plasma rabies virus neutralizing antibody concentrations declined in a biphasic manner after the absorption phase was complete.
Figure 1: Plasma HRIG Concentrations [Mean (±SD)] at Scheduled PK Sampling Days (Semi-log Scale), Phase 2/3 Study, Pharmacokinetic Analysis
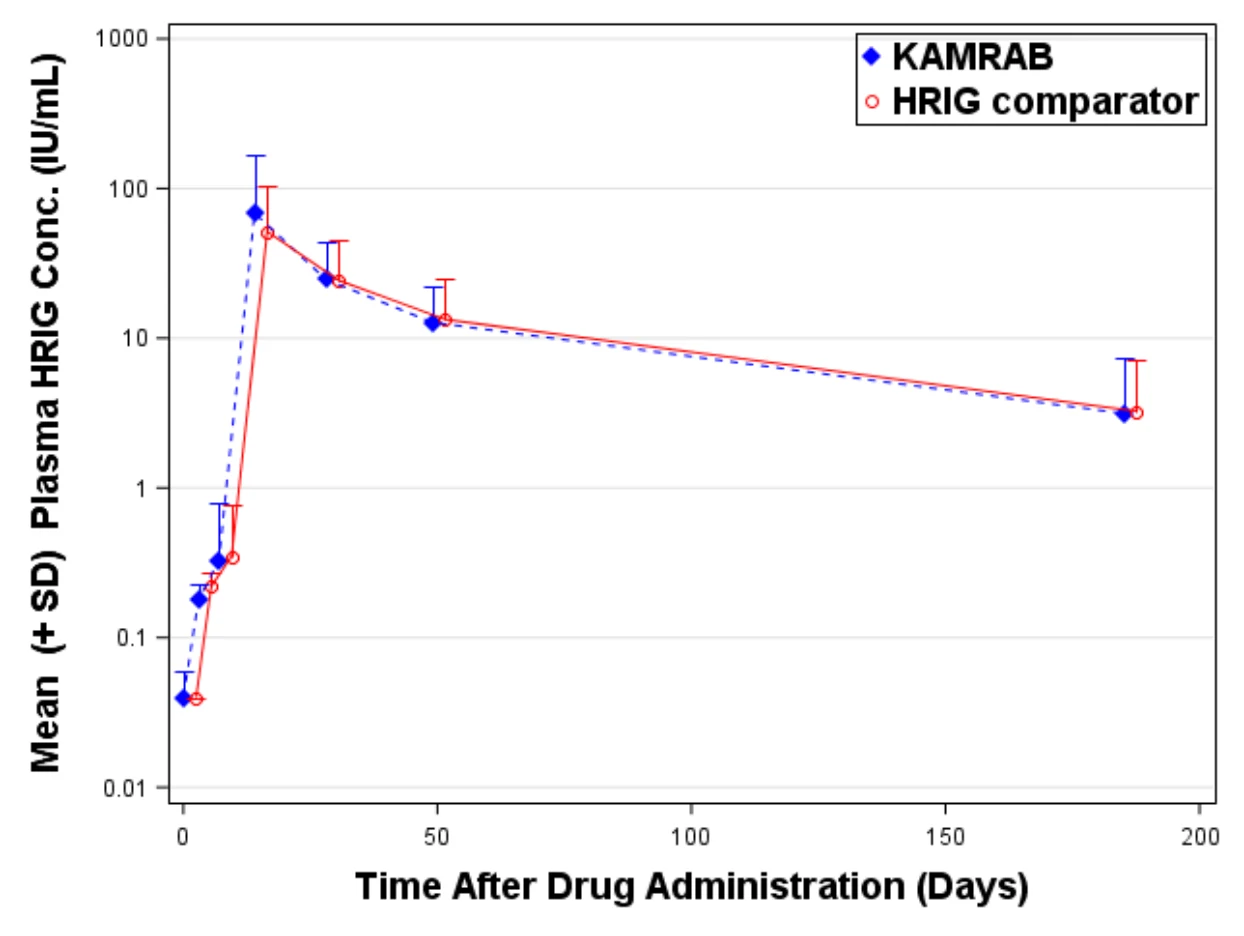
Table 7: Pharmacokinetic Comparison of PK Parameters for Plasma HRIG concentration, Phase 2/3 Study, Pharmacokinetic Analysis
PK Parameter Units | Statistic | Kamada-HRIG1 | Comparator HRIG1 |
|---|---|---|---|
Cmax (IU/mL) | N | 59 | 58 |
| Median | 51.7 | 35.7 | |
| Geometric mean (SD) | 39.9 (3.11) | 36.2 (2.64) | |
AUC0-last (Days*IU/mL) | N | 59 | 58 |
| Median | 1595 | 1447 | |
| Geometric mean (SD) | 1313 (2.93) | 1480 (2.24) | |
| AUC0-Inf | N | 43 | 44 |
PK Parameter Units | Statistic | Kamada-HRIG1 | Comparator HRIG1 |
|---|---|---|---|
| (Days*IU/mL) | Median | 1574 | 1635 |
| Geometric mean (SD) | 1603 (2.27) | 1657 (2.17) |
No pharmacokinetics studies in pediatrics have been conducted to facilitate comparisons between children and adult pharmacokinetic profiles.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Intramuscular administration of a single dose of KamRAB to rats at 60 and 120 IU/kg (3-fold and 6-fold higher than the recommended human dose of 20 IU/kg), did not result in any signs of toxicity.