


Product Monograph - Mekinist (Novartis Pharmaceuticals Canada, 1 mg)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablet / 0.5 mg, 1.0 mg and 2.0 mg | No clinically relevant nonmedicinal ingredients. For a complete listing see the DOSAGE FORMS, COMPOSITION, AND PACKAGING section. |
INDICATIONS AND CLINICAL USE
MEKINIST (trametinib) is indicated, as a monotherapy or in combination with dabrafenib, for the treatment of patients with unresectable or metastatic melanoma with a BRAF V600 mutation.
A validated test is required to identify BRAF V600 mutation status.
Clinical data supporting the effectiveness of MEKINIST monotherapy in patients with BRAF V600K mutation are limited and fewer responses were reported in BRAF V600K patients compared to BRAF V600E patients (see PART II, CLINICAL TRIALS). There are no clinical data for other less common BRAF V600 mutations.
MEKINIST monotherapy should not be used in patients who have progressed on a prior BRAF inhibitor therapy (see WARNINGS AND PRECAUTIONS, General and PART II, CLINICAL TRIALS).
MEKINIST monotherapy has not been compared with a BRAF inhibitor in a clinical study in patients with unresectable or metastatic melanoma (see WARNINGS AND PRECAUTIONS, General).
MEKINIST in combination with dabrafenib is not recommended in patients who have previously progressed on a BRAF inhibitor due to its limited efficacy in patients who progressed on dabrafenib monotherapy (see WARNINGS AND PRECAUTIONS).
When MEKINIST is used in combination with dabrafenib, see also the TAFINLAR® Product Monograph.
Geriatrics (≥ 65 years of age)
No overall differences in effectiveness of MEKINIST were observed between elderly patients (≥ 65 years) and younger patients. However, permanent discontinuation and dose reductions/interruptions of MEKINIST were reported more frequently in elderly patients than in younger patients (see WARNINGS AND PRECAUTIONS, Special Populations and ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Paediatrics (< 18 years of age)
The safety and efficacy of MEKINIST have not been established in children and adolescents less than 18 years of age (see WARNINGS AND PRECAUTIONS, Special Populations). Toxicology studies in rats showed dose-related thickening of the growth plate and subepiphyseal infarcts/degeneration in long bones (see PART II, TOXICOLOGY). MEKINIST is not recommended for use in children and adolescents (see WARNINGS AND PRECAUTIONS, Special Population).
CONTRAINDICATIONS
MEKINIST is contraindicated in patients who are hypersensitive to trametinib or to any ingredient in the formulation or component of the container. For a complete listing of the ingredients, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
WARNINGS AND PRECAUTIONS
When MEKINIST is used in combination with dabrafenib, also consult the TAFINLAR® Product Monograph for important warnings and precautions for dabrafenib in regard to secondary malignancies, non-infectious febrile events, decreased efficacy of oral contraceptives, valve abnormalities, QTc prolongation, hyperglycaemia, pancreatitis, uveitis, effects on fertility in males, renal failure, teratogenicity and use in paediatrics, geriatrics, moderate or severe hepatic impairment or severe renal impairment.
Serious Warnings and Precautions MEKINIST should be prescribed by a physician experienced in the administration of anti-cancer agents. |
The following are significant adverse drug reactions identified in clinical trials conducted with MEKINIST:
In addition to the above events, the following are significant adverse drug reactions identified in clinical trials conducted with MEKINIST in combination with dabrafenib:
|
General
Confirmation of BRAF V600 mutation in a tumour biopsy using a validated test is required for selection of patients appropriate for treatment with MEKINIST.
MEKINIST monotherapy has not been compared with a BRAF inhibitor in a clinical study in patients with BRAF V600 mutation positive unresectable or metastatic melanoma. However, overall response rates were lower in patients treated with MEKINIST than those reported in patients treated with BRAF inhibitors.
Prior BRAF Inhibitory Therapy: MEKINIST monotherapy was not effective in patients with BRAF V600 mutation positive unresectable or metastatic melanoma who progressed on a prior BRAF inhibitor therapy (see PART II, CLINICAL TRIALS). MEKINIST monotherapy should not be used in this patient population.
The combination of MEKINIST and dabrafenib demonstrated limited clinical activity in patients who had progressed on dabrafenib monotherapy and is not recommended for patients who have progressed on a prior BRAF inhibitor. Of 43 patients in a phase I/II study who crossed over from dabrafenib monotherapy to the combination of MEKINIST plus dabrafenib following progression, only 9 % (95% CI: 2.6, 22.1) had an ORR and the median PFS was 3.6 months (95% CI: 1.8, 3.9).
Pyrexia and Serious Non-Infectious Febrile Events: MEKINIST increases the incidence and severity of pyrexia associated with dabrafenib when used as a combination therapy. Refer to the TAFINLAR Product Monograph for further details on these events. See Table 5 (DOSAGE and ADMINISTRATION) for dose modifications of MEKINIST in patients who have serious non-infectious febrile events while on the combination therapy.
Brain Metastases: The safety and efficacy of the combination of MEKINIST and dabrafenib has not been evaluated in patients with a BRAF V600 mutation-positive melanoma which has metastasized to the brain. Three patients who developed brain metastases while on treatment with MEKINIST in combination with dabrafenib in phase III trials experienced fatal cerebral haemorrhage (see WARNINGS AND PRECAUTIONS, Haematologic).
Carcinogenesis and Mutagenesis
Carcinogenicity studies have not been performed with trametinib.
There was no indication for a genotoxic potential of trametinib after testing in standard in vitro assays and in vivo in rats (see PART II, TOXICOLOGY).
Secondary malignancies have occurred in patients treated with dabrafenib including patients receiving combination therapy with dabrafenib and MEKINIST.
Cardiovascular
Left Ventricular Dysfunction: MEKINIST has been reported to decrease left ventricular ejection fraction (LVEF) (see ADVERSE REACTIONS). In clinical trials with patients treated with MEKINIST at the recommended dose, patients with abnormal left ventricular ejection fraction were excluded.
In the randomized clinical study in patients with unresectable or metastatic melanoma, cardiac adverse events including decreased LVEF, left ventricular dysfunction, and cardiac failure were reported in 8% patients treated with MEKINIST monotherapy whereas none was reported in patients in the chemotherapy arm. In clinical trials with MEKINIST monotherapy, the median time to onset of left ventricular dysfunction and decreased LVEF was 58.5 (range: 16-526) days. Cardiac failure, left ventricular dysfunction or decreased LVEF leading to dose interruption was reported in 5% of patients, and leading to dose reduction in 3% of patients. MEKINIST was permanently discontinued in 2% of patients due to the cardiac adverse events.
In a phase III clinical study of MEKINIST in combination with dabrafenib compared to dabrafenib monotherapy, cardiac-related events (LVEF reduction and/or cardiac failure) were reported in 6% (12/209) of patients treated with combination therapy. Cardiac related events led to dose interruption of both drugs in 5% (10/209) of patients in the combination arm, with subsequent dose reduction of MEKINIST in two of these patients. Three patients discontinued therapy due to AEs of LVEF reduction (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). The median time to onset of the first occurrence of left ventricular dysfunction, cardiac failure and LVEF decrease in patients treated with MEKINIST in combination with dabrafenib was 157 (range: 28-758) days.
LVEF should be evaluated in all patients prior to initiation of treatment with MEKINIST with a recommendation of periodic follow-up within 8 weeks of initiating therapy. LVEF should continue to be evaluated during treatment with MEKINIST as clinically appropriate. MEKINIST is not recommended in patients with decreased LVEF at baseline. Dose modifications for managing decreased LVEF/left ventricular dysfunction are outlined in Table 5 (see DOSAGE AND ADMINISTRATION). MEKINIST should be permanently discontinued if left ventricular dysfunction cannot be resolved within 4 weeks after interruption of MEKINIST treatment or is of ≥ Grade 3 (see DOSAGE and ADMINISTRATION, Dose Modifications). MEKINIST should be used with caution in patients with conditions that could impair left ventricular function.
Venous Thromboembolism: Deep vein thrombosis (DVT) and pulmonary embolism (PE) can occur with MEKINIST. Across clinical studies in patients receiving MEKINIST monotherapy (n = 329), DVT was reported in 3 patients (1%) and PE was reported in 12 (4%) patients.
Fatal venous thromboembolism events have occurred when MEKINIST was used in combination with dabrafenib. In a Phase I/II study, DVT and PE occurred in 6% (12/204) of patients treated with combination therapy, including 2 fatalities (1%). In the phase III combination study, DVT or PE occurred in 3% (6/209) of patients receiving combination therapy.
If patients develop symptoms of pulmonary embolism or deep vein thrombosis such as shortness of breath, chest pain, or arm or leg swelling, they should immediately seek medical care.
Electrocardiography: MEKINIST was associated with a concentration-dependent prolongation of the PR interval in a phase I study. Analyses of Holter-derived ECG data in an ECG study showed a statistically significant decrease in heart rate and prolongation of the PR interval following dosing with MEKINIST versus placebo (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Cardiovascular Effects). Caution should be observed in patients with pre-existing conduction system disease (e.g. first degree, second degree or third degree AV block) or a history of syncope of unknown etiology. There are no data regarding concomitant use of MEKINIST with medications that result in PR interval prolongation. Nonetheless, these medications should be used with caution with MEKINIST (see DRUG INTERACTIONS).
Hypertension: Elevations in blood pressure have been reported in association with MEKINIST in patients with or without pre-existing hypertension. In a retrospective review of blood pressure measured every 3 weeks in the randomized clinical study in patients with unresectable or metastatic melanoma, there was a statistically significant increase in mean systolic and diastolic pressure in the MEKINIST monotherapy arm versus the chemotherapy arm at week 3 and 6, and diastolic pressure at week 9 following initiation of treatments. The comparator adjusted mean increase in systolic pressure was 5 mmHg and the diastolic pressure 4 mmHg. In this randomized study, hypertension as an adverse event was reported in 35 patients (17%) of which 28 (13%) were Grade 3.
In a phase III clinical study of MEKINIST in combination with dabrafenib compared to dabrafenib monotherapy, hypertension as an adverse event was reported in 52 patients (25%) in the combination arm. Grade 3 hypertension was reported in 12 (6%) of these patients.
Blood pressure should be monitored during MEKINIST treatment, with control of hypertension by standard therapy as appropriate (See Monitoring and Laboratory Tests below).
Gastrointestinal
Colitis and Gastrointestinal Perforation: Colitis and gastrointestinal perforation, including fatal outcome, have been reported in patients taking MEKINIST (see ADVERSE REACTIONS). Treatment with MEKINIST monotherapy or in combination with dabrafenib should be used with caution in patients with risk factors for gastrointestinal perforation, including a history of diverticulitis, metastases to the gastrointestinal tract and concomitant use of medications with a recognised risk of gastrointestinal perforation.
Patients should be advised to seek immediate medical care if they develop symptoms of colitis and gastrointestinal perforation.
Haematologic
Haemorrhage: Bleeding events including major haemorrhagic events (defined as symptomatic bleeding in a critical site, and fatal intracranial haemorrhages) have been reported in patients taking MEKINIST.
Bleeding events (any grade) were reported in 22% (73/329) of patients receiving MEKINIST monotherapy across clinical studies. Major haemorrhagic events of intracranial or gastric haemorrhage occurred in 0.6% (2/329) of patients.
In a phase I/II study, bleeding events (any grade) were reported in 31% (17/55) of patients treated with the combination of MEKINIST and dabrafenib. Intracranial haemorrhage occurred in 5% (3/55) and were fatal in 4% (2/55) of patients treated with the combination therapy. Gastrointestinal haemorrhage occurred in 7% (4/55) of patients in the combination arm; none of the events were fatal. In a phase III study, bleeding events (any grade) were reported in 19% (40/209) of patients treated with combination therapy and intracranial haemorrhage was fatal in 1% (3/209) of patients. Gastrointestinal haemorrhage occurred in 6% (12/209) of patients in the combination arm; none of the events were fatal.
In the phase III trials, 6 patients (1%) taking MEKINIST in combination with dabrafenib experienced fatal cerebral haemorrhage, including 2 who were taking anticoagulants and 3 who had developed brain metastases. The risk for serious haemorrhagic events in patients with unstable and/or symptomatic brain metastases or low platelets (< 75,000) is not established, as patients with these conditions were excluded from clinical trials. The risk of haemorrhage may be increased with concomitant use of antiplatelet or anticoagulant therapy or in patients who develop brain metastases while on treatment. If haemorrhage occurs, patients should be treated as clinically indicated.
Patients should be advised to seek immediate medical care if they develop symptoms of haemorrhage.
Cerebral haemorrhage (including fatal cases) associated with MEKINIST in combination with dabrafenib were reported in clinical trials and during post-marketing use.
Neutropenia: Neutropenia, including Grade 3 or 4 occurrences (14%, 30/209), has been reported in association with the combination of MEKINIST and dabrafenib. Patients receiving the combination therapy should have their complete blood counts determined at baseline and periodically on treatment (see Monitoring and Laboratory Results).
Hepatic
Hepatotoxicity: Hepatic adverse events have been reported when MEKINIST is used in combination with dabrafenib. In the phase III combination study 19% (39/209) of patients had hepatic events in the combination therapy arm including 7% with Grade 3 adverse events. In the combination arm, adverse events that led to dose reduction occurred in 4 patients (2%) due to MEKINIST and 3 patients (1%) due to dabrafenib; adverse events that led to dose interruption occurred in 9 patients (4%) due to MEKINIST and 8 patients (4%) due to dabrafenib in the combination arm ; adverse events that led to the drug being withdrawn occurred in 1 patient (< 1%) due to MEKINIST and in 2 patients (< 1%) due to dabrafenib. Two patients receiving the combination therapy permanently discontinued either dabrafenib or both MEKINIST and dabrafenib due to elevations in liver enzymes (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Musculoskeletal
Rhabdomyolysis: Rhabdomyolysis has been reported in patients taking MEKINIST (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). Many cases were severe and resulted in hospitalization with interruption or permanent discontinuation of MEKINIST.
Signs or symptoms of rhabdomyolysis warrant an appropriate clinical evaluation and treatment as indicated. MEKINIST therapy should be interrupted until rhabdomyolysis resolves. Carefully consider the benefits and risks when deciding if treatment with MEKINIST should be re-initiated and, if so, consider resuming at a reduced dose.
Ophthalmologic
Retinal Pigment Epithelial Detachment: Retinal pigment epithelial detachments (RPED) can occur during treatment with MEKINIST monotherapy and in combination with dabrafenib (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). In phase III clinical studies of MEKINIST monotherapy and in combination with dabrafenib, RPED was reported in < 1% of patients. The drug-induced RPEDs were often bilateral, multifocal, occurring in the macular region of the retina, and were associated with symptoms such as blurred vision and decreased visual acuity. Optical coherence tomography (OCT) abnormalities may persist beyond a month. Recurrence was reported in some patients who had experienced ≥ Grade 2 RPED after MEKINIST was re-initiated at reduced doses.
Perform ophthalmological evaluation any time a patient reports new visual disturbances and compare to baseline, if available. Withhold MEKINIST if RPED is diagnosed. If resolution of RPED is documented on repeat ophthalmological evaluation within 3 weeks, MEKINIST can be resumed at a reduced dose. If RPED recurs or does not improve within 3 weeks to grade 0-1, MEKINIST should be permanently discontinued.
Retinal Vein Occlusion (RVO): RVO has been reported in patients treated with MEKINIST (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). The incidence of RVO was 0.2% across MEKINIST monotherapy clinical trials. RVO may lead to macular oedema, acute and progressive loss of vision, neovascularization, and glaucoma. Full recovery may not occur in patients developing RVO on MEKINIST treatment. Patients with hypertension, diabetes, hypercholesterolemia, or glaucoma are at higher risk for RVO. MEKINIST is not recommended in patients with a history of RVO. In patients who experience RVO, treatment with MEKINIST should be permanently discontinued.
Uveitis: MEKINIST increases the severity of uveitis (including iridocyclitis) events associated with dabrafenib when used as a combination therapy.
Respiratory
Interstitial Lung Disease: In the clinical study in patients with unresectable or metastatic melanoma, interstitial lung disease or pneumonitis was reported in 2.8% of patients treated with MEKINIST (n = 211) compared to none in patients in the chemotherapy arm (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions). All six cases were serious (including one fatal case) leading to permanent discontinuation of MEKINIST.
In a phase III clinical study of MEKINIST in combination with dabrafenib compared to dabrafenib monotherapy, less than 1% (2/209) of patients on combination treatment developed pneumonitis. One of the cases of pneumonitis was serious (Grade 2). Doses of both MEKINIST and dabrafenib were interrupted and reduced; the event resolved.
MEKINIST should be permanently discontinued if pneumonitis is diagnosed (see Table 5 in DOSAGE AND ADMINISTRATION).
Sexual Function/Reproduction
Infertility: There is no information on the effect of MEKINIST on human fertility. In animals, no fertility studies have been performed. In a repeat-dose toxicity study, adverse effects were seen on female reproductive organs in rats at sub-therapeutic exposures. There were no effects on male reproductive organs; however, systemic exposures at doses tolerated by animals were lower than exposure at the recommended therapeutic dose (see PART II, TOXICOLOGY). MEKINIST may impair fertility in humans.
Skin
Skin Toxicity: In clinical studies with MEKINIST monotherapy, skin toxicities of all grades have occurred in 87% of patients. Severe skin toxicities have occurred in 12% of patients. These skin toxicities included rash, dermatitis acneiform, and palmar-plantar erythrodysesthesia syndrome (see ADVERSE REACTIONS). Skin toxicities leading to dose reduction and interruption were reported in 12% and 12% of patients, respectively.
Serious skin infections including dermatitis, folliculitis, paronychia, cellulitis, and infective skin ulcer were also reported. In the randomized study in patients with unresectable or metastatic melanoma, six percent of patients treated with MEKINIST compared to none in the chemotherapy arm required hospitalization and intravenous antibiotics due to serious skin toxicity or secondary infections.
In a phase III clinical study of MEKINIST in combination with dabrafenib compared to dabrafenib monotherapy, skin toxicities occurred in 48% of patients who received combination treatment. Most skin-related toxicities were Grade 1 or Grade 2, and most were events of rash. No serious skin-related toxicities were reported. Skin toxicities leading to dose reduction and interruption were reported in 4% and 2%, respectively, of patients who received MEKINIST in combination with dabrafenib.
Skin toxicity and infections should be monitored during MEKINIST treatment. MEKINIST should be withheld for up to 3 weeks if Grade 2 intolerable or ≥ Grade 3 skin toxicity occurs. MEKINIST should be permanently discontinued if the skin toxicity does not improve within three weeks despite interruption of therapy (see DOSAGE AND ADMINISTRATION, Dose Modifications).
Special Populations
Pregnant Women: There are no adequate and well-controlled studies of MEKINIST in pregnant women. Animal studies have shown reproductive toxicity. In rabbits, post-implantation loss, including total loss of pregnancy, and foetal toxicity, consisting of decreased body weight and ossification defects, occurred at sub-therapeutic systemic trametinib exposure levels (see PART II, TOXICOLOGY). MEKINIST should not be administered to pregnant women. Women of childbearing potential should use effective methods of contraception during therapy and for 4 months following discontinuation of MEKINIST. If MEKINIST is used during pregnancy, or if the patient becomes pregnant while taking MEKINIST, the patient should be informed of the potential hazard to the foetus.
Women of childbearing potential receiving MEKINIST in combination with dabrafenib should be advised that dabrafenib may decrease the efficacy of hormonal contraceptives and an alternate method of contraception, such as barrier methods, should be used.
Nursing Women: No studies have been conducted with MEKINIST in nursing mothers. MEKINIST should not be administered to nursing mothers. It is not known whether trametinib is excreted in human milk. Because many drugs are excreted in human milk, a risk to the nursing infant cannot be excluded. A decision should be made whether to discontinue nursing or to discontinue MEKINIST, taking into account the importance of MEKINIST to the mother.
Paediatrics (< 18 years of age): The safety and efficacy of MEKINIST have not been established in children and adolescents less than 18 years of age. MEKINIST may affect bone growth (see PART II, TOXICOLOGY). MEKINIST is not recommended for use in children and adolescents.
Geriatrics (≥ 65 years of age): In clinical studies with MEKINIST monotherapy in patients with unresectable or metastatic melanoma (n = 329), 67 patients (20%) were 65 years of age and older, and 13 patients (4%) were 75 years of age and older. Higher rates of discontinuation and dose interruptions/ reductions were reported in elderly patients than the younger patients (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Of the number of patients in a phase III clinical study receiving MEKINIST in combination with dabrafenib (N = 209), 56 patients (27%) were 65 years of age and older, and 11 patients (5%) were 75 years of age and older. Compared with younger patients (< 65 years), more patients ≥ 65 years’ old had adverse events that led to dose reductions (43% versus 23%) or interruptions (66% versus 53%) of therapy with MEKINIST or dabrafenib. In addition, older patients experienced more serious adverse events compared to younger patients (59% versus 36%). The incidences of peripheral oedema in the combination (34% vs. 16%) and monotherapy arms (18% vs. 5%) and of decreased appetite in the combination (21% vs. 9%) and monotherapy arms (15% vs. 13%) were more frequent in patients ≥ 65 years than in patients < 65 years, respectively.
Gender: Female patients with lower body weights had higher systemic exposure of trametinib compared to male patients (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions). Common and Grade 3 adverse reactions were reported more frequently in female than male patients in the randomized clinical trial (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
Renal impairment: A pharmacokinetic study in patients with renal impairment has not been conducted. Renal impairment is unlikely to have a clinically relevant effect on trametinib pharmacokinetics given the low renal excretion of trametinib.
Based on a population pharmacokinetic analysis, mild or moderate renal impairment had no significant effect on the oral clearance and systemic exposure of trametinib (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics). There are no data with MEKINIST in patients with severe renal impairment.
Hepatic impairment: A pharmacokinetic study in patients with hepatic impairment has not been conducted.
Based on a population pharmacokinetic analysis, trametinib oral clearance was not significantly different in patients with mild hepatic impairment compared to patients with normal hepatic function (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics). There are no clinical data in patients with moderate or severe hepatic impairment.
Monitoring and Laboratory Tests
Confirmation of BRAF V600 mutation using a validated test is required for selection of patients appropriate for MEKINIST therapy.
LVEF should be evaluated in all patients prior to initiation of treatment with MEKINIST with a recommendation of periodic follow-up within 8 weeks of initiating therapy. LVEF should continue to be evaluated during treatment with MEKINIST, as clinically appropriate (see DOSAGE AND ADMINISTRATION).
Blood pressure should be measured at baseline and monitored during treatment with MEKINIST (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions).
A thorough ophthalmological evaluation should be performed at baseline, if clinically warranted. Perform ophthalmological evaluation any time a patient reports new visual disturbances and compare to baseline, if available.
Patients should be monitored for skin toxicity 2 weeks after initiating MEKINIST treatment and periodically thereafter or, as clinically warranted.
Monitor patients receiving MEKINIST carefully for bleeding events and neurologic symptoms.
Patients receiving MEKINIST in combination with dabrafenib should have their complete blood counts determined at baseline and periodically on treatment.
Monitor liver function in patients receiving treatment with MEKINIST in combination with dabrafenib approximately every 4 weeks for 6 months after treatment initiation of this combination therapy. Liver monitoring may be continued thereafter as clinically indicated during therapy.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The safety of MEKINIST monotherapy has been evaluated in an integrated population of 329 patients with unresectable or metastatic melanoma treated with MEKINIST 2 mg orally once daily in clinical trials with median duration of treatment of 3.8 (range: 0.03-24.5) months.
Almost all patients (> 99%) treated with MEKINIST monotherapy reported at least one adverse reaction. The most common adverse reactions (≥ 20%) included rash, diarrhoea, fatigue, peripheral oedema, nausea, dermatitis acneiform and vomiting. Serious adverse drug reactions were reported in 22% of patients treated with MEKINIST. Serious adverse drug reactions reported in > 1% of patients included cellulitis, pulmonary embolism, anaemia, dyspnoea, pneumonitis and vomiting.
Adverse reactions leading to permanent discontinuation were reported in 10% of patients treated with MEKINIST monotherapy. The most common adverse reactions leading to permanent discontinuation were ejection fraction decreased/left ventricular dysfunction, pneumonitis, and alanine aminotransferase increased. Adverse reactions leading to dose reduction and interruption were reported in 26% and 36%, respectively. The most common adverse reactions leading to dose reductions or interruptions included rash, ejection fraction decreased/left ventricular dysfunction, dermatitis acneiform, diarrhoea and peripheral oedema.
The safety of MEKINIST in combination with dabrafenib has been evaluated in a multicentre, randomized phase III study (MEK115306) in a pooled a safety population of 209 patients with advanced or metastatic melanoma. In this study, approximately 71% of patients received treatment with MEKINIST and dabrafenib for more than 6 months. The median durations of treatment in the combination and dabrafenib monotherapy arms were 11 and 8 months, respectively.
A higher percentage of patients had AEs leading to permanent discontinuation of study treatment in the combination therapy arm of the MEK115306 study (11%) than in the dabrafenib monotherapy arm (7%). The percentage of patients with AEs leading to dose interruptions and dose reductions was also higher in the combination therapy arm than with dabrafenib monotherapy. Fifty six percent (56%) and 28% of patients receiving the combination therapy had dose interruptions and reductions, respectively, compared to 37% and 14% of patients treated with dabrafenib monotherapy.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
MEKINIST Monotherapy
The adverse drug reactions described in this section were those reported in a randomized, open-label study where patients with unresectable or metastatic melanoma were randomized to receive MEKINIST 2 mg orally once daily or chemotherapy (dacarbazine 1,000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks). Patients who received at least one dose of study drug were included in the safety population. The median duration of study treatment was 4.8 (range: 0.3-16.3) months for MEKINIST arm and 2.1 (range: 0.1-14.0) months for chemotherapy arm.
The incidence of adverse events resulting in permanent discontinuation of study medication was 12% for patients treated with MEKINIST and 9% for patients treated with chemotherapy. The incidence of adverse events leading to dose reductions was 32% for MEKINIST and 10% for chemotherapy. The incidence of adverse events leading to dose delay/interruption was 38% for MEKINIST and 24% for chemotherapy.
Fatal treatment-emergent adverse events were reported in 1.9% of patients in the MEKINIST arm (myocardial infarction, renal failure, hepatic and renal failure, death of unknown cause) and in 2% of patients in the chemotherapy arm (pneumonia, pseudomembranous colitis). Two fatal adverse events (infected skin ulcer, pneumonitis) were reported in patients treated with MEKINIST after crossover from the chemotherapy arm.
Adverse reactions were reported in > 99% and 93% of patients in the safety population treated with MEKINIST and chemotherapy, respectively. The majority of patients (97% in the MEKINIST arm and 80% in the chemotherapy arm) reported adverse events considered drug-related by the investigators. Among the commonly reported adverse events, rash, diarrhoea, peripheral oedema, dermatitis acneiform, dry skin, pruritus, paronychia and hypertension were more frequent in patients in the MEKINIST arm, while nausea, vomiting and constipation were more frequent in patients in the chemotherapy arm. Table 1 lists the adverse reactions with an incidence of ≥ 10% in patients receiving MEKINIST.
Table 1 Adverse Reactions (%) Occurring in ≥ 10% of Patients Treated With MEKINIST Monotherapy
| MEKINIST 2mg QD | Chemotherapyb | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| (N = 211) | (N = 99) | |||||||||||||
| Adverse Drug Reactions by System Organ Class and Preferred Term | All Gradesa | Grade 3/4 | All Gradesa | Grade 3/4 | ||||||||||
| Any adverse reaction | > 99 | 52 | 93 | 32 | ||||||||||
| Gastrointestinal disorders | 70 | 7 | 65 | 5 | ||||||||||
| Diarrhoea | 44 | < 1 | 17 | 2 | ||||||||||
| Nausea | 22 | < 1 | 39 | 1 | ||||||||||
| Constipation | 16 | < 1 | 23 | 1 | ||||||||||
| Vomiting | 15 | 1 | 20 | 2 | ||||||||||
| General disorders and administrative site conditions | 64 | 9 | 55 | 6 | ||||||||||
| Fatigue | 29 | 4 | 28 | 3 | ||||||||||
| Oedema peripheral | 29 | < 1 | 3 | 0 | ||||||||||
| Infections and Infestations | 42 | 7 | 21 | 1 | ||||||||||
| Paronychia | 11 | 0 | 1 | 0 | ||||||||||
| Folliculitis | 10 | < 1 | 2 | 0 | ||||||||||
| Skin and subcutaneous tissue disorders | 92 | 13 | 36 | 0 | ||||||||||
| Rash | 59 | 7 | 10 | 0 | ||||||||||
| Dermatitis acneiform | 19 | < 1 | 2 | 0 | ||||||||||
| Alopecia | 18 | < 1 | 19 | 0 | ||||||||||
| Dry Skin | 13 | 0 | 1 | 0 | ||||||||||
| Pruritus | 11 | 2 | 1 | 0 | ||||||||||
| Vascular Disorders | 30 | 15 | 16 | 4 | ||||||||||
| Hypertension | 17 | 13 | 7 | 3 | ||||||||||
| Haemorrhage | 13 | < 1 | 0 | 0 | ||||||||||
| MEKINIST 2mg QD | Chemotherapyb |
|---|
| (N = 211) | (N = 99) | |||||
|---|---|---|---|---|---|---|
| Nervous system disorders | 33 | 4 | 38 | 3 | ||
| Headache | 14 | 1 | 15 | 0 | ||
| Respiratory, thoracic and mediastinal disorders | 29 | 7 | 20 | 0 | ||
| Cough | 11 | 0 | 6 | 0 | ||
| Investigations | 31 | 11 | 19 | 8 | ||
| Aspartate aminotransferase increased | 10 | 2 | 1 | 0 | ||
a National Cancer Institute Common Terminology Criteria for Adverse Events, version 4
b Chemotherapy included patients on dacarbazine (DTIC) 1000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks
Elderly patients (≥ 65 years) reported the following adverse reactions more frequently than the younger counterpart (< 65 years): peripheral oedema, pruritus, decreased appetite, rash pustular, paraesthesia, lymphoma, pain in extremity, vision blurred, blood creatine phosphokinase increased, blood lactate dehydrogenase increased, erythema, oedema, syncope, weight decreased and periorbital oedema. Grade 3 adverse events (57% vs. 37%) and serious adverse events (26% vs. 16%) were also reported more frequently in elderly than younger patients. In addition, a higher percentage of elderly patients compared to younger patients experienced adverse events leading to dose interruption (45% vs. 32%), reduction (47% vs. 22%) or permanent discontinuation (21% vs. 6%).
Female patients reported the following adverse reactions more frequently than male patients: peripheral oedema, alopecia, vomiting, dry skin, pruritus, stomatitis, dry mouth, abdominal pain/abdominal pain upper, epistaxis, mucosal inflammation, rash pustular, eczema, palmar-plantar erythrodysesthesia syndrome and periorbital oedema.
Less Common Clinical Trial Adverse Drug Reactions (< 10%) with MEKINIST Monotherapy
Treatment emergent adverse events considered clinically significant in studies with MEKINIST monotherapy at the recommended dose (n = 329) are presented below. As the list includes adverse events from the integrated safety population of three clinical trials, some adverse events with frequency > 10% are not included in Table 1.
Blood and lymphatic system disorders: Anaemia (9%), Thrombocytopenia (2%), Neutropenia (2%)
Cardiac disorders: Ejection fraction decreased (5%), Bradycardia (2%), Left ventricular dysfunction (4%), Cardiac failure (< 1%)
Cardiovascular disorders: Pulmonary embolism (4%), Deep vein thrombosis (1%)
Eye disorders: Vision blurred (6%), Periorbital oedema (3%), Dry eye (3%), Visual impairment (2%), Retinal pigment epithelial detachment (< 1%), Papilledema (< 1%), Retinal detachment (< 1%), Retinal vein occlusion (< 1%)
Gastrointestinal disorders: Abdominal pain (13%), Dry mouth (10%), Stomatitis (7%), Dysphagia (2%)
General disorders and administration site conditions: Pyrexia (12%), Mucosal inflammation (7%), Face oedema (7%), Asthenia (5%), Sudden death (< 1%)
Hepatobiliary disorders: Alanine aminotransferase increased (8%), Blood alkaline phosphatase increased (5%), Cytolytic hepatitis (< 1%), Blood bilirubin increased (< 1%)
Immune system disorders: Hypersensitivity (1%), Corneal graft rejection (< 1%)
Infections and infestations: Cellulitis (5%), Rash pustular (3%), Erysipelas (2%), Eye infection (2%), Fungal skin infection (< 1%)
Metabolism and nutrition disorders: Hypoalbuminemia (6%), Dehydration (4%)
Musculoskeletal and connective tissue disorders: Arthralgia (10%), Back pain (7%), pain in extremity (7%), Muscle spasm (5%), Joint swelling (2%), Blood creatine phosphokinase increased (2%), Rhabdomyolysis (< 1%)
Nervous system disorders: Dizziness (8%), Dysgeusia (6%), Syncope (2%)
Reproductive system and breast disorders: Scrotal oedema (< 1%)
Respiratory, thoracic and mediastinal disorders: Cough (11%), Dyspnoea (11%), Epistaxis (8%), (4%), Pneumonitis (2%), Interstitial lung disease (< 1%)
Skin and subcutaneous tissue disorders: Erythema (5%), Palmar plantar erythrodysesthesia syndrome (4%), Skin chapped (4%), Skin fissures (3%), Dermatitis (2%), Hyperkeratosis (1%), Skin ulcer (1%)
Vascular disorders: Lymphedema (7%)
Abnormal Haematologic and Clinical Chemistry Findings
Table 2 lists the laboratory adverse events with an incidence of ≥ 1% in patients receiving MEKINIST monotherapy in the randomized study in patients with unresectable or metastatic melanoma.
Table 2 Abnormal Laboratory Adverse Events (%) Occurring in ≥ 1% of Patients Treated With MEKINIST Monotherapy
| Adverse Events by Preferred Term | MEKINIST 2mg QD (N = 211) | Chemotherapyb (N = 99) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| All Gradesa | Grades 3 and 4 | All Gradesa | Grades 3 and 4 | ||||||||
| Hypoalbuminemia | 4 | 1 | 1 | 1 | |||||||
| Hypocalcaemia | 2 | 0 | 0 | 0 | |||||||
| Hyponatremia | 1 | 1 | 0 | 0 | |||||||
| Aspartate aminotransferase increased | 10 | 2 | 1 | 0 | |||||||
| Alanine aminotransferase increased | 9 | 3 | 3 | 0 | |||||||
| Blood alkaline phosphatase increased | 6 | 1 | 1 | 0 | |||||||
| Blood lactate dehydrogenase increased | 4 | < 1 | 0 | 0 | |||||||
| Blood creatinine phosphokinase increased | 4 | 2 | 1 | 0 | |||||||
| Blood albumin decreased | 2 | < 1 | 1 | 1 | |||||||
| Haemoglobin decreased | 1 | < 1 | 1 | 0 | |||||||
| White blood cell count decreased | 1 | 0 | 2 | 0 | |||||||
a National Cancer Institute Common Terminology Criteria for Adverse Events, version 4
b Chemotherapy included patients on dacarbazine (DTIC) 1000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks
MEKINIST in Combination with Dabrafenib
Table 3 and Table 34 present adverse drug reactions and laboratory abnormalities, respectively, from the phase III study of MEKINIST 2 mg given once daily in combination with dabrafenib 150 mg given twice daily compared to dabrafenib monotherapy (see Part II, CLINICAL TRIALS). The common adverse reactions in Table 3 were reported in ≥ 10% of patients treated with the combination of MEKINIST with dabrafenib or were Grade 3 and 4 events reported in ≥ 2% of patients treated with the combination.
Table 3 Adverse Reactions (%) Occurring in ≥ 10% (All Grades) or ≥ 2% (Grades 3 or 4) of Patients Treated with MEKINIST in Combination with Dabrafenib in Study MEK115306
| MEK115306 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Dabrafenib 150 mg BID + MEKINIST 2 mg QD (N = 209) | Dabrafenib 150 mg BID + Placebo (N = 211) | |||||||||||
All Grades (%) | Grade 3 and Grade 4 (%) | All Grades (%) | Grade 3 and Grade 4 (%) | |||||||||
| Neoplasms benign and malignant (including cysts and polyps) | ||||||||||||
| cuSCCa,b | 3 | 3 | 10 | 10 | ||||||||
| Metabolism and nutritional disorders | ||||||||||||
| Decreased appetite | 12 | < 1 | 13 | < 1 | ||||||||
| Hyperglycaemiac | 7 | 3 | 3 | < 1 | ||||||||
| Nervous system disorders | ||||||||||||
| Headache | 33 | < 1 | 30 | 1 | ||||||||
| Dizziness | 14 | 0 | 7 | 0 | ||||||||
| Respiratory, thoracic, and mediastinal disorders | ||||||||||||
| Cough | 21 | 0 | 21 | 0 | ||||||||
| Gastrointestinal disorders | ||||||||||||
| Nausea | 34 | < 1 | 27 | 1 | ||||||||
| Diarrhoea | 30 | 1 | 16 | < 1 | ||||||||
| Vomiting | 25 | < 1 | 14 | < 1 | ||||||||
| Constipation | 13 | < 1 | 10 | 0 | ||||||||
| Abdominal pain | 13 | < 1 | 9 | 2 | ||||||||
| Skin and subcutaneous tissue disorders | ||||||||||||
| Rash | 27 | 0 | 22 | < 1 | ||||||||
| Dry skin | 12 | 0 | 16 | 0 | ||||||||
| Pruritus | 12 | 0 | 14 | 0 | ||||||||
| Dermatitis acneiform | 10 | 0 | 4 | 0 | ||||||||
| Musculoskeletal, connective tissue and bone disorders | ||||||||||||
| Arthralgia | 26 | < 1 | 31 | 0 | ||||||||
| Pain in extremity | 15 | 1 | 17 | < 1 | ||||||||
| Myalgia | 13 | < 1 | 13 | 0 | ||||||||
| General disorders and administrative site conditions | ||||||||||||
| Pyrexia | 57 | 7 | 33 | 2 | ||||||||
| Fatigue | 39 | 2 | 37 | 1 | ||||||||
| Chills | 31 | 0 | 17 | < 1 | ||||||||
| Asthenia | 12 | 1 | 14 | < 1 | ||||||||
| Oedema peripheral | 21 | < 1 | 9 | < 1 | ||||||||
| MEK115306 |
|---|
Dabrafenib 150 mg BID + MEKINIST 2 mg QD (N = 209) | Dabrafenib 150 mg BID + Placebo (N = 211) |
|---|
All Grades (%) | Grade 3 and Grade 4 (%) | All Grades (%) | Grade 3 and Grade 4 (%) | |
|---|---|---|---|---|
| Infections and infestations | ||||
| Nasopharyngitis | 12 | 0 | 10 | 0 |
| Urinary tract infection | 11 | 2 | 3 | < 1 |
| Vascular disorders | ||||
| Hypertension | 25 | 6 | 16 | 6 |
| Hypotension | 6 | 2 | 3 | < 1 |
| Haemorrhaged | 19 | 2 | 15 | 2 |
| Cardiac disorders | ||||
| Ejection fraction decreased | 6 | 1 | 3 | 2 |
| Blood and Lymphatic System Disorders | ||||
| Neutropenia | 10 | 3 | 2 | < 1 |
| Anaemia | 6 | 3 | 9 | 4 |
| Hepatobiliary Disorders | ||||
| ALT increased | 13 | 2 | 6 | < 1 |
| AST increased | 13 | 3 | 4 | < 1 |
a Includes squamous cell carcinoma of skin, squamous cell carcinoma in situ (Bowen’s disease) and keratoacanthoma
b Cases of cutaneous squamous cell carcinoma were required to be reported as Grade 3 per protocol c Includes hyperglycaemia, type 2 diabetes, diabetes mellitus, and blood glucose increase
d Includes intracranial and gastric haemorrhage
Less Common Clinical Trial Adverse Drug Reactions with MEKINIST in combination with dabrafenib
In addition to adverse reactions observed in MEKINIST monotherapy studies, other clinically relevant adverse reactions which are specific to or more common, or occur with greater severity when MEKINIST is used in combination with dabrafenib and reported in < 10% of patients or < 2% of patients with Grade 3 or 4 events treated with MEKINIST 2 mg once daily in combination with dabrafenib 150 mg twice daily in the safety population from the phase III clinical trial include:
Blood and Lymphatic System Disorders: Thrombocytopenia (4%), Leukopenia (4%)
Cardiac Disorders: Bradycardia (< 1%)
Eye Disorders: Vision blurred (3%), Visual impairment (2%), Periorbital oedema (< 1%), Uveitis (< 1%), Retinal detachment (< 1%)
Gastrointestinal Disorders: Dry mouth (8%), Stomatitis (1%), Pancreatitis (< 1%)
General Disorders: Mucosal inflammation (2%), Influenza-like illness (8%), Face oedema (2%)
Hepatobiliary Disorders: Blood alkaline phosphatase increased (8%), Gamma-glutamyltransferase increased (2%)
Immune: Hypersensitivity (< 1%)
Infections and Infestations: Cellulitis (3%), Folliculitis (6%), Paronychia (2%), Rash pustular (3%)
Metabolism and Nutrition Disorders: Hyponatremia (2%), Dehydration (1%), Hypophosphatemia (4%)
Musculoskeletal and Connective Tissue Disorders: Muscle spasms (9%), Blood creatine phosphokinase increased (3%)
Neoplasms Benign, Malignant and Unspecified (including cysts and polyps): Seborrheic keratosis (4%), Skin papilloma (2%), Acrochordon (skin tags) (1%), New primary melanoma (< 1%)
Renal: Renal failure (< 1%), Granulomatous nephritis/tubulointerstitial nephritis (< 1%)
Respiratory, Thoracic and Mediastinal Disorders: Dyspnoea (6%), Pneumonitis (< 1%)
Skin and Subcutaneous Tissue Disorders: Erythema (9%), Alopecia (7%), Night sweats (6%), Hyperhidrosis (7%), Hyperkeratosis (7%), Skin lesion (3%), Palmar-plantar erythrodysesthesia syndrome (hand-foot syndrome) (5%), Actinic keratosis (5%), Urticaria (3%), Panniculitis, including erythema nodosum (3%), Skin fissures (2%)
Vascular Disorders: Deep vein thrombosis and pulmonary embolism (3%), Lymphedema (<1%)
Table 4 Laboratory Abnormalities Changed from Baseline in the Phase III Study MEK115306
| MEK115306 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Preferred Term | Dabrafenib 150 mg BID + MEKINIST 2 mg QD (N = 209) | Dabrafenib 150 mg BID + Placebo (N = 211 ) | ||||||||
All Grades (%) | Grades 3 and 4 (%) | All Grades (%) | Grades 3 and 4 (%) | |||||||
| Hyperglycaemia | 65 | 6 | 57 | 4 | ||||||
| Hypophosphatemia | 38 | 4 | 35 | 7 | ||||||
| Hyponatremia | 24 | 6 | 14 | 3 | ||||||
| Hypoalbuminemia | 53 | 1 | 27 | 0 | ||||||
Post-market Adverse Drug Reactions
The following adverse reaction has been reported during post-approval use of MEKINIST. These include spontaneous case reports as well as serious adverse events from registries, investigator sponsored studies, clinical pharmacology studies and exploratory studies in unapproved indications.
Gastrointestinal: Colitis, gastrointestinal perforation
Musculoskeletal and connective tissue disorders: Rhabdomyolysis
DRUG INTERACTIONS
Overview
Formal clinical drug interaction studies with MEKINIST have not been conducted.
Trametinib is metabolized predominantly via deacetylation by hydrolytic enzymes (including carboxylesterases). In microsomes and hepatocytes, trametinib was metabolically stable with low intrinsic clearance. The NADPH-dependent (oxidative) metabolism of 14C-trametinib was very low in both human liver microsomes (~1%) and recombinant CYPs (~3%).
Drug-Drug Interactions
Effects of Trametinib on Drug Metabolizing Enzymes and Transporters: Based on in vitro studies, trametinib is not an inhibitor of CYP1A2, CYP2A6, CYP2B6, CYP2D6 and CYP3A4. The inhibition of CYP2C8, CYP2C9 and CYP2C19 in vitro occurred at concentrations that are at multiples of therapeutic concentrations of trametinib (9- to > 100 fold) and therefore drug interactions with sensitive CYP2C8, CYP2C9, and CYP2C19 substrates are not anticipated.
In vitro, trametinib was an inducer of CYP3A4 and an inhibitor of the transporters OAT1, OAT3, OCT2, MATE1, OATP1B1, OATP1B3, Pgp and BCRP. Based on the low dose and low clinical systemic exposure relative to the in vitro potency of inhibition or induction, trametinib treatment is unlikely to have an effect on the kinetics of substrates of CYP3A4 and the transporters.
Effects of Other Drugs on Trametinib: Trametinib metabolism by CYP enzymes is minor and trametinib is not a substrate for the transporters BCRP, OATP1B1, OATP1B3, OATP2B1, OCT1, MRP2 and MATE1. Trametinib is deacetylated via carboxylesterases. Drug-drug interactions via competition for carboxylesterases have been reported and could influence the exposure to trametinib. Trametinib is an in vitro substrate of the efflux transporter Pgp, but it is unlikely to be significantly affected by inhibition of this transporter given its high passive permeability and high bioavailability.
| Creatinine | 10 | < 1 | 7 | < 1 |
| Increased Alkaline Phosphatase | 50 | < 1 | 25 | < 1 |
Drugs that Prolong the PR Interval: MEKINIST may be associated with concentration-dependent prolongation of the PR interval (See WARNINGS AND PRECAUTIONS, Cardiovascular; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics, Cardiovascular Effects). Caution should therefore be exercised when MEKINIST is administered concomitantly with other drugs that prolong the PR interval, including, but not limited to, antiarrhythmics, beta blockers, non-dihydropyridine calcium channel blockers, digitalis glycosides, sphingosine-1 phosphate receptor modulators, and some HIV protease inhibitors.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Recommended Dose
When using MEKINIST in combination with dabrafenib, please refer to the TAFINLAR Product Monograph for full dosing instructions.
The recommended dose regimens of MEKINIST are:
Monotherapy: 2 mg given orally once daily with a full glass of water.
Combination with dabrafenib: 2 mg given orally once daily with 150 mg (two 75 mg capsules) of dabrafenib given orally twice daily (corresponding to a total daily dose of 300 mg).
MEKINIST alone or in combination with dabrafenib should be taken without food and with a full glass of water, at least one hour before or two hours after a meal (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
When MEKINIST and dabrafenib are taken in combination, the once-daily dose of MEKINIST should be taken at the same time each day with either the morning dose or the evening dose of dabrafenib.
It is recommended that patients continue treatment until disease progression or the development of unacceptable toxicity.
Dose modifications
The management of adverse reactions may require treatment interruption, dose reduction, or treatment discontinuation (see Table 5). Discontinue MEKINIST treatment permanently if a dose reduction below 1 mg once daily is required.
Table 5 Recommended Dose Modifications for MEKINIST Monotherapy and for MEKINIST and Dabrafenib Combination Therapy
| Adverse Reactiona | MEKINIST | Dabrafenib (when used in combination) |
|---|---|---|
| Cutaneous | ||
|
|
|
|
|
|
|
|
|
| Cardiac | ||
|
|
|
|
|
|
|
|
|
|
|
|
| Adverse Reactiona | MEKINIST | Dabrafenib (when used in combination) |
|---|---|---|
| Febrile Drug Reaction | ||
|
|
|
|
|
|
| Ocular | ||
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
|
| Pulmonary | ||
|
|
|
| Adverse Reactiona | MEKINIST | Dabrafenib (when used in combination) |
|---|---|---|
| Other | ||
|
|
|
|
|
|
|
|
|
a The intensity of clinical adverse events graded by the Common Terminology Criteria for Adverse Events v4.0 (CTC-AE)
Table 6 Recommended Dose Level Reductions for MEKINIST and for Dabrafenib When Used in Combination Therapy
| Dose Level Reductions for MEKINIST | |
|---|---|
| First reduction | 1.5 mg once daily |
| Second reduction | 1 mg once daily |
| If unable to tolerate 1 mg once daily | Discontinue MEKINIST |
| Dose Level Reductions for Dabrafenib When Used in Combination Therapy with MEKINIST | |
| First reduction | 100 mg twice daily (2x 50 mg twice daily) |
| Second reduction | 75 mg twice daily (1x 75 mg twice daily) |
| Third reduction | 50 mg twice daily (1x 50 mg twice daily) |
| If unable to tolerate 50 mg twice daily | Discontinue dabrafenib |
Dosing Considerations
Paediatrics: MEKINIST is not recommended in this population (see INDICATIONS AND CLINICAL USE).
Geriatrics: No dose adjustment is required in patients over 65 years (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Renal impairment: No dosage adjustment is required in patients with mild or moderate renal impairment. There are no clinical data with MEKINIST in patients with severe renal impairment; the need for starting dose adjustment is unknown (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Hepatic impairment: No dosage adjustment is required in patients with mild hepatic impairment. There are no clinical data in patients with moderate or severe hepatic impairment; the need for starting dose adjustment is unknown (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics).
Missed Dose
If a dose is missed, MEKINIST should not be taken if it is less than 12 hours until the next dose.
OVERDOSAGE
There were no cases of MEKINIST dosed above 4 mg once daily reported from the clinical trials. Doses of up to 4 mg orally once daily or loading doses of up to 10 mg on two consecutive days, have been administered to limited numbers of patients in a clinical study. Doses above the recommended 2 mg orally once daily regimen were associated with increased toxicities including retinal pigment epithelial detachment.
There is no specific antidote for overdosage of MEKINIST or dabrafenib, and treatment of overdose should consist of general supportive measures. Haemodialysis is not expected to enhance the elimination as trametinib is highly bound to plasma proteins.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
MEKINIST monotherapy: Trametinib is small molecule inhibitor of mitogen-activated extracellular signal regulated kinase 1 and 2 (MEK1 and MEK2). MEK1 and MEK2 are components of the mitogen-activated protein kinase (MAPK) pathway. The RAS effector pathway RAF-MEK-ERK, is an essential, shared element of mitogenic signalling involving tyrosine kinase receptors, leading to a wide range of cellular responses, including growth, differentiation, inflammation, and apoptosis. Mutant BRAF and RAS proteins subsequently signal through MEK1 and MEK2 leading to consecutive activation of the MAPK pathway and stimulation of cell growth. BRAF mutations have been identified at a high frequency in specific cancers, including approximately 50% of melanoma. Trametinib is a reversible, and selective allosteric inhibitor of MEK1 and MEK2 activation and kinase activity. The IC50 values for the unphosphorylated form of MEK1 and MEK2 are 0.7 nM and 0.9 nM, respectively. The IC50 values for the phosphorylated form of MEK1 and MEK2 are 13.2 nM and 10.7 nM, respectively. Trametinib inhibits growth of BRAF V600 mutant melanoma cell lines and demonstrates anti-tumour effects in BRAF V600 mutant melanoma xenograft models.
MEKINIST in combination with dabrafenib: Dabrafenib is a small molecule inhibitor of RAF kinases, including BRAF. Oncogenic mutations in BRAF lead to constitutive activation of the MAPK pathway (including RAS/RAF/MEK/ERK) and may promote tumour cell growth. Dabrafenib and trametinib provide concomitant inhibition of the pathway at the level of the RAF and MEK kinases, respectively. The combination of dabrafenib with trametinib was synergistic in BRAF V600 mutation-positive melanoma cell lines and delayed the emergence of resistance in BRAF V600 mutation-positive melanoma xenografts.
Pharmacodynamics
In patients (n = 5-6) with BRAF mutant melanoma, administration of trametinib (1 mg or 2 mg once daily) resulted in dose-dependent changes in biomarkers including inhibition of phosphorylated ERK, inhibition of Ki67 (a marker of cell proliferation), and increases in p27 (a marker of apoptosis).
Cardiovascular Effects: Initially, the effect of MEKINIST on ECG intervals was assessed as part of the first time in human study to determine the relationship between the manually read ECG interval parameters and plasma concentrations of trametinib using a nonlinear mixed effect model. Data were available from 50 patients with a total of 498 matched ECG interval and plasma concentration values collected on day 1 and day 15. The slope (95% CI) of the exposure-relationship with PR was positive (0.371 [0.223, 0.519] msec/ng/mL) indicating an increase in PR interval with increasing trametinib concentrations. A median increase of 8.3 msec in the PR interval is predicted at the geometric mean Cmax value of 22.2 ng/mL, with an upper 95th percentile limit of 10.9 msec. At the maximum Cmax value of 32.9 ng/mL, a median increase of 12.2 msec of the PR interval is predicted, with an upper 95th percentile limit of 16.2 msec. The slopes of the relationship between trametinib concentration and QTc, QRS, and heart rate were not statistically significant.
In a modified QT study in patients with solid tumours, 35 patients received placebo on study day 1 followed by a 2 mg once daily dose of MEKINIST on study days 2 to 14. On study day 15, 27 patients received a single dose of 3 mg MEKINIST (supratherapeutic dose) and the other 3 patients received 2 mg MEKINIST. The study showed no potential for MEKINIST to alter the QTcF interval after repeat dose administration of 2 mg MEKINIST, including at the supratherapeutic dose of 3 mg on day 15. Analyses of Holter-derived ECG data showed a statistically significant prolongation of the PR interval and decrease in heart rate. The worst-case on therapy mean increase in PR interval from baseline was 25.3 msec with MEKINIST vs. 6.0 msec with placebo. The worst-case on therapy mean decrease in heart rate from baseline was 11.5 bpm following treatment with MEKINIST vs. 3.0 bpm following placebo treatment.
The 24-hr Ambulatory Blood Pressure Monitoring (ABPM) results showed an overall increase from baseline in blood pressure. The mean worst post-baseline diastolic blood pressure (DBP) was 81.4 mmHg up from mean baseline DBP of 71.2 mmHg. The mean worst post-baseline systolic blood pressure (SBP) was 131.7 mmHg up from mean baseline SBP of 120.1 mmHg following treatment with MEKINIST. Post-treatment LVEF measured on Day 16 showed decreased LVEF from baseline in 20 (57%) patients, including 6 (17%) patients with LVEF decreased by 10 - 19 % and no patient had a LVEF decrease of > 20%. No clinically significant changes from baseline in other ECG parameters or LVEF results were identified.
Pharmacokinetics
The pharmacokinetics of trametinib were characterized following single- and repeat-oral administration and were adequately described by a 2-compartment model with dual sequential first-order absorption in patients.
Absorption: Trametinib is absorbed orally with median time to achieve peak concentrations of 1.5 hours post-dose (see Table 7). The mean absolute bioavailability of a single 2 mg tablet dose is 72% relative to an intravenous (IV) microdose. The increase in exposure (Cmax and AUC) was dose-proportional following repeat dosing. Following administration of 2 mg daily, geometric mean Cmax, AUC(0-τ) and predose concentration were 22.2 ng/mL, 370 ng*hr/mL (see Table 7) and 12.1 ng/mL, respectively with a low peak:trough ratio (1.8). Inter-subject variability was low (< 28%).
Administration of a single dose of trametinib with a high-fat, high-calorie meal resulted in a 70% and 24% decrease in Cmax and AUC(0-168h), respectively compared to fasted conditions (see DOSAGE AND ADMINISTRATION).
Distribution: Binding of trametinib to human plasma proteins is 97.4%. Trametinib has a volume of distribution of 1060 L determined following administration of a 5μg IV microdose.
Metabolism: In vitro studies demonstrated that trametinib is metabolized predominantly via deacetylation alone or with mono-oxygenation or in combination with glucuronidation biotransformation pathways. Following a single dose (2 mg) of [14C]-trametinib, about 50% of circulating radioactivity is represented as parent. The deacetylation is mediated by carboxyl-esterases (i.e. carboxylesterase 1b/c and 2) and may also be mediated by other hydrolytic enzymes. The deacetylated metabolite (M5) has been shown to be active based on in vitro studies. However, based on its exposure (~10%) relative to parent, it is unlikely to contribute to the clinical activity of trametinib.
Elimination: Trametinib accumulates with repeat daily dosing with a mean accumulation ratio of 6.0 following a 2 mg once daily dose. Mean terminal half-life is 127 hours (5.3 days) after single dose administration in a study with a 7 day sampling period (see Table 7), although a longer terminal phase (11 days) has been observed with a longer sampling period (10 days), presumably due to elimination from deep compartments. Steady-state was estimated to be achieved by Day 15-20 following administration of 2 mg once daily. The mean accumulation ratio of patients receiving continuous dosing of 2 mg once daily was 6.5 (95% CI: 5.5, 7.6) on Day 15 over Day 1. Trametinib plasma IV clearance is 3.21 L/hr.
Total dose recovery is low after a 10-day collection period (< 50%) following administration of a single oral dose of radiolabelled trametinib as a solution, due to the long half-life. Faecal excretion is the major route of elimination after [14C]-trametinib oral dose, accounting for > 80% of excreted radioactivity recovered while urinary excretion accounted for < 19% of excreted radioactivity recovered. Less than 0.1% of the excreted dose was recovered as parent in urine.
Combination with dabrafenib: Co-administration of MEKINIST 2 mg once daily and dabrafenib 150 mg twice daily resulted in a 16% increase in dabrafenib Cmax and 23 % increase in AUC at steady-state. A small decrease in trametinib bioavailability was also observed with the combination therapy, corresponding to a decrease in the trametinib AUC of 12 % (estimated by Population PK analysis).
Table 7 Summary of Trametinib’s Pharmacokinetic Parameters in Patients with Cancer
| Study | Tmax (h) Median (Min, Max) | Cmax (ng/mL) Geometric Mean (95% CI) | AUCa (ng*hr/mL) Geometric Mean (95% CI) | t1/2 (hr) Geometric Mean (95% CI) |
|---|---|---|---|---|
Single 2.0 mg Dose b (n = 22) | 1.5 (1.0, 4.0) | 9.1 (7.2, 11.6) | 415 (359, 479) | 127 (113, 143) |
Repeat Dose (Day 15) c, d (n = 13) | 1.8 (1.0, 3.0) | 22.2 (18.7, 26.4) | 370 (320, 427) | NA |
Abbreviations: CI, confidence interval; NA, not applicable
a AUC refers to AUC(0-∞) for single dose and AUC(0-τ) for repeat dose
b Data is from the Phase I food effect study (fasting conditions)
c 2.0 mg once daily; includes patients who received loading dose regimens
d Data is from the Phase I first time in human study
Special Populations and Conditions
Paediatrics: No studies have been conducted to investigate the pharmacokinetics of trametinib in paediatric patients.
Geriatrics: Based on a population pharmacokinetics analysis, age had no relevant clinical effect on trametinib pharmacokinetics.
Gender/Weight: Based on a population pharmacokinetic analysis, sex and body weight were found to influence trametinib oral clearance. At a median weight of 79 kg, female patients had 21% lower trametinib clearance (4.9 vs. 6.2 L/h) and 25% higher AUC (402 vs. 322 ng•h.mL) than males.
Race/Ethnicity: There are insufficient data to evaluate potential differences in the pharmacokinetics of trametinib by race or ethnicity.
Hepatic Insufficiency: A clinical pharmacokinetic study has not been conducted in patients with hepatic impairment. Based on a population pharmacokinetic analysis, trametinib oral clearance to trametinib was not significantly different in patients with mild hepatic impairment (defined by total bilirubin ≤ ULN and AST > ULN, or total bilirubin > 1.0-1.5x ULN with any
AST level) relative to those with normal hepatic function. No data are available in patients with moderate or severe hepatic impairment (see DOSAGE AND ADMINISTRATION).
Renal Insufficiency: A clinical pharmacokinetic study in patients with renal impairment has not been conducted. The pharmacokinetics of trametinib were characterized in 223 patients enrolled in clinical trials with trametinib who had mild renal impairment and 35 patients with moderate renal impairment. Based on a population pharmacokinetic analysis mild (60 ≤ GFR < 90 mL/min/1.73m2) and moderate renal impairment (30 ≤ GFR < 60 mL/min/1.73m2) had no effect on trametinib oral clearance (< 6% decrease for either renal impaired group compared to normal renal function). No data are available in patients with severe renal impairment (see DOSAGE AND ADMINISTRATION).
STORAGE AND STABILITY
Store refrigerated, 2-8 °C. Protect from light and moisture. Do not remove desiccant. Dispense in original bottle.
Once opened, the bottle may be stored for 30 days at not more than 30°C.
DOSAGE FORMS, COMPOSITION AND PACKAGING
MEKINIST 0.5 mg tablets are yellow, modified oval, biconvex, film-coated tablets with ‘GS’ debossed on one face and ‘TFC’ on the opposing face. Available in bottles of 30 tablets. Bottles contain a silica gel desiccant.
MEKINIST 1.0 mg tablets of are white, round, biconvex, film-coated tablets with ‘GS’ debossed on one face and ‘LHE’ on the opposing face. Available in bottles of 30 tablets. Bottles contain a silica gel desiccant.
MEKINIST 2.0 mg tablets are pink, round, biconvex, film-coated tablets with ‘GS’ debossed on one face and ‘HMJ’ on the opposing face. Available in bottles of 30 tablets. Bottles contain a silica gel desiccant.
MEKINIST tablets contain 0.5, 1.0, or 2.0 mg of trametinib and the following nonmedicinal ingredients: croscarmellose sodium, hypromellose, magnesium stearate (vegetable source), mannitol, microcrystalline cellulose, silicon dioxide (colloidal), and sodium lauryl sulphate. The tablet coating contains: hypromellose polyethylene glycol, and titanium dioxide. In addition, the 0.5 mg tablets contain iron oxide yellow and the 2.0 mg tablets contain iron oxide red and polysorbate 80.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: trametinib dimethyl sulfoxide
Chemical name: equimolecular combination of N-(3-{3-cyclopropyl-5-[(2-fluoro-4-iodophenyl)amino]-6,8-dimethyl-2,4,7-trioxo-3,4,6,7-tetrahydropyrido[4,3-d]pyrimidin-1(2H)-yl}phenyl)acetamide with (methylsulfinyl)methane
Molecular formula: C26H23FIN5O4.C2H6OS
Molecular mass: 693.53 (DMSO solvate of parent)
615.39 (non-solvated parent)
Structural formula:
S O CH3 H3C N N N NH O CH3 O NH O H3C O F I H3C .
Tablets are formulated to contain trametinib DMSO solvate equivalent to the labelled amount of trametinib as the unsolvated parent.
Physicochemical properties: Trametinib dimethyl sulfoxide is a white to almost white solid. Trametinib dimethyl sulfoxide has low solubility (0.2 − 0.3 μg/mL) in the pH range of 2 to 8 in aqueous media at 37°C. Trametinib dimethyl sulfoxide is soluble in organic solvents (3.8 mg/mL in dimethyl sulfoxide (DMSO)) at 20°C.
pKa (basic) = 0.25
CLINICAL TRIALS
The efficacy and safety of MEKINIST monotherapy were evaluated in a Phase III randomized, multi-centre, international, open label study comparing MEKINIST to chemotherapy in patients with unresectable or metastatic BRAF V600E or V600K mutation-positive cutaneous melanoma.
The efficacy and safety of MEKINIST in combination with dabrafenib in the treatment of patients with BRAF V600E/K mutation positive unresectable or metastatic melanoma has been evaluated in a phase III multi-centre, international clinical study MEK115306.
Screening for the two studies included central laboratory testing of BRAF mutation (V600E or V600K) using a BRAF mutation assay conducted on the most recent tumour sample available from either a primary tumour or a tumour from a metastatic site.
MEKINIST Monotherapy
Trial Design
Patients may have received up to one prior chemotherapy in unresectable or metastatic setting. Patients previously treated with a BRAF or MEK inhibitor were excluded. Patients were randomized 2:1 to receive MEKINIST 2 mg once daily or chemotherapy (dacarbazine 1000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks). Treatment for all patients continued until disease progression, death or withdrawal. Patients in the chemotherapy arm were allowed to cross-over to MEKINIST therapy after independent confirmation of progression.
The Intent to Treat (ITT) population included all randomized patients with BRAF V600E, or V600K mutation-positive unresectable or metastatic melanoma with or without a prior history of brain metastases.
The primary efficacy population included patients with unresectable or metastatic BRAF V600E mutation-positive cutaneous melanoma without a prior history of brain metastases. The primary efficacy endpoint was progression-free survival (PFS). The secondary endpoints included PFS in the ITT population as well as overall survival (OS), overall response rate (ORR), and duration of response (DoR) in the primary efficacy and ITT populations.
Study demographics and Baseline Characteristics
Study demographics and baseline characteristics were balanced between treatment groups in the primary efficacy population and the ITT population (see Table 8).
Table 8 Summary of patient demographics and baseline characteristics in pivotal clinical trial of MEKINIST (ITT Population)
| MEKINIST (N = 214) | Chemotherapya (N = 108) | Total (N = 322) | ||||||||||
Age (years) Median (Min. – Max.) | 54.5 (23-85) | 54.0 (21-77) | 54.0 (21 -85) | |||||||||
Age Category, n (%) < 65 years | 165 (77) | 86 (80) | 251 (78) | |||||||||
| ≥ 65 years | 49 (23) | 22 (20) | 71 (22) | |||||||||
Sex, n (%) Male | 120 (56) | 53 (49) | 173 (54) | |||||||||
| Female | 94 (44) | 55 (51) | 149 (46) | |||||||||
Baseline lactate dehydrogenase, n (%) ≤ ULN | 134 (63) | 66 (61) | 200 (62) | |||||||||
| > ULN | 77 (36) | 42 (39) | 119 (37) | |||||||||
| Unknown | 3 (1) | 0 | 3 (< 1) | |||||||||
Any prior therapy, n (%) No | 14 (7) | 7 (6) | 31 (10) | |||||||||
| Yes | 200 (93) | 101 (94) | 291 (90) | |||||||||
Prior chemotherapy in unresectable or metastatic setting, n (%) No | 143 (67) | 70 (65) | 213 (66) | |||||||||
| Yes | 71 (33) | 38 (35) | 109 (34) | |||||||||
Prior immunotherapy, n (%)b No | 146 (68) | 78 (72) | 224 (70) | |||||||||
| Yes | 68 (32) | 30 (28) | 98 (30) | |||||||||
Prior biologic therapy, n (%) No | 198 (93) | 95 (88) | 293 (91) | |||||||||
| Yes | 16 (7) | 13 (12) | 29 (9) | |||||||||
ECOG PS at Baseline, n (%) ECOG 0 | 136 (64) | 69 (64) | 205 (64) | |||||||||
| ECOG 1 | 78 (36) | 39 (36) | 117 (36) | |||||||||
Stage at screening, n (%) IIIC, IV M1a, or IV M1b | 69 (32) | 45 (42) | 114 (35) | |||||||||
| IV M1c | 144 (67) | 63 (58) | 207 (64) | |||||||||
| Unknown | 1 (< 1) | 0 | 1 (< 1) | |||||||||
Number of disease sites at Baseline, n (%) ≥ 3 sites | 123 (57) | 56 (52) | 179 (56) | |||||||||
| < 3 sites | 91 (43) | 52 (48) | 143 (44) | |||||||||
BRAF mutation status, n (%) V600E | 184 (86) | 97 (90) | 281 (87) | |||||||||
| V600K | 29 (14) | 11 (10) | 40 (12) | |||||||||
| V600E/V600K | 1 (< 1) | 0 | 1 (< 1) | |||||||||
History of brain metastases, n (%) No | 205 (96) | 106 (98) | 311 (97) | |||||||||
| Yes | 9 (4) | 2 (2) | 11 (3) | |||||||||
| Abbreviations: ECOG = Eastern Cooperative Oncology Group; PS = performance status; ULN = upper limit of normal | ||||||||||||
a Chemotherapy included patients on dacarbazine (DTIC) 1,000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks.
b The majority of patients received adjuvant interferon. Patients were not permitted ipilimumab in the unresectable or metastatic setting.
Study results
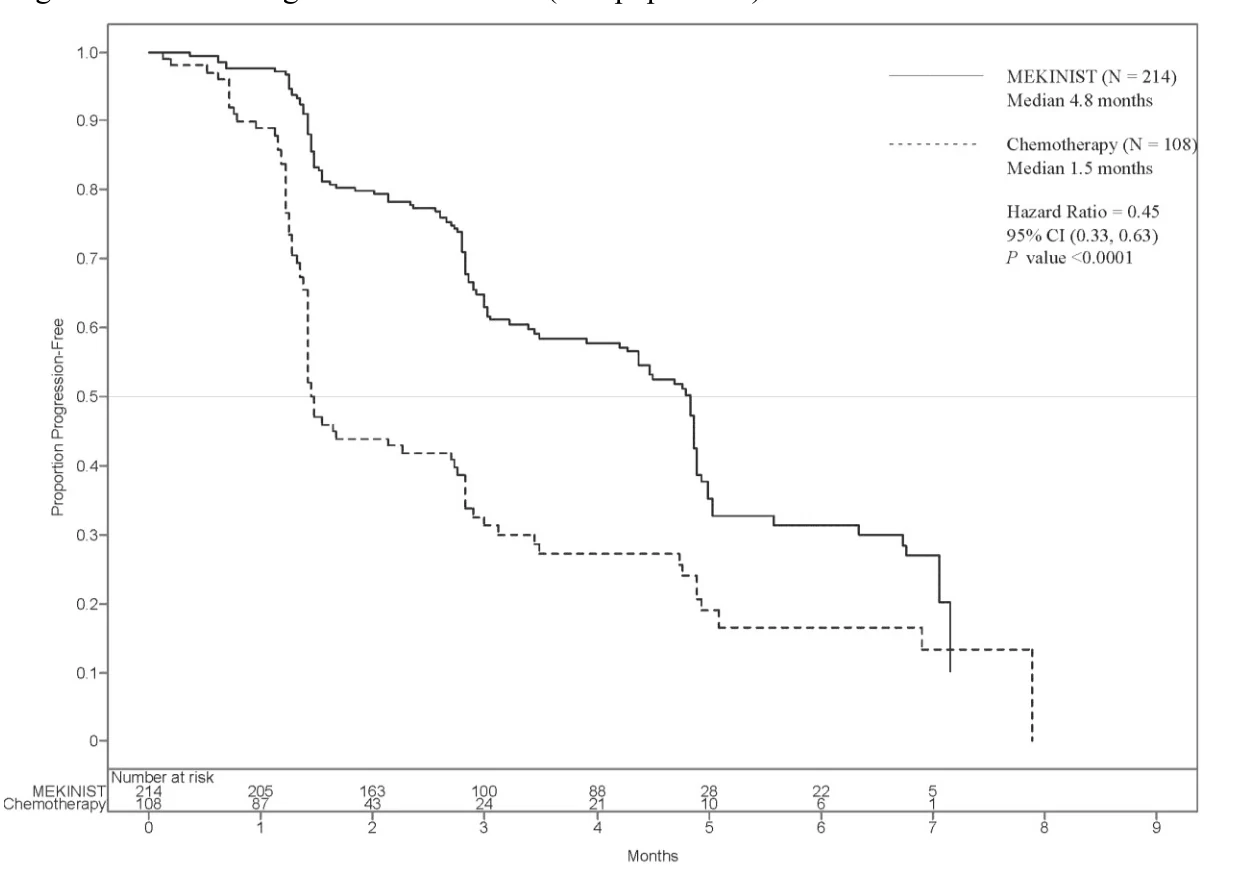
In the primary efficacy population, MEKINIST demonstrated a statistically significant improvement in investigator-assessed PFS (HR = 0.44; [95% CI: 0.31, 0.64], N = 273, P < 0.0001) which represents a 56% reduction in the risk of tumour progression or death for patients treated with MEKINIST compared with those treated with chemotherapy. Comparable PFS results were observed in the ITT population (HR = 0.45; [95% CI: 0.33, 0.63], N = 322, P < 0.0001; see Table 9 and Figure 1). Similar PFS results were seen based on an Independent Review Committee evaluation. At the time of the primary analysis, the median follow-up were 4.9 months for patients treated with MEKINIST and 4.8 months for those treated with chemotherapy.
At the time of primary analysis, OS data were not mature with 20% events reported in the ITT population and 51 (47%) patients in the chemotherapy arm had crossed over to receive MEKINIST after a confirmed disease progression. An updated analysis was conducted with 63% events. See Table 9 for results.
The investigator-assessed best confirmed ORR was 22% in the MEKINIST arm compared to 8% in the chemotherapy arm (see Table 9). However, in the MEKINIST treatment arm, the confirmed ORR was 10% in patients with BRAF V600K mutation compared to 24% in those with BRAF V600E mutation.
Treatment effect with MEKINIST was observed across all subgroups. However, in patients with BRAF V600K mutation, the investigator-assessed best confirmed ORR was 10% in the MEKINIST arm (n = 29) compare to 18% in the chemotherapy arm (n = 11).
Table 9 Investigator-Assessed Efficacy Results
| Endpoint | MEKINIST | Chemotherapya | |||||||
| Primary Efficacy Population | (N = 178) | (N = 95) | |||||||
| PFS | |||||||||
Number of events, n (%) Median PFS (months) (95% CI) | 96 (54) 4.8 (3.5, 4.9) | 68 (72) 1.4 (1.4, 2.7) | |||||||
Hazard Ratiob (95% CI) P valueb | 0.44 (0.31, 0.64) < 0.0001 | ||||||||
| ITT Population | (N = 214) | (N = 108) | |||||||
| PFS | |||||||||
Number of events, n (%) Median PFS (months) (95% CI) | 118 (55) 4.8 (4.3, 4.9) | 77 (71) 1.5 (1.4, 2.7) | |||||||
Hazard Ratiob (95% CI) P valueb | 0.45 (0.33, 0.63) < 0.0001 | ||||||||
| OS | |||||||||
| Primary analysis: OSc | |||||||||
| Died, n (%) | 35 (16) | 29 (27) | |||||||
Hazard Ratiob (95% CI) P valueb | 0.54 (0.32, 0.92) 0.014 | ||||||||
| OS censored at the time of crossover | |||||||||
| Died, n (%) | 35 (16) | 15 (14) | |||||||
Hazard Ratiob (95% CI) P valueb | 0.59 (0.30, 1.18) 0.073 | ||||||||
| Updated OS | |||||||||
| Died, n (%) | 137 (64) | 67 (62) | |||||||
Hazard Ratiob (95% CI) P value | 0.78 (0.57, 1.06) 0.091 | ||||||||
Median overall survival (months) (95% CI) | 15.6 (5.9, 9.2) | 11.3 (7.2, 14.8) | |||||||
Overall Response Best Response, n (%) CR PR ORR (CR+PR), (%) (95% CI) | 4 (2)d 43 (20) 22 (16.6, 28.1) | 0 9 (8) 8 (3.9, 15.2) | |||||||
| Duration of Response | (N = 47) | (N = 9) | |||||||
Median, months (95% CI) | 5.5 (4.1, 5.9) | NR(5.0, NR) | |||||||
ITT = Intent to treat; PFS = Progression-free survival; CI = Confidence interval; CR = Complete response; ORR = Overall response rate; PR = Partial response; NR = Not reached
a Chemotherapy included patients on dacarbazine (DTIC) 1000 mg/m2 every 3 weeks or paclitaxel 175 mg/m2 every 3 weeks.
b Hazard ratios are estimated using a Pike estimator. A hazard ratio < 1 indicates a lower risk with this treatment. Hazard Ratio and p-value from stratified log-rank test are adjusted for prior chemotherapy for unresectable or metastatic disease and baseline LDH.
c Fifty-one (47%) patients crossed over to receive MEKINIST following disease progression.
d The four patients were reported as 2 PR, 1 stable disease and 1 ‘not evaluable’ by the Independent Review Committee.
Figure 1 Investigator-Assessed PFS (ITT population)
Lack of efficacy in patients previously treated with BRAF inhibitors
In a single arm Phase II study, efficacy of MEKINIST monotherapy was evaluated in 40 patients with BRAF V600E or V600K mutation positive unresectable or metastatic cutaneous melanoma who had received prior treatment with a BRAF inhibitor. At baseline, the median age was 58 (range: 23-76) years, 63% were male, 100% were Caucasian, 98% had ECOG performance status of 0 or 1. No patient achieved a confirmed complete or partial response after treatment with MEKINIST at 2 mg once daily (see INDICATIONS AND CLINICAL USE and WARNINGS AND PRECAUTIONS, General).
MEKINIST in Combination with Dabrafenib
Phase III Pivotal Study MEK115306
Trial design
MEK115306 was a phase III, randomized, double-blind study comparing the combination of MEKINIST and dabrafenib to dabrafenib and placebo as first-line therapy for subjects with unresectable (Stage IIIC) or metastatic (Stage IV) BRAF V600E/K mutation-positive cutaneous melanoma.
Patients were not allowed to have prior systemic anti-cancer treatment in the advanced or metastatic setting, although prior systemic treatment in the adjuvant setting was allowed. The primary endpoint was investigator-assessed progression-free survival (PFS), which was to be assessed after 193 events (progression or death) were observed (Primary PFS Analysis); upon formal declaration of a data cut based on the 193 known events, an additional 18 progressions were discovered during the data retrieval and cleaning process. Secondary endpoints ORR and duration of response were reported at the time of this primary PFS analysis. The secondary endpoint OS analysis was to be performed when 220 events (death) had occurred (Final OS Analysis).
Patients were stratified by lactate dehydrogenase (LDH) level (above the upper limit of normal [ULN] versus ≤ ULN) and BRAF mutation (V600E versus V600K). Crossover was not allowed.
MEKINIST and dabrafenib were administered at their recommended monotherapy doses of 2 mg once daily and 150 mg twice daily, respectively.
Study Demographics and Baseline Characteristics
Study demographics were balanced between treatment arms. Baseline disease characteristics and prognostic factors were well balanced between the treatment arms, with the exception of the occurrence of visceral disease, which was higher in the combination therapy arm compared with the dabrafenib monotherapy arm (see Table 10).
Table 10 Demographic and Baseline Characteristics, Study MEK115306
MEKINIST + Dabrafenib (N = 211) | Placebo + Dabrafenib (N = 212) | |
| Age (years) | ||
| Median (Min, Max) | 55.1 (22, 89) | 56.5 (22, 86) |
| Age Group, n (%) | ||
| < 65 | 154 (73) | 151 (71) |
| ≥ 65 | 57 (27) | 61 (29) |
| Sex, n (%) | ||
| Female | 100 (47) | 98 (46) |
| Male | 111 (53) | 114 (54) |
| ECOG PS at Baseline, n (%) | ||
| 0 | 155 (73) | 150 (71) |
| 1 | 55 (26) | 61 (29) |
| Baseline LDH, n (%) | ||
| ≤ ULN | 133 (63) | 140 (66) |
| > ULN | 77 (36) | 71 (33) |
| Visceral Disease at Baseline, n (%) | ||
| Yes | 165 (78) | 145 (68) |
| No | 46 (22) | 66 (31) |
| BRAF Mutation Status, n (%) | ||
| V600E | 179 (85) | 181 (85) |
| V600Ka | 32 (15) | 30 (14) |
| (M stage) at Screening, n (%) | ||
| M0 | 5 (2) | 10 (5) |
| M1a | 19 (9) | 31 (15) |
| M1b | 45 (21) | 32 (15) |
| M1c | 142 (67) | 138 (65) |
a One subject was both BRAF V600E and BRAF V600K mutation positive and is included in the V600K subset in this display
Study results
Treatment with the combination therapy resulted in a statistically significant improvement in investigator-assessed PFS compared with dabrafenib monotherapy treatment (HR 0.75; 95% CI: 0.57, 0.99; p = 0.035). This represents a 25% reduction in risk of tumour progression or death in the combination therapy arm compared with dabrafenib monotherapy. Median PFS for the combination therapy arm was 9.3 months compared with 8.8 months for the dabrafenib monotherapy arm. Independent reviewer assessed PFS results were not statistically significant (HR 0.78; 95% CI: 0.59, 1.04).
The secondary endpoint of investigator assessed best confirmed ORR favoured the combination therapy over dabrafenib monotherapy. See Table 11 for details.
Efficacy results are presented in Table 11 and Figure 2 and Figure 3.
Table 11 Efficacy Results, Study MEK115306
*Primary data cut: 26 August 2013, Final OS data cut: 12 January 2015
CI = Confidence Interval; HR = Hazard Ratio; CR = Complete Response; ORR = Overall Response Rate; PR = Partial Response; NR = Not Reached
- a. Hazard ratio and log-rank p-value are adjusted for randomized strata: baseline LDH and BRAF mutation status
- b. The stopping boundary for overall survival (one-sided alpha) for this interim analysis is based on the available information (95 events), and is 0.00014. Confidence interval is based on the allocated alpha. The results were not statistically significant
- c. 95% CI
- d. Includes only patients with measurable disease at baseline
| Primary Analysis* | Updated Analysis* | |||||||||||||||||||||
| TAFINLAR + Trametinib | TAFINLAR + Placebo | TAFINLAR + Trametinib | TAFINLAR + Placebo | |||||||||||||||||||
| Primary endpoint | ||||||||||||||||||||||
| PFS | (N = 211) | (N = 212) | (N = 211) | (N = 212) | ||||||||||||||||||
| Median, months (95% CI) | 9.3 (7.7, 11.1) | 8.8 (5.9, 10.9) | 11.0 (8.0, 13.9) | 8.8 (5.9, 9.3) | ||||||||||||||||||
| HR (95% CI) and log-rank p-valuea | 0.75 (0.57, 0.99) p = 0.035 | 0.67 (0.53, 0.84) p < 0.001 | ||||||||||||||||||||
| Secondary endpoints | ||||||||||||||||||||||
| ORRd | N = 210 | N = 210 | N = 210 | N = 210 | ||||||||||||||||||
| CR, n (%) | 22 (10) | 18 (9) | 33 (16) | 28 (13) | ||||||||||||||||||
| PR, n (%) | 118 (56) | 90 (43) | 111 (53) | 84 (40) | ||||||||||||||||||
| ORR (CR+PR), n (%) | 140 (67) | 108 (51) | 144 (69) | 112 (53) | ||||||||||||||||||
| (95% CI) | (59.9, 73.0) | (44.5, 58.4) | (61.8, 74.8) | (46.3, 60.2) | ||||||||||||||||||
| Duration of Response | N = 140 | N = 109 | N = 144 | N = 113 | ||||||||||||||||||
| Median, months (95% CI) | 9.2 (7.4, NR) | 10.2 (7.5, NR) | 12.9 (9.4, 19.5) | 10.6 (9.1, 13.8) | ||||||||||||||||||
| Interim Analysis | Final Analysis | |||||||||||||||||||||
| OS | (N = 211) | (N = 212) | (N = 211) | (N = 212) | ||||||||||||||||||
| Died (%) | 40 (19) | 55 (26) | 99 (47) | 123 (58) | ||||||||||||||||||
HR (CI) and log-rank p-valuea | 0.63 (0.30, 1.32)b | 0.71 (0.55, 0.92)c p = 0.011 | ||||||||||||||||||||
| Median, months (95% CI) | NR | 25.1 (19.2, NR) | 18.7 (15.2, 23.7) | |||||||||||||||||||
Figure 2 Kaplan-Meier Curves for PFS Primary Analysis (ITT Population), Study MEK115306
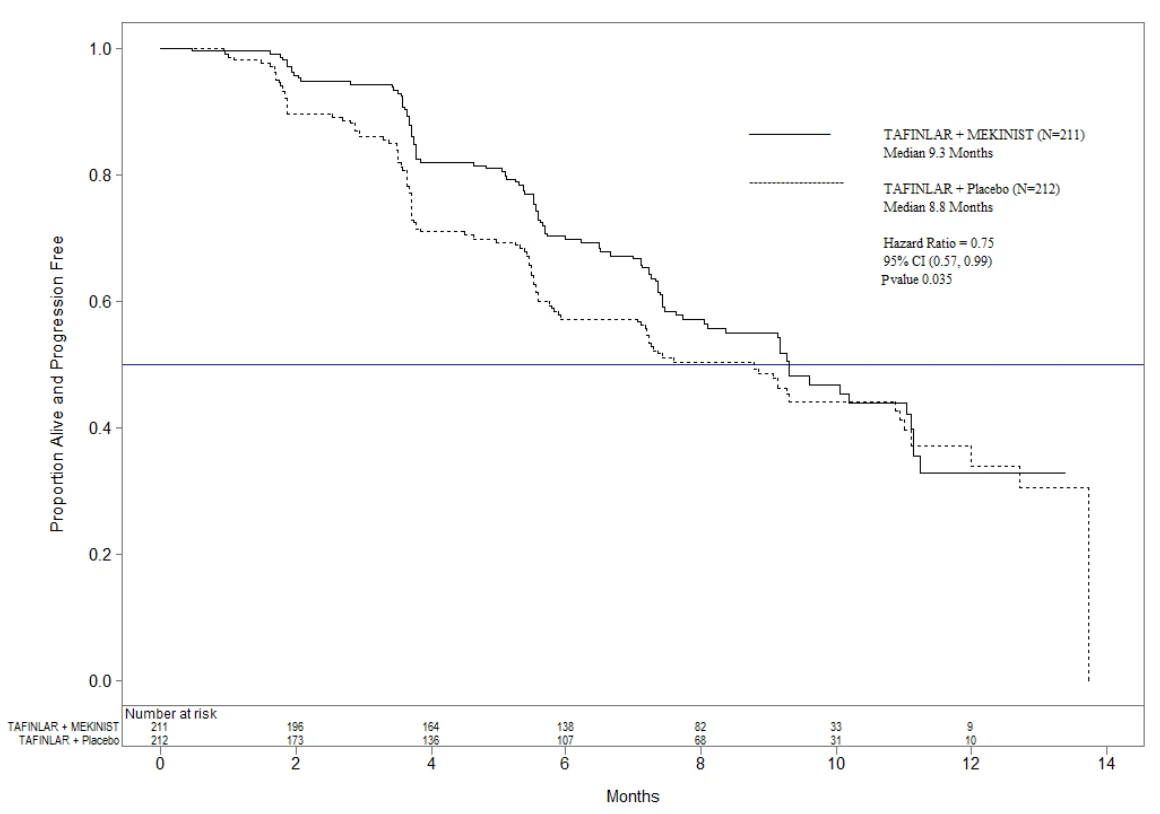
Figure 3 Kaplan-Meier Curves for Final OS (ITT population), Study MEK115306
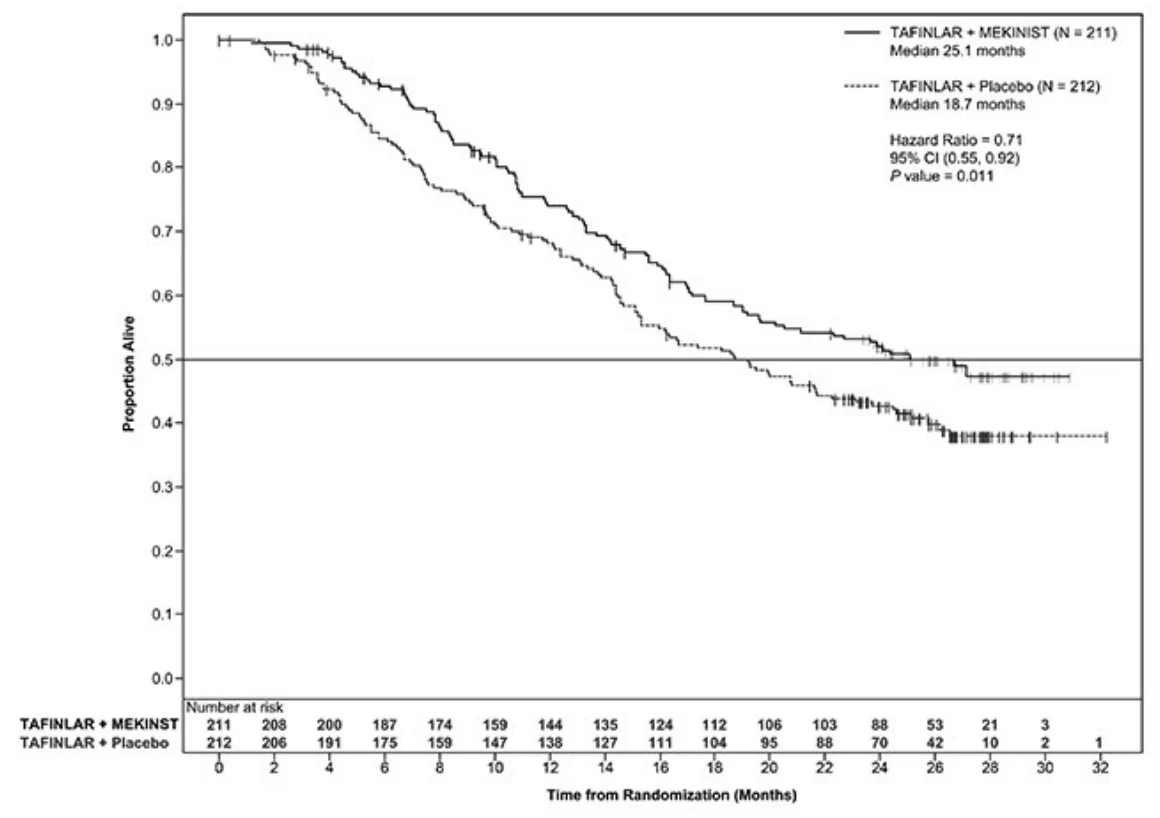
DETAILED PHARMACOLOGY
Refer to PART I, ACTION AND CLINICAL PHARMACOLOGY.
SAFETY PHARMACOLOGY
In vitro, trametinib inhibited hERG channel repolarization in HEK293 cells in a concentration dependent manner, with an IC50 of 1.54 μM (950 ng/mL). In a rabbit left ventricular wedge assay, trametinib had no significant effect on QT interval at concentrations up to 30 μM (18450 ng/mL, limit of solubility). In this preparation, significant decreases in isometric contractile force occurred at concentrations of 10 and 30 μM. A single intravenous infusion of trametinib in dogs given 1 mg/kg over 10 minutes produced no changes in electrocardiogram (ECG) parameters, blood pressure, or heart rate during the 30 minute post-dose measurement period. The highest plasma concentrations were determined at the end of the 10 minute infusion and the mean was 2.5±0.4 μM (1500 ng/mL). Single oral trametinib doses of up to 0.075 mg/kg in dogs produced no changes in arterial blood pressure, heart rate, body temperature, or ECG intervals, including QTc. Based on estimated exposures, the Cmax at this dose would be less than therapeutic (< 22 ng/mL).
In vitro, trametinib was a selective inhibitor of MEK1 and MEK2 with no affinity for other kinases at concentrations up to 10 μM (6154 ng/mL). Trametinib showed no significant binding activity (IC50 > 10 μM, 6154 ng/mL) in a screen for a number of receptors, enzymes, and ion channels.
TOXICOLOGY
Trametinib administration in non-clinical toxicology studies resulted in dose-dependent findings attributed primarily to its pharmacologic mechanism of action (inhibition of MAPK which leads to inhibition of cell proliferation in tissues with high proliferative rates including gastrointestinal, integument, and hematopoietic systems). These effects occurred in animals at systemic trametinib exposures generally below those achieved at the oral therapeutic dose of 2 mg/day in cancer patients (Cmax = 22.2 ng/mL; AUC = 370 ng.h/mL). Other findings included effects on phosphate homeostasis and soft tissue mineralization, liver, bone, ovary, and the developing embryo or foetus.
Skin lesions were seen in rats and dogs, but were more prevalent in rats where they included acanthosis, erosion, and ulceration as well as inflammatory responses in more severe cases.
Adverse gastrointestinal tract effects were observed in all repeated dose toxicology studies and were more common in dogs than rats. In both species, gastrointestinal-related clinical effects included reduced food consumption, body weight loss, and abnormal faeces. Microscopic findings in dogs included erosions and/or neutrophilic inflammation and were observed throughout the GI tract and were accompanied by lymphoid depletion in gut-associated lymphoid tissue (GALT). In rats, erosion and ulceration of stomach and cecum mucosal epithelium were seen in exploratory studies and erosion, inflammation, and hyperplasia of the glandular mucosa seen in the 13 week pivotal study.
Hematopoietic effects were seen in rats and dogs. Microscopic changes in rats included hematopoietic cell and lymphoid necrosis, bone marrow hypocellularity, and splenic necrosis in short term studies and hematopoietic cell necrosis in a 13-week study. In dogs, lymphoid depletion in GALT and thymus, bone marrow hypocellularity, and myeloid hyperplasia were seen in one or more studies. Total WBC count was frequently increased, due mainly to increased neutrophils, and likely related to the inflammatory lesions in the skin and gastrointestinal tract. Decreases in RBC parameters and reticulocyte count were seen in most of the rat studies and all dog studies.
Trametinib caused dose-dependent serum phosphatemia in rats and dogs and presumably the related soft tissue mineralization in rat tissues including stomach, kidney, heart, lung, aorta, cornea, and liver, that was shown to be due to calcium deposition. In the exploratory studies, myocardial necrosis, hepatocellular necrosis, renal cortical tubular degeneration, and alveolar/bronchiolar lesions and haemorrhage seen at non-tolerated doses were usually associated with tissue mineralization.
Thickening of the growth plate was observed in the long bones of rats with subepiphyseal infarcts/degeneration observed at higher doses. Serum and urine biomarkers indicated that both bone resorption (urinary deoxypyridinoline-to-creatinine ratio) and formation (serum crosslinked C-telopeptide of type 1 collagen, osteocalcin, tartrate-resistant acid phosphatase) occurred in rats in a 3-day investigative study.
In repeat-dose studies in rats, hepatocellular necrosis and transaminase elevations were seen after 8 weeks at ≥ 0.062 mg/kg/day (approximately 0.8 times human clinical exposure based on AUC). Mild aminotransferase and alkaline phosphatase increases at ≥ 0.03 mg/kg/day in dogs correlated with sinusoidal neutrophilia and Kupffer cell activation may have been related to gastrointestinal toxicity.
In mice, lower heart rate, heart weight and left ventricular function were observed without cardiac histopathology after 3 weeks at ≥ 0.25 mg/kg/day trametinib (approximately 3 times human clinical exposure based on AUC) for up to 3 weeks. In adult rats, myocardial mineralization and/or necrosis associated with increased serum phosphorus were seen at ≥ 0.3 mg/kg/day. In juvenile rats, increased heart weight with no histopathology was observed at 0.35 mg/kg/day (approximately 2 times adult human clinical exposure based on AUC).
Trametinib was phototoxic in an in vitro mouse fibroblast 3T3 Neutral Red Uptake (NRU) assay at significantly higher concentrations than clinical exposures (IC50 at 2.92 μg/mL, ≥ 130 times the clinical exposure based on Cmax).
Dogs given trametinib in combination with dabrafenib for 4 weeks demonstrated decreased serum albumin concentrations consistent with an acute phase response secondary to mild granulomatous changes in the stomach and mesenteric lymph node. Decreases in serum albumin have also been reported in patients receiving combination therapy as compared to those receiving dabrafenib monotherapy in the phase III combination study (see ADVERSE REACTIONS, Clinical Trial Adverse Reactions, Table 4).
Dogs given trametinib in combination with dabrafenib for 4 weeks also demonstrated decreased lymphoid cellularity of the thymus at a lower dose than in a 3-week dog study in which single agent trametinib was administered.
Carcinogenesis and Mutagenesis
Carcinogenicity studies with trametinib have not been conducted. Trametinib was not genotoxic in studies evaluating reverse mutations in bacteria, mutagenicity and chromosomal aberrations in cultured mouse lymphoma cells, and micronuclei in the bone marrow of rats.
Reproductive Toxicology
Fertility: No formal fertility studies were conducted. Trametinib may impair female fertility in humans. In adult rat repeat dose studies with female rats given trametinib for up to 13 weeks, alterations in follicular maturation, consisting of increases in cystic follicles and decreases in corpora lutea, were observed at doses ≥ 0.016 mg/kg/day (approximately 0.3 times the human clinical exposure based on AUC). Decreases in corpora lutea were also observed in a 6 week juvenile rat repeat dose study at 0.05/0.35 mg/kg/day. Additionally, in juvenile rats given trametinib, decreased ovarian weights, slight delays in hallmarks of female sexual maturation (vaginal opening and increased incidence of prominent terminal end buds within the mammary gland) and slight hypertrophy of the surface epithelium of the uterus were observed. All of these effects were reversible following an off-treatment period and likely attributable to the pharmacology of trametinib. However, in adult rat and dog toxicity studies up to 13 weeks in duration, there were no treatment effects observed on male reproductive tissues; although systemic exposure to trametinib was at sub-therapeutic levels.
Pregnancy: In reproductive toxicity studies in rats, maternal and developmental toxicity (decreased foetal weights) were seen at ≥ 0.031 mg/kg/day (approximately 0.3 times human clinical exposure based on AUC). In pregnant rabbits, maternal toxicity and post-implantation loss, including total loss of pregnancy, and foetal toxicity, consisting mainly of incomplete ossification defects, occurred at ≥ 0.039 mg/kg/day (approximately 0.1 times human clinical exposure based on AUC) and a low incidence of skeletal malformations was seen at ≥ 0.077 mg/kg/day (approximately 1/6th the human therapeutic AUC).
REFERENCES
- 1. Abe H, Kikuchi S, Hayakawa K, et al. Discovery of a highly potent and selective MEK inhibitor: GSK1120212 (JTP-74057 DMSO solvate). ACS Med Chem Lett. 2011; 2:320-324.
- 2. Falchook GS, Lewis KD, Infante JR, Gordon MS, Vogelzang NJ, DeMarini DJ, et al. Activity of the oral MEK inhibitor trametinib in patients with advanced melanoma: a phase 1 dose-escalation trial. Lancet Oncol. 2012; 13(8):782-9.
- 3. Flaherty KT, Robert C, Hersey P, Nathan P, Garbe C, Milhem M, et al. Improved Survival with MEK Inhibition in BRAF-Mutated Melanoma. N Engl J Med. 2012; 367 (2):107-14.
- 4. Gilmartin AG, Bleam MR, Groy A, et al. GSK1120212 (JTP-74057) is an inhibitor of MEK activity and activation with favorable pharmacokinetic properties for sustained in vivo pathway inhibition. Clin Cancer Res. 2011;17(5):989-1000.
- 5. Infante JR, Fecher LA, Falchook GS, Nallapareddy S, Gordon MS, Becerra C, et al. Safety, pharmacokinetic, pharmacodynamic, and efficacy data for the oral MEK inhibitor trametinib: a phase 1 dose-escalation trial. Lancet Oncol. 2012; 13(8):773-81.
- 6. Jing J, Greshock J, Holbrook JD, et al. Comprehensive predictive biomarker analysis for MEK inhibitor GSK1120212. Mol Cancer Ther. 2012;11(3):720–729.
- 7. Long GV, Stroyakovskiy D, Gogas H, Levchenko E, de Braud F, Larkin J et al. Combined BRAF and MEK Inhibition versus BRAF Inhibition Alone in Melanoma. N. Engl. J. Med. 2014; 371: 1877-1888.
- 8. Product Monograph TAFINLAR (dabrafenib mesylate) 50 mg and 75 mg. Novartis Pharmaceuticals Canada Inc.
- 9. Solit DB, Garraway LA, Pratilas CA, et al. BRAF mutation predicts sensitivity to MEK inhibition. Nature. 2006;439:358-362.