


Product Monograph - Myxredlin
1 INDICATIONS
Indications have been granted on the basis of similarity between MYXREDLIN and the reference biologic drug Novolin ge Toronto.
MYXREDLIN (Insulin Human in 0.9% Sodium Chloride Injection) is indicated for:
- The treatment of patients with diabetes mellitus who require insulin by intravenous administration for the control of hyperglycemia.
MYXREDLIN, using intravenous administration, should be used for the treatment of emergencies, such as diabetic coma and pre-coma, and in diabetics undergoing surgery. (See also CONTRAINDICATIONS)
1.1 Pediatrics
- Pediatrics (<18 years of age): No data are available to Health Canada.
1.2 Geriatrics
- Geriatrics (≥65 years): No data are available to Health Canada.
2 CONTRAINDICATIONS
Myxredlin is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- During episodes of hypoglycemia.
- In patients who are hypersensitive to human insulin or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the product monograph.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Hypoglycemia is the most common adverse effect of insulin products. As with all insulins products, the timing of hypoglycemia may differ. Glucose monitoring shall be performed for all patients with Diabetes Mellitus treated with insulins. (see HYPOGLYCEMIA AND TREATMENT OF OVERDOSAGE)
- Uncorrected hypoglycemic or hyperglycemic reactions can cause loss of consciousness, coma or even death. (see ENDOCRINE AND METABOLISM – HYPOGLYCEMIA)
- Any transfer of insulin products should be made cautiously and only under medical supervision. (see WARNINGS AND PRECAUTIONS)
- Insulin products shall not be mixed with any other insulin unless clearly indicated and done under medical supervision. (see WARNINGS AND PRECAUTIONS)
- This product shall not be used if it is not clear and colourless or if particulate matter or colouration is seen. (see DOSAGE AND ADMINISTRATION)
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Concomitant stress or illness, especially infections and feverish conditions, usually increases the patient’s insulin requirement. In these instances, patients should contact their physicians and carefully control their blood glucose.
Inspect Myxredlin visually before use. It should appear clear and colourless. Do not use if particulate matter or colouration is seen.
Administer Myxredlin intravenously ONLY under medical supervision with close monitoring of blood glucose and potassium levels (see WARNINGS AND PRECAUTIONS).
Do not add supplementary medication or additives.
Do not use in series connections.
Do not shake. Do not freeze. Discard any unused portion in accordance with local requirements.
4.2 Recommended Dose and Dosage Adjustment
The individual insulin requirement is usually between 0.3 and 1.0 IU/kg/day. The daily insulin requirement may be higher in patients with insulin resistance (e.g. during puberty in the young or due to obesity) and lower in patients with residual, endogenous insulin production.
Dosage Adjustments
- Renal or hepatic impairment may reduce insulin requirement.
- Adjustment of dosage may also be necessary if patients undertake increased physical activity or change their usual diet.
- In insulin resistance, e.g. during puberty or due to obesity, the daily insulin requirement may be substantially higher.
4.4 Administration
Insulin solution should not be used if it does not appear water-clear and colourless.
Myxredlin is administered intravenously as an infusion. This should be carried out by healthcare professionals.
The infusion rate should be adjusted according to the individual circumstances and blood glucose levels.
Monitoring of blood glucose is necessary during the insulin infusion.
5 OVERDOSAGE
Excess insulin administration may cause hypoglycemia and, particularly when given intravenously, hypokalemia. Hypoglycemia may occur as a result of an excessive dose of insulin relative to food intake, energy expenditure, or both. Omission of a meal or unplanned strenuous physical exercise may lead to hypoglycemia. Symptoms of hypoglycemia may occur suddenly. They may include cold sweat, cool pale skin, fatigue, nervousness or tremor, anxiousness, unusual tiredness or weakness, confusion, difficulty in concentration, drowsiness, excessive hunger, vision changes, headache, nausea and palpitation. Severe hypoglycemia may lead to unconsciousness and/or convulsions and may be fatal.
Mild episodes of hypoglycemia can be treated by oral administration of glucose or sugary products. It is therefore recommended that patients with diabetes always carry some sugar candy.
Severe hypoglycemic episodes, where the patient has become unconscious, can be treated with glucagon (0.5 to 1 mg) given intramuscularly or subcutaneously by a trained person or glucose given intravenously by a medical professional. Glucose must also be given intravenously if the patient does not respond to glucagon within 10 to 15 minutes. Upon regaining consciousness, administration of an oral carbohydrate is recommended for the patient in order to prevent relapse. Hypokalemia must be corrected appropriately.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous | Solution for infusion, 100 units | Dibasic Sodium Phosphate Anhydrous, USP; |
For management of a suspected drug overdose, contact your regional poison control centre.
Myxredlin for intravenous use is a sterile, preservative-free, nonpyrogenic, clear, aqueous, and colourless solution supplied in a 100 mL GALAXY single-dose container. The pH range is 6.5 - 7.2.
Description
The active substance in Myxredlin is a polypeptide that is structurally identical to natural human insulin. Insulin human is produced by recombinant DNA technology in Pichia pastoris.
7 WARNINGS AND PRECAUTIONS
Please see the SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
As with all insulin products, the duration of Myxredlin may vary in different individuals or in the same individual according to dose, injection site, blood flow, temperature and level of physical activity.
Thiazolidinediones (TZDs), alone or in combination with other antidiabetic agents (including Insulin), can cause heart failure and oedema. The combination of Insulin with a TZD is not indicated for the treatment of Type 2 Diabetes Mellitus. Please refer to the respective TZD product monograph WARNINGS AND PRECAUTIONS information when the use of these drugs in combination with any insulin, including Myxredlin, is contemplated.
Carcinogenesis and Mutagenesis
See Part II – Scientific Information – NON-CLINICAL TOXICOLOGY.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism Hypoglycemia
As with other insulins, hypoglycemia is the most frequently occurring undesirable effect of insulin therapy. Such reactions following treatment with Myxredlin are mostly mild and easily managed.
As with all insulin preparations, hypoglycemic reactions may be associated with the administration of Myxredlin. Early warning symptoms of hypoglycemia may be different or less pronounced under certain conditions, such as long duration of diabetes, diabetic nerve disease, use of medications such as beta-blockers, or intensified diabetes control.
Patients, whose blood glucose control is greatly improved, e.g. by intensified insulin therapy, may experience a change in their usual warning symptoms of hypoglycemia, and should be advised
| insulin human in 100 mL 0.9% sodium chloride (1 unit per mL). | Monobasic Sodium Phosphate Monohydrate, USP; Sodium Chloride, USP; and Water for Injection, USP. |
accordingly. Usual warning symptoms may disappear in patients with longstanding diabetes. Hypoglycemia may occur if the insulin dose is too high in relation to the insulin requirement. (see ADVERSE REACTIONS and HYPOGLYCEMIA AND TREATMENT OF OVERDOSAGE)
Omission of a meal or unplanned strenuous physical exercise may lead to hypoglycemia.
Stress or concomitant illness, especially infectious and febrile conditions may change insulin requirements. In these instances, patients should contact their physician and carefully control their blood glucose. Concomitant diseases in the kidney, liver or affecting the adrenal, pituitary or thyroid gland can require changes in the insulin dose.
Hypoglycemia can occur regardless of what type of insulin you take and can cause fatigue, sweating, heart palpitations, disturbed behaviour, hunger, convulsions, loss of consciousness, temporary or permanent impairment of brain function, or, in extreme circumstances, even death which can occur without recognizable symptoms.
Some people may not recognize when their blood sugar drops low.
The patient’s ability to concentrate and react may be impaired as a result of hypoglycemia. This may constitute a risk in situations where these abilities are of special importance (e.g. driving a car or operating machinery).
Patients should be advised to take precautions to avoid hypoglycemia while driving. This is particularly important in those who have reduced or absent awareness of the warning signs of hypoglycemia or have frequent episodes of hypoglycemia. The advisa bility of driving should be considered in these circumstances.
Glucose monitoring is recommended for all patients with diabetes.
Hepatic/Biliary/Pancreatic
There is no experience of the treatment with Myxredlin patients with hepatic impairment. As with other insulins, Myxredlin requirements may need to be adjusted in patients with hepatic impairment (see CLINICAL PHARMACOLOGY – Pharmacokinetics). As Myxredlin is used for treatment of diabetes mellitus, there is experience with treatment of pancreatic impairment concerned with diabetes mellitus, but not with other types pancreatic impairment.
Hyperglycemia
Inadequate dosing or discontinuation of insulin treatment, especially in type 1 diabetes, may lead to hyperglycemia and diabetic ketoacidosis. Usually the first symptoms of hyperglycemia develop gradually over a period of hours or days. They include thirst, increased frequency of urination, nausea, vomiting, drowsiness, flushed dry skin, dry mouth, loss of appetite as well as acetone odour of breath (see ADVERSE REACTIONS). In type 1 diabetes, untreated hyperglycemic events eventually lead to diabetic ketoacidosis, which is potentially lethal.
Hypokalemia
All insulin products, including Myxredlin, cause a shift in potassium from the extracellular to intracellular space, possibly leading to hypokalemia that, if left untreated, may cause respiratory paralysis, ventricular arrhythmia, and death. Use caution in patients who may be at risk for hypokalemia (e.g., patients using potassium-lowering medications, patients taking medications sensitive to serum potassium concentrations, patients receiving intravenously administered insulin or patients losing potassium through other means (e.g., diarrhea)]. (see ADVERSE REACTIONS)
Immune
Local Allergic Reaction
As with any insulin therapy, injection site reactions may occur and include pain, redness, itching, hives, swelling, bruising and inflammation. Continuous rotation of the injection site within a given area may help to reduce or prevent these reactions. Reactions usually resolve in a few days to a few weeks. On rare occasions, injection site reactions may require discontinuation of Myxredlin.
Systemic Allergic Reaction
Systemic allergic reactions have rarely occurred with Myxredlin as with other insulin treatment. These reactions may be characterized by a generalized rash (with pruritus), shortness of breath, wheezing and drop in blood pressure. Severe cases of generalized allergy including anaphylactic reaction may be life threatening.
Antibody Production
Immune responses can occur in response to insulin. This may be associated with elevated IgG levels however this does not appear to affect HbA1c.
Human insulin is known to be antigenic, with low titres of antibodies developing in most patients (up to 80%). The effect of insulin antibodies on insulin pharmacokinetics, with the presence of binding IgG in serum, may delay time to peak levels of free insulin. Antibodies may be cross-reactive between different types of insulin.
Monitoring and Laboratory Tests
In patients with diabetes mellitus optimised metabolic control delays the onset and slows the progression of late diabetic complications. Optimised metabolic control, including glucose monitoring, is therefore recommended.
Renal
There is no experience of the treatment with Myxredlin patients with renal impairment. As with other insulins, Myxredlin requirements may need to be adjusted in patients with renal impairment (see CLINICAL PHARMACOLOGY – Pharmacokinetics).
Reproductive Health: Female and Male Potential
Function
There is no information available on teratogenicity of human insulin products.
Reproduction
There is no information available on teratogenicity of human insulin products.
Transferring Patients from Other Insulins
When patients are transferred between different types of insulin products, including animal insulins, the early warning symptoms of hypoglycemia may have changed or become less pronounced than those experienced with their previous insulin. Transferring a patient to a new type or brand of insulin should be done only under strict medical supervision. Changes in insulin strength, timing of administration, manufacturer, type (e.g. regular, NPH or insulin analogs), or method of manufacture (recombinant DNA versus animal source insulin) may result in the need for a change in dosage. Concomitant oral anti-diabetic treatment may also need to be adjusted. If an adjustment is needed, it may be done with the first doses or during the first weeks or months and under medical supervision.
Any patient on a total daily dose of greater than 100 units of insulin may need to be closely monitored by the physician when transferring to a different insulin preparation, preferably in hospital.
7.1 Special Populations
7.1.1 Pregnant Women
During pregnancy and lactation, diabetes may become more difficult to manage. However, optimal metabolic control not only during pregnancy, but also prior to conception has proven to be beneficial in reducing the risk of miscarriage and malformation of the fetus. Insulin requirements usually decrease during the first trimester and increase during the second and third trimesters. Diabetics who have become pregnant or desiring to become pregnant should consult their doctor for advice. Insulin ingested with the mother's milk has not been associated with any risk for the baby.
7.1.2 Breast-feeding
There are no restrictions on the treatment of diabetes with Myxredlin during lactation. Insulin treatment of the nursing mother presents no risk to the baby. However, the dosage of Myxredlin and/or diet may need to be adjusted.
7.1.3 Pediatrics
No data available to Health Canada.
7.1.4 Geriatrics
No data available to Health Canada.
Others
The presence of diseases such as Acromegaly, Cushing’s syndrome, Hyperthyroidism and Pheochromocytoma can complicate the control of diabetes mellitus.
8 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared Myxredlin to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
At institution of insulin therapy, oedema and refraction anomalies may occur. These conditions are usually of a transitory nature.
Hypoglycemia is the most frequent undesirable effect. It may occur if the insulin dose is too high in relation to the insulin requirement. In clinical trials and during marketed use, the frequency varies with patient population and dose regimes. Therefore, no specific frequency can be presented. Severe hypoglycemia may lead to unconsciousness and/or convulsions and may result in temporary or permanent impairment of brain function or even death.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse events were reported in three comparative studies performed with the reference biologic drug Novolin®ge. In one study, one patient in the Novolin®ge treatment group experienced pain at the injection site. In one study, two patients in the Novolin®ge treatment group had suspected insulin allergy. However, skin tests showed no evidence of a response to either Novolin®ge or Novolin®, Insulin Human Semi-synthetic (ss). One patient receiving Novolin®ge was hospitalized with mild ketoacidosis but fully recovered after hospital treatment. In one study seven patients receiving Novolin®ge and two Novolin® (ss) reported headaches. There was no clear etiology for these. In addition, eight patients receiving Novolin®ge and one receiving Novolin® (ss) experienced pain and burning after injection. These latter findings are difficult to interpret as they are currently seen in clinical practice. They were not related to insulin allergy except in one patient who tested positive to protamine.
8.3 Less Common Clinical Trial Adverse Reactions
No clinical trials, where human insulin has been used as the primary investigational medicinal products (IMP), have been conducted recently. However, human insulin has been used as comparator or concomitant medication in clinical trials where other products have been the IMP.
The overall profile of adverse events – frequency, severity or type of adverse events – reported on human insulin during these clinical trials, has not caused any safety concern. No specific clustering of less common adverse drug reactions have been seen and no changes to the core safety information have been necessary for safety reasons.
8.5 Post-Market Adverse Reactions
The following are adverse drug reactions based on post-marketing experience.
Metabolism and Nutrition Disorders
Rare (<1/1000)
Change in blood glucose: hypoglycemia / hyperglycemia.
Hypoglycemia:
Symptoms of hypoglycemia usually occur suddenly. They may include cold sweats; cool pale skin; fatigue; nervousness or tremor; anxiousness; unusual tiredness or weakness; confusion; difficulty in concentration; drowsiness; excessive hunger; vision changes; headache; nausea and palpitation.
Severe hypoglycemia may lead to unconsciousness and/or convulsions and may result in temporary or permanent impairment of brain function or even death.
Hyperglycemia:
Usually the first symptoms of hyperglycemia set in gradually, over a period of hours or days. They include thirst; increased frequency of urination; nausea; vomiting; drowsiness; flushed dry skin; dry mouth; loss of appetite as well as acetone odour of breath.
In type 1 diabetes, untreated hyperglycemic events eventually lead to diabetic ketoacidosis which is potentially lethal.
Immune system disorder
Uncommon (>1/1000, <1/100) – Urticaria, rash. Very rare (<1/10 000) – Anaphylactic reactions.
Symptoms of generalized hypersensitivity may include generalized skin rash; itching; sweating; gastrointestinal upset; angioneurotic oedema; difficulties in breathing; palpitation; reduction in blood pressure and fainting/loss of consciousness. Generalized hypersensitivity reactions are potentially life threatening.
Nervous system disorders
Uncommon (>1/1000, <1/100) – Peripheral neuropathy.
Fast improvement in blood glucose control may be associated with a condition termed “acute painful neuropathy”, which is usually reversible.
Eye disorders
Very rare (<1/10 000) – Diabetic retinopathy.
Long-term improved glycemic control decreases the risk of progression of diabetic retinopathy. However, intensification of insulin therapy with abrupt improvement in glycemic control may be associated with temporary worsening of diabetic retinopathy.
Uncommon (>1/1000, <1/100) – Refraction disorders.
Refraction anomalies may occur upon initiation of insulin therapy. These symptoms are usually transitory in nature.
Skin and subcutaneous tissue disorders
Uncommon (>1/1000, <1/100) – Lipodystrophy.
Lipodystrophy may occur at the injection site as a consequence of failure to rotate injection sites within an area.
General disorders and administration site conditions
Uncommon (>1/1000, <1/100) - Injection site reactions.
Injection site reactions (redness, swelling, itching, pain and haematoma at the injection site) may occur during treatment with insulin. Most reactions are usually transitory and disappear during continued treatment.
Uncommon (>1/1000, <1/100) – Oedema.
Oedema may occur upon initiation of insulin therapy. These symptoms are usually transitory in nature.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
As with insulin in general, concomitant use of other drugs may influence insulin requirements.
9.4 Drug-Drug Interactions
The following substances may reduce the insulin requirements: Oral antidiabetic drugs, monoamine oxidase inhibitors (MAOI), beta-blockers, angiotensin converting enzyme (ACE) inhibitors, salicylates, anabolic steroids, sulphonamides and alcohol.
The following substances may increase insulin requirements: Oral contraceptives, thiazides, glucocorticosteroids, thyroid hormones, sympathomimetics, growth hormone and danazol.
Beta-blocking agents may mask the symptoms of hypoglycemia and delay recovery from hypoglycemia.
Octreotide/lanreotide may either increase or decrease insulin requirements. Alcohol may intensify or reduce the hypoglycemic effect of insulin.
To avoid the risk of developing new or worsening heart failure, the use of TZDs in combination therapy with Myxredlin is not indicated. (see WARNINGS AND PRECAUTIONS).
9.5 Drug-Food Interactions
Please refer to CLINICAL PHARMACOLOGY, Mechanism of Action and DOSAGE AND ADMINISTRATION for interactions with food and timing of food consumption, respectively.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
Drug-Lifestyle Interactions
Changes in insulin therapy or changes in lifestyle (i.e. diet, exercise/physical activity) may require a change in dosage.
Patients should be informed about the potential advantages and disadvantages of Myxredlin therapy including the possible side effects. Patients should also be offered continued education and advice on insulin therapies, life-style management, self-monitoring, complications of insulin therapy, timing of dosage, instruction for use of injection devices and storage of insulin.
The need for regular blood glucose self-monitoring should be considered when using Myxredlin to obtain optimal glycemic control.
Female patients should be advised to discuss with their physician if they intend to or if they become pregnant.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The primary activity of Myxredlin is the regulation of glucose metabolism. The blood glucose lowering effect of insulins, including Myxredlin is due to the facilitated uptake of glucose following binding of insulin to receptors on muscle and fat cells and to the simultaneous inhibition of glucose output from the liver.
10.2 Pharmacodynamics
Myxredlin is a fast-acting insulin which is administered by intravenous infusion.
In a double-blind, randomized, crossover, euglycemic glucose clamp study (see COMPARATIVE BIOAVAILABILITY STUDIES), the average onset of action, defined as start of intravenous glucose infusion during the clamp, was approximately 18.5 minutes, after initiation of the intravenous infusion administration. The glucose infusion rate gradually increased to a maximum response of 12.7 mg/kg/min after 5.4 hours of human insulin infusion (see PHARMACOKINETICS).
10.3 Pharmacokinetics
Insulin in the blood stream has a half-life of a few minutes. Consequently, the time-action profile of an insulin preparation is determined solely by its absorption characteristics.
This process is influenced by several factors (e.g. insulin dosage, injection route and site, thickness of subcutaneous fat, type of diabetes). The pharmacokinetics of insulin is therefore affected by significant intra- and inter-individual variation.
| Absorption |
In comparison to subcutaneously administered insulin which have a peak insulin effect between 1.5 and 2.5 hours post dose, serum insulin concentrations increase rapidly immediately upon administration by intravenous infusion.
Distribution:
No profound binding to plasma proteins, except circulating insulin antibodies (if present) has been observed.
Metabolism:
Human insulin is reported to be degraded by insulin protease or insulin -degrading enzymes and possibly protein disulfide isomerase. A number of cleavage (hydrolysis) sites on the human insulin molecule have been proposed; none of the metabolites formed following the cleavage are active.
Elimination
Following cessation of intravenous infusion, serum insulin concentration decreases with a median half-life of 29 minutes.
Special Populations and Conditions
No specific pharmacokinetic data on Myxredlin in special patient populations are available. The approved indication covers "Treatment of insulin requiring diabetics" (see Indications and Clinical use) without any restrictions regarding age, gender or ethnicity of the diabetes patients.
Dosage is individual and is determined by the physician in accordance with the needs of the patients. However, renal or hepatic impairment may reduce insulin requirements.
Detailed Pharmacology
Animal Pharmacology
The reference biologic drug, Novolin®ge, Insulin, Human Biosynthetic was tested in a number of pharmacological models in order to exclude secondary effects different from those which could be expected with Novolin ®, Insulin, Human Semi-synthetic (ss). In a similar series of tests, Novolin® (ss) was compared with pork insulin of equal purity in doses up to 50 U/kg. The models used for both comparisons covered a wide range of target systems and can be seen in the following table:
Table 2 - Animal pharmacological models tested to exclude secondary effects from Novolin®ge different from those expected with Novolin® (ss).
| Target System | Pharmacological Model | Secondary Effects Seen (Yes/No) | ||
Novolin® ge compared with Novolin® (ss) | Novolin® (ss) compared with pork insulin | |||
| Mice | Ataxia (animex and rotarod) and narcosis potentiation | Yes | Yes |
| Cat | Ganglionic Transmission | No | No |
3. Neuromuscular Transmission | Rat | Tibial nerve- gastrocnemius muscle preparation | No | No |
| Cat | General Hemodynamics, respiration and ECG | No | No |
| Rat (conscious) | Blood pressure | No | No | |
| Rat | Diuresis and antidiuresis | No | Yes |
| Pig | Bromsulfophthalein test | No | No |
| Rat | Effects on streptozocin induced diabetes | Yes | Yes |
| Guinea-Pig | Illuem stimulated with acetylcholine, histamine, serotonim and nicotine | No | No |
| Guinea-Pig | Vas deferens stimulated with noradrenaline (concentration of the insulins 50 U/I) | No | No |
When comparing Novolin®ge and Novolin® (ss), effects were seen in two of the tests (1 and 7). When comparing Novolin® (ss) and pork insulin, in addition to tests 1 and 7, effects were also seen in test 5. This may be due to the dose given or minor differences in experimental design. In all cases, these effects were the same for the two insulin preparations being compared. In other tests no effects were observed with any of the insulin preparations being compared. The immunogenicity of Novolin®ge was compared with Novolin® (ss) insulin. The immunization was performed in rabbits with 20 IU per injection in incomplete Freund's adjuvant. No statistically significant difference between the immunogenicity of Novolin®ge and Novolin® (ss) insulins was found.
Human Pharmacology
Owens compared the bioavailability of Novolin-Toronto® semi-synthetic with Novolin®ge Toronto, the reference biologic drug, following subcutaneous injection in ten normal male volunteer subjects. The study was undertaken with both U40 and U100 insulin preparations. All subjects participated in four separate study days, approximately one week apart. The subjects receive d, in random order,
0.1 IU/kg body weight of the following: Novolin®ge Toronto 40 IU/ml, Novolin®ge Toronto 100 IU/ml, and the equivalent Novolin® (ss) insulin preparations following a ten-hour overnight fast prior to each study day. Only the results from the study with U100 insulin are reviewed. No statistically significant differences were observed in terms of plasma insulin and plasma glucose profiles between the two insulin preparations following subcutaneous injections. Plasma glucose and immunoreactive insulin levels were virtually identical. The two comparative preparations were well tolerated by all subjects and no untoward side effects were reported.
Table 3 - Human pharmacological model tested to exclude secondary effect from Novolin®ge that differ from those expected with Novolin® (ss).
| Target | Pharmacological | Secondary Effects Seen | ||
| System | Model | (Yes/No) | ||
| Novolin® ge | Novolin® (ss) | |||
| compared | compared | |||
| with Novolin® | with pork | |||
| (ss) | insulin | |||
| Thrombocytes | Man | In vitro aggregation (In this test concentrations up to 7.3 U/mL were used) | No | No |
11 STORAGE, STABILITY AND DISPOSAL
Store Myxredlin under refrigeration (2 to 8°C) in the original carton to protect from light. Do not use after the expiration date printed on the carton and container label.
If needed, Myxredlin may be removed from the original carton and stored at room temperature up to 25°C for up to 25 days, but not exceeding the original expiry date. Once stored at room temperature, do not place back in the refrigerator. Discard Myxredlin in accordance with local requirements after 25 days if stored at room temperature.
Do not freeze and do not use Myxredlin if it has been frozen (see SPECIAL HANDLING INSTRUCTIONS).
12 SPECIAL HANDLING INSTRUCTIONS
For single use only. Product should be used immediately after insertion of the infusion set to the bag.
Insulin preparations which have been frozen must not be used.
Insulin solutions should not be used if they do not appear water-clear and colourless.
Do not use Myxredlin if particulate matter or colouration is seen.
Do not use if infusion bag is damaged. In case of leaks, discard in accordance with local requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Insulin, Human
Chemical name: TBC
Molecular formula and molecular mass: C257 H383 N65 O77 S6, approximately 5808 Dalton
Structural formula:
Figure 1. Human insulin - molecular structure.
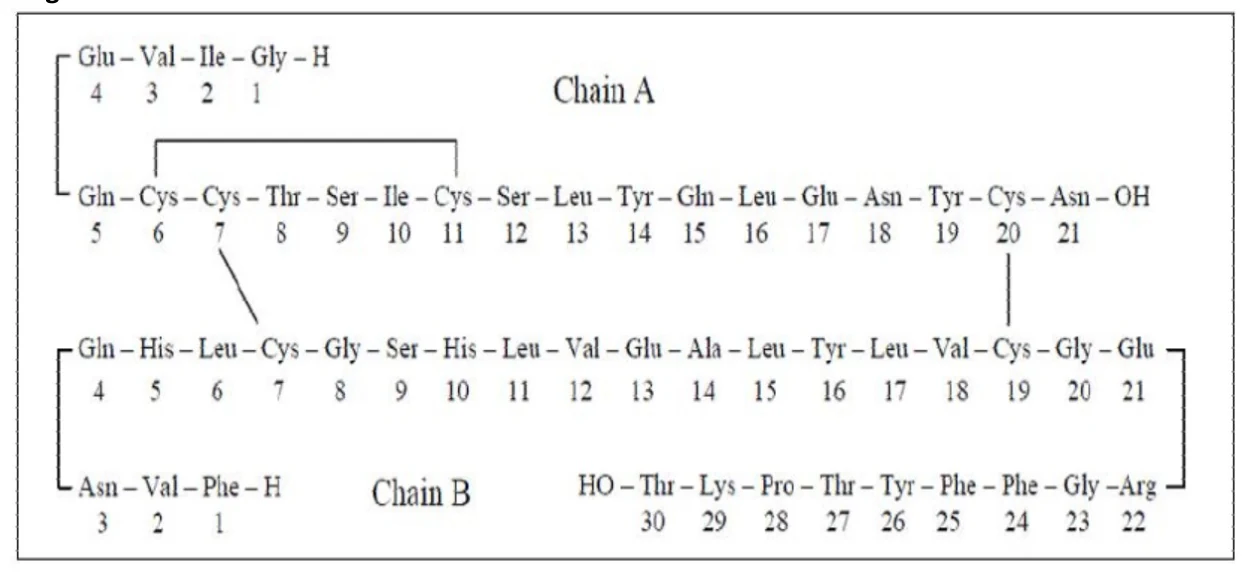
Physicochemical properties:
Description:
Myxredlin for intravenous use is a sterile, preservative-free, nonpyrogenic, clear, aqueous, and colourless solution supplied in a 100 mL GALAXY single-dose container. It contains 100 units of regular insulin human in 100 milliliters of 0.9% sodium chloride injection. Each milliliter of solution contains 1 unit Insulin Human, USP; 0.412 mg Dibasic Sodium Phosphate Anhydrous, USP; 0.290 mg Monobasic Sodium Phosphate Monohydrate, USP; 9.0 mg Sodium Chloride, USP; and Water for Injection, USP. The pH range is 6.5-7.2.
Pharmaceutical standard:
Insulin Human USP reference standard.
Product Characteristics
Insulin Human is a polypeptide hormone and is produced by recombinant DNA technology, utilizing Pichia pastoris (a yeast) as the production organism. During fermentation, the organism secretes a single peptide chain insulin precursor directly into the growth medium. The insulin precursor is then converted to human insulin and subsequently purified to a high degree.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Clinical studies conducted to support similarity between Myxredlin and the reference biologic drug included a double-blinded, randomized comparative bioavailability study performed in healthy adult male subjects.
Study CEL-HI-203 was conducted with Myxredlin and Actrapid (sourced from EU), which was deemed to be an appropriate proxy for the Canadian reference biologic drug, Novolin ge Toronto.
Table 4 - Summary of patient demographics for clinical trials
| Study # | Study design | Dosage, route of administratio n and duration | Study subjects (n) | Mean age (Range) | Sex |
| CEL-HI-203 | Phase 1, double-blind, randomized, two treatment, two-period, two-way crossover, euglycemic glucose clamp trial | 1.0 mU/kg/min, Intravenous, 6 hours (total dose of 0.36 IU/kg) | Normal healthy volunteers; 60 randomize d and 54 PK/PD set | 33.4 years (19-50 years) | Male |
14.2 Study Results
See 14.3 Comparative Bioavailability Studies.
14.3 Comparative Bioavailability Studies
Table 5 - Study CEL-HI-203 – Statistical Analysis of Primary Pharmacokinetic and Pharmacodynamic Parameters From measured data Geometric Mean Arithmetic Mean (CV %) | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Parameter | Test1 (N=54) | Reference2 (N=54) | % Ratio of Geometric Means | Confidence Interval | |||||
AUCINS-SS 300-360 min (min*pmol/L) | 21002.74 21436.48 (20.39) | 20328.07 20798.06 (21.95) | 103.3 | 100.23-106.503 | |||||
| Cmax INS 300-360 min (pmol/L) | 390.16 399.13 (21.41) | 372.35 380.20 (20.77) | 105 | 101.8-107.93 | |||||
AUCGIR-SS 300-360 min (mg) | 45855.42 47670.15 (29.48) | 44872.15 46722.72 (30.90) | 102.0 | 96.60-107.454 | |||||
Table 5 - Study CEL-HI-203 – Statistical Analysis of Primary Pharmacokinetic and Pharmacodynamic Parameters From measured data Geometric Mean Arithmetic Mean (CV %) |
|---|
| Parameter | Test1 (N=54) | Reference2 (N=54) | % Ratio of Geometric Means | Confidence Interval |
|---|---|---|---|---|
GIRmax-SS 300-360 min (mg/min) | 941.53 971.11 (26.36) | 922.93 947.28 (23.95) | 102.5 | 97.23-107.804 |
1 Myxredlin (insulin human in 0.9% sodium chloride injection) by Baxter Corporation 2 Actrapid (insulin human) (sourced from EU) by Novo Nordisk Limited (as a suitable proxy for the reference biologic drug, Novolin GE Toronto from Novo Nordisk Canada Inc.) 3 90% Confidence interval 4 95% Confidence interval Abbreviations: AUCINS-SS 300-360 min = area under the insulin concentration-time curve at steady state measured from 300 – 360 minutes, CmaxINS-SS 300-360 min = maximal concentration measured at steady state from 300-360 minutes, AUCGIR-SS, 300-360 min=area under the glucose infusion rate time curve at SS measured from 300 – 360 minutes, GIRmax-SS 300-360 min=maximal glucose infusion rate measured at steady state from 300-360 minutes,. | ||||
14.5 Clinical Trials – Reference Biologic Drug
There have been no clinical trials conducted with human insulin since 2002.
Study demographics and trial design
Clinical studies have been designed not only to compare the safety and efficacy of Novolin ®ge with Novolin® (ss) insulins, but also to screen for the formation of antibodies to S. cerevisiae. In order to do this a very sensitive ELISA technique has been developed. Evaluation of sera from 216 healthy volunteers without any history of atopy has been used to establish a normal range for antibodies to yeast and to provide a reference for comparison with samples from clinical trials with Novolin®ge.
Fourteen clinical studies investigating the safety and efficacy of Novolin ®ge have been undertaken. All studies were of twelve months duration. A total of 396 diabetic patients, all previously treated with Novolin® (ss), completed their respective studies. One study was uncontrolled and sequential. Twelve were open, randomized, parallel, asymmetrical comparisons of Novolin®ge with the corresponding Novolin® (ss) preparations employing a similar protocol. One study was a multicentre, double blind, randomized, parallel, asymmetrical comparison of Novolin®ge with the corresponding Novolin® (ss) preparations.
The safety and efficacy of treatment with a series of premixed preparations of Novolin ®ge Toronto and Novolin®ge NPH was compared with individual mixtures of biosynthetic human insulin manufactured by Eli Lilly in a 12-week crossover study of 38 insulin requiring diabetics. Metabolic control (as judged by HbA1c), 8 point blood glucose profiles (laboratory and home monitored), fasting blood sugar, occurrence and severity of hypoglycemic episodes, and complaints were recorded at predetermined intervals
Study results
No significant differences were found between the two groups for mean 8 point blood glucose profiles (laboratory or home monitored), fasting blood glucose, or the occurrence of hypoglycemic episodes at week 6 or week 12 (crossover and completion). Metabolic control, as judged by HbA1c, remained unchanged between the 2 study groups irrespective of treatment order and no significant differences were found between the 2 groups at week 6 or week 12.
Two studies evaluated the bioequivalence of four different Novolin®ge premixed preparations and fresh admixtures of Novolin®ge Toronto / Novolin®ge NPH of similar proportions in 12 normal volunteers. In each study the serum concentration of immunoreactive insulin, C- peptide and blood glucose were compared after subcutaneous injection of 12 units according to a randomized 4-way crossover design. Bioequivalence was concluded to exist between all four premixed Novolin®ge preparations and the comparable admixture of Novolin®ge Toronto and Novolin®ge NPH as assessed by Tmax, Cmax, and AUC.
In both studies some subjects experienced hypoglycemia after administration of insulin especially in the study with Novolin®ge 40/60 and Novolin®ge 50/50. However, there were no differences between the premixed insulins and the admixtures in this regard. This is not unexpected in view of the proportion of regular insulin given and the fact that the subjects were fasting.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
16.1 Comparative Non-Clinical Pharmacology and Toxicology
The non-clinical pharmacodynamic and toxicological comparability between Myxredlin and reference biologic drug (Actrapid-EU and/or Novolin R-US) were investigated in in vitro and in vivo studies. Actrapid-EU (comparable to Novolin R-US) was a suitable proxy for the Canadian reference biologic drug, Novolin ge Toronto.
- 16.1.1 Comparative Non-Clinical Pharmacodynamics
In vitro Studies
The nonclinical pharmacodynamic data package with Myxredlin has investigated the following aspects relative to Actrapid-EU:
Comparative receptor binding on both human insulin receptors (IR-A and IR-B) including on – off kinetics.
- Insulin binding studies by surface plasmon resonance (SPR; long and short form)
Biological activity addressing receptor autophosphorylation and metabolic activity of Insulin:
- Insulin receptor phosphorylation (IR-A and IR-B)
- Adipogenesis
- Inhibition of lipolysis
- Glucose uptake
Effects mediated by Insulin-like growth factor-1 (IGF-1) Reactivity with Insulin:
- IGF-1 receptor binding assay
- Mitogenic activity
Taken together, the in vitro assessment of the pharmacodynamics of Myxredlin showed that the binding profiles to the insulin receptors (IR-A and IR-B) and Insulin-like growth factor 1 (IGF-1) receptor, biological activity (adipogenesis, inhibition of lipolysis and glucose uptake), and mitogenic activity were similar relative to the reference biologic drug.
- 16.1.2 Comparative Toxicology
A comparative 14-day continuous intravenous infusion rat toxicology study (including toxicokinetic analysis) was conducted with Myxredlin containing up to 10% desamido insulin-related substances and the reference biologic drug (Novolin R-US, Insulin Human 100 U/mL).
Rats administered Myxredlin with up to 10% desamido insulin-related substances did not show any unique toxicology findings when compared to rats administered reference biologic drug.
16.2 NON-CLINICAL TOXICOLOGY – Reference Biologic
General Toxicology
Table 6 - Details of Animal Toxicity Studies.
| Animal Species | ||||
| Mice and Rats | Rats | Rabbits | Beagles | |
| Objective | Compare Novolin®ge (Insulin, Human Biosynthetic) with Novolin®(ss) (Insulin, Human Semi- synthetic) insulin | Compare Insulin, Human Biosynthetic with Insulin, Human Semi-synthetic | Inject 3.0 U/kg/day over a 13 week period. | |
| Route | Subcutaneous | Subcutaneous | Intermuscular injection | Subcutaneous Injection |
| Dosage Regimen | Acute | 4 week | 13 week Period | |
| Results | No differences observed between Insulin, Human Biosynthetic and Insulin, Human Semi- synthetic | No differences observed between Insulin, Human Biosynthetic and Insulin, Human Semi- synthetic | No evidence of toxicity |
Local irritation in rabbits after intermuscular injection with Insulin, Human Biosynthetic was similar to that caused by isotonic saline.
Insulin, Human Biosynthetic has been shown to be pyrogen free.
Carcinogenicity
Preclinical data with Insulin, Human Biosynthetic reveal no special hazard for humans based on conventional studies of carcinogenic potential.
Genotoxicity
In a series of sensitive tests designed to evaluate mutagenic Insulin, Human Biosynthetic activity has been shown to be non-mutagenic. Preclinical data with Insulin, Human Biosynthetic reveal no special hazard for humans based on conventional studies of genotoxicity.
17 SUPPORTING PRODUCT MONOGRAPHS
1- Novolin®ge (Insulin, Human Biosynthetic), Injectable Solution/Suspension, Submission Control Number 251302, Product Monograph, Novo Nordisk Canada, August 12, 2021.