


Product Monograph - Nu-Salbutamol Plastic Ampules 1 mg/mL
INDICATIONS AND CLINICAL USE
NU-SALBUTAMOL Respirator Solutions (Salbutamol Sulfate Solution BP) are indicated for the treatment of severe bronchospasm associated with exacerbations of chronic bronchitis and bronchial asthma. They can be used by 'wet' nebulization. When administered through a nebulizer, NU-SALBUTAMOL Respirator Solutions (Salbutamol Sulfate Solution BP) should be used with compressed air or oxygen.
CONTRAINDICATIONS
Hypersensitivity to any of the ingredients and in patients with tachyarrhythmias.
WARNINGS
Use Of Anti-Inflammatory Agents
In accordance with the present practice for asthma treatment, concomitant anti-inflammatory therapy (e.g. corticosteroid) should be part of the regimen if inhaled salbutamol needs to be used on a regular daily basis (see DOSAGE AND ADMINISTRATION). It is essential that the physician instruct the patient in the need for further evaluation if the patient's asthma becomes worse.
Deterioration of Asthma
The management of asthma should normally follow a stepwise program and patient response should be monitored clinically and by lung function tests. The increasing use of fast-acting, short-duration inhaled beta2-adrenergic agonists to control symptoms indicates deterioration of asthma control and the patient's therapy plan should be reassessed. Sudden or progressive deterioration in asthma control is potentially life-threatening; the treatment plan must be re-evaluated, and consideration be given to corticosteroid therapy.
Cardiovascular Effects
In individual patients, any beta2-adrenergic agonist, including salbutamol, may have a clinically significant cardiac effect. Care should be taken with patients suffering from cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias and hypertension. Special care and supervision are required in patients with idiopathic hypertrophic subvalvular aortic stenosis, in whom an increase in the pressure gradient between the left ventricle and the aorta may occur, causing increased strain on the left ventricle.
Hypokalemia
In common with other beta-adrenergic agents, salbutamol can induce reversible metabolic changes such as potentially serious hypokalemia, particularly following nebulized or especially infused administration. Particular caution is advised in acute severe asthma since hypokalemia may be potentiated by concomitant treatment with xanthine derivatives, steroids and diuretics and by hypoxia. Hypokalemia will increase the susceptibility of digitalis-treated patients to cardiac arrhythmias. It is recommended that serum potassium levels be monitored in such situations.
Diabetes
Care should be taken with patients with diabetes mellitus. Salbutamol can induce reversible hyperglycemia during nebulized administration or especially during infusions of the drug. The diabetic patient may be unable to compensate for this and the development of ketoacidosis has been reported. Concurrent administration of corticosteroids can exaggerate this effect.
Paradoxical Bronchospasm
With repeated excessive use of sympathomimetic inhalation preparations, some patients have been reported to have developed severe paradoxical bronchospasm, occasionally leading to death.
The cause of either the refractory state or death is unknown. However, it is suspected in the fatal episodes that cardiac arrest occurred following the unexpected development of a severe acute asthmatic crisis and subsequent hypoxia. Several cases have been reported in which intermittent positive pressure ventilation in acute asthma attacks was related to lethal episodes of hypoxia and pneumothorax. This method of drug administration may be ineffective in patients with severe obstruction and greatly increased airway resistance, and it may induce severe hypercapnia and hypoxia. During intermittent ventilation therapy, the monitoring of arterial blood gases is highly desirable. It is advisable that in the event of either hypoxia and pneumothorax or paradoxical bronchospasm the use of the preparation should be discontinued immediately and alternate therapy instituted, since in the reported cases the patients did not respond to other forms of therapy until the drug was withdrawn.
Care should be taken with patients with convulsive disorders, hyperthyroidism or in patients who are unusually responsive to sympathomimetic amines.
Do Not Exceed Recommended Dose
Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
Immediate Hypersensitivity Reactions
Immediate hypersensitivity reactions may occur after administration of salbutamol or salbutamol sulfate, as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm, anaphylaxis and oropharyngeal edema.
PRECAUTIONS
General
If therapy does not produce a significant improvement or if the patient's condition worsens, medical advice must be sought in order to determine a new plan of treatment. In the case of acute or rapidly worsening dyspnea, a doctor should be consulted immediately.
Failure to respond for at least 3 hours to a previously effective dose of salbutamol indicates a deterioration of the condition and the physician should be contacted promptly. Patients should be warned not to exceed the recommended dose. Increasing use of β2-agonists to control symptoms is usually a sign of worsening asthma. In worsening asthma it is inadequate to increase beta2-agonist use only, especially over an extended period of time. Instead, a reassessment of the patient's therapy plan is required and concomitant anti-inflammatory therapy should be considered (see DOSAGE AND ADMINISTRATION).
Patients should always carry their salbutamol aerosol or dry powder to use immediately if an episode of asthma is experienced.
To ensure administration of the proper dose of the drug, the patient should be instructed by the physician or other health professional in the proper use of the nebulizer system. The application of this inhalation system in children depends on the ability of the individual child to learn the proper use of the device. During inhalation, children should be assisted or supervised by an adult who knows the proper use of the device.
Use In Women
Pregnant Women: Salbutamol has been in widespread use for many years in human beings without apparent ill consequence. However, there are no adequate and well-controlled studies in pregnant women, and there is little published evidence of its safety in the early stages of human pregnancy. Administration of any drug to pregnant women should only be considered if the anticipated benefits to the expectant woman are greater than any possible risks to the fetus.
A reproduction study in CD-1 mice with salbutamol showed cleft palate formation in 5 of
111 (4.5%) fetuses at 0.25 mg/kg and in 10 of 108 (9.3%) fetuses at 2.5 mg/kg. None was observed at 0.025 mg/kg. Cleft palate also occurred in 22 of 72 (30.5%) fetuses treated with 2.5 mg/kg isoproterenol positive control. A reproduction study in Stride
Dutch rabbits revealed cranioschisis in 7 of 19 (37%) fetuses at 50 mg/kg, corresponding
to 78 times the maximum human oral dose of salbutamol.
Labour and Delivery: Although there have been no reports concerning the use of inhaled salbutamol formulations during labour and delivery, intravenously administered salbutamol given at high doses may inhibit uterine contractions. While this effect is extremely unlikely as a consequence of using inhaled formulations, it should be kept in mind. Oral salbutamol has been shown to delay preterm labour in some reports, but there are no well-controlled studies which demonstrate that it will stop preterm labour or prevent labour at term. When given to pregnant patients for relief of bronchospasm, cautious use of salbutamol products is required to avoid interference with uterine contractility.
Lactating Mothers: Since salbutamol is probably excreted in breast milk and because of its observed tumorigenicity in animal studies, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the benefit of the drug to the mother. It is not known whether salbutamol in breast milk has a harmful effect on the neonate.
Drug Interactions
Monoamine Oxidase Inhibitors or Tricyclic Antidepressants: Salbutamol should be administered with extreme caution to patients being treated with MAO inhibitors or tricyclic antidepressants since the action of salbutamol on the cardiovascular system may be potentiated.
Other Inhaled Sympathomimetic Bronchodilators or Epinephrine: Other inhaled sympathomimetic bronchodilators or epinephrine should not be used concomitantly with salbutamol. If additional adrenergic drugs are to be administered by any route to the patient using inhaled salbutamol, the adrenergic drugs should be used with caution to avoid deleterious cardiovascular effects. Such concomitant use must be individualized and not given on a routine basis. If regular coadministration is required then alternative therapy must be considered.
Beta-Blockers: Beta-adrenergic blocking drugs, especially the non-cardioselective ones, may effectively antagonize the action of salbutamol, and therefore, salbutamol and non-selective beta-blocking drugs, such as propranolol, should not usually be prescribed together.
Ipratropium Bromide: A small number of cases of acute angle closure glaucoma have been reported in patients treated with a combination of nebulized salbutamol and ipratropium bromide. Therefore, a combination of nebulized salbutamol with nebulized anticholinergics should be used cautiously. Patients should receive adequate instruction in correct administration and be warned not to let the solution or mist enter the eye.
Diuretics: The ECG changes and/or hypokalemia that may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with non-potassium sparing diuretics.
Digoxin: Mean decreases of 16 to 22% in serum digoxin levels were demonstrated after single dose intravenous and oral administration of salbutamol, respectively, to normal volunteers who had received digoxin for 10 days. The clinical significance of these findings for patients with obstructive airways disease who are receiving salbutamol and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate serum digoxin levels in patients who are currently receiving digoxin and salbutamol.
ADVERSE REACTIONS
The most frequent adverse reactions associated with salbutamol inhalation aerosol, dry powder or respiratory solution formulations are nervousness and tremor. In some patients inhaled salbutamol may cause a fine tremor of skeletal muscle, particularly in the hands. This effect is common to all beta2-adrenergic stimulants. Adaptation occurs during he first few days of dosing, and the tremor usually disappears as treatment continues. Headache, palpitations, transient muscle cramps, insomnia, nausea, weakness and dizziness have been reported as untoward effects following salbutamol administration. Peripheral vasodilation and a compensatory small increase in heart rate may occur in some patients.
Cardiac arrhythmias (including atrial fibrillation, supraventricular tachycardia dn extrasystoles)
have been reported, usually in susceptible patients.
Rarely reported adverse effects include drowsiness, flushing, restlessness, irritability, chest discomfort, difficulty in micturition, hypertension, angina, vomiting, vertigo, central nervous
stimulation, hyperactivity in children, unusual taste and drying or irritation of the oropharynx.
Immediate hypersensitivity reactions including angioedema, urticaria, bronchospasm, hypotension, rash, oropharyngeal edema, anaphylaxis and collapse have been reported very rarely.
As with other bronchodilator inhalation therapy, the potential for paradoxical bronchospasm should be kept in mind. If it occurs, the preparation should be discontinued immediately and alternative therapy instituted.
Potentially serious hypokalemia may result from beta2-agonist therapy, primarily from parenteral and nebulized routes of administration.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Overdosage may cause tachycardia, cardiac arrhythmia, hypokalemia, hypertension and, in extreme cases, sudden death. To antagonize the effect of salbutamol, the judicious use of a cardioselective beta-adrenergic blocking agent (e.g. metoprolol, atenolol) may be considered, bearing in mind the danger of inducing an asthmatic attack. Serum potassium levels should be monitored.
DOSAGE AND ADMINISTRATION
Dosage should be individualized, and the patient's response should be monitored by the prescribing physician on an ongoing basis.
In accordance with current Canadian asthma guidelines, if salbutamol is required more than three times a week (not including its use to prevent exercise-induced brochospasm), anti-inflammatory therapy (corticosteroids) should be a part of the regimen.
Increasing demand for salbutamol preparations in bronchial asthma is usually a sign of worsening asthma and indicates that the treatment plan should be reviewed.
If a previously effective dose fails to provide the usual relief, or if the effects of a dose last for less than three hours, patients should seek prompt medical advice since this is usually a sign of worsening asthma.
As there may be adverse effects associated with excessive dosing the dosage or frequency of administration should only be increased on medical advice. However, if a more severe attack has not been relieved by the usual dose, additional doses may be required. In these cases, patients should immediately consult their doctors or the nearest hospital.
NU-SALBUTAMOL Respirator Solutions (Salbutamol Sulfate Solution BP) may be preferred in the treatment of severe bronchospasm associated with exacerbations of chronic bronchitis and bronchial asthma.
NU-SALBUTAMOL Respirator Solution
Adults: In adults, 0.5 to 1.0 mL (2.5 to 5.0 mg of salbutamol) should be diluted in 2 to 5 mL or more of sterile normal saline. Treatment may be repeated 4 times a day, if necessary.
Children (5-12 years): The average dose for a single treatment is 0.25 to 0.5 mL (1.25 to 2.5 mg of salbutamol) diluted in 2 to 5 mL or more of sterile normal saline. For more refractory cases, the single dose of NU-SALBUTAMOL Respirator Solution may be increased to 1 mL (5 mg of salbutamol). Treatment may be repeated 4 times a day, if necessary.
NU-SALBUTAMOL Plastic Ampules
Adults: Patients requiring single doses of 2.5 or 5.0 mg may be administered the contents of a single unit dose (NU-SALBUTAMOL Plastic Ampules 2.5 or 5.0 mg of salbutamol). Treatment may be repeated 4 times a day, if necessary.
Children (5 - 12 years): Children requiring single doses of 2.5 mg may be administered the contents of a single unit dose (NU-SALBUTAMOL Plastic Ampules (Salbutamol Sulfate
Solution BP) 2.5 mg of salbutamol). For more refractory cases, children may use a 5 mg unit dose (see dosage above). Treatment may be repeated 4 times a day, if necessary.
If a more severe attack has not been relieved by a treatment, further treatments may be required.
In these cases, patients should immediately consult their doctor or the nearest hospital.
Use of NU-SALBUTAMOL Respirator Solutions
NU-SALBUTAMOL Respirator Solutions (Salbutamol Sulfate Solution BP) are to be used only under the direction of a physician employing either a respirator or nebulizer. NU-
SALBUTAMOL Respirator Solutions can be taken by either the nebuilization or intermittent
positive pressure ventilation method.
When used in a nebulizer, a mouthpiece or a face mask may be applied. The nebulizer should be connected to a compressed air or oxygen pump. Gas flow should be in the range of 6 to 10
L/minute. With an average volume of 3 mL, a single treatment lasts approximately 10 minutes.
It is advisable to prepare one dose at a time, or to utilize the unit dose (NU-SALBUTAMOL
Plastic Ampules) presentation. When administered through intermittent positive pressure ventilation, the inspiratory pressure is usually 10-20 cm H2O and the duration of administration varies from 5 to 20 minutes, depending upon the patient and the control of the apparatus. This length of administration provides a more gradual and more complete lysis of bronchospasm. In several cases it has been reported that the use of intermittent positive pressure ventilation in acute asthma attacks was related to lethal episodes of hypoxia and pneumothorax. This method of drug administration may be ineffective in patients with severe obstruction and may greatly increase airway resistance and possibly induce severe hypercapnia and hypoxia. It is highly desirable to monitor arterial blood gases during intermittent positive pressure ventilation therapy.
In hospitals, NU-SALBUTAMOL Respirator Solution, diluted (1:5 or 1:10) with sterile normal saline, should be used within 24 hours from time of dilution when stored at room temperature not exceeding 25°C or within 48 hours when stored under refrigeration.
Cleansing and maintenance of the nebulizer must be carefully exercised by strict adherence to the manufacturer's instructions.
The respirator solution must not be injected.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: salbutamol sulfate BP
Chemical Name: 2-t-butylamino-1-(4-hydroxy-3-hydroxymethylphenyl) ethanol sulfate
Structural Formula:
Molecular Formula: (C13H21NO3)2 . H2SO4
Molecular Weight: 576.7
Description: Salbutamol sulfate is a white, crystalline solid that is soluble in water.
Composition
NU-SALBUTAMOL Respirator Solution (Salbutamol Sulfate Solution BP)(sterile) contains salbutamol sulfate equivalent to 5 mg of salbutamol base per mL. In addition to salbutamol sulfate, NU-SALBUTAMOL Respirator Solution also contains the non-medicinal ingredients:
dilute sulfuric acid, benzalkonium chloride and water.
NU-SALBUTAMOL Plastic Ampules (Salbutamol Sulfate Solution BP) (unit dose) (sterile)
contain salbutamol sulfate equivalent to 2.5 or 5 mg of salbutamol base in 2.5 mL. It is an isotonic solution adjusted to pH 3.0 to 4.5. In addition to salbutamol sulfate, NU-
SALBUTAMOL Plastic Ampules also contain the non-medicinal ingredients: dilute sulfuric acid, sodium chloride and water.
Stability And Storage Recommendations
NU-SALBUTAMOL Respirator Solution: Store between 15-25°C. Protect from light.
NU-SALBUTAMOL Plastic Ampules: Store between 15-25°C. Protect from light.
Reconstituted NU-SALBUTAMOL Respirator Solution
In hospitals, NU-SALBUTAMOL Respirator Solution, diluted (1:5 or 1:10) with sterile normal saline, should be used within 24 hours from the time of dilution when stored at room temperature not exceeding 25°C or within 48 hours when stored under refrigeration. Instructions for the dilution of NU-SALBUTAMOL Respirator Solution are given below in the Dilution Table.
In the home, the unit dose preparation (NU-SALBUTAMOL Plastic Ampules), which is pre-diluted and ready to use, is the most convenient preparation. However, if the standard NU-
SALBUTAMOL Respirator Solution is used, it may be diluted with sterile normal saline immediately before use. Any unused solution in the nebulizer should be discarded.
| DILUTION TABLE FOR NU-SALBUTAMOL RESPIRATOR SOLUTION | ||
Dose (mg) of Salbutamol (per treatment) | Volume (mL) of NU-SALBUTAMOL Respirator Solution (per treatment) | Volume* (mL) of Sterile Normal Saline to be added as diluent |
| 1.25 2.5 5 | 0.25 0.50 1.00 | 2 - 5 mL or more 2 - 5 mL or more 2 - 5 mL or more |
*Approximate volumes only are given. Actual volume of diluent used may vary according to the type of nebulizer and individual patient needs.
AVAILABILITY OF DOSAGE FORMS
NU-SALBUTAMOL Respirator Solution (salbutamol sulfate solution BP) is available in bottles of 10 mL.
NU-SALBUTAMOL Plastic Ampules (Salbutamol Sulfate Solution BP)(Respirator Solution Unit
Dose) are available in:
Cartons of 10 and 20 (1 and 2 mg/mL).
INFORMATION FOR THE PATIENT
NU-SALBUTAMOL Respirator Solution
Information for the patient on the directions for use of NU-SALBUTAMOL Respirator Solution at home.
Please read this insert carefully before you start your medicine. For further information or advice, ask your doctor or pharmacist.
You may want to read this insert again. PLEASE DO NOT THROW IT AWAY until you have finished your medicine.
Introduction
Your doctor has prescribed a medicine called NU-SALBUTAMOL Respirator Solution
(salbutamol sulfate solution BP) to you. NU-SALBUTAMOL Respirator Solution is a bronchodilator medicine that your doctor has chosen to suit you and your condition. It can relieve chest tightness and wheezing if you have asthma or another chest illness. NU-
SALBUTAMOL Respirator Solution works by relieving spasm in the small air passages in the lungs and so helps to ease breathing problems. Please follow these instructions carefully. It is important that you use your NU-SALBUTAMOL Respirator Solution properly to ensure that you receive the maximum benefit from your medicine.
Precautions
Use your NU-SALBUTAMOL Respirator Solution only as directed by your doctor. He will tell you how often, and how much to use for a treatment. If you are not sure how much or when to take your medicine, ask your doctor or pharmacist. The action of NU-SALBUTAMOL
Respirator Solution (salbutamol sulfate solution BP) may last up to 6 hours and should last at least 4 hours. Call your doctor immediately if the effect of your usual dose lasts for less than three hours or if you suddenly get worse shortness of breath and you wheeze after using your NU-SALBUTAMOL Respirator Solution. Do not increase the dose or how often you take your medicine without informing your doctor. If symptoms get worse, tell your doctor as soon as possible.
When using NU-SALBUTAMOL Respirator Solution, other medicines (including asthma medicines) should only be used when prescribed by your doctor.
Important Points To Note Before Taking Your Medicine
- 1) Have you ever had to stop taking another medication for this illness because you were allergic to it or because it caused problems?
- 2) Are you having treatment for a thyroid condition?
- 3) Are you having treatment for raised blood pressure or a heart problem?
If the answer is YES to any of these questions, tell your doctor or pharmacist as soon as possible if you have not already done so.
Very occasionally some people feel a little shaky or have a headache after using NU-
SALBUTAMOL Respirator Solution. Muscle cramps can occur although these are quite rare.
These effects usually wear off with continued treatment. Tell your doctor but do not stop using the medicine unless told to do so.
If you accidentally take a LARGER DOSE THAN PRESCRIBED, you may notice that your heart is beating faster than usual and that you feel shaky. These effects usually wear off within a few hours but you should tell your doctor as soon as possible.
In the event of an EXCESSIVE overdosage, tell your doctor without delay or contact your hospital or nearest poison control centre.
Your doctor may decide not to prescribe this medicine during the first three months of pregnancy, nor if you are breast feeding a baby. However, there may be circumstances when your doctor advises you differently.
Remember: This medicine is for YOU only. Only your doctor can prescribe it for you. NEVER give it to someone else. It may harm that person even if his/her symptoms are the same as yours.
Children: NU-SALBUTAMOL Respirator Solution should be used under the supervision of an adult who understands the proper use of the NU-SALBUTAMOL Respirator Solution and of the nebulizer, and only as prescribed by the doctor.
Dosage
An effective treatment with NU-SALBUTAMOL Respirator Solution should last at least four hours. Call your doctor immediately if the effect of your usual dose lasts for less than three hours. If you regularly use NU-SALBUTAMOL Respirator Solution more than three times per week, and take no other asthma medication, you should talk to your doctor who may want to reassess your treatment plan. If you do not get relief from three or four treatments during a day, contact your physician. Do not exceed the prescribed dose or frequency of administration without contacting your physician.
Adults: In adults, 0.5 to 1.0 mL (2.5 to 5.0 mg of salbutamol) should be diluted in 2 to 5 mL or more of sterile normal saline. Treatment may be repeated 4 times a day, if necessary.
Children (5 - 12 years): The average dose for a single treatment is 0.25 to 0.5 mL (1.25 to 2.5 mg of salbutamol) diluted in 2 to 5 or more of sterile normal saline. For more refractory cases, the single dose of APO-SALVENT Respirator Solution may be increased to 1 mL (5 mg of salbutamol). Treatment may be repeated 4 times a day, if necessary.
Directions for Use
NU-SALBUTAMOL Respirator Solution is a bronchodilator, containing salbutamol 5 mg per mL. For proper administration, 0.25 to 1.0 mL (1.25 to 5.0 mg) of the solution is usually diluted with 2 to 5 mL of sterile normal saline.
Before starting treatment with this drug, be certain that you are completely familiar with the use and proper care of your nebulizer.
- 1) This solution is for inhalation only; do not inject or drink it.
- 2) Prepare the nebulizer for filling according to the manufacturer’s instructions.
- 3) Using a syringe, withdraw the prescribed dose of NU-SALBUTAMOL Respirator Solution from the bottle and add to the nebulizer chamber. Close the NU-SALBUTAMOL bottle as soon as the solution is drawn into the syringe.
- 4) Using a syringe, add the proper amount of Sterile Normal Saline Solution as directed by your physician.
- 5) Gently shake the nebulizer, assemble and use as directed.
- 6) Breathe calmly and evenly as much as possible until no more mist is formed in the nebulizer chamber. At this point, treatment is finished.
- 7)
Store your re-capped bottles of NU-SALBUTAMOL Respirator Solution and Sterile Normal
Saline Solution in the refrigerator until the next treatment. Do not open the bottles unnecessarily.
- 8) After use, discard any solution remaining in the nebulizer chamber. Clean the nebulizer according to the manufacturer’s instructions.
After Taking Your Medicine
If you notice a sudden worsening of your shortness of breath and wheeze shortly after taking your medicine, tell your doctor as soon as possible.
If the relief of wheezing or chest tightness is not as good as usual, tell your doctor as soon as
possible. It may be that your chest condition is worsening and you may need to add another type of medicine to your treatment.
General Instructions
In the home, unopened bottles of NU-SALBUTAMOL Respirator Solution should be stored at room temperature between 15 and 25ºC. NU-SALBUTAMOL Respirator Solution should be diluted immediately before use. Pre-diluted solutions of NU-SALBUTAMOL Respirator
Solution should not be stored.
Discard all NU-SALBUTAMOL Respirator Solution not used within one month after opening the bottle.
Follow all manufacturer's instructions for the proper care and maintenance of the nebulizer.
Store between 15 – 25˚C. Protect from light.
NU-SALBUTAMOL Plastic Ampules
Information for the patient on the directions for use of NU-SALBUTAMOL Plastic Ampules at home.
Please read this insert carefully before you start your medicine. For further information or advice, ask your doctor or pharmacist.
You may want to read this insert again. PLEASE DO NOT THROW IT AWAY until you have finished your medicine.
Introduction
Your doctor has prescribed a medicine called NU-SALBUTAMOL Plastic Ampules (salbutamol sulfate solution BP) to you. NU-SALBUTAMOL Plastic Ampules are a bronchodilator medicine that your doctor has chosen to suit you and your condition. It can relieve chest tightness and wheezing if you have asthma or another chest illness. NU-SALBUTAMOL Plastic Ampules work by relieving spasm in the small air passages in the lungs and so help to ease breathing problems. Please follow these instructions carefully. It is important that you use your NU-
SALBUTAMOL Plastic Ampules properly to ensure that you receive the maximum benefit from your medicine.
Precautions
Use your NU-SALBUTAMOL Plastic Ampules only as directed by your doctor. He will tell you how often, and how many ampules to use for a treatment. If you are not sure how much or when to take your medicine, ask your doctor or pharmacist. The action of NU-SALBUTAMOL Plastic
Ampules (salbutamol sulfate solution BP) may last up to 6 hours and should last at least 4 hours.
Call your doctor immediately if the effect of your usual dose lasts for less than three hours or if you suddenly get worse shortness of breath and you wheeze after using your NU-
SALBUTAMOL Plastic Ampules. Do not increase the dose or how often you take your medicine without informing your doctor. If symptoms get worse, tell your doctor as soon as possible.
When using NU-SALBUTAMOL Plastic Ampules, other medicines (including asthma medicines) should only be used when prescribed by your doctor.
Important Points To Note Before Taking Your Medicine
- 1) Have you ever had to stop taking another medication for this illness because you were allergic to it or because it caused problems?
- 2) Are you having treatment for a thyroid condition?
- 3) Are you having treatment for raised blood pressure or a heart problem?
If the answer is YES to any of these questions, tell your doctor or pharmacist as soon as possible if you have not already done so.
Very occasionally some people feel a little shaky or have a headache after using NU-
SALBUTAMOL Plastic Ampules. Muscle cramps can occur although these are quite rare. These effects usually wear off with continued treatment. Tell your doctor but do not stop using the medicine unless told to do so.
If you accidentally take a LARGER DOSE THAN PRESCRIBED, you may notice that your heart is beating faster than usual and that you feel shaky. These effects usually wear off within a few hours but you should tell your doctor as soon as possible.
In the event of an EXCESSIVE overdosage, tell your doctor without delay or contact your hospital or nearest poison control centre.
Your doctor may decide not to prescribe this medicine during the first three months of pregnancy, nor if you are breast feeding a baby. However, there may be circumstances when your doctor advises you differently.
Remember: This medicine is for YOU only. Only your doctor can prescribe it for you. NEVER give it to someone else. It may harm that person even if his/her symptoms are the same as yours.
Children: NU-SALBUTAMOL Plastic Ampules should be used under the supervision of an adult who understands the proper use of the NU-SALBUTAMOL Plastic Ampules and of the nebulizer, and only as prescribed by the doctor.
Dosage
An effective treatment with NU-SALBUTAMOL Plastic Ampules should last at least four hours.
Call your doctor immediately if the effect of your usual dose lasts for less than three hours.
If you regularly use NU-SALBUTAMOL Plastic Ampules (Salbutamol Sulfate Solution BP)
more than three times a week, and take no other asthma medication, you should talk to your doctor who may want to reassess your treatment plan. If you do not get relief from three or four treatments during a day, contact your physician. Do not exceed the prescribed dose or frequency of administration without contacting your physician.
Adults: Patients requiring single doses of 2.5 mg or 5.0 mg may be administered the contents of a single NU-SALBUTAMOL Plastic Ampule unit dose (2.5 or 5.0 mg of salbutamol). Treatment may be repeated 4 times a day if necessary.
Children (5 - 12 years): Children requiring single doses of 2.5 mg may be administered the contents of a single NU-SALBUTAMOL Plastic Ampule unit dose (2.5 mg of salbutamol). More refractory cases may use a 5 mg unit dose (see dosage above).
Directions For Use
NU-SALBUTAMOL Plastic Ampules are prediluted, preservative free unit doses of the bronchodilator salbutamol (2.5 or 5 mg salbutamol in 2.5 mL saline).
Before starting treatment with this drug, be sure that you are fully familiar with the use and proper care of your nebulizer.
- 1)
The contents of NU-SALBUTAMOL Plastic Ampules are to be inhaled from a nebulizer.
Do not open the foil pouch until the plastic ampules are required.
- 2) Prepare the nebulizer for filling according to the manufacturer's instructions.
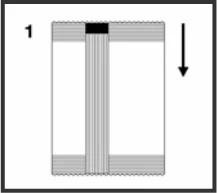
- 3)
To open the foil pouch, tear the foil at the centre and peel downwards (Diagram
1). Do not peel the foil wrap of the pouch completely. Remove the Plastic
Ampules. 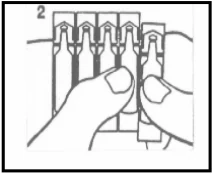
- 4) To detach a NU-SALBUTAMOL Plastic Ampule, push one plastic ampule downwards and away while holding the remaining plastic ampules securely
(Diagram 2). Return the remaining plastic ampules to the foil pouch and place the 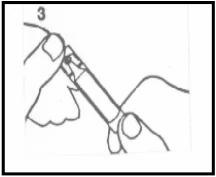
pouch back in the carton.
- 5)
Holding the top of the plastic ampule securely, twist the body to open (Diagram
3).
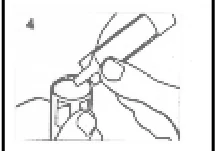
- 6) Place the open end of the plastic ampule well into the nebulizer cup and squeeze slowly (Diagram 4). Ensure the contents are emptied into the nebulizer cup.
- 7) Assemble the nebulizer and use as directed.
- 8) Breathe calmly and evenly as much as possible until no more mist is formed in the nebulizer chamber. At this point, treatment is finished.
- 9) After use discard any solution remaining in the nebulizer cup. Clean the nebulizer according to the manufacturer's instructions.
After Taking Your Medicine
If you notice a sudden worsening of your shortness of breath and wheeze shortly after taking your medicine, tell your doctor as soon as possible.
If the relief of wheezing or chest tightness is not as good as usual, tell your doctor as soon as possible. It may be that your chest condition is worsening and you may need to add another type of medicine to your treatment.
General Instructions
Open only one foil pouch at a time and use all 5 plastic ampules before opening the next foil pouch. Record the date when the foil pouch is first opened using a ballpoint pen. Always place
the foil pouch back in the carton after use.
Discard any unused plastic ampules in opened foil pouches after 3 months.
Follow all manufacturer's instructions for the proper care and maintenance of the nebulizer.
Store between 15-25°C. Protect from light.
PHARMACOLOGY
Animal Pharmacology
In vitro studies and in vivo pharmacologic studies have demonstrated that salbutamol has a preferential effect on beta2-adrenergic receptors compared with isoprenaline. While it is recognized that beta2-adrenergic receptors are the predominant receptors in bronchial smooth muscle, recent data indicate that there is a population of beta2-receptors in the human heart existing in a concentration between 10% and 50%. The precise function of these, however, is not yet established.
The pharmacologic effects of beta-adrenergic agonist drugs, including salbutamol, are at least in part attributable to stimulation through beta-adrenergic receptors of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3′,5′-adenosine monophosphate (cAMP). Increased cAMP levels are associated with relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells.
The muscle-relaxing effect of salbutamol was found to be more prolonged than when the effect was induced by isoprenaline. As suggested from the results of experiments in isolated animal tissues, salbutamol has been shown to produce a substantial bronchodilator effect in the intact animal. In the anesthetized guinea pig, salbutamol completely prevents acetylcholine-induced bronchospasm at the dose of 100 mcg/kg intravenously. Administration of salbutamol aerosol at a dose of 250 mcg for one minute to guinea pigs prevented acetylcholine-induced bronchospasm without any chronotropic effect. A prolonged bronchodilator effect of salbutamol compared to isoprenaline (in terms of mean times to dyspnea following acetylcholine challenge) was observed following oral administration of salbutamol to conscious guinea pigs. The protective action of salbutamol in this case persisted for up to six hours.
In anesthetized cats and dogs, salbutamol prevented the bronchospasm elicited by vagal stimulation without any significant effect on heart rate and blood pressure. Comparative tests of salbutamol and isoprenaline in isolated dog papillary muscle, guinea pig atrial muscle and human heart muscle have shown that the effect of salbutamol on beta1-adrenergic receptors in the heart is minimal.
In a number of studies using guinea pig atria, it was found that on a weight-to-weight basis, salbutamol was from 2,000 to 2,500 times less active in terms of inotropic effect and 500 times less active in terms of chronotropic effect than isoprenaline. Compared to orciprenaline, salbutamol was about 40 times less active in terms of inotropic effect and four times less potent in terms of chronotropic effect. Salbutamol has been shown to be one-fifth as potent a vasodilator in skeletal muscle as isoprenaline, as measured by effects on hind limb blood flow in the anesthetized dog. In the perfused rabbit ear, salbutamol was shown to possess only one-tenth the activity of isoprenaline in terms of vasodilating effect. In dogs, salbutamol was shown to increase coronary blood flow, which was subsequently shown to be the result of a direct coronary vasodilating effect of salbutamol.
In six dogs with right-sided cardiac by-pass, salbutamol, given at the dose of 25 mcg/kg, improved left ventricular efficiency and increased coronary blood flow. Recent studies in minipigs, rodents and dogs recorded the occurrence of cardiac arrhythmias and sudden death
(with histologic evidence of myocardial necrosis) when beta-agonists and methylxanthines were administered concurrently. The significance of these findings when applied to humans is currently unknown.
Animal studies show that salbutamol does not pass the blood brain barrier.
Clinical Pharmacology
In controlled clinical trials, the onset of improvement in pulmonary function was within 15 minutes, as determined by both maximum mid-expiratory flow rate (MMEF) and FEV1. MMEF measurements also showed that near maximum improvement in pulmonary function generally occurs within 60 to 90 minutes following two inhalations of salbutamol and that clinically significant improvement generally continues for three to four hours in most patients. In clinical trials some patients with asthma showed a therapeutic response (defined as maintaining FEV1 values 15% or more above baseline) that was still apparent at six hours. Continued effectiveness of salbutamol was demonstrated over a 13-week period in these same trials.
In clinical studies, two inhalations of salbutamol taken approximately 15 minutes before exercise
prevented exercise-induced bronchospasm, as demonstrated by the maintenance of FEV1 within
80/%/ of baseline values in the majority of patients. One of these studies also evaluated the duration of the prophylactic effect to repeated exercise challenges which was evident at four hours in the majority of patients and at six hours in approximately one third of the patients.
The ability of salbutamol to produce bronchodilation in humans has been demonstrated in many spirometric and plethysmographic studies. Following a challenge with acetylcholine aerosol, in a study examining the effects of salbutamol in airway resistance following challenge testing in 12 patients, the mean airway resistance increased 250%. After salbutamol aerosol (200 mcg), the mean airway resistance decreased to 78% of the initial value. Challenges with grass pollen or house dust aerosols in five and eight patients, respectively, increased activity resistance 265% and
255%, respectively. Administration of salbutamol decreased airway resistance to initial levels.
Controlled clinical studies and other clinical experience have shown that inhaled salbutamol, like other beta-adrenergic agonist drugs, can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms and/or ECG changes.
When salbutamol was administered as a metered-dose inhaler preparation to six normal volunteers, at doses of three or seven inhalations of 100 mcg, it was observed that three inhalations of salbutamol did not alter serum potassium while seven inhalations resulted in a decrease in serum potassium from 4.4 to 3.8 mEq/L. Thus, recommended doses of salbutamol aerosol (two inhalations) would not be expected to alter serum potassium levels.
A double-blind placebo controlled comparison of the bronchodilator effects of salbutamol, inhaled either as a dry powder or as a conventional aerosol, was carried out in 20 adult patients with chronic bronchial asthma. All treatments were significantly better than placebo. There was no significant difference between responses to any of the three dry powder doses (100 mcg, 200 mcg, 300 mcg) but the average response to 200 mcg aerosol was significantly greater than that to
200 mcg dry powder.
Salbutamol dry powder (400 mcg) and conventional aerosol (200 mcg) were administered to 10 adult asthmatics. There was no statistically significant difference between the improvement in
FEV1 obtained 10 minutes after administration of either the dry powder or the aerosol formulation.
Salbutamol was administered as a dry powder (50 mcg, 100 mcg, 200 mcg, 400 mcg) and as an aerosol (200 mcg) to 10 adult asthmatics. The greatest responses were obtained with salbutamol
400 mcg administered as a dry powder. No effect on blood pressure or pulse rate was observed.
Daily improvements in PEFR in response to single doses of inhaled salbutamol (200 mcg dry powder and 100 mcg conventional aerosol) was measured in nine asthmatic children (aged 5-13 years) for six weeks. The order of administration of powder and aerosol was reversed at the end of three weeks. There was no statistically significant difference between the increase in PEFR 5 minutes after either 200 mcg dry powder or after 100 mcg aerosol. The total mean increases in
PEFR 10 minutes after inhalation of powder and aerosol (weeks 1-3) and inhalation of aerosol and powder (weeks 4-6) were not significantly different.
In a double-blind placebo-controlled study, salbutamol (200 mcg) completely prevented exercise-induced bronchospasm in three of five children, and greatly reduced the effects in the other two patients.
Administration of 10 mg salbutamol as a 0.5% solution through IPPV from a Bennett ventilator, given in a 3 minute period, resulted in a 40% increase of FEV1 with maximum effect in about 90 minutes. The average duration of effect was 3 hours. The heart rate had an average increase of 9 beats/minute, peaking after 25 minutes, and lasting for about 36 minutes. No ECG changes were observed.
Salbutamol solution 0.5% was self-administered at home via a portable nebulizer, without IPPV, by 28 adult patients with severe chronic asthma. The dose was 0.5 mL (2.5 mg salbutamol) in 4.5 mL normal saline, 2 to 4 times daily, and the duration of treatment period ranged from 0.9 to 2.7 years (mean 1.7 years). For each patient the treatment period was compared retrospectively with a control period of the same duration preceding nebulizer therapy. No statistically significant differences between treatment and control periods were found for pulmonary function tests performed before and after 5 puffs of a salbutamol pressurized aerosol, or for number of out-patient emergency department visits, hospitalizations, sick leaves, and days hospitalized.
However, there were significant reductions during the treatment period in the duration of sick leaves and medical ward treatments, while half of the patients reported that it was easier to sleep and two-thirds said it was easier to exercise.
In 10 pediatric studies, a total of 189 patients up to 14 years of age were treated with salbutamol solution 0.5% administered via a portable nebulizer. In most cases, the dose was between 0.5 mL and 1.0 mL per treatment, diluted with normal saline, bringing the total volume to 2.0 mL.
Children with asthma had very good results from the treatment, while children with bronchitis or bronchiolitis did not respond well. Salbutamol was very well tolerated in these studies. One
author reported 2 cases of skeletal muscle tremor, but drew attention to the fact that both patients received concurrent oral bronchodilator. Otherwise, the only reported side effect was an occasional mild tachycardia.
Prolonged use of salbutamol in most patients caused no significant changes in ECG pattern, blood sugar, liver and kidney functions and hematological values.
The hemodynamic effects of intravenous salbutamol were studied in patients with mitral valve disease. At the dose of 1 mcg/kg, salbutamol reduced mean aortic pressure by 7 mmHg, increased the cardiac output by 0.6 L/minute and reduced systemic vascular resistance by 7 units.
It caused no change in left ventricular ejection time. At the dose of 2 mcg/kg, salbutamol increased the mean oxygen uptake by 21 mL/minute, narrowing the mean arteriovenous oxygen difference by 10 mL/minute. Salbutamol has no effect on the pulmonary ventilation/perfusion ratio, therefore, unlike isoprenaline, it does not increase hypoxia during acute asthmatic attacks.
Metabolism
After inhalation of recommended doses of salbutamol, plasma drug levels are very low. When
100 mcg of tritiated salbutamol aerosol was administered to two normal volunteers, plasma levels of drug-radioactivity were insignificant at 10, 20 and 30 minutes following inhalation. The plasma concentration of salbutamol may be even less as the amount of plasma drug-radioactivity does not differentiate salbutamol from its principal metabolite, a sulphate ester. In a separate study, plasma salbutamol levels ranged from less than 0.5 ng/mL to 1.6 ng/mL in ten asthmatic children one hour after inhalation of 200 micrograms of salbutamol.
Five asthmatic patients were given tritium-labelled salbutamol from the nebulizer of an intermittent positive pressure ventilator. In all patients, there was a rapid initial rise in plasma concentration of total radioactivity. In 4 of the 5 patients, there was a further rise in plasma concentration to a peak at 2 to 4 hours. All patients showed an improvement in FEV1 with peak improvement at 30 minutes to 2 hours. An average 12.5% of the initial dose was recovered in the urine. Of the radioactivity recovered, 88% was recovered in the first 24 hours. The metabolite in the urine was the same as that in the plasma. During the first 2 hours, the ratio of free salbutamol to metabolite averaged 2:1, whereas by 8 hours, the ratio was 9:11, and thereafter this reversed ratio was maintained.
Approximately 10% of an inhaled salbutamol dose is deposited in the lungs. Eighty-five percent of the remaining salbutamol administered from a metered-dose inhaler is swallowed, however, since the dose is low (100 to 200 mcg), the absolute amount swallowed is too small to be of
clinical significance. Salbutamol is only weakly bound to plasma proteins. Results of animal studies indicate that following systemic administration, salbutamol does not cross the blood-brain barrier but does cross the placenta using an in vitro perfused isolated human placenta model. It has been found that between 2% and 3% of salbutamol was transferred from the maternal side to the fetal side of the placenta.
Salbutamol is metabolized in the liver. The principal metabolite in humans is salbutamo-o-sulphate, which has negligible pharmacologic activity. Salbutamol may also be metabolized by oxidative deamination and/or conjugation with glucuronide.
Salbutamol is longer acting than isoprenaline in most patients by any route of administration because it is not a substrate for the cellular uptake processes for catecholamines nor for catechol-
O-methyl transferase. Salbutamol and its metabolites are excreted in the urine (>80%) and the feces (5% to 10%). Plasma levels are insignificant after administration of aerosolized salbutamol;
the plasma half-life ranges from 3.8 to 7.1 hours.
TOXICOLOGY
Acute Toxicity
| Species (n) | Oral LD50 | Intravenous LD50 |
| Mouse (10) Rat (10) | >2000 mg/kg >2000 mg/kg | 72 mg/kg 60 mg/kg |
| Rat (n) | Intraperitoneal LD50 |
| Newborn (155) Weanling (100) 2 week old (90) | 216 mg/kg 524 mg/kg 437 mg/kg |
The rate of respiration in test animals initially increased, but subsequently became abnormally slow and deep. Death, preceded by convulsions and cyanosis, usually occurred within four hours after drug administration.
Rabbits, cats and dogs survived a single dose of 50 mg/kg salbutamol.
Intermediate (Four Months) Toxicity
Rats received salbutamol twice daily, in oral doses from 0.5 to 25 mg/kg, on an increasing scale.
The only significant hematological changes were a small increase in hemoglobin and packed cell volume. BUN and SGOT values were elevated while blood glucose and plasma protein levels remained unchanged. Pituitaries had increased amount of PAS-positive material in the cleft at the higher dose levels.
Salbutamol was given to dogs twice daily, in oral doses from 0.05 to 12.5 mg/kg, on an increasing scale. The rate of increase of hemoglobin and packed cell volume was depressed, particularly at higher doses. Leukocyte count decreased after 16 weeks of treatment at each dose level. Platelet count was increased after 8 weeks at the highest dose. No significant biochemical effects were observed. The only significant histological change was the appearance of corpora amylacea in the stomach which was attributed to altered mucous secretion. Inhalation of 1000 mcg of salbutamol aerosol twice daily for 3 months did not produce any morphological changes in lungs, trachea, lymph nodes, liver or heart.
Long-Term Toxicity
Fifty female, Charles River CD Albino rats received salbutamol orally at 2, 10, and 50 mg/kg/day for 104 weeks; 50 female Charles River CD Sprague-Dawley derived rats received 20 mg/kg/day salbutamol orally for 50 weeks, and 50 female Charles River Long-Evans rats received 20 mg/kg/day salbutamol orally for 96 weeks. These rat studies demonstrated a dose-related incidence of mesovarian leiomyomas. No similar tumors were seen in mice.
Mutagenicity
In vitro tests involving 4 microorganisms revealed no mutagenic activity.
Carcinogenicity
In a two-year study in the rat, salbutamol sulfate caused a significant dose-related increase in the incidence of benign leiomyomas of the mesovarium at doses corresponding to 111, 555 and
2,800 times the maximum human inhalation dose. In another study, the effect was blocked by the co-administration of propranolol. The relevance of these findings to humans is not known. An
18-month study in mice and a lifetime study in hamsters revealed no evidence of tumorigenicity.
Teratogenicity Studies
Salbutamol has been shown to be teratogenic in mice when given in doses corresponding to
14 times the human aerosol dose; when given subcutaneously in doses corresponding to 0.2 times the maximum human (child weighing 21 Kg) oral dose; and when given subcutaneously in doses corresponding to 0.4 times the maximum human oral dose.
A reproduction study in CD-1 mice given salbutamol at doses of 0.025, 0.25 and 2.5 mg/kg subcutaneously, corresponding to 1.4, 14 and 140 times the maximum human aerosol dose respectively, showed cleft palate formation in 5 of 111 (4.5%) fetuses at 0.25 mg/kg and in 10 of
108 (9.3%) fetuses at 2.5 mg/kg. No cleft palates were observed at a dose of 0.025 mg/kg salbutamol. Cleft palate occurred in 22 of 72 (30.5%) fetuses treated with 2.5 mg/kg isoprenaline
(positive control).
In rats, salbutamol treatment given orally at 0.5, 2.32, 10.75 and 50 mg/kg/day throughout pregnancy resulted in no significant fetal abnormalities. However, at the highest dose level there was an increase in neonatal mortality. Reproduction studies in rats revealed no evidence of impaired fertility.
Salbutamol had no adverse effect when given orally to Stride Dutch rabbits, at doses of 0.5, 2.32 and 10.75 mg/kg/day throughout pregnancy. At a dose of 50 mg/kg/day, which represents 2800 times the maximum human inhalation dose, cranioschisis was observed in 7 of 19 (37%) fetuses.
BIBLIOGRAPHY
- 1) Anderson PB, Goude A, Peake MD. Comparison of salbutamol given by intermittent positive-pressure breathing and pressure-packed aerosol in chronic asthma. Thorax 1982; 37: 612-616.
- 2) Becker AB, Nelson NA, Simons FER. Inhaled salbutamol (albuterol) vs injected epinephrine in the treatment of acute asthma in children. J Pediatr 1983; 102: 465-469.
- 3) Boe J, Wicksell M. Domiciliary nebulized salbutamol solution in the treatment of severe asthma bronchiale. Curr Ther Res 1982; 32; 555-565.
- 4) Cayton RM, Webber B, Paterson JW, Clark TJH. A comparison of salbutamol given by pressure-packed aerosol or nebulization via IPPB in acute asthma. Br J Dis Chest 1978; 72: 222-224.
- 5) Choo-Kang YFJ, Grant IWB. Comparison of two methods of administering bronchodilator aerosol to asthmatic patients. Br Med J 1975; 2: 119-120.
- 6)
Christensson P, Arborelius M, Lilja B. Salbutamol inhalation in chronic asthma bronchiale;
dose aerosol vs jet nebulizer. Chest 1981; 79: 416-419.
- 7) Douglas JG, Leslie MJ, Crompton GK, Grant IWB. A comparative study of two doses of salbutamol nebulized at 4 and 8 litres per minute in patients with chronic asthma. Br J Dis Chest 1986; 80: 55-58.
- 8)
Evans ME, Walker SR, Brittain RT, Paterson JW. The metabolism of salbutamol in man.
Xenobiotica 1973; 3: 113-120.
- 9) Fergusson RJ, Carmichael J, Rafferty P, Willery RF, Crompton GK, Grant IWB. Nebulized salbutamol in life-threatening asthma: is IPPB necessary? Br J Dis Chest 1983; 77: 255-261.
- 10) Grimwood K, Johnson-Barrett JJ, Taylor B. Salbutamol: Tablets, inhalation powder, or nebulizer? Br Med J 1981; 282: 105-106.
- 11)
Harrison BA, Pierce RJ. Comparison of wet and dry aerosol salbutamol. Aust NZ J Med
1983; 13: 29-33.
- 12) Konig P. Treatment of severe attacks of asthma in children with nebulized beta2-adrenergic agents. Ann Allergy 1978; 40: 185-188.
- 13)
Lenney W, Milner AD. At what age do bronchodilator drugs work? Arch Dis Child 1978;
53: 532-535.
- 14) Neville A, Palmer JBD, Gaddie J, May CS, Palmer KNV, Murchison LE. Metabolic effects of salbutamol: comparison of aerosol and intravenous administration. Br Med J 1977; 1: 413-414.
- 15)
Radford M. Effect of salbutamol in infants with wheezy bronchitis. Arch Dis Child 1975;
50: 535-538.
- 16)
Review and evaluation of pharmacology and toxicology data for NDA 18-473, April 21,
1980.
- 17)
Ruffin RE, Obminski G, Newhouse MT. Aerosol salbutamol administration by IPPB:
lowest effective dose. Thorax 1978; 33: 689-693.
- 18) Rutter N, Milner AD, Hiller EJ. Effect of bronchodilators on respiratory resistance in infants and young children with bronchiolitis and wheezy bronchitis. Arch Dis Child 1975; 50: 719-722.
- 19)
Shenfield GM, Evans ME, Walker SR, Paterson JW. The fate of nebulized salbutamol
(albuterol) administered by intermittent positive pressure respiration to asthmatic patients. Am Rev Resp Dis 1973; 108: 501-505.
- 20) Shenfield GM, Evans ME, Paterson JW. The effect of different nebulizers with and without intermittent positive pressure breathing on the absorption and metabolism of salbutamol. Br J Clin Pharmacol 1974; 1: 295-300.
- 21) Tal A, Bavilski C, Yohai D, Bearman JE, Gorodischer R, Moses SW. Dexamethasone and salbutamol in the treatment of acute wheezing in infants. Pediatrics 1983; 71: 13-18.
- 22) Tarala R, Madsen BW, Paterson JW. Comparative efficacy of salbutamol by pressurized aerosol and wet nebulizer in acute asthma. Br J Clin Pharmacol 1980; 10: 393-397.
- 23) Walker SR, Evans ME, Richards AJ, Paterson JW. The clinical pharmacology of oral and inhaled salbutamol. Clin Pharmacol Ther 1972; 13: 861-867.
- 24) Walters EH, Crockroft A, Griffiths T, Rocchiccioli K, Davies BH. Optimal dose of salbutamol respiratory solution: comparison of three doses with plasma levels. Thorax 1981; 36: 625-628.
- 25) Webber BA, Collins JV, Branthwaite MA. Severe acute asthma: a comparison of three methods of inhaling salbutamol. Br J Dis Chest 1982; 76: 69-74.
- 26) Webber BA, Shenfield GM, Paterson JW. A comparison of three different techniques for giving nebulized albuterol to asthmatic patients. Am Rev Resp Dis 1974; 109: 293-295.
- 27)
Wood DO, Chandler D, Dugdale AE. Two methods of administering nebulized salbutamol.
A controlled study. Aust Pediatr J 1978; 14: 150-153.
- 28)
CPS Monograph. Ventodisk® Blisters, Ventolin® Respirator Solution/Ventolin® Nebules P.F.
(Salbutamol) – Bronchodilator, Beta2-adrenergic Stimulant. IN: Welbanks L, Bisson R, Bergeron D, et al, eds. Compendium of Pharmaceuticals and Specialties. Canadian Pharmacists Association, Ottawa, 2004; pp. 2150 – 2151.
- 29)
Product Monograph. Ventolin® Respirator Solutions/Ventolin® Nebules P.F.
Bronchodilator, Beta2-adrenergic Stimulant. GlaxoSmithKline Inc., Mississauga, Ontario, September 27, 2002.