


Product Monograph - Nuceiva
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 12/2022 |
|---|---|
| 13 PHARMACEUTICAL INFORMATION | 08/2024 |
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ............................................................................ 2
TABLE OF CONTENTS .................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................... 4
1 Indications........................................................................................................... 4
1.1 Pediatrics ................................................................................................... 4
1.2 Geriatrics ................................................................................................... 4
2 CONTRAINDICATIONS ....................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................ 4
4 DOSAGE AND ADMINISTRATION ..................................................................... 5
4.1 Dosing Considerations ............................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .......................................... 5
4.3 Reconstitution ............................................................................................ 5
4.4 Administration ............................................................................................ 5
5 OVERDOSAGE .................................................................................................... 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............. 7
7 WARNINGS AND PRECAUTIONS ...................................................................... 7
7.1 Special Populations ................................................................................... 9
7.1.1 Pregnant Women ....................................................................................... 9
7.1.2 Breast-feeding ......................................................................................... 10
7.1.3 Pediatrics ................................................................................................. 10
7.1.4 Geriatrics ................................................................................................. 10
8 ADVERSE REACTIONS .................................................................................... 10
8.1 Adverse Reaction Overview ..................................................................... 10
8.2 Clinical Trial Adverse Reactions .............................................................. 10
8.5 Post-Market Adverse Reactions .............................................................. 11
9 DRUG INTERACTIONS ..................................................................................... 12
9.2 Drug Interactions Overview ...................................................................... 12
9.3 Drug-Behavioral Interactions ................................................................... 12
9.4 Drug-Drug Interactions............................................................................. 12
9.5 Drug-Food Interactions ............................................................................ 13
9.6 Drug-Herb Interactions............................................................................. 13
9.7 Drug-Laboratory Test Interactions ........................................................... 13
10 CLINICAL PHARMACOLOGY ........................................................................... 13
10.1 Mechanism of Action................................................................................ 13
10.2 Pharmacodynamics ................................................................................. 14
10.3 Pharmacokinetics .................................................................................... 14
11 STORAGE, STABILITY AND DISPOSAL ......................................................... 14
12 SPECIAL HANDLING INSTRUCTIONS ............................................................ 14
PART II: SCIENTIFIC INFORMATION ......................................................................... 14
13 PHARMACEUTICAL INFORMATION ............................................................... 14
14 CLINICAL TRIALS ............................................................................................. 15
14.1 Trial Design and Study Demographics .................................................... 15
14.2 Study Results ........................................................................................... 16
15 MICROBIOLOGY ............................................................................................... 17
16 NON-CLINICAL TOXICOLOGY ......................................................................... 17
PATIENT MEDICATION INFORMATION ..................................................................... 19
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
NUCEIVA prabotulinumtoxinA for injection is indicated for:
- The temporary improvement in the appearance of moderate to severe glabellar lines in adult patients < 65 years of age.
1.1 Pediatrics
Pediatrics (< 18 years of age): Nuceiva is not recommended for use in children.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): The clinical data for subjects ≥ 65 years of age are limited. No specific dose adjustment is required for use in the elderly.
2 CONTRAINDICATIONS
Nuceiva is contraindicated in patients:
- who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging;
- with infection or inflammation at the proposed injection sites.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- DISTANT SPREAD OF TOXIN EFFECT: The effects of Nuceiva and all botulinum toxin products may spread from the area of injection to produce symptoms consistent with botulinum toxin effects. These symptoms have been reported hours to weeks after injection. Swallowing and breathing difficulties can be life-threatening and there have been reports of death. The risk of symptoms is probably greatest in children treated for spasticity but symptoms can occur in adults, particularly in those patients who have underlying conditions that would predispose them to these symptoms.
- The term “unit” upon which dosing is based is a specific measurement of toxin activity that is unique to EVOLUS’ formulation of Nuceiva. Therefore, the “units” used to describe Nuceiva’s activity are different from those used to describe that of other botulinum toxin preparations and the units representing Nuceiva’s activity are not interchangeable with other products.
- Nuceiva should only be administered by physicians with the appropriate qualifications and experience in the use of botulinum toxins.
- Follow the recommended dosage and frequency of administration for Nuceiva (See WARNINGS AND PRECAUTIONS, General and DOSAGE AND ADMINISTRATION).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- For Intramuscular Use Only
- The potency Units of Nuceiva are specific to the preparation and assay method utilized. They are not interchangeable with other preparations of botulinum toxin products and, therefore, Units of biological activity of Nuceiva cannot be compared to or converted into Units of any other botulinum toxin products assessed with any other specific assay method.
- Treatment should be administered at no more than the recommended dose and interval.
- Injection intervals of Nuceiva should be no more frequent than every three months.
4.2 Recommended Dose and Dosage Adjustment
Glabellar Lines
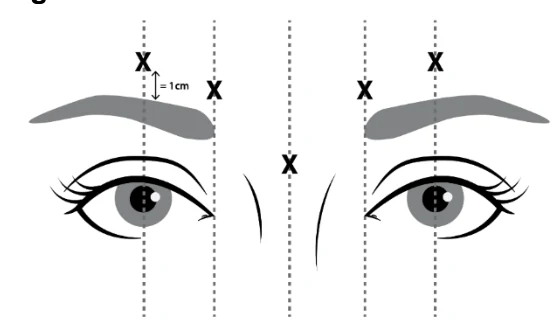
Four (4) Units should be injected intramuscularly at each of five injection sites, 2 in each corrugator muscle and 1 in the procerus muscle for a total dose of 20 Units (see Figure 1).
Typically, Nuceiva induces chemical denervation of the injected muscles two days after injection, increasing in effect during the first two weeks.
4.3 Reconstitution
Each 100 Unit vial of Nuceiva is to be reconstituted with 2.5 mL of 0.9% sterile, preservative-free, saline. As per the dilution table below, the 2.5 mL of sodium chloride 0.9% solution for injection is to be drawn into a sterile syringe and mixed in the vial in order to obtain a reconstituted solution at a concentration of 4 Units/0.1 mL.
Table 1. Reconstitution
| Vial Size | Volume of Diluent to be Added to Vial | Nominal Concentration per mL |
| 100 Unit Vial | 2.50 mL | 4 Units/0.1 mL |
Inject the diluent into the vial gently. Discard the vial if a vacuum does not pull the diluent into the vial. Gently mix Nuceiva with the saline by rotating the vial.
Once reconstituted, Nuceiva should be stored in a refrigerator at 2–8°C and used within 24 hours. Do not freeze reconstituted Nuceiva. Discard the vial and needle in accordance with local regulations.
4.4 Administration
Glabellar facial lines arise from the activity of the corrugator and orbicularis oculi muscles. These muscles move the brow medially, and the procerus and depressor supercilii pull the brow inferiorly. This creates a frown or “furrowed brow”. The location, size, and use of the muscles can vary among individuals. Lines induced by facial expression occur perpendicular to the direction of action of contracting facial muscles.
Physicians administering Nuceiva must understand the relevant neuromuscular and/or orbital anatomy of the area involved and any alterations to the anatomy due to prior surgical procedures.
In order to reduce the incidence of eyelid ptosis the following steps should be taken:
- Avoid injection near the levator palpebrae superioris, particularly in patients with larger brow depressor complexes.
- Lateral corrugator injections should be placed at least 1 cm above the bony supraorbital ridge.
- Do not inject toxin closer than 1 centimeter above the central eyebrow.
- Ensure the injected volume/dose is accurate and where feasible kept to a minimum.
- The use of one vial for more than one injection session or one patient is not recommended because the product and diluent do not contain a preservative.
Following reconstitution (see below), the needle used could remain in the vial and the required amount of solution drawn up with a new sterile syringe suitable for injection, preferably a 1.0mL tuberculin syringe. Draw at least 0.5 mL of the properly reconstituted toxin into the syringe and expel any air bubbles seen in the barrel. Disconnect the syringe and attach a sterile 30 gauge needle.
Inject a dose of 0.1 mL (4 Units) intramuscularly into each of 5 sites, the inferomedial and superior middle of each corrugator and 1 in the mid-line of the procerus muscle for a total dose of 20 Units (see Figure 1).
Nuceiva vials are for single-use only. Discard remaining solution.
Figure 1.
5 OVERDOSAGE
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
Excessive doses of Nuceiva may be expected to produce neuromuscular weakness with a variety of symptoms. Respiratory support may be required when excessive doses cause paralysis of respiratory muscles. In the event of overdose, the patient should be medically monitored for symptoms of excessive muscle weakness or muscle paralysis. Symptomatic treatment may be necessary.
Symptoms of overdose are not likely to be present immediately following injection. Should accidental injection or oral ingestion occur, the person should be medically supervised for several weeks for signs and symptoms of excessive muscle weakness or paralysis.
In the event of suspected or actual cases of botulinum toxin poisoning, please contact your local Health Department to process a request for antitoxin and also notify the company. However, the antitoxin will not reverse any botulinum toxin-induced effects already apparent by the time of antitoxin administration.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2. Dosage Forms, Strengths, Composition and Packaging
Each vial of Nuceiva contains 100 Units of botulinum type A neurotoxin complex, 0.5 mg of human serum albumin, and 0.9 mg of sodium chloride in a sterile, vacuum-dried form without a preservative.
The top and bottom flaps of the Nuceiva cartons have a tamper-evident seal. Vials of the Nuceiva have a holographic film. In order to see the hologram, rotate the vial back and forth between your fingers under a desk lamp or fluorescent light source. If the tamper-evident seal is not intact and present on both ends of the carton or if you do not see the hologram, do not use the product.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Use Nuceiva only as directed. Injection intervals of Nuceiva should be no more frequent than every three months. Indication-specific dosage and administration recommendations should be followed.
Do not use dosage recommendations and potency Units applied to other botulinum toxin products when using Nuceiva. Do not exceed the recommended dosage and frequency of administration of Nuceiva.
The safe and effective use of Nuceiva depends upon proper storage of the product, selection of the correct dose, reconstitution, and injection technique.
Caution should be exercised when administering Nuceiva to patients with neuromuscular junction disorders or when excessive weakness or atrophy is present in the target muscle, and in patients with prolonged bleeding times, surgical alterations to the facial anatomy, marked
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intramuscular | Sterile, vacuum-dried powder for reconstitution; 100 Units per vial | Human Serum Albumin, Sodium Chloride |
facial asymmetry, inflammation at the injection site(s), ptosis, excessive dermatochalasis, deep dermal scarring, or thick sebaceous skin.
Local muscle weakness represents the expected pharmacological action of botulinum toxin in muscle tissue. Muscle weakness remote to the site of injection and other serious adverse effects have been very rarely reported in the cosmetic applications. Progressive signs or symptoms of muscular weakness remote to the site of injection may include ptosis and diplopia, as well as other serious adverse effects including swallowing and speech disorders.
Patients with a history of underlying neurologic disorders, dysphagia and/or aspiration are at a greater risk of these effects and should be treated with extreme caution. The botulinum toxin product should be used under specialist supervision in these patients and should only be used if the benefit of treatment is considered to outweigh the risk.
Patients or caregivers should be advised to seek immediate medical care if swallowing, speech or respiratory disorders arise.
This product contains human serum albumin, a derivative of human blood. Based on effective donor screening and product manufacturing processes, it carries an extremely remote risk for transmission of viral diseases. The theoretical risk for transmission of Creutzfeldt-Jakob disease (CJD) also is considered extremely remote. No known cases of transmission of viral diseases or CJD have been identified for human serum albumin.
Carcinogenesis and Mutagenesis
Animal studies to evaluate the carcinogenic and genotoxic potential of Nuceiva have not been conducted.
Cardiovascular
There have been reports following administration of other botulinum toxin products of adverse events involving the cardiovascular system, including arrhythmia and myocardial infarction, some with fatal outcomes. Some of these patients had risk factors including pre-existing cardiovascular disease. Use caution when administering to patients with pre-existing cardiovascular disease.
Immune
As with all biologic products, an anaphylactic reaction may occur. Necessary precautions should be taken and epinephrine should be available. Serious and/or immediate hypersensitivity reactions such as anaphylaxis and serum sickness have been rarely reported, as well as other manifestations of hypersensitivity including urticaria, soft tissue edema, and dyspnea.
Treatment with botulinum toxins may result in the formation of antibodies that may reduce the effectiveness of subsequent treatments by inactivating biological activity of the toxin. The results from some studies suggest that botulinum toxin injections at more frequent intervals or at higher doses may lead to greater incidence of antibody formation.
The presence of antibotulinum antibodies in subjects receiving Nuceiva was evaluated in two single dose Phase III studies (EV-001and EV-002) and one repeat dose Phase II study (EV-006). There were no cases of seroconversion with Nuceiva. One subject who had a history of exposure to botulinum toxin and tested positive at baseline did not respond to treatment.
The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies to Nuceiva with the incidence of antibodies to other products may be misleading.
Monitoring and Laboratory Tests
There are no specific requirements for laboratory test monitoring when patients are treated with Nuceiva.
Neurologic
Caution should be exercised when administering Nuceiva to individuals with peripheral motor neuropathy (e.g., amyotrophic lateral sclerosis or other motor neuropathy), facial palsy or neuromuscular junctional disorders (e.g., myasthenia gravis or Lambert-Eaton syndrome). Patients with neuromuscular disorders may be at an increased risk of clinically significant systemic effects such as severe dysphagia and respiratory compromise. There have been rare cases of administration of a botulinum toxin to patients with known or unrecognized neuromuscular junction disorders where the patients have shown extreme sensitivity to the systemic effects of typical clinical doses. In some of these cases, dysphagia has lasted several months and required placement of a gastric feeding tube.
Ophthalmologic
Caution should be exercised when administering Nuceiva to individuals with eye disorders, including dry eye and eyelid oedema.
Risk of ptosis can be mitigated by careful examination of the upper lid for separation or weakness of the levator palpebrae muscle (true ptosis) and evaluation of the range of lid excursion while manually depressing the frontalis to assess compensation.
The potential risk of localized muscle weakness or visual disturbances linked with the use of Nuceiva may temporarily impair the ability to drive or operate machinery.
Skin
Caution should be exercised when administering Nuceiva to patients with inflammation at the injection site(s), deep dermal scarring, or thick sebaceous skin. As is expected for any injection procedure, localized pain, inflammation, paresthesia, hypoesthesia, tenderness, swelling/edema, erythema, localized infection, bleeding and/or bruising have been associated with injections.
7.1 Special Populations
7.1.1 Pregnant Women
There is limited data from the use of Botulinum toxin Type A in pregnant women. Animal studies do not indicate direct or indirect harmful effects with respect to pregnancy, embryo/fetal development, parturition or postnatal development other than at high doses causing maternal toxicity. The potential risk to pregnant women is unknown. Nuceiva should not be used during pregnancy. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be informed of the potential risks, including abortion or fetal malformations, which have been observed in rabbits.
7.1.2 Breast-feeding
It is unknown if the drug is excreted in human milk. The excretion of Nuceiva in milk has not been studied in animals. Because many drugs are excreted in human milk precaution should be exercised. The use of Nuceiva during lactation is not recommended.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Nuceiva is not recommended for use in children.
7.1.4 Geriatrics
The clinical data for subjects ≥ 65 years of age are limited. No specific dose adjustment is required for use in the elderly.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse reactions may occur within the first few days following injection and while generally transient may have a duration of several months.
Local muscle weakness represents the expected pharmacological action of botulinum toxin in muscle tissue; however, weakness of adjacent muscles associated with local diffusion and/or injection technique has been reported. Muscle weakness remote to the site of injection and other serious adverse effects have been very rarely reported in the cosmetic application.
As is expected for any injection procedure, localized pain, inflammation, paresthesia, hypoesthesia, tenderness, swelling/oedema, erythema, localized infection, bleeding and/or bruising have been associated with injections. Needle-related pain and/or anxiety have resulted in vasovagal responses, including transient symptomatic hypotension and syncope.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse events were evaluated in subjects receiving 20 U of Nuceiva in the glabellar region in three single dose Phase III studies (EV-001, EV-002 and EVB-003; Table 3), and one repeat dose EV-006 study where 570 subjects could receive repeat treatments every 3 months up to a possible maximum total dose of 80 U. The demographics were similar in these studies: mean age was 50.3 years, 89.7% of the subjects were female, and commonly identified races were 83.6% White and 5.3% Black. Most treatment emergent adverse events (TEAEs) were mild to moderate in severity and none considered study drug related were serious.
Table 3. Treatment-emergent adverse events with > 1% incidence following a single dose of 20 Units in the glabellar region
| System Organ Class | Pooled Placebo (N=211) | Pooled Single Dose (N=737) |
|---|---|---|
| and Preferred Term | (%) | (%) |
| All AEs in ≥1% of subjects | 21.8% | 22.7% |
| Nervous System Disorders | 13.3% | 12.3% |
| Headache | 13.3% | 12.3% |
| Infections and Infestations | 7.6% | 8.8% |
| Gastroenteritis viral | 1.4% | 0.4% |
| Influenza | 0.9% | 0.7% |
| Nasopharyngitis | 1.4% | 3.5% |
| Sinusitis | 2.4% | 0.9% |
| Upper respiratory tract infection | 1.4% | 1.8% |
| Eye Disorders | 0.0% | 1.6% |
| Eyelid ptosis | 0.0% | 1.6% |
| Vascular Disorders | 0.9% | 0.5% |
| Hypertension | 0.9% | 0.5% |
In the pooled single dose Phase III studies, all TEAEs with an incidence >1%, included headache, viral gastroenteritis, influenza, nasopharyngitis, sinusitis, upper respiratory tract infection, eyelid ptosis and hypertension. Common TEAEs that were considered study drug related included headache, 7.6% in placebo and 9.4% in the Nuceiva group, and eyelid ptosis with 0% in placebo and 1.2% in the Nuceiva group.
Other TEAEs that were less frequent included dysphagia, dysphonia, paresthesia, pyrexia, urinary tract infection, urticaria and increased white blood cell count. Less frequent TEAEs considered study drug related included blepharospasm, blurred vision, diplopia, dry eye, eyebrow ptosis, eyelid edema, muscle twitching and injection site bruising.
In one year, open label, multi-dose Study EV-006, all TEAE’s that occurred with an incidence of >1% included headache, bronchitis, nasopharyngitis, sinusitis, upper respiratory tract infection, urinary tract infection, contusion, contact dermatitis, pain in extremity, eyelid ptosis, cough, hypertension and injection site reactions (e.g. bruising/pain/swelling/pruritus). Headache and eyelid ptosis were the only study drug related TEAE’s with an incidence of >1%.
The presence of antibotulinum antibodies in subjects receiving Nuceiva was evaluated in two single dose Phase III studies (EV-001 and EV-002) and one repeat dose Phase II study (EV-006). There were no cases of seroconversion with Nuceiva. One subject who had a history of exposure to botulinum toxin and tested positive at baseline did not respond to treatment.
8.5 Post-Market Adverse Reactions
Nuceiva contains the same active ingredient as other botulinum toxin containing products. Therefore, adverse events observed with these products also have the potential to be associated with the use of Nuceiva.
Adverse reactions reported during post-marketing and not reflected elsewhere in the Product Monograph include the following:
Ear and labyrinth disorders: Vertigo
Eye disorders: Periorbital haematoma
Gastrointestinal disorders: Dry mouth, Nausea
General disorders: Asthenia, Malaise
Immune system disorders: Hypersensitivity
Investigations: Neutralizing antibodies
Nervous system disorders: Amyotrophy, Burning sensation, Dizziness, Dysarthria, Facial paresis, Hypoaesthesia
Renal and urinary disorders: Urinary incontinence
Respiratory, thoracic and mediastinal disorders: Dyspnea
Skin and subcutaneous tissue disorders: Erythema, Excessive granulation tissue.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No formal drug interaction studies have been conducted with Nuceiva.
Patients treated concomitantly with botulinum toxins and aminoglycosides or other agents interfering with neuromuscular transmission (e.g., curare-like agents) should be observed closely because the effect of the botulinum toxin may be potentiated. Use of anticholinergic drugs after administration of Nuceiva may potentiate systemic anticholinergic effects such as blurred vision.
The effect of administering different botulinum toxin products at the same time or within several months of each other is unknown. Excessive weakness may be exacerbated by another administration of botulinum toxin prior to the resolution of the effects of a previously administered botulinum toxin.
Excessive weakness may also be exaggerated by administration of a muscle relaxant before or after administration of Nuceiva.
9.3 Drug-Behavioral Interactions
Lifestyle interactions have not been established.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
Table 4. Potential Drug-Drug Interactions
| Proper/Common Name of Drug | Source of Evidence | Effect | Clinical Comment |
| aminoglycoside antibiotics or other medicinal products that interfere with neuromuscular transmission (e.g., curare-like agents, lincosamides, polymyxins, and anticholinesterases). | T | Theoretically, the effect of botulinum toxin may be potentiated. | The effect of botulinum toxin may be potentiated by aminoglycoside antibiotics or other drugs that interfere with neuromuscular transmission. Caution should be exercised when Nuceiva is used with aminoglycosides or any other drugs that interfere with neuromuscular transmission. |
| Different botulinum neurotoxin serotypes | T | Unknown | The effect of administering different botulinum neurotoxin serotypes at the same time or within several months of each other is unknown. Excessive weakness may be exacerbated by administration of another botulinum toxin prior to the resolution of the effects of a previously administered botulinum toxin. |
Legend: T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory test have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Nuceiva inhibits release of the neurotransmitter, acetylcholine, from peripheral cholinergic nerve endings, causing a flaccid paralysis of muscles. Toxin activity occurs in the following sequence: toxin heavy chain mediated binding to specific surface receptors on nerve endings, internalization of the toxin by receptor mediated endocytosis, pH-induced translocation of the toxin light chain to the cell cytosol and cleavage of SNAP25 leading to intracellular blockage of neurotransmitter (acetylcholine) exocytosis into the neuromuscular junction. This accounts for the therapeutic utility of the toxin in diseases characterized by excessive efferent activity in motor nerves.
Recovery of transmission occurs gradually as the neuromuscular junction recovers from SNAP25 cleavage and as new nerve endings are formed.
10.2 Pharmacodynamics
The primary pharmacodynamic effect of Nuceiva is due to chemical denervation of the treated muscle resulting in a measurable decrease of the compound muscle action potential, causing a localized reduction of muscle activity.
10.3 Pharmacokinetics
Nuceiva is not expected to be present in the peripheral blood at measurable levels following intramuscular injection at the recommended doses. Using currently available analytical technology, it is not possible to detect Nuceiva in the peripheral blood following intramuscular injection at the recommended doses.
11 STORAGE, STABILITY AND DISPOSAL
Nuceiva must be stored under refrigeration at 2–8°C.
Administer Nuceiva within 24 hours of reconstitution. Reconstituted Nuceiva should be clear, colorless and free of particulate matter. Do not freeze after reconstitution.
Do not use after the expiration date on the vial.
12 SPECIAL HANDLING INSTRUCTIONS
All vials, including unused product remaining and expired vials, or equipment used with Nuceiva should be disposed of carefully as is done with all medical waste. In cases when deactivation of the toxin is desired (e.g., spills), the use of dilute hypochlorite solution (0.5% or 1%) for five minutes is recommended prior to disposal as medical waste.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: prabotulinumtoxinA for injection
Chemical name: Botulinum toxin Type A (BoNT/A)
Molecular formula and molecular mass: 150 kDa toxin within a 900 kDa protein complex
Structural formula: The drug substance in Nuceiva is purified from Clostridium botulinum, Type A and composed of a dimer of 2 covalently bonded complexes consisting of a neurotoxin, non-toxic, non-haemagglutinin protein (NTNH), and haemagglutinin (HA) proteins (HA50, HA33, HA20, and HA17). It has the same structural characteristics, physiochemical, and biological properties as Botulinum toxin, Type A variant. The molecular weight is 900 kDa.
Physicochemical properties: Nuceiva (Botulinum toxin, Type A) is a sterile, preservative free, white to yellowish powder. Nuceiva is composed of 100 units of Botulinum Toxin, Type A (active ingredient), 0.5 mg of human serum albumin (stabilizing agent), and 0.9 mg of sodium chloride (isotonic agent). Nuceiva is reconstituted with a preservative free, 0.9% sodium chloride (USP) to form a clear, transparent solution. See Dosage and Administration and Warnings sections for further details.
The primary release procedure for Nuceiva uses a cell-based potency assay to determine the potency relative to a reference standard. One Unit of Nuceiva corresponds to the calculated median intraperitoneal lethal dose (LD50) in mice. The method for performing the assay is specific to Nuceiva. Due to differences in specific details of this assay such as the vehicle, dilution scheme and laboratory protocols, Units of biological activity of Nuceiva are not interchangeable with Units of any other botulinum toxin or any toxin assessed with any other specific assay method. The specific activity of Nuceiva is approximately 28 Units/nanogram of neurotoxin complex.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Two identical multi-center, randomized, double blind placebo-controlled Phase III clinical trials (EV-001 and EV-002) were conducted to evaluate Nuceiva for the use in the temporary improvement of moderate to severe glabellar lines at maximum frown in healthy adults. The primary endpoint was based on the responder rate on Day 30 using a composite endpoint, where both the investigator and subject independently agreed that a ≥2 point improvement had occurred on a 4-point severity glabellar line scale (none, mild, moderate, severe) at maximum frown.
In a supportive Phase III trial (EVB-003), the efficacy of Nuceiva was evaluated in a non-inferiority design with a comparator product containing onabotulinumtoxinA. In this study, subject’s satisfaction was evaluated as a secondary endpoint using a 5-point satisfaction scale on Day 30.
In these studies, exclusion criteria included the inability to substantially lessen glabellar frown lines by physically spreading them apart or any condition that might have affected neuromuscular function. Subjects received as single dose of 20U, divided into 5 injection sites (4U) in the corrugator and procerus muscles (see Figure 1).
Table 5. Summary of patient demographics for Studies EV-001, EV-002 and EV-003
| Study # | Trial designs | Dosage, route of administration and duration | Study subjects (N) | Mean age (range) |
|---|---|---|---|---|
| EV-001 | Phase III, multi-center, double blind, placebo-controlled | Single dose (20U), administered on Day 0;and study duration of 150 days | Males 24 Females 306 | Placebo 50.4 (23, 74) PrabotulinumtoxinA 50.2 (22, 81) |
| EV-002 | Males 34 Females 290 | Placebo 50.4 (18, 71) PrabotulinumtoxinA 51.5 (21, 81) | ||
| EV-003 | Phase III multicenter, double blind, placebo and active controlled | Males 64 Females 476 | Placebo 48.4 (26, 71) PrabotulinumtoxinA 48.8 (22, 79) OnabotulinumtoxinA 49.7 years (24, 75) | |
14.2 Study Results
Based on the composite primary endpoint, the responder rates in the Nuceiva (prabotulinumtoxinA) and placebo groups were, respectively, 67.5% and 1.2% in EV-001; and 70.4% and 1.3% in EV-002 (Table 6). The absolute differences between groups were 66.3% and 69.1% in EV-001 and EV-002, respectively (both p<0.001).
Table 6. Responder rates in Studies EV-001 and EV-002 based on ≥ 2 point improvement at maximum frown on Day 30 using a 4-point severity glabellar line scale
| Study | Responder rate (%) | Nuceiva | PLACEBO |
|---|---|---|---|
| EV-001 | Composite endpoint Absolute difference 95% CI for difference p-value (Exact Test) Investigator’s assessment Subject assessment | 67.5 66.3 59.0, 72.4 <0.001 77.5 76.7 | 1.2 1.2 3.6 |
| EV-002 | Composite endpoint Absolute difference 95% CI for difference p-value (Exact Test) Investigator’s assessment Subject assessment | 70.4 69.1 61.5, 75.1 <0.001 82.5 76.3 | 1.3 2.7 4.0 |
In the EVB-003 Study, the proportion of subjects reporting satisfied or very satisfied with Nuceiva supported the results of the primary endpoint.
15 MICROBIOLOGY
NA
16 NON-CLINICAL TOXICOLOGY
Carcinogenicity: Long term studies in animals have not been performed to evaluate carcinogenic potential of Nuceiva.
Mutagenicity: Genotoxicity studies have not been conducted with Nuceiva.
Fertility and Reproductive Toxicity: No studies have been conducted for Nuceiva to evaluate the potential of fertility impairment.
In an embryo-fetal developmental study, Nuceiva was administered (0.5, 1, or 4 U/kg) intramuscularly to pregnant rats daily during the period of organogenesis (on gestation days 6 to 16). No significant test article-related toxicological effects were evident on embryo-development or in the maternal animals compared to the control group. Clinical signs in dams were consistent with pharmacologically mediated effects of botulinum toxin Type A (paralytic gait and curling of toes on the injected hind limb). No test substance-related toxicological changes on body weights, food consumption, organ weights and necropsy findings were evident in any dosing groups. The no observed adverse effect level (NOAEL) for developmental toxicity was ≤ 4 U/kg, approximately 2-fold the human dose of 20 U based on a body surface area for a 60 kg subject.
Animal Toxicity Studies: In two studies to evaluate the acute and repeat-dose toxicity of Nuceiva, a single or once-weekly (for 4 weeks) intramuscular injection of 4, 8 or 32 U/kg was administered to rats in the hind limb. Nuceiva produced similar pharmacologically mediated effects, including limb paralysis and correlated reductions in food consumption and body weight. At 32 U/kg/dose, these effects were statistically significant and were associated with additional clinical signs of toxicity. Decreased muscle weight and microscopic muscle atrophy of the injected limb as well as local inflammatory responses were observed at doses ≥ 4 U/kg. In male rats, unilateral seminiferous tubule degeneration and atrophy were also observed at doses ≥ 4 U/kg. The maximum tolerated dose for acute and repeat-dose toxicity was ≤ 8 U/kg.