


Product Monograph - PMS-Fentanyl Mtx
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/ Strength | Nonmedicinal Ingredients |
|---|---|---|
| Transdermal | Patches; 12 mcg/h, 25 mcg/h, 50 mcg/h, 75 mcg/h, and 100 mcg/h | acrylic-vinylacetate copolymer adhesive, polyethyleneterephthalate backing foil, and siliconized polyethyleneterephthalate release liner |
INDICATIONS AND CLINICAL USE
Adults
pms-FENTANYL MTX (fentanyl transdermal system) is indicated for the management of pain severe enough to require daily, continuous, long-term opioid treatment, and:
- that is opioid-responsive; and
- for which alternative options are inadequate.
Only for use in patients who are already receiving opioid therapy at a total daily dose of at least 60 mg/day morphine equivalents.
pms-FENTANYL MTX is not indicated as an as-needed (prn) analgesic.
The initial dose of pms-FENTANYL MTX should be obtained or calculated from the conversion tables (see DOSAGE AND ADMINISTRATION), and must not be higher than that dose which is equivalent to the total dose of opioids the patient is receiving at the time of the switch to the patch.
Because serious or life-threatening hypoventilation could occur, pms-FENTANYL MTX should not be used in:
- non-opioid-tolerant patients
- the management of postoperative pain
Pediatrics (˂ 18 years of age):
The safety and efficacy of fentanyl transdermal system has not been studied in the pediatric population. Therefore, the use of pms-FENTANYL MTX in patients under 18 years of age is not recommended. Life-threatening hypoventilation has been reported in some pediatric patients receiving fentanyl transdermal system.
Geriatrics (˃ 65 years of age):
In elderly, cachectic, or debilitated patients, fentanyl transdermal system may have altered pharmacokinetics due to poor fat stores, muscle wasting or altered clearance. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION). Therefore, it may be appropriate, according to clinical judgment, to initiate these patients on a lower pms-FENTANYL MTX dose than that which the conversion tables recommend, including the use of the 12 mcg/h dose by itself or in combination with another dose, provided the patient is not opioid-naive (see CONTRAINDICATIONS). The 12 mcg/h strength may also be used for dose titration up or down, as using small increments for dose adjustment is recommended to enhance tolerability of opioid therapy (see DOSAGE AND ADMINISTRATION).
CONTRAINDICATIONS
Because serious or life-threatening hypoventilation could occur, pms-FENTANYL MTX is contraindicated in:
- 1) patients with acute or perioperative pain, especially use in out-patient or day surgeries (see WARNINGS AND PRECAUTIONS, Perioperative Considerations);
- 2) patients with mild, intermittent or short duration pain that can otherwise be managed;
- 3) opioid-naive patients, at any dose;
- 4) situations of significant respiratory depression, especially in unmonitored settings where there is a lack of resuscitative equipment;
- 5) patients who have acute or severe bronchial asthma;
- 6) patients who are hypersensitive to the active substance (fentanyl) or other opioid analgesics or to any ingredient in the formulation. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph;
- 7) patients with known or suspected mechanical gastrointestinal obstruction (e.g., bowel obstruction, strictures) or any diseases/conditions that affect bowel transit (e.g., ileus of any type);
- 8) patients with suspected surgical abdomen (e.g., acute appendicitis or pancreatitis);
- 9) patients with acute alcoholism, delirium tremens, and convulsive disorders;
- 10) patients with severe CNS depression, increased cerebrospinal or intracranial pressure, and head injury;
- 11) patients taking monoamine oxidase (MAO) inhibitors (or within 14 days of such therapy);
- 12) women who are breast-feeding, pregnant, or during labour and delivery (see SERIOUS WARNINGS AND PRECAUTIONS and WARNINGS AND PRECAUTIONS).
Because serious or life-threatening hypoventilation could occur, the maximum initiation dose of pms-FENTANYL MTX should not be higher than that equivalent to the total dose of opioids the patient is receiving at the time of the switch (see conversion tables in DOSAGE AND ADMINISTRATION).
WARNINGS AND PRECAUTIONS
SERIOUS WARNINGS AND PRECAUTIONS
Limitations of Use
Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, and because of the greater risks of overdose and death with extended-release opioid formulations, pms-FENTANYL MTX should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics), or would be otherwise inadequate to provide sufficient management of pain (e.g., immediate-release opioids) (see DOSAGE AND ADMINISTRATION).
Addiction, Abuse, and Misuse
pms-FENTANYL MTX poses risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Each patient’s risk should be assessed prior to prescribing pms-FENTANYL MTX, and all patients should be monitored regularly for the development of these behaviours or conditions (see WARNINGS AND PRECAUTIONS). pms-FENTANYL MTX should be stored securely to avoid theft or misuse.
Life-threatening Respiratory Depression: OVERDOSE
Serious, life-threatening, or fatal respiratory depression may occur with use of pms-FENTANYL MTX. Infants exposed in-utero or through breast milk are at risk of life-threatening respiratory depression upon delivery or when nursed. Patients should be monitored for respiratory depression, especially during initiation of pms-FENTANYL MTX or following a dose increase. Placing pms-FENTANYL MTX in the mouth, chewing it, swallowing it or using it in any way other than indicated may cause choking or overdose that could result in death (see WARNINGS AND PRECAUTIONS). Further, instruct patients of the hazards related to taking opioids: addiction, tolerance and fatal overdose.
Accidental Exposure
Serious medical consequences, including death, may occur if people, especially children, are accidentally exposed to pms-FENTANYL MTX. Examples of accidental exposure include transfer of pms-FENTANYL MTX while hugging, sharing a bed, or moving a patient (see DOSAGE AND ADMINISTRATION subsection Disposal of pms-FENTANYL MTX, for instructions on proper disposal).
Neonatal Opioid Withdrawal Syndrome
Prolonged maternal use of pms-FENTANYL MTX during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening (see WARNINGS AND PRECAUTIONS).
Interactions with Alcohol
The co-ingestion of alcohol with pms-FENTANYL MTX should be avoided as it may result in dangerous additive effects, causing serious injury or death (see WARNINGS AND PRECAUTIONS and DRUG INTERACTIONS).
Risks From Concomitant Use with Benzodiazepines or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other CNS depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death (see WARNINGS AND PRECAUTIONS, Neurologic and DRUG INTERACTIONS).
- Reserve concomitant prescribing of pms-FENTANYL MTX and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate.
- Limit dosages and durations to the minimum required.
- Follow patients for signs and symptoms of respiratory depression and sedation.
General
Use in non-opioid-tolerant patients, or use of an initiating dose which is higher than the opioid equivalent to which the patient is tolerant at the time of the switch, may lead to fatal respiratory depression.
The following contraindications reduce the potential risk of serious or life-threatening hypoventilation:
pms-FENTANYL MTX should not be used in the management of acute or postoperative pain since there is no opportunity for dose titration during short-term use and serious or life-threatening hypoventilation could result. Similarly, pms-FENTANYL MTX should not be administered to patients who do not have some degree of tolerance to opioid-induced side effects. pms-FENTANYL MTX should ONLY be prescribed to patients who require continuous opioids for pain management, and who are tolerant to at least the morphine equivalent of the lowest initiating pms-FENTANYL MTX dose.
The initial dose of pms-FENTANYL MTX should be obtained from the conversion tables in DOSAGE AND ADMINISTRATION, and must not be higher than that dose which is equivalent to the total dose of opioids the patient is receiving at the time of the switch to the patch. It may be appropriate, according to clinical judgment, to initiate some patients on a lower pms-FENTANYL MTX dose than that which the conversion tables recommend, which may include use of the 12 mcg/h dose. Opioid-naive patients should not be given pms-FENTANYL MTX at any dose, inclusive of 12 mcg/h (see CONTRAINDICATIONS). In general, the 12 mcg/h dose, which allows for smaller dose increases than does the 25 mcg/h patch, is to be used for titration/adjustments of dosage (see DOSAGE AND ADMINISTRATION).
pms-FENTANYL MTX should only be prescribed by persons knowledgeable in the continuous administration of potent opioids, in the management of patients receiving potent opioids for treatment of pain, and in the detection and management of respiratory depression including the use of opioid antagonists.
PATIENTS WHO HAVE EXPERIENCED SERIOUS ADVERSE EVENTS SHOULD BE MONITORED FOR AT LEAST 24 HOURS AFTER pms-FENTANYL MTX REMOVAL, OR MORE, AS CLINICAL SYMPTOMS DICTATE, BECAUSE SERUM
FENTANYL CONCENTRATIONS DECLINE GRADUALLY AND ARE REDUCED BY ABOUT 50% 20 TO 27 HOURS LATER.
Due to the formation of a subcutaneous depot of fentanyl, not only does continued exposure occur after system removal but, in the case of removal prior to attainment of peak fentanyl exposure, fentanyl plasma levels may, in fact, continue to increase after removal of pms-FENTANYL MTX.
pms-FENTANYL MTX is intended for transdermal use on intact skin only; use on compromised skin can lead to increased exposure to fentanyl.
Risk of Unintentional Increase in Drug Exposure
Patients with Fever: Serum fentanyl concentrations could theoretically increase by approximately one-third for patients with a body temperature of 40°C (104°F) due to temperature-dependent increases in fentanyl release from the system and increased skin permeability. Patients who develop fever should be monitored for opioid side effects and have their pms-FENTANYL MTX dose adjusted if necessary.
External Heat Sources: There is a potential for temperature-dependent increases in fentanyl released from the system resulting in possible overdose and death. A clinical pharmacology trial conducted in healthy adult subjects has shown that the application of heat over the fentanyl transdermal system increased mean fentanyl AUC values by 120% and mean Cmax values by 61%. All patients should be advised to avoid exposing the pms-FENTANYL MTX application site to direct external heat sources, such as heating pads, electric blankets, heated water beds, heat lamps, hot water bottles, saunas and hot whirlpool spa baths, intensive sunbathing, etc.
Cardiovascular
Cardiac disease:
Intravenous fentanyl may produce bradycardia. pms-FENTANYL MTX should be administered with caution to patients with bradyarrhythmias.
Hypotension: Fentanyl may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or the concurrent administration of drugs such as phenothazines and other tranquilizers, sedative/hypnotics, tricyclic antidepressants or certain anesthetics (see also DRUG INTERACTIONS). These patients should be monitored for signs of hypotension after initiating or titrating the dose of pms-FENTANYL MTX. The use of pms-FENTANYL MTX in patients with circulatory shock should be avoided as it may cause vasodilation that can further reduce cardiac output and blood pressure. Fentanyl may also produce orthostatic hypotension in ambulatory patients.
Concomitant Use of CYP3A4 Inhibitors and Inducers
The concomitant use of pms-FENTANYL MTX with potent cytochrome P450 3A4 inhibitors (including, but not limited to, ritonavir, ketoconazole, itraconazole, troleandomycin, clarithromycin, nelfinavir, nefazodone, verapamil, diltiazem, amiodarone, amprenavir, fosamprenavir, aprepitant, fluconazole, erythromycin, and grapefruit juice) may result in an increase in fentanyl plasma concentrations, which could increase or prolong adverse drug effects and may cause potentially fatal respiratory depression. In this situation, close monitoring and observation are appropriate. Therefore, the concomitant use of pms-FENTANYL MTX and CYP3A4 inhibitors is not recommended unless the patient is closely monitored, for an extended period of time, for signs of respiratory depression, with dosage adjustments made as warranted (see DRUG INTERACTIONS).
Similarly, discontinuation of a CYP3A4 inducer, such as rifampin, carbamazepine, and phenytoin, in pms-FENTANYL MTX-treated patients may increase fentanyl plasma concentrations and prolong opioid adverse reactions including respiratory depression. When using pms-FENTANYL MTX with CYP3A4 inducers, monitor patients closely at frequent intervals and consider increasing the opioid dosage if needed to maintain adequate analgesia or if symptoms of opioid withdrawal occur (see DRUG INTERACTIONS).
Addiction, Abuse and Misuse
pms-FENTANYL MTX is a potential drug of abuse and misuse, which can lead to overdose and death. Therefore, pms-FENTANYL MTX should be prescribed and handled with caution.
Patients should be assessed for their clinical risks for opioid abuse or addiction prior to being prescribed opioids. All patients receiving opioids should be routinely monitored for signs of misuse and abuse.
Opioids, such as pms-FENTANYL MTX, should be used with particular care in patients with a history of alcohol and illicit/prescription drug abuse. However, concerns about abuse, addiction, and diversion should not prevent the proper management of pain.
Since pms-FENTANYL MTX may be diverted for non-medical use, careful record keeping of prescribing information, including quantity, frequency, and renewal requests is strongly advised. Proper assessment of the patient, proper prescribing practices, periodic re-evaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs (see Dependence/Tolerance).
Dependence/Tolerance
As with other opioids, tolerance and physical dependence may develop upon repeated administration of pms-FENTANYL MTX and there is a potential for development of psychological dependence. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g. major depression).
Physical dependence and tolerance reflect the neuroadaptation of the opiate receptors to chronic exposure to an opiate, and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse.
Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness, and yawning (see DOSAGE AND ADMINISTRATION, Decreased Dosing or Discontinuation of pms-FENTANYL MTX).
Do not abruptly discontinue pms-FENTANYL MTX in a patient physically dependent on opioids. There have been reports that rapid tapering of pms-FENTANYL MTX in a patient physically dependent on opioids may lead to serious withdrawal symptoms and uncontrolled pain (see DOSAGE AND ADMINISTRATION, Decreased Dosing or Discontinuation of pms-FENTANYL MTX).
Drug or Alcohol Dependence
Use of pms-FENTANYL MTX in combination with CNS depressants, including alcohol, can result in increased risk to the patient (see DRUG INTERACTIONS).
pms-FENTANYL MTX should be used with caution in individuals who have a history of drug or alcohol abuse, especially those outside a medically controlled environment. While the management of severe pain in patients with a history of addiction requires special consideration, the use of opioids is not necessarily contraindicated in these patients. There may also be an increased risk of diversion in this population; this risk may be decreased by attention to patterns of prescription requests, and by prescribing opioids only as part of an ongoing relationship between a patient and a healthcare provider. Patients with a history of addiction to drugs or alcohol may be at higher risk of becoming addicted to pms-FENTANYL MTX unless used under extreme caution and awareness.
“Drug seeking” behaviour includes emergency calls or visits near the end of office hours; refusal to undergo appropriate examination, testing or referral; repeated “loss” of prescriptions; tampering with prescriptions; “doctor shopping” to obtain additional prescriptions; and reluctance to provide prior medical records or contact information for other treating physician(s).
Neurologic
Use in Patients with Convulsive or Seizure Disorders: The fentanyl in pms-FENTANYL MTX may aggravate convulsions in patients with convulsive disorders, and may induce or aggravate seizures in some clinical settings. Therefore, pms-FENTANYL MTX should not be used in these patients (see CONTRAINDICATIONS).
Serotonin Syndrome: Caution is advised when pms-FENTANYL MTX is co-administered with drugs that affect the serotonergic neurotransmitter systems. The concomitant administration of pms-FENTANYL MTX and serotonergic drugs (e.g. anti-depressants, anxiolytics, migraine medications) could cause serotonin syndrome, a rare but potentially life-threatening condition. This may occur within the recommended dose. If such events (characterized by clusters of symptoms such as hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, mental status changes including confusion, irritability, extreme agitation progressing to delirium and coma and/or gastrointestinal symptoms such as nausea, vomiting, diarrhea) occur, the healthcare professional should determine whether treatment with pms-FENTANYL MTX and/or the serotoninergic drug should be discontinued and supportive symptomatic treatment should be initiated. pms-FENTANYL MTX should not be used in combination with MAO inhibitors or serotonin-precursors (such as L-tryptophan, oxitriptan) and should be used with caution in combination with other serotonergic drugs (triptans, certain tricyclic antidepressants, lithium, tramadol, St. John’s Wort) due to the risk of serotonergic syndrome (see DRUG INTERACTIONS).
Interactions with Central Nervous System (CNS) Depressants (including benzodiazepines, alcohol and some illegal drugs)
pms-FENTANYL MTX should be used with caution and in a reduced dosage during concomitant administration of other opioid analgesics, general anesthetics, phenothiazines and other tranquilizers, sedative-hypnotics, tricyclic antidepressants, antipsychotics, antihistamines, benzodiazepines, centrally-active anti-emetics and other CNS depressants including alcohol and some illegal drugs. Respiratory depression, hypotension and profound sedation, coma or death may result. When such combination therapy is contemplated, the lowest effective dosages and minimum duration for both drugs should be prescribed. Patients should be carefully monitored for signs of respiratory depression and sedation (see DRUG INTERACTIONS).
Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioid analgesics alone. Because of similar pharmacological properties, it is reasonable to expect similar risks with the concomitant use of other CNS depressant drugs with opioid analgesics (see DRUG INTERACTIONS). If the decision is made to prescribe a benzodiazepine or other CNS depressant concomitantly with an opioid analgesic, prescribe the lowest effective dosages and minimum durations of concomitant use. In patients already receiving an opioid analgesic, prescribe a lower initial dose of the benzodiazepine or other CNS depressant than indicated in the absence of an opioid, and titrate based on clinical response. If an opioid analgesic is initiated in a patient already taking a benzodiazepine or other CNS depressant, prescribe a lower initial dose of the opioid analgesic, and titrate based on clinical response. Follow patients closely for signs and symptoms of respiratory depression and sedation.
Advise both patients and caregivers about the risks of respiratory depression and sedation when pms-FENTANYL MTX is used with benzodiazepines or other CNS depressants (including alcohol and illicit drugs). Advise patients not to drive or operate heavy machinery until the effects of concomitant use of the benzodiazepine or other CNS depressant have been determined. Screen patients for risk of substance use disorders, including opioid abuse and misuse, and warn them of the risk for overdose and death associated with the use of additional CNS depressants including alcohol and illicit drugs (see DRUG INTERACTIONS).
pms-FENTANYL MTX should not be consumed with alcohol as it may increase the chance of experiencing dangerous side effects, including death (see CONTRAINDICATIONS and ADVERSE REACTIONS and DRUG INTERACTIONS).
Severe pain antagonizes the subjective and respiratory depressant actions of opioid analgesics.
Should pain suddenly subside, these effects may rapidly become manifest.
Head Injuries and Increased Intracranial Pressure
pms-FENTANYL MTX should not be used in patients who may be particularly susceptible to the intracranial effects of CO2 retention such as those with evidence of increased intracranial pressure, impaired consciousness, or coma. Opioids may obscure the clinical course of patients with head injury. pms-FENTANYL MTX should be used with caution in patients with brain tumours.
Neonatal Opioid Withdrawal Syndrome (NOWS)
Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn.
Use of pms-FENTANYL MTX is contraindicated in pregnant women (see CONTRAINDICATIONS).
Perioperative Considerations
pms-FENTANYL MTX is contraindicated for perioperative pain relief, especially in the elective surgical setting. In the case of planned chordotomy, or other pain-relieving operations, patients should not be treated with pms-FENTANYL MTX within 72 hours before the operation and should not be used in the immediate post-operative period. Thereafter, if pms-FENTANYL MTX is to be continued after the patient recovers from the post-operative period, a new dosage should be administered in accordance with the changed need for pain relief, if needed, and to reduce the risk of withdrawal in highly opioid-tolerant patients.
The administration of analgesics in the perioperative period should be managed by health care providers with adequate training and experience (e.g., an anesthesiologist) (see CONTRAINDICATIONS).
Hepatic/Biliary/Pancreatic
Because of the hepatic metabolism of fentanyl, pms-FENTANYL MTX should be used with caution in patients with liver dysfunction.
pms-FENTANYL MTX may cause spasm of the sphincter of Oddi and should be used with caution in patients with biliary tract disease, including acute pancreatitis. Opioids like pms-FENTANYL MTX may cause increases in the serum amylase concentration.
If patients with hepatic impairment receive pms-FENTANYL MTX, they should be observed carefully for signs of fentanyl toxicity and the dose of pms-FENTANYL MTX reduced if necessary (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Psychomotor Impairment
pms-FENTANYL MTX may impair the mental and/or physical ability required for the performance of potentially hazardous tasks such as driving a car or operating machinery. Patients using pms-FENTANYL MTX should not drive or operate dangerous machinery unless they are tolerant to the effects of the drug.
Renal
Because of the renal excretion of fentanyl, pms-FENTANYL MTX should be used with caution in patients with kidney dysfunction.
If patients with renal impairment receive pms-FENTANYL MTX, they should be observed carefully for signs of fentanyl toxicity and the dose should be reduced if necessary. The pharmacokinetic properties of fentanyl have not been studied in this population and, therefore, caution is warranted (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Treatment with fentanyl should only be considered in patients with kidney dysfunction if the benefits outweigh the risks.
Respiratory Depression
Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression from opioid use, if not immediately recognized and treated, may lead to respiratory arrest and death. Carbon dioxide (CO2) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids.
While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of pms-FENTANYL MTX, the risk is greatest during the initiation of therapy or following a dose increase. However, the risk of hypoventilation increases at serum fentanyl concentrations greater than 2 ng/mL in non-opioid-tolerant patients, especially for patients who have an underlying pulmonary condition or who receive usual doses of opioids or other CNS drugs associated with hypoventilation in addition to pms-FENTANYL MTX (see DRUG INTERACTIONS). Patients should be closely monitored for respiratory depression when initiating therapy with pms-FENTANYL MTX and following dose increases. As with other drug-level measurements, serum fentanyl concentrations may be useful clinically, although they do not reflect patients’ sensitivity to fentanyl and should not be used by physicians as a sole indicator of effectiveness or toxicity.
The duration of the respiratory depressant effect of pms-FENTANYL MTX may extend beyond the removal of the system (see also OVERDOSAGE concerning respiratory depression).
To reduce the risk of respiratory depression, proper dosing and titration of pms-FENTANYL MTX are essential (see DOSAGE AND ADMINISTRATION). Overestimating the pms-FENTANYL MTX dose when converting patients from another opioid product can result in fatal overdose with the first dose.
Opioids can cause sleep-related breathing disorders such as sleep apnea syndromes (including central sleep apnea [CSA]) and hypoxia (including sleep-related hypoxia) (see ADVERSE REACTIONS). Opioid use increases the risk of CSA in a dose-dependent fashion. Evaluate patients on an ongoing basis for the onset of a new sleep apnea, or a worsening of an existing sleep apnea. In these patients, consider reducing or stopping the opioid treatment if appropriate, using best practices for tapering of opioids. (see DOSAGE AND ADMINISTRATION, Decreased Dosing or Discontinuation of pms-FENTANYL MTX).
Endocrine
Adrenal Insufficiency
Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Presentation of adrenal insufficiency may include non-specific symptoms and signs including nausea, vomiting, anorexia, fatigue, weakness, dizziness, and low blood pressure. If adrenal insufficiency is suspected, confirm the diagnosis with diagnostic testing as soon as possible. If adrenal insufficiency is diagnosed, treat with physiologic replacement doses of corticosteroids. Wean the patient off of the opioid to allow adrenal function to recover and continue corticosteroid treatment until adrenal function recovers. Other opioids may be tried as some cases reported use of a different opioid without recurrence of adrenal insufficiency. The information available does not identify any particular opioids as being more likely to be associated with adrenal insufficiency.
Sexual Function/Reproduction
Long-term use of opioids may be associated with decreased sex hormone levels and symptoms such as low libido, erectile dysfunction, or infertility (see ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Gastrointestinal Tract
Opioids increase the tone and decrease the propulsive contractions of the smooth muscle of the gastrointestinal tract. The resultant prolongation in gastrointestinal transit time may be responsible for the constipating effect of fentanyl. Patients should be advised on measures to prevent constipation and prophylactic laxative use should be considered. Extra caution should be used in patients with chronic constipation. If paralytic ileus is present or suspected, treatment with pms-FENTANYL MTX should be stopped (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics).
Patients with Chronic Pulmonary Disease
Fentanyl should be used with caution in patients with chronic pulmonary disease, patients with decreased respiratory reserve and others with potentially compromised respiration. Normal analgesic doses of opioids may further decrease respiratory drive in these patients to the point of respiratory failure.
Information for Patients
The Patient Medication Information is included in the package of pms-FENTANYL MTX dispensed to the patient.
Patients receiving pms-FENTANYL MTX should be given the following instructions by the physician:
- 1. Patients should be informed that accidental exposure or use by individuals (including children and pets) other than the patient for whom it was originally prescribed, may lead to severe, even fatal, consequences.
- 2. Patients should be advised that pms-FENTANYL MTX contain fentanyl, an opioid pain medicine similar to morphine, hydromorphone, methadone, oxycodone, and oxymorphone.
- 3. Patients should be advised that each pms-FENTANYL MTX may be worn continuously for 72 hours, and that each patch should be applied to a different skin site after removal of the previous transdermal patch.
- 4.
Patients should be advised that pms-FENTANYL MTX should be applied to intact, non-irritated, and non-irradiated skin on a flat surface such as the chest, back, flank, or upper arm. Additionally, patients should be advised of the following:
- In young children or persons with cognitive impairment, the patch should be put on the upper back to lower the chances that the patch will be removed and placed in the mouth.
- Hair at the application site should be clipped (not shaved) prior to patch application.
- If the site of pms-FENTANYL MTX application must be cleansed prior to application of the patch, do so with clear water.
- Do not use soaps, oils, lotions, alcohol, or any other agents that may irritate the skin or alter its characteristics.
- Allow the skin to dry completely prior to patch application.
- 5.
Patients should be advised that pms-FENTANYL MTX should be applied immediately upon removal from the sealed package and after removal of the protective liner.
Additionally, the patient should be advised of the following:
- pms-FENTANYL MTX should not be used if the seal is broken, or if it is altered, cut, or damaged in any way prior to application. The transdermal patch should be pressed firmly in place with the palm of the hand for 30 seconds, making sure the contact is complete, especially around the edges.
- The patch should not be folded so that only part of the patch is exposed.
- 6.
Patients should be advised that, while wearing the patch, they should avoid exposing the pms-FENTANYL MTX application site to direct external heat sources, such as:
- heating pads,
- electric blankets,
- heat lamps,
- saunas,
- hot tubs, and
- heated water beds, etc.
- 7. Patients should be advised that there is a potential for temperature-dependent increase in fentanyl release from the patch that could result in an overdose of fentanyl; therefore, if patients develop a high fever while wearing the patch, they should contact their physician.
- 8.
Patients should be advised that if they experience problems with adhesion of the
- pms-FENTANYL MTX, they may tape the edges of the patch with first aid tape. If problems with adhesion persist, patients may overlay the patch with a transparent adhesive film dressing.
- 9. Patients should be advised that if the patch falls off before 72 hours a new patch may be applied to a different skin site.
- 10. Patients should be advised to fold (so that the adhesive side adheres to itself) used pms-FENTANYL MTX after removal from the skin and return to a pharmacy for proper disposal.
- 11. Patients should be instructed that, if the drug adhesive layer accidentally contacts the skin, the area should be washed clean with clear water and not soap, alcohol, or other chemicals, because these products may increase the ability of fentanyl to go through the skin.
- 12. Patients should be advised that the dose of pms-FENTANYL MTX should NEVER be adjusted without the prescribing health care professional’s instruction.
- 13. Patients should be advised that pms-FENTANYL MTX may impair mental and/or physical ability required for the performance of potentially hazardous tasks (e.g. driving, operating machinery).
- 14. Patients should be advised to refrain from any potentially dangerous activity when starting on pms-FENTANYL MTX or when their dose is being adjusted, until it is established that they have not been adversely affected.
- 15. Patients should be advised that pms-FENTANYL MTX should not be combined with alcohol or other CNS depressants (e.g. sleep medications, tranquilizers) because dangerous additive effects may occur, resulting in serious injury or death.
- 16. Patients should be advised to consult their physician or pharmacist if other medications are being or will be used with pms-FENTANYL MTX.
- 17. Patients should be advised of the potential for severe constipation.
- 18. Patients should be advised that if they have been receiving treatment with pms-FENTANYL MTX and cessation of therapy is indicated, it may be appropriate to taper the pms-FENTANYL MTX dose, rather than abruptly discontinue it, due to the risk of precipitating withdrawal symptoms.
- 19. Patients should be advised that pms-FENTANYL MTX contains fentanyl, a drug with high potential for abuse.
- 20. Patients, family members and caregivers should be advised to protect pms-FENTANYL MTX from theft or misuse in the work or home environment.
- 21.
Patients should be advised that pms-FENTANYL MTX should never be given to anyone
- other than the individual for whom it was prescribed because of the risk of death or other serious medical problems to that person for whom it was not intended.
- 22. Patients should be instructed to keep pms-FENTANYL MTX in a secure place out of the reach of children due to the high risk of fatal respiratory depression.
- 23. When pms-FENTANYL MTX is no longer needed, the unused patches should be removed from their pouches, folded so that the adhesive side of the patch adheres to itself, and returned to a pharmacy for proper disposal.
- 24. Women of childbearing potential who become or are planning to become pregnant should be advised to consult a physician prior to initiating or continuing therapy with pms-FENTANYL MTX.
- 25. Patients should be informed that accidental exposure or misuse may lead to death or other serious medical problems.
- 26. Patients should be informed that, if the patch dislodges and accidentally sticks to the skin of another person, they should immediately take the patch off, wash the exposed area with water and seek immediate medical attention for the accidentally exposed individual.
Special Populations
Pregnant Women: Fentanyl has been shown to impair fertility and to have an embryocidal effect in rats when given in intravenous doses 0.3 times the human dose for a period of 12 days. No evidence of teratogenic effects has been observed after the administration of fentanyl to rats.
The safe use of fentanyl has not been established with respect to possible adverse effects upon human fetal development. Therefore, pms-FENTANYL MTX should not be used in women of childbearing potential unless, in the judgment of the physician, the potential benefits outweigh the possible hazards. Prolonged maternal use of opioids during pregnancy can result in withdrawal signs in the neonate. Neonatal opioid withdrawal syndrome, unlike opioid withdrawal syndrome in adults, may be life-threatening (see WARNINGS AND PRECAUTIONS, Neonatal Opioid Withdrawal Syndrome).
Use of pms-FENTANYL MTX is contraindicated in pregnant women (see CONTRAINDICATIONS).
Use of pms-FENTANYL MTX during childbirth is contraindicated because fentanyl passes through the placenta and may cause respiratory depression in the newborn child.
Nursing Women: Fentanyl is excreted in human milk; therefore, pms-FENTANYL MTX is contraindicated for use in nursing women because of the possibility of effects in their infants.
Life-threatening respiratory depression may occur in the infant if opioids are administered to the mother. Naloxone, a drug that counters the effects of opioids, should be readily available if pms-FENTANYL MTX is used in this population.
Pediatrics (< 18 years of age): The use of pms-FENTANYL MTX in children under 18 years of age is not recommended, as the safety and efficacy of fentanyl transdermal system have not been studied in the pediatric population. Life-threatening hypoventilation has been reported in some pediatric patients receiving fentanyl transdermal system.
Geriatrics (˃ 65 years of age): In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, concomitant disease or other drug therapy (see DOSAGE AND ADMINISTRATION). Therefore, it may be appropriate, according to clinical judgment, to initiate these patients on a lower pms-FENTANYL MTX dose than that which the conversion tables recommend, including the use of the 12 mcg/h dose by itself or in combination with another dose, provided the patient is not opioid-naive (see CONTRAINDICATIONS). The 12 mcg/h strength may also be used for dose titration up or down, as using small increments for dose adjustment is recommended to enhance tolerability of opioid therapy (see DOSAGE AND ADMINISTRATION). As with all pms-FENTANYL MTX patients, they should be carefully monitored for pain levels and adverse events, particularly hypoventilation.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Cancer Trials – Adults
Open-Label and Active-Control Double-Blind Studies
The safety of fentanyl transdermal system has been evaluated in 153 cancer patients and 357 postoperative patients. The duration of fentanyl transdermal system use varied in cancer patients; 56% of patients used fentanyl transdermal system for over 30 days, 28% continued treatment for more than 4 months, and 10% used fentanyl transdermal system for more than 1 year. In cancer patients, fentanyl transdermal system was administered in doses of 25 mcg/h to 600 mcg/h. Patients with acute pain used fentanyl transdermal system for 1 to 3 days.
Respiratory depression, the most serious adverse reaction, was observed in 3 (2%) of the cancer patients and 13 (4%) of postoperative patients. Hypotension and hypertension were observed in 11 (3%) and 4 (1%) of the opioid-naive patients.
Placebo-Controlled Study
Adverse events occurring at a greater frequency than placebo were identified in a placebo-controlled clinical trial of fentanyl transdermal system (25 mcg/h to 100 mcg/h) in cancer patients. Patients were stabilized on morphine for 7 days, and those who achieved adequate pain relief (n=131) were then switched to fentanyl transdermal system. During the initial open-label dose-titration and stabilization period of 15 days, a total of 43 patients dropped out; four experienced dyspnea, three nausea and one severe hallucinations.
Following this stabilization period, the nine-day double-blind period began, with patients randomized to either continue the dose of fentanyl transdermal system achieved during stabilization (n=47) or to switch to placebo (n=48). Rescue morphine was available. The median dose of fentanyl transdermal system was 50 mcg/h. Adverse events during this period, as reported by at least 1 fentanyl transdermal system patient (2.1%), and with a higher frequency of occurrence versus placebo include: vomiting (4.3% vs. 0%), and the following events at 2.1% vs. 0%: abscess, vertigo, hemorrhage, abdominal pain and jaundice.
Chronic Non-Cancer Pain Trials – Adults
The safety findings from the two primary trials (FEN-INT-12, n=248 patients, and FEN-INT-13, n=532 patients) are described below (see Product Monograph, Part II: CLINICAL TRIALS, Chronic Non-Cancer Pain (CNCP) Trials for methodological details on the trials).
Safety Findings
Adverse events related to respiratory depression (reported as either bradypnea or hypoventilation) have been reported in 3/780 (0.4%) of the CNCP patients, leading to discontinuation in all three cases.
There were nine deaths (all in the one-year trial): four were due to cardiac events, three to pneumonia, one to a cerebrovascular event, and one to cancer.
The discontinuation rates were 16% for the one-month crossover trial (FEN-INT-12) and 43% for the one-year trial (FEN-INT-13).
Of the 780 patients, 149 (19%) received less than one month fentanyl transdermal system treatment, 272 (35%) used fentanyl transdermal system for one to six months, 137 (18%) for six months to one year, and 222 patients (28%) continued treatment for more than one year.
Among patients who completed the one-year trial (n=301 of 530 ITT patients), the mean dose at the 12-month endpoint was 90.4 mcg/h, with the most common dose being 75 mcg/h.
Most Common Adverse Events
A causal relationship of adverse events to fentanyl transdermal system was not always determined. The most commonly observed adverse events in the non-cancer chronic pain clinical trials, regardless of causal relationship, are: nausea or vomiting, somnolence, constipation, sweating, headache, dizziness, pruritus and depression.
Other reported adverse reactions occurring in > 1% of patients that are probably or likely related to fentanyl transdermal system treatment are:
Application Site: application site reaction.
Body as a Whole: fatigue, pain, malaise, asthenia, hot flushes, withdrawal syndrome, back pain, rigors, temperature changed sensation.
Central & Peripheral Nervous System: tremor, vertigo, hypertonia.
Gastrointestinal System: dry mouth, diarrhea, abdominal pain, dyspepsia.
Heart Rate and Rhythm: palpitation.
Liver and Biliary System: hepatic enzymes increased, gamma-GT increased.
Metabolic and Nutritional: weight decreased, LDH increased.
Psychiatric: anorexia, anxiety, confusion, insomnia, nervousness, agitation, hallucination, concentration impaired, emotional lability, amnesia.
Respiratory System: dyspnea.
Skin and Appendages: rash erythematous, skin disorder.
Chronic Pain Trials – Pediatrics
The safety of fentanyl transdermal system has been evaluated in 293 opioid-tolerant pediatric patients (age 18 years or less) with chronic pain, with n=63 receiving fentanyl transdermal system for at least 2 months. Approximately 60% of the patients had underlying pain due to malignancy. The number of patients in the lower age ranges were as follows: n=2 patients <2 years old; n=65 patients 2 to <6 years old; n=100 patients 6 to <12 years old. The most commonly reported adverse events regardless of causality include: vomiting (14.3%), nausea (11.6%), constipation (9.2%), pruritus (8.2%), and somnolence (5.8%). Three patients experienced respiratory depression within 96 hours of beginning fentanyl transdermal system; two of these patients died. The underlying condition of the patients contributed to the deaths. The third patient’s decreased respiratory rate was resolved after temporary discontinuation of fentanyl transdermal system.
Dosing recommendations for the safe and effective use of fentanyl transdermal system in this patient population have not been established, in view of the combination of:
- i) the variety of factors which could lead to overexposure from fentanyl transdermal system in children as compared to adults (including smaller body weight and significantly different body surface area; differential skin characteristics; potential for magnification, compared to adults, of the impact of amount of body fat stores, muscle wasting, fever, external heat), and
ii) the limitations in both formal PK data (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions) and exposure data (as above).
Post-Market Adverse Drug Reactions
In post-marketing experience, deaths from hypoventilation have been reported in cases of inappropriate use of fentanyl transdermal system. Other respiratory events associated with the use of fentanyl transdermal system include apnea, sleep apnea syndrome, respiratory distress and hypoxia.
Other opioid-related adverse reactions include: nausea, vomiting, constipation, ileus or subileus, upper abdominal pain, hypotension, bradycardia, cyanosis, miosis, somnolence, headache, confusion, disorientation, hallucination, euphoria, depressed level of consciousness or loss of consciousness, blurred vision, pruritus, sweating, pyrexia, influenza like illness, tachycardia, hypoesthesia, paresthesia, peripheral edema, muscle spasms or muscle twitching, sexual dysfunction, erectile dysfunction, and urinary retention.
Skin reactions such as rash, erythema and itching have occasionally been reported. These reactions usually resolve within 24 hours or upon removal of the patch. Other skin reactions such as application site hypersensitivity, application site erosion, application site ulcer, dermatitis, allergic dermatitis, contact dermatitis, and eczema have also been reported.
Hypersensitivity has been reported following use of fentanyl transdermal system. There have also been very rare reports of anaphylactic and anaphylactoid reaction, including Stevens-Johnson Syndrome, airway constriction, swelling, anaphylactic shock, and two deaths that occurred within 24 hours of the anaphylactic reaction. In one case, it was the caregiver of the patient who experienced dyspnea, urticaria, and swelling, within ten minutes of applying the patch to the patient.
There have also been rare reports of convulsions, including clonic convulsions and grand mal convulsions. In two cases, vegetative state or coma was reported to immediately follow the convulsions.
Opioid withdrawal symptoms, such as nausea, vomiting, diarrhea, anxiety, and shivering are possible in some patients after conversion from their previous opioid analgesic to pms-FENTANYL MTX or if therapy is stopped suddenly. There have been very rare reports of newborn infants experiencing neonatal withdrawal syndrome when mothers chronically used fentanyl transdermal system during pregnancy (see WARNINGS AND PRECAUTIONS: Special Populations, Pregnant Women).
Post-marketing reports describe patients with symptoms suggestive of, or diagnostic of, serotonin syndrome following the concomitant use of fentanyl with a serotonergic drug, such as a Selective Serotonin Re-uptake Inhibitor (SSRI) or a Serotonin Norepinephrine Re-uptake Inhibitor (SNRI) (see WARNINGS AND PRECAUTIONS, Neurologic and DRUG INTERACTIONS, Drug-Drug Interactions).
Androgen deficiency: Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
DRUG INTERACTIONS
Drug-Drug Interactions
Based on its pharmacodynamic and pharmacokinetic properties, fentanyl exhibits a potential for pharmacodynamic and pharmacokinetic interactions. The various types of interaction, associated general recommendations, and lists of examples are described below. These lists of examples are not comprehensive and therefore it is recommended that the label of each drug that is coadministered with fentanyl be consulted for information related to interaction pathways, potential risks, and specific actions to be taken with regards to coadministration.
U
Overview
Interactions with Central Nervous System (CNS) Depressants (including benzodiazepines and alcohol)
pms-FENTANYL MTX (fentanyl) should be dosed with caution in patients who are currently taking other CNS depressants or other drugs that may cause respiratory depression, hypotension, profound sedation, or may potentially result in coma. Such agents include antidepressants, antihistamines, antipsychotics, anxiolytics, barbiturates, benzodiazepines, centrally acting antiemetics, chloral hydrate, clonidine and related substances, general anaesthetics, some heart medications (e.g. beta-blockers), neuroleptics, other opioid derivatives (analgesic and antitussive) phenothiazines, and sedatives or hypnotics. When such combined therapy is contemplated, a substantial reduction in dose of one or both agents should be considered and patients carefully monitored. Patients should also be warned that these combinations increase central nervous system depression and can make driving vehicles and operating machinery hazardous (see
WARNINGS AND PRECAUTIONS, Psychomotor Impairment). pms-FENTANYL MTX should not be consumed with alcohol as it may increase chance of experiencing dangerous side effects.
CYP3A4 Inhibitors
Fentanyl, a high clearance drug, is rapidly and extensively metabolized mainly by the human cytochrome P450 3A4 isoenzyme system (CYP3A4); therefore, potential interactions may occur when pms-FENTANYL MTX is given concurrently with agents that affect CYP3A4 activity. The concomitant use of transdermal fentanyl with ritonavir or other potent 3A4 inhibitors such as ketoconazole, itraconazole, troleandomycin, clarithromycin, nelfinavir, nefazodone, verapamil, diltiazem, amiodarone, amprenavir, fosamprenavir, aprepitant, fluconazole, voriconazole, erythromycin and grapefruit juice may result in an increase in fentanyl plasma concentrations which could increase or prolong adverse drug effects and may cause serious respiratory depression (see also WARNINGS AND PRECAUTIONS, Concomitant Use of CYP3A4 Inhibitors). In this situation, special patient care and observation are appropriate. The concomitant use of CYP3A4 inhibitors and pms-FENTANYL MTX is not recommended, unless the patient is closely monitored.
CYP3A4 Inducers
Coadministration with agents that induce 3A4 activity such as rifampicin, carbamazepine, phenobarbital, phenytoin may reduce the efficacy of pms-FENTANYL MTX. This may require a dose adjustment of transdermal fentanyl. After stopping the treatment of a CYP3A4 inducer, the effects of the inducer decline gradually and may result in an increase in fentanyl plasma concentration which could increase or prolong both the therapeutic and adverse effects, and may cause serious respiratory depression.
MAO Inhibitors
Severe and unpredictable potentiation by MAO inhibitors (MAOIs) has been reported with opioid analgesics. MAOI interactions with opioids may manifest as serotonin syndrome or opioid toxicity (e.g., respiratory depression, coma). pms-FENTANYL MTX is contraindicated in patients taking MAOIs (e.g., phenelzine, tranylcypromine, linezolid) or within 14 days of stopping treatment (see CONTRAINDICATIONS).
Serotonergic Drugs
Coadministration of fentanyl with a serotonergic agent, such as a Selective Serotonin Re-uptake
Inhibitor (SSRI) or a Serotonin Norepinephrine Re-uptake Inhibitor (SNRI), may increase the risk of serotonin syndrome, a potentially life-threatening condition. Use concomitantly with caution. Carefully observe the patient, particularly during treatment initiation and dose adjustment (see WARNINGS AND PRECAUTIONS, Neurologic and ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Interaction with Mixed Agonist/Antagonist Analgesics: The concomitant use of pms-FENTANYL MTX with mixed agonist/antagonist analgesics (e.g., buprenorphine, butorphanol, nalbuphine, pentazocine) is not recommended. They have high affinity to opioid receptors with relatively low intrinsic activity and therefore partially antagonise the analgesic effect of fentanyl and may induce withdrawal symptoms in opioid-dependent patients (see WARNINGS AND PRECAUTIONS, Dependence/Tolerance).
Muscle Relaxants
Fentanyl may enhance the neuromuscular blocking action of skeletal muscle relaxants and produce an increased degree of respiratory depression. Monitor patients for signs of respiratory depression that may be greater than otherwise expected and decrease the dosage of pms-FENTANYL MTX and/or the muscle relaxant as necessary.
Diuretics
Opioids can reduce the efficacy of diuretics by inducing the release of antidiuretic hormone. Monitor patients for signs of diminished diuresis and/or effects on blood pressure and increase the dosage of the diuretic as needed.
Anticholinergic Drugs
The concomitant use of anticholinergic drugs may increase risk of urinary retention and/or severe constipation, which may lead to paralytic ileus. Monitor patients for signs of urinary retention or reduced gastric motility when pms-FENTANYL MTX is used concomitantly with anticholinergic drugs.
Drug-Lifestyle Interaction
The concomitant use of alcohol should be avoided (see WARNINGS AND PRECAUTIONS, Neurologic).
DOSAGE AND ADMINISTRATION
General
pms-FENTANYL MTX should only be used in patients for whom alternative treatment options are ineffective or not tolerated (e.g., non-opioid analgesics), or would be otherwise inadequate to provide sufficient management of pain (e.g., immediate-release opioids).
pms-FENTANYL MTX should only be prescribed by persons knowledgeable in the continuous administration of potent opioids, in the management of patients receiving potent opioids for treatment of pain, and in the detection and management of respiratory depression including the use of opioid antagonists.
At the time of the switch to pms-FENTANYL MTX from other opioids, patients must be tolerant to opioid therapy of comparable potency to that of the intended initiating dose. Use of pms-FENTANYL MTX in patients who are non-opioid-tolerant, or insufficiently tolerant, may lead to fatal respiratory depression.
Placing pms-FENTANYL MTX in mouth, chewing it, swallowing it or using it in any ways other than indicated may cause choking or overdose that could result in death (see SERIOUS WARNINGS AND PRECAUTIONS Box).
Dosing Considerations
pms-FENTANYL MTX doses must be individualized based upon the status of each patient and should be assessed at regular intervals after application. Proper optimization of doses scaled to the relief of the individual’s pain should aim at the regular administration of the lowest effective dose of pms-FENTANYL MTX which will achieve the overall treatment goal of satisfactory pain relief with acceptable side effects. Dosage of the drug must be individualized according to the response and tolerance of the patient. The most important factor to be considered in determining the appropriate dose is the extent of pre-existing opioid tolerance. Reduced doses of pms-FENTANYL MTX are suggested for the elderly and other groups discussed in WARNINGS AND PRECAUTIONS.
There has been no systematic evaluation of fentanyl transdermal system as an initial opioid analgesic in the management of chronic pain. Most patients in the clinical trials were converted to fentanyl transdermal system from other opioid therapies on which inadequate to moderate pain control had been experienced prior to conversion.
Initiation of pms-FENTANYL MTX in patients who are opioid-naive is contraindicated at any dose (see CONTRAINDICATIONS). The initial dose of pms-FENTANYL MTX should be obtained from the conversion tables in DOSAGE AND ADMINISTRATION, and must NOT be higher than that dose which is equivalent to the total dose of opioids the patient is receiving at the time of the switch to the patch. It may be appropriate, according to clinical judgment, to initiate some patients on a lower pms-FENTANYL MTX dose than that which the conversion tables recommend, including the use of the 12 mcg/h dose by itself or in combination with another dose, provided the patient is not opioid-naive (see CONTRAINDICATIONS).
In general the 12 mcg/h dose, which allows for smaller dose increases than does the 25 mcg/h patch, is to be used for titration/adjustments of dosage (for oral morphine equivalency in dose adjustment, see Recommended Dose and Dose Adjustment, Dose Adjustment and Titration Dose Increment). The 12 mcg/h dose is not included in the conversion tables (Tables 1.1 and 1.2) because it is generally not to be used as the initiating dose.
Opioid analgesics may be only partially effective in relieving dysesthetic pain, postherpetic neuralgia, stabbing pains, activity-related pain and some forms of headache. That is not to say that patients with these types of pain should not be given an adequate trial of opioid analgesics, but it may be necessary to refer such patients at an early time to other forms of pain therapy.
pms-FENTANYL MTX has a high potential for abuse and diversion (see WARNINGS AND PRECAUTIONS).
Concomitant Use of CYP3A4 Inhibitors
The concomitant use of pms-FENTANYL MTX with potent cytochrome P450 3A4 inhibitors (ritonavir, ketoconazole, itraconazole, troleandomycin, clarithromycin, nelfinavir, nefazodone, verapamil, diltiazem, amiodarone, amprenavir, fosamprenavir, aprepitant, fluconazole, erythromycin and grapefruit juice) may result in an increase in fentanyl plasma concentrations, which could increase or prolong adverse drug effects and may cause potentially fatal respiratory depression. Patients concomitantly exposed to pms-FENTANYL MTX and potent CYP3A4 inhibitors should be carefully monitored for an extended period of time and dosage adjustments should be made if warranted (see DRUG INTERACTIONS).
Recommended Dose and Dosage Adjustment
Pediatrics
The use of pms-FENTANYL MTX in children under 18 years of age is not recommended as the safety and efficacy of fentanyl transdermal system have not been studied in the pediatric population. Life-threatening hypoventilation has been reported in some pediatric patients receiving fentanyl transdermal system.
Adults: Initial Dose Selection
In selecting an initial pms-FENTANYL MTX dose, attention should be given to 1) the daily dose, potency, and characteristics of the opioid the patient has been taking previously (e.g. whether it is a pure agonist or mixed agonist-antagonist), 2) the reliability of the relative potency estimates used to calculate the pms-FENTANYL MTX dose needed (potency estimates may vary with the route of administration), 3) the degree of opioid tolerance, and 4) the general condition and medical status of the patient.
At the time of the switch to pms-FENTANYL MTX, patients must be tolerant to opioid therapy of comparable potency to that of the intended initiating dose. It may be appropriate, according to clinical judgment, to initiate some patients on a lower pms-FENTANYL MTX dose than that which the conversion tables recommend, which may include use of the 12 mcg/h dose. The 12 mcg/h dose is not included in the conversion tables (Tables 1.1 and 1.2), because it is generally to be used for dose adjustment rather than as the initiation dose, except in the case of patients who, because of their clinical status, are to be initiated on a lower dose than that which the conversion tables recommend. Overestimating the pms-FENTANYL MTX dose when converting patients from another opioid medication can result in fatal overdose with the first dose. Due to the mean elimination half-life of 20 hours of the fentanyl transdermal system, patients who are thought to have had a serious adverse event, including overdose, will require monitoring and treatment for at least 24 hours or until the adverse event has subsided.
Parenteral/Oral/Equianalgesic Potency Conversion
To convert adult patients from oral or parenteral opioids to pms-FENTANYL MTX, use Table 1.1.
Alternatively, for adult patients taking opioids or doses not listed in Table 1.1, use the following methodology:
- 1. Calculate the previous 24-hour analgesic requirement expressed in morphine equivalents.
- 2. Use Table 1.2 to convert this equianalgesic morphine dose to the recommended initial pms-FENTANYL MTX dose. This conversion recommendation is intentionally conservative to minimize the potential for pms-FENTANYL MTX overdosage.
For delivery rates in excess of 100 mcg/h, multiple systems may be applied.
Because of the gradual increase in serum fentanyl concentration over the first 24 hours following initial system application, the initial evaluation of the maximum analgesic effect of pms-FENTANYL MTX cannot be made before 24 hours of wearing. Patients should use short-acting analgesics after the initial dose application as needed until analgesic efficacy with pms-FENTANYL MTX is attained.
Initial Dose Selection in Elderly, Cachectic, or Debilitated Patients
In patients from these populations, pms-FENTANYL MTX may have altered pharmacokinetics due to poor fat stores, muscle wasting or altered clearance. Therefore, it may be appropriate, according to clinical judgment, to initiate these patients on pms-FENTANYL MTX at a dose level lower than that which the conversion tables recommend, including the use of the 12 mcg/h dose by itself or in combination with another dose, provided the patient is not opioid-naive (see CONTRAINDICATIONS). As with all pms-FENTANYL MTX patients, they should be carefully monitored for pain levels and adverse events, particularly hypoventilation.
Dose Adjustment
Dose titration is the key to success with opioid analgesic therapy. The recommended initial pms-FENTANYL MTX dose based upon the daily morphine dose is conservative, and 50% of patients are likely to require a dose increase after initial application of pms-FENTANYL MTX. If analgesia is insufficient after the initial application, the first dosage increase should occur three days after application, while all subsequent dosage increases should occur six days following the previous application.
Initial Dosage Increase: The initial pms-FENTANYL MTX dosage may be increased after 3 days based on the daily dose of supplemental analgesics required by the patients in the second or third day of the initial application.
All Other Dosage Increases: Physicians are advised that it may take up to 6 days after increasing the dose of pms-FENTANYL MTX for the patient to reach equilibrium on the new dose. Therefore, patients should wear a higher dose through two applications before any further increase in dosage is made on the basis of the average daily use of a supplemental analgesic.
Titration Dose Increment: Dosage of pms-FENTANYL MTX must be individualized according to the pain relief and tolerance of the patient. Appropriate dosage increments should be based on the daily dose of supplementary opioids, using the ratio of 45-59 mg/24 hours of oral morphine to a 12 mcg/h increase in pms-FENTANYL MTX dose. For example, if at the end of the required 6-day duration with a new patch strength, a patient is consuming an average daily dose of 150 mg of oral morphine, then the recommended pms-FENTANYL MTX dose increase would be 3x12 mcg/h, which can be achieved by three 12 mcg/h patches, or one of 25 mcg/h and one of 12 mcg/h. The use of 12 mcg/h in the ratio for calculation of pms-FENTANYL MTX dose increases allows for achieving smaller increments when needed, i.e. increments that are as close as possible to the actual average amount of supplementary oral morphine. Some patients may continue to require periodic supplemental doses of short-acting analgesic for “breakthrough” pain.
Maintenance
The majority of patients are adequately maintained with pms-FENTANYL MTX administered every 72 hours. A small number of patients may not achieve adequate analgesia using this dosing interval and may require systems to be applied every 48 hours rather than every 72 hours. If breakthrough pain repeatedly occurs at the end of the dosing interval, it is generally an indication for a dosage increase rather than more frequent administration. An increase in the pms-FENTANYL MTX dose should be considered before changing dosing intervals in order to maintain patients on a 72-hour regimen.
Some patients may require additional or alternative methods of opioid administration when the pms-FENTANYL MTX dose exceeds 300 mcg/h.
Decreased Dosing or Discontinuation of pms-FENTANYL MTX
Following the successful relief of severe pain, periodic attempts should be made to reduce the opioid dose. Lower doses or complete discontinuation of the opioid analgesic may become feasible due to physiological change or improved mental state of the patient.
For all downward titration, it is important to note that it takes 20 hours or more for the fentanyl serum concentration to fall by 50% after system removal.
Physical dependence with or without psychological dependence tends to occur with chronic administration of opioids, including pms-FENTANYL MTX. Withdrawal (abstinence) symptoms may occur following abrupt discontinuation of therapy. These symptoms may include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.
There have been reports that rapid discontinuation of opioid analgesics in patients who are physically dependent on opioids has resulted in serious withdrawal symptoms and uncontrolled pain.
Patients on prolonged therapy should be withdrawn gradually from the drug if it is no longer required for pain control. In patients who are appropriately treated with opioid analgesics and who undergo gradual withdrawal for the drug, these symptoms are usually mild (see WARNINGS AND PRECAUTIONS). Tapering should be individualized and carried out under medical supervision.
Patient should be informed that reducing and/or discontinuing opioids decreases their tolerance to these drugs. If treatment needs to be re-initiated, the patient must start at the lowest dose and titrate up to avoid overdose.
Safe Use of Tables 1.1 and 1.2
To convert patients to another opioid, remove pms-FENTANYL MTX and titrate the dose of the new analgesic, based upon the patient’s report of pain, until adequate analgesia has been attained.
Tables 1.1 and 1.2 should not be used to convert from pms-FENTANYL MTX to other opioid therapies. Because the conversion to pms-FENTANYL MTX is conservative, use of Tables 1.1 and 1.2 for conversion to other analgesic therapies can overestimate the dose of the new agent. Overdosage of the new analgesic agent is possible.
Table 1.1 1 : Dose Conversion Guidelines Dose Conversion Guidelines are Unidirectional and for Chronic Use. Use this table to convert patients from the Current Analgesic ONLY to pms-FENTANYL MTX. Do NOT use this table to convert patients from pms-FENTANYL MTX to other opioids; doing so may result in overdose and toxicity. | |||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Current Analgesic | Daily Dosage (mg/d) | ||||||||||||||||||||||||
| Oral morphine | 60-134 | 135-179 | 180-224 | 225-269 | 270-314 | 315-359 | 360-404 | ||||||||||||||||||
IM/IV morphine (based on a 1:3 IM:PO ratio) | 20-44 | 45-60 | 61-75 | 76-90 | NA2 | NA2 | NA2 | ||||||||||||||||||
| Oral oxycodone | 30-66 | 67-90 | 91-112 | 113-134 | 135-157 | 158-179 | 180-202 | ||||||||||||||||||
| Oral codeine | 150-447 | 448-597 | 598-747 | 748-897 | 898-1047 | 1048-1197 | 1198-1347 | ||||||||||||||||||
| Oral hydromorphone | 8-16 | 17-22 | 23-28 | 29-33 | 34-39 | 40-45 | 46-51 | ||||||||||||||||||
| IV Hydromorphone3 | 4-8.4 | 8.5-11.4 | 11.5-14.4 | 14.5-16.5 | 16.6-19.5 | 19.6-22.5 | 22.6-25.5 | ||||||||||||||||||
| ⇓ | ⇓ | ⇓ | ⇓ | ⇓ | ⇓ | ⇓ | |||||||||||||||||||
| pms-FENTANYL MTX Dose | 25 mcg/h | 37 mcg/h | 50 mcg/h | 62 mcg/h | 75 mcg/h | 87 mcg/h | 100 mcg/h | ||||||||||||||||||
1Table 1.1 should not be used to convert from pms-FENTANYL MTX to other therapies because this conversion to pms-FENTANYL MTX is conservative. Use of Table 1.1 for conversion to other analgesic therapies can overestimate the dose of the new agent. Overdosage of the new analgesic agent is possible (see DOSAGE AND ADMINISTRATION, Safe Use of Tables 1.1 and 1.2).
2 NA reflects insufficient data available for guidance. Prescribers should make these conversions very carefully and conservatively.
3The conversion ratio of parenteral hydromorphone to oral hydromorphone of 1:2 is based on clinical experience in patients with chronic pain. Reference: Parenteral Drug Therapy Manual, Vancouver General Hospital, Pharmaceutical Sciences Clinical Services.
Table 1.2#
Recommended Initial pms-FENTANYL MTX Dose Based Upon Daily Oral Morphine Dose‡
Oral 24-hour morphine (mg/day) | pms-FENTANYL MTX Dose (mcg/h) |
| Dose Adjustment | |
| 45-59 | 12 |
| Initiation Dose | |
| 60-134 | 25 |
| 135-179 | 25+12 |
| 180-224 | 50 |
| 225-269 | 50+12 |
| 270-314 | 75 |
| 315-359 | 75+12 |
| 360-404 | 100 |
| 405-494 | 125 |
| 495-584 | 150 |
| 585-674 | 175 |
| 675-764 | 200 |
| 765-854 | 225 |
| 855-944 | 250 |
| 945-1034 | 275 |
| 1035-1124 | 300 |
‡ In clinical trials these ranges of chronic daily oral morphine doses were used as a basis for conversion to fentanyl transdermal system. See Recommended Dose and Dosage Adjustment and Dose Adjustment.
# 12 mcg/h dose is included in this table for dose adjustment. 12 mcg/h dose generally should not be used as the initiating dose, except in the case of patients for whom clinical judgment deems it appropriate to start pms-FENTANYL MTX at less than 25 mcg/h; pms-FENTANYL MTX at any dose is contraindicated in opioid-naive patients (see CONTRAINDICATIONS).
Administration
Application of pms-FENTANYL MTX
pms-FENTANYL MTX should be applied to non-irritated and non-irradiated skin on a flat surface such as the chest, back, flank, or upper arm. Hair at the application site should be clipped (not shaved) prior to application. If the site of pms-FENTANYL MTX application must be cleansed prior to application of the system, do so with clear water. Do not use soaps, oils, lotions, alcohol, or any other agents that may irritate the skin or alter its characteristics. Allow the skin to dry completely prior to system application.
pms-FENTANYL MTX should be applied immediately upon removal from the sealed package. The system should not be altered, e.g. cut, in any way prior to its application. The transdermal system should be pressed firmly in place with the palm of the hand for 30 seconds, making sure the contact is complete, especially around the edges.
Each pms-FENTANYL MTX system may be worn continuously for 72 hours. A new system should be applied on a different skin site after removal of the previous transdermal system.
Disposal of pms-FENTANYL MTX
pms-FENTANYL MTX should be kept in a safe place, out of the sight and reach of children before, during and after use. pms-FENTANYL MTX should not be used in front of children, since they may copy these actions.
Upon removal, the used patch should be folded in half so that the adhesive side of the patch adheres to itself, and should be immediately packaged in such a way as to prevent accidental exposure to others, including children or pets until it can be returned to a pharmacy for proper disposal. If the drug adhesive layer accidentally contacts the skin, the area should be washed with clear water. Do not use soap, alcohol or other solvents as these may enhance the drug’s ability to penetrate the skin. Used patches still contain a considerable amount of drug. Unused patches should be removed from their pouch, folded so that the adhesive side of the patch adheres to itself, and disposed of similarly to used patches. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
pms-FENTANYL MTX should never be disposed of in household trash. Disposal via a pharmacy take-back program is recommended.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
Symptoms
The manifestations of fentanyl overdosage are an extension of its pharmacologic actions with the most serious effect being respiratory depression.
Treatment
For management of respiratory depression, immediate countermeasures include removing the pms-FENTANYL MTX and physically or verbally stimulating the patient. These actions can be followed by administration of a specific opioid antagonist such as naloxone. Following removal of the fentanyl transdermal system, serum concentrations of fentanyl decline slowly, with a mean half-life of 20 hours. Due to this the duration of respiratory depression following an overdose may be longer than the effects of the opioid antagonist’s action (the half-life of naloxone ranges from 30 to 81 minutes). The interval between IV antagonist doses should be carefully chosen because of the possibility of re-narcotization after system removal; repeated administration of naloxone may be necessary. Reversal of the opioid effect may result in acute onset of pain and release of catecholamines.
If the clinical situation warrants, establish and maintain a patent airway, administer oxygen and assist or control respiration as indicated, and use an oropharyngeal airway or endotracheal tube if necessary. If depressed respiration is associated with muscular rigidity, an intravenous neuromuscular blocking agent may be required to facilitate assisted or controlled respiration. Adequate body temperature and fluid intake should be maintained.
If severe or persistent hypotension occurs, the possibility of hypovolemia should be considered, and managed with appropriate parenteral fluid therapy.
ACTION AND CLINICAL PHARMACOLOGY
Pharmacodynamics
Fentanyl is an opioid analgesic which interacts predominantly with the µ-opioid receptor. Fentanyl produces analgesia, sedation, respiratory depression, constipation, and physical dependence but appears to have less emetic activity than other opioid analgesics. Fentanyl may produce muscle rigidity, miosis, cough reflex suppression, alterations in mood, bradycardia and bronchoconstriction.
Analgesic blood levels of fentanyl may cause nausea and vomiting directly by stimulating the chemoreceptor trigger zone, but nausea and vomiting are significantly more common in ambulatory than in recumbent patients, as is postural syncope.
Opioids increase the tone and decrease the propulsive contractions of the smooth muscle of the gastrointestinal tract. The resultant prolongation in gastrointestinal transit time may be responsible for the constipating effect of fentanyl. Because opioids may increase biliary tract pressure, some patients with biliary colic may experience worsening rather than relief of pain.
While opioids generally increase the tone of urinary tract smooth muscle, the net effect tends to be variable, in some cases producing urinary urgency, in others, difficulty in urination.
At therapeutic dosages, fentanyl usually does not exert major effects on the cardiovascular system. However, some patients may exhibit orthostatic hypotension and fainting.
Histamine assays and skin wheal testing in man indicate that histamine release rarely occurs with fentanyl. Assays in man show no clinically significant histamine release in dosages up to 50 mcg/kg.
Both the minimum effective concentration and the concentration at which toxicity occurs rise with increasing tolerance. The rate of development of tolerance varies widely among individuals.
Pharmacokinetics
pms-FENTANYL MTX provides continuous systemic delivery of fentanyl for up to 72 hours. Fentanyl is released along the concentration gradient existing between the drug adhesive layer of the system and the lower concentration in the skin.
Adults
Fentanyl transdermal system
Absorption: Fentanyl is released at a relatively constant rate. The concentration gradient existing between the matrix and the lower concentration in the skin drives drug release. Following initial fentanyl transdermal system administration, serum fentanyl concentrations increase gradually, generally levelling off between 12 and 24 hours and remaining relatively constant for the remainder of the 72-hour application period. Peak serum levels of fentanyl generally occur between 24 and 72 hours after the first application. The AUC and Cmax over a dosing interval at a steady state are approximately 40% higher than a single application
Serum fentanyl concentrations achieved are proportional to the fentanyl transdermal system delivery rate (see Table 1.3). With continuous use, serum fentanyl concentrations continue to rise for the first few system applications. After several sequential 72-hour applications, patients reach and maintain a steady-state serum concentration that is determined by individual variation in skin permeability and body clearance of fentanyl.
Table 1.3
Pharmacokinetic Parameters of TTS (fentanyl) in Adults
Mean (SD) Maximal Concentration Cmax (ng/mL) | Mean (SD) Time to Maximal Concentration Tmax (h) | |
| Fentanyl transdermal system 12 mcg/h | 0.3 (0.2) | 27.5 (9.6) |
| Fentanyl transdermal system 25 mcg/h | 0.6 (0.3) | 38.1 (18) |
| Fentanyl transdermal system 50 mcg/h | 1.4 (0.5) | 34.8 (15.4) |
| Fentanyl transdermal system 75 mcg/h | 1.7 (0.7) | 33.5 (14.5) |
| Fentanyl transdermal system 100 mcg/h | 2.5 (1.2) | 36.8 (15.7) |
After fentanyl transdermal system removal, serum fentanyl concentrations decline gradually, falling about 50% in approximately 20 (range 20-27) hours. Continued absorption of fentanyl from the skin accounts for a slower disappearance of the drug from the serum than is seen after an IV infusion, where the apparent half-life ranges from 3-12 hours.
Skin temperature elevation may enhance the absorption of transdermally-applied fentanyl (see WARNINGS AND PRECAUTIONS, Risk of Unintentional Increase in Drug Exposure). An increase in skin temperature through the application of a heating pad on low setting over the fentanyl transdermal system during the first 10 hours of a single application increased the mean fentanyl AUC value by 2.2-fold and the mean concentration at the end of heat application by 61%.
Distribution: Fentanyl is rapidly distributed to various tissues and organs, as indicated by the large volume of distribution (3 to 10 L/kg after intravenous dosing in patients). Fentanyl accumulates in skeletal muscle and fat and is released slowly into blood. Plasma protein binding of fentanyl has been reported to be approximately 84% in healthy subjects. In a study in cancer patients treated with transdermal fentanyl, plasma protein binding was on average 95% (range 77-100%). Fentanyl crosses the blood-brain barrier easily. It also crosses the placenta and is excreted in breast milk.
Metabolism: Skin does not appear to metabolize fentanyl delivered transdermally. Fentanyl is metabolized primarily in the liver. This was determined in a human keratinocyte cell assay and in clinical studies in which 92% of the dose delivered from the system was accounted for as unchanged fentanyl that appeared in the systemic circulation. In humans, the drug is metabolized primarily by N-dealkylation to norfentanyl and other inactive metabolites.
Excretion: Within 72 hours of IV fentanyl administration, approximately 75% of the fentanyl dose is excreted in urine, mostly as metabolites, with less than 10% representing unchanged drug. Approximately 9% of the dose is recovered in the feces, primarily as metabolites.
Special Populations and Conditions
Pediatrics Under 18 Years of Age: Fentanyl transdermal system was not studied in children under 2 years of age. Fentanyl concentrations were measured in more than 250 children aged 2 to 17 years who were applied fentanyl patches in the dose range of 12 to 300 mcg/hour. Adjusting for body weight, clearance (L/h/kg) appears to be approximately 80% higher in children 2 to 5 years old and 25% higher in children 6 to 10 years old when compared to children 11 to 16 years old, who are expected to have a similar clearance as adults.
Dosing recommendations for the safe and effective use of pms-FENTANYL MTX in this patient population have not been established, in view of the combination of:
- i) the variety of factors which could lead to overexposure from pms-FENTANYL MTX in children as compared to adults (including smaller body weight and significantly different body surface area; differential skin characteristics; potential for magnification, compared to adults, of the impact of amount of body fat stores, muscle wasting, fever, external heat), and
ii) the limitations in both formal PK data (as above) and exposure data (see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions, Chronic Pain Trials – Pediatrics)
Elderly or Debilitated Patients: In elderly, cachectic, or debilitated patients, pms-FENTANYL MTX may have altered pharmacokinetics due to poor fat stores, muscle wasting or altered clearance. The clearance of fentanyl may be reduced, and the terminal half-life prolonged (see DOSAGE AND ADMINISTRATION).
Data from intravenous studies with fentanyl suggest that elderly patients may have reduced clearance, a prolonged half-life, and they may be more sensitive to the drug than younger patients. In a study conducted with fentanyl transdermal system healthy elderly subjects had fentanyl pharmacokinetics which did not differ significantly from healthy young subjects although peak serum concentrations tended to be lower and mean half-life values were prolonged to approximately 34 hours. Elderly patients should be observed carefully for signs of fentanyl toxicity and the dose reduced if necessary (see DOSAGE AND ADMINISTRATION).
Hepatic Impairment: In a study conducted with patients with hepatic cirrhosis, the pharmacokinetics of a single 50 mcg/hr application of fentanyl transdermal system were assessed. Although tmax and t1/2 were not altered, the mean plasma Cmax and AUC values increased by approximately 35% and 73%, respectively, in these patients. Based on a population pharmacokinetic model, simulated data in patients with different grades of impaired liver function treated with transdermal fentanyl suggest that the steady-state AUC of patients with Grade B (Child-Pugh Score = 8) and Grade C (Child- Pugh Score = 12.5) liver disease would be approximately 1.36 and 3.72 times larger, respectively, compared with patients with normal liver function (Grade A [Child-Pugh Score 5.5]).
Patients with hepatic impairment should be observed carefully for signs of fentanyl toxicity and the dose of pms-FENTANYL MTX reduced if necessary.
Renal Impairment: Data obtained from a study administering IV fentanyl in patients undergoing renal transplantation suggest that the clearance of fentanyl may be reduced in this patient population. If patients with renal impairment receive pms-FENTANYL MTX, they should be observed carefully for signs of fentanyl toxicity and the dose should be reduced if necessary.
STORAGE AND STABILITY
pms-FENTANYL MTX is stable for 2 years from date of manufacturing when stored in sealed pouch between 15°C and 25°C. Do not refrigerate. Protect from freezing.
Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store pms-FENTANYL MTX securely, in a location not accessible by others. Keep out of the sight and reach of children and pets.
SPECIAL HANDLING INSTRUCTIONS
pms-FENTANYL MTX should be kept in a safe place, out of the sight and reach of children before, during and after use.
Do not cut pms-FENTANYL MTX.
Upon removal, the used patch should be folded in half so that the adhesive side of the patch adheres to itself, and should be immediately packaged in such a way as to prevent accidental exposure to others, including children or pets until it can be returned to a pharmacy for proper disposal. If the drug adhesive layer accidentally contacts the skin, the area should be washed with clear water. Do not use soap, alcohol or other solvents as these may enhance the drug’s ability to penetrate the skin. Used patches still contain a considerable amount of drug. Unused patches should be removed from their pouch, folded so that the adhesive side of the patch adheres to itself, and disposed of similarly to used patches. If temporary storage is required before disposal, a sealed child-proof container, such as a biohazard waste container or a lockable medication box could be obtained from a pharmacy.
Wash hands with water only, after applying or removing the patch.
DOSAGE FORMS, COMPOSITION AND PACKAGING
pms-FENTANYL MTX is a transdermal patch providing continuous systemic delivery of fentanyl, a potent opioid analgesic, for 72 hours.
The construction of the fentanyl transdermal system is a typical matrix-based system where the matrix acts simultaneously as drug reservoir and as adhesive layer. The resorption of the active ingredient to the systemic circulation is controlled by the contact area with the skin. There is no release-controlling element in this type of system. The matrix is covered by a flexible transparent foil (backing foil) which enables a comfortable wearing of the system and protects the matrix from outer influences during application.
The opposite side of the matrix is covered by a siliconized, easy removable protective foil (release liner), which has to be removed prior to application.
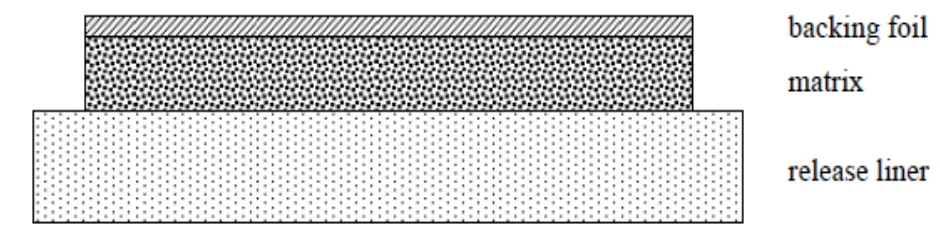
pms-FENTANYL MTX is available in five different strengths. Each system is labelled with a nominal flux which represents the average amount of drug delivered to the systemic circulation per hour across average skin. The active component of the system is fentanyl. The amount of fentanyl released from each system per hour is proportional to the surface area. The release rate of fentanyl in [mcg/h] correlates directly to the Fentanyl content (2.1 mg, 4.2 mg, 8.4 mg, 12.6 mg and 16.8 mg) and to the effective release area of the patches (5.25 cm2, 10.5 cm2, 21 cm2, 31.5 cm2 and 42 cm2).
Total fentanyl contents and system sizes for the five strengths are summarized below:
Table 1.4
Dose (mcg/h) | (cm2) | Fentanyl content (mg) |
| 12 | 5.25 | 2.1 |
| 25 | 10.5 | 4.2 |
| 50 | 21 | 8.4 |
| 75 | 31.5 | 12.6 |
| 100 | 42 | 16.8 |
Nonmedicinal Ingredients: acrylic-vinylacetate copolymer adhesive, polyethyleneterephthalate backing foil, and siliconized polyethyleneterephthalate release liner.
pms-FENTANYL MTX is supplied in cartons containing 5 individually packaged systems. Each patch system is packaged in foil paper/PE/AL/PE sachets.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: fentanyl base
Chemical Name: N-phenyl-N-(1-2-phenylethyl-4-piperidyl) propanamide
Molecular Formula and Molecular Mass: C22H28N2O 336.46 g/mol
Structural Formula:
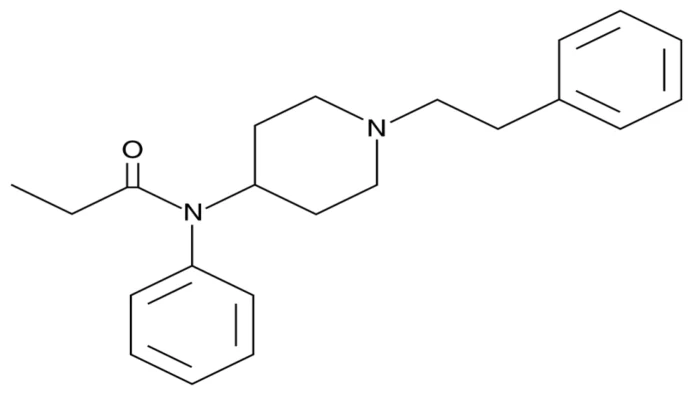
Physiochemical Properties: Fentanyl base is a white or slightly creamy white crystalline powder with a melting range of 84-86°C. It is very slightly soluble in water (0.16 mg/mL), slightly soluble in a neutral buffer (1.2 mg/mL), freely soluble in ethanol, acetonitrile and methylene chloride. The n-octanol:water partition coefficient is 860:1. The pKa is 8.4.
CLINICAL TRIALS
Comparative Bioavailability Study Summary
This was a randomised, double blinded, single-dose, two-period crossover bioequivalence study of pms-FENTANYL MTX 100 mcg/h versus DURAGESIC 100 Patches (Janssen-Ortho) for 72 hours to assess the relative bioavailability of fentanyl from two different transdermal systems in healthy subjects.
Twenty-eight healthy male subjects between ages of 18 to 45 were enrolled in the study, and 26 subjects completed the clinical phase of the study. The statistical and pharmacokinetic analyses were performed based on 26 (between ages of 22 to 44 with a median of 34 years old) subjects.
Fentanyl (1 patch, 100 mcg/h) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | pms-FENTANYL MTX | DURAGESIC® ‡ | % Ratio of Geometric Means | 90% Confidence Interval |
AUC72 (h*pg/mL) | 88744.4 94765.7 (38.3) | 91513.1 94060.9 (23.3) | 96.97 | 90.56 – 103.84 |
AUC1 (h*pg/mL) | 109159.4 116459.5 (37.8) | 112919.3 116576.4 (25.7) | 96.67 | 90.56 – 103.19 |
AUC1 (h*pg/mL) | 113363.6 121267.4 (38.6) | 117847.7 122119.4 (27.7) | 96.20 | 90.11 – 102.69 |
Cmax (pg/mL) | 1817.15 1959.66 (42.1) | 1939.36 1998.54 (24.5) | 93.70 | 86.84 – 101.10 |
| Tmax§ | 23.77 (38.8) | 34.16 (37.1) | ||
t½§ (h) | 17.62 (17.2) | 18.47 (19.8) | ||
pms-FENTANYL MTX 100mcg/h manufactured for Pharmascience Inc.
‡DURAGESIC®, manufactured by Janssen-Ortho Inc., was purchased in Canada
§ expressed as arithmetic mean (%CV) only
Cancer Trials – Adults
During the pre-marketing phase, clinical trials were conducted in 153 patients to evaluate the efficacy and safety of fentanyl transdermal system therapy for pain due to cancer. The studies were open-labelled with the exception of one trial which incorporated a randomized, double-blind crossover component (fentanyl transdermal system therapy versus placebo) in 46 patients. Doses in these studies varied between 25 and 600 mcg/h. Patients used fentanyl transdermal system continuously for up to 866 days; 56% received fentanyl transdermal therapy for over 30 days, 28% continued treatment for more than 4 months and 10% used fentanyl transdermal therapy for more than 1 year. The results of these studies demonstrated that: 1) satisfactory analgesia was achieved in the majority of patients, and 2) fentanyl transdermal therapy was accepted by cancer patients, their caregivers and physicians.
Since the introduction of fentanyl transdermal therapy, additional trials have been conducted in approximately 350 chronic cancer pain patients to confirm earlier conclusions. In the largest of these, a Canadian post-marketing surveillance study in 199 patients, a reduction in pain intensity and improved pain relief and well-being were observed in the 127 patients evaluable for efficacy.
Patient preference for fentanyl transdermal therapy over their previous analgesic therapy was also observed. In these patients, the average treatment duration was 68 days (range: 17-118). The mean dose for all study patients increased from 51 mcg/h at baseline to 128 mcg/h at the last dose on therapy.
Chronic Non-Cancer Pain (CNCP) Trials – Adults
The safety of fentanyl transdermal system has been evaluated in 908 patients with chronic pain conditions from a total of 5 trials. Pain conditions included low back pain, neuropathic pain and AIDS-associated pain. One of the two primary trials was an open-label single-arm one-year study with 530 patients (FEN-INT-13), and the other an open-label two-month crossover trial with 250 patients and slow-release morphine as the comparator (FEN-INT-12). In both trials, neuropathic and nociceptive pain were present in 50% and 71% of the patients, respectively. The most frequent body regions causing pain were the lower back (43% of the patients) and lower limbs (22%); the body systems most frequently responsible for pain were the nervous (45%), and musculoskeletal systems and connective tissue (43%). The most common etiology was degenerative, mechanical (38%) or trauma (26%). Patients ranged from 22 to 88 years in age, with a median age of 49 years. Patients had experienced chronic pain for a median duration of six years, and reported at least moderate pain control over the preceding 7 days from a stable daily dose of opioids.
For more detail on the safety profiles from fentanyl transdermal system trials, see ADVERSE REACTIONS, Clinical Trial Adverse Drug Reactions.
DETAILED PHARMACOLOGY
Animal Pharmacology
Fentanyl exerts a typical opioid analgesic effect. Results were obtained in animal studies to define this activity.
Fentanyl was effective in the Haffner tail clamp test in mice, a test used to detect opioid analgesic activity. The ED50 for fentanyl was calculated to be 0.08 mg/kg SC and that for morphine, 15 mg/kg SC. The onset of the analgesic effect occurred in 4 minutes with fentanyl and the duration was 30 minutes.
The compound exhibited activity in the tail-withdrawal test in rats, a test measuring the time elapsing for a rat to remove its tail from a water bath heated to 55°C. Fentanyl was found to be 269 times more potent than morphine after subcutaneous administration and had a faster onset and shorter duration of action than the latter compound.
Fentanyl has been shown to produce analgesia in rabbits as evidenced by the failure of a painful stimulus applied to the trigeminal nerve to produce desynchronization of the EEG. Depression of the cortical activating system was evidenced by the increased cortical potentials seen after administration of fentanyl.
Low concentrations of fentanyl shifted the oxygen dissociation curve to the left, whereas high concentrations were ineffective.
Fentanyl, like other potent opioid analgesics, produces skeletal muscle rigidity. This muscular rigidity can be blocked or reversed by succinylcholine. Fentanyl has been demonstrated to have no effect on neuromuscular transmission in anesthetized cats.
The interaction of fentanyl with diazepam and pancuronium was investigated in the anesthetized dog. Fentanyl alone in a dose of 0.5 mg/kg IV decreased heart rate, cardiac output and arterial pressure in these animals. The administration of diazepam, 0.5 mg/kg IV after fentanyl caused some reversal of the decrease in heart rate and cardiac output. The subsequent administration of pancuronium completely reversed the decreased heart rate, cardiac output and arterial pressure. A decrease in cardiac output and arterial pressure leads to decreased pulmonary arterial pressure and blood flow.
Fentanyl was administered to anesthetized dogs in increasing dosages from 0.002 to 0.16 mg/kg IV. These doses caused no change in left ventricular pressure. Doses up to 0.03 mg/kg increased left ventricular maximum dp/dt, heart rate and cardiac afterload. Higher doses decreased pressure-time index and myocardial oxygen consumption by approximately 30%. Higher doses of fentanyl, administered rapidly, produced a fall in mean peripheral arterial pressure.
Moreover, other studies conducted in anesthetized dogs demonstrate that fentanyl decreases lactate production in the ischemic ventricle. This decrease in myocardial lactate production indicates that the compound decreased myocardial oxygen demand. Cardiovascular dynamics are not compromised in anesthetized dogs receiving large doses of fentanyl or fentanyl plus nitrous oxide.
In anesthetized cats, fentanyl produced a central sympatho-inhibitory effect, with the main site of action being the medulla oblongata.
Fentanyl, administered to isolated dog Purkinje and ventricular muscle fibres, was devoid of any action on cardiac transmembrane potentials.
When fentanyl was administered to anesthetized dogs with experimental coronary occlusion at a dose of 0.05 mg/kg IV, it markedly decreased heart rate, left ventricular maximum dp/dt and cardiac output. These effects were reversed by the administration of atropine. Fentanyl was effective in preventing the occurrence of ventricular fibrillation in these animals.
Intra-arterial injections of fentanyl in anesthetized dogs in doses of 0.01 and 0.05 mg caused no change in femoral blood flow. Intra-arterial injection of 0.2 mg of fentanyl caused a decrease in vascular resistance indicating that higher doses of the compound possess a vasodilator component.
In anesthetized dogs, fentanyl significantly lowered pulmonary arterial pressure as well as pulmonary arterial driving pressure with little change in pulmonary vascular resistance and compliance. This reduction of pulmonary arterial pressure by fentanyl is caused by a decrease in pulmonary blood flow resulting from a decrease in cardiac output and mean arterial pressure.
In mice, fentanyl induced an increase in spontaneous motor activity, Straub tail reaction, increased muscle tone, respiratory depression and convulsions.
In dogs, fentanyl induced decreased motor activity, ataxia, decreased responsiveness to auditory and painful stimuli, respiratory depression, salivation and defecation. Nalorphine, 1 mg/kg IV, caused an immediate reversal of the central depression induced by fentanyl, indicating that the compound was acting by an opioid-like mechanism.
Fentanyl induced a constipating effect in mice. In approximately equivalent analgesic doses, morphine appeared to have a greater constipating effect.
Fentanyl possesses a spasmogenic effect on the sphincter of Oddi in guinea pigs.
Human Pharmacology
The pharmacokinetics of fentanyl transdermal system were determined in serum of human surgical patients using radioimmunoassay and GC mass spectrophotometry. The time course of serum fentanyl concentrations was demonstrated during application and after removal of fentanyl transdermal system applied for 24 hours, daily application for 3 days, and system application for a 72-hour period.
Following initial system application, there is a 1 to 2 hour lag time before serum fentanyl concentrations are detected (0.2 mg/mL). Serum fentanyl concentrations increase gradually, generally levelling off between 12 and 24 hours. The amount of drug delivered by fentanyl transdermal system is proportional to the size of the system. Absorption of fentanyl continues throughout the entire 72-hour dosing interval. The serum fentanyl kinetics are linear within the dose range studied (25-100 mcg/h) and do not change with multiple doses.
Following system removal, serum fentanyl concentrations decline gradually, falling about 50% in approximately 20 hours. Following a 72-hour application, the mean half-life ranges from 20-27 hours. Continued absorption of fentanyl from the skin accounts for a slower disappearance of the drug from the serum than is seen after an IV infusion, where the apparent half-life is 7 hours. Fentanyl delivered transdermally is 92% bioavailable.
As with other opioid analgesics, fentanyl produces respiratory depression which may last longer than the analgesic effect. The absolute duration cannot be stated definitively, because it will vary considerably depending on a number of factors, such as size and number of doses, method of administration, physical condition of the patient, other drugs given, if any, and the parameters of respiratory function that are observed. It has been reported, however, that in comparison with meperidine or morphine at doses producing similar degrees of respiratory depression, the onset and peak effect occur sooner with fentanyl and the observed parameters return to, or toward, control levels more rapidly.
The ventilatory effects of fentanyl, within the therapeutic range of 0.75 ng/mL to 3 ng/mL, were evaluated in normal volunteers. End tidal CO2 concentration increased and the slope of the ventilatory-CO2 response curve decreased with increasing fentanyl concentration. At equianalgesic serum concentrations, there were no significant differences between alfentanil, morphine and fentanyl on ventilatory effects.
Fentanyl can produce skeletal muscle rigidity, the occurrence of which is related primarily to the speed of intravenous injection.
Rarely, there have been reports of bronchoconstriction in conjunction with the use of IV fentanyl. It has been said that this effect is usually encountered in patients with allergic diathesis, such as bronchial asthma, and may be attributed to histamine release.
In general, fentanyl appears to produce only minimal effects on the cardiovascular system. There is a tendency toward transient bradycardia. There may be some hypotension, particularly following the administration of nitrous oxide to unstressed patients. However, in patients undergoing surgery, even when in relatively poor physical condition and given moderate to large doses, the relative stability of cardiovascular function has been particularly noted as well as the ability to reposition patients without significant blood pressure changes.
Observations on the occurrence of skin whealing at the injection site and assays of plasma histamine indicate that fentanyl rarely causes histamine release, and is therefore not likely to be associated with the opioid-induced hypotension attributed to this phenomenon.
Consistent with results seen in animal studies, fentanyl appears to be associated with minimal emetic activity in man. However, data from clinical studies can be difficult to interpret because they are subject to distortions introduced by such elements as the procedures being performed and the other drugs used.
TOXICOLOGY
Fentanyl has been administered by the oral, intravenous, intramuscular or subcutaneous routes either acutely or subacutely to rats, mice, guinea pigs, hamsters and cats. Laboratory animals tolerate relatively large doses of fentanyl in comparison to the doses recommended for human use (generally not more than 0.002-0.005 mg/kg).
Acute Toxicity
Intravenous LD50 determinations showed that the rat and guinea pig, with an LD50 in the 2-3 mg/kg range, were the most sensitive species tested; the mouse and dog were more tolerant, having LD50’s in the 11-14 mg/kg range. Intramuscular LD50 determinations showed that the rat was the most sensitive species tested, having an LD50 of 1 mg/kg; the most tolerant species was the hamster with an LD50 of 65 mg/kg.
Carcinogenicity
In a two-year carcinogenicity study conducted in rats, fentanyl was not associated with an increased incidence of tumors at subcutaneous doses up to 33 mcg/kg/day in males or 100 mcg/kg/day in females (0.16 and 0.39 times the human daily exposure obtained via the 100 mcg/h patch based on AUC0-24h comparison).
Subacute Toxicity – Rats
Four weeks of repeated administration of fentanyl by the intramuscular route (0, 0.1 and 0.4 mg/kg/day) and intravenous routes (0, 0.01, 0.02, 0.03, 0.05 and 0.075 mg/kg/day) were without effect on hematologic profile, food consumption, or gross or microscopic examination, with the exception of some local irritation at intramuscular sites. Intramuscular administration was associated with a low mortality incidence; following intravenous administration, mortality was present at 0.03 mg/kg/day and above.
Oral administration of fentanyl at doses of 5, 10, 20, 40, 80, 160 and 320 mg/kg/day for 14 days resulted in mortality at 10 mg/kg/day and above; survivors were noted to have bloody urine and bloody diarrhea which subsided during the second week of treatment.
Subacute Toxicity – Dogs
Intramuscular administration of 0, 0.1 and 0.4 mg/kg/day of fentanyl for four weeks did not produce significant effects on hematologic profile, body weight, organ weight, or gross or microscopic examinations. Intravenous administration of 0.1, 0.3 and 1mg/kg/day for four weeks did not produce any mortality or significant gross lesions.
Physical signs associated with intravenous treatment included slight decrease in body weight, sedation, hypercapnia and decreased food consumption at all dosage levels, and convulsions principally at the high-dosage level. In addition, dogs in the high-dosage group had some pathology of the liver (mild cholestasis and granular cytoplasm in hepatocytes) and kidney (granular casts in collecting tubules or vacuolation) that may have been drug-related; however, none of the lesions were considered severe or irreversible.
Tissue Irritation Studies
Tissue irritation studies demonstrated that fentanyl transdermal system elicited mild skin irritation and had little or no sensitization potential.
Studies of rabbits receiving 28 and 90 days of transdermal fentanyl administration showed no differences among the 3 treatment groups (negative control, TT placebo and TT fentanyl) with regard to hematology, blood chemistries or histological evaluations of skin and systemic tissues.
Teratology
Adult rats of a Wistar substrain were used in studies to determine the possible teratological effects of fentanyl on dams and their offspring. Three successive generations received fentanyl subcutaneously during the first 21 days of pregnancy, in daily doses of 0.04, 0.08, 0.16 and 0.31 mg/rat. No congenital abnormalities were produced in the experimental groups, but there were dose-related decreases in dam survival, survival in utero and average litter size and weight. A slight delay in delivery time and an increased mortality of the newborn were also observed in rats receiving fentanyl.
Mutagenicity
Fentanyl tested negative in the Ames Assay, UDS Assay and Mammalian Cell Transformation Assay. Fentanyl did not cause chromosomal aberrations in vitro in human lymphocytes or in Chinese hamster ovary cells in the presence or absence of an exogenous metabolic source.
In the L5178Y Mouse Lymphoma Assay, fentanyl was nongenotoxic without activation. With activation, fentanyl at concentrations of 37 mcg/mL and higher demonstrated mutation frequencies above control levels; these concentrations are approximately 2000 times greater than plasma levels observed with a fentanyl transdermal system in clinical use.
REFERENCES
Preclinical
- 1. Daskalopoulos N, Laubie M, Schmitt H. Localization of the central sympatho-inhibitory effect of a narcotic analgesic agent, fentanyl, in cats. Eur. J. Pharmacol. 1975;33:91-97.
- 2. Freye E. Cardiovascular effects of high dosages of fentanyl, meperidine and naloxone in dogs. Anesth. Analg. 1974;53:40-47.
- 3. Gardocki JF, Yelnosky J. A study of some of the pharmacologic actions of fentanyl citrate. Toxic. Appl. Pharmacol. 1964;6:48-62.
- 4. Jageneau AHM, van Gerven W, Kruger R, van Belle H, Reneman RS. An improved animal model for studying the effect of drugs on myocardial metabolism during ischemia, in: Roy PE and Rona G. eds.: Recent Advances in Studies on Cardiac Structure and Metabolism. Vol. 10, Baltimore, University Park Press, 1975:331-341.
- 5. Janssen PAJ, Niemegeers CJE, Dony JGH. The inhibitory effect of fentanyl and other morphine-like analgesics on the warm water induced tail withdrawal reflex in rats. Arzneim.-Forsch. 1963;13:502-507.
- 6. Liu WS, Bidway AV, Stanley TH, Isern-Amaral J. Cardiovascular dynamics after large doses of fentanyl and fentanyl plus N2O in the dog. Anesth. Analg. 1976;55:168-172.
- 7. Liu WS, Bidway AV, Stanley TH, Loeser EA, Bidway V. The cardiovascular effects of diazepam and of diazepam and pancuronium during fentanyl and oxygen anesthesia. Can. Anæsth. Soc. J. 1976;23:395-403.
- 8. Petty C, Bageant T. The effect of morphine, meperidine, fentanyl and naloxone on the oxyhemoglobin dissociation curve. J. Pharmacol. Exp. Ther. 1974;190:176-179.
- 9. Wojtczak J, Beresewicz A. Electrophysiological effects of the neuroleptanalgesic drugs on the canine cardiac tissue. Naunyn-Schmiedeberg's Arch. Pharmacol. 1974;286:211-220.
- 10. Zattoni J, Giunta F. Behavioral and electroencephalographic changes induced by a new synthetic morphine-like analgesic in the rabbit. Boll. Soc. Ital. Biol. Sper. 1964;40:1491-1501.
Clinical
- 11. Allen GD, Meyer RA. An evaluation of the analgesic activity of meperidine and fentanyl. Anesth. Progr. 1973;20:72-75.
- 12. Ahmedzai S and Brooks D, et al. Transdermal fentanyl versus sustained-release oral morphine in cancer pain: preference, efficacy, and quality of life. J. Pain Symptom. Manage. 1997;13:254-261.
- 13. Andrews CJH, Prys-Roberts C. Fentanyl – a review. Clin. Anesthesiol. 1983;1:97-122.
- 14. Caplan RA, Southam M. Transdermal drug delivery and its application to pain control. Adv. Pain Res. 1990;14:233-40.
- 15. Duthie DJR, Rowbotham DJ, Wyld R, Henderson PD, Nimmo WS. Plasma fentanyl concentrations during transdermal delivery of fentanyl to surgical patients. Br J Anæsth. 1988;60:614-18.
- 16. Ferrari HA, Gorten RJ, Talton IH, Canent R, Goodrich JK. The action of droperidol and fentanyl on cardiac output and related hemodynamic parameters. Southern Med. J. 1974;67:49-53.
- 17. Foley K. The treatment of cancer pain. NEJM 1985;313(2):84-95.
- 18. Foley KM, In: Cancer, Principles and Practice of Oncology, 4th Ed., VT Devita, Jr., S Hellman, SA Rosenberg (Ed.), JB Lippincott Co., Philadelphia, pp. 2417-2448, 1993.
- 19. Gourlay GK, Cousins MJ. Strong analgesics in severe pain. Drugs 1984;28:79-91.
- 20. Holley FO, van Steennis CV. Postoperative analgesia with fentanyl: pharmacokinetics and pharmacodynamics of constant-rate IV and transdermal delivery. Br. J. Anæsth. 1988;60:608-613.
- 21. Jeal W and Benfield P. Transdermal fentanyl: a review of its pharmacological properties and therapeutic efficacy in pain control. Drugs 1997;53:109-138.
- 22. Miser AW, Narang PK, Dothage JA, Young RC, Sindelar W, Miser JS. Transdermal fentanyl for pain control in patients with cancer. Pain 1989;37:15-21.
- 23. Plezia PM, Kramer TH, Linford J, Hameroff SR. Transdermal fentanyl: pharmacokinetics and preliminary clinical evaluation. Pharmacotherapy 1989;9:2-9.
- 24. Schleimer R, Benjamine E, Eisele J, Henderson G. Radioimmunoassay of fentanyl pharmacokinetics in man. Proc. Western Pharmacol. Soc. 1976;19:237-238.
- 25. Simmonds MA, Blain C, Richenbacher J, Southam MA, Hershey MS. A new approach to the administration of opiates: TTS (fentanyl) in the management of pain in patients with cancer. J. Pain Symptom Management 1988;3(3):S18.
- 26. Sokoll MD, Hoyt JL, Gergis SD. Studies in muscle rigidity, nitrous oxide and narcotic analgesic agents. Anesth. Analg. 1972;51:16-20.
- 27. Stoelting RK, Gibbs RS, Creasser CS, Peterson C. Hemodynamic and ventilatory responses to fentanyl, fentanyl-droperidol and nitrous oxide in patients with acquired valvular heart disease. Anesthesiology 1975;2:319-324.
- 28. Tammisto T, Takki S, Tiokka P. A comparison of the circulatory effects in man of the analgesics fentanyl, pentazocine and pethidine. Brit. J. Anaesth. 1970;42:317-324.
- 29. Varvel JR, Shafer SL, Hwang SS, Coen PA, Stanski DR. Absorption characteristics of transdermally administered fentanyl. Anesthesiology 1989;70:928-34.
- 30. Woodroffe MA, Hays H. Fentanyl transdermal system. Pain management at home. Can Fam Physician 1997:43:268-272.
- 31. Allan L, Hays H, Jensen N-H, Le Polain de Waroux B, Bolt M, Donald R, Kalso E. Randomised crossover trial of transdermal fentanyl and oral morphine in chronic non-cancer pain. British Medical Journal 2001; 322:1154-58.
- 32. Milligan K, Lanteri-Minet M, Borchert K, Helmers H, Donald R, Kress H-G, Adriaensen H, Moulin D, Jarvimaki V, Haazen L. Evaluation of long-term efficacy and safety of transdermal fentanyl in the treatment of chronic non-cancer pain. Journal of Pain 2001; 2(4): 197-204.
- 33.
Parentral Drug Therapy Manual, Vancouver General Hospital, Pharmaceutical Sciences
Clinical Services.
- 34.
Skater TL. Practice Guidelines for Transdermal Opioids in Malignant Pain. Drugs: 64
(23) 2629 – 2638, 2004.
- 35.
Berdine HJ, Nesbit SA. Equianalgesic Dosing of Opioids. Journal of Pain & Palliative
Care Pharmacotherapy: 20 (4) 79 – 84, 2006.
- 36. Johnson BL, Gross J. Chapter 8, Pharmacological Treatment of Cancer Pain in Handbook of Oncology Nursing, Jones & Bartlett Publishers, 1998. p. 313 – 327.
- 37.
Ripamont, C. Pharmacology of Opioid Analgesia: Clinical Principles in Cancer Pain:
Assessment and Management, edited by Bruera E and Portenoy RK. Cambridge
University Press, 2003. p. 124.
- 38. Janssen Inc. Product Monograph for NDURAGESIC® (fentanyl transdermal system), Control No. 232433, Date of Revision: December 16, 2019.