


Product Monograph - Pro-Levofloxacin
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 02/2026 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance | 02/2026 |
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
1 INDICATIONS ................................................................................................................ 4
1.1 Pediatrics ............................................................................................................... 5
1.2 Geriatrics ............................................................................................................... 6
2 CONTRAINDICATIONS ................................................................................................... 6
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .............................................................. 6
4 DOSAGE AND ADMINISTRATION .................................................................................. 6
4.1 Dosing Considerations ........................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment ....................................................... 7
4.4 Administration ....................................................................................................... 9
4.5 Missed Dose .......................................................................................................... 9
5 OVERDOSAGE ............................................................................................................... 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 10
7 WARNINGS AND PRECAUTIONS .................................................................................. 10
7.1 Special Populations .............................................................................................. 16
7.1.1 Pregnant Women ............................................................................................. 16
7.1.2 Breast-feeding .................................................................................................. 16
7.1.3 Pediatrics ......................................................................................................... 17
7.1.4 Geriatrics ......................................................................................................... 17
8 ADVERSE REACTIONS ................................................................................................. 17
8.1 Adverse Reaction Overview ................................................................................. 17
8.2 Clinical Trial Adverse Reactions ............................................................................ 18
8.2.1 Clinical Trial Adverse Reactions – Pediatrics..................................................... 19
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 19
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 20
8.5 Post-Market Adverse Reactions ........................................................................... 21
9 DRUG INTERACTIONS ................................................................................................. 23
9.2 Drug Interactions Overview ................................................................................. 23
9.4 Drug-Drug Interactions ........................................................................................ 23
9.5 Drug-Food Interactions ........................................................................................ 26
9.6 Drug-Herb Interactions ........................................................................................ 26
9.7 Drug-Laboratory Test Interactions ....................................................................... 26
10 CLINICAL PHARMACOLOGY ........................................................................................ 26
10.1 Mechanism of Action ........................................................................................... 26
10.2 Pharmacodynamics ............................................................................................. 27
10.3 Pharmacokinetics ................................................................................................ 28
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 34
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 34
PART II: SCIENTIFIC INFORMATION ........................................................................................ 35
13 PHARMACEUTICAL INFORMATION ............................................................................. 35
14 CLINICAL TRIALS ......................................................................................................... 36
14.1 Clinical Trials by Indication ................................................................................... 36
14.2 Comparative Bioavailability Studies ..................................................................... 52
15 MICROBIOLOGY .......................................................................................................... 53
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 59
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 67
PATIENT MEDICATION INFORMATION .................................................................................... 68
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
PRO-LEVOFLOXACIN (levofloxacin tablets) is indicated for the treatment of adults with bacterial infections caused by susceptible strains of the designated microorganisms in the infections listed below.
- To reduce the development of drug-resistant bacteria and maintain the effectiveness of PRO-LEVOFLOXACIN and other antibacterial drugs, PRO-LEVOFLOXACIN should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
- Upper Respiratory Tract
Acute bacterial sinusitis (mild to moderate) due to Streptococcus pneumoniae, Haemophilus influenzae, or Moraxella (Branhamella) catarrhalis.
Restrict the use of PRO-LEVOFLOXACIN to settings where no other treatment options exist, and the clinical presentation meets the diagnostic criteria for acute bacterial sinusitis.1
- Lower Respiratory Tract
Acute bacterial exacerbations of chronic bronchitis (mild to moderate) due to Staphylococcus aureus, Streptococcus pneumoniae, Haemophilus influenzae, Haemophilus parainfluenzae, or Moraxella (Branhamella) catarrhalis. PRO-LEVOFLOXACIN should not be prescribed to patients with acute bacterial exacerbations of simple/uncomplicated chronic obstructive pulmonary disease (i.e., patients who have chronic obstructive pulmonary disease without underlying risk factors). 2
Community-acquired pneumonia (mild, moderate and severe infections) due to Staphylococcus aureus, Streptococcus pneumoniae (including penicillin-resistant strains), Haemophilus influenzae, Haemophilus parainfluenzae, Klebsiella pneumoniae, Moraxella (Branhamella) catarrhalis, Chlamydia pneumoniae, Legionella pneumophila, or Mycoplasma pneumoniae (see 4 DOSAGE AND ADMINISTRATION, and 14 CLINICAL TRIALS).
Nosocomial pneumonia due to methicillin-susceptible Staphylococcus aureus, Pseudomonas aeruginosa, Serratia marcescens, Escherichia coli, Klebsiella pneumoniae, Haemophilus influenzae or Streptococcus pneumoniae. Adjunctive therapy should be used as clinically indicated. Where Pseudomonas aeruginosa is a documented or presumptive pathogen, combination therapy with an anti-pseudomonal β-lactam is recommended.
1 Canadian clinical practice guidelines for acute and chronic rhinosinusitis. Desrosiers et al. Allergy, Asthma and Clinical Immunology, 2011, 7:2
2 Canadian Thoracic Society recommendations for management of chronic obstructive pulmonary disease – 2008 update – highlights for primary care. O’Donnell et al. Can Respir J 2008; 15 (Suppl A): 1A-8A.
PRO-LEVOFLOXACIN is not indicated for acute bronchitis.
- Skin and Skin Structure
Uncomplicated skin and skin structure infections (mild to moderate) due to Staphylococcus aureus or Streptococcus pyogenes.
Complicated skin and skin structure infections (mild to moderate), excluding burns, due to Enterococcus faecalis, methicillin-sensitive Staphylococcus aureus, Streptococcus pyogenes, Proteus mirabilis, or Streptococcus agalactiae.
- Urinary Tract
Complicated urinary tract infections (mild to moderate) due to Enterococcus (Streptococcus) faecalis, Enterobacter cloacae, Escherichia coli, Klebsiella pneumoniae, Proteus mirabilis, or Pseudomonas aeruginosa (see 4 DOSAGE AND ADMINISTRATION and 14 CLINICAL TRIALS).
Uncomplicated urinary tract infections (mild to moderate) due to Escherichia coli, Klebsiella pneumoniae or Staphylococcus saprophyticus.
Acute pyelonephritis (mild to moderate) caused by Escherichia coli (see 4 DOSAGE AND ADMINISTRATION and 14 CLINICAL TRIALS).
Chronic bacterial prostatitis due to Escherichia coli, Enterococcus faecalis, or Staphylococcus epidermidis.
In cases of uncomplicated acute bacterial cystitis, limit the use of PRO-LEVOFLOXACIN to circumstances where no other treatment options are available. A urine culture should be obtained prior to treatment to ensure levofloxacin susceptibility.
Appropriate culture and susceptibility tests should be performed before treatment in order to isolate and identify the organisms causing the infection, and to determine their susceptibility to levofloxacin. Therapy with levofloxacin may be initiated before the results of these tests are known; once results become available, appropriate therapy should be continued.
As with other drugs in this class, some strains of Pseudomonas aeruginosa may develop resistance fairly rapidly during treatment with levofloxacin. Culture and susceptibility testing performed periodically during therapy, will reveal not only the therapeutic effect of the antimicrobial agent, but also the possible emergence of bacterial resistance.
1.1 Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness in children under 18 years of age have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Drug absorption appears to be unaffected by age. Dose adjustment based on age alone is not necessary (see 7.1.4 Geriatrics and 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions).
2 CONTRAINDICATIONS
- PRO-LEVOFLOXACIN is contraindicated in persons with a history of hypersensitivity to levofloxacin, quinolone antimicrobial agents or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section.
- Levofloxacin is also contraindicated in persons with a history of tendinitis or tendon rupture associated with the use of any member of the quinolone group of antimicrobial agents.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The dosage of PRO-LEVOFLOXACIN tablets for patients with normal renal function (i.e., ClCr > 80 mL/min) is described in the following dosing chart. For patients with altered renal function (i.e., ClCr ≤ 80 mL/min), see 4.2 Recommended Dose and Dosage Adjustment, Patients with Impaired Renal Function subsection.
4.2 Recommended Dose and Dosage Adjustment
Patients with Normal Renal Function
| Infection* | Dose | Freq. | Duration |
|---|---|---|---|
| Acute Bacterial Exacerbation of Chronic Bronchitis | 500 mg 750 mg | q24h q24h | 7 days 5 days |
| Comm.-Acquired Pneumonia | 500 mg 750 mg** | q24h q24h | 7-14 days (10-14 days for severe infections) 5 days |
| Sinusitis | 500 mg 750 mg*** | q24h q24h | 10-14 days 5 days |
| Nosocomial Pneumonia | 750 mg | q24h | 7-14 days |
| Uncomplicated SSSI | 500 mg | q24h | 7-10 days |
| Complicated SSSI | 750 mg | q24h | 7-14 days |
| Chronic Bacterial Prostatitis | 500 mg | q24h | 28 days |
| Complicated UTI | 250 mg 750 mg‡ | q24h q24h | 10 days 5 days |
| Acute Pyelonephritis | 250 mg 750 mg | q24h q24h | 10 days 5 days |
| Uncomplicated UTI | 250 mg | q24h | 3 days |
* DUE TO THE DESIGNATED PATHOGENS (see 1 INDICATIONS).
** Efficacy of this alternative regimen has only been documented for infections caused by penicillin-susceptible Streptococcus pneumoniae, Haemophilus influenzae, Haemophilus parainfluenzae, Mycoplasma pneumoniae, Chlamydia pneumoniae, and Legionella pneumophila.
*** The efficacy of a regimen of 750 mg daily for 5 days has been demonstrated to be non-inferior to a regimen of 500 mg daily for 10 days. The 750 mg daily 5-day regimen has not been compared to a regimen of 500 mg daily for 11-14 days.
‡ The efficacy of this alternative regimen has been documented for infections caused by Escherichia coli, Klebsiella pneumoniae, and Proteus mirabilis. Efficacy against infections caused by Enterococcus faecalis, Enterobacter cloacae, or Pseudomonas aeruginosa has not been demonstrated with this regimen.
Patients with Impaired Renal Function
On the basis of the altered levofloxacin disposition pharmacokinetics in subjects with impaired renal function, dose adjustment is recommended for patients with impaired renal function as given below (see 7 WARNINGS AND PRECAUTIONS, Renal; 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).
Dosing recommendations for renally impaired patients are based on data collected from a clinical safety and pharmacokinetic study in renally impaired patients treated with a single 500 mg oral dose of levofloxacin. There is no clinical experience available in this patient population for the 250 mg dose or 750 mg dose. Pharmacokinetic modelling was used to determine a recommended dosing regimen which would provide equivalent drug exposures for which clinical efficacy has been demonstrated. The potential effects of levofloxacin associated with possible increased serum/tissue levels in renal impaired patients, such as effect on QTc interval, have not been studied.
| Renal Status | Initial Dose | Subsequent Dose |
|---|---|---|
| Acute Sinusitis/Acute Bacterial Exacerbation of Chronic Bronchitis/Community Acquired Pneumonia/Uncomplicated SSSI/Chronic Bacterial Prostatitis | ||
| ClCr from 50 to 80 mL/min | No dosage adjustment required | |
| ClCr from 20 to 49 mL/min | 500 mg | 250 mg q24h |
| ClCr from 10 to 19 mL/min | 500 mg | 250 mg q48h |
| Hemodialysis | 500 mg | 250 mg q48h |
| CAPD | 500 mg | 250 mg q48h |
| Complicated UTI/Acute Pyelonephritis | ||
| ClCr ≥20 mL/min | No dosage adjustment required | |
| ClCr from 10 to 19 mL/min | 250 mg | 250 mg q48h |
| Complicated SSSI/Nosocomial Pneumonia/Community Acquired Pneumonia/Acute Bacterial Exacerbation of Chronic Bronchitis/Acute Sinusitis/Complicated UTI/Acute Pyelonephritis | ||
| ClCr from 50 to 80 mL/min | No dosage adjustment required | |
| ClCr from 20 to 49 mL/min | 750 mg | 750 mg q48h |
| ClCr from 10 to 19 mL/min | 750 mg | 500 mg q48h |
| Hemodialysis | 750 mg | 500 mg q48h |
| CAPD | 750 mg | 500 mg q48h |
| Uncomplicated UTI | No dosage adjustment required | |
ClCr = creatinine clearances
CAPD = chronic ambulatory peritoneal dialysis
When only the serum creatinine is known, the following formula may be used to estimate creatinine clearance.
Men: Creatinine Clearance (mL/min)
= Weight (kg) x (140 - age) x 1.2
serum creatinine (mcmol/L)
Women: 0.85 x the value calculated for men.
The serum creatinine should represent a steady state of renal function.
4.4 Administration
PRO-LEVOFLOXACIN can be administered without regard to food. Doses should be administered at least 2 hours before or 2 hours after antacids containing calcium, magnesium, aluminum, sucralfate, metal cations such as iron, multi-vitamin preparations with zinc, or products containing any of these components.
4.5 Missed Dose
More than the prescribed dose of PRO-LEVOFLOXACIN should not be taken, even if a dose is missed.
5 OVERDOSAGE
In the event of an acute overdosage, activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are recommended. The patient should be observed, including ECG monitoring (see 10 CLINICAL PHARMACOLOGY, 10.2 Pharmacodynamics, Studies Measuring Effects on QT and Corrected QT (QTc) Intervals), and appropriate hydration maintained. Treatment should be supportive. Levofloxacin is not efficiently removed by hemodialysis or peritoneal dialysis.
Levofloxacin exhibits a low potential for acute toxicity. Mice, rats, dogs and monkeys exhibited the following clinical signs after receiving a single high dose of levofloxacin: ataxia, ptosis, decreased locomotor activity, dyspnea, prostration, tremors, and convulsions. Doses in excess of 1500 mg/kg orally produced significant mortality in rodents.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets 250 mg, 500 mg and 750 mg | Colloidal silicon dioxide, croscarmellose sodium, ferric oxide yellow (250 mg and 500 mg strengths only), ferric oxide red (250 mg and 500 mg strengths only), glycerol dibehenate, hypromellose, hydroxypropyl cellulose, lactose monohydrate, polyethylene glycol, povidone, sodium starch glycolate, talc, titanium dioxide. |
Levofloxacin 250 mg film-coated tablets, containing 250 mg of levofloxacin (as levofloxacin hemihydrate), are terra cotta pink, octagonal, biconvex tablets, with imprint “LVF 250” on one side. Available in bottles of 50 tablets.
Levofloxacin 500 mg film-coated tablets, containing 500 mg of levofloxacin (as levofloxacin hemihydrate), are peach, octagonal biconvex tablets, with imprint “LVF 500” on one side. Available in bottles of 100 tablets.
Levofloxacin 750 mg film-coated tablets, containing 750 mg of levofloxacin (as levofloxacin hemihydrate), are white, octagonal biconvex tablets, with imprint “LVF 750” on one side. Available in bottles of 50 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
The administration of levofloxacin increased the incidence and severity of osteochondrosis in immature rats and dogs. Other quinolones also produce similar erosions in the weight-bearing joints and other signs of arthropathy in immature animals of various species. Consequently, levofloxacin should not be used in pre-pubertal patients (see 16 NON-CLINICAL TOXICOLOGY).
Although levofloxacin is soluble, adequate hydration of patients receiving levofloxacin should be maintained to prevent the formation of a highly concentrated urine. Crystalluria has been observed rarely in patients receiving other quinolones, when associated with high doses and an alkaline urine. Although crystalluria was not observed in clinical trials with levofloxacin, patients are encouraged to remain adequately hydrated.
As with any antimicrobial drug, periodic assessment of organ system functions, including renal, hepatic, and hematopoietic, is advisable during prolonged therapy (see 8 ADVERSE REACTIONS).
Use of levofloxacin with other drugs may lead to drug-drug interactions (see 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions).
Sexually Transmitted Diseases
Levofloxacin is not indicated for the treatment of syphilis or gonorrhea. Levofloxacin is not effective in the treatment of syphilis. Antimicrobial agents used in high doses for short periods of time to treat gonorrhea may mask or delay the symptoms of incubating syphilis. All patients with gonorrhea should have a serologic test for syphilis at the time of diagnosis. Patients treated with antimicrobial agents with limited or no activity against Treponema pallidum should have a follow-up serologic test for syphilis after 3 months.
Cardiovascular
Aortic Aneurysm and Aortic Dissection
Epidemiologic studies report an increased risk of aortic aneurysm and dissection, particularly in elderly patients, and of aortic and mitral valve regurgitation after intake of fluoroquinolones. Cases of aortic aneurysm and dissection, sometimes complicated by rupture (including fatal ones), and of regurgitation/incompetence of any of the heart valves have been reported in patients receiving fluoroquinolones.
Therefore, fluoroquinolones should only be used after careful benefit-risk assessment and after consideration of other therapeutic options in patients with positive family history of aneurysm disease or congenital heart valve disease, or in patients diagnosed with pre-existing aortic aneurysm and/or dissection or heart valve disease, or in presence of other risk factors or conditions predisposing for:
- Both aortic aneurysm and dissection and heart valve regurgitation/incompetence (e.g., connective tissue disorders such as Marfan syndrome or Ehlers-Danlos syndrome, Turner syndrome, Behcet's disease, hypertension, rheumatoid arthritis) or additionally
- Aortic aneurysm and dissection (e.g., vascular disorders such as Takayasu arteritis or giant cell arteritis, or known atherosclerosis, or Sjögren’s syndrome) or additionally
- Heart valve regurgitation/incompetence (e.g., infective endocarditis).
The risk of aortic aneurysm and dissection, and their rupture may also be increased in patients treated concurrently with systemic corticosteroids.
In case of sudden severe abdominal, chest or back pain, acute dyspnea, new onset of heart palpitations, or development of oedema of the abdomen or lower extremities, patients should be advised to immediately consult a physician in an emergency department.
QT Prolongation
Some quinolones, including levofloxacin, have been associated with prolongation of the QT interval on the electrocardiogram and infrequent cases of arrhythmia. During post-marketing surveillance, very rare cases of torsades de pointes have been reported in patients taking levofloxacin. These reports generally involved patients with concurrent medical conditions or concomitant medications that may have been contributory. The risk of arrhythmias may be reduced by avoiding concurrent use with other drugs that prolong the QT interval including macrolide antibiotics, antipsychotics, tricyclic antidepressants, Class IA (e.g., quinidine, procainamide) or Class III (e.g., amiodarone, sotalol) antiarrhythmic agents, and cisapride. In addition, use of levofloxacin in the presence of risk factors for torsades de pointes such as hypokalemia, significant bradycardia, cardiomyopathy, patients with myocardial ischemia, and patients with congenital prolongation of the QT interval should be avoided (see
10 CLINICAL PHARMACOLOGY, 10.2 Pharmacodynamics, Studies Measuring Effects on QT and Corrected QT (QTc) Intervals).
Driving and Operating Machinery
Neurologic adverse effects such as dizziness and lightheadedness may occur. Therefore, patients should know how they react to levofloxacin before operating an automobile or machinery or engaging in other activities requiring mental alertness and coordination.
Endocrine and Metabolism
Fluoroquinolones, including levofloxacin, have been associated with disturbances of blood glucose, including symptomatic hyperglycemia and hypoglycemia, usually in diabetic patients receiving concomitant treatment with an oral hypoglycemic agent (e.g., glyburide) or with insulin. In these patients, careful monitoring of blood glucose is recommended. SEVERE CASES OF HYPOGLYCEMIA RESULTING IN COMA OR DEATH HAVE BEEN REPORTED. If a hypoglycemic reaction occurs, discontinue PRO-LEVOFLOXACIN immediately and initiate appropriate therapy.
Serious hypoglycemia and hyperglycemia have also occurred in patients without a history of diabetes (see 8 ADVERSE REACTIONS and 9.4 Drug-Drug Interactions, Antidiabetic Agents).
Hypoglycemic coma has been observed in diabetic patients with the use of levofloxacin. Fatal outcomes have been reported. All cases of hypoglycemic coma had multiple confounding factors; a temporal relationship with the use of levofloxacin was identified (onset of altered consciousness occurred within 3 days in most cases). Caution should be exercised when using levofloxacin in diabetic patients taking concomitant treatment with an oral hypoglycemic agent and/or insulin, especially those who are elderly or who have renal impairment (see 7 WARNINGS AND PRECAUTIONS, Renal and 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Antidiabetic Agents).
Gastrointestinal
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including levofloxacin. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases (see 8 ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic
Very rare post-marketing reports of severe hepatotoxicity (including acute hepatitis and fatal events) have been received for patients treated with levofloxacin. No evidence of serious drug-associated hepatotoxicity was detected in clinical trials of over 7,000 patients. Severe hepatotoxicity generally occurred within 14 days of initiation of therapy and most cases occurred within 6 days. Most cases of severe hepatotoxicity were not associated with hypersensitivity. The majority of fatal hepatotoxicity reports occurred in patients 65 years of age or older and most were not associated with hypersensitivity. Levofloxacin should be discontinued immediately if the patient develops signs and symptoms of hepatitis (see 8 ADVERSE REACTIONS, 8.5 Post-Market Adverse Reactions).
Immune
Hypersensitivity
Serious and occasionally fatal hypersensitivity and/or anaphylactic reactions have been reported in patients receiving therapy with quinolones, including levofloxacin. These reactions often occur following the first dose. Some reactions have been accompanied by cardiovascular collapse, hypotension/shock, seizure, loss of consciousness, tingling, angioedema (including tongue, laryngeal, throat or facial edema/swelling), airway obstruction (including bronchospasm, shortness of breath, and acute respiratory distress), dyspnea, urticaria, itching, and other serious skin reactions. Levofloxacin should be discontinued immediately at the first appearance of a skin rash or any other sign of hypersensitivity. Serious acute hypersensitivity reactions may require treatment with epinephrine and other resuscitative measures, including oxygen, intravenous fluids, antihistamines, corticosteroids, pressor, amines and airway management, as clinically indicated (see 8 ADVERSE REACTIONS).
Serious and sometimes fatal events, some due to hypersensitivity and some due to uncertain etiology, have rarely been reported in patients receiving therapy with quinolones, including levofloxacin. These events may be severe and generally occur following the administration of multiple doses. Clinical manifestations may include one or more of the following: fever; rash or severe dermatologic reactions (e.g., toxic epidermal necrolysis, Stevens-Johnson syndrome); vasculitis; arthralgia; myalgia; serum sickness; allergic pneumonitis; interstitial nephritis; acute renal insufficiency or failure; hepatitis, including acute hepatitis; jaundice; acute hepatic necrosis or failure; anemia, including hemolytic and aplastic; thrombocytopenia, including thrombotic thrombocytopenic purpura; leukopenia; agranulocytosis; pancytopenia; and/or other hematologic abnormalities. The administration of levofloxacin should be discontinued immediately, at the first appearance of a skin rash or any other sign of hypersensitivity, and supportive measures instituted (see
8 ADVERSE REACTIONS).
Musculoskeletal
Tendinitis
Rupture of the shoulder, hand and Achilles tendons that required surgical repair or resulted in prolonged disability have been reported in patients receiving quinolones, including levofloxacin. Levofloxacin should be discontinued if the patient experiences pain, inflammation or rupture of a tendon. Patients should rest and refrain from exercise until the diagnosis of tendinitis or tendon rupture has been confidently excluded. The risk of developing fluoroquinolone-associated tendinitis and tendon rupture is further increased in older patients usually over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart or lung transplants. Factors, in addition to age and corticosteroid use, that may independently increase the risk of tendon rupture include strenuous physical activity, renal failure, and previous tendon disorders such as rheumatoid arthritis. Tendinitis and tendon rupture have also occurred in patients taking fluoroquinolones who do not have the above risk factors. Tendon rupture can occur during or after completion of therapy; cases occurring up to several months after completion of therapy have been reported. Levofloxacin should be discontinued if the patient experiences pain, swelling, inflammation or rupture of a tendon. Patients should be advised to rest at the first sign of tendinitis or tendon rupture, and to contact their healthcare provider regarding changing to a non-quinolone antimicrobial drug (see 8 ADVERSE REACTIONS).
Levofloxacin should not be used in patients with a history of tendon disease/disorder related to previous quinolone treatment (see 2 CONTRAINDICATIONS).
Myasthenia Gravis
Fluoroquinolones have neuromuscular blocking activity and may exacerbate muscle weakness in persons with myasthenia gravis. Post-marketing serious adverse events, including deaths and requirement for ventilatory support, have been associated with fluoroquinolone use (including levofloxacin) in persons with myasthenia gravis. Avoid levofloxacin in patients with a known history of myasthenia gravis (see 8 ADVERSE REACTIONS, 8.5 Post-Market Adverse Reactions).
Neurologic
Central Nervous System Adverse Reactions
Fluoroquinolones, including levofloxacin, have been associated with an increased risk of seizures (convulsions), increased intracranial pressure (including pseudotumor cerebri), tremors, and light-headedness. As with other fluoroquinolones, PRO-LEVOFLOXACIN should be used with caution in patients with a known or suspected central nervous system (CNS) disorder that may predispose them to seizures or lower the seizure threshold (e.g., severe cerebral arteriosclerosis, epilepsy) or in the presence of other risk factors that may predispose them to seizures or lower the seizure threshold (e.g., certain drug therapy, renal dysfunction). If these reactions occur in patients receiving PRO-LEVOFLOXACIN, discontinue PRO-LEVOFLOXACIN immediately and institute appropriate measures.
Peripheral Neuropathy
Rare cases of sensory or sensorimotor axonal polyneuropathy affecting small and/or large axons resulting in paresthesias, hypoesthesias, dysesthesias and weakness have been reported in patients receiving quinolones, including levofloxacin. Symptoms may occur soon after initiation of treatment and may be irreversible. Levofloxacin should be discontinued immediately if the patient experiences symptoms of neuropathy including pain, burning, tingling, numbness, and/or weakness or other alterations of sensation including light touch, pain, temperature, position sense, and vibratory sensation in order to prevent the development of an irreversible condition.
Ophthalmologic
Vision Disorders
Consult an eye specialist if vision disorder occurs in association with the use of PRO-LEVOFLOXACIN.
Psychiatric
Fluoroquinolones, including levofloxacin, have been associated with an increased risk of psychiatric adverse reactions, including: toxic psychoses, hallucinations, or paranoia; depression, or suicidal thoughts; anxiety, agitation, restlessness, or nervousness; confusion, delirium, disorientation, or disturbances in attention; insomnia or nightmares; and memory impairment. Cases of attempted or completed suicide have been reported, especially in patients with a medical history of depression, or an underlying risk factor for depression. These reactions may occur following the first dose. If these reactions occur in patients receiving PRO-LEVOFLOXACIN, discontinue PRO-LEVOFLOXACIN and institute appropriate measures.
Renal
Safety and efficacy of levofloxacin in patients with impaired renal function (creatinine clearance ≤ 80 mL/min) have not been studied. Since levofloxacin is known to be substantially excreted by the kidney, the risk of toxic reactions to this drug may be greater in patients with impaired renal function. The potential effects of levofloxacin associated with possible increased serum/tissue levels in renal impaired patients, such as effect on QTc interval, have not been studied. Adjustment of the dosage regimen may be necessary to avoid the accumulation of levofloxacin due to decreased clearance. Careful clinical observation and appropriate laboratory studies should be performed prior to and during therapy, since elimination of levofloxacin may be reduced. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection and it may be useful to monitor renal function. Administer levofloxacin with caution in the presence of renal insufficiency (see 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Patients with Impaired Renal Function and 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).
Sensitivity/Resistance
Superinfection
The use of levofloxacin may result in overgrowth of non-susceptible organisms. If superinfection occurs during therapy, appropriate measures should be taken.
Development of Drug Resistant Bacteria
Prescribing PRO-LEVOFLOXACIN in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Methicillin-resistant Staphylococcus aureus (MRSA) is very likely to possess co-resistance to fluoroquinolones, including levofloxacin. Therefore, PRO-LEVOFLOXACIN is not recommended for the treatment of known or suspected MRSA infections unless laboratory results have confirmed susceptibility of the organism to levofloxacin. In this case PRO-LEVOFLOXACIN can be used when commonly recommended antibacterial agents for the treatment of MRSA-infections are considered inappropriate.
Resistance of Escherichia coli, the most common pathogen involved in urinary tract infections, to fluoroquinolones varies. Prescribers are advised to take into account the local prevalence of resistance in E. coli to fluoroquinolones.
Skin
Phototoxicity
Moderate to severe phototoxicity reactions have been observed in patients exposed to direct sunlight or ultraviolet (UV) light while receiving drugs in this class. Excessive exposure to sunlight or UV light should be avoided. However, in clinical trials with levofloxacin, phototoxicity has been observed in less than 0.1% of patients. Therapy should be discontinued if phototoxicity (e.g., skin eruption) occurs.
7.1 Special Populations
The safety and efficacy of levofloxacin tablets in children, adolescents (under the age of 18 years), pregnant women, and nursing mothers have not been established.
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Levofloxacin should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
Levofloxacin has not been measured in human milk. Based upon data from ofloxacin, it can be presumed that levofloxacin can be excreted in human milk. Because of the potential for serious adverse reactions from levofloxacin in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother (see
16 NON-CLINICAL TOXICOLOGY).
7.1.3 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of levofloxacin in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. Quinolones, including levofloxacin, cause arthropathy in juvenile animals of several species (see 16 NON-CLINICAL TOXICOLOGY). The incidence of protocol-defined musculoskeletal disorders in a prospective long-term surveillance study was higher in children treated for approximately 10 days with levofloxacin than in children treated with non-fluoroquinolone antibiotics for approximately 10 days (see 8 ADVERSE REACTIONS).
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): The pharmacokinetic properties of levofloxacin in younger adults and elderly adults do not differ significantly when creatinine clearance is taken into consideration. However, since the drug is known to be substantially excreted by the kidney, the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection. It may also be useful to monitor renal function.
Elderly patients may be more susceptible to drug-associated effects on the QT interval (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Geriatric patients are at increased risk for developing severe tendon disorders including tendon rupture when being treated with a fluoroquinolone such as levofloxacin. This risk is further increased in patients receiving concomitant corticosteroid therapy (see 7 WARNINGS AND PRECAUTIONS, Musculoskeletal).
Severe and sometimes fatal cases of hepatotoxicity have been reported post-marketing in association with levofloxacin. The majority of fatal hepatotoxicity reports occurred in patients 65 years of age or older and most were not associated with hypersensitivity (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In North American Phase III clinical trials involving 7537 subjects, the incidence of treatment-emergent adverse events in patients treated with levofloxacin tablets and injection was comparable to comparators. The majority of adverse events were considered to be mild to moderate, with 5.6% of patients considered to have severe adverse events. Among patients receiving multiple-dose therapy, 4.2% discontinued therapy with levofloxacin due to adverse experiences. The incidence of drug-related adverse reactions was 6.7%.
In clinical trials, the most frequently reported adverse drug reactions occurring in > 3% of the study population were nausea, headache, diarrhea, insomnia, dizziness and constipation.
Serious and otherwise important adverse drug reactions are discussed in greater detail in other sections (see 7 WARNINGS AND PRECAUTIONS).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The data described below reflect exposure to levofloxacin in 7537 patients in 29 pooled Phase III clinical trials. The population studied had a mean age of 49.6 years (74.2% of the population was < 65 years), 50.1% were male, 71% were Caucasian and 18.8% were Black. Patients were treated with levofloxacin for a wide variety of infectious diseases (See 1 INDICATIONS). Treatment duration was usually 3-14 days, the mean number of days on therapy was 9.6 days and the mean number of doses was 10.2. Patients received levofloxacin doses of 750 mg once daily, 250 mg once daily, or 500 mg once or twice daily. The overall incidence, type and distribution of adverse reactions were similar in patients receiving levofloxacin doses of 750 mg once daily, 250 mg once daily, and 500 mg once or twice daily.
Adverse reactions (characterized as likely related to drug-therapy) occurring in ≥1% of levofloxacin-treated patients are shown in Table 2 below.
Table 2 - Common (≥1%) Adverse Reactions Reported in Clinical Trials with Levofloxacin
| System/Organ Class | Adverse Reaction | % (N=7537) |
| Infections and Infestations | moniliasis | 1 |
| Psychiatric Disorders | insomnia | 4a |
| Nervous System Disorders | headache dizziness | 6 3 |
| Respiratory, Thoracic and Mediastinal Disorders | dyspnea | 1 |
| Gastrointestinal Disorders | nausea diarrhea constipation abdominal pain vomiting dyspepsia | 7 5 3 2 2 2 |
| Skin and Subcutaneous Tissue Disorders | rash pruritus | 2 1 |
| Reproductive System and Breast Disorders | vaginitis | 1b |
| System/Organ Class | Adverse Reaction | % (N=7537) |
| General Disorders and Administration Site Conditions | edema injection site reaction chest pain | 1 1 1 |
a N = 7274 b N = 3758 (women) | ||
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In a group of 1534 pediatric patients (6 months to 16 years of age) treated with levofloxacin for respiratory infections, children 6 months to 5 years of age received 10 mg/kg of levofloxacin twice a day for approximately 10 days and children greater than 5 years of age received 10 mg/kg to a maximum of 500 mg of levofloxacin once a day for approximately 10 days. The adverse reaction profile was similar to that reported in adult patients. Vomiting and diarrhea were reported more frequently in children than reported in adults. However, the frequency of vomiting and diarrhea was similar in levofloxacin-treated and non-fluoroquinolone antibiotic comparator-treated children.
A subset of 1340 of these children treated with levofloxacin for approximately 10 days was enrolled in a prospective, long-term, surveillance study to assess the incidence of protocol-defined musculoskeletal disorders (arthralgia, arthritis, tendinopathy, gait abnormality) during 60 days and 1 year following the first dose of levofloxacin.
During the 60-day period following the first dose, the incidence of protocol-defined musculoskeletal disorders was greater in levofloxacin-treated children than in non-fluoroquinolone antibiotic comparator-treated children (2.1% vs. 0.9%, respectively [p=0.038]). In 22/28 (78%) of these children, reported disorders were characterized as arthralgia. A similar observation was made during the one-year period, with a greater incidence of protocol-defined musculoskeletal disorders in levofloxacin-treated children than in non-fluoroquinolone antibiotic comparator-treated children (3.4% vs. 1.8%, respectively [p=0.025]). The majority of these disorders occurring in children treated with levofloxacin were mild and resolved within 7 days. Disorders were moderate in 8 children and mild in 35 (76%) children.
8.3 Less Common Clinical Trial Adverse Reactions
Less common adverse reactions occurring in 0.1 to <1% of levofloxacin-treated patients are shown in Table 3 below.
Table 3 - Less Common (0.1 to <1%) Adverse Reactions Reported in Clinical Trials with Levofloxacin
| System/Organ Class | Adverse Reaction |
| Blood and Lymphatic System Disorders | anemia, thrombocytopenia, granulocytopenia |
| Cardiac Disorders | cardiac arrest, palpitation, ventricular tachycardia, ventricular arrhythmia |
| System/Organ Class | Adverse Reaction |
| Gastrointestinal Disorders | gastritis, stomatitis, pancreatitis, oesophagitis, gastroenteritis, glossitis, pseudomembranous/ C.difficile colitis |
| Hepatobiliary Disorders | abnormal hepatic function, increased hepatic enzymes, increased alkaline phosphatase |
| Immune System Disorders | allergic reaction |
| Infections and Infestations | genital moniliasis |
| Metabolism and Nutrition Disorders | hyperglycemia, hypoglycemia, hyperkalemia |
| Musculoskeletal and Connective Tissue Disorders | tendinitis, arthralgia, myalgia, skeletal pain |
| Nervous System Disorders | tremor, convulsions, paresthesia, vertigo, hypertonia, hyperkinesias, abnormal gait, somnolencea, syncope |
| Psychiatric Disorders | anxiety, agitation, confusion, depression, hallucination, nightmarea, sleep disordera, anorexia, abnormal dreaminga |
| Renal and Urinary Disorders | abnormal renal function, acute renal failure |
| Respiratory, Thoracic and Mediastinal Disorders | epistaxis |
| Skin and Subcutaneous Tissue Disorders | urticaria |
| Vascular Disorders | phlebitis |
a N = 7274
Rare (<0.1%) adverse reactions from Phase III studies include dyspnea and rash maculo-papular.
In clinical trials using multiple-dose therapy, ophthalmologic abnormalities, including cataracts and multiple punctate lenticular opacities, have been noted in patients undergoing treatment with other quinolones. The relationship of the drugs to these events is not presently established.
Crystalluria and cylindruria have been reported with other quinolones.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Laboratory abnormalities seen in > 2% of patients receiving multiple doses of levofloxacin: decreased glucose 2.1%.
It is not known whether this abnormality was caused by the drug or the underlying condition being treated.
8.5 Post-Market Adverse Reactions
Table 4 lists adverse reactions that have been identified during post-approval use of levofloxacin. Because these reactions are reported voluntarily from a population of uncertain size, reliably estimating their frequency or establishing a causal relationship to drug exposure is not always possible.
Table 4 - Post-Marketing Reports of Adverse Drug Reactions
| System Organ Class | Adverse Reaction |
| Blood and Lymphatic System Disorders | pancytopenia, aplastic anemia, leucopenia, hemolytic anemia, eosinophilia, thrombocytopenia including thrombotic thrombocytopenic purpura, agranulocytosis |
| Cardiac Disorders | isolated reports of torsades de pointes, electrocardiogram QT prolonged, tachycardia |
| Eye Disorders | uveitis, vision disturbance (including diplopia), visual acuity reduced, vision blurred, scotoma |
| Ear and Labyrinth Disorders | hypoacusis, tinnitus |
| General Disorders and Administration Site Conditions | multi-organ failure, pyrexia, rash |
| Hepatobiliary Disorders | hepatic failure (including fatal cases), hepatitis, jaundice, hepatic necrosis |
| Immune System Disorders | hypersensitivity reactions, sometimes fatal including: anaphylactic/anaphylactoid reactions, anaphylactic shock, angioneurotic edema, serum sickness, Kounis syndrome (acute coronary syndrome associated with an allergic reaction) |
| Investigations | prothrombin time prolonged, international normalized ratio (INR) prolonged, muscle enzymes increased (CPK) |
| Musculoskeletal and Connective Tissue Disorders | tendon rupture, muscle injury (including rupture), rhabdomyolysis, myositis, myalgia |
| Nervous System Disorders | anosmia, ageusia, parosmia, dysgeusia, peripheral neuropathy (may be irreversible), isolated reports of encephalopathy, abnormal EEG, dysphonia, exacerbation of myasthenia gravis, amnesia, pseudotumor cerebri |
| Psychiatric Disorders | psychosis, paranoia, isolated reports of suicide attempt and suicidal ideation |
| Renal and Urinary Disorders | interstitial nephritis, nephrosis, glomerulonephritis |
| Respiratory, Thoracic and Mediastinal Disorders | isolated reports of allergic pneumonitis, interstitial pneumonia, laryngeal edema, apnea |
| Skin and Subcutaneous Tissue Disorders | bullous eruptions to include: Stevens-Johnson Syndrome, toxic epidermal necrolysis, erythema multiforme, photosensitivity/phototoxicity reaction, leukocytoclastic vasculitis |
| Vascular Disorders | vasodilation, vasculitis, DIC, aortic aneurysm, dissection, heart valves regurgitation |
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Levofloxacin undergoes limited metabolism in humans and is primarily excreted as unchanged drug in the urine. The P450 system is not involved in the levofloxacin metabolism, and is not affected by levofloxacin. Levofloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these enzymes. Disturbances of blood glucose have been reported in patients treated concomitantly with levofloxacin and an antidiabetic agent. Therefore, careful monitoring of blood glucose is recommended when these agents, including levofloxacin, are co-administered.
As with all other quinolones, iron and antacids significantly reduced bioavailability of levofloxacin.
The risk of aortic aneurysm and dissection, and their rupture may also be increased in patients treated concurrently with systemic corticosteroids.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5 - Established or Potential Drug-Drug Interactions
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| Antacids, Sucralfate, Metal Cations, Multi-Vitamins | T | Tablets: Due to the chelation of levofloxacin by multivalent cations, concurrent administration of levofloxacin tablets with antacids containing calcium, magnesium, or aluminum, as well as sucralfate, metal cations such as iron, multi-vitamin preparations with zinc, or any products containing any of these components may interfere with the gastrointestinal absorption of levofloxacin, resulting in systemic levels considerably lower than desired. | These agents should be taken at least 2 hours before or 2 hours after levofloxacin tablet administration. |
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| Antidiabetic Agents | C | Disturbances of blood glucose, including hyperglycemia and hypoglycemia, have been reported in patients treated concomitantly with levofloxacin and an antidiabetic agent. Some of these cases were serious including hypoglycemic coma. | Careful monitoring of blood glucose is recommended when these agents, including levofloxacin, are co-administered. |
| Cyclosporine | CT | No significant effect of levofloxacin on the peak plasma concentrations, AUC, and other disposition parameters for cyclosporine was detected in a clinical study involving healthy volunteers. However, elevated serum levels of cyclosporine have been reported in the patient population when co-administered with some other quinolones. Levofloxacin Cmax and ke were slightly lower, while Tmax and t½ were slightly longer in the presence of cyclosporine, than those observed in other studies without concomitant medication. The differences, however, are not considered to be clinically significant. | No dosage adjustment is required for levofloxacin or cyclosporine when administered concomitantly. |
| Digoxin | CT | No significant effect of levofloxacin on the peak plasma concentrations, AUC, and, other disposition parameters for digoxin was detected in a clinical study involving healthy volunteers. Levofloxacin absorption and disposition kinetics were similar in the presence or absence of digoxin. | No dosage adjustment for levofloxacin or digoxin is required when administered concomitantly. Digoxin levels should be closely monitored in patients receiving concomitant therapy with digoxin. |
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) | T | Although not observed with levofloxacin in clinical trials, some quinolones have been reported to have proconvulsant activity that is exacerbated with concomitant use of NSAIDs. | The concomitant administration of a non-steroidal anti-inflammatory drug with a quinolone, including levofloxacin, may increase the risk of CNS stimulation and convulsive seizures (see 7 WARNINGS AND PRECAUTIONS, Neurologic). |
| Probenecid and Cimetidine | CT | No significant effect of probenecid or cimetidine on the rate and extent of levofloxacin absorption was observed in a clinical study involving healthy volunteers. The AUC and t½ of levofloxacin were 27-38% and 30% higher, respectively, while CL/F and Clr were 21-35% lower during concomitant treatment with probenecid or cimetidine compared to levofloxacin alone. | No dosage adjustment for levofloxacin is required when administered concomitantly with probenecid or cimetidine except dosage adjustment for levofloxacin may be required based on the renal function of the patient. |
| Theophylline | CT/T | No significant effect of levofloxacin on the plasma concentrations, AUC, and other disposition parameters for theophylline was detected in a clinical study involving 14 healthy volunteers. Similarly, no apparent effect of theophylline on levofloxacin absorption and disposition was observed. However, concomitant administration of other quinolones with theophylline has resulted in prolonged elimination, elevated serum theophylline levels, and a subsequent increase in the risk of theophylline-related adverse reactions in the patient population. | Theophylline levels should be closely monitored, and theophylline dosage adjustments made if appropriate, when levofloxacin is co-administered. Adverse reactions, including seizures, may occur with or without an elevation in serum theophylline level (see 7 WARNINGS AND PRECAUTIONS, Neurologic). |
| Proper / Common name | Source of Evidence | Effect | Clinical comment |
| Warfarin | T | Certain quinolones, including levofloxacin, may enhance the effects of oral anticoagulant warfarin or its derivatives. | When these products are administered concomitantly, prothrombin time, International Normalized Ratio (INR), or other suitable coagulation tests should be monitored closely, especially in the elderly patients. |
| Zidovudine | CT | Levofloxacin absorption and disposition in HIV-infected subjects, with or without concomitant zidovudine treatment, were similar. The effect of levofloxacin on zidovudine pharmacokinetics has not been studied. | No dosage adjustment for levofloxacin appears to be required when co-administered with zidovudine. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Levofloxacin may be taken with or without food.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Some quinolones, including levofloxacin, may produce false-positive urine screening results for opiates using commercially available immunoassay kits. Confirmation of positive opiate screens by more specific methods may be necessary.
Levofloxacin may interfere in the bacteriological diagnosis of tuberculosis and thus give false-negative results; therefore, tuberculosis diagnostic tests should be repeated on the patient after termination of PRO-LEVOFLOXACIN treatment.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Levofloxacin is a synthetic broad-spectrum antibacterial agent for oral administration and intravenous administration.
Levofloxacin is the L-isomer of the racemate, ofloxacin, a quinolone antibacterial agent. The antibacterial activity of ofloxacin resides primarily in the L-isomer. The mechanism of action of levofloxacin and other quinolone antibacterials involves inhibition of bacterial topoisomerase II (DNA gyrase) and topoisomerase IV. Topoisomerases are essential in controlling the topological state of DNA, and are vital for DNA replication, transcription, repair and recombination.
Fluoroquinolones, including levofloxacin, differ in chemical structure and mode of action from other classes of antimicrobial agents, such as β-lactam antibiotics, aminoglycosides, and macrolides. Therefore, microorganisms resistant to these latter classes of antimicrobial agents may be susceptible to fluoroquinolones. For example, β-lactamase production and alterations in penicillin-binding proteins have no effect on levofloxacin activity. Conversely, microorganisms resistant to fluoroquinolones may be susceptible to other classes of antimicrobial agents.
10.2 Pharmacodynamics
Studies Measuring Effects on QT and Corrected QT (QTc) Intervals
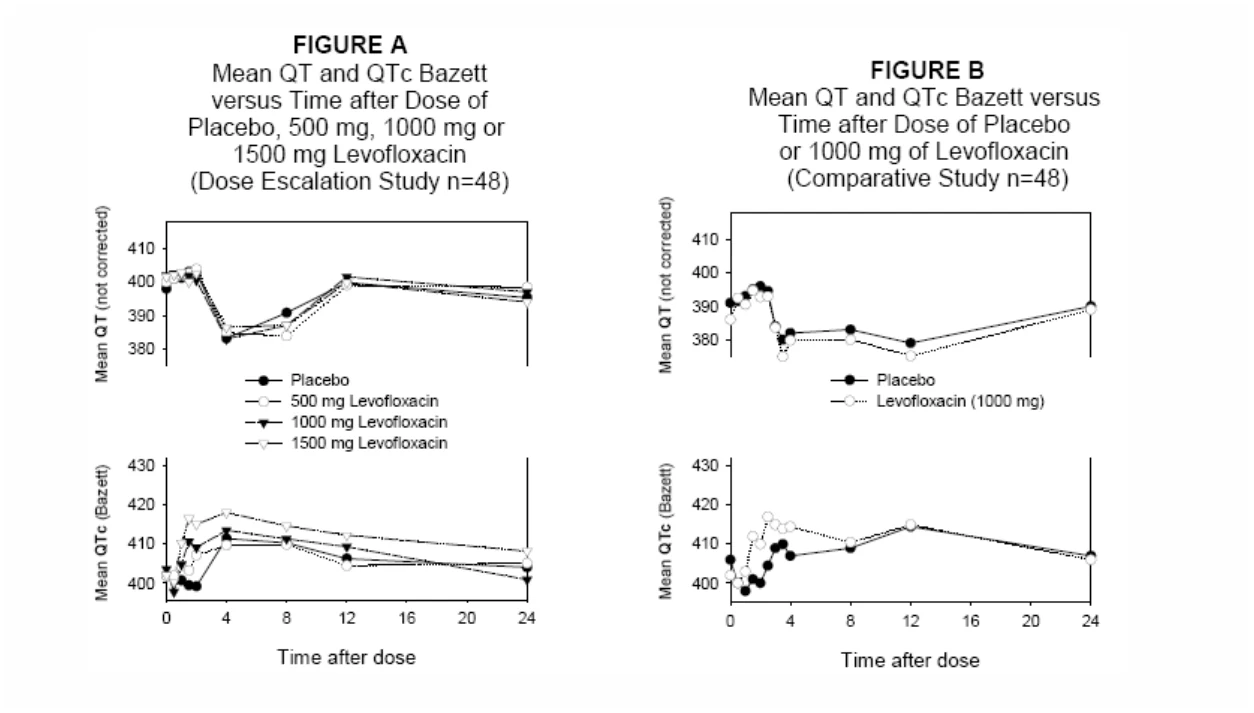
Two double-blind, placebo-controlled studies have been conducted to assess specifically the effect of levofloxacin on QT and corrected QT (QTc) intervals in healthy male and female volunteers 18-84 years of age. Each had a four-treatment crossover, single-dose study design. One study evaluated dose-response. The other was a comparative study that involved measuring the effects of doses of levofloxacin and two other fluoroquinolones. In this comparative study, subjects were given twice the doses of these antibiotics that are recommended for the treatment of otherwise healthy subjects with community-acquired pneumonia. In these trials, no effect on QT intervals compared to placebo was evident at any of the doses studied. The clinical relevance of the results of these studies is not known (top panels of figure A and figure B).
Dose escalation study (Figure A): In a dose escalation study (n=48) where the effect on average QTc, after single doses of 500, 1000, and 1500 mg of levofloxacin, was measured between the baseline QTc (calculated as the average QTc measured 24, 20, 16 hours and immediately before treatment) and the average post-dose QTc interval (calculated from measurements taken every half hour for two hours and at 4, 8, 12 and 24 hours after treatment), an effect on the average QTc (Bazett) was -1.84, 1.55 and 6.40 msec, respectively. The change in QTc interval at Cmax (calculated using the Bazett formula) after treatment with 500 mg of levofloxacin was not significantly different from that measured after treatment with placebo. In this trial, the mean change in the QTc (Bazett) at Cmax from baseline QTc (calculated as the average QTc measured 24, 20, 16 hours and immediately before treatment) was -3.20 msec after treatment with 500 mg of levofloxacin, 7.82 msec after treatment with 1000 mg of levofloxacin and 10.58 msec after treatment with 1500 mg of levofloxacin.
Comparative, placebo-controlled study (Figure B; only levofloxacin and placebo data shown): In a study which compared the effect of 3 antimicrobials (n=48) where the difference was measured between the baseline QTc (calculated as the average QTc measured 24, 20, 16 hours and immediately before treatment) and the average post-dose QTc interval (calculated from measurements taken every half hour for four hours and at 8, 12 and 24 hours after treatment), an effect on the average QTc was an increase of 3.58 msec after the 1000 mg dose of levofloxacin. In this study, the change in the QTc (Bazett) at Cmax from a baseline QTc (calculated as the average QTc measured 24, 20, 16 hours and immediately before treatment) was 5.32 msec after treatment with 1000 mg of levofloxacin.
10.3 Pharmacokinetics
The mean (± SD) pharmacokinetic parameters of levofloxacin determined under single and steady-state conditions following oral (PO) or intravenous (IV) doses of levofloxacin are summarized in Table 6.
| Table 6 - Summary of Pharmacokinetic Parameters (mean ± SD) | |||||||||||
| Regimen | N | Cmax (mcg/mL) | Tmax (h) | AUCj (mcg•h/mL) | CL/F (mL/min) | Vd/F (L) | t ½ (h) | Clr (mL/min) | |||
| Single dose | |||||||||||
| 250 mg POa | 15 | 2.8 ± 0.4 | 1.6 ± 1 | 27.2 ± 3.9 | 156 ± 20 | ND | 7.3 ± 0.9 | 142 ± 21 | |||
| 500 mg POa* | 23 | 5.1 ± 0.8 | 1.3 ± 0.6 | 47.9 ± 6.8 | 178 ± 28 | ND | 6.3 ± 0.6 | 103 ± 30 | |||
| 500 mg IVa | 23 | 6.2 ± 1 | 1 ± 0.1 | 48.3 ± 5.4 | 175 ± 20 | 90 ± 11 | 6.4 ± 0.7 | 112 ± 25 | |||
| 750 mg POcc | 10 | 7.1 ± 1.4 | 1.9 ± 0.7 | 82.2 ± 14.3 | 157 ± 28 | 90 ± 14 | 7.7 ± 1.3 | 118 ± 28 | |||
| 750 mg IVc | 4 | 7.99 ± 1.2b | ND | 74.4 ± 8 | 170 ± 19 | 97 ± 14.8 | 7.5 ± 1.9 | ND | |||
| Multiple dose | |||||||||||
| 500 mg q24h POa | 10 | 5.7 ± 1.4 | 1.1 ± 0.4 | 47.5 ± 6.7x | 175 ± 25 | 102 ± 22 | 7.6 ± 1.6 | 116 ± 31 | |||
| 500 mg q24h IVa | 10 | 6.4 ± 0.8 | ND | 54.6 ± 11.1x | 158 ± 29 | 91 ± 12 | 7 ± 0.8 | 99 ± 28 | |||
| 500 mg or 250 mg q24h IV patients with bacterial infectionsd | 272 | 8.7 ± 4i | ND | 72.5 ±51.2i,x | 154 ± 72 | 111 ± 58 | ND | ND | |||
| 750 mg q24h POcc | 10 | 8.6 ± 1.9 | 1.4 ± 0.5 | 90.7 ± 17.6 | 143 ± 29 | 100 ± 16 | 8.8 ± 1.5 | 116 ± 28 | |||
| 750 mg q24h IVc | 4 | 7.92 ± 0.91b | ND | 72.5 ± 0.8x | 172 ± 2 | 111 ± 12 | 8.1 ± 2.1 | ND | |||
| 500 mg PO single dose, effects of gender and age: | |||||||||||
| malee | 12 | 5.5 ± 1.1 | 1.2 ± 0.4 | 54.4 ± 18.9 | 166 ± 44 | 89 ± 13 | 7.5 ± 2.1 | 126 ± 38 | |||
| femalef | 12 | 7 ± 1.6 | 1.7 ± 0.5 | 67.7 ± 24.2 | 136 ± 44 | 62 ± 16 | 6.1 ± 0.8 | 106 ± 40 | |||
| youngg | 12 | 5.5 ± 1 | 1.5 ± 0.6 | 47.5 ± 9.8 | 182 ± 35 | 83 ± 18 | 6 ± 0.9 | 140 ± 33 | |||
| elderlyh | 12 | 7 ± 1.6 | 1.4 ± 0.5 | 74.7 ± 23.3 | 121 ± 33 | 67 ± 19 | 7.6 ± 2 | 91 ± 29 | |||
| 500 mg PO single dose, patients with renal insufficiency: | |||||||||||
| ClCr 50-80 mL/min | 3 | 7.5 ± 1.8 | 1.5 ± 0.5 | 95.6 ± 11.8 | 88 ± 10 | ND | 9.1 ± 0.9 | 57 ± 8 | |||
| ClCr 20-49 mL/min | 8 | 7.1 ± 3.1 | 2.1 ± 1.3 | 182.1 ± 62.6 | 51 ± 19 | ND | 27 ± 10 | 26 ± 13 | |||
| ClCr < 20 mL/min | 6 | 8.2 ± 2.6 | 1.1 ± 1 | 263.5 ± 72.5 | 33 ± 8 | ND | 35 ± 5 | 13 ± 3 | |||
| Hemodialysis | 4 | 5.7 ± 1 | 2.8 ± 2.2 | ND | ND | ND | 76 ± 42 | ND | |||
| CAPD | 4 | 6.9 ± 2.3 | 1.4 ± 1.1 | ND | ND | ND | 51 ± 24 | ND | |||
| 750 mg IV single dose and multiple dose, patients with renal insufficiency: | |||||||||||
| Single dose - ClCr 50-80 mL/mink | 8 | 13.3 ± 3.6 | ND | 128 ± 37 | 104 ± 25 | 62.7 ± 15.1 | 7.5 ± 1.5 | ND | |||
| Multiple q24h dose - ClCr 50-80 mL/mink | 8 | 14.3 ± 3.2 | ND | 145 ± 36 | 103 ± 20 | 64.2 ± 16.9 | 7.8 ± 2 | ND | |||
a healthy males 18-53 years of age; b 60 min infusion for 250 mg and 500 mg doses, 90 min infusion for 750 mg dose; c healthy male subjects 32-46 years of age; cc healthy male subjects 19-51 years of age; d including 500 mg q48h for 8 patients with moderate renal impairment (ClCr20-50 mL/min) and infections of the respiratory tract or skin; e healthy males 22-75 years of age; f healthy females 18-80 years of age; g young healthy male and female subjects 18-36 years of age; h healthy elderly male and female subjects 66-80 years of age; i dose-normalized values (to 500 mg dose), estimated by population pharmacokinetic modelling; j AUC for 0-∞ reported, unless otherwise specified; k male and female subjects 34-54 years of age; x AUC 0-24 h; * Absolute bioavailability; F = 0.99 ± 0.08 from a 500 mg tablet and F = 0.99 ± 0.06 from a 750 mg tablet. ND = Not Determined | |||||||||||
Absorption
Oral
Levofloxacin is rapidly and essentially completely absorbed after oral administration. Peak plasma concentrations are usually attained 1 to 2 hours after oral dosing. The absolute bioavailability of a 500 mg tablet and a 750 mg tablet of levofloxacin is approximately 99% in both cases, demonstrating complete oral absorption of levofloxacin. Levofloxacin pharmacokinetics are linear and predictable after single and multiple oral dosing regimens. After single oral doses of 250 to 1000 mg of levofloxacin to healthy subjects, plasma concentrations increase proportionally with the dose as shown (mean ± SD):
Oral Dose (mg) | n | Peak Plasma Concentration (mcg/mL) | Area Under the Curve (AUC0-∞, mcg·h/mL) |
|---|---|---|---|
| 250 | 15 | 2.8 ± 0.4 | 27.2 ± 3.9 |
| 500 | 23 | 5.1 ± 0.8 | 47.9 ± 6.8 |
| 750 | 10 | 7.1 ± 1.4 | 82.2 ± 14.3 |
| 1000 | 10 | 8.9 ± 1.9 | 111 ± 20.8 |
Steady-state conditions are reached within 48 hours following a 500 mg or 750 mg once-daily dosage regimen. The peak and trough plasma concentrations attained following multiple once-daily oral dosage regimens were approximately 5.7 mcg/mL and 0.5 mcg/mL after the 500 mg doses, and 8.6 mcg/mL and 1.1 mcg/mL after the 750 mg doses, respectively.
There was no clinically significant effect of food on the extent of absorption of levofloxacin. Oral administration with food slightly prolongs the time to peak concentration by approximately 1 hour, and slightly decreases the peak concentration by approximately 14%. Therefore, levofloxacin can be administered without regard to food.
Distribution
The mean volume of distribution of levofloxacin generally ranges from 74 to 112 L after single and multiple 500 mg or 750 mg doses, indicating widespread distribution into body tissues. Levofloxacin reaches its peak levels in skin tissues (11.7 mcg/g for a 750 mg dose) and in blister fluid (4.33 mcg/g for a 500 mg dose) at approximately 3-4 hours after dosing. The skin tissue biopsy to plasma AUC ratio is approximately 2. The blister fluid to plasma AUC ratio is approximately 1, following multiple once-daily oral administration of 750 mg and 500 mg levofloxacin to healthy subjects, respectively. Levofloxacin also penetrates into lung tissues. Lung tissue concentrations were generally 2- to 5-fold higher than plasma concentrations, and ranged from approximately 2.4 to 11.3 mcg/g over a 24-hour period after a single 500 mg oral dose.
Levofloxacin also penetrates into cortical and spongiosa bone tissues in both the femoral head and distal femur. Peak levofloxacin concentrations in these tissues ranging from 2.4 to 15 mcg/g were generally attained by 2 to 3 hours after a single 500 mg oral dose.
In vitro, over a clinically relevant range (1 to 10 mcg/mL) of serum/plasma levofloxacin concentrations, levofloxacin is 24 to 38% bound to serum proteins across all species studied, as determined by the equilibrium dialysis method. Levofloxacin is mainly bound (approximately 21 to 30%) to serum albumin in humans. Levofloxacin binding to serum proteins is independent of the drug concentration.
Metabolism
Levofloxacin is stereochemically stable in plasma and urine, and does not invert metabolically to its enantiomer, D-ofloxacin. Levofloxacin undergoes limited metabolism in humans and is primarily excreted as unchanged drug in the urine. Following oral administration, approximately 87% of an administered dose was recovered as unchanged drug in urine within 48 hours, whereas less than 4% of the dose was recovered in feces in 72 hours. Less than 5% of an administered dose was recovered in the urine as the desmethyl and N-oxide metabolites, the only metabolites identified in humans. These metabolites have little relevant pharmacological activity.
Elimination
The major route of elimination of levofloxacin in humans is as unchanged drug in the urine. The mean terminal plasma elimination half-life of levofloxacin ranges from approximately 6 to 8 hours following single or multiple doses of levofloxacin given orally or intravenously. The mean apparent total body clearance and renal clearance range from approximately 144 to 226 mL/min and 96 to 142 mL/min, respectively. Renal clearance in excess of the glomerular filtration rate suggests that tubular secretion of levofloxacin occurs in addition to its glomerular filtration. Concomitant administration of either cimetidine or probenecid results in approximately 24% and 35% reduction in the levofloxacin renal clearance, indicating that secretion of levofloxacin occurs in the renal proximal tubule. No levofloxacin crystals were found in any of the urine samples freshly collected from subjects receiving levofloxacin.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of levofloxacin in pediatric patients have not been studied; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics: There are no significant differences in levofloxacin pharmacokinetics between young and elderly subjects when the subjects’ differences in creatinine clearance are taken into consideration. Following a 500 mg oral dose of levofloxacin to healthy elderly subjects (66-80 years of age), the mean terminal plasma elimination half-life of levofloxacin was about 7.6 hours, as compared to approximately 6 hours in younger adults. The difference was attributable to the variation in renal function status of the subjects and was not believed to be clinically significant. Drug absorption appears to be unaffected by age. Levofloxacin dose adjustment based on age alone is not necessary.
- Sex: There are no significant differences in levofloxacin pharmacokinetics between male and female subjects when the differences in creatinine clearance are taken into consideration. Following a 500 mg oral dose of levofloxacin to healthy male subjects, the mean terminal plasma elimination half-life of levofloxacin was about 7.5 hours, as compared to approximately 6.1 hours in female subjects. This difference was attributable to the variation in renal function status of the male and female subjects, and was not believed to be clinically significant. Drug absorption appears to be unaffected by the gender of the subjects. Dose adjustment based on gender alone is not necessary.
- Ethnic Origin: The apparent total body clearance and apparent volume of distribution were not affected by race in a covariate analysis performed on data from 72 subjects.
- Hepatic Insufficiency: Pharmacokinetic studies in hepatically impaired patients have not been conducted. Due to the limited extent of levofloxacin metabolism, the pharmacokinetics of levofloxacin are not expected to be affected by hepatic impairment.
Renal Insufficiency: Pharmacokinetic parameters of levofloxacin following oral or intravenous doses of levofloxacin in patients with impaired renal function (creatinine clearance ≤ 80 mL/min) are presented in Table 6. Clearance of levofloxacin is reduced and plasma elimination half-life is prolonged in this patient population. Dosage adjustment may be required in such patients to avoid accumulation.
A dosage reduction is being recommended depending on the levels of renal insufficiency. Dosing recommendations are based on pharmacokinetic modelling of data collected from a clinical safety and pharmacokinetic study in renally impaired patients treated with a single 500 mg oral dose of levofloxacin (see 7 WARNINGS AND PRECAUTIONS, Renal, and 4 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment, Patients with Impaired Renal Function).
Neither hemodialysis nor continuous ambulatory peritoneal dialysis (CAPD) is effective in removal of levofloxacin from the body, indicating supplemental doses of levofloxacin are not required following hemodialysis or CAPD.
Plasma Ratio
Comparison of the expected steady-state AUC valuesa in renally impaired patients relative to those in patients with normal renal function:
| Creatinine Clearance 50-80 mL/min receiving 500 mg q24h | Creatinine Clearance 20-49 mL/min receiving 250 mg q24h | Creatinine Clearance <20 mL/min receiving 250 mg q48h | |
|---|---|---|---|
| AUC value relative to patients with normal renal function receiving 500 mg q24h | 172% | 183% | 139% |
| AUC value relative to patients with normal renal function receiving 500 mg q12h | 89% | 94% | 71% |
a Values were extrapolated from the mean levofloxacin plasma concentration-time data in subjects with normal renal function (n=23) and subjects with impaired renal function (n=3 for ClCr 50-80 mL/min, n=8 for ClCr 20-49 mL/min, and n=6 for ClCr <20 mL/min).
Urine Concentrations
The mean ± SD concentrations (mcg/mL) of levofloxacin in the urine following a 500 mg PO dose of levofloxacin in subjects with impaired renal function are summarized as followsa:
| Collection Interval | ClCr 50-80 mL/min Nb=3 | ClCr 20-49 mL/min N=8 | ClCr <20 mL/min N=6 |
|---|---|---|---|
| 0-6 h | 185 ± 61.7 | 98.1 ± 48.1 | 66.5 ± 27.3 |
| 6-12 h | 91.6 ± 24.4 | 75.2 ± 22.1 | 39 ± 23.1 |
| 12-24 h | 156 ± 183 | 58.6 ± 31.1 | 29.5 ± 20.7 |
| 24-36 h | 49.7 ± 16.2 | 44.1 ± 10.6 | <25 |
| 36-48 h | <25 | <25 | <25 |
a limit of quantitation = 25 mcg/mL
b N= number of subjects
Expected steady-state urinary concentrations (mcg/mL) of levofloxacin in renally impaired patients with the recommended adjusted dose regimen in the treatment of complicated UTI and acute pyelonephritisa:
| Collection Interval | ClCr 50-80 mL/min receiving 250 mg q24h | ClCr 20-49 mL/min receiving 250 mg q24h | ClCr <20 mL/min receiving 250 mg q48h |
|---|---|---|---|
| 0-6 h | 161 | 103 | 54 |
| 6-12 h | 61 | 76 | 29 |
| 12-24 h | 40 | 58 | 24 |
| 24-36 h | - | - | 23 |
| 36-48 h | - | - | 16 |
a Values were extrapolated from the mean pharmacokinetic profiles in subjects with impaired renal function (n=12 for ClCr 50-80 mL/min, n=8 for ClCr 20-49 mL/min, and n=6 for ClCr <20 mL/min).
- Bacterial Infection: The pharmacokinetics of levofloxacin in patients with community-acquired bacterial infections are comparable to those observed in healthy subjects.
- HIV Infection: The pharmacokinetics of levofloxacin in HIV seropositive subjects (with CD4 cell counts ranging from 17 to 772) are comparable to those observed in healthy subjects.
11 STORAGE, STABILITY AND DISPOSAL
PRO-LEVOFLOXACIN tablets should be stored at controlled room temperature between 15°C and 30°C in well closed containers. Protect from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
None.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Levofloxacin hemihydrate
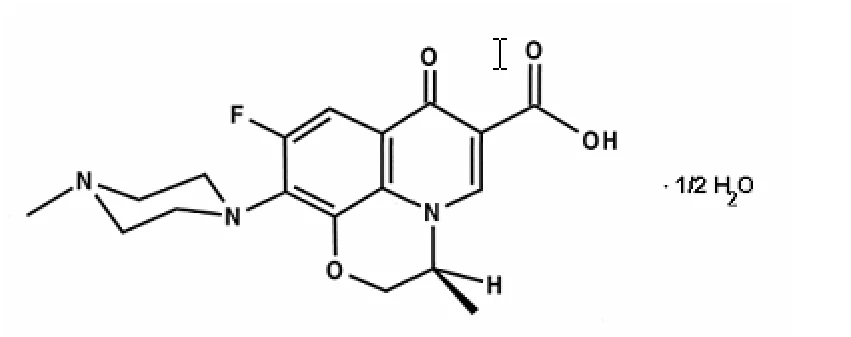
Chemical name: (S)-9-fluoro-2,3-dihydro-3-methyl-10-(4-methyl-1-piperazinyl)-7-oxo-7H-pyrido[1,2,3-de]-1,4-benzoxazine-6-carboxylic acid hemihydrate
Molecular formula and molecular mass: C18H20FN3O4 . ½ H2O, 370.4 g/mol (levofloxacin hemihydrate)
Structural formula:
Physicochemical properties: Light yellowish powder, odourless.
Solubility: Sparingly soluble in water and in methanol.
Solubility of Levofloxacin in water depends on pH
(PDR): -pH 2-5, solubility 100 mg/ml
-pH 5.8, solubility 272 mg/ml
-pH 7 and more, solubility 30-50 mg/ml pKa: pKa1: 6
pKa2: 8.2 (4, 5, 6)
Partition Coefficient: log P: - 0.4 (3)
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Acute Sinusitis
Study demographics and trial design
Table 7 - Summary of patient demographics for clinical trials in Acute Sinusitis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number)a | Mean age (Range) | Gender Male/female |
|---|---|---|---|---|---|
| CAPSS-232 | Double-blind, randomized, prospective, multicentre | oral levofloxacin 750 mg once daily for 5 days | n=389b | 41.7 (18-86) | 152/237 |
| oral levofloxacin 500 mg once daily for 10 days | n=391b | 42.2 (18-85) | 173/218 | ||
| M92-040 | Randomized, open-label, active-controlled | oral levofloxacin 500 mg once daily for 10-14 days | n=306 | 39.2 (18-85) | 115/191 |
| oral amoxicillin 500 mg/clavulanate 125 mg three times daily for 10-14 days | n=309 | 38.6 (18-84) | 110/199 | ||
| N93-006 | Open-label, non-comparative | oral levofloxacin 500 mg once daily for 10-14 days | n=329 | 41.6 (18-89) | 137/192 |
a Subjects enrolled and randomized to treatment
b 780 outpatient adults with clinically and radiologically determined acute maxillary sinusitis (ITT population)
Study Results
5 Day Treatment Regimen
Table 8 - Results of study CAPSS-232 in Acute Sinusitis
| Endpoints | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Intervalc |
|---|---|---|---|
| Clinical Success Ratea,b | 81/90 (90) (45.6% cured; 44.4% improved) | 89/95 (93.7) (55.8% cured; 37.9% improved) | (-4.8, 12.1) |
| Microbiologic Eradication Rated | 140/152 (92.1) | 133/149 (89.3) | (-9.7, 4.1) |
a Test-of-Cure visit 17 to 22 days after first dose of active study drug (7-12 days after last dose for 500 mg arm, 12-17 days after last dose for 750 mg arm) in microbiologically clinically evaluable population (subset of 462 patients where sinus samples were taken by sinus puncture)
b Clinical success was defined as complete (cured) or partial (improved) resolution of pre-treatment signs and symptoms of ABS to such extent that no further antibiotic treatment was deemed necessary c Two-sided 95% CIs (with continuity correction) around the difference in response rates
d Microbiologically evaluable population
Table 9 - Clinical Success Ratesa for Microbiologically Evaluable Populationb (CAPSS-232)
| Pathogen | Levofloxacin 750 mg x 5 days n/N (%) | Comparator n/N (%) |
|---|---|---|
| Streptococcus pneumoniae | 25/27 (92.6) | 26/27 (96.3) |
| Haemophilus influenzae | 19/21 (90.5) | 25/27 (92.6) |
| Moraxella catarrhalis | 10/11 (90.9) | 13/13 (100) |
a Eradication rate for the three pathogens was the same as clinical success rate because microbiological success was presumed based on clinical success
b Subset of 462 patients where sinus samples were taken by sinus puncture
10-14 Day Treatment Regimen
Table 10 – Clinical Successa in Pivotal Acute Sinusitis Studies – Clinically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
|---|---|---|---|
| M92-040 | 236/267 (88.4) | 234/268 (87.3) | (-6.8, 4.6) |
| N93-006 | 265/300 (88.3) | N/A | N/A |
a cured plus improved
Table 11– Microbiologic Eradication in Pivotal Acute Sinusitis Studies – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
|---|---|---|---|
| M92-040 | N/A | N/A | N/A |
| N93-006 | 127/138 (92) | N/A | N/A |
Table 12 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable
Population (N93-006)
| Pathogen | Levofloxacin n/N (%) |
|---|---|
| Haemophilus influenzae | 35/36 (97.2) |
| Streptococcus pneumoniae | 32/32 (100) |
| Staphylococcus aureus | 31/33 (93.9) |
| Moraxella (Branhamella) catarrhalis | 14/15 (93.3) |
Community Acquired Pneumonia
Study demographics and trial design
Table 13 - Summary of patient demographics for clinical trials in Community Acquired Pneumonia
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number)a | Mean age (Range) | Gender Male/female |
|---|---|---|---|---|---|
| CAPSS-150 | Double-blind, randomized, prospective, multicentre | oral or IV levofloxacin 750 mg once daily for 5 days | n=256b | 53.1 (18-86) | 148/108 |
| oral or IV levofloxacin 500 mg once daily for 10 days | n=272 b | 55.3 (18-89) | 162/110 | ||
| K90-071 | Open-label, randomized, active-controlled | levofloxacin oral 488 mg or IV 500 mg once daily for 7-14 days | n=295 | 49 (18-87) | 162/133 |
| oral cefuroxime axetil 500 mg twice daily or IV ceftriaxone sodium 1 to 2 g once daily or in equally divided doses given twice daily for 7-14 days | n=295 | 50.3 (18-96) | 163/132 | ||
| M92-075 | Open-label, non-comparative | oral or IV levofloxacin 500 mg once daily for 7-14 days | n=264 | 51.9 (18-93) | 146/118 |
a Subjects enrolled and randomized to treatment
b 528 outpatient and hospitalized adults with clinically and radiologically determined mild to severe community-acquired pneumonia
Study Results
5 Day Treatment Regimen
Table 14 - Results of study CAPSS-150 in Community Acquired Pneumonia
| Endpoints | Levofloxacin 750 mg once daily for 5 days n/N (%) | Comparator n/N (%) | 95% Confidence Intervalc |
|---|---|---|---|
| Clinical Success Rate a,b | 183/198 (92.4) | 175/192 (91.1) | (-7, 4.4) |
| Microbiologic Eradication Rated | 96/103 (93.2) | 85/92 (92.4) | (-8.6, 7) |
a 7-14 days after last dose of active study medication for clinically evaluable population
b success rates include the clinical response category of cured and improved
c two-sided 95% CIs (with continuity correction) around the difference in response rates
d 7-14 days after last dose of active study medication for microbiologically evaluable population
In the clinically evaluable population (31-38 days after enrollment) pneumonia was observed in 7 out of 151 patients in the levofloxacin 750 mg group and 2 out of 147 patients in the levofloxacin 500 mg group. Given the small numbers observed, the significance of this finding cannot be determined statistically.
Table 15 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable
Population (5-day regimen)
| Pathogen | Levofloxacin 750 mg n/N (%) |
| Penicillin susceptible S. pneumoniae | 19/22 (86.4) |
| Haemophilus influenzae | 12/13 (92.3) |
| Haemophilus parainfluenzae | 12/12 (100) |
| Mycoplasma pneumoniae | 32/34 (94.1) |
| Chlamydia pneumoniae | 20/22 (90.9) |
| Legionella pneumophila | 12/12 (100) |
7 to 14 Day Treatment Regimen
In three North American clinical studies, of 655 patients treated with levofloxacin for community-acquired pneumonia, 45 clinically and microbiologically evaluable patients were defined as severely ill by study criteria and met American Thoracic Society criteria for severe community-acquired pneumonia (American Thoracic Society, 1993). Clinical success (cure and improvement) was achieved in 98% of these 45 patients. Data on the treatment of patients with severe Legionella pneumonia is limited to one patient.
Data on the treatment of community-acquired pneumonia due to penicillin-resistant S. pneumoniae is limited to 12 evaluable patients from the combined clinical trials database. Of these, 4 were considered to have been severe. All 12 patients achieved clinical success (see 15 MICROBIOLOGY).
The following tables describe the results from the two pivotal trials for community-acquired pneumonia (7-14 day treatment regimen).
Table 16 – Clinical Successa in Pivotal Community Acquired Pneumonia Studies – Clinically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-071 | 218/226 (96.5) | 208/230 (90.4) | (-10.7, -1.3) |
| M92-075 | 222/234 (94.9) | N/A | N/A |
a cured plus improved
Table 17 – Microbiologic Eradication in Pivotal Community Acquired Pneumonia Studies -Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-071 | 126/128 (98.4) | 126/144 (87.5) | (-17.1, -4.7) |
| M92-075 | 155/163 (95.1) | N/A | N/A |
Table 18 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (K90-071)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Chlamydia pneumoniae | 46/47 (97.9) | 49/53 (92.5) |
| Streptococcus pneumoniae | 39/39 (100) | 39/40 (97.5) |
| Haemophilus influenzae | 30/30 (100) | 19/24 (79.2) |
| Mycoplasma pneumoniae | 19/19 (100) | 22/22 (100) |
| Staphylococcus aureus | 10/10 (100) | 9/9 (100) |
| Haemophilus parainfluenzae | 7/8 (87.5) | 15/21 (71.4) |
| Moraxella (Branhamella) catarrhalis | 7/7 (100) | 6/7 (85.7) |
| Legionella pneumophila | 5/5 (100) | 3/4 (75) |
| Klebsiella pneumonia | 3/3 (100) | 8/8 (100) |
Table 19 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (M92-075)
| Pathogen | Levofloxacin n/N (%) |
| Chlamydia pneumoniae | 71/75 (94.7) |
| Streptococcus pneumoniae | 43/44 (97.7) |
| Haemophilus influenzae | 38/39 (97.4) |
| Staphylococcus aureus | 10/12 (83.3) |
| Moraxella (Branhamella) catarrhalis | 11/11 (100) |
| Mycoplasma pneumoniae | 10/10 (100) |
| Haemophilus parainfluenzae | 8/9 (88.9) |
| Klebsiella pneumonia | 7/7 (100) |
| Legionella pneumophila | 4/5 (80) |
Acute Bacterial Exacerbation of Chronic Bronchitis
Study demographics and trial design
Table 20 - Summary of patient demographics for clinical trials in Acute Bacterial Exacerbation of Chronic Bronchitis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number)a | Mean age (Range) | Gender Male/Female |
| CAPSS-197 | Multicentre, randomized, blinded, non- | oral levofloxacin 750 mg once daily for 5 days | n=187b | 58 (18-91) | 93/94 |
| oral amoxicillin 875 mg/clavulanate 125 | n=182b | 59 (20-85) | 88/94 | ||
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number)a | Mean age (Range) | Gender Male/Female |
| inferiority | mg twice daily for 10 days | ||||
| K90-070 | Open-label, randomized, active- controlled | oral levofloxacin 488 mg once daily for 5-7 days | n=187 | 59.8 (21-89) | 107/80 |
| oral cefaclor 250 mg three times daily for 7-10 days | n=186 | 61.2 (19-89) | 108/78 | ||
| M92-024 | Open-label, randomized, active-controlled | oral levofloxacin 500 mg once daily for 5-7 days | n=248 | 51.7 (18-97) | 124/124 |
| oral cefuroxime axetil 250 mg twice daily for 10 days | n=244 | 53.1 (18-87) | 140/104 | ||
a Subjects enrolled and randomized to treatment
b From ITT population. Study subjects were characterized by FEV1<50% predicted, or FEV1 between 50% and 65% predicted, with ≥4 exacerbations in the preceding 12 months and/or the presence of significant co-morbidity. About half (48.2%) of the subjects were current smokers, with a mean pack-year history of 42.4
Study Results
5 Day Treatment Regimen
Table 21 - Results of Study CAPSS-197 in Acute Bacterial Exacerbation of Chronic Bronchitis
| Endpoints | Levofloxacin 750 mg once daily for 5 days n/N (%) | Comparator n/N (%) | Differencec | 95% Confidence Intervald |
| Clinical Success Ratea | Successb: 95/120 (79.2) Non-success: 25/120 (20.8) | Successb: 103/126 (81.7) Non-success: 23/126 (18.3) | 2.6 | (-7.8, 12.9) |
| Microbiologic Eradication Ratee | 70/86 (81.4) | 71/89 (79.8) | -1.6 | (-13.9, 10.7) |
a 17 to 26 days after the first dose of study drug for clinical evaluable subjects
b Success rates include the clinical response category of cured and improved
c Difference in success rates
d Two-sided 95% CIs (with continuity correction) around the difference (amoxicillin/clavulanate minus levofloxacin) in clinical success rates
e Microbiologically evaluable population
Table 22 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Staphylococcus aureus | 4/5 (80) | 3/5 (60) |
| Streptococcus pneumoniae | 16/18 (88.9) | 10/13 (76.9) |
| Haemophilus influenzae | 25/30 (83.3) | 20/20 (100) |
| Haemophilus parainfluenzae | 18/20 (90) | 15/18 (83.3) |
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Moraxella catarrhalis | 10/12 (83.3) | 16/19 (84.2) |
7 Day Treatment Regimen
Table 23– Clinical Successa in Pivotal Acute Bacterial Exacerbation of Chronic Bronchitis Studies – Clinically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-070 | 141/154 (91.6%) | 142/155 (91.6%) | (-6.5, 6.6) |
| M92-024 | 210/222 (94.6%) | 212/229 (92.6%) | (-6.8, 2.7) |
a Cured plus improved
Table 24 – Microbiologic Eradication in Pivotal Acute Bacterial Exacerbation of Chronic Bronchitis Studies – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-070 | 97/103 (94.2) | 77/89 (86.5) | (-16.6, 1.3) |
| M92-024 | 129/134 (96.3) | 137/147 (93.2) | (-8.6, 2.5) |
Table 25 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (K90-070)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Haemophilus influenzae | 21/21 (100) | 17/24 (70.8) |
| Moraxella (Branhamella) catarrhalis | 18/19 (94.7) | 8/8 (100) |
| Haemophilus parainfluenzae | 14/15 (93.3) | 7/7 (100) |
| Pseudomonas aeruginosa | 8/10 (80) | 11/14 (78.6) |
| Streptococcus pneumoniae | 9/10 (90) | 6/7 (85.7) |
| Staphylococcus aureus | 8/9 (88.9) | 2/3 (66.7) |
Table 26 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (M92-024)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Haemophilus influenzae | 42/44 (95.5) | 29/31 (93.5) |
| Haemophilus parainfluenzae | 27/27 (100) | 30/32 (93.8) |
| Moraxella (Branhamella) catarrhalis | 25/25 (100) | 29/32 (90.6) |
| Streptococcus pneumoniae | 14/16 (87.5) | 10/10 (100) |
| Staphylococcus aureus | 10/10 (100) | 34/35 (97.1) |
| Pseudomonas aeruginosa | 9/10 (90) | 8/9 (88.9) |
Nosocomial Pneumonia
Study demographics and trial design
Table 27 - Summary of patient demographics for clinical trials in Nosocomial Pneumonia
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number)a | Mean age (Range) | Gender Male/female |
| CAPSS-117 | Open-label, randomized, active-controlled multicentre | IV levofloxacin 750 mg once daily for ≥ 24 hours with switch to oral levofloxacin 750 mg once daily at investigator discretion (7-15 days total) | n=220 | 55.8 (19-93) | 161/59 |
IV imipenem/cilastatin 0.5-1 g q6-8h for ≥3 days with switch to oral ciprofloxacin 750 mg q12h at investigator discretion (7-15 days total) | n=218 | 55.5 (18-93) | 154/64 | ||
a Subjects enrolled and randomized to treatment
Table 28 - Results of study CAPSS-117 in Nosocomial Pneumonia
| Endpoints | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| Clinical Success Ratea | 70/118 (59.3%) | 70/112 (62.5%) | (-9.9, 16.2) |
| Microbiologic Eradication Rateb | 62/93 (66.7%) | 57/94 (60.6%) | (-20.3, 8.3) |
a Success includes Cured and Improved; clinically evaluable population
b overall microbiologic eradication rates by subject for microbiologically evaluable population
Table 29 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (CAPSS-117)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Staphylococcus aureus | 14/21 (66.7) | 13/19 (68.4) |
| Pseudomonas aeruginosa | 10/17 (58.8) | 5/17 (29.4) |
| Haemophilus influenzae | 13/16 (81.3) | 14/15 (93.3) |
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Escherichia coli | 10/12 (83.3) | 7/11 (63.6) |
| Klebsiella pneumoniae | 9/11 (81.8) | 6/7 (85.7) |
| Serratia marcescenes | 9/11 (81.8) | 2/7 (28.6) |
| Streptococcus pneumoniae | 3/4 (75) | 5/7 (71.4) |
Uncomplicated Skin and Skin Structure Infections
Study demographics and trial design
Table 30 - Summary of patient demographics for clinical trials in Uncomplicated Skin and Skin Structure Infections
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number)a | Mean age (Range) | Gender Male/Female | ||||||
| K90-075 | Open-label, randomized, active-controlled | oral levofloxacin 488 mg once daily for 7-10 days | n=231 | 42.8 (15-85) | 124/107 | ||||||
| oral ciprofloxacin HCl 500 mg twice daily for 7-10 days | n=238 | 45.2 (18-88) | 118/120 | ||||||||
| L91-031 | Double-blind, randomized, active-controlled | oral levofloxacin 500 mg once daily for 7 days | n=136 | 43 (16-79) | 67/69 | ||||||
| oral ciprofloxacin HCl 500 mg twice daily for 10 days | n=136 | 44.3 (15-81) | 78/58 | ||||||||
a Subjects enrolled and randomized to treatment
Study Results
Table 31 – Clinical Successa in Pivotal Uncomplicated Skin and Skin Structure Infection Studies – Clinically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-075 | 178/182 (97.8) | 182/193 (94.3) | (-7.7, 0.7) |
| L91-031 | 124/129 (96.1) | 116/124 (93.5) | (-8.4, 3.3) |
a cured plus improved
Table 32 – Microbiologic Eradication in Pivotal Uncomplicated Skin and Skin Structure Infection Studies – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| K90-075 | 153/157 (97.5) | 135/152 (88.8) | (-14.5, -2.7) |
| L91-031 | 93/100 (93) | 87/97 (89.7) | (-11.7, 5.1) |
Table 33 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (K90-075)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Staphylococcus aureus | 87/87 (100) | 76/87 (87.4) |
| Streptococcus pyogenes | 14/14 (100) | 18/20 (90) |
| Pseudomonas aeruginosa | 7/8 (87.5) | 10/10 (100) |
Table 34 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (L91-031)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Staphylococcus aureus | 66/70 (94.3) | 70/75 (93.3) |
| Streptococcus pyogenes | 17/18 (94.4) | 12/13 (92.3) |
| Pseudomonas aeruginosa | 5/5 (100) | 5/5 (100) |
Complicated Skin and Skin Structure Infections
Study demographics and trial design
Table 35 - Summary of patient demographics for clinical trial in Complicated Skin and Skin Structure Infections
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number)a | Mean age (Range) | Gender male/female |
| LOFBIV-SSS-040 | Multicentre, open-label, randomized, comparative | oral or IV levofloxacin 750 mg once daily for 7-14 days | n=200 | 51.9 (18-90) | 126/74 |
| IV ticarcillin/clavulanate 3.1 g every 4-6 hours alone or followed by amoxicillin/clavulanate 875 mg twice daily (7-14 days total) | n=199 | 49.8 (18-90) | 117/82 | ||
a Subjects enrolled and randomized to treatment
Table 36 - Results of study LOFBIV-SSS-040 in Complicated Skin and Skin Structure Infections
| Endpoints | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| Clinical Success Ratea | 116/138 (84.1) | 106/132 (80.3) | (-13.3, 5.8) |
| Microbiologic Eradication Rateb | 82/98 (83.7) | 70/98 (71.4) | (-24.3, -0.2) |
a Success includes Cured and Improved; clinically evaluable population
b overall microbiologic eradication rates by subject for microbiologically evaluable population
Table 37 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (LOFBIV-SSS-040)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Staphylococcus aureus | 50/56 (89.3) | 35/49 (71.4) |
| Streptococcus faecalis | 8/10 (80) | 6/11 (54.5) |
| Streptococcus pyogenes | 5/6 (83.3) | 6/7 (85.7) |
| Proteus mirabilis | 9/10 (90) | 7/12 (58.3) |
| Streptococcus agalactiae | 9/12 (75) | 9/13 (69.2) |
| Pseudomonas aeruginosa | 4/7 (57.1) | 5/6 (83.3) |
Complicated Urinary Tract Infection and Acute Pyelonephritis
Study demographics and trial design
Table 38 - Summary of patient demographics for clinical trials in Complicated Urinary Tract Infection (cUTI) and Acute Pyelonephritis (AP)
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number)a | Mean age (Range) | Gender male/female |
| CAPSS-349 | Multicentre, randomized, double-blind | IV levofloxacin 750 mg and /or oral levofloxacin 750 mg once daily for 5 days | n=537b | 54 (18-94) | 207/330 |
| IV ciprofloxacin 400 mg and/or oral ciprofloxacin 500 mg twice daily for 10 days | n=556b | 54.4 (18-93) | 220/336 | ||
| L91-058 | Double-blind, randomized, active-controlled | oral levofloxacin 250 mg once daily for 10 days | n=285 | 51.7 (18-95) | 117/168 |
| oral ciprofloxacin 500 mg twice daily for 10 days | n=282 | 49.7 (18-93) | 112/170 | ||
| L91-059 | Open-label, randomized, active-controlled | oral levofloxacin 250 mg once daily for 7-10 days | n=326 | 62.5 (19-92) | 124/202 |
| oral lomefloxacin HCl 400 mg once-daily for 14 days | n=324 | 59.9 (18-91) | 105/219 |
a Subjects enrolled and randomized to treatment
b Intent-to-treat population. Patients with AP complicated by underlying renal diseases or conditions such as complete obstruction, surgery, transplantation, concurrent infection or congenital malformation were excluded.
Study results
5 Day Treatment Regimen
Table 39 – Clinical Successa in Complicated Urinary Tract Infection (cUTI) and Acute Pyelonephritis (AP) – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Intervalb |
| CAPSS-349 | 229/265 (86.4) | 213/241 (88.4) | (-3.8, 7.7) |
a Clinical success includes subjects who were cured or improved at the Posttherapy Visit
b Two-sided 95% confidence interval around the difference (comparator minus levofloxacin)
Table 40 - Results of Study CAPSS-349 in Complicated Urinary Tract Infection (cUTI) and Acute Pyelonephritis (AP)
| Primary Endpoint |
| Diagnosis | Levofloxacin |
750 mg once daily for 5
days
| Comparator | Differencef | 95% Confidence Intervalg |
Microbiologic Eradicationa
mITT Population b,c
Overall (cUTI or
AP) 240/317 (75.7)
| 229/302 (75.8) |
0.1 (-6.6, 6.9)
| cUTI | 162/223 (72.6) | 151/204 (74) | 1.4 | (-7, 9.8) | |||||
| AP | 78/94 (83) | 78/98 (79.6) | -3.4 | (-14.4, 7.6) | |||||
| Microbiologically Evaluable Population d,e | |||||||||
| Overall (cUTI or AP) | 228/265 (86%) | 215/241 (89.2%) | 3.2 | (-2.5, 8.9) | |||||
| cUTI | 154/185 (83.2%) | 144/165 (87.3%) | 4 | (-3.4, 11.4) | |||||
| AP | 74/80 (92.5%) | 71/76 (93.4%) | 0.9 | (-7.1, 8.9) | |||||
a At posttherapy visit (10-14 days after last active dose of levofloxacin and 5-9 days after last active dose of ciprofloxacin).
b The mITT population included patients who had a clinical diagnosis of AP or cUTI and who had a positive (≥105 CFU/mL) urine culture with no more than 2 uropathogens at Study Entry.
c In the mITT population there were a limited number of patients treated with IV therapy (levofloxacin-8, comparator-9), with catheters (levofloxacin-4, comparator-5) and with bacteremia (levofloxacin-13, comparator-12).
d The microbiologically evaluable population included patients with a confirmed diagnosis of cUTI or AP according to the protocol-specified inclusion criteria and with a known uropathogen with adequate growth (≥ 105 CFU/mL) who met all other microbiologic evaluability criteria.
e In the microbiologically evaluable population there were a limited number of patients treated with IV therapy (levofloxacin-4, comparator-3), with catheters (levofloxacin-3, comparator-3) and with bacteremia (levofloxacin-10, comparator-8).
f Difference in eradication rates (comparator minus levofloxacin).
g Two-sided 95% confidence interval around the difference (comparator minus levofloxacin) in microbiologic eradication rates.
Table 41 - Microbiologic Eradication Rates by Pathogen at Posttherapy Visit
| Pathogen | Levofloxacin 750 mg x 5 days n/N (%) | Comparator n/N (%) | |||||
| mITT Population | |||||||
| Overall | AP | cUTI | Overall | AP | cUTI | ||
| Escherichia coli | 165/206 (80.1) | 67/81 (82.7) | 98/125 (78.4) | 158/216 (73.1) | 70/89 (78.7) | 88/127 (69.3) | |
| Klebsiella pneumoniae | 21/29 (72.4) | 19/26 (73.1) | 26/29 (89.7) | 22/25 (88) | |||
| Proteus mirabilis | 13/13 (100) | 10/10 (100) | 6/7 (85.7) | 6/7 (85.7) | |||
| Escherichia coli with bacteremia | 7/12 (58.3) | 8/12 (66.7) | |||||
| Microbiologically Evaluable Population | |||||||
| Overall | AP | cUTI | Overall | AP | cUTI | ||
| Escherichia coli | 155/172 (90.1) | 63/69 (91.3) | 92/103 (89.3) | 148/168 (88.1) | 63/67 (94) | 85/101 (84.2) | |
| Klebsiella pneumoniae | 20/23 (87) | 18/21 (85.7) | 24/26 (92.3) | 21/23 (91.3) | |||
| Proteus mirabilis | 12/12 (100) | 9/9 (100) | 6/6 (100) | 6/6 (100) | |||
| Escherichia coli with bacteremia | 6/9 (66.7) | 7/8 (87.5) | |||||
Table 42 - Relapse Rates at Post-Study Visita
Levofloxacin 750 mg x 5 days n/N (%) | Comparator n/N (%) | ||
| mITT Population | |||
| Overall (cUTI or AP) | 13/207 (6.3) | 11/204 (5.4) | |
| cUTI | 8/136 (5.9) | 10/139 (7.2) | |
| AP | 5/71 (7) | 1/65 (1.5) | |
| Microbiologically Evaluable Population | |||
| Overall (cUTI or AP) | 12/199 (6) | 11/195 (5.6) | |
| cUTI | 7/131 (5.3) | 10/135 (7.4) | |
| AP | 5/68 (7.4) | 1/60 (1.7) | |
a 33-40 days after the last active dose of levofloxacin and 28-35 days after the last active dose of ciprofloxacin
10 Day Treatment Regimen
Table 43 – Clinical Successa in Pivotal cUTI and AP Studies – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| L91-058 | 163/177 (92.1) | 155/171 (90.6) | (-7.6, 4.7) |
| L91-059 | 195/209 (93.3) | 183/204 (89.7) | (-9.2, 2) |
a cured plus improved
Table 44 – Microbiologic Eradication in Pivotal cUTI and AP Studies – Microbiologically Evaluable Subjects
| Study Number | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| L91-058 | 164/177 (92.7) | 159/171 (93) | (-5.4, 6) |
| L91-059 | 198/209 (94.7) | 189/204 (92.6) | (-7, 2.8) |
Table 45 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (L91-058)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Escherichia coli | 88/92 (95.7) | 96/99 (97) |
| Klebsiella pneumonia | 31/32 (96.9) | 22/23 (95.7) |
| Streptococcus faecalis | 8/9 (88.9) | 6/11 (54.5) |
| Proteus mirabilis | 13/14 (92.9) | 5/5 (100) |
| Pseudomonas aeruginosa | 7/12 (58.3) | 7/7 (100) |
| Enterobacter cloacae | 9/9 (100) | 4/4 (100) |
Table 46 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (L91-059)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Escherichia coli | 118/119 (99.2) | 116/118 (98.3) |
| Klebsiella pneumonia | 29/31 (93.5) | 23/25 (92) |
| Proteus mirabilis | 11/11 (100) | 9/9 (100) |
| Streptococcus faecalis | 4/8 (50) | 6/8 (75) |
| Pseudomonas aeruginosa | 8/9 (88.9) | 4/6 (66.7) |
| Enterobacter cloacae | 6/7 (85.7) | 4/6 (66.7) |
Uncomplicated Urinary Tract Infections
Study demographics and trial design
Table 47 - Summary of patient demographics for clinical trials in Uncomplicated Urinary Tract Infections
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number)a | Mean age (Range) | Gender Male/female | ||||
| LOFBO-UTI-060 | Double-blind, randomized, active-controlled, multi-centre | oral levofloxacin 250 mg once daily for 3 days | n=298 | 31.3 (18-57) | 0/298 | ||||
| oral ofloxacin 200 mg twice daily for 3 days | n=296 | 32 (18-71) | 0/296 | ||||||
a Subjects enrolled and randomized to treatment
Study Results
Table 48 - Results of study LOFBO-UTI-060 in Uncomplicated Urinary Tract Infections
| Endpoints | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| Clinical Success Ratea | 154/157 (98.1) | 160/165 (97) | (-4.8, 2.6) |
| Microbiologic Eradication Rateb | 151/157 (96.2) | 153/165 (92.7) | (-8.7, 1.8) |
a Success includes Cured and Improved; microbiologically evaluable population
b Overall microbiologic eradication rates by subject for microbiologically evaluable population
Table 49 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (LOFBO-UTI-060)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Escherichia coli | 125/127 (98.4) | 131/138 (94.9) |
| Klebsiella pneumoniae | 10/11 (90.9) | 8/8 (100) |
| Staphylococcus saprophyticus | 8/8 (100) | 3/3 (100) |
| Staphylococcus aureus | 5/5 (100) | 3/3 (100) |
Chronic Bacterial Prostatitis
Study demographics and trial design
Table 50 - Summary of patient demographics for clinical trials in Chronic Bacterial Prostatitis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n = number)a | Mean age (Range) | Gender Male/female |
| CAPSS-101 | Double-blind, randomized, active-controlled, comparative | oral levofloxacin 500 mg once daily for 28 days | n=197 | 50.9 (18-81) | 197/0 |
| oral ciprofloxacin 500 mg twice daily for 28 days | n=180 | 51.5 (19-83) | 180/0 | ||
a Subjects enrolled and randomized to treatment
Study Results
Table 51 - Results of study CAPSS-101 in Chronic Bacterial Prostatitis
| Endpoints | Levofloxacin n/N (%) | Comparator n/N (%) | 95% Confidence Interval |
| Clinical Success Ratea | 122/170 (71.8) | 107/151 (70.9) | (-11.15, 9.34) |
| Microbiologic Eradication Rateb | 102/136 (75) | 96/125 (76.8) | (-8.98, 12.58) |
a Success includes Cured and Improved; mITT
b Overall microbiologic eradication rates by subject for microbiologically evaluable population
Table 52 - Microbiologic Eradication Rates by Pathogen for Microbiologically Evaluable Population (CAPSS-101)
| Pathogen | Levofloxacin n/N (%) | Comparator n/N (%) |
| Escherichia coli | 14/15 (93.3) | 9/11 (81.8) |
| Enterococcus faecalis | 39/54 (72.2) | 34/45 (75.6) |
| Staphylococcus epidermis | 20/24 (83.3) | 26/29 (89.7) |
14.2 Comparative Bioavailability Studies
Comparative bioavailability AA05476 employed a randomized, single dose two-way crossover bioavailability study of Pro Doc Ltée. and Ortho-McNeil Pharmaceutical, USA (Levaquin®) 750 mg Levofloxacin tablets in eight healthy male and ten healthy nonpregnant female subjects under fasting conditions. The following table presents a summary of the comparative bioavailability data demonstrating bioequivalence of the test and reference tablets.
Summary Table of the Comparative Bioavailability Data
Levofloxacin (1 x 750 mg) From measured data Least Square Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* Levofloxacin tablets | Reference† Levaquin® tablets | % Ratio of Least Square Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 66473.02 67651.2 (21.6) | 68106.69 69096.8 (18.9) | 97.6% | 94.4%-100.9% |
AUCI (ng·h/mL) | 68208.39 69342.4 (21) | 69870.88 70898.9 (18.5%) | 97.6% | 94.6%-100.7% |
Cmax (ng/mL) | 6442.074 6632.22 (22) | 6760.017 6934.44 (22) | 95.3% | 89.4%-101.6% |
| Tmax§ (h) | 1.882 (46) | 1.793 (44) | ||
| T½§ (h) | 5.919 (17.3) | 5.915 (16.4) | ||
* Levofloxacin 750 mg tablets manufactured for Pro Doc Ltée.
† Levaquin® (levofloxacin) 750 mg tablets manufactured by Ortho-McNeil Pharmaceutical, USA were purchased in USA.
§ Expressed as the arithmetic mean (CV %) only.
15 MICROBIOLOGY
Levofloxacin is the L-isomer of the racemate, ofloxacin, a quinolone antibacterial agent. The antibacterial activity of ofloxacin resides primarily in the L-isomer. The mechanism of action of levofloxacin and other quinolone antibacterials involves inhibition of bacterial topoisomerase II (DNA gyrase) and topoisomerase IV, enzymes required for DNA replication, transcription, repair, and recombination. In this regard, the L-isomer produces more hydrogen bonds and therefore, more stable complexes with DNA gyrase than does the D-isomer. Microbiologically, this translates into a 25- to 40-fold greater antibacterial activity for the L-isomer, levofloxacin, over the D-isomer. Quinolones rapidly and specifically inhibit bacterial DNA synthesis.
Levofloxacin has in vitro activity against a broad spectrum of gram-positive and gram-negative aerobic and anaerobic bacteria. Levofloxacin is often bactericidal at concentrations equal to or greater than the Minimum Inhibitory Concentrations (MIC). The in vitro activity of levofloxacin against clinical isolates is summarized in Table 53.
Table 53 - In Vitro Activity of Levofloxacin Against Clinical Isolates
| Organism | (# of isolates) | MIC (mcg/mL) | ||
|---|---|---|---|---|
| 50% | 90% | Range | ||
| Acinetobacter baumannii | (57) | 0.120 | 16 | 0.060->16 |
| Acinetobacter calcoaceticus | (48) | 0.250 | 0.250 | 0.030-64 |
| Chlamydia pneumoniae | (10) | 0.250 | 0.250 | 0.125-0.500 |
| Citrobacter diversus | (20) | 0.030 | 0.030 | 0.015-0.060 |
| Citrobacter freundii | (50) | 0.060 | 1 | 0.015-8 |
| Enterobacter spp. | (200) | 0.060 | 0.500 | ≤0.008->16 |
| Enterobacter aerogenes | (44) | 0.250 | 0.500 | 0.060-2 |
| Enterobacter agglomerans | (13) | 0.250 | 0.250 | 0.060-0.500 |
| Enterobacter cloacae | (97) | 0.250 | 0.500 | 0.025-16 |
| Enterococcus spp. | (162) | 1 | >16 | 0.500->16 |
| Enterococcus (Streptococcus) faecalis | (122) | 1 | 16 | 0.250-64 |
| Escherichia coli | (817) | 0.030 | 0.060 | ≤0.008->16 |
| Haemophilus influenzae | (94) | 0.015 | 0.015 | ≤0.008-0.030 |
| Haemophilus parainfluenzae | (127) | 0.250 | 0.250 | 0.015-1 |
| Haemophilus parahemolyticus | (12) | 0.250 | 0.250 | 0.008-0.250 |
| Klebsiella spp. | (345) | 0.060 | 1 | 0.015-16 |
| Klebsiella oxytoca | (43) | 0.250 | 0.250 | 0.030-2 |
| Organism | (# of isolates) | MIC (mcg/mL) | ||
| 50% | 90% | Range | ||
| Klebsiella pneumoniae | (225) | 0.250 | 0.500 | 0.060-18 |
| Legionella pneumophila | (10) | 0.030 | 0.0079-0.030 | |
| Moraxella (Branhamella) catarrhalis | (110) | 0.250 | 0.250 | 0.0150-1 |
| Morganella morganii | (43) | 0.060 | 1 | 0.0150->16 |
| Mycoplasma pneumoniae | (60) | 0.250 | 0.500 | 0.250-0.500 |
| Neisseria gonorrhoeae | (47) | ≤ 0.008 | 0.016 | ≤0.008-0.060 |
| Neisseria meningitidis | (13) | 0.250 | 0.250 | 0.250-0.500 |
| Proteus and Providencia spp. | (36) | 0.060 | 1 | 0.015->16 |
| Proteus mirabilis | (123) | 0.060 | 0.120 | 0.015-4 |
| Proteus vulgaris | (14) | 0.250 | 0.250 | 0.250-0.500 |
| Pseudomonas aeruginosa* | (378) | 1 | 8 | 0.030->16 |
| Pseudomonas maltophilia | (17) | 0.500 | 2 | 0.250-4 |
| Salmonella spp. | (10) | 0.060 | 0.060 | 0.060-0.250 |
| Serratia spp. | (65) | 0.120 | 0.500 | 0.030->16 |
| Serratia marcescens | (42) | 0.250 | 1 | 0.125-4 |
| Staphylococcus aureus | (565) | 0.250 | 0.500 | 0.125-32 |
| Staphylococcus aureus, methicillin-resistant (MRSA)** | (25) | 0.250 | 0.500 | 0.120-1 |
| Staphylococcus aureus, methicillin-susceptible (MSSA) | (25) | 0.250 | 0.500 | 0.120-0.500 |
| Staphylococcus aureus, oxacillin-resistant | (62) | 8.000 | >16 | 0.120->16 |
| Staphylococcus aureus, oxacillin-susceptible | (367) | 0.120 | 0.500 | 0.030-16 |
| Staphylococcus epidermidis | (47) | 0.250 | 8 | 0.250-32 |
| Staphylococcus epidermidis, methicillin-resistant (MRSE) | (14) | 0.250 | 0.250 | 0.120-0.500 |
| Staphylococcus epidermidis, methicillin-susceptible (MSSE) | (12) | 0.250 | 1 | 0.250-1 |
| Staphylococcus saprophyticus | (16) | 0.500 | 1 | 0.250-2 |
| Stenotrophomonas maltophilia | (43) | 2 | 16 | 0.250-16 |
| Organism | (# of isolates) | MIC (mcg/mL) | ||
| 50% | 90% | Range | ||
| Streptococcus (Viridans group) | (8) | 0.750 | 1 | 0.250-1 |
| Streptococcus (Group C) | (28) | 0.500 | 1 | 0.250-2 |
| Streptococcus (Group G) | (34) | 0.500 | 1 | 0.250-2 |
| Streptococcus agalactiae | (96) | 1 | 2 | 0.500-2 |
| Streptococcus milleri | (35) | 0.500 | 1 | 0.250-4 |
| Streptococcus pneumoniae | (99) | 1 | 1 | 0.500-2 |
| Streptococcus pneumoniae, penicillin-susceptible (MIC ≤0.06 mcg/mL)† | (2699) | 0.500 | 1 | ≤0.004->8 |
| Streptococcus pneumoniae, penicillin-resistant (MIC ≥2.0 mcg/mL)† | (538) | 0.500 | 1 | ≤0.004-2 |
| Streptococcus pneumoniae, clarithromycin-susceptible (MIC≤0.25 mcg/mL)† | (502) | 0.500 | 1 | 0.250->16 |
| Streptococcus pneumoniae, clarithromycin-resistant (MIC ≥1.0 mcg/mL)† | (136) | 1 | 2 | 0.12-16 |
| Streptococcus pneumoniae, erythromycin-resistant (MIC ≥1.0 mcg/mL)† | (27) | 1 | 1 | 0.500-16 |
| Streptococcus pyogenes | (87) | 0.500 | 1 | 0.250-2 |
| Streptococcus sanguis | (19) | 1 | 2 | 0.250-2 |
* As with other drugs in this class, some strains of Pseudomonas aeruginosa may develop resistance fairly rapidly during treatment with levofloxacin.
** Data obtained for isolates from Complicated Skin and Skin Structure clinical studies, and literature, indicate the MIC value has increased for MRSA (see 1 INDICATIONS for approved organisms).
† Based on NCCLS classification
Levofloxacin is not active against Treponema pallidum (see 7 WARNINGS AND PRECAUTIONS, General, Sexually Transmitted Diseases).
Resistance
Resistance to levofloxacin due to spontaneous mutation in vitro is a rare occurrence (range: 10-9 to 10-10). Although cross-resistance has been observed between levofloxacin and other fluoroquinolones, some organisms resistant to other quinolones, including ofloxacin, may be susceptible to levofloxacin.
Susceptibility Tests
Susceptibility testing for levofloxacin should be performed, as it is the optimal predictor of activity.
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimal inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a dilution method*1 (broth or agar) or equivalent with standardized inoculum concentrations and standardized concentrations of levofloxacin powder. The MIC values should be interpreted according to the following criteria:
For testing aerobic microorganisms other than Haemophilus influenzae, Haemophilus parainfluenzae, and Streptococcus pneumoniae:
MIC (mcg/mL) Interpretation
≤2 Susceptible (S)
4 Intermediate (I)
≥8 Resistant (R)
For testing Haemophilus influenzae and Haemophilus parainfluenzae:a
MIC (mcg/mL) Interpretation
≤2 Susceptible (S)
a These interpretive standards are applicable only to broth microdilution susceptibility testing with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium*1.
The current absence of data on resistant strains precludes defining any categories other than “Susceptible”. Strains yielding MIC results suggestive of a “nonsusceptible” category should be submitted to a reference laboratory for further testing.
For testing Streptococcus pneumoniae:b
MIC (mcg/mL) Interpretation
≤2 Susceptible (S)
4 Intermediate (I)
≥8 Resistant (R)
b These interpretive standards are applicable only to broth microdilution susceptibility tests using cation-adjusted Mueller-Hinton broth with 2-5% lysed horse blood.
A report of “Susceptible” indicates that the pathogen is likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable. A report of “Intermediate” indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where a high dosage of drug can be used. This category also provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of “Resistant” indicates that the pathogen is not likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable; other therapy should be selected.
Standardized susceptibility test procedures require the use of laboratory control microorganisms to control the technical aspects of the laboratory procedures. Standard levofloxacin powder should give the following MIC values:
| Microorganism | MIC (mcg/mL) | |
| Enterococcus faecalis | ATCC 29212 | 0.25-2 |
| Escherichia coli | ATCC 25922 | 0.008-0.06 |
| Escherichia coli | ATCC 35218 | 0.015-0.06 |
| Pseudomonas aeruginosa | ATCC 27853 | 0.5-4 |
| Staphylococcus aureus | ATCC 29213 | 0.06-0.5 |
| Haemophilus influenzae | ATCC 49247c | 0.008-0.03 |
| Streptococcus pneumoniae | ATCC 49619d | 0.5-2 |
c This quality control range is applicable to only H. influenzae ATCC 49247 tested by a broth microdilution procedure using Haemophilus Test Medium (HTM)*1.
d This quality control range is applicable to only S. pneumoniae ATCC 49619 tested by a broth microdilution procedure using cation-adjusted Mueller-Hinton broth with 2-5% lysed horse blood.
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure*2 requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 5 mcg levofloxacin to test the susceptibility of microorganisms to levofloxacin. Reports from the laboratory, providing results of the standard single-disk susceptibility test with a 5 mcg levofloxacin disk, should be interpreted according to the following criteria:
For aerobic microorganisms other than Haemophilus influenzae, Haemophilus parainfluenzae, Streptococcus pneumoniae and Neisseria gonorrhoeae:
Zone diameter (mm) Interpretation
≥17 Susceptible (S)
14-16 Intermediate (I)
≤13 Resistant (R)
For Haemophilus influenzae and Haemophilus parainfluenzae:e
Zone diameter (mm) Interpretation
≥17 Susceptible (S)
e These interpretive standards are applicable only to disk diffusion susceptibility testing with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium* (HTM) 2.
The current absence of data on resistant strains precludes defining any categories other than “Susceptible”. Strains yielding zone diameter results suggestive of a “Nonsusceptible” category should be submitted to a reference laboratory for further testing.
For Streptococcus pneumoniae:f
Zone diameter (mm) Interpretation
≥17 Susceptible (S)
14-16 Intermediate (I)
≤13 Resistant (R)
f These zone diameter standards for Streptococcus pneumoniae apply only to tests performed using Mueller-Hinton agar supplemented with 5% sheep blood and incubated in 5% CO2.
Interpretation should be as stated above for results using dilution techniques. Interpretation involves correlation of the diameter obtained in the disk test with the MIC for levofloxacin.
As with standardized dilution techniques, diffusion methods require the use of laboratory control microorganisms to control the technical aspects of the laboratory procedures. For the diffusion technique, the 5 mcg levofloxacin disk should provide the following zone diameters in these laboratory test quality control strains
| Microorganism | Zone Diameter (mm) | |
| Escherichia coli | ATCC 25922 | 29-37 |
| Pseudomonas aeruginosa | ATCC 27853 | 19-26 |
| Staphylococcus aureus | ATCC 25923 | 25-30 |
| Microorganism | Zone Diameter (mm) | |
| Haemophilus influenzae | ATCC 49247g | 32-40 |
| Streptococcus pneumoniae | ATCC 49619h | 20-25 |
g This quality control range is applicable to only H. influenzae ATCC 49247 tested by a disk diffusion procedure using Haemophilus Test Medium (HTM)* 2.
h This quality control range is applicable to only S. pneumoniae ATCC 49619 tested by a disk diffusion procedure using Mueller-Hinton agar supplemented with 5% sheep blood and incubated in 5% CO2.
* References
- 1. National Committee for Clinical Laboratory Standards: Methods for Dilution Antimicrobial Susceptibility Tests for Bacteria that Grow Aerobically, Fourth Edition, 1997.
- 2. National Committee for Clinical Laboratory Standards: Performance Standards for Antimicrobial Disk Susceptibility Tests, Sixth Edition,1997.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
The potential toxicity of levofloxacin has been evaluated in acute, sub-chronic, carcinogenicity, mutagenicity, reproduction and teratology, and special toxicity studies.
Acute Toxicity
Table 54 - Summary of the acute toxicity studies
STRAIN/ SPECIES | # ANIMAL/ GROUP | ROUTE | LD50 mg/kg | SUMMARY TOXIC SIGNS |
|---|---|---|---|---|
| Mouse | M-10 F-10 | PO | 1881 1803 | ↓ locomotor activity, ptosis, respiratory depression, tremor, convulsion |
| Mouse | M-10 | PO | 1943 | ↓ locomotor activity, ptosis, prostration, tremor, convulsion |
| Rat | M-10 F-10 | PO | 1478 1507 | Salivation, ptosis, ↓ locomotor activity, tremor, convulsion, respiratory depression |
| Rat | M-10 | PO | 1754 | |
| Monkey | F-2 | PO | >250 | Soft stool, transient ↓ platelet count and ↑ bw at 250 mg/kg, transient ↑ bilirubin, ↓ bw, and emesis at 500 mg/kg |
| Mouse | M-10 F-10 | IV | 268 323 | ↓ locomotor activity, ptosis, abnormal posture, tachypnea, convulsion, dyspnea |
STRAIN/ SPECIES | # ANIMAL/ GROUP | ROUTE | LD50 mg/kg | SUMMARY TOXIC SIGNS |
| Mouse | M-5 | IV | 244 | Symptoms prior to death: tachypnea, collapse, dyspnea, convulsions, respiratory arrest. In survivors, ↓ locomotor activity and collapse |
| Rat | M-10 F-10 | IV | 423 395 | ↓ locomotor activity, prostration followed by respiratory depression, tachypnea, dyspnea, convulsion, tremor, salivation |
| Dog | F-2 | IV | 200 | Salivation, dyspnea, tonic and clonic convulsion, death from respiratory arrest at 200 mg/kg, lacrimation, vomiting, lethargy, and tremors. ↑ RBC, WBC, ALT and ALP, and ↓ P on Day 2. Values returned to normal by Day 8 |
| Monkey | F-2 | IV | >200 | At 200 mg/kg – ptosis, vomiting, ↓ locomotor activity, prostration and anorexia, ketone urine, proteinuria, ↓ glucose. Ptosis and emesis at 100 mg/kg |
Signs of acute toxicity with metabolites (desmethyl and N-oxide) were similar to that of levofloxacin and were produced at doses significantly greater than would be encountered with therapeutic use.
Sub-Chronic Toxicity
Table 55 – Summary of the sub-chronic toxicity studies
Species, Age/Grp/No., Sex/Grp | Route, Dosage, Duration | Results |
Rat 4-6 wk old 4 grp 10 ♀ & 10♂ /grp | PO 0, 50, 200, 800 4 weeks | Lethality: No treatment-related deaths. Clin Obs: Salivation, body staining, transient pallor and hypothermia at 800 mg/kg. Transient ↓ fc in treated ♂ and ↓ bw gain during week 1 in ♂ at 800 mg/kg. Clin Path: ↑ WBC due to ↑ in lymphocytes at 800 mg/kg. PMNs ↓ in treated ♀ and at 50 and 200 mg/kg in ♂. ↓ K+, Cl-, and urea and ↑ P and ALT (primarily at 800 mg/kg). Higher M:E ratio at 800 mg/kg. Micro: ↓ relative heart weights at 800 mg/kg and ↑ cecal weights at 200 and 800 mg/kg. Slight vacuolization and minimal hypertrophy of hepatocytes at 800 mg/kg and arthropathy (minor) at 800 mg/kg. |
Species, Age/Grp/No., Sex/Grp | Route, Dosage, Duration | Results |
| NOAEL = 200 mg/kg/day. TI= 2.8 | ||
Rat 4-5 wk old 4 grp 20 ♀ & 20 ♂ /grp | PO 0, 20, 80, 320 26 wk | Lethality: No treatment-related deaths. Clin Obs: Salivation, ↑ large fecal pellets, and stained haircoat mainly at 320 mg/kg. ↑ fc at 80 and 320 mg/kg, ↑ food conversion ratios in ♀ at 320 mg/kg. Clin Path: ↓ PMNs in all treated rats, ↑ glucose (treated ♂ ), ↓ triglycerides (320 mg/kg ♀), ↓ ß-globulin (treated rats), ↓ α-globulin (treated ♀), ↓ Cl- (320 mg/kg rats and 80 mg/kg ♀), ↓ total protein (80 and 320 mg/kg ♂), and ↑ urinary pH at 80 and 320 mg/kg. Micro: Dosage-related ↑ cecal weight, elongated and/or distended ceca and engorged goblet cells of the cecal mucosa. Changes in intestinal flora and lower nutrient absorption in the intestines probably responsible for most changes. No arthropathy. NOAEL = 20 mg/kg/day. TI = 2.8 |
Rat 6 wk old 5 grp 10 ♀ & 10 ♂ /grp | Diet 0, 100, 200, 400, 800 13 wk | Lethality: No deaths. Clin Obs:↓ bw at 400 and 800 mg/kg. Clin Path: ↓ total protein (≥200 mg/kg), globulin, and triglycerides (at 800 mg/kg ♂ only). ↑ ALP at 800 mg/kg (♀). Micro: ↓ absolute liver weight ≥400 (♂), ↑ cecal weight and cecal distension (≥100). No arthropathy. NOAEL = 100 mg/kg/day. TI = 14 |
Rat 4 wk old 3 grp, 5 ♂ /grp | IV 0, 20, 100 10 days | NSF |
Rat 4 wk old 4 grp, 4 ♂ /grp | IV 0, 10, 40, 160 2 wk | Lethality: No mortality. Clin Obs: NSF. Clin Path and Micro: Crystalluria, ↑ cecal weight and ↓ (mild) AST and ALT at 160 mg/kg. No arthropathy. NOAEL = 40 mg/kg/day. TI= 5.6 |
| Rat | IV | Lethality: No mortality. Clin Obs: Transient ↓ spontaneous activity, blepharoptosis (♂), ↓ bw gain and fc, and swelling at |
Species, Age/Grp/No., Sex/Grp | Route, Dosage, Duration | Results |
5 wk old 4 grp 10 ♀ & 10 ♂ /grp | 0, 20, 60, 180 4 wk | the injection site at 180 mg/kg. Clin Path: ↓ total protein, albumin, A/G ratio, cholinesterase activity, urinary protein, and RBC. ↑ WBC, retic, and fibrinogen at 180 mg/kg. Crystalluria. Micro: ↓ weights of thymus, liver, heart, ovaries, and brain due to ↓ bw gain. ↑ cecal weight at 60 and 180 mg/kg. Arthropathy at 60 and 180 mg/kg. NOAEL = 20 mg/kg/day. TI = 2.8. |
Rat 6 wk old 4 grp 10 ♀ & 10♂ /grp | IV 0, 10, 30, 90 13 wk | Lethality: None. Clin Obs: Slight ↓ fc at 30 and 90 mg/kg (♂). Clin Path: Mild ↓ total protein, phospholipids, and cholesterol at 90 mg/kg (♂) due to ↓ fc. Mild ↑ A/G and albumin at 30 and 90 mg/kg (♂). Crystalluria at 30 and 90 (♂) and 90 mg/kg (♀). Micro: ↑ cecal weight, arthropathy (mild) at 90 mg/kg. NOAEL = 30 mg/kg/day. TI = 4.2 |
Dog 4-5 mo old 5 grp 3 ♂ /grp | IV 0, 2, 4, 15, 60 2 wk | Lethality: None. Clin Obs: Histamine-like effects at 15 and 60 mg/kg, ↓ bw gain and fc at 60 mg/kg. Clin Path: ↑ plasma fibrinogen and urine specific gravity; ↓ serum Fe. Micro: ↓ absolute liver weight at 60 mg/kg and ↓ absolute and relative testes weight at 4, 15, and 60 mg/kg; and thrombus formation in injected vessels at 60 mg/kg, arthropathy and delayed testicular maturation at ≥4 mg/kg. NOAEL = 2 mg/kg/day. TI= 0.28 |
Dog 18 mo old 3 grp 3 ♂/grp | IV 0, 10, 30 2 wk | Lethality: None. Clin Obs: Histamine-like effects and ↓ activity at 10 and 30 mg/kg. Signs subsided by 30 min post-administration except ↓ activity. Clin Path: NSF. Micro: NSF. NOAEL for arthropathy = 30 mg/kg/day. TI=4.2 |
Dog 7-8 mo old 4 grp 3 ♀ & 3 ♂/grp | Infusion 0, 3, 10, 30 4 wk | Lethality: None. Clin Obs: Histamine-like effects in a dosage-related manner. Clin Path: NSF. Micro: Arthropathy at ≥10 mg/kg/day. NOAEL = 3 mg/kg/day. TI=0.42 |
Monkey 2-4 yr old 4 grp | PO 0, 10, 30, 100 4 wk | Lethality: None. Clin Obs and Clin Path: Salivation and diarrhea at 100 mg/kg. Some animals occasionally had what appeared to be blood in the urine. Slight bw losses, unusually large adrenal glands in one monkey and low urinary pH in two monkeys at 100 |
Species, Age/Grp/No., Sex/Grp | Route, Dosage, Duration | Results |
| 3 ♀ & 3♂/grp | mg/kg/day. Micro: NSF. NOAEL = 30 mg/kg/day. TI= 4.2 | |
Monkey 2-4 yr old 4 grp 4 ♀ & 4 ♂/grp | PO 0, 10, 25, 62.5 26 wk | Lethality: None. Clin Obs: ↓ fc in one high-dosage male during the first half of the study. Clin Path and Micro: NSF. NOAEL = 62.5 mg/kg/day. TI = 8.75 |
Monkey 2-4 yr old 4 grp 3 ♀ & 3 ♂/grp | IV 0, 10, 25, 63 4 wk | Lethality: None. Clin Obs: Loose stools and slightly ↓ wc at 25 and 63 mg/kg and ptosis, occasional quietness, and ↓ fc ( ♀) at 63 mg/kg. Clin Path: NSF. Micro: NSF. NOAEL = 10 mg/kg/day. TI= 1.4 |
Dosage = mg/kg/day; Clin Obs = clinical observations; Clin Path = clinical pathology; Micro = macroscopic and microscopic findings; NOAEL = No Observable Adverse Effect Level; NSF = No Significant Findings;
TI= Therapeutic Index - relationship of toxic dose to the projected human dose (calculation based on maximum daily dose of 500 mg and body weight of 70 kg);
ALT = alanine aminotransferase; ALP = alkaline phosphatase; AST = aspartate aminotransferase;
A/G = albumin/globulin;
fc = food consumption; wc = water consumption; bw = body weight;
RBC = red blood cells; WBC = white blood cells; retic = reticulocyte; PMN = neutrophil; M:E = myeloid: erythroid;
K+ = potassium; Cl- = chloride; P = phosphorus; Fe = iron.
Carcinogenicity:
Levofloxacin exhibited no carcinogenic or tumourigenic potential after dietary administration of 10, 30 or 100 mg/kg/day for 2 years in a rat carcinogenicity study. The highest dose was 1.4 or 6.7 times the highest recommended human dose (750 mg) based on surface area or body weight, respectively. The mean levofloxacin plasma concentration in the 2-year rat bioassay (at 100 mg/kg/day) was 34% of the human steady-state concentration after 500 mg b.i.d. dosing. In a 2-stage multiple organ carcinogenesis model in rats, levofloxacin at a dosage level of approximately 668 mg/kg/day in diet for 16 weeks did not promote the development of preneoplastic or neoplastic lesions after pretreatment with a number of wide spectrum carcinogens.
Genotoxicity:
Levofloxacin was not mutagenic in the following assays: Ames bacterial mutation assays (S. typhimurium and E. coli), CHO/HGPRT forward mutation assay, mouse micronucleus test, mouse dominant lethal test, rat unscheduled DNA synthesis and the mouse sister chromatid exchange
(SCE) assays. It was positive in the in vitro chromosomal aberration (CHL cell line) and SCE assays (CHL/IU cell line).
Reproductive and Developmental Toxicology:
Table 56 - Segment I: Fertility and Reproductive Performance Studies
| Studya | Parental Toxicity | Embryo/Fetal Toxicity | Teratogenicity |
Oral gavage, rat 0, 10, 60, 360 mg/kg/day 24/sex/group | salivation (at 60 mg/kg mostly ♂ and at 360 mg/kg ♀ & ♂ ) and soft stool at 360 mg/kg; ↑ wc at 360 mg/kg for ♂ and ≥60 mg/kg for ♀ ; ↓ in placental weights at 360 mg/kg. No effect on mating performance. | No effect on intrauterine survival or fetal development. | None |
Intravenous, rat 0, 10, 30, 100 mg/kg/day 24/sex/group | swollen tail, soft feces, and urinary incontinence at 100 mg/kg in ♂ and ♀. In females, ↓ bw gain and fc (wk 1 only) at 100 mg/kg. In males, ↓ bw gain ≥30 and slight ↓ fc at all levels, enlarged cecum ≥30 mg/kg. No effect on reproductive performance. NOAEL = 10 mg/kg/day for ♂ rats, 30 mg/kg/day for ♀ rats. | No effect on intrauterine survival or development. Slight non-dose-related ↑ in resorptions. NOAEL = 100 mg/kg/day for in utero exposure for rat fetuses. | None |
wc = water consumption; bw = body weight; fc = food consumption
a In both studies, males (8 weeks old) were administered levofloxacin daily for 9 weeks prior to mating, throughout the mating period, and until necropsy. The females (11-12 weeks old) were treated daily for 2 weeks prior to mating, throughout the mating period, and for 7 days after copulation.
NOAEL = No Observable Adverse Effect Level.
Table 57 - Segment II: Teratogenicity
| Studya | Maternal Toxicity | Embryo/Fetal Toxicity | Teratogenicity |
Oral gavage, rat 0, 10, 90, 810 mg/kg/day 36 ♀ /group | salivation, piloerection, alopecia, and poor hair coat, soft stool, hyperuresis and/or watery eyes at 90 mg/kg and 810 mg/kg. ↓ bw gain at 810 mg/kg, ↓ fc ≥90 mg/kg, ↑ wc at 810 mg/kg, | No effect on survival and weaning rate, sexual maturation, development or reproductive performance of F1 generation. ↓ mean bw for pups at birth (♂ and ♀) on Days 63-77 postpartum (♀) at 810 mg/kg. ↑ fetal mortality, and ↓ fetal weight at 810 mg/kg. Maternal | None |
| Studya | Maternal Toxicity | Embryo/Fetal Toxicity | Teratogenicity |
enlarged cecum ≥90 mg/kg. NOAEL = 10 mg/kg. | toxicity at 810 mg/kg led to delayed ossification of sternum, metatarsal, proximal phalange, and caudal vertebrae. | ||
Intravenous, rat 0, 10, 40, 160 mg/kg/day 36 ♀ /group | ↓ fc at 40 mg/kg (Days 7-12 only) and at 160 mg/kg. Swollen tails (inj. site) and ↑ wc at 160 mg/kg. NOAEL= 10 mg/kg for dams. | Maternal toxicity led to delayed ossification of sternum and caudal vertebrae. No effect other than delayed ossification was observed. NOAEL = 40 mg/kg for fetuses, ≥160 mg/kg for pups. | None |
Oral gavage, rabbit 0, 5, 16, 50 mg/kg/day 16 ♀ /group | ↓ fc and bw gain at 50 mg/kg, transient ↓ fc at 16 mg/kg, ↑ number placental remnants at 50 mg/kg, 4 dams aborted. NOAEL = 5 mg/kg/day for dams. | No adverse effects. NOAEL = 50 mg/kg/day for fetuses. | None |
Intravenous, rabbit 0, 6.25, 12.5, 25 mg/kg/day 20 ♀ /group | transient ↓ bw and fc at 25 mg/kg early in gestation (Days 6-9). NOAEL = 12.5 mg/kg/day for maternal toxicity. | No adverse effects. NOAEL = 25 mg/kg/day for developmental toxicity. | None |
bw = body weight; wc = water consumption; fc = food consumption; inj. = injection
a In both rat studies, the rats were dosed from Day 7 to Day 17 of gestation.
NOAEL = No Observable Adverse Effect Level
Table 58 - Segment III: Perinatal and Postnatal
| Study | Maternal Toxicity | Embryo/Fetal Toxicity | Parturition/ Neonatal Growth and Survival |
Oral gavage, rat 0, 10, 60, 360 mg/kg/day 24 ♀ /group Dosed daily from Day 17 of gestation to Day 21 of lactation | salivation, diarrhea and soft feces at 360 mg/kg, salivation in some at 60 mg/kg, ↓ fc at 60 mg/kg during gestation and lactation (Days 14-18), ↓ fc during gestation and ↑ fc during lactation at 360 mg/kg, ↓wc on 2 days during gestation and ↑ wc during lactation at 360 mg/kg. NOAEL = 10 mg/kg for dams. | No effects on either F1 or F2 generation. NOAEL = 360 mg/kg for pups. | No effects |
NOAEL = No Observable Adverse Effect Level
Special Toxicology:
Arthropathic Potential
Levofloxacin and other quinolones have been shown to cause arthropathy in immature animals of most species tested (see 7 WARNINGS AND PRECAUTIONS). In juvenile rats, 7 days of oral administration of 300 mg/kg/day levofloxacin results in blister and cavity formation in articular cartilage. In juvenile dogs (4 months old), 7 days of oral administration of 10 mg/kg/day levofloxacin produces blister formation, cavitation, and increased synovial fluid of diarthroidal joints. In young immature dogs (13 months old), blister formation and cavitation of the arthritic joint were observed in 1/3 dogs following oral administration of 40 mg/kg/day levofloxacin for 7 days.
In long-term multidose studies, arthropathy in rats was observed after oral administration of 800 mg/kg/day for 4 weeks, after intravenous administration at 60 mg/kg/day for 4 weeks and 90 mg/kg/day for 13 weeks. Arthropathic lesions were observed in 4-month-old dogs following 4 mg/kg/day intravenous administration for 2 weeks and in 7-8-month-old dogs following 10 mg/kg/day intravenous administration for 4 weeks. No arthropathy was observed following 2-week intravenous dosing at dosages up to 30 mg/kg/day in young adult dogs (18 months old).
Three-month old beagle dogs dosed orally with up to 40 mg/kg/day levofloxacin for 8 or 9 consecutive days, with an 18-week recovery period, exhibited musculoskeletal clinical signs by the final dose at dose levels ≥2.5 mg/kg (approximately 0.2-fold the pediatric dose based upon AUC comparisons). Synovitis and articular cartilage lesions were observed at the 10 and 40 mg/kg dose levels (equivalent to and 3-fold greater than the potential therapeutic dose, respectively). All musculoskeletal clinical signs were resolved by week 5 of recovery; synovitis was resolved by the end of the 18-week recovery period; whereas, articular cartilage erosions and chondropathy persisted.
Phototoxicity
When tested in a mouse ear swelling bioassay, levofloxacin exhibited phototoxicity similar in magnitude to ofloxacin but less phototoxicity than some of the other quinolones tested. A single oral administration of 800 mg/kg levofloxacin followed by UVA exposure has been shown to result in ear erythema and swelling.
Crystalluria
When tested in rats with 20, 60, 120 or 180 mg/kg of levofloxacin, crystalluria has been observed in some intravenous rat studies; urinary crystals are not formed in the bladder, being present only after micturition and are not associated with nephrotoxicity.
Cardiac Effects
Levofloxacin exhibits a weak interaction with the human HERG channel. The IC50 for levofloxacin in inhibiting human HERG K+ channel is 915 mcM. At therapeutic doses of 250, 500, and 750 mg levofloxacin, the peak unbound plasma concentrations ranged from 6 mcM for a single oral levofloxacin dose of 250 mg to 12 mcM and 15 mcM for 500 and 750 mg levofloxacin doses, respectively.
Studies in rabbit Purkinje fibers and studies in guinea pig right ventricular myocardium revealed no detectable effect on action potential duration with levofloxacin at concentrations up to 100 mcM.
The potential for levofloxacin to induce torsades de pointes was examined in a canine model of chronic high-degree atrioventricular block. Oral administration of levofloxacin at 6 and 60 mg/kg induced no ventricular arrhythmias. Monophasic action potential duration (MAP90) was not significantly affected by levofloxacin 0.3 and 3 mg/kg IV.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. TEVA-LEVOFLOXACIN® (levofloxacin tablets and Injection), Submission control 226600, Product Monograph, Teva Canada Limited. (JUL 17, 2019).
- 2. LEVAQUIN®, Product Monograph, Janssen Inc., Canada. (AUG 13, 2014).
- 3. LEVOFLOXACIN IN 5% DEXTROSE INJECTION (levofloxacin, 5 mg / mL Sterile solution for intravenous infusion), submission control 279109, Product Monograph, Pfizer Canada ULC. (FEB 13, 2024).
- 4. APO-LEVOFLOXACIN® (levofloxacin tablets, 250 mg, 500 mg, 750 mg), submission control 289861, Product Monograph, Apotex Inc. (FEB 14, 2025)