


Product Monograph - Mylan-Moxifloxacin
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Oral | tablet, 400 mg moxifloxacin (as moxifloxacin hydrochloride) | Croscarmellose sodium, copovidone, iron oxide red, isopropyl alcohol, lecithin (soya), magnesium stearate, microcrystalline cellulose, polyvinyl alcohol, talc, titanium dioxide, and xanthan gum. |
INDICATIONS AND CLINICAL USE
MYLAN-MOXIFLOXACIN (moxifloxacin hydrochloride) is indicated for the treatment of adults (≥18 years of age) with the following bacterial infections caused by susceptible strains of the designated microorganisms for which treatment is appropriate.
Oral Administration
Respiratory Tract Infections
Acute bacterial sinusitis caused by:
Haemophilus influenzae
Moraxella catarrhalis
Streptococcus pneumoniae
Acute bacterial exacerbation of chronic bronchitis caused by:
Haemophilus influenzae
Haemophilus parainfluenzae
Klebsiella pneumoniae
Moraxella catarrhalis
Staphylococcus aureus
Streptococcus pneumoniae
Community acquired pneumonia of mild to moderate severity caused by:
Chlamydia pneumoniae
Haemophilus influenzae
Moraxella catarrhalis
Mycoplasma pneumoniae
Streptococcus pneumoniae (including Multi-drug resistant strains)
Multi-Drug Resistant Streptococcus pneumoniae (MDRSP) are strains resistant to two or more of the following antibiotics: penicillin (MIC ≥2 µg/mL), 2nd generation cephalosporins (e.g., cefuroxime axetil), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole.
Appropriate culture and susceptibility tests should be performed before treatment with MYLAN-MOXIFLOXACIN in order to isolate and identify organisms causing the infection and to determine their susceptibility to moxifloxacin. Therapy with MYLAN-MOXIFLOXACIN may be initiated while awaiting the results of these tests; once results become available, appropriate therapy should be continued. Culture and susceptibility testing performed periodically during therapy will provide information not only on the therapeutic effect of the antimicrobial agent, but also on the possible emergence of bacterial resistance. The frequency of acquired resistance may vary geographically and with time for certain species. Local area information on resistance patterns is desirable, particularly when treating severe infections.
Pediatrics (<18 years of age)
MYLAN-MOXIFLOXACIN is not recommended for children under the age of 18 years (see WARNINGS AND PRECAUTIONS, TOXICOLOGY).
Geriatrics (≥65 years of age)
Clinical trial data demonstrate that there is no significant difference in the safety of moxifloxacin hydrochloride in patients aged 65 or older. Dosage adjustments based on age are not necessary (see ACTION AND CLINICAL PHARMACOLOGY).
CONTRAINDICATIONS
- Patients who are hypersensitive to moxifloxacin hydrochloride or other quinolone antibacterial agents (see WARNINGS AND PRECAUTIONS, ADVERSE REACTIONS).
- Patients who are hypersensitive to any ingredient in the formulation or component of the container (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
|
Carcinogenesis and Mutagenesis
From the results of animal studies, there is no evidence to suggest that moxifloxacin hydrochloride is carcinogenic or mutagenic (see TOXICOLOGY).
Cardiovascular
QT Interval Prolongation
Moxifloxacin hydrochloride has been shown to prolong the QT interval of the electrocardiogram in some patients. The drug should be avoided in patients with known prolongation of the QT interval, patients with hypokalemia and patients receiving Class IA (e.g., quinidine, procainamide) or Class III (e.g., amiodarone, sotalol) antiarrhythmic agents, due to the lack of clinical experience with the drug in these patient populations and the potential risk.
Sotalol, a Class III antiarrhythmic, has been shown to increase the QTc interval when combined with high doses of intravenous moxifloxacin hydrochloride in dogs. (see DETAILED PHARMACOLOGY).
Pharmacokinetic studies between moxifloxacin hydrochloride and other drugs that prolong the QT interval such as cisapride, erythromycin, antipsychotics and tricyclic antidepressants have not been performed. An additive effect of moxifloxacin hydrochloride and these drugs cannot be excluded, therefore MYLAN-MOXIFLOXACIN should be used with caution when given concurrently with these drugs.
The effect of moxifloxacin hydrochloride on patients with congenital prolongation of the QT interval has not been studied, but it is expected that these individuals may be more susceptible to drug-induced QT prolongation. MYLAN-MOXIFLOXACIN should be used with caution in patients with ongoing proarrhythmic conditions such as clinically significant bradycardia, acute myocardial ischemia, clinically relevant heart failure with reduced left-ventricular ejection fraction or previous history of symptomatic arrhythmias.
The magnitude of QT prolongation may increase with the infusion rate and with increasing plasma concentrations of the drug. Therefore, the recommended duration of infusion (60 minutes) should not be shortened and the recommended dose should not be exceeded (see DOSAGE AND ADMINISTRATION).
QT prolongation may lead to an increased risk for ventricular arrhythmias including Torsades de Pointes. It has been observed with drugs that prolong the QT interval (including moxifloxacin) that females may be at greater risk compared to males for developing Torsades de Pointes because women tend to have a longer baseline QT interval compared to men. Elderly patients may also be more susceptible to drug-associated effects on the QT interval.
In 787 patients with paired valid ECGs in Phase III clinical trials, the mean ± SD prolongation of the QTc interval after oral dosing with moxifloxacin hydrochloride 400 mg was 6±26 msec. (see ACTION AND CLINICAL PHARMACOLOGY, DETAILED PHARMACOLOGY). In patients with paired valid ECGs in Phase III clinical trials, the mean ±SD prolongation of the QTc interval within 0-4 hours after a one hour infusion of intravenous moxifloxacin hydrochloride 400 mg was 9±24 msec (Day 1; n=176) and 3±29 msec (Day 3, n=290) (see ACTION AND CLINICAL PHARMACOLOGY, DETAILED PHARMACOLOGY).
No cardiovascular morbidity or mortality attributable to QTc prolongation occurred with moxifloxacin hydrochloride treatment in clinical trials involving over 4000 patients. However, certain predisposing conditions may increase the risk for ventricular arrhythmias.
MYLAN-MOXIFLOXACIN should be used with caution in patients with liver cirrhosis as pre-existing QT prolongation in these patients cannot be excluded.
To assure safe and effective use of MYLAN-MOXIFLOXACIN, patients should be advised of the following information and instructions when appropriate:
- that moxifloxacin hydrochloride may produce changes in the electrocardiogram (QTc interval prolongation)
- that moxifloxacin hydrochloride should be avoided if they are currently receiving Class IA (e.g., quinidine, procainamide) or Class III (e.g., amiodarone, sotalol) antiarrhythmic agents
- that moxifloxacin hydrochloride may add to the QTc prolonging effects of other drugs such as cisapride, erythromycin, antipsychotics and tricyclic antidepressants
- to inform their physician of any personal or family history of QTc prolongation or proarrhythmic conditions such as recent hypokalemia, significant bradycardia, acute myocardial ischemia, clinically relevant heart failure with reduced left-ventricular ejection fraction or previous history of symptomatic arrhythmias
- to contact their physician if they experience palpitations or fainting spells while taking
- moxifloxacin hydrochloride
- to inform their physician of any other medications being taken concurrently with
- moxifloxacin hydrochloride, including over-the-counter medications.
Atrial Fibrillation
Twenty-five patients from the moxifloxacin hydrochloride clinical datapool (7284 patients) had an episode of atrial fibrillation. In 4 of these patients the relationship between the event and moxifloxacin hydrochloride therapy was assessed as possible, though in each case it could also be explained by pre-existing cardiac disease. There was one episode of atrial fibrillation observed in patients who received a comparator agent (3994 patients).
Chondrotoxic Effects
As with other members of the quinolone class, moxifloxacin has caused arthropathy and/or chondrodysplasia in immature dogs. The significance of these findings to humans is unknown (see ACTION AND CLINICAL PHARMACOLOGY, DETAILED PHARMACOLOGY).
Endocrine and Metabolism
Disturbances of Blood Glucose
Disturbances of blood glucose, including symptomatic hyper-and hypoglycemia, have been reported with the use of quinolones, including Moxifloxacin hydrochloride. In patients treated with Moxifloxacin hydrochloride, some of these cases were serious. Blood glucose disturbances were usually in diabetic patients receiving concomitant treatment with an oral hypoglycemic agent (eg, glyburide/glibenclamide and sulfonylurea) and/or with insulin. In these patients, careful monitoring of blood glucose is recommended. If a hypoglycemic reaction occurs in a patient being treated with Moxifloxacin hydrochloride, discontinue Moxifloxacin hydrochloride immediately and initiate appropriate therapy. Serious hypoglycemia and hyperglycemia have also occurred in patients without a history of diabetes (see ADVERSERE ACTIONS and DRUG INTERACTIONS, Drug-Drug Interactions).
Gastrointestinal
Clostridium difficile-Associated Disease
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including moxifloxacin hydrochloride (see ADVERSE REACTIONS). CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against C. difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against C. difficile. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases.
Hepatic/Biliary
In 400 mg single dose studies in 6 patients with mild (Child Pugh Class A) and 10 patients with moderate (Child Pugh Class B) hepatic insufficiency, oral moxifloxacin mean systemic exposure (AUC) was 78% and 102%, respectively, of that in 18 healthy controls and mean peak concentration (Cmax) was 79% and 84% of that in controls. The clinical significance of increased exposure to the sulfate and glucuronide conjugates has not been studied. No dosage adjustment is recommended for patients with mild or moderate hepatic insufficiency (Child Pugh Classes A and B). Due to limited clinical data, the use of moxifloxacin is not recommended for patients with severe hepatic insufficiency (Child Pugh Class C) (see ACTION AND CLINICAL PHARMACOLOGY, DOSAGE AND ADMINISTRATION).
Cases of fulminant hepatitis potentially leading to liver failure (including fatal cases) have been reported with moxifloxacin. Patients should be advised to discontinue treatment and contact their doctor immediately if they develop signs and symptoms of hepatitis (including abdominal pain, anorexia, jaundice, dark urine, pale stools, pruritus).
Hypersensitivity
Serious hypersensitivity and/or anaphylactic reactions have been reported in patients receiving quinolone therapy, including moxifloxacin hydrochloride.
There have been occasional reports of fatal hypersensitivity and/or anaphylactic reactions observed with quinolone therapy. These reactions may occur following the first dose. Some reactions have been accompanied by cardiovascular collapse, hypotension/shock, seizure, loss of consciousness, tingling, angioedema (including tongue, laryngeal, throat or facial edema/swelling), airway obstruction (including bronchospasm, shortness of breath and acute respiratory distress), dyspnea, urticaria, itching and other serious skin reactions.
MYLAN-MOXIFLOXACIN should be discontinued at the first appearance of a skin rash or any other sign of hypersensitivity. Serious acute hypersensitivity reactions may require treatment with epinephrine and other resuscitative measures, including oxygen, intravenous fluids, antihistamines, corticosteroids, pressor amines and airway management, as clinically indicated.
Serious and sometimes fatal events, some due to hypersensitivity and some due to uncertain etiology, have been reported in patients receiving therapy with all antibiotics, including moxifloxacin. These events may be severe and generally occur following the administration of multiple doses. Clinical manifestations may include one or more of the following: fever, rash or severe dermatologic reactions (e.g., toxic epidermal necrolysis, Stevens-Johnson Syndrome), vasculitis, arthralgia, myalgia, serum sickness, allergic pneumonitis, interstitial nephritis, acute renal insufficiency or failure, hepatitis, jaundice, acute hepatic necrosis or failure, anemia including hemolytic and aplastic, thrombocytopenia including thrombotic thrombocytopenic purpura, leukopenia, agranulocytosis, pancytopenia, and/or other hematologic abnormalities (see CONTRAINDICATIONS, ADVERSE REACTIONS).
Musculoskeletal
Myasthenia gravis
Fluoroquinolones, including moxifloxacin hydrochloride, have neuromuscular blocking activity and may exacerbate muscle weakness in persons with myasthenia gravis. Postmarketing serious adverse events, including deaths and requirement for ventilatory support, have been associated with fluoroquinolone use in persons with myasthenia gravis. Avoid MYLAN-MOXIFLOXACIN in patients with a known history of myasthenia gravis (see ADVERSE REACTIONS).
Tendinitis
Rupture of the shoulder, hand, and Achilles tendons that required surgical repair or resulted in prolonged disability have been reported in patients receiving quinolones, including moxifloxacin hydrochloride (see ADVERSE REACTIONS). MYLAN-MOXIFLOXACIN should be discontinued if the patient experiences pain, inflammation or rupture of a tendon. Patients should rest and refrain from exercise until the diagnosis of tendinitis or tendon rupture has been confidently excluded. The risk of developing fluoroquinolone-associated tendinitis and tendon rupture is further increased in older patients usually over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart, or lung transplants. Factors, in addition to age and corticosteroid use, that may independently increase the risk of tendon rupture include strenuous physical activity, renal failure, and previous tendon disorders such as rheumatoid arthritis. Tendinitis and tendon rupture have also occurred in patients taking fluoroquinolones who do not have the above risk factors. Tendon rupture can occur during or after completion of therapy; cases occurring up to several months after completion of therapy have been reported. MYLAN-MOXIFLOXACIN should be discontinued if the patient experiences pain, swelling, inflammation, or rupture of a tendon. Patients should be advised to rest at the first sign of tendinitis or tendon rupture, and to contact their healthcare provider regarding changing to a non-quinolone antimicrobial drug.
MYLAN-MOXIFLOXACIN should not be used in patients with a history of tendon disease/disorder related to previous quinolone treatment.
Neurologic
Convulsions, increased intracranial pressure (including pseudotumor cerebri) and toxic psychoses have been reported in patients receiving quinolones. Quinolones, including moxifloxacin hydrochloride, may also cause central nervous system stimulation which may lead to abnormal dreams, agitation, anxiety, confusion, depression, dizziness, emotional lability, hallucinations, insomnia, lightheadedness, nervousness, nightmares, paranoia, restlessness and tremors. These reactions may occur after the first dose. If these reactions occur in patients receiving MYLAN-MOXIFLOXACIN, the drug should be discontinued and appropriate measures instituted.
As with all quinolones, MYLAN-MOXIFLOXACIN should be used with caution in patients with known or suspected CNS disorders, such as severe cerebral arteriosclerosis, epilepsy, and other factors that predispose to seizures or lower the seizure threshold (see ADVERSE REACTIONS).
Peripheral Neuropathy
Rare cases of sensory or sensorimotor axonal polyneuropathy affecting small and/or large axons resulting in paresthesias, hypoesthesias, dysesthesias and weakness have been reported in patients receiving quinolones including moxifloxacin hydrochloride.
Patients under treatment with MYLAN-MOXIFLOXACIN should be advised to inform their doctor prior to continuing treatment if symptoms of neuropathy such as pain, burning, tingling, numbness, or weakness develop (see ADVERSE REACTIONS - Post-Market Adverse Drug Reactions).
Psychiatric
Psychiatric reactions may occur even after the first administration of fluoroquinolones, including moxifloxacin hydrochloride. In very rare cases, depression or psychotic reactions have progressed to suicidal thoughts and self- injurious behavior such as suicide attempts (see ADVERSE REACTIONS). In the event that the patient develops these reactions, MYLAN-MOXIFLOXACIN should be discontinued and appropriate measures instituted. Caution is recommended if MYLAN-MOXIFLOXACIN is to be used in psychotic patients or in patients with a history of psychiatric disease.
Renal
The pharmacokinetic parameters of moxifloxacin hydrochloride are not significantly altered by mild, moderate, or severe renal impairment. No dosage adjustment is necessary in patients with renal impairment, including patients on chronic dialysis, i.e., hemodialysis or continuous ambulatory peritoneal dialysis. In clinical studies, as renal function decreased, mean exposure (AUC) to the glucuronide conjugate (M2) increased by a factor of 2.8 (Clcr<30 mL/min), 7.5 (hemodialysis) and 13.3 (continuous ambulatory peritoneal dialysis).
The sulfate and glucuronide conjugates are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal impairment has not been studied (see ACTION AND CLINICAL PHARMACOLOGY, DOSAGE AND ADMINISTRATION).
Sensitivity/Resistance
MYLAN-MOXIFLOXACIN is not recommended for the treatment of methicillin-resistant Staphylococcus aureus (MRSA) infections. In case of a suspected or confirmed infection due to MRSA, treatment with an appropriate antibacterial agent should be started (see ACTION AND CLINICAL PHARMACOLOGY - Pharmacodynamics).
Because of the widespread and rising prevalence of fluoroquinolone-resistant Neisseria gonorrhoeae infections, monotherapy with MYLAN-MOXIFLOXACIN should be avoided in patients with pelvic inflammatory disease, unless fluoroquinolone-resistant N. gonorrhoeae can be excluded. If fluoroquinolone-resistant N. gonorrhoeae cannot be excluded, the addition of an appropriate antibiotic which is regularly active against N. gonorrhoeae (eg, a cephalosporin) to empirical MYLAN-MOXIFLOXACIN therapy should be considered.
Skin
Phototoxicity
Phototoxicity has been reported in patients receiving certain quinolones. In keeping with good medical practice, the patient should be advised to avoid excessive sunlight or artificial ultraviolet light (e.g., sunlamps) during treatment with MYLAN-MOXIFLOXACIN and for one day following completion of treatment. If a sunburn-like reaction or skin eruptions occur, the physician should be contacted. A study in human volunteers concluded that moxifloxacin hydrochloride has no measurable phototoxic potential.
Photocarcinogenicity
Some members of the fluoroquinolone class of drugs (of which MYLAN-MOXIFLOXACIN is a member) have been shown to produce skin tumours in the Hairless (Skh-1) mouse when concomitantly exposed to daily irradiations of UV-A light for 16 weeks. In this model, in the absence of exposure to UV-A light, mice treated with the fluoroquinolone did not develop skin tumours. The clinical significance of these findings, particularly for short term use, is not known. Photocarcinogenicity studies with moxifloxacin hydrochloride have not yet been carried out. During treatment with MYLAN-MOXIFLOXACIN and for one day following completion of treatment, exposure to excessive sunlight or artificial ultraviolet light (e.g., sunlamps) should be avoided.
Vision Disorders
If vision disorder occurs in association with the use of Moxifloxacin hydrochloride, consult an eye specialist immediately.
Special Populations
The safety and efficacy of moxifloxacin hydrochloride in children, pregnant women and nursing women have not been established. MYLAN-MOXIFLOXACIN is not recommended for children under the age of 18 years.
Pregnant Women
Adequate and well-controlled studies have not been performed in pregnant women. The extent of exposure in pregnancy is very limited. MYLAN-MOXIFLOXACIN should not be used in pregnant women unless the potential benefits outweigh the potential risk to the fetus (see TOXICOLOGY).
Moxifloxacin was not teratogenic when administered to pregnant rats during organogenesis at oral doses as high as 500 mg/kg/day or 0.24 times the maximum recommended human dose based on systemic exposure (AUC), but decreased fetal body weights and slightly delayed fetal skeletal development (indicative of fetotoxicity) were observed. Intravenous administration of 80 mg/kg to pregnant rats resulted in maternal toxicity and a marginal effect on fetal and placental weights and the appearance of the placenta. There was no evidence of teratogenicity at intravenous doses as high as 80 mg/kg/day. Intravenous administration of 20 mg/kg/day (approximately equal to the maximum recommended human oral dose based upon systemic exposure) to pregnant rabbits resulted in maternal toxicity, decreased fetal body weights and delayed fetal skeletal ossification. There was no evidence of teratogenicity when pregnant Cynomolgus monkeys were given oral doses as high as 100 mg/kg/day (12.5 times the maximum recommended human dose based upon systemic exposure). An increased incidence of smaller fetuses was observed at 100 mg/kg/day. In an oral pre- and postnatal development study conducted in rats, effects observed at 500 mg/kg/day included slight increases in duration of pregnancy and prenatal loss, reduced pup birth weight and decreased neonatal survival. Treatment-related maternal mortality occurred during gestation at 500 mg/kg/day in this study.
Nursing Women
The safety and efficacy of moxifloxacin hydrochloride in nursing women have not been established.
Moxifloxacin hydrochloride is excreted in the breast milk of rats and may also be excreted in human milk. Because of the potential for unknown effects from moxifloxacin in infants being nursed by mothers taking moxifloxacin, a decision should be made to either discontinue nursing or discontinue the administration of moxifloxacin, taking into account the importance of moxifloxacin therapy to the mother and the possible risk to the infant (see TOXICOLOGY).
Pediatrics (<18 years of age)
MYLAN-MOXIFLOXACIN is not recommended for children under the age of 18 years. Quinolones, including moxifloxacin hydrochloride, cause arthropathy and osteochondrosis in juvenile animals of several species. The significance of these findings to humans is unknown (see TOXICOLOGY).
Geriatrics (≥65 years of age)
In controlled multiple-dose clinical trials with oral moxifloxacin, 23% of patients who received moxifloxacin were ≥65 years of age and 9% were ≥75 years of age. The clinical trial data demonstrate that there is no significant difference in the safety of moxifloxacin in patients aged 65 or older compared to younger adults (see ACTION AND CLINICAL PHARMACOLOGY, DOSAGE AND ADMINISTRATION).
In the pool of 248 moxifloxacin-treated and 243 comparator-treated elderly (≥ 65 years) patients enrolled in the two pivotal intravenous trials of community acquired pneumonia, the following ECG abnormalities were reported in moxifloxacin vs. comparator patients: QT prolongation (4 vs. 1), ventricular tachycardia (3 vs. 0), tachycardia (2 vs. 1), atrial fibrillation (1 vs. 0), supraventricular tachycardia (1 vs. 0), ventricular extrasystoles (1 vs. 0), and arrhythmia (0 vs. 1). A majority of these patients completed a full-course of therapy.
Monitoring and Laboratory Tests
Moxifloxacin in vitro activity may interfere with the Mycobacterium spp. culture test by suppression of mycobacterial growth, causing false negative results in specimens from patients currently taking moxifloxacin hydrochloride.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Over 8600 courses of moxifloxacin hydrochloride tablets and injection treatments have been evaluated for drug safety during clinical development. Of these, 8050 patients received the 400 mg dose. Most adverse events reported in trials were described as transient in nature, mild to moderate intensity, and required no additional treatment. Moxifloxacin hydrochloride was discontinued due to adverse drug reactions (those judged by the investigators to be possibly or probably related to moxifloxacin hydrochloride) in 3.1% of patients (206 out of 6734) treated with moxifloxacin hydrochloride tablets and 7.0% of patients (131 out of 1872) treated with intravenous moxifloxacin hydrochloride.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The overall rate of adverse drug reactions during clinical trials was 26% (1734/6734) with moxifloxacin hydrochloride tablets and 26% (483/1872) with moxifloxacin hydrochloride injection. The common adverse drug reactions seen in clinical trials (those judged by the investigators to be possibly or probably related to moxifloxacin) are summarized in Table 2.
| Table 2 – Common Clinical Trial Adverse Drug Reactions (≥1% to <10%) | ||
|---|---|---|
| moxifloxacin hydrochloride n=8606 | ||
| Body as a Whole | ||
| abdominal pain | 2% | |
| headache | 2% | |
| injection site reaction | 1% | |
| Cardiovascular | ||
in patients with concomitant hypokalemia: QT interval prolongation | 1% | |
| Digestive | ||
| nausea | 7% | |
| diarrhea | 5% | |
| dyspepsia | 1% | |
| vomiting | 2% | |
| Metabolic | ||
| liver function test abnormal | 1% | |
| Nervous | ||
| dizziness | 3% | |
Uncommon Clinical Trial Adverse Drug Reactions
Uncommon adverse drug reactions seen in clinical trials (those judged by the investigators to be possibly or probably related to moxifloxacin) are listed in Table 3 and Table 4.
Table 3 – Uncommon Clinical Trial Adverse Drug Reactions (≥0.1% to <1%)
moxifloxacin hydrochloride n=8606 | |
|---|---|
| Body as a Whole | asthenia, chest pain, fever, infection, malaise, moniliasis, pain |
| Cardiovascular | hypertension, palpitation, phlebitis, QT interval prolongation, tachycardia, vasodilatation |
| Digestive | decreased appetite and food intake, constipation, dry mouth, flatulence, gastrointestinal disorder, GGTP increased, glossitis, nausea and vomiting, oral moniliasis, stomatitis |
| Hemic and Lymphatic | anemia, eosinophilia, leukopenia, prothrombin/INR decreased, thrombocythemia |
| Metabolic and Nutritional | amylase increased, lactic dehydrogenase increased (in connection with abnormal liver function tests) |
| Musculo-Skeletal | arthralgia, myalgia |
| Nervous | anxiety, insomnia, nervousness, paresthesia, somnolence, tremor, vertigo |
| Respiratory | dyspnea, pharyngitis, pneumonia, rhinitis |
| Skin and Appendages | pruritus, rash, sweating, urticaria |
| Special Senses | taste perversion |
| Urogenital | kidney function abnormal, vaginal moniliasis, vaginitis |
| Table 4 – Rare Clinical Trial Adverse Drug Reactions (<0.1%) | ||
|---|---|---|
moxifloxacin hydrochloride n=8606 | ||
| Body as a Whole | abdomen enlarged, accidental overdose, aggravation reaction, allergic reaction, back pain, cachexia, cellulitis, chest pain substernal, chills, drug level increased, edema, face edema, hand pain, hernia, infection fungal, inflammation, injection site edema, injection site hypersensitivity, injection site inflammation, injection site pain, lab test abnormal, lack of drug effect, leg pain, multisystem organ failure, neoplasm, overdose, pelvic pain, peritonitis, photosensitivity reaction, reaction unevaluable, sepsis | |
| Cardiovascular | AV block first degree, angina pectoris, atrial fibrillation, cardiovascular disorder, cerebrovascular accident, congestive heart failure, deep thrombophlebitis, electrocardiogram abnormal, heart failure, hemorrhage, hypotension, migraine, myocardial infarct, peripheral edema, peripheral vascular disorder, postural hypotension, shock, supraventricular tachycardia, syncope, thrombophlebitis, vascular headache, ventricular tachycardia, ventricular extrasystoles | |
| Digestive | aphthous stomatitis, cheilitis, cholestatic jaundice, colitis, cholangitis, diarrhea (Clostridium difficile), dysphagia, eructation, esophagitis, gastritis, gastroenteritis, gastrointestinal hemorrhage, gastrointestinal moniliasis, gingivitis, hepatic failure, hyperchlorhydria, increased appetite, jaundice (predominantly cholestatic), liver damage, melena, mouth ulceration, pancreatitis, pseudomembraneous colitis, salivary gland | |
| Table 4 – Rare Clinical Trial Adverse Drug Reactions (<0.1%) |
|---|
moxifloxacin hydrochloride n=8606 | ||
|---|---|---|
| enlargement, thirst, tongue discoloration, tongue disorder, tongue edema | ||
| Endocrine | diabetes mellitus, female lactation | |
Hemic and Lymphatic | abnormal platelets, coagulation disorder, hypochromic anemia, lymphocytosis, lymphangitis, monocytosis, pancytopenia, prothrombin/INR increased, sedimentation rate increased, thrombocytopenia, thromboplastin decreased | |
| Hypersensitivity | allergic reaction, face edema, urticaria | |
Metabolic and Nutritional | bilirubinemia, dehydration, enzymatic abnormality, gamma globulins increased, gout, hypercholesteremia, hyperglycemia, hyperlipemia, hyperuricemia, hypoproteinemia, hypophosphatemia, lipase increased, NPN increased, weight gain | |
| Musculo-Skeletal | arthritis, arthrosis, leg cramps, myasthenia, tendon disorder | |
| Nervous | abnormal dreams, agitation, amnesia, aphasia, cerebral infarct, circumoral parasthesia, coma, confusion, convulsion, depersonalization, depression (in very rare cases potentially culminating in self-injurious behavior, such as suicidal ideation/thoughts or suicide attempts), emotional lability, euphoria, grand mal convulsion, hallucinations, hyperkinesia, hypertonia, hypesthesia, hypotonia, incoordination, parasthesia, personality disorder, sleep disorder, speech disorder, thinking abnormal, twitching, vestibular disorder | |
| Respiratory | apnea, asthma, atrophic rhinitis, cough increased, dyspnea, epistaxis, hemoptysis, hiccup, hyperventilation, lung disorder, pleural effusion, respiratory disorder, sinusitis, surgery | |
Skin and Appendages | acne, dry skin, eczema, fungal dermatitis, herpes simplex, maculopapular rash, psoriasis, purpuric rash, pustular rash, skin disorder, skin ulcer, vesiculobullous rash, Stevens-Johnson syndrome | |
| Special Senses | abnormal vision, amblyopia, blindness, deafness, diplopia, ear pain, eye disorder, hyperacusis, parosmia (including smell perversion, decreased smell and loss of smell), hearing impairment including partial permanent deafness, photophobia, taste loss, tinnitus | |
| Urogenital | acute kidney failure, albuminuria, balanitis, cystitis, dysuria, hematuria, hypomenorrhea, kidney function abnormal, kidney pain, leukorrhea, menstrual disorder, polyuria, pyuria, salpingitis, urinary frequency, urinary retention, urinary tract infection, urine abnormality, vulvovaginitis | |
Abnormal Hematologic and Clinical Chemistry Findings
Changes in laboratory parameters without regard to drug relationship that are not listed above as adverse drug reactions and which occurred in ≥2% of oral moxifloxacin-treated patients in controlled clinical trials (n=4301) are summarized in Table 5.
| Table 5 – Changes in Laboratory Parameters seen in Clinical Trials | ||
|---|---|---|
moxifloxacin hydrochloride n=4301 | ||
| increases in: | albumin, alkaline phosphatase, amylase, basophils, bicarbonate, calcium, chloride, cholesterol, creatinine, eosinophils, globulin, glucose, hematocrit, hemoglobin, LDH, lymphocytes, monocytes, neutrophils, PCO2, phosphorus, platelets, potassium, prothrombin time/INR , RBCs, serum transaminases, sodium, theophylline, total bilirubin, triglycerides, urea, uric acid, WBCs | |
| decreases in: | albumin, amylase, basophils, bicarbonate, calcium, chloride, creatinine, eosinophils, globulin, glucose, hematocrit, hemoglobin, LDH, lymphocytes, monocytes, neutrophils, phosphorus, platelets, PO2, potassium, prothrombin time/INR, RBCs, serum transaminases, sodium, theophylline, total bilirubin, urea, uric acid, WBCs | |
Post-Market Adverse Drug Reactions
The safety of moxifloxacin has been studied in two prospective post-marketing surveillance studies involving nearly 33,000 patients.
Adverse reactions with moxifloxacin based on post-marketing reports (from more than eight million patient treatments) are summarized in Table 6.
Table 6 – Adverse Reactions Identified in Post-Marketing Surveillance
| Cardiovascular | ventricular tachyarrythmias including Torsades de Pointes and cardiac arrest have been reported especially in patients with severe underlying proarrhythmic conditions in very rare cases (see WARNINGS AND PRECAUTIONS) |
| Endocrine and Metabolism | hypoglycemia |
| Hepatic | hepatitis, fulminant hepatitis |
| Hypersensitivity | anaphylactic reaction, shock (anaphylactic), angioedema (including laryngeal edema; potentially life-threatening) |
| Musculo-Skeletal | Exacerbation of symptoms of myasthenia gravis, tendon rupture |
| Nervous | psychotic reaction (potentially culminating in self-injurious behavior, such as suicidal ideation/thoughts or suicide attempts), peripheral neuropathy and polyneuropathy |
| Special Senses | transient loss of vision |
Additional serious adverse events reported with moxifloxacin regardless of drug relationship are listed in Table 7.
Table 7 – Serious Adverse Events Reported Regardless of Drug Relationship
| Cardiac | atrial arrhythmia, atrial flutter, bradycardia, myocardial infarct (death), tachyarrhythmia, ventricular fibrillation, ventricular tachycardia |
| Hepatic | cholestatic hepatitis, fulminant hepatitis potentially leading to life-threatening liver failure (including fatal cases), hepatic failure, hepatitis |
| Hypersensitivity | allergic vasculitis, anaphylactoid reaction, anaphylaxis, tongue edema |
| Renal | acute kidney failure |
| Skin and Appendages | Toxic Epidermal Necrolysis (potentially life threatening) |
DRUG INTERACTIONS
Overview
Moxifloxacin hydrochloride is metabolized via glucuronide and sulfate conjugation. The cytochrome P450 system is not involved in moxifloxacin metabolism, and is not affected by moxifloxacin. Moxifloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these enzymes. As with all other quinolones, iron and antacids significantly reduced bioavailability of moxifloxacin.
Drug-Drug Interactions
| Table 8 – Established or Potential Drug-drug Interactions | ||||||
|---|---|---|---|---|---|---|
| Proper Name | Ref | Effect | Clinical Comment | |||
Antacids, Sucralfate, Metal Cations, Multivitamins | CT/T | Quinolones form chelates with alkaline earth and transition metal cations. Administration of quinolones with antacids containing aluminum or magnesium, as well as sucralfate, metal cations such as iron, and multivitamins containing iron or zinc, and formulations containing divalent and trivalent cations such as didanosine chewable/buffered tablets or the pediatric powder for oral solution, may substantially interfere with the absorption of quinolones, resulting in systemic concentrations considerably lower than desired. | MYLAN-MOXIFLOXACIN should be taken at least 4 hours before or 8 hours after these agents (see DOSAGE AND ADMINISTRATION). | |||
| Ranitidine | CT | Concomitant administration with ranitidine does not change the absorption characteristics of moxifloxacin. Absorption parameters (Cmax, tmax, AUC) are comparable indicating absence of an influence of gastric pH on moxifloxacin uptake from the GI-tract. | No clinically relevant interactions. | |||
Nonsteroidal anti- inflammatory drugs (NSAIDs) | T | Although not observed with moxifloxacin in preclinical and clinical trials, some quinolones have been reported to have proconvulsant activity that is exacerbated with concomitant use of non-steroidal anti-inflammatory drugs (NSAIDs). | Concomitant administration of a nonsteroidal anti-inflammatory drug with a quinolone may increase the risks of CNS stimulation and convulsions. | |||
| Table 8 – Established or Potential Drug-drug Interactions |
|---|
| Proper Name | Ref | Effect | Clinical Comment |
|---|---|---|---|
Calcium supplements | CT | When moxifloxacin is given with high dose calcium supplements, only a slightly reduced rate of absorption is observed while the extent of absorption remains unaffected. | No clinically relevant interactions. |
| Warfarin | CT | Changes in INR: Cases of increased anticoagulant activity have been reported in patients receiving oral anticoagulants concurrently with antibiotics, including moxifloxacin. The infectious disease (and its accompanying inflammatory process), age and general status of the patient are risk factors. | Although an interaction between moxifloxacin and warfarin was not demonstrated in clinical trials, INR monitoring should be performed, and if necessary, the oral anticoagulant dosage should be adjusted as appropriate. |
Drugs metabolized by Cytochrome P450 enzymes (e.g., midazolam, cyclosporine, warfarin, theophylline) | CT/T | In vitro studies with cytochrome P450 isoenzymes (CYP) indicate that moxifloxacin does not inhibit CYP3A4, CYP2D6, CYP2C9, CYP2C19, or CYP1A2, suggesting that moxifloxacin is unlikely to alter the pharmacokinetics of drugs metabolized by these enzymes. | No clinically relevant interactions. |
Antidiabetic agents | CT/T | Disturbances of blood glucose, including symptomatic hyper- and hypoglycemia, have been reported with quinolones, including moxifloxacin, usually in diabetic patients receiving concomitant treatment with an oral hypoglycemic agent (e.g., glyburide/glibenclamide, etc) or with insulin. | In diabetic patients, careful monitoring of blood glucose is recommended. If a hypoglycemic reaction occurs in a patient receiving moxifloxacin, discontinue the drug immediately and an appropriate therapy should be instituted (see ADVERSE REACTIONS). |
Oral contraceptives | CT | No interaction has occurred following concomitant oral administration of moxifloxacin with oral contraceptives. | No clinically relevant interactions. |
| Itraconazole | CT | Exposure (AUC) to itraconazole is only marginally altered under concomitant moxifloxacin treatment. Pharmacokinetics of moxifloxacin are not significantly altered by itraconazole. | No clinically relevant interactions. |
| Digoxin | CT | The pharmacokinetics of digoxin are not significantly influenced by moxifloxacin and vice versa. After repeated dosing in healthy volunteers, moxifloxacin increased Cmax of digoxin by approximately 30% at steady state without affecting AUC or trough levels. | No clinically relevant interactions. |
| Morphine | CT | Parenteral administration of morphine does not reduce the oral availability of moxifloxacin and only slightly decreases Cmax (17%). | No clinically relevant interactions. |
| Atenolol | CT | The pharmacokinetics of atenolol are not significantly altered by moxifloxacin. Following single dose administration in healthy subjects, AUC was marginally increased (by approximately 4%) and peak concentrations were decreased by 10%. | No clinically relevant interactions. |
| Probenecid | CT | No significant effect on apparent total body clearance and renal clearance of moxifloxacin | No clinically relevant interactions. |
| Table 8 – Established or Potential Drug-drug Interactions |
|---|
| Proper Name | Ref | Effect | Clinical Comment | |
|---|---|---|---|---|
| was found in a clinical study investigating the impact of probenecid on renal excretion. | ||||
Legend: C=Case Study; CT=Clinical Trial; T=Theoretical
Drug-Food Interactions
MYLAN-MOXIFLOXACIN may be taken with or without food.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
There are no reported laboratory test interactions.
Drug-Lifestyle Interactions
Fluoroquinolones including moxifloxacin hydrochloride may result in an impairment of the patient's ability to drive or operate machinery due to central nervous system (CNS) reactions and vision disorders (see ADVERSE REACTIONS).
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
The recommended dose for MYLAN-MOXIFLOXACIN (moxifloxacin hydrochloride tablets) is 400 mg once daily for all indications. The duration of therapy and route of administration is dependent upon the type and severity of infection as described in Table 9.
Table 9 – Dosage and Administration Information for Approved Indications
| Infection a | Daily Dose | Route of Administration | Usual Duration |
| Acute Bacterial Sinusitis | 400 mg | PO | 7-10 days |
| Acute Bacterial Exacerbation of Chronic Bronchitis | 400 mg | PO | 5 days |
Community Acquired Pneumonia (Mild/Moderate) | 400 mg | PO | 10 days |
a due to the designated pathogens (see INDICATIONS AND CLINICAL USE).
Special Populations
Gender
Clinical trial data indicate that there are no significant differences in moxifloxacin pharmacokinetics between male and female subjects when differences in body weight are taken into consideration. Dosage adjustments based on gender are not necessary (see ACTION AND CLINICAL PHARMACOLOGY).
Pediatrics (<18 years of age)
MYLAN-MOXIFLOXACIN is not recommended for children under the age of 18 years (see WARNINGS AND PRECAUTIONS, TOXICOLOGY).
Geriatrics (≥65 years of age)
Clinical trial data demonstrate that there is no significant difference in the safety of moxifloxacin in patients aged 65 or older. Dosage adjustments based on age are not necessary (see ACTION AND CLINICAL PHARMACOLOGY, WARNINGS AND PRECAUTIONS).
Hepatic Impairment
Based on the pharmacokinetic data, no dosage adjustment is required for patients with mild or moderate hepatic insufficiency (Child Pugh Classes A and B). Due to limited clinical data, the use of moxifloxacin is not recommended in patients with severe hepatic insufficiency (Child Pugh Class C) (see ACTION AND CLINICAL PHARMACOLOGY, WARNINGS AND PRECAUTIONS).
Renal Impairment
Based on pharmacokinetic data, no dosage adjustment is necessary in renally impaired patients, including patients on chronic dialysis (i.e., hemodialysis or continuous ambulatory peritoneal dialysis). A study in 24 patients with renal impairment found no significant changes in the pharmacokinetic properties of oral moxifloxacin As renal function decreases, concentrations of the glucuronide conjugate (M2) increased by a factor of 2.8 (Clcr<30 mL/min), 7.5 (hemodialysis) and 13.3 (continuous ambulatory peritoneal dialysis) (see ACTION AND CLINICAL PHARMACOLOGY, WARNINGS AND PRECAUTIONS).
The clinical implication of increased exposure to the sulfate (M1) and the glucuronide (M2) conjugates of moxifloxacin in renally impaired patients, including those undergoing hemodialysis and continuous ambulatory peritoneal dialysis (HD and CAPD), has not been studied. Clinical efficacy of moxifloxacin treatment in dialysis patients (HD and CAPD) has not been studied.
Administration
MYLAN-MOXIFLOXACIN (moxifloxacin hydrochloride) is administered orally, independent of meals. The tablets are swallowed whole. Patients should be advised to drink fluids liberally and take moxifloxacin at least 4 hours before or 8 hours after antacids containing magnesium or aluminium, or multivitamins containing iron or zinc. Do not crush or chew the tablets. Swallow each tablet whole with a drink of water.
Missed Dose
If a dose is missed, another should be taken as soon as possible. Continue with the next dose 24 hours later. Two doses should not be taken in any 24-hour period.
Reconstitution
Not applicable.
OVERDOSAGE
In the event of acute overdosage of MYLAN-MOXIFLOXACIN (moxifloxacin hydrochloride), the stomach should be emptied. ECG monitoring is recommended due to the possible prolongation of the QT interval. The patient should be carefully observed and given supportive treatment. Adequate hydration must be maintained. Moxifloxacin and the glucuronide conjugate (M2) are removed from the body by hemodialysis (approximately 9% and 4%, respectively, 5 hour dialysis sessions) and by continuous ambulatory peritoneal dialysis (approximately 3% and 2%, respectively).
The administration of activated charcoal as soon as possible after oral overdose may prevent excessive increase of systemic moxifloxacin exposure.
Toxic signs after administration of a single high dose of moxifloxacin in animals included CNS and gastrointestinal effects (see WARNINGS AND PRECAUTIONS, TOXICOLOGY).
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Moxifloxacin hydrochloride is a synthetic fluoroquinolone with a broad spectrum of activity and a bactericidal mode of action. The bactericidal action results from the interference of moxifloxacin with bacterial topoisomerases II (DNA gyrase) and IV. Topoisomerases are essential enzymes which control DNA topology and assist in DNA replication, repair and transcription.
Killing curves demonstrated that moxifloxacin exhibits a concentration dependent bactericidal effect. Minimum bactericidal concentrations are in the range of minimum inhibitory concentrations.
Fluoroquinolones, including moxifloxacin, differ in chemical structure and mechanism of action from macrolides, beta-lactams, aminoglycosides, or tetracyclines; therefore, microorganisms resistant to these classes of drugs may be susceptible to moxifloxacin. Conversely, microorganisms resistant to fluoroquinolones may be susceptible to other classes of antimicrobial agents. Although cross-resistance has been observed between moxifloxacin and other fluoroquinolones against Gram negative bacteria, Gram positive bacteria resistant to other fluoroquinolones may be susceptible to moxifloxacin. Conversely, Gram positive bacteria that are resistant to moxifloxacin may be susceptible to other fluoroquinolones (see MICROBIOLOGY).
Pharmacodynamics
Resistance
Resistance mechanisms which inactivate penicillins, cephalosporins, aminoglycosides, macrolides and tetracyclines do not interfere with the antibacterial activity of moxifloxacin.
There is no cross-resistance between moxifloxacin and these agents. Plasmid-mediated resistance has not been observed to date.
It appears that the C8-methoxy moiety contributes to enhanced activity and lower selection of resistant mutants of Gram-positive bacteria compared to the C8-H moiety. The presence of the bulky bicycloamine substituent at the C-7 position prevents active efflux, a proposed mechanism of fluoroquinolone resistance.
In vitro resistance to moxifloxacin develops slowly via multiple-step mutations. Resistance to moxifloxacin occurs in vitro at a general frequency of between 1.8 x 10⁻⁹ to <1 x 10-11 in one strain of Staphylococcus aureus and one strain of Streptococcus pneumoniae.
Effect on the Intestinal Flora
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of clostridia.
Pharmacokinetics
Pharmacokinetics are linear in the range of 50 to 800 mg (single dose) and up to 600 mg (once daily oral dosing over 10 days).
The mean (±SD) Cmax and AUC values at steady-state with a 400 mg oral once daily dosage regimen are 4.5±0.53 g/L and 48±2.7 mg*h/L, respectively. Cmax is attained 1 to 3 hours after oral dosing. The mean (±SD) trough concentration is 0.95±0.10 mg/L. The mean (±SD) Cmax and AUC values at steady-state with a once daily dosage regimen of 400 mg intravenous moxifloxacin hydrochloride infused over 60 minutes in healthy young males are 4.2±0.8 g/L and 38±4.7 mg*h/L, respectively. Cmax is achieved at the end of a 60 minute infusion (see DOSAGE AND ADMINISTRATION).
Plasma concentrations increase proportionately with dose up to the highest dose tested (1200 mg single oral dose). Moxifloxacin hydrochloride is eliminated from plasma by first-order process. The mean (±SD) elimination half-life from plasma is 12±1.3 hours; steady-state is achieved after at least three days with a 400 mg once daily regimen. The time course of plasma concentrations of moxifloxacin hydrochloride following steady-state oral and intravenous administration is illustrated in Figure 1, and pharmacokinetic parameters of moxifloxacin hydrochloride are presented in Table 10.
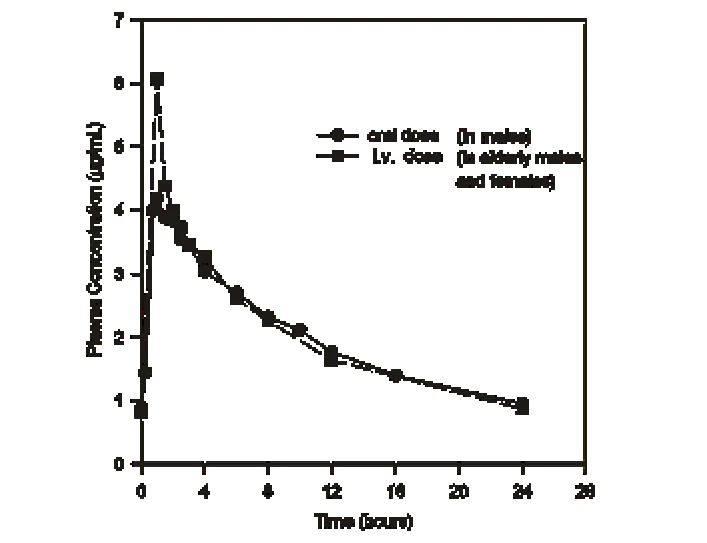
Figure 1 – Mean Steady-State Plasma Concentrations of Moxifloxacin Obtained with Once Daily Dosing of 400 mg Either Orally (n=10 males) or by IV Infusion (n=12 elderly males and females)
| Table 10 – Pharmacokinetic Parameters of Moxifloxacin After Oral and Intravenous Administration of 400 mg Single or Multiple Doses | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Population years (range) | Dose | Cmax (CV)a mg/L | AUC (CV)a mg*h/L | tmaxb (range) hr | t1/2 (CV)a hr | Comment | ||||
| Single Dose Studies – Oral Administration | ||||||||||
| 38 males (23-45) | 400 mg | 2.50 (27%) | 26.9 (17%) | 1.5 (0.5-2.6) | 13.1 (6%) | |||||
| 18 males (20-25) | 400 mg | 4.13 (27%) | 51.5 (10%) | 1.75 (0.5-2.5) | 13.9 (10%) | |||||
| Single Dose Studies – Intravenous Administration | ||||||||||
| 6 males (19-43) | 400 mg | 4.6 (33%) | 36.9 (19%) | N/A | 13.4 (17%) | 30 min. infusion | ||||
| 6 males (24-44) | 400 mg | 4.5 (25%) | 34.0 (22%) | 0.5 | 11.9 (10%) | 30 min. infusion | ||||
| 12 males (20-44) | 400 mg | 4.3 (21%) | 42.9 (11%) | 0.5 | 13.5 (20%) | 33 min. infusion | ||||
| 12 males (23-41) | 400 mg | 3.6 (28%) | 34.6 (19%) | 1.0 (1.0-1.25) | 15.4 (16%) | 60 min. infusion | ||||
9 males, 11 females (19-32) | 400 mg | 4.6 (18%) | 46.3 (18%) | 1.0 (0.5-1.3) | 12.4 (10%) | 60 min. infusion | ||||
| 13 males (24-36) | 400 mg | 3.6 (20%) | 39.8 (14%) | 1.0 (0.55-1.5) | 14.1 (17%) | 60 min. infusion | ||||
| 7 males (25-41) | 400 mg | 5.0 (22%) | 44.7 (19%) | 1.0 (0.5-1.0) | 8.0 (18%) | 60 min. infusion | ||||
| Multiple Dose Studies | ||||||||||
| 8 males (22-43) | 400 mg OD/PO x 5 days | 3.10 (29%) | 30.9 (11%) | 0.5 (0.5-4.0) | 9.6 (11%) | Day 1 | ||||
| 3.24 (17%) | 33.9 (20%) | 1.5 (0.5-3.0) | 15.1 (5%) | Day 5 | ||||||
10 males, 5 females (19-41) | 400 mg OD/PO x 10 days | 3.4 (22%) | 36.7 (13%) | 1.8 (0.75-3.0) | 9.3 (12%) | Day 1 | ||||
| 4.5 (12%) | 48.0 (6%) | 1.0 (0.75-2.5) | 12.7 (15%) | Day 10 | ||||||
| 9 males (20-40) | 400 mg OD | 4.1 (39%) | 40.9 (10%) | 1.0 (0.5-2.5) | 10.7 (16%) | Day 1 | ||||
| 4.1 (28%) | 46.7 (15%) | 1.8 (0.5-3.0) | 14.0 (15%) | Day 7 | ||||||
| 9 males (23-38) | 400 mg IV | 6.6 (30%) | 36.3 (11%) | 0.25 | 9.3 (17%) | Day 1; 15 min. infusion | ||||
11 males, 7 females (65-75) | 400 mg IV | 6.6 (27%) | 38.6 (21%) | 0.26 | 8.6 (15%) | Day 1; 15 min. infusion | ||||
| 5.9 (21%) | 47.4 (20%) | 1.0 | 10.1 (16%) | Day 5; 60 min. infusion | ||||||
12 males (25-42); | 400 mg | 3.6 (20%) | 34.8 (11%) | 1.0 | 9.9 (15%) | Day 1; 60 min. infusion | ||||
| Table 10 – Pharmacokinetic Parameters of Moxifloxacin After Oral and Intravenous Administration of 400 mg Single or Multiple Doses |
|---|
| Population years (range) | Dose | Cmax (CV)a mg/L | AUC (CV)a mg*h/L | tmaxb (range) hr | t1/2 (CV)a hr | Comment | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
8 active, 4 placebo | IV | 4.1 (20%) | 37.8 (11%) | 1.0 | 14.7 (16%) | Day 10; 60 min. infusion | ||||||
20 males, 12 females (23-74); varying degrees of renal function | 400 mg, PO | 4.4 (34%) | 43.4 (31%) | 0.8 (0.5-1.5) | 14.9 (38%) | C1cr>90 mL/min | ||||||
| 4.9 (30%) | 40.1 (22%) | 0.3 (0.3-2.5) | 15.2 (15%) | C1cr>60-90 mL/min | ||||||||
| 3.5 (41%) | 35.8 (30%) | 0.8 (0.5-2.5) | 16.2 (15%) | C1cr>30-60 mL/min | ||||||||
| 3.2 (14%) | 43.9 (29%) | 1.5 (0.5-2.5) | 14.5 (19%) | C1cr>30-60 mL/min | ||||||||
12 males, 4 females (22-62) 8 HD; 8 CAPD | 400 mg PO | 3.2 (23%)c | 40.4 (29%)c, d | 3.0 (1.0-4.0)c | 18.7 (25%)c | C1cr<20 mL/min and on HD | ||||||
| 4.0 (18%)c | 49.6 (25%)c, d | 2.5 (0.9-4.2)c | 11.4 (23%c | Clcr<20 mL/min and on CAPD | ||||||||
18 males (30-64); 10 healthy; 8 with hepatic disease | 400 mg PO | 3.0 (26%) | 32.8 (26%) | 0.8 (0.5-3.0) | 13.4 (18%) | healthy volunteers | ||||||
| 2.5 (34%) | 25.1 (26%) | 0.5 (0.5-2.5) | 11.7 (26%) | patients with hepatic disease, Child Pugh Class A and B | ||||||||
16 males (42-64); 8 healthy; 8 with hepatic disease | 400 mg PO | 3.3 (1.4)e | 30.8 (1.3)e | 1.5 (0.5-3.0) | 11.6 (1.1)e | healthy volunteers | ||||||
| 2.6 (1.2)e | 34.6 (1.2)e | 1.25 (0.5-2.5) | 13.6 (1.2)e | patients with hepatic disease, Child Pugh Class B | ||||||||
9 healthy males (23-45) | 400 mg IV/PO | 3.4 (20%) | 35.5 (14%) | 1.0 (0.75-1.5) | 11.6 (10%) | IV alone; 60 min. infusion | ||||||
| 3.0 (12%) | 28.5 (12%) | 1.0 (0.5-1.5) | 11.8 (6%) | IV plus 5 g charcoal 5 minutes prior to infusion; immediately after infusion and 2, 4, 8 hours post- infusion; 60 min. infusion | ||||||||
| 0.6 (73%) | 5.4 (65%) | 0.75 (0.5-1.25) | 10.8 (11%) | PO plus 10 g charcoal 15 minutes before, 2, 4, 8 hours after dosing | ||||||||
a values are geometric means (Coefficient of Variation)
b median (range)
c pharmacokinetic values are after 7-day once-daily dosing regimen d values are AUC(0-24)ss
e values are geometric means (SD)
Legend: OD=once daily; Cmax= maximum serum concentration; tmax=time to Cmax; AUC=area under concentration vs. time curve; t1/2=serum half-life, Clcr=creatinine clearance, HD=hemodialysis, CAPD=continuous ambulatory peritoneal dialysis
Absorption
Moxifloxacin hydrochloride, given as an oral tablet, is well absorbed from the gastrointestinal tract.
The absolute bioavailability of moxifloxacin hydrochloride is approximately 90 percent. Co-administration with a high fat meal (i.e., 500 calories from fat) does not affect absorption of moxifloxacin hydrochloride.
Consumption of one cup of yogurt with moxifloxacin does not significantly affect the extent or rate of systemic absorption (AUC).
Distribution
Moxifloxacin hydrochloride is approximately 50% bound to serum proteins, independent of drug concentration. As shown in Table 11, the volume of distribution of moxifloxacin hydrochloride ranges from 1.7 to 2.7 L/kg. Moxifloxacin hydrochloride is widely distributed throughout the body, with tissue concentrations often exceeding plasma concentrations. Moxifloxacin has been detected in the saliva, nasal and bronchial secretions, mucosa of the sinuses, and abdominal tissues and fluids following oral or intravenous administration of 400 mg. Moxifloxacin concentrations measured post dose in various tissues and fluids following a 400 mg oral or I.V. dose are summarized in the following table. The rates of elimination of moxifloxacin from tissues generally parallel the elimination from plasma.
In animal experiments, radiolabelled moxifloxacin hydrochloride was shown to cross the blood- brain barrier only to a small extent.
Table 11 – Moxifloxacin Concentrations (mean±SD) in Plasma and Tissues After Oral or Intravenous Dosing with 400 mga
| Tissue or Fluid | N | Tissue or Fluid Concentration (mg/L or μg/g) | Tissue or Fluid: Plasma Ratiob |
|---|---|---|---|
| Respiratory | |||
| Alveolar Macrophages | 5 | 61.8±27.3 | 21.2±10.0 |
| Bronchial Mucosa | 8 | 5.5±1.3 | 1.7±0.3 |
| Epithelial Lining Fluid | 5 | 24.4±14.7 | 8.7±6.1 |
| Sinusc | |||
| Maxillary Sinus Mucosa | 4 | 7.6±1.7 | 2.0±0.3 |
| Anterior Ethmoid Mucosa | 3 | 8.8±4.3 | 2.2±0.6 |
| Nasal Polyps | 4 | 9.8±4.5 | 2.6±0.6 |
| Intra-Abdominal | |||
| Abdominal tissued | 8 | 7.6±2.0 | 2.7±0.8 |
| Abdominal exudated | 10 | 3.5±1.25 | 1.6±0.7 |
| Abscess fluid | 6 | 2.3±1.5 | 0.8±0.4 |
| Skin, Musculoskeletal | |||
| Blister Fluid | 5 | 2.6±0.9 | 0.9±0.2 |
| Subcutaneous Tissue | 6 | 0.9±0.3e | 0.4±0.6 |
| Skeletal Muscle | 6 | 0.9±0.3e | 0.4±0.1 |
a moxifloxacin concentrations were measured 3 hours after a single oral or intravenous 400 mg dose, except as noted.
b tissue or fluid: plasma ratio was determined on an individual patient basis and then averaged for each site of infection
c sinus concentrations were measured after 5 days of dosing
d measured 2 hours after dosing
e reflects only non-protein bound concentrations of drug
Metabolism
Moxifloxacin is metabolized via glucuronide and sulfate conjugation. The cytochrome P450 system is not involved in moxifloxacin metabolism, and is not affected by moxifloxacin. The sulfate conjugate (M1) accounts for approximately 38% of the dose, and is eliminated primarily in the feces. Approximately 14% of an oral dose is converted to a glucuronide conjugate (M2), which is found exclusively in the urine. Peak plasma concentrations of M2 are approximately
40% of the parent drug, while plasma concentrations of M1 are generally less than 10% those of moxifloxacin. The sulfate (M1) and glucuronide (M2) conjugates are not microbiologically active.
Excretion
Approximately 45% of an oral dose of moxifloxacin is excreted as unchanged drug (~20% in urine and ~25% in feces). A total of 96%±4% of an oral dose is excreted as either unchanged drug or known metabolites. The mean (±SD) apparent total body clearance and renal clearance are 12±2.0 L/hr and 2.6±0.5 L/hr, respectively.
Special Populations and Conditions
Pediatrics (<18 years of age)
The pharmacokinetics of moxifloxacin in pediatric subjects have not been established (see TOXICOLOGY).
Geriatrics (≥65 years of age)
Following oral administration of 400 mg moxifloxacin for 10 days in 16 elderly (8 male; 8 female) and 16 young (8 male; 8 female) healthy volunteers, there were no age-related changes in moxifloxacin pharmacokinetics. In 16 healthy male volunteers (8 young; 8 elderly) given a single 200 mg oral dose of moxifloxacin, the extent of systemic exposure (AUC and Cmax) was not statistically different between young and elderly males and elimination half-life was unchanged. No dosage adjustment is necessary based on age.
In Phase I studies, the pharmacokinetics in elderly patients following infusion of 400 mg were similar to those observed in young patients (see DETAILED PHARMACOLOGY).
Gender
Following oral administration of 400 mg moxifloxacin daily for 10 days to 23 healthy males (19-75 years) and 24 healthy females (19-70 years), the mean AUC and Cmax were 8% and 16% higher, respectively, in females compared to males. There are no significant differences in moxifloxacin pharmacokinetics between male and female subjects when differences in body weight are taken into consideration.
A 400 mg single dose study was conducted in 18 young males and females. The comparison of moxifloxacin pharmacokinetics in this study (9 young females and 9 young males) showed no differences in AUC or Cmax due to gender. Dosage adjustments based on gender are not necessary.
Race
Steady state moxifloxacin pharmacokinetics in male Japanese subjects were similar to those determined in Caucasians, with a mean Cmax of 4.1 mg/L, an AUC24 of 47 mg*h/mL, and an elimination half-life of 14 hours following 400 mg daily PO.
Hepatic Insufficiency
In 400 mg single oral dose studies in 6 patients with mild, (Child Pugh Class A) and 10 patients with moderate (Child Pugh Class B) hepatic insufficiency, moxifloxacin mean systemic exposure (AUC) was 78% and 102%, respectively, of that in 18 healthy controls. The mean peak concentration (Cmax) was 79% and 84%, respectively, of control values.
The mean AUC of the sulfate conjugate of moxifloxacin (M1) increased by 3.9-fold (ranging up to 5.9-fold) and 5.7-fold (ranging up to 8.0-fold) in the mild and moderate groups, respectively. The mean Cmax of M1 increased by approximately 3-fold in both groups (ranging up to 4.7- and
3.9-fold), respectively. The mean AUC of the glucuronide conjugate of moxifloxacin (M2)
increased by 1.5-fold (ranging up to 2.5-fold) in both groups. The mean Cmax of M2 increased by
1.6- and 1.3-fold (ranging up to 2.7- and 2.1-fold), respectively. The clinical significance of increased exposure to the sulfate and glucuronide conjugates has not been studied. No dosage adjustment is recommended for mild or moderate hepatic insufficiency (Child Pugh Classes A and B). Due to limited clinical data, the use of moxifloxacin is not recommended with severe hepatic insufficiency (Child Pugh Class C) (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION).
Renal Insufficiency
The pharmacokinetic parameters of moxifloxacin are not significantly altered by mild, moderate, or severe renal impairment. No dosage adjustment is necessary in patients with renal impairment, including those patients on hemodialysis (HD) or continuous ambulatory peritoneal dialysis (CAPD).
In a single oral dose study of 24 patients with varying degrees of renal function from normal to severely impaired, the mean peak concentrations (Cmax) of moxifloxacin were reduced by 22% and 21% in the patients with moderate (Clcr≥30 and ≤60 mL/min) and severe (Clcr<30 mL/min) renal impairment, respectively. The mean systemic exposure (AUC) in these patients was increased by 13%. In the moderate and severe renally impaired patients, the mean AUC for the sulfate conjugate (M1) increased by 1.7-fold (ranging up to 2.8-fold) and mean AUC and Cmax for the glucuronide conjugate (M2) increased by 2.8-fold (ranging up to 4.8-fold) and 1.4-fold (ranging up to 2.5-fold), respectively. The sulfate and glucuronide conjugates are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal impairment has not been studied.
The pharmacokinetics of single- and multiple-dose moxifloxacin were studied in patients with Clcr<20 mL/min on either hemodialysis or continuous ambulatory peritoneal dialysis (8 HD, 8 CAPD). Pharmacokinetic comparisons are to historical pharmacokinetic values from healthy volunteers (Clcr>90 mL/min; administered a single 400 mg oral dose of moxifloxacin). Following a single 400 mg oral dose, the AUC of moxifloxacin in these HD and CAPD patients did not vary significantly from the AUC generally found in healthy volunteers. Cmax values of moxifloxacin were reduced by about 45% and 33% in HD and CAPD patients, respectively, compared to healthy subjects. The exposure (AUC) to the sulfate conjugate (M1) increased by 1.4- to 1.5-fold in these patients. The mean AUC of the glucuronide conjugate (M2) increased by a factor of 7.3 to 13.2, whereas the mean Cmax values of the glucuronide conjugate (M2) increased by a factor of 2.5 to 3, compared to healthy subjects. The sulfate and the glucuronide conjugates of moxifloxacin are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal disease including those undergoing HD and CAPD has not been studied.
Oral administration of 400 mg moxifloxacin once daily for 7 days to patients on HD or CAPD produced mean systemic exposure (AUCss) to moxifloxacin similar to that generally seen in healthy volunteers. Steady-state Cmax values were about 28% lower in HD patients but were comparable between CAPD patients and healthy volunteers. Moxifloxacin and the glucuronide conjugate (M2) were removed from the body by HD (approximately 9% and 4%, respectively) and by CAPD (approximately 3% and 2%, respectively). Systemic exposure (AUC) to M2 was equal to or greater than moxifloxacin exposure in HD and CAPD subjects following single dosing and at steady state (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION).
QT Prolongation
One pharmacokinetic study in 9 male and 9 female healthy volunteers showed that at the expected time of peak plasma concentrations and at a heart rate of 75 beats/minute, a 400 mg oral dose of moxifloxacin was associated with a mean QT prolongation (uncorrected for heart-rate) of 14±13 msec (3.8%±3.5%) compared to baseline. Exercise data indicated the absence of a reverse-rate dependence.
In clinical pharmacology studies (n=112 subjects), the aggregate mean prolongation of the QTc interval at the expected time of peak plasma concentrations after a single oral dose of 400 mg moxifloxacin was 7±23 msec (1.8%±5.6%). One patient had an increase in QTc greater than 60 msec.
In clinical pharmacology studies (n=29) with 400 mg intravenous moxifloxacin, the aggregate mean prolongation of the QTc interval at the end of a one hour infusion was 20.6±23 msec (5.5%±5.9%). Two patients had an increase in QTc greater than 60 msec (see WARNINGS AND PRECAUTIONS).
STORAGE AND STABILITY
Store between 15°C and 30°C. Avoid freezing.
SPECIAL HANDLING INSTRUCTIONS
Not applicable.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Availability
Mylan-Moxifloxacin 400 mg tablets are supplied in HDPE bottles of 100’s.
Composition
Mylan-Moxifloxacin 400 mg Tablets
Mylan-Moxifloxacin 400 mg tablets are pink, film-coated, capsule shaped, biconvex, beveled edge tablets debossed with M on one side of the tablet and MOI on the other side.
Each tablet contains 400 mg of moxifloxacin as moxifloxacin hydrochloride and the following non-medicinal ingredients: croscarmellose sodium, copovidone, isopropyl alcohol, magnesium stearate, and microcrystalline cellulose. The coating contains: iron oxide red, lecithin (soya), polyvinyl alcohol, talc, titanium dioxide, and xanthan gum.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | moxifloxacin hydrochloride |
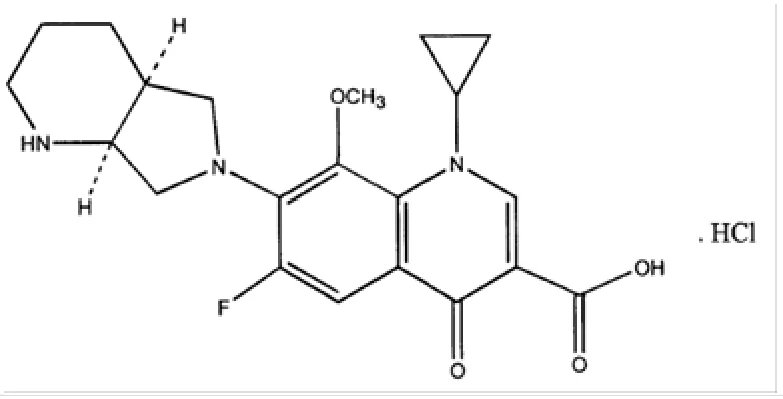
| Chemical name: | 1-cyclopropyl-7-[(S,S)-2,8-diaza-bicyclo[4.3.0]non-8-yl]- 6-fluoro-8-methoxy-1,4-dihydro-4-oxo-3- quinolinecarboxylic acid hydrochloride |
| Molecular formula and molecular mass: | C21H24FN3O4●HCl 437.93 g/mol C21H24FN3O4 (base) 401.43 g/mol |
| Structural formula: | |
| Physicochemical properties: | Physical Description Pale yellow to yellow colored powder pKa Value(s) 6.19 & 9.28 pH Value(s) 3.9 to 4.6 Melting Range 237.7˚ to 246.2˚ UV MaximA 294.48 nm |
Specific Optical Rotation -125° to -138° Hygroscopicity Moxifloxacin Hydrochloride is hygroscopic in nature. Partition Coefficient -1.78 Chirality Asymmetric Carbons: Two Chiral centers are present |
CLINICAL TRIALS
Comparative Bioavailability Studies
A double blind, randomized, single oral dose, two-treatment, two-period, two-sequence, two way crossover bioequivalence study comparing 1 x Mylan-Moxifloxacin (moxifloxacin hydrochloride) 400 mg tablet (Mylan Pharmaceuticals ULC) and 1 x Avelox® 400 mg (moxifloxacin hydrochloride) tablet (Bayer Inc.) was performed in healthy Asian male adult subjects (n=20) under fasting conditions.
A summary of the results is presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Moxifloxacin (1x400mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
AUCT (ng•hr/mL) | 28369.72 29246.48 (27.6) | 28795.83 29812.41 (28.9) | 98.5 | 95.93-101.18 |
AUCI (ng•hr/mL) | 30038.38 30883.421 (26.1) | 30536.66 31480.07 (27.2) | 98.4 | 96.11-100.68 |
Cmax (ng/mL) | 2068.07 2154.97 (31.7) | 2101.78 2161.53 (25.9) | 98.4 | 88.81-109.01 |
Tmax§ (h) | 1.84 (0.50-4.00) | 2.33 (1.00-4.00) | ||
T½€ (h) | 12.6 (14.3) | 12.0 (15.3) | ||
* Mylan- Moxifloxacin 400 mg tablets (Mylan Pharmaceuticals ULC).
† PrAVELOX® 400 mg tablets (Bayer Inc.) were purchased in Canada.
§ Expressed as the median (range) only.
€ Expressed as the arithmetic mean (CV %) only
Acute Bacterial Sinusitis
Trial Design
Table 12 – Design of Acute Bacterial Sinusitis Pivotal Trials
a demographic data refers to patients valid for efficacy
b all patients underwent antral puncture in this study
c Overall Clinical Response for Studies 0125 and 0126 includes failures occurring at end of therapy which are carried forward and included in the clinical evaluations at the follow-up (Day 27-31 post-treatment) timepoint
Legend: OD=once daily; BID=twice daily
Study No. / Country | Study Design | Primary Efficacy Parameter | Treatment Regimen | # of Pts. | Gendera | Mean Age ± SD (Years)a | |||||||
0116 Europe and Israel | Randomized, Double-blind, Active Controlled | Clinical Response at Day 3 post-treatment | Moxifloxacin 400 mg OD x 7 days | 211 | F: 114 (54%) M: 97 (46%) | 39.6±14.5 | |||||||
Cefuroxime Axetil 250 mg BID x 10 days | 225 | F: 126 (56%) M: 99 (44%) | 39.9±13.9 | ||||||||||
0125b USA | Open-label, Uncontrolled | Overall Clinical Response at Day 27-31 post- treatmentc | Moxifloxacin 400 mg OD x 7 days | 336 | F: 208 (62%) M: 128(38%) | 41.0±13.4 | |||||||
0126 Canada, USA | Randomized, Double-blind, Active Controlled | Overall Clinical Response at Day 27-31 post- treatmentc | Moxifloxacin 400 mg OD x 7 days | 191 | F: 126 (66%) M: 65 (34%) | 42.5±13.8 | |||||||
Cefuroxime Axetil 250 mg BID x 10 days | 193 | F: 134 (69%) M: 59 (31%) | 42.4±14.8 | ||||||||||
0161 Europe and Israel (1) | Randomized, Double-blind, Active Controlled | Clinical Response at Day 4-7 post- treatment | Moxifloxacin 400 mg OD x 10 days | 217 | F: 110 (51%) M: 107 (49%) | 38.6±14.7 | |||||||
Cefuroxime Axetil 250 mg BID x 10 days | 222 | F: 124 (56%) M: 98 (44%) | 39.3±14.5 | ||||||||||
100107 USA (2) | Randomized, Double-blind, Active Controlled | Clinical Response at Day 7-14 post- treatment | Moxifloxacin 400 mg OD x 10 days | 223 | F: 139 (62%) M: 84 (38%) | 40.1±13.9 | |||||||
Cefuroxime Axetil 250 mg BID x 10 days | 234 | F: 140 (60%) M: 94 (40%) | 39.0±12.7 | ||||||||||
Efficacy – Clinical Response
| Table 13 – Clinical Response Rates – Clinically Evaluable Patients in Pivotal Acute Bacterial Sinusitis Trials | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Study Number | Moxifloxacin 400 mg OD x 7 days n/N (%) | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/N (%) | 95% Confidence Intervals | |||||||||
| 0116 | 204/211 (97%) | N/A | 204/225 (91%) | 1.5%, 10.6% | |||||||||
| 0125 | 270/336 (80%) | N/A | N/A | 76%, 84%a | |||||||||
| 0126 | 154/191 (81%) | N/A | 176/193 (91%) | -17.1%, -3.8% | |||||||||
| 0161 | N/A | 203/217 (94%) | 210/222 (95%) | -5.5%, 3.4% | |||||||||
| 100107 | N/A | 200/223 (90%) | 209/234 (89%) | -5.1%, 6.2% | |||||||||
a the 95% confidence interval for Study 0125 was constructed using a normal approximation to the binomial distribution, with a continuity correction, in contrast to the confidence intervals for the other studies which were constructed using Mantel-Haenszel weights
Efficacy – Microbiological Outcome
Table 14 – Bacteriological Response Rates – Clinically and Microbiologically Evaluable Patients in Pivotal Acute Bacterial Sinusitis Trials
Study Number | Moxifloxacin 400 mg OD x 7 days n/N (%)a | Moxifloxacin 400 mg OD x 10 days n/N (%)a | Comparator n/N (%)a | 95% Confidence Intervals |
| 0116 | 103/109 (95%) | N/A | 96/115 (84%) | 3.6%, 19.7% |
| 0125 | 72/74 (97%)b | N/A | N/A | N/Ac |
| 0161 | N/A | 84/86 (98%) | 68/72 (94%) | -3.2%, 8.7% |
a culture specimens obtained by needle aspirate, endoscopic cannulation and swab
b Bacteriological Response for Study 0125 was determined at end of therapy
c statistical analysis was not performed for the Bacteriological Response for Study 0125
Table 15 – Pathogen Eradication Rates – Clinically and Microbiologically Evaluable Patients in Acute Bacterial Sinusitis Trials
| Study Number | Moxifloxacin 400 mg OD x 7 days n/N (%) | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/n (%) |
|---|---|---|---|
| Streptococcus pneumoniae | |||
| 0116 | 38/39 (97%) | N/A | 45/48 (94%) |
| 0125 | 29/30 (97%) | N/A | N/A |
| 0161 | N/A | 36/38 (95%) | 32/32 (100%) |
| Combined | 67/69 (97%) | 36/38 (95%) | 77/80 (96%) |
| Haemophilus influenzae | |||
| 0116 | 28/29 (97%) | N/A | 30/35 (86%) |
| 0125 | 24/30 (80%) | N/A | N/A |
| 0161 | N/A | 17/17 (100%) | 15/16 (94%) |
| Combined | 52/59 (88%) | 17/17 (100%) | 45/51 (88%) |
| Moraxella catarrhalis | |||
| 0116 | 14/14 (100%) | N/A | 8/9 (89%) |
| 0125 | 15/18 (83%) | N/A | N/A |
| 0161 | N/A | 10/10 (100%) | 5/5(100%) |
| Combined | 29/32 (91%) | 10/10 (100%) | 13/14 (93%) |
Acute Bacterial Exacerbations of Chronic Bronchitis
Trial Design
Table 16 – Design of Acute Exacerbations of Chronic Bronchitis Pivotal Trials
Study No. / Country | Study Design | Primary Efficacy Parameter | Treatment Regimen | # of Pts. | Gendera | Mean Age ± SD (Years)a | ||
0124 Europeb (3) | Randomized, Double-blind, Active Controlled | Clinical Response at Day 7 post-treatment | Moxifloxacin 400 mg OD x 5 days | 322 | F: 131 (41%) M: 191 (59%) | 60.0±14.0 | ||
Clarithromycin 500 mg BID x 7 days | 327 | F: 136 (42%) M: 191 (58%) | 60.2±13.5 | |||||
0127 Canada, USA (4) | Randomized, Double-blind, Active Controlled | Overall Clinical Response at Day 7-17 post- treatmentc | Moxifloxacin 400 mg OD x 5 days | 250 | F: 115 (46%) M: 135 (56%) | 56.8±15.2 | ||
Moxifloxacin 400 mg OD x 10 days | 256 | F: 116 (45%) M: 140 (55%) | 56.1±15.6 | |||||
Clarithromycin 500 mg BID x 10 days | 251 | F: 124 (49%) M: 127 (51%) | 55.4±15.9 | |||||
a demographic data refers to patients valid for efficacy
b Europe: Austria, France, Germany, Greece, Spain, Switzerland, United Kingdom
c Overall Clinical Response for Study 0127 includes failures occurring at end of therapy which are carried forward and included in the clinical evaluations at the follow-up (Day 7-17 post-treatment) timepoint
Legend: OD=once daily; BID=twice daily
Efficacy – Clinical Response
Table 17 –Clinical Response Rates – Clinically Evaluable Patients in Pivotal AECB Trials
| Study Number | Moxifloxacin 400 mg OD x 5 days n/N (%) | Comparator a n/N (%) | 95% Confidence Intervals |
| 0124 | 287/322 (89%) | 289/327 (88%) | -3.9%, 5.8% |
| 0127 | 222/250 (89%) | 224/251 (89%) | -6.1%, 4.2% |
a 10-day regimen for 0127, 7-day regimen for 0124
Efficacy – Microbiological Outcome
Table 18 – Bacteriological Response Rates – Clinically and Microbiologically Evaluable Patients in Pivotal AECB Trials
| Study Number | Moxifloxacin 400 mg OD x 5 days n/N (%) | Comparator a n/N (%) | 95% Confidence Intervals |
| 0124 | 89/115 (77%) | 71/114 (62%) | 3.6%, 26.9% |
| 0127 | 127/143 (89%) | 110/129 (85%) | -3.7%, 10.5% |
a 10-day regimen for 0127, 7-day regimen for 0124
Table 19 – Pathogen Eradication Rates – Clinically and Microbiologically Evaluable Patients in Pivotal AECB Trials
| Study Number | Moxifloxacin 400 mg OD x 5 days n/N (%) | Comparatora n/N (%) |
|---|---|---|
| Haemophilus influenzae | ||
| 0124 | 40/44 (91%) | 23/43 (53%) |
| 0127 | 33/37 (89%) | 31/41 (76%) |
| Combined | 73/81 (90%) | 54/84 (64%) |
| Haemophilus parainfluenzae | ||
| 0124 | 5/9 (56%) | 4/4 (100%) |
| 0127 | 16/16 (100%) | 14/14 (100%) |
| Combined | 21/25 (84%) | 18/18 (100%) |
| Streptococcus pneumoniae | ||
| 0124 | 32/38 (84%) | 35/36 (97%) |
| 0127 | 16/16 (100%) | 21/23 (91%) |
| Combined | 48/54 (89%) | 56/59 (95%) |
| Staphylococcus aureus | ||
| 0124 | 1/1 (100%) | 9/11 (82%) |
| 0127 | 15/16 (94%) | 7/8 (88%) |
| Combined | 16/17 (94%) | 16/19 (84%) |
| Moraxella catarrhalis | ||
| Study Number | Moxifloxacin 400 mg OD x 5 days n/N (%) | Comparatora n/N (%) |
|---|---|---|
| 0124 | 14/16 (87%) | 23/24 (96%) |
| 0127 | 29/34 (85%) | 24/24 (100%) |
| Combined | 43/50 (86%) | 47/48 (98%) |
| Klebsiella pneumoniae | ||
| 0124 | N/A | N/A |
| 0127 | 17/20 (85%) | 10/11 (91%) |
| Combined | 17/20 (85%) | 10/11 (91%) |
a 10-day regimen for Study 0127, 7-day regimen for Study 0124
Community Acquired Pneumonia – Oral Administration
Trial Design
| Table 20 – Design of Community Acquired Pneumonia Pivotal Trials for Oral Administration | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Study No. / Country | Study Design | Primary Efficacy Parameter | Treatment Regimen | # of Pts. | Gendera | Mean Age ± SD (Years)a | |||||||
0119 Europeb, ROWc (5) | Randomized, Double-blind, Active Controlled | Clinical Response at Day 3-5 post-treatment | Moxifloxacin 200 mg OD x 10 days | 180 | F: 65 (36%) M: 115 (64%) | 47.8±20.5 | |||||||
Moxifloxacin 400 mg OD x 10 days | 177 | F: 71 (40%) M: 106 (60%) | 48.1±20.8 | ||||||||||
Clarithromycin 500 mg BID x 10 days | 174 | F: 63 (36%) M: 111 (64%) | 46.3±18.7 | ||||||||||
0129 USA (6) | Open-label, Uncontrolled | Overall Clinical Response at Day 14-35 post- treatmentd | Moxifloxacin 400 mg OD x 10 days | 196 | F: 83 (42%) M: 113 (58%) | 48.9±18.5 | |||||||
0130 USA (7) | Randomized, Double-blind, Active Controlled | Overall Clinical Response at Day 14-35 post- treatmenta | Moxifloxacin 400 mg OD x 10 days | 194 | F: 104 (54%) M: 90 (46%) | 48.4±17.3 | |||||||
Clarithromycin 500 mg BID x 10 days | 188 | F: 95 (51%) M: 93 (49%) | 48.5±17.5 | ||||||||||
a demographic data refers to patients valid for efficacy
b Europe: Austria, Germany, Greece, Italy, Norway, Sweden, Switzerland, United Kingdom
c ROW (Rest of the World): Australia, Hong-Kong, Indonesia, Israel, New Zealand, Philippines, South Africa, Taiwan d Overall Clinical Response for Studies 0129 and 0130 includes failures occurring at end of therapy which are carried forward and included in the clinical evaluations at the follow-up (Day 14-35 post-treatment) timepoint
Legend: OD=once daily; BID=twice daily
Efficacy – Clinical Response
Table 21 – Clinical Response Rates – Clinically Evaluable Patients in Pivotal CAP Trials
Study Number | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/N (%) | 95% Confidence Intervals |
| 0119 | 167/177 (94%) | 164/174 (94%) | -6.7%, 4.1% |
| 0129 | 182/196 (93%) | N/A | 88.1%, 95.9%a |
| 0130 | 184/194 (95%) | 178/188 (95%) | -3.7%, 5.3% |
a the 95% confidence interval for Study 0129 was constructed using a normal approximation to the binomial distribution, with a continuity correction, in contrast to the confidence intervals for the other studies which were constructed using Mantel-Haenszel weights
Efficacy – Microbiological Outcome
Table 22 – Bacteriological Response Rates – Clinically and Microbiologically Evaluable Patients in Pivotal CAP Trials
Study Number | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/N (%) | 95% Confidence Intervals |
| 0119 | 37/47 (79%) | 29/41 (71%) | -10.2%, 26.2% |
| 0129 | 106/116 (91%) | N/A | 84.3%, 95.6%a |
| 0130b | 107/110 (97%) | 105/109 (96%) | -4.6%, 6.5% |
a the 95% confidence interval for Study 0129 was constructed using a normal approximation to the binomial distribution, with a continuity correction, in contrast to the confidence intervals for the other studies which were constructed using Mantel-Haenszel weights
b Bacteriological Response rates for Study 0130 were determined at end of therapy, in contrast to Clinical Response (end of therapy plus follow-up)
Table 23 – Pathogen Eradication Rates – Clinically and Microbiologically Evaluable Patients in Pivotal CAP Trials
| Study Number | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/N (%) |
|---|---|---|
| Streptococcus pneumoniae | ||
| 0119a | 14/16 (88%) | 12/13 (92%) |
| 0129 | 13/14 (93%) | N/A |
| 0130 | 17/17 (100%) | 18/19 (95%) |
| Combined | 44/47 (74%) | 30/32 (94%) |
| Haemophilus influenzae | ||
| 0119a | 6/8 (75%) | 5/10 (50%) |
| 0129 | 11/13 (85%) | N/A |
| 0130 | 22/23 (96%) | 14/16 (88%) |
| Combined | 39/44 (87%) | 19/26 (73%) |
| Mycoplasma pneumoniae | ||
| 0119a | 22/24 (92%) | 30/32 (94%) |
| 0129 | 27/29 (93%) | N/A |
| 0130 | 23/24 (96%) | 20/20 (100%) |
| Combined | 72/77 (94%) | 50/52 (96%) |
| Chlamydia pneumoniae | ||
| Study Number | Moxifloxacin 400 mg OD x 10 days n/N (%) | Comparator n/N (%) |
|---|---|---|
| 0119a | 19/19 (100%) | 21/23 (91%) |
| 0129 | 56/63 (89%) | N/A |
| 0130 | 42/45 (93%) | 43/44 (98%) |
| Combined | 117/127 (92%) | 64/67 (96%) |
| Moraxella catarrhalis | ||
| 0119a | 1/2 (50%) | 3/3 (100%) |
| 0129 | 4/4 (100%) | N/A |
| 0130 | 6/7 (86%) | 2/2 (100%) |
| Combined | 11/13 (85%) | 5/5 (100%) |
a patients who only had positive serology for a CAP pathogen in Study 0119 were not included in the clinically and microbiologically evaluable population
| S. pneumoniae with MDRSP | Clinical Cure Rate | Bacteriological Eradication Rate |
| Resistant to 2 antimicrobials | 12/13 (92.3%) | 12/13 (92.3%) |
| Resistant to 3 antimicrobials | 10/11 (90.9%) | 10/11 (90.9%) |
| Resistant to 4 antimicrobials | 6/6 (100%) | 6/6 (100%) |
| Resistant to 5 antimicrobials | 7/7 (100%) | 7/7 (100%) |
| Screening Susceptibility | Clinical Cure Rate | Bacteriological Eradication Rate |
| Penicillin-resistant | 21/21 (100%) | 21/21 (100%) |
| Second Generation Cephalosporin-resistant | 25/26 (96%) | 25/26 (96%) |
| Macrolide-resistanta | 22/23 (96%) | 22/23 (96%) |
| Trimethoprim/sulfamethoxazole-resistant | 28/30 (93%) | 28/30 (93%) |
| Tetracycline-resistant | 17/18 (94%) | 17/18 (94%) |
Community Acquired Pneumonia Caused by Multi-drug Resistant Streptococcus pneumoniae (MDRSP)
Multi-Drug Resistant Streptococcus pneumoniae (MDRSP) are strains resistant to two or more of the following antibiotics: penicillin (MIC ≥2 µg/mL), 2nd generation cephalosporins
(eg, cefuroxime axetil), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole.
Table 24 – Clinical Cure and Bacteriological Eradication Rates for All Moxifloxacin-treated MDRSP CAP Patients According to the Number of Antimicrobials the Isolate was Resistant to – Valid-per-protocol Population (n=37)
Table 25 – Clinical Cure and Bacteriological Eradication Rates for All Moxifloxacin-treated MDRSP CAP Patients According to Multi-drug Resistant Phenotype – Valid-per-protocol Population (n=37)
a Macrolide antimicrobials tested included azithromycin, clarithromycin, and erythromycin
DETAILED PHARMACOLOGY
Animal Pharmacology
Quinolones have been shown to cause arthropathy in immature animals. In studies in juvenile dogs oral doses of moxifloxacin, the active ingredient in MYLAN-MOXIFLOXACIN, >30 mg/kg/day (approximately 1.5 times the maximum recommended human dose based upon systemic exposure) for 28 days resulted in arthropathy. There was no evidence of arthropathy in mature monkeys and rats at oral doses up to 135 and 500 mg/kg, respectively.
Unlike some other members of the quinolone class, crystalluria was not observed in 6-month repeat dose studies in rats and monkeys with moxifloxacin.
Ocular toxicity was not observed in 6-month oral repeat dose studies in rats and monkeys. In Beagle dogs, electroretinographic (ERG) changes were observed in a 2-week study at oral doses of 60 and 90 mg/kg. Histopathological changes were observed in the retina from one of four dogs at 90 mg/kg, a dose associated with mortality in this study.
Some quinolones have been reported to have proconvulsant activity that is exacerbated with concomitant use of non-steroidal anti-inflammatory drugs (NSAIDs). Moxifloxacin at an oral dose of 300 mg/kg did not show an increase in acute toxicity or potential for CNS toxicity (e.g. seizures) in mice when used in combination with NSAIDs such as diclofenac, ibuprofen, or fenbufen.
In dog studies, at plasma concentrations about five times the human therapeutic level, a QT- prolonging effect of moxifloxacin was found. Electrophysiological in vitro studies suggested an inhibition of the rapid activating component of the delayed rectifier potassium current (IKr) as an underlying mechanism. In dogs, the combined infusion of sotalol, a Class III antiarrhythmic agent, with moxifloxacin induced a higher degree of QTc prolongation than that induced by the same dose (30 mg/kg) of moxifloxacin alone.
Elevated liver transaminase levels occurred in rats, monkeys and dogs. Single cell necrosis in the liver was observed in rats at 500 mg/kg/day and in monkeys at 250 mg/kg/day.
Human Pharmacology
Pharmacokinetics
Pharmacokinetics are linear in the range of 50-800 mg (single dose) and up to 600 mg (once daily oral dosing over 10 days).
The mean (±SD) Cmax and AUC values at steady-state with a 400 mg oral once daily dosage regimen are 4.5±0.53 g/L and 48±2.7 mg*h/L, respectively. Cmax is attained 1 to 3 hours after oral dosing. The mean (±SD) trough concentration is 0.95±0.10 mg/L. The mean (±SD) Cmax and AUC values at steady-state with a once daily dosage regimen of 400 mg intravenous moxifloxacin infused over 60 minutes in healthy young males are 4.2±0.8 g/L and 38±4.7 mg*h/L, respectively. Cmax is achieved at the end of a 60 minute infusion (see DOSAGE AND ADMINISTRATION).
Plasma concentrations increase proportionately with dose up to the highest dose tested (1200 mg single oral dose). Moxifloxacin is eliminated from plasma by first-order process. The mean (±SD) elimination half-life from plasma is 12±1.3 hours; steady-state is achieved after at least three days with a 400 mg once daily regimen. The time course of plasma concentrations of moxifloxacin following steady-state oral and intravenous administration is illustrated in Figure 1, and pharmacokinetic parameters of moxifloxacin are presented in Table 10 (see ACTION AND CLINICAL PHARMACOLOGY).
Absorption and Bioavailability
Moxifloxacin hydrochloride, given as an oral tablet, is well absorbed from the gastrointestinal tract. The absolute bioavailability of moxifloxacin is approximately 90 percent. Co- administration with a high fat meal (i.e., 500 calories from fat) does not affect absorption of moxifloxacin.
Consumption of one cup of yogurt with moxifloxacin does not significantly affect the extent or rate of systemic absorption (AUC).
Distribution
Moxifloxacin is approximately 50% bound to serum proteins, independent of drug concentration. The volume of distribution of moxifloxacin ranges from 1.7 to 2.7 L/kg. Moxifloxacin is widely distributed throughout the body, with tissue concentrations often exceeding plasma concentrations. Moxifloxacin has been detected in the saliva, nasal and bronchial secretions, mucosa of the sinuses, and abdominal tissues and fluids following oral or intravenous administration of 400 mg. Moxifloxacin concentrations measured post dose in various tissues and fluids following a 400 mg oral or I.V. dose are summarized in Table 11 (see ACTION AND CLINICAL PHARMACOLOGY). The rates of elimination of moxifloxacin from tissues generally parallel the elimination from plasma.
Metabolism
Moxifloxacin is metabolized via glucuronide and sulfate conjugation. The cytochrome P450 system is not involved in moxifloxacin metabolism, and is not affected by moxifloxacin. The sulfate conjugate (M1) accounts for approximately 38% of the dose, and is eliminated primarily in the feces. Approximately 14% of an oral dose is converted to a glucuronide conjugate (M2), which is excreted exclusively in the urine. Peak plasma concentrations of M2 are approximately
40% those of the parent drug, while plasma concentrations of M1 are generally less than 10% those of moxifloxacin. The sulfate (M1) and glucuronide (M2) conjugates are not microbiologically active.
Excretion
Approximately 45% of an oral dose of moxifloxacin is excreted as unchanged drug (~20% in urine and ~25% in feces). A total of 96%±4% of an oral dose is excreted as either unchanged drug or known metabolites. The mean (±SD) apparent total body clearance and renal clearance are 12±2.0 L/hr and 2.6±0.5 L/hr, respectively.
Special Populations
Pediatrics (<18 years of age)
The pharmacokinetics of moxifloxacin in pediatric subjects have not been established.
Geriatrics (≥65 years of age)
Following oral administration of 400 mg moxifloxacin for 10 days in 16 elderly (8 male; 8 female) and 16 young (8 male; 8 female) healthy volunteers, there were no age-related changes in moxifloxacin pharmacokinetics. In 16 healthy male volunteers (8 young; 8 elderly) given a single 200 mg oral dose of moxifloxacin, the extent of systemic exposure (AUC and Cmax) was not statistically different between young and elderly males and elimination half-life was unchanged. No dosage adjustment is necessary based on age.
In Phase I studies, the pharmacokinetics in elderly patients following infusion of 400 mg were similar to those observed in young patients.
Gender
Following oral administration of 400 mg moxifloxacin daily for 10 days to 23 healthy males
(19-75 years) and 24 healthy females (19-70 years), the mean AUC and Cmax were 8% and 16% higher, respectively, in females compared to males. There are no significant differences in moxifloxacin pharmacokinetics between male and female subjects when differences in body weight are taken into consideration.
A 400 mg single dose study was conducted in 18 young males and females. The comparison of moxifloxacin pharmacokinetics in this study (9 young females and 9 young males) showed no differences in AUC or Cmax due to gender. Dosage adjustments based on gender are not necessary.
Race
Steady state moxifloxacin pharmacokinetics in male Japanese subjects were similar to those determined in Caucasians, with a mean Cmax of 4.1 g/L, an AUC24 of 47 g*h/mL, and an elimination half-life of 14 hours following 400 mg daily PO.
Renal Insufficiency
The pharmacokinetic parameters of moxifloxacin are not significantly altered by mild, moderate, or severe renal impairment. Based on pharmacokinetic data, no dosage adjustment is necessary in patients with renal impairment, including those patients on hemodialysis (HD) or continuous ambulatory peritoneal dialysis (CAPD).
In a single oral dose study of 24 patients with varying degrees of renal function from normal to severely impaired, the mean peak concentrations (Cmax) of moxifloxacin were reduced by 22% and 21% in the patients with moderate (Clcr≥30 and ≤60 mL/min) and severe (Clcr<30 mL/min) renal impairment, respectively. The mean systemic exposure (AUC) in these patients was increased by 13%. In the moderate and severe renally impaired patients, the mean AUC for the sulfate conjugate (M1) increased by 1.7-fold (ranging up to 2.8-fold) and mean AUC and Cmax for the glucuronide conjugate (M2) increased by 2.8-fold (ranging up to 4.8-fold) and 1.4-fold (ranging up to 2.5-fold), respectively. The sulfate and glucuronide conjugates are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal impairment has not been studied.
The pharmacokinetics of single and multiple dose moxifloxacin were studied in patients with
Clcr<20 mL/min on either hemodialysis or continuous ambulatory peritoneal dialysis (8 HD, 8
CAPD). Pharmacokinetic comparisons are to historical pharmacokinetic values from health volunteers (Clcr>90 mL/min; administered a single 400 mg oral dose of moxifloxacin). Following a single 400 mg oral dose, the AUC of moxifloxacin in these HD and CAPD patients did not vary significantly from the AUC generally found in healthy volunteers. Cmax values of moxifloxacin were reduced by about 45% and 33% in HD and CAPD patients, respectively, compared to healthy subjects. The exposure (AUC) to the sulfate conjugate (M1) increased by 1.4- to 1.5-fold in these patients. The mean AUC of the glucuronide conjugate (M2) increased by a factor of 7.3 to 13.2, whereas the mean Cmax values of the glucuronide conjugate (M2) increased by a factor of 2.5 to 3, compared to healthy subjects. The sulfate and the glucuronide conjugates of moxifloxacin are not microbiologically active, and the clinical implication of increased exposure to these metabolites in patients with renal disease including those undergoing HD and CAPD has not been studiedOral administration of 400 mg moxifloxacin once daily for 7 days to patients on HD or CAPD produced mean systemic exposure (AUCss) to moxifloxacin similar to that generally seen in healthy volunteers. Steady-state Cmax values were about 28% lower in HD patients but were comparable between CAPD patients and healthy volunteers. Moxifloxacin and the glucuronide conjugate (M2)
were removed from the body by HD (approximately 9% and 4%, respectively) and by CAPD (approximately 3% and 2%, respectively). Systemic exposure (AUC) to M2 was equal to or greater than moxifloxacin exposure in HD and CAPD subjects following single dosing and at steady state. (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION).
Hepatic Insufficiency
In 400 mg single oral dose studies in 6 patients with mild (Child Pugh Class A) and 10 patients with moderate (Child Pugh Class B) hepatic insufficiency, moxifloxacin mean systemic exposure (AUC) was 78% and 102%, respectively, of that in 18 healthy controls. The mean peak concentration (Cmax) was 79% and 84%, respectively, of control values.
The mean AUC of the sulfate conjugate of moxifloxacin (M1) increased by 3.9-fold (ranging up to 5.9-fold) and 5.7-fold (ranging up to 8.0-fold) in the mild and moderate groups, respectively. The mean Cmax of M1 increased by approximately 3-fold in both groups (ranging up to 4.7- and
3.9-fold), respectively. The mean AUC of the glucuronide conjugate of moxifloxacin (M2)
increased by 1.5-fold (ranging up to 2.5-fold) in both groups. The mean Cmax of M2 increased by
1.6- and 1.3-fold (ranging up to 2.7- and 2.1-fold), respectively. The clinical significance of increased exposure to the sulfate and glucuronide conjugates has not been studied. No dosage adjustment is recommended for mild or moderate hepatic insufficiency (Child Pugh Classes A and B). Due to limited clinical data, the use of moxifloxacin is not recommended with severe hepatic insufficiency (see WARNINGS AND PRECAUTIONS, DOSAGE AND ADMINISTRATION).
QT Prolongation
The effect of moxifloxacin on the QT interval has been extensively studied in pre-clinical models, healthy volunteers and patients. These data are briefly described below. The clinical pharmacology program included single-dose, multiple-dose and cross-over studies of healthy male and female volunteers aged 18 to 75 years treated with oral and intravenous moxifloxacin 400 mg. The patient data are derived from the Phase III clinical studies with oral and intravenous moxifloxacin 400 mg. In all cases, the QT data presented are corrected for heart rate (QTc) using Bazett’s correction. The baseline pre-treatment QTc interval measured on Day 1 of treatment prior to drug administration was used in all cases for calculations of the relative QTc interval change. QTc at Cmax was defined to be end of infusion for the intravenous data, and 2 hours after drug administration for the oral data.
In clinical pharmacology single-dose studies (n=112 subjects) with 400 mg oral moxifloxacin, the aggregate mean prolongation of the QTc interval at the expected time of peak plasma concentration after a single oral dose of 400 mg moxifloxacin was 7±23 msec (1.8%±5.6%). In a multi-dose clinical pharmacology study (n=47) with 400 mg oral moxifloxacin, the mean prolongation at steady-state of the QTc interval (measured on Day 10) was 12.3 msec. There were four male patients with a QTc greater than 450 msec and one male patient with a QTc increase of greater than 60 msec.
In clinical pharmacology single-dose studies (n=29) with 400 mg intravenous moxifloxacin, the aggregate mean prolongation of the QTc interval at the end of a one hour infusion was 20.6±23 msec (5.5%±5.9%). In a multi-dose clinical pharmacology study (n=7) with 400 mg intravenous moxifloxacin, the mean prolongation of the QTc interval at steady-state (Day 10) was 12.6 msec. There were four male patients with a QTc interval greater than 450 msec. Two patients had a QTc increase of greater than 60 msec.
In 787 patients with paired valid ECGs in Phase III clinical trials, the mean±SD prolongation of the QTc interval was 6±26 msec at the estimated time of Cmax after oral dosing with moxifloxacin 400 mg. In 176 patients with paired valid ECGs in Phase III clinical trials, the mean±SD prolongation of the QTc interval after a one hour infusion of intravenous moxifloxacin 400 mg was 9±24 msec (Day 1; n=176) and 3±29 msec (Day 3; n=290). An analysis of data from the two Phase III studies at various time intervals after moxifloxacin infusion revealed the following increases in QTc. Within 0-3 hours after a 60 minute 400 mg moxifloxacin infusion (n=86) on the first day of exposure, the mean±SD increase in QTc was 14±26 msec. However, on the first day of exposure, if a time window of 0-4 hours after a 60 minute 400 mg moxifloxacin infusion (n=176) is utilized, the mean±SD increase in QTc was 9±24 msec. If the time window of 1-3 hours after a 60 minute 400 mg moxifloxacin infusion (n=90) is examined, the mean±SD increase in QTc was 5±20 msec. The corresponding values on Day 3 of a daily 60 minute infusion of 400 mg moxifloxacin were 7±30 msec (0-3 hours; n=71), 3±29 msec (0-4 hours; n=290) and 0±26 msec (1-4 hours; n=83) (see WARNINGS AND PRECAUTIONS).
MICROBIOLOGY
Moxifloxacin hydrochloride has in vitro activity against a wide range of Gram- positive and Gram-negative aerobic, anaerobic, as well as intracellular organisms. The bactericidal action of moxifloxacin results from inhibition of both topoisomerase II (DNA gyrase) and topoisomerase IV. Both are required for bacterial DNA replication, transcription, repair, and recombination. The presence of the bulky bicycloamine substituent at the C-7 position prevents active efflux, a proposed mechanism of fluoroquinolone resistance.
The mechanism of action for quinolones, including moxifloxacin, is different from that of macrolides, beta-lactams, aminoglycosides, or tetracyclines; therefore, microorganisms resistant to these classes of drugs may be susceptible to moxifloxacin. There is no known cross-resistance between moxifloxacin and other classes of antibiotics. Conversely, microorganisms resistant to fluoroquinolones may be susceptible to other classes of antimicrobial agents.
In vitro resistance to moxifloxacin develops slowly via multiple-step mutations. Resistance to moxifloxacin occurs in vitro at a general frequency of between 1.8 x 10⁻⁹ to <1 x 10-11 in one strain of Staphylococcus aureus and one strain of Streptococcus pneumoniae.
Although cross-resistance has been observed between moxifloxacin and other fluoroquinolones against Gram-negative bacteria, Gram-positive bacteria resistant to other fluoroquinolones may be susceptible to moxifloxacin. Conversely, Gram-positive bacteria that are resistant to moxifloxacin may be susceptible to other fluoroquinolones.
Moxifloxacin has been shown to be active against most strains of the following microorganisms, both in vitro and in clinical infections as described in the INDICATIONS AND CLINICAL USE section. In vitro activity of moxifloxacin against clinical isolates is presented in Table 26.
Table 26 – Moxifloxacin In Vitro Activity Against Clinical Isolates
| Species | No. of Isolates | MIC (mg/L) | ||
|---|---|---|---|---|
| MIC50 | MIC90 | Range | ||
| GRAM-POSITIVE | ||||
| Enterococcus faecalis a,b | 16 | 0.25 | 2 | 0.25-16 |
| Streptococcus anginosus a | 40 | 0.125 | 0.25 | 0.06-0.25 |
| Staphylococcus aureus | 115 | 0.06 | 0.125 | 0.03-4 |
Streptococcus pneumoniae Penicillin-susceptible Penicillin-intermediate Penicillin-resistant (penicillin MIC>2 μg/mL) | 77 5324 964 348 | 0.125 | 0.25 0.25 0.25 0.25 | 0.06-0.5 0.06-1 0.06-1 0.06-0.25 |
| GRAM-NEGATIVE | ||||
| Bacteroides fragilesa | 71 | 0.5 | 1 | 0.03-8 |
| Bacteroides thetaiotaomicrona | 52 | 1 | 2 | 0.125-16 |
| Clostridium perfringensa | 10 | 0.5 | 0.5 | 0.25-0.5 |
| Escherichia colia | 182 | 0.125 | 0.25 | 0.008-16 |
| Haemophilus influenzae | 120 | 0.03 | 0.06 | 0.008-0.25 |
| Haemophilus parainfluenzae | 39 | 0.06 | 0.5 | 0.015-8 |
| Klebsiella pneumoniae | 48 | 0.125 | 0.5 | 0.06-4 |
| Moraxella catarrhalis | 86 | 0.06 | 0.125 | 0.03-0.25 |
| Proteus mirabilisa | 10 | 0.25 | 0.5 | 0.25-0.5 |
| OTHER MICROORGANISMS | ||||
| Chlamydia pneumoniae | 19 | 1 | 0.06-1 | |
| Mycoplasma pneumoniae | 131 | 0.06 | 0.06-0.12 | |
a from clinical trials only
b (Vancomycin sensitive strains only; many strains are only moderately susceptible)
Moxifloxacin exhibits in vitro minimum inhibitory concentrations (MICs) of 2 mg/L or less against most (≥90%) strains of the microorganisms listed in Table 27; however the safety and effectiveness of moxifloxacin in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trials.
The following in vitro data are available and presented in Table 27, but their clinical significance is unknown.
Table 27 – Moxifloxacin In Vitro Activity with Unknown Clinical Significance
| Species | No. of Isolates | MIC (mg/L) | ||
| MIC50 | MIC90 | Range | ||
| Bacteroides fragiles a | 310 | 2 | 0.25-4 | |
| Clostridium perfringens a | 88 | 0.5 | 0.5 | |
| Enterobacter cloacae | 92 | 0.5 | 0.06-0.5 | |
| Enterococcus faecalis a | 1019 | 16 | 0.5-16 | |
| Enterococcus faecium | 925 | 16 | 0.12- >32 | |
| Enterococcus species | 2562 | 16 | 0.25- >32 | |
| Escherichia coli a | 276 | 0.06 | 0.008-4 | |
| Fusobacterium species | 160 | 1 | 0.25-8 | |
Haemophilus influenzae Beta-lactamase positive Beta-lactamase negative | 477 999 | 0.06 0.06 | 0.016-0.06 0.016-0.06 | |
| Legionella pneumophila | 67 | 0.015-0.03 | 0.015-0.125 | 0.03-0.125 |
| Legionella species | 149 | 0.125 | 0.015-0.25 | |
| Listeria monocytogenes | 80 | 0.25 | 0.5 | 0.06-0.5 |
| Morganella morganii | 92 | 0.06-0.25 | 0.13-16 | 0.03-8 |
| Moraxella catarrhalis | 1203 | 0.06 | 0.03-0.125 | |
Beta-lactamase positive Beta-lactamase negative | 712 83 | 0.06 0.06 | 0.03-0.125 0.03-0.12 | |
| Mycobacterium tuberculosis | 276 | 0.5 | 0.25-0.5 | |
| Neisseria gonorrhoeae | 68 | 0.008-0.016 | 0.015-0.03 | 0.004-0.12 |
| Peptostreptococcus species | 125 | 0.25 | 0.25-1 | |
| Prevotella species | 176 | 0.5 | 0.125-4 | |
| Proteus mirabilisa | 236 | 0.25 | 0.25-4 | |
| Pseudomonas aeruginosa | 371 | 8 | 8- >32 | |
Staphylococcus aureus Methicillin-susceptible Methicillin-resistant | 526 309 | 0.12 4 | 0.06-2 2-8 | |
| Staphylococcus epidermidis | 233 | 0.12 | 0.1-2 | |
| Streptococcus viridans group | 334 | 0.25 | 0.25-0.5 | |
| Streptococcus agalactiae | 191 | 0.5 | 0.25-0.5 | |
| Streptococcus pyogenes | 1607 | 0.25 | 0.1-0.25 | |
a not from clinical trials
Susceptibility Tests
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimum inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a broth or agar dilution method such as CLSI Performance Standards for Antimicrobial
Susceptibility Testing or equivalent with standardized inoculum concentrations and standardized concentrations of moxifloxacin powder. The MIC values should be interpreted according criteria listed in Table 28.
Table 28 – Interpretation of MIC Values
| MIC (mg/L) | Interpretation |
| For testing Enterobacteriaceae and Staphylococcus spp. | |
| ≤2.0 | Susceptible (S) |
| 4.0 | Intermediate (I) |
| ≥8.0 | Resistant (R) |
| For testing Haemophilus influenzae and Haemophilus parainfluenzaea | |
| ≤1.0 | Susceptible (S) |
| For testing Streptococcus species (including Streptococcus pneumoniae)b and Enterococcus species | |
| ≤1.0 | Susceptible (S) |
| 2.0 | Intermediate (I) |
| ≥4.0 | Resistant (R) |
a This interpretive standard is applicable only to broth microdilution susceptibility tests with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium (HTM) broth incubated in ambient air at 35ºC ± 2 degrees for 20-24 hours (12)
b This interpretive standard is applicable only to broth microdilution susceptibility tests using cation-adjusted Mueller-Hinton broth (CAMHB) with 2-5% (v/v) lysed horse blood broth incubated in ambient air at 35ºC ± 2 degrees for 20-24 hours (12)
The current absence of data on resistant strains of Enterobacteriaceae, Staphylococcus spp, Haemophilus influenzae and Haemophilus parainfluenzae precludes defining any results other than “Susceptible”. Strains yielding MIC results suggestive of a “nonsusceptible” category should be submitted to a reference laboratory for further testing.
For Streptococcus species (including Streptococcus pneumoniae) and Enterococcus species, a report of “Susceptible” indicates that the pathogen is likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable. A report of “Intermediate” indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high dosage of drug can be used. This category also provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of “Resistant” indicates that the pathogen is not likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable; other therapy should be selected.
Standardized susceptibility test procedures require the use of laboratory control microorganisms to control the technical aspects of the laboratory procedures. Standard moxifloxacin powder should provide the MIC values listed in Table 29.
Table 29 – Acceptable Limits for Quality Control Strains to Monitor the Accuracy of MICs (mg/L) for Moxifloxacin Susceptibility Testing
| Organism | MIC (mg/L) |
| Escherichia coli ATCCa 25922 | 0.008-0.06 |
| Enterococcus faecalis ATCC 29212 | 0.06-0.5 |
| Staphylococcus aureus ATCC 29213 | 0.015-0.06 |
| Haemophilus influenzae ATCC 49247b | 0.008-0.03 |
| Streptococcus pneumoniae ATCC 49619c | 0.06-0.5 |
a ATCC is a registered trademark of the American Type Culture Collection
b This quality control range is applicable to only H. influenzae ATCC 49247 tested by a broth microdilution procedure using Haemophilus Test Medium (HTM) broth (12)
c This quality control range is applicable to only S. pneumoniae ATCC 49619 tested by a broth microdilution procedure using cation-adjusted Mueller-Hinton broth with 2-5% (v/v) lysed horse blood (12)
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure (CLSI Performance Standards for Antimicrobial Susceptibility Testing) requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with
5 μg of moxifloxacin to test the susceptibility of microorganisms to moxifloxacin.
Reports from the laboratory providing results of the standard single-disk susceptibility test with a
5 μg moxifloxacin disk should be interpreted according to the criteria listed in Table 30.
Table 30 – Interpretation of Zone Diameters
| Zone Diameter (mm) | Interpretation |
| For testing Enterobacteriaceae and Staphylococcus spp. | |
| >19 | Susceptible (S) |
| 16-18 | Intermediate (I) |
| <15 | Resistant (R) |
| For testing Haemophilus influenzae and Haemophilus parainfluenzaea | |
| >18 | Susceptible (S) |
| For testing Streptococcus species (including Streptococcus pneumoniae)b and Enterococcus species | |
| >18 | Susceptible (S) |
| 15-17 | Intermediate (I) |
| <14 | Resistant (R) |
a interpretive standard is applicable only to disk diffusion tests with Haemophilus influenzae and Haemophilus parainfluenzae using Haemophilus Test Medium (HTM) incubated in 5% CO2 at 35ºC ± 2 degrees for 16-18 hours (12)
bThis interpretive standard is applicable only to disk diffusion tests using Mueller-Hinton agar supplemented with 5% (v/v) sheep blood incubated in 5% CO2 at 35ºC ± 2 degrees for 20-24 hours (12).
The current absence of data on resistant strains of Enterobacteriaceae, Staphylococcus spp, Haemophilus influenzae and Haemophilus parainfluenzae precludes defining any results other than “Susceptible”. Strains yielding zone diameter results suggestive of a “nonsusceptible” category
| Organism | Zone Diameter (mm) |
| Escherichia coli ATCC a 25922 | 28-35 |
| Staphylococcus aureus ATCC 25923 | 28-35 |
| Haemophilus influenzae ATCC 49247 b | 31-39 |
| Streptococcus pneumoniae ATCC 49619 c | 25-31 |
should be submitted to a reference laboratory for further testing.
For Streptococcus pneumoniae, interpretation should be as stated above for results using dilution techniques. Interpretation involves correlation of the diameter obtained in the disk test with the MIC for moxifloxacin.
As with standardized dilution techniques, diffusion methods require the use of laboratory control microorganisms that are used to control the technical aspects of the laboratory procedures. For the diffusion technique, the 5 µg moxifloxacin disk should provide the zone diameters listed in Table 31.
Table 31 – Acceptable Limits for Quality Control Strains used to Monitor Accuracy of Disk Diffusion Tests with 5 μg Moxifloxacin Disk
a ATCC is a registered trademark of the American type Culture Collection
b These quality control limits are applicable to only H. influenzae ATCC 49247 testing using Haemophilus
Test Medium (HTM) incubated in 5% CO2 at 35ºC ± 2 degrees for 16-18 hours (12)
c These quality control limits are applicable only to tests conducted with S. pneumoniae ATCC 49619 performed by disk diffusion using Mueller-Hinton agar supplemented with 5% (v/v) defibrinated sheep blood incubated in 5% CO2 at 35ºC ± 2 degrees for 20-24 hours
Anaerobic Techniques
For anaerobic bacteria, the susceptibility to moxifloxacin as MICs can be determined by standardized procedures (13) such as reference agar dilution methodsa. The MICs obtained should be interpreted according to the criteria listed in Table 32.
Table 32 – Interpretation of MIC Values for Anaerobic Bacteriaa
| MIC (mg/L) | Interpretation |
|---|---|
| <2.0 | Susceptible (S) |
| 4.0 | Intermediate (I) |
| >8.0 | Resistant (R) |
a This interpretive standard is applicable to reference agar dilution susceptibility tests using Brucella agar supplemented with 5 μg hemin, 1 μg vitamin K1 per mL and 5% (v/v) laked sheep blood (13)
Acceptable ranges of MICs (mg/L) for control strains for reference broth microdilution testing and reference agar dilution testing are listed in Table 33.
Table 33 – Acceptable Limits for Quality Control Strains to Monitor the Accuracy of MICs (mg/L) for Moxifloxacin Susceptibility Testing for Anaerobic Bacteria
| Organism | MIC (mg/L) |
|---|---|
| Reference Agar Dilution Susceptibility Testinga | |
| Bacteroides fragilis ATCCb 25285 | 0.125-0.5 |
| Bacteroides thetaiotaomicron ATCC 29741 | 1.0-4.0 |
| Eubacterium lentum ATCC 43055 | 0.125-0.5 |
a These quality control ranges are applicable to reference agar dilution tests using Brucella agar supplemented with 5 μg hemin, 1 μg vitamin K1 per mL and 5% (v/v) laked sheep blood (13)
b ATCC is a registered trademark of the American Type Culture Collection
TOXICOLOGY
The major toxicological target organs for moxifloxacin, the active ingredient in MYLAN-MOXIFLOXACIN, are the same as have been seen with other quinolones. These include the hemopoietic system (hypocellularity of the bone marrow in dogs and monkeys), the central nervous system (convulsions in monkeys) and the liver (raised liver enzymes, single cell necrosis in rats, dogs and monkeys). These changes were commonly seen only after prolonged treatment or treatment with high doses of moxifloxacin.
Acute Toxicity
The acute toxicity was investigated in mice and rats following oral and intravenous administration and in monkeys following oral administration (see Table 34).
Table 34– Results of Acute Toxicity Animal Studies
| Species | Strain (Sex) | #/Group | Route of Administration | LD50 mg/kg B.W. (Confidence Interval for 95%) |
|---|---|---|---|---|
| Mouse | NMRI (♂) NMRI (♀) NMRI (♂) NMRI (♀) WU (♂) WU (♀) WU (♂) WU (♀) | 5 | PO PO IV IV PO PO IV IV | approx. 435 approx. 758 (440-1305) approx. 105 (84-132) approx. 130 (116-145) approx. 1320 approx. 1320 approx. 112 approx. 146 |
| Monkey | Cynomolgus (♂) | 2 | single dose/PO | approx. 1500 mg/kg |
Repeated Dose Toxicity
As shown in Table 35, moxifloxacin was examined in repeated dose toxicity studies in rats (oral and intravenous), Beagle dogs (oral) and Rhesus monkeys (oral and intravenous).
| Table 35 – Results of Repeated Dose Toxicity Animal Studies | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Species (# per Group) | Dose / Route | Treatment Duration | Findings | |||||||
Wistar rats (10 ♂, 10 ♀) | 0, 20, 100 mg/kg orally (young animals), 100 mg/kg orally (old animals) | 4 weeks | Treatment was tolerated without symptoms. The clear NOAEL is 100 mg/kg for both old and young rats. | |||||||
Wistar rats (10 ♂, 10 ♀) | 0, 20, 100, 500 mg/kg orally by gavage | 4 weeks | ↓ body weight gain at 100 and 500 mg/kg in males. NOAEL for males=20 mg/kg (Cmax=0.712 mg/L). NOAEL for females=500 mg/kg (Cmax=5.22 mg/L). | |||||||
Wistar rats (10 ♂, 10 ♀) | 0, 5, 15, 45 mg/kg IV | 4 weeks | With the exception of local effects at the injection site, no other effects were observed. The NOAEL for local irritation=5 mg/kg. The systemic NOAEL is 45 mg/kg (Cmax=8.57 mg/L). | |||||||
Wistar rats (15 ♂, 15 ♀) | 0, 20, 100, 500, 750 mg/kg orally by gavage (2 groups per dose) | 13 weeks for all groups 1 group was examined after a 4 week recovery period | ↓ body weight gain at 100, 500 and 750 mg/kg males. ↑ ASAT, ALAT, LDH in 500 and 750 mg/kg males; 750 mg/kg females. No histopathology results. NOAEL for females=100 mg/kg (Cmax=0.756 mg/L) NOAEL for males=20 mg/kg (Cmax=1.22 mg/L). | |||||||
Wistar rats (20 ♂, 20 ♀) | 0, 20, 100, 500 mg/kg orally by gavage | 28 weeks | ↑ water consumption in 100 mg/kg males; 500 mg/kg males and females. ↓ body weight gain at 500 mg/kg in both sexes. ↑ ASAT, ALAT in all 500 mg/kg males; ↑ LDH and bilirubin in 500 mg/kg males; ↑ APH at 500 mg/kg in both sexes. ↓ N-DEM, O-DEM in 100 and 500 mg/kg males. ↓ P450 in 500 mg/kg males; ↑ P450 in 20, 100, 500 mg/kg females. Histopath: liver 500 mg/kg in both sexes; thyroid 500 mg/kg in males. NOAEL for females=100 mg/kg (Cmax=0.822 mg/L) NOAEL for males=20 mg/kg (Cmax=1.48 mg/L). | |||||||
Beagle dogs (4 ♂, 4 ♀) | 0, 10, 30, 90 mg/kg PO (capsule) | 4 weeks | Female terminated (2 weeks) in poor condition. Forepaws flexed at 10, 30, 90 mg/kg. ↑ vacuolization subcapsular cortex of the lens at 90 mg/kg. Prolongation of QT interval at 90 mg/kg. Histopath: chondropathy at 90 and 30 mg/kg. NOAEL= >10 mg/kg (Cmax=2.19 mg/L) | |||||||
Beagle pups (2 ♂, 2 ♀) | 0, 10, 30, 90 mg/kg PO (capsule) | 4 weeks | 90 mg/kg female terminated in poor condition. Vomiting, salivation and ↓ body weight gain at 90 mg/kg. Histopath: blistering of articular cartilage at 30 and 90 mg/kg. NOAEL=10 mg/kg (Cmax=2.97 mg/L) | |||||||
| Table 35 – Results of Repeated Dose Toxicity Animal Studies |
|---|
Species (# per Group) | Dose / Route | Treatment Duration | Findings |
|---|---|---|---|
Rhesus monkeys (3 ♂, 3 ♀) | 0, 10, 50, 250* mg/kg orally by gavage *reduced to 150 mg/kg from Day 23 | 4 weeks | ↓ body weight gain, ↑ ASAT, ALAT, GLDH. Convulsions at 250 mg/kg. Histopath: liver, bone marrow, testes and prostate at 250 mg/kg NOAEL=50 mg/kg (Cmax=5.32 mg/L) |
Rhesus monkeys (3 ♂, 3 ♀) | 0, 100, 150 mg/kg orally by gavage | 4 weeks | ↓ body weight gain at 150 mg/kg; histopath: liver and bone marrow at 100 and 150 mg/kg. NOAEL= <100 mg/kg (Cmax=9.63 mg/L) |
Rhesus monkeys (4 ♂, 4 ♀) | 0, 15, 45, 135 mg/kg orally by gavage | 13 weeks | Salivation at 45 mg/kg. Salivation, vomiting, reduced activity and ↓ body weight gain in males at 135 mg/kg. NOAEL=15 mg/kg (Cmax=2.35 mg/L for males, 1.95 mg/L for females) |
Rhesus monkeys (4 ♂, 4 ♀) | 0, 15, 45, 135 mg/kg orally by gavage | 26 weeks | Mortality at 135 mg/kg. ↑ ALAT and GLDH at 45 mg/kg. Histopath: liver and bone marrow at 135 mg/kg. NOAEL=15 mg/kg (Cmax=2.42 mg/L) |
Rhesus monkeys (3 ♂, 3 ♀) | 0, 5, 15, 45 mg/kg IV | 4 weeks | Vomiting, salivation, drooping eyelid at 45 mg/kg NOAEL for local irritation=15 mg/kg NOAEL for systemic toxicity=15 mg/kg (Cmax=5.07 mg/L) |
Rhesus monkeys (3 ♂, 3 ♀) | 0, 200, 400 mg/animal IV infusion | 4 weeks | Hypoactivity, vomiting, salivation and spastic movements at 400 mg/animal; vascular and perivascular inflammation at 200 and 400 mg/animal. NOAEL for local irritation= >200 mg/kg. NOAEL for systemic toxicity=200 mg/kg (Cmax=9.90 mg/L) |
Legend: ALAT=Serum alanine aminotransferase; ASAT=Aspartate aminotransferase; N-DEM=aminopyrin-N- demethylase; O-DEM=p-nitroanisol-N-demethylase; GLDH=glutamate dehydrogenase; LDH=Lactate dehydrogenase; NOAEL=No Observable Adverse Effect Level
Carcinogenicity
Conventional long term studies in animals to determine the carcinogenic potential of moxifloxacin have not been performed. However, a 38-week rat initiation-promotion bioassay showed moxifloxacin to have no carcinogenic potential.
Reproductive Toxicology
Moxifloxacin was not teratogenic in rats at oral doses as high as 500 mg/kg/day (63 times the recommended human dose on a mg/kg basis or 13 times on a mg/m2 basis). Decreased fetal body weights and slightly delayed fetal skeletal development occurred in rats at a maternally toxic dose of 500 mg/kg. Maternal toxicity was observed at 100 and 500 mg/kg/day. There was no evidence of teratogenicity when Cynomolgus monkeys were dosed as high as 100 mg/kg/day (12.5 times the recommended human dose on a mg/kg basis or 4.5 times on a mg/m2 basis). An increased incidence of smaller fetuses was observed at 100 mg/kg/day. There was an increase in abortions observed in Cynomolgus monkeys at doses of 30 mg/kg and higher. In an oral
pre-postnatal development study conducted in rats, marginal effects observed at 500 mg/kg/day included extended duration of pregnancy, increased prenatal loss, reduced birth weight and decreased survival index. Treatment-related maternal mortality occurred at 500 mg/kg/day.
Moxifloxacin had no effect on fertility in male and female rats at oral doses as high as 500 mg/kg/day (3500 mg/m2) which corresponds to 63 times the recommended human dose on a mg/kg basis or 13 times on a mg/m2 basis. At the systemically toxic dose of 500 mg/kg there were slight effects on sperm morphology (head-tail separation) in male rats and on the estrous cycle in female rats.
In an intravenous rabbit study, moxifloxacin at 20 mg/kg was found to decrease the gestation rate, decrease fetal weights and delay ossification.
Since there are no adequate or well-controlled studies in pregnant women, moxifloxacin should be used during pregnancy only if the potential benefit to the mother justifies any potential risk to the fetus.
Mutagenesis
Moxifloxacin was not mutagenic in 4 strains (TA 98, TA 100, TA 1535, TA 1537) of the Ames Salmonella reversion assay. As with other quinolones, the Ames test with strain TA102 was positive and may be due to the inhibition of DNA gyrase. Moxifloxacin was not mutagenic in the HGPRT mutation assay in Chinese Hamster Ovary cells. An equivocal result was obtained in the HGPRT mutation assay with v79 cells. Under in vitro conditions, moxifloxacin was clastogenic in the v79 chromosome aberration assay at a concentration of 300 µg/mL. No evidence of genotoxicity was observed in the Unscheduled DNA Synthesis assay in rat primary hepatocytes. There was no evidence of genotoxicity in vivo in a mouse micronucleus test and in a mouse dominant lethal test.
Cardiac Effects
As has been observed with other quinolones, a prolongation of the QT-interval was observed in dogs treated with an oral dose of 90 mg/kg or with an intravenous bolus dose of 30 mg/kg. The effect was only slight when the drug was given as a slow infusion or orally. No arrhythmias were observed in dogs following treatment with oral doses of moxifloxacin. At intravenous doses of more than 300 mg/kg resulting in a plasma concentration greater than 200 mg/L, moxifloxacin caused reversible ventricular arrythmias in dogs.
In beagle dogs, moxifloxacin at a dose of 30 mg/kg IV in combination with sotalol lowered mainly the systolic blood pressure and increased the heart rate back to starting values (before sotalol). In combination with sotalol, the QTc was markedly elevated by moxifloxacin (+113 msec); this effect seems to be additive to the sotalol-effect.
Arthrotoxicity
Quinolones are known to cause lesions in the cartilage of the major diarthodial joints in immature animals. The lowest oral dose of moxifloxacin causing joint toxicity in juvenile dogs was four times the maximum recommended therapeutic dose (400 mg/50 kg person) on a mg/kg basis, with plasma concentrations two to three times higher than those at the recommended therapeutic dose.
Phototoxicity
Double-blind placebo controlled clinical studies with moxifloxacin have shown it to be without measurable phototoxicity (see WARNINGS AND PRECAUTIONS).
Moxifloxacin has been evaluated in several in vitro and in vivo photostability and phototoxicity studies under conditions of UV-A/B light to simulate natural sunlight exposure. Moxifloxacin has been shown to be photostable, and to lack photogenotoxicity or photomutagenicity in mouse
3T3 fibroblasts. It was also negative in phototoxicity studies in guinea pigs, pigmented and non- pigmented rats and hairless mice.
REFERENCES
- 1. Siegert R, Gehanno P, Nikolaidis P, Bagger-Sjoback D, Ibanez JM, Hampel B, et al. A comparison of the safety and efficacy of moxifloxacin (BAY 12-8039) and cefuroxime axetil in the treatment of acute bacterial sinusitis in adults. The Sinusitis Study Group. Respir Med 2000;94:337-44.
- 2. Burke T, Villanueva C, Mariano H, Jr., Huck W, Orchard D, Haverstock D, et al. Comparison of moxifloxacin and cefuroxime axetil in the treatment of acute maxillary sinusitis. Sinusitis Infection Study Group. Clin Ther 1999;21(10):1664-77.
- 3. Wilson R, Kubin R, Ballin I, Deppermann KM, Bassaris HP, Leophonte P, et al. Five day moxifloxacin therapy compared with 7 day clarithromycin therapy for the treatment of acute exacerbations of chronic bronchitis. J Antimicrob Chemother 1999;44(4):501-13.
- 4. Chodosh S, DeAbate CA, Haverstock D, Aneiro L, Church D. Short-course moxifloxacin therapy for treatment of acute bacterial exacerbations of chronic bronchitis. The Bronchitis Study Group. Respir Med 2000;94(1):18-27.
- 5. Hoeffken G, Meyer HP, Winter J, Verhoef L. The efficacy and safety of two oral moxifloxacin regimens compared to oral clarithromycin in the treatment of community- acquired pneumonia. Respir Med 2001;95(7):553-64.
- 6.
Patel T, Pearl J, Williams J, Haverstock D, Church D. Efficacy and safety of ten day moxifloxacin 400 mg once daily in the treatment of patients with community-acquired pneumonia. Community Acquired Pneumonia Study Group. Respir Med 2000;94(2):97-
105.
- 7.
Fogarty C, Grossman C, Williams J, Haverstock D, Church D. Efficacy and safety of moxifloxacin vs. clarithromycin for community-acquired pneumonia. Infect Med
1999;16:748-763.
- 8. File TM, Larsen SL, Fogarty CM, Schechter RB, Peloquin S, Choudhri SH, et al. Safety and efficacy of sequential (IV to PO) moxifloxacin for the treatment of community- acquired pneumonia in hospitalized patients. Today's Therapeutic Trends 2001;19:251-270.
- 9.
Lode H, Grossman C, Choudhri S, Haverstock D, McGivern J, Herman-Gnjidic Z, et al.
Sequential IV/PO moxifloxacin treatment of patients with severe community-acquired pneumonia. Respir Med 2003;97(10):1134-42.
- 10.
Finch R, Schurmann D, Collins O, Kubin R, McGivern J, Bobbaers H, et al. Randomized controlled trial of sequential intravenous (i.v.) and oral moxifloxacin compared with sequential i.v. and oral co-amoxiclav with or without clarithromycin in patients with community-acquired pneumonia requiring initial parenteral treatment. Antimicrob Agents
Chemother 2002;46:1746-54.
- 11.
Giordano P, Song J, Pertal P, Herrington J, Kowalsky S. Sequential intravenous/oral moxifloxacin versus intravenous piperacillin-tazobactam followed by oral amoxicillin-
- clavulanate for the treatment of complicated skin and skin structure infection. Int J Antimicrob Agents 2005;26(5):357-64.
- 12.
CLSI. Performance standards for antimicrobial susceptibility testing, 15th Informational
Supplement. Performance standards for antimicrobial susceptibility testing. Wayne, PA.
2005; Vol. 25, No. 1.
- 13.
NCCLS. Methods for antimicrobial susceptibility testing of anaerobic bacteria, 6th ed.
Methods for antimicrobial susceptibility testing of anaerobic bacteria. Wayne, PA. 2004; Vol. 24, No. 2.
- 14. Product Monograph, Avelox®, Control No. 194225, August 16, 2016, Bayer Inc., Toronto, Ontario.