


Product Monograph - PRZ-Doxycycline
INDICATIONS AND CLINICAL USE
PRZ-DOXYCYCLINE (doxycycline hyclate) may be indicated for the treatment of:
Pneumonia
Single and multilobe pneumonia and bronchopneumonia due to susceptible strains of Streptococcus pneunomiae and other Streptococcus spp., Staphylococcus spp., H. influenzae and Klebsiella pneumoniae.
Other Respiratory Tract Infections
Pharyngitis, tonsillitis, sinusitis, otitis media, bronchitis caused by susceptible strains of β- hemolytic Streptococcus, Staphylococcus spp., Streptococcus pneunomiae and H. influenzae.
Genitourinary Tract Infections
Pyelonephritis, cystitis, urethritis caused by susceptible strains of Klebsiella spp., Enterobacter aerogenes, E. coli, Enterococcus spp., Staphylococcus spp., Streptococcus spp. and gonococcal urethritis caused by Neisseria gonorrhoeae.
In adult patients with urethritis, cervicitis and vaginitis with a positive test for Chlamydia trachomatis and/or Ureaplasma urealyticum, clinical resolution and absence of detectable organisms have only been observed at completion of ORAL therapy with doxycycline. Relapses or reinfection can occur. In these cases, limited data suggest that some patients may derive clinical benefit from an alternative therapy. The effect on long term morbidity has not been established.
Skin and Soft Tissue Infections
Impetigo, furunculosis, cellulitis, abscess, wound infections, paronychia, caused by susceptible strains of Staphylococcus aureus and epidermidis, Streptococcus spp., E. coli, Klebsiella spp. and Enterobacter aerogenes.
Gastro-intestinal Infections
Caused by susceptible strains of Shigella spp., Salmonella spp. and E. coli.
Up to 44 percent of strains of Streptococcus pyogenes and 74 percent of Streptococcus faecalis have been found to be resistant to tetracycline drugs.
Appropriate culture and susceptibility studies should be carried out prior to initiation of therapy with PRZ-DOXYCYCLINE and if clinically indicated during treatment. Consideration may be given to the initiation of therapy before obtaining results of these tests, however modification of such treatment may be required once the results become available.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of PRZ-DOXYCYCLINE and other antibacterial drugs, PRZ-DOXYCYCLINE should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
PRZ-DOXYCYCLINE (doxycycline hyclate) is contraindicated in individuals who have shown hypersensitivity to PRZ-DOXYCYCLINE (doxycycline hyclate), and to any of its inert ingredients or to any other tetracycline, and in patients with myasthenia gravis.
PRZ-DOXYCYCLINE (doxycycline hyclate) is contraindicated in patients taking isotretinoin (see PRECAUTIONS and Drug Interactions).
WARNINGS
General
Doxycycline hyclate like other tetracyclines, may form a stable calcium complex in any bone- forming tissue, though in vitro it binds calcium less strongly than other tetracyclines. It should be anticipated that the use of doxycycline hyclate during tooth development (last trimester of pregnancy, during lactation, neonatal period and early childhood to the age of 8 years) may cause permanent discoloration of the teeth
(yellow-gray-brown). Though more commonly associated with long term use of tetracyclines, this effect has also been known to occur after short courses. Enamel hypoplasia has also been reported.
PRZ-DOXYCYCLINE should, therefore, not be used in these age groups unless other drugs are unlikely to be effective or are contraindicated.
Carcinogenesis and Mutagenesis
Long-term studies in animals to evaluate carcinogenic potential of doxycycline have not been conducted. However, there has been evidence of oncogenic activity in rats in studies with the related antibiotics, oxytetracycline (adrenal and pituitary tumors) and minocycline (thyroid tumors).
Likewise, although mutagenicity studies of doxycycline have not been conducted, positive results in in-vitro mammalian cell assays have been reported for related antibiotics (tetracycline).
Gastrointestinal
Instances of esophageal lesions (esophagitis and ulcerations), sometimes severe, have been reported in patients receiving doxycycline. The patients must be instructed to take PRZ-DOXYCYCLINE with a full glass of water, to keep in orthostatic position after the administration and not to go to bed within 1-2 hours after the intake. If symptoms such as dysphagia and retrosternal pain occur, PRZ-DOXYCYCLINE should be discontinued and an esophagic lesion must be investigated (see PRECAUTIONS, ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION). PRZ-DOXYCYCLINE should not be prescribed to patients with obstructive esophagic pathology, such as stenosis and achalasia.
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including doxycycline hyclate. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Skin
Photosensitivity reaction manifested by an exaggerated sunburn reaction has been observed in some individuals taking tetracyclines. Patients apt to be exposed to direct sunlight or ultraviolet light should be advised that this reaction can occur with PRZ-DOXYCYCLINE, and treatment should be discontinued at the first evidence of skin erythema (see PRECAUTIONS and ADVERSE REACTIONS). The use of sunscreen or sunblock prior to sun or UV light exposure should be considered in patients taking PRZ-DOXYCYCLINE.
Hypersensitivity
Hypersensitivity adverse drug reactions that included, but not limited to anaphylactic reaction, angioedema, dyspnea, tachycardia, hypotension, pericarditis, urticaria, rash, erythema multiforme, Stevens-Johnson and toxic epidermal necrolysis have been reported with doxycycline hyclate use. Some of these reactions were serious. If an allergic reaction occurs, administration of PRZ-DOXYCYCLINE should be discontinued and appropriate therapy should be initiated.
Doxycycline hyclate has been associated with the development of autoimmune adverse drug reactions including exacerbation of systemic lupus erythematous, rash, peripheral edema, arthralgia, myalgia, serum sickness. If patients with autoimmune reactions are suspected, administration of PRZ-DOXYCYCLINE should be discontinued and liver function tests, ANA, CBC, and other appropriate tests should be performed to evaluate the patients.
Renal
The anti-anabolic action of tetracyclines may cause an increase in BUN. Studies to date indicate that this anti-anabolic effect does not occur with the use of doxycycline in patients with impaired renal function.
Usage in Pregnancy
PRZ-DOXYCYCLINE should not be administered to pregnant women, unless in the judgment of the physician the potential benefit to the mother outweighs the risk to the fetus (see above WARNINGS section about use during tooth development).
Results of animal studies indicate that tetracyclines cross the placenta, are found in fetal tissues, and can have toxic effects on the developing fetus (often related to retardation of skeletal development). Evidence of embryotoxicity has also been noted in animals treated early in pregnancy.
Usage During Lactation
Tetracyclines are excreted in the milk of lactating women. Accordingly the use of PRZ-
DOXYCYCLINE is not recommended in women while they are breast feeding (see above WARNINGS section about use during tooth development).
Use in Newborns, Infants and Children
The use of PRZ-DOXYCYCLINE in children under 8 years is not recommended because safe conditions for its use have not been established (see above WARNINGS section about use during tooth development).
Doxycycline hyclate like other tetracyclines forms a stable calcium complex in any bone-forming tissue. A decrease in the fibula growth rate has been observed in prematures given oral tetracycline in doses of 25 mg/kg every six hours. This reaction was shown to be reversible when the drug was discontinued.
Susceptibility/Resistance
Prescribing PRZ-DOXYCYCLINE in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug- resistant bacteria.
PRECAUTIONS
In clinical studies to date, administration of doxycycline hyclate did not lead to increased serum levels nor to an increase in the serum half-life of doxycycline in patients with impaired renal function. Modification of doxycycline hyclate dosage for these patients is not necessary. Although no evidence of increased toxicity has been observed in such patients, the potential for increased hepatic or other toxicity should be considered until further data on the metabolic fate of doxycycline under these conditions become available.
Concurrent administration of PRZ-DOXYCYCLINE with agents known to be hepatotoxic should be avoided.
The use of antibiotics may occasionally result in overgrowth of non-susceptible organisms including fungi; thus, observation of the patient is essential.
Patients should be advised that the use of doxycycline might increase the incidence of vaginal candidiasis (see ADVERSE REACTIONS).
Benign intracranial hypertension (pseudotumor cerebri) has been associated with the use of tetracyclines including doxycycline. Benign intracranial hypertension (pseudotumor cerebri) is usually transient, however cases of permanent visual loss secondary to benign intracranial hypertension (pseudotumor cerebri) have been reported with tetracyclines including doxycycline. If visual disturbance occurs during treatment, prompt ophthalmologic evaluation is warranted. Since intracranial pressure can remain elevated for weeks after drug cessation patients should be monitored until they stabilize. Concomitant use of isotretinoin and doxycycline should be avoided because isotretinoin is also known to cause benign intracranial hypertension (pseudotumor cerebri) (see ADVERSE REACTIONS).
Cases of esophageal injury consisting of esophagitis and esophageal ulceration have been reported in patients receiving doxycycline hyclate orally. Most of these patients took medication immediately before going to bed and/or without adequate amount of fluid (see DOSAGE AND ADMINISTRATION). If this should occur, doxycycline hyclate should be discontinued until healing occurs. Administration of antacids and/or cimetidine has provided relief in the treatment of such cases. TO REDUCE THE RISK OF ESOPHAGEAL INJURY, PATIENTS SHOULD BE ADVISED TO TAKE PRZ-DOXYCYCLINE WITH AN ADEQUATE AMOUNT OF FLUID WHILE STANDING OR SITTING UPRIGHT. PRZ-DOXYCYCLINE should not be given at bedtime.
In long term therapy with PRZ-DOXYCYCLINE, periodic laboratory evaluation of organ systems, including hematopoietic, renal and hepatic studies should be performed. Liver function tests should be carried out at regular intervals on patients receiving high doses for prolonged periods of time.
Drug Interactions
PRZ-DOXYCYCLINE should be given with caution to patients receiving oral anticoagulants. Because the tetracyclines have been shown to depress plasma prothrombin activity, patients who are on anticoagulant therapy may require downward adjustment of their anticoagulant dosage.
Antacids containing aluminum, calcium or magnesium impair absorption and should not be given to patients taking PRZ-DOXYCYCLINE.
The concurrent use of doxycycline hyclate with alcohol, barbiturates, phenytoin and carbamazepine (hepatic enzyme inducers) has been reported to result in a reduction of plasma half-life of doxycycline, thereby reducing the antimicrobial effectiveness of Doxycycline. This effect may last for several days after discontinuation of therapy with the interacting agent. Therefore, consideration should be given to re-adjustment of the daily dose of PRZ-DOXYCYCLINE when administered concomitantly with alcohol and with drugs known to be enzyme inducers.
It has been reported that concurrent administration of ferrous sulphate (iron) lowered serum concentrations of doxycycline given orally and shortened the serum half-life after a single intravenous injection. In the event that iron and iron-containing products have to be given during treatment with PRZ-DOXYCYCLINE the interval between administration of each drug should be as wide as possible.
It has been reported that when subsalicylate bismuth was given simultaneously and as a multiple-dose regimen before oral doxycycline hyclate there was a reduced bioavailability of doxycycline. Also peak serum concentrations of doxycycline were significantly decreased when subsalicylate bismuth was given 2 hours before oral doxycycline but not when given 2 hours after oral doxycycline. Therefore subsalicylate bismuth should not be taken during therapy with oral PRZ-DOXYCYCLINE.
Since bacteriostatic drugs may interfere with the bactericidal action of penicillin, it is advisable to avoid giving PRZ-DOXYCYCLINE or any other tetracycline, in conjunction with penicillin.
There have been anecdotal reports that concurrent use of tetracyclines may render oral contraceptives less effective.
The concurrent use of tetracycline and Penthrane (methoxyflurane) has been reported to result in fatal renal toxicity.
Concomitant use of isotretinoin and doxycycline should be avoided because isotretinoin is also known to cause benign intracranial hypertension (pseudotumor cerebri) (see PRECAUTIONS).
Drug Laboratory Test Interactions
False elevations of urinary catecholamine levels may occur due to interference with the fluorescence test.
ADVERSE REACTIONS
GASTROINTESTINAL
As with other broad spectrum antibiotics administered orally and parenterally, gastro-intestinal disturbances such as decreased appetite, nausea, vomiting, diarrhea, glossitis, dysphagia, stomatitis, proctitis and enterocolitis, may occur, but have rarely been sufficiently troublesome to warrant discontinuation of therapy with doxycycline hyclate. Abdominal pain, dyspepsia (heartburn/gastritis), pseudomembranous colitis, Clostridium difficile colitis and inflammatory lesions (with monilial overgrowth) in the anogenital region have also been reported. Due to oral doxycycline’s virtually complete absorption, side effects of the lower bowel, particularly diarrhea, have been infrequent.
Cases of esophagitis and esophageal ulcer, sometimes severe, in patients receiving capsule and tablet form of doxycycline hyclate have been reported (see WARNINGS, PRECAUTIONS and DOSAGE AND ADMINISTRATION).
AUTONOMIC NERVOUS SYSTEM
Flushing.
HYPERSENSITIVITY
Hypersensitivity reactions consisting of urticaria, angioedema, anaphylactic reaction, anaphylactoid reaction, Henoch-Schonlein Purpura, dyspnea, hypotension, pericarditis, peripheral edema, serum sickness, tachycardia and exacerbation of systemic lupus erythematosus have been reported.
SKIN
Maculopapular and erythematous rashes, photosensitivity reaction, photo-onycholysis, erythema multiforme, Stevens-Johnson syndrome and Toxic epidermal necrolysis have been reported. Dermatitis exfoliative has also been reported but is uncommon (see WARNINGS, skin).
MUSCULO-SKELETAL
Arthralgia and myalgia.
CENTRAL NERVOUS SYSTEM
Headache, fontanelle bulging in infants and benign intracranial hypertension (pseudotumor cerebri) in adults. In relation to benign intracranial hypertension, symptoms included blurring of vision, scotomata and diplopia. Permanent visual loss has been reported (see PRECAUTIONS).
LIVER/BILIARY
There have been reports of hepatotoxicity (including hepatic failure, autoimmune hepatitis and cholestasis) and hepatic function abnormal. As with other tetracyclines, hepatitis, elevation of SGOT or SGPT values have been reported, the significance of which is not known.
HAEMATOLOGIC
Hemolytic anemia, thrombocytopenia, neutropenia, eosinophilia, leukopenia.
IMMUNE SYSTEM DISORDERS
Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS).
HEARING/VESTIBULAR
Tinnitus.
INVESTIGATIONS (Renal Function Analyses)
Blood urea increased (apparently dose related) has been reported.
UROGENITAL
Vaginal candidiasis (see PRECAUTIONS).
OTHERS
When given over prolonged periods tetracyclines have been reported to produce brown- black microscopic discolouration of the thyroid gland. Abnormalities of thyroid function have not been shown to date (see TOXICOLOGY, Subacute Toxicity).
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Specific information on symptoms or treatment of overdosage with doxycycline hyclate is not available. In case of overdosage, discontinue medication. Treatment, therefore, should be symptomatic and gastric lavage may be considered for overdosage with the oral preparation. Dialysis does not alter serum half-life and thus would not be of benefit in treating cases of overdosage.
DOSAGE AND ADMINISTRATION
DOSAGE
EXCEEDING THE RECOMMENDED DOSAGE MAY RESULT IN AN INCREASED INCIDENCE OF SIDE EFFECTS.
Adults
The recommended dosage of oral PRZ-DOXYCYCLINE for the majority of susceptible infections is a single loading dose of 200 mg on the first day of treatment followed by a maintenance dosage of 100 mg once daily at the same time each day thereafter.
In the management of more severe infections (particularly chronic infections of the urinary tract), 200 mg should be given daily throughout the treatment period.
Therapy should be continued for at least 24-48 hours after symptoms and fever have subsided. It should be noted, however, that effective antibacterial levels are usually present 24 to 36 hours following discontinuance of PRZ-DOXYCYCLINE therapy.
When used in streptococcal infections, therapy should be continued for 10 days to prevent the development of rheumatic fever or glomerulonephritis.
For treatment of uncomplicated acute gonococcal infections, the recommended dosage is 200 mg starting and 100 mg in the evening, the first day, followed by 100 mg b.i.d. for 3 days.
For treatment of uncomplicated urethral, endocervical, or vaginal infections in adults associated with Chlamydia trachomatis and Ureaplasma urealyticum: 100 mg, by mouth, twice a day for at least 10 days.
No alteration in recommended dosage schedule need be made when treating patients with impaired renal function.
For management of a suspected drug overdose, contact your regional Poison Control Centre.
ADMINISTRATION
PRZ-DOXYCYCLINE should be given with or after a meal in order to minimize the possibility of gastric upset. Antacids and iron preparations impair absorption and should not be given concomitantly to patients taking oral PRZ-DOXYCYCLINE.
Patients should be advised to take PRZ-DOXYCYCLINE with a full glass of water, to keep in orthostatic position after the administration and not to go to bed within 1-2 hours after the intake.
PHARMACEUTICAL INFORMATION
CHEMISTRY
Trade name(s) PRZ-DOXYCYCLINE
Drug Substance
Proper Name(s): Doxycycline Hyclate
Chemical Name: 2-Naphthacenecarboxamide, 4-(dimethyIamino)-1,4,4a,5,5a,6,11,12a- octahydro-3,5,10,12,12a-pentahydroxy-6- methyl-1,11-dioxo- monohydrochloride, compound with ethanol (2:1), monohydrate,
[4S- (4α,4aα,5α,5aα,6α,12α)]
Structural Formula:
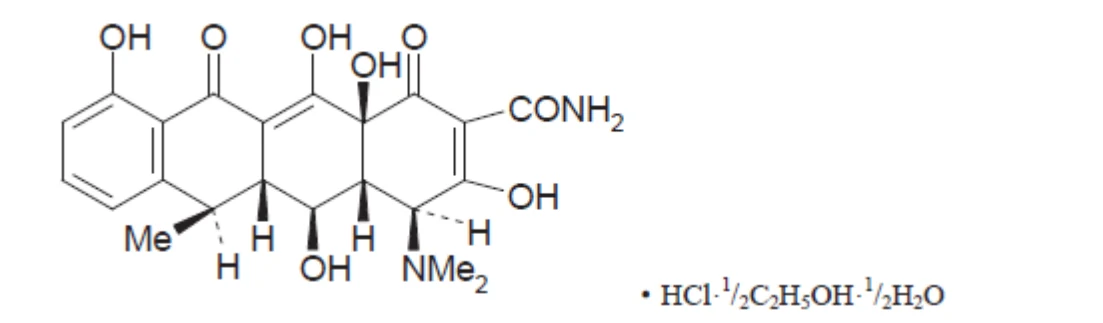
Molecular Formula: C22H24N2O8.HCl.1/2C2H5OH.1/2H2O
Molecular Mass: 512.93 g/mol
Description: A yellow, crystalline powder. Freely soluble in water and in methanol, sparingly soluble in ethanol, practically insoluble in ether and chloroform. pH (1% H2O) is between 2.0 and 3.0. Melting point about200°C
Composition
PRZ-DOXYCYCLINE contain doxycycline hyclate equivalent to 100 mg of doxycycline base. Also contains croscarmellose sodium, HPMC 2910/Hypromellose, lactose monohydrate, Lake Sunset Yellow, Lake Ponceau 4R, magnesium stearate, microcrystalline cellulose, polyethylene glycol, titanium dioxide. Supplied High Density Polyethylene (HDPE) bottle of 100 tablets.
DOSAGE FORMS
AVAILABILITY
PRZ-DOXYCYCLINE 100 mg are available as round, orange, film coated tablets of 100 mg, debossed ‘PRZ’ on one side and ‘DOXY-100’ on other side, containing doxycycline hyclate equivalent to 100 mg of doxycycline, supplied in bottles of 100.
STORAGE
PRZ-DOXYCYCLINE 100 mg: Store at room temperature 15°C to 30ºC. Protect from light. Keep in a tightly closed container.
MICROBIOLOGY
Doxycycline is a broad spectrum antibiotic and has been shown to be active in vitro against the following Gram-negative, Gram-positive and other micro-organisms:
Staphylococcus aureus Klebsiella pneumoniae
Staphylococcus epidermidis (albus)
Streptococcus pyogenes Salmonella typhi
Streptococcus faecalis Salmonella typhimurium
Streptococcus pneumoniae Salmonella enteriditis
Streptococcus viridans Shigella sonnei
Listeria monocytogenes Shigella flexneri
Corynebacterium diphtheriae
Bacillus anthracis
Bacillus subtilis
Neisseria gonorrhoeae
Neisseria catarrhalis
Escherichia coli
Enterobacter aerogenes
Pseudomonas aeruginosa
Haemophilus influenzae
Serratia spp.
Brucella spp.
Proteus spp.
Pasteurella spp.
Mycoplasma pneumoniae
Chlamydia trachomatis
Ureaplasma urealyticum
The drugs in the tetracycline class have closely similar antimicrobial spectra, and cross- resistance among them is common.
SUSCEPTIBILITY TESTING
The Kirby-Bauer method of disc susceptibility testing (using the 30 mcg doxycycline disc) and dilution susceptibility should be interpreted according to the criteria in TABLE 1.
TABLE 1
SUSCEPTIBILITY TEST
ZONE DIAMETER (30 mcg doxycycline disc) mm | M.I.C. mg/L | |
|---|---|---|
Susceptible Intermediate Resistant | ≥ 16 13-15 ≤ 12 | ≤ 4 8 ≥16 |
PHARMACOLOGY
A double blind, balanced, randomized, two way cross-over, single oral dose bioequivalence study comparing PRZ-DOXYCYCLINE (Doxycycline Hyclate)
100 mg tablets (Pharmaris Canada Inc.) to APO-DOXY-TABS (Doxycycline Hyclate) 100 mg tablets (Apotex Inc.) was conducted in 36 healthy, adult, Asian subjects under high-fat, high-calorie fed conditions. All 36 subjects (21 males and 15 females) completed the study and the results are summarized in the table below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Doxycycline (1 × 100 mg) Geometric Mean Arithmetic Mean (CV%) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng •h/mL) | 33592.56 34385.67 (21.94) | 33159.91 33798.14 (20.00) | 101.3 | 95.1 - 107.9 |
AUCI (ng •h/mL) | 35228.50 36093.57 (22.39) | 34922.17 35643.98 (20.71) | 100.9 | 94.6 - 107.6 |
Cmax (ng/mL) | 1538.70 1558.21 (15.81) | 1535.51 1550.20 (14.24) | 100.2 | 93.7 - 107.2 |
Tmax3 (h) | 3.17 (1.00 - 10.00) | 2.84 (1.00 - 6.00) | - | - |
T½4 (h) | 20.83 (24.23) | 20.65 (22.83) | - | - |
1PRZ-DOXYCYCLINE (Doxycycline Hyclate) tablets, 100 mg (Pharmaris Canada Inc.)
2 PrAPO-DOXY-TABS (Doxycycline Hyclate) tablets. 100 mg (Apotex Inc.), purchased in Canada.
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
Serum levels of doxycycline administered orally follow a similar pattern to those obtained with equivalent dosages administered intravenously as shown in TABLE 2. Peak serum levels were slightly higher and occurred earlier following intravenous administration than for oral administration (see TABLE 2).
TABLE 2
Serum levels (mg/L) after oral and I.V. infusion over 60 minutes (0.5 mg/mL) of a total daily dose of 200 mg of doxycycline hyclate on the first day (100 mg every 12 hours) and a dose of 100 mg on the second and third day of administration (22 Male Volunteers/Group).
| Time (hr: min) | Mean Serum Level I.V. | Mean Serum Level Capsules | p |
|---|---|---|---|
| 0:05 | 2.455 | 0.000 | <.001 |
| 1:00 | 1.608 | 1.206 | <.01 |
| 2:00 | 1.551 | 1.643 | |
| 3:00 | 1.421 | 1.482 | |
| 16:00 | 1.131 | 1.124 | |
| 11:00 | 0.800 | 0.815 | |
| 13:00 | 2.397 | 1.107 | <.001 |
| 15:00 | 2.130 | 2.000 | |
| 24:00 | 1.468 | 1.663 | .088 |
| 35:00 | 1.734 | 1.725 | |
| 48:00 | 1.159 | 1.078 | |
| 48:05 | 3.658 | 1.124 | <.001 |
| 49:00 | 2.945 | 2.147 | <.001 |
| 50:00 | 2.848 | 2.406 | .056 |
| 51:00 | 2.760 | 2.436 | |
| 54:00 | 2.150 | 1.989 | |
| 59:00 | 1.665 | 1.516 | |
| 72:00 | 1.021 | 0.945 | |
| 83:00 | 0.700 | 0.709 | |
| 96:00 | 0.426 | 0.399 | |
| 107:00 | 0.247 | 0.234 | |
| Mean area | Mean area | ||
| I.V. | Capsules | ||
| AUC (mg·h/L) | 138 | 128 | |
| 0-107 hr |
Where no p is stated, p>.10
— time of dosing
Doxycycline was rapidly and almost completely absorbed following oral administration. The absorption of doxycycline was not significantly influenced by ingestion of food or milk (see TABLE 3).
TABLE 3
Effect of Food or Milk on Absorption of a Single Oral Dose of Doxycycline 100 mg as Hyclate (5 Male Volunteers/Group).
| AVERAGE SERUM LEVELS (mg/L) | |||
|---|---|---|---|
| Hour s | Breakfas t | Fasting | 6 oz. milk |
| 0 | 0 | 0 | 0 |
| 1 | 0.966 | 1.004 | 1.081 |
| 2 | 1.188 | 1.377 | 1.325 |
| 3 | 1.269 | 1.296 | 1.244 |
| 5 | 1.036 | 1.133 | 1.046 |
| 8 | 0.973 | 0.936 | 0.885 |
| 12 | 0.738 | 0.801 | 0.686 |
| 24 | 0.498 | 0.528 | 0.475 |
Doxycyline is approximately 93% protein bound. The serum half-life of doxycycline is 18 hours. Doxycycline is excreted in the urine (approximately 35-40% of the administered dose) and in the bile. The volume of distribution is approximately 0.7 L/kg. Hemodialysis does not alter the serum half-live.
Excretion of doxycycline by the kidney is about 40%/72 hours in individuals with normal renal function (creatinine clearance about 75 mL/min.). This percentage excretion may fall to a range as low as 1-5%/72 hours in individuals with severe renal insufficiency (creatinine clearance below 10 mL/min.). The serum half-life of doxycycline is not increased, nor does it accumulate in the blood of patients with impaired renal function.
TOXICOLOGY
Doxycycline Hyclate
- a) Acute Toxicity
The acute oral and parenteral toxicity of doxycycline in mice, rats and dogs are as follows:
| LD50 (95% Confidence Limits) mg/kg | ||||||
|---|---|---|---|---|---|---|
| ORAL | I.V. | |||||
| Mice | 1,900 (1696-2128) | 241 (230-253) | ||||
| Rats | >2,000 | 228 (202-258) | ||||
| Dogs | >500 | >100 | ||||
The intraperitoneal LD50's of doxycycline in weanling and newborn rats are 262 (222-309) and 300 (275-327) mg/kg, respectively.
- b) Subacute Toxicity
One to 2 1/2 - month subacute toxicity studies were conducted in rats, hamsters, dogs and monkeys. Doxycycline induced a yellow fluorescence (under ultraviolet light) of bone, teeth, kidney and/or liver, in all animal species tested. In rats, doxycycline produced no toxic effects in doses of up to 500 mg/kg/day for 30 days. In hamsters, doxycycline in dosages of 500 or 250 mg/kg/day produced weight loss and early death, but the 50 mg/kg level (for 30 days) was nontoxic. In dogs, doxycycline in dosages of 250 mg/kg/day for one month produced discoloration of the thyroid gland with the presence of intracytoplasmic granules in follicular acini and occasional amorphous body formation within follicular colloid.
Certain biochemical, functional and histological changes of the liver occurred in the dogs (but not in the rats, hamsters, or monkeys) receiving doxycycline for 30 days at dosage levels of 250 and 50 mg/kg/day, but not at the 25 mg/kg/day level. The biochemical changes in the blood were elevations of alkaline phosphatase, SGPT and/or BSP retention. Histologic changes were confined to bile ductular proliferation and hepatocellular intracytoplasmic inclusion bodies and Kupffer cells swollen with PAS-positive granular material. These changes in the dog were reversible upon drug withdrawal.
Monkeys which received doxycycline at dosages of 25 and 50 mg/kg/day for 1 1/2 to 2 ½ months showed mild yellow ultraviolet fluorescence of liver, kidney and bone, and the presence of small amounts of intracytoplasmic granular material in the thyroid gland.
- c) Chronic Toxicity
In an 18-month chronic toxicity study, rats were fed diets containing doxycycline at levels to provide daily drug intake of 500, 250, 50 and 0 mg/kg. Slight depression of weight gains in some rats receiving the 500 mg/kg/day dose occurred during the middle third of the study. The usual yellow ultraviolet fluorescence of bone, teeth and/or kidneys was seen in rats receiving all levels of doxycycline for 6, 12 or 18 months. Dark to light brown discoloration of the thyroid gland was also noted in rats receiving doxycycline for 12 months at levels of 500 and 250 mg/kg/day, and at 18 months at all levels. The only other change noted was depletion of hepatic glycogen in four rats receiving the highest dose level for 12 months.
Beagle dogs received doxycycline at levels of 10 and 100 mg/kg, six days per week. Moderate to marked elevations of alkaline phosphatase and SGPT (occasionally SGOT) were observed in animals receiving doxycycline, 100 mg/kg/day. One of two dogs receiving doxycycline, 100 mg/kg/day, displayed mild bile ductular proliferation and hepatocellular inclusion bodies after 5 months (biopsy sample) and 12 months (necropsy sample). Administration of doxycycline for 5 and 12 months at a level of 100 mg/kg/day and for 12 months at a level of 10 mg/kg caused black and brownish discoloration of the thyroid gland, respectively, with intracytoplasmic granules. Other changes included vasodilatation and focal areas of necrosis of the mucosa of the pyloric and fundic stomach of dogs, and yellow ultraviolet fluorescence of teeth and bones of animals at 100 mg/kg/day dose levels of doxycycline.
Additional groups of 4 beagles each received doxycycline in dosages of 5, 1 and 0 mg/kg/day for 6 months. The only abnormal findings were slight elevations of SGPT values in 3 dogs at the 5 mg/kg level at 180 days.
In a one year chronic toxicity study, groups of four rhesus monkeys each received doxycycline in oral doses of 0, 5, 25 and 50 mg/kg/day, respectively. Oral dosage of 100 mg/kg produced severe gastrointestinal symptoms, e.g., vomiting and diarrhea. In one out of 4 monkeys receiving the 50 mg/kg/day dose, occasional anorexia and diarrhea were observed during the first six months.
Significant pathologic changes noted in monkeys sacrificed after receiving doxycycline for 1 year at dose levels of 50 mg/kg/day were: 1) grossly, very light brown discoloration of the thyroid gland in one of the four monkeys, and 2) microscopically, brownish intracytoplasmic inclusions in the acinar cells of thyroid follicles of three out of four monkeys. Bone and dentin exhibited slight to moderate ultraviolet fluorescence.
Two monkeys, in another study, receiving the 25 mg/kg/day dosage, were sacrificed after 6 and 8 months on test, respectively. Significant gross and histopathologic findings were slight yellow ultraviolet fluorescence of the endosteum and periosteum of bone, and microscopic appearance of small amounts of granular intracytoplasmic material in the acinar cells of thyroid follicles.
The highlights of the chronic toxicity studies can be summarized as follows:
- 1) Discoloration of the thyroid gland, with deposition of intracytoplasmic granules in the acinar cells of the follicle. Thyroid function, however, did not seem to be affected. This phenomenon appears to be a result of the interaction of the antibiotic with the active iodinating system of the gland.
- 2) Yellow staining of bones and teeth, which is thought to be due to formation of a tetracycline- calcium-phosphate complex.
Otherwise doxycycline was well tolerated by the rat and monkey at doses up to and including 500 and 50 mg/kg/day for 18 and 12 months, respectively. In dogs, however, repeated daily oral administration of large doses of doxycycline resulted in certain hepatic functional and histopathologic changes which are reversible after drug withdrawal. No adverse hepatic effects were noted in the hamster (1 month), rats (18 months) or monkeys (12 months) for doses up to and including 500, 500 and 50 mg/kg/day, respectively. In view of this and in view of the lack of notable toxicity in our wide human clinical program, it is our opinion that this is a species specific phenomenon, for the dog only.
- d) Reproduction and Teratogenic Studies
Doxycycline has no teratologic effects in rats, rabbits or monkeys.
Breeding rats received doxycycline by gavage in doses of 50 and 250 mg/kg/day prior to and throughout two consecutive litters. There was no evidence that doxycycline interfered with the reproductive process in rats.
Pregnant female white New Zealand rabbits received doxycycline orally in doses of 8 and 40 mg/kg/day, respectively, from day 8 to day 16 of pregnancy. Spina bifida and partial anencephaly in one pup each in the control and the 8 mg/kg group, respectively, are believed to be spontaneous and drug-induced.
In teratogenic studies using a limited number of monkeys, doxycycline, in doses ranging from 1 to 50 mg/kg/day, did not produce any teratologic effects.
Doxycycline Monohydrate
With bulk doxycycline monohydrate administered in a 10% aqueous suspension, the oral LD50 for albino male mice was greater than 5000 mg/kg.
DoxycycIine Hyclate with Ascorbic Acid
Studies in mice and rats showed the LD50 of doxycycline (as hyclate) I.V to be 75 mg/kg in mice and 88 mg/kg in rats of doxycycline (using a preparation of doxycycline hyclate equivalent to 100 mg of doxycycline with 480 mg of ascorbic acid as a sterile powder).
No signs of drug toxicity were seen in dogs receiving 20 to 21 daily doses of doxycycline (as hyclate) I.V. at a dose level of 5 mg/kg when administered as a 0.5% solution at a rate of 1 mg/kg/min. Dogs receiving 14, 16 or 17 daily intravenous doses of 10 mg doxycycline (as hyclate) I.V. per kg of bodyweight, or 4 daily 60 minute infusions of 300 mg doxycycline (as hyclate) I.V., or 300 mg degraded doxycycline (as hyclate) I.V. evidenced serum alkaline phosphatase and serum glutamic pyruvic transaminase elevations. No morphological basis for these enzyme elevations was established although moderate bile ductular proliferation was seen in 1 of 2 dogs receiving 4 daily intravenous infusions of degraded doxycycline (as hyclate) I.V.
In 8 dogs receiving daily intravenous doses of 10 mg doxycycline (as hyclate)
I.V./kg/day (0.5% solution), 5 of 24 vessels used for injections evidenced degrees of thrombosis with recanalization.
Thrombosis in 3 of 6 sites occurred in 2 dogs receiving infusions of degraded doxycycline (as hyclate) I.V. (30 mg/kg-0.5% solution). Injection site thrombosis did not occur in 6 dogs (18 sites) receiving daily doses of 5 mg doxycycline (as hyclate) I.V./kg bodyweight administered as a 0.5% solution at a rate of 1 mg/kg/min (approximately 1 mL/min).
Studies to date indicate that the maximum tolerated intravenous daily dose of doxycycline (as hyclate) I.V. in dogs for 21 consecutive days is 5 mg/kg/day when administered as a 0.5% solution at a rate of 1 mg/kg/min.
BIBLIOGRAPHY
DOXYCYCLINE - GENERAL
- 1. Aitchison WRC, Grant IWB, Gould JC. Treatment of acute exacerbations in chronic bronchitis. Brit J Clin Pract 1968; 22:343-45.
- 2. Barteaux JW. Clinical experience with doxycycline, a new tetracycline. Intl J Clin Pharmacol Ther Toxicol 1968; 1:404-405.
Clinical Research Reports, Medical Division, Pfizer Co. Ltd. Montreal
- 1. Colemore JP, Braden B, Wilkerson R. Effectiveness of doxycycline treatment in chronic urinary tract infections. Antimicrob Agents Chemother 1966; 118-120.
- 2. Domescik G, McLone DG, Scotti A, Mackey DM. Use of a single dose of doxycycline monohydrate for treating gonorrheal urethritis in men. Public Health Reports 1969; 84:182-83.
- 3. Gallai Z, Sylvestre L, Breault JP. Doxycycline in the treatment of acute gonorrhea in couples. Presented at the 6th International Congress of Chemotherapy. Aug. 11-14 1969, Tokyo, Japan.
- 4. Gallai Z, Sylvestre L, Breault JP. Instant treatment of acute gonococcal urethritis with doxycycline. Presented at the second world congress of the Int. Soc. of Tropical Dermatology. Aug. 16-18 1969, Kyoto, Japan.
- 5. Grossan M. Management of infections of the ear, nose and throat with a new tetracycline antibiotic: doxycycline. EENT Month 1968; 47:321-24.
- 6. Hany A, Petite J, Robert M, Fabre J. La doxycycline en clinique (fre). Chemotherapy 1968; 13(Suppl):59-63.
- 7. Hinton NA. The effect of oral tetracycline HCI and doxycycline on the intestinal flora. Curr Ther Res 1970; 12:341-52.
- 8. Huang NN, Shang K, Basavanand N. Doxycycline treatment of children with cystic fibrosis of pancreas. Antimicrob Agents Chemother 1966; :127-133.
- 9. Isenberg D. In Vitro activity of doxycycline against bacteria from clinical material. Appl Microbiol 1967; 15(5):1074-78.
- 10.
Kalfopoulos P at al. Absorption digestive de la doxycycline chez I'homme comparee
- a celle des autres tetracyclines. Policlinique de medecine (Pr. J. Fabre) et Clinique Medicale Therapeutique (Pr. R.S. Mach) de l'universite de Geneve.
- 11. Lassus A. The treatment of gonorrhea with doxycycline as a single dose. Chemotherapy 1968; 13(6):366-68.
- 12. Lundberg C, Gullers K, MaImborg AS. Antibiotics in sinus secretions. Lancet 1968; 2:107- 108.
- 13. Migliardi JR, Schach von Wittenau M. Pharmacokinetic properties of doxycycline in man. In: Proceedings of the 5th Intl Cong of Chemother, Vienna, pp. 167-172, 1967.
- 14. Monnier J, Bourse R, Onfray J. Doxycycline: In Vitro bacteriostatic activity and serum levels in man. Antibiotica 1966; 4:268-82.
- 15. Neuvonen PJ, Gothoni G, Hackman R, Bjorksten KAF. Interference of iron with the absorption of tetracyclines in man, Brit Med J 1970; 4:532-34.
- 16. Pankey GA. Sinusitis. Current Therapy 1971, edited by Howard F. Conn. M.D., W.B. Saunders Co. Toronto, pp. 125-27.
- 17. Roberge R, Lauchance W. Etude de la doxycycline en clinique et en laboratoire. Saguenay Med 1968; 15:101-107.
- 18. Rosenblatt JE, Barrett JE, Brodie JL, Kirhy WM. Comparison of In Vitro Activity and Clin. Pharm. of Doxycycline and other tetracyclines. Antimicrobial Agents Chemother 1966; 6:134-41.
- 19. Schach von Wittenau M. Some pharmacokinetic aspects of doxycycline metabolism in man. Chemotherapy 1968; 13(Suppl):41-50.
- 20. Steigbigel NH, Reed CW, Finland M. Susceptibility of common pathogenic bacteria to seven tetracycline antibiotics in vitro. Amer J Med Sci 1968; 255:179-95.
- 21. Sylvestre L, Gallai Z. Traitement minute de la gonorrhee par un nouveau derive de l'oxytetracycline: la doxycycline. Union Med Can 1968; 97:639-40.
- 22. Sylvestre L, Gallai Z. Instant treatment of gonorrhea with a new oxytetracycline derivative: doxycycline (preliminary report), Intl Clin Pharm Ther Toxicol 1968; 1:401-403.
- 23. Williamson GM. Laboratory studies of Vibramycin (doxycycline) International Symposium. New resource in antibiotic therapy: doxycycline, Buenos Aires, June 14-15, 1967.
- 24.
Williamson GM. The in vitro activity of Vibramycin (doxycycline). Chemotherapy
- 1968; 13(Suppl):1-6.
DOXYCYCLINE IN RENAL INSUFFICIENCY
- 1. Edel. Doxycycline in renal insufficiency. VI Intern Congress of Chemotherapy. Tokyo, August 1969.
- 2. Fabre J, Pitton JS, Kunz JP. Distribution and excretion of doxycycline in man. Chemotherapy 1966; 11:73-85.
- 3. Fabre J Pitton JS, Virieux C, Laurencet FL, Bernhardt JP, Godel JC. Doxycycline absorption, distribution of a new broad-spectrum antibiotic in man. Schweiz Med Wochenschr 1967; 97(28):915-24.(translation)
- 4. Fabre J. Medicaments et fonctions renales. HeIv Med Acta 1967; 47(34):24-41.
- 5. Fabre J, Kunz JP, Virieux C, Laurencet JL, Pitton JS. Le comportement de la doxycycline chez I'homme. Chemotherapy 1968; 13(Suppl):2340.
- 6. Giromini M, Wasem R, Merier G, Fabre J. Influence de I'anurie et des hemodialyses sur le comportement des antibiotiques. Praxis 1969; 38:1181-87.
- 7. Laurencet FL, Fabre J. Influence de l'insuffisance renale sur le comportement de la doxycycline. J Urol Nephrol 1968; 74:1038-47.
- 8. Little PJ, Bailey FIR. Tetracyclines and renal failure. N Z Med J 1970; 72:183-84.
- 9. Mahon WA, Wittenberg JVP, Tuffnel PG. Studies on the absorption and distribution of doxycycline in normal patients and in patients with severely impaired renal function. Can Med Assoc J 1970; 103:1031-34.
- 10. Merier G, Laurencet FL, Rudhardt M, Chuit A, Fabre J. Behaviour of doxycycline in renal insufficiency. HeIv Med Acta 1969; 35:124-34.
- 11. Porpaczy P. Doxycycline (Vibramycin) in renal insufficiency. Wien Klin Wschr. 1970; 82:710-14.
- 12. Ritzerfeld W, Westerboer S, Geller R. Doxycyclin in serum, diallysate and urine in patients with renal functional disease. Intl J Clin Pharmacol Ther Toxicol 1970; 3:325-29.
- 13. Schach von Wittenau M, Twomey TM. The disposition of doxycycline by man and dog. Chemotherapy 1971; 16:217-28.
- 14.
Schach von Wittenau, Twomey TM, Swindell AC. The disposition of doxycycline by
- the rat. Chemotherapy. 1971; 17(l):26-39.
- 15. Stein W, Schoog M, Franz HE. Doxycycline serum levels in patients with renal insufficiency (Ger). Arzneim Forsch (Drug Research). 1969; 19:827-28.
- 16. Vibramycin. Pharmacology Actua September 1969; 1(8): 8.
- 17. Zech P, Traeger J. Tolerance de la doxycycline dans l'insuffisance renale severe. Lyon Med 1969; 999:943-45.
DOXYCYCLINE IN GONORRHEA
- 1. Caldwell JG, Wessler S, Avioli LV. Current therapy of gonorrhea. JAMA 1971; 218:714-17.
- 2. Ketterer WA. Homosexuality and venereal disease. Medical Aspects of Human Sexuality. December 1971; 1(4):43-50.
- 3. Neumann HH, Baecker JM. Treatment of gonorrhea. Penicillin or tetracyclines? JAMA 1972; 219:471-74.
- 4. Smart WH, Lighter AC. Gonorrhea, the silent epidemic. A Scientific Exhibit, 23rd Clinical Convention of the A.M.A., Denver, Colorado. November 30-December 3, 1969.
DOXYCYCLINE IN CHLAMYDIA TRACHOMATIS AND UREAPLASMA UREALYTICUM INFECTlONS
- 1. Cunha BA, Comer JB, Jonas M. Symposium on antimicrobial therapy: The tetracyclines. Med Clin North Am 1982;66(l):293-302.
- 2. Health and Welfare Canada, Bureau of Epidemiology. Canada Diseases Weekly Report 1981;7(21):101-108.
- 3. Jaffe HW. Nongonococcal urethritis: Treatment of men and their sexual partners. Rev Infect Dis 1982;4(6 Suppl):S772-S777.
- 4. Johannisson G, Sernryd A, Lycke E. Susceptibility of Chlamydia trachomatis to antibiotics in vitro and in vivo. Sex Trans Dis 1979;6(2):50-57.
- 5. Lassus A, Perko RL, Stubb S, Mattila R, Jansson E. Doxycycline treatment of nongonococcal urethritis with special reference to T-strain mycoplasmas. Br J Vener Dis 1971;47:126-130.
- 6.
McNeil PJ, Fiumara NJ, Caliando JJ, Benes S, McCormack WM. Evaluation of
- doxycycline hyclate in the treatment of nongonococcal urethritis. Sex Transm Dis 1981;8(2 Suppl):127-131.
- 7. Root TE, Edwards LID, Spengler PJ. Nongonococcal urethritis: A survey of clinical and laboratory features. Sex Transm Dis 1980;7(2):59-65.
- 8. Siboulet A, Bohbot JM, Catalan F, Siboulet A, Henry-Suchet J. Les infections uretro- genitales a Chlamydia trachomatis. Bull Mem Soc Med Paris 1982;(4):103-13.
- 9. Thompson SE, ed. Urogenital chlamydial infections: an international perspective with a focus on doxycycline. Proceedings of a symposium held in conjunction with The Second World Congress of Sexually Transmitted Diseases, Paris, June 1986. Clin Ther 1986;9(Suppl A):1-39.
- 10. Product Monograph-Vibramycin Capsules, doxycycline hyclate capsules doxycycline 100 mg and Vibra-Tabs Film Coated Tablets, doxycycline hyclate tablets doxycycline 100 mg. Pfizer Canada Inc. Date of Revision: December 22, 2015.
- 11. Product Monograph- APO-DOXY and APO-DOXY-TABS (doxycycline hyclate). APOTEX Inc., Submission Control No. 194708, Date of Revision: November 29, 2016.