


Product Monograph - Relaxa
INDICATIONS AND CLINICAL USE
RelaxaTM is indicated for the treatment of occasional constipation in adults (≥ 18 years).
CONTRAINDICATIONS
RelaxaTM should not be used in patients who are hypersensitive to polyethylene glycol.
RelaxaTM should not be used in patients with a known or suspected bowel obstruction.
RelaxaTM is contraindicated for use in children under 18 years of age unless advised by a physician.
WARNINGS AND PRECAUTIONS
General:
RelaxaTM should not be used in subjects with kidney disease except under the supervision of a physician.
Patients with symptoms suggestive of bowel obstruction, appendicitis, or inflamed bowel, (fever, nausea, vomiting, abdominal pain or bloating) should consult a physician to rule out these
RelaxaTM Page 4 of 10
conditions before initiating RelaxaTM therapy (see contraindications).
Patients presenting with symptoms of constipation, should be advised that changes to lifestyle measures like adequate fibre and fluid intake, and regular exercise can result in consistent bowel habits, and these measures should be tried before attempting any medical therapy for constipation.
Patients should not take any type of laxative for more than one (1) week, unless recommended by a physician. Overuse or extended use of any laxative may cause dependence for bowel function.
If no constipation relief is seen, the patient should be instructed to see a physician.
RelaxaTM should not be taken within two (2) hours of another medicine because the desired effect of the other medicine may be reduced.
Relaxa may result in a potential interactive effect when used with starch-based food thickeners. The PEG ingredient counteracts the thickening effect of starch, effectively liquefying preparations that need to remain thick for people with swallowing problems. This warning applies to all polyethylene glycol (PEG) containing-products.
Patients with severe diarrhea symptoms should stop using RelaxaTM and contact a physician immediately.
Elderly patients experiencing diarrhea should stop using Relaxa™ and contact a physician immediately.
Patients developing an allergic reaction (e.g. rash, swelling, difficulty breathing) should stop using RelaxaTM and contact a physician immediately.
Special Populations:
Pregnant Women: No clinical studies have been performed in pregnant women, therefore RelaxaTM should be avoided in pregnant women unless clearly needed and directed by a physician.
Nursing Women: No clinical studies have been performed in nursing women, therefore RelaxaTM should be avoided in nursing women unless clearly needed and directed by a physician.
Pediatrics: The safety and efficacy of RelaxaTM for use in children under age 18 years have not been established. Do not use in children (<18 years of age), unless advised by a physician.
RelaxaTM Page 5 of 10
Elderly Patients: No dose adjustment is recommended for elderly patients solely on the basis of their age. However, if diarrhea occurs, RelaxaTM should be discontinued.
MONITORING AND LABORATORY TESTS
No clinically significant changes in laboratory values have been reported.
ADVERSE REACTIONS
Occasional nausea, abdominal cramping or bloating and flatulence have been reported. High doses may also cause loose, watery and more frequent stools, especially in the elderly.
Rare instances of severe allergic reactions have been reported in users of other medications containing polyethylene glycol 3350.
DRUG INTERACTIONS
No specific drug interactions have been demonstrated. However, the desired effect of othe r medications may be reduced if taken with laxatives. Avoid taking Relaxa ™ within two (2) hours of taking another medication.
DOSAGE AND ADMINISTRATION
Adults:
The normal dose in adults is 17 grams (about 1 heaping tablespoon) of RelaxaTM per day (or as directed by a physician) to be stirred in a cup (250 mL or 8 ounces) of water, juice, soda, soft drink, coffee, tea, or any other non-alcoholic beverage until completely dissolved.
Treatment for two to four days (48 to 96 hours) may be required to produce a bowel movement. This product should be used for up to one week or as directed by a physician.
Special Patient Populations:
Pregnant or Nursing Women: RelaxaTM should be avoided in pregnant women or nursing women unless clearly needed and directed by a physician (see WARNINGS AND PRECAUTIONS).
RelaxaTM Page 6 of 10
Elderly Patients: No dose adjustment is recommended for elderly patients solely on the basis of their age. However, if diarrhea occurs, RelaxaTM should be discontinued (see WARNINGS AND PRECAUTIONS).
Pediatrics: The safety and efficacy of RelaxaTM for use in children under 18 years have not been established. Do no use in children (<18 years of age), unless advised by a physician (see WARNINGS AND PRECAUTIONS).
OVERDOSAGE
There have been no reports of accidental overdosage. In the event of an overdose, dehydration due to diarrhea may result. The patient should stop taking RelaxaTM and drink plenty of water.
ACTION AND CLINICAL PHARMACOLOGY
Polyethylene glycol 3350 is an osmotic agent which causes water to be retained with the stool.
Constipation relief with polyethylene glycol 3350 has been demonstrated in subjects with occasional constipation. Results from clinical studies have shown that it may take 2 to 4 days to produce a bowel movement.
An in- vitro study showed indirectly that polyethylene glycol 3350 was not fermented into hydrogen or methane by the colonic microflora in human feces. Polyethylene glycol 3350 appears to have no effect on the active absorption or secretion of glucose or electrolytes. There is no evidence of tachyphylaxis.
STORAGE AND STABILITY
Store in a dry place at room temperature at 15° - 30°C (59° - 86°F).
SPECIAL HANDLING INSTRUCTIONS
No special handling is required.
DOSAGE FORMS, COMPOSITION AND PACKAGING
RelaxaTM is available as a powder form for oral administration after dissolution in water, juice, soda, coffee, tea, or any other non-alcoholic beverage.
RelaxaTM is available in bottles of 510 g and cartons of 30 with 17 g sachets. The dosing scoop included with each bottle is pre-measured for a single dose of 17 grams when filled to the rim.
Composition of Product: RelaxaTM contains polyethylene glycol 3350.
RelaxaTM Page 7 of 10
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance:
Proper name: Polyethylene glycol 3350 Chemical name: Polyethylene glycol
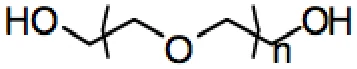
Molecular formula and molecular mass: HO[~CH2CH2O~]nH
Structural formula:
Physicochemical properties: White powder, fully soluble in water.
CLINICAL EVIDENCE
A number of published studies have been performed to investigate the efficacy and safety of polyethylene glycol for constipation.
A study conducted by Di Palma et al (2007) compared polyethylene glycol 3350 to Zelnorm (tegaserod) in the treatment of patients with chronic constipation. Two hundred and thirty seven
(237) subjects were randomized in an open label study to either 17g of polyethylene glycol 3350 in a single daily dose or 6 mg tegaserod b.i.d. for 28 days. Subjects were enrolled based on the modified ROME criteria as noted in the above trial. The primary efficacy endpoint was calculated based upon the patient reported ROME criteria during the week.2
Fifty percent of the polyethylene glycol 3350 subjects were responders compared to 30.8% of the tegaserod subjects. The authors concluded that while polyethylene glycol 3350 and tegaserod are safe for use in chronic constipation polyethylene glycol has superior efficacy and caused fewer side effects such as headache and produced greater improvement of constipation symptoms.
Di Palma et al (2002) also evaluated the safety and effectiveness of three single doses of polyethylene glycol 3350 laxative (51, 68, and 85 g) and placebo in constipated patients. Subjects who met one or more of the ROME II criteria and who had satisfactory stool less than three times per week, were enrolled into the study. Twenty–four adult subjects were randomized to receive a single dose of placebo or polyethylene glycol laxative at doses of 51, 68 or 85 g. Frequency of bowel movement was the primary efficacy variable compared across doses.
RelaxaTM Page 8 of 10
Secondary efficacy variables included the various ROME II criteria.
The average time to first bowel movement after a 68-g dose of polyethylene glycol 3350 was
14.8 hours compared to 27.3 hours for placebo. Complete evacuation was reported by 100% of subjects for the second bowel movement in the polyethylene glycol group compared to 60% in the placebo group.
The investigation showed that a 68-g dose of polyethylene glycol 3350 laxative provided safe and effective relief of constipation in adults within a 24 -h period, without loss of control.4
Di Palma et al (2007) performed a randomized placebo controlled trial to investigate the safety and efficacy of polyethylene glycol over a six month period. Subjects were randomized to either placebo or polyethylene glycol as a single daily dose of 17g for 6 months. Constipation was defined based on modified ROME criteria, where on average satisfactory stool was less frequent than three per week and one or more of the ROME criteria were met; straining in more than 25% of defecations, lumpy or hard stools in more than 25% of defecations, and a sense of incomplete evacuation in more than 25% of defecations.1
A total of 309 subjects were randomly assigned in a 2:1 ratio to polyethylene glycol or placebo. The ITT population consisted of 304 subjects as two subjects did not receive any medication after randomization. Study subjects treated with polyethylene glycol achieved a statistically significant benefit over placebo (p<0.001). Polyethylene glycol treatment resulted in a rapid increase in the number of successfully treated patients in the first month, with the maximum response by the second month. The difference between polyethylene glycol and placebo was statistically significant at all study months.
Di Palma et al (2000) also conducted a randomized, multicenter, placebo-controlled study to evaluate the safety and efficacy of polyethylene glycol 3350. A total of 151 adults with less than 2 bowel movements in a 7-day period were randomized to receive polyethylene glycol -3350, 17 g or placebo for 14 days. Effective treatment was defined as >3 bowel movements per 7-day period. By the second week of treatment, polyethylene glycol resulted in 4.5 bowel movements weekly compared to placebo at 2.7 movements weekly. No statistically or clinically significant differences between placebo and laxative groups were detected for laboratory measurements.
These authors confirmed that polyethylene glycol laxative is safe and effective for the short term treatment of constipation as it increases bowel movement frequency and was well tolerated by study subjects.5
Cleveland et al (2001) evaluated the safety and effectiveness of polyethylene glycol 3350 in patients reporting a history of constipation. Twenty-three male and female patients over the age of 18 with a known history of constipation were enrolled in this study. Patients were randomly assigned to receive either polyethylene glycol or placebo over a 14-day treatment period, followed by a second 14 day period with an alternate test article. The laxative solution contained 17g of polyethylene glycol 3350 per 250 mL dose.
RelaxaTM Page 9 of 10
Polyethylene glycol laxative therapy resulted in a dramatic increase in bowel movement frequency compared with placebo. This effect was most pronounced by the second week of therapy, when the mean weekly bowel movement frequency increased to once per day (7.0/week) for polyethylene glycol laxative versus once every second day (3.6/week) for placebo (P = 0.0001). 6
Patients with mild constipation had twice as many bowel movements as those with severe constipation. All of the mildly constipated patients rated polyethylene glycol therapy as “effective”.
The authors concluded that polyethylene glycol laxative is an effective agent for patients who are typically treated for constipation, as well as for patients with more severe disease.6
Ramkumar et al conducted a systematic literature review of randomized, controlled trials addressing the efficacy and safety of various medical therapies in adult patients with chronic constipation. Polyethylene glycol therapy was given a Grade A recommendation (good evidence in support of the use of a modality in the treatment of constipation) and a Level 1 (good evidence – consistent results from well-designed, well-conducted studies) evidence of strength.7
TOXICOLOGY
Polyethylene glycols are generally considered to be inert and possess a low order of toxicity in animals and humans. Administration of 0.5 g high-molecular mass (polyethylene glycol)/kg Body Weight in the form of an aqueous solution caused no visible signs of intoxication. No mortality occurred. Histological examination revealed small areas of round-cell infiltration, expanded vessels in the kidneys, and a plethoric spleen. A dose of 2.5 g/kg Body Weight of polyethylene glycol with molecular mass (M= 2,000000 and 7,000000) was not lethal to rats or mice. In the last case, the acute effect threshold was 0.5 g/kg Body Weight. In the same doses, polyethylene glycol synthesized on an organocalcium compound was not lethal. The acute effect threshold was not established.3
Rats and mice received 3.1 g polyethylene glycol/kg Body Weight in aqueous solutions with molecular mass (M = 5,000000) for 12 months. There were no manifestations of toxic action. 2
Reproductive Toxicity:
In a 2-year feeding study, oral and parenteral administration of polyethylene glycol caused no effect on reproduction.8
RelaxaTM Page 10 of 10
REFERENCES
- 1. DiPalma, JA, Cleveland MB, McGowan J, Herrera JL. A randomized, multicenter, placebo-controlled trial of polyethylene glycol laxative for chronic treatment of chronic constipation. Am J Gastroenterol. 2007 Jul;102(7):1436-41.
- 2. DiPalma, JA, Cleveland MB, McGowan J, Herrera JL. A randomised multicentre comparison of polyethylene glycol laxative and tegaserod in treatment of patients with chronic constipation. Am J Gastroenterol. 2007 Sep;102(9):1964-71.
- 3. Sheftel, VO. Polyethylene Glycols Indirect Food Additives and Polymers: Migration and Toxicology. Lewis 2000 pp.1114-1116.
- 4. Di Palma JA, Smith JR, Cleveland MvB Overnight Efficacy of Polyethylene Glycol Laxative. Am J Gastroenterol. 2002 Jul; 97(7); 1776-79.
- 5. DiPalma, JA, DeRidder, PH, Orlando, RC, Kolts, BE, Cleveland M vB. A randomized, placebo-controlled, multicenter study of the Safety and Efficacy of a New Polyethylene Glycol Laxative. Am J Gastroenterol. 2000 Feb;95(2):446-450.
- 6. Cleveland vB. M, Flavin DP, Ruben RA, Epstein RM, Clark GE New Polyethylene Glycol Laxative for Treatment of Constipation on Adults: A randomized double-blind, placebo controlled study. Southern Medical Journal 2001 May; Vol. 94, No. 5; 478-81.
- 7. Ramkumar D, Rao Satish SC Efficacy and Safety of Traditional Medical Therapies for Chronic Constipation: Systematic Review. Am J Gastroenterol. 2005;100;936-71.
- 8. Pashankar DS, Bishop WP. Efficacy and optimal dose of daily polyethylene glycol 3350 for treatment of constipation and encoporesis in children. J Pediatr. 2001 Sep;139(3):428- 32.
Last revised: August 26, 2025