


Product Monograph - Sandoz Imatinib
RECENT MAJOR LABEL CHANGES
| Section 7 Warnings and Precautions, Musculoskeletal | 12/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 5
2 CONTRAINDICATIONS ................................................................................................. 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 5
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 6
4.5 Missed Dose ............................................................................................................. 9
5 OVERDOSAGE .............................................................................................................. 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................... 10
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
7.1 Special Populations ................................................................................................ 17
7.1.1 Pregnant Women ............................................................................................. 17
7.1.2 Breast-feeding .................................................................................................. 17
7.1.3 Pediatrics .......................................................................................................... 17
7.1.4 Geriatrics .......................................................................................................... 17
8 ADVERSE REACTIONS ................................................................................................ 18
8.1 Adverse Reaction Overview ................................................................................... 18
8.2 Clinical Trial Adverse Reactions ............................................................................. 18
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .................................................... 29
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 29
8.5 Post-Market Adverse Reactions ............................................................................. 32
9 DRUG INTERACTIONS ................................................................................................ 33
9.2 Drug Interactions Overview ................................................................................... 33
9.3 Drug-Behavioural Interactions ............................................................................... 33
9.4 Drug-Drug Interactions .......................................................................................... 33
9.5 Drug-Food Interactions .......................................................................................... 37
10 CLINICAL PHARMACOLOGY ....................................................................................... 37
10.1 Mechanism of Action ....................................................................................... 37
10.2 Pharmacodynamics .......................................................................................... 37
10.3 Pharmacokinetics ............................................................................................. 38
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 41
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 41
PART II: SCIENTIFIC INFORMATION ....................................................................................... 41
13 PHARMACEUTICAL INFORMATION ............................................................................ 41
14 CLINICAL TRIALS ........................................................................................................ 42
14.1 Clinical Trials by Indication .............................................................................. 42
Chronic Myeloid Leukemia .............................................................................................. 42
Acute Lymphoblastic Leukemia ....................................................................................... 48
Myelodysplastic/Myeloproliferative Diseases (MDS/MPD) ............................................ 50
Aggressive sub-types of Systemic Mastocytosis (ASM and SM-AHNMD) ....................... 50
Hypereosinophilic Syndrome and/or Chronic Eosinophilic Leukemia (HES/CEL) ............ 51
Dermatofibrosarcoma Protuberans (DFSP) ..................................................................... 52
Unresectable and/or Metastatic Malignant Gastrointestinal Stromal Tumors .............. 52
Adjuvant Treatment of GIST ............................................................................................ 55
15 MICROBIOLOGY ........................................................................................................ 57
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 57
PATIENT MEDICATION INFORMATION .................................................................................. 60
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Sandoz Imatinib (imatinib mesylate) is indicated for:
- the treatment of adult patients with newly diagnosed, Philadelphia chromosome-positive, chronic myeloid leukemia (CML) in chronic phase (see 14 CLINICAL TRIALS).
- the treatment of adult patients with Philadelphia chromosome-positive chronic myeloid leukemia (CML) in blast crisis or accelerated phase, or in chronic phase after failure of interferon- alpha therapy (see 14 CLINICAL TRIALS).
- use as a single agent for induction phase therapy in adult patients with newly diagnosed Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ALL) (see 14 CLINICAL TRIALS).
- the treatment of adult patients with relapsed or refractory Ph+ALL as monotherapy (see 14 CLINICAL TRIALS).
- the treatment of adult patients with myelodysplastic/myeloproliferative diseases (MDS/MPD) associated with platelet-derived growth factor receptor (PDGFR) gene re-arrangements (see 14 CLINICAL TRIALS).
- the treatment of adult patients with aggressive sub-types of systemic mastocytosis (ASM and SM-AHNMD1) without the D816V c-Kit mutation. If c-Kit mutational status in patients with ASM or SM-AHNMD1 is not known or unavailable, treatment with Sandoz Imatinib may be considered if there is no satisfactorily response to other therapies (see 14 CLINICAL TRIALS).
- the treatment of adult patients with advanced hypereosinophilic syndrome (HES) and/or chronic eosinophilic leukemia (CEL) with FIP1L1-PDGFRα rearrangement (see 14 CLINICAL TRIALS).
- the treatment of adult patients with unresectable, recurrent and/or metastatic dermatofibrosarcoma protuberans (DFSP) (see 14 CLINICAL TRIALS).
- the treatment of adult patients with Kit (CD117) positive unresectable and/or metastatic malignant gastrointestinal stromal tumors (GIST) (see 14 CLINICAL TRIALS).
- the adjuvant treatment of adult patients who are at intermediate to high risk of relapse following complete resection of Kit (CD117) positive GIST (see 14 CLINICAL TRIALS).
1 ASM: Aggressive systemic mastocytosis; SM-AHNMD: Systemic mastocytosis with an associated clonal hematological non-mast-cell disorder.
1.1 Pediatrics
Pediatrics (<18 years of age): Health Canada has authorized an indication for pediatric use for the treatment of pediatric patients with newly diagnosed, Philadelphia chromosome-positive, chronic myeloid leukemia (CML) in chronic phase (see 7.1.3 Pediatrics).
There is no experience with the use of Sandoz Imatinib in pediatric patients with CML under 2 years of age. There is very limited to no experience with the use of Sandoz Imatinib in pediatric patients in other indications.
1.2 Geriatrics
Geriatrics (≥65 years of age):
No clinically meaningful differences in effectiveness was observed between older and younger patients in the CML phase II study (see 7.1.4 Geriatrics).
No clinically meaningful differences in safety was observed between older and younger patients in the adjuvant GIST study (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
- Sandoz Imatinib (imatinib mesylate) is contraindicated in patients with hypersensitivity to imatinib or to any other component of Sandoz Imatinib (see 6 DOSAGE FORMS, STRENGTHS, and COMPOSITION AND PACKAGING).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Sandoz Imatinib should only be administered under the supervision of a physician experienced with the use of chemotherapy and with treatment of hematological malignancies and/or malignant sarcomas including gastrointestinal stromal tumors (GISTs) and dermatofibrosarcoma protuberans (DFSP). The following are significant adverse drug reactions identified in clinical trials conducted with Sandoz Imatinib:
|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Therapy should be administered under the supervision of a physician experienced in the treatment of patients with hematological malignancies and/or malignant sarcomas.
The prescribed dose should be administered orally, during a meal and with a large glass of water to minimize the risk of gastrointestinal disturbances. Doses of 400 mg or 600 mg should be administered once daily, whereas a dose of 800 mg should be administered as 400 mg twice a day in the morning and in the evening. Efficacy data for the 800 mg/day dose are limited.
For patients unable to swallow the film-coated tablets, the tablets may be dispersed in a glass of water or apple juice. The required number of tablets should be placed in the appropriate volume of beverage (approximately 50 mL for a 100 mg tablet, and 200 mL for a 400 mg tablet) and stirred with a spoon. The suspension should be administered immediately after complete disintegration of the tablet(s). Traces of the disintegrated tablet left in the glass after drinking should also be consumed
Treatment should be continued as long as the patient continues to benefit.
Tumour Lysis Syndrome (TLS)
Preventative measures should be considered prior to treatment with Sandoz Imatinib in patients with increased risk for TLS (See 7 WARNINGS AND PRECAUTIONS - General and 7 WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests).
Iron Exposure
For daily dosing of 800 mg, Sandoz Imatinib should be administered using the 400 mg tablet twice a day to reduce exposure to iron.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
Chronic myeloid leukemia (CML)
The recommended dosage of Sandoz Imatinib is 400 mg/day for adult patients with newly diagnosed CML or in chronic phase CML. The recommended dosage for adult patients in accelerated phase or blast crisis is 600 mg/day. The recommended dosage of Sandoz Imatinib for pediatric patients with newly diagnosed Ph+ CML is 340 mg/m2/day (rounded to the nearest 100 mg, i.e not to exceed 600 mg).
In CML, a dose increase from 400 mg to 600 mg or to 800 mg/day in adult patients with chronic phase disease, or from 600 mg to 800 mg (given as 400 mg twice daily) in adult patients in accelerated phase or blast crisis may be considered in the absence of severe adverse drug reactions and severe non-leukemia related neutropenia or thrombocytopenia in the following circumstances: disease progression (at any time); failure to achieve a satisfactory hematologic response after at least 3 months of treatment; failure to achieve a cytogenetic response after 12 months of treatment; or loss of a previously achieved hematologic and/or cytogenetic response.
Patients with CML should undergo regular response monitoring (see 7 WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests). Any changes to patient imatinib therapy (for example, when imatinib dose is lowered due to occurrence of side effects) should be followed by close response monitoring.
Ph+ Acute Lymphoblastic Leukemia (Ph+ALL)
The recommended dose of Sandoz Imatinib for use as a single-agent for induction phase therapy in adult patients with newly diagnosed Ph+ALL, or for adult patients with relapsed or refractory Ph+ ALL is 600 mg/day.
Myelodysplastic/Myeloproliferative Diseases (MDS/MPD)
The recommended dose of Sandoz Imatinib is 400 mg/day for adult patients with MDS/MPD
Aggressive sub-types of Systemic Mastocytosis (ASM and SM-AHNMD)
The recommended dose of Sandoz Imatinib is 400 mg/day for adult patients with ASM or SM-AHNMD without the D816V c-Kit mutation or mutational status unknown and not responding satisfactory to other therapies.
For patients with ASM or SM-AHNMD associated with eosinophilia, a clonal hematological disease related to the fusion kinase FIP1L1-PDGFRα, a starting dose of 100 mg/day is recommended. A dose increase from 100 mg to 400 mg for these patients may be considered in the absence of adverse drug reactions if assessments demonstrate an insufficient response to therapy.
Hypereosinophilic Syndrome (HES) and/or Chronic Eosinophilic Leukemia (CEL)
The recommended dose of Sandoz Imatinib is 100 mg/day for adult patients with HES/CEL.
For HES/CEL patients, a dose increase from 100 mg to 400 mg may be considered in the absence of adverse drug reactions if assessments demonstrate an insufficient response to therapy.
Treatment should be continued as long as the patient continues to benefit.
Dermatofibrosarcoma Protuberans (DFSP)
The recommended dose of Sandoz Imatinib is 800 mg/day for adult patients with DFSP
Gastrointestinal Stromal Tumors (GIST), Unresectable and/or metastatic malignant GIST
The recommended dose of Sandoz Imatinib is 400 mg/day or 600 mg/day for adult patients with unresectable and/or metastatic malignant GIST, depending on the stage and the progression of the disease. In GIST, a dose increase from 400 mg/day to 600 mg/day or to 800 mg/day for adult patients may be considered in the absence of adverse drug reactions if assessments demonstrate an insufficient response to therapy.
Adjuvant Treatment of GIST
The recommended dose of Sandoz Imatinib is 400 mg/day for the adjuvant treatment of adult patients at intermediate to high risk of relapse following complete resection of Kit (CD117) positive GIST. In the clinical study, Sandoz Imatinib was administrated for one year. The optimal treatment duration with Sandoz Imatinib is not known.
No dose adjustment of the initial 400 mg a day dose was made in patients with GIST with mild liver function abnormalities.
Dosage Adjustment
Hepatotoxicity and Other Non-Hematologic Adverse Drug Reactions
If a severe non-hematologic adverse drug reaction develops (such as severe hepatotoxicty or severe fluid retention), Sandoz Imatinib should be withheld until the event has resolved. Thereafter, treatment can be resumed as appropriate depending on the initial severity of the event.
If elevations in bilirubin >3 x institutional upper limit of normal (IULN) or in liver transaminases >5 x IULN occur, Sandoz Imatinib should be withheld until bilirubin levels have returned to a <1.5 x IULN and transaminase levels to <2.5 x IULN. In adults, treatment with Sandoz Imatinib may then be continued at a reduced daily dose (i.e., from 400 mg to 300 mg or from 600 mg to 400 mg, or from 800 mg to 600 mg). In pediatric patients, daily doses can be reduced under the same circumstances from 340 mg/m2/day to 260 mg/m2/day.
Hepatic Impairment
Patients with mild, and moderate liver dysfunction should be dosed at the minimum effective dose of
400 mg daily and patients with severe liver dysfunction should start at 200 mg daily. In the absence of severe toxicity, a dose increase up to 300 mg daily may be considered. The dose should be reduced if the patient develops unacceptable toxicity (see 10.3 Pharmacokinetics – Hepatic Insufficiency).
Renal Impairment
Sandoz Imatinib and its metabolites are not excreted via the kidney to a significant extent. However, it has been shown that exposure to imatinib is increased up to 2-fold in patients with mild (CrCL: 40-59 mL/min) and moderate (CrCL: 20-39 mL/min) renal dysfunction, and that there is a significant correlation in the incidence of serious adverse events with decreased renal function.
In clinical trials to date, the safety and efficacy of Sandoz Imatinib in patients with renal impairment has not been established. Patients with mild or moderate renal dysfunction should be treated with caution, and be given the minimum recommended effective dose of 400 mg daily as starting dose (see 10.3 Pharmacokinetics – Renal Insufficiency). The dose should be reduced if not tolerable. If tolerated, the dose can be increased for lack of efficacy (see section 7 WARNINGS AND PRECAUTIONS - Renal). Treatment of patients with moderate renal insufficiency at 800 mg cannot be recommended as this dose has not been investigated in these patients. The effect of Sandoz Imatinib treatment on patients with severe renal dysfunction (CrCL: <20 mL/min) and on hemodialysis has not been assessed, so treatment of these patients with imatinib cannot be recommended.
Pediatric Populations
Dosing in pediatric patients should be on the basis of body surface area (mg/m2). Treatment can be given as a once daily dose or alternatively the daily dose may be split into two administrations – one in the morning and one in the evening (see 14.1 Clinical Trials by Indication - Pediatric newly diagnosed chronic myeloid leukemia and 10.3 Pharmacokinetics - Pediatrics). There is no experience with the use of Sandoz Imatinib in pediatric patients with CML under 2 years of age. There is very limited to no experience with the use of Sandoz Imatinib in pediatric patients in other indications.
Hematologic adverse drug reactions
Dose reduction or treatment interruptions for severe neutropenia and thrombocytopenia are recommended as indicated in Table 1.
Table 1 Dose adjustments for neutropenia and thrombocytopenia.
| ASM or SM-AHNMD associated with eosinophilia and HES/CEL with FIP1L1-PDGFRα fusion kinase (starting dose 100 mg) | ANC < 1.0 x10⁹/L and/or platelets <50 x109/L |
|
Chronic phase CML (starting at dose 400 mg) MDS/MPD, ASM/SM-AHNMD, HES/CEL (at 400 mg dose) or GIST (starting dose either 400 mg or 600 mg) | ANC < 1.0 x10⁹/L and/or platelets < 50x109/L |
|
| ||
| Newly diagnosed pediatric chronic phase CML (at dose 340 mg/m2/day) | ANC < 1.0x10⁹/L and/or platelets <50x109/L |
|
Accelerated phase CML and blast crisis and Ph+ALL (starting dose 600 mg) | 1ANC < 0.5x10⁹/L and/or platelets <10x109/L |
ANC > 1 x10⁹/L and platelets > 20 x109/L and then resume treatment at 300 mg. |
DFSP (at 800 mg dose) | ANC < 1.0 x10⁹/L and/or platelets <50x109/L |
|
ANC: absolute neutrophil count
1occurring after at least 1 month of treatment
4.5 Missed Dose
If a dose is missed, the patient should not take the missed dose, but take the next prescribed dose.
5 OVERDOSAGE
Experience with higher than therapeutic doses is limited. Isolated cases of Sandoz Imatinib overdosage have been reported spontaneously and in the literature. Generally the reported outcome in these cases was improvement or recovery. In the event of overdosage the patient should be observed and appropriate symptomatic treatment should be given.
Events that have been reported at different dose ranges are as follows:
Adult Overdose
1,200 to 1,600 mg (duration varying between 1 to 10 days): Nausea, vomiting, diarrhea, rash, erythema, oedema, swelling, fatigue, muscle spasms, thrombocytopenia, pancytopenia, abdominal pain, headache, decreased appetite, increased bilirubin and liver transaminase level. 1,800 to 3,200 mg (as high as 3,200 mg daily for 6 days): Weakness, myalgia, increased CPK, increased bilirubin, gastrointestinal pain. 6,400 mg (single dose): A case report in the literature about one patient who experienced nausea, vomiting, abdominal pain, pyrexia, facial swelling, neutrophil count decreased, increased transaminases.
8 to 10 g (single dose): Vomiting and gastrointestinal pain have been reported.
Pediatric Overdose
One 3 year-old male exposed to a single dose of 400 mg experienced vomiting, diarrhoea and anorexia and another 3 year old male exposed to a single dose of 980 mg dose experienced decreased white blood cell count and diarrhea.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
Dosage Form
Sandoz Imatinib (imatinib mesylate) 100 mg scored tablets are supplied in cartons containing 6, 12, or 18 blister strips of 10 tablets.
Sandoz Imatinib (imatinib mesylate) 400 mg tablets are supplied in cartons containing 1, 3, or 9 blister strips of 10 tablets.
Sandoz Imatinib (imatinib mesylate) 400 mg scored tablets are supplied in cartons containing 1, 3, or 9 blister strips of 10 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Fluid Retention and edema
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | tablet 100 mg and 400 mg | Tablet content: cellulose (microcrystalline), crospovidone, colloidal silicon dioxide, hydroxypropyl methylcellulose, magnesium stearate. Tablet coating: ferric oxide (red), ferric oxide (yellow), hydroxypropyl methylcellulose, polyethylene glycol, and talc. |
Sandoz Imatinib (imatinib mesylate) is often associated with edema and occasionally serious fluid retention (see 8.2 Clinical Trial Adverse Reactions). All Grades of fluid retention/edema were reported in up to 61.7% for newly diagnosed CML patients, up to 76.2% for other CML patients across all clinical trials, and up to 80.3% for GIST patients. Patients should be weighed and monitored regularly for signs and symptoms of fluid retention as fluid retention can occur after months of treatment. An unexpected rapid weight gain should be carefully investigated and appropriate treatment provided. The probability of edema was increased with higher imatinib dose. Severe superficial edema was reported in 1.5% of newly diagnosed CML patients taking Sandoz Imatinib and in 2.1% to 5.8% of other adult CML patients taking Sandoz Imatinib. In addition, other severe fluid retention events (e.g., pleural effusion, pericardial effusion, pulmonary edema, and ascites) were reported in 1.3% of newly diagnosed CML patients taking Sandoz Imatinib and in 1.7% to 6.2% of other adult CML patients taking Sandoz Imatinib.
Hemorrhage
All Grades of hemorrhage were reported in up to 28.9% for newly diagnosed CML patients, up to 53% for other CML patients across all clinical trials, and up to 29.9% for GIST patients.
In the newly diagnosed CML trial, 1.8% of patients had Grades 3/4 hemorrhage. In the unresectable and/or metastatic malignant GIST clinical trial (B2222) eight patients (5.4%, five patients in the 600 mg dose group and three patients in the 400 mg dose group) were reported to have had gastrointestinal (GI) bleeds or intra-tumoral bleeds. Four patients with intra-tumoral bleeds had either intra-abdominal or intra-hepatic, depending on the anatomical location of the tumor lesions. One patient, who had a history of GI bleeding prior to the study, died due to gastrointestinal bleeding.
In addition, gastric antral vascular ectasia (GAVE), a rare cause of GI hemorrhage, has been reported in post-marketing experience in patients with CML, GIST, ALL and other diseases. Patients should therefore be monitored for gastrointestinal symptoms at the start of and during therapy with Sandoz Imatinib. When needed, Sandoz Imatinib discontinuation may be considered. Time to GAVE diagnosis was commonly reported at about 1 year of exposure but was variable (6 days to 7 years) after starting treatment with Sandoz Imatinib (see 8.2 Clinical Trial Adverse Reactions).
Subdural hematomas have been reported in association with imatinib administration in patients with other contributing factors, including older age (e.g., age greater than 50-55 years); thrombocytopenia due to the underlying malignancy or concomitant administration of multi-agent chemotherapy; concomitant administration of medications that increase bleeding risk; and prior lumbar puncture or head trauma. In clinical trials, the incidence of subdural hematoma has ranged from 0 to 2.4%.
This risk of bleeding should be evaluated carefully in all patients. Caution should be exercised with the concomitant use of antiplatelet agents or warfarin, especially in patients who are thrombocytopenic. Platelet counts and prothrombin time should be measured on a regular basis when imatinib is used concurrently with anticoagulants, prostacyclins, or other medications that increase bleeding risk. Patients who experience head trauma or have unexplained neurological symptoms should be evaluated for subdural hematoma. In view of a potential interaction between Sandoz Imatinib and warfarin leading to increased exposure to warfarin, patients who require anticoagulation with warfarin should be monitored especially closely when Sandoz Imatinib dose adjustments are necessary (see 9.4 Drug-Drug Interactions).
Toxicities From Long-Term Use
It is important to consider potential toxicities suggested by animal studies, specifically, liver kidney and cardiac toxicity, and immunosuppression. Liver toxicity was observed in rats, dogs and cynomolgus monkeys in repeated dose studies. Most severe toxicity was noted in dogs and included elevated liver enzymes, hepatocellular necrosis, bile duct necrosis, and bile duct hyperplasia.
Tumour Lysis Syndrome (TLS)
Tumor lysis syndrome has occurred in patients taking Sandoz Imatinib, including fatal cases (see 8.5 Post-Market Adverse Reactions). Patients at increased risk for TLS include those with tumours having a high proliferative rate (e.g. CML-blast crisis), concomitant chemotherapy or radiotherapy or having a solid tumour of large size (bulky disease), decreased kidney function or elevated lactate dehydrogenase (LDH) at baseline. Preventative measures, including correction of clinically significant dehydration and treatment of high uric acid levels, should be considered for patients at increased risk of developing TLS (see 4.1 Dosing Considerations and 7 WARNINGS AND PRECAUTIONS - Monitoring and Laboratory Tests).
Carcinogenesis and Mutagenesis
A 2-year preclinical carcinogenicity study conducted in rats demonstrated renal adenomas/carcinomas, urinary bladder and urethra papillomas, papillomas/carcinomas of the preputial and clitoral gland, adenocarcinomas of the small intestine, adenomas of the parathyroid glands, benign and malignant tumors of the adrenal medulla and papillomas/carcinomas of the nonglandular stomach (See 16 NON-CLINICAL TOXICOLOGY - Carcinogenicity).
Long-term, non-neoplastic histological changes identified in the preclinical carcinogenicity study in rats include cardiomyopathy.
The relevance of these findings in the rat carcinogenicity study for humans is not known. An analysis of the clinical safety data from clinical trials and spontaneous adverse event reports did not provide evidence of an increased overall incidence of malignancies in patients treated with imatinib mesylate compared to that of the general population.
However, adverse events in cancer patients are significantly under reported and a large proportion of patients treated with Sandoz Imatinib have had limited follow-up thus not permitting a final analysis of the potential for an increased incidence of a secondary malignancy in patients treated with Sandoz Imatinib.
Cardiovascular
Severe congestive heart failure (CHF) and reduction of left ventricular ejection fraction (LVEF) have been reported in patients taking Sandoz Imatinib. Although several of these patients had pre-existing conditions including hypertension, diabetes and prior coronary artery disease, they were subsequently diagnosed with CHF. Patients with known cardiac disease or risk factors for cardiac failure should be monitored carefully and those with symptoms or signs consistent with CHF should be evaluated and treated. In patients with history of cardiac disease or in elderly patients, a baseline evaluation of LVEF is recommended prior to initiation of Sandoz Imatinib therapy.
In patients with hypereosinophilic syndrome (HES) with occult or known infiltration of HES cells within the myocardium, isolated cases of cardiogenic shock/left ventricular dysfunction believed to be associated with HES cell degranulation upon initiation of Sandoz Imatinib therapy, have been reported. The condition was reported to be reversible with the administration of systemic steroids, circulatory support measures and temporarily withholding Sandoz Imatinib. Myelodysplastic/myeloproliferative diseases (MDS/MPD) and systemic mastocytosis (SM) might be associated with high eosinophil levels. Performance of an echocardiogram and determination of serum troponin should therefore be considered in patients with HES/CEL and in patients with MDS/MPD or ASM and SM-AHNMD associated with high eosinophil levels. These patients with HES/CEL or ASM, SM-AHNMD and MDS/MPD must be also on 1-to 2 mg/kg of prednisone equivalent oral steroids for one to two weeks, initiated at least 2 days prior to beginning Sandoz Imatinib therapy.
Driving and Operating Machinery
Reports of motor vehicle accidents have been received in patients receiving Sandoz Imatinib. Caution should be recommended when driving a car or operating machinery (see 8.5 Post-Market Adverse Reactions and 9.3 Drug-Behavioural Interactions).
Endocrine and Metabolism
Clinical cases of hypothyroidism have been reported in thyroidectomy patients undergoing levothyroxine replacement during treatment with Sandoz Imatinib. Thyroid-Stimulating Hormone (TSH) levels should be closely monitored in such patients.
Gastrointestinal
Sandoz Imatinib is sometimes associated with GI irritation. Sandoz Imatinib should be taken with food and a large glass of water to minimize this problem. There have been rare reports, including fatalities, of gastrointestinal perforation.
See 7 WARNINGS AND PRECAUTIONS, General for more information on gastrointestinal hemorrhage.
Hematologic
Hematologic Toxicity
Treatment with Sandoz Imatinib is often associated with neutropenia or thrombocytopenia (see 8.4 Abnormal Laboratory Findings). Complete blood counts should be performed weekly for the first month, biweekly for the second month, and periodically thereafter as clinically indicated (for example every 2-3 months). The occurrence of these cytopenias is dependent on the stage of disease and is more frequent in patients with accelerated phase CML or blast crisis than in patients with chronic phase CML. In pediatric CML patients the most frequent toxicities observed were Grade 3 or 4 cytopenias involving neutropenia (31%), thrombocytopenia (16%) and anemia (14%). These generally occur within the first several months of therapy (see 4.2 Recommended Dose and Dosage Adjustment - Hematologic adverse drug reactions).
An increased rate of opportunistic infections was observed in a monkey study with chronic imatinib treatment. In a 39-week monkey study, treatment with imatinib resulted in worsening of normally suppressed malarial infections in these animals. Lymphopenia was observed in animals (as in humans, where all grades of lymphopenia were observed in 0.3% patients).
Hepatic/Biliary/Pancreatic
Liver Failure
There have been cases of cytolytic and cholestatic hepatitis and hepatic failure; in some cases the outcome was fatal. One patient, who was taking acetaminophen regularly for fever along with Sandoz Imatinib, died of acute liver failure (see 9.4 Drug-Drug Interactions).
Hepatotoxicity
Hepatotoxicity, occasionally severe, may occur with Sandoz Imatinib (see 8.2 Clinical Trial Adverse Reactions). Liver function (transaminases, bilirubin, and alkaline phosphatase) should be monitored before initiation of treatment and monthly or as clinically indicated. Laboratory abnormalities should be managed with interruption and/or dose reduction of the treatment with Sandoz Imatinib (see 8.2
Clinical Trial Adverse Reactions and 4.2 Recommended Dose and Dosage Adjustment – Hepatic Impairment). Patients with hepatic impairment should be closely monitored. Although pharmacokinetic analysis results showed there is considerable inter-subject variation, the mean exposure to imatinib did not differ significantly between patients with mild and moderate liver dysfunction (as measured by dose normalized AUC) and patients with normal liver function. Patients with severe liver dysfunction demonstrated increased exposure to imatinib and its active metabolite CGP 74588. Liver function monitoring remains crucial as no long term toxicity and tolerability have been established (see 10.3 Pharmacokinetics – Hepatic Insufficiency).
In GIST patients with liver metastases, exposure to Sandoz Imatinib may be higher than in CML patients, due to impaired liver function (see 8.2 Clinical Trial Adverse Reactions).
Hepatotoxicity has been observed in patients treated with Sandoz Imatinib. All Grades of liver toxicity (including liver failure) were reported in up to 11.6% for newly diagnosed CML patients, up to 12% for other CML patients across all clinical trials, and up to 12.2% for unresectable and/or metastatic malignant GIST patients.
Immune
Hepatitis B virus Reactivation
Reactivation of hepatitis B virus (HBV) has occurred in patients who are chronic carriers of this virus after receiving a Bcr-Abl tyrosine kinase inhibitor (TKI), including Sandoz Imatinib. Some cases resulted in acute hepatic failure or fulminant hepatitis leading to liver transplantation or death.
Patients should be tested for HBV infection before initiating treatment with Sandoz Imatinib. Patients currently on Sandoz Imatinib should have baseline testing for HBV infection in order to identify chronic carriers of the virus. Experts in liver disease and in the treatment of hepatitis B should be consulted before treatment is initiated in patients with positive HBV serology (including those with active disease) and for patients who test positive for HBV infection during treatment. Carriers of HBV who require treatment with Sandoz Imatinib should be closely monitored for signs and symptoms of active HBV infection throughout therapy and for several months following termination of therapy.
Monitoring and Laboratory Tests
Patients with known cardiac disease or risk factors for cardiac failure should be monitored carefully and those with symptoms or signs consistent with CHF should be evaluated and treated. In patients with history of cardiac disease or in elderly patients, a baseline evaluation of LVEF is recommended prior to initiation of Sandoz Imatinib therapy (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular).
For patients receiving Sandoz Imatinib, complete blood counts should be performed weekly for the first month, biweekly for the second month, and periodically thereafter as clinically indicated (for example every 2-3 months) (see 7 WARNINGS AND PRECAUTIONS - Hematologic and 4.2 Dosage and Dosage Adjustment – Hematologic adverse drug reactions).
Liver function (transaminases, bilirubin, and alkaline phosphatase) should be monitored before initiation of treatment and monthly or as clinically indicated (see 7 WARNINGS AND PRECAUTIONS - Hepatic/Biliary/Pancreatic and 4.2 Recommended Dose and Dosage Adjustment – Hepatic Impairment).
Patients should be weighed and monitored regularly for signs and symptoms of fluid retention as fluid retention can occur after months of treatment with Sandoz Imatinib (see 7 WARNINGS AND PRECAUTIONS - General).
Thyroid-Stimulating Hormone (TSH) levels should be closely monitored in thyroidectomy patients undergoing levothyroxine replacement during treatment with Sandoz Imatinib (see 7 WARNINGS AND PRECAUTIONS – Endocrine and Metabolism).
Signs and symptoms consistent with tumour lysis syndrome (e.g., hyperuricemia, hyperkalemia, hypocalcemia, hyperphosphatemia, acute renal failure, elevated LDH, high fevers) should be monitored at baseline and during initial treatment with Sandoz Imatinib (see 7 WARNINGS AND PRECAUTIONS - General and 4.1 Dosing Considerations – Tumour Lysis Syndrome (TLS)).
Close monitoring of growth in children under Sandoz Imatinib treatment is highly recommended (see 7.1.3 Pediatrics).
During treatment with Sandoz Imatinib serum electrolytes should be regularly monitored for possible hypophosphatemia, hyperkalemia, and hyponatremia in all patients as well as glucose, blood urea nitrogen (BUN) and creatinine. In addition, in pediatric patients, serum calcium and albumin should also be regularly monitored. Grades 3/4 hypophosphatemia have been observed in 16.5% (15% Grade 3 and 1.5% Grade 4) of patients in a phase I dose finding study 03001 (N=143) and a phase II study 0102 (N=260) of chronic myeloid leukemia in blast crisis.
In patients with CML, regular response monitoring, particularly when therapy is modified, is essential to detect early signs of loss of response so that appropriate actions can be taken to avoid disease progression. A loss of response can occur at any time, but is more likely when imatinib treatment is modified (see 4.2 Recommended Dose and Dosage Adjustment – Chronic myeloid leukemia (CML)).
Females of reproductive potential should have a negative serum or urine pregnancy test with a sensitivity of at least 25 mIU/ml within 1 week prior to beginning therapy (see 7.1.1 Pregnant Women – Female Patients of Reproductive Potential).
Musculoskeletal
Cases of osteonecrosis have been uncommonly reported in adult and pediatric patients treated with Sandoz Imatinib, including serious cases requiring treatment discontinuation, and/or surgical interventions. The femur head was the most commonly affected site; less commonly affected sites included the tibia, femur shaft, jaw, finger, and calcaneus (see 8.5 Post-Market Adverse Reactions).
Renal
Renal toxicity was observed in monkeys treated for 2 weeks, with focal mineralization and dilation of the renal tubules and tubular nephrosis. Increased BUN and creatinine were observed in several of these animals.
Sandoz Imatinib and its metabolites are not excreted via the kidney to a significant extent. Creatinine clearance (CrCL) is known to decrease with age, and age did not significantly affect imatinib kinetics.
In patients with impaired renal function, Sandoz Imatinib plasma exposure is higher (1.5- to 2-fold increase) than in patients with normal renal function, probably due to an elevated plasma level of alpha-acid glycoprotein (AGP), a Sandoz Imatinib-binding protein, in patients with renal dysfunction. As well, there is a significant correlation in the incidence of serious adverse events with decreased renal function (p=0.0096). Patients with mild or moderate renal impairment should be treated with caution (see 4.2 Recommended Dose and Dosage Adjustment – Renal Impairment). Since the effect of Sandoz Imatinib treatment on patients with severe renal dysfunction or on dialysis has not been sufficiently assessed, recommendations on the treatment of these patients with Sandoz Imatinib cannot be made. Patients with history of renal failure should be monitored carefully, and any patient with signs or symptoms consistent with renal failure should be evaluated and treated.
Long term treatment with Sandoz Imatinib may result in declines in renal function. Patients treated with imatinib in clinical studies had a decrease over time in estimated glomerular filtration rate (eGFR). Treatment-naive patients with newly-diagnosed CML initiated on imatinib among three Phase III trials showed a decline in eGFR from a median baseline value of 100.1 ml/min/1.73m2 (N=1279) to 93.5 ml/min/1.73m2 at 6 months (N=1213), 92.8 ml/min/1.73m2 at 1 year (N=1161) and 85.5 ml/min/1.73m2 at 5 years (N=585). Monitoring for renal function should be undertaken before initiating therapy and periodically thereafter.
Reproductive Health: Female and Male Potential
Fertility
Stem cell factor and c-Kit genes are known to be important for germ cell development. Human studies on male patients receiving Sandoz Imatinib and its effect on male fertility and spermatogenesis have not been performed. However, clinical evidence of profound oligospermia with Sandoz Imatinib use has been reported in the literature as has clinical evidence for maintained male fertility. There is also pre-clinical evidence of impaired spermatogenesis, lower testes and epididymal weights as well as a reduced number of motile sperm without a reduction in fertility (see 16 NON-CLINICAL TOXICOLOGY - Reproductive and Developmental Toxicology). Therefore, physicians should advise and counsel their male patients as appropriate.
Teratogenic Risk
Teratogenicity and significant post-implantation loss have been observed in rat studies (see 16 NON-CLINICAL TOXICOLOGY - Reproductive and Developmental Toxicology). There have been post-marketing reports of spontaneous abortions and infant congenital anomalies from women who have taken Sandoz Imatinib.
Respiratory
Pulmonary Events
Rare cases of pulmonary fibrosis and interstitial pneumonitis have been reported in patients who have received Sandoz Imatinib. However, no definitive relationship has been established between the occurrence of these pulmonary events and treatment with Sandoz Imatinib.
Skin
Skin and Mucosa
Although rare, Erythema multiforme (EM), Toxic epidermal Necrolysis (TEN) and Stevens Johnson syndrome (SJS) have been reported in patients who have received Sandoz Imatinib. Skin biopsies in some cases of exfoliative skin rash associated with Sandoz Imatinib use have shown a mixed cellular infiltrate characteristic of a toxic drug reaction. Severe cases of exfoliative rash may require treatment interruption or discontinuation.
Drug reaction with eosinophilia and systemic symptoms (DRESS), a potentially life-threatening syndrome including fever, severe skin eruption, lymphadenopathy, hematologic abnormalities (eosinophilia or atypical lymphocytes), and internal organ involvement, has also been reported in Sandoz Imatinib-treated patients. DRESS regressed when Sandoz Imatinib was discontinued, and in all cases where the drug was re-introduced, DRESS recurred. If DRESS occurs, Sandoz Imatinib should be interrupted, and permanent discontinuation should be considered.
7.1 Special Populations
7.1.1 Pregnant Women
Sandoz Imatinib should not be administered to pregnant women.
Sandoz Imatinib can cause fetal harm when administered to a pregnant woman. There are no adequate and well-controlled studies on the use of Sandoz Imatinib in pregnant women.
Patients should advise their physician if they are pregnant. If it is used during pregnancy the patient should be apprised of the potential risk to the fetus.
Females of reproductive potential should be advised to use effective birth control (methods that result in less than 1 % pregnancy rates) when using Sandoz Imatinib during treatment and for at least 15 days after stopping treatment with Sandoz Imatinib (see 7.1.1 Pregnant Women).
Females of reproductive potential should have a negative serum or urine pregnancy test with a sensitivity of at least 25 mIU/ml within 1 week prior to initiating Sandoz Imatinib.
7.1.2 Breast-feeding
Imatinib and its active metabolite can be excreted into breast milk in humans and in animals. There are cases of imatinib exposure during lactation in humans including one case reported the milk: plasma ratio of 0.5 for imatinib and 0.9 for the metabolite. Since the effects of exposure of the infant to imatinib are potentially serious, women should not breast feed during treatment and for at least 15 days after stopping treatment with Sandoz Imatinib.
7.1.3 Pediatrics
Pediatrics (<18 years of age): There is no experience with the use of Sandoz Imatinib in pediatric patients with CML under 2 years of age. There is very limited to no experience with the use of Sandoz Imatinib in pediatric patients in other indications.
There have been case reports of growth retardation in children and pre-adolescents receiving Sandoz Imatinib. No prospective studies have been carried out in this regard and the long term effects of prolonged treatment with Sandoz Imatinib on growth in pediatric patients are unknown. In a juvenile toxicology study, an impact on growth and a delay in sexual maturation were observed in rats (see 16 NON-CLINICAL TOXICOLOGY - Juvenile Toxicology). Therefore, close monitoring of growth in children under Sandoz Imatinib treatment is highly recommended.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): In the CML phase II studies, approximately 20% of patients were older than 65 years. The efficacy of Sandoz Imatinib was similar in all age groups studied.
In the adjuvant GIST study, 221 patients (31%) were older than 65 years. No difference was observed in the safety profile in patients older than 65 years as compared to younger patients. The efficacy of Sandoz Imatinib was similar in patients older than 65 years and younger patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Sandoz Imatinib (imatinib mesylate) was generally well tolerated across all studies in CML and GIST. Complications of advanced malignancies and co-administered medications make causality of adverse events difficult to assess in single arm studies. The majority of Sandoz Imatinib-treated patients experienced adverse events at some time.
Recent published literature revealed cases of musculoskeletal pain symptoms occurring upon imatinib discontinuation following long-term treatment, with a high frequency of 18% to 46% in CML patients. Those events may persist for months and were referred to as imatinib withdrawal symptoms (IWS).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Chronic Myeloid Leukemia
Sandoz Imatinib was generally well tolerated with chronic oral daily dosing in patients with CML including pediatric patients. The majority of patients experienced adverse events at some point in time, however, most events were of mild to moderate Grade. In adult clinical trials, drug discontinuation for drug-related adverse events was observed in 2.4% of newly diagnosed patients, in 5 % of patients in chronic phase, 8% in accelerated phase and 9% in blast crisis.
The most frequently reported drug-related adverse events were fluid retention (superficial edema and other fluid retention events), nausea, vomiting, diarrhea, muscle cramps, fatigue and rash (Refer to Table 3 and 4 for newly diagnosed CML and other CML patients, respectively). Superficial edemas were a common finding in all studies described primarily as periorbital edemas or lower limb edemas. However, these edemas were rarely severe and may be managed with diuretics, other supportive measures, or by reducing the dose of Sandoz Imatinib (see 4.2 Recommended Dose and Dosage Adjustment – Chronic myeloid leukemia (CML)).
Other adverse events such as pleural effusion, ascites, pulmonary edema and rapid weight gain with or without superficial edema may be collectively described as “other fluid retention events”. These events were usually managed by withholding Sandoz Imatinib treatment temporarily and/or with diuretics and/or other appropriate supportive care measures. However, a few of these events may be serious or life threatening and several patients with blast crisis died with a complex clinical history of pleural effusion, congestive heart failure and renal failure. The following tables list the adverse experiences which occurred in ≥ 10% of patients in the clinical trials, regardless of relationship to therapy.
Table 3 Adverse experiences Regardless of Relationship to Study Drug reported in newly diagnosed CML ( ≥10% of all patients)(1)
| Adverse event (preferred term) | All Grades | CTC Grades 3/4 | ||||||||
| Sandoz Imatinib N=551 (%) | IFN+Ara-C N=533 (%) | Sandoz Imatinib N=551 (%) | IFN+Ara-C N=533 (%) | |||||||
| Any event | 99.1 | 99.6 | 57.2 | 77.3 | ||||||
| Gastrointestinal disorders | ||||
| Nausea | 49.5 | 61.5 | 1.3 | 5.1 |
| Diarrhea | 45.4 | 43.3 | 3.3 | 3.2 |
| Abdominal pain | 36.5 | 25.9 | 4.2 | 3.9 |
| Vomiting | 22.5 | 27.8 | 2.0 | 3.4 |
| Dyspepsia | 18.9 | 8.3 | 0 | 0.8 |
| Constipation | 11.4 | 14.4 | 0.7 | 0.2 |
| Dry mouth | 2.9 | 10.9 | 0 | 0.2 |
| General disorders and administration site conditions | ||||
| Fluid retention | 61.7 | 11.1 | 2.5 | 0.9 |
| 59.9 | 9.6 | 1.5 | 0.4 |
| 6.9 | 1.9 | 1.3 | 0.6 |
| Fatigue | 38.8 | 67.0 | 1.8 | 25.1 |
| Pyrexia | 17.8 | 42.6 | 0.9 | 3.0 |
| Rigors | 9.3 | 34.0 | 0.2 | 0.8 |
| Asthenia | 8.0 | 16.9 | 0.2 | 3.8 |
| Influenza like illness | 7.3 | 15.9 | 0 | 0.9 |
| Mucosal inflammation | 1.1 | 10.3 | 0 | 3.2 |
| Hepatobiliary disorders | ||||
| Liver toxicity (including liver failure) | 11.6 | 17.3 | 4.0 | 5.1 |
| Infections and infestations | ||||
| Nasopharyngitis | 30.5 | 8.8 | 0 | 0.4 |
| Upper respiratory tract infection | 21.2 | 8.4 | 0.2 | 0.4 |
| Influenza | 13.8 | 6.2 | 0.2 | 0.2 |
| Sinusitis | 11.4 | 6.0 | 0.2 | 0.2 |
| Investigations | ||||
| Weight increased | 15.6 | 2.6 | 2.0 | 0.4 |
| Weight decreased | 5.1 | 17.3 | 0.4 | 1.3 |
| Metabolic and nutritional disorders | ||||
| Anorexia | 7.1 | 31.7 | 0 | 2.4 |
| Musculoskeletal. & connective tissue disorders | ||||
| Muscle cramps | 49.2 | 11.8 | 2.2 | 0.2 |
| Musculoskeletal pain | 47.0 | 44.8 | 5.4 | 8.6 |
| Joint pain | 31.4 | 38.1 | 2.5 | 7.7 |
| Myalgia | 24.1 | 38.8 | 1.5 | 8.3 |
| Bone pain | 11.3 | 15.6 | 1.6 | 3.4 |
| Nervous system disorders | ||||
| Headache | 37.0 | 43.3 | 0.5 | 3.8 |
| Dizziness | 19.4 | 24.4 | 0.9 | 3.8 |
| Psychiatric disorders | ||||
| Depression | 14.9 | 35.8 | 0.5 | 13.1 |
| Insomnia | 14.7 | 18.6 | 0 | 2.3 |
| Anxiety | 9.6 | 11.8 | 0.5 | 2.6 |
| Respiratory disorders | ||||
| Cough | 20.0 | 23.1 | 0.2 | 0.6 |
| Pharyngolaryngeal pain | 18.1 | 11.4 | 0.2 | 0 |
| Dyspnea | 9.3 | 14.4 | 1.8 | 1.7 |
| Skin and subcutaneous disorders | ||||
| Rash and related terms | 40.1 | 26.1 | 2.9 | 2.4 |
| Night sweats | 9.8 | 15.8 | 0.2 | 0.4 |
| Pruritus | 9.8 | 11.8 | 0.2 | 0.2 |
| Sweating increased | 5.8 | 14.8 | 0.2 | 0.4 |
| Alopecia | 4.9 | 22.3 | 0 | 0.6 |
| Vascular disorders | ||||
| Hemorrhage | 28.9 | 21.2 | 1.8 | 1.7 |
| 1.6 | 1.1 | 0.5 | 0.2 |
| 0.2 | 0.4 | 0 | 0.4 |
(1)All adverse events occurring in ≥10% of patients are listed regardless of suspected relationship to treatment.
Table 4 Adverse Experiences Regardless of Relationship to Study Drug Reported in Other CML Clinical Trials (≥10% of All patients in any trial)(1)
| System Affected | Myeloid blast crisis N=260 (%) | Accelerated phase N=235 (%) | Chronic phase IFN failure N=532 (%) | |||||||||||
| All Grades | CTC Grades 3/4 | All Grades | CTC Grades 3/4 | All Grades | CTC Grades 3/4 | |||||||||
| Gastrointestinal disorders | ||||||||||||||
| Nausea | 71 | 5 | 73 | 5 | 63 | 3 | ||||||||
| Vomiting | 54 | 4 | 58 | 3 | 36 | 2 | ||||||||
| Diarrhea | 43 | 4 | 57 | 5 | 48 | 3 | ||||||||
| Abdominal pain¥ | 30 | 6 | 33 | 4 | 32 | 1 | ||||||||
| Constipation | 16 | 2 | 16 | 0.9 | 9 | 0.4 | ||||||||
| Dyspepsia | 12 | 0 | 22 | 0 | 27 | 0 | ||||||||
| General disorders and administration site conditions | ||||||||||||||
| Fluid retention¥ | 72 | 11 | 76 | 6 | 69 | 4 | ||||||||
| 66 | 6 | 74 | 3 | 67 | 2 | ||||||||
| 22 | 6 | 15 | 4 | 7 | 2 | ||||||||
| Pyrexia | 41 | 7 | 41 | 8 | 21 | 2 | ||||||||
| Fatigue | 30 | 4 | 46 | 4 | 48 | 1 | ||||||||
| Asthenia | 18 | 5 | 21 | 5 | 15 | 0.2 | ||||||||
| Rigors | 10 | 0 | 12 | 0.4 | 10 | 0 | ||||||||
| Chest pain | 7 | 2 | 10 | 0.4 | 11 | 0.8 | ||||||||
| Hepatobiliary disorders | ||||||||||||||
| Liver toxicity (including liver failure) | 10 | 5 | 12 | 6 | 6 | 3 |
| Infections and infestations | ||||||
| Nasopharyngitis | 10 | 0 | 17 | 0 | 22 | 0.2 |
| Pneumonia NOS | 13 | 7 | 10 | 7 | 4 | 1 |
| Upper respiratory tract infection NOS | 3 | 0 | 12 | 0.4 | 19 | 0 |
| Sinusitis NOS | 4 | 0.4 | 11 | 0.4 | 9 | 0.4 |
| Influenza | 0.8 | 0.4 | 6 | 0 | 11 | 0.2 |
| Investigations | ||||||
| Weight increase | 5 | 1 | 17 | 5 | 32 | 7 |
| Metabolic and nutritional disorders | ||||||
| Anorexia | 14 | 2 | 17 | 2 | 7 | 0 |
| Hypokalemia | 13 | 4 | 9 | 2 | 6 | 0.8 |
| Musculoskeletal. & connective tissue disorders | ||||||
| Musculoskeletal pain ¥ | 42 | 9 | 49 | 9 | 38 | 2 |
| Muscle cramps ¥ | 28 | 1 | 47 | 0.4 | 62 | 2 |
| Joint pain (Arthralgia)¥ | 25 | 5 | 34 | 6 | 40 | 1 |
| Myalgia | 9 | 0 | 24 | 2 | 27 | 0.2 |
| Nervous system disorders | ||||||
| Headache | 27 | 5 | 32 | 2 | 36 | 0.6 |
| Dizziness | 12 | 0.4 | 13 | 0 | 16 | 0.2 |
| Psychiatric disorders | ||||||
| Insomnia | 10 | 0 | 14 | 0 | 14 | 0.2 |
| Anxiety | 8 | 0.8 | 12 | 0 | 8 | 0.4 |
| Respiratory disorders | ||||||
| Dyspnea NOS | 15 | 4 | 21 | 7 | 12 | 0.9 |
| Cough | 14 | 0.8 | 27 | 0.9 | 20 | 0 |
| Pharyngitis | 10 | 0 | 12 | 0 | 15 | 0 |
| Skin and subcutaneous disorders | ||||||
| Rash and related terms¥ | 36 | 5 | 47 | 5 | 47 | 3 |
| Night sweats | 13 | 0.8 | 17 | 1 | 14 | 0.2 |
| Pruritis | 8 | 1 | 14 | 0.9 | 14 | 0.8 |
| Vascular disorders | ||||||
| Hemorrhages¥ | 53 | 19 | 49 | 11 | 30 | 2 |
| 9 | 7 | 3 | 3 | 2 | 1 |
| 8 | 4 | 6 | 5 | 2 | 0.4 |
¥ Grouped events
(1) All adverse events occurring in ≥10% of patients are listed regardless of suspected relationship to treatment
(2) Other fluid retention events include pleural effusion, ascites, pulmonary edema, pericardial effusion, anasarca, edema aggravated, and fluid retention not otherwise specified.
Acute Lymphoblastic Leukemia
The adverse reactions were similar for Ph+ ALL as for CML. The most frequently reported non-hematologic drug-related adverse events were fluid retention (superficial edema and other fluid retention events), nausea, vomiting, diarrhea, muscle cramps, fatigue and rash. Superficial edemas were a common finding in all studies described primarily as periorbital edemas or lower limb edemas. However, these edemas were rarely severe and may be managed with diuretics, other supportive measures, or by reducing the dose of Sandoz Imatinib (see 4.2 Recommended Dose and Dosage Adjustment – Ph+ Acute Lymphoblastic Leukemia (Ph+ALL)).
Myelodysplastic/Myeloproliferative Diseases
Adverse events, regardless of relationship to study drug, that were reported in at least 10% of the patients treated with Sandoz Imatinib for MDS/MPD in Trial B2225, are shown in Table 5.
Table 5 Adverse Experiences Regardless of Relationship to Study Drug Reported (more than one patient) in MDS/MPD Patients in Trial B2225 (≥10% all patients) all Grades
| Preferred term | N=7 n (%) |
| Nausea | 4 (57.1) |
| Diarrhea | 3 (42.9) |
| Anemia | 2 (28.6) |
| Fatigue | 2 (28.6) |
| Muscle cramp | 3 (42.9) |
| Arthralgia | 2 (28.6) |
| Periorbital edema | 2 (28.6) |
Aggressive sub-types of Systemic Mastocytosis (ASM and SM-AHNMD)
All ASM patients experienced at least one adverse event at some time. The most frequently reported adverse events were diarrhea, nausea, ascites, muscle cramps, dyspnea, fatigue, peripheral edema, anemia, pruritis, rash and lower respiratory tract infection. None of the 5 patients in Study B2225 with ASM discontinued Sandoz Imatinib due to drug-related adverse events or abnormal laboratory values.
Hypereosinophilic Syndrome and Chronic Eosinophilic Leukemia
The overall safety profile in this HES/CEL small patient population does not seem different from the known safety profile of Sandoz Imatinib observed in other larger populations of hematologic malignancies, such as CML. However, in patients with HES and cardiac involvement, isolated cases of cardiogenic shock/left ventricular dysfunction have been associated with the initiation of Sandoz Imatinib therapy. The condition was reported to be reversible with the administration of systemic steroids, circulatory support measures and temporarily withholding Sandoz Imatinib (see 7 WARNINGS AND PRECAUTIONS - Cardiovascular). All patients experienced at least one adverse event, the most common being gastrointestinal, cutaneous and musculoskeletal disorders. Hematologic abnormalities were also frequent, with instances of CTC Grade 3 leukopenia, neutropenia, lymphopenia and anemia.
Dermatofibrosarcoma Protuberans
Adverse events, regardless of relationship to study drug, that were reported in at least 10% of the 12 patients treated with Sandoz Imatinib for DFSP in Trial B2225 are shown in Table 6.
Table 6 Adverse Experiences Regardless of Relationship to Study Drug Reported in DFSP Patients in Trial B2225 (≥10% all patients) all Grades
| Preferred term | N=12 n (%) |
| Nausea | 5 (41.7) |
| Diarrhea | 3 (25.0) |
| Vomiting | 3 (25.0) |
| Periorbital edema | 4 (33.3) |
| Face edema | 2 (16.7) |
| Rash | 3 (25.0) |
| Fatigue | 5 (41.7) |
| Edema peripheral | 4 (33.3) |
| Pyrexia | 2 (16.7) |
| Eye edema | 4 (33.3) |
| Lacrimation increased | 3 (25.0) |
| Dyspnea exertional | 2 (16.7) |
| Anemia | 3 (25.0) |
| Rhinitis | 2 (16.7) |
| Anorexia | 2 (16.7) |
Gastrointestinal Stromal Tumors
Unresectable and/or Metastatic Malignant GIST
Sandoz Imatinib was generally well tolerated in patients with unresectable and/or metastatic malignant GIST. Most events were of mild to moderate severity. Drug was discontinued for adverse events in 7 (4.7%) patients in both treatment groups. The most frequently reported adverse events were edema, nausea, diarrhea, abdominal pain, muscle cramps, fatigue and rash.
Adverse events, regardless of relationship to study drug, that were reported in at least 10% of the patients treated with Sandoz Imatinib are shown in Table 7. No major differences were seen in the incidence or severity of adverse events between the 400 mg or 600 mg dose groups.
Table 7 Adverse Experiences Regardless of Relationship to Study Drug Reported in the Unresectable and/or Metastatic Malignant GIST (B2222) trial (≥10%) of all patients(1)
| All doses | |||||||
| (n=147) | |||||||
600 mg n=73 400 mg n=74 | |||||||
All Grades (%) | Grades 3/4 (%) | ||||||
| Preferred Term | |||||||
| Blood and lymphatic system disorders | |||||||
| Anemia | 19.7 | 5.4 | |||||
| Eye disorders | |||||||
| Lacrimation increased | 17.0 | 0 | |||||
| Gastrointestinal disorders | |||||||
| Nausea | 68.7 | 4.8 | |||||
| Diarrhea | 64.6 | 4.8 | |||||
| Abdominal pain | 57.1 | 8.8 | |||||
| Vomiting | 36.7 | 4.1 | |||||
| Flatulence | 32.0 | 0 | |||||
| Dyspepsia | 15.0 | 0 | |||||
| Constipation | 10.2 | 0.7 | |||||
| General disorders and administration site conditions | ||
| Any Fluid retention | 80.3 | 9.5 |
| Superficial edema | 78.9 | 5.4 |
| Other fluid retention events (2) | 13.6 | 5.4 |
| Fatigue | 50.3 | 1.4 |
| Pyrexia | 20.4 | 1.4 |
| Other hemorrage | 24.5 | 2.7 |
| Hepatobiliary disorders | ||
| Liver Toxicity | 12.2 | 6.8 |
| Infections and infestations | ||
| Nasopharyngitis | 23.8 | 0 |
| Upper Respiratory Tract Infection | 15.6 | 0 |
| Musculoskeletal. & connective tissue disorders | ||
| Muscle cramps | 52.4 | 0 |
| Musculoskeletal pain | 33.3 | 3.4 |
| Back pain | 24.5 | 0 |
| Join Pain | 12.9 | 0.7 |
| Nervous system disorders | ||
| Headache | 36.1 | 0 |
| Dizziness | 11.6 | 0 |
| Peaces abnormal | ||
| Loose Stools | 10.9 | 0 |
| Psychiatric disorders | ||
| Insomnia | 18.4 | 0.7 |
| Anxiety | 8.8 | 0 |
| Respiratory disorders | ||
| Pharyngolaryngeal Pain | 9.5 | 0 |
| Skin and subcutaneous disorders | ||
| Rash and related terms | 45.6 | 3.4 |
| Surgical and medical procedures | ||
| Operation | 10.2 | 4.8 |
| Vascular disorders | ||
| Any Hemorrhage | 29.9 | 8.2 |
| Upper G-I tract bleeding/perforation | 4.1 | 3.4 |
| Tumor Hemorrhage | 2.7 | 2.7 |
(1) All adverse events occurring in ³10% of patients are listed regardless of suspected relationship to treatment.
(2) Other fluid retention events included pleural effusion and ascites.
Adjuvant Treatment of GIST
The majority of both Sandoz Imatinib and placebo treated patients experienced at least one adverse reaction at some time. The most frequently reported adverse reactions were similar to those reported in other clinical studies in other patient populations and include diarrhea, fatigue, nausea, edema, decreased hemoglobin, rash, vomiting and abdominal pain. No new adverse reactions were reported in the adjuvant GIST treatment setting that had not been previously reported in other patient populations including patients with unresectable and/or malignant metastatic GIST. Drug was discontinued for adverse reactions in 57 patients (17%) and 11 patients (3%) of the Sandoz Imatinib and placebo treated patients respectively. Edema, gastrointestinal disturbances (nausea, vomiting, abdominal distension and diarrhea), fatigue, low hemoglobin and rash were the most frequently reported adverse reactions at the time of discontinuation.
Adverse reactions, regardless of relationship to study drug, that were reported in at least 5% of the patients treated with Sandoz Imatinib are shown in Table 8.
Table 8 Adverse Reactions Regardless of Relationship to Study Drug Reported in the Adjuvant GIST Trial (≥5% of Sandoz Imatinib Treated Patients)
| All CTC Grades | CTC Grade 3 and above | |||||||||||||
Sandoz Imatinib (n=337) | Placebo (n=345) | Sandoz Imatinib (n=337) | Placebo (n=345) | |||||||||||
| Preferred Term | % | % | % | % | ||||||||||
| Blood and lymphatic system disorders | ||||||||||||||
| Leukopenia | 5.0 | 2.6 | 0.3 | 0 | ||||||||||
| Eye disorders | ||||||||||||||
| Lacrimation Increased | 9.8 | 3.8 | 0 | 0 | ||||||||||
| Vision Blurred | 5.0 | 2.3 | 0 | 0 | ||||||||||
| Gastrointestinal disorders | ||||||||||||||
| Diarrhea | 59.3 | 29.3 | 3.0 | 1.4 | ||||||||||
| Nausea | 53.1 | 27.8 | 2.4 | 1.2 | ||||||||||
| Vomiting | 25.5 | 13.9 | 2.4 | 0.6 | ||||||||||
| Abdominal Pain | 21.1 | 22.3 | 3.0 | 1.4 | ||||||||||
| Dyspepsia | 17.2 | 13.0 | 0.9 | 0 | ||||||||||
| Constipation | 12.8 | 17.7 | 0 | 0.3 | ||||||||||
| Abdominal Distension | 7.4 | 6.4 | 0.3 | 0.3 | ||||||||||
| Flatulence | 8.9 | 9.6 | 0 | 0 | ||||||||||
| Abdominal Pain Upper | 6.2 | 6.4 | 0.3 | 0 | ||||||||||
| Stomatitis | 5.0 | 1.7 | 0.6 | 0 | ||||||||||
| General disorders and administration site conditions | ||||||||||||||
| Fatigue | 57.0 | 40.9 | 2.1 | 1.2 | ||||||||||
| Peripheral Edema | 26.7 | 14.8 | 0.3 | 0 | ||||||||||
| Facial Edema | 6.8 | 1.2 | 0.3 | 0 | ||||||||||
| Hepatobiliary disorders | ||||||||||||||
| Liver enzymes (ALT) Increased | 16.6 | 13.0 | 2.7 | 0 | ||||||||||
| Liver Enzymes (AST) Increased | 12.2 | 7.5 | 2.1 | 0 | ||||||||||
| Investigations | ||||||||||||||
| Hemoglobin Decreased | 46.9 | 27.0 | 0.6 | 0 | ||||||||||
| Weight Increased | 16.9 | 11.6 | 0.3 | 0 | ||||||||||
| Neutrophil Count Decreased | 16.0 | 6.1 | 3.3 | 0.9 | ||||||||||
| White Blood Cell Count Decreased | 14.5 | 4.3 | 0.6 | 0.3 | ||||||||||
| Blood Creatinine Increased | 11.6 | 5.8 | 0 | 0.3 | ||||||||||
| Weight Decreased | 10.1 | 5.2 | 0 | 0 | ||||||||||
| Blood Alkaline Phosphatase Increased | 6.5 | 7.5 | 0 | 0 | ||
| Platelet Count Decreased | 5.0 | 3.5 | 0 | 0 | ||
| Metabolic and nutritional disorders | ||||||
| Anorexia | 16.9 | 8.7 | 0.3 | 0 | ||
| Hyperglycemia | 9.8 | 11.3 | 0.6 | 1.7 | ||
| Hypokalemia | 7.1 | 2.0 | 0.9 | 0.6 | ||
| Hypocalcemia | 5.6 | 1.7 | 0.3 | 0 | ||
| Musculoskeletal. & connective tissue disorders | ||||||
| Muscle spasms | 16.3 | 3.3 | 0 | 0 | ||
| Myalgia | 12.2 | 11.6 | 0 | 0.3 | ||
| Arthralgia | 15.1 | 14.5 | 0 | 0.3 | ||
| Back Pain | 7.4 | 8.1 | 0.6 | 0 | ||
| Pain in Extremity | 7.4 | 7.2 | 0.3 | 0 | ||
| Nervous system disorders | ||||||
| Headache | 19.3 | 20.3 | 0.6 | 0 | ||
| Dizziness | 12.5 | 10.7 | 0 | 0.3 | ||
| Insomnia | 9.8 | 7.2 | 0.9 | 0 | ||
| Depression | 6.8 | 6.4 | 0.9 | 0.6 | ||
| Dysgeusia | 6.5 | 2.9 | 0 | 0 | ||
| Neuropathy Peripheral | 5.9 | 6.4 | 0 | 0 | ||
| Respiratory disorders | ||||||
| Cough | 11.0 | 11.3 | 0 | 0 | ||
| Upper Respiratory Tract Infection | 5.0 | 3.5 | 0 | 0 | ||
| Skin and subcutaneous disorders | ||||||
| Periorbital Edema | 47.2 | 14.5 | 1.2 | 0 | ||
| Rash (Exfoliative) | 26.1 | 12.8 | 2.7 | 0 | ||
| Pruritus | 11.0 | 7.8 | 0.9 | 0 | ||
| Alopecia | 9.5 | 6.7 | 0 | 0 | ||
| Rash | 8.9 | 5.2 | 0.9 | 0 | ||
| Dry skin | 6.5 | 5.2 | 0 | 0 | ||
1All adverse reactions occurring in ≥5% of patients are listed regardless of suspected relationship to treatment. A patient with multiple occurrences of an adverse reaction is counted only once in the adverse reaction category. | ||||||
Adverse Drug Reactions in clinical studies for CML and Unresectable and/or Metastatic Malignant GIST
The following adverse reactions as applicable are ranked under headings of frequency, the most frequent first, using the following convention: Very common (≥ 1/10); common (≥ 1/100, <1/10); uncommon (≥ 1/1000, < 1/100); rare (≥ 1/10,000, < 1/1000); very rare (< 1/10,000), including isolated reports. Adverse reactions reported below are based on the registration studies for CML and GIST. Frequencies are determined by reported related events according to the investigator.
Cardiovascular
Common: flushing1
Uncommon: palpitations, cardiac failure congestive (on a patient-year basis, cardiac events including congestive heart failure were more commonly observed in patients with transformed CML than in patients with chronic CML), pulmonary edema, tachycardia, hypertension1, hematoma1, hypotension1, peripheral coldness1, Raynaud’s phenomenon1
Rare: arrhythmia, atrial fibrillation, cardiac arrest, myocardial infarction, angina pectoris, pericardial effusion
Clinical laboratory tests (See Tables 9, 10 and 12)
Uncommon: blood CPK increased, blood LDH increased
Rare: blood amylase increased
Dermatologic
Common: pruritus, face edema, dry skin, erythema, alopecia, photosensitivity reaction
Uncommon: rash pustular, sweating increased, urticaria, increased tendency to bruise, exfoliative dermatitis, onychoclasis, folliculitis, petechie, psoriasis, bullous eruption, nail disorder, skin pigmentation changes, purpura, palmar-plantar erythrodysaesthesia syndrome
Rare: nail discolouration, vesicular rash, erythema multiforme, leucocytoclastic vasculitis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis (AGEP), acute febrile neutrophilic dermatosis (Sweet’s syndrome)
Digestive
Common: flatulence, abdominal distension, gastroesophageal reflux, dry mouth, gastritis
Uncommon: stomatitis, mouth ulceration, eructation, malaena, oesophagitis, ascites, gastric ulcer, hematemesis, cheilitis, dysphagia, pancreatitis
Rare: colitis, ileus, inflammatory bowel disease.
General Disorders and Administration Site Conditions
Common: weakness, anasarca, chills, rigors
Uncommon: chest pain, malaise
Hematologic (See Tables 10, 11 and 13)
Common: pancytopenia, febrile neutropenia
Uncommon: thrombocythemia, lymphopenia, eosinophilia, lymphadenopathy
Rare: aplastic anemia, hemolytic anemia
Hepatobiliary disorders
Uncommon: jaundice, hepatitis, hyperbilirubinemia
Rare: hepatic failure, hepatic necrosis (some fatal cases of hepatic necrosis have been reported)
Hypersensitivity
Rare: angioedema
Infections
Uncommon: sepsis, herpes simplex, herpes zoster, sinusitis, cellulitis, influenza, urinary tract infection, gastroenteritis
Rare: fungal infection
Metabolic and nutritional
Common: anorexia, weight decreased
Uncommon: hypophosphatemia, dehydration, gout, appetite disturbances, hyperuricemia, hypercalcemia, hyperglycemia, hyponatremia
Rare: hyperkalemia, hypomagnesemia
Musculoskeletal
Common: joint swelling
Uncommon: joint and muscle stiffness
Rare: muscular weakness, arthritis
Nervous system/psychiatric
Common: paresthesia, taste disturbance, hypoesthesia
Uncommon: depression2, libido decrease, syncope, peripheral neuropathy, somnolence, migraine, memory impairment, sciatica, restless leg syndrome, tremor
Rare: increased intracranial pressure, confusion, convulsions, optic neuritis
Neoplasm benign, malignant and unspecified (including cysts and polyps)
Uncommon: Tumor lysis syndrome
Renal
Uncommon: renal pain, renal failure acute, urinary frequency increased, hematuria
Reproductive
Uncommon: erectile dysfunction, breast enlargement, menorrhagia, menstruation irregular, sexual dysfunction, nipple pain, scrotal edema
Respiratory
Common: dyspnea, epistaxis, cough
Uncommon: pleural effusion (pleural effusion was reported more commonly in patients with GIST and in patients with transformed CML (CML-AP and CML-BC) than in patients with chronic CML), pharyngolaryngeal pain, pharyngitis
Rare: pleuritic pain, pulmonary fibrosis, pulmonary hypertension, pulmonary hemorrhage
Special senses
Common: eyelid edema, lacrimation increased, conjunctival hemorrhage, conjunctivitis, dry eye, vision blurred
Uncommon: eye irritation, eye pain, orbital edema, scleral hemorrhage, retinal hemorrhage, blepharitis, macular edema, vertigo, tinnitus, hearing loss
Rare: cataract, papilledema, glaucoma
1 Vascular disorders (flushing was most common in GIST patients and hematoma was most common in patients with GIST and transformed CML (CML-AP and CML-BC).
2 Depression may lead to suicide ideation and/or suicide attempts.
Second malignancies in Sandoz Imatinib- treated patients:
Table 9 Observed and expected numbers of cases of second malignancies (excluding non-melanoma skin cancer) in clinical trials
| Cancer type | Person-years | Number of cases Observed | Expected1 | SIR (95% CI) |
| Cancer any type | 10,967.03 | 79 | 91.16 | 0.87 (0.69-1.08) |
| Prostate | 6,106.54 | 16 | 18.70 | 0.86 (0.49-1.39) |
| Kidney | 10,769.60 | 3 | 2.26 | 1.33 (0.27-3.88) |
| Urinary bladder | 10,766.46 | 2 | 3.72 | 0.54 (0.06-1.94) |
1 Expected in the general population
SIR: Standardized incidence ratio
The numbers of cancers reported in the clinical trials were similar to those expected in the general population. The observed numbers of cases for all cancers, prostate cancer and urinary bladder cancer were slightly lower than those expected in the general population, while the number of observed kidney cancer cases was slightly higher (3 compared to 2.26 expected cases respectively). In all cases, the differences were not statistically significant.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
The overall safety profile of Sandoz Imatinib treatment in 93 pediatric patients was similar to that observed in studies with adult patients. Nausea, vomiting were the most commonly reported individual adverse events with an incidence similar to that seen in adult patients. Although most patients experienced adverse events at some time during the studies, the incidence of Grade 3/4 adverse events was low.
Significantly higher frequencies of hypocalcemia (23.5 vs 1.1%), hyperglycemia (19.6 vs 2.9%), hypoglycemia (21.6 vs 1.5%), hypophosphatemia (19.6 vs 3.3%), hypoalbuminemia (13.7 vs 0.2%) and hyponatremia (13.7 vs 0.2%) were observed in pediatric patients compared to adult patients.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Laboratory test abnormalities in CML clinical trials
Cytopenias, and particularly neutropenia and thrombocytopenia, have been a consistent finding in all studies, with the suggestion of a higher frequency at doses ≥ 750 mg (phase I study). However, the occurrence of cytopenias was also clearly dependent on the stage of the disease.
In patients with newly diagnosed CML, cytopenias were less frequent than in other CML patients (Tables 10 and 11). The frequency of Grade 3 or 4 neutropenia (ANC <1.0x10⁹/L) and thrombocytopenia (platelet count <50x109/L) were higher in blast crisis and accelerated phase (36-48% and 32-33% for neutropenia and thrombocytopenia, respectively, Table 11) as compared to chronic phase CML (27% neutropenia and 21% thrombocytopenia). In chronic phase CML a Grade 4 neutropenia (ANC <0.5x10⁹/L) and thrombocytopenia (platelet count <10x109/L) were observed in 9% and <1% of patients, respectively. The median duration of the neutropenic and thrombocytopenic episodes ranged usually from 2 to 3 weeks and from 3 to 4 weeks, respectively. These events can usually be managed with either a reduction of the dose or an interruption of treatment with Sandoz Imatinib, but can, in rare cases, lead to permanent discontinuation of treatment (see 7 WARNINGS AND PRECAUTIONS - Hematologic Toxicity).
Severe elevation of transaminases or bilirubin has been seen in <5% CML patients and were usually managed with dose reduction or interruption (the median duration of these episodes was approximately one week). Treatment was discontinued permanently because of liver laboratory abnormalities in less than 1.0% of CML patients. There have been cases of hepatic necrosis and cholestatic hepatitis and hepatic failure; in some of which outcome was fatal (see 9 DRUG INTERACTIONS).
Table 10 Newly occurring Grades 3/4 biochemical toxicities in newly diagnosed CML patients
| Parameter | Sandoz Imatinib n=551 % | IFN + Ara-C n=533 % | ||||||||||||
| Grade 3 | Grade 4 | Grade 3 | Grade 4 | |||||||||||
| Hematologic | ||||||||||||||
| Leucopenia | 9.3 | 0.5 | 12.9 | 0.8 | ||||||||||
| Neutropenia* | 13.1 | 3.6 | 20.8 | 4.5 | ||||||||||
| Thrombocytopenia* | 8.5 | 0.4 | 15.9 | 0.6 | ||||||||||
| Anemia | 3.3 | 1.1 | 4.1 | 0.2 | ||||||||||
| Biochemistry | ||||||||||||||
| Elevated creatinine | 0 | 0 | 0.4 | 0 | ||||||||||
| Elevated bilirubin | 0.9 | 0.2 | 0.2 | 0 | ||||||||||
| Elevated alkaline phosphatase | 0.2 | 0 | 0.8 | 0 | ||||||||||
| Elevated SGOT (AST)/ SGPT (ALT) | 4.7 | 0.5 | 7.1 | 0.4 | ||||||||||
*p<0.001 (Difference in Grade 3 + Grade 4 abnormalities between the two treatment groups).
Table 11 Laboratory test abnormalities in other CML clinical trials
Myeloid blast crisis n= 260 (%) | Accelerated phase n=235 (%) | Chronic phase, IFN failure n=532 (%) | ||||||||||||
| Grade 3 | Grade 4 | Grade 3 | Grade 4 | Grade 3 | Grade 4 | |||||||||
| Hematology parameters | ||||||||||||||
| Neutropenia | 16 | 48 | 23 | 36 | 27 | 9 | ||||||||
| Thrombocytopenia | 30 | 33 | 32 | 13 | 21 | <1 | ||||||||
| Anemia | 42 | 11 | 34 | 7 | 6 | 1 |
| Biochemistry parameters | ||||||
| Elevated creatinine | 1.5 | 0 | 1.3 | 0 | 0.2 | 0 |
| Elevated bilirubin | 3.8 | 0 | 2.1 | 0 | 0.6 | 0 |
| Elevated alkaline phosphatase | 4.6 | 0 | 5.5 | 0.4 | 0.2 | 0 |
| Elevated SGOT (AST) | 1.9 | 0 | 3 | 0 | 2.3 | 0 |
| Elevated SGPT (ALT) | 2.3 | 0.4 | 4.3 | 0 | 2.1 | 0 |
CTC grades: neutropenia (grade 3 ³0.5 - 1.0 x 10⁹/L), grade 4 <0.5 x 10⁹/L), thrombocytopenia (grade 3 ³10 - 50 x 109/L, grade 4 <10 x 109/L), anemia (hemoglobin ³65 - 80 g/L, grade 4 <65 g/L), elevated creatinine (grade 3 >3-6 x upper limit normal range (ULN), grade 4 >6 x ULN), elevated bilirubin (grade 3 >3-10 x ULN, grade 4 >10 x ULN), elevated alkaline phosphatase (grade 3 >5-20 x ULN, grade 4 >20 x ULN), elevated SGOT or SGPT (grade 3 >5-20 x ULN, grade 4 >20 x ULN).
Clinically relevant or severe abnormalities of the 12 patients treated with Sandoz Imatinib for DFSP in Trial B2225 are presented in Table 12.
Table 12 Laboratory Abnormalities Reported in DFSP Patients in Trial B2225
| N=12 | |||||
| CTC Grades | Grade 3 | Grade 4 | |||
| Hematology Parameters | |||||
| 17% | 0% | |||
| 17% | 0% | |||
| 0% | 8% | |||
| Biochemistry Parameters | |||||
| 0% | 8% | |||
CTC Grades: neutropenia (Grade 3 ≥0.5-1.0 x 10⁹/L, Grade 4 <0.5 x 10⁹/L), thrombocytopenia (Grade 3 ≥10 - 50 x 109/L, Grade 4 <10 x 109/L), anemia (Grade 3 ≥65-80 g/L, Grade 4 <65 g/L), elevated creatinine (Grade 3 >3-6 x upper limit normal range [ULN], Grade 4 >6 x ULN).
In unresectable and/or metastatic malignant GIST patients (study B2222), 6.8% Grade 3 or 4 SGPT (serum glutamic pyruvic transferase) elevations and 4.8% Grade 3 or 4 SGOT (serum glutamic oxaloacetic transferase) elevations were observed. Bilirubin elevation was below 3%.
Clinically relevant or severe abnormalities of routine hematologic or biochemistry laboratory values were rare (Table 13).
Table 13 Laboratory Abnormalities in the Unresectable and/or Metastatic Malignant GIST B2222 Trial
All doses (n=147) 400 mg n=73 600 mg n=74 | |
| Parameter | n (%) |
| Baseline † | New or Worsening Highest CTC Grade During Treatment | ||||||
| CTC Grading | All Grades (1-4) | Grade 3 | Grade 4 | ||||
| Hematology parameters | |||||||
| Anemia | 70 (47.6) | 8 (5.4) | 1 (0.7) | ||||
| Thrombocytopenia | 7 (4.8) | 1 (0.7) | 0 | ||||
| Neutropenia | 10 (6.8) | 11 (7.5) | 4 (2.7) | ||||
| Biochemistry parameters | |||||||
| Elevated creatinine | 8 (5.4) | 2 (1.4) | 0 | ||||
| Reduced albumin | 60 (40.8) | 5 (3.4) | 0 | ||||
| Elevated bilirubin | 5 (3.4) | 2 (1.4) | 2 (1.4) | ||||
| Elevated alkaline phosphatase | 58 (39.5) | 2 (1.4) | 0 | ||||
| Elevated SGOT (AST) | 32 (21.8) | 5 (3.4) | 2 (1.4) | ||||
| Elevated SGPT (ALT) | 19 (13.0) | 9 (6.1) | 1 (0.7) | ||||
† New or worsening of CTC Grade for any individual patient for whom data is included in the All Grade (1-4)
Baseline data cannot be inferred from this table.
CTC grades: neutropenia (grade 1= 1.5-< 2.0 x 10⁹ /L, grade 2=1.0 - < 1.5 x 10⁹ /L, grade 3 =0.5 -< 1.0 x 10⁹/L, grade 4 <0.5 x 10⁹/L), thrombocytopenia (grade 1 < LLN - 75.0 x 10⁹/L, grade 2=50.0 - <75.0 x 10⁹ /L, grade 3=10.0 - <50.0 x 10⁹/L, grade 4 <10.0 x 10⁹/L), anemia (hemoglobin: grade 1< LLN - 100 g/L, grade 2= 80 - < 100 g/L, grade 3=65 - <80 g/L, grade 4 <65 g/L), elevated creatinine (grade 1 > ULN - 1.5 x ULN, grade 2 > 1.5 - 3.0 x ULN, grade 3 >3.0 - 6.0 x upper limit normal range (ULN), grade 4 >6.0 x ULN), reduced albumin (grade 1 < LLN - 30 g/L, grade 2= 20 - < 30 g/L, grade 3 < 20 g/L, grade 4 -), elevated bilirubin (grade 1 > ULN - 1.5 x ULN, grade 2 > 1.5 - 3 x ULN, grade 3 >3-10 x ULN, grade 4 >10 x ULN), elevated alkaline phosphatase (grade 1 > ULN - 2.5 x ULN, grade 2 > 2.5-5 x ULN, grade 3 >5-20 x ULN, grade 4 >20 x ULN), elevated SGOT or SGPT (grade 1 > ULN - 2.5 x ULN, grade 2 > 2.5 - 5.0 x ULN, grade 3 >5-20 x ULN, grade 4 >20 x ULN).
8.5 Post-Market Adverse Reactions
The following types of ADRs have been reported from post-marketing experience and from additional clinical studies with Sandoz Imatinib. They include spontaneous case reports as well as serious ADRs from smaller or ongoing clinical studies and the expanded access programs. Because these reactions are reported from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to Sandoz Imatinib exposure.
Cardiovascular: Thrombosis/embolism1, pericarditis, cardiac tamponade, anaphylactic shock1, subdural hematoma1, thrombotic microangiopathy
Dermatology: Panniculitis (including erythema nodosum), lichenoid keratosis, lichen planus, pemphigus, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic syndromes (DRESS), pseudoporphyria
Digestive: Ileus/intestinal obstruction, tumor hemorrhage/tumor necrosis, gastrointestinal perforation (some fatal cases of gastrointestinal perforation have been reported), diverticulitis, gastric antral vascular ectasia (GAVE)
General: Motor vehicle accidents
Hepatic: Hepatitis, Hepatotoxicity with fatal outcomes (See 7 WARNINGS AND PRECAUTIONS – Hepatic Insufficiency and 9 DRUG INTERACTIONS)
Infections and
Infestations: Hepatitis B virus reactivation
Musculoskeletal: Musculoskeletal pain upon treatment discontinuation (including myalgia, pain in extremity, arthralgia, bone pain) following long-term treatment observed in CML patients, osteonecrosis, rhabdomyolysis/myopathy, growth retardation in children.
Neoplasm benign, malignant and unspecified (including cysts and polyps):
Tumor lysis syndrome, some of which were fatal.
Nervous system/
psychiatric: Cerebral edema (including fatalities)
Reproductive: Hemorrhagic corpus luteum / hemorrhagic ovarian cyst
Renal: Chronic renal impairment
Respiratory: Acute respiratory failure (fatal cases have been reported in patients with advanced disease, severe infections, severe neutropenia and other serious concomitant conditions), interstitial lung disease
Special senses: Vitreous hemorrhage
1 Vascular disorders.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
There is limited data on drug interactions. Since the major metabolic pathway is CYP3A4 mediated and Sandoz Imatinib is an inhibitor of CYP2D6, caution should be exercised with the co-administration of CYP3A4 inhibitors, inducers, and substrates, as well as CYP2D6 inhibitors and substrates (see 9.4 Drug-Drug Interactions).
9.3 Drug-Behavioural Interactions
Effects on ability to drive and use machines
Reports of motor vehicle accidents have been received in patients receiving Sandoz Imatinib. Patients should be advised that they may experience undesirable effects such as dizziness, blurred vision or somnolence during treatment with Sandoz Imatinib. Therefore, caution should be recommended when driving a car or operating machinery.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 14 Established or Potential Drug-Drug Interactions
| Drug Class | Source of Evidence | Effect | Clinical Comment |
| Drugs that may increase imatinib plasma concentrations | |||
| Substances that inhibit the cytochrome P450 isoenzyme (CYP3A4) activity | CT | There was a significant increase in exposure to imatinib (mean Cmax and AUC of imatinib increased by 26% and 40%, respectively) in healthy subjects when Sandoz Imatinib was co-administered with a single dose of ketoconazole (CYP3A4 inhibitor). | Caution is recommended when administering Sandoz Imatinib with inhibitors of the CYP3A4 family (e.g. ketoconazole, erythromycin, clarithromycin, itraconazole, grapefruit juice). |
| Drugs that may decrease imatinib plasma concentrations | |||
| Substances that are inducers of CYP3A4 activity | CT | Co-medications that induce CYP3A4 (e.g., dexamethasone, phenytoin, carbamazepine, rifampicin, phenobarbital or St. John’s Wort) may significantly reduce exposure to Sandoz Imatinib. Administration of rifampin 600 mg daily for eight days to 14 healthy adult volunteers, followed by a single 400 mg dose of Sandoz Imatinib increased imatinib oral dose clearance by 3.8-fold (90% CI 3.5- to 4.3-fold). Mean Cmax, AUC0-24 and AUC0-∞ decreased by 54%, 68% and 74%, respectively compared to treatment without rifampin. Similar results were observed in patients with malignant gliomas treated with Sandoz Imatinib while taking enzyme-inducing anti-epileptic drugs (EIAEDs) such as carbamazepine, oxcarbazepine, phenytoin, fosphenytoin, phenobarbital, and primidone. The plasma AUC for imatinib decreased by 73% compared to patients not on EIADs. In two published studies, concomitant administration of Sandoz Imatinib and a product containing St. John’s Wort led to a 30 to 32% reduction in the AUC of Sandoz Imatinib. | In patients in whom rifampin or other CYP3A4 inducers are indicated, alternate therapeutic agents with less enzyme induction potential should be considered. |
| Drugs that may have their plasma concentration altered by Sandoz Imatinib | |||
CYP3A4 Inhibitors, such as: Cyclosporine, Imidazole antifungals, Macrolide antibiotics, Metronidazole | T | There is limited data on drug interactions. | Caution should be exercised with the co-administration of this class of drugs. |
CYP3A4 Inducers, such as: Antiepileptics, Glucocorticoids, Rifampicin, St. John’s Wort | T | There is limited data on drug interactions. | Caution should be exercised with the co-administration of this class of drugs. |
CYP3A4 Substrates, such as: Busulphan, Calcium-channel blockers, Cyclophosphamide, Cyclosporine, Doxorubicin , Epipodophyllotoxins, Glucocorticoids, Ifosphamide, Imidazole antifungals, Macrolide antibiotics (Azithromycin, Clarithromycin, Erythromycin), PPIs, Retinoic acid, Rifampicin, Serotonin-H3 antagonists, Vinca alkaloids | CT/T | There is limited data on drug interactions. Sandoz Imatinib increases the mean Cmax and AUC of simvastatin (CYP3A4 substrate) 2- and 3.5- fold, respectively, suggesting an inhibition of the CYP3A4 by Sandoz Imatinib. In vitro, human liver microsome studies demonstrated that imatinib is a potent competitive inhibitor of CYP2C9, CYP2D6, and CYP3A4/5 with Ki values of 27, 7.5, and 8 µM, respectively. Imatinib is likely to increase the blood level of drugs that are substrates of CYP2C9, CYP2D6 and CYP3A4/5. | Caution should be exercised with the co-administration of this class of drugs. Caution is recommended when administering Sandoz Imatinib with CYP3A4 substrates with a narrow therapeutic window (e.g. cyclosporine, pimozide) (see 8 ADVERSE REACTION). |
CYP2D6 Inhibitors, such as: Dextropropoxyphene, Doxorubicin, Quinidine, Vinca alkaloids | T | There is limited data on drug interactions. | Caution should be exercised with the co-administration of this class of drugs. |
CYP2D6 Substrates, such as: Cyclophosphamide, Beta blockers, Morphine, Oxycodone, Serotonin-H3 antagonists | T | There is limited data on drug interactions. In vitro, human liver microsome studies demonstrated that imatinib is a potent competitive inhibitor of CYP2C9, CYP2D6, and CYP3A4/5 with Ki values of 27, 7.5, and 8 µM, respectively. Imatinib is likely to increase the blood level of drugs that are substrates of CYP2C9, CYP2D6 and CYP3A4/5. In vitro, Sandoz Imatinib inhibits the cytochrome P450 isoenzyme CYP2D6 activity at similar concentrations that | Caution should be exercised with the co-administration of this class of drugs. Caution is advised for CYP2D6 substrates with a narrow therapeutic window such as metoprolol. In patients treated with Sandoz Imatinib and metoprolol clinical monitoring should be considered. |
| affect CYP3A4 activity. Imatinib at 400 mg twice daily had a weak inhibitory effect on CYP2D6-mediated metoprolol metabolism, with metoprolol Cmax and AUC being increased by approximately 23%. | |||
Drugs metabolized by CYP2C9, such as: Warfarin | T | In vitro data suggest that Sandoz Imatinib has some capacity to act as an inhibitor of CYP2C9, although at concentrations higher than would be expected in plasma with recommended doses. | Caution should be exercised with the concomitant use of drugs metabolized by CYP2C9 (e.g. warfarin). In view of the potential interaction between Sandoz Imatinib and warfarin, the international normalised ratio (INR) of patients who require anticoagulation with warfarin should be monitored closely, especially when Sandoz Imatinib dose adjustments are necessary. Consideration should be given to anticoagulation with low-molecular weight heparin or unfractionated heparin. |
| Acetaminophen | CT/T | In vitro, Sandoz Imatinib inhibits acetaminophen O-glucuronidation metabolic pathway with Ki value of 58.5µmol/L. Based on the in vitro results, systemic exposure to acetaminophen would be expected to increase when co-administered with Sandoz Imatinib. A clinical study showed that co-administration of Sandoz Imatinib (400 mg/day between days two and eight) in the presence of single dose acetaminophen (1000 mg/day on day eight) in CML patients did not alter the pharmacokinetics of acetaminophen. Sandoz Imatinib pharmacokinetics was also not altered in the presence of single-dose acetaminophen. However, there are no pharmacokinetic or safety data on the concomitant use of | CAUTION is recommended in patients on the concomitant use of Sandoz Imatinib with acetaminophen |
| Sandoz Imatinib at doses >400 mg/day or the chronic use of concomitant acetaminophen and Sandoz Imatinib. |
Legend: CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
There were no clinically relevant differences in absorption when Sandoz Imatinib was administered either with food or in the fasting state. The concomitant use of grapefruit juice should be avoided.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Sandoz Imatinib (imatinib mesylate) is a protein tyrosine kinase inhibitor, which inhibits the Bcr-Abl tyrosine kinase at the in vitro, cellular, and in vivo levels. The compound selectively inhibits proliferation and induces apoptosis in Bcr-Abl positive cell lines as well as fresh leukemic cells from Philadelphia chromosome-positive chronic myeloid leukemia (CML) and acute lymphoid leukemia (ALL) patients. In colony formation assays using ex vivo peripheral blood and bone marrow samples, imatinib shows selective inhibition of Bcr-Abl positive colonies from CML patients.
In addition, imatinib is an inhibitor of several receptor tyrosine kinases: the platelet-derived growth factor receptors (PDGFR-α and PDGFR–β), and the stem cell factor (SCF), receptor (c-Kit), and it inhibits the cellular events mediated by these receptors. In vitro, imatinib inhibits proliferation and induces apoptosis in gastrointestinal stromal tumor (GIST) cells, which express an activating kit mutation.
10.2 Pharmacodynamics
In vivo, imatinib inhibits tumor growth of Bcr-Abl transfected murine myeloid cells as well as Bcr-Abl positive leukemia lines derived from CML patients in blast crisis.
Constitutive activation of the PDGFR or the Abl protein tyrosine kinases as a consequence of fusion to diverse partner proteins or constitutive production of PDGF have been implicated in the pathogenesis of several conditions including MDS/MPD, HES/CEL and DFSP. In addition, constitutive activation of c-Kit or the PDGFR has been implicated in the pathogenesis of SM. Imatinib inhibits signalling and proliferation of cells driven by dysregulated PDGFR, Kit and Abl kinase activity.
Several mechanisms of resistance have been identified from in vitro studies of Bcr-Abl positive cell lines. Mechanisms include amplification of the Bcr-Abl gene and overexpression of the multidrug resistance P-glycoprotein. Mutation or amplification of the Bcr-Abl gene has been described in relapsed patients with advanced stage CML.
Prevalence of Abl kinase domain mutations among samples of resistant CML patients varies across studies, likely reflecting variations in time frames for testing, the duration of imatinib exposure, patient selection differences, and perhaps differences in techniques and sensitivity.
The specific clinical relevance of Abl kinase domain mutations in the prognosis and management of patients with CML requires further study. It is likely that mutations will have different clinical phenotypes, with some being subject to higher-dose imatinib therapy, depending on the IC50 of the mutation, and others requiring alternative treatment strategies.
Recent in-vitro experiments have indicated that some mutations remain sensitive to Sandoz Imatinib at high concentrations, other mutants remain unresponsive to dose escalation, which may indicate a kinase-independent, or even Bcr-Abl independent mechanisms of resistance.
Currently identified possible mechanisms of resistance to Sandoz Imatinib can be categorized in two main groups: the mechanisms where Bcr-Abl is reactivated and cell proliferation remains dependent on Bcr-Abl signaling, and mechanisms where the Bcr-Abl protein remains inactivated by Sandoz Imatinib but alternative signalling pathways become activated. Whereas the primary resistance to Sandoz Imatinib seems mostly associated with amplification of the Bcr-Abl gene, secondary resistance (ie. loss of response or progression) appears to be associated with the emergence of mutations of the Bcr-Abl gene (see Table 15):
Table 15 Currently identified mechanisms of resistance to imatinib
Bcr Abl dependent mechanisms (cells remain dependent of Bcr-Abl signaling) | Bcr-Abl independent mechanisms (Bcr-Abl is inactivated) |
| Amplification of Bcr-Abl gene | Activation of signaling pathways downstream of Bcr-Abl |
| Mutations of Bcr-Abl preventing correct Bcr-Abl imatinib binding | Clonal evolution with appearance of new chromosomal abnormalities |
| Efflux of imatinib by PgP associated MDR protein | Activation of leukemogenic pathways unrelated to Bcr-Abl |
| Protein binding of imatinib (eg. to circulating AGP) |
P-gP: Protein–glyco-Protein
MDR: Multidrug Resistance
AGP: Alpha 1-acid glycoprotein
The clinical utility of detecting mutations remains to be demonstrated, since mutations have been described among Sandoz Imatinib treated patients without evidence of disease progression. In addition, the approach to managing resistance will differ by CML disease stage, irrespective of treatment. Clinical and molecular resistance is much more prevalent among patients with blast crisis and accelerated phase CML, than among patients with chronic phase CML.
10.3 Pharmacokinetics
The pharmacokinetics (PK) of Sandoz Imatinib have been evaluated in 591 patients and 33 healthy subjects over a dosage range of 25 to 1000 mg.
Absorption
Mean absolute bioavailability for the capsule formulation is 98%. The coefficient of variation for plasma imatinib AUC is in the range of 40-60% after an oral dose. When given with a high fat meal the rate of absorption of imatinib was reduced (11% decrease in Cmax and prolongation of tmax by 1.5 h), with a small reduction in AUC (7.4%) compared to fasting conditions.
Distribution
At clinically relevant concentrations of imatinib, binding to plasma proteins is approximately 95% on the basis of in vitro experiments, mostly to albumin and α1-acid glycoprotein, with little binding to lipoproteins.
In in vitro experiments, the active metabolite, CGP74588, exhibited similar protein binding behaviour to imatinib at clinically relevant concentrations.
Metabolism
CYP3A4 is the major enzyme responsible for metabolism of imatinib. Other cytochrome P450 enzymes, such as CYP1A2, CYP2D6, CYP2C9, and CYP2C19, play a minor role in its metabolism.
The main circulating active metabolite in humans is the N-demethylated piperazine derivative, formed predominantly by CYP3A4. It shows in vitro potency similar to the parent imatinib. The plasma AUC for this metabolite is about 15% of the AUC for imatinib and the terminal half-life is approximately 40 h at steady state. The plasma protein binding of the N-demethylated metabolite CGP74588 was shown to be similar to that of the parent compound in both healthy volunteers and Acute Myeloid Leukemia (AML) patients although there were variabilities in blood distribution and protein binding between AML patients. Some of the AML patients showed a significantly higher unbound fraction of both compounds which led to a higher blood cell uptake.
A phase I study has shown a 4- to 7-fold accumulation of the metabolite CGP74588 at steady state following once daily dosing, which was greater than the parent drug (See below: plasma pharmacokinetics). This might be due to the fact that CGP74588 is metabolized at a 53% lower metabolic conversion rate compared to Sandoz Imatinib in human hepatocytes. The reduced metabolic clearance of CGP74588 is further implied by in vitro experiments which showed a lower affinity of CGP74588 to CYP3A4 in comparison to STI571.
Elimination
Based on the recovery of compound(s) after an oral 14C-labelled dose of imatinib, approximately 81% of the dose was eliminated within 7 days in feces (68% of dose) and urine (13% of dose). Unchanged imatinib accounted for 25% of the dose (5% urine, 20% feces), the remainder being metabolites.
Following oral administration in healthy volunteers, the t½ was approximately 18 hours suggesting that once daily dosing is appropriate. Plasma pharmacokinetic profiles were analyzed in CML patients on Day 1 and on either Day 7 or 28, by which time plasma concentrations had reached steady state. The increase in mean imatinib AUC with increasing dose was linear and dose proportional in the range 25-1000 mg after oral administration. There was no change in the kinetics of imatinib on repeated dosing, and accumulation is 1.5-2.5 fold at steady state when Sandoz Imatinib is dosed once daily.
The effect of body weight on the clearance of imatinib is such that for a patient weighing 50 kg the mean clearance is expected to be 8.5 l/h, while for a patient weighing 100 kg the clearance will rise to 11.8 l/h. These changes are not considered sufficient to warrant dose adjustment based on body weight. There is no effect of gender on the kinetics of imatinib.
Special Populations and Conditions
Pediatrics: A total of 31 pediatric patients with either chronic phase CML (n=15), CML in blast crisis (n = 4) or acute leukemias (n=12) have been enrolled in a dose-escalation phase I trial. In this trial the effective dose in pediatric patients was not identified. This was a population of heavily pretreated patients; 45% had received prior BMT and 68% prior multi-agent chemotherapy. Newly diagnosed patients or those eligible for bone marrow transplantation were not studied. The median age was 14 years (range 3 to 20 years). Of the 31 patients, n=12 were three to 11 years old at the start of the study, n= 17 were between 12 and 18 years, and only two were more than 18 years old. Patients were treated with doses of Sandoz Imatinib of 260 mg/m2/day (n=6), 340 mg/m2/day (n=11), 440 mg/m2/day (n= 8) and 570 mg/m2/day (n=6).
- Dosing based upon body surface area resulted in some patients receiving higher than the adult therapeutic dose, and the effect of this on pediatric patient safety is limited.
As in adult patients, imatinib was rapidly absorbed after oral administration in pediatric patients in both phase I and phase II studies. Dosing in children at 260 and 340 mg/m2/day achieved similar exposure, respectively, as doses of 400 mg and 600 mg in adult patients, although this was based upon a small sample size. The comparison of AUC0-24 on Day 8 versus Day 1 at the 340 mg/m2/day dose level revealed a 1.7- fold drug accumulation after repeated once daily dosing. As in adults, there was considerable inter-patient variability in the pharmacokinetics, and the coefficient of variation for AUC0-24 ranged from 21% (260 mg/m2/day) to 68% (570 mg/m2/day). The AUC did not increase proportionally with dose within the range of doses examined. The active metabolite, GCP 74588, contributed about 20% of the AUC for imatinib. Total plasma clearance is about 8 - 10 L/h at steady state. The plasma AUC of imatinib is significantly lower (p=0.02) in children at ages between 2 and <12 years old (29.3 ug*hr/mL) than those at ages between 12 and <20 years old (34.6 ug*hr/mL). However, the difference between the two age groups does not seem to be clinically significant, only 15% of difference (geometric mean of 29.3 in children compared to 34.6 in adolescents). The AUC exposure in both age groups falls within the adult AUC(0-24h) range, between 24.8 and 39.7 μg*h/ml, achieved at 400 mg and 600 mg daily doses, respectively.
- Geriatrics: Based on population PK analysis, there was an effect of age on the volume of distribution (12% increase in patients > 65 years old). This change is not thought to be clinically significant.
Hepatic Insufficiency: In a study of patients with mild and moderate hepatic dysfunction (Table 16), the mean exposure to imatinib (dose normalized AUC) did not differ significantly compared with patients with normal liver function. There was a tendency toward an increased exposure in patients with severe liver dysfunction (approximately 45% increase compared with patients with normal liver function). In this study up to 500 mg daily was used in patients with mild liver dysfunction, up to 400 mg daily in patients with moderate, and up to 300 mg daily in patients with severe liver dysfunction.
In the severe liver dysfunction group 29% of patients experienced serious adverse events at the 100 mg dose level, 60% at the 200 mg and 50% of patients treated at the 300 mg dose levels. (See sections 7 WARNINGS AND PRECAUTIONS – Hepatic Insufficiency and 4.2 Recommended Dose and Dosage Administration – Hepatic Impairment)
Table 16 Liver Dysfunction Classification
| Liver Dysfunction | Liver Dysfunction Tests |
| Mild | Total bilirubin: = 1.5 ULN SGOT: >ULN (can be normal or <ULN if Total bilirubin is >ULN) |
| Moderate | Total bilirubin: >1.5-3.0 ULN SGOT: any |
| Severe | Total bilirubin: >3-10 ULN SGOT: any |
ULN=upper limit of normal for the institution
SGOT= serum glutamic oxaloacetic transferase
Renal Insufficiency: Imatinib and its metabolites are not excreted via the kidney to a significant extent.
In a study of patients with varying degrees of renal dysfunction (mild, moderate and severe - see Table 17 below for renal function classification), the mean exposure to imatinib (dose normalized AUC) increased 1.5- to 2-fold compared to patients with normal renal function, which corresponded to an elevated plasma level of AGP, a protein to which imatinib binds strongly. There was a correlation with the incidence of serious adverse events and decreasing renal function (p = 0.0096). In this study, 800 mg daily was used in patients with mild renal dysfunction and 600 mg daily was used in patients with moderate renal dysfunction. The 800 mg dose was not tested in patients with moderate renal dysfunction due to the limited number of patients enrolled. Similarly, only 2 patients with severe renal dysfunction were enrolled at the low (100 mg) dose, and no higher doses were tested. No patients on hemodialysis were enrolled in the study. Since the effect of Sandoz Imatinib treatment on patients with severe renal dysfunction and on hemodialysis has not been sufficiently assessed, treatment of these patients with imatinib cannot be recommended. Patients with mild or moderate renal dysfunction should be treated with caution, and be given the minimum recommended dose of 400 mg daily as starting dose. The dose should be reduced if not tolerable. If tolerated, the dose can be increased for lack of efficacy. Dosing of patients with moderate renal insufficiency at 800 mg cannot be recommended as this has not been investigated (see sections 8 ADVERSE REACTIONS; 4.2 Recommended Dose and Dosage Administration – Renal Impairment; 7 WARNINGS AND PRECAUTIONS – Renal Insufficiency).
Table 17 Renal function classification
| Renal dysfunction | Renal function tests |
|---|---|
| Mild | CrCL = 40-59 mL/min |
| Moderate | CrCL = 20-39 mL/min |
| Severe | CrCL = < 20 mL/min |
CrCL = Creatinine Clearance
11 STORAGE, STABILITY AND DISPOSAL
- 100 mg: Store Sandoz Imatinib at room temperature (15-30oC). Protect tablets from moisture.
- 400 mg: Store Sandoz Imatinib at room temperature (15-25oC). Protect tablets from moisture.
12 SPECIAL HANDLING INSTRUCTIONS
No special requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Imatinib mesylate
Chemical name: (4-[(4-Methyl-1-piperazinyl)methyl]-N-[4-methyl-3-[[4-(3-pyridinyl)-2-pyrimidinyl]amino]-phenyl]benzamide methanesulfonate)
Molecular formula and molecular mass: C29H31N7O . CH4SO3 and 589.7
Structural formula:
Physicochemical properties:
- Description: White to off-white to brownish or yellowish tinged powder
- Solubility: Very to freely soluble in water and aqueous solutions at low pH values. The solubility drops in aqueous buffer solution to “insoluble” with an increase of the pH from pH 5.5 to 8.0.
- pH: The pH of a 1% solution in water is approximately 5.5
- Melting range: 210-220°C (beta crystal form)
- pKa: 7.8, 3.8, and 3.3
Distribution coefficient: > 100 (n-octanol/phosphaste buffer pH 6.8 medium at 37±1°C).
Log D = 3.5
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Chronic Myeloid Leukemia
Newly diagnosed chronic myeloid leukemia (adults)
Trial Design and Study Demographics
An open label, multicenter, international randomized phase III study has been conducted in adult patients with newly diagnosed chronic myeloid leukemia (CML) in which Sandoz Imatinib was compared to a combination of interferon-α plus cytarabine (IFN+Ara-C). Patients showing a lack of response [lack of complete hematologic response (CHR) at six months, increasing white blood cell (WBC) counts or no major cytogenetic response (MCyR) at 24 months], loss of response (loss of CHR or MCyR) or severe intolerance to treatment were allowed to cross over to the alternate treatment arm.
In the Sandoz Imatinib arm, patients were treated with 400 mg daily. Dose escalations were allowed from 400 mg daily to 600 mg daily, then from 600 mg daily to 800 mg daily. In the IFN+Ara-C arm, patients were treated with a target dose of IFN of 5 MU/m2/day subcutaneously. In addition, subcutaneous Ara-C, (20 mg/m2/day), was administered for ten days every month until a complete cytogenetic response (CCyR) had been achieved and confirmed by cytogenetic analysis on two consecutive occasions not more than three months apart. In this trial, at least 80% of patients were brought to baseline conditions by previous treatment with hydroxyurea. Median WBC decreased from 90 x 109/L at diagnosis to 19x109/L. Moreover concurrent administration of hydroxyurea during the first six months of the study was permitted in 44.6% and 74.3% of patients in the Sandoz Imatinib and IFN+Ara-C arms, respectively, to keep the WBC under 20x109/L.
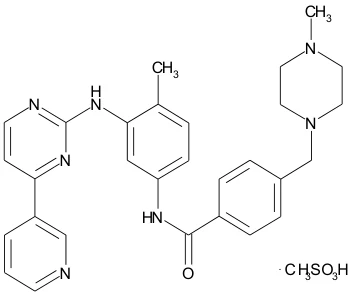
A total of 1106 patients were randomized at 177 centers in 16 countries, 553 to each arm. Baseline characteristics were well balanced between the two arms. Median age was 51 years (range 18 to 70 years), with 21.9% of patients 60 years of age or older. There were 59% males and 41% females: 89.9% Caucasian and 4.7% Black patients. At an analysis 7 years after the last patient had been recruited, the median duration of first-line treatment was 82 months and 8 months in the Sandoz Imatinib and IFN + Ara-C arms, respectively, with 60% of patients randomized to Sandoz Imatinib still receiving first-line treatment. Due to discontinuations and crossover, only 2% of those patients randomized to IFN+Ara-C were still on first-line treatment. In the IFN+Ara-C arm withdrawal of consent (13.7%) was the most frequent reason for discontinuation of first-line therapy. Of the patients who crossed over from the control arm (360/553), the reasons for crossover to the Sandoz Imatinib arm were intolerance to treatment (N=145, 40.3%), lack of response (N=97, 27.0%), progression (N=77, 21.4%), and patient refusal to continue on IFN + Ara-C (N=41, 11.4%).
Results
The primary efficacy endpoint of the study was progression-free survival. Progression was defined as any of the following events: progression to accelerated phase or blast crisis (AP/BC); death; loss of CHR or MCyR; or an increasing WBC despite appropriate therapeutic management in those patients not achieving a CHR. Major cytogenetic response, complete hematologic response, evaluation of minimal residual disease (molecular response), time to accelerated phase or blast crisis, and survival and quality of life were the main secondary endpoints. Response data are provided in Table 18.
Table 18 Response in newly diagnosed CML study (First Line) (84-month data)
| Best response rates | Sandoz Imatinib n=553 | IFN + Ara-C n=553 |
| Hematological response1 | ||
| CHR rate n (%) | 534 (96.6)* | 313 (56.6)* |
| [95% CI] | [94.7, 97.9] | [52.4, 60.8] |
| Cytogenetic response2 | ||
| Major Cytogenetic response n (%) | 472 (85.4)* | 93 (16.8)* |
| [95% CI] | [82.1, 88.2] | [13.8, 20.2] |
| Unconfirmed3 | 490 (88.6)* | 129 (23.3)* |
| Complete Cytogenetic Response n (%) | 413 (74.7)* | 36 (6.5) |
| [95% CI] | [70.8, 78.3] | [4.6, 8.9] |
| Unconfirmed3 | 456 (82.5)* | 64 (11.6)* |
| Molecular response4 | ||
Major response at 12 months (%) Major response at 24 months (%) | 40 54* | 2 NA5 |
*p<0.001, Fischer’s exact test
1 Hematological response criteria (all responses to be confirmed after ≥4 weeks): WBC<10x109/L; platelet <450x109/L; myelocyte+metamyelocyte <5% in peripheral blood; no blasts and promyelocytes in peripheral blood; basophils <20%; no extramedullary involvement.
2 Cytogenetic response criteria : complete (0% Ph+metaphases or partial (1-35%).
3 Unconfirmed cytogenetic response is based on a single bone marrow cytogenetic evaluation, therefore unconfirmed complete or partial cytogenetic responses might have had a lesser cytogenetic response on a subsequent bone marrow evaluation.
4 Major molecular response criteria: in the peripheral blood, reduction of ≥ 3 logarithms in the amount of Bcr-Abl transcripts (measured by real-time quantitative reverse transcriptase PCR assay) over a standardized baseline.
5 Not Applicable: insufficient data, only two patients available with samples
For analysis of long-term outcomes patients randomized to receive Sandoz Imatinib were compared with patients randomized to receive IFN+ Ara-C. Patients who crossed over prior to progression were not censored at the time of crossover, and events that occurred in these patients following crossover were attributed to the original randomized treatment.
With 7 years of follow-up, there were 93 (16.8%) progression events in the Sandoz Imatinib arm: 37 (6.7%) involving progression to AP/BC, 31 (5.6%) loss of MCyR, 15 (2.7%) loss of CHR or increase in WBC and 10 (1.8%) CML unrelated deaths. In contrast, there were 165 (29.8%) events in the IFN+Ara-C arm of which 130 occurred during first-line treatment with IFN+Ara-C. These progression events in the IFN + Ara-C arm included 61 (11%) involving progression to AP/BC, 31 (5.6%) loss of MCyR, 46 (8.3%) loss of CHR, 18 (3.3%) increase in WBC, and 5 (0.9%) CML-unrelated deaths.
The estimated rate of progression-free survival at 84 months was 81.2% with [95% CI: 78%, 85%] in the Sandoz Imatinib arm and 60.6% with [95% CI: 56%, 65%] in the IFN+Ara-C arm (p<0.001) (Figure 1).
The estimated rate of patients free of progression to AP or BC at 84 months was significantly higher in the Sandoz Imatinib arm compared to the IFN+Ara-C arm (92.5% with [95% CI: 90, 95] versus 85.1% with [95% CI: 82, 89], (p<0.001 respectively)) (Figure 2).
Figure 1 Time to progression (ITT principle)
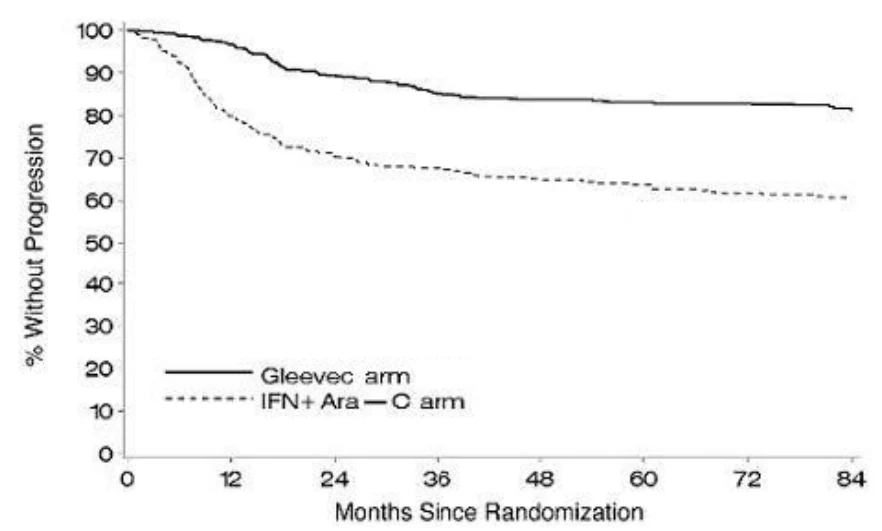
Figure 2 Time to progression to AP or BC (ITT principle)
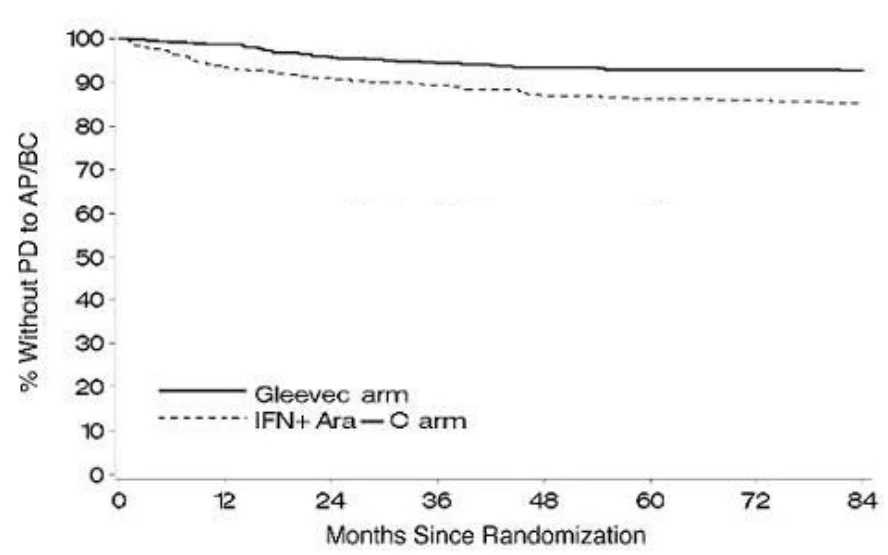
A total of 71 (12.8%) and 85 (15.4%) patients died in the Sandoz Imatinib and IFN+Ara-C groups, respectively. At 84 months the estimated overall survival is 86.4% [95% CI: 83, 90] vs. 83.3% [95% CI: 80, 87] in the randomized Sandoz Imatinib and IFN+Ara-C groups, respectively (p=0.073, log-rank test; p=0.065, Wilcoxon test). The probability of remaining progression-free at 60 months was 95% for patients who were in complete cytogenetic response with major molecular response (≥ 3 log reduction in Bcr-Abl transcripts as measured by quantitative reverse transcriptase polymerase chain reaction) at 12 months, compared to 89% for patients in complete cytogenetic response, but without a major molecular response, and 70% in patients who were not in complete cytogenetic response at 12 months (p<0.001).
In this study, dose escalation were allowed from 400 mg daily to 600 mg daily, then from 600 mg daily to 800 mg daily. After 42 months of follow-up, half of the patients who had increased the dose due to lack of CHR at 3 months, achieved a CHR thereafter. Of the 55 patients who did not have a dose increase 44 patients (80%) also achieved a CHR. Six (50%) of 12 patients with one assessment indicating loss of PCyR or CCyR achieved a MCyR after dose increase and 12 (48%) of the 25 patients without dose increase also achieved a MCyR. Eleven patients who did achieve a complete hematological response at 3 months and a major cytogenetic response at 12 months while on 400 mg daily dose experienced a confirmed (within 4 weeks) loss of their cytogenetic response. Of those, 4 patients did escalate up to 800 mg daily and 2 of them regained a cytogenetic response (1 partial and 1 complete, the latter also achieving a molecular response), while out of 7 patients that did not escalate the dose, only one regained a complete cytogenetic response. The percentage of some adverse events were higher in the 40 patients in whom the dose was increased to 800 mg daily compared to the population of patients before dose increase (n=551). These more frequent adverse events included gastrointestinal hemorrhages, conjunctivitis, elevation of transaminases or bilirubin, hematologic toxicities (mainly anemia and thrombocytopenia) and upper respiratory tract infections. Other adverse events were reported with lower or equal frequency.
Quality of Life (QoL) was measured using the validated FACT-BRM instrument. All domains were assessed and showed that patients in the Sandoz Imatinib arm had significantly higher scores compared to those in the IFN-Ara-C arm. QoL data showed that patients maintain their physical, functional and emotional well-being while on treatment with Sandoz Imatinib.
Pediatric newly diagnosed chronic myeloid leukemia
A total of 51 pediatric patients with newly diagnosed and untreated CML in chronic phase were enrolled in an open-label, multicenter, single arm phase II trial. Patients were treated with Sandoz Imatinib 340 mg/m2/day, with no interruptions in the absence of dose limiting toxicity. Sandoz Imatinib treatment induces a rapid response in newly diagnosed pediatric CML patients with a CHR of 80% after 8 weeks of therapy. Those patients for whom cytogenetics was evaluable (46/51) developed a complete cytogenetic response (CCyR) at a rate of 72%. Additionally, partial cytogenetic response (PCyR) was observed in 15% adding up to a Major Cytogenetic response (MCyR) rate of 87%. The majority of patients who achieved a CCyR developed the CCyR between months 3 and 10 with a median time to response based on the Kaplan-Meier estimate of 5.6 months. Fifteen of these patients who achieved CCyR underwent quantitative measurement of BCR-ABL transcript (PCR). Six of these patients (40%) achieved a major molecular response (five of which were complete responses). Patients were allowed to be removed from protocol therapy to undergo alternative therapy including hematopoietic stem cell transplantation as this is the known curative option. Thirty one children received stem cell transplantation. Of the 31 children, 5 were transplanted after disease progression on study and 1 withdrew from study during the first week of treatment and received transplant approximately 4 months after withdrawal. Twenty five children withdrew from protocol therapy to undergo stem cell transplant after receiving a median of 9 twenty-eight day courses (range 4 to 24). Of the 25 patients 13 (52%) had CCyR and 5 (20%) had PCyR at the end of protocol therapy.
Late chronic phase CML and advanced stage CML
Three large, international, open-label, uncontrolled phase II studies were conducted in patients with Philadelphia chromosome-positive (Ph+) chronic myeloid leukemia (CML) in advanced, blast or accelerated phase disease, in myeloid blast crisis or with CML in the chronic phase in patients who were resistant/refractory to or intolerant of prior interferon-alpha (IFN) therapy. About 45% of patients were women and 6% were Black. In clinical studies 38-40% of patients were ≥ 60 years of age and 10-12% of patients were ≥ 70 years of age.
Chronic phase, Interferon-failure
532 patients were treated at a starting dose of 400 mg; The patients were distributed in three main categories according to their response to prior interferon therapy: hematologic failure (29%), cytogenetic failure (35%), or intolerance to interferon (36%). Patients had received a median of 14 months of prior IFN therapy at doses ≥ 25 x106 IU/week and were all in late chronic phase, with a median time from diagnosis of 32 months. The primary efficacy variable of the study was the rate of major cytogenetic response (complete plus partial response, 0 to 35% Ph+ metaphases in the bone marrow). Median duration of treatment was 29 months with 81% of patients treated for ≥ 24 months (maximum = 31.5 months). Efficacy results are reported in Table 16. In this study, 65% of the patients achieved a major cytogenetic response (MCyR), which was confirmed in 59% of patients. Complete cytogenetic response (CCyR) was achieved in 48% of patients, and was confirmed in 38% of patients.
Accelerated phase
235 patients with accelerated phase disease were enrolled. The first 77 patients were started at 400 mg, the protocol was subsequently amended to allow higher dosing and the remaining 158 patients were started at 600 mg.
The primary efficacy variable was the rate of hematologic response, reported as either complete hematologic response, no evidence of leukemia (i.e., clearance of blasts from the marrow and the blood, but without a full peripheral blood recovery as for complete responses), or return to chronic phase CML. Median duration of treatment was 18 months with 45% of patients treated for ≥ 24 months (maximum = 35 months). A confirmed hematologic response was achieved in 72% of patients (Table 16). Importantly, 27% of patients also achieved a major cytogenetic response, which was confirmed in 21% of patients. Complete cytogenetic response was achieved in 20% of patients, and confirmed in 16%. For the patients treated at 600 mg, the 24-month estimate of the rate of progression-free survival and overall survival is 50% and 66%, respectively. In a multivariate analysis, a dose of 600 mg was associated with an improved time to progression, independent of platelets ≥ 100 x 109/L, blood blasts < 15%, and hemoglobin ≥ 10 g/L.
Myeloid blast crisis
260 patients with myeloid blast crisis were enrolled. 165 (63%) had received prior chemotherapy for treatment of either accelerated phase or blast crisis (“pretreated patients”) whereas 95 (37%) had not (“untreated patients”). The first 37 patients were started at 400 mg, the protocol was subsequently amended to allow higher dosing and the remaining 223 patients were started at 600 mg.
The primary efficacy variable was the rate of hematologic response, reported as either complete hematologic response, no evidence of leukemia, or return to chronic phase CML using the same criteria as for the study in accelerated phase. Median duration of treatment was 4 months with 21% of patients treated for ≥ 12 months and 10% for ≥ 24 months (maximum = 35 months). In this study, 31% of patients achieved a hematologic response (36% in previously untreated patients and 22% in previously treated patients).
Table 19 Response in other CML clinical studies
Chronic phase IFN failure 400mg (n=532) | Accelerated phase 600 mg n=158 400 mg n=77 | Myeloid blast crisis 600 mg n=223 400 mg n=37 | |||||||||
| % of patients (CI 95%) | |||||||||||
| Hematologic response1 | 95% (92.3,96.3) | 72% (65.3, 69.2) | 31% (25.2, 36.8) | ||||||||
Complete hematologic response (CHR) | 95% | 42% | 8% | ||||||||
| No evidence of leukemia (NEL) | Not applicable | 12% | 5% | ||||||||
| Return to chronic phase (RTC) | Not applicable | 17% | 18% | ||||||||
Major cytogenetic response2 Unconfirmed Confirmed | 65% (60.2, 68.5) 59% ( 54.9, 63.4) | 27% (21.7, 33.4) 21% (16.2, 27.1) | 15% (11.2, 20.4) 7% (4.5, 11.2) | ||||||||
Complete Cytogenetic response3 Unconfirmed Confirmed | 48% 38% | 20% 16% | 7% 2% |
1Hematologic response criteria (all responses to be confirmed after ≥4 weeks):
CHR: Chronic phase study [WBC <10 x109/L, platelet <450 x109/L, myelocytes+metamyelocytes <5% in blood, no blasts and promyelocytes in blood, basophils <20%, no extramedullary involvement] and in the accelerated and blast crisis studies [ANC≥1.5 x10⁹/L, platelets ≥100 x109/L, no blood blasts, BM blasts <5% and no extramedullary disease]
NEL: same criteria as for CHR but ANC ≥1 x10⁹/L and platelets ≥20 x109/L (accelerated and blast crisis studies)
RTC: <15% blasts BM and PB, <30% blasts+promyelocytes in BM and PB, <20% basophils in PB, no extramedullary disease other than spleen and liver (accelerated and blast crisis studies).
BM=bone marrow, PB=peripheral blood
2Cytogenetic response criteria: A major response combines both complete and partial responses: complete (0% Ph+ metaphases), partial (1%-35%).
3Complete cytogenetic response confirmed by a second bone marrow cytogenetic evaluation performed at least one month after the initial bone marrow study.
The median time to hematologic response was 1 month.
In late chronic phase CML, with a median time from diagnosis of 32 months, an estimated 87.8% of patients who achieved MCyR maintain their response 2 years after achieving their initial response. After 2 years of treatment, an estimated 85.4% of patients were free of progression to AP or BC, and estimated overall survival was 90.8% [88.3, 93.2].
In accelerated phase, median duration of hematologic response was 28.8 months for patients with an initial dose of 600 mg (16.5 months for 400 mg, p=0.0035). An estimated 63.8% of patients who achieved MCyR were still in response 2 years after achieving initial response. The median survival was 20.9 [13.1, 34.4] months for the 400 mg group and was not yet reached for the 600 mg group (p=0.0097). An estimated 46.2% [34.7, 57.7] vs. 65.8% [58.4, 73.3] of patients were still alive after 2 years of treatment in the 400 mg vs. 600 mg dose groups, respectively (p=0.0088).
In blast crisis, the estimated median duration of hematologic response is 10 months. An estimated 27.2% [16.8, 37.7] of hematologic responders maintained their response 2 years after achieving their initial response. Median survival was 6.9 [5.8, 8.6] months and an estimated 18.3% [13.4, 23.3] of all patients with blast crisis were alive 2 years after start of study.
Acute Lymphoblastic Leukemia
Newly diagnosed Ph+ ALL
Sandoz Imatinib, when used as a single agent in an induction phase in a controlled trial of 55 newly diagnosed patients aged 55 years and over (ADE10) resulted in a significantly higher rate of complete hematological remission when compared to chemotherapy induction (96.3% vs. 50%; p=0.0001).
Table 20 Effect of Sandoz Imatinib in newly diagnosed Ph+ ALL patients (600 mg/day)
| Study | ADE10§ (Controlled study) | |||||||
|---|---|---|---|---|---|---|---|---|
Sandoz Imatinib induction | CHT induction | |||||||
| N (evaluable for CHR) | 27 | 26 | ||||||
| CHR (%) | 96 | 50* | ||||||
| 95% C.I. | 81 - 100 | 30 - 70 | ||||||
| N (overall) | 28 | 27 | ||||||
| 1-year DFS (%) | 54 | |||||||
| 1-year OS (%) | 54 | |||||||
CHR = complete haematological response CHT = chemotherapy * p<0.01 § after induction (Complete remission was achieved as a result of induction treatment in both arms). | ||||||||
Relapsed or refractory Ph+ ALL
In study 0109, a total of 43 patients with relapsed or refractory Ph+ALL received the initial dose of 600 mg and 3 patients with relapsed or refractory Ph+ALL received the initial dose 400 mg.
The results in 3 patients with relapsed or refractory Ph+ALL showed that the initial dose of 400 mg/day was insufficient for achieving hematological responses.
Table 21 Effect of Sandoz Imatinib on relapsed or refractory Ph+ALL (600 mg/day)
Phase II Study No. 0109 (N=46)1 N(%) | |
| Confirmed Hematologic Response | 12 (26.1) |
| CHR | 4 (8.7) |
| NEL | 1(2.2) |
| RTC | 7 (15.2) |
| Confirmed Cytogenetic Responses | |
| MCyR | 12 (26.1) |
| CCyR | 7 (15.2) |
| PCyR | 5 (10.9) |
143/46 patients were relapsed or refractory Ph+ALL
NEL= No Evidence of Leukemia
CHR = Complete Hematological Response
RTC= Return to Chronic Phase
The median time to hematologic response was 1 month.
The median duration of hematologic response was 3.42 months
The median time to progression in patients started with 600 mg was 2.56 months
Myelodysplastic/Myeloproliferative Diseases (MDS/MPD)
One open label, multicentre, phase II clinical trial (Study B2225) was conducted testing Sandoz Imatinib in diverse populations of patients suffering from life-threatening diseases associated with Abl, Kit or PDGFR protein tyrosine kinases. This study included 7 patients with MDS/MPD. These patients were treated with Sandoz Imatinib 400 mg daily. The ages of the enrolled patients ranged from 20 to 86 years. A further 24 patients with MDS/MPD aged 2 to 79 years were reported in 12 published case reports and a clinical study. These patients also received Sandoz Imatinib at a dose of 400 mg daily with the exception of three patients who received lower doses. Of the total population of 31 patients treated for MDS/MPD, 14 (45%) achieved a complete hematologic response and 9 (29%) a complete cytogenetic response (39% including major and partial responses). Of note, the malignancy carried a translocation, usually involving the chromosome t5q33 or t4q12, resulting in a PDGFR gene re-arrangement in 14 evaluable patients. All of these patients achieved a hematologic response (12 completely). Cytogenetic response was evaluated in 11 out of 14 patients, all of whom responded (9 patients completely). Only 2 (13%) out of the 16 patients without a translocation associated with PDGFR gene re-arrangement achieved a complete hematologic response and one (6%) achieved a major cytogenetic response. A further patient with a PDGFR gene re-arrangement in molecular relapse after bone marrow transplant responded molecularly. Median duration of therapy was 12.9 months (0.8 to 26.7) in the 7 patients treated within Study B2225 and ranged between 1 week and more than 18 months in responding patients in the published literature. Results are provided in Table 22.
Table 22 Response in MDS/MPD
| N | Complete hematologic response | Cytogenetic response | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| (Number of patients) | (%) | (%) | ||||||||
| Overall population | 31 | 14 (45) | 12 (39) | |||||||
| Chromosome t5 involved | 12 | 12 (100) | 10 (83) | |||||||
| Chromosome t4 involved | 2 | 2 (100) | 1 (50) | |||||||
| Others / no translocation | 16 | 2 (13) | 1 (6) | |||||||
| Molecular relapse | 1 | NE | NE | |||||||
| NE: Not evaluable | ||||||||||
Aggressive sub-types of Systemic Mastocytosis (ASM and SM-AHNMD)
One open-label, multicentre, phase II clinical trial (Study B2225) was conducted testing Sandoz Imatinib in diverse populations of patients suffering from life-threatening diseases associated with Abl, Kit or PDGFR protein tyrosine kinases. This study included 5 patients with aggressive systemic mastocytosis (ASM). The ASM patients were treated with Sandoz Imatinib 100 mg to 400 mg daily. The ages of these
5 patients ranged from 49 to 74 years. A further 25 patients with ASM aged 26 to 85 years were reported in 10 published case reports and case series. These patients also received Sandoz Imatinib at doses of 100 mg to 400 mg daily. Of the total population of 30 patients treated for SM, 10 (33%) achieved a complete hematologic response and 9 (30%) a partial hematologic response (63% overall response rate).
Cytogenetic abnormalities were evaluated in 21 of the 30 ASM patients treated Sandoz Imatinib from the published reports and Study B2225. Eight out of these 21 patients had FIP1L1-PDGFRα fusion kinase (or CHIC2 deletion). Patients with this cytogenetic abnormality are most likely to be males and to have eosinophilia associated with their systemic mast cell disease. Two patients had a Kit mutation in the juxtamembrane region (one Phe522Cys and one K509I). Sixteen patients had unknown or no detectable cytogenetic abnormality and 50% achieved hematologic responses (7 partial and 1 complete) with Sandoz Imatinib. Four patients showed a D816V c-Kit mutation and one with concomitant CML and SM achieved a complete hematologic response with Sandoz Imatinib. The majority of ASM patients reported in the reviewed published medical literature with the D816V c-Kit mutation are not considered sensitive to Sandoz Imatinib. Median duration of Sandoz Imatinib therapy for the 5 ASM patients in Study 2225 was 13 months (range 1.4-22.3 months) and ranged between 1 month and more than 30 months in the responding patients reported in the published medical literature. A summary of the response rates to Sandoz Imatinib in ASM is provided in Table 23.
Table 23 Response in ASM
| Cytogenetic abnormality | Number of patients | Complete hematologic response | Partial hematologic response | ||||||
|---|---|---|---|---|---|---|---|---|---|
| FIP1L1-PDGFRα fusion kinase (or CHIC2 deletion) | 8 | 8 (100%) | 0 (0%) | ||||||
| Juxtamembrane mutation | 2 | 0 (0%) | 2 (100%) | ||||||
| Unknown or no cytogenetic abnormality detected | 16 | 1(6%) | 7(44%) | ||||||
| D816V mutation | 4 | 1*(25%) | 0 (0%) | ||||||
| Overall totals | 30 | 10 (33%) | 9 (30%) | ||||||
| *Patient had concomitant CML and ASM | |||||||||
Hypereosinophilic Syndrome and/or Chronic Eosinophilic Leukemia (HES/CEL)
One open-label, multicentre, phase II clinical trial (Study B2225) was conducted testing Sandoz Imatinib in diverse populations of patients suffering from life-threatening diseases associated with Abl, Kit or PDGFR protein tyrosine kinases. In this study, 14 patients with HES/CEL were treated with 100 mg to 1000 mg of Sandoz Imatinib daily (the recommended dose for this indication is 100 mg/day to 400 mg/day). The ages of these patients ranged from 16 to 64 years. A further 170 patients with HES/CEL aged 11 to 78 years were reported in 42 published case reports and case series. These patients received Sandoz Imatinib at doses of 75 mg to 800 mg daily. Results are provided in Table 24.
Table 24 Response in HES/CEL
| Cytogenetic abnormality | Number of patients | Complete hematologic response | Partial hematologic response |
|---|---|---|---|
| Positive FIP1L1-PDGFRα fusion kinase | 69 | 69 (100%) | 0 (0%) |
| Cytogenetic abnormality | Number of patients | Complete hematologic response | Partial hematologic response |
|---|---|---|---|
| Negative FIP1L1-PDGFRα fusion kinase | 56 | 12 (21%) | 9 (16%) |
| Unknown cytogenetic abnormality | 59 | 34 (58%) | 7 (12%) |
| Overall totals | 184 | 115 (62%) | 16 (9%) |
Dermatofibrosarcoma Protuberans (DFSP)
One open label, multicentre, phase II clinical trial (Study B2225) was conducted testing Sandoz Imatinib in a diverse population of patients suffering from life-threatening diseases associated with Abl, Kit or PDGFR protein tyrosine kinases. This study included 12 patients with DFSP who were treated with Sandoz Imatinib 800 mg daily. The primary efficacy endpoint was an objective response rate. The age of the DFSP patients ranged from 23 to 75 years; DFSP was metastatic, locally recurrent following initial resective surgery and not considered amenable to further resective surgery at the time of study entry.
The median duration of therapy in Study B2225 was 6.2 months, with a maximum duration of 24.3 months. In Study B2225, one of the 12 DFSP patients achieved a complete response (8%) and 8 patients (66%) achieved partial response, 3 of which were rendered disease free by surgery. Responses to treatment are described in Table 25.
Table 25 Response in DFSP
| Tumor response | Number of patients (N=12) (Study B2225) | % | ||
|---|---|---|---|---|
| Complete response | 1 | 8 | ||
| Partial response ® | 8 (5+3) | 66 | ||
| Total | 9 | 75 | ||
| ® 5 patients made disease free by surgery | ||||
A further 6 DFSP patients treated with Sandoz Imatinib are reported in 5 published case reports. Their ages ranging from 18 months to 49 years. The adult patients reported in the published literature were treated with either 400 mg (4 cases) or 800 mg (1 case) Sandoz Imatinib daily. The pediatric patient received 400 mg/m2/daily, subsequently increased to 520 mg/m2/daily. The approved pediatric dose in CML is 340 mg/m2/day (rounded to the nearest 100 mg, i.e not to exceed 600 mg). In the published literature duration of therapy ranged between 4 weeks and more than 20 months. Three (50%) of the 6 patients achieved a complete response and 2 (33%) achieved partial response, with one of the partial responders then rendered disease free by surgery.
Unresectable and/or Metastatic Malignant Gastrointestinal Stromal Tumors
One phase 2, open-label, randomized multinational study (B2222) was conducted in patients with unresectable or metastatic malignant gastrointestinal stromal tumors (GIST). In this study 147 patients were enrolled and randomized to receive either 400 mg or 600 mg orally q.d. for up to 24 months. These patients ranged in age from 18 to 83 years old and had a pathologic diagnosis of Kit -positive malignant GIST that was unresectable and/or metastatic. Immunohistochemistry was routinely performed with Kit antibody (A-4502, rabbit polyclonal antiserum, 1:100; DAKO Corporation, Carpinteria, CA) according to analysis by an avidin-biotin-peroxidase complex method after antigen retrieval.
The primary evidence of efficacy was based on objective response rates. Tumors were required to be measurable in at least one site of disease, and response characterization based on Southwestern Oncology Group (SWOG) criteria. Results are provided in Table 26.
Table 26 Best Tumor Response in Trial STIB2222 (GIST)
| All doses | |
| (n=147) | |
400 mg n= 73 600 mg n=74 | |
| Best response | n (%) |
| Complete response | 1(0.7) |
| Partial response | 98 (66.7) |
| Stable disease | 23 (15.6) |
| Progressive disease | 18 (12.2) |
| Not evaluable | 5 (3.4) |
| Unknown | 2 (1.4) |
There were no differences in response rates between the two dose groups. A significant number of patients who had stable disease at the time of the interim analysis did achieve a partial response with longer treatment (median follow-up 31 months). Median time to response was 13 weeks (95% CI 12 to 23). Median time to treatment failure in responders is 122 weeks (95% CI 106 to 147), while in the overall population is 84 weeks (95% CI 71 to 109). The median overall survival has not been reached. The Kaplan-Meier estimate for survival after 36-months follow-up is 68% (Figure 3).
Figure 3: Kaplan-Meier estimate for survival after 36-months
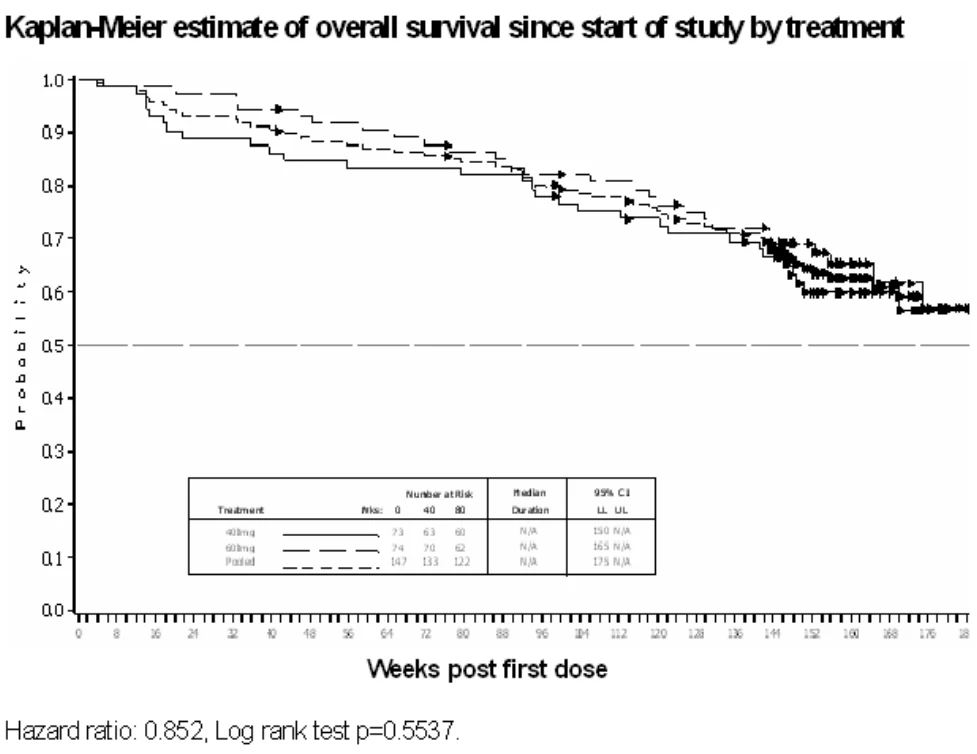
Figure 4: Kaplan-Meier estimate of overall survival since start of study by best response.
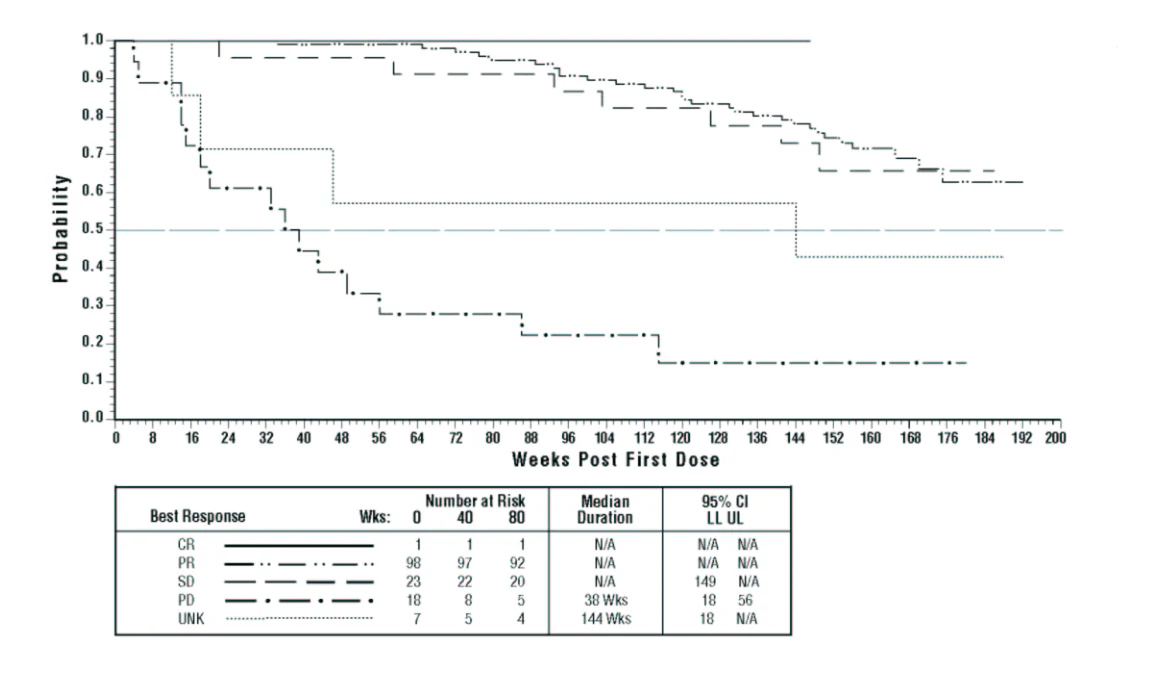
Two randomized studies were conducted comparing Sandoz Imatinib 400 mg versus 800 mg/day as a starting dose: Intergroup Study S0033 and a European-Australian phase III trial (EORTC). Study S0033 showed no significant differences in efficacy between a starting dose of 400 mg and a starting dose of 800 mg daily. The EORTC trial also did not show significant differences in terms of response or overall survival. However, the EORTC trial reported a statistically significant advantage in progression-free survival with the higher dose of Sandoz Imatinib. Grade 3 to 5 toxicities were described more often in high-dose patients in both studies.
The clinical benefit of dose escalation to 800 mg after progression is uncertain. In three randomized clinical trials (B2222, S0033 and EORTC) the daily dose of Sandoz Imatinib was escalated to 800 mg in patients progressing at the lower daily dose of 400 mg. A total of 257 escalated their dose to 800 mg daily; 8 patients achieved a partial response and 71 patients a stabilization of their disease after dose escalation. The dose escalation in the EORTC study led to a significant increase in anemia and fatigue, although fewer cases of neutropenia were reported after the dose escalation to 800 mg.
Adjuvant Treatment of GIST
In the adjuvant setting, Sandoz Imatinib was investigated in a multicentre, double-blind, placebo-controlled, randomized phase III study (Z9001) involving 713 patients. The ages of these patients ranged from 18 to 91 years. Patients who were included had a histologic diagnosis of primary GIST expressing KIT protein by immunochemistry and a tumor size ≥3 cm in maximum dimension, with complete gross resection of primary GIST within 14 to 70 days prior to registration. After complete gross resection of primary GIST, patients were randomized to one of the two arms: Sandoz Imatinib at 400 mg/day or matching placebo for one year.
The primary efficacy endpoint of the study was recurrence free survival (RFS) defined as the time from date of randomization to the date of recurrence or death from any cause. At a median follow up of 14.0 months, there had been 30 RFS events in the Sandoz Imatinib arm and 70 RFS events in the placebo arm (hazard ratio 0.398 [95%CI: 0.259 to 0.610], two-sided log-rank p<0.0001). Based on an interim analysis, the trial was stopped early and placebo patients were allowed to cross over to Sandoz Imatinib. Overall survival data are immature due to short follow up time
Figure 5 Recurrences Free Survival
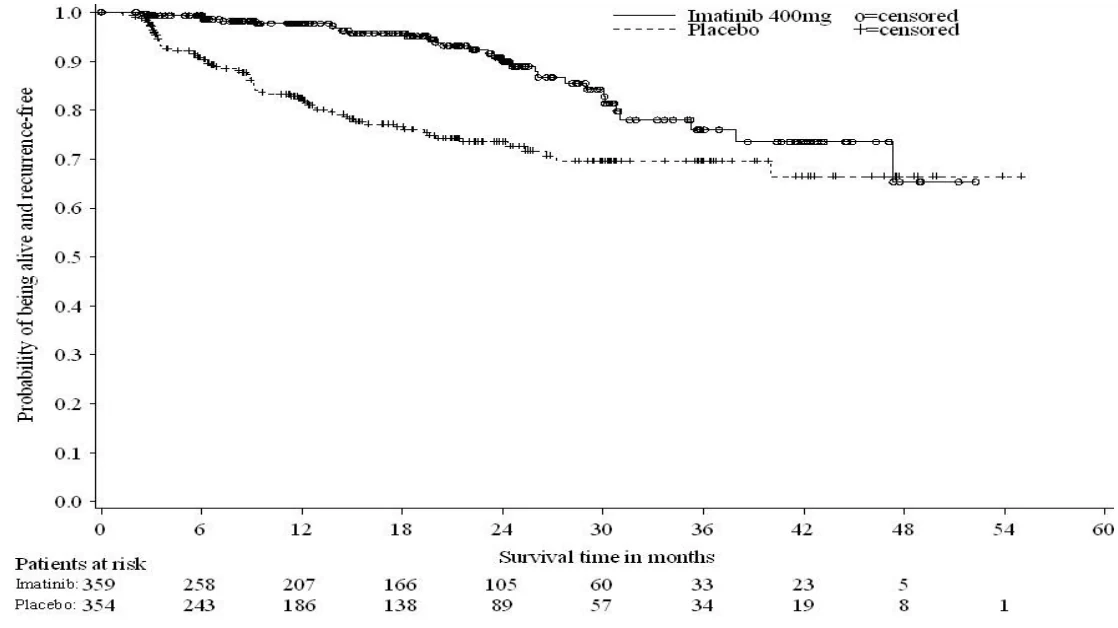
Risk of recurrence was also retrospectively assessed in this trial based on the prognostic factors of tumour size, mitotic index, and tumour location. Mitotic index data were available for 556 of 713 patients in the ITT population. The results of subgroup analyses using the United States National Institutes of Health (NIH) and the Armed Forces Institute of Pathology (AFIP) risk classifications demonstrate benefit from use of adjuvant Sandoz Imatinib in the moderate and high risk groups, but not in the low and very low risk groups. See Table 27:
Table 27 Summary of Z9001 trial RFS analyses by NIH and AFIP risk classifications
| RISK CRITERIA | Risk Level | % of pts | #events / #pts | Overall HR (95%Cl)¥ | RFS Rates (%) | |
| 12 month | 24 month | |||||
| Sandoz Imatinib vs. Placebo | Sandoz Imatinib vs. Placebo | Sandoz Imatinib vs. Placebo | ||||
| NIH | Low | 29.5 | 0/86 vs 2/90 | N.E. | 100 vs 98.7 | 100 vs 95.5 |
| Intermediate | 25.7 | 4/75 vs 6/78 | 0.59 (0.17, 2.10) | 100 vs 94.8 | 97.8 vs 89.5 | |
| High | 44.8 | 21/140 vs 51/127 | 0.29 (0.18, 0.49) | 94.8 vs 64.0 | 80.7 vs 46.6 | |
| AFIP | Very Low | 20.7 | 0/52 vs 2/63 | N.E. | 100 vs 98.1 | 100 vs 93.0 |
| Low | 25.0 | 2/70 vs 0/69 | N.E. | 100 vs 100 | 97.8 vs 100 | |
| Moderate | 24.6 | 2/70 vs 11/67 | 0.16 (0.03, 0.70) | 97.9 vs 90.8 | 97.9 vs 73.3 | |
| High | 29.7 | 16/84 vs 39/81 | 0.27 (0.15, 0.48) | 98.7 vs 56.1 | 79.9 vs 41.5 | |
¥Full follow-up period
N.E = Non Estimate
15 MICROBIOLOGY
N/A
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Subacute and Chronic Toxicity
| Study Type | Species | Route | Doses (mg/kg) | Findings |
|---|
| Oral |
| 26-weeks | Rat | p.o. | 5, 15, 50 | 50 mg/kg: Mortality (2m). Red ears, squinting, swollen appendages, red feet, dry perineal staining, apparent blood or dark yellow urine on cage paper, swollen muzzles and appendages, and dry staining of fur. Slight decrease in body weight (f). Decreased neutrophils, eosinophils, hematocrit, hemoglobin, platelets; increased MCV, MCH, MCHC and red cell distribution width. Increased AST, ALT, total protein, albumin, globulin; decreased A/G ratio, sodium, cholesterol and triglycerides. Increased heart (f), adrenal, liver (m), thyroid (m) and ovary weights; decreased pituitary (f) and testis weights. Enlarged masseter muscles and dark or red ovarian nodules. Hemorrhagic and/or cystic corpora lutea, hemosiderin-laden macrophages in ovaries, foamy macrophage accumulation in lungs, focal angiectasis of adrenal cortex, hypertrophy of masseter muscles, focal mineralization/hyperplasia of renal pelvic epithelium and focal new bone formation. ³ 15 mg/kg: Prominent eyes, wet perineal staining, increased incidence/frequency of chromodacryorrhea and red penile discharge. Decreased RBC counts and platelets. Increased heart (m) and spleen weights. Focal fibrosis of bone marrow, atrophy of acinar cells of harderian gland, increased eosinophilic macrophages in mesenteric lymph nodes. ³ 5 mg/kg: Salivation, presence of oral red substance, chromodacryorrhea, increased incidence/frequency of chromorhinorrhea. Most changes were reversible or partially reversible by the end of the recovery period. NTEL = 5 mg/kg. |
| 13 weeks | Dog | p.o. | 3, 10, 30 & 100 reduced to 50 | Death in 1 male at 100 reduced to 50 mg/kg. At ³ 10 mg/kg, dose-related diarrhea; decreases in RBC counts, and bone marrow hypo-cellularity in some animals; increased ovary weights, hepatic inflammation; gastric & small intestinal changes; thyroid weights decreased with follicular atrophy; increased splenic hemopoiesis. At >30 mg/kg dose-related emesis; decreased WBC, liver toxicity markers in serum; bile duct hyperplasia; pigment deposition in various tissues; thymic atrophy; focal acinar atrophy in the pancreas; reduced spermatogenesis. At high dose decreased testis weight, vacuolation of hepatocytes & bile duct epithelium; cystic corpora lutea containing hemorrhagic fluid; after recovery period peri-biliary fibrosis also present. NOEL = 3 mg/kg. |
| 39-weeks b.i.d. | Monkey | p.o. | 15, 30, 80 | Results at 6 months: Twice daily dosing 80 mg/kg: Reduced feces, diarrhea (m, f), and reddened conjunctiva/eyelid, pale gingiva (m). Decreased food consumption and body weight change (f). ³ 30 mg/kg: Decreased food consumption and body weight change (m). Reduced albumin. Decreased RBC count, hemoglobin and hematocrit, increased MCV, MCH and MCHC. Presence of Plasmodium species (malaria). ³ 15 mg/kg: Soft feces. |
Carcinogenicity: In a 2-year rat carcinogenicity study, imatinib was administered in feed at doses of 15, 30 and 60 mg/kg/day and resulted in a statistically significant reduction in the longevity of males rats at 60 mg/kg/day and females rats at ≥30 mg/kg/day. Histopathological examination of decedents revealed cardiomyopathy (both rats sexes), chronic progressive nephropathy (females rats) and preputial gland papilloma as principal causes of death or reasons for sacrifice. Target organs for neoplastic changes were the kidneys, urinary bladder, urethra, preputial and clitoral gland, small intestine, parathyroid glands, adrenal glands and non-glandular stomach. The no observed effect levels (NOEL) for the various target organs with neoplastic lesions were established as follows: 30 mg/kg/day for the kidneys, urinary bladder, urethra, small intestine, parathyroid glands, adrenal glands and non-glandular stomach, and 15 mg/kg/day for the preputial and clitoral gland.
The papilloma/carcinoma of the preputial/clitoral gland were noted at 30 and 60 mg/kg/day in rats, representing (approximately 0.5 to 4 times the human daily exposure at 400 mg/day (based on AUC), 0.3 to 2.4 times the human daily exposure at 800 mg/day (based on AUC), and 0.4 to 3.0 times the daily exposure in children at 340 mg/m2 (based on AUC). The renal adenoma/carcinoma, the urinary bladder and urethra papilloma, the small intestine adenocarcinomas, the parathyroid glands adenomas, the benign and malignant medullary tumors of the adrenal glands and the non-glandular stomach papillomas/carcinomas were noted only at 60 mg/kg/day.
Non-neoplastic histological lesions not identified in earlier preclinical studies were the cardiovascular system, pancreas, endocrine organs and teeth. The most important changes included cardiac hypertrophy and dilatation, leading to signs of cardiac insufficiency in some animals.
Genotoxicity:
The genotoxic potential of imatinib was assessed in a battery of mutagenicity tests.
Imatinib was devoid of genotoxicity in bacterial and cellular assays for mutagenic effects. The rat micronucleus assay which detects clastogenic and aneugenic effects was also negative. Positive results were obtained in an in vitro assay for clastogenicity (chromosome aberration) in the presence of metabolic activation, but only at concentrations which resulted in significant cytotoxicity.
Reproductive and Developmental Toxicology:
Reproductive toxicity studies indicated that imatinib has a teratogenic potential in rats at doses ³ 30 mg/kg. A dose of 10 mg/kg appeared to represent the no effect level (NOEL). In rats, doses ³30 mg/kg induced embryo-fetal toxicity and/or teratogenicity (exencephaly, encephalocele, absent or reduced frontal, parietal and/or interparietal bones; dose-dependent protruded tongues) in surviving fetuses. In rabbits, there was no evidence of teratogenicity. Although testes and epididymal weights and percent motile sperm were decreased in male rats at 60 mg/kg, there were no effects on mating or on the number of pregnant females.
Three groups of time-pregnant female rats (n=24/group) were administered STI571 orally by gavage at dosages of 5, 15 and 45 mg/kg/day. The animals were treated from gestation day 6 through lactation day 20.
There was no maternal mortality. A red vaginal discharge was noted in the 45 mg/kg/day group on either day 14 or 15 of gestation. At this dose the number of stillborn pups was slightly increased while the number of viable pups and the number of pups dying between postpartum days 0 and 4 were decreased. In the F1 offspring, at the same dose level, mean body weights were reduced from birth until terminal sacrifice and the number of litters achieving criterion for preputial separation was slightly decreased. F1 fertility was not affected while an increased number of resorptions and a decreased number of viable fetuses was noted at 45 mg/kg/day. The No Effect Level (NOEL) for both the maternal animals and the F1 generation was 15 mg/kg/day (one-fourth the maximum human dose of 800 mg/day).
Fertility was not affected in the preclinical fertility and early embryonic development study although lower testes and epididymal weights as well as a reduced number of motile sperm were observed in the high dose males rats. In the preclinical pre- and postnatal study in rats, fertility in the first generation offspring was also not affected by Sandoz Imatinib.
Juvenile Toxicity:
In a juvenile development toxicology study in rats (day 10 to 70 post-partum) administered imatinib, a delay in vaginal opening and preputial separation were observed at approximately 0.3 to 2 times the average pediatric exposure at the highest recommended dose of 340 mg/m2. Transitory decreases in crown to rump length also were observed (between days 17 and 52 post-partum) in rats administered approximately 2X the highest recommended human pediatric dose of 340 mg/m2. At this dose, shortened tibia and femur lengths were non-reversible in female rats while a trend towards reversibility was seen in male rats. Furthermore, mortality was observed in juvenile animals (around weaning phase) at approximately 2-times the average pediatric exposure at the highest recommended dose of 340 mg/m2. Another juvenile study demonstrated that rats administered imatinib resulted in premature growth plate closure.