


Product Monograph - Bosulif (Pfizer Canada, 400 mg)
Recent Major Label Changes
| 3 Serious Warnings and Precautions Box | 2024-07 |
|---|---|
| 7 Warnings and Precautions, General | 2024-07 |
| 7 Warnings and Precautions, Infections and Infestations | 2024-07 |
| 7 Warnings and Precautions, Cardiovascular | 2024-07 |
| 7 Warnings and Precautions, Endocrine and Metabolism | 2024-07 |
| 7 Warnings and Precautions, Gastrointestinal | 2024-07 |
| 7 Warnings and Precautions, Hematologic | 2024-07 |
| 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic | 2024-07 |
| 7 Warnings and Precautions, Immune | 2024-07 |
| 7 Warnings and Precautions, Musculoskeletal | 2024-07 |
| 7 Warnings and Precautions, Renal | 2024-07 |
| 7 Warnings and Precautions, Respiratory | 2024-07 |
| 7 Warnings and Precautions, Sensitivity/Resistance | 2024-07 |
| 7 Warnings and Precautions, 7.1 Special Populations | 2024-07 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 5
- 1.
Indications ....................................................................................................................... 5
1.1. Pediatrics ................................................................................................................... 5
1.2. Geriatrics .................................................................................................................... 5
- 2. Contraindications ............................................................................................................ 5
- 3. Serious Warnings and Precautions Box ............................................................................ 6
- 4.
Dosage and Administration ............................................................................................. 6
4.1. Dosing Considerations................................................................................................ 6
4.2. Recommended Dose and Dosage Adjustment ........................................................... 7
4.3. Administration ........................................................................................................... 8
4.4. Missed Dose ............................................................................................................... 8
- 5. Overdose ......................................................................................................................... 8
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................... 9
- 7.
Warnings and Precautions ............................................................................................. 10
General ............................................................................................................................... 10
Carcinogenesis and Genotoxicity ........................................................................................ 10
Cardiovascular .................................................................................................................... 11
Driving and Operating Machinery ....................................................................................... 12
Endocrine and Metabolism ................................................................................................. 12
Gastrointestinal .................................................................................................................. 12
Hematologic ....................................................................................................................... 13
Hepatic/Biliary/Pancreatic .................................................................................................. 13
Immune .............................................................................................................................. 14
Monitoring and Laboratory Tests ....................................................................................... 15
Musculoskeletal .................................................................................................................. 15
Renal ................................................................................................................................... 16
Reproductive Health ........................................................................................................... 16
Respiratory ......................................................................................................................... 17
Sensitivity/Resistance ......................................................................................................... 17
Skin ..................................................................................................................................... 18
7.1. Special Populations .................................................................................................. 18
7.1.1. Pregnancy ...................................................................................................... 18
7.1.2. Breastfeeding ................................................................................................ 18
7.1.3. Pediatrics ....................................................................................................... 18
7.1.4. Geriatrics ....................................................................................................... 18
7.1.5. Asian Race ..................................................................................................... 18
- 8.
Adverse Reactions ......................................................................................................... 18
8.1. Adverse Reaction Overview ..................................................................................... 18
8.2. Clinical Trial Adverse Reactions ................................................................................ 19
8.3. Less Common Clinical Trial Adverse Reactions ......................................................... 35
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................... 35
8.5. Post-Market Adverse Reactions ............................................................................... 39
- 9.
Drug Interactions ........................................................................................................... 39
9.1. Serious Drug Interactions ......................................................................................... 39
9.2. Drug Interactions Overview ..................................................................................... 39
9.3. Drug-Behavioural Interactions ................................................................................. 39
9.4. Drug-Drug Interactions ............................................................................................ 39
9.5. Drug-Food Interactions ............................................................................................ 43
9.6. Drug-Herb Interactions ............................................................................................ 44
9.7. Drug-Laboratory Test Interactions ........................................................................... 44
- 10.
Clinical Pharmacology ................................................................................................... 44
10.1. Mechanism of Action .......................................................................................... 44
10.2. Pharmacodynamics ............................................................................................ 44
10.3. Pharmacokinetics ............................................................................................... 45
- 11. Storage, Stability, and Disposal ...................................................................................... 47
Part 2: Scientific Information ................................................................................................ 48
- 13. Pharmaceutical Information .......................................................................................... 48
- 14.
Clinical Trials .................................................................................................................. 49
14.1. Clinical Trials by Indication ................................................................................. 49
- 16. Non-Clinical Toxicology .................................................................................................. 63
Patient Medication Information ........................................................................................... 68
Part 1: Healthcare Professional Information
1. Indications
BOSULIF (bosutinib) is indicated for:
- the treatment of adult patients with newly-diagnosed chronic phase (CP) Philadelphia chromosome positive chronic myelogenous leukemia (Ph+ CML).
Market authorization in patients with newly-diagnosed chronic phase Ph+ CML is based on major molecular response (MMR) rates in a Phase 3 clinical trial with a minimum of 12 months of follow-up (see 14 Clinical Trials).
- the treatment of chronic, accelerated, or blast phase Philadelphia chromosome-positive (Ph+) chronic myelogenous leukemia (CML) in adult patients with resistance or intolerance to prior TKI therapy.
Market authorization in patients with resistance or intolerance to prior TKI therapy, is based on cytogenetic and hematologic response rates observed in a single-arm, Phase 1/ 2 study. Overall survival benefit has not been demonstrated (see 14 Clinical Trials).
BOSULIF should only be prescribed by a qualified healthcare professional who is experienced in the use of antineoplastic therapy and in the treatment of chronic myeloid leukemia.
1.1. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years of age): No clinically relevant age-related pharmacokinetic differences have been observed in the elderly.
2. Contraindications
- Do not use BOSULIF (bosutinib) in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. Cases of Grade 3 or 4 drug hypersensitivity were reported in patients treated with BOSULIF in single-agent cancer studies.
- Two cases (less than 0.2%) of Grade 4 drug-related anaphylactic shock were reported in patients treated with BOSULIF (see 8 Adverse Reactions). For a complete listing of ingredients, see the 6 Dosage Forms, Strengths, Composition, and Packaging section of the product monograph.
- Do not use BOSULIF in patients with a known history of long QT syndrome or with a persistent QT interval of >480 ms (see 8 Adverse Reactions).
- Do not use BOSULIF in cases of uncorrected hypokalemia or hypomagnesemia (see 8 Adverse Reactions).
- Do not use BOSULIF in hepatically impaired patients. Higher risk of QT prolongation has been seen in patients with declining hepatic function (see 10 Clinical Pharmacology, 7 Warnings and Precautions, Special Populations, and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Impairment).
3. Serious Warnings and Precautions Box
- Drug interactions with inhibitors or inducers of CYP3A4. The concomitant use of BOSULIF with strong or moderate CYP3A4 inhibitors or inducers should be avoided (see 7 Warnings and Precautions, 9.4 Drug-Drug Interactions, 9.5 Drug-Food Interactions and 4 Dosage and Administration)
- Gastrointestinal toxicity, including diarrhea (see 7 Warnings and Precautions and 8 Adverse Reactions)
- Hepatic toxicity, including Hy’s Law case (see 7 Warnings and Precautions and 8 Adverse Reactions)
- Cardiac failure, including fatal outcomes (see 7 Warnings and Precautions and 8 Adverse Reactions)
- Fluid retention (including pleural effusion, pulmonary edema and pericardial effusion, including fatal outcomes (see 7 Warnings and Precautions and 8 Adverse Reactions)
- Hemorrhage (see 7 Warnings and Precautions and 8 Adverse Reactions)
- QT interval prolongation (see 7 Warnings and Precautions and 8 Adverse Reactions)
4. Dosage and Administration
4.1. Dosing Considerations
Concomitant Use With CYP3A Inhibitors
Avoid the concomitant use of strong or moderate CYP3A inhibitors with BOSULIF as an increase in bosutinib plasma concentration is possible (see 9.4 Drug-Drug Interactions and 9.5 Drug-Food Interactions).
Concomitant Use With CYP3A Inducers
Avoid the concomitant use of strong or moderate CYP3A inducers with BOSULIF. Based on the large reduction in bosutinib exposure that occurred when BOSULIF was co-administered with rifampin, increasing the dose of BOSULIF when co-administering with strong or moderate CYP3A inducers is unlikely to sufficiently compensate for the loss of exposure (see 9.4 Drug-Drug Interactions).
Hepatic Impairment
BOSULIF is contraindicated in patients with hepatic impairment at baseline (see 2 Contraindications and 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Impairment).
Renal Impairment
Newly-diagnosed chronic phase Ph+ CML
In patients with moderate renal impairment (creatinine clearance [CLCr] 30 to <50 mL/min, estimated by the Cockcroft Gault formula), the recommended dose of bosutinib is 300 mg daily with food (see 7 Warnings and Precautions and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment).
In patients with severe renal impairment (CLCr <30 mL/min, estimated by the Cockcroft Gault formula), the recommended dose of bosutinib is 200 mg daily with food (see 7 Warnings and Precautions and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment).
Chronic, accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy
In patients with moderate renal impairment [creatinine clearance (CrCL) 30 to 50 mL/min, estimated by the Cockcroft-Gault formula], the recommended dose of bosutinib is 400 mg daily with food (see 7 Warnings and Precautions and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment).
In patients with severe renal impairment (CrCL <30 mL/min, estimated by the Cockcroft-Gault formula), the recommended dose of bosutinib is 300 mg daily with food (see 7 Warnings and Precautions and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment).
The starting dose recommendation in patients with moderate or severe renal impairment was based on pharmacological modeling; the efficacy and safety of BOSULIF have not been investigated in these patients. Initiate BOSULIF therapy in these patients only when perceived benefits outweigh the potential risks. Patients should be closely monitored for renal function at baseline and during therapy (see 7 Warnings and Precautions and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment).
4.2. Recommended Dose and Dosage Adjustment
- Bosutinib should be taken orally once daily, swallowed whole, with a meal. Patients should take their dose of bosutinib at approximately the same time each day. Do not take with grapefruit products and star fruit, pomegranate, Seville oranges and other similar fruits that are known to inhibit CYP3A4 (see 9.1 Serious Drug Interactions and 9.5 Drug-Food Interactions). Tablets should not be crushed or cut, and should not be dissolved in a liquid.
- In clinical trials, treatment with bosutinib continued until disease progression or until intolerance to therapy.
- If a patient misses a dose (delayed by more than 12 hours), the patient should not take a dose that day, but take the usual prescribed dose on the following day.
- In clinical studies of adult Ph+ CML patients, dose escalation by increments of 100 mg once daily to a maximum of 600 mg once daily was allowed in patients who did not achieve a hematologic, cytogenetic, or molecular response and who did not have Grade 3 or higher adverse reactions at the recommended starting dosage. Dose escalations are expected to result in greater toxicity.
- Health Canada has not authorized an indication for pediatric use.
Newly-diagnosed chronic phase Ph+ CML
- The recommended dose of BOSULIF is 400 mg orally once daily swallowed whole with a meal.
Chronic, accelerated, or blast phase Ph+ CML with resistance or intolerance to prior therapy
- The recommended dose and schedule of BOSULIF is 500 mg orally once daily swallowed whole, with a meal.
Dose Adjustments for Non-Hematologic Adverse Reactions
Elevated liver transaminases: If elevations in liver transaminases >5 x institutional upper limit of normal (ULN) occur, BOSULIF should be interrupted until recovery to ≤2.5 x ULN and may be resumed at 400 mg once daily thereafter. If recovery takes longer than 4 weeks, discontinuation of BOSULIF should be considered. If transaminase elevations ≥3 x ULN occur concurrently with bilirubin elevations >2 x ULN and alkaline phosphatase <2 x ULN, BOSULIF should be discontinued.
Diarrhea: For NCI CTCAE Grade 3-4 diarrhea (increase of ≥7 stools/day over baseline/pretreatment), BOSULIF should be interrupted temporarily. Patients with these events should be managed using standard of care treatment, including antidiarrheal medication, and/or fluid replacement. BOSULIF may be resumed at a dose reduced by 100 mg taken once daily upon recovery to grade ≤1.
If other clinically significant moderate or severe non-hematological toxicity develops, BOSULIF should be interrupted, and may be resumed at a dose reduced by 100 mg taken once daily after the toxicity has resolved. If clinically appropriate, re-escalation of the dose to the starting dose taken once daily may be considered. Doses less than 300 mg/day have been used in patients; however, efficacy has not been established.
Dose Adjustments for Hematologic Adverse Reactions
Dose reductions are recommended for severe or persistent neutropenia and thrombocytopenia as described below. Dose interruptions and/or reductions may be needed for hematologic toxicities (neutropenia, thrombocytopenia) that are not related to underlying leukemia (Table 1).
| Table 1 – Dose Adjustments for Neutropenia and Thrombocytopenia | |
|---|---|
Absolute Neutrophil Count ANC <1.0x10⁹/L or Platelets <50x109/L | Hold BOSULIF until ANC ³1.0x10⁹/L and platelets ³50x109/L. Resume treatment with BOSULIF at the same dose if recovery occurs within 2 weeks. If blood counts remain low for >2 weeks, upon recovery, reduce dose by 100 mg and resume treatment. If either of these cytopenias recurs, reduce dose by an additional 100 mg upon recovery and resume treatment. Doses less than 300 mg/day have been used in patients; however, efficacy has not been established. |
4.3. Administration
For oral use.
4.4. Missed Dose
If a dose is missed (delayed by more than 12 hours), the patient should not take a dose that day, but take the usual prescribed dose on the following day.
5. Overdose
Experience with BOSULIF overdose in clinical studies was limited to isolated cases. There were no reports of any serious adverse events associated with the overdoses. Patients who take an overdose of BOSULIF should be observed and given appropriate supportive treatment.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 2 – Dosage Forms, Strengths, and Composition
Description
BOSULIF (bosutinib) 100 mg tablets:
Each 100 mg BOSULIF tablet contains 103.40 mg of bosutinib monohydrate, equivalent to 100 mg of bosutinib.
Yellow, oval, biconvex, film-coated tablet debossed with “Pfizer” on one side and “100” on the other.
BOSULIF (bosutinib) 500 mg tablets:
Each 500 mg BOSULIF tablet contains 516.98 mg of bosutinib monohydrate, equivalent to 500 mg of bosutinib.
Red, oval, biconvex, film-coated tablet debossed with “Pfizer” on one side and “500” on the other.
BOSULIF (bosutinib) tablets are available in the following packaging configurations (Table 3):
| Table 3 – Tablet Presentations | |||||
|---|---|---|---|---|---|
| Tablet Strength (mg) | Package Configuration | Tablet Description | |||
| 100 mg | 28 tablets (2 blister packs* with 14 tablets each) | Yellow, oval, biconvex, film-coated tablets, debossed “Pfizer” on one side and “100” on the other. | |||
| 500 mg | 28 tablets (2 blister packs* with 14 tablets each) | Red, oval, biconvex, film-coated tablets, debossed “Pfizer” on one side and “500” on the other | |||
*White opaque 3-ply Polyvinyl chloride (PVC)/ACLAR/PVC blisters sealed with push-through foil backing
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablets 100 mg and 500 mg | Coating: iron oxide yellow (100 mg), , iron oxide red (500 mg). Tablet: Croscarmellose sodium, iron oxide yellow, magnesium stearate, microcrystalline cellulose, poloxamer, polyethylene glycol, polyvinyl alcohol, povidone, talc, and titanium dioxide. |
7. Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
CYP3A inhibitors
Bosutinib exposure can be increased when administered concomitantly with CYP3A inhibitors. Avoid the concomitant use of strong or moderate CYP3A inhibitors (see 9.1 Serious Drug Interactions and 9.5 Drug-Food Interactions).
CYP3A inducers
Bosutinib exposure is decreased when administered concomitantly with CYP3A inducers. Avoid the concomitant use of strong or moderate CYP3A inducers (see 9.4 Drug-Drug Interactions).
Fluid Retention
Treatment with BOSULIF is associated with fluid retention (pericardial effusion, pleural effusion, pulmonary edema, and/or peripheral edema) (see 8 Adverse Reactions).
In the Phase 3 clinical study in 268 patients with newly-diagnosed CP CML treated with BOSULIF 400mg, severe (Grade 3 or 4) fluid retention was reported in three (1.1%) patients. Of these, 2 patients experienced grade 3 pleural effusion and 1 patient experienced Grade 3 pericardial effusion. Six patients (2.2%) reported SAEs: most common (≥1%) was pleural effusion (4 patients [1.5%]).
In the single-arm Phase 1/2 clinical study in 570 patients with Ph+ leukemias treated with prior therapy, thirty-two (5.6%) patients had severe (Grade 3 or 4) fluid retention. Of these, 25 patients experienced Grade 3 or 4 pleural effusion, 9 patients experienced Grade 3 or 4 pericardial effusion, 3 patients experienced Grade 3 fluid retention, 2 patients experienced Grade 3 edema peripheral, 2 patients experienced Grade 3 edema, 1 patient experienced Grade 3 pulmonary edema, and 1 patient experienced Grade 3 swelling. Thirty-eight patients (6.7%) reported SAEs: most common (≥1%) were pleural effusion (31 patients [5.4%]) and pericardial effusion (9 patients [1.6%]). One patient died due to pulmonary edema.
Patients should be weighed regularly and monitored for signs and symptoms of fluid retention, and managed using standard of care treatment, such as diuretics. In addition, these events can also be managed by withholding BOSULIF temporarily, dose reduction, and/or discontinuation of BOSULIF (see 4 Dosage and Administration).
Infections and Infestations
BOSULIF may predispose patients who are immunocompromised or older patients to bacterial, fungal, viral or protozoan infections. Grade 3 or 4 infections were reported in 10.5% of patients treated with bosutinib in pooled leukemia studies (n=1372). Of these, the most common (≥1%) were pneumonia (3.9%) and sepsis (1.2%). SAE’s and fatal treatment-emergent events of infections were reported in 12.2% and 0.3% of patients.
Carcinogenesis and Genotoxicity
Cases of second primary malignancies have been reported in humans in clinical trials with BOSULIF (see 8 Adverse Reactions).
In the 2-year rat carcinogenicity study, overall, no relevant bosutinib-related increase in neoplastic lesion was shown. Nonclinical studies showed that bosutinib was not genotoxic or mutagenic (see 16 Non-Clinical Toxicology).
Cardiovascular
In clinical studies, patients with uncontrolled or significant cardiac disease (e.g. recent myocardial infarction, congestive heart failure or unstable angina) were excluded.
QT Prolongation
In pooled leukemia studies, 0.5% of patients treated with bosutinib experienced QtcF intervals of greater than 500 ms and 0.8% of patients experienced QtcF increase of >60ms from baseline (n=1372). Patients with uncontrolled or significant cardiovascular disease, including QT interval prolongation, at baseline were excluded by protocol criteria from the clinical trials (see 8 Adverse Reactions).
In a Phase 3 study of newly diagnosed Ph+ CP CML patients treated with bosutinib 500 mg, BOSULIF was associated with statistically significant decreases from baseline in heart rate of approximately 4 bpm at months 2 and 3 (see 8 Adverse Reactions).
BOSULIF should be administered with caution to patients who have a history of or predisposition for QTc prolongation, who have uncontrolled or significant cardiac disease including recent myocardial infarction, congestive heart failure, unstable angina or clinically significant bradycardia, or who are taking medicinal products that are known to prolong the QT interval (e.g. anti-arrhythmic medicinal products and other substances that may prolong QT (see 9.4 Drug-Drug Interactions). The presence of hypokalemia and hypomagnesemia may further increase this effect. Monitoring for an effect on the QTc interval is advisable and a baseline ECG is recommended prior to initiating therapy with BOSULIF and as clinically indicated. Hypokalemia or hypomagnesemia must be corrected prior to BOSULIF administration and should be monitored periodically during therapy (see 2 Contraindications).
Patients with hepatic impairment who are receiving treatment with BOSULIF are at higher risk of developing QT interval prolongation (see 2 Contraindications and 7 Warnings and Precautions, Special Populations).
Cardiac Toxicity
BOSULIF can cause cardiovascular toxicity including cardiac failure, left ventricular dysfunction, cardiac ischemic events and atrial fibrillation (see 8 Adverse Reactions). Cardiac failure events occurred more frequently in previously treated patients than in patients with newly diagnosed CML and were more frequent in patients with advanced age or risk factors, including previous medical history of cardiac failure. Cardiac ischemic events occurred in both previously treated patients and in patients with newly diagnosed CML. Caution should be exercised in patients with a history of or predisposition to relevant cardiac disorders.
Monitor patients for signs and symptoms consistent with cardiac failure and cardiac ischemia and treat as clinically indicated. Interrupt, dose reduce, or discontinue BOSULIF as necessary (see 4 Dosage and Administration).
In the Phase 3 clinical study of 268 patients with newly-diagnosed CML treated with BOSULIF 400 mg, 14.2% of patients in the BOSULIF arm experienced cardiac events (5.2% with Grade 3 or 4) versus 6.0% of patients in the imatinib arm (1.1% with Grade 3 or 4). Cardiac failure occurred in 1.9% of patients treated with bosutinib compared to 0.8% of patients treated with imatinib. Cardiac ischemic events occurred in 4.9% of patients treated with bosutinib compared to 0.8% of patients treated with imatinib. Two (0.7%) patients had treatment-emergent cardiac events (Cardiac failure acute, Myocardial ischemia) leading to death in the bosutinib arm compared to none in the imatinib arm.
In a single-arm Phase 1/2 study of 570 patients with Ph+ leukemias treated with prior therapy, 16.7% of patients experienced cardiac events (8.4% with Grade 3 or 4). Cardiac failure was observed in 5.3% of patients, cardiac ischemic events were observed in 5.1% of patients treated with bosutinib. Ten (1.8%) patients had treatment-emergent cardiac events leading to death.
Driving and Operating Machinery
No studies on the effects of bosutinib on the ability to drive and operate machines have been performed. Patients experiencing dizziness or other undesirable effects with a potential impact on the ability to safely drive or use machines should refrain from these activities as long as these undesirable effects persist (see 8 Adverse Reactions).
Endocrine and Metabolism
Tumour Lysis Syndrome
Grade 3 or 4 tumour lysis syndrome was reported in 0.3% of patients treated with bosutinib in pooled leukemia studies (n=1372). Renal function should be closely monitored and adequate hydration should be maintained if tumour lysis syndrome is considered a substantial risk.
Gastrointestinal
Diarrhea and Vomiting
Patients with recent or ongoing clinically significant gastrointestinal disorder should use BOSULIF with caution and only after a careful benefit-risk assessment, as patients with recent or ongoing clinically significant gastrointestinal disorder (e.g. severe vomiting and/or diarrhea) were excluded from CML clinical studies.
Diarrhea and vomiting were observed in 80% and 34% of patients treated with BOSULIF in pooled leukemia studies (n=1372).
Of the 1,103 (80.4%) patients that experienced diarrhea, 14 patients discontinued bosutinib due to this event. Concomitant medicinal products were given to treat diarrhea in 756 (68.5%) patients. Maximum toxicity of Grade 1 occurred in 575 (41.9%) patients, Grade 2 in 383 (27.9%) patients, Grade 3 in 144 (10.5%) patients; 1 patient (0.1%) experienced a Grade 4 event. Among patients with diarrhea, the median time to first event was 2 days (range: 1 to 2,702 days) and the median duration of any grade of diarrhoea was 2 days (range: 1 to 4,247 days). Among bosutinib treated patients who reported diarrhea, 40.3% of patients reported an individual episode of diarrhea for more than 28 consecutive days.
Among the 1,103 patients with diarrhea, 218 patients (19.8%) were managed with treatment interruption and of these 208 (95.4%) were rechallenged with bosutinib. Of those who were rechallenged, 201 (96.6%) did not have a subsequent event or did not discontinue bosutinib due to a subsequent event of diarrhea.
Patients with these events should be managed using standard of care treatment, including antidiarrheal medication, and/or fluid replacement. Since some antiemetics and antidiarrheals are associated with a risk of increased QT interval prolongation with the potential to induce “torsade de pointes”, concomitant treatment with these agents should be carefully considered. In addition, these events can also be managed by withholding BOSULIF temporarily, dose reduction, and/or discontinuation of BOSULIF (see 4 Dosage and Administration and 8 Adverse Reactions).
Hematologic
Myelosuppression
Thrombocytopenia, anemia and neutropenia were reported in 27%, 25% and 13% of patients treated with bosutinib in pooled leukemia studies (n=1372) (see 8 Adverse Reactions).
Patients with Ph+ leukemias who are receiving BOSULIF should have a complete blood count (including platelet count) performed weekly for the first month and then monthly thereafter, or as clinically indicated. Myelosuppression can be managed by withholding BOSULIF temporarily, dose reduction, and/or discontinuation of BOSULIF (see 4 Dosage and Administration and 8 Adverse Reactions).
Hemorrhage
Bosutinib is associated with hemorrhage, which is most commonly Grade 1 epistaxis. Serious adverse events of hemorrhage were reported in 4.2% of patients treated with bosutinib and fatal events were reported in 0.5% of patients in pooled leukemia studies (n=1372). The most common SAEs were gastrointestinal hemorrhage (1.5%), which includes gastrointestinal hemorrhage, rectal hemorrhage, haematochezia, abdominal wall hematoma, duodenal ulcer hemorrhage, gastric hemorrhage, intestinal hemorrhage, lower gastrointestinal hemorrhage, retroperitoneal hemorrhage and melaena.
In the Phase 3 clinical study of 268 patients with newly-diagnosed CML treated with BOSULIF 400mg , ten patients (3.7%) had hemorrhage SAE’s, none of which were fatal.
In the single-arm Phase 1/2 clinical study in 570 patients with Ph+ leukemias treated with prior therapy, thirty-six (6.3%) patients had hemorrhage SAE’s. There were five (0.9%) deaths associated with hemorrhagic events (lower gastrointestinal hemorrhage, intraventricular hemorrhage and cerebral hemorrhage in one patient each and subarachnoid hemorrhage in two patients).
Coagulation Dysfunction/Platelet Disorders
Patients with coagulation dysfunction /platelet disorders and who are taking BOSULIF may be at higher risk of bleeding events and should be closely monitored during treatment with BOSULIF.
Hepatic/Biliary/Pancreatic
Hepatotoxicity
Treatment with bosutinib is associated with elevations in serum transaminases (alanine aminotransferase [ALT], aspartate aminotransferase [AST]) (see 8 Adverse Reactions).
Two cases consistent with Hy’s Law and drug induced liver injury (defined as concurrent elevations in ALT or AST greater than or equal to 3 x ULN with total bilirubin greater than 2 x ULN and alkaline phosphatase less than 2 x ULN) occurred without alternative causes. This represented 2/1711 (0.1%) patients treated with bosutinib in pooled studies of solid and hematological malignancies.
In clinical studies in patients (n=1372) with CML or Ph+ leukemias, transaminase elevations generally occurred early in the course of treatment; of patients who experienced transaminase elevations of any grade, more than 80% experienced their first event within the first 3 months.
In the 570 patients from the single arm phase 1/2 study in patients with CML who were resistant or intolerant to prior therapy, adverse events associated with liver injury were reported in 151 (26.5%) patients overall. The incidence of ALT elevation was 18.1% for all grades (6.8% Grade 3/4) and AST elevation was 15.1 % for all grades (3.3% Grade 3/4). The median time to onset of increased ALT and AST was 36 and 41.5 days, respectively, and the median duration for each was 21 days. Eighteen (3.2%) patients discontinued BOSULIF due to liver injury-related events.
In the Phase 3 clinical study of 268 patients with newly-diagnosed CML treated with BOSULIF 400 mg , adverse events associated with liver injury were reported in 118 (44.0%) patients. The incidence of ALT elevation was 33.6% (20.9% Grade 3/4) and AST elevation was 25.7% (10.4% Grade 3/4). The median time to onset of increased ALT and AST was 33.5 and 56 days, respectively, and the median duration was 19 and 15 days, respectively. Twenty-one (7.8%) patients discontinued due to liver injury related events.
Patients receiving BOSULIF should have monthly hepatic enzyme tests for the first three months of treatment, or as clinically indicated. Patients with transaminase elevations can be managed by withholding BOSULIF temporarily, dose reduction, and/or discontinuation of BOSULIF (see 4.1 Dosing Considerations, Hepatic Impairment).
Patients with Hepatic Impairment
Metabolism of bosutinib is mainly hepatic. Clinical studies have excluded patients with ALT and/or AST >2.5 (or >5, if related to disease) x ULN range and/or bilirubin >1.5 x ULN range. BOSULIF should not be used in hepatically impaired patients.
Higher risk of QT prolongation has been seen in patients with declining hepatic function. In a single-oral-dose study, higher bosutinib plasma levels with reduced clearance were reported in non-CML patients with mild, moderate or severe hepatic impairment (Child-Pugh class) at baseline, compared to matching healthy volunteers. Treatment-emergent QTc prolongation was observed in 50% of hepatically impaired patients (including all 6 patients with severe hepatic impairment) versus 11% of healthy volunteers; the frequency, magnitude and duration of QTc prolongation appeared to increase with severity of baseline hepatic impairment (see 2 Contraindications, 4.1 Dosing considerations, 8 Adverse Reactions and 10 Clinical Pharmacology).
Elevated Serum lipase /Amylase and Pancreatitis
Grade 3 or 4 lipase increased (including hyperlipasemia) (10.1%) and amylase increased (including hyperamylasemia) (2.2%) and Grade 3 or 4 acute pancreatitis (1%) has been observed in patients treated with BOSULIF in pooled leukemia studies (n=1372). Caution is recommended in patients with previous history of pancreatitis. In case lipase elevations are accompanied by abdominal symptoms, bosutinib should be interrupted and appropriate diagnostic measures considered to exclude pancreatitis (see 4.2 Recommended Dose and Dose Adjustment).
Immune
Hypogammaglobulinemia and hypersensitivity vasculitis were reported in 0.1% and 0.1% of patients treated with bosutinib in pooled leukemia studies (n=1327). Patients with immunocompromising diseases or risk factors for immunosuppression, such as patients with HIV, AIDS, or patients receiving immunosuppressive therapies, should be closely monitored for signs of immunotoxicity.
Hepatitis B virus reactivation
Reactivation of hepatitis B virus (HBV) has occurred in patients who are chronic carriers of this virus after receiving a Bcr-Abl tyrosine kinase inhibitor (TKI). Some cases resulted in acute hepatic failure or fulminant hepatitis leading to liver transplantation or death.
Patients should be tested for hepatitis B infection before initiating treatment with BOSULIF. Patients currently on BOSULIF should have baseline testing for hepatitis B infection if clinically indicated, in order to identify chronic carriers of the virus. Experts in liver disease and in the treatment of hepatitis B should be consulted before treatment is initiated in patients with positive hepatitis B serology (including those with active disease) and for patients who test positive for HBV infection during treatment. Carriers of HBV who require treatment with BOSULIF should be closely monitored for signs and symptoms of active HBV infection throughout therapy and for several months following termination of therapy.
Monitoring and Laboratory Tests
Patients should have a complete blood count (including platelet counts) performed weekly for the first month then monthly thereafter, or as clinically indicated (see 7 Warnings and Precautions, Hematologic).
Patients should have baseline and monthly liver function tests (including total bilirubin) and renal function tests for the first three months of treatment and periodically thereafter (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
Serum electrolytes (including phosphorus), calcium and magnesium, as well as serum lipase/amylase, should be monitored at baseline and frequently during treatment with BOSULIF, and as clinically indicated. Patients with endocrine abnormalities (e.g. hyperparathyroidism) and/or severe osteoporosis should be monitored closely for changes in bone and mineral abnormalities, including bone density (see 2 Contraindications and 7 Warnings and Precautions).
Monitor patients for renal function at baseline and during therapy with BOSULIF, with particular attention to those patients who have pre-existing renal compromise or risk factors for renal dysfunction.
Adequate hydration should be maintained if tumour lysis syndrome is considered a substantial risk.
Patients should be weighed and monitored regularly for fluid retention and managed using standard of care treatment (see 7 Warnings and Precautions, General, Fluid Retention).
Monitoring for an effect on the QTc interval is recommended and a baseline ECG is recommended prior to initiating therapy with BOSULIF and as clinically indicated. Hypokalemia or hypomagnesemia must be corrected prior to BOSULIF administration and should be monitored periodically during therapy (see 7 Warnings and Precautions, Cardiovascular, QT Prolongation).
Musculoskeletal
Changes in Bone Density
In pooled leukemia studies (N=1372) the frequency of fractures was 6.1 % in patients treated with BOSULIF, of which 1.0% were Grade 3 or 4 factures (see 8 Adverse Reactions).
Hypophosphatemia (including blood phosphorus decreased) has been reported in 6.2% of patients treated with BOSULIF (n=1372).
Patients with endocrine abnormalities (e.g. hyperparathyroidism) and severe osteoporosis treated with BOSULIF could be at greater risk from the impact of bone mineralization abnormalities, and should be monitored closely for changes in bone and mineral abnormalities, including bone density (see 7 Warnings and Precautions, Monitoring and Laboratory Tests).
Renal
An on-treatment decline in estimated glomerular filtration rate (eGFR) was observed in patients treated with bosutinib in pooled leukemia studies. Severe renal impairment and kidney failure was observed in 5.2% and 1.2% of patients during treatment with bosutinib in pooled leukemia studies (n=1372) (see 8 Adverse Reactions, Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and other Quantitative findings). The median duration of treatment with bosutinib was approximately 26.3 months (range, 0.03 to 170.49) for patients in these studies.
Across pooled leukemia studies, fatal treatment-emergent renal events were reported in 4/1372 (0.3%) patients treated with bosutinib (3 events of acute kidney injury, 1 event of renal failure).
The reversibility of the eGFR decline following treatment interruption, dose reduction or treatment discontinuation is unclear, due to limited clinical data.
Monitor patients for renal function at baseline and during therapy with BOSULIF, with particular attention to those patients who have pre-existing renal compromise or risk factors for renal dysfunction.
Patients with Renal Impairment
In a renal impairment study, bosutinib exposures were increased in patients with moderate or severe renal impairment. Reduced starting doses are recommended for patients with moderate and severe renal impairment, respectively (see 4.1 Dosing Considerations, Renal Impairment and 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Impairment). The efficacy and safety of BOSULIF were not investigated in these patients, as those with reduced renal function (serum creatinine > 1.5 x ULN) were excluded from the Phase 1/ 2 and Phase 3 BOSULIF CML studies. Initiate BOSULIF therapy in these patients only when perceived benefits outweigh the potential risks. Patients should be closely monitored for renal function at baseline and during therapy (see 7 Warnings and Precautions, Renal).
Hypertension was reported at a common (9.6%) frequency in patients treated with BOSULIF (see 8 Adverse Reactions). Patients with renal impairment who are receiving treatment with BOSULIF were at higher risk of developing hypertension. Among patients with renal insufficiency (eGFR ≥ Grade 3b at any time during the study), the frequency of hypertension was greater than for patients without renal insufficiency (eGFR ≥ Grade 3b) (18.8% versus 7.3%, respectively).
Reproductive Health
Females of childbearing potential
Females of childbearing potential (i.e. females who are menstruating, amenorrheic from previous treatments, and/or perimenopausal) must be advised to use highly effective contraception during treatment with BOSULIF and for at least 1 month after the final dose. If pregnancy does occur during treatment, BOSULIF should be stopped and the patients should be referred to an obstetrician/gynecologist experienced in reproductive toxicity for further evaluation and counselling.
Male Patients:
There is a potential risk to the developing fetus if exposed to BOSULIF through the semen of male patients, therefore physicians should advise their male patients to use highly effective contraception (including condom) during any sexual contact with females of childbearing potential even if they have undergone a successful vasectomy. The method of contraception should be used while the patient is taking BOSULIF, during interruption of BOSULIF treatment, and for at least 4 weeks after stopping BOSULIF. Physicians should advise their male patients to inform their female sexual partners (with childbearing potential) that they are taking BOSULIF and that there are risks to the developing fetus if exposed to their semen (see 10 Clinical Pharmacology).
Fertility
Human studies on male patients receiving BOSULIF and its effect on male fertility and spermatogenesis have not been performed. Studies in rats showed that fertility was slightly decreased in male rats treated with bosutinib. Female rats had increased embryonic resorptions and decreases in implantations and viable embryos. The dose at which no adverse reproductive effects were observed in males and females resulted in exposures equal to 0.5 times and 0.2 times, respectively, the human exposure based on the clinical dose of 500 mg (based on unbound AUC in the respective species). In a rat pre- and postnatal development study, there were reduced number of pups born, decreased postnatal survival (including increased incidence of total litter loss), and decreased growth of offspring after birth (see 16 Non-Clinical Toxicology, Developmental Toxicity). BOSULIF has the potential to impair reproductive function and fertility in humans. Physicians should advise and counsel their male and female patients as appropriate (see 10 Clinical Pharmacology).
Respiratory
In pooled leukemia studies, 7.9% of patients treated with BOSULIF reported serious respiratory disorders including pleural effusion, dyspnea, respiratory failure, acute pulmonary edema, pulmonary hypertension, pneumonitis and interstitial lung disease (n=1372). Grade 3-4 respiratory disorders were reported in 7.1% of patients treated with BOSULIF (see 8 Adverse Reactions).
Sensitivity/Resistance
Hypersensitivity
Cases of Grade 3 or 4 drug hypersensitivity (0.4%), anaphylactic shock (0.1%), and urticaria (0.4%) have been reported with BOSULIF in pooled leukemia studies (n=1372). (see 2 Contraindications and 8 Adverse Reactions).
Patients with hypersensitivity to excipients in BOSULIF, such as polyethylene glycol 3350, poloxamer 188, povidone, or other excipients, may be at risk.
Skin
Stevens-Johnson syndrome has been rarely reported in the post-market setting. Discontinue BOSULIF should this condition be suspected.
7.1. Special Populations
7.1.1. Pregnancy
Based on mechanism of action and findings of embryofetal toxicities in rabbits, BOSULIF is teratogenic and can cause fetal harm when administered to a pregnant woman (see 16 Non-Clinical Toxicology). There are no adequate and well-controlled studies of BOSULIF in pregnant women. If BOSULIF is used during pregnancy, the patient should be advised of the potential serious risks to a developing fetus.
7.1.2. Breastfeeding
An animal study demonstrated excretion of bosutinib-derived radioactivity in breast milk. Because many drugs are excreted in human milk and because a potential risk to the nursing infant cannot be excluded, women that are taking BOSULIF should not breast-feed or provide breast milk to infants (see 16 Non-Clinical Toxicology).
7.1.3. Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (≥ 65 years of age): The type and frequency of TEAEs of was generally similar between younger (<65 years) vs. older (> 65 years) subjects. The overall frequency of AEs leading to discontinuation was higher in older subjects, however the type of AEs leading to discontinuation was similar.
7.1.5. Asian Race
According to population pharmacokinetic analyses, Asians had a lower clearance of BOSULIF resulting in increased exposure. Therefore, these patients should be closely monitored for adverse reactions, especially in case of dose escalation.
8. Adverse Reactions
8.1. Adverse Reaction Overview
The safety information provided in this section represents an assessment of the adverse reactions from 1621 patients who received at least 1 oral dose of single-agent BOSULIF in newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy, other Ph+ leukemias, and advanced malignant solid tumors. The safety information in Section 7 represents an assessment of 1372 patients who received BOSULIF monotherapy in newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy and other Ph+ leukemias. The median duration of exposure to bosutinib was 26.3 (0.03-170.49) months in pooled leukemia studies.
Serious adverse reactions reported include anaphylactic shock (see 2 Contraindications), myelosuppression, gastrointestinal toxicity (diarrhea), fluid retention, hepatotoxicity and rash.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Newly Diagnosed Chronic Phase Ph+ CML
In a randomized Phase 3 clinical study in newly-diagnosed patient with CP CML a total of 268 patients received at least 1 dose of single-agent bosutinib 400 mg and 265 patients received at least one dose of imatinib 400 mg. After 60 months of follow-up in the bosutinib arm, the median duration of therapy was 55.1 months (range: 0.3 to 58.9 months); the median dose intensity was 393.6 mg/day.
The most frequent adverse reactions reported for ≥20% of patients in the bosutinib treatment group were diarrhoea (75.0% of patients), nausea (37.3%), thrombocytopenia (35.8%), ALT increased (33.6%), fatigue (32.8%), abdominal pain (32.5%), rash (30.2%) AST increased (25.7%), anemia (22.0%), headache (22.0%), lipase increased (21.3%), vomiting (20.4%), and arthralgia (20.1%).
The Grade 3 and 4 adverse reactions reported for ≥5% of patients in the bosutinib treatment group were ALT increased (20.9%), thrombocytopenia (14.2%), lipase increased (13.4%), AST increased (10.4%), diarrhoea (9.0%), and neutropenia (7.5%).
Table below presents adverse reactions (all causality) of any toxicity and grades 3/4 very commonly reported (frequencies ≥10%) in the Phase 3 safety population.
| Table 4 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Table 4 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | ||||||||||
| Table 4 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | ||||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | |||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | |||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | |||||||||
| System Organ Class (1) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||
| System Organ Class (1) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||
| System Organ Class (1) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||
| Preferred Term | ||||||||||
| Preferred Term | ||||||||||
| Preferred Term | ||||||||||
| Any Adverse Events | 97 | 60 | 96 | 45 | ||||||
| Blood and lymphatic system disorders | 47 | 18 | 46 | 22 | ||||||
| Thrombocytopenia | 36 | 14 | 20 | 6 | ||||||
| Anemia | 22 | 4 | 23 | 6 | ||||||
| Neutropenia | 12 | 8 | 23 | 14 | ||||||
| Gastrointestinal disorders | 82 | 12 | 66 | 3 | ||||||
| Diarrhea | 75 | 9 | 40 | 1 | ||||||
| Nausea | 37 | 0 | 42 | 0 | ||||||
| Abdominal pain | 33 | 2 | 20 | 1 | ||||||
| Vomiting | 21 | 1 | 20 | 0 | ||||||
| General disorders and administration site conditions | 47 | 2 | 60 | 1 | ||||||
| Fatiguea | 33 | 1 | 30 | 0 | ||||||
| Pyrexia | 17 | 1 | 11 | 0 | ||||||
| Edema | 13 | 0 | 43 | 1 | ||||||
| Infections and infestations | 41 | 2 | 34 | 2 | ||||||
| Respiratory tract infection | 18 | 0 | 16 | 0 | ||||||
| Nasopharyngitis | 13 | 0 | 11 | 0 | ||||||
| Investigations | 54 | 34 | 37 | 14 | ||||||
| ALT increased | 34 | 21 | 6 | 2 | ||||||
| AST increased | 26 | 10 | 7 | 2 | ||||||
| Lipase increased | 21 | 14 | 11 | 6 | ||||||
| Metabolism and nutrition disorders | 16 | 4 | 15 | 4 | ||||||
| Appetite decreased | 11 | 0 | 6 | 0 | ||||||
| Musculoskeletal and connective tissue disorders | 28 | 2 | 37 | 2 | ||||||
| Arthralgia | 20 | 1 | 20 | 0 | ||||||
| Back pain | 12 | 0 | 9 | 0 | ||||||
| Nervous system disorders | 28 | 1 | 22 | 1 | ||||||
| Headache | 22 | 1 | 15 | 1 | ||||||
| Respiratory, thoracic and mediastinal disorders | 23 | 2 | 15 | 1 | ||||||
| Cough | 11 | 0 | 10 | 0 | ||||||
| Dyspnea | 11 | 1 | 6 | 1 | ||||||
| Skin and subcutaneous disorders | 38 | 2 | 23 | 2 | ||||||
| Rash | 30 | 2 | 19 | 2 | ||||||
| Pruritus | 11 | 0 | 4 | 0 | ||||||
| Vascular disorders | 10 | 5 | 11 | 5 | ||||||
| Hypertension | 10 | 5 | 11 | 5 | ||||||
Note: Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA, Version 23.1) 10% cutoff is based on Bosutinib "All Grades" column. 1. Totals for the No. of Subjects at a higher level are not necessarily the sum of those at the lower levels since a subject may report two or more different adverse events within the higher level category. SOC for some preferred terms does not follow MedDRA classification. Abbreviations: CML=Chronic myelogenous leukemia; N=number of patients. Abdominal pain includes the following preferred terms: Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper, Abdominal tenderness, Gastrointestinal pain. Alanine aminotransferase increased includes Alanine aminotransferase increased, Alanine aminotransferase abnormal Anemia includes the following preferred terms: Anemia, Hemoglobin decreased, Red blood cell count decreased. Fatigue includes the following preferred terms: Asthenia, Fatigue, Malaise. Hypertension includes the following high level term and preferred terms: HLT- Accelerated and malignant hypertension, PT- Blood pressure ambulatory increased, Blood pressure diastolic increased, Blood pressure increased, Blood pressure systolic increased, Diastolic Hypertension, Essential Hypertension, Hypertension, Labile Hypertension, Systolic Hypertension Lipase increased includes the following preferred terms: Hyperlipasemia, Lipase increased Neutropenia includes the following preferred terms: Neutropenia, Neutrophil count decreased. Edema includes the following preferred terms: Face edema, Localised Edema, Edema, Edema peripheral, Generalised edema Periorbital edema, Eyelid edema, Peripheral swelling, Swelling, Swelling of eyelid, Periorbital swelling Rash includes the following preferred terms: Rash, Rash generalized, Rash macular, Rash maculo-papular, Rash papular, Rash pruritic. Respiratory tract infection includes the following preferred terms: Lower respiratory tract infection, Respiratory tract infection, Respiratory tract infection viral, Upper respiratory tract infection, Viral upper respiratory tract infection. Thrombocytopenia includes the following preferred terms: Platelet count decreased, Thrombocytopenia. | ||||||||||
Table 5 below presents adverse reactions (all causality) of any toxicity and grades 3/4 commonly reported (frequencies ≥ 1% to <10%) in the Phase 3 safety population.
| Table 5 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Table 5 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | |||||||||
| Table 5 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | |||||||||
| Table 5 – Newly-Diagnosed CML Patient Receiving BOSULIF 400 mg Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 3 Safety Population | |||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | ||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | ||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | ||||||||
Bosutinib 400 mg N=268 | Imatinib 400 mg N=265 | ||||||||
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | |||||
| Preferred Term | |||||||||
| Preferred Term | |||||||||
| Preferred Term | |||||||||
| Preferred Term | |||||||||
| Any Adverse Events | 97 | 60 | 96 | 45 | |||||
| Blood and lymphatic system disorders | |||||||||
| Leukopenia | 7 | 1 | 13 | 5 | |||||
| Cardiac Disorders | |||||||||
| Pericardial effusion | 2 | 0 | 0 | 0 | |||||
| Cardiac Failure | 2 | 1 | 1 | 0 | |||||
| Cardiac ischemic events | 5 | 3 | 1 | 0 | |||||
| Atrial Fibrilation | 2 | 1 | 2 | 1 | |||||
| Ear and labyrinth disorders | |||||||||
| Tinnitus | 3 | 0 | 1 | 0 | |||||
| Gastrointestinal disorders | |||||||||
| Gastritis | 3 | 0 | 2 | 0 | |||||
| Gastrointestinal hemorrhage | 2 | 0 | 3 | 0 | |||||
| General disorders and administration site conditions | |||||||||
| Chest Pain | 4 | 0 | 4 | 0 | |||||
| Pain | 2 | 0 | 4 | 0 | |||||
| Hepatobiliary disorders | |||||||||
| Hepatic function abnormal | 6 | 3 | 2 | 1 | |||||
| Hepatotoxicity | 3 | 2 | 1 | 0 | |||||
| Immune Disorders | |||||||||
| Drug hypersensitivity | 1 | 0 | 1 | 0 | |||||
| Infections and infestations | |||||||||
| Influenza | 9 | 0 | 6 | 1 | |||||
| Bronchitis | 7 | 0 | 3 | 0 | |||||
| Pneumonia | 5 | 1 | 3 | 2 | |||||
| Injury, poisoning and procedural complications | |||||||||
| Fractures | 9 | 2 | 4 | 0 | |||||
| Investigations | |||||||||
| Amylase increased | 10 | 2 | 4 | 2 | |||||
| Blood bilirubin increased | 9 | 1 | 3 | 0 | |||||
| Blood creatinine increased | 7 | 0 | 8 | 0 | |||||
| Blood creatine phosphokinase increased | 5 | 2 | 12 | 4 | |||||
Gamma-glutamyl transferase increased | 3 | 0 | 1 | 0 | |||||
| Electrocardiogram QT prolonged | 1 | 0 | 4 | 0 | |||||
| Metabolism and nutrition disorders | |||||||||
| Hypophosphatemia | 3 | 2 | 8 | 4 | |||||
| Hyperkalemia | 3 | 1 | 2 | 0 | |||||
| Dehydration | 1 | 1 | 1 | 0 | |||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Myalgia | 5 | 0 | 18 | 1 | |||||
| Nervous system disorders | |||||||||
| Dizziness | 9 | 0 | 9 | 0 | |||||
| Dysgeusia | 1 | 0 | 3 | 0 | |||||
| Renal and urinary disorders | |||||||||
| Acute kidney injury | 2 | 1 | 1 | 0 | |||||
| Renal impairment | 1 | 0 | 0 | 0 | |||||
| Chronic kidney disease | 1 | 1 | 1 | 0 | |||||
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Pleural effusion | 5 | 1 | 2 | 0 | |||||
| Respiratory failure | 1 | 1 | 0 | 0 | |||||
| Skin and subcutaneous disorders | |||||||||
| Acne | 3 | 0 | 0 | 0 | |||||
| Urticaria | 2 | 0 | 1 | 0 | |||||
Note: Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA, Version 23.1). Abbreviations: CML=Chronic myelogenous leukemia; N=number of patients. Totals for the No. of Subjects at a higher level are not necessarily the sum of those at the lower levels since a subject may report two or more different adverse events within the higher level category. SOC for some preferred terms does not follow MedDRA classification. The commonality stratification is based on 'All Grade' under Total column. 'Grade 3', 'Grade 4' columns indicate maximum toxicity. Amylase increased includes the following preferred terms: Amylase increased, Hyperamylasemia. Blood bilirubin increased includes the following preferred terms: Blood bilirubin increased, Hyperbilirubinemia, Bilirubin conjugated increased, Blood bilirubin unconjugated increased. Cardiac failure includes the following preferred terms: Cardiac Acute left ventricular failure, Acute right ventricular failure, Cardiac asthma, Cardiac failure, Cardiac failure acute, Cardiac failure chronic, Cardiac failure congestive, Cardiac failure high output, Cardiogenic shock, Cardiopulmonary failure, Cardiorenal syndrome, Chronic left ventricular failure, Chronic right ventricular failure, Cor pulmonale, Cor pulmonale chronic, Ejection fraction decreased, Hepatojugular reflux, Left ventricular failure, Low cardiac output syndrome, Neonatal cardiac failure, Obstructive shock, Radiation associated cardiac failure, Right ventricular ejection fraction decreased, Right ventricular failure, Ventricular failure, Cardiohepatic syndrome, Congestive hepatopathy. Cardiac ischemic events includes the following preferred terms: Acute coronary syndrome, Acute myocardial infarction, Angina pectoris, Angina unstable, Arteriosclerosis coronary artery, Coronary artery disease, Coronary artery occlusion, Coronary artery stenosis, Myocardial infarction, Myocardial ischemia, Troponin I increased, Troponin increased Chest pain includes the following preferred terms: Chest discomfort, Chest pain Electrocardiogram QT prolonged includes the following MedDRA SMQ: Torsade de pointes/QT prolongation (Narrow) Fractures includes the following preferred terms: Spinal pain, Foot fracture, Hand fracture, Osteoporosis, Rib fracture, Femoral neck fracture, Humerus fracture, Pain in jaw, Clavicle fracture, Coccydynia, Fibula fracture, Hip fracture, Lumbar vertebral fracture, Metatarsalgia’ Osteitis, Osteopenia, Patella fracture, Radius fracture, Sternal fracture, Stress fracture, Thoracic vertebral fracture, Tooth fracture, Wrist fracture Gastrointestinal hemorrhage includes the following preferred terms: Anal hemorrhage, Gastric hemorrhage, Gastroduodenal hemorrhage, Gastrointestinal hemorrhage, Intestinal hemorrhage, Large intestinal hemorrhage, Lower gastrointestinal hemorrhage, Oesophageal hemorrhage, Rectal hemorrhage, Small intestinal hemorrhage, Upper gastrointestinal hemorrhage Hepatic function abnormal includes the following preferred terms: Hepatic function abnormal, Hyper transaminasemia, Liver function test abnormal, Liver function test increased, Transaminases increased, Hepatic enzyme increased Hepatotoxicity includes the following preferred terms: Hepatitis, Hepatitis acute, Hepatitis cholestatic, Hepatitis toxic, Hepatotoxicity, Liver disorder Hyperkalemia includes the following preferred terms: Blood potassium increased, Hyperkalemia Hypophosphatemia includes the following preferred terms: Blood phosphorus decreased, Hypophosphatemia Influenza includes Influenza, H1N1 influenza Leukopenia includes the following preferred terms: Leukopenia, White blood cell count decreased Pneumonia includes the following preferred terms: Atypical pneumonia, Pneumonia, bacterial, Pneumonia fungal, Pneumonia necrotising, Pneumonia streptococcal | |||||||||
Bone fracture
In the Phase 3 clinical study (N=268) in patients newly-diagnosed with CP CML treated with bosutinib 400 mg, the frequency of Grade 3 or 4 fractures was 1.5% in the bosutinib arm (femoral neck fractures in 0.7% of patients and coccydynias and clavicle fracture in 0.4% each).
Chronic Phase (CP), Accelerated Phase (AP) and Blast Phase (BP) CML and ALL Patients Resistant or Intolerant to Previous TKIs Treatment
The single-arm Phase 1/2 clinical study enrolled a total of 571 patients with Ph+ chronic (n=284), accelerated (n=79), or blast (n=64) phase chronic myelogenous leukemia (CML) and 24 patients with Ph+ acute lymphoblastic leukemia (ALL) who were resistant or intolerant to prior TKI therapy. The safety population (received at least 1 dose of BOSULIF) included 570 patients.
After a minimum of 10 years (120 months) of follow up, the median duration of therapy was 11.13 months (range: 0.03 to 170.49 months); the median dose intensity was 442.02 mg/day. The majority of BOSULIF-treated patients (99.3%) experienced at least one adverse drug reaction. The most common (incidence ≥ 20%) were diarrhea (82.1%), nausea (47.4%), thrombocytopenia (41.4%), vomiting (39.6%), abdominal pain (39.1%), rash (34.7%), fatigue (33.7%), anemia (31.8%), pyrexia (28.6%), and headache (20.7%).
Overall, 70.9% of patients experienced, Grade 3 and 4 adverse drug reaction, and 28.6% of patients experienced serious adverse events (SAEs). The most common SAEs (>2% of patients overall) were pneumonia (6.7%), pleural effusion (5.4%), pyrexia (3.7%), thrombocytopenia (2.5%), dyspnea (2.6%), and diarrhea (2.3%).
Overall, 105 (18%) of patients permanently discontinued bosutinib due to an adverse drug reaction (ADR). The most common ADR leading to discontinuation (≥ 2% of patients overall) was thrombocytopenia (4.7%). Overall, 61.4% of patients had at least one dose interruption due to adverse events. The most common ADRs (≥ 5% of patients) resulting in dose interruption were thrombocytopenia (21.6%), diarrhea (12.3%), rash (11.0%), neutropenia (8.1%), vomiting (6.3%), pleural effusion (7.7%), ALT increased (7.0%) and AST increased (5.1%). Overall, 43.9% of patients had ≥1 dose reduction due to ADRs. The most common ADRs (≥ 5% of patients) resulting in reductions in bosutinib dose were thrombocytopenia (13.5%), rash (6.0%), diarrhea (5.6%).
Table below presents adverse reactions (all causality) of any toxicity and grades 3/4 very commonly reported (frequencies ≥10%) in the Phase 1/2 safety population.
| Table 6 – CML Patients Receiving BOSULIF Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Event by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||
|---|---|---|---|---|---|---|---|---|
| Table 6 – CML Patients Receiving BOSULIF Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Event by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||
| Table 6 – CML Patients Receiving BOSULIF Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Event by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||
| Table 6 – CML Patients Receiving BOSULIF Reporting Very Common (≥10%) Frequencies Treatment Emergent Adverse Event by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||
| CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||
| CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||
| CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||
| CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) |
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) |
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) |
| System Organ Class | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) |
| Preferred Term | ||||||||
| Preferred Term | ||||||||
| Preferred Term | ||||||||
| Preferred Term | ||||||||
| Any Adverse Event | 100 | 70 | 100 | 63 | 100 | 82 | 97 | 72 |
| Blood and lymphatic system disorders | ||||||||
| Thrombocytopenia | 42 | 25 | 38 | 26 | 53 | 44 | 34 | 33 |
| Anaemia | 31 | 14 | 24 | 7 | 46 | 33 | 30 | 20 |
| Neutropenia | 16 | 10 | 21 | 16 | 19 | 18 | 25 | 23 |
| Leukopenia | 13 | 5 | 4 | 1 | 13 | 6 | 19 | 19 |
| Gastrointestinal disorders | ||||||||
| Diarrhea | 86 | 10 | 83 | 9 | 86 | 4 | 64 | 5 |
| Nausea | 46 | 2 | 49 | 1 | 46 | 3 | 50 | 2 |
| Abdominal pain | 46 | 2 | 36 | 1 | 35 | 6 | 27 | 8 |
| Vomiting | 38 | 4 | 39 | 1 | 44 | 4 | 41 | 3 |
| General disorders and administration site conditions | ||||||||
| Fatigue | 38 | 4 | 29 | 2 | 29 | 6 | 25 | 5 |
| Pyrexia | 28 | 1 | 16 | 0 | 35 | 3 | 39 | 3 |
| Edema | 20 | 1 | 18 | 0 | 19 | 0 | 16 | 3 |
| Chest pain | 8 | 2 | 6 | 0 | 15 | 3 | 8 | 0 |
| Infections and infestations | ||||||||
| Respiratory tract infection | 16 | 0 | 15 | 1 | 15 | 0 | 5 | 0 |
| Nasopharyngitis | 14 | 0 | 12 | 0 | 10 | 0 | 2 | 0 |
| Influenza | 12 | 1 | 11 | 1 | 6 | 0 | 0 | 0 |
| Pneumonia | 10 | 6 | 4 | 0 | 18 | 13 | 19 | 11 |
| Investigations | ||||||||
| ALT increased | 24 | 8 | 16 | 7 | 14 | 8 | 6 | 2 |
| AST decreased | 21 | 4 | 8 | 3 | 15 | 5 | 6 | 0 |
| Blood creatinine increased | 13 | 1 | 13 | 0 | 9 | 1 | 5 | 0 |
| Lipase increased | 11 | 7 | 8 | 6 | 8 | 3 | 5 | 3 |
| Metabolism and nutrition disorders | ||||||||
| Decreased appetite | 15 | 1 | 13 | 1 | 10 | 0 | 19 | 0 |
| Musculoskeletal and connective tissue disorders | ||||||||
| Arthralgia | 21 | 1 | 21 | 2 | 19 | 0 | 14 | 0 |
| Back pain | 15 | 0 | 13 | 3 | 10 | 1 | 6 | 2 |
| Nervous system disorders | ||||||||
| Headache | 19 | 0 | 27 | 3 | 15 | 3 | 22 | 6 |
| Dizziness | 9 | 0 | 15 | 0 | 15 | 1 | 13 | 0 |
| Respiratory, thoracic and mediastinal disorders | ||||||||
| Cough | 25 | 0 | 22 | 0 | 30 | 0 | 13 | 0 |
| Dyspnea | 13 | 2 | 12 | 3 | 20 | 9 | 19 | 3 |
| Pleural effusion | 13 | 4 | 18 | 6 | 14 | 5 | 5 | 3 |
| Skin and subcutaneous disorders | ||||||||
| Rash | 38 | 9 | 30 | 4 | 37 | 4 | 31 | 5 |
| Pruritus | 10 | 1 | 17 | 1 | 8 | 0 | 6 | 0 |
| Vascular disorders | ||||||||
| Hypertension | 12 | 4 | 9 | 2 | 11 | 5 | 3 | 2 |
* CP = Chronic Phase; AP = Accelerated Phase; BP = Blast Phase Note: Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA, Version 23.1).(a)Totals for the No. of Subjects at a higher level are not necessarily the sum of those at the lower levels since a subject may report two or more different adverse events within the higher level category. SOC for some preferred terms does not follow Meddra classification. Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA). The commonality stratification is based on 'All Grade' under Total column. 'Grade 3', 'Grade 4' column indicate maximum toxicity. Abdominal pain includes the following preferred terms: Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper, Abdominal tenderness, Gastrointestinal pain. Anaemia includes the following preferred terms: Anaemia, Haemoglobin decreased, Red blood cell count decreased. Alanine aminotransferase increased includes Alanine aminotransferase increased, Alanine aminotransferase abnormal Chest pain includes the following preferred terms: Chest discomfort, Chest pain. Fatigue includes the following preferred terms: Asthenia, Fatigue, Malaise. Hypertension* includes the following high level term and preferred terms: HLT- Accelerated and malignant hypertension, PT- Blood pressure ambulatory increased, Blood pressure diastolic increased, Blood pressure increased, Blood pressure systolic increased, Diastolic Hypertension, Essential Hypertension, Hypertension, Labile Hypertension, Systolic Hypertension Influenza includes Influenza, H1N1 influenza Leukopenia includes the following preferred terms: Leukopenia, White blood cell count decreased. Lipase increased includes the following preferred terms: Hyperlipasemia, Lipase increased Neutropenia includes the following preferred terms: Neutropenia, Neutrophil count decreased. Edema includes the following preferred terms: Face edema, Localised Edema, Edema, Edema peripheral, Generalized edema Periorbital edema, Eyelid edema, Peripheral swelling, Swelling, Swelling of eyelid, Periorbital swelling. Pneumonia includes the following preferred terms: Atypical pneumonia, Pneumonia, Pneumonia bacterial, Pneumonia fungal, Pneumonia necrotising, Pneumonia streptococcal Rash includes the following preferred terms: Rash, Rash generalised, Rash macular, Rash maculo-papular, Rash pruritic. Respiratory tract infection includes the following preferred terms: Lower respiratory tract infection, Respiratory tract infection, Respiratory tract infection viral, Upper respiratory tract infection, Viral upper respiratory tract infection Thrombocytopenia includes the following preferred terms: Platelet count decreased, Thrombocytopenia. | ||||||||
Table 7 below presents adverse reactions (all causality) of any toxicity and grades 3/4 commonly reported (frequencies ≥ 1% to <10%) in the Phase 1/2 safety population.
| Table 7 – CML Patients Receiving BOSULIF Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Table 7 – CML Patients Receiving BOSULIF Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||||||||||||||
| Table 7 – CML Patients Receiving BOSULIF Reporting Common (≥ 1% to <10%) Frequencies Treatment Emergent Adverse Events by All Grades and Grades 3 or 4 for the Phase 1/2 Safety Population | ||||||||||||||||||||
CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||||||||||||||
CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||||||||||||||
CP* CML Imatinib Resistant or Intolerant N=284 | CP* CML Resistant or Intolerant ≥2 TKIs N=119 | AP* CML Resistant or Intolerant to at least Imatinib N=79 | BP* CML Resistant or Intolerant to at least Imatinib N=64 | |||||||||||||||||
| System Organ Class Preferred Term | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||||||
| System Organ Class Preferred Term | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||||||
| System Organ Class Preferred Term | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | All Grades (%) | Grade 3/4 (%) | ||||||||||||
| Any Adverse Event | 100 | 70 | 100 | 63 | 100 | 82 | 97 | 72 | ||||||||||||
| Blood and lymphatic system disorders | ||||||||||||||||||||
| Febrile Neutropenia | 0 | 0 | 2 | 2 | 1 | 1 | 5 | 3 | ||||||||||||
| Cardiac disorders | ||||||||||||||||||||
| Cardiac failure | 6 | 4 | 6 | 3 | 4 | 1 | 3 | 3 | ||||||||||||
| Cardiac ischemic events | 6 | 3 | 5 | 3 | 6 | 4 | 2 | 2 | ||||||||||||
| Pericardial effusion | 4 | 2 | 7 | 3 | 6 | 1 | 2 | 0 | ||||||||||||
| Pericarditis | 1 | 0 | 1 | 1 | 1 | 1 | 0 | 0 | ||||||||||||
| Atrial Fibrillation | 3 | 1 | 6 | 3 | 4 | 0 | 0 | 0 | ||||||||||||
| Ear and labyrinth disorders | ||||||||||||||||||||
| Tinnitus | 2 | 0 | 3 | 0 | 0 | 0 | 0 | 0 | ||||||||||||
| Gastrointestinal disorders | ||||||||||||||||||||
| Gastritis | 4 | 0 | 3 | 1 | 4 | 0 | 3 | 2 | ||||||||||||
| Gastrointestinal hemorrhage | 2 | 0 | 3 | 0 | 1 | 1 | 5 | 3 | ||||||||||||
| Acute pancreatitis | 2 | 1 | 0 | 0 | 3 | 3 | 0 | 0 | ||||||||||||
| General disorders and administration site conditions | ||||||||||||||||||||
| Pain | 8 | 0 | 6 | 0 | 9 | 1 | 8 | 3 | ||||||||||||
| Hepatobiliary disorders | ||||||||||||||||||||
| Hepatotoxicity | 4 | 1 | 3 | 3 | 1 | 0 | 3 | 0 | ||||||||||||
| Hepatic function abnormal | 4 | 2 | 3 | 0 | 4 | 1 | 3 | 0 | ||||||||||||
| Immune system disorders | ||||||||||||||||||||
| Drug hypersensitivity | 1 | 1 | 4 | 2 | 1 | 0 | 2 | 0 | ||||||||||||
| Infections and infestations | ||||||||||||||||||||
| Bronchitis | 7 | 1 | 7 | 1 | 8 | 0 | 0 | 0 | ||||||||||||
| Injury, poisoning and procedural complications | ||||||||||||||||||||
| Fractures | 7 | 2 | 2 | 0 | 4 | 0 | 2 | 0 | ||||||||||||
| Investigations | ||||||||||||||||||||
| Amylase increased | 6 | 2 | 5 | 0 | 3 | 0 | 5 | 2 | ||||||||||||
| Blood creatine phosphokinase increased | 6 | 3 | 2 | 0 | 4 | 0 | 0 | 0 | ||||||||||||
| Blood bilirubin increased | 4 | 0 | 4 | 0 | 3 | 0 | 9 | 8 | ||||||||||||
| Gamma-glutamyl transferase increased | 2 | 0 | 4 | 1 | 3 | 0 | 0 | 0 | ||||||||||||
| Electrocardiogram QT prolonged | 1 | 0 | 0 | 0 | 0 | 0 | 2 | 0 | ||||||||||||
| Metabolism and nutrition disorders | ||||||||||||||||||||
| Hypophosphatemia | 6 | 2 | 4 | 0 | 8 | 4 | 6 | 3 | ||||||||||||
| Hyperkalemia | 4 | 1 | 5 | 1 | 5 | 1 | 5 | 0 | ||||||||||||
| Dehydration | 3 | 0 | 2 | 0 | 4 | 1 | 6 | 0 | ||||||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||||||||||
| Myalgia | 9 | 0 | 5 | 0 | 9 | 0 | 9 | 2 | ||||||||||||
| Nervous system disorders | ||||||||||||||||||||
| Dysgeusia | 1 | 0 | 1 | 0 | 3 | 0 | 0 | 0 | ||||||||||||
| Renal and urinary disorders | ||||||||||||||||||||
| Acute kidney injury | 3 | 2 | 1 | 1 | 3 | 3 | 5 | 3 | ||||||||||||
| Renal failure | 2 | 1 | 3 | 2 | 6 | 0 | 2 | 2 | ||||||||||||
| Renal impairment | 2 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | ||||||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||||||||||
| Pulmonary hypertension | 2 | 1 | 2 | 0 | 0 | 0 | 0 | 0 | ||||||||||||
| Respiratory failure | 0 | 0 | 0 | 0 | 1 | 1 | 5 | 3 | ||||||||||||
| Pneumonitis | 1 | 0 | 1 | 1 | 1 | 1 | 2 | 2 | ||||||||||||
| Skin and subcutaneous disorders | ||||||||||||||||||||
| Acne | 4 | 0 | 1 | 0 | 3 | 0 | 2 | 0 | ||||||||||||
| Urticaria | 2 | 0 | 3 | 1 | 3 | 0 | 2 | 2 | ||||||||||||
| Exfoliative rash | 1 | 0 | 0 | 0 | 1 | 0 | 0 | 0 | ||||||||||||
| Photosensitivity reaction | 1 | 1 | 0 | 0 | 0 | 0 | 2 | 0 | ||||||||||||
| Drug eruption | 1 | 0 | 0 | 0 | 3 | 0 | 0 | 0 | ||||||||||||
Note: Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA, Version 23.1). * CP = Chronic Phase; AP = Accelerated Phase; BP = Blast Phase Totals for the No. of Subjects at a higher level are not necessarily the sum of those at the lower levels since a subject may report two or more different adverse events within the higher level category. SOC for some preferred terms does not follow MedDRA classification. Classifications of adverse events are based on the Medical Dictionary for Regulatory Activities (MedDRA). The commonality stratification is based on 'All Grade' under Total column. 'Grade 3', 'Grade 4' columns indicate maximum toxicity. Amylase increased includes the following preferred terms: Amylase increased, Hyperamylasaemia. Blood bilirubin increased includes the following preferred terms: Blood bilirubin increased, Hyperbilirubinemia, Bilirubin conjugated increased, Blood bilirubin unconjugated increased. Cardiac failure includes the following preferred terms: Cardiac Acute left ventricular failure, Acute right ventricular failure, Cardiac asthma, Cardiac failure, Cardiac failure acute, Cardiac failure chronic, Cardiac failure congestive, Cardiac failure high output, Cardiogenic shock, Cardiopulmonary failure, Cardiorenal syndrome, Chronic left ventricular failure, Chronic right ventricular failure, Cor pulmonale, Cor pulmonale chronic, Ejection fraction decreased, Hepatojugular reflux, Left ventricular failure, Low cardiac output syndrome, Neonatal cardiac failure, Obstructive shock, Radiation associated cardiac failure, Right ventricular ejection fraction decreased, Right ventricular failure, Ventricular failure, Cardiohepatic syndrome, Congestive hepatopathy. | ||||||||||||||||||||
Cardiac ischemic events includes the following preferred terms: Acute coronary syndrome, Acute myocardial infarction, Angina pectoris, Angina unstable, Arteriosclerosis coronary artery, Coronary artery disease, Coronary artery occlusion, Coronary artery stenosis, Myocardial infarction, Myocardial ischaemia, Troponin I increased, Troponin increased Electrocardiogram QT prolonged includes the following Electrocardiogram Torsade de pointes/QT prolongation (Narrow) Fractures includes the following terms: Tooth fracture, Ankle fracture, Facial bones fracture, Foot fracture, Hand fracture, Humerus fracture, Osteonecrosis, Osteopenia, Rib fracture, Upper limb fracture, Bone cyst, Cervical vertebral fracture, Clavicle fracture, Osteoporosis, Pain in jaw, Skull fracture, Spinal pain Gastrointestinal hemorrhage includes the following preferred terms: Anal hemorrhage, Gastric hemorrhage, Gastroduodenal hemorrhage, Gastrointestinal hemorrhage, Intestinal hemorrhage, Large intestinal hemorrhage, Oesophageal hemorrhage, Small intestinal hemorrhage, Upper gastrointestinal hemorrhage, Lower gastrointestinal hemorrhage, Rectal hemorrhage. Hepatic function abnormal includes the following preferred terms: Hepatic function abnormal, Hypertransaminasemia, Liver function test abnormal, Liver function test increased, Transaminases increased, Hepatic enzyme increased Hepatotoxicity includes the following preferred terms:, Hepatitis, Hepatitis acute, Hepatitis cholestatic, Hepatitis toxic, Hepatotoxicity, Liver disorder. Hyperkalemia includes the following preferred terms: Blood potassium increased, Hyperkalemia. Hypophosphatemia includes the following preferred terms: Blood phosphorus decreased, Hypophosphatemia. Lipase increased includes the following preferred terms: Hyperlipasemia, Lipase increased. Pancreatitis acute includes the following preferred terms: Pancreatitis, Pancreatitis acute. Photosensitivity reaction includes the following high level term: HLT- Photosensitivity and photo dermatosis conditions Pneumonia includes the following preferred terms: Atypical pneumonia, Pneumonia, Pneumonia bacterial, Pneumonia fungal, Pneumonia necrotising, Pneumonia streptococcal. Pulmonary hypertension includes the following preferred terms: Pulmonary arterial pressure increased, Pulmonary arterial hypertension, Pulmonary Hypertension | ||||||||||||||||||||
Bone fracture
In the single arm phase 1/2 study in 570 patients with CML who were resistant or intolerant to prior therapy, the frequency of fractures was 4.6% (with 0.9% of Grade 3 or 4 events). Grade 3 or 4 AEs reported in 0.2% of patients each were humerus fracture, rib fracture, bone cyst, skull fracture and upper limb fracture.
ECG Findings
In the Phase 1/ 2 clinical study in 570 patients with Ph+ leukemias treated with prior therapy treated with 500 mg bosutinib, 3 patient (0.5%) experienced QTcF (corrected QT by the Fridericia method) intervals of greater than 500 ms. Nine (1.6%) of the patients experienced QTcF increases from baseline exceeding 60 ms. Patients with uncontrolled or significant cardiovascular disease, including QT interval prolongation, at baseline were excluded by protocol criteria from the clinical trials.
In the phase 3 study in patients newly diagnosed with CP CML treated with 400 mg, there was 1 patient in the bosutinib treatment group and 0 patients in the imatinib treatment group who experienced corrected QT by the Fridericia method (QTcF) interval of greater than 500 msec.
In a Phase 1 study of 27 subjects with hepatic impairment and in matched healthy adults, of 27 patients, an increasing frequency of QTc prolongation > 450 ms was observed in 10 (37 %) of subjects (9 hepatically impaired subjects and 1 healthy subject).
Tabulated Summary of Adverse Reactions
The following adverse reactions in Table 8 were reported in patients in pooled clinical studies with BOSULIF. They represent an evaluation of the adverse reaction data from 1372 patients who received at least 1 dose of single-agent BOSULIF in newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy, other Ph+ leukemias. These adverse reactions are presented by system organ class and by frequency. Frequency categories are defined as: very common (≥10%), common (≥1% to <10%), uncommon (≥0.1% to <1%), rare (≥0.01% to <0.1%), very rare (<0.01%), not known (cannot be estimated from the available data).
Table 8 – Adverse Reactions for BOSULIF Pooled Safety (Newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy, other Ph+ leukemias) N= 1372
Infections and infestations
Very common
respiratory tract infection (including upper respiratory tract infection, lower respiratory tract infection, viral upper respiratory tract infection, respiratory tract infection viral), nasopharyngitis
Common
pneumonia (including atypical pneumonia, Pneumonia bacterial, Pneumonia fungal, Pneumonia necrotizing, Pneumonia streptococcal), influenza (including H1N1 Influenza), bronchitis
Blood and lymphatic system disorders
Very common
thrombocytopenia (including platelet count decreased), anemia (including hemoglobin decreased, red blood cell count decreased), neutropenia (including neutrophil count decreased)
Common
leukopenia (including white blood cell count decreased)
Uncommon
febrile neutropenia, granulocytopenia
Immune system disorders
Common
Uncommon
drug hypersensitivity
anaphylactic shock
Metabolism and nutrition disorders
Very common
decreased appetite
Common
hyperkalemia (including blood potassium increased), hypophosphatemia (including blood phosphorus decreased), dehydration
Nervous system disorders
Very common
headache, dizziness
Common
dysgeusia
Ear and labyrinth disorders
Common
tinnitus
Cardiac disorders
Table 8 – Adverse Reactions for BOSULIF Pooled Safety (Newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy, other Ph+ leukemias) N= 1372
Common
cardiac ischemic events (including Acute coronary syndrome, Acute myocardial infarction, Angina pectoris, Angina unstable, Arteriosclerosis coronary artery, Coronary artery disease, Coronary artery occlusion, Coronary artery stenosis, Myocardial infarction, Myocardial ischaemia,
Troponin increased), pericardial effusion, cardiac failure (including
Cardiac failure acute, Cardiac failure chronic, Cardiac failure congestive, Cardiogenic shock, Cardiorenal syndrome, Ejection fraction decreased, Left ventricular failure)
Uncommon
pericarditis
Vascular disorders
Common
hypertension (including blood pressure increased, blood pressure systolic increased, essential hypertension, hypertensive crisis)
Respiratory, thoracic and mediastinal disorders
Very common
Dyspnea, Pleural effusion
Common
Respiratory failure, Pulmonary hypertension (including Pulmonary arterial hypertension, Pulmonary arterial pressure increased)
Uncommon
acute pulmonary edema (including, pulmonary edema), Interstitial lung disease
Gastrointestinal disorders
Very common
diarrhea, vomiting, abdominal pain (including abdominal pain upper, abdominal pain lower, abdominal discomfort, abdominal tenderness, gastrointestinal pain), nausea
Common
gastritis, gastrointestinal hemorrhage (including anal hemorrhage, gastric hemorrhage, Intestinal hemorrhage, upper gastrointestinal hemorrhage, lower gastrointestinal hemorrhage, rectal hemorrhage), pancreatitis acute (including pancreatitis)
Hepatobiliary disorders
Common
hepatotoxicity (including hepatitis, hepatitis toxic, liver disorder), hepatic function abnormal (including Hepatic enzyme increased, liver function test abnormal, liver function test increased, transaminases increased)
Uncommon
liver injury (including drug-induced liver injury, hepatocellular injury)
Skin and subcutaneous tissue disorders
Very common
rash (including rash maculo-papular, rash pruritic, rash papular, rash macular), pruritus
Common
urticaria, acne
Uncommon
erythema multiforme, exfoliative rash, drug eruption
Musculoskeletal and connective tissue disorders
Very common
arthralgia, back pain
Common
myalgia
Table 8 – Adverse Reactions for BOSULIF Pooled Safety (Newly diagnosed Ph+ CP CML, CML resistant or intolerant to prior therapy, other Ph+ leukemias) N= 1372
Renal and urinary disorders
Common
acute kidney injury, renal failure, renal impairment
General disorders and administration site conditions
Very common
fatigue (including asthenia, malaise), pyrexia, edema (including eyelid edema, face edema, generalized edema, localized edema, peripheral edema, periorbital edema, periorbital swelling, peripheral swelling, swelling, swelling of eyelid)
Common
chest pain (including chest discomfort), pain
Investigations
Very common
alanine aminotransferase increased (including ALT abnormal, aspartate aminotransferase increased, lipase increased (including hyperlipasemia), blood creatinine increased
Common
Amylase increased (including hyperamylasemia), gamma-glutamyltransferase increased, blood creatine phosphokinase increased, blood bilirubin increased (including bilirubin conjugated increased, blood bilirubin unconjugated increased, hyperbilirubinemia), electrocardiogram QT prolonged (including long QT syndrome, ventricular tachycardia)
Note: Preferred Terms shown in parenthesis were grouped to determine a more accurate frequency.
8.3. Less Common Clinical Trial Adverse Reactions
Please see Table 8.
8.4. Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Potential clinically relevant or severe Grade 3/ 4 laboratory test abnormalities that were reported in BOSULIF clinical studies, regardless of causality and frequency, are listed in Table 9 below.
Abnormal Hematologic and Clinical Chemistry Findings
Table 9 presents potential clinically relevant or severe abnormalities of routine hematological, or biochemistry laboratory values in the study patient population who received at least one dose of BOSULIF in the Phase 1/2 study B1871006.
Table 9 – Percent of Patients with Potential Clinically Relevant or Severe Grade 3/ 4 Laboratory Test Abnormalities in the Phase 1/2 Clinical Study
CP* CML
Imatinib- Resistant or Intolerant
N=284
CP* CML Resistant or Intolerant ≥2 TKIs N=119
AP* CML, BP* CML
Resistant or Intolerant to at least Imatinib N=143
Hematology parameters
%
%
%
Platelet Count <50 X 109/L
26
26
57
Absolute Neutrophil Count <1 X10⁹/L
16
18
39
Hemoglobin (Low) <80 g/L
15
8
38
Biochemistry parameters
SGPT/ALT >5.0 X ULN
12
10
6
SGOT/AST >5.0 X ULN
5
4
4
Lipase >2 X ULN
12
8
6
Phosphorus (Low) <0.6 mmol/L
10
3
7
Total Bilirubin (High) >3XULN
0
3
3
*CP = Chronic Phase; AP = Accelerated Phase; BP = Blast Phase
Table 10 presents potential clinically relevant or severe abnormalities of routine hematological, or biochemistry laboratory values in the study patient population who received at least one dose of BOSULIF in the Phase 3 BFORE study.
Table 10 – Percent of Patients with Potential Clinically Relevant or Severe Grade 3/ 4 Laboratory Test Abnormalities in the Phase 3 Clinical Study
Bosutinib 400 mg
Newly Diagnosed Chronic Phase CML
N=268
Hematology parameters
%
Platelet Count <50 X 109/L
14
Absolute Neutrophil Count <1 X10⁹/L
9
Hemoglobin (Low) <80 g/L
9
Biochemistry parameters
SGPT/ALT >5.0 X ULN
26
SGOT/AST >5.0 X ULN
13
Lipase >2 X ULN
19
Phosphorus (Low) <0.6 mmol/L
9
Total Bilirubin (High) >3XULN
2
Table 11 shows the shift from baseline to lowest observed eGFR during bosutinib treatment for patients in the pooled leukemia studies regardless of line of therapy.
| Table 11 – Shift From Baseline to Lowest Observed eGFR Group During Treatment Safety Population in Clinical Studies (N=1372)* | |||||||
|---|---|---|---|---|---|---|---|
| Table 11 – Shift From Baseline to Lowest Observed eGFR Group During Treatment Safety Population in Clinical Studies (N=1372)* | |||||||
| Baseline | Follow-Up | ||||||
| Baseline | Follow-Up | ||||||
| Renal Function Status | N | Normal n (%) | Mild n (%) | Mild to Moderate n (%) | Moderate to Severe n (%) | Severe n (%) | Kidney Failure n (%) |
| Renal Function Status | N | Normal n (%) | Mild n (%) | Mild to Moderate n (%) | Moderate to Severe n (%) | Severe n (%) | Kidney Failure n (%) |
| Normal | 527 | 115 (21.8) | 330 (62.6) | 50 (9.5) | 23 (4.4) | 3 (0.6) | 5 (0.9) |
| Mild | 672 | 10 (1.5) | 259 (38.5) | 271 (40.3) | 96 (14.3) | 26 (3.9) | 6 (0.9) |
| Mild to Moderate | 137 | 0 | 6 (4.4) | 40 (29.2) | 66 (48.2) | 24 (17.5) | 2 (1.5) |
| Moderate to Severe | 33 | 0 | 1 (3.0) | 1 (3.0) | 8 (24.2) | 19 (57.6) | 4 (12.1) |
| Severe | 1 | 0 | 0 | 0 | 0 | 0 | 1 (100.0) |
| Total | 1372 | 125 (9.1) | 598 (43.6) | 362 (26.4) | 193 (14.1) | 72 (5.2) | 17 (1.2) |
Abbreviations: eGFR=estimated glomerular filtration rate; N/n=number of patients. Notes: eGFR was calculated using Modification in Diet in Renal Disease method (MDRD).Notes: Grading is based on Kidney Disease Improving Global Outcomes (KDIGO) Classification by eGFR: Normal: greater than or | |||||||
equal to 90, Mild: 60 to less than 90, Mild to Moderate: 45 to less than 60, Moderate to Severe: 30 to less than 45, Severe: 15 to less than 30, Kidney Failure: less than 15 ml/min/1.73 m2. *Among the 1372 patients, eGFR was missing in 7 patients at baseline or on-therapy. There were no patients with kidney failure at baseline. | |||||||
Table 12 presents the on-treatment median (95% CI) change in eGFR from baseline over time in patients with a baseline creatinine value in the Phase 1/2 study B1871006 (see 14 Clinical Trials).
| Table 12 – On-treatment eGFR Change from Baseline Over Time In previously treated Patients in the Phase 1/2 study | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
Time Point (months) | Total (N=569) | eGRF (mL/min/1.73 m2) Median Change (95% CI) | ||||||||
| Baseline | 569 | NA | ||||||||
| 3 | 429 | -5.3 (-6.3, -3.9) | ||||||||
| 12 | 290 | -7.6 (-8.9, -6.0) | ||||||||
| 24 | 210 | -8.5 (-10.5, -6.1) | ||||||||
| 36 | 185 | -10.9 (-13.2, -8.1) | ||||||||
| 48 | 167 | -11.1 (-14.2, -9.0) | ||||||||
| 60 | 149 | -12.3 (-15.4, -10.4) | ||||||||
| 120 | 70 | -15.9 (-21.4, -11.1) | ||||||||
Table 13 presents the on-treatment median (95% CI) change in eGFR from baseline over time in patients with a baseline creatinine value in the Phase 3 BFORE study (see 14 Clinical Trials).
| Table 13 – On-treatment eGFR Change from Baseline Over Time in Patients in the Phase 3 study in newly diagnosed CP CML patients treated with BOSULIF 400mg | |||||||||
|---|---|---|---|---|---|---|---|---|---|
Time Point (months) | Total (N=268) | eGRF (mL/min/1.73 m2) Median Change (95% CI) | |||||||
| Baseline | 268 | NA | |||||||
| 3 | 248 | -4.9 (-6.9, -2.4) | |||||||
| 12 | 217 | -11.1 (-12.8, -9.2) | |||||||
| 60 | 154 | -14.1 (-17.8, -12.0) | |||||||
8.5. Post-Market Adverse Reactions
Skin and subcutaneous tissue disorders: Stevens-Johnson syndrome has been rarely reported in the post-market setting.
9. Drug Interactions
9.1. Serious Drug Interactions
- Strong and moderate CYP3A inhibitors increase BOSULIF exposure. Avoid concomitant use of these inhibitors.
- Strong and moderate CYP3A inducers decrease BOSULIF exposure. Avoid concomitant use of these inducers.
9.2. Drug Interactions Overview
In vitro studies with human liver microsomes indicated that the major CYP450 isozyme involved in the metabolism of bosutinib is CYP3A4. No metabolism of bosutinib was observed with CYPs 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, or 3A5. Flavin-containing monooxygenase enzymes (FMO1, FMO3, and FMO5) are capable of metabolizing bosutinib to its N-oxide metabolite.
9.3. Drug-Behavioural Interactions
Alcohol
No studies have been performed on the potential interaction between bosutinib and alcohol consumption.
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 14 – Established or Potential Drug-Drug Interactions
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment | ||
| CYP3A inhibitors | CT | Co-administration of BOSULIF with a strong CYP3A inhibitor (ketoconazole) increased BOSULIF Cmax and AUC by 5.2-fold and 8.6 -fold, respectively, in healthy fasting subjects receiving BOSULIF 100 mg daily. Co-administration of BOSULIF with a moderate CYP3A inhibitor (aprepitant) increased BOSULIF Cmax and AUC by 1.5-fold and 2.0-fold, respectively, of the values when 500 mg of BOSULIF was administered alone under fed state in healthy subjects. | Avoid the concomitant use of strong CYP3A inhibitors (e.g., including but not limited to boceprevir, clarithromycin, conivaptan, indinavir, itraconazole, ketoconazole, lopinavir/ritonavir, mibefradil, nefazodone, nelfinavir, posaconazole, ritonavir, saquinavir, telaprevir, telithromycin, troleandomycin, voriconazole), or moderate CYP3A inhibitors (e.g., including but not limited to amprenavir, aprepitant, atazanavir, cimetidine, ciprofloxacin, crizotinib, darunavir/ritonavir, diltiazem, erythromycin, fluconazole, fosamprenavir, imatinib, verapamil, grapefruit products including star fruit, pomegranate, Seville oranges and other similar fruits that are known to inhibit CYP3A4) with BOSULIF, as an increase in bosutinib plasma concentration is possible. Use caution if mild CYP3A inhibitors are used concomitantly with BOSULIF. Selection of an alternate concomitant medication with no or minimal enzyme inhibition potential, if possible, is recommended. | ||
| CYP3A Inducers | CT | Co-administration of BOSULIF with a strong CYP3A inducer (rifampin) decreased BOSULIF Cmax and AUC to 14% and 6%, respectively, of the values when 500 mg of BOSULIF was administered alone in the fed state in healthy subjects. | Avoid the concomitant use of strong CYP3A inducers (e.g., including but not limited to carbamazepine, phenytoin, rifampin, St. John’s wort or moderate CYP3A inducers (e.g., including but not limited to bosentan, efavirenz, etravirine, modafinil, nafcillin) with BOSULIF. Based on the large reduction in bosutinib exposure that occurred when BOSULIF was co-administered with rifampin (strong CYP3A inducer), increasing the dose of BOSULIF when co-administering with strong or moderate CYP3A inducers is unlikely to sufficiently compensate for the loss of exposure. Use caution if mild CYP3A inducers are used concomitantly with BOSULIF. | ||
| Proton Pump Inhibitors (PPIs) | CT | BOSULIF displays pH dependent aqueous solubility in vitro. Co-administration of BOSULIF with a PPI (lansoprazole) decreased BOSULIF Cmax and AUC to 54% and 74%, respectively, of the values when 400 mg of BOSULIF was administered alone in healthy fasting subjects. | Use caution when administering BOSULIF concomitantly with PPIs. Short-acting antacids should be considered as an alternative to PPIs, administration times of BOSULIF and antacids should be separated (e.g take BOSULIF in the morning, and antacids in the evening) whenever possible. | ||
| Anti-arrhythmic Medicines and Other Drugs | T | May Prolong QT | Concomitant use of BOSULIF with another QT/QTc-prolonging drug is discouraged. Drugs that have been associated with QT/QTc interval prolongation and/or torsade de pointes include, but are not limited to, the examples in the following list. Chemical/pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QT/QTc prolongation and/or torsade de pointes:
e.g., amitriptyline, imipramine, maprotiline);
| ||
The use of BOSULIF is discouraged with drugs that can disrupt electrolyte levels, including, but not limited to, the following:
The above lists of potentially interacting drugs are not comprehensive. Current information sources should be consulted for newly approved drugs that prolong the QT/QTc interval, inhibit metabolizing enzymes and/or transporters, or cause electrolyte disturbances, as well as for older drugs for which these effects have recently been established. | |||||
Legend: CT = Clinical Trial; T = Theoretical
In vitro studies
Bosutinib and transporters: In vitro transporter studies demonstrated that bosutinib is a substrate for efflux transporters P-gp, BCRP and MRPs. Possible interactions with BOSULIF and concomitant drug efflux transporter inhibitors may occur.
In vitro studies indicate that bosutinib has a low potential to inhibit breast cancer resistance protein (BCRP, systemically), organic anion transporting polypeptide (OATP)1B1, OATP1B3, organic anion transporter (OAT)1, OAT3, organic cation transporter (OCT)1, and OCT2 at clinically relevant concentrations, but may have the potential to inhibit BCRP in the gastrointestinal tract and OCT1.
Bosutinib and substrates of CYP: An in vitro study indicates that clinical drug-drug interactions are unlikely to occur as a result of induction by BOSULIF on the metabolism of drugs that are substrates for CYP1A2, CYP2B6, CYP2C9, CYP2C19, and CYP3A4.
Bosutinib and CYP enzymes: In vitro, bosutinib inhibited CYP2C19, CYP2D6, and CYP3A4/5 at concentrations that were 26 to 71-fold higher than the Cmax in humans at 500 mg once daily.
9.5. Drug-Food Interactions
Administration of BOSULIF with a meal increased BOSULIF Cmax 1.8- fold and AUC 1.7-fold, respectively at the dose of 400 mg in healthy subjects (see 4 Dosage and Administration and 10.2 Pharmacokinetics, Absorption and 7 Warnings and Precautions, Hepatic/ Biliary/Pancreatic and Renal). BOSULIF taken without a meal may decrease BOSULIF’s bioavailability.
Products and juices containing grapefruit, star fruit, pomegranate, Seville oranges and other similar fruits that are known to inhibit CYP3A4, should be avoided at any time as they may increase BOSULIF plasma concentrations.
9.6. Drug-Herb Interactions
St. John’s Wort is a strong CYP3A4 inducer. Avoid the concomitant use of strong CYP3A inducers with BOSULIF as this may lead to decreased plasma concentrations of BOSULIF (see 9.4 Drug-Drug Interaction and 4 Dosage and Administration).
9.7. Drug-Laboratory Test Interactions
Interactions between BOSULIF and laboratory tests have not been studied.
10. Clinical Pharmacology
10.1. Mechanism of Action
BOSULIF belongs to a pharmacologic class of drugs known as tyrosine kinase inhibitors. BOSULIF inhibits the activity of the oncogenic Bcr-Abl kinase that promotes CML, and Src-family of kinases such as Src, Lyn and Hck, which participate in Bcr-Abl signaling. Modeling studies indicate that BOSULIF binds the kinase domain of Bcr-Abl. BOSULIF also inhibits other kinases such as EPH, TEC and STE20 kinases. BOSULIF minimally inhibits platelet-derived growth factor (PDGF) receptor and c-Kit (protein-tyrosine kinase Kit).
BOSULIF exhibits potent anti-leukemic activity in imatinib-sensitive and resistant BCR-ABL-dependent leukemia cells. In in vitro studies, BOSULIF inhibits proliferation and survival of established CML cell lines, Ph+ ALL cell lines, and patient-derived primary primitive CML cells. BOSULIF inhibited 16 of 18 imatinib-resistant forms of Bcr-Abl expressed in murine myeloid cell lines, except T315I. Bosutinib treatment reduced the size of CML tumors growing in nude mice and inhibited growth of murine myeloid tumors expressing imatinib-resistant forms of Bcr-Abl. BOSULIF also inhibits receptor tyrosine kinases c-Fms, EphA and B receptors, Trk-family kinases, Axl-family kinases, Tec-family kinases, some members of the ErbB-family, the non-receptor tyrosine kinase Csk, serine/threonine kinases of the Ste20-family and two calmodulin-dependent protein kinases.
10.2. Pharmacodynamics
QT/QTc Prolongation
The effect of single dose BOSULIF 500 mg administration on corrected QT interval (QTcF=QT/RR0.33) was evaluated in a two-part study (Part A & Part B).
Part A was a randomized, double-blind (with respect to bosutinib), 3 period crossover in which healthy male subjects (N=58) received single doses of bosutinib 500 mg, placebo, or moxifloxacin 400 mg in the fed state. The maximum observed QTcF difference from placebo during treatment with bosutinib 500 mg was 2.46 msec (90% CI: [0.54, 4.38]) at 8 h. The results for Part A cannot be extrapolated to steady-state use of bosutinib because the maximal plasma concentrations achieved after the single 500 mg dose (mean Cmax 114±39.8 ng/mL) were only 42-57% of the maximal plasma concentrations observed in the target patient population receiving bosutinib 500 mg at steady-state (mean Cmax 200-273 ng/mL).
Part B was a randomized, double-blind (with respect to bosutinib), 2 period crossover in which healthy male subjects (N=54) were administered a single dose of test article (bosutinib 500 mg or placebo) concomitantly with ketoconazole in the fed state. On day -1, ketoconazole was administered as a single oral 400 mg dose in each period. On day 1, the subjects received bosutinib 500 mg or placebo concomitantly with 400 mg ketoconazole in the fed state. On days 2 and 3, subjects received single oral doses of 400 mg ketoconazole. Part B did not have a placebo only treatment arm or a drug-free baseline. The maximal mean difference in QTcF interval between ketoconazole plus bosutinib and ketoconazole plus placebo was 7.36 msec (90% CI: [5.09, 9.63]) at 8 h on day 1. The mean Cmax achieved after a single 500 mg dose of bosutinib in the presence of ketoconazole was 326±77.2 ng/mL.
Patients with hepatic impairment may be at increased risk of developing QT/QTc prolongation. In a single-oral-dose (200 mg) study in non-CML patients, treatment-emergent QTc prolongation was observed in 50% of hepatically impaired patients (Child-Pugh class A, B or C), versus 11% of matching healthy volunteers; the frequency, magnitude and duration of QTc prolongation appeared to increase with severity of hepatic impairment: all 6 patients with Child-Pugh C at baseline had QTc prolongation following treatment, versus 1/6 and 2/6 of patients of Child-Pugh A and B, respectively. Except for one patient who recorded QTc of 450 msec at day 1 predose, all other Child-Pugh C patients (n=5) had QTc prolongation starting 3 hours post-dose lasted from Day 4 and beyond. The greatest relative QTc increase over baseline was 48 msec in one patient with Child-Pugh C hepatic impairment. However, no QTc > 500 msec was reported for any volunteer in the study.
10.3. Pharmacokinetics
| Table 15 – Summary of BOSULIF’s Pharmacokinetic Parameters in CML Fed Patients at Steady-state after 15 Consecutive Days of 400, 500 and 600 mg Oral Dose | |||||||||
Dose (mg) | N | Cmax (ng/mL) | t½ (h) | AUC0-24 (ng*h/mL) | Clearance (CL/F) (L/h) | ||||
| 400 | 3 | 146 (20) | 46.0 (32.3) | 2720 (442) | 150 (23) | ||||
| 500 | 3 | 200 (12) | 21.7 (4.6) | 3650 (425) | 138 (17) | ||||
| 600 | 10 | 208 (73) | 25.9 (24.9)a | 3630 (1270)b | 185 (66)b | ||||
Data are mean (standard deviation) values. a: n = 7 b: n = 9 | |||||||||
Absorption
Following administration of a single oral dose of BOSULIF (500 mg) with food in healthy subjects, the absolute bioavailability was 34%. Absorption was relatively slow, with a median time-to-peak concentration (tmax) reached after 6 hours. The mean (SD) Cmax value was 90 (24) ng/mL and the mean AUC was 2060 (448) ng•h/mL after a single dose of bosutinib (400 mg) with food; and the mean standard deviation (SD) Cmax value was 112 (29) ng/mL, and the mean (SD) AUC was 2740 (790) ng•h/mL after a single dose of bosutinib (500 mg) with food in healthy subjects, respectively.
Food increased bosutinib Cmax 1.8-fold and bosutinib AUC 1.7-fold compared to the fasting state. The mean (SD) Cmax value was 146 (20) ng/mL and the mean (SD) AUCtau was 2720 (442) ng•h/mL after 15 daily dosing of bosutinib tablet (400 mg) with food; and the mean (SD) Cmax value was 200 (12) ng/mL, and the mean (SD) AUCtau was 3650 (425) ng•h/mL after 15 daily dosing of bosutinib tablet (500 mg) with food in patients with CML.
Bosutinib displays pH dependent aqueous solubility in vitro. Lansoprazole decreases bosutinib exposure (see 9.4 Drug-Drug Interactions).
Distribution:
After administration of a single intravenous (IV) dose of BOSULIF 120 mg to healthy subjects, bosutinib had a mean volume of distribution (standard deviation) of 2441 (796) L suggesting that bosutinib is extensively distributed to extra-vascular tissue and/or with low oral bioavailability. In an animal study with rat, bosutinib did not cross the blood-brain barrier.
Bosutinib was highly bound to human plasma proteins in vitro (94%) and ex vivo in healthy subjects (96%), and binding was not concentration-dependent.
Metabolism:
In vitro studies with human liver microsomes indicated that the major CYP450 isozyme involved in the metabolism of bosutinib is CYP3A4. No metabolism of bosutinib was observed with CYPs 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, or 3A5. Flavin-containing monooxygenase enzymes (FMO1, FMO3, and FMO5) are capable of metabolizing bosutinib to its N-oxide metabolite. In vitro and in vivo studies indicated that bosutinib (parent compound) undergoes predominantly hepatic metabolism (by CYP3A4) in humans. Following administration of single or multiple doses of BOSULIF (400 mg or 500 mg) to humans, the major circulating metabolites appeared to be oxydechlorinated (M2) and N desmethylated (M5) bosutinib, with bosutinib N-oxide (M6) as a minor circulating metabolite. The systemic exposure of N-desmethylated metabolite was 25% of the parent compound, while the oxydechlorinated metabolite was 19% of the parent compound. All three metabolites exhibited activity that was ≤ 5% that of bosutinib in a Src-transformed fibroblast anchorage-independent proliferation assay. In feces, bosutinib and N-desmethyl bosutinib were the major drug-related components.
Elimination
In 14 healthy subjects given a single IV dose (120 mg) of bosutinib, the mean (SD) terminal phase elimination half-life (t1/2) was 35.5 (8.5) hours, and the mean (SD) clearance (Cl) was 63.6 (14.1) L/h. In six healthy male subjects given a single oral dose of [14C] radiolabeled bosutinib, an average of 94.6% of the total administered radioactivity was recovered in 9 days; feces (91.3% of dose) was the major route of excretion, with 3.29% of the dose recovered in urine. Excretion was rapid, with 75% of the dose recovered within 96 hours. Excretion of unchanged bosutinib in urine was low, approximately 1% of the administered dose, in healthy subjects.
Linearity / Non-linearity:
Both observed Cmax and AUC values of bosutinib increased with increasing dose in a linear fashion when single, ascending oral doses of 200- to 800 mg bosutinib were administered with food to healthy subjects. At steady state (reached in approximately 15 days), Cmax and AUC values of bosutinib increased in a less than dose proportional manner between 500 and 600 mg taken with food in CML patients in a dose escalation study (see Table 15). The interpretation of bosutinib dose proportionality finding at steady state may be limited by small number of subjects and high interindividual variability. Based on a population pharmacokinetic analysis in cancer patients, bosutinib is predicted to exhibit dose proportional increase over the dose range of 200 -600 mg with food.
Special Populations and Conditions
Pediatrics (<18 years of age): The safety and efficacy of BOSULIF in patients less than 18 years of age have not been evaluated. No data are available.
Geriatrics (≥ 65 years of age): No clinically relevant age-related pharmacokinetic differences have been observed in the elderly. No specific dose recommendation is necessary in the elderly.
Hepatic Impairment: Metabolism of bosutinib is mainly hepatic. Clinical studies have excluded patients with ALT and/or AST >2.5 (or >5, if related to disease) x ULN range and/or bilirubin >1.5 x ULN range.
In a single-oral-dose study, BOSULIF (200 mg) administered with food was evaluated in a cohort of 18 hepatically impaired subjects (Child-Pugh classes A, B, and C) and 9 matched healthy subjects. Cmax of bosutinib in plasma increased 2.4-fold, 2-fold, and 1.5-fold, respectively, in Child-Pugh classes A, B, and C; and bosutinib AUC in plasma increased 2.3 fold, 2-fold, and 1.9-fold, respectively. The t1/2 of bosutinib increased 1.6-fold, 2.0-fold and 2.0 fold and CL/F decreased to 45, 50 and 52% in hepatic impaired patients (subjects (Child-Pugh classes A, B, and C) as compared to the healthy subjects (see 2 Contraindications; 7 Warnings and Precautions, Special Populations; 4.1 Dosing considerations; 8 Adverse Reactions and 10 Clinical Pharmacology).
Renal Impairment: In a dedicated renal impairment trial, a single dose of Bosulif 200 mg was administered with food to 26 non-CML subjects with mild, moderate or severe renal impairment and to 8 matching healthy volunteers. Renal impairment was based on CrCl (calculated by Cockcroft-Gault formula) of <30 mL/min (severe renal impairment), 30 ≤ CrCl ≤50 mL/min (moderate renal impairment), or 50 <CrCl ≤80 mL/min (mild renal impairment). Subjects with moderate and severe renal impairment had an increase in AUC over healthy volunteers of 35 % (90%CI: [-1.0, 85.0]) and 60% (90%CI: [16.0, 121.0]), respectively. Bosutinib exposure was not changed in subjects with mild renal impairment. Based on pharmacokinetic linearity, a daily dose of 400 mg in patients with moderate renal impairment and 300 mg in patients with severe renal impairment are predicted to result in an area under the concentration curve (AUC) that are 108% and 96%, respectively of the AUC seen in patients with normal renal function receiving 500 mg daily. The half-life (57, 55 and 57 hours) of bosutinib in subjects with mild, moderate and severe renal impairment was similar to its half-life (54 hours) in healthy subjects. CL/F values of bosutinib in healthy subjects and in subjects with mild, moderate and severe renal impairment were 3021, 2965, 2238 and 1892 mL/min.
- 11. Storage, Stability, and Disposal
Store at 20°C to 25°C.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Bosutinib
Chemical name: 3-Quinolinecarbonitrile, 4-[(2,4-dichloro-5-methoxyphenyl)amino]-6-methoxy-
7-[3-(4-methyl-1-piperazinyl)propoxy]-, hydrate (1:1)
Molecular formula and molecular mass: C26H29Cl2N5O3•H20 (monohydrate) and 548.46 (monohydrate), equivalent to 530.46 (anhydrous)
Structural formula:
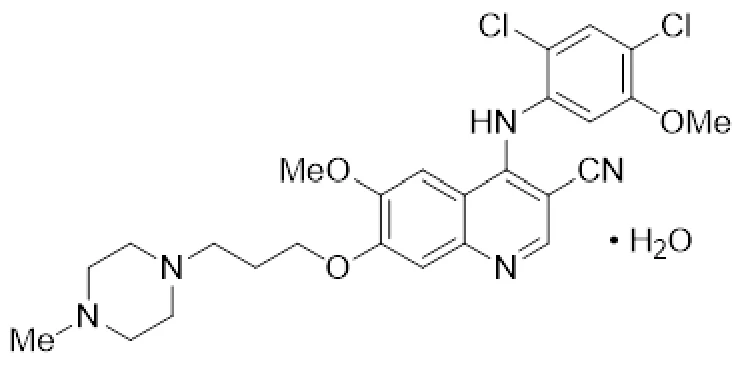
Physicochemical properties: Bosutinib monohydrate is a white to yellowish-tan powder. Bosutinib monohydrate has a pH dependent solubility across the physiological pH range. At or below pH 5, bosutinib behaves as a highly soluble compound. Above pH 5, the solubility of bosutinib reduces rapidly.
14. Clinical Trials
14.1. Clinical Trials by Indication
Newly-diagnosed CP Ph+ CML
Table 16 – Summary of patient demographics for clinical trials in Newly-diagnosed CP Ph+ CML
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
B1871053 (BFORE) | A Multicenter Phase 3 Randomized, Open-Label Study of Bosutinib versus Imatinib in Adult Patients with Newly Diagnosed Chronic Phase Chronic Myelogenous Leukemia | Bosutinib Route: Oral; Dose Regimen: 400 mg once Daily Median duration of treatment: 55.10 (0.3-60.1) months | N=268 | 52 (18 to 84) years | 57.7% M 42.3% F |
Imatinib Route: Oral; Dose Regimen: 400 mg once daily Median duration of treatment: 55.03 (0.7-56.8) months | N=268 | 53 (19 to 84) years | 56% M 44% F |
A 2-arm, Phase 3, open-label, multicenter superiority trial was conducted to investigate the efficacy and safety of bosutinib 400 mg once daily alone compared with imatinib 400 mg once daily alone in adult patients with newly-diagnosed CP Ph+ CML (BFORE Trial, Study B1871053). The trial randomized 536 patients (268 in each treatment group) with Ph+ or Ph- newly-diagnosed CP CML (intent-to-treat [ITT] population) including 487 patients with Ph+ CML harboring b2a2 and/or b3a2 transcripts at baseline, and baseline BCR-ABL copies >0 (modified intent-to-treat [mITT] population).
The mITT population excluded 12 Ph– patients (i.e., 0 out of ≥10–99 metaphases at baseline; 6 in each treatment group), 8 patients with atypical transcripts (3 treated with bosutinib and 5 treated with imatinib), and 31 patients with unknown Ph status (13 treated with bosutinib and 18 treated with imatinib, including 2 imatinib-treated patients also listed as having atypical transcripts).
The primary efficacy endpoint was the proportion of patients demonstrating major molecular response (MMR) at 12 months (48 weeks) in the bosutinib arm compared with that in the imatinib arm in the mITT population. MMR was defined as ≤0.1% BCR ABL (corresponding to ≥3 log reduction from standardized baseline) with a minimum of 3000 ABL transcripts as assessed by the central laboratory. The secondary efficacy endpoints included MMR by 18 months (72 weeks), duration of MMR, complete cytogenetic response (CCyR) by 12 months, duration of CCyR, event free survival (EFS), and overall survival (OS). CCyR by 12 months, was defined as the absence of Ph+ metaphases in chromosome banding analysis of ≥20 metaphases derived from bone marrow aspirate or MMR if an adequate cytogenetic assessment was unavailable. The p values for endpoints other than MMR at 12 months, CCyR by 12 months, and MMR by 18 months have not been adjusted for multiple comparisons.
Baseline characteristics for the mITT population were well balanced between the 2 treatment groups with respect to age (median age was 52 years for the bosutinib group and 53 years for the imatinib group with 19.5% and 17.4% of patients 65 years of age or older, respectively); gender (women 42.3% and 44.0%, respectively); and race (Caucasian 78.0% and 77.6%, Asian 12.2% and 12.4%, Black or African American 4.1% and 4.1% and Other 5.7% and 5.4%, respectively, and 1 unknown in the imatinib group); and Sokal risk score (low risk 35.0% and 39.4%, intermediate risk 43.5% and 38.2%, high risk 21.5% and 22.4%, respectively). Baseline characteristics were similar in the ITT population.
After 60 months of follow up in the mITT population, 60.2% of patients treated with bosutinib (N=246) and 59.8% of patients treated with imatinib (N=239) were still receiving first-line treatment.
After 60 months of follow up in the mITT population, discontinuations due to disease progression to accelerated or blast phase CML for bosutinib-treated patients were 0.8% (2 patients) compared to 1.7% (4 patients) for imatinib-treated patients. Six (2.4%) bosutinib patients and 7 (2.9%) imatinib patients had CML that transformed to AP CML or BP CML while on treatment in the mITT population. No additional transformations occurred in the ITT population.
After 60 months of follow-up in the mITT population, discontinuations due to suboptimal response or treatment failure as assessed by the investigator occurred for 5.3% of patients in the bosutinib-treated group compared to 15.5% of patients in the imatinib-treated group.
Twelve (4.9%) patients on bosutinib and 14 (5.8%) patients on imatinib died while on study. There were 3 and 4 on-treatment deaths (up to 28 days after last dose of study drug) in the bosutinib and imatinib groups respectively. On-treatment deaths in the bosutinib arm occurred due to acute cardiac failure, myocardial ischemia, and renal failure (n=1 each). On-treatment deaths in the imatinib arm occurred due to pneumonia, sepsis, disease progression, and cerebrovascular accident (n=1 each). There were no treatment-related deaths, as assessed by the investigator, in the bosutinib group and 1 treatment-related death of sepsis in the imatinib group in both the mITT and ITT populations.
The efficacy results are summarized in Table 17
| Table 17 – Summary of MMR at Months 12 and 18, MMR by Month 18 and 60 and CCyR by Month 12, by Treatment Group in the mITT Population | ||||||
|---|---|---|---|---|---|---|
| Response | Bosutinib (N=246) | Imatinib (N=241) | Odds ratio (95% CI)a | |||
MMR at Month 12 (95% CI) | 116 (47.2)a (40.9, 53.4) | 89 (36.9) (30.8, 43.0) | 1.55 (1.07, 2.23) | |||
| 2-sided p-value | 0.0200b | |||||
MMR at Month 18, n (%) (95% CI) | 140 (56.9) (50.7, 63.1) | 115 (47.7) (41.4, 54.0) | 1.45 (1.02, 2.07) | |||
| 2-sided p-value | 0.0416c | |||||
MMR by Month 18, n (%) (95% CI) | 150 (61.0) (54.9, 67.1) | 127 (52.7) (46.4, 59.0) | 1.42 (0.99, 2.04) | |||
| 2-sided p-value | 0.0606c | |||||
MMR by Month 60, n (%) (95% CI) | 182 (74.0%) (68.5, 79.5) | 158 (65.6%) (59.6,71.6) | 1.52 (1.02, 2.25) | |||
CCyR by Month 12, n (%) (95% CI) | 190 (77.2)b (72.0, 82.5) | 160 (66.4) (60.4, 72.4) | 1.74 (1.16, 2.61) | |||
| 2-sided p-value | 0.0075b | |||||
Note: MMR was defined as ≤ 0.1% BCR-ABL/ABL ratio by international scale (corresponding to ≥ 3 log reduction from standardised baseline) with a minimum of 3,000 ABL transcripts assessed by the central laboratory. Complete cytogenetic response was defined as the absence of Ph+ metaphases in chromosome banding analysis of ≥ 20 metaphases derived from bone marrow aspirate or MMR if an adequate cytogenetic assessment was unavailable. Abbreviations: BCR-ABL=breakpoint cluster; CI=confidence interval; CMH=Cochran Mantel Haenszel; CCyR=complete cytogenetic response; mITT=modified intent-to-treat; MMR=major molecular response; N/n=number of patients; Ph+=Philadelphia chromosome-positive. a Adjusted for geographical region and Sokal score at randomization. b Statistically significant comparison at the pre-specified significance level; based on CMH test stratified by Geographical region and Sokal score at randomization. c Based on CMH test stratified by geographical region and Sokal score at randomization. | ||||||
The MMR rates at Month 12, at Month 18, and by Month 60 for all randomised subjects (ITT population) was consistent with the mITT population; odds ratio of 1.57 [95% CI: 1.10, 2.22] and 1.50 [95% CI: 1.07, 2.10] and 1.57 [95% CI: 1.08, 2.28], respectively. After 60 months of follow-up, the median time to MMR in responders was 9.0 months for bosutinib and 11.6 months for imatinib
MMR rates by 60 months of follow-up across Sokal risk subgroups are summarised in Table 18.
| Table 18 – Summary of MMR by Month 60 by Sokal Risk Score in the mITT population | ||
|---|---|---|
| Response | Bosutinib | Imatinib |
Low Sokal risk MMR, n (%) (95% CI) | N=86 67 (77.9) (69.1, 86.7) | N=95 68 (71.6) (62.5,80.6) |
Intermediate Sokal risk MMR, n (%) (95% CI) | N=107 79 (73.8) (65.5,82.2) | N=92 62 (67.4) (57.8,77.0) |
High Sokal risk MMR, n (%) (95% CI) | N=53 36 (67.9) (55.4,80.5) | N=54 28 (51.9) (38.5,65.2) |
Note: Percentages were based on number of patients in each treatment group. MMR was defined as ≤ 0.1% BCR-ABL/ABL ratio on international scale (corresponding to ≥ 3 log reduction from standardized baseline) with a minimum of 3,000 ABL transcripts assessed by the central laboratory. Abbreviations: BCR-ABL=breakpoint cluster region-Abelson; CI=confidence interval; mITT=modified intent-to-treat; MMR=major molecular response; N/n=number of patients. | ||
After 60 months of follow-up, the Kaplan-Meier estimates of overall survival (OS) at Month 60 for bosutinib and imatinib patients in the mITT population were 94.9% (95% CI: 91.1%, 97.0%) and 94.0% (95% CI: 90.1%, 96.4%), respectively.
Chronic Phase (CP), Accelerated Phase (AP) and Blast Phase (BP) Ph+CML and Ph+ALL Patients Resistant or Intolerant to Previous TKIs Treatment
Table 19 – Summary of patient demographics for clinical trials in Chronic Phase (CP), Accelerated Phase (AP) and Blast Phase (BP) Ph+CML and Ph+ALL Patients Resistant or Intolerant to Previous TKIs Treatment
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| B1871006 | A multicenter Phase 1/2 single-arm Study open-label, to evaluate Bosutinib in Philadelphia Chromosome Positive Leukemias | Bosutinib Route: Oral; Dose Regimen Part 1: Starting dose 400 mg/500 mg/600 mg oral, daily dosing in the dose escalation component Part 2: 500 mg once daily Median duration of therapy 11.13 (0.03 to 170.49) months | N=570 | 53 (18 -91) years | 52.6% M 47.4% F |
A single-arm, Phase 1/2 open-label, multicenter study was conducted to evaluate the efficacy and safety of BOSULIF 500 mg once daily in patients with imatinib-resistant or -intolerant CML with separate cohorts for chronic, accelerated, and blast phase disease treated with imatinib only or imatinib followed by dasatinib and/or nilotinib (Study B1871006, NCT00261846). The definition of imatinib resistance included failure to achieve or maintain any hematologic improvement within 4 weeks, or achieve a complete hematologic response (CHR) by 3 months, cytogenetic response (CyR) by 6 months or major cytogenetic response (MCyR) by 12 months or progression of disease after a previous cytogenetic or hematologic response, or presence of a genetic mutation in the BCR-Abl gene associated with imatinib resistance. Imatinib intolerance was defined as inability to tolerate imatinib due to toxicity, or progression on imatinib and inability to receive a higher dose due to toxicity. The definitions of resistance and intolerance to both dasatinib and nilotinib were similar to those for imatinib.
There were 570 patients with Ph+ leukemias treated with bosutinib in this trial including CP CML patients previously treated with only 1 prior TKI (imatinib), CP CML patients previously treated with imatinib and at least 1 additional TKI (dasatinib and/or nilotinib), CML patients in accelerated or blast phase previously treated with at least 1 TKI (imatinib) and patients with Ph+ ALL previously treated with at least 1 TKI (imatinib). Among all treated patients, 52.6% of patients were male, 65.8% were White, and 20.9% were age 65 years or older.
The primary objective of the study was to determine the Major Cytogenetic response (MCyR) rate at Week 24 in patients with imatinib-resistant CP CML who have had imatinib exposure only (primary endpoint analysis cohort).
Other efficacy endpoints include the cumulative cytogenetic and molecular response rates, time to and duration of cytogenetic and molecular responses, response in baseline mutations, transformation to AP/BP, progression free survival and OS for all cohorts. For patients with AP and BP CML previously treated with at least 1 prior TKI (imatinib), additional secondary endpoints were cumulative haematological responses.
Patients who were still receiving bosutinib at the end of the Phase 1/2 study and were benefiting from bosutinib treatment as judged by the investigator, as well as those patients who had already discontinued bosutinib as part of the Phase 1/2 study and were in long-term follow-up for survival or had completed the Phase 1/2 study, were eligible for enrollment into the extension study. Each patient remained in the extension study, either on bosutinib treatment or in long term survival follow up, until the last patient reached 10 years of follow up, as calculated from the date of his/her first dose of bosutinib administered in the Phase 1/2 study.
Extension study efficacy endpoints included duration of cytogenetic and molecular responses, transformation to AP/BP, progression free survival, and OS.
The efficacy analyses included data from this completed extension study.
Table 20 presents the duration of follow-up and treatment with BOSULIF in the 10-year extension study.
| Table 20 – Duration of Follow-up and Treatment with BOSULIF | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| CP CML | AP CML N=79 | BP CML N=64 | ||||||||||||
Previously Treated with IM N=284 | IM + (D or NI) N=119 | |||||||||||||
| Minimum Time to Database Snapshot, months | 120 | 120 | 120 | 120 | ||||||||||
| Median Follow Up, months (range) | 53.7 (0.5-171.6)) | 34.1 (0.2-165.2) | 28.3 (0.3-158.8) | 10.4 (0.4-79.9) | ||||||||||
| Median Duration of Treatment, months (range) | 25.6 (0.2-170.5) | 8.6 (0.2-164.3) | 10.2 (0.1-156.15) | 2.8 (0.03-71.38) | ||||||||||
Percentage of patients still on treatment 5 years 10 years | 40.5 19.4 | 20.2 7.6 | 12.7 7.6 | 3.1 0 | ||||||||||
Abbreviations: D=dasatinib, IM=imatinib, NI=nilotinib,
CP CML previously treated with imatinib only
Table 21 – Demographic and Baseline Characteristics of Ph+ CP CML Patients Previously Treated with imatinib only
Characteristic
Imatinib Resistant
N=195
Imatinib Intolerant
N=89
Total
N=284
Sex, n (%)
Female
82 (42.1)
53 (59.6)
135 (47.5)
Male
113 (57.9)
36 (40.4)
149 (52.5)
Race, n (%)
Asia n
40 (20.5)
21 (23.6)
61 (21.5)
11 (5.6)
5 (5.6)
16 (5.6)
Othera
13 (6.7)
7 (7.9)
20 (7.0)
White
131 (67.2)
55 (61.8)
186 (65.5)
Age category, n (%)
Age <65 years
156 (80.0)
61 (68.5)
217 (76.4)
Age ≥65 years
39 (20.0)
28 (31.5)
67 (23.6)
ECOG Performance Status, n (%)
0
151 (77.4)
66 (74.2)
217 (76.4)
1
44 (22.6)
21 (23.6)
65 (22.9)
2
0
1 (1.1)
1 (0.4)
Missing
0
1 (1.1)
1 (0.4)
Number of prior therapies,b n (%)
1
118 (60.5)
66 (74.2)
184 (64.8)
2
77 (39.5)
23 (25.8)
100 (35.2)
Prior interferon therapy, n (%)
No
118 (60.5)
66 (74.2)
184 (64.8)
Yes
77 (39.5)
23 (25.8)
100 (35.2)
Prior imatinib therapy, n (%)
Intolerant
0
89 (100)
89 (31.3)
Resistant
195 (100)
0
195 (68.7)
Prior stem cell transplant, n (%)
Table 21 – Demographic and Baseline Characteristics of Ph+ CP CML Patients Previously Treated with imatinib only
Characteristic
Imatinib Resistant
N=195
Imatinib Intolerant
N=89
Total
N=284
No
189 (96.9)
87 (97.8)
276 (97.2)
Yes
6 (3.1)
2 (2.2)
8 (2.8)
Reason for stopping imatinib, n (%)
Adverse event (intolerance)
0
88 (98.9)
88 (31.0)
Disease progression/Inadequate response
195 (100)
0
195 (68.7)
Otherc
0
1 (1.1)
1 (0.4)
Abbreviations: ECOG=Eastern Cooperative Oncology Group; N/n=number of subjects
(a) Race Other: American Indian or Alaska Native-1, Eurasian-1, Hispanic-15, Mestizo-2, Mixed Race-1, North-African-1.
(b) If a subject received more than 1 treatment regimen with imatinib, dasatinib, nilotinib or interferon the subject is only counted once for the respective treatment.
(c) Other reason for stopping imatinib: Subject wanted to get pregnant.
Of the 284 patients with CP CML previously treated with imatinib only, 262 patients were evaluable for cytogenetic response and 197 for molecular response.
The efficacy results in the CP CML patients previously treated with imatinib with a minimum follow-up of 120 months are in Table 22 MCyR was achieved in 66 of 186 evaluable patients (35.7%; 95% CI: [28.8, 43.1]) at Week 24 in the primary endpoint analysis cohort (CP CML imatinib-resistant).
Table 22 – Efficacy Results in Ph+ CP CML Patients Previously Treated with Imatinib Only
Imatinib Resistant (n= 195)
Imatinib Intolerantb (n=89)
Total (N=284)
At Week 24
MCyR
(95% CI)a
35.7%
(28.8,43.1)
30.0%)
(20.3,41.3)
34.0%
(28.3,40.1)
CCyR
(95% CI)a
24.2%
(18.2,31.1)
25.0%
(16.0,35.9)
24.4%
(19.4, 30.1)
Cumulativec
MCyRa
(95% CI)a
59.3%
(51.8,66.5)
61.3%
(49.7,71.9)
59.9%
(53.7,65.9)
CCyRa
(95% CI)a
48.4%
(40.9, 55.9)
52.5%
(41.0, 63.8)
49.6%
(43.4, 55.8)
MMRa
(95% CI)a
45.7%
(36.8, 54.7)
35.7%
(24.6, 48.1)
42.1%
(35.1,49.4)
Time to MCyR for responders only, median (range), weeks
-
-
12.3 (12.1,12.7)
Duration of MCyR
KM at year 5, (95% CI)
KM at year 10, (95% CI)
Median weeks (95% CI)
66.6 (57.2,76.0)
61.4 (51.0,71.7)
N/R
80.2 (67.6,92.7)
74.4 (58.5,90.3)
N/R
70.7 (63.1,78.3)
65.3 (56.6,74.0)
N/R
Time to CCyR for responders only, median (range), weeks
24.1(7.7,240.6)
12.6 (11.1,120.0)
24.0 (7.7,240.6)
Duration of CCyR
KM at year 5, (95% CI)
KM at year 10, (95% CI)
Median weeks (95% CI)
70.1 (60.0,80.3)
63.1 (51.9,74.4)
N/R
68.9 (53.4,84.4)
64.0 (46.8, 81.1)
N/R
69.7 (61.3,78.2)
63.4 (54.0,72.8)
N/R
Time to MMR for responders only, median (range), weeks
36.1 (3.1,367.1)
12.3 (4.4,210.0)
35.6 (3.1,367.1)
Duration of MMR
KM at year 5, (95% CI)
KM at year 10, (95% CI)
Median, weeks (95% CI)
67.8 (55.5,80.1)
54.8 (39.2,70.4)
N/R
89.8 (76.2,100.0)
89.8 (76.2,100.0)
N/R
74.1 (64.2,83.9)
63.4 (50.2,76.6)
N/R
Transformation to AP/BP on treatment, n (%)
(95% CI)
13 (6.7)
(3.6,11.1)
2 (2.2)
(0.3,7.9)
15 (5.4)
(3.0,8.6)
Progression free survivald
KM at year 5,
(95% CI)
69.4%
(61.9, 76.9)
81.0%
(70.1, 92.0)
72.5%
(66.2, 78.8)
KM at year 10,
(95% CI)
58.2%
(49.1, 67.3)
72.0%
(56.6, 87.3)
61.8%
(53.9, 69.7)
Median weeks
(95% CI)
N/R
N/R
N/R
Overall survivald
KM at year 5,
(95% CI)
80.8%
(74.7, 86.8)
89.6%
(82.2, 97.1)
83.5%
(78.7, 88.3)
KM at year 10,
(95% CI)
71.0%
(62.7, 79.4)
73.4
(60.1, 86.6)
71.5%
(64.4, 78.7)
Median weeks
(95% CI)
N/R
N/R
N/R
Abbreviations: MCyR=major cytogenetic response, CCyR=complete cytogenetic response, KM= Kaplan-Meier estimate, MMR=major molecular response, N/R= not reached at time of data cut-off
aCytogenetic/molecular response results are presented for the respective evaluable populations (imatinib-resistant n=182/127; imatinib-intolerant n=80/70; Total n = 262/197). bExploratory cohort
cThese are cumulative rates of response representing minimum follow up of 120 months
Unconfirmed response definition: a response which may or may not be confirmed at least 28 days later
Cytogenetic response criteria: Major Cytogenetic response included Complete (0% Ph+ metaphases) or partial (1%-35%) cytogenetic responses. Cytogenetic responses were based on the percentage of Ph-positive metaphases among ≥20 metaphase cells in each bone marrow sample. Fluorescent in situ hybridization analysis (≥200 cells) could be used for post-baseline cytogenetic assessments if ≥20 metaphases were not available.
Molecular response criteria: In the Phase 1/2 Study, MMR was defined as ≤0.1% BCR-ABL transcripts as
assessed by a central laboratory (not on the international scale). In the extension study, responders had MMR denoted on the case report form as assessed by a local laboratory.
d Including patients (N) who received at least one dose of bosutinib.
CP CML previously treated with imatinib and another TKI
A total of 119 patients with CP CML who were imatinib-resistant or intolerant and received at least 1 additional prior TKI therapy (i.e. dasatinib and/or nilotinib) were enrolled and treated. Patients had a median age of 56 years (range 20 to 79 years), most were <65 years of age (77%), and slightly less than half (45%) of patients were male. Most patients were white (73%) or Asian (13%). Patients had an ECOG performance score of 0 (71%) or 1 (28%) at baseline (data was missing for 1 patient). Slightly more than half of patients (55%) had received prior interferon therapy and 8% had undergone a stem cell transplant. The most common reasons for stopping imatinib treatment were disease progression (70%) and intolerance (30%). Of these 119 patients, 112 patients were evaluable for cytogenetic response and 107 for molecular response.
Among the 119 patients receiving BOSULIF, all patients received prior therapy with imatinib (resistant or intolerant), 38 patients were dasatinib-resistant, 50 were dasatinib-intolerant, and 26 were nilotinib resistant, and 1 patient was nilotinib intolerant. There were 4 patients who received BOSULIF following all previous TKI treatments: 1 was resistant to all 3 prior TKI therapies (imatinib, dasatinib, nilotinib), 1 was intolerant of all 3 prior TKI therapies, 1 was resistant to imatinib and nilotinib and intolerant to dasatinib, and 1 was intolerant to imatinib and nilotinib and resistant to dasatinib.
The efficacy results of these 119 patients with a minimum follow-up of 120 months are summarized in Table 23.
Table 23 – Efficacy Results in Ph+ CP CML Patients Previously Treated with Imatinib and Dasatinib and/or Nilotinib
IM + (NI + D) or IM + NI Intolerantb (n=5)
IM + D Resistantb
(n=38)
IM +
D Intolerantb
(n=50)
IM + NI Resistantb
(n=26)
Total
(N=119)
By Week 24
MCyR
(95% CI)a
40.0%
(5.3, 85.3)
30.6%
(16.4, 48.1)
20.0% (9.6, 34.6)
26.9%
(11.6, 47.8)
25.9%
(18.1, 35.0)
CCyR
(95% CI)a
20.0%
(0.5, 71.6)
8.3%
(1.8, 22.5)
17.8%
(8.0, 32.1)
11.5%
(2.5, 30.2)
13.4%
(7.7, 21.1)
Cumulativec
MCyR
(95% CI)a
40.0%
(5.3, 85.3)
38.9%
(23.1, 56.5)
42.2%
(27.7, 57.9)
38.5%
(20.2, 59.4)
40.2%
(31.0, 49.9)
CCyR
(95% CI)a
40.0%
(5.3, 85.3)
22.2%
(10.1, 39.2)
40.0%
(25.7, 55.7)
30.8%
(14.3, 51.8)
32.1%
(23.6, 41.6)
MMR
(95% CI)a
25.0%
(0.6, 80.6)
5.6%
(0.7, 18.7)
25.0%
(13.6, 39.6)
21.1%
(6.1, 45.6)
17.8% (11.0,26.3)
Time to MCyR for responders only, median (range), weeks
18.0
(12.0, 24.0)
12.1
(3.9, 550.6)
12.3
(11.1, 335.3)
13.3
(11.1, 47.7)
12.3 (3.9, 550.6)
Duration of MCyR
KM at 5 years (95% CI)
KM at 10 years (95% CI)
Median weeks
(95% CI)
N/R
N/R
N/R
(57.5, N/R)
43.3
(15.2, 71.3)
43.3
(15.2, 71.3)
47.3
(18.0, N/R)
79.9
(59.1, 100.0)
58.2
(28.3, 88.1)
N/R
(286.6, N/R)
77.8
(50.6, 100.0)
77.8
(50.6, 100.0)
N/R
66.6
(51.5, 81.7)
55.3
(36.3, 74.4)
N/R
(286.6, N/R)
Time to CCyR for responders only, median (range), weeks
30.1
(24.0, 36.1)
47.6
(11.7, 168.0)
12.3
(11.6, 216.0)
41.9
(12.0, 108.9)
24.0
(11.6, 216.0)
Duration of CCyR
KM at 5 years (95% CI)
KM at 10 years (95% CI)
Median weeks
(95% CI)
N/R
N/R
N/R
16.7
(0.0, 46.5)
16.7
(0.0, 46.5)
24.1
(12.0, 36.1)
65.8
(41.1, 90.6)
47.0
(18.8, 75.2)
365.3
(60.0, N/R)
62.5
(29.0, 96.0)
46.9
(10.3, 83.4)
252.0
(12.0, N/R)
54.4
(36.7, 72.1)
40.8
(22.0, 59.6)
252.0
(24.0, N/R)
Time to MMR for responders only, median (range), weeks
24.0
(24.0, 24.0)
11.9
(11.7, 12.1)
11.9
(4.0, 75.0)
70.6
(12.4, 171.7)
12.4
(4.0, 171.1)
Table 23 – Efficacy Results in Ph+ CP CML Patients Previously Treated with Imatinib and Dasatinib and/or Nilotinib
IM + (NI + D) or IM + NI Intolerantb (n=5)
IM + D Resistantb
(n=38)
IM +
D Intolerantb
(n=50)
IM + NI Resistantb
(n=26)
Total
(N=119)
Duration of MMR
KM at 5 years (95% CI)
KM at 10 years (95% CI)
Median weeks
(95% CI)
100.0
(100.0, 100.0)
N/R
N/R
50.0
(0.0, 100.0)
50.0
(0.0, 100.0)
N/R
58.2
(25.1, 91.2)
58.2
(25.1, 91.2)
N/R
100.0
(100.0, 100.0)
100.0
(100.0, 100.0)
N/R
70.0
(47.5,92.5)
70.0
(47.5, 92.5)
N/R
Progression free survivald
KM at year 5, (95% CI)
53.3%
(4.7, 100.0)
65.0%
(45.5, 84.6)
73.7%
(58.3, 89.0)
55.6%
(32.7, 78.4)
65.1%
(54.2, 76.0)
KM at year 10, (95% CI)
Median weeks
(95% CI)
N/R
N/R
65.0%
(45.5, 84.6)
N/R
50.5%
(26.2, 74.8)
N/R
55.6%
(32.7, 78.4)
N/R
53.4%
(38.2, 68.6)
N/R
Overall survivald
KM at year 5, (95% CI)
80.0%
(44.9, 100.0)
66.2%
(47.9, 84.6)
73.1%
(58.9, 87.4)
87.3%
(73.7, 100.0)
74.1%
(64.8, 83.4)
KM at year 10, (95% CI)
Median weeks
(95% CI)
N/R
N/R
49.7%
(18.4, 81.0)
100.1
(34.4, N/R)
63.9%
(46.6, 81.2)
N/R
67.9%
(41.9, 93.8)
N/R
60.4%
(47.2, 73.7)
N/R
Abbreviations: CI=confidence interval, D=dasatinib, IM=imatinib, NA=not applicable, NI=nilotinib, MCyR=major cytogenetic response, CCyR = complete cytogenetic response, MMR= major molecular response,
N/R= not reached at time of data cut-off a. Cytogenetic/molecular response results are presented for the respective evaluable populations (IM + (NI + D) or IM + NI Intolerant n=5/4; IM + D resistant n=36/36; IM + D intolerant n=46/48; IM + NI resistant n=26/19; Total n=112/107). bExploratory cohort
cThese are cumulative rates of response representing minimum follow up of 120 months
Unconfirmed response definition: a response which may or may not be confirmed at least 28 days later d Including patients (N) who received at least one dose of bosutinib
Of the 119 patients in the CP CML population that were previously treated with imatinib and another TKI, 5 patients [4.2% (95% CI: 1.4, 9.5)] had confirmed disease transformation to AP while on treatment with BOSULIF; no patients transformed to BP.
Advanced Phase CML
A total of 143 advanced phase leukemia patients were treated with BOSULIF, including 79 patients with AP CML and 64 with BP CML. In the AP CML cohort, the median age was 51.0 years (range 18.0 to 83.0 years), 90% were <65 years of age, and a little more than half (56%) of patients were male. Most patients were white (58%) or Asian (28%). Most patients had an ECOG performance score of 0 (57%) or 1 (41%) at baseline. Half of patients (52%) had received prior interferon therapy, 32% had received prior dasatinib therapy, 19% had received prior nilotinib therapy, and 9% had a prior stem cell transplant. The primary reasons for stopping imatinib were disease progression (86%) and AE (14%). Of the 79 AP CML patients, 72 patients were evaluable for hematologic and cytogenetic response and 54 were evaluable for molecular response.
In the BP CML cohort, the median age was 47.0 years (range 19.0 to 82.0 years), 84% were <65 years of age, and a little more than half (66%) of patients were male. Most patients were white (58%) or Asian (23%). Patients had an ECOG performance score of 0 (34%), 1 (45%), or 2 (20%) at baseline. Thirty-one percent (31%) had received prior interferon therapy, 34% had received prior dasatinib therapy, 17% had received prior nilotinib therapy, and 6% had a prior stem cell transplant. The primary reasons for stopping imatinib were disease progression (84%) and AE (16%). Of the 64 BP CML patients, 60 patients were evaluable for hematologic response, 54 patients were evaluable for cytogenetic response, and 48 patients were evaluable for molecular response.
The efficacy results in the advanced leukemia patients at a minimum follow-up of 120 months are summarized in Table 24.
Table 24 – Efficacy Results in Accelerated Phase and Blast Phase Patients Treated with at Least Imatinib
AP
IM Onlyb
(n=49)
AP
Multi TKIb
(n= 30)
AP
Total
(N=79)
BP
IM Onlyb
(n= 36)
BP
Multi TKIb
(n= 28)
BP
Total
(N= 64)
OHR
Cumulative by Week 48
(95% CI)a
67.4%
(51.5,80.9)
41.4%
(23.5,61.1)
56.9%
(44.7,68.6)
38.2%
(22.2,56.4)
15.4%
(4.4,34.9)
28.3%
(17.5,41.4)
Duration of OHR
KM at 5 years (95% CI)
KM at 10 years (95% CI)
Median weeks
(95% CI)
37.6
(14.6, 60.6)
37.6
(14.6, 60.6)
119,9
(56.0,N/R)
66.7
(35.1, 98.2)
66.7
(35.1, 98.2)
N/R
46.2
(26.6,65.9)
46.2
(26.6,65.9)
207.0
(63.1,N/R)
12.3
(0.0, 34.3)
N/R
30.9
(28.9, 54.6)
N/R
N/R
48.0
(24.0, N/R)
19.0
(0.0, 41.7)
N/R
32.0 (29.0,54.6)
Cumulativec
MCyR
(95% CI)a
47.8%
(32.9,63.1)
26.9%)
(11.6,47.8)
40.3%
(28.9,52.5)
50.0%
(31.3,68.7)
20.8%
(7.1,42.2)
37.0%
(24.3,51.3)
CCyRc
(95% CI)a
34.8%
(21.4,50.3)
23.1%
(9.0,43.7)
30.6%
(20.2,42.5)
36.7%
(19.9,56.1)
16.7%
(4.7,37.4)
27.8%
(16.5,41.6)
MMRc
(95% CI)a
26.9%
(11.6, 47.8)
7.1%
(0.9, 23.5)
16.7% (7.9,29.3)
13.0%
(2.8, 33.6)
8.0%
(1.0, 26.0)
10.4% (3.5,22.7)
Duration of MCyR ,
39.8
(16.3, 63.4)
39.8
(16.3, 63.4)
84.0
42.9
(6.2, 79.5)
42.9
(6.2, 79.5)
24.0
40.8
(20.9, 60.7)
40.8
(20.9, 60.7)
84.0
21.7
(0.0, 48.1)
N/R
29.1
N/R
N/R
34.3
21.2
(0.1, 42.3)
N/R
29.1
KM at 5 years (95% CI)
KM at 10 years (95% CI)
median weeks (95% CI)
(47.3, N/R)
(13.4,N/R)
(24.0, N/R)
26.9, 29.6)
(4.0, N/R)
(11.9, 38.3)
Time to MCyR for responders only, median weeks (range)
12.0
(3.9, 42.0)
23.6
4.0, 144.7)
12.0
(3.9, 144.7)
8.4
(3.9, 25.1)
7.0
(4.1, 12.3)
8.2
(3.9, 25.1)
Duration of CCyR
KM at 5 years (95% CI)
KM at 10 years (95% CI)
median weeks (95% CI)
35.7
(10.6, 60.8)
35.7
(10.6, 60.8)
59.8
(36.1, N/R)
50.0
(10.0, 90.0)
50
(10.0, 90.0)
-
(16.0, N/R)
40.0
(18.5, 61.5)
40.0
(18.5, 61.5)
72.0
(36.1, N/R)
23.9
(0.0, -)
N/R
23.6
(16.9, N/R)
N/R
N/R
10.6
(4.0, N/R)
24.9
(09, 48.9)
N/R
20.0
(9.1, 29.6)
Time to CCyR for responders only, median weeks (range),
23.9
(4.1, 84.1)
23.6
(12.0, 120.0)
23.8
(4.1, 120.0)
8.9
(3.9, 25.1)
5.9
(4.1, 12.1)
8.43
(3.9, 25.1)
Duration of MMR,
KM at 5 years (95% CI)
KM at 10 years (95% CI)
median weeks (95% CI)
57.1
(20.5, 93.8)
57.1
(20.5, 93.8)
N/R
100.0
(100.0, 100.0)
N/R
N/R
66.7
(35.9, 97.5)
66.7
(35.9, 97.5)
N/R
N/R
N/R
N/R
50.0
(0.0, 100.0)
N/R
N/R
60.0
(17.1, 100.0)
N/R
N/R
Time to MMR for responders only, median weeks (range),
36.1
(22.9, 144.1)
30.1
(12.1, 48.1)
36.1
(12.1, 144.1)
11.7
(3.9, 168.9)
4.4
(4.1, 4.7)
4.7
(3.9, 168.9)
Transformation from AP to BP on treatment,
n (%)
(95% CI)
3 (3.8)
(0.8,10.7)
Progression Free Survivald
K-M at year 5
(95% CI)
33.2%
(16.2, 50.2)
46.4%
(19.5, 73.3)
37.4%
(22.9, 51.9)
8.1%
(0.0, 22.0)
NR
8.0%
(0.0, 17.9)
K-M at year 10
(95% CI)
33.2%
(16.2, 50.2)
46.4%
(19.5, 73.3)
37.4%
(22.9, 51.9)
N/R
N/R
N/R
Median months
(95% CI)
20.4
(11.8, N/R)
35.4
(14.6, N/R)
22.1
(14.6, N/R)
7.9
(3.9, 10.1)
1.8
(0.9, 5.5)
4.4
(3.2, 8.5)
Overall Survivald
K-M at year 5
(95% CI)
66.4%
(52.1, 80.7)
45.1%
(25.6, 64.6)
58.5%
(46.9, 70.2)
27.6%
(2.9, 52.2)
16.7%
(2.4, 30.9))
22.5%
(7.1, 37.9)
K-M at year 10
(95% CI)
59.7%
(41.9, 77.6)
36.1%
(13.8, 58.3)
50.7%
(36.5, 65.0)
27.6%
(2.9, 52.2)
--
22.5%
(7.1, 37.9)
Median months
(95% CI)
N/R
33.4
(14.6, N/R)
N/R
11.2
(9.4, N/R)
8.9
(4.0, 17.4)
10.9
(8.7, 19.7)
Abbreviations: OHR=overall hematologic response, MCyR=major cytogenetic response, CCyR = complete cytogenetic response, MMR= major molecular response, NR= not reached with minimum follow-up aHematologic, cytogenetic, and molecular response results are presented for the evaluable population (AP IM Only/AP Multi TKI/AP Total n=43/29/72 for hematologic, n=46/26/72 for cytogenetic, and n=26/28/54 for molecular; BP IM Only/BP Multi TKI/BP Total n=34/26/60 for hematologic, n=30/24/54 for cytogenetic, and n=23/25/48 for molecular). N/R= not reached at time of data cut-off
bExploratory cohort
cThese are cumulative rates of response representing minimum follow up of 120 months
Confirmed hematologic response definition: two consecutive responses at least 28 days apart.
Unconfirmed cytogenetic response definition: a response which may or may not be confirmed at least 28 days later
d Including patients (N) who received at least one dose of bosutinib
Overall hematologic response (OHR) = major hematologic response (complete hematologic response + no evidence of leukemia) or return to chronic phase (RCP). All responses were confirmed after 4 weeks. Complete hematologic response (CHR) for AP and BP CML: WBC ≤ institutional ULN, 100,000/mm3 ≤ platelets <450,000/mm3, absolute neutrophil count (ANC) ≥1.0 x 10⁹ /L, no blasts or promyelocytes in peripheral blood, <5% myelocytes + metamyelocytes in bone marrow, <20% basophils in peripheral blood, and no extramedullary involvement. No evidence of leukemia (NEL): Meets all other criteria for CHR except may have thrombocytopenia (20,000/mm3 < platelets <100,000/mm3) and/or neutropenia (0.5 x 10⁹ /L < ANC < 1.0 x 10⁹ /L. Return to chronic phase (RCP)=disappearance of features defining accelerated or blast phases but still in chronic phase
16. Non-Clinical Toxicology
Nonclinical Pharmacodynamics
Nonclinical studies indicate that bosutinib is a potent inhibitor of the kinase activity of BCR-ABL, the oncogenic driver of CML, and SRC kinases, which contribute to BCR-ABL signalling. Several other kinases and kinase families are inhibited by bosutinib, including STE20, EPH, TEC and AXL family kinases. Bosutinib did not inhibit PDGF receptor or c-KIT and is not a substrate for multidrug resistance transporters. Modeling studies indicate that bosutinib binds to the catalytic domain of BCR-ABL.
Bosutinib (10 µM) has affinity towards several off-target proteins including non-selective adrenergic Alpha 1 and Alpha 2 receptors, histamine H2 receptor, non-selective central muscarinic receptor, serotonin transporter receptor, Sigma non-selective receptor, sodium site 2 ion channel and neurokinin A receptor.
In vitro, bosutinib inhibits BCR-ABL signaling in CML cells. Proliferation of established CML cell lines as well as patient-derived CML progenitor cells is inhibited by bosutinib treatment. Bosutinib overcomes imatinib-resistance acquired via mutations in BCR-ABL and by BCR-ABL independent mechanisms such as overexpression of the Src family kinase LYN. Murine myeloid cells that require BCR-ABL activity to grow were inhibited by bosutinib treatment. When mutated forms of BCR-ABL resistant to imatinib were expressed in place of wild type BCR-ABL, sixteen of eighteen of these imatinib-resistant mutants of BCR-ABL were inhibited by bosutinib, with the T315I mutation as one notable exception. Oral administration of bosutinib shrinks BCR-ABL-dependent tumors growing in nude mice, and can inhibit growth of tumors dependent on expression of imatinib-resistant forms of BCR-ABL.
Nonclinical Pharmacokinetics
Bosutinib pharmacokinetics were characterized by moderate to high CL and high Vss in mice, rats, and dogs after single-dose IV administration. Absorption was moderate to rapid in all evaluated species. A higher drug plasma concentration was observed in female rats compared to males. Bosutinib was widely distributed in various rat tissues, as measured by the presence of radioactivity, but did not cross the blood brain barrier. In Caco-2 cell monolayers, bosutinib was a substrate of the efflux transporters P gp, BCRP, and MRPs. Moreover, oral absorption and bioavailability did not appear to be limited by these efflux transporters. The pharmacokinetic and toxicokinetic results showed that sufficient drug exposure was achieved with the oral route of administration for pharmacology and toxicology evaluations.
After oral administration to rats, [14C]bosutinib-derived radioactivity was well distributed to most tissues and organs, with the exception of the brain, and was consistent with a high volume of distribution for bosutinib. The uptake and retention of [14C]bosutinib-derived radioactivity was particularly prominent in the pigmented tissues such as those containing melanin. In gravid Sprague-Dawley (S-D) rats, drug-derived radioactivity was associated with the placenta, amniotic fluid and fetuses. In lactating S-D rats, drug-derived radioactivity was excreted into milk and detected in plasma from nursing pups.
Bosutinib and its N-desmethyl metabolite (M5) showed high, concentration-independent protein binding in mouse, rat, rabbit, dog, and human plasma.
Bosutinib was the predominant component in plasma of mice, rats, dogs, and humans following oral administration of unlabeled or [14C] bosutinib. In humans, the prominent circulating metabolites were oxydechlorinated bosutinib (M2) and M5. In rats, systemic exposure to M2 (administered as the metabolite) and to M5 (at the no observed adverse effect level (NOAEL), in the 6-month toxicity study) were approximately 2- to 3-fold and 2-fold higher, respectively, than that observed in humans after oral administration of a single 500 mg dose of bosutinib. Based on the exposure comparisons, coverage for M2 and M5 was achieved in the nonclinical toxicology species. The M5, M2 and M6 metabolites demonstrated only 5% inhibitory activity compared to bosutinib itself in in vitro cellular assays.
In vitro, bosutinib was predominantly metabolized by CYP3A4. In vitro, bosutinib inhibited CYP3A4/5 (non-mechanism-based inhibition) and CYP2C19 and CYP2D6 activity at concentrations that were 26- to 71-fold higher than the Cmax in humans at 500 mg once daily. Bosutinib also reduced mRNA expression of CYP3A4 and CYP1A2.
After oral administration of [14C]bosutinib to rats, dogs, and humans, the major route of excretion of radioactivity was via the feces.
General Toxicology:
Bosutinib has been evaluated in safety pharmacology, repeated dose toxicity, genotoxicity, reproductive toxicity, and phototoxicity studies. No safety pharmacology studies were conducted to specifically assess the secondary pharmacological effects of bosutinib on the gastrointestinal or renal systems. Toxicology studies indicated that effects on the gastrointestinal system were likely.
Bosutinib did not have effects on respiratory functions. In a study of the central nervous system (CNS), bosutinib-treated rats displayed decreased pupil size and impaired gait at exposures approximately > 8-fold and > 24-fold, respectively, those in CML patients receiving the 500 mg dose and > 11-fold those in CML patients receiving the 400 mg dose (comparing Cmax and based on unbound fraction in the respective species). Bosutinib activity in vitro in hERG assays suggested a potential for prolongation of cardiac ventricular repolarization (QT interval). In an oral study of bosutinib in dogs, bosutinib did not produce changes in blood pressure, abnormal atrial or ventricular arrhythmias, or prolongation of the PR, QRS, or QTc interval of the electrocardiogram (ECG) at exposures up to 3-fold the human exposure resulting from the clinical dose of 400 mg and 2-fold the human exposure resulting from the clinical dose of 500 mg (comparing Cmax and based on unbound fraction in the respective species). A delayed increase in heart rate was observed. In an intravenous study in dogs, transient increases in heart rate and decreases in blood pressure and minimal prolongation of the QTc interval (<10 msec) were observed at exposures ranging from approximately 5.8- to 20-fold the human exposure resulting from the clinical dose of 400 mg and 4.2- to 14.6-fold the human exposure resulting from the clinical exposure following the 500 mg dose. The relationship between the observed effects and drug treatment was inconclusive.
In an echocardiography study in male Sprague-Dawley rats, increased left ventricular (LV) diastolic thickness, decreased LV endocardial area and decreased mitral valve deceleration time were observed at week 4 in animals treated with daily 50 mg/kg bosutinib. Bosutinib exposure was approximately 1.2-fold the human AUC following administration of the 500 mg daily dose. These effects were not observed at subsequent time points (6 and 8 weeks) despite higher exposures (1.5-fold the human AUC at the 500 mg dose in the same animals at the 8 week time point). No apparent heart weight increase or change in left ventricular function was reported. The toxicological implications of these findings are not understood. In a subsequent echocardiography study of similar design, male and female Sprague-Dawley rats received bosutinib treatment (50 mg/kg/day) for 6 months. Bosutinib-treated female rats had slightly increased absolute (9%) and statistically significant increased relative heart weight (13%) when compared to vehicle-treated animals at biopsy. Increased end diastolic volume, diastolic posterior wall thickness, LV endocardial and epicardial areas and LV mass were observed in bosutinib-treated female rats starting at 2 months and persisting until 6 months, which is consistent with LV hypertrophy. No significant LV deficit (examined by fractional shortening or ejection fraction) was observed. No heart weight increase or LV mass increase based on echocardiography was found in bosutinib-treated male animals. Bosutinib exposure in male and female rats was approximately 0.8- and 4.4-fold clinical exposure following the 500 mg daily dose, respectively.
Following a single oral (10 mg/kg) administration of [14C] radiolabeled bosutinib to lactating Sprague-Dawley rats; radioactivity was readily excreted into breast milk as early as 0.5 h after dosing. Concentration of radioactivity in milk was up to 8-fold higher than in plasma. This allowed measurable concentrations of radioactivity to appear in the plasma of nursing pups.
Carcinogenicity:
Bosutinib was not carcinogenic in rats or transgenic mice. The rat 2-year carcinogenicity study was conducted at bosutinib doses up to 25 mg/kg in males and 15 mg/kg in females. Exposures at these doses were approximately 1.5 times (males) and 3.1 times (females) the total human population pharmacokinetic exposure (based on AUC) at the 400 mg dose and 1.2 times (males) and 2.4 times (females) exposure in humans at the 500 mg dose. The 6-month RasH2 transgenic mouse carcinogenicity study was conducted at bosutinib doses up to 60 mg/kg. The exposure at this dose was 11.9 times the total human population pharmacokinetic exposure (based on AUC) at the 400 mg dose and 9.3 times the human exposure at the 500 mg dose.
Genotoxicity:
Genotoxicity studies in bacterial in vitro systems and in mammalian in vitro and in vivo systems with and without metabolic activation did not reveal evidence for a mutagenic potential of bosutinib. Bosutinib was evaluated for its potential to induce micronucleated polychromatic erythrocytes (PCEs)
in the bone marrow of male CD-1 mice at single oral (gavage) doses of 0 (vehicle control), 500, 1000, or 2000 mg/kg. There was no bosutinib related, statistically significant increase, compared with controls, in the frequency of micronucleated PCEs in the bone marrow of male mice at bosutinib doses up to 2000 mg/kg. Therefore, bosutinib did not induce cytogenetic damage in this study at exposures as high as 47-fold the clinical exposure following the 500 mg dose.
Reproductive and Developmental Toxicology:
Impairment of Fertility
There was no evidence of adverse developmental toxicity in rats treated with bosutinib less than 10 mg/kg/day at exposures equal to 1.6 times the human exposure resulting from the clinical dose of 400 mg and 1.2-times the human exposure at the 500 mg dose (based on unbound AUC in the respective species) of bosutinib.
Based on non-clinical findings, bosutinib has the potential to impair reproductive function and fertility in humans. In a rat fertility study, fertility was slightly decreased in males at 70 mg/kg/day when mated with treatment-naive females. Females mated with treatment-naive males were observed with decreased body weight gain and food consumption, increased embryonic resorptions at ≥10 mg/kg/day (40% of human exposure), decreases in implantations, and viable embryos at 30 mg/kg/day (1.4 times the human exposure). The dose at which no adverse reproductive effects were observed in males (30 mg/kg/day) and females (3 mg/kg/day) resulted in exposures equal to 0.6 and 0.3-times, respectively, the human exposure resulting from the clinical dose of 400 mg, and 0.4 and 0.2-times, respectively, the human exposure resulting from the clinical dose of 500 mg (based on unbound AUC in the respective species).
Maternal toxicity was associated with bosutinib, when given throughout gestational days 6 to 15 to pregnant rabbits, and occurred at all doses (10, 30 and 60 mg/kg/day). With regard to fetal toxicity, bosutinib exposure during gestation caused early embryonic death at 60 mg/kg/day and decreased fetal weights at 30 and 60 mg/kg/day. Bosutinib did not cause any major malformations in fetuses. Together, the data indicate that bosutinib administration during pregnancy leads to maternal toxicity and at higher doses fetal toxicity (early fetal death).
Developmental Toxicity
In a rabbit developmental-toxicity study at a maternally-toxic dosage, there were fetal anomalies observed (fused sternebrae, and two fetuses had various visceral observations), and a slight decrease in fetal body weight. The exposure at the highest dose tested in rabbits (10 mg/kg) that did not result in adverse fetal effects was 0.9 times the human exposure resulting from the clinical dose of 400 mg and 0.7-times that in humans at the 500 mg dose (based on unbound AUC in the respective species) of bosutinib. When administered to pregnant rats on GD 19, bosutinib was highly distributed to the placenta and crossed to fetal tissues. Bosutinib was also excreted via mammary milk and was detected in the plasma of lactating rat pups.
In a rat pre- and postnatal development study, there were reduced number of pups born at ≥30 mg/kg/day, decreased postnatal survival (including increased incidence of total litter loss) and decreased growth of offspring after birth occurred at 70 mg/kg/day. The dose at which no adverse development effects were observed in offspring was a maternal dose of 10 mg/kg/day, which resulted in exposures equal to 1.3 and 1.0 times human exposure resulting from the clinical dose of 400 mg and 500 mg, respectively (based on unbound AUC in the respective species).
Phototoxicity:
Bosutinib was shown to absorb light in the UV-B and UV-A range and is distributed into the skin and uveal tract of pigmented rats. However, bosutinib did not demonstrate a potential for phototoxicity of the skin or eyes in pigmented rats exposed to bosutinib in the presence of UV radiation at bosutinib exposures at least 8 times greater than human exposure resulting from the 500 mg dose.
Repeated-dose Toxicity:
Repeated-dose toxicity studies in rats of up to 6 months in duration and in dogs of up to 9 months in duration revealed the gastrointestinal system to be the primary target organ of toxicity of bosutinib. Clinical signs of toxicity included fecal changes and were associated with decreased food consumption, and body weight loss which occasionally led to deaths or elective euthanasia. The exposure comparisons indicate that exposures that did not elicit adverse effects in the 6- and 9-month toxicity studies in rats and dogs, respectively, were similar to the human exposure resulting from a clinical dose of 400 mg or 500 mg (based on unbound AUC in the respective species). In the 2-year rat carcinogenicity study, adverse gastrointestinal effects, (mucosal collagen deposition) were at dose levels as low as 1.5 mg/kg and exposures as low as 0.08-fold those in humans at the 500 mg daily dose. There was an increased incidence and/or severity of focal/multifocal lobular atrophy of the exocrine pancreas which was accompanied by varying degrees of chronic inflammatory cell infiltrate and fibrosis at exposures in male and female rats 0.23-fold and 2.8-fold, respectively, the human exposure at 500 mg. The pancreatic effects were accompanied by acinar apoptosis in male rats at an exposure 1.4-fold the human exposure at the 500 mg dose level. Renal tubular atrophy was observed at an increased incidence, but not severity, in male and female rats at exposures 1.4- and 2.8-fold respectively, the exposure at the daily 500 mg dose. In the highest dose group, there were more early deaths and euthanasia of undetermined causes in male rats at 1.4-fold (25 mg/kg/day) the human exposure, but not in female rats at 2.8-fold (15 mg/kg/day) the human exposure at the 500 mg dose level.