


Product Monograph - Taro-Benzoyl Peroxide / Clindamycin Kit
SUMMARY PRODUCT INFORMATION
Route of
Administration
Dosage Form/Strength Clinically Relevant Nonmedicinal
Ingredients
Topical (dermal) Topical Gel:
5% benzoyl peroxide and 1%
clindamycin, as phosphate after
reconstitution by the pharmacist.
None.
For a complete listing of nonmedicinal ingredients, see DOSAGE FORMS, COMPOSITION AND PACKAGING section.
INDICATIONS AND CLINICAL USE
Taro-Benzoyl Peroxide / Clindamycin Kit (benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate)) is indicated for:
- The topical treatment of moderate acne vulgaris characterized by comedones, inflammatory papules/pustules, with or without an occasional cyst or nodule (Grade II to III1).
Taro-Benzoyl Peroxide / Clindamycin Kit contains an antibacterial ingredient, clindamycin. To reduce the risk of development of drug-resistant bacteria and maintain the effectiveness of clindamycin, Taro-Benzoyl Peroxide / Clindamycin Kit should only be used for the authorized indication and clinical use.
Taro-Benzoyl Peroxide / Clindamycin Kit is not indicated for the treatment of cystic acne (Grade IV1).
CONTRAINDICATIONS
- Patients who have a history of hypersensitivity to preparations containing clindamycin, lincomycin or any other component of the preparation. For a complete listing of the ingredients in the formulation, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section.
1 Pillsbury DM, Heaton C. Manual of Dermatology 1980.
- Patients with a history of regional enteritis, ulcerative colitis, or a history of antibiotic- associated colitis (see WARNINGS AND PRECAUTIONS).
WARNINGS AND PRECAUTIONS
General
For external (dermatological) use only. Not for ophthalmic use.
Concomitant topical acne therapy is not recommended because a possible cumulative irritancy effect may occur, especially with the use of peeling, desquamating, or abrasive agents.
Exposure to sunlight or unnecessary UV light should be minimized.
Gastrointestinal
Orally and parenterally administered clindamycin have been associated with severe colitis, which may result in patient death. Use of the topical formulation of clindamycin can result in absorption of the antibiotic from the skin surface. Diarrhea, bloody diarrhea, and colitis (including pseudomembranous colitis) have been reported with the use of topical and systemic clindamycin.
Studies indicate that a toxin produced by clostridia is a primary cause of antibiotic-associated colitis. The colitis is usually characterized by severe persistent diarrhea and severe abdominal cramps and may be associated with the passage of blood and mucus. Endoscopic examination may reveal pseudomembranous colitis. Stool culture for Clostridium difficile and stool assay for Clostridium difficile toxin may be helpful diagnostically. When significant diarrhea occurs, the drug should be discontinued. Large bowel endoscopy should be considered to establish a definitive diagnosis in cases of severe diarrhea.
Diarrhea, colitis, and pseudomembranous colitis have been observed to begin up to several weeks following cessation of oral and parenteral therapy with clindamycin.
Ophthalmologic/Mucosal/Skin
Avoid contact with eyes and mucous membranes. In the event of accidental contact with such sensitive surfaces (mucous membranes, eyes, abraded skin), rinse with large amounts of tepid tap water.
Special Populations
Pregnant Women: There are no well-controlled trials in pregnant women treated with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate). It is not known whether benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) can cause fetal harm when administered to a pregnant woman or can affect reproductive capacity. Taro-Benzoyl Peroxide / Clindamycin Kit should not be given to a pregnant woman unless the benefits to the mother clearly outweigh the possible risks to the fetus.
Nursing Women: It is not known whether benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) is excreted in human milk after topical application. However, orally and parenterally administered clindamycin has been reported to appear in breast milk. Because of the potential for serious adverse reactions in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
Pediatrics (<12 years of age): The safety and effectiveness of this product in pediatric patients below the age of 12 have not been established.
Geriatrics (>65 years of age): The safety and effectiveness of this product in geriatric patients above the age of 65 years have not been established.
Susceptibility/Resistance
Development of Drug-Resistant Bacteria
Prescribing Taro-Benzoyl Peroxide / Clindamycin Kit in the absence of the authorized indications is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Potential for Microbial Overgrowth
Prolonged use of Taro-Benzoyl Peroxide / Clindamycin Kit may result in overgrowth of non-susceptible organisms including fungi. If this should occur, therapy with Taro-Benzoyl Peroxide / Clindamycin Kit should be discontinued and appropriate measures taken.
P. acnes resistance to clindamycin has been documented. Resistance to clindamycin is often associated with resistance to erythromycin. If this should occur, therapy with Taro-Benzoyl Peroxide / Clindamycin Kit should be discontinued and alternative therapy should be initiated.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The most frequent adverse reactions that may occur with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) are mild to moderate adverse reactions of the skin; most commonly, dry skin.
Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Table 1, below presents a pooled summary of the most frequent (≥ 1%) adverse reactions reported during four randomized, double-blind, vehicle-controlled, multicentre trials conducted with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) in patients with moderate acne vulgaris. A total of 420 male and female patients with an average age of 19 years received benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) in these studies; 168 patients received vehicle. The average duration of treatment with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) was 69 days.
Table 1 - Most Frequent Adverse Events (≥ 1%) Reported in the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) or Vehicle Groups Considered to be Possibly, Probably or Definitely Related to Product Administration
Body System:
Skin and Appendages
benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin
phosphate)
n= 420
Vehicle
n= 168
Very Common Adverse Reaction:
Dry Skin 12% 6%
Common Adverse Reactions:
Application site reaction 3% <1% Peeling 2% - Pruritus 2% <1% Erythema 1% <1%
Sunburn was observed in 1% of the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) group but considered related to the drug in less than 1% (2 patients). The use of a moisturizer in the studies may have reduced the incidence of dry skin.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Body as a Whole: Face edema, headache
Nervous System: Dizziness
Skin and Appendages: Rash, skin burning
Post-Market Adverse Drug Reactions
The most frequently reported post-market adverse events are related to the application site, and are consistent with the type of events recorded in the controlled clinical trials. Typically, these application site reactions have included dry skin, erythema, burning sensation, rash, peeling and pruritis. Application site hypersensitivity (allergic reaction), colitis and diarrhea have also been reported.
DRUG INTERACTIONS
Drug-Drug Interactions
The interactions discussed in this section are based on either drug interaction case reports, or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Clindamycin, erythromycin, lincomycin and chloramphenicol containing products should not be used concurrently. In vitro studies have shown antagonism among these antimicrobials. In vitro studies suggest that benzoyl peroxide contributes to the degradation of tretinoin especially when combined with exposure to UV light.
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Taro-Benzoyl Peroxide / Clindamycin Kit (benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate)) should be applied twice daily, morning and evening, or as directed by a physician, to affected areas of the skin after it is gently washed with a mild non-medicated soap, rinsed with warm water and patted dry. Improvement has been seen as early as two weeks, although up to ten weeks of treatment may be required for best results.
Administration
Reconstitution: Taro-Benzoyl Peroxide / Clindamycin Kit is supplied to the pharmacist as two components: 1) a jar of benzoyl peroxide gel; 2) a bottle containing clindamycin phosphate solution, both of which are to be admixed by the pharmacist and dispensed to the patient in the jar as 1% clindamycin and 5% benzoyl peroxide.
Table 2 – How Supplied and Mixing Instructions for the Pharmacist
| (Net Weight) | Benzoyl Peroxide Gel | Clindamycin Phosphate Solution |
| 50 grams | 40.0 g | 10.0 g |
Prior to dispensing, add the solution in the bottle to the gel and stir until homogenous in appearance (1 to 1½ minutes). Taro-Benzoyl Peroxide / Clindamycin Kit (as dispensed) can be stored between 15°C- 25°C for 3 months. Place a 3-month expiration date on the label immediately following mixing.
OVERDOSAGE
Acute overdosage with the topical use of Taro-Benzoyl Peroxide / Clindamycin Kit (benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate)) is unlikely. If Taro-Benzoyl Peroxide / Clindamycin Kit is applied excessively, marked dryness, peeling and redness might occur. The literature indicates that clindamycin could be absorbed topically (see WARNINGS AND PRECAUTIONS). In the event of accidental ingestion, treatment should be symptomatic.
ACTION AND CLINICAL PHARMACOLOGY
Taro-Benzoyl Peroxide / Clindamycin Kit (benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate)) contains 1% clindamycin (as phosphate) and 5% benzoyl peroxide. The use of a clindamycin and benzoyl peroxide combination product in acne is predicated upon the facts that both clindamycin and benzoyl peroxide are active against Propionibacterium acnes (P. acnes), and benzoyl peroxide is an oxidizing agent exhibiting keratolytic and desquamative activity (1, 2). Clindamycin phosphate is a water-soluble ester and semi-synthetic antibiotic which is derived from the parent antibiotic lincomycin (3). Taro-Benzoyl Peroxide / Clindamycin Kit penetrates the skin and has greater clinical and P. acnes reducing effects than either of its components. Taro-Benzoyl Peroxide / Clindamycin Kit inhibits clindamycin-resistant P. acnes. Topical clindamycin and benzoyl peroxide penetrate systemically to a minimal degree.
STORAGE AND STABILITY
Store Taro-Benzoyl Peroxide / Clindamycin Kit and its individual components between 15°C and 25°C (before and after reconstitution).
After reconstitution for dispensing to the patient, label Taro-Benzoyl Peroxide / Clindamycin Kit with a 3-month expiration date.
Do not freeze. Keep tightly closed. Keep out of the reach of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Taro-Benzoyl Peroxide / Clindamycin Kit (benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate)) is supplied as two components: a jar of benzoyl peroxide gel and a bottle containing clindamycin phosphate solution. The pharmacist will add the solution to the jar of benzoyl peroxide gel and mix (see DOSAGE AND ADMINISTRATION).
As dispensed to the patient after reconstitution by the pharmacist, Taro-Benzoyl Peroxide / Clindamycin Kit contains 1% clindamycin (as clindamycin phosphate) and 5% benzoyl peroxide in an aqueous gel medium. It also contains the following nonmedicinal ingredients: carbomer homopolymer, potassium hydroxide, propylene glycol, and purified water. Taro-Benzoyl Peroxide / Clindamycin Kit is dispensed in 50 g jar.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substances
Clindamycin Phosphate
Proper Name: Clindamycin Phosphate
Chemical Name: Methyl-7-chloro-6, 7, 8-trideoxy-6-(1-methyl-trans-4-propyl-L-2- pyrrolidinecarboxamido)-1-thio-L-threo-alpha-D-galacto-octopyranoside-2-(dihydrogen phosphate).
Molecular formula and molecular mass: The molecular formula for clindamycin phosphate is C18H34ClN2O8PS; the molecular weight is 504.97 g/mol.
Structural Formula:
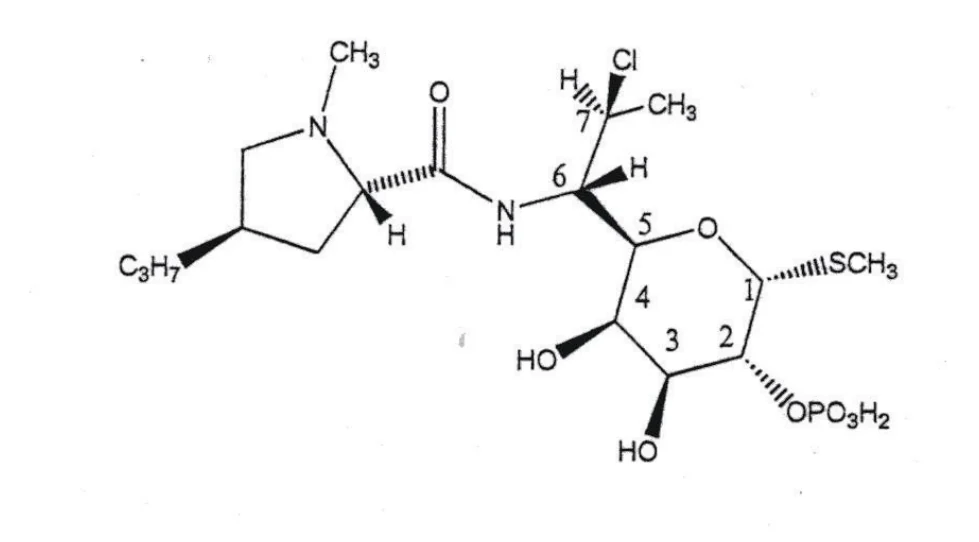
Physicochemical Properties: Clindamycin is a white to off-white, hygroscopic, crystalline powder.
Benzoyl Peroxide
Proper name: Benzoyl Peroxide.
Chemical name: peroxide, dibenzoyl
Molecular formula and molecular mass: The molecular formula for benzoyl peroxide is C14H10O4; the molecular weight is 242.23 g/mol.
Structural formula:
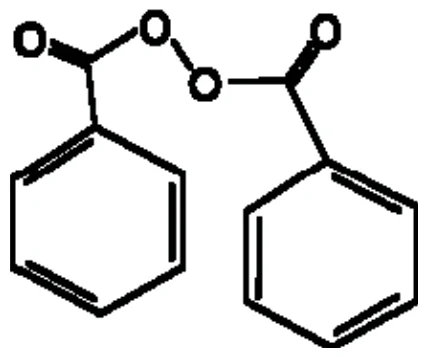
Physicochemical properties: Hydrous Benzoyl Peroxide is a white granular powder.
CLINICAL TRIALS
Comparative Bioavailability Studies
A Multi-Center, Double-Blind, Randomized, Placebo Controlled, Parallel-Group Study Comparing Clindamycin and Benzoyl Peroxide Gel 1%/5% (Taro Pharmaceuticals, Inc.) to Benzaclin® (Clindamycin as Phosphate 1% And Benzoyl Peroxide 5%) Topical Gel (Valeant Canada LP) and both Active Treatments to a Placebo Control in the Treatment of Acne Vulgaris was performed. The primary measure of bioequivalence was determined in the Per-Protocol (PP) population by evaluating the Test/Reference ratio of the mean percent change from baseline to Week 10 in the number of inflamed (papules/pustules) and non-inflamed (open and closed comedones) lesions. The secondary measure was the proportion of subjects who were considered a “clinical success” at Week 10 (Day 70 ± 4 days). In addition superiority to placebo and safety were evaluated for Test and Reference treatments.
Following 10 weeks of twice daily treatment, Clindamycin and Benzoyl Peroxide Gel 1%/5%, (Taro Pharmaceuticals USA, Inc.) was determined to be therapeutically equivalent to PrBENZACLIN® TOPICAL GEL (Clindamycin as phosphate 1% and Benzoyl Peroxide 5%) (Valeant Canada LP) in the treatment of acne vulgaris. Results are summarized in the table below.
Table 3
Equivalence Testing: Primary Efficacy Parameters (Mean Percent Change from Baseline to Week 10) PP Population, LS Mean | ||||
| Parameter | Test (N=262) | Reference (N=260) | Ratio | 90% CIa |
| Inflammatory Lesion Counts | -58.08 | -57.44 | 1.01 | (0.96, 1.06) |
| Non-Inflammatory Lesion Counts | -49.51 | -48.79 | 1.01 | (0.96, 1.07) |
Equivalence Testing: Secondary Efficacy Parameter (Proportion of Patients with a Clinical Response of “Success” at Week 10) PP Population | ||||
| Parameter | Test (N= 262) | Reference (N= | Difference | 90% CId |
| 260) | ||||
| Percent Clinical Success | 45.0 | 44.6 | 0.4 | (-7.1, 8.0) |
Superiority Testing: Primary Efficacy Parameters (Mean Percent Change from Baseline to Week 10) mITT Population | ||||
| Test (N=286) vs Vehicle (N=146)b | Reference (N=292) vs Vehicle (N=146)c | |||
| Parameter | LS Mean Difference | p-value | LS Mean Difference | p-value |
| Inflammatory Lesion Counts | -23.21 | < 0.0001 | -24.24 | < 0.0001 |
| Non-Inflammatory Lesion Counts | -21.76 | < 0.0001 | -21.56 | < 0.0001 |
mITT = modified intent to treat; PP = per protocol a LS Means from ANOVA with 90% confidence interval for the test/reference ratio calculated using Fieller's method. b LS Mean differences and p-values from ANOVA on Test and Vehicle subjects only. c LS Mean differences and p-values from ANOVA on Reference and Vehicle subjects only. d Two-sided, continuity-corrected 90% confidence interval for test-reference difference. | ||||
The effectiveness of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate), versus clindamycin, benzoyl peroxide and vehicle was established in three independent and well controlled clinical studies involving 1259 patients. Among these studies 380, 379, 169 and 168 patients were randomized to receive benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate), 5% benzoyl peroxide gel, 1% clindamycin gel, or vehicle, respectively and 348, 327, 149, 144 completed 10 weeks. In all trials, eligible patients were between 13 and 30 years of age and had moderate acne. Additionally, at baseline, patients had to have a minimum of 10 to a maximum of 50 or 80 inflammatory lesions, and 10-100 comedones (baseline means of 23 and 35 respectively for the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) groups). Treatments were applied twice daily for 10 weeks. Patients returned for clinic visits at weeks 2, 4, 6, 8, and 10 during which efficacy was evaluated. The efficacy measures were the change from baseline in number of inflammatory lesions, comedones and total lesions (combined inflammatory and comedones), and the physician and patient overall improvement ratings.
In these studies, benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) demonstrated significantly greater clinical improvements by 10 weeks than did vehicle or clindamycin alone against inflammatory and non-inflammatory lesions or than benzoyl peroxide alone against inflammatory lesions. The benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) groups also showed greater overall improvement than the benzoyl peroxide, clindamycin and vehicle groups according to the physician overall global improvement score in two studies and showed greater overall improvement than the clindamycin and vehicle groups in the third study. Improvements occurred as early as two weeks. The percent mean reduction in lesion counts for the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate), the active constituents and the vehicle at week 10 are presented below.
Table 4 - Mean Percent Reduction in Lesion Counts for Treatment Groups and Vehicle
Benzoyl peroxide and clindamycin gel, 5% /
1%, w/w (as
clindamycin phosphate)
(n=348)
Benzoyl peroxide
(n=327) Clindamycin
(n=149) Vehicle
(n=144)
Mean percent reduction in inflammatory lesions at Week 10
Study 1 46% 32% 16% - 3%* Study 2 55% 48% -- -- Study 3 63% 53% 45% 42%
Mean percent reduction in non-inflammatory lesions at Week 10
Study 1 22% 22% 9% - 1%* Study 2 34% 31% -- -- Study 3 54% 50% 39% 36%
Mean percent reduction in total lesions at Week 10
Study 1 36% 28% 15% - 0.2%* Study 2 44% 37% -- -- Study 3 58% 52% 42% 39%
*minus sign indicates increase
Two other clinical studies, conducted in acne patients and healthy volunteers, respectively, evaluated the topical antimicrobial efficacy of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) versus 1% clindamycin gel alone.
The superior antimicrobial and clinical efficacy of twice daily treatment with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) compared to clindamycin was seen in the 16-week study in acne patients. Significantly greater reductions in total Propionibacterium acnes (P. acnes) were generally obtained with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) compared to clindamycin. Significantly fewer clindamycin-resistant P. acnes were observed in the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) group than in the clindamycin group at the end of the study. In the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) group, counts of clindamycin -resistant P. acnes were lowered to 65% of baseline values at the end of 16 weeks, while in the clindamycin group, counts of clindamycin-resistant P. acnes were increased by >1600%. The superior clinical efficacy of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) was demonstrated by significantly greater reductions in inflammatory lesions (47.9%) and comedones (44.5%) than were obtained with clindamycin (27.9% and 22.9%, respectively) at Week 16. The superiority of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) was demonstrated against clindamycin-resistant P. acnes as well as coagulase negative staphylococci (CONS) resistant or sensitive to clindamycin.
In a two-week comparative study in healthy volunteers, benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) produced a reduction in P. acnes, which exceeded that of three clindamycin formulations by two orders of magnitude by the end of the first week of treatment. At the end of the study, benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) produced a 99.9% reduction (> 3 log) in the number of P. acnes organisms over the face and was significantly more effective than the clindamycin formulations of lotion, gel and solution whose log reductions ranged from 0.9 to 1.68 (See MICROBIOLOGY section).
DETAILED PHARMACOLOGY
Use of topical formulations of clindamycin can result in absorption of the antibiotic from the skin surface. Benzoyl peroxide has been shown to be absorbed by the skin where it is converted to benzoic acid (11). Less than 2% of the dose enters systemic circulation as benzoic acid. It is suggested that the lipophilic nature of benzoyl peroxide acts to concentrate the compound into the lipid-rich sebaceous follicle (2). Studies conducted with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) demonstrated that the combination of clindamycin and benzoyl peroxide in the product formulation does not alter the dermal absorption of either compound.
Pharmacokinetic studies
An in-vitro percutaneous penetration study comparing benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) and topical 1% clindamycin gel alone, demonstrated there was no difference in clindamycin penetration between the two drugs. Minimal penetration (less than 1%) occurred for both products. A second in-vitro skin penetration study of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) demonstrated that the 1% clindamycin did not affect the penetration of benzoyl peroxide.
A single dose study in normal volunteers demonstrated that facial application of a 1g dose of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) did not produce detectable (Lower Limit of Quantification was 2.5 ng/mL) plasma levels of clindamycin or other related compounds up to 24 hours later. Mean systemic bioavailability of topical clindamycin in benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) is suggested to be less than 1%.
Dermal Pharmacology Studies
Clinical studies have demonstrated that benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) did not have detectable phototoxic or photocontact allergic potential. The irritation and contact sensitization potential of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) was found to be mild.
MICROBIOLOGY
Benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate), is indicated for use in the topical treatment of moderate acne vulgaris, a condition in which
Propionibacterium acnes (P. acnes) is implicated in the pathogenesis. Minimum inhibitory concentrations (MIC, (µg/mL)) of clindamycin as well as benzoyl peroxide for P. acnes and staphylococci have been reported in the literature as follows:
Table 5 MIC (µg/mL)
P. acnes S. aureus S. epidermidis
Clindamycin (4,5,6) 0.125 - 0.5 0.02 0.003 Benzoyl Peroxide (1,7) 64 - 800 NA 512 NA = not available
P. acnes resistance to clindamycin is common, as is cross-resistance to macrolides (6, 7, 8, 9). MICs for resistant strains of propionibacterium and staphylococci have been reported in the literature to reach 512 µg/mL. (5,8) No resistance to benzoyl peroxide has been reported. Combining benzoyl peroxide with a topical antibiotic has been demonstrated to inhibit clindamycin-resistant bacteria and prevent their emergence. (7, 10)
In clinical studies, the effects of the benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) combination of clindamycin and benzoyl peroxide and that of clindamycin alone were evaluated in clindamycin sensitive and clindamycin-resistant P. acnes.
In one two week clinical study, involving human volunteers benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) reduced facial baseline P. acnes counts by 99.9% (>3 logs) whereas topical clindamycin solution, lotion and gel formulations reduced P. acnes by 88% to 95% (See CLINICAL TRIALS section).
In a second 16-week clinical study of benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) and clindamycin alone in the treatment of acne, clinical efficacy was significantly greater with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) than with clindamycin alone. In addition, benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) produced a 10-fold greater reduction in P. acnes compared with clindamycin, and reduced clindamycin-resistant P. acnes counts at 16 weeks to 65% of baseline values. In the clindamycin group clindamycin-resistant P. acnes increased more than 1600% (>1.2 log) (10) (See CLINICAL TRIALS section).
TOXICOLOGY
There is extensive toxicology information in the scientific literature on clindamycin and benzoyl peroxide. (e.g. 12, 13, 14, 15, 16). The following information relates specifically to studies conducted with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate).
Subchronic Toxicity
Two subchronic (3-month) topical toxicity studies showed only mild dermal irritation and mild infiltrative microscopic changes of the skin in New Zealand white rabbits and Sprague-Dawley albino rats. Both species were dosed at 20, 40, and 400 mg/kg/day of the product clindamycin 1% and benzoyl peroxide 5% gel, administered dermally (non-occluded) in 2 divided doses, 6 hours apart per day for a period of at least 90 days. Control groups in both studies were treated with 5% benzoyl peroxide alone at the same dose volume as administered to the high dose clindamycin 1% and benzoyl peroxide 5% gel group. The untreated control groups were not administered any material, but were merely observed. All animals survived the full duration of the studies and were free of systemic toxic effects. Mild dermal irritation and minimal to slight microscopic skin changes were seen for both clindamycin 1% and benzoyl peroxide 5% gel and 5% benzoyl peroxide alone. These changes are attributed to the benzoyl peroxide content of each product. Untreated animals exhibited no dermal irritation. No systemic toxicity was seen in any group.
Mutagenicity
Mutagenicity studies were not conducted with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate). Clindamycin phosphate was not mutagenic in Salmonella typhimurium or in a rat micronucleus test. Clindamycin phosphate sulfoxide, an oxidative degradation product of clindamycin phosphate and benzoyl peroxide, was not clastogenic in a mouse micronucleus test. Benzoyl peroxide has been found to cause DNA strand breaks in a variety of mammalian cell types, to be mutagenic in Salmonella typhimurium tests by some (17) but not all investigators (15, 16), and to cause sister chromatid exchanges in Chinese hamster ovary cells (12,18).
Carcinogenicity
In a controlled laboratory evaluation of photocarcinogenicity in albino hairless mice, median time to onset of skin tumors was decreased and the number of skin tumors was increased following 40 weeks of topical dosing with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) accompanied with exposure to ultraviolet radiation. Although the significance of this study to humans is not clear, patients should minimize exposure to sunlight or artificial ultraviolet irradiation sources.
Benzoyl peroxide has been shown to be a tumor promoter and progression agent in a number of animal studies. The clinical significance of this is unknown (12).
Benzoyl peroxide in acetone at doses of 5 and 10 mg administered twice per week induced skin tumors in transgenic TG.AC mice in a study using 20 weeks of topical treatment (12). However, in 2-year dermal oncogenicity studies, there was no evidence of carcinogenic potential at doses up to 45 mg/day in Fischer 344 rats or doses up to 25 mg/day in B6C3F1 mice (19, 20).
Reproduction and Teratology
Animal reproductive/developmental toxicity studies have not been conducted with benzoyl
peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate). Developmental toxicity studies performed in rats and mice using oral doses of clindamycin up to 600 mg/kg/day (240 and 120 times amount of clindamycin in the highest recommended adult human dose based on mg/m2 respectively) or subcutaneous doses of clindamycin up to 250 mg/kg/day (100 and 50 times the amount of clindamycin in the highest recommended adult human dose based on mg/m2, respectively) revealed no evidence of teratogenicity (21,13).
Doses of up to 1.7 µmol benzoyl peroxide were dissolved in acetone and injected onto the inner shell membrane in the air chamber of three-day-old White Leghorn chicken eggs. There was a dose-related increase in early embryonic deaths at all but the lowest dose level, with an LD50 estimated at 0.99 µmol/egg. All doses of benzoyl peroxide increased the malformation rate, although no clear dose-response was evident (perhaps due to the increased embryonic death). The ED50 for mortality and malformations was calculated to be 0.27 µmol/egg (22).
Studies have not been performed with benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate) or benzoyl peroxide to evaluate the effect on fertility. Fertility studies in rats treated orally with up to 300 mg/kg/day of clindamycin (approximately 120 times the amount of clindamycin in the highest recommended adult human dose of 2.5 g benzoyl peroxide and clindamycin gel, 5% / 1%, w/w (as clindamycin phosphate), based on mg/m2) revealed no effects on fertility or mating ability (21, 13).
REFERENCES
- 1. Decker LC, Deuel DM, Sedlock, DM. Role of lipids in augmenting the antibacterial activity of benzoyl peroxide against Propionibacterium acnes. Antimicrob Agents Chemother 1989;33:326-30.
- 2. Tucker SB, Tausend R, Cochran R, Flannigan SA. Comparison of topical clindamycin phosphate, benzoyl peroxide, and a combination of the two for the treatment of acne vulgaris. Br J Dermatol 1984;110:487-92.
- 3.
Algra RJ, Rosen T, Waisman M. Topical clindamycin in acne vulgaris, Safety and
Stability. Arch. Dermatol 1977;113:1390-1.
- 4. Werner H, Heizmann W, Luft G. In vitro activity of flomoxef compared to maxalactam, cefoxitin, and clindamycin against anaerobes. Arzneimittelforschung 1988;38(11):1553-6.
- 5. Amr S, Brown MB, Martin GP, Forbes B. Activation of clindamycin phosphate by human skin. J Appl Microbiol 2001;90:550-4.
- 6.
Ross JI, Snelling AM, Eady EA, Cove JH, Cunliffe WJ, Leyden JJ, Collignon P, Dreno B,
Reynaud A, Fluhr J, Oshima S. Phenotypic and genotypic characterization of antibiotic- resistant Propionibacterium acnes isolated from acne patients attending dermatology clinics in Europe, the U.S.A., Japan and Australia. Br J Dermatol 2001;144:339-46.
- 7. Eady EA, Farmery MR, Ross JI, Cove JH, Cunliffe WJ. Effects of benzoyl peroxide and erythromycin alone and in combination against antibiotic-sensitive and -resistant skin bacteria from acne patients. Br J Dermatol 1994;131:331-6.
- 8. Ross JI, Eady EA, Carnegie E, Cove JH. Detection of transposon Tn5432-mediated macrolide-lincanoside-streptoframin B (MLSB) resistance in cutaneous propionibacteria from six European cities. J Antimicrob Chemother 2002;49:165-8.
- 9.
Ross JI, Snelling AM, Carnegie E, Coates P, Cunliffe WJ. Clinical and Laboratory
Investigations. Antibiotic-resistant acne: Lessons from Europe. Br J Dermatol 2003; 148:467-78.
- 10. Cunliffe WJ, Holland KT, Bojar R, Levy SF. A randomized, double-blind comparison of a clindamycin phosphate/benzoyl peroxide gel formulation and a matching clindamycin gel with respect to microbiologic activity and clinical efficacy in the topical treatment of acne vulgaris. Clin Ther 2002;24:1117-33.
- 11. Nacht S, Yueng D, Beasley JN, Anjo MD, Maibach HI. Benzoyl peroxide: percutaneous penetration and metabolic disposition. J Am Acad Dermatol 1981;4: 31-37.
- 12.
Binder RL, Aardema MJ, Thompson ED. Benzoyl Peroxide: Review of Experimental
Carcinogenesis and Human Safety Data. In Growth Factors and Tumor Promotion: Implications for Risk Assessment. Wiley-Liss, Inc. 1995;245-94.
- 13.
Gray JE, Weaver RN, Bollert JA, Feenstra ES. The oral toxicity of clindamycin in
Laboratory Animals. Toxicol Appl Pharmacol 1972;21:516-531.
- 14. Gray JE, Weaver RN, Moran J, Feenstra ES. The parenteral toxicity of clindamycin 2- phosphate in laboratory animals. Toxicol Appl Pharmacol 1974;27:308-21.
- 15.
World Health Organization, International Agency for Research on Cancer. IARC
Monographs on the evaluation of carcinogenic risk of chemicals to humans. Benzoyl peroxide. IARC Monographs 1987;Suppl 7: 267-283.
- 16.
Kraus AL, Munro IC, Orr JC, Binder RL, LeBoeuf RA, Williams GM. Benzoyl Peroxide:
An integrated human safety assessment for carcinogenicity. Regul Toxicol Pharmacol 1995;21:87-107.
- 17.
Matula TI, Downie RH, Barrett N. Mutagenicity studies of benzoyl peroxide in bacteria.
Environ Mutag 1987;9(Suppl 8):69.
- 18. Järventaus H, Norppa H, Linnainmaa K and Sorsa M. SCE induction in CHO cells by peroxides used in the plastic industry (Abstract II-3C-8). Mutat Res 1984;130:249.
- 19. Binder RL, Totman LC, Freeman SJ, Winkelman EJ, Minnema DJ, Nash JF. Dermal oncogenicity study of Benzoyl Peroxide carbopol gel in B6C3F1 mice. In SOT annual meeting 2000:398.
- 20. Totman LC, Binder RL, Freeman SJ, Winkelman EJ, Minnema DJ, Nash JF. Dermal oncogenicity study of Benzoyl Peroxide carbopol gel in Fischer rats. In SOT annual meeting 2000:398.
- 21. Bollert JA, Gray JE, Highstrete JD, Moran J, Purmalis BP, and Weaver RN. Teratogenicity and neonatal toxicity of clindamycin 2-phosphate in laboratory animals. Toxicol Appl Pharmacol 1974;27:322-9.
- 22. Korhonen A, Hemminki K, Vainio H. Embryotoxic effects of eight organic peroxides and hydrogen peroxide on three-day chicken embryos. Environ Res 1984;33:54-61.
- 23. Leyden JJ, Berger RS, Dunlap FE, Ellis CN, Connolly MA, Levy MA. Comparison of the efficacy and safety of a combination topical gel formulation of benzoyl peroxide and clindamycin with benzoyl peroxide, clindamycin and vehicle gel in the treatments of acne vulgaris. Am J Clin Dermatol 2001;2(1):33-9.
- 24.
Product Monograph: Pr BENZACLIN® TOPICAL GEL, Valeant Canada LP. Control
No.205918, Date ofRevision: March 9, 2018.