


Product Monograph - Teva-Salbutamol HFA
Recent Major Label Changes
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 2025-10 |
|---|---|
| 4 Dosage and Administration, 4.4 Administration | 2026-04 |
| 7 Warnings and Precautions, General | 2026-04 |
| 7 Warnings and Precautions, Respiratory | 2025-10 |
Table of Contents
Certain sections (as indicated in section 2.1. of the PM Guidance) or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ......................................................................................................... 2
Table of Contents .......................................................................................................................... 2
Part 1: Healthcare Professional Information ................................................................................. 4
1 Indications ................................................................................................................................. 4
1.1 Pediatrics .................................................................................................................................... 4
2 Contraindications ....................................................................................................................... 4
4 Dosage and Administration ........................................................................................................ 4
4.1 Dosing Considerations ................................................................................................................ 4
4.2 Recommended Dose and Dosage Adjustment............................................................................ 5
4.4 Administration ............................................................................................................................ 5
5 Overdosage ................................................................................................................................ 6
6 Dosage Forms, Strengths, Composition and Packaging ............................................................... 7
7 Warnings and Precautions .......................................................................................................... 8
7.1 Special Populations ................................................................................................................... 11
7.1.1 Pregnancy .............................................................................................................................. 11
7.1.2 Breast-feeding ....................................................................................................................... 11
7.1.3 Pediatrics ............................................................................................................................... 12
7.1.4 Geriatrics ............................................................................................................................... 12
8 Adverse Reactions .................................................................................................................... 12
8.1 Adverse Reaction Overview ...................................................................................................... 12
8.2 Clinical Trial Adverse Reactions ................................................................................................ 13
8.5 Post–Market Adverse Reactions ............................................................................................... 14
9 Drug Interactions ..................................................................................................................... 15
9.4 Drug-Drug Interactions ............................................................................................................. 15
9.5 Drug-Food Interactions ............................................................................................................. 16
9.6 Drug-Herb Interactions ............................................................................................................. 16
9.7 Drug-Laboratory Test Interactions ............................................................................................ 16
10 Clinical Pharmacology ............................................................................................................ 16
10.1 Mechanism of Action .............................................................................................................. 16
10.3 Pharmacokinetics ................................................................................................................... 17
11 Storage, Stability, and Disposal .............................................................................................. 18
12 Special Handling Instructions .................................................................................................. 18
Part 2: Scientific Information ...................................................................................................... 19
13 Pharmaceutical Information ................................................................................................... 19
14 Clinical Trials .......................................................................................................................... 19
14.1 Clinical Trials by Indication ..................................................................................................... 19
15 Microbiology .......................................................................................................................... 22
16 Non-Clinical Toxicology .......................................................................................................... 22
17 Supporting Product Monographs ............................................................................................ 25
Patient Medication Information .................................................................................................. 26
Part 1: Healthcare Professional Information
1 Indications
Adults and Children (4 years and older):
TEVA-SALBUTAMOL HFA (salbutamol sulfate inhalation aerosol) is indicated for:
- the symptomatic relief and prevention of bronchospasm due to bronchial asthma, chronic bronchitis and other chronic bronchopulmonary disorders in which bronchospasm is a complicating factor.
- the prevention of exercise-induced bronchospasm.
1.1 Pediatrics
Pediatrics (<4 years of age): The safety and efficacy in children below the age of 4 years has not been established.
2 Contraindications
TEVA-SALBUTAMOL HFA is contraindicated:
- in patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing (see 6 Dosage Forms, Strengths, Composition, and Packaging).
- as a tocolytic in patients at risk of premature labour or threatened abortion.
4 Dosage and Administration
4.1 Dosing Considerations
The dosage should be individualized, and the patient’s response should be monitored by the prescribing physician on an ongoing basis.
Increasing demand for TEVA-SALBUTAMOL HFA in bronchial asthma is usually a sign of poorly controlled or worsening asthma and indicates that the patient should be re-evaluated, the treatment plan should be reviewed and the regular asthma controller treatment should be optimized. If inhaled salbutamol treatment alone is not adequate to control asthma, concomitant anti-inflammatory therapy should be part of the treatment regimen.
If a previous effective dose regimen fails to provide the usual relief, or the effects of a dose last for less than 3 hours, medical advice should be sought immediately; this is a sign of seriously worsening asthma that requires reassessment of therapy.
As there may be adverse effects associated with excessive dosing, the dosage or frequency of administration should only be increased on medical advice. However, if a more severe attack has not been relieved by the usual dose, additional doses may be required. In these cases, patients should immediately consult their physicians or the nearest hospital.
4.2 Recommended Dose and Dosage Adjustment
Bronchospasm
For treatment of acute episodes of bronchospasm or prevention of symptoms associated with bronchospasm, the usual dosage is:
Adolescents and adults (12 years and older): two inhalations (200 mcg) repeated every 4 to 6 hours. More frequent administration or a larger number of inhalations is not recommended. In some patients, one inhalation (100 mcg) every 4 hours may be sufficient.
Maximum Daily Dose: Eight sprays (800 mcg)
Children (4-11): One inhalation (100 mcg) repeated every 4 to 6 hours.. May be increased to two sprays (200 mcg salbutamol), if required.
Maximum Daily Dose: Four sprays (400 mcg)
Exercise-Induced Bronchospasm
The usual dosage is:
- Adolescents and adults (12 years and older): two inhalations (200 mcg) 15 to 30 minutes before exercise.
- Children (4-11): one inhalation (100 mcg) 15 to 30 minutes before exercise. May be increased to two sprays (200 mcg salbutamol), if required.
DO NOT EXCEED RECOMMENDED DOSE (See 7 Warnings and Precautions)
4.4 Administration
TEVA-SALBUTAMOL HFA is administered by the inhaled route only. To ensure administration of the proper dose of the drug, the patient should be instructed by the physician or other health professional in the proper use of the inhalation aerosol.
Inhaler actuation should be synchronised with inspiration to ensure optimum delivery of drug to the lungs.
The use of open mouth technique to administer TEVA-SALBUTAMOL HFA has not been investigated in clinical trials.
Shake well before each spray. To maintain proper use of this product and to prevent medication build-up and blockage, it is important to follow the cleaning directions carefully.
Priming
Prime the inhaler before using for the first time and in cases where the inhaler has not been used for more than 2 weeks by releasing three sprays into the air, away from the face.
The inhaler contains enough salbutamol for 200 actuations (puffs) only. After 200 actuations (puffs), the inhaler can continue to spray but without the prescribed dose of salbutamol. Methods such as shaking, weighing or submerging inhalers are not accurate for determining that an inhaler is empty of the prescribed dose of salbutamol. Maintaining a record of the number of actuations (puffs) administered to the patient should be considered, towards avoiding inadvertent use of an empty inhaler. Keeping a back-up inhaler could be considered. If the patient has more than one inhaler, it is recommended to keep track of each inhaler separately.
Cleaning
As with all HFA-containing salbutamol inhalers, to maintain proper use of this product and to prevent medication build-up and blockage, it is important to keep the plastic mouthpiece clean. The inhaler may cease to deliver medication if the plastic actuator mouthpiece is not properly cleaned and dried. To clean: Wash the plastic mouthpiece with warm running water for 30 seconds, shake off excess water, and air dry thoroughly at least once a week. If the mouthpiece becomes blocked, washing the mouthpiece will remove the blockage. If it is necessary to use the inhaler before it is completely dry, shake off excess water, replace canister, spray twice into the air away from face, and take the prescribed dose. After such use, the mouthpiece should be rewashed and allowed to air dry thoroughly.
Missed Dose
If a single dose is missed, instruct the patient to take the next dose when it is due or if they become wheezy.
5 Overdosage
Signs and Symptoms
The expected symptoms with overdosage are those of excessive beta-adrenergic stimulation and/or occurrence or exaggeration of any of the symptoms listed under Adverse Reactions, e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats per minute, arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, and insomnia.
Hypokalemia may also occur. As with all sympathomimetic medications, cardiac arrest and even death may be associated with abuse of TEVA-SALBUTAMOL HFA Inhalation Aerosol.
Lactic acidosis has been reported in association with high therapeutic doses as well as overdoses of short-acting beta-agonist therapy, therefore monitoring for elevated serum lactate and consequent metabolic acidosis (particularly if there is persistence or worsening of tachypnea despite resolution of other signs of bronchospasm such as wheezing) may be indicated in the setting of overdose.
Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
Treatment
Consideration should be given to discontinuation of treatment and appropriate symptomatic therapy. To antagonise the effect of salbutamol, the judicious use of a cardioselective beta-adrenergic blocking agent (e.g. metoprolol, atenolol) may be considered, bearing in mind the danger of inducing an asthmatic attack. Serum potassium levels should be monitored. There is insufficient evidence to determine if dialysis is beneficial for overdosage of salbutamol sulfate inhalation aerosol.
Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral inhalation | Inhalation aerosol/ 100 mcg salbutamol/actuation | 1,1,1,2-tetrafluoroethane (HFA-134a) and Ethanol |
TEVA-SALBUTAMOL HFA (salbutamol sulfate inhalation aerosol) is a pressurized metered dose inhaler (MDI) consisting of an aluminum canister fitted with a metering valve. Each canister is fitted into an actuator. A dust cap is fitted over the actuator’s mouthpiece when not in use. Each spray delivers 100 mcg of salbutamol (as sulfate).
TEVA-SALBUTAMOL HFA contains an active ingredient of salbutamol sulfate and the nonmedicinal ingredients are ethanol and HFA-134a (1, 1, 1, 2-tetrafluoroethane). This product does not contain chlorofluorocarbons (CFCs) as the propellant.
TEVA-SALBUTAMOL HFA is available in canisters of two hundred dose formats.
7 Warnings and Precautions
General
Patients should always carry their TEVA-SALBUTAMOL HFA to use immediately if an episode of asthma is experienced. If therapy does not produce a significant improvement or if the patient’s condition worsens, medical advice must be sought to determine a new plan of treatment. In the case of acute or rapidly worsening dyspnea, a physician should be consulted immediately.
The inhaler contains enough salbutamol for 200 actuations (puffs) only. After 200 actuations (puffs), the inhaler can continue to spray but without the prescribed dose of salbutamol. Methods such as shaking, weighing or submerging inhalers are not accurate for determining that an inhaler is empty of the prescribed dose of salbutamol. Maintaining a record of the number of actuations (puffs) administered to the patient should be considered, towards avoiding inadvertent use of an empty inhaler. Keeping a back-up inhaler could be considered. If the patient has more than one inhaler, it is recommended to keep track of each inhaler separately.
The bronchodilating action of sympathomimetic drugs may be antagonized by β adrenergic blocking agents with the result that the respiratory status of patients may worsen when the two drugs are used concomitantly. In patients requiring concomitant treatment with TEVA-SALBUTAMOL HFA and a β adrenergic blocking agent, the use of a relatively cardioselective β blocker (e.g. metoprolol, atenolol, acebutolol) must be considered. During the concomitant treatment, patients should be monitored carefully for possible deterioration in pulmonary function or for the need to adjust the dosage of either drug.
Excessive Use and Use with other Sympathomimetics
Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
DO NOT EXCEED RECOMMENDED DOSE.
Concomitant use of TEVA-SALBUTAMOL HFA with other sympathomimetic agents is not recommended since the combined use may lead to deleterious cardiovascular effects. If concomitant use is necessary, this should take place only under strict medical supervision.
Deterioration of Asthma
Asthma may deteriorate over time. If the patient needs to use TEVA-SALBUTAMOL HFA more often than usual, this may be a sign of worsening asthma. This requires reevaluation of the patient and treatment plan and consideration of adjusting the asthma maintenance therapy. If inhaled salbutamol treatment alone is not adequate to control asthma, concomitant anti-inflammatory therapy should be part of the treatment regimen (see 4 Dosage and Administration). It is essential that the physician instruct the patient in the need for further evaluation if the patient's asthma becomes worse.
Cardiovascular
In individual patients, any beta2-adrenergic agonist, including salbutamol, may have a clinically significant cardiac effect. There is some evidence from post-marketing data and published literature of rare occurrences of myocardial ischaemia associated with beta agonists. Care should be taken with patients suffering from cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias and hypertension. Special care and supervision are required in patients with idiopathic hypertrophic subvalvular aortic stenosis, in whom an increase in the pressure gradient between the left ventricle and the aorta may occur, causing increased strain on the left ventricle. In addition, beta-agonists have been reported to produce ECG changes, such as flattening of the T-wave, prolongation of the QTc interval, and ST-segment depression. Attention should be paid to assessment of symptoms such as dyspnoea and chest pain, as they may be of either respiratory or cardiac origin. Cardiac arrest was noticed in several instances.
Endocrine and Metabolism
As with other beta-agonists, TEVA-SALBUTAMOL HFA may produce significant hypokalemia in some patients, possibly through intracellular shunting, which has the potential to produce adverse cardiovascular effects. The decrease is usually transient, not requiring supplementation. Particular caution is advised in acute severe asthma since hypokalemia may be potentiated by concomitant treatment with xanthine derivatives, steroids and diuretics and by hypoxia. Hypokalemia will increase the susceptibility of digitalis-treated patients to cardiac arrhythmias. It is recommended that serum potassium levels be monitored in such situations.
Care should be taken with patients with diabetes mellitus. Salbutamol can induce reversible hyperglycemia during nebulised administration or especially during infusions of the drug. The diabetic patient may be unable to compensate for this and the development of ketoacidosis has been reported. Concurrent administration of corticosteroids can exaggerate this effect.
Care should be taken with patients with hyperthyroidism.
Immune
Hypersensitivity
Immediate hypersensitivity reactions may occur after administration of salbutamol sulfate, as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm, hypotension, anaphylaxis and oropharyngeal edema.
Care should be taken in patients who are unusually responsive to sympathomimetic amines.
Monitoring and Laboratory Tests
In accordance with the present practice for asthma treatment, patient response should be monitored clinically and by lung function tests.
Neurologic
Care should be taken with patients with convulsive disorders.
Respiratory
- Paradoxical Bronchospasm
TEVA-SALBUTAMOL HFA can produce paradoxical bronchospasm, which may be life threatening. If paradoxical bronchospasm occurs, TEVA-SALBUTAMOL HFA should be discontinued immediately and alternative therapy instituted. It should be recognized that paradoxical bronchospasm, when associated with inhaled formulations, frequently occurs with the first use of a new canister.
Monitoring Control of Asthma
Failure to respond for at least three hours to a previously effective dose of TEVA-SALBUTAMOL HFA indicates a deterioration of the condition and the physician should be contacted promptly. Patients should be warned not to exceed the recommended dose.
Failure to respond to treatment with TEVA-SALBUTAMOL HFA may signal a need for urgent medical advice or treatment.
The increasing use of fast-acting, short duration inhaled beta2-adrenergic agonists to control symptoms indicates deterioration of asthma control and the patient’s therapy plan should be reassessed by a physician.
Patients who are taking TEVA-SALBUTAMOL HFA more than twice a week on an “as needed” basis, not counting prophylactic use prior to a known trigger should be re-evaluated (i.e., daytime symptoms, nighttime awakening, and activity limitation due to asthma) for proper treatment adjustment as these patients are at risk for overuse of TEVA-SALBUTAMOL HFA. A reassessment of the patient's therapy plan may be required.
In worsening asthma, it is inadequate to increase beta2-agonist use only, especially over an extended period of time. In the case of acute or rapidly worsening dyspnea, a physician should be consulted immediately. Sudden or progressive deterioration in asthma control is potentially life threatening; the treatment plan must be re-evaluated, and consideration be given to corticosteroid therapy (see 4.1 Dosing Considerations).
Overuse of short-acting beta-agonists may mask the progression of the underlying disease and contribute to deteriorating asthma control, leading to an increased risk of severe asthma exacerbations and mortality.
Patients who are prescribed regular asthma anti-inflammatory therapy (e.g., inhaled corticosteroids) should be advised to continue taking their anti-inflammatory medication even when symptoms improve, and they no longer require TEVA-SALBUTAMOL HFA.
- Deterioration of Asthma
Asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If the patient needs more doses of TEVA-SALBUTAMOL HFA than usual, this may be a marker of destabilization of asthma and requires re-evaluation of the patient and treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids.
7.1 Special Populations
7.1.1 Pregnancy
Salbutamol, in common with other beta-agonists, is not approved to stop or prevent premature labour. There are no adequate and well-controlled studies in pregnant women and there is little published evidence of its safety in the early stages of human pregnancy.
Administration of any drug to pregnant women should only be considered if the anticipated benefits to the expectant woman are greater than any possible risks to the fetus (see 16 Non-Clinical Toxicology, Teratogenicity Studies).
During worldwide marketing experience, rare cases of various congenital anomalies, including cleft palate and limb defects have been reported in the offspring of patients being treated with salbutamol. Some of the mothers were taking multiple medications during their pregnancies. Because no consistent pattern of defects can be discerned, and baseline rate for congenital anomalies is 2-3%, a relationship with salbutamol use cannot be established.
Labour & Delivery
Because of the potential for beta-agonist interference with uterine contractility, use of TEVA-SALBUTAMOL HFA for relief of bronchospasm during labour should be restricted to those patients in whom the benefits clearly outweigh the risks.
TEVA-SALBUTAMOL HFA is contraindicated for the management of pre-term labour. Serious adverse reactions, including pulmonary edema, have been reported during or following treatment of premature labour with beta2-agonists, including salbutamol.
7.1.2 Breast-feeding
Plasma levels of salbutamol sulfate and HFA-134a after inhaled therapeutic doses are very low in humans, but it is not known whether the components are excreted in human milk. Because of the potential for tumorigenicity shown for salbutamol in some animal studies, a decision should be made whether to discontinue nursing or to discontinue the drug taking into account the benefit of the drug to the mother. It is not known whether salbutamol in breast milk has a harmful effect on the neonate.
7.1.3 Pediatrics
Pediatrics (4 to <12 years): The use of metered-dose inhalers in children depends on the ability of the individual child to learn the proper use of this device. Metered-dose inhalers with spacers are recommended for children under 5 years of age.
Conversion from a face mask to a mouthpiece is strongly encouraged as soon as the age and the cooperation of the child permit.
During inhalation, children should be assisted or supervised by an adult who knows the proper use of the device.
Rarely, in children, hyperactivity occurs and occasionally, sleep disturbances, hallucination or atypical psychosis have been reported.
Pediatrics (< 4 years of age): The safety and efficacy in children below the age of 4 years has not been established.
7.1.4 Geriatrics
Clinical studies of salbutamol inhalation aerosol did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. As with other beta2-agonists, special caution should be observed when using TEVA-SALBUTAMOL HFA in elderly patients who have concomitant cardiovascular disease that could be adversely affected by this class of drug. (see 7 WARNINGS and PRECAUTIONS, Cardiovascular).
All beta2-adrenergic agonists, including salbutamol, are known to be substantially excreted by the kidney, and the risk of toxic reactions may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
8 Adverse Reactions
8.1 Adverse Reaction Overview
As with other bronchodilator inhalation therapy, the potential for paradoxical bronchospasm should be kept in mind. If it occurs, the preparation should be discontinued immediately and alternative therapy instituted.
Potentially serious hypokalemia may result from beta2-agonist therapy primarily from parenteral and nebulised routes of administration (see 7 Warnings and Precautions, Endocrine and Metabolism, Metabolic Effects).
Peripheral vasodilation and a compensatory small increase in heart rate may occur in some patients. Cardiac arrhythmias (including atrial fibrillation, supraventricular tachycardia, extrasystoles) have been reported, usually in susceptible patients.
Other adverse reactions associated with salbutamol are nervousness and tremor. In some patients inhaled salbutamol may cause a fine tremor of skeletal muscle, particularly in the hands. This effect is common to all beta2-adrenergic stimulants. Adaptation occurs during the first few days of dosing and the tremor usually disappears as treatment continues.
In addition, salbutamol, like other sympathomimetic agents, can cause adverse effects such as drowsiness, flushing, restlessness, irritability, chest discomfort, difficulty in micturition, hypertension, angina, vomiting, vertigo, central nervous system stimulation, hyperactivity in children, unusual taste and drying or irritation of the oropharynx, headache, palpitations, transient muscle cramps, insomnia, nausea, weakness and dizziness.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and that should not be compared to frequencies in clinical trials of another drug.
Adults and Adolescents 12 year of age and older
The adverse reaction information presented in the table below concerning TEVA-SALBUTAMOL HFA is derived from a 6-week, blinded study which compared salbutamol inhalation aerosol (200 mcg four times daily) with a double-blinded matched placebo HFA-inhalation aerosol and an evaluator-blinded marketed active comparator HFA-134a salbutamol inhaler in 172 asthmatic patients 12 to 76 years of age. The table lists the incidence of all adverse events (whether considered by the investigator drug related or unrelated to drug) from this study which occurred at a rate of 3% or greater in the salbutamol HFA inhalation aerosol treatment group and more frequently in the salbutamol HFA inhalation aerosol treatment group than in the matched placebo group. Overall, the incidence and nature of the adverse events reported for salbutamol HFA inhalation aerosol and the marketed active comparator HFA-134a salbutamol inhaler were comparable.
Table 2: Adverse Experience Incidences (% of Patients) in a Six Week Clinical Trial*
| Body System/ Adverse Event (as Preferred Term) | TEVA-SALBUTAMOL HFA (N=58) | Placebo (N=58) | ||
| Body as a Whole | Headache | 7 | 2 | |
| Cardiovascular | Tachycardia | 3 | 0 | |
| Musculoskeletal | Pain | 3 | 0 | |
| Nervous System | Dizziness | 3 | 0 | |
| Respiratory System | Pharyngitis | 14 | 9 | |
| Rhinitis | 5 | 2 | ||
* This table includes all adverse events (whether considered by the investigator drug related or unrelated to drug) which occurred at an incidence rate of at least 3.0% in the TEVA-SALBUTAMOL HFA group and more frequently than in placebo.
Adverse events reported by less than 3% of the patients receiving salbutamol HFA inhalation aerosol but by a greater proportion of salbutamol HFA inhalation aerosol patients than the matched placebo patients, which have the potential to be related to salbutamol HFA inhalation aerosol, included chest pain, infection, diarrhea, glossitis, accidental injury (nervous system), anxiety, dyspnea, ear disorder, ear pain, and urinary tract infection.
In small cumulative dose studies, tremor, nervousness, and headache were the most frequently occurring adverse events.
Paediatric Patients 4- to 11 years of Age:
Adverse events reported in a 3-week pediatric clinical trial comparing the same formulation of salbutamol as in salbutamol HFA inhalation aerosol (200 mcg salbutamol four times daily) to a matching placebo HFA inhalation aerosol occurred at a low incidence rate (no greater than 2% in the active treatment group) and were similar to those seen in adult and adolescent trials.
8.5 Post–Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of salbutamol HFA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Reports have included rare cases of aggravated bronchospasm, lack of efficacy, asthma exacerbation (reported fatal in one case), muscle cramps, and various oropharyngeal side-effects such as throat irritation, altered taste, glossitis, tongue ulceration, and gagging.
The following adverse events have been observed in post-approval use of inhaled salbutamol: urticaria, angioedema, rash, bronchospasm, hoarseness, oropharyngeal edema, and arrhythmias (including atrial fibrillation, supraventricular tachycardia, extrasystoles). In addition, salbutamol, like other sympathomimetic agents, can cause adverse reactions such as: angina, hypertension or hypotension, palpitations, central nervous system stimulation, insomnia, headache, nervousness, tremor, muscle cramps, drying or irritation of the oropharynx, hypokalemia, hyperglycemia, and metabolic acidosis.
9 Drug Interactions
9.4 Drug-Drug Interactions
Table 2 - Established or Potential Drug-Drug Interactions
| Proper Name | Ref | Effect | Clinical comment |
|---|---|---|---|
| Monoamine oxidase inhibitors or tricycle antidepressants | CS | May potentiate action of salbutamol on cardiovascular system | Salbutamol should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants. |
| Other inhaled sympathomimetic bronchodilators or epinephrine | CS | May lead to deleterious cardiovascular effects | Other inhaled sympathomimetic bronchodilators or epinephrine should not be used concomitantly with salbutamol. If additional adrenergic drugs are to be administered by any route to the patient using inhaled salbutamol, the adrenergic drugs should be used with caution. Such concomitant use must be individualized and not given on a routine basis. If regular co administration is required then alternative therapy must be considered. |
| Beta-blockers | CS | May effectively antagonize the action of salbutamol | Beta-adrenergic blocking drugs, especially the non- cardioselective ones, such as propranolol, should not usually be prescribed together. |
| Diuretics | CS | May lead to ECG changes and/or hypokalemia although the clinical significance of these effects is not known. | The ECG changes and/or hypokalemia that may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists especially when the recommended dose of the beta-agonist is exceeded. Caution is advised in the co-administration of beta agonists with non-potassium sparing diuretics. |
| Digoxin | CS | May lead to a decrease in serum digoxin levels, although the clinical significance of these findings for patients with obstructive airways disease who are receiving salbutamol and digoxin on a chronic bases is unclear | Mean decreases of 16-22% in serum digoxin levels were demonstrated after single dose intravenous and oral administration of salbutamol, respectively, to normal volunteers who had received digoxin for 10 days. It would be prudent to carefully evaluate serum digoxin levels in patients who are currently receiving digoxin and salbutamol. |
Legend: C = Case Study; CS = Class Statement; CT = Clinical Trial; T = Theoretical
Because of content of ethanol, there is a theoretical potential for interaction in patients taking disulfiram or metronidazole.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Salbutamol produces bronchodilation through stimulation of beta2-adrenergic receptors in bronchial smooth muscle, thereby causing relaxation of bronchial muscle fibres. This action is manifested by an improvement in pulmonary function as demonstrated by spirometric measurements. At therapeutic doses, salbutamol has little action on the beta1-adrenergic receptors in cardiac muscle.
A measurable decrease in airway resistance is typically observed 5 to 15 minutes after inhalation of salbutamol. The maximum improvement in pulmonary function usually occurs 60 to 90 minutes after salbutamol treatment, and significant bronchodilator activity has been observed to persist for 3 to 6 hours.
10.3 Pharmacokinetics
The systemic levels of salbutamol are low after inhalation of recommended doses. In a crossover study conducted in healthy males and female volunteers, high cumulative doses of salbutamol (1.080 mcg of salbutamol base administered over one hour) yielded mean peak plasma concentrations (Cmax) and systemic exposure (AUCinf) of approximately 4,100 pg/mL and 28,426 pg/mL* hr, respectively compared to approximately 3,900 pg/mL and 28,395 pg/mL* hr, respectively following the same dose of an active HFA-134a salbutamol inhaler comparator. The terminal plasma half-life of salbutamol delivered by salbutamol HFA Inhalation Aerosol was approximately 6 hours. Comparison of the pharmacokinetic parameters demonstrated no differences between the products.
The pharmacokinetic profile of salbutamol HFA Inhalation Aerosol was evaluated in a two-way cross-over study in 11 healthy pediatric volunteers, 4 to 11 years of age. A single dose administration of salbutamol HFA Inhalation Aerosol (180 mcg salbutamol base) yielded a least square mean Cmax and AUC0-∞ of 1.0 ng/mL and 307.2 ng/mL/min, respectively. The least square mean (SE) terminal plasma half-life of salbutamol delivered by Salbutamol Inhalation Aerosol was 166 minutes.
Approximately 10% of an inhaled salbutamol dose is deposited in the lungs. Eighty- five per cent of the remaining salbutamol administered from a metered-dose inhaler is swallowed, however, since the dose is low (100 to 200 mcg), the absolute amount swallowed is too small to be of clinical significance. Salbutamol is only weakly bound to plasma proteins. Results of animal studies indicate that following systemic administration, salbutamol does not cross the blood-brain barrier but does cross the placenta using an in vitro perfused isolated human placenta model. It has been found that between 2% and 3% of salbutamol was transferred from the maternal side to the fetal side of the placenta.
Salbutamol is metabolized in the liver. The principal metabolite in humans is salbutamol-o-sulfate, which has negligible pharmacologic activity. Salbutamol may also be metabolized by oxidative deamination and/or conjugation with glucuronide.
Salbutamol is longer acting than isoprenaline in most patients by any route of administration because it is not a substrate for the cellular uptake processes for catecholamines nor for catechol-O-methyl transferase. Salbutamol and its metabolites are excreted in the urine (>80%) and the feces (5% to 10%). Plasma levels are insignificant after administration of aerosolized salbutamol; the plasma half-life ranges from 3.8 to 7.1 hours.
Propellant HFA-134a is devoid of pharmacological activity except at very high doses in animals (140 to 800 times the maximum human exposure based on comparisons of AUC values), primarily producing ataxia, tremors, dyspnea, or salivation. These are similar to effects produced by the structurally related CFCs, which have been used extensively in metered-dose inhalers.
In animals and humans, propellant HFA-134a was eliminated rapidly in the breath, with no evidence of metabolism or accumulation in the body. Time to maximum plasma concentration (tmax) and mean residence time are both extremely short, leading to a transient appearance of HFA-134a in the blood with no evidence of accumulation.
11 Storage, Stability, and Disposal
Keep out of the reach and sight of children. Store at a temperature between 15°C and 25°C.
12 Special Handling Instructions
The contents of TEVA-SALBUTAMOL HFA are under pressure. The container may explode if heated. Do not place in hot water or near radiators, stoves or other sources of heat. Even when empty, do not puncture or incinerate container.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
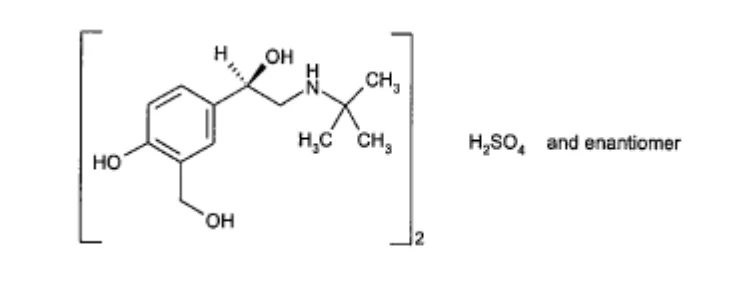
Proper Name: Salbutamol Sulfate
Chemical Name: α1-[(tert-butylamino)methyl]-4-hydroxy-m-xylene-α, α’-diol sulfate (2:1) salt
Molecular Formula and Molecular mass: (C13H21NO3)2 . H2SO4 576.7
Structural Formula:
Physiochemical properties:
Description: Salbutamol is a white or almost white crystalline powder.
Solubility: Soluble in water and slightly soluble in chloroform and ether.
pKa Values: 9.3 and 10.3
pH values: 4.8 to 6.5 (1% aqueous solution)
14 Clinical Trials
14.1 Clinical Trials by Indication
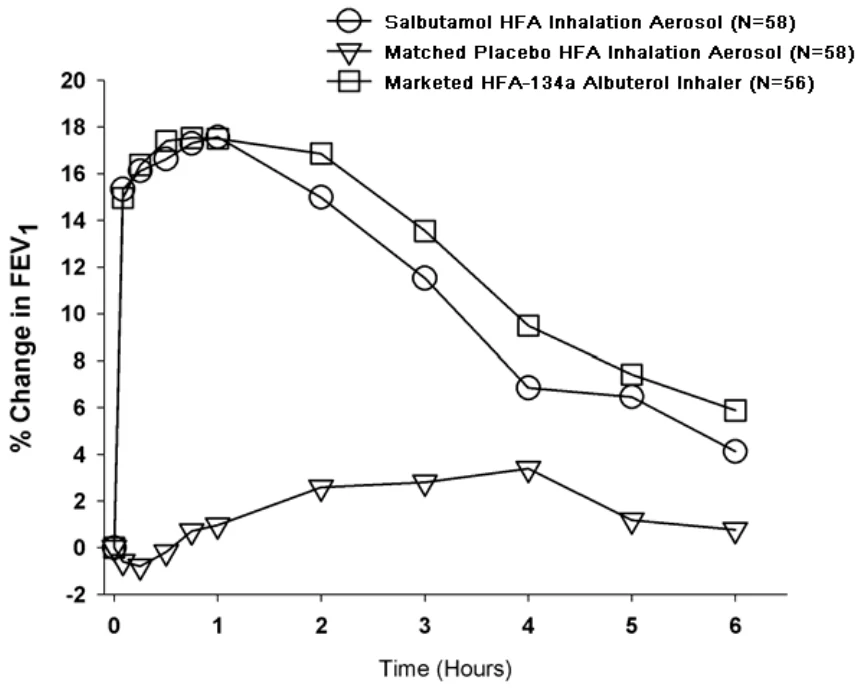
Adult and Adolescent Patients 12 Years of Age and Older: In a 6-week, randomized, double-blind, placebo-controlled trial, salbutamol HFA inhalation aerosol (58 patients) was compared to a matched placebo HFA inhalation aerosol (58 patients) in asthmatic patients 12 to 76 years of age at a dose of 180 mcg salbutamol four times daily. An evaluator-blind marketed active comparator HFA-134a salbutamol inhaler arm (56 patients) was included.
Serial FEV1 measurements, shown below as percent change from test-day baseline at Day 1 and at Day 43, demonstrated that two inhalations of salbutamol HFA inhalation aerosol produced significantly greater improvement in FEV1 over the pre-treatment value than the matched placebo, as well as a comparable bronchodilator effect to the marketed active comparator HFA-134a salbutamol inhaler.
FEV1 as Mean Percent Change from Test-Day Pre-Dose in a 6-Week Clinical Trial
Day 1
Day 43
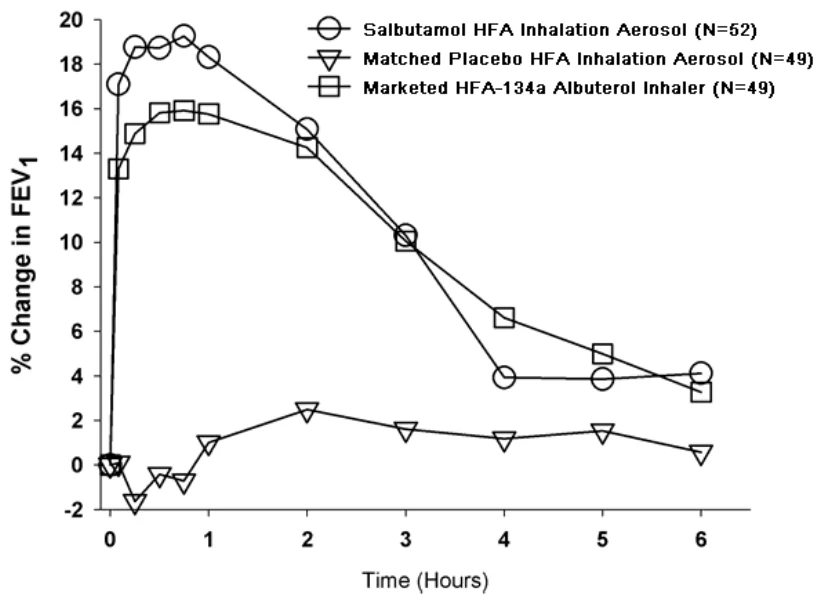
In this study, 31 of 58 patients treated with salbutamol HFA inhalation aerosol achieved a 15% increase in FEV1 within 30 minutes post-dose on Day 1. In these patients, the median time to onset, median time to peak effect, and median duration of effect were 8.2 minutes, 47 minutes, and approximately 3 hours, respectively. In some patients, the duration of effect was as long as 6 hours.
In a placebo-controlled, single-dose, crossover study, salbutamol HFA inhalation aerosol, administered at salbutamol doses of 100, 200 and 300 mcg, produced bronchodilator responses significantly greater than those observed with a matched placebo HFA inhalation aerosol and comparable to a marketed active comparator HFA-134a salbutamol inhaler.
Paediatric Patients 4 to 11 years of age: In a 3-week, randomized, double-blind, placebo-controlled trial, the same formulation of salbutamol as in salbutamol HFA inhalation aerosol (50 patients) was compared to a matched placebo HFA inhalation aerosol (45 patients) in asthmatic children 4 to 11 years of age at a dose of 200 mcg salbutamol four times daily. Serial FEV1 measurements, expressed as the maximum percent change from test-day baseline in percent predicted FEV1 at Day 1 and at Day 22 observed within two hours post-dose, demonstrated that two inhalations of HFA salbutamol sulfate produced significantly greater improvement in FEV1 over the pre-treatment value than the matched placebo.
In this study, 21 of 50 pediatric patients treated with the same formulation of salbutamol as in salbutamol HFA inhalation aerosol achieved a 15% increase in FEV1 within 30 minutes post-dose on Day 1. In these patients, the median time to onset, median time to peak effect and median duration of effect were 10 minutes, 31 minutes, and approximately 4 hours, respectively. In some pediatric patients, the duration of effect was as long as 6 hours.
In a placebo-controlled, single-dose, crossover study in 55 pediatric patients 4 to 11 years of age, salbutamol HFA inhalation aerosol, administered at salbutamol doses of 90 and 180 mcg, was compared with a matched placebo HFA inhalation aerosol. Serial FEV1 measurements, expressed as the baseline-adjusted percent predicted FEV1 observed over 6 hours post-dose, demonstrated that one and two inhalations of salbutamol HFA inhalation aerosol produced significantly greater bronchodilator responses than the matched placebo.
Exercise-Induced Bronchospasm
In a randomized, single-dose, crossover study in 24 adults and adolescents with exercise-induced bronchospasm (EIB), two inhalations of salbutamol HFA taken 30 minutes before exercise prevented EIB for the hour following exercise (defined as maintenance of FEV1 within 80% of post-dose, pre-exercise baseline values) in 83% (20 of 24) of patients as compared to 25% (6 of 24) of patients when they received placebo.
Some of the patients who participated in this clinical trial were using concomitant inhaled or intranasal steroid therapy (no oral or injectable steroids were allowed).
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
Animal Pharmacology
In vitro studies and in vivo pharmacologic studies have demonstrated that salbutamol has a preferential effect on beta2-adrenergic receptors compared with isoprenaline. While it is recognized that beta2-adrenergic receptors are the predominant receptors in bronchial smooth muscle, recent data indicate that there is a population of beta2-adrenergic receptors in the human heart existing in a concentration between 10% and 50%. The precise function of these, however, is not yet established.
The pharmacologic effects of beta-adrenergic agonist drugs, including salbutamol, are at least in part attributable to stimulation through beta-adrenergie receptors of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3’,5’-adenosine monophosphate (cAMP). Increased cAMP levels are associated with relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells.
The muscle-relaxing effect of salbutamol was found to be more prolonged than when the effect was induced by isoprenaline. As suggested from the results of experiments in isolated animal tissues, salbutamol has been shown to produce a substantial bronchodilator effect in the intact animal. In the anaesthetised guinea pig, salbutamol completely prevents acetylcholine-induced bronchospasm at the dose of 100 micrograms/kg intravenously.
Administration of salbutamol aerosol at a dose of 250 mcg/mL for one minute to guinea pigs prevented acetylcholine-induced bronchospasm without any chronotropic effect. A prolonged bronchodilator effect of salbutamol compared to isoprenaline (in terms of mean times to dyspnea following acetylcholine challenge) was observed following oral administration of salbutamol to conscious guinea pigs. The protective action of salbutamol in this case persisted for up to six hours.
In anaesthetised cats and dogs, salbutamol prevented the bronchospasm elicited by vagal stimulation without any significant effect on heart rate and blood pressure. Comparative tests of salbutamol and isoprenaline in isolated dog papillary muscle, guinea pig atrial muscle and human heart muscle have shown that the effect of salbutamol on beta1-adrenergic receptors in the heart is minimal.
In a number of studies using guinea pig atria, it was found that on a weight-to-weight basis, salbutamol was from 2,000 to 2,500 times less active in terms of inotropic effect and 500 times less active in terms of chronotropic effect than isoprenaline. Compared to orciprenaline, salbutamol was about 40 times less active in terms of inotropic effect and four times less potent in terms of chronotropic effect. Salbutamol has been shown to be one-fifth as potent a vasodilator in skeletal muscle as isoprenaline, as measured by effects on hind limb blood flow in the anaesthetised dog. In the perfused rabbit ear, salbutamol was shown to possess only one-tenth the activity of isoprenaline in terms of vasodilating effect. In dogs, salbutamol was shown to increase coronary blood flow, which was subsequently shown to be the result of a direct coronary vasodilating effect of salbutamol.
In six dogs with right-sided cardiac by-pass, salbutamol, given at the dose of 25 mcg/kg, improved left ventricular efficiency and increased coronary blood flow. Recent studies in minipigs, rodents, and dogs recorded the occurrence of cardiac arrhythmias and sudden death (with histologic evidence of myocardial necrosis) when beta-agonists and methylxanthines were administered concurrently. The significance of these findings when applied to humans is currently unknown.
Animal studies show that salbutamol does not pass the blood brain barrier.
Acute Toxicity
| Species (n) | Oral LD50 | Intravenous LD50 |
|---|---|---|
| Mouse (10) | >2000 mg/kg | 72 mg/kg |
| Rat (10) | >2000 mg/kg | 60 mg/kg |
| Rat (n) | Intraperitoneal LD50 |
|---|---|
| Newborn (155) | 216 mg/kg |
| Weanling (100) | 524 mg/kg |
| 2 week old (90) | 437 mg/kg |
The rate of respiration in test animals initially increased but subsequently became abnormally slow and deep. Death, preceded by convulsions and cyanosis, usually occurred within four hours after drug administration.
Rabbits, cats and dogs survived a single dose of 50 mg/kg salbutamol.
Intermediate (Four Months) Toxicity
Rats received salbutamol twice daily, in oral doses from 0.5 to 25 mg/kg, on an increasing scale. The only significant hematological changes were a small increase in hemoglobin and packed cell volume. BUN and SGOT values were elevated while blood glucose and plasma protein levels remained unchanged. Pituitaries had increased amount of PAS-positive material in the cleft at the higher dose levels.
Salbutamol was given to dogs twice daily, in oral doses from 0.05 to 12.5 mg/kg, on an increasing scale. The rate of increase of hemoglobin and packed cell volume was depressed, particularly at higher doses. Leukocyte count decreased after sixteen weeks of treatment at each dose level. Platelet count was increased after eight weeks at the highest dose. No significant biochemical effects were observed. The only significant histological change was the appearance of corpora amylacea in the stomach which was attributed to altered mucus secretion. Inhalation of 1000 mcg of salbutamol CFC 11/12-propelled aerosol twice daily for three months did not produce any morphological changes in the lungs, trachea, lymph nodes, liver or heart.
Long-Term Toxicity
Fifty female, Charles River CD Albino rats received salbutamol orally at 2, 10 and 50 mg/kg/day for one hundred and four weeks; fifty female Charles River CD Sprague Dawley-derived rats received 20 mg/kg/day salbutamol orally for fifty weeks, and fifty female Charles River Long-Evans rats received 20 mg/kg/day salbutamol orally for ninety-six weeks. These rat studies demonstrated a dose-related incidence of mesovarian leiomyomas. No similar tumors were seen in mice.
Mutagenicity
In vitro tests involving four micro-organisms revealed no mutagenic activity.
Carcinogenicity
In a two-year study in the rat, salbutamol sulfate caused a significant dose-related increase in the incidence of benign leiomyomas of the mesovarium at doses corresponding to 111, 555, and 2,800 times the maximum human inhalation dose. In another study, the effect was blocked by the co-administration of propranolol. The relevance of these findings to humans is not known. An 18-month study in mice and a lifetime study in hamsters revealed no evidence of tumorigenicity.
Teratogenicity Studies
Salbutamol has been shown to be teratogenic in mice when given in doses corresponding to 14 times the human aerosol dose; when given subcutaneously in doses corresponding to 0.2 times the maximum human (child weighing 21 kg) oral dose; and when given subcutaneously in doses corresponding to 0.4 times the maximum human oral dose.
A reproduction study in CD-1 mice given salbutamol at doses of 0.025, 0.25, and 2.5 mg/kg subcutaneously, corresponding to 1.4, 14, and 140 times the maximum human aerosol dose respectively, showed cleft palate formation in 5 of 111 (4.5%) fetuses at 0.25 mg/kg and in 10 of 108 (9.3%) fetuses at 2.5 mg/kg. No cleft palates were observed at a dose of 0.025 mg/kg salbutamol. Cleft palate occurred in 22 of 72 (30.5%) fetuses treated with 2.5 mg/kg isoprenaline (positive control).
In rats, salbutamol treatment given orally at 0.5 2.32, 10.75 and 50 mg/kg/day throughout pregnancy resulted in no significant fetal abnormalities. However, at the highest dose level there was an increase in neonatal mortality. Reproduction studies in rats revealed no evidence of impaired fertility.
Salbutamol had no adverse effect when given orally to Stride Dutch rabbits, at doses of 0.5, 2.32 and 10.75 mg/kg/day throughout pregnancy. At a dose of 50 mg/kg/day which represents 2800 times the maximum human inhalation dose, cranioschisis was observed in 7 of 19 (37%) fetuses.
A reproduction study in New Zealand White rabbits using salbutamol sulfate/HFA 134a formulation, revealed enlargement of the frontal portion of the fontanelles in 6 of 95 (6%) and 15 of 107 (14%) fetuses at 28 and 149 mcg/kg, respectively (approximately 2/5 and 2 times, respectively, the maximum recommended human daily dose on a mg/m2 basis) giving plasma levels of approximately 12 and 60 ng/mL, respectively.
17 Supporting Product Monographs
- 1. VENTOLIN HFA (salbutamol pressurised inhalation, suspension, 100 mcg salbutamol (as salbutamol sulfate), Submission Control Number.; 295222, Product Monograph, GSK group of companies, (August 22, 2025).