


Product Monograph - Tevimbra
Recent Major Label Changes
| Section | Date |
|---|---|
| 1 Indications | 2026-04 |
| 4 Dosage and administration, 4.2 Recommended Dose and dose adjustment | 2026-04 |
| 4 Dosage and Administration, 4.3 Reconstitution | 2026-04 |
| 4 Dosage and administration, 4.4 Administration | 2026-04 |
| 7 Warnings and Precautions | 2026-04 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
1 Indications ................................................................................................................... 4
1.1 Pediatrics ............................................................................................................... 4
1.2 Geriatrics ............................................................................................................... 4
2 Contraindications ......................................................................................................... 4
3 Serious Warnings and Precautions Box ........................................................................ 4
4 Dosage and Administration .......................................................................................... 5
4.1 Dosing Considerations ........................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.3 Reconstitution ..................................................................................................... 10
4.4 Administration ..................................................................................................... 10
4.5 Missed Dose ........................................................................................................ 11
5 Overdose.................................................................................................................... 11
6 Dosage Forms, Strengths, Composition and Packaging ............................................... 11
7 Warnings and Precautions .......................................................................................... 12
General ............................................................................................................................ 12
Driving and Operating Machinery ................................................................................... 12
Immune ........................................................................................................................... 12
Infusion-related reactions ............................................................................................... 15
Monitoring and Laboratory Tests .................................................................................... 15
Reproductive Health ....................................................................................................... 15
7.1 Special Populations .............................................................................................. 15
7.1.1 Pregnancy ........................................................................................................ 15
7.1.2 Breastfeeding .................................................................................................. 16
7.1.3 Pediatrics ......................................................................................................... 16
7.1.4 Geriatrics ......................................................................................................... 16
8 Adverse Reactions ...................................................................................................... 16
8.1 Adverse Reaction Overview ................................................................................. 16
8.2 Clinical Trial Adverse Reactions ........................................................................... 17
8.3 Less Common Clinical Trial Adverse Reactions .................................................... 26
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................ 27
8.5 Post-Market Adverse Reactions .......................................................................... 28
9 Drug Interactions ....................................................................................................... 29
9.2 Drug Interactions Overview ................................................................................. 29
9.4 Drug-Drug Interactions ........................................................................................ 29
10 Clinical Pharmacology ................................................................................................ 29
10.1 Mechanism of Action ........................................................................................... 29
10.3 Pharmacokinetics ................................................................................................ 29
10.4 Immunogenicity ................................................................................................... 31
11 Storage, Stability and Disposal ................................................................................... 32
12 Special Handling Instructions ..................................................................................... 32
Part 2: Scientific Information ................................................................................................. 33
13 Pharmaceutical Information ....................................................................................... 33
14 Clinical Trials .............................................................................................................. 33
14.1 Clinical Trials by Indication .................................................................................. 33
15 Microbiology .............................................................................................................. 38
16 Non-Clinical Toxicology .............................................................................................. 38
PATIENT MEDICATION INFORMATION ................................................................................... 40
Part 1: Healthcare Professional Information
1 Indications
TEVIMBRA (tislelizumab for injection)
- in combination with gemcitabine and cisplatin is indicated for the first-line treatment of adult patients with recurrent or metastatic nasopharyngeal carcinoma (NPC).
- as monotherapy, is indicated for the treatment of adult patients with unresectable or metastatic esophageal squamous cell carcinoma (ESCC) after one prior systemic chemotherapy that did not include a PD-(L)1 inhibitor.
1.1 Pediatrics
Pediatrics (below 18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Limited safety and efficacy information is available for TEVIMBRA in patients ≥ 65 years (see 4 Dosage and Administration).
2 Contraindications
TEVIMBRA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing of ingredients, (see 6 Dosage Forms, Strengths, Composition and Packaging).
3 Serious Warnings and Precautions Box
- TEVIMBRA may cause severe and fatal immune-mediated adverse reactions, in any organ system or tissue including: colitis, endocrinopathies, hepatitis, myocarditis, myositis, nephritis with renal dysfunction, organ transplant rejection, pancreatitis, pneumonitis, and severe cutaneous adverse reactions (SCARS e.g. Steven’s Johnson Syndrome, and Toxic Epidermal Necrolysis) (see 7. Warnings and Precautions).
- TEVIMBRA can cause severe or life-threatening infusion-related reactions including hypersensitivity and anaphylaxis (see 7. Warnings and Precautions).
- Fatal and other serious complications can occur in patients who receive allogeneic hematopoietic stem cell transplantation (HSCT) before or after being treated with a PD-1/PD-L1 blocking antibody (see 7. Warnings and Precautions).
4 Dosage and Administration
4.1 Dosing Considerations
TEVIMBRA is administered as an intravenous infusion. Refer to Table 1 for dosing administration time.
No dose reductions of TEVIMBRA are recommended.
TEVIMBRA is for intravenous infusion after dilution (see 4.3 Reconstitution; 4.4 Administration).
4.2 Recommended Dose and Dosage Adjustment
Recommended Dosage for recurrent or metastatic Nasopharyngeal Carcinoma when administered in combination with chemotherapy
- The recommended dose of TEVIMBRA is 200 mg once every 3 weeks in combination with cisplatin and gemcitabine chemotherapy for 4 to 6 cycles. then continued as monotherapy until unacceptable toxicity or disease progression at the preferred dosing interval.
- When administering TEVIMBRA in combination with chemotherapy, administer TEVIMBRA before chemotherapy when both are given on the same day. Refer to the Product Monographs for the chemotherapy agents administered in combination with TEVIMBRA for recommended dosing information, as appropriate.
Recommended Dosage for unresectable or metastatic Esophageal Squamous Cell Carcinoma when administered as Monotherapy
- The recommended dose of TEVIMBRA is 200 mg once every 3 weeks, or 150 mg once every 2 weeks, or 300 mg once every 4 weeks, or 400 mg once every 6 weeks, as monotherapy until unacceptable toxicity or disease progression.
TEVIMBRA should be administered over the recommended infusion duration based on the dosing regimen selected, see 4.4 Administration.
Patients should be treated with TEVIMBRA until disease progression or unacceptable toxicity. For patients who are considered to be deriving clinical benefit despite initial evidence of disease progression, it is recommended to continue TEVIMBRA treatment until disease progression is confirmed.
The recommended dosages, infusion duration, and treatment duration of TEVIMBRA for each authorized indication are provided in Table 1.
Table 1: Recommended Dosages, Infusion Duration, and Treatment Duration for TEVIMBRA by Indication
| Indication | Recommended Dosage of TEVIMBRA | Infusion Duration | Treatment Duration | |||
|---|---|---|---|---|---|---|
| NPC | 200 mg every 3 weeks |
| ||||
| Until disease progression or unacceptable toxicity. | |||||
| ESCC | 150 mg every 2 weeks |
| ||||
| OR | ||||||
| 200 mg every 3 weeks | ||||||
| OR | ||||||
| 300 mg every 4 weeks |
| |||||
| OR | ||||||
| 400 mg every 6 weeks |
| |||||
Dose modifications for adverse reactions
Dose reduction of TEVIMBRA is not recommended.
Recommended treatment modifications to manage immune-related adverse reactions (ARs) are provided in Table 1.
Detailed guidelines for the management of immune-related ARs are described in Section 7 Warnings and Precautions.
Table 2: Recommended treatment modifications for TEVIMBRA
| Immune-related Adverse Reaction | Grade or Severity1 | TEVIMBRA treatment modification | |
| Immune-related Adverse Reaction | Grade or Severity1 | TEVIMBRA treatment modification | |
| Immune-related Adverse Reaction | Grade or Severity1 | TEVIMBRA treatment modification | |
| Immune-related Adverse Reaction | Grade or Severity1 | TEVIMBRA treatment modification | |
| Pneumonitis | Grade 2 | Withhold2 | |
Recurrent Grade 2; Grade 3 or 4 | Permanently discontinue | ||
| Hepatitis | ALT or AST >3 and up to 8 times ULN (or) total bilirubin >1.5 | Withhold2 | |
| and up to 3 times ULN | |||
| ALT or AST >8 times ULN (or) total bilirubin >3 times ULN | Permanently discontinue | ||
| Rash | Grade 3 | Withhold2 | |
| Grade 4 | Permanently discontinue | ||
| Severe cutaneous adverse reactions (SCARs) | Suspected SCARs, including Steven’s Johnson Syndrome (SJS), Toxic Epidermal Necrolysis (TEN | Withhold2 For suspected SCARs (SJS, TEN), do not resume unless SJS/TEN has been ruled out in consultation with appropriate specialist. | |
| Confirmed SCARs, including SJS or TEN | Permanently discontinue | ||
| Colitis | Grade 2 or 3 | Withhold2 | |
Recurrent Grade 3; Grade 4 | Permanently discontinue | ||
| Myositis/Rhabdomyolysis | Grade 2 or 3 | Withhold2 | |
Recurrent Grade 3; Grade 4 | Permanently discontinue | ||
| Endocrinopathies | |||
| Hypothyroidism | Hypothyroidism may be managed with replacement therapy without treatment interruption | ||
| Adrenal insufficiency | Grade 2 adrenal insufficiency and hypophysitis | Consider withholding treatment until controlled by HRT | |
| Grade 3 or 4 adrenal insufficiency or symptomatic hypophysitis | Withhold2 Grade 3 or Grade 4 that improved to Grade ≤2 and is controlled with HRT, if indicated, continuation of TEVIMBRA may be considered after corticosteroid taper, if needed. Otherwise, treatment should be discontinued. Withhold2 | ||
| Hyperthyroidism | Hyperthyroidism Grade ≥3 | Withhold2 Grade 3 or Grade 4 that improved to Grade ≤2 and are controlled with anti-thyroid therapy, if indicated, continuation of TEVIMBRA may be considered after corticosteroid taper, if needed. Otherwise, treatment should be discontinued. | |
| Diabetes mellitus | Diabetes mellitus associated with Grade ≥3 hyperglycemia (glucose >250 mg/dL or >13.9 mmol/L) or associated with ketoacidosis | Withhold2 Grade 3 or 4 that improved to Grade ≤2, with insulin therapy, if indicated, continuation of TEVIMBRA may be considered once metabolic control is achieved. Otherwise, treatment should be discontinued. | |
| Nephritis with renal dysfunction | Grade 2 (creatinine >1.5 to 3 times baseline or >1.5 to 3 times ULN) | Withhold2 | |
| Grade 3 (creatinine >3 times baseline or >3 to 6 times ULN) Grade 4 (creatinine >6 times ULN) | Permanently discontinue | ||
| Myocarditis | Grade 2, 3 or 4 | Permanently discontinue | |
| Neurological toxicities, ie myasthenia gravis, Guillain-Barre syndrome and encephalitis | Grade 2 | Withhold2 | |
| Grade 3 or 4 | Permanently discontinue | ||
| Pancreatitis | Grade 2 pancreatitis | Withhold if clinically significant | |
Grade 3 pancreatitis or Grade 3 or Grade 4 serum amylase or lipase levels increased (>2 times ULN) | Withhold2 | ||
| Grade 4 | Permanently discontinue | ||
| Other immune-related ADRs | Grade 3 | Withhold2 | |
| Recurrent Grade 3; Grade 4 | Permanently discontinue | ||
| Other Adverse Reactions | |||
| Infusion-related reactions | Grade 1 | Consider pre-medication for prophylaxis of subsequent infusion reactions. Slow the rate of infusion by 50% | |
| Grade 2 | Interrupt infusion3 | ||
| Grade 3 or 4 | Permanently discontinue | ||
ALT = alanine aminotransferase, AST = aspartate aminotransferase, BSA = body surface area, HRT= hormone replacement therapy, ULN = upper limit of normal 1Toxicity grades are in accordance with National Cancer Institute Common Terminology Criteria for Adverse Events Version 4.03 (NCI-CTCAE v4). 2 Resume in patients with complete or partial resolution (Grades 0 to 1) after corticosteroid taper. Permanently discontinue if no complete or partial resolution within 12 weeks of initiating corticosteroids or inability to reduce prednisone to 10 mg per day or less (or equivalent) within 12 weeks of initiating corticosteroids. 3 Resume infusion if resolved or decreased to Grade 1 and slow the rate of infusion by 50%. | |||
Special Populations
Pediatrics (below 18 years): Health Canada has not authorized an indication for pediatric use.
Geriatrics (65 years or above): No dose adjustment of TEVIMBRA is required in patients aged 65 years or above (see section 10 Clinical Pharmacology).
Renal Impairment: Based on population pharmacokinetic analysis, no dose adjustment of TEVIMBRA is necessary in patients with mild (CLcr 60 to 89 mL/min) or moderate (CLcr 30 to 59 mL/min) renal impairment. Data from patients with severe renal impairment are too limited to draw conclusions for this population (see section 10 Clinical Pharmacology).
Hepatic Impairment: Based on population pharmacokinetic analysis, no dose adjustment of TEVIMBRA is necessary in patients with mild (bilirubin ≤ ULN and AST > ULN or bilirubin > 1 to 1.5 x ULN and any AST) or moderate (bilirubin > 1.5 to 3 × ULN and any AST) hepatic impairment. Data from patients with severe hepatic impairment are too limited to draw conclusions for this population (see section 10 Clinical Pharmacology).
4.3 Reconstitution
Preparation for Intravenous Infusion
Vials are for single use only. Each vial contains 100 mg of tislelizumab (10 mg/mL). This product must not be mixed with products except sodium chloride, which is used to prepare diluted solution.
- 1.
- 2. Inspect each vial visually for particulate matter and discoloration prior to administration. The concentrate is a clear to slightly opalescent, colorless to slightly yellowish solution. Do not use a vial if the solution is cloudy or if visible particles or discoloration are observed.
- 3. Invert the vials gently, without shaking. Withdraw the required volume of TEVIMBRA from the vials and transfer into an intravenous (I.V.) infusion bag containing approximately 100 mL sodium chloride 9 mg/mL (0.9%) to prepare a diluted solution with a final concentration ranging from 2 to 5 mg/mL. Mix diluted solution by gentle inversion to avoid foaming or excessive shearing of the solution.
4.4 Administration
TEVIMBRA is for intravenous use only.
When TEVIMBRA is administered in combination with chemotherapy, it should be administered before chemotherapy when both are given on the same day. Refer to the Product Monograph for details of any chemotherapy administered in combination with TEVIMBRA.
The diluted solution must be administered by infusion, given via an intravenous line containing a sterile, non-pyrogenic, low-protein binding 0.2 or 0.22 micron in-line or add-on filter.
- For 150 mg and 200 mg doses, administer the initial infusion over 60 minutes. If tolerated, all subsequent infusions may be administered over 30 minutes.
- For 300 mg doses, administer the initial infusion over 90 minutes. If tolerated, all subsequent infusions may be administered over 60 minutes.
- For 400 mg doses, administer the initial infusion over 120 minutes. If tolerated, all subsequent infusions may be administered over 60 minutes.
- TEVIMBRA must not be administered as an intravenous push or single bolus injection.
- Other drugs should not be co-administered through the same infusion line.
- TEVIMBRA does not contain any preservatives. It is recommended to prepare the solution immediately after taking it out of the refrigerator. From a microbiological point of view, once infusion is prepared, it is recommended to use the solution immediately after dilution.
- The diluted solution may be stored at 2°C to 8°C for up to 20 hours, followed by up to four hours at room temperature (25°C and below). This includes the time to reach room temperature as well as completing the infusion.
- The diluted solution must not be frozen.
- TEVIMBRA vials are for single use only. Discard any unused portion left in the vial.
The intravenous line must be flushed at the end of the infusion.
4.5 Missed Dose
If a planned dose of TEVIMBRA is missed, it should be administered as soon as possible. The schedule of administration should be adjusted to maintain the prescribed dosing interval.
5 Overdose
There is no information on overdose with TEVIMBRA. In case of overdose, patients should be closely monitored for signs or symptoms of adverse reactions, and appropriate symptomatic treatment instituted immediately.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition and Packaging
To help ensure the traceability of biologic products, healthcare professionals should record both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 3: Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous infusion | Concentrate for solution for infusion 100 mg tislelizumab /10 mL (10mg/mL) | Citric acid monohydrate, L-histidine, L-histidine hydrochloride monohydrate, polysorbate-20, sodium citrate dihydrate, trehalose dihydrate and water for injection (WFI). |
Each single-use vial contains 100 mg of tislelizumab in 10 mL solution, at a concentration of 10 mg/mL.
Description
TEVIMBRA is a preservative free, clear to slightly opalescent, colorless to slightly yellowish solution. TEVIMBRA concentrate (100mg/10mL) is provided in a single-use, clear Type 1 glass vial, with a grey chlorobutyl stopper with FluroTec coating, and a seal cap with a flip-off button.
Each carton contains one vial.
7 Warnings and Precautions
See 3. Serious Warnings and Precautions Box.
General
TEVIMBRA should be administered under the supervision of a healthcare professional experienced in the treatment of cancer.
Driving and Operating Machinery
No studies on the effects on the ability to drive and to use machines have been performed. Caution when driving or using machines is advised for patients who report dizziness, fatigue, asthenia, and/or malaise during treatment with TEVIMBRA (see 8 Adverse Drug Reactions).
Immune
Severe, including fatal, cases of pneumonitis and hepatitis have been reported. Most immune-related adverse reactions occurring during treatment with TEVIMBRA were reversible and managed with interruptions of TEVIMBRA, administration of corticosteroids and/or supportive care. Immune-related adverse reactions have also occurred after the last dose of TEVIMBRA. Immune-related adverse reactions affecting more than one body system can occur simultaneously.
For suspected immune‑related adverse reactions, adequate evaluation to confirm etiology or exclude alternative etiologies, including infection, should be ensured. Based on the severity of the adverse reaction, TEVIMBRA should be withheld and corticosteroids administered. Administration of other systemic immunosuppressants can be considered in patients whose immune-related adverse reactions are not controlled with corticosteroid therapy (see 4 Dosage And Administration and 8 Adverse Reactions).
Immune-related pneumonitis
Immune-related pneumonitis, including fatal cases, has been reported in patients receiving TEVIMBRA. Patients should be monitored for signs and symptoms of pneumonitis. Patients with suspected pneumonitis should be evaluated with radiographic imaging and infectious or disease-related etiologies should be excluded. Patients with immune-related pneumonitis should be managed according to the treatment modifications as recommended in Table 1 (4.2 Recommended Dose And Dosage Adjustment).
Immune-related hepatitis
Immune-related hepatitis has been reported in patients treated with TEVIMBRA, including fatal cases. Patients should be monitored for signs and symptoms of hepatitis and changes in liver function. Liver function test (LFT) should be performed at baseline and periodically during treatment. Patients with immune-related hepatitis should be managed according to the treatment modifications as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Immune-related skin reactions
Immune-related skin rash or dermatitis has been reported in patients receiving TEVIMBRA. Patients should be monitored for signs and symptoms of suspected skin reactions, and other causes should be excluded. Depending on the severity of the skin adverse reactions, TEVIMBRA should be withheld or permanently discontinued as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Cases of severe cutaneous adverse reactions (SCARs), including erythema multiforme (EM), Stevens-Johnson syndrome (SJS), and toxic epidermal necrolysis (TEN), some with fatal outcome, have been reported in patients receiving TEVIMBRA (see 8 Adverse Reactions). Patients should be monitored for signs or symptoms of SCARs (e.g., a prodrome of fever, flu-like symptoms, mucosal lesions, or progressive skin rash) and other causes should be excluded. For suspected SCARs, TEVIMBRA should be withheld, and the patient should be referred to specialized care for assessment and treatment. If SCARs is confirmed, TEVIMBRA should be permanently discontinued (see 4.2 Recommended Dose And Dosage Adjustment).
Immune-related colitis
Immune-related colitis, frequently associated with diarrhea, has been reported in patients treated with TEVIMBRA. Patients should be monitored for signs and symptoms of colitis. Infectious and disease-related etiologies should be excluded. Patients with immune-related colitis should be managed according to treatment modifications as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Immune-related endocrinopathies
Immune-related endocrinopathies, including thyroid disorders, adrenal insufficiency, hypophysitis and diabetes mellitus have been reported with TEVIMBRA, which may require supportive treatment.
Patients with immune-related endocrinopathies should be managed according to treatment modifications as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Thyroid disorders
Thyroid disorders, including hyperthyroidism, hypothyroidism and thyroiditis have been reported in patients treated with TEVIMBRA. Thyroiditis can present with or without endocrinopathy. Hypothyroidism can follow hyperthyroidism. Patients should be monitored for changes in thyroid function (at the start of treatment, periodically during treatment and as indicated based on clinical evaluation) and clinical signs and symptoms of thyroid disorders. Hypothyroidism may be managed with hormone replacement therapy without treatment interruption and without corticosteroids. Hyperthyroidism may be managed symptomatically (see Table 2: Recommended treatment modifications for TEVIMBRA).
Adrenal insufficiency
Adrenal insufficiency has been reported in patients treated with TEVIMBRA. Patients should be monitored for signs and symptoms of adrenal insufficiency. Monitoring of adrenal function and hormone levels should be considered as clinically indicated. Corticosteroids and hormone replacement should be administered as clinically indicated.
Hypophysitis/hypopituitarism
Hypophysitis/hypopituitarism has been reported in patients treated with TEVIMBRA. Hypophysitis can cause hypopituitarism. Patients should be monitored for signs and symptoms of hypophysitis/hypopituitarism. Monitoring of pituitary function and hormone levels should be considered as clinically indicated. Corticosteroids and hormone replacement should be administered as clinically indicated.
Diabetes mellitus
Diabetes mellitus, including diabetic ketoacidosis, has been reported in patients treated with TEVIMBRA. Patients should be monitored for hyperglycemia or other signs and symptoms of diabetes. Insulin should be administered as clinically indicated for diabetes. In patients with severe hyperglycemia or ketoacidosis (Grade ≥3), TEVIMBRA should be withheld, and anti-hyperglycemic treatment should be administered. Treatment with TEVIMBRA should be resumed when metabolic control is achieved (see 4.2 Recommended Dose And Dosage Adjustment).
Immune-related nephritis with renal dysfunction
Immune-related nephritis with renal dysfunction has been reported in patients treated with TEVIMBRA. Patients should be monitored for changes in renal function (elevated serum creatinine) and other causes of renal dysfunction should be excluded. Patients with immune-related nephritis with renal dysfunction should be managed according to the treatment modifications as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Immune-mediated myocarditis-myositis-myasthenia gravis overlap syndrome
Cases of immune-mediated myocarditis-myositis-myasthenia gravis overlap syndrome (presenting as a concurrent manifestation of either two or all three conditions), some with fatal outcome, have been observed with other immune checkpoint inhibitors. It is important to recognize overlapping symptoms; patients presenting with signs or symptoms of one condition should also be monitored and evaluated for the other two conditions. Early recognition and aggressive management are essential to address associated morbidity and risk of mortality (See 4.2. Recommended Dose and Dosage Adjustment).
Other immune-related ADRs
Other clinically important immune-related ADRs were reported in patients treated with TEVIMBRA: myositis, myocarditis, arthritis, polymyalgia rheumatica, pericarditis, immune thrombocytopenia, encephalitis, myasthenia gravis, Sjogren’s syndrome, Guillain-Barré syndrome, and hemophagocytic lymphohistiocytosis (HLH).
Patients with other immune-related ADRs should be managed according to the treatment modifications as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Solid organ transplant rejection
Solid organ transplant rejection has been reported in the post marketing setting in patients treated with PD-1 inhibitors. Treatment with TEVIMBRA may increase the risk of rejection in solid organ transplant recipients. The benefit of treatment with TEVIMBRA versus the risk of possible organ rejection should be considered in these patients.
Complications of Allogeneic Hematopoietic Stem Cell Transplantation
Cases of graft-versus-host disease (GvHD) have been reported in patients treated with PD-1/PD-L1 inhibitors in association with allogeneic hematopoietic stem cell transplant. This complication may occur despite intervening therapy between PD-1/PD-L1 blockade and the allogeneic HSCT. Follow patients closely for evidence of transplant-related complications and intervene promptly.
Infusion-related reactions
Severe infusion-related reactions (Grade 3 or higher) have been reported in patients receiving TEVIMBRA. Cases of anaphylaxis, including anaphylactic reaction and anaphylactic shock, have been reported in the post marketing setting. Patients should be monitored for signs and symptoms of infusion-related reactions.
Infusion-related reactions should be managed as recommended in Table 1 (see 4.2 Recommended Dose And Dosage Adjustment).
Monitoring and Laboratory Tests
Monitor liver function including AST, ALT, and bilirubin, renal function, pituitary, adrenal and thyroid function prior to initiation and as indicated based on clinical evaluation. Refer to Section 4 Dosage And Administration for recommended dosing adjustments.
Reproductive Health
Fertility
No data are available on the possible effects of TEVIMBRA on fertility.
No reproductive and development toxicity studies have been conducted with tislelizumab. Based on a 3-month repeat-dose toxicity study, there were no notable effects in the male and female reproductive organs in cynomolgus monkeys when given tislelizumab (See 16 Non-Clinical Toxicology).
Contraception
Sexually active females of reproductive potential should be advised to use effective contraception (methods that result in less than 1 % pregnancy rates) during treatment with TEVIMBRA and for at least 4 months after the last dose of TEVIMBRA.
7.1 Special Populations
7.1.1 Pregnancy
There are no available data on the use of TEVIMBRA in pregnant women. Based on its mechanism of action, TEVIMBRA can cause fetal harm when administered to a pregnant woman. Animal studies have demonstrated that inhibition of PD-1/PD-L1 pathway can lead to increased risk of immune-related rejection of the developing fetus resulting in fetal death.
Human IgG4 (immunoglobulins) are known to cross the placental barrier. Therefore, TEVIMBRA, being an IgG4 variant, has the potential to be transmitted from the mother to the developing fetus.
For women of childbearing potential, pregnancy status should be established prior to initiating TEVIMBRA. Women should be advised to use highly effective contraception (methods that result in less than 1% pregnancy rates) and take active measures to avoid pregnancy while undergoing TEVIMBRA treatment and for at least 4 months after the last dose (See 16 Non-Clinical Toxicology).
If TEVIMBRA is used during pregnancy or if the patient becomes pregnant while taking TEVIMBRA, the patient should be apprised of the potential hazard to the fetus.
7.1.2 Breastfeeding
It is unknown whether TEVIMBRA is excreted in human milk. Its effects on breast-fed newborns/infants and on milk production are also unknown.
Because of the potential for serious adverse reactions in breastfed children from TEVIMBRA, women should be advised not to breastfeed during treatment and for at least 4 months after the last dose of TEVIMBRA.
7.1.3 Pediatrics
Pediatrics (below 18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Limited safety and efficacy information is available for TEVIMBRA in patients ≥ 65 years; therefore, efficacy and safety is not well established in patients over 65 years of age.
8 Adverse Reactions
8.1 Adverse Reaction Overview
The following clinically significant treatment-emergent adverse events have been observed in patients treated with TEVIMBRA and are detailed under 7 Warnings And Precautions:
- Severe and fatal immune-mediated adverse reactions (see 7. Warnings and Precautions, Immune and 8.2 Clinical Trial Adverse Reactions).
- Infusion-related reactions (see 7. Warnings and Precautions, Immune and 8.2 Clinical Trial Adverse Reactions).
The overall safety profile of TEVIMBRA is based on pooled data from 1952 patients receiving TEVIMBRA as monotherapy across multiple tumor types and 133 patients receiving TEVIMBRA in combination with gemcitabine and cisplatin for NPC.
Tislelizumab as Monotherapy
In the monotherapy pool the most common treatment-emergent adverse events (TEAEs) (≥ 10%) were anemia (26%), AST increased (25%), ALT increased (22%), pyrexia (16%), cough (15%), decreased appetite (15%), weight decreased (15%), blood bilirubin increased (13%), hypoalbuminemia (13%), hypothyroidism (13%), constipation (12%), pruritus (11%), asthenia (11%), rash (10%), diarrhea (10%), and nausea (10%).
Tislelizumab in Combination with Gemcitabine and Cisplatin
In combination therapy with gemcitabine and cisplatin, the most common treatment-emergent adverse events (TEAEs) (≥ 20%) were anemia (87%), neutrophil count decreased, (62%), white blood cell count decreased (62%), nausea (59%), platelet count decreased (54%), decreased appetite (48%), vomiting (41%), neutropenia (35%), constipation (35%), leukopenia (35%), hyponatremia (31%), hypothyroidism (31%), AST increased (29%), ALT increased (29%), pyrexia (26%), rash (26%), blood creatinine increased (24%), hypokalemia (23%), cough (22%), malaise (22%) and pruritus (22%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Nasopharyngeal Carcinoma (NPC)
The safety of TEVIMBRA was evaluated in patients with recurrent or metastatic NPC in RATIONALE-309. Patients received tislelizumab 200 mg once every 3 weeks in combination with gemcitabine plus cisplatin (T+GC arm). The median duration of exposure to tislelizumab was 10.51 months (range 0.3 to 53.1 months).
Serious treatment-emergent adverse events (TEAEs) occurred in 35% of patients who received tislelizumab; the most frequent serious adverse reactions (≥2%) were platelet count decreased (6.8%), sepsis (3%), thrombocytopenia (3%), anemia, neutrophil count decreased, and white blood cell count decreased (2%). In the placebo plus chemotherapy arm, serious TEAEs occurred in 35.4% of patients, the most frequent TEAEs (>2%) were platelet count decreased, neutrophil count decreased, white blood cell count decreased, anemia, thrombocytopenia, leukopenia, pneumonia, and hypokalemia. There were 6 fatal TEAEs in the tislelizumab arm: depressed level of consciousness (1), pharyngeal hemorrhage (1), pneumonia aspiration and hypoxia (1), myelodysplastic syndrome (1), accidental death (1), and death (1), and 2 in the placebo arm of the trial: arrhythmia (1) and hypernatremia (1).
TEAEs leading to discontinuation of tislelizumab occurred in 9% of patients; the most common (>1%) TEAE resulting in permanent discontinuation was myocarditis (1.5%). TEAEs leading to discontinuation of placebo occurred in 5% of patients in the placebo plus chemotherapy arm, with no TEAE occurring at an incidence of more than 1%.
TEAEs leading to the dose interruption of tislelizumab occurred in 50% of patients; the most common TEAEs leading to dose interruptions of tislelizumab (≥2%) were anemia (10%), neutropenia (9%), white blood cell count decreased (9%), leukopenia (8%), neutrophil count decreased (7%), platelet count decreased (6%), ALT increased (3%), AST increased (3%), and pneumonia (2%). In the placebo plus chemotherapy arm, 41 % of patients experienced a dose reduction due to TEAEs, the most common (≥2%) were anemia (12%), white blood cell count decreased (11%), neutrophil count decreased (11%), platelet count decreased (9%), leukopenia (8%), neutropenia (6%), lymphocyte count decreased (2%), and pneumonia (2%).
Treatment-emergent adverse events are listed in Table 4.
Table 4: Treatment-Emergent Adverse Events with Incidence ≥ 5% by System Organ Class and Preferred Term in RATIONALE-309 (Safety Analysis Set)
Tislelizumab + Gemcitabine + Cisplatin (N = 133) | Placebo + Gemcitabine + Cisplatin (N = 130) | ||||||||||||
Tislelizumab + Gemcitabine + Cisplatin (N = 133) | Placebo + Gemcitabine + Cisplatin (N = 130) | ||||||||||||
| System Organ Class Preferred Term | All Grades n (%) | Grade 3-4 n (%) | All Grades n (%) | Grade 3-4 n (%) | |||||||||
| System Organ Class Preferred Term | All Grades n (%) | Grade 3-4 n (%) | All Grades n (%) | Grade 3-4 n (%) | |||||||||
| Blood and lymphatic system disorders | 120 (90) | 63 (47) | 122 (94) | 63 (49) | |||||||||
| Anemia | 116 (87) | 41 (31) | 118 (91) | 43 (33) | |||||||||
| Neutropenia | 47 (35) | 30 (23) | 38 (29) | 23 (18) | |||||||||
| Leukopenia | 46 (35) | 29 (22) | 45 (35) | 20 (15) | |||||||||
| Thrombocytopenia | 15 (11) | 6 (5) | 17 (13) | 10 (8) | |||||||||
| Ear and labyrinth disorders | 18 (14) | 1 (1) | 20 (15) | 1 (1) | |||||||||
| Tinnitus | 11 (8) | 1 (1) | 8 (6) | 0 (0) | |||||||||
| Endocrine disorders | 51 (38) | 1 (1) | 27 (21) | 0 (0) | |||||||||
| Hypothyroidism* | 47 (35) | 1 (1) | 26 (20) | 0 (0) | |||||||||
| Gastrointestinal disorders | 114 (86) | 2 (2) | 118 (91) | 6 (5) | |||||||||
| Nausea | 78 (59) | 0 (0) | 94 (72) | 2 (2) | |||||||||
| Vomiting | 55 (41) | 1 (1) | 69 (53) | 2 (2) | |||||||||
| Constipation | 46 (35) | 0 (0) | 60 (46) | 0 (0) | |||||||||
| Diarrhea* | 22 (17) | 0 (0) | 14 (11) | 1 (1) | |||||||||
| Abdominal pain* | 19 (14) | 0 (0) | 23 (18) | 0 (0) | |||||||||
| Abdominal distension | 18 (14) | 0 (0) | 15 (12) | 0 (0) | |||||||||
| Dry mouth | 17 (13) | 0 (0) | 6 (5) | 0 (0) | |||||||||
| Mouth ulceration | 10 (8) | 0 (0) | 3 (2) | 0 (0) | |||||||||
| Toothache | 9 (7) | 0 (0) | 4 (3) | 0 (0) | |||||||||
| Gingival pain | 7 (5) | 0 (0) | 0 (0) | 0 (0) | |||||||||
| Stomatitis | 5 (4) | 0 (0) | 8 (6) | 1 (1) | |||||||||
| General disorders and administration site conditions | 90 (68) | 5 (4) | 77 (59) | 3 (2) | |||||||||
| Fatigue* | 57 (43) | 2 (2) | 54 (42) | 2 (2) | |||||||||
| Pyrexia | 35 (26) | 2 (2) | 13 (10) | 0 (0) | |||||||||
| Chest discomfort | 9 (7) | 0 (0) | 8 (6) | 0 (0) | |||||||||
| Oedema peripheral | 5 (4) | 0 (0) | 8 (6) | 1 (1) | |||||||||
| Infections and infestations | 62 (47) | 14 (11) | 35 (27) | 9 (7) | |||||||||
| Upper respiratory tract infection | 22 (17) | 0 (0) | 12 (9) | 1 (1) | |||||||||
| Pneumonia* | 13 (10) | 3 (2) | 7 (5) | 4 (3) | |||||||||
| Otitis media | 7 (5) | 0 (0) | 2 (2) | 0 (0) | |||||||||
| Investigations | 122 (92) | 69 (52) | 114 (88) | 75 (58) | |||||||||
| Weight decreased | 19 (14) | 0 (0) | 14 (11) | 0 (0) | |||||||||
| Metabolism and nutrition disorders | 115 (87) | 22 (17) | 106 (82) | 14 (11) | |||||||||
| Decreased appetite | 64 (48) | 1 (1) | 65 (50) | 1 (1) | |||||||||
| Hyponatraemia | 41 (31) | 4 (3) | 37 (29) | 1 (1) | |||||||||
| Hypokalaemia | 30 (23) | 7 (5) | 30 (23) | 8 (6) | |||||||||
| Hypocalcaemia | 25 (19) | 1 (1) | 17 (13) | 0 (0) | |||||||||
| Hyperuricaemia | 24 (18) | 2 (2) | 25 (19) | 1 (1) | |||||||||
| Hypoalbuminaemia | 22 (17) | 1 (1) | 29 (22) | 0 (0) | |||||||||
| Hypomagnesaemia | 22 (17) | 3 (2) | 16 (12) | 3 (2) | |||||||||
| Hypochloraemia | 16 (12) | 0 (0) | 22 (17) | 0 (0) | |||||||||
| Hypertriglyceridaemia | 12 (9) | 3 (2) | 6 (5) | 0 (0) | |||||||||
| Hypoproteinaemia | 12 (9) | 0 (0) | 7 (5) | 0 (0) | |||||||||
| Hypophosphataemia | 8 (6) | 0 (0) | 8 (6) | 0 (0) | |||||||||
| Hyperglycaemia | 7 (5) | 0 (0) | 4 (3) | 0 (0) | |||||||||
| Musculoskeletal and connective tissue disorders | 48 (36) | 2 (2) | 48 (37) | 1 (1) | |||||||||
| Musculoskeletal pain* | 41 (31) | 1 (1) | 42 (32) | 1 (1) | |||||||||
| Muscular weakness | 10 (8) | 0 (0) | 5 (4) | 0 (0) | |||||||||
| Nervous system disorders | 54 (41) | 7 (5) | 49 (38) | 5 (4) | |||||||||
| Dizziness | 23 (17) | 1 (1) | 19 (15) | 0 (0) | |||||||||
| Hypoaesthesia | 20 (15) | 0 (0) | 20 (15) | 0 (0) | |||||||||
| Headache | 15 (11) | 1 (1) | 23 (18) | 0 (0) | |||||||||
| Psychiatric disorders | 17 (13) | 0 (0) | 20 (15) | 0 (0) | |||||||||
| Insomnia | 14 (11) | 1 (1) | 17 (13) | 0 (0) | |||||||||
| Respiratory, thoracic and mediastinal disorders | 66 (50) | 1 (1) | 40 (31) | 1 (1) | |||||||||
| Cough* | 43 (32) | 0 (0) | 19 (15) | 0 (0) | |||||||||
| Hiccups | 17 (13) | 0 (0) | 10 (8) | 0 (0) | |||||||||
| Oropharyngeal pain | 12 (9) | 0 (0) | 10 (8) | 0 (0) | |||||||||
| Rhinorrhoea | 8 (6) | 0 (0) | 2 (2) | 0 (0) | |||||||||
| Nasal congestion | 7 (5) | 0 (0) | 2 (2) | 0 (0) | |||||||||
| Skin and subcutaneous tissue disorders | 61 (46) | 6 (5) | 53 (41) | 0 (0) | |||||||||
| Rash* | 40 (30) | 6 (5) | 40 (31) | 0 (0) | |||||||||
| Pruritus | 29 (22) | 0 (0) | 18 (14) | 0 (0) | |||||||||
| Alopecia | 10 (8) | 0 (0) | 11 (9) | 0 (0) | |||||||||
| Vascular disorders | 37 (28) | 1 (1) | 33 (25) | 4 (3) | |||||||||
| Hemorrhage* | 19 (14) | 0 (0) | 17 (13) | 0 (0) | |||||||||
*Grouped terms
Abdominal pain includes Abdominal discomfort, Abdominal pain, Abdominal pain lower, and Abdominal pain upper.
Cough includes Cough, and Productive cough.
Diarrhea includes Colitis, and Diarrhea.
Fatigue includes Asthenia, Fatigue, and Malaise.
Hemorrhage includes Epistaxis, Gingival bleeding, Hematuria, Hemoptysis, and Upper gastrointestinal hemorrhage.
Hypothyroidism includes Blood thyroid stimulating hormone increased, and Hypothyroidism.
Musculoskeletal pain includes Arthralgia, Arthritis, Back pain, Bone pain, Musculoskeletal chest pain, Musculoskeletal pain, Myalgia, Neck pain, Non-cardiac chest pain, Pain in extremity, and Spinal pain.
Pneumonia includes Pneumonia and Pneumonia aspiration.
Rash includes Dermatitis, Dermatitis acneiform, Dermatitis allergic, Eczema, Erythema, Rash, Rash maculo-papular.
Previously Treated Unresectable or Metastatic Esophageal Squamous Cell Carcinoma (ESCC)
The safety of TEVIMBRA was evaluated in RATIONALE-302 in 255 patients with unresectable or metastatic ESCC.
Patients received either TEVIMBRA 200 mg by intravenous infusion or investigator’s choice of chemotherapy: paclitaxel 135-175 mg/m2 every 3 weeks or 80-100 mg/m2 weekly, docetaxel 75 mg/m2 every 3 weeks, or irinotecan 125 mg/m2. The median duration of exposure was 2.8 months (range: 0.2 to 28.3 months) in TEVIMBRA-treated patients and 1.5 months (range: 0.2 to 19.2 months) in paclitaxel-, docetaxel-, or irinotecan-treated patients.
Serious adverse events occurred in 42.7% of patients on TEVIMBRA compared to 44.2% of patient on ICC; the most common serious adverse events occurring at ≥2% in the TEVIMBRA arm were: pneumonia (7.5%), dysphagia (5.1%), esophageal obstruction (2.0%), and pneumonitis (2.0%).
Fatal adverse events occurred in 7% of patients in the Tevimbra arm: including the following which occurred in more than one patient: pneumonia/pneumonitis (5 patients), hemorrhage (3 patients), and death of unknown cause (3 patients). Fatal adverse events occurred in 5.8% of patients in the ICC arm including the following which occurred in more than one patient: septic shock (3 patients) and death of unknown cause (3 patients).
Adverse events leading to discontinuation were reported in 19.2% of patients in the TEVIMBRA arm compared to 26.7% in the ICC arm. The most frequent adverse events (≥1%) leading to discontinuation in the TEVIMBRA arm were pneumonia (2.0%), pneumonitis (1.2%), immune-mediated pneumonitis (1.2%), and upper gastrointestinal haemorrhage (1.2%).The most frequent adverse events (≥1%) leading to discontinuation in the ICC arm were diarrhoea (2.1%), asthenia (1.7%), pneumonia (1.7%), febrile neutropenia (1.7%), malaise (1.3%), acquired tracheo-oesophageal fistula (1.3%), pleural effusion (1.3%), septic shock (1.3%), and decreased appetite (1.3%).
The incidence of adverse events leading to dose interruption in the TEVIMBRA arm was 22.7% compared to 47.9% in ICC arm. The most frequently reported adverse events (≥ 2%) leading to dose interruption in the TEVIMBRA arm were pneumonia (4.7%), and pneumonitis (2.7%). The most frequently reported adverse events (≥ 2%) leading to dose interruption in the ICC arm were neutrophil count decreased (16.7%), white blood cell count decreased (8.3%), decreased appetite (5.0%), nausea (4.6%), vomiting (4.2%), neutropenia (4.2%), diarrhoea (4.2%), asthenia (4.2%), malaise (3.8%), leukopenia (3.3%), peripheral sensory neuropathy (2.5%), fatigue (2.5%), and pneumonia (2.1%).
Treatment-emergent adverse events are listed in Table 5.
Table 5: Treatment-Emergent Adverse Events with Incidence ≥5% in Patients with Unresectable or Metastatic ESCC in RATIONALE-302 (Safety Analysis Set)
| Tislelizumab (N = 255) n (%) | ICC# (N = 240) n (%) | ||||||||||||||||
| Tislelizumab (N = 255) n (%) | ICC# (N = 240) n (%) | ||||||||||||||||
| System Organ Class Preferred Term | Any Grade | Grade 3-4 | Any Grade | Grade 3-4 | |||||||||||||
| System Organ Class Preferred Term | Any Grade | Grade 3-4 | Any Grade | Grade 3-4 | |||||||||||||
| Blood and lymphatic system disorders | 95 (37) | 18 (7) | 140 (58) | 55 (23) | |||||||||||||
| Anemia | 80 (31) | 15 (6) | 109 (45) | 26 (11) | |||||||||||||
| Leukopenia | 9 (4) | 0 (0.0) | 30 (13) | 17 (7) | |||||||||||||
| Neutropenia | 2 (1) | 1 (0.4) | 31 (13) | 16 (7) | |||||||||||||
| Febrile neutropenia | 0 (0) | 0 (0) | 12 (5) | 10 (4) | |||||||||||||
| Endocrine disorders | 45 (18) | 1 (0.4) | 3 (1) | 0 (0) | |||||||||||||
| Hypothyroidism* | 35 (14) | 1 (0.4) | 2 (1) | 0 (0) | |||||||||||||
| Gastrointestinal disorders | 148 (58) | 34 (13) | 170 (71) | 38 (16) | |||||||||||||
| Constipation | 41 (16) | 0 (0) | 45 (19) | 1 (0.4) | |||||||||||||
| Nausea | 37 (15) | 1 (0.4) | 72 (30) | 8 (3) | |||||||||||||
| Diarrhea* | 33 (13) | 3 (1) | 76 (32) | 16 (7) | |||||||||||||
| Dysphagia | 30 (12) | 17 (7) | 20 (8) | 7 (3) | |||||||||||||
| Abdominal pain* | 28 (11) | 2 (1) | 39 (16) | 4 (2) | |||||||||||||
| Vomiting | 27 (11) | 2 (1) | 48 (20) | 9 (4) | |||||||||||||
| Gastroesophageal reflux disease | 14 (6) | 1 (0.4) | 12 (5) | 0 (0) | |||||||||||||
| Stomatitis | 9 (4) | 1 (0.4) | 14 (6) | 0 (0) | |||||||||||||
| General disorders and administration site conditions | 118 (46) | 10 (4) | 148 (62) | 18 (8) | |||||||||||||
| Fatigue* | 75 (29) | 6 (2) | 111(46) | 15 (6) | |||||||||||||
| Pyrexia | 41 (16) | 1 (0.4) | 34 (14) | 0 (0.0) | |||||||||||||
| Infections and infestations | 80 (31) | 21 (8) | 77 (32) | 26 (11) | |||||||||||||
| Pneumonia* | 44 (17) | 16 (6) | 29 (12) | 16 (7) | |||||||||||||
| Investigations | 133 (52) | 25 (10) | 165 (69) | 90 (38) | |||||||||||||
| Weight decreased | 62 (24) | 3 (1) | 45 (19) | 0 (0.0) | |||||||||||||
| Metabolism and nutrition disorders | 123 (48) | 29 (11) | 141 (59) | 31 (13) | |||||||||||||
| Decreased appetite | 42 (17) | 2 (1) | 84 (35) | 10 (4) | |||||||||||||
| Hypoalbuminaemia | 36 (14) | 2 (1) | 30 (13) | 2 (1) | |||||||||||||
| Hyponatraemia | 32 (13) | 14 (6) | 33 (14) | 10 (4) | |||||||||||||
| Hypokalaemia | 22 (9) | 2 (1) | 22 (9) | 6 (3) | |||||||||||||
| Hyperglycaemia | 17 (7) | 0 (0) | 8 (3) | 1 (0.4) | |||||||||||||
| Hypoproteinaemia | 13 (5) | 0 (0) | 8 (3) | 1 (0.4) | |||||||||||||
| Musculoskeletal and connective tissue disorders | 70 (28) | 5 (2) | 64 (27) | 4 (2) | |||||||||||||
| Musculoskeletal pain* | 66 (26) | 3 (1) | 59(25) | 3 (1) | |||||||||||||
| Nervous system disorders | 31 (12) | 6 (2) | 62 (26) | 8 (3) | |||||||||||||
| Dizziness | 11 (4) | 0 (0) | 19 (8) | 2 (1 | |||||||||||||
| Peripheral sensory neuropathy | 2 (1) | 0 (0) | 23 (10) | 2 (1) | |||||||||||||
| Psychiatric disorders | 28 (11) | 0 (0.0) | 27 (11) | 1 (0.4) | |||||||||||||
| Insomnia | 21 (8) | 0 (0.0) | 17 (7) | 0 (0) | |||||||||||||
| Respiratory, thoracic and mediastinal disorders | 98 (38) | 19 (8) | 79 (33) | 14 (6) | |||||||||||||
| Cough* | 56 (22) | 1 (0.4) | 39 (16) | 1 (0.4) | |||||||||||||
| Dyspnoea | 25 (10) | 6 (2) | 19 (8) | 3 (1) | |||||||||||||
| Pneumonitis | 13 (5) | 5 (2) | 4 (2) | 2 (1) | |||||||||||||
| Skin and subcutaneous tissue disorders | 62 (24) | 2 (1) | 67 (28) | 0 (0.0) | |||||||||||||
| Rash* | 38 (15) | 2 (1) | 15 (6) | 0 (0.0) | |||||||||||||
| Pruritus | 25 (10) | 0 (0) | 11 (5) | 0 (0.0) | |||||||||||||
| Alopecia | 1 (0.4) | 0 (0) | 42 (18) | 0 (0.0) | |||||||||||||
| Vascular Disorders | 28 (11) | 9 (4) | 17 (7) | 0 (0) | |||||||||||||
| Hemorrhage* | 30 (12) | 4 (2) | 23 (10) | 6 (3) | |||||||||||||
| Hypertension | 13 (5) | 5 (2) | 6 (3) | 0 (0) | |||||||||||||
#ICC = investigator’s choice of chemotherapy
*Grouped terms
Abdominal pain includes Abdominal discomfort, Abdominal pain, Abdominal pain lower, Abdominal pain upper, Gastrointestinal pain.
Cough includes Cough, Productive cough.
Diarrhea includes Colitis, Diarrhea.
Fatigue includes Asthenia, Fatigue, Malaise.
Hemorrhage includes Epistaxis, Gastric hemorrhage, Gastrointestinal hemorrhage, Gingival bleeding, Hematuria, Hemoptysis, Oesophageal hemorrhage, Procedural hemorrhage, Pulmonary hemorrhage, Rectal hemorrhage, Stoma site hemorrhage, Tracheal hemorrhage, Upper gastrointestinal hemorrhage.
Hypothyroidism includes Blood thyroid stimulating hormone increased, Hypothyroidism.
Musculoskeletal pain includes Arthralgia, Arthritis, Back pain, Bone pain, Musculoskeletal chest pain, Musculoskeletal pain, Myalgia, Neck pain, Non-cardiac chest pain, Pain in extremity, Spinal pain.
Pneumonia includes Lower respiratory tract infection, Pneumonia, Pneumonia aspiration, Pneumonia bacterial.
Rash includes Dermatitis, Dermatitis acneiform, Dermatitis allergic, Eczema, Erythema, Psoriasis, Rash, Rash follicular, Rash maculo-papular, Rash pruritic.
Additional Information on Selected Adverse Reactions
The selected adverse reactions described below are based on the safety of TEVIMBRA 200 mg Q3W in combination with gemcitabine and cisplatin in 133 patients with metastatic or recurrent, locally advanced nasopharyngeal carcinoma treated in the RATIONALE 309 trial, and on the safety of TEVIMBRA 200 mg/kg Q3W as a single agent in the monotherapy pool consisting of 1952 patients across various tumor types. (see 8.1.Adverse Reaction Overview for additional details). For information on management of these adverse reactions, see 4.2 Recommended Dose And Dosage Adjustment and 7 Warnings and Precautions.
Immune-mediated Pneumonitis
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated pneumonitis occurred in 2.3%) of patients receiving TEVIMBRA. All AEs were ≤ Grade 2. One patient received corticosteroid treatment and pneumonitis resolved in one of these patients. No patients discontinued due to imAEs.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related pneumonitis occurred in 5.1% of patients, including Grade 1 (1.3%), Grade 2 (2.1%), Grade 3 (1.3%), Grade 4 (0.3%) and Grade 5 (0.1%) events.
In patients treated with tislelizumab as monotherapy receiving prior radiotherapy,immune-related pneumonitis occurred in 8.4% of patients, including Grade 1 (1.9%), Grade 2 (3.5%), Grade 3 (2.7%), Grade 4 (0.2%), and Grade 5 (0.2%) events.
Tislelizumab was permanently discontinued in 1.8% of patients and tislelizumab treatment was interrupted in 1.9% of patients and 47.0% of patients the pneumonitis resolved.
Immune-mediated Colitis
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated colitis occurred in 0.8%) of patients receiving TEVIMBRA. The one reported imAE was ≤Grade 2. No patients discontinued due to imAEs.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related colitis occurred in 0.6% of patients, including Grade 2 (0.4%) and Grade 3 (0.2%) events.
Tislelizumab was permanently discontinued in 0.1% of patients and tislelizumab treatment was interrupted in 0.4% of patients, and 81.8% of patients the event resolved.
Hepatotoxicity and Immune-mediated Hepatitis
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated hepatitis occurred in 0.8% of patients receiving TEVIMBRA, the one reported imAE was Grade 1. No patients discontinued due to imAEs.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related hepatitis occurred in 1.2% of patients, including Grade 1 (0.1%), Grade 2 (0.2%), Grade 3 (0.6%), and Grade 4 (0.3%) events.
Tislelizumab was permanently discontinued in 0.3% of patients and tislelizumab treatment was interrupted in 0.8% of patients for immune-related hepatitis, and in 60.9% of patients with hepatitis the event resolved.
Immune-mediated Endocrinopathies
Adrenal Insufficiency
TEVIMBRA in combination with gemcitabine and cisplatin:
No imAEs of adrenal insufficiency were reported.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, adrenal insufficiency occurred in 0.5% of patients, including Grade 2 (0.3%), Grade 3 (0.2%), and Grade 4 (0.1%) events.
Tislelizumab was not permanently discontinued in any patient and tislelizumab treatment was interrupted in 0.4% of patients, and in 30.0% of patients with adrenal insufficiency the event resolved.
Hypophysitis
TEVIMBRA in combination with gemcitabine and cisplatin:
Hypophysitis occurred in 0.8% of the patients receiving combination therapy. The one reported imAE was Grade 2. No patients discontinued due to imAEs.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, hypophysitis (Grade 2) occurred in 0.3% of patients.
Tislelizumab was not permanently discontinued in any patients and tislelizumab treatment was not interrupted in any patients. Twenty percent (20%) of patients with hypophysitis, the event resolved.
Thyroid Disorders
TEVIMBRA in combination with gemcitabine and cisplatin:
Thyroiditis was not reported as an imAE.
Hyperthyroidism occurred in 4.5% of patients receiving TEVIMBRA in combination with gemcitabine and cisplatin. All AEs were ≤ Grade 2, 1 patient required hormone therapy, in 5 of 6 patients the event resolved. No patients discontinued due to imAEs.
Hypothyroidism occurred in 29.3% of patients receiving TEVIMBRA in combination with gemcitabine and cisplatin. There were 38 patients who experienced AE of Grade 1 or 2. One patient experienced an AE of Grade 3 which led to modified treatment, 29/39 patients required hormone replacement therapy, in 16 patients the event fully resolved, and 2 patients discontinued treatment. No patients discontinued due to imAEs.
TEVIMBRA as monotherapy:
Thyroiditis occurred in 1.1% of patients treated with tislelizumab as monotherapy, including Grade 1 (0.5%) and Grade 2 (0.6%) events.
Tislelizumab was not permanently discontinued in any patient and tislelizumab treatment was interrupted in 0.2% of patients and in 38.1% of patients with thyroiditis, the event resolved.
Hyperthyroidism occurred in 5.1% of patients treated with tislelizumab as monotherapy, including Grade 1 (4.4%) and Grade 2 (0.7%) events.
Tislelizumab was permanently discontinued in 0.1% of patients and tislelizumab treatment was interrupted in 0.3% of patients and in 77.0% of patients with hyperthyroidism, the event resolved.
Hypothyroidism occurred in 13.8% of patients treated with tislelizumab as monotherapy, including Grade 1 (6.4%), Grade 2 (7.3%), Grade 3 (0.1%), and Grade 4 (0.1%) events.
Tislelizumab was permanently discontinued in 0.1% of patients and tislelizumab treatment was interrupted in 0.6% of patients and in 36.4% of patients with hypothyroidism, the event resolved.
Type 1 Diabetes Mellitus
TEVIMBRA in combination with gemcitabine and cisplatin:
No imAEs of Diabetes mellitus were reported.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, type 1 diabetes mellitus occurred in 0.6% of patients, including Grade 1 (0.1%), Grade 2 (0.3%), Grade 3 (0.2%), and Grade 4 (0.1%) events.
Tislelizumab was permanently discontinued in 0.2% of patients and tislelizumab treatment was interrupted in 0.2% of patients and 8.3% of patients with Type 1 diabetes mellitus resolved.
Immune-mediated Nephritis with Renal Dysfunction
TEVIMBRA in combination with gemcitabine and cisplatin:
No imAEs of Nephritis were reported.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related nephritis and renal dysfunction occurred in 0.2% of patients, including Grade 1 (0.1%), Grade 2 (0.1%), and Grade 3 (0.1%) events.
Tislelizumab was permanently discontinued in 0.1% of patients and tislelizumab treatment was interrupted in 0.1% of patients and in 50.0% of patients with immune-related nephritis and renal dysfunction, the event resolved.
Immune-mediated Myocarditis
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated myocarditis occurred in 1.5% of patients receiving TEVIMBRA, 1 patient required corticosteroid treatment. Both imAEs were Grade 2, and both patients discontinued treatment.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related myocarditis occurred in 0.8% of patients, including Grade 1 (0.4%), Grade 2 (0.2%), Grade 3 (0.2%), and Grade 4 (0.1%) events.
Tislelizumab was permanently discontinued in 0.4% of patients and tislelizumab treatment was interrupted in 0.4% of patients and in 60.0% of patients with myocarditis, the event resolved.
Immune-mediated Myositis
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated myositis occurred in 1.5% of patients receiving TEVIMBRA, all adverse events were ≤ Grade 2. One patient required corticosteroid treatment. One patient (0.8%) had treatment interruption.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related myositis/rhabdomyolysis occurred in 0.8% of patients, including Grade 1 (0.3%), Grade 2 (0.3%), Grade 3 (0.2%), and Grade 4 (0.1%) events.
Tislelizumab was permanently discontinued in 0.2% of patients and tislelizumab treatment was interrupted in 0.5% of patients and in 75.0% of patients with myositis/rhabdomyolysis, the event resolved.
Immune-mediated Pancreatitis
TEVIMBRA in combination with gemcitabine and cisplatin:
No imAEs of pancreatitis were reported.
TEVIMBRA as monotherapy:
Immune-mediated pancreatitis occurred in 0.3% of patients receiving TEVIMBRA, all imAEs were Grade 3. Tislelizumab was treatment interrupted in 0.3% of patients and in 100% of patients the event resolved.
Immune-mediated Skin Reactions
TEVIMBRA in combination with gemcitabine and cisplatin:
Immune-mediated dermatologic adverse reactions occurred in 29.3% of patients receiving TEVIMBRA, 2 patients required treatment modification, 3.8% of patients experienced a reaction ≥ Grade 3, and 12.8% of patients required corticosteroid treatment. No patients discontinued due to imAEs. Skin adverse reactions resolved in 92.3% of patients.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, immune-related skin adverse reactions occurred in 12.6% of patients, including Grade 1 (7.7%), Grade 2 (3.7%), Grade 3 (1.0%), and Grade 4 (0.1%) events.
Tislelizumab was permanently discontinued in 0.1% of patients, and tislelizumab treatment was interrupted in 1.3% of patients and in 76.6% of patients with skin adverse reactions resolved.
Infusion Related Reactions
TEVIMBRA in combination with gemcitabine and cisplatin:
Infusion-related reactions have been reported in 5.3 % of patients receiving TEVIMBRA in combination with gemcitabine and cisplatin, no ≥ Grade 3 reactions were reported.
TEVIMBRA as monotherapy:
In patients treated with tislelizumab as monotherapy, infusion-related reactions occurred in 3.0% of patients, including Grade 3 (0.1%) events. Tislelizumab was permanently discontinued in 0.1% of patients and tislelizumab treatment was interrupted in 0.1% of patients.
8.3 Less Common Clinical Trial Adverse Reactions
The following are clinically important less common adverse events, reported in <5% of patients treated with TEVIMBRA in study RATIONALE-309.
Blood and lymphatic System Disorders: Myelosuppression.
Cardiac disorders: Myocarditis
Endocrine disorders: Central hypothyroidism, Hyperthyroidism
Gastrointestinal disorders: Chronic gastritis, Colitis, Duodenitis, Enteritis
Hepatobiliary disorders : Drug-induced liver injury, Hepatic function abnormal
Infections and infestations: COVID-19, Periodontitis, Sepsis
Metabolism and nutrition disorders: Hypoglycemia, Type 2 diabetes mellitus
Musculoskeletal and connective tissue disorders: Myositis
Neoplasms benign, malignant and unspecified (incl cysts and polyps): Myelodysplastic syndrome
Nervous system disorders: Peripheral sensory neuropathy
Renal and urinary disorders: Acute kidney injury
Respiratory, thoracic and mediastinal disorders : Pneumonitis
Skin and subcutaneous tissue disorders : Vitiligo
Vascular disorders: Venous thrombosis limb
The following are clinically important less common adverse events, reported in <5% of patients treated with TEVIMBRA in study RATIONALE-302.
Blood and lymphatic System Disorders: Thrombocytopenia
Cardiac disorders: Autoimmune myocarditis, Immune-mediated myocarditis
Endocrine disorders: Hyperthyroidism, Adrenal insufficiency, Hypopituitarism, Thyroiditis, Hypophysitis
General disorders and administration site conditions: Multiple organ dysfunction syndrome
Hepatobiliary disorders: Hepatitis, Immune-mediated hepatitis
Infections and infestations: Nasopharyngitis, Sepsis, Septic shock
Metabolism and nutrition disorders: Hypoglycemia, Type 1 diabetes mellitus, Type 2 diabetes mellitus
Musculoskeletal and connective tissue disorders: Myositis, Immune-mediated myositis
Renal and urinary disorders: Renal impairment
Respiratory, thoracic and mediastinal disorders: Immune-mediated pneumonitis, Pulmonary embolism
Skin and subcutaneous tissue disorders: Erythema multiforme
Eye Disorder: Uveitis
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Nasopharyngeal Carcinoma
Table 6 summarizes the Hematological and Chemistry laboratory abnormalities in study RATIONALE-309.
Table 6: Laboratory abnormalities worsening from baseline with TEVIMBRA in Study RATIONALE-309
Tislelizumab Gemcitabine + Cisplatin N = 133 | Placebo Gemcitabine + Cisplatin N=130 | |||
| Laboratory abnormality parameter* | All Grades n (%) | Grade 3-4 n (%) | All Grades n (%) | Grade 3-4 n (%) |
| Hematology | ||||
| Hemoglobin increased | 5 (3.8) | 0 (0.0) | 1 (0.8) | 0 (0.0) |
| Hemoglobin decreased | 130 (99.2) | 43 (32.8) | 125 (97.7) | 47 (36.7) |
| Leukocytes decreased | 123 (93.9) | 69 (52.7) | 121 (94.5) | 73 (57.0) |
| Lymphocytes increased | 8 (6.1) | 1 (0.8) | 4/ (3.2) | 0 (0.0) |
| Lymphocytes decreased | 111 (84.7) | 76 (58.0) | 119 (94.4) | 72 (57.1) |
| Neutrophils decreased | 118 (90.1) | 66 (50.4) | 116 (92.1) | 77 (61.1) |
| Platelets decreased | 90 (68.7) | 34 (26.0) | 99 (77.3) | 41 (32.0) |
| Chemistry | ||||
| Alanine aminotransferase increased | 53 (40.8) | 3 (2.3) | 46 (36.2) | 2 (1.6) |
| Albumin decreased | 51 (39.2) | 1 (0.8) | 62 (48.8) | 0 (0.0) |
| Alkaline phosphatase increased | 34 (26.2) | 0 (0.0) | 31 (24.6) | 0 (0.0) |
| Aspartate aminotransferase increased | 53 (40.5) | 1 (0.8) | 45 (35.4) | 2 (1.6) |
| Bilirubin increased | 18 (13.8) | 3 (2.3) | 12 (9.4) | 1 (0.8) |
| Creatine kinase increased | 42 (32.6) | 5 (3.9) | 21 (16.5) | 2 (1.6) |
| Creatinine increased | 49 (37.7) | 0 (0.0) | 42 (33.1) | 0 (0.0) |
| Glucose increased | 57 (43.8) | 0 (0.0) | 51 (40.5) | 0 (0.0) |
| Glucose decreased | 30 (23.1) | 1 (0.8) | 23 (18.3) | 1 (0.8) |
| Potassium increased | 11 (8.4) | 1 (0.8) | 10 (7.8) | 0 (0.0) |
| Potassium decreased | 50 (38.2) | 12 (9.2) | 38 (29.7) | 11 (8.6) |
| Sodium increased | 4 (3.1) | 0 (0.0) | 1 (0.8) | 1 (0.8) |
| Sodium decreased | 78 (59.5) | 16 (12.2) | 80 (62.5) | 16 (12.5) |
| *Each test incidence is based on the number of patients who had both baseline and at least one post-baseline | ||||
laboratory measurement available: n is the number of patients for whom the laboratory abnormalities deteriorated by ≥1 CTCAE toxicity grade from baseline.
Previously Treated Unresectable or Metastatic Esophageal Squamous Cell Carcinoma (ESCC)
Table 7: Laboratory Abnormalities Worsening from Baseline Occurring in ≥10% of Patients in RATIONALE-302
| Laboratory Abnormality | TEVIMBRAa (N=255) | ICCa (N=240) | ||||||||||
| All Grades n(%) | Grade 3 or 4 n(%) | All Grades n(%) | Grade 3 or 4 n(%) | |||||||||
| Chemistry | ||||||||||||
| Glucose increased | 110 (45.8) | 9 (3.8) | 83 (39.7) | 4 (1.9) | ||||||||
| Sodium decreased | 82 (34.2) | 22 (9.2) | 76 (36.4) | 17 (8.1) | ||||||||
| Albumin decreased | 79 (32.9) | 2 (0.8) | 77 (36.8) | 2 (1.0) | ||||||||
| Alkaline phosphatase increased | 76 (31.7) | 7 (2.9) | 32 (15.3) | 1 (0.5) | ||||||||
| AST increased | 64 (26.7) | 2 (0.8) | 25 (11.9) | 1 (0.5) | ||||||||
| ALT increased | 54 (22.5) | 2 (0.8) | 32 (15.2) | 3 (1.4) | ||||||||
| Phosphate decreased | 35 (14.8) | 9 (3.8) | 41 (19.8) | 7 (3.4) | ||||||||
| Creatine kinase increased | 28 (13.4) | 3 (1.4) | 3 (2.2) | 0 | ||||||||
| Potassium decreased | 30 (12.5) | 3 (1.3) | 31 (14.8) | 7 (3.3) | ||||||||
| Bilirubin increased | 26 (11.1) | 4 (1.7) | 16 (7.8) | 1 (0.5) | ||||||||
| Glucose decreased | 24 (10.0) | 1 (0.4) | 20 (9.6) | 1 (0.5) | ||||||||
| Hematology | ||||||||||||
| Hemoglobin decreased | 108 (45.0) | 14 (5.8) | 130 (61.3) | 21 (9.9) | ||||||||
| Lymphocytes decreased | 102 (43.4) | 26 (11.1) | 126 (59.7) | 59 (28.0) | ||||||||
| Platelets decreased | 27 (11.3) | 3 (1.3) | 24 (11.3) | 2 (0.9) | ||||||||
a The denominator used to calculate the rate varied from 136 to 240 based on the number of patients with a baseline value and at least one post-treatment value.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of TEVIMBRA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
- Skin and subcutaneous tissue disorders: Stevens-Johnson Syndrome, toxic epidermal necrolysis (including fatal cases),
- Immune system disorders: immune-mediated cystitis, anaphylactic reaction, anaphylactic shock, immune-mediated myocarditis-myositis-myasthenia gravis overlap syndrome.
9 Drug Interactions
9.2 Drug Interactions Overview
No formal pharmacokinetic drug interaction studies have been conducted. Since tislelizumab is cleared from the circulation through catabolism, no metabolic drug-drug interactions are expected.
9.4 Drug-Drug Interactions
The use of systemic corticosteroids and other immunosuppressants, before starting TEVIMBRA, should be avoided because of their potential interference with the pharmacodynamic activity and efficacy. However, systemic corticosteroids and other immunosuppressants can be used after starting TEVIMBRA to treat immune-related ADRs (see 7 Warnings And Precautions).
10 Clinical Pharmacology
10.1 Mechanism of Action
Tislelizumab is a humanized immunoglobulin G4 (IgG4) variant monoclonal antibody against PD-1. Binding to the extracellular domain of PD-1 receptor blocks the interaction with both PD-L1 and PD-L2 ligands, inhibiting T-cell proliferation and cytokine production. Upregulation of PD-1 ligands occurs in some tumors and signaling through this pathway can contribute to inhibition of active T-cell immune surveillance of tumors.
Tislelizumab does not bind to Fc gamma receptors (FcγRs) and C1q, and therefore not induce antibody-dependent cellular cytotoxicity (ADCC), antibody dependent cellular phagocytosis (ADCP) or complement-dependent cytotoxicity (CDC).
10.3 Pharmacokinetics
The pharmacokinetics (PK) of tislelizumab was assessed following administration as monotherapy and in combination with chemotherapy. The PK of tislelizumab was characterized using population PK analysis with concentration data from 2,596 patients with advanced malignancies who received tislelizumab doses of 0.5 to 10 mg/kg every 2 weeks, 2.0 and 5.0 mg/kg every 3 weeks, and 200 mg every 3 weeks (Q3W). The PK of tislelizumab in patients dosed with 200 mg Q3W is described below.
Table 8: PK of tislelizumab in patients dosed with 200 mg Q3W
| 200 mg Q3W | Cmax (mg/mL) (%CV) | Ctrough (mg/mL) (%CV) | AUC (mg/mL*day) (%CV) | CL (mL/day) (%CV) | Vd (L) (%CV) | T1/2 (d) (%CV) | |||
|---|---|---|---|---|---|---|---|---|---|
| First dose | 67.8 (18.1) | 16.5 (27.0) | 601.0 (17.7) |
|
|
| |||
| Steady state | 110.0 (22.2) | 41.0 (38.3) | 1283.0 (28.7) | ||||||
a PK parameters are reported as geometric mean (CV%) based on population pharmacokinetic analysis. AUC: area under the concentration time curve from the last dose to the next dose; CL: clearance; Cmax: maximum concentration; Ctrough: trough concentration; T1/2: terminal elimination half-life; Vd: volume of distribution.
Peak concentrations were observed at the end of the infusion. The time to reach 90% steady-state level is approximately 84 days (12 weeks) after 200 mg Q3W doses, and the steady-state accumulation ratio of tislelizumab after repeat dosing is approximately 2.1-fold.
Absorption
Tislelizumab is administered via the intravenous route and therefore is immediately and completely bioavailable.
Distribution
A population PK analysis indicates that the steady state volume of distribution is 6.42 L, which is typical of monoclonal antibodies with limited distribution.
Metabolism
Tislelizumab is expected to be degraded into small peptides and amino acids via catabolic pathways.
Elimination
Based on population PK analysis, the clearance of tislelizumab was 0.153 L/day with an inter-individual variability of 26.3% and the geometrical mean terminal half-life was approximately 23.8 days with a coefficient variation (CV) of 31%. Time-varying clearance was not observed in tislelizumab PK.
At the dosing regimens of 0.5 mg/kg to 10 mg/kg once every 2 or 3 weeks (including 200 mg once every 3 weeks), PK of tislelizumab were observed to be linear and dose proportional, suggesting saturation of the target-mediated drug disposition.
Special Populations and Conditions
Pediatrics: PK of tislelizumab has not been evaluated in children and adolescents <18 years of age. Health Canada has not authorized tislelizumab for pediatric use.
Geriatrics: Based on population PK analysis, no clinically relevant differences in PK of tislelizumab were observed between patients aged <65 years (n=1750), patients aged between 65 and 75 years (n=737), and patients aged >75 years (n=109) (see 4 Dosage And Administration).
- Ethnic Origin: Population PK analysis showed that exposures in Asian patients were 12% to 21% higher than those of Caucasian patients; however, the differences were not considered clinically relevant.
- Hepatic Insufficiency: No dedicated studies of tislelizumab have been conducted in patients with hepatic impairment. In the population PK analyses of tislelizumab, no clinically important differences in the clearance of tislelizumab were found between patients with mild hepatic impairment (bilirubin ≤ULN and AST >ULN or bilirubin >1.0 to 1.5 × ULN and any AST, n=396) or moderate hepatic impairment (bilirubin >1.5 to 3 × ULN and any AST, n=12) and patients with normal hepatic function (bilirubin ≤ULN and AST ≤ULN, n=2,182). Data in patients with severe hepatic impairment (bilirubin >3 × ULN and any AST, n=2) were too limited to draw any conclusions (see 4 Dosage And Administration).
Renal Insufficiency: No dedicated studies of tislelizumab have been conducted in patients with renal impairment. In the population PK analyses of tislelizumab, no clinically relevant differences in the clearance of tislelizumab were found between patients with mild renal impairment (CLcr) 60 to 89 mL/min, n=1,046) or moderate renal impairment (CLcr 30 to 59 mL/min, n=320) and patients with normal renal function (CLcr ≥90 ml/min, n=1223). Mild and
- moderate renal impairment had no effect on the exposure of TEVIMBRA). Data in patients with severe renal impairment (CLcr 15 to 29 mL/min, n=5) were too limited to draw any conclusions (see 4 Dosing And Administration).
- Body Weight: Population PK analysis showed that increased body weight was associated with increased clearance (CL and Vc), resulting in decreased exposure. However, no clinically meaningful differences in the PK of tislelizumab based on body weight (32 to 130 kg) was observed.
10.4 Immunogenicity
All therapeutic proteins have the potential for immunogenicity. The detection of antibody formation is highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody (including neutralizing antibody) positivity in an assay may be influenced by several factors including assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of incidence of antibodies in the studies described below with the incidences of antibodies in other studies or to other products may be misleading.
Among the 3034 antidrug antibody (ADA)-evaluable patients receiving 200 mg once every 3 weeks as monotherapy or in combination with chemotherapies, the incidence of ADA and neutralizing antibody (NAbs) was 16.5% (236/1427) and 0.8% (11/1427), respectively, for monotherapy, and 22.2% (357/1607) and 1.0% (16/1607), respectively, for combination therapy.
The incidence of ADA and NAbs observed in NPC patients treated with tislelizumab in combination with chemotherapy in Study 309 and in ESCC patients treated with tislelizumab monotherapy in Study 302 are summarized below:
Table 9: Incidence of ADA and NAbs in Studies 309 and 302
| Treatment Regimen | Indication | ADA Incidence | NAb Incidence |
|---|---|---|---|
| Tislelizumab + chemotherapy | NPC | 8.8% (11/125) | 0.0% (0/125) |
| Tislelizumab monotherapy | ESCC | 14.5% (32/221) | 0.5% (1/221) |
A higher incidence of adverse events (AEs) was observed in ADA-positive patients compared to ADA-negative patients in the following studies:
In Study 309, where NPC patients were treated with tislelizumab in combination with chemotherapies, a higher incidence of serious adverse events (63.6% vs. 30.7%) and infusion related reactions (18.2% vs. 4.4%) was observed in ADA-positive patients compared to ADA-negative patients, respectively.
In Study 302, where ESCC patients were treated with tislelizumab monotherapy, a higher incidence of Grade ≥ 3 AEs (62.5% vs. 39.2%) and serious adverse events (50.0% vs. 34.4%) was observed in ADA-positive patients compared to ADA-negative patients, respectively.
11 Storage, Stability and Disposal
Store under refrigeration at 2°C to 8°C in the original carton to protect from light. Do not freeze. Do not shake.
For storage conditions after dilution of the medicinal product,(See 4 Dosage And Administration).
12 Special Handling Instructions
Any unused product or waste material should be disposed of in accordance with local requirements.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Proper name: tislelizumab
Chemical name: Anti-human PD-1, Immunoglobulin G4 (IgG4) variant monoclonal antibody
Molecular formula and molecular mass: The molecular weight of the intact tislelizumab molecule calculated from the complementary DNA (cDNA) sequence is 144,044 Daltons excluding the glycan moiety or 146,972 Daltons if including two A2FG1 glycan chains.
Structure:
Tislelizumab is a humanized IgG4 variant monoclonal antibody. The binding target of tislelizumab is PD-1. Tislelizumab is composed of two heterodimers. Each of the heterodimers is composed of a heavy and a light polypeptide chain. The heavy chains (HCs) of the antibody molecule are linked together by two disulfide bonds and the light chains (LCs) are linked to the HCs by one disulfide bond each.
Physicochemical properties: Clear to slightly opalescent, colorless to slightly yellowish solution.
The solution has a pH of approximately 6.5 and an osmolality of approximately 270 to 330 mOsm/kg.
Product Characteristics:
TEVIMBRA (tislelizumab for injection) is an Fc-engineered humanized IgG4 variant monoclonal antibody produced in recombinant Chinese Hamster Ovary cells, followed by purification and formulation.
14 Clinical Trials
14.1 Clinical Trials by Indication
Nasopharyngeal Carcinoma (NPC)
Table 10: Summary of patient demographics for Study RATIONALE-309
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Min -Max) | Sex (%) |
| RATIONALE-309 | Phase 3, multicenter, double-blind, placebo-controlled, randomized (1:1) | Intravenous infusion Arm A Tislelizumab 200mg Q3W +GC Arm B Placebo + GC | All: 263 Arm A: 131 Arm B: 132 | 50 (23-74) 50 (26-74) 50 (23-73) | M (78.3) F (21.7) |
RATIONALE-309 (NCT03924986) was a randomized, multi-center, double-blind, placebo-controlled phase 3 study comparing the efficacy and safety of TEVIMBRA in combination with gemcitabine and cisplatin versus placebo in combination with gemcitabine and cisplatin as first-line treatment in patients with recurrent or metastatic nasopharyngeal carcinoma (NPC).
A total of 263 patients were randomized (1:1) to receive either TEVIMBRA in combination with gemcitabine and cisplatin (N = 131) or placebo in combination with gemcitabine and cisplatin (N = 132). Randomization was stratified by gender and metastatic status (based on the presence or absence of liver metastases). Patients received either TEVIMBRA 200 mg or placebo plus cisplatin 80 mg/m2 on Day 1 plus gemcitabine 1 g/m2 on Day 1 and Day 8 of each 21-day cycle for 4 to 6 cycles. TEVIMBRA or placebo was administered until disease progression or unacceptable toxicity.
The study included patients with pathologically confirmed recurrent or metastatic NPC who have not received prior systemic treatment and an ECOG performance status of 0 or 1.The RATIONALE-309 study excluded patients who received any approved systemic anticancer therapy including hormonal therapy within 28 days before initiation of study treatment, prior therapies targeting PD-1 or PD-L1, or who have active leptomeningeal disease or uncontrolled, untreated brain metastasis.
The primary endpoint was progression-free survival (PFS) as assessed by the Independent Review Committee (IRC) per RECIST v1.1 in the Intention-to-Treat (ITT) Analysis Set. The secondary endpoints were descriptive in nature and included Overall Survival (OS), Objective Response Rate (ORR), and Duration of Response (DOR). At the time of the primary PFS analysis, the median follow-up time was 10.2 months.
The baseline characteristics for the study population were: median age of 50 years (min, max: 23, 74); 91.6% of patients < 65 years old; 78.3% of patients were male; 63.1% with baseline ECOG PS score of 1; 100% Asian (from China, Thailand, and Taiwan); and 95% were never or former smokers.
Efficacy results are shown in Table 11 and Figure 1.
Table 11: Efficacy Results in RATIONALE-309
| Endpoint | Tislelizumab + Gemcitabine + Cisplatin (N = 131) | Placebo + Gemcitabine + Cisplatin (N = 132) | ||||||
| PFS | ||||||||
| Events, n (%) | 65 (49.6) | 87 (65.9) | ||||||
| Median PFS (months) (95% CI) a | 9.2 (7.6, 10.1) | 7.4 (5.6, 7.5) | ||||||
| Hazard Ratio (95% CI) b, c | 0.52 (0.38, 0.73) | |||||||
| p-valuec, d | < 0.0001 | |||||||
Abbreviations: PFS = progression-free survival
a Medians were estimated by Kaplan-Meier method with 95% CIs estimated using the method of Brookmeyer and Crowley b Estimated from stratified Cox model
c Stratified by gender and liver metastases status (with versus without)
d One-sided p-value from log-rank test
Figure 1: Kaplan-Meier Plot of Progression-Free Survival in RATIONALE-309
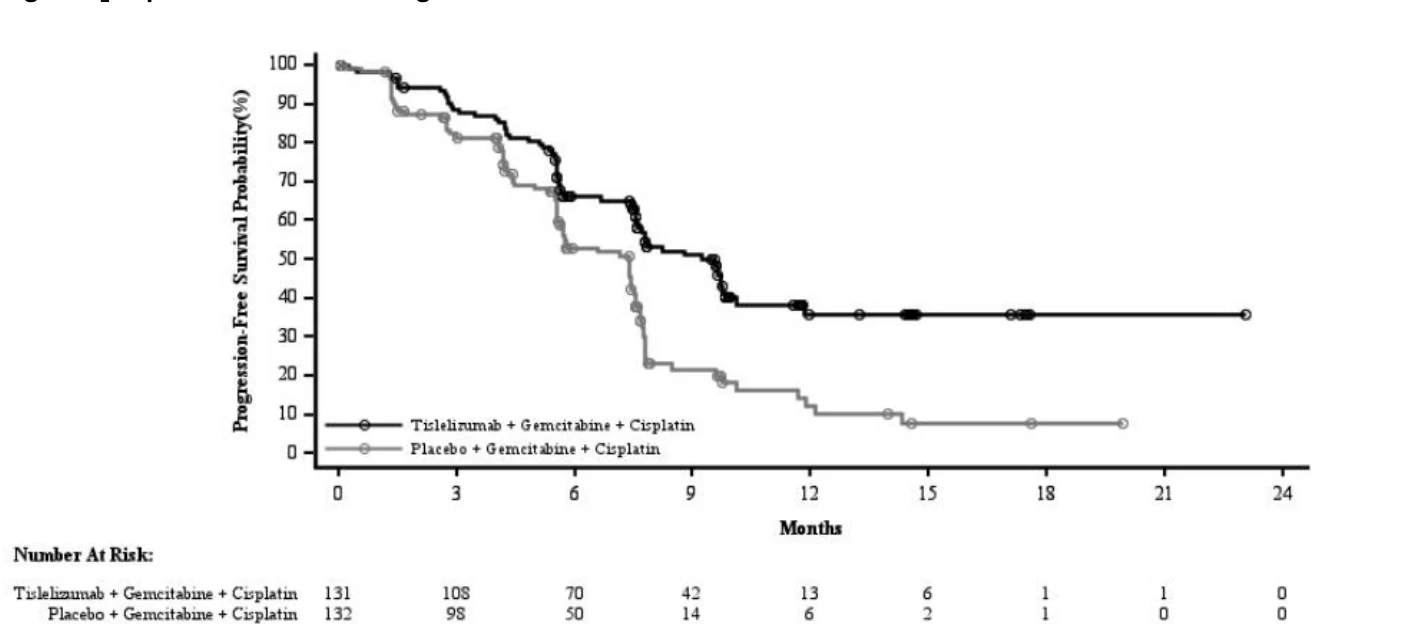
In addition, ORR was 69.5% (95% CI: 60.8%–77.2%) in the TEVIMBRA plus gemcitabine and cisplatin arm and 55.3% (95% CI: 46.4%–64.0%) in the placebo plus gemcitabine and cisplatin arm.
Among responders, the median DOR was 8.5 months (95% CI: 6.5, Not Estimable) in the TEVIMBRA in combination with gemcitabine and cisplatin arm and 6.1 months (95% CI: 4.7, 6.2) in the placebo plus gemcitabine and cisplatin arm.
Previously Treated Unresectable or Metastatic Esophageal Squamous Cell Carcinoma (ESCC)
Table 12:Summary of Patient Demographics for Study BGB-A317-302 (RATIONALE-302)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| BGB-A317-302 | Randomized, Controlled, Open-label | TEVIMBRA 200 mg i.v. Q3W Or ICC: Paclitaxel: 135 to 175 mg/m2 i.v. Q3W Or Docetaxel: 75 mg/m2 i.v. Q3W Or Irinotecan: 125 mg/m2 i.v. on Days 1 and 8, given every 3 weeks | 256 256 | 61.8 (40-86) 61.8 (35-81) | 217 M 39 F 215 M 41 F |
RATIONALE-302 (NCT03430843) was a multicenter, randomized (1:1), open-label study comparing the efficacy and safety of TEVIMBRA monotherapy versus investigator’s choice of chemotherapy: paclitaxel, docetaxel or irinotecan in adult patients with unresectable advanced or metastatic ESCC who had progressed on or after one prior systemic chemotherapy.
Patients were enrolled regardless of their tumor PD-L1 expression level. PD-L1 expression was evaluated at a central laboratory using the Ventana PD-L1 (SP263) assay that identified PD-L1 staining on both tumor and tumor-associated immune cells (Tumor Area Positivity or TAP). The trial excluded patients who received a prior immune checkpoint inhibitor, had brain or leptomeningeal metastases that were symptomatic or required treatment, active autoimmune disease, a medical condition requiring systemic corticosteroids or immunosuppressants, or apparent tumor invasion of organs adjacent to the esophageal tumor.
A total of 512 patients were randomized (1:1) to receive either TEVIMBRA 200 mg every 3 weeks or investigator’s choice of chemotherapy (ICC), all given intravenously: paclitaxel 135-175 mg/m2 every 3 weeks or 80 to 100 mg/m2 weekly, docetaxel 75 mg/m2 every 3 weeks, or irinotecan 125 mg/m2 on Days
1 and 8 of every 3-week cycle. Patients were treated until disease progression assessed by the investigator or unacceptable toxicity.
Randomization was stratified by geographic region (Asia [excluding Japan] vs Japan vs US/EU), ECOG performance status (0 vs 1), and ICC option (paclitaxel vs docetaxel vs irinotecan). Tumor assessments were conducted every 6 weeks for the first 6 months, then every 9 weeks until disease progression.
The major efficacy outcome measure was overall survival (OS) in the Intent-to-Treat (ITT) population. Additional efficacy outcome measures were investigator-assessed progression-free survival (PFS), overall response rate (ORR), and duration of response (DOR) per RECIST v1.1.
The baseline characteristics for the study population were: median age of 62 years (range: 35 to 86), 38% age ≥65 years of age; 84% male; 19% White and 80% Asian; 95% had metastatic disease. Baseline ECOG performance status was 0 (25%) or 1 (75%).
A total of 512 patients were enrolled and randomized to TEVIMBRA (n=256) or ICC (n=256) (irinotecan [46%], paclitaxel [33%], or docetaxel [21%]). Of the 512 patients, 142 (28%) had PD-L1 ≥10%, 222 (43%) had PD-L1 <10%, and 148 (29%) had unknown baseline PD-L1 status.
Efficacy results are shown in Table 13 and Figure 2.
Table 13: Efficacy Results in RATIONALE-302
| Endpoint | TEVIMBRA (N=256) | ICC (N=256) | ||||||
|---|---|---|---|---|---|---|---|---|
| Overall Survival | ||||||||
| Deaths n (%) | 197 (77) | 213 (83.2) | ||||||
| Median (months)a (95% CI) | 8.6 (7.5, 10.4) | 6.3 (5.3, 7.0) | ||||||
| Hazard ratiob (95% CI) | 0.70 (0.57, 0.85) | |||||||
| p-valuec | 0.0001 | |||||||
CI = confidence interval
a Estimated using Kaplan-Meier method.
b Based on Cox regression model stratified by baseline ECOG status and ICC option.
c One-sided p-value based on log-rank test stratified by ECOG performance status and ICC option.
Figure 2: Kaplan-Meier Curve for Overall Survival in RATIONALE-302
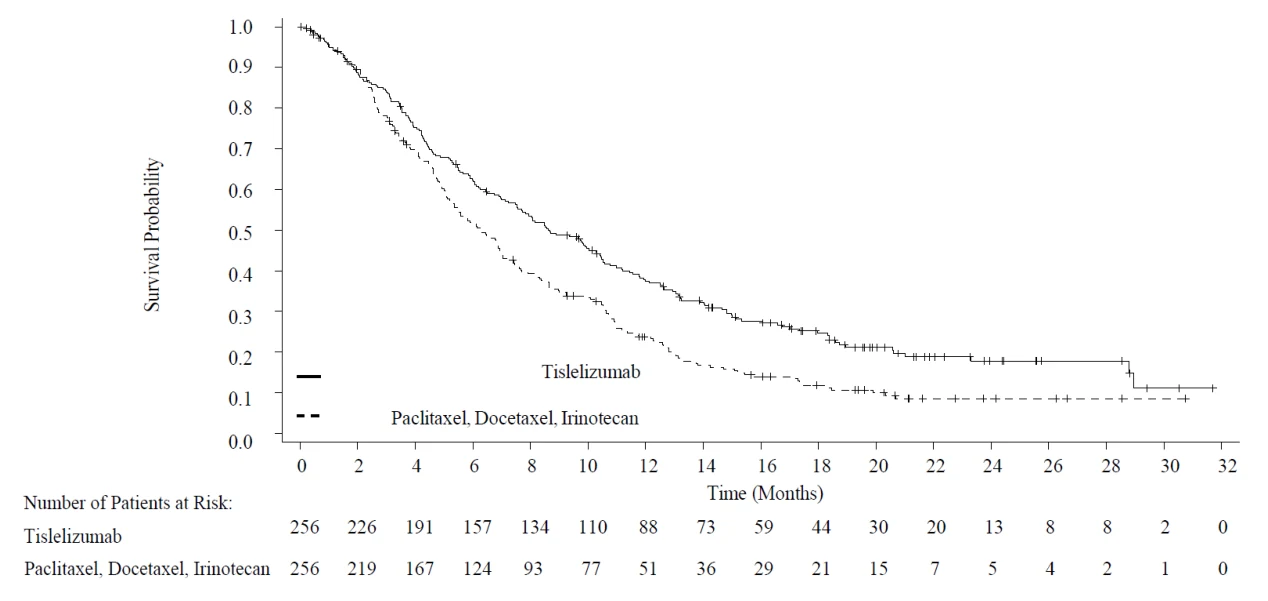
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General toxicology:
In non-clinical toxicology studies in cynomolgus monkeys, no treatment related toxicity was noted at single doses up to 100 mg/kg. In repeat-dose toxicology studies in cynomolgus monkeys, following intravenous infusion at 3, 10, 30 or 60 mg/kg (once every 2 weeks (Q2W), 7 dose administrations) for 13 weeks, no apparent treatment-related toxicity or histopathological changes were observed in any tissues or organs, including the reproductive system of male and females up to 30 mg/kg Q2W, corresponding to 4 to 7 times human exposure than those observed at the clinical dose of 200 mg. A higher dose (60 mg/kg) was associated with article-related adverse histopathology findings in the kidney and vascular changes in multiple tissues corresponding to moderate to severe immunogenic reactions in several animals, which may have been due to ADA development.
Genotoxicity:
No long-term animal studies have been performed to evaluate the genotoxic potential of tislelizumab.
Carcinogenesis:
No long-term animal studies have been performed to evaluate the carcinogenic potential of tislelizumab.
Reproductive and Developmental Toxicity:
No developmental and reproductive toxicity studies or animal fertility studies have been conducted with tislelizumab. In a 13-week repeat-dose toxicology study in cynomolgus monkeys, there were no notable effects in the male and female reproductive organs; however, most animals in the study were not sexually mature.
Animal studies have demonstrated that inhibition of the PD-1/PD-L1 pathway can lead to increased risk of immune-mediated rejection of the developing fetus resulting in fetal death. IgG4 is also known to cross the placental barrier; hence, tislelizumab has the potential to cross the placenta during pregnancy and cause harm to the fetus.
Special Toxicology:
In animal models, inhibition of PD-L1/PD-1 signaling resulted in an increased severity of some infections and enhanced inflammatory responses. Mycobacterium tuberculosis–infected PD-1 knockout mice exhibit markedly decreased survival compared with wild-type controls, which correlated with increased bacterial proliferation and inflammatory responses in these animals. PD-1 blockade using a primate anti-PD-1 antibody was also shown to exacerbate M. tuberculosis infection in rhesus macaques. PD-L1 and PD-1 knockout mice have also shown decreased survival following infection with lymphocytic choriomeningitis virus.