


Product Monograph - Zykadia
Recent Major Label Changes
| 1 INDICATIONS | 2024-09 |
|---|
Table of Contents
Certain sections (as indicated in section 2.1. of the PM Guidance) or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
1 Indications ....................................................................................................................... 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 Contraindications ............................................................................................................ 4
3 Serious Warnings and Precautions Box ............................................................................ 4
4 Dosage and Administration ............................................................................................. 5
4.1 Dosing Considerations .............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration .......................................................................................................... 7
4.5 Missed Dose ............................................................................................................. 7
5 Overdose ......................................................................................................................... 7
6 Dosage Forms, Strengths, Composition, and Packaging ................................................... 7
7 Warnings and Precautions ............................................................................................... 8
General ................................................................................................................................. 8
Carcinogenesis and Genotoxicity .......................................................................................... 8
Cardiovascular ...................................................................................................................... 8
Endocrine and Metabolism ................................................................................................. 10
Gastrointestinal .................................................................................................................. 10
Hepatic/Biliary/Pancreatic .................................................................................................. 11
Monitoring and Laboratory Tests ....................................................................................... 12
Renal ................................................................................................................................... 13
Reproductive Health ........................................................................................................... 13
7.1 Special Populations ................................................................................................ 14
7.1.1 Pregnancy ...................................................................................................... 14
7.1.2 Breastfeeding ................................................................................................ 14
7.1.3 Pediatrics ....................................................................................................... 14
7.1.4 Geriatrics ....................................................................................................... 14
8 Adverse Reactions ......................................................................................................... 15
8.1 Adverse Reaction Overview .................................................................................... 15
8.2 Clinical Trial Adverse Reactions .............................................................................. 15
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 25
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data ............................................................................................................... 25
9 Drug Interactions ........................................................................................................... 27
9.4 Drug-Drug Interactions ........................................................................................... 27
9.5 Drug-Food Interactions........................................................................................... 32
9.6 Drug-Herb Interactions ........................................................................................... 32
9.7 Drug-Laboratory Test Interactions ......................................................................... 32
10 Clinical Pharmacology ................................................................................................... 32
10.1 Mechanism of Action .............................................................................................. 32
10.2 Pharmacodynamics ................................................................................................ 32
10.3 Pharmacokinetics ................................................................................................... 33
11 Storage, Stability, and Disposal ...................................................................................... 35
Part 2: Scientific Information ................................................................................................ 36
13 Pharmaceutical Information .......................................................................................... 36
14 Clinical Trials .................................................................................................................. 36
14.1 Clinical Trials by Indication ..................................................................................... 36
16 Non-Clinical Toxicology .................................................................................................. 48
Patient Medication Information ........................................................................................... 51
Part 1: Healthcare Professional Information
1 Indications
ZYKADIA® (ceritinib) as monotherapy is indicated for:
- the first-line treatment of adult patients with anaplastic lymphoma kinase (ALK)-positive locally advanced (not amenable to curative therapy) or metastatic non-small cell lung cancer (NSCLC)
- the treatment of adult patients with ALK-positive locally advanced (not amenable to curative therapy) or metastatic NSCLC who have progressed on or who were intolerant to crizotinib
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of ZYKADIA have not been established in pediatric patients. Therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥65 years of age): Across seven clinical studies in patients with ALK+ advanced NSCLC receiving a fasted dose of 750 mg daily, 168 of 925 patients (18.2%) treated with ZYKADIA were aged 65 years and older. No overall differences in safety or efficacy were observed between younger (<65 years) and older patients (≥ 65 years).
2 Contraindications
- Zykadia is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging.
- Zykadia is contraindicated in patients with congenital long QT syndrome or with a persistent Fridericia-corrected electrocardiogram interval (QTcF) of >500 msec (see 7 Warnings and Precautions, 8 Adverse Reactions).
3 Serious Warnings and Precautions Box
- QT interval prolongation. (See 3 Contraindications, 7 Warnings and Precautions, 8 Adverse Reactions, 9 Drug Interactions)
- Interstitial Lung Disease/Pneumonitis, including fatal cases. (See 7 Warnings and Precautions, 8 Adverse Reactions)
- ZYKADIA has not been studied in patients with severe renal impairment requiring peritoneal dialysis or hemodialysis. (See 7 Warnings and Precautions, 8 Adverse Reactions)
- Hepatotoxicity. (See 7 Warnings and Precautions, 8 Adverse Reactions)
- Gastrointestinal toxicity. (See 7 Warnings and Precautions, 8 Adverse Reactions)
ZYKADIA (ceritinib) should only be prescribed and supervised by a qualified physician experienced in the use of anticancer agents.
4 Dosage and Administration
4.1 Dosing Considerations
- Renal impairment
Ceritinib has not been evaluated in patients with renal impairment in a dedicated study. However, based upon available data, ceritinib elimination via the kidney is negligible. Dose adjustment is not required for patients with mild and moderate renal impairment based on results of a population pharmacokinetic analysis. Caution should be used in patients with severe renal impairment as there is no experience with ceritinib in this population (see 10 Clinical Pharmacology).
- Hepatic impairment
For patients with severe hepatic impairment (Child-Pugh C), reduce the dose of ZYKADIA by approximately one-third, rounded to the nearest multiple of the 150 mg dosage strength (see 7 Warnings and Precautions, 7.1 Special populations and 10 Clinical Pharmacology).
4.2 Recommended Dose and Dosage Adjustment
- Recommended Dose
The recommended dose of ZYKADIA is 450 mg taken orally once daily with food at the same time each day. Food can range from a snack to a full meal (see 9 Drug Interactions and 10 Clinical Pharmacology).
The maximum recommended dose is 450 mg taken orally once daily with food.
Treatment should be continued as long as the patient is deriving clinical benefit from therapy.
- Dosage Adjustments
Temporary dose interruption and/or dose reduction of ZYKADIA therapy may be required based on individual safety and tolerability. If dose reduction is required due to any adverse drug reaction, then the daily dose of ZYKADIA should be reduced by decrements of 150 mg.
Early identification and management of adverse drug reactions (including gastrointestinal disorders) with standard supportive care measures should be considered.
Discontinue ZYKADIA in patients unable to tolerate 150 mg taken once daily with food.
Table 1 summarizes recommendations for dose interruption, reduction, or discontinuation of ZYKADIA in the management of select adverse drug reactions (ADRs).
Table 1 – ZYKADIA dose adjustment and management recommendations for adverse drug reactions
| Criteria | ZYKADIA Dosing |
|---|---|
| Severe or intolerable nausea, vomiting, or diarrhea despite optimal anti-emetic or anti-diarrheal therapy | Withhold ZYKADIA until improved, then reinitiate ZYKADIA by reducing dose by 150 mg |
| Alanine aminotransferase (ALT) or aspartate aminotransferase (AST) elevation greater than 5 times upper limit of normal (ULN) with concurrent total bilirubin less than or equal to 1.5 times ULN | Withhold ZYKADIA until recovery to baseline ALT/AST levels or to less than or equal to 3 times ULN, then reinitiate ZYKADIA by reducing dose by one 150 mg |
| ALT or AST elevation greater than 3 times ULN with concurrent total bilirubin elevation greater than 2 times ULN (in the absence of cholestasis or hemolysis) | Permanently discontinue ZYKADIA |
| Any Grade treatment-related ILD/pneumonitis | Permanently discontinue ZYKADIA |
| QTc greater than 500 msec on at least 2 separate electrocardiograms (ECGs) | Withhold ZYKADIA until recovery to baseline or to a QTc less than 481 msec, then reinitiate ZYKADIA by reducing dose by 150 mg |
| Torsade de pointes or polymorphic ventricular tachycardia or signs/symptoms of serious arrhythmia | Permanently discontinue ZYKADIA |
| Symptomatic bradycardia that is not life-threatening in patients who are taking a concomitant medication also known to cause bradycardia or hypotension.a | Withhold ZYKADIA until recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above. If contributing concomitant medication is identified and discontinued, or its dose is adjusted, reinitiate ZYKADIA at previous dose upon recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above |
| Symptomatic bradycardia that is not life-threatening in patients who are not taking a concomitant medication also known to cause bradycardia or hypotension a | Withhold ZYKADIA until recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above. If no contributing concomitant medication is identified, or if contributing concomitant medications are not discontinued or dose modified, reinitiate ZYKADIA by reducing dose by 150 mg upon recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above |
| Bradycardiaa (that is life-threatening or requires medical intervention) in patients taking a concomitant medication also known to cause bradycardia or hypotension. | Withhold ZYKADIA until recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above. If contributing concomitant medication is identified and discontinued, or its dose is adjusted, reinitiate ZYKADIA by reducing the dose by 150mg, with frequent monitoringb |
| Bradycardiaa (that is life-threatening or requires urgent intervention) in patients who are not taking a concomitant medication also known to cause bradycardia or hypotension | Permanently discontinue ZYKADIA |
| Severe (grade 3) or intolerable nausea, vomiting or diarrhea despite optimal anti-emetic or anti-diarrheal therapy | Withhold ZYKADIA until improved, then reinitiate ZYKADIA by reducing dose by 150 mg |
| Persistent hyperglycemia greater than | Withhold ZYKADIA until hyperglycemia is adequately |
| 250mg/dL despite optimal anti-hyperglycemic therapy | controlled, then reinitiate ZYKADIA by reducing dose by 150 mg If adequate glucose control cannot be achieved with optimal medical management, permanently discontinue ZYKADIA |
| Elevated lipase or amylase greater than or equal to grade 3 (greater than 2 times ULN) | Withhold ZYKADIA until lipase or amylase returns to less than or equal to grade 1 (less than 1.5 times ULN), then reinitiate by reducing dose by 150 mg |
| a Heart rate less than 60 beats per minute (bpm) b Permanently discontinue for recurrence | |
4.4 Administration
ZYKADIA should be administered orally once daily at the same time every day. ZYKADIA capsules should be swallowed whole with water. The capsules should not be chewed or crushed. (see 10 Clinical Pharmacology).
4.5 Missed Dose
If a dose is missed, the patient should make up that dose, unless the next dose is due within 12 hours. If vomiting occurs during the course of treatment, the patient should not take an additional dose, but should continue with the next scheduled dose.
5 Overdose
A 750 mg once daily fasted dosing regimen was the maximum tolerated dose for ZYKADIA determined in a Phase I dose-escalation study in patients with ALK-positive malignancies. There is limited reported experience with overdose in humans. General supportive measures, including ECG monitoring, should be initiated in all cases of overdose.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition, and Packaging
Table 2 – Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| oral | capsule 150 mg | Capsule content: colloidal anhydrous silica; hydroxypropyl cellulose low-substituted; magnesium stearate; microcrystalline cellulose; sodium starch glycolate. The capsule shell components contain gelatin; indigotine (E132); titanium dioxide (E171). |
Description
ZYKADIA (ceritinib) 150 mg capsules: Hard gelatin capsule, size #00, opaque white and opaque blue capsule, opaque blue cap marked in black ink with “LDK 150MG”, opaque white body marked in black ink with “NVR”.
ZYKADIA capsules are available in one dosage strength, 150 mg, containing 150 mg of ceritinib.
Packaging
ZYKADIA is supplied in blister packaging: 150 capsules (3 packs of 50 capsules).
7 Warnings and Precautions
See 3 Serious Warnings and Precautions Box.
General
- ALK Testing
In order to receive ZYKADIA, patients must have a documented ALK-positive status for locally advanced or metastatic NSCLC based on a validated ALK assay (See 7 Warnings and Precautions, Monitoring and Laboratory Tests).
- Drug Interactions
Avoid co-administration of ZYKADIA with strong CYP3A inhibitors or CYP3A inducers. The concurrent use of ZYKADIA should also be avoided with CYP3A or CYP2C9 substrates with narrow therapeutic indices or substrates primarily metabolized by CYP3A or CYP2C9 (see Section 9.4 Drug–Drug Interactions).
Carcinogenesis and Genotoxicity
Carcinogenicity studies have not been performed with ceritinib. Ceritinib was not mutagenic in vitro in the bacterial reverse mutation (Ames) assay. Ceritinib was not clastogenic in the in vivo rat micronucleus assay. However, ceritinib induced numerical aberrations (aneugenic) in the in vitro cytogenetic assay using human lymphocytes, and micronuclei in the in vitro micronucleus test using TK6 cells. (See 16 Non-Clinical Toxicology).
Cardiovascular
- Bradycardia
Bradycardia adverse events (including bradycardia and sinus bradycardia), all Common Terminology Criteria for Adverse Events (CTCAE) Grade 1 or 2, were reported in 2.3% of patients in the pooled analysis comprised of 925 patients with ALK+ advanced NSCLC treated with ZYKADIA at a fasted dose of 750 mg daily across seven clinical studies. Based on ECG data, there were 4.4% of patients in the ceritinib arm having a decrease in heart rate (HR) more than 25% and less than 50 beats per minute compared to baseline. Bradycardia led to dose adjustments or interruptions in 0.2% of patients (see 4 Dosage and Administration, 8 Adverse Reactions, 9 Drug Interactions, 10 Clinical Pharmacology).
| The printing ink contains black iron oxide. |
Caution should be exercised in patients with a low heart rate at baseline (<60 beats per minute), a history of syncope or arrhythmia, sick sinus syndrome, sinoatrial block, atrioventricular block, ischemic heart disease, or congestive heart failure. Avoid use of ZYKADIA in combination with other agents known to cause bradycardia (e.g., beta-blockers, non-dihydropyridine calcium channel blockers, clonidine, and digoxin) to the extent possible (see 4 Dosage and Administration, 8 Adverse Reactions, 9 Drug Interactions, 10 Clinical Pharmacology). Monitor heart rate and blood pressure regularly. In cases of symptomatic bradycardia that is not life-threatening, withhold ZYKADIA until recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above, evaluate the use of concomitant medications, and reduce the dose of ZYKADIA if necessary. Permanently discontinue ZYKADIA for life-threatening bradycardia if no contributing concomitant medication is identified; however, if associated with concomitant medication known to cause bradycardia or hypotension, withhold ZYKADIA until recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above, and if concomitant medication can be adjusted or discontinued, reinitiate ZYKADIA by reducing dose by 150 mg upon recovery to asymptomatic bradycardia or to a heart rate of 60 bpm or above, with frequent monitoring (see 4 Dosage and Administration and 8 Adverse Reactions).
- QT Interval Prolongation
QTc prolongation occurs in patients treated with ZYKADIA (see 4 Dosage and Administration, 8 Adverse Reactions, 9 Drug Interactions, 10 Clinical Pharmacology).
In a pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC treated with ZYKADIA at a fasted dose of 750 mg daily, a categorical outlier analysis of ECG data in 919 patients with available data demonstrated new QTc >500 msec in 12 patients (1.3%) among which six had elevated QTc>450 msec at baseline. There were 58 patients (6.3%) with a QTc increase from baseline >60 msec.
A pharmacokinetic/pharmacodynamic analysis suggested that ceritinib causes concentration-dependent increases in QTc (see 10 Clinical Pharmacology).
QTc prolongation may lead to an increased risk of ventricular arrhythmias including torsade de pointes. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death. Treatment with ZYKADIA is not recommended in patients with congenital long QT syndrome, or who are taking medicinal products known to prolong the QTc interval (see 9 Drug Interactions). Hypokalemia, hypomagnesemia, and hypocalcemia must be corrected prior to ZYKADIA administration.
Particular care should be exercised when administering ZYKADIA to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug.
Risk factors for torsade de pointes in the general population include, but are not limited to, the following: female gender; age ≥ 65 years; baseline prolongation of the QT/QTc interval; presence of genetic variants affecting cardiac ion channels or regulatory proteins, especially congenital long QT syndromes; family history of sudden cardiac death at <50 years of age; cardiac disease (e.g., myocardial ischemia or infarction, congestive heart failure, cardiomyopathy, conduction system disease); history of arrhythmias; electrolyte disturbances (e.g., hypokalemia, hypomagnesemia, hypocalcemia) or conditions leading to electrolyte disturbances (e.g., persistent vomiting, eating disorders); bradycardia; acute neurological events (e.g., intracranial or subarachnoid haemorrhage, stroke, intracranial trauma); diabetes mellitus; and autonomic neuropathy.
Monitor electrocardiogram and electrolytes regularly. Permanently discontinue ZYKADIA in patients who develop torsade de pointes or polymorphic ventricular tachycardia or signs/symptoms of serious arrhythmia. Withhold ZYKADIA in patients who develop QTc greater than 500 msec on at least 2 separate ECGs until recovery to baseline or a QTc less than 481 msec, then reinitiate ZYKADIA by reducing dose by 150 mg (see 8 Adverse Reactions and 10 Clinical Pharmacology).
When drugs that prolong the QTc interval are prescribed, health professionals should counsel their patients concerning the nature and implications of the ECG changes, underlying diseases and disorders that are considered to represent risk factors, demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug. Patients should be advised to contact their health professional immediately to report any new chest pain or discomfort, changes in heartbeat, palpitations, dizziness, light headedness, fainting, or changes in or new use of other medications.
Endocrine and Metabolism
- Hyperglycemia
In a pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC, hyperglycemia (all grades) has been reported in 9.4% of patients treated with ZYKADIA at a fasted dose of 750 mg daily; 5.4% of patients reported a Grade 3/4 event.
The risk of hyperglycemia was higher in patients with diabetes mellitus and/or concurrent steroid use.
Monitor fasting serum glucose prior to the start of ZYKADIA treatment and periodically thereafter as clinically indicated. Initiate or optimize anti-hyperglycemic medications as indicated. Based on the severity of hyperglycemia, interruption of ZYKADIA treatment and/or dose reduction may be required. Permanently discontinue ZYKADIA if adequate glycemic control cannot be achieved with optimal medical management (see 4 Dosage and Administration 7 Warnings and Precautions, Monitoring and Laboratory Tests and 8 Adverse Reactions).
Gastrointestinal
In a pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC, gastrointestinal toxicity (nausea, vomiting and diarrhea all grades) occurred in 94.8% of patients treated with ZYKADIA at a fasted dose of 750 mg. Diarrhea, nausea and vomiting occurred in 82.1%, 74.7% and 63.2% of patients, respectively. Persistent Grade 1/2 nausea, vomiting and diarrhea requiring dose reduction have been observed. Grade 3/4 (severe) diarrhea, nausea and vomiting occurred in 5.2%, 5.3% and 5.6% of patients, respectively. Nausea led to dose discontinuation in 0.5%, vomiting in 0.4%, and diarrhea in 0.1% of patients. Diarrhea, nausea and vomiting led to dose adjustments or interruptions in 15.0%, 16.8% and 19.2% of patients, respectively.
Diarrhea, nausea, or vomiting occurred in 76.9% of 108 patients treated with ZYKADIA at the recommended dose of 450 mg taken with food in a dose optimization study A2112 (ASCEND-8) and were mainly grade 1 events (52.8%) and grade 2 (22.2%) events. Two patients (1.9%) experienced one grade 3 event each (diarrhea and vomiting). Nine patients (8.3%) required study drug interruption due to diarrhea or nausea or vomiting. One patient (0.9) required dose adjustment due to vomiting. No patients required dose reduction or discontinuation of ZYKADIA due to diarrhea, nausea, or vomiting (see 8 Adverse Reactions).
Monitor and manage patients using standards of care, including anti-diarrheals, anti-emetics, or fluid replacement, as indicated. Dose interruption and/or reduction may be employed (see 4 Dosage and
Administration and 8 Adverse Reactions). If vomiting occurs during the course of treatment, the patient should not take an additional dose, but should continue with the next scheduled dose.
The pivotal Studies X2101, A2301 and A2303 excluded patients if they had unresolved nausea, vomiting or diarrhea > CTCAE Grade 1.
Hepatic/Biliary/Pancreatic
- Hepatotoxicity
In the pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC treated with ZYKADIA at a fasted dose of 750 mg daily, hepatotoxicity grouped AEs were reported in 60.5%, and the most frequently reported AEs (in ≥ 5% of patients) were: alanine aminotransferase (ALT) increased (51.0%), aspartate aminotransferase (AST) increased (43.4%), and gamma-glutamyl transferase (GGT) increased (20.8%).
Grade 3/4 hepatotoxicity grouped AEs were reported in 37.8% of patients. The most frequently reported (>10%) Grade 3/4 hepatotoxicity grouped AEs were elevations in liver function tests - ALT increased (25.0%), GGT increased (15.2%), and AST increased (12.6%).
The hepatotoxicity grouped AEs were managed by dose interruptions or adjustments of ceritinib treatment in 40.6% and led to discontinuation of ceritinib treatment in 1.0% of patients. The events were serious in 2.5%, and the most frequently reported (>0.5%) were ALT increased (1.1%) and AST increased (0.9%). There were no deaths due to a hepatotoxicity grouped AE.
Concurrent elevations in ALT or AST greater than three times the upper limit of normal (ULN) and total bilirubin greater than two times the ULN, with normal alkaline phosphatase, occurred in less than 1% of patients in clinical studies.
Monitor liver laboratory tests (including ALT, AST, and total bilirubin) prior to the start of treatment and monthly thereafter. In patients who develop transaminase elevations, more frequent monitoring of liver transaminases and total bilirubin should be done as clinically indicated. Based on the severity of the adverse drug reactions, dose interruption and reduction or discontinuation of ZYKADIA may be required (see 4 Dosage and Administration, 7 Warnings and Precautions, Monitoring and Laboratory Tests and 8 Adverse Reactions).
- Hepatic impairment
For patients with severe hepatic impairment (Child-Pugh C), reduce the dose of ZYKADIA by approximately one-third, rounded to the nearest multiple of the 150 mg dosage strength (see 4 Dosage and Administration and 10 Clinical Pharmacology). No dose adjustment is recommended in patients with mild (Child-Pugh A) or moderate (Child-Pugh B) hepatic impairment.
- Pancreatic Toxicity
ZYKADIA has demonstrated pancreatic toxicity in non-clinical studies (see 16 Non-Clinical Toxicology).
In a pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC treated with ZYKADIA at a fasted dose of 750 mg daily, the event of pancreatitis was reported in 0.5% of patients, all serious with one fatality. Pancreatitis related events (such as events of pancreatitis, lipase and amylase increased) were reported in 9.6% of patients, 5.8% of which were Grade 3/4, and 0.6% were serious.
Lipase and amylase should be monitored prior to the start of ZYKADIA treatment and periodically thereafter as clinically indicated. Patients should be observed carefully for signs and symptoms of pancreatitis. If pancreatitis is suspected, ZYKADIA should be interrupted or discontinued and appropriate management should be initiated (see 4 Dosage and Administration, 7 Warnings and Precautions, Monitoring and Laboratory Tests and 8 Adverse Reactions).
Monitoring and Laboratory Tests
- ALK Testing
In order to receive ZYKADIA, patients must have a documented ALK-positive status for locally advanced or metastatic NSCLC based on a validated ALK assay. Assessment for ALK positive locally advanced or metastatic NSCLC should have been performed by laboratories with demonstrated proficiency in the specific technology being utilized. Improper assay performance can lead to unreliable test results. In Study X2101 and Study A2303, 99% and 99.1% of patients were demonstrated to have documented ALK positive status by retrospective collection of ALK test pathological reports (See 14 Clinical Trials). In Study A2301, all randomized patients had centrally confirmed ALK-positive status using the VENTANA ALK (D5F3) CDx Assay (Ventana immunohistochemistry [IHC] test). The clinical benefit of ZYKADIA in patients with ALK-negative NSCLC has not been established; therefore, ZYKADIA is not recommended for these patients.
- Cardiac Safety Monitoring
Monitor heart rate and blood pressure regularly. Patients receiving ZYKADIA should be monitored for heart rate and blood pressure. ECG evaluations should be performed at baseline prior to initiating therapy with ZYKADIA and should be repeated periodically during treatment with ZYKADIA, to monitor for decreased heart rate and QTc prolongation (see 7 Warnings and Precautions, Cardiovascular; 10 Clinical Pharmacology, 10.2 Pharmacodynamics, Cardiac Electrophysiology). Consultation with a cardiologist should be considered when assessing the QT interval to ensure appropriate treatment decisions.
Electrolyte levels (potassium, calcium, and magnesium) should be assessed at baseline and monitored periodically during treatment with ZYKADIA, particularly in patients at risk for these electrolyte abnormalities (see 7 Warnings and Precautions, Cardiovascular; 9 Drug Interactions). Hypokalemia, hypocalcemia, and hypomagnesia should be corrected prior to ZYKADIA administration.
- Glucose Monitoring
Monitor fasting serum glucose prior to the start of ZYKADIA treatment and periodically thereafter as clinically indicated. Initiate or optimize anti-hyperglycemic medications as indicated (see 4 Dosage and Administration, 7 Warnings and Precautions and 8 Adverse Reactions).
- Lipase and Amylase Monitoring
Monitor lipase and amylase prior to the start of ZYKADIA treatment and periodically thereafter as clinically indicated (See 4 Dosage and Administration, 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic and 8 Adverse Reactions).
- Liver Function Test Monitoring
Monitor liver laboratory tests (including ALT, AST, and total bilirubin) prior to the start of treatment, and monthly thereafter. In patients who develop transaminase elevations, more frequent monitoring of liver transaminases and total bilirubin should be done as clinically indicated.
- Renal Monitoring
Monitor creatinine prior to the start of ZYKADIA treatment and periodically thereafter as clinically indicated (See 8 Adverse Reactions).
Renal
- Renal impairment
ZYKADIA has not been evaluated in patients with renal impairment in a dedicated study. However, based upon available data, ceritinib elimination via the kidney is negligible. Dose adjustment is not required for patients with mild and moderate renal impairment based upon the results of the population pharmacokinetic analyses. Caution should be used in patients with severe renal impairment as there is no experience with ZYKADIA in this population (see 10 Clinical Pharmacology).
Reproductive Health
Fertility
The potential for ZYKADIA to cause infertility in male and female patients is unknown.
- Females of Childbearing potential
Women of childbearing potential should be advised to use a highly effective method of contraception while receiving ZYKADIA and for up to 3 months after discontinuing treatment.
If ZYKADIA is used during pregnancy, or if the patient or their partner becomes pregnant while receiving ZYKADIA, the patient or their partner should be appraised of the potential hazard to the fetus or potential risk for loss of the pregnancy.
- Males patients
Adequate contraceptive methods should be used by men during therapy, and for at least 3 months after completing therapy. If the patient’s partner becomes pregnant while receiving ZYKADIA, the patient and his partner should be apprised of the potential hazard to the fetus or potential risk for loss of the pregnancy.
Respiratory
- Interstitial Lung Disease/Pneumonitis
Severe, life-threatening, or fatal interstitial lung disease (ILD)/pneumonitis have been observed in patients treated with ZYKADIA. In a pooled analysis of seven clinical studies comprised of 925 patients with ALK+ advanced NSCLC treated with ZYKADIA at a fasted dose of 750 mg daily, ILD/pneumonitis AEs were reported in 2.4% of patients – pneumonitis in 1.6%, ILD in 0.4% and lung infiltration in 0.3%. Grade 3/4 AEs were reported in 1.3% of patients – pneumonitis in 1.0%, ILD in 0.2% and lung infiltration in 0.1%.
The events required dose adjustment or interruption in 1.2% and led to discontinuation of ceritinib treatment in 1.1% of patients. The events were serious in 1.7% of patients. Two deaths due to pneumonitis were reported.
Monitor patients for pulmonary symptoms indicative of ILD/pneumonitis. Exclude other potential causes of ILD/pneumonitis and permanently discontinue ZYKADIA in patients diagnosed with treatment-related ILD/pneumonitis (see 4 Dosage and Administration and 8 Adverse Reactions).
7.1 Special Populations
7.1.1 Pregnancy
- Teratogenic Risk
Based on its mechanism of action, ZYKADIA may cause fetal harm when administered to a pregnant woman (see 7.1 Special Populations and 16 Non-Clinical Toxicology). Advise females of reproductive potential to use highly effective contraception during treatment with ZYKADIA and for up to 3 months following completion of therapy.
There are no data regarding the use of ZYKADIA in pregnant women. ZYKADIA may cause fetal harm when administered to a pregnant woman. In an embryo-fetal development study in which pregnant rats were administered daily doses of ceritinib during organogenesis, dose-related skeletal anomalies were observed at doses as low as 50 mg/kg (less than 0.5-fold the human exposure by AUC at the recommended dose). Findings included delayed ossifications and skeletal variations.
In pregnant rabbits administered ceritinib daily during organogenesis, dose-related skeletal anomalies, including incomplete ossification, were observed at doses equal to or greater than 2 mg/kg/day (approximately 0.015-fold the human exposure by AUC at the recommended dose). A low incidence of visceral anomalies, including absent or malpositioned gallbladder and retroesophageal subclavian cardiac artery, was observed at doses equal to or greater than 10 mg/kg/day (approximately 0.13-fold the human exposure by AUC at the recommended dose). Maternal toxicity and abortion occurred in rabbits at doses of 35 mg/kg or greater (approximately 0.72-fold the human exposure by AUC at the recommended dose). In addition, embryolethality was observed in rabbits at a dose of 50 mg/kg (approximately equivalent to human exposure by AUC at the recommended dose). The potential risk in humans is unknown. ZYKADIA should not be given to pregnant women unless the potential benefit outweighs the potential risk to the fetus.
7.1.2 Breastfeeding
It is unknown whether ceritinib is excreted in human milk. Because many drugs are excreted in human milk, and because of the potential for serious adverse drug reactions in breastfed newborns/infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of ZYKADIA have not been established in pediatric patients; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Across seven clinical studies in patients with ALK+ advanced NSCLC receiving a fasted dose of 750 mg daily, 168 of 925 patients (18.2%) treated with ZYKADIA were aged 65 years and older. No overall differences in safety or efficacy were observed between younger (<65 years) and older patients (≥ 65 years).
8 Adverse Reactions
8.1 Adverse Reaction Overview
Adverse events (AEs) regardless of study drug relationship described below reflect exposure to ZYKADIA in 925 patients with ALK-positive advanced NSCLC treated at a fasted dose of 750 mg taken orally once daily in seven clinical studies including studies A2301, X2101 and A2303 described below.
The median duration of exposure to ZYKADIA 750 mg fasted was 44.9 weeks (range 0.1 to 200.1 weeks).
Adverse events with an incidence of ≥20% of 925 pooled patients treated with ZYKADIA 750 mg fasted were diarrhea (82.1%), nausea (74.7%), vomiting (63.2%), alanine aminotransferase increased (51.0%), aspartate aminotransferase increased (43.4%), decreased appetite (39.5%), fatigue (33.9%), abdominal pain (31.0%), weight decreased (27.6%), constipation (24.0%), cough (23.4%), blood creatinine increased (22.1%), blood alkaline phosphatase (21.6%), gamma-glutamyl transferase increased (20.8%), headache (20.6%) and dyspnea (20.2%).
In the pooled analysis of 925 patients treated with ZYKADIA 750 mg fasted, serious adverse events (SAEs) regardless of study drug relationship were reported in 409 patients (44.2%). The most frequently reported SAEs in ≥ 1% of the patients were: pneumonia, dyspnea, nausea, vomiting, pleural effusion, seizure, pericardial effusion, pyrexia, hyperglycemia, respiratory failure, general physical health deterioration, dehydration, lung infection, pneumonitis, pulmonary embolism, pericarditis, ALT increased, asthenia, non-cardiac chest pain and diarrhea.
Adverse events requiring dose adjustment or interruption were reported in 715 patients (77.3%), among whom 498 patients (53.8%) had a grade 3/4 AE. The most frequently occurring (any grade, in ≥ 5% of the patients) AEs requiring dose adjustment or interruption were ALT increased (34.8%), AST increased (22.8%), vomiting (19.2%), nausea (16.8%), diarrhea (15.0%), blood creatinine increased (6.9%), fatigue (6.4%), decreased appetite and GGT increased (each 5.6%).
Among the 925 patients in the pooled analysis, the proportion of patients with AEs leading to permanent discontinuation of ceritinib treatment was 12.1%. The most frequent AEs (>0.5%) leading to discontinuation of ZYKADIA 750 mg fasted were pneumonia (0.6%) and respiratory failure (0.6%).
In the dose optimization study A2112 (ASCEND-8) in both previously treated and untreated patients with ALK-positive advanced NSCLC, the overall safety profile of ZYKADIA at the recommended dose of 450 mg with food (N=108) was consistent with ZYKADIA 750 mg fasted (N=110), except for a reduction in gastrointestinal adverse drug reactions, while achieving comparable steady-state exposure (see 10 Clinical Pharmacology).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Previously Untreated ALK-positive Locally Advanced or Metastatic NSCLC
Phase III study A2301
Study A2301 was an open-label, randomized, active-controlled, global, Phase III study of ceritinib (750 mg daily under fasted conditions) versus standard first-line chemotherapy (cisplatin or carboplatin with pemetrexed administered every 21 days for 4 cycles followed by pemetrexed maintenance in patients without progressive disease) in adult patients with ALK+ advanced NSCLC. Patients in the chemotherapy arm were allowed to receive ZYKADIA after BIRC-confirmed disease progression (see 14 Clinical Trials).
Overall, the majority of the patients were Caucasian (53.7%) or Asian (42.0%). The median age was 54.0 years (range: 22 to 81 years); 78.5% of patients were younger than 65 years. The majority of patients had adenocarcinoma (96.5%) and had never smoked (61.2%). The (Eastern Cooperative Oncology Group) ECOG performance status was 0/1/2 in 37.0%/56.4%/6.4% of patients respectively, and 32.2% had stable brain metastasis at baseline (see 14 Clinical Trials).
Ten patients (5.3%) in the ceritinib arm and nine patients (4.8%) in the chemotherapy arm received prior chemotherapy in the neo-adjuvant/adjuvant setting.
The median duration of exposure to the study drug was higher in the ZYKADIA arm (66.4 weeks, range: 1.0 to 144.4) compared to chemotherapy arm including pemetrexed (26.9 weeks, range: 0.7 to 126.7).
The safety population comprised patients who received at least one dose of study drug (189 in the ceritinib arm and 175 in the chemotherapy arm). All patients (100%) in the ceritinib arm and 170 patients (97.1%) in the chemotherapy arm experienced at least one AE during the treatment phase.
The most frequently reported adverse events regardless of study drug relationship in the ZYKADIA arm (in ≥ 10% of patients) included: diarrhea, nausea, vomiting, ALT increased, AST increased, GGT increased, blood ALP increased, decreased appetite, fatigue, abdominal pain, cough, weight decreased, blood creatinine increased, abdominal pain upper, non-cardiac chest pain, constipation, back pain, pyrexia, asthenia, headache, dyspnea, anemia, rash, dizziness, musculoskeletal pain, electrocardiogram QT prolonged, hyperglycemia, pain in extremity, pruritus and amylase increased.
Serious adverse events (SAE) regardless of study drug relationship were reported in 37.0% of patients in the ZYKADIA arm and 35.4% of patients in the chemotherapy arm, majority of whom were noted with grade 3/4 AEs (31.2% in ZYKADIA arm vs. 30.3% in chemotherapy arm). The most frequently reported SAEs in the ZYKADIA arm (>1%) were pneumonia, pleural effusion, vomiting, nausea, dyspnea, hyperglycemia, AST increased, pericardial effusion, ALT increased, diarrhea, back pain, lung infection, pulmonary embolism, blood creatinine increased, metastases to central nervous system, pyrexia, general physical health deterioration, fatigue, non-cardiac chest pain, atrial fibrillation, dizziness, malaise, paresthesia and hepatic function abnormal.
Adverse events that required dose adjustment or interruption were 80.4% and 44.6% in the ZYKADIA arm and chemotherapy arm, respectively. The most frequent adverse events regardless of study drug relationship reported in at least 10% of patients that led to dose adjustment or interruption were ALT increased (47.6%), AST increased (33.9%), vomiting (15.3%), blood creatinine increased (13.8%), GGT increased (13.2%), diarrhea (12.7%) and nausea (11.6%) in the ZYKADIA arm and neutropenia (10.3%) in the chemotherapy arm.
Adverse events regardless of study drug relationship that led to treatment discontinuation were reported in 21 patients (11.1%) in the ZYKADIA arm and 29 patients (16.6%) in the chemotherapy arm. The adverse events reported (in ≥ 1% of the patients) leading to discontinuation of study treatment regardless of study drug relationship were blood creatinine increased (2.1%), lipase increased (1.1%)
and amylase increased (1.1%) in the ZYKADIA arm and blood creatinine increased (3.4%), creatinine renal clearance decreased (1.7%), dyspnea (1.1%) and tinnitus (1.1%) in the chemotherapy arm.
On-treatment deaths were reported in 11 patients (5.8%) in the ZYKADIA arm, 7 due to disease progression and 4 patients due to AEs (one each for myocardial infarction, respiratory tract infection, pneumonitis, and unknown cause).
Table 3 lists the incidences of very common and common adverse reactions in patients receiving ZYKADIA 750 mg fasted in Study A2301.
Table 3 – Adverse drug reactions ≥ 1% in patients treated with ZYKADIA at a dose of 750 mg fasted in Study A2301
| System organ class/preferred term | Ceritinib N=189 | Chemotherapy N=175 | |||||||||||
| System organ class/preferred term | Ceritinib N=189 | Chemotherapy N=175 | |||||||||||
| System organ class/preferred term | Ceritinib N=189 | Chemotherapy N=175 | |||||||||||
All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
| Blood And Lymphatic System Disorders | |||||||||||||
| Anemia | 28 (14.8) | 4 (2.1) | 62 (35.4) | 13 (7.4) | |||||||||
| Cardiac Disorders | |||||||||||||
| Bradycardiae | 6 (3.2) | 0 | 1 (0.6) | 0 | |||||||||
| Pericarditish | 8 (4.2) | 3 (1.6) | 3 (1.7) | 2 (1.1) | |||||||||
| Eye Disorders | |||||||||||||
| Vision disorderl | 7 (3.7) | 0 | 7 (4.0) | 0 | |||||||||
| Gastrointestinal Disorders | |||||||||||||
| Abdominal Paina | 75 (39.7) | 7 (3.7) | 20 (11.4) | 0 | |||||||||
| Constipation | 36 (19.0) | 0 | 38 (21.7) | 0 | |||||||||
| Diarrhea | 160 (84.7) | 10 (5.3) | 19 (10.9) | 2 (1.1) | |||||||||
| Nausea | 130 (68.8) | 5 (2.6) | 97 (55.4) | 9 (5.1) | |||||||||
| Esophageal disorderf | 28 (14.8) | 1 (0.5) | 13 (7.4) | 1 (0.6) | |||||||||
| Vomiting | 125 (66.1) | 10 (5.3) | 63 (36.0) | 10 (5.7) | |||||||||
| General Disorders And Administration Site Conditions | |||||||||||||
| Fatigueg | 83 (43.9) | 13 (6.9) | 85 (48.6) | 11 (6.3) | |||||||||
| Back pain | 36 (19.0) | 3 (1.6) | 32 (18.3) | 4 (2.3) | |||||||||
| Pain in extremity | 21 (11.1) | 0 | 13 (7.4) | 0 | |||||||||
| Hepatobiliary Disorders | |||||||||||||
| Abnormal liver function testsc | 3 (1.6) | 2 (1.1) | 2 (1.1) | 1 (0.6) | |||||||||
| Hepatotoxicityd | 4 (2.1) | 1 (0.5) | 1 (0.6) | 0 | |||||||||
| Investigations | |||||||||||||
| Amylase Increased | 19 (10.1) | 9 (4.8) | 9 (5.1) | 3 (1.7) | |||||||||
| Blood Creatinine Increased | 42 (22.2) | 4 (2.1) | 17 (9.7) | 0 | |||||||||
| Electrocardiogram QT Prolonged | 21(11.1) | 4 (2.1) | 2 (1.1) | 1 (0.6) | |||||||||
| Lipase Increased | 7 (3.7) | 7 (3.7) | 0 | 0 | |||||||||
| Liver laboratory test abnormalitiesb | 130 (68.8) | 94 (49.7) | 50 (28.6) | 10 (5.7) | |||||||||
| Weight Decreased | 45 (23.8) | 7 (3.7) | 26 (14.9) | 1 (0.6) | |||||||||
| Metabolism And Nutrition Disorders | |||||||||||||
| Decreased Appetite | 64 (33.9) | 2 (1.1) | 55 (31.4) | 2 (1.1) | |||||||||
| Hyperglycemia | 21 (11.1) | 12 (6.3) | 13 (7.4) | 5 (2.9) | |||||||||
| Hypophosphatemia | 8 (4.2) | 3 (1.6) | 0 | 0 | |||||||||
| Renal And Urinary Disorders | |||||||||||||
| Renal Failurek | 4 (2.1) | 0 | 3 (1.7) | 1 (0.6) | |||||||||
| Respiratory, Thoracic And Mediastinal Disorders | |||||||||||||
| Pneumonitisi | 3 (1.6) | 1 (0.5) | 0 | 0 | |||||||||
| Skin And Subcutaneous Tissue Disorders | |||||||||||||
| Rashj | 38 (20.1) | 2 (1.1) | 14 (8.0) | 1 (0.6) | |||||||||
Includes cases reported within the clustered terms: a Abdominal pain includes PTs of Abdominal Pain, Abdominal Pain Upper, Abdominal Discomfort, Epigastric Discomfort b Liver laboratory test abnormalities includes PTs of Alanine Aminotransferase Increased, Aspartate Aminotransferase Increased, Gamma-Glutamyltransferase Increased, Blood Bilirubin Increased, Transaminases Increased, Hepatic Enzyme Increased, Liver Function Test Abnormal, Liver Function Test Increased, Blood Alkaline Phosphatase Increased c Abnormal liver function tests includes PTs of Hepatic Function Abnormal, Hyperbilirubinemia d Hepatotoxicity includes PTs of Drug-Induced Liver Injury, Hepatitis Cholestatic, Hepatocellular Injury, Hepatotoxicity e Bradycardia includes PTs of Bradycardia and Sinus Bradycardia f Esophageal Disorder includes PTs of Dyspepsia, Gastroesophageal Reflux Disease, Dysphagia g Fatigue includes PTs of Fatigue and Asthenia h Pericarditis includes PTs of Pericardial Effusion and Pericarditis i Pneumonitis includes PTs of Interstitial Lung Disease (ILD) and Pneumonitis j Rash includes PTs of Rash, Dermatitis Acneiform, Rash Maculo-Papular k Renal Failure includes PTs of Acute Renal Injury and Renal Failure l Vision disorder includes PTs of Visual Impairment, Vision Blurred, Photopsia, Vitreous Floaters, Visual Acuity Reduced, Accommodation Disorder, Presbyopia | |||||||||||||
Previously Treated ALK-positive Locally Advanced or Metastatic NSCLC
Phase I Study X2101
Study X2101 was a single arm, phase I, open-label, dose-escalation and expansion study investigating the safety, pharmacokinetics, and anti-tumor activity of ZYKADIA in patients with tumors confirmed to have genetic abnormalities in ALK. Adverse drug reaction (ADR) information is based on safety data from this registration study in 255 patients (246 ALK-positive NSCLC patients and 9 non-NSCLC patients) treated at a dose of 750 mg of ZYKADIA under fasted conditions.
The Study X2101 population characteristics were: median age 53 years, age less than 65 (84.3%), female (53.3%), Caucasian (62.7%), Asian (34.1%), Others (3.1%), NSCLC adenocarcinoma histology (89.8%), never or former smoker (96.9%), ECOG PS 0 or 1 (88.6%), brain metastasis (48.6%), and number of prior therapies 2 or more (66.7%).
The median exposure to ZYKADIA was 43.0 weeks (range: 0.4 to 200.1 weeks). The median dose intensity was 610.3 mg/day (range: 226.5 mg/day to 750 mg once daily fasted). Dosing interruptions due to adverse events occurred in 88.9% of patients. Dose reductions due to adverse events occurred in 97.5% of patients. The most frequent adverse events reported in at least 10% of patients that led to dose reduction or interruption were ALT increased (32.5%), nausea (20.8%), diarrhea (19.2%), AST increased (18.8%), and vomiting (18.0%).
In Study X2101, 54.5% of patients permanently discontinued the treatment due to disease progression and 11.0% due to an AE as primary reason for discontinuation. The most frequent AEs that led to discontinuation in more than 1 patient were pneumonia (1.6%), respiratory failure (1.2%), pneumonitis (0.8%), decreased appetite (0.8%), general physical health deterioration (0.8%), and nausea (0.8%).
In Study X2101, 56.9% of patients reported a SAE. SAEs with an incidence of ≥1% were: pneumonia (7.5%), seizure (6.3%), dyspnea (5.9%), pneumonitis (3.5%), respiratory failure (2.4%), pericardial effusion (2.4%), general physical health deterioration (2.4%), hyperglycemia (2.4%), nausea (2.4%), ALT increased (2.0%), headache (2.0%), pericarditis (2.0%), dehydration (1.6%), pneumothorax (1.6%), non-cardiac chest pain (1.6%), pyrexia (1.6%), vomiting (1.2%), AST increased (1.2%), pulmonary embolism (1.2%), ataxia (1.2%), diarrhea (1.2%), pleural effusion (1.2%), and sepsis (1.2%).
Deaths in patients during treatment or within 28 days of last dose with ZYKADIA occurred in 17.3% including 11.8% of deaths due to study indication and 5.5% of patients, consisting of: pneumonia (3 patients), respiratory failure (3 patients), ILD/pneumonitis, pneumothorax, gastric hemorrhage, pulmonary tuberculosis, cardiac tamponade, multi-organ failure, euthanasia and sepsis (1 patient each).
Table 4 lists the incidences of very common and common adverse reactions in patients receiving ZYKADIA 750 mg fasted in Study X2101.
Table 4 – Adverse drug reactions ≥1% in patients treated at a dose of 750 mg fasted in Study X2101
| System organ class/preferred term | Ceritinib N=255 | |||||||
|---|---|---|---|---|---|---|---|---|
| System organ class/preferred term | Ceritinib N=255 | |||||||
All Grades n (%) | Grade 3/4 n (%) | |||||||
All Grades n (%) | Grade 3/4 n (%) | |||||||
| Blood and lymphatic system disorders | ||||||||
| Anemia | 34 (13.3) | 13 (5.1) | ||||||
| Cardiac disorders | ||||||||
| Bradycardiaa | 9 (3.5) | 0 | ||||||
| Eye disorders | ||||||||
| Vision disorderb | 34 (13.3) | 0 | ||||||
| Gastrointestinal disorders | ||||||||
| Diarrhea | 221 (86.7) | 16 (6.3) | ||||||
| Nausea | 216 (84.7) | 17 (6.7) | ||||||
| Vomiting | 160 (62.7) | 15 (5.9) | ||||||
| Abdominal painc | 145 (56.9) | 6 (2.4) | ||||||
| Constipation | 91 (35.7) | 0 | ||||||
| Esophageal disorderd | 55 (21.6) | 2 (0.8) | ||||||
| General disorders and administration site conditions | ||||||||
| Fatiguee | 148 (58) | 17 (6.7) | ||||||
| Investigations | ||||||||
| Alanine aminotransferase increased | 122 (47.8) | 81 (31.8) | ||||||
| Aspartate aminotransferase increased | 91 (35.7) | 36 (14.1) | ||||||
| Blood creatinine increased | 48 (18.8) | 0 | ||||||
| Lipase increased | 35 (13.7) | 23 (9.0) | ||||||
| Electrocardiogram QT prolonged | 12 (4.7) | 3 (1.2) | ||||||
| Blood bilirubin increased | 10 (3.9) | 1 (0.4) | ||||||
| Metabolism and nutrition disorders | ||||||||
| Decreased appetite | 99 (38.8) | 5 (2.0) | ||||||
| Hyperglycemia | 26 (10.2) | 17 (6.7) | ||||||
| Hypophosphatemia | 19 (7.5) | 10 (3.9) | ||||||
| Nervous system disorders | ||||||||
| Neuropathyf | 44 (17.3) | 0 | ||||||
| Renal and urinary disorders | ||||||||
| Renal failureg | 6 (2.4) | 1 (0.4) | ||||||
| Renal impairmenth | 5 (2.0) | 1 (0.4) | ||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||
| Pneumonitisi | 12 (4.7) | 9 (3.5) | ||||||
| Skin and subcutaneous tissue disorders | ||||||||
| Rashj | 50 (19.6) | 0 | ||||||
| Includes cases reported within the clustered terms: a Bradycardia (bradycardia, sinus bradycardia) b Vision disorder (vision impairment, vision blurred, photopsia, vitreous floaters, accommodation disorder, presbyopia, visual acuity reduced) c Abdominal pain (abdominal pain, abdominal pain upper, abdominal discomfort, epigastric discomfort) d Esophageal disorder (dyspepsia, gastroesophageal reflux disease, dysphagia) e Fatigue (fatigue, asthenia) f Neuropathy (paraesthesia, muscular weakness, gait disturbance, neuropathy peripheral, hypoaesthesia, peripheral sensory neuropathy, dysaesthesia, neuralgia, peripheral motor neuropathy, hypotonia, polyneuropathy) g Renal failure (acute kidney injury, renal failure) h Renal impairment (azotemia, renal impairment) i Pneumonitis (interstitial lung disease, pneumonitis) j Rash (rash, rash maculo-papular, dermatitis acneiform) | ||||||||
Phase III Study A2303
Study A2303 was a Phase III, randomized, open-label study of ZYKADIA versus standard chemotherapy (pemetrexed/docetaxel) in adult patients. Patients in the chemotherapy arm were allowed to cross-over to the ZYKADIA 750 mg fasted arm after BIRC-confirmed PD. Adverse drug reaction (ADR) information is based on safety data from this registration study in 115 patients.
In Study A2303, population characteristics were: median age 54.0 years (range: 28 to 84 years), age less than 65 (77.1%), female (55.8%), Caucasians (64.5%), Asians (29.4%), Blacks (0.4%) and other races (2.6%). The majority of patients had adenocarcinoma (97.0%) and had either never smoked or were former smokers (96.1%). The ECOG performance status was 0/1/2 in 46.3%/47.6%/6.1% of patients respectively, and 58.0% had brain metastasis at baseline. All patients were treated with prior crizotinib. All except one patient received prior chemotherapy (including a platinum doublet) for advanced disease; 11.3% of the patients in the ZYKADIA arm and 12.1% of the patients in the chemotherapy arm were treated with two prior chemotherapy regimens for advanced disease.
The median duration of exposure to the study drug was higher in the ZYKADIA arm (30.3 weeks, range: 0.3 to 122.9) compared to chemotherapy arm (6.3 weeks, range: 3.0 to 69.1; pemetrexed: 14.1 weeks, range: 3.0 to 69.1; docetaxel: 6.1 weeks, range: 3.0 to 36.0).
The safety population comprised patients who received at least one dose of study drug (115 in the ceritinib arm and 113 in the chemotherapy arm). All patients (100%) in the ceritinib arm and all but one (99%) patient in the chemotherapy arm experienced at least one AE during the treatment phase. The overall incidence of severe (Grade 3/4) adverse events was higher in the ZYKADIA than in the chemotherapy arm (77% vs 64%) as was the incidence of serious adverse events (43% vs 32%). Adverse events requiring dose modification (reduction, interruption or delay) were reported in 80% of patients in the ZYKADIA arm and 38% of patients in the chemotherapy arm. The most common adverse events requiring dose modifications in the ceritinib arm were hepatotoxicity in 36.5% of patients and GI toxicity in 34.8% of patients.
Table 5 lists the incidences of very common and common adverse reactions in patients receiving ZYKADIA 750 mg fasted in Study A2303.
Table 5 – Adverse drug reactions ≥1% in patients treated at a dose of 750 mg fasted in Study A2303
| System organ class/preferred term | Ceritinib N=115 | Chemotherapy N=113 | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| System organ class/preferred term | Ceritinib N=115 | Chemotherapy N=113 | |||||||||||
| System organ class/preferred term | Ceritinib N=115 | Chemotherapy N=113 | |||||||||||
| All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
| All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
| All Grades n (%) | Grades 3/4 n (%) | All Grades n (%) | Grades 3/4 n (%) | ||||||||||
| Blood And Lymphatic System Disorders | |||||||||||||
| Anemia | 6 (5.2) | 0 | 19 (16.8) | 5 (4.4) | |||||||||
| Cardiac Disorders | |||||||||||||
| Pericarditisg | 8 (7.0) | 4 (3.5) | 1 (0.9) | 1 (0.9) | |||||||||
| Bradycardiad | 3 (2.6) | 0 | 1 (0.9) | 0 | |||||||||
| Eye Disorders | |||||||||||||
| Vision disorderl | 4 (3.5) | 0 | 3 (2.7) | 1 (0.9) | |||||||||
| Gastrointestinal Disorders | |||||||||||||
| Diarrhea | 83 (72.2) | 5 (4.3) | 20 (17.7) | 1 (0.9) | |||||||||
| Nausea | 76 (66.1) | 9 (7.8) | 26 (23.0) | 2 (1.8) | |||||||||
| Vomiting | 60 (52.2) | 9 (7.8) | 6 (5.3) | 1 (0.9) | |||||||||
| Abdominal Paina | 41 (35.7) | 2 (1.7) | 17 (15.0) | 1 (0.9) | |||||||||
| Constipation | 22 (19.1) | 0 | 15 (13.3) | 0 | |||||||||
| Esophageal disordere | 10 (8.7) | 1 (0.9) | 4 (3.5) | 0 | |||||||||
| General Disorders And Administration Site Conditions | |||||||||||||
| Fatiguef | 54 (47.0) | 11 (9.6) | 53 (46.9) | 12 (10.6) | |||||||||
| Back pain | 25 (21.7) | 1 (0.9) | 8 (7.1) | 3 (2.7) | |||||||||
| Hepatobiliary Disorders | |||||||||||||
| Abnormal liver function testsb | 4 (3.5) | 0 | 2 (1.8) | 1 (0.9) | |||||||||
| Hepatotoxicityc | 2 (1.7) | 0 | 0 | 0 | |||||||||
| Investigations | |||||||||||||
| Alanine Aminotransferase (ALT) Increased | 49 (42.6) | 24 (20.9) | 10 (8.8) | 2 (1.8) | |||||||||
| Aspartate Aminotransferase (AST) Increased | 42 (36.5) | 16 (13.9) | 5 (4.4) | 1 (0.9) | |||||||||
| Weight Decreased | 34 (29.6) | 3 (2.6) | 7 (6.2) | 1 (0.9) | |||||||||
| Gamma-Glutamyl transferase (GGT) Increased | 26 (22.6) | 24 (20.9) | 2 (1.8) | 1 (0.9) | |||||||||
| Blood Creatinine Increased | 22 (19.1) | 0 | 0 | 0 | |||||||||
| Electrocardiogram QT Prolonged | 13 (11.3) | 1 (0.9) | 0 | 0 | |||||||||
| Amylase Increased | 7 (6.1) | 5 (4.3) | 3 (2.7) | 3 (2.7) | |||||||||
| Blood Bilirubin Increased | 1 (0.9) | 0 | 1 (0.9) | 0 | |||||||||
| Metabolism And Nutrition Disorders | |||||||||||||
| Decreased Appetite | 48 (41.7) | 2 (1.7) | 22 (19.5) | 3 (2.7) | |||||||||
| Hyperglycemia | 8 (7.0) | 6 (5.2) | 3 (2.7) | 2 (1.8) | |||||||||
| Hypophosphatemia | 3 (2.6) | 0 | 4 (3.5) | 1 (0.9) | |||||||||
| Renal And Urinary Disorders | |||||||||||||
| Renal Failurej | 1 (0.9) | 0 | 0 | 0 | |||||||||
| Renal Impairmentk | 1 (0.9) | 0 | 0 | 0 | |||||||||
| Respiratory, Thoracic And Mediastinal Disorders | |||||||||||||
| Pneumonitish | 1 (0.9) | 1 (0.9) | 3 (2.7) | 3 (2.7) | |||||||||
| Skin And Subcutaneous Tissue Disorders | |||||||||||||
| Rashi | 15 (13.0) | 0 | 14 (12.4) | 0 | |||||||||
Includes cases reported within the clustered terms: aAbdominal Pain, Abdominal Pain Upper, Abdominal Discomfort, Epigastric Discomfort bHepatic Function Abnormal, Hyperbilirubinaemia cDrug-Induced Liver Injury, Hepatitis Cholestatic, Hepatocellular Injury, Hepatotoxicity dBradycardia, Sinus Bradycardia eDyspepsia, Gastrooesophageal Reflux Disease, Dysphagia fFatigue, Asthenia gPericardial Effusion Pericarditis hInterstitial Lung Disease, Pneumonitis iRash, Dermatitis Acneiform, Rash Maculo-Papular jAcute kidney Injury, Renal Failure kAzotaemia, Renal Impairment lVisual Impairment, Vision Blurred, Photopsia, Vitreous Floaters, Visual Acuity Reduced, Accommodation Disorder, Presbyopia | |||||||||||||
Phase I Study A2112
Study A2112 was a Phase I, randomized, open-label study in which the systemic exposure, efficacy, and safety of ZYKADIA administered once daily at 450 mg or 600 mg with a low-fat meal was assessed versus 750 mg under fasted conditions. Adverse drug reaction (ADR) information is based on safety data from this study in 304 patients.
In Study A2112, population characteristics were: median age 54.0 years (range: 21 to 87 years), age less than 65 (79.7%), female (50.7%), Caucasians (59.8%), Asians (33.3%), Blacks (0.7%) and Other (3.9%). The majority of patients had adenocarcinoma (94.8%) and had either never smoked (59.2%) or were former smokers (34.6%). The WHO performance status was 0/1/2 in 32.7%/58.8%/8.5% of patients respectively, and 35.6% had brain metastasis at baseline.
Overall, 211 patients (69.0%) did not receive any prior regimen of anti-cancer medication (69.4% of patients in the 450 mg fed arm, 64.4% of patients in the 600 mg fed arm and 72.1% of patients in the 750 mg fasted arm). Six (5.6%), five (5.7%), and three patients (2.7%) received at least 3 prior lines of anti-cancer regimens, in the 450 mg fed arm, 600 mg fed arm, and 750 mg fasted arm, respectively. Most frequently used anti-cancer medications (>20.0% of all patients in FAS) were cisplatin (22.5%), crizotinib (21.6%) and pemetrexed (21.2%).
The safety population comprised patients who received at least one dose of study drug (108 in 450 mg fed arm, 86 in 600 mg fed arm and 110 in 750 mg fasted arm.
Overall, the median duration of exposure was 78.21 weeks (range: 0.3 to 228.1) for all treated patients, and was similar across the three treatment arms.
Almost all treated patients (99.0%) reported at least one adverse event; the proportion of patients who experienced one adverse event regardless of study drug relationship was similar across the three treatment arms (100.0% of patients in the 450 mg fed arm, 97.7% in the 600 mg fed arm, and 99.1% in the 750 mg fasted arm).
Overall, 107 (35.2%) patients experienced any grade serious adverse events, regardless of study drug relationship during the on-treatment period with a lower proportion of patients in the 450 mg fed arm (32.4%) and 750 mg fasted arm (30.9%), compared to 600 mg fed arm (44.2%). The proportions of patients with serious adverse events suspected to study drug was low (10.9% patients) specially in the 450 mg fed (7.4%) and the 750 mg fasted (10.9%) treatment arms compared to 15.1% in the 600 mg treatment arm.
The proportion of patients with adverse events that led to study drug discontinuation was similar among treatment arms: 26 (8.6%) patients (nine, seven and ten patients in the 450 mg fed arm, in the 600 mg fed arm and in the 750 mg fasted arm, respectively).
Overall 70.1% of patients were reported with adverse events that required dose adjustment or study drug interruption which was lowest (56.5%) in the 450 mg fed arm compared to 77.9% in the 600 mg fed arm and 77.3% in the 750 mg fasted arm.
The incidence and severity of gastrointestinal adverse drug reactions (diarrhea 59.3%, nausea 42.6%, vomiting 38.0%; 0.9% reported a Grade 3/4 event) were reduced for patients treated with ZYKADIA 450 mg with food compared to 750 mg fasted (diarrhea 80.0%, nausea 60.0%, vomiting 65.5%; 4.5% reported a Grade 3/4 event). In patients treated with ZYKADIA 450 mg with food, 24.1% of patients had at least one adverse event that required dose reduction and 55.6% of patients had at least one adverse event that required study drug interruption.
8.3 Less Common Clinical Trial Adverse Reactions
Less Common Clinical Trial Adverse Drug Reactions (<1%) in study X2101
Gastrointestinal disorders
Uncommon: Pancreatitis
Hepatobiliary disorders
Uncommon: Drug-induced liver injury
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry, and Other Quantitative Data
Clinical Trial Findings
Previously Untreated ALK-positive Locally Advanced or Metastatic NSCLC
Table 6 – Key Laboratory Abnormalities Occurring in >10% (All NCI CTCAE Grades) of patients treated with ZYKADIA at a dose of 750 mg fasted in Study A2301
| Ceritinib N=189 | Chemotherapy N=175 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
All Grades n (%) | Grade 3/4 n (%) | All Grades n (%) | Grade 3/4 n (%) | ||||||||
| Chemistry | |||||||||||
| Alanine transaminase (ALT) increased | 92.6 | 33.9 | 66.3 | 3.4 | |||||||
| Aspartate transaminase (AST) increased | 87.8 | 20.1 | 59.4 | 2.3 | |||||||
| Gamma-Glutamyl transferase (GGT) Increased | 84.7 | 48.7 | 69.1 | 9.1 | |||||||
| Increased alkaline phosphatase | 81.5 | 11.6 | 46.9 | 1.7 | |||||||
| Creatinine increased | 78.8 | 4.2 | 37.1 | 0.6 | |||||||
| Glucose increased | 51.9 | 10.1 | 69.1 | 10.3 | |||||||
| Phosphate decreased | 37.6 | 3.7 | 27.4 | 3.4 | |||||||
| Amylase increased | 37.0 | 7.4 | 44.0 | 4.6 | |||||||
| Increased bilirubin (total) | 16.4 | 0.5 | 6.9 | 0.6 | |||||||
| Hematology | |||||||||||
| Hemoglobin decreased | 68.8 | 3.7 | 85.7 | 10.9 | |||||||
| Neutrophils decreased | 28.0 | 2.1 | 60.0 | 19.4 | |||||||
| Platelets decreased | 17.5 | 1.0 | 39.4 | 5.1 | |||||||
Previously Treated ALK-positive Locally Advanced or Metastatic NSCLC
Table 7 – Key Laboratory Abnormalities Occurring in >10% (All NCI CTCAE Grades) of patients treated at a dose of 750 mg fasted in Study X2101
| Ceritinib N=255 | |||||||
|---|---|---|---|---|---|---|---|
| Ceritinib N=255 | |||||||
All Grades n (%) | Grade 3/4 n (%) | ||||||
All Grades n (%) | Grade 3/4 n (%) | ||||||
| Chemistry | |||||||
| Alanine transaminase (ALT) increased | 83.9 | 32.1 | |||||
| Aspartate transaminase (AST) increased | 77.6 | 18.1 | |||||
| Creatinine increased | 51.4 | 2.4 | |||||
| Glucose increased | 58 | 15.3 | |||||
| Uric acid increased | 50.2 | 9.0 | |||||
| Phosphate decreased | 43.9 | 9.0 | |||||
| Amylase increased | 32.9 | 8.3 | |||||
| Lipase increased | 34.1 | 14.1 | |||||
| Bilirubin (total) increased | 20.4 | 0.8 | |||||
| Hematology | |||||||
| Hemoglobin decreased | 85.9 | 7.1 | |||||
| Lymphocytes decreased | 79.2 | 35.7 | |||||
| Neutrophils decreased | 30.6 | 3.9 | |||||
Table 8 – Key Laboratory Abnormalities Occurring in >10% (All NCI CTCAE Grades) of patients treated at a dose of 750 mg fasted in Study A2303
| Ceritinib N=115 | Chemotherapy N=113 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
All Grades n (%) | Grade 3/4 n (%) | All Grades n (%) | Grade 3/4 n (%) | ||||||||||
| Chemistry | |||||||||||||
| Alanine transaminase (ALT) increased | 80.9 | 24.3 | 45.1 | 2.7 | |||||||||
| Creatinine increased | 79.1 | 0 | 20.3 | 0 | |||||||||
| Aspartate transaminase (AST) increased | 75.6 | 14.8 | 32.7 | 1.8 | |||||||||
| Gamma-Glutamyl transferase (GGT) Increased | 74.8 | 40.0 | 44.2 | 5.3 | |||||||||
| Glucose increased | 49.6 | 9.6 | 46.0 | 6.2 | |||||||||
| Phosphate decreased | 40.0 | 5.2 | 22.1 | 2.7 | |||||||||
| Amylase increased | 37.4 | 5.2 | 26.5 | 5.3 | |||||||||
| Hematology | |||||||||||||
| Lymphocytes decreased | 67.0 | 18.3 | 60.2 | 23.9 | |||||||||
| Hemoglobin decreased | 64.3 | 0.9 | 50.4 | 4.4 | |||||||||
| Neutrophils decreased | 20.9 | 1.7 | 39.9 | 26.6 | |||||||||
9 Drug Interactions
9.4 Drug-Drug Interactions
The drugs listed in this table are based on drug interaction case reports, drug interaction studies, or potential drug interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 9 – Established or Potential Drug-Drug Interactions
| [Non-proprietary name(s) of the drug product(s)] | Source of evidence | Effect | Clinical comment |
CYP3A Inhibitors (e.g., ritonavir, saquinavir, telithromycin, ketoconazole, itraconazole, voriconazole, posaconazole, and nefazodone) | CT | Increased ceritinib plasma concentration | Avoid concomitant use of strong CYP3A inhibitors. Exercise caution with concomitant use of moderate CYP3A inhibitors and carefully monitor adverse drug reactions. |
| P-gp Inhibitors | CT | Increased ceritinib plasma concentration | Exercise caution with concomitant use of P-gp inhibitors and carefully monitor adverse drug reactions. |
CYP3A and P-gp Inducers (e.g. carbamazepine, phenobarbital, phenytoin, rifabutin, rifampin, and St. John’s Wort (Hypericum perforatum)) | CT | Decreased ceritinib plasma concentration | Avoid concomitant use of strong CYP3A inducers. Exercise caution with concomitant use of P-gp inducers. |
CYP3A and CYP2C9 Substrates (e.g. midazolam, cyclosporine, dihydroergotamine, ergotamine, fentanyl, pimozide, quinidine, tacrolimus, alfentanil, sirolimus, phenytoin and warfarin) | CT | Plasma concentration of the substrate(s) may be altered by ceritinib | Avoid co-administration of ZYKADIA with substrates primarily metabolized by CYP3A or CYP3A substrates known to have narrow therapeutic indices. If unavoidable, consider dose reduction for co-administered medicines that are CYP3A substrates with narrow therapeutic indices. Avoid co-administration of ZYKADIA with substrates primarily metabolized by CYP2C9 or CYP2C9 substrates known to have narrow therapeutic indices. If unavoidable, consider dose reduction for co-administered medicines that are CYP2C9 substrates with narrow therapeutic indices. Increase the frequency of international normalized ratio (INR) monitoring if co-administration with warfarin is unavoidable as the anti-coagulant effect of warfarin may be enhanced. |
| CYP2A6 and CYP2E1 Substrates | CT | Ceritinib increases plasma concentrations of co-administered drugs | Exercise caution with concomitant use of CYP2A6 and CYP2E1 substrates and carefully monitor adverse drug reactions. |
Other CYP substrates (e.g. CYP1A2, CYP2B6, CYP2C8, CYP2C19, and CYP2D6) | CT | Plasma concentration of the substrate(s) may be altered by ceritinib | Drug-drug interactions are unlikely to occur as a result of ceritinib-mediated inhibition of the metabolism of drugs that are substrates for CYP1A2, CYP2B6, CYP2C8, CYP2C19, and CYP2D6. |
Antacids, H2-receptor antagonists, or proton-pump inhibitors (e.g., esomeprazole) | CT | Alter the solubility of ceritinib and reduce its bioavailability | When the concurrent use of a H2-receptor antagonist or an antacid with ceritinib is necessary, the H2 blocker should be administered 10 hours before or 2 hours after the ceritinib dose, and the antacid should be administered 2 hours before or 2 hours after the ceritinib dose. |
Heart Rate-Lowering Drugs (e.g., beta-blockers, digitalis glycosides, non-dihydropyridine calcium channel blockers, cholinesterase inhibitors, alpha2-adrenoceptor agonists, and sphingosine-1 phosphate receptor modulators) | CT | Asymptomatic bradycardia | Avoid using ZYKADIA in combination with other bradycardic agents. (See 7 Warnings and Precautions, Cardiovascular, Monitoring and Laboratory Tests; 10 Clinical Pharmacology, 10.2 Pharmacodynamics, Cardiac Electrophysiology). |
Anti-arrhythmic medicines (e.g., quinidine, amiodarone, flecainide) Other drugs that may prolong the QT interval (e.g., chlorpromazine, fluoxetine, methadone, erythromycin, moxifloxacin, pentamidine, quinine, chloroquine, ketoconazole, domperidone, ondansetron, sunitinib, arsenic trioxide, vorinostat, salmeterol) | CT | Anti-arrhythmic Medicines and Other Drugs That May Prolong the QT Interval | The concomitant use of ZYKADIA with QT interval-prolonging drugs should be avoided to the extent possible (See 7 Warnings and Precautions, Cardiovascular, Monitoring and Laboratory Tests; 10 Clinical Pharmacology, 10.2 Pharmacodynamics, Cardiac Electrophysiology). |
Medicines and Other Drugs that May Affect Electrolytes (e.g., loop, thiazide, and related diuretics; laxatives and enemas; amphotericin B and high-dose corticosteroids) | CT | Medicines and Other Drugs that May Affect Electrolytes | Caution should be observed if ZYKADIA is administered with drugs that can disrupt electrolyte levels. Current information sources should be consulted for newly approved drugs that decrease heart rate, prolong the QT/QTc interval, or decrease electrolytes, as well as for older drugs for which these effects have recently been established. |
Legend: CT = Clinical Trial.
Drugs That May Increase Ceritinib Plasma Concentrations
CYP3A Inhibitors
Ceritinib is primarily metabolized by CYP3A and is a substrate of CYP3A. Co-administration of a single 450 mg fasted ceritinib dose with ketoconazole (a strong CYP3A/P-gp inhibitor) 200 mg twice daily for 14 days increased ceritinib AUC (90% CI) by 2.9-fold (2.5, 3.3) and Cmax (90% CI) by 1.2-fold (1.1, 1.4) in 19 healthy subjects.
The steady-state AUC and Cmax of ceritinib at reduced doses after co-administration with ketoconazole 200 mg twice daily for 14 days was predicted by simulations to be similar to the steady-state AUC and Cmax of ceritinib alone.
P-gp Inhibitors
Based on in vitro data, ceritinib is a substrate of the efflux transporter P-glycoprotein (P-gp).
Drugs That May Decrease Ceritinib Plasma Concentrations
CYP3A and P-gp Inducers
Co-administration of a single 750 mg fasted ceritinib dose with rifampin (a strong CYP3A/P-gp inducer) 600 mg daily for 14 days decreased ceritinib AUC (90% CI) by 70% (61%, 77%) and Cmax (90% CI) by 44% (24%, 59%) in 19 healthy subjects.
Drugs Whose Plasma Concentrations May Be Altered by Ceritinib
CYP3A and CYP2C9 Substrates
Based on in vitro data, ceritinib competitively inhibits the metabolism of CYP3A and CYP2C9 substrates. Time-dependent inhibition of CYP3A was also observed. Co-administration of a single dose of midazolam (a sensitive CYP3A substrate) following 3 weeks of ZYKADIA dosing in patients (750 mg daily fasted) increased the midazolam AUCinf (90% CI) by 5.4-fold (4.6, 6.3) compared to midazolam alone.
Enzyme induction studies in primary human hepatocytes indicate that there is a potential for ceritinib to be an inducer of CYP3A in vivo. However, due to the concomitant time-dependent inhibition of CYP3A and observed decrease in CL/F of ceritinib after multiple dosing relative to a single dose in Study X2101, it is unlikely that ceritinib would act as a CYP3A inducer clinically.
Co-administration of a single dose of warfarin (a CYP2C9 substrate) following 3 weeks of ZYKADIA dosing in patients (750 mg daily fasted) increased the S-warfarin AUCinf (90% CI) by 54% (36%, 75%) compared to warfarin alone.
CYP2A6 and CYP2E1 Substrates
Based on in vitro data, ceritinib also inhibits CYP2A6 and CYP2E1 at clinically relevant concentrations.
Other CYP substrates
In vitro studies indicated that clinical drug-drug interactions are unlikely to occur.
Drugs That Are Substrates of Transporters
Based on in vitro data, ceritinib does not inhibit apical efflux transporters, BCRP, P-gp or MRP2, hepatic uptake transporters OATP1B1 or OATP1B3, renal organic anion uptake transporters OAT1 and OAT3, or the organic cation uptake transporters OCT1 or OCT2 at clinically relevant concentrations. Therefore, clinical drug-drug interactions as a result of ceritinib-mediated inhibition of substrates for these transporters are unlikely to occur.
Gastric acid reducing agents
Ceritinib demonstrates pH-dependent solubility and becomes poorly soluble as pH increases in vitro. In a drug interaction study in healthy subjects (N=22), co-administration of a single dose of 750 mg of ceritinib fasted and esomeprazole (a proton pump inhibitor) at 40 mg daily for 6 days decreased the ceritinib AUC by 76% (90% CI: 66%, 83%) and Cmax by 79% (90% CI: 70%, 86%). However, coadministration of a single 750 mg ceritinib dose fasted with proton pump inhibitors for 6 days in a subgroup of patients from Study X2101 suggested less effect on ceritinib exposure than that observed in healthy subjects as AUC (90% CI) decreased by 30% (0%, 52%) and Cmax (90% CI) decreased by 25% (5%, 41%) and no clinically meaningful effect on ceritinib exposure was observed at steady-state after ceritinib once daily dosing.
Heart Rate-Lowering Drugs
Asymptomatic cases of bradycardia have been observed in patients treated with ZYKADIA.
QT Interval-Prolonging Drugs
Drugs that have been associated with QT interval prolongation and/or torsade de pointes include, but are not limited to, the examples in the following list. Chemical/pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QT/QTc interval prolongation and/or torsade de pointes:
- Class IA antiarrhythmics (e.g., quinidine, procainamide, disopyramide)
- Class III antiarrhythmics (e.g., amiodarone, sotalol, ibutilide, dronedarone)
- Class 1C antiarrhythmics (e.g., flecainide, propafenone)
- antipsychotics (e.g., chlorpromazine, pimozide, haloperidol, droperidol, ziprasidone)
- antidepressants (e.g., fluoxetine, citalopram, venlafaxine, tricyclic/tetracyclic antidepressants [e.g., amitriptyline, imipramine, maprotiline])
- opioids (e.g., methadone)
- macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, azithromycin, tacrolimus)
- quinolone antibiotics (e.g., moxifloxacin, levofloxacin, ciprofloxacin)
- pentamidine
- antimalarials (e.g., quinine, chloroquine)
- azole antifungals (e.g., ketoconazole, fluconazole, voriconazole)
- domperidone
- 5-hydroxytryptamine (5-HT)3 receptor antagonists (e.g., ondansetron)
- tyrosine kinase inhibitors (e.g., sunitinib, nilotinib, lapatinib, vandetanib)
- arsenic trioxide
- histone deacetylase inhibitors (e.g., vorinostat)
- beta-2 adrenoceptor agonists (e.g., salmeterol, formoterol)
Drugs that Affect Electrolytes
Drugs that can disrupt electrolyte levels include, but are not limited to, the following:
- loop, thiazide, and related diuretics
- laxatives and enemas
- amphotericin B
- high-dose corticosteroids
The above list of potentially interacting drugs is not comprehensive.
9.5 Drug-Food Interactions
ZYKADIA should be taken with food. The bioavailability of ceritinib is increased in the presence of food.
Patients should be instructed to avoid grapefruit or grapefruit juice as they may inhibit CYP3A in the gut wall and may increase the bioavailability of ceritinib.
9.6 Drug-Herb Interactions
St. John’s Wort (Hypericum perforatum) is a potent CYP3A4 inducer. Co-administration with ZYKADIA may lead to increased ZYKADIA metabolism, therefore decreased ZYKADIA plasma concentrations (see 9.4 Drug-Drug Interactions).
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Ceritinib is a highly selective and potent ALK kinase inhibitor. Ceritinib inhibits autophosphorylation of ALK, ALK-mediated phosphorylation of downstream signaling protein STAT3, and proliferation of ALK-dependent cancer cells both in vitro and in vivo. Ceritinib also inhibits insulin-like growth factor 1 receptor (IGF-1R), insulin receptor (INSR), and ROS1 (ROS1, c-ros) at clinically relevant doses.
Ceritinib was demonstrated effective against EML4-ALK and NPM-ALK kinase activity in a NSCLC and lymphoma cell line, resulting in inhibition of cell proliferation in vitro and regression of tumors in EML-ALK and NPM-ALK derived xenografts in mouse and rat.
A single-dose pharmacodynamic study and multiple-daily dose efficacy study performed in lymphoma and lung cancer tumor models indicated that a 60% to 80% reduction in the ALK signaling pathway may be required to achieve tumor regression.
10.2 Pharmacodynamics
Cardiac Electrophysiology
The potential for QTc interval prolongation by ceritinib was assessed in Study X2101, an open-label, dose-escalation and expansion study investigating the safety, pharmacokinetics, and anti-tumor activity of ceritinib in patients with tumors confirmed to have genetic abnormalities in ALK. Serial ECGs were collected following a single dose and at steady-state to evaluate the effect of ceritinib on the QT interval in patients treated with ZYKADIA 750 mg once daily fasted.
The mean change from baseline in ECG parameters in Study X2101 was 13.6 ms (90% CI: 11.73; 15.41) for the QTc interval, -9.2 bpm (90% CI: -10.58; -7.86) for heart rate, 3.7 ms (90% CI: 2.37; 5.10) for the PR interval, and 1.2 ms (90% CI: 0.45; 1.96) for the QRS duration in the 750 mg fasted dose arm (N=223) at steady-state pre-dose on Day 22. A central analysis of ECG data demonstrated no cases of QTc >500 msec in the 750 mg arm (N=255) under fasted conditions. There were 7 patients (2.8%) with a QTc increase from baseline >60 msec. A pharmacokinetic/pharmacodynamic analysis suggested that ceritinib causes concentration-dependent increases in QTc.
In Study A2303, the observed mean change from baseline QTc at pre-dose on Day 22 was 14.9 ms (90% CI: 12.2, 17.6) in 101 patients receiving ceritinib 750 mg once daily fasted. According to a PK/PD analysis based on data from 86 patients in Study A2303, the predicted change from baseline QTc at mean steady-state Cmin was 14.1 ms (90% CI: 10.0, 18.2).
In Study A2303, a categorical outlier analysis of ECG data in 115 patients demonstrated new QTc >500 msec in 1 patient (0.9%) and increases from baseline >60 ms in 7 patients (6.1%). Adverse events of QT prolongation (primarily ECG QT prolonged) were reported for 13 patients (11.3%).
In Study A2301, the observed mean change from baseline QTc at pre-dose on Day 22 was 13.5 ms (90% CI: 11.8, 15.3) in 182 patients receiving ceritinib 750 mg once daily fasted. According to a PK/PD analysis based on data from 167 patients in Study A2301, the predicted change from baseline QTc at mean steady-state Cmin was 11.7 ms (90% CI: 8.5, 14.9).
In Study A2301, a categorical outlier analysis of ECG data in 189 patients demonstrated new QTc >500 msec in 5 patients (2.6%) and increases from baseline >60 ms in 15 patients (7.9%). Adverse events of QT prolongation (primarily ECG QT prolonged) were reported for 21 patients (11.1%).
A pharmacokinetic/pharmacodynamic analysis suggested that ceritinib causes concentration-dependent increases in QTc (see 4 Dosage and Administration, 7 Warnings and Precautions, 8 Adverse Reactions, 9 Drug Interactions).
10.3 Pharmacokinetics
Table 10 – Summary of ceritinib pharmacokinetic parameters in patients following Single 750 mg Fasted Dose of Ceritinib and Multiple 750 mg Fasted Daily Dosing of Ceritinib
| Parameters, Units | Cmax (ng/mL) | Tmax (h) | t½ (h) | AUC0-last (ng*hr/mL) | CL/F (L/h) | Vd (L) | ||||||||
| Parameters, Units | Cmax (ng/mL) | Tmax (h) | t½ (h) | AUC0-last (ng*hr/mL) | CL/F (L/h) | Vd (L) | ||||||||
| Dose Escalation* | Single Dose Mean | 186 (127) n=10 | 6.02 (3.95-23.8) n=10 | 40.6 (34.7) n=9 | 7870 (127) n=10 | 88.5 | 4230 | |||||||
| Expansion | Cycle 1 Day 1 | 203 (101) n=208 | 6.00 (1.13-24.0) n=208 | NA | 2040 (175) n=208 | NA | NA | |||||||
| Cycle 2 Day 2 | 1010 (44.8) n=133 | 6.00 (0-22.6) n=133 | NA | 8900 (76.1) n=133 | 33.2 (37.1) n=23 | NA | ||||||||
Abbreviations: NA=not applicable; n=number of patients with non-missing values; AUClast=area under the plasma concentration-time curve calculated to the last quantifiable concentration point;Cmax=maximum concentration; CL/F=apparent plasma clearance; t1/2=elimination half-life; Tmax=time to maximum plasma concentration *Dose escalation part of the study included a 3-day single-dose PK run-in period to fully characterize the PK of ceritinib, followed by a period of daily dosing in continuous 21-day treatment cycles. Values are median (range) for Tmax, geometric mean (CV% of geometric mean) for all others. | ||||||||||||||
Absorption
After single oral administration of ceritinib in patients, the area under the curve (AUC) and Cmax increased dose proportionally over 50 to 750 mg dose range under fasted conditions. The absolute bioavailability of ceritinib has not been determined (see Table 10).
Following ceritinib 750 mg once daily fasted dosing, steady-state was reached by approximately 15 days with a geometric mean accumulation ratio of 6.2 after 3 weeks. Systemic exposure increased in a greater than dose proportional manner after repeat doses of 50 to 750 mg dose range under fasted conditions once daily.
Food effect
Systemic exposure of ceritinib was increased when administered with a meal. A food effect study conducted in healthy subjects with a single 500 mg ceritinib dose showed that a high‐fat meal (containing approximately 1000 calories and 58 grams of fat) increased ceritinib AUC by 73% and Cmax by 41% and a low‐fat meal (containing approximately 330 calories and 9 grams of fat) increased ceritinib AUC by 58% and Cmax by 43% as compared with the fasted state.
In a dose optimization study A2112 (ASCEND-8) in patients comparing ZYKADIA 450 mg or 600 mg daily with food (approximately 100 to 500 calories and 1.5 to 15 grams of fat) to 750 mg daily under fasted conditions, there was no clinically meaningful difference in the systemic steady-state exposure of ceritinib for the 450 mg with food arm (N=36) compared to the 750 mg fasted arm (N=31), with only small increases in steady-state AUC (90% CI) by 4% (-13%, 24%) and Cmax (90% CI) by 3% (-14%, 22%). In contrast, the steady-state AUC (90% CI) and Cmax (90% CI) for the 600 mg with food arm (N=30) increased by 24% (3%, 49%) and 25% (4%, 49%), respectively, compared to the 750 mg fasted arm. The maximum recommended dose of ZYKADIA is 450 mg taken orally once daily with food (see 4 Dosage and Administration).
Distribution
Binding of ceritinib to human plasma proteins in vitro is approximately 97% in a concentration independent manner, from 50 ng/mL to 10,000 ng/mL. Ceritinib also has a slight preferential distribution to red blood cells, relative to plasma, with a mean in vitro blood-to-plasma ratio of 1.35. In vitro studies suggest that ceritinib is a substrate for P-glycoprotein (P-gp), but not of breast cancer resistance protein (BCRP) or multi-resistance protein 2 (MRP2). The in vitro apparent passive permeability of ceritinib was determined to be low.
In rats, ceritinib crosses the intact blood brain barrier with a brain-to-blood exposure (AUCinf) ratio of about 15%. There are no data related to brain-to-blood exposure ratio in humans.
Metabolism
In vitro studies demonstrated that CYP3A was the major enzyme involved in the metabolic clearance of ceritinib.
Following oral administration of a single 750 mg fasted radiolabeled ceritinib dose, ceritinib as the parent compound was the main circulating component (82%) in human plasma. A total of 11 metabolites were found circulating in plasma at low levels with mean contribution to the radioactivity AUC of ≤2.3% for each metabolite. Main biotransformation pathways identified in healthy subjects included mono-oxygenation, O-dealkylation, and N-formylation. Secondary biotransformation pathways involving the primary biotransformation products included glucuronidation and dehydrogenation. Addition of a thiol group to O-dealkylated ceritinib was also observed.
Based on in vitro data, ceritinib may inhibit CYP3A and CYP2C9 at clinical concentrations. Time-dependent inhibition of CYP3A was also observed.
Elimination
Ceritinib demonstrates nonlinear PK over time (see Table 10). Following oral administration of a single 750 mg radiolabeled ceritinib dose under fasted conditions, 91% of the administered oral dose was recovered in the feces (with a mean 68% of an oral dose as unchanged parent compound) while 1.3% of the administered oral dose was recovered in the urine.
Special populations and conditions
- Effects of age, gender, and race: Age, gender, race, and body weight had no clinically important effect on the systemic exposure of ceritinib based on population pharmacokinetic analyses.
- Hepatic Insufficiency: Following a single 750 mg ZYKADIA dose under fasted conditions, the geometric mean systemic exposure (AUCinf) of ceritinib was increased by 66% and unbound ceritinib AUCinf was increased by 108% in subjects with severe (Child-Pugh C) hepatic impairment compared to healthy subjects with normal hepatic function (see 4 Dosage and Administration and 7 Warnings and Precautions, 7.1 Special populations). Total and unbound systemic exposure of ceritinib were similar in subjects with mild (Child-Pugh A) to moderate (Child-Pugh B) hepatic impairment compared to healthy subjects with normal hepatic function.
- Renal Insufficiency: A pharmacokinetic trial in patients with renal impairment has not been conducted as ceritinib elimination via the kidney is low (1.3% of a single oral administered dose). Based on a population pharmacokinetic analysis of 345 patients with mild renal impairment (CrCl 60 to <90 mL/min), 82 patients with moderate renal impairment (CrCl 30 to <60 mL/min) and 546 patients with normal renal function (≥90 mL/min), ceritinib exposures were similar in patients with mild and moderate renal impairment and normal renal function. Patients with severe renal impairment (CrCl <30 mL/min) were not included in the clinical trial.
11 Storage, Stability, and Disposal
ZYKADIA (ceritinib) should not be stored above 30°C.
ZYKADIA capsules must be kept out of the reach and sight of children.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s): Ceritinib
Chemical name: 5-Chloro-2-N-{5-methyl-4-(piperidin-4-yl)-2-[(propan-2- sulfonyl) oxy]phenyl}-4-N-[2- (propane-2-sulfonyl)phenyl]pyrimidine-2,4-diamine
Molecular formula and molecular mass: C28H36ClN5O3S and 558.14
Structural formula:
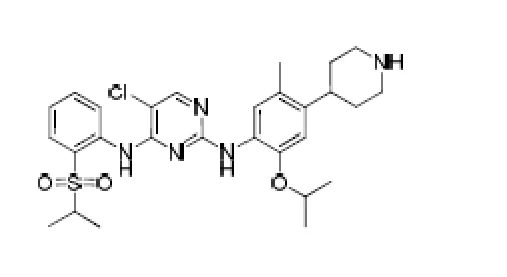
Physicochemical properties:
Physical Description: White to almost white or light yellow or light brown powder.
Solubility: At 25oC, ceritinib drug substance has good solubility in very acidic aqueous medium. The solubility decreases significantly with increasing pH. A good solubility is found in the organic medium methanol.
pH: The pH of a 1% aqueous suspension of LDK378 in water is 6.86.
pKa: The pKa values for ceritinib are 9.7 and 4.1
Partition Coefficient/Distribution coefficient: The measured log P of ceritinib in octanol/water is 4.6. The log D of ceritinib in octanol/buffer pH 6.8 is 1.69
Melting point: The melting point is 174.0°C (as determined by Thermogravimetry-Differential Thermal Analysis [TGA-DTA])
14 Clinical Trials
14.1 Clinical Trials by Indication
Previously Untreated ALK-Positive Locally Advanced or Metastatic NSCLC
Phase III study A2301
The efficacy and safety of ZYKADIA for the treatment of locally advanced or metastatic ALK-positive NSCLC patients with and without brain metastasis, who have not received previous systemic treatment anti-cancer therapy (including ALK inhibitor) with the exception of neo-adjuvant or adjuvant therapy, was investigated in a global multicenter, randomized, open-label Phase 3 Study A2301 (ASCEND 4).
Patients with symptomatic central nervous system (CNS) metastases who were neurologically unstable or had required increasing doses of corticosteroids within the 2 weeks prior to screening to manage CNS symptoms were excluded from the study.
The primary efficacy endpoint was Progression-Free Survival (PFS), as determined by a Blinded Independent Review Committee (BIRC), according to Response Evaluation Criteria in Solid Tumors (RECIST) 1.1. The key secondary endpoint was Overall Survival (OS). Other secondary endpoints included Overall Response Rate (ORR), Duration of Response (DOR), determined by BIRC and by Investigators and patient reported outcomes (PROs).
Intracranial ORR (OIRR), intracranial DCR (IDCR) and duration of intracranial response (DOIR) determined by BIRC neuro-radiologist per modified RECIST 1.1 (i.e. up to 5 lesions in the brain) were used to assess the antitumor activity in the brain.
Patients were allowed to continue the assigned study treatment beyond initial progression in case of continued clinical benefit as per the Investigator's opinion. Patients randomized to the chemotherapy arm could crossover to receive ceritinib upon RECIST-defined disease progression by BIRC.
A total of 376 patients were randomized in a 1:1 ratio (stratified by WHO performance status, prior adjuvant/neoadjuvant chemotherapy and presence/absence of brain metastasis at screening) to receive either ceritinib (750 mg daily, fasted) or chemotherapy (based on Investigator’s choice - pemetrexed [500 mg/m2] plus cisplatin [75 mg/m2] or carboplatin [AUC 5-6], administered every 21 days for 4 cycles. Patients who completed 4 cycles of chemotherapy (induction) without progressive disease subsequently received pemetrexed (500 mg/m2) as single-agent maintenance therapy every 21 days. One hundred and eighty-nine (189) patients were randomized to ceritinib and one hundred eighty-seven (187) were randomized to chemotherapy.
Baseline disease characteristics were balanced between the two treatment arms as shown in Table 11.
Table 11 – Demographics and Disease Characteristics in Study A2301
| Characteristics | Ceritinib 750 mg fasted N=189 n (%) | Chemotherapy N=187 n (%) | |||||||||
| Characteristics | Ceritinib 750 mg fasted N=189 n (%) | Chemotherapy N=187 n (%) | |||||||||
| Sex, n (%) | |||||||||||
| Male | 87 (46.0) | 73 (39.0) | |||||||||
| Female | 102 (54.0) | 114 (61.0) | |||||||||
| Age (years), n (%) | |||||||||||
| Median (range) | 55.0 (22-81) | 54.0 (22-80) | |||||||||
| <65 years | 143 (75.7) | 152 (81.3) | |||||||||
| ≥65 years | 46 (24.3) | 35 (18.7) | |||||||||
| Race, n (%) | |||||||||||
| Caucasian | 104 (55.0) | 98 (52.4) | |||||||||
| 3 (1.6) | 3 (1.6) | ||||||||||
| Asian | 76 (40.2) | 82 (43.9) | |||||||||
| Native American | 3 (1.6) | 2 (1.1) | |||||||||
| Other | 3 (1.6) | 2 (1.1) | |||||||||
| WHO/ECOG Performance Status at baseline, n (%) | |||||||||||
| 0 | 69 (36.5) | 70 (37.4) | |||||||||
| 1 | 107 (56.6) | 105 (56.1) | |||||||||
| 2 | 13 (6.9) | 11 (5.9) | |||||||||
| Missing | 0 | 1 (0.5) | |||||||||
| Smoking status, n (%) | |||||||||||
| Never smoked | 108 (57.1) | 122 (65.2) | |||||||||
| Former smoker | 66 (34.9) | 50 (26.7) | |||||||||
| Current smoker | 15 (7.9) | 15 (8.0) | |||||||||
| Disease Stage, n (%) | |||||||||||
| Locally advanced | 9 (4.8%) | 5 (2.7%) | |||||||||
| Metastatic | 180 (95.2%) | 182 (97.3%) | |||||||||
| Histological classification, n (%) | |||||||||||
| Adenocarcinoma | 180 (95.2) | 183 (97.9) | |||||||||
| Adenosquamous cell carcinoma | 2 (1.1) | 2 (1.1) | |||||||||
| Large cell carcinoma | 3 (1.6) | 1 (0.5) | |||||||||
| Undifferentiated carcinoma | 1 (0.5) | 0 | |||||||||
| Other | 3 (1.6) | 1 (0.5) | |||||||||
Brain Metastases, n (%) Present Absent | 59 (31.2) 130 (68.8) | 62 (33.2) 125 (66.8) | |||||||||
The median duration of follow-up was 19.7 months (from randomization to data cut-off date) at the primary analysis.
The study met its primary objective by demonstrating a statistically significant and clinically meaningful improvement in PFS by BIRC with an estimated 45% risk reduction in the ceritinib arm compared to the chemotherapy arm (HR: 0.55 with 95% CI: 0.42, 0.73, p<0.001). The median PFS was 16.6 months (95% CI: 12.6, 27.2) and 8.1 months (95% CI: 5.8, 11.1) for the ceritinib arm and chemotherapy arm, respectively (see Table 11 and Figure 1).
The PFS results by Investigator assessment and in subgroups including age, gender, race, smoking class, Eastern Cooperative Oncology Group (ECOG) performance status and disease burden were generally consistent.
At the final OS analysis, 113 (59.8%) patients had died in the ceritinib arm and 122 (65.2%) in the chemotherapy arm. The median OS was 62.9 months (95% CI: 44.2, 77.6) and 40.7 months (95% CI: 28.5, 54.5) for the ceritinib arm and the chemotherapy arm, respectively. There was a statistically significant 24% reduction in the risk of death in the ceritinib arm compared to the chemotherapy arm (HR 0.76; 95% CI: 0.59, 0.99; p=0.020). There was a high rate of crossover, with 61.5% of patients in the chemotherapy arm switching to receive ceritinib. Additionally, patients in both arms received next line antineoplastic therapies, including other ALK inhibitors.
Key Efficacy data from Study A2301 are summarized in Table 12, and the Kaplan-Meier plot for PFS is shown in Figure 1.
Table 12 – Efficacy results in patients with previously untreated ALK-positive locally advanced or metastatic NSCLC in Study A2301 (primary analysis)
| Ceritinib (N=189) | Chemotherapy (N=187) | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Progression-Free Survival (based on BIRC) | ||||||||||||
| Number of events, n (%) | 89 (47.1) | 113 (60.4) | ||||||||||
| Median, monthsc (95% CI) | 16.6 (12.6, 27.2) | 8.1 (5.8, 11.1) | ||||||||||
| HR (95% CI)a | 0.55 (0.42, 0.73) | |||||||||||
| p-valueb | <0.001 | |||||||||||
| Tumor Response (based on BIRC) | ||||||||||||
| Objective response rate (95% CI) | 72.5% (65.5, 78.7) | 26.7% (20.5, 33.7) | ||||||||||
| Duration of response (based on BIRC) | ||||||||||||
| Number of responders | 137 | 50 | ||||||||||
| Median, monthsc (95% CI) | 23.9 (16.6, NE) | 11.1 (7.8, 16.4) | ||||||||||
| Event-free rate at 18 monthsc, % (95% CI) | 59.0 (49.3, 67.4) | 30.4 (14.1, 48.6) | ||||||||||
HR=hazard ratio; CI=confidence interval; BIRC=Blinded Independent Review Committee; NR=not reached; CR=complete response; PR=partial response a Based on the Cox proportional hazards stratified analysis. b Based on the stratified log-rank test. c Estimated using the Kaplan-Meier method. | ||||||||||||
Figure 1 – Kaplan-Meier plot of progression-free survival as assessed by BIRC in Study A2301 (FAS, primary analysis)
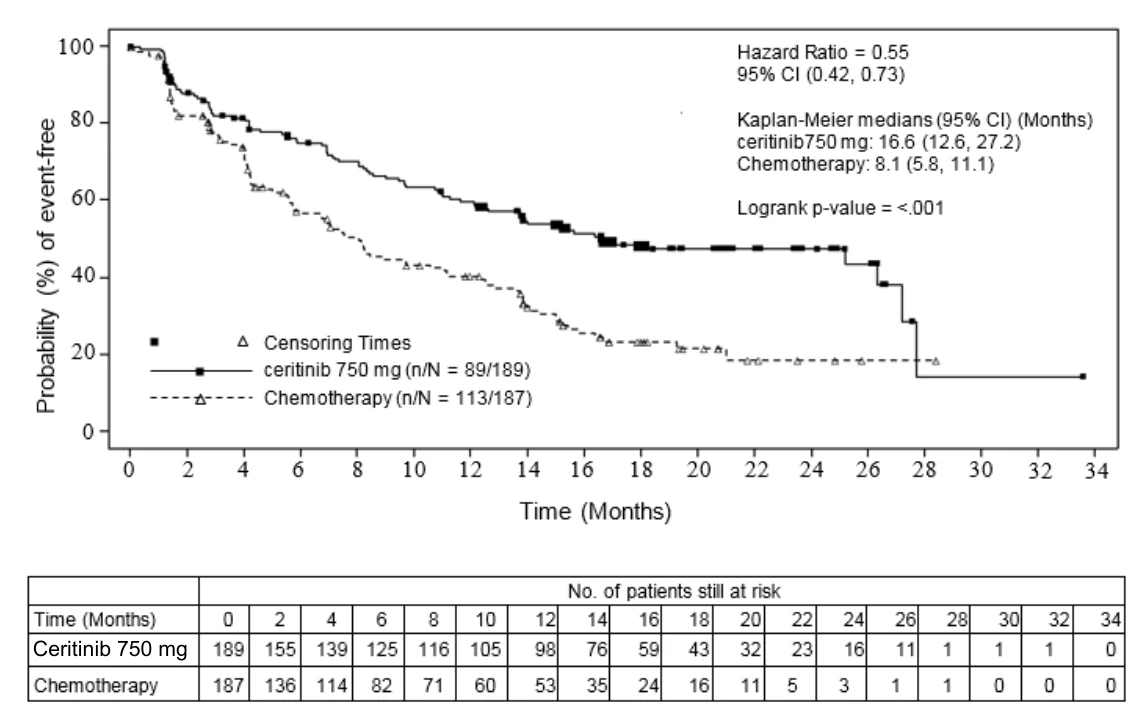
Ceritinib 750 mg
Analyses of patient-reported outcome (PRO) measures suggested a delay in time to deterioration for lung cancer specific symptoms (composite endpoint of cough, pain and dyspnea based on Lung Cancer Symptom Score [LCSS] questionnaire: HR 0.61; 95% CI: 0.41, 0.90) in patients treated with ceritinib compared to chemotherapy. Patients in the ceritinib arm (750 mg daily, fasted) appeared to have reported more intense diarrhea experience (difference between ceritinib and chemotherapy arms in change of diarrhea score [least square means] from baseline: 22.1; 95% CI: 19.5, 24.7 based on EORTC QLQ-C30 questionnaire). These PRO results should be interpreted with caution, as patients were not blinded to treatment assignment.
In Study A2301, 44 out of 121 patients had measurable brain metastasis at baseline and at least one post-baseline brain radiological assessment (22 in the ceritinib arm and 22 patients in the chemotherapy arm). Intracranial ORR based on BIRC assessment were 72.7% (95% CI: 49.8, 89.3) and 27.3% (95% CI: 10.7, 50.2) in the ceritinib and chemotherapy arms, respectively. Among these patients with measurable brain metastasis at baseline and at least one post-baseline, 59.1% (13/22) in the ceritinib arm and 81.8% (18/22) in the chemotherapy arm did not receive prior radiotherapy to the brain. PFS results in patients with and without CNS metastases (measurable or non-measurable) at baseline based on BIRC assessment are summarized in Table 13.
Table 13 – PFS with and without brain metastases in Study A2301 by BIRC assessment (primary analysis)
| BIRC | |||||||
| Ceritinib | Chemotherapy | ||||||
| With Brain Metastases | N=59 | N=62 | |||||
| Progression Free Survival | |||||||
| Median, months (95% CI) | 10.7 (8.1, 16.4) | 6.7 (4.1, 10.6) | |||||
| HR (95% CI) | 0.70 (0.44, 1.12) | ||||||
| Without Brain Metastases | N=130 | N=125 | |||||
| Progression Free Survival | |||||||
| Median, months (95% CI) | 26.3 (15.4, 27.7) | 8.3 (6.0, 13.7) | |||||
| HR (95% CI) | 0.48 (0.33, 0.69) | ||||||
Previously Treated ALK-positive Locally Advanced or Metastatic NSCLC
Phase I Study X2101
The use of ZYKADIA (ceritinib) in the treatment of patients with ALK-positive NSCLC was investigated in a multicenter, open-label study (X2101) which included a dose-escalation phase and an expansion phase at a fasted dose of 750 mg. All patients enrolled in the registration study had locally advanced or metastatic malignancy that had progressed despite standard therapy and all patients were previously tested for ALK rearrangement. Patients with controlled or asymptomatic brain metastases were eligible for the study. Prior ALK inhibitor therapy was permitted. Two-hundred and ninety of the 304 patients enrolled in the study were ALK-positive NSCLC patients. At the time of the data cut-off, a total of 246 ALK-positive NSCLC patients were enrolled who were treated at a ZYKADIA dose of 750 mg once daily fasted: 163 who had received prior treatment with crizotinib (Full Analysis Set).
Of the 163 patients who were treated with a prior ALK inhibitor (all treated with crizotinib) with an available report, ALK positivity was confirmed in 162 patients (99.4%): by FISH in 157 patients (96.3%), by RT-PCR in 3 patients (1.8%), by IHC in 1 patient (0.6%), and by other method in 1 patient (0.6%).
The primary evaluation was based on overall response rate (ORR) and duration of response (DOR) by Investigator assessment according to Response Evaluation Criteria in Solid Tumors (RECIST) 1.0 for patients who were treated with a ZYKADIA dose of 750 mg fasted. An additional evaluation of ORR and DOR was also performed based on a central Blinded Independent Review Committee (BIRC) assessment according to RECIST 1.0. Demographic and disease characteristics for the study are provided in Table 14.
Table 14 – Demographics and Disease Characteristics in Study X2101
| Characteristics | NSCLC patients treated with 750 mg/day fasted N=163 | |||
| Characteristics | NSCLC patients treated with 750 mg/day fasted N=163 | |||
| Sex, n (%) | ||||
| Male | 75 (46) | |||
| Female | 88 (54) | |||
| Age (years), n (%) | ||||
| Median (range) | 52 (24-80) | |||
| <65 years | 141 (86.5) | |||
| ≥65 years | 22 (13.5) | |||
| Race, n (%) | ||||
| Caucasian | 108 (66.3) | |||
| 4 (2.5) | ||||
| Asian | 47 (28.8) | |||
| Native Islander | 1 (0.6) | |||
| Other | 3 (1.8) | |||
| WHO/ECOG Performance Status at baseline, n (%) | ||||
| 0 | 38 (23.3) | |||
| 1 | 104 (63.8) | |||
| 2 | 20 (12.3) | |||
| 3 | 1 (0.6) | |||
| Smoking status, n (%) | ||||
| Never smoked | 109 (66.9) | |||
| Former smoker | 49 (30.1) | |||
| Current smoker | 5 (3.1) | |||
| Disease Stage, n (%) | ||||
| Locally advanced | 3 (1.8) | |||
| Metastatic | 157 (96.3) | |||
| Data missing | 3 (1.8) | |||
| Histological classification, n (%) | ||||
| Adenocarcinoma | 152 (93.3) | |||
| Large cell carcinoma | 2 (1.2) | |||
| Squamous cell carcinoma | 3 (1.8) | |||
| Adenosquamous cell carcinoma | 2 (1.2) | |||
| Other | 2 (1.2) | |||
| Missing | 2 (1.2) | |||
| Number of prior antineoplastic regimens, n (%) | ||||
| 1 | 26 (16.0) | |||
| 2 | 45 (27.6) | |||
| 3 | 35 (21.5) | |||
| >3 | 57 (35.0) | |||
Of the 163 ALK-positive NSCLC patients treated at a dose of 750 mg fasted, 89% (54.6%; 95% CI: 46.6, 62.4) of patients by Investigator assessment and 71% (43.6%; 95% CI: 35.8, 51.5) by BIRC assessment had a tumor response that was confirmed at least 4 weeks after the initial assessment (Table 15). The median time to the first objective tumor response (complete response [CR] or partial response [PR]) that was subsequently confirmed was 6.1 weeks by Investigator and BIRC assessment. The median DOR in patients who responded was 7.4 months (95% CI: 5.4, 10.1) by Investigator assessment and 7.1 months (95% CI: 5.6, Not estimable) by BIRC assessment.
Table 15 – Locally advanced or metastatic ALK-positive NSCLC efficacy results for the 750 mg fasted treatment dose arm who received prior crizotinib treatment (FAS) in Study X2101
| Efficacy Parameter | Investigator assessment | BIRC assessment | |||||
| (N=163) | (N=163) | ||||||
| Overall Response Rate (CR+PR)a, [ (%) (95% CI)] | 54.6% (46.6, 62.4) | 43.6% (35.8, 51.5) | |||||
| CR, (%) | 1.2% | 2.5% | |||||
| PR, (%) | 53.4% | 41.1% | |||||
| Duration of Response [Median (95% CI)] | 7.4 months (5.4, 10.1) | 7.1 months (5.6, NEb) | |||||
a CR (complete response), PR (partial response) confirmed BIRC = blinded independent review committee ORR and DOR assessed by RECIST 1.0 b NE = Not estimable | |||||||
Post-baseline tumor measurements were available for 151 patients with measurable disease at baseline and at least 1 valid post-baseline assessment without an unknown response for overall or target lesions out of the 163 patients. A waterfall plot displaying the maximum decrease from baseline in the sum of the longest tumor diameters shows that the majority of patients treated with ZYKADIA had a reduction in tumor burden (Figure 2).
Figure 2 – Waterfall Plot of Best Percent Change in Target Lesions from Baseline by Patient Based on Investigator Assessment (ALK-Positive NSCLC) in Study X2101
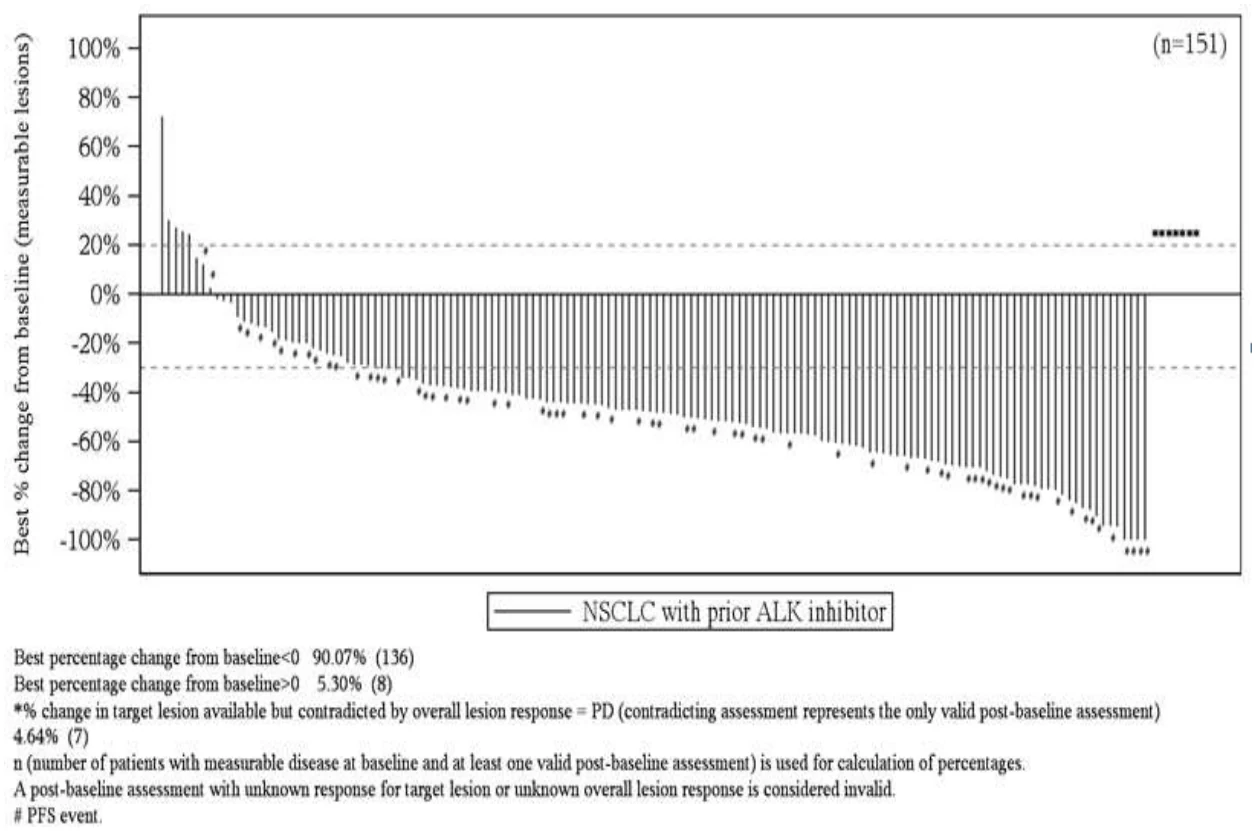
Phase III Study A2303
The efficacy and safety of ZYKADIA for the treatment of locally advanced or metastatic ALK-positive NSCLC adult patients with and without brain metastasis, who have received previous treatment with crizotinib, was demonstrated versus standard chemotherapy (pemetrexed/docetaxel) in a global multicenter, randomized, open-label Phase III Study A2303 (ASCEND 5).
The primary efficacy endpoint was Progression-Free Survival (PFS), as determined by a Blinded independent review committee (BIRC), according to RECIST 1.1. The key secondary endpoint was Overall Survival (OS). Other secondary endpoints included Overall Response Rate (ORR), Duration of Response (DOR), disease control rate (DCR), and time to response (TTR) determined by BIRC and by Investigator, PFS by Investigator and patient reported outcomes (PROs), including disease-related symptoms, functioning, and health-related quality of life.
Intracranial ORR (OIRR), intracranial DCR (IDCR) and duration of intracranial response (DOIR) determined by BIRC neuro-radiologist per modified RECIST 1.1 (i.e. up to 5 lesions in the brain) were used to assess the antitumor activity in the brain.
Patients were allowed to continue the assigned study treatment beyond initial progression in case of continued clinical benefit as per the Investigator's opinion. Patients randomized to the chemotherapy arm could crossover to receive ceritinib upon RECIST-defined disease progression confirmed by BIRC.
A total of 231 patients with advanced ALK positive NSCLC who have received prior treatment with crizotinib and chemotherapy (one or two regimen including a platinum-based doublet) were included in the analysis. 115 patients were randomized to ceritinib and 116 were randomized to chemotherapy (either pemetrexed or docetaxel). 73 patients received docetaxel and 40 received pemetrexed. In the ceritinib arm, 115 patients were treated with 750 mg once daily fasted.
Baseline disease characteristics were well-balanced between the two treatment arms as shown in Table 16.
Table 16 – Demographics and Disease Characteristics in Study A2303
| Characteristics | Ceritinib 750 mg fasted N=115 n (%) | Chemotherapy N=116 n (%) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Sex, n (%) | |||||||||||
| Male | 47 (40.9) | 55 (47.4) | |||||||||
| Female | 68 (59.1) | 61 (52.6) | |||||||||
| Age (years), n (%) | |||||||||||
| Median (range) | 54.0 (30-77) | 54.0 (28-84) | |||||||||
| <65 years | 89 (77.4) | 89 (76.7) | |||||||||
| ≥65 years | 26 (22.6) | 27 (23.3) | |||||||||
| Race, n (%) | |||||||||||
| Caucasian | 81 (70.4) | 68 (58.6) | |||||||||
| 0 | 1 (0.9) | ||||||||||
| Asian | 30 (26.1) | 38 (32.8) | |||||||||
| Unknown | 2 (1.7) | 5 (4.3) | |||||||||
| Other | 2 (1.7) | 4 (3.4) | |||||||||
| WHO/ECOG Performance Status at baseline, n (%) | |||||||||||
| 0 | 56 (48.7) | 51 (44.0) | |||||||||
| 1 | 50 (43.5) | 60 (51.7) | |||||||||
| 2 | 9 (7.8) | 5 (4.3) | |||||||||
| Smoking status, n (%) | |||||||||||
| Never smoked | 71 (61.7) | 61 (52.6) | |||||||||
| Former smoker | 39 (33.9) | 51 (44.0) | |||||||||
| Current smoker | 4 (3.5) | 1 (0.9) | |||||||||
| Missing | 1 (0.9) | 3 (2.6) | |||||||||
| Disease Stage, n (%) | |||||||||||
| Locally advanced | 1 (0.9) | 1 (0.9) | |||||||||
| Metastatic | 114 (99.1) | 115 (99.1) | |||||||||
| Histological classification, n (%) | |||||||||||
| Adenocarcinoma | 111 (96.5) | 113 (97.4) | |||||||||
| Squamous cell carcinoma | 0 | 2 (1.7) | |||||||||
| Undifferentiated carcinoma | 3 (2.6) | 1 (0.9) | |||||||||
| Other | 1 (0.9) | 0 | |||||||||
| Brain Metastases, n (%) | |||||||||||
| Present | 65 (56.5) | 69 (59.5) | |||||||||
| Absent | 50 (43.5) | 47 (40.5) | |||||||||
All patients were treated with prior crizotinib. 198 patients (81.8%) received crizotinib as last treatment (81.7% in the ceritinib arm, 81.9% in the chemotherapy arm). All except one patient received prior chemotherapy (including a platinum doublet) for advanced disease; 11.3% of the patients in the ceritinib arm and 12.1% of the patients in the chemotherapy arm were treated with two prior chemotherapy regimen for advanced disease.
The median duration of follow-up was 16.5 months (from randomization to data cut-off date) at the primary analysis.
The study met its primary objective by demonstrating a statistically significant and clinically meaningful improvement in PFS by BIRC with an estimated 51% risk reduction in the ceritinib arm compared to chemotherapy arm (HR: 0.49 with 95% CI: 0.36, 0.67). The median PFS was 5.4 months (95% CI: 4.1, 6.9) and 1.6 months (95% CI: 1.4, 2.8) for the ceritinib arm and chemotherapy arm, respectively (see Table 17 and Figure 3).
The PFS benefit of ceritinib was consistent across various subgroups including age, gender, race, smoking class, ECOG performance status, and presence of brain metastases or prior response to crizotinib.
The benefit was further supported by analysis of ORR and DCR. Ceritinib also significantly improved BIRC-assessed ORR as compared to chemotherapy with durable response (see Table 17).
At the primary analysis, OS data was not mature with 48 (41.7%) events in the ceritinib arm and 50 (43.1%) events in the chemotherapy arm, corresponding to approximately 50% of the required events for final OS. At the final OS analysis, with a median duration of follow-up of 110 months, 102 (88.7%) patients had died in the ceritinib arm and 88 (75.9%) in the chemotherapy arm. The median OS was 17.7 months (95% CI: 14.2, 23.7) and 20.1 months (95% CI: 11.9, 31.2) for the ceritinib arm and the chemotherapy arm, respectively. There was no statistically significant difference in OS between the two treatment arms (HR 1.29; 95% CI: 0.96, 1.72; p=0.955). There was a high rate of early crossover, with 88 (76%) of patients in the chemotherapy arm switching to receive ceritinib. Additionally, patients in both arms received next-line antineoplastic therapies, including other ALK inhibitors. Overall, the OS results are difficult to be interpreted.
Key efficacy data from Study A2303 are summarized in Table 17, and the Kaplan-Meier curve for PFS is shown in Figure 3.
Table 17 – Efficacy results in patients with previously treated ALK-positive locally advanced or metastatic NSCLC in Study A2303 (primary analysis)
| Ceritinib (N=115) | Chemotherapy (N=116) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Progression-free survival (based on BIRC) | ||||||||||||||||
| Number of events, n (%) | 83 (72.2%) | 89 (76.7%) | ||||||||||||||
| Median, months (95% CI) | 5.4 (4.1, 6.9) | 1.6 (1.4, 2.8) | ||||||||||||||
| HR (95% CI)a | 0.49 (0.36, 0.67) | |||||||||||||||
| p-valueb | <0.001 | |||||||||||||||
| Tumor response (based on BIRC) | ||||||||||||||||
| Objective response rate (95% CI) | 39.1% (30.2, 48.7) | 6.9% (3.0, 13.1) | ||||||||||||||
| Duration of response | ||||||||||||||||
| Number of responders | 45 | 8 | ||||||||||||||
| Median, monthsc (95% CI) | 6.9 (5.4, 8.9) | 8.3 (3.5, NE) | ||||||||||||||
| Event-free probability estimate at 9 monthsc (95% CI) | 31.5% (16.7%, 47.3%) | 45.7% (6.9%, 79.5%) | ||||||||||||||
HR=hazard ratio; CI=confidence interval; BIRC=Blinded Independent Review Committee; NE=not estimable; a Based on the Cox proportional hazards stratified analysis. b Based on the stratified log-rank test. c Estimated using the Kaplan-Meier method. | ||||||||||||||||
Figure 3 – Kaplan-Meier plot of progression-free survival as assessed by BIRC in Study A2303 (FAS, primary analysis)
| No. of patients still at risk | |||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Time (Months) | 0 | 2 | 4 | 6 | 8 | 10 | 12 | 14 | 16 | 18 | 20 | 22 | 24 | ||||||||||
| LDK378 750 mg | 115 | 87 | 68 | 40 | 31 | 18 | 12 | 9 | 4 | 3 | 2 | 1 | 0 | ||||||||||
| Chemotherapy | 116 | 45 | 26 | 12 | 9 | 6 | 2 | 2 | 2 | 0 | 0 | 0 | 0 | ||||||||||
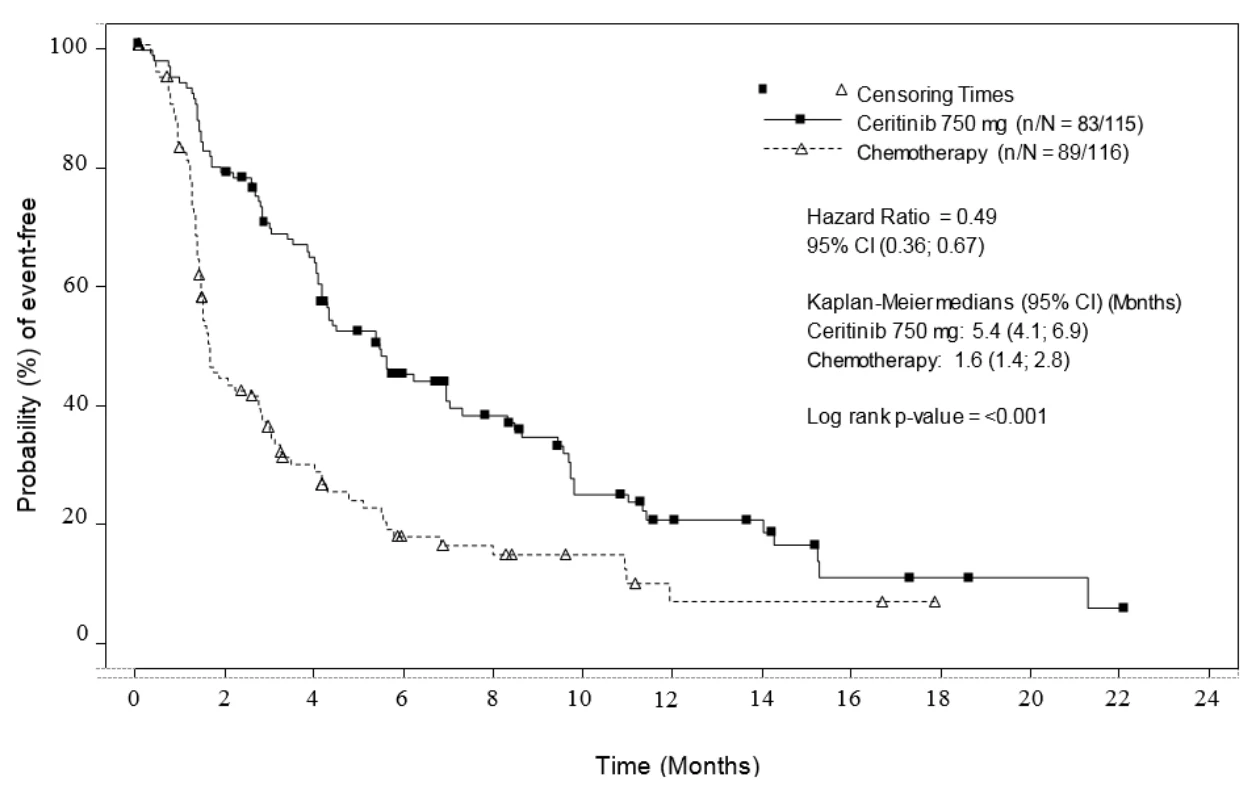
Patient reported outcome questionnaires were completed by 75% or more of patients in the ceritinib and chemotherapy arms for all questionnaires at most time points during the course of the study.
Significant improvements were reported for the majority of lung cancer specific symptoms for ZYKADIA versus chemotherapy (LCSS and QLQ-LC13 scores). Time to deterioration for cough, pain and dyspnea was significantly prolonged for the individual scales (p-value<0.05) or when combined into a composite score (p-value <0.001) in the LCSS and LC13 instruments. Median time to definitive deterioration for the LCSS composite endpoint (pain, cough, shortness of breath) was 18 months (95% CI: 13.4, NE) in the ceritinib arm versus 4.4 months (95% CI: 1.6, 8.6) in the chemotherapy arm. Median time to definitive deterioration for the same endpoint in the LC13 instrument was 11.1 months (95% CI 7.1, 14.2) in the ceritinib arm versus 2.1 months (95% CI: 1.0, 5.6) in the chemotherapy arm.
The EQ-5D questionnaire showed a significant overall health status improvement for ZYKADIA in comparison to the chemotherapy.
In Study A2303, 133 patients with baseline brain metastasis (66 patients in the ceritinib arm and 67 patients in the chemotherapy arm) were assessed for intracranial response by BIRC neuro-radiologist.
| Ceritinib 750 mg |
|---|
The intracranial ORR (OIRR) in patients with measurable disease in the brain at baseline and at least one post-baseline assessment was higher with ceritinib (35.3%, 95% CI: 14.2, 61.7) compared to chemotherapy (5.0%, 95% CI: 0.1, 24.9).
The median PFS by BIRC and Investigator using RECIST 1.1 was longer in the ceritinib arm compared to the chemotherapy arm in both subgroups of patients with brain metastases and without brain metastases (based on the extent of cancer CRF, see Table 18).
Table 18 – PFS with and without brain metastases in Study A2303 (primary analysis)
| BIRC | Investigator | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Ceritinib | Chemotherapy | Ceritinib | Chemotherapy | |||||||||||||
| With Brain Metastases | N=65 | N=69 | N=65 | N=69 | ||||||||||||
| Progression Free Survival | ||||||||||||||||
| Median, months (95% CI) | 4.4 (3.4, 6.2) | 1.5 (1.3, 1.8) | 5.4 (3.9, 7.0) | 1.5 (1.3, 2.1) | ||||||||||||
| HR (95% CI) | 0.54 (0.36, 0.80) | 0.45 (0.31, 0.66) | ||||||||||||||
| Without Brain Metastases | N=50 | N=47 | N=50 | N=47 | ||||||||||||
| Progression Free Survival | ||||||||||||||||
| Median, months (95% CI) | 8.3 (4.1, 14.0) | 2.8 (1.4, 4.1) | 8.3 (5.6, 13.4) | 2.6 (1.4, 4.2) | ||||||||||||
| HR (95% CI) | 0.41 (0.24, 0.69) | 0.32 (0.19, 0.54) | ||||||||||||||
Dose optimization Study A2112 (ASCEND-8)
The pharmacokinetics, safety, and efficacy of ZYKADIA 450 mg with food were evaluated in a dose optimization Study A2112 (ASCEND-8). A key secondary efficacy endpoint was overall response rate (ORR) according to RECIST 1.1 as evaluated by a Blinded Independent Review Committee (BIRC). The ORR in previously untreated ALK-positive NSCLC was consistent between the ZYKADIA 450 mg once daily with food (N=73) and ZYKADIA 750 mg once daily under fasted conditions (N=74) arms, 78.1% (95% CI: 66.9, 86.9) and 75.7% (95% CI: 64.3, 84.9), respectively.
16 Non-Clinical Toxicology
No long-term animal studies have been performed to evaluate the carcinogenic potential of Ceritinib.
General Toxicology
Target organs in nonclinical animal models included, but were not limited to, the pancreas, biliopancreatic/bile ducts, gastrointestinal tract, liver, lung, lymphatic system and hematopoietic system.
Pancreatic focal acinar cell atrophy was observed in rats at 1.5-fold the human exposure by AUC at the recommended dose (RD). Biliopancreatic duct and bile duct necrosis/hyperplasia of epithelium were observed in rats and monkeys at exposures equal to or greater than the human exposure by AUC at the RD. Bile duct inflammation and vacuolation were also noted in monkeys at exposures equal to or greater than 0.5-fold the human exposure by AUC at the RD.
Gastrointestinal toxicity was observed in both species characterized by body weight loss, decreased food consumption, emesis (monkey), diarrhea, and at high doses, by histopathologic lesions including erosion, mucosal inflammation, and foamy macrophages in the duodenal crypts and submucosa at 1.4-fold the human exposure by AUC at the RD. Minimal necrosis and hemorrhage of the duodenum was exhibited in monkeys and rats at an exposure similar to that observed clinically.
Liver was also affected in both species, but only at the highest dose levels studied, and included minimal increases in liver transaminases in a few animals, and vacuolation of the intra-hepatic bile duct epithelium at exposures 1.4-fold the human exposure by AUC at the RD.
Alveolar foamy macrophages (confirmed phospholipidosis) were seen in the lungs of rats, but not in monkeys. Evidence of phospholipidosis (lung) occurred at exposures 1.4-fold the human exposure by AUC at the RD and was completely reversible. The human relevance of phospholipidosis is not known.
The mesenteric lymph nodes of rats and monkeys showed increased numbers of macrophages at exposures equivalent to human exposure by AUC at the RD, which was reversible. Thymus lymphoid depletion was observed in monkeys at exposures that were 1.4 fold the human exposures by AUC at the RD, and was reversible.
Effects were observed in the hematopoietic system, in both rats and monkeys, including increased monocytes, neutrophils, lymphocytes, and platelets and decreased reticulocytes and mean corpuscular volume (MCV), mean corpuscular hemoglobin (MCH), hematocrit, and hemoglobin in rats and in monkeys, mild decreases in neutrophils, moderate decreases in reticulocytes and decreased cellularity in bone marrow were seen at exposures 1.4-fold of the human exposure by AUC at the RD, and were completely reversible. In the 13 week studies (at exposures equivalent to human exposure by AUC at the RD) hematological effects were seen only in rats (increased fibrinogen and platelets), and were reflective of inflammatory changes seen histologically in the biliopancreatic/hepatic ducts. The hematopoietic system was affected in rats (increased neutrophils) at exposures 1.4 fold of the human AUC exposure by AUC at the RD.
In 13-week study in monkeys, glucose concentrations were mildly increased, and reversible at exposures similar to human exposures by AUC at the RD. A mechanism for this modest effect was undetermined, but because animals were not fasted before sample collections, differences in relative timing of food consumption between arms and/or individuals may have impacted results.
Ceritinib crossed the blood brain barrier in rats with a brain-to-blood exposure (AUCinf) ratio of approximately 15%.
Genotoxicity
Ceritinib was not mutagenic in vitro in the bacterial reverse mutation (Ames) assay. Ceritinib was not clastogenic in the in vivo rat micronucleus assay (at exposures 40-fold the human exposure by AUC at the recommended dose). However, ceritinib induced numerical aberrations (aneugenic) in the in vitro cytogenetic assay using human lymphocytes (at a concentration 120-fold higher than the human recommended dose Cmax), and micronuclei in the in vitro micronucleus test using TK6 cells. As such, ceritinib is considered genotoxic.
Carcinogenicity
Carcinogenicity studies have not been performed with ceritinib.
Reproductive and developmental toxicology
In an embryo-fetal development study in which pregnant rats were administered daily doses of ceritinib during organogenesis, dose-related skeletal anomalies were observed at doses as low as 50 mg/kg (approximately 0.5-fold the human exposure by AUC at the recommended dose). Findings included delayed ossifications and skeletal variations.
In pregnant rabbits administered ceritinib daily during organogenesis, dose-related skeletal anomalies, including incomplete ossification, were observed at doses equal to or greater than 2 mg/kg/day (approximately 0.015-fold the human exposure by AUC at the recommended dose). A low incidence of visceral anomalies, including absent or malpositioned gallbladder and retroesophageal subclavian cardiac artery, was observed at doses equal to or greater than 10 mg/kg/day (approximately 0.13-fold the human exposure by AUC at the recommended dose). Maternal toxicity and abortion occurred in rabbits at doses of 35 mg/kg or greater (approximately 0.72-fold the human exposure by AUC at the recommended dose). In addition, embryolethality was observed in rabbits at a dose of 50 mg/kg (approximately equivalent to the human exposure by AUC at the recommended dose). Formal non-clinical studies on the potential effects of ceritinib on fertility have not been conducted.
Special toxicology
Phototoxicity
Ceritinib showed phototoxic potential in the 3T3 NRU in vitro assay (PIF=8.1), while a subsequent in vivo assessment of phototoxicity, the mouse ultraviolet local lymph node assay (UV LLNA), demonstrated that ceritinib is not phototoxic.