


Product Monograph - 20% Prosol
RECENT MAJOR LABEL CHANGES
WARNINGS AND PRECAUTIONS, General MARCH 2020
DOSAGE AND ADMINISTRATION, Recommended Dose MARCH 2020
CONSUMER INFORMATION, Reporting Side Effects MARCH 2020
TABLE OF CONTENTS
RECENT MAJOR LABEL CHANGES ......................................................................................2
TABLE OF CONTENTS ..............................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................4
1 INDICATIONS....................................................................................................................4
1.1 Pediatrics ....................................................................................................................4
1.2 Geriatrics ....................................................................................................................4
2 CONTRAINDICATIONS ..................................................................................................4
3 DOSAGE AND ADMINISTRATION ...............................................................................4
3.1 Dosing Considerations ...............................................................................................4
3.2 Recommended Dose and Dosage Adjustment ...........................................................5
3.3 Administration ...........................................................................................................5
3.4 Missed Dose ...............................................................................................................6
4 OVERDOSAGE .................................................................................................................6
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................7
6 WARNINGS AND PRECAUTIONS ...............................................................................8
6.1 Special Populations ..................................................................................................12
6.1.1 Pregnant Women ................................................................................................. 12
6.1.2 Breast-feeding ..................................................................................................... 12
6.1.3 Pediatrics ............................................................................................................. 12
6.1.4 Geriatrics ............................................................................................................. 12
7 ADVERSE REACTIONS................................................................................................13
7.1 Adverse Reaction Overview ....................................................................................13
7.2 Post-Market Adverse Reactions ...............................................................................13
8 DRUG INTERACTIONS .................................................................................................13
8.1 Overview ..................................................................................................................13
8.2 Drug-Drug Interactions ............................................................................................13
9 ACTION AND CLINICAL PHARMACOLOGY ...........................................................14
9.1 Mechanism of Action ...............................................................................................14
9.2 Pharmacodynamics ..................................................................................................14
9.3 Pharmacokinetics .....................................................................................................14
10 STORAGE, STABILITY AND DISPOSAL..................................................................14
11 SPECIAL HANDLING INSTRUCTIONS .....................................................................14
12 PHARMACEUTICAL INFORMATION ........................................................................16
13 CLINICAL TRIALS .........................................................................................................18
14 NON-CLINICAL TOXICOLOGY ...................................................................................18
PATIENT MEDICATION INFORMATION ...............................................................................19
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
20% ProSol (Amino Acid Injection 20% w/v) when administered with a source of energy is indicated as a source of amino acid in the treatment of negative nitrogen balance in patients where:
(1) the alimentary tract cannot or should not be used.
(2) gastrointestinal absorption of amino acids is impaired, or
(3) metabolic requirements for protein are substantially increased, as with extensive burns.
1.1 Pediatrics
Pediatrics (<18 years of age): There have been no studies performed by Baxter Healthcare Corporation in the pediatric population. See Special Populations, Pediatrics section regarding monitoring for hyperammonemia in pediatric patients.
1.2 Geriatrics
Geriatrics (> 65 years of age): In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or drug therapy.
2 CONTRAINDICATIONS
The use of 20% ProSol (Amino Acid Injection 20% w/v) is contraindicated in the following populations/situations:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- Patients with severe liver failure or hepatic coma.
- Patients with acute renal failure and without undergoing renal replacement therapy.
- Congenital abnormality of amino acid metabolism.
3 DOSAGE AND ADMINISTRATION
ProSol product is a pharmacy bulk package, and not for direct infusion. The high osmolarity of these products precludes direct administration due to potential phlebitic complications (see DOSAGE FORMS, COMPOSITION AND PACKAGING, Composition).
3.1 Dosing Considerations
Administration of ProSol as a Component of Parental Nutrition Therapy
Infusion of hypertonic nutrient injections into a peripheral vein may result in vein irritation, vein damage, and thrombosis.
Any unused portion of 20% ProSol (Amino Acid Injection 20% w/v) should be discarded and should not be used for subsequent admixing.
3.2 Recommended Dose and Dosage Adjustment
Electrolyte supplementation may be indicated according to the clinical needs of the patient.
The total daily dose of these solutions depends on the patient's metabolic requirements and clinical response. The determination of nitrogen balance and accurate daily body weight, corrected for fluid balance, are probably the best means of assessing individual nitrogen requirements.
Recommended Dietary Allowances* of protein range from approximately 0.75 g/kg of body weight for adults to 1.68 g/kg for infants. It must be recognized, however, that protein as well as caloric requirements in traumatized or malnourished patients may be increased substantially. Daily amino acid doses of approximately 1.0 to 1.5 g/kg of body weight for adults and 2 to 3 g/kg of body weight for infants with adequate calories are generally sufficient to satisfy protein needs and promote positive nitrogen balance.
*Food and Nutrition Board National Academy of Sciences - National Research Council (Revised 1989).
As indicated on an individual basis, vitamins and trace elements and other components (including dextrose and lipids) can be added to the parenteral nutrition regimen to prevent deficiencies and complications from developing (see SPECIAL HANDLING INSTRUCTIONS).
When used in neonates and children below 2 years, the solution (in containers and administration sets) should be protected from light exposure after admixture through administration.
Fat emulsion coadministration should be considered when prolonged parenteral nutrition is required in order to prevent essential fatty acid deficiency (EFAD).
3.3 Administration
The flow should start at a low rate and should be increased gradually. The flow rate must be adjusted taking into account the dose being administered, the daily volume intake, and the duration of the infusion.
Initiation and termination of infusions of TPN fluids must be gradual to permit adjustment of endogenous insulin release.
Central Vein Infusion
In unstressed adult patients with no unusual nitrogen losses, a minimum dosage of 0.1 gram nitrogen (3mL of 20% ProSol (Amino Acid Injection 20% w/v) plus 4.4 grams (15 calories) of dextrose/fat emulsion per kilogram of body weight per day is required to achieve nitrogen balance and weight stability. For patients stressed by surgery, trauma or sepsis, and those with unusual nitrogen losses, the dosage required for maintenance may be as high as 0.3 to 0.4 grams of nitrogen (9.4 to 12.5 mL of 20% ProSol (Amino Acid Injection 20% w/v) per kilogram of body weight per day, with proportionate increases in non-protein calories. Periodic assessment of nitrogen balance of the individual patient is the best indicator of proper dosage. Use of an infusion pump is advisable to maintain a steady infusion rate during central venous infusion.
Administration by central venous catheter should be used only by those familiar with this technique and its complications.
Peripheral Infusion
The osmolarity of a specific an infusion solution must be taken into account when peripheral administration is considered. The osmolarity of an IV final solution administrated administered via peripheral vein should be below 900 mOsm/L. Osmolarity of 20% ProSol (Amino Acid Injection 20% w/v) exceeds this level (see DOSAGE FORMS, COMPOSITION AND PACKAGING). Therefore, for patients who require parenteral nutrition and in whom the central vein route is not indicated, the solution should be diluted accordingly and then infused by peripheral vein. Sterile water for injection or sterile dextrose solution for injection with low concentration of dextrose may be used for dilution.
In patients for whom central vein catheterization is not advisable, appropriate admixtures made by adequate dilution of 20% ProSol (Amino Acid Injection 20% w/v) can be administered by peripheral vein. If infused simultaneously, fat emulsion will provide a dilution effect upon the osmolarity, as well.
A sample TPN mixture of Baxter products is as follows (Typical Adult TPN Formula):
| Solution | Volume | Final Solution | Protein | Calories |
| ProSol 20% | 250 mL | 5% | 50g | 200 |
| Dextrose 70% | 357 mL | 25% | 850 | |
| Sterile Water for Injection | 393 mL | |||
| Total | 1000 mL |
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. Use of a final filter is recommended during administration. For administration of parenteral solutions without lipids a 0.22 micron filter should be used. If lipid is also administered then a 1.2 micron filter should be used.
3.4 Missed Dose
In the event of a missed dose, the infusion should be restarted at the recommended dose and flow rate. Doses should NOT be doubled.
4 OVERDOSAGE
In the event of inappropriate administration (overdose, and/or infusion rate higher than recommended), hyperammonemia, hypervolemia, electrolyte disturbances, acidosis and/or azotemia may occur and result in severe or fatal consequences. In such situations, the infusion must be stopped immediately. If medically appropriate, further intervention may be indicated to prevent clinical complications. See WARNINGS AND PRECAUTIONS.
There is no specific antidote for overdose. Emergency procedures should include appropriate corrective measures.
| For management of a suspected drug overdose, contact your regional poison control centre. |
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging.
20% ProSol (Amino Acid Injection 20% w/v) is a sterile, clear, nonpyrogenic, hypertonic solution of essential and nonessential amino acids. A Pharmacy Bulk Package, available in 2000 mL, is a container of a sterile preparation for parenteral use that contains many single doses. The contents are intended for use in a pharmacy admixture program and are restricted to the preparation of admixtures for intravenous infusion.
The Viaflex® plastic container is fabricated from a specially formulated polyvinyl chloride (PL 146® Plastic). The amount of water that can permeate from inside the container into the overwrap is insufficient to affect the solution significantly. Solutions in contact with the plastic container can leach out certain of its chemical components in very small amounts within the expiration period,(e.g. di-2-ethylhexyl phthalate (DEHP), up to 5 parts per million). The studies in tissue culture and animals did not reveal safety concern.
Availability
20% ProSol (Amino Acid Injection 20% w/v) is available in Viaflex plastic Pharmacy Bulk Package containers of:
2000 mL
Composition:
20% ProSol (Amino Acid Injection 20% w/v) is a sterile, non-pyrogenic solution of amino acids in water for injection USP.
Each 100 mL of 20% ProSol (Amino Acid Injection 20% w/v) contains:
| Essential Amino Acids | |
| L-Valine | 1.44 g |
| L-Histidine | 1.18 g |
| L-Isoleucine | 1.08 g |
| L-Leucine | 1.08 g |
| L-Phenylalanine | 1.00 g |
| L-Threonine | 0.980 g |
| L-Lysine1 | 0.957 g |
| L-Methionine | 0.760 g |
| L-Tryptophan | 0.320 g |
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Intravenous | Solution for Infusion (Not for direct infusion) Amino Acid Injection 20% w/v | Glacial Acetic Acid Water for Injection |
| Non-Essential Amino Acids | |
| L-Alanine | 2.76 g |
| Glycine | 2.06 g |
| L-Arginine | 1.96 g |
| L-Proline | 1.34 g |
| L-Glutamic acid | 1.02 g |
| L-Serine | 1.02 g |
| L-Aspartic acid | 0.600 g |
| L-Tyrosine | 0.050 g |
| (pH adjusted with glacial acetic acid) | |
| Total Amino Acids | 20.0 g |
| Total Nitrogen | 3.21 g |
| pH | 5.5 to 6.5 |
| Anion profiles per liter (balanced by ions from amino acids) | |
| Acetate from Lysine Acetate and glacial acetic acid | See package label |
| Osmolarity (Calc.) | See package label |
| 1 One gram equivalent Lysine is equal to 1.41 grams Lysine Acetate |
6 WARNINGS AND PRECAUTIONS
General
- The contents of the products are intended for use in a pharmacy admixture program and are restricted to the preparation of admixtures for intravenous infusion.
- Proper administration of a ProSol product requires a knowledge of fluid and electrolyte balance, nutritional status, nature of the disease, vital organ function as well as clinical expertise in prescribing PN regimens and recognition and treatment of the complications which may occur.
- It is essential to provide adequate calories concurrently if parenterally administered amino acids are to be retained by the body and utilized for protein synthesis.
- Severe water and electrolyte disorders, severe fluid overload states, and severe metabolic disorders should be corrected before starting the infusion.
- Do not administer unless solution is clear.
- A slight yellow color does not alter the quality and efficacy of this product.
Exercise caution to ensure that precipitates are not formed in any parenteral nutrient products since precipitates may result in life-threatening clinical outcomes (see Respiratory subsection and ADVERSE REACTIONS section).
If additional substances (other PN solution, additional electrolytes and/or other additives) are to be admixed with ProSol product, compatibility of the substances with the product must be evaluated to ensure that the final solution is stable and free of precipitates (see DOSAGE AND ADMINISTRATION section).
During infusion, the infusion set and catheter should also periodically be checked for precipitates. If precipitates (particular matters) are observed, infusion MUST be immediately stopped and medical evaluation is initiated.
Aseptic techniques are required when additives are added as nutrients in the products may support growth of microorganisms.
The administration of 20% ProSol (Amino Acid Injection 20% w/v) as part of total parenteral nutrition (TPN) with large volumes of hyperosmotic fluids requires periodic monitoring of the patient for signs of hyperosmolarity, hyperglycemia, glycosuria and hypertriglyceridemia.
During prolonged parenteral nutrition with amino acid and dextrose solutions, essential fatty acid deficiency syndrome may develop but may not be clinically apparent. Early demonstration of this condition can only be accomplished by analysis of plasma lipids. The syndrome may be prevented or corrected by appropriate treatment with intravenous lipid emulsions.
Administration of amino acid solutions and other nutrients via central or peripheral venous catheter may be associated with complications which can be prevented or minimized by careful attention to all aspects of the procedure. This includes attention to solution preparation, administration, and patient monitoring. It is essential that a carefully prepared protocol, based on current medical practices, be followed, preferably by an experienced team.
Infection and sepsis may occur as a result of the use of intravenous catheters to administer parenteral formulations, poor maintenance of catheters or contaminated solutions.
Immunosuppression and other factors such as hyperglycemia, malnutrition and/or their underlying disease state may predispose patients to infectious complications.
Careful symptomatic and laboratory monitoring for fever/chills, leukocytosis, technical complications with the access device, and hyperglycemia can help recognize early infections.
The occurrence of septic complications can be decreased with heightened emphasis on aseptic technique in catheter placement, maintenance, as well as aseptic technique in nutritional formula preparation.
Refeeding severely undernourished patients may result in the refeeding syndrome that is characterized by the shift of potassium, phosphorus, and magnesium intracellularly as the patient becomes anabolic. Thiamine deficiency and fluid retention may also develop. Careful monitoring and slowly increasing nutrient intakes while avoiding overfeeding can prevent these complications.
Hypertonic infusion solutions may cause irritation of the vein when administered into a peripheral vein (see ADVERSE REACTIONS, Post-Marketing Adverse Reactions).
During protein sparing therapy in the absence of supporting carbohydrate metabolism, an accumulation of ketone bodies in the blood often occurs. Correction of ketonemia usually can be accomplished by administration of carbohydrates.
20% ProSol (Amino Acid Injection 20% w/v) must not be infused through the same tubing with blood or blood components unless there is documentation that it is safe.
Do not use plastic containers in series connections. Such use could result in air embolism due to residual air being drawn from the primary container before administration of the fluid from the secondary container is completed.
Light exposure of solutions for intravenous parenteral nutrition, after admixture with trace elements and/or vitamins, may have adverse effects on clinical outcome in neonates, due to generation of peroxides and other degradation products. When used in neonates and children below 2 years, 20% ProSol (Amino Acid Injection 20% w/v) should be protected from ambient light after admixture until administration is complete.
Cardiovascular
Use with caution in patients with pulmonary edema or heart failure. Fluid status should be closely monitored.
Endocrine and Metabolism
Metabolic complications may occur if the nutrient intake is not adapted to the patient's requirements, or the metabolic capacity of any given dietary component is not accurately assessed. Adverse metabolic effects may arise from administration of inadequate or excessive nutrients or from inappropriate composition of an admixture for a particular patient's needs.
When administered as component of parenteral nutrition, the following metabolic complications have been reported: metabolic acidosis, hypophosphatemia, alkalosis, hyperglycemia and glycosuria, osmotic diuresis and dehydration, rebound hypoglycemia, elevated liver enzymes, hypo and hypervitaminosis, electrolyte imbalances, and hyperammonemia. Frequent clinical evaluation and laboratory determinations are necessary, especially during the first few days of therapy, to prevent or minimize these conditions.
Depending on extent and etiology, hyperammonemia may require immediate intervention. Should symptoms of hyperammonemia develop, administration should be discontinued and the patient’s clinical status re-evaluated.
Hyperammonemia is of special significance in newborns and infants. In some patients this may indicate the presence of a congenital disorder of amino acid metabolism or hepatic insufficiency. It is essential that blood ammonia be measured frequently in newborns and infants.
Blood and urine glucose should be monitored regularly.
In patients with myocardial infraction, infusion of amino acids should always be accompanied by dextrose since in anoxia, fatty acids cannot be properly utilized by myocardium.
Special care must be taken when giving hypertonic dextrose to patients with impaired glucose tolerance such as diabetics or prediabetics and uremic patients, especially when the latter are receiving peritoneal dialysis. To prevent severe hyperglycemia in such patients, insulin may be required.
When ProSol is administered with dextrose, to reduce the risk of hyperglycemia-associated complications, the infusion rate must be adjusted and/or insulin administered if blood glucose levels exceed levels considered acceptable for the individual patient.
Handling of glucose load is also frequently impaired in patients with liver failure.
Hepatic/Biliary/Pancreatic
Administration of amino acid solutions at excessive rates or to patients with hepatic insufficiency may result in plasma amino acid imbalances, hyperammonemia, stupor and coma.
Parenteral nutrition in general as well as amino acid solutions should be used with caution in patients with preexisting liver disease or liver insufficiency. Liver function parameters should be closely monitored in these patients, and they should be monitored for possible symptoms of hyperammonemia. Should symptoms of hyperammonemia develop, amino acid administration should be discontinued and the patient's clinical status re-evaluated.
Hepatobiliary disorders including cholestasis, hepatic steatosis, fibrosis and cirrhosis, possibly leading to hepatic failure, as well as cholecystitis and cholelithiasis are known to develop in some patients on parenteral nutrition. The etiology of these disorders is thought to be multifactorial and may differ between patients. Patients developing abnormal laboratory parameters or other signs of hepatobiliary disorders should be assessed early by a clinician knowledgeable in liver diseases in order to identify possible causative and contributory factors, and possible therapeutic and prophylactic interventions.
Immune
Anaphylactic/anaphylactoid reactions and other hypersensitivity/infusion reactions have been reported with amino acid solutions administered as a component of parenteral nutrition (see ADVERSE REACTIONS, Post-Marketing Adverse Reactions). The infusion must be stopped immediately if any signs or symptoms of a reaction develop.
Monitoring and Laboratory Tests
Monitoring should be appropriate to the patient’s clinical situation and condition, and should include determinations of water and electrolyte balance, blood glucose, serum electrolytes, serum creatinine, BUN, liver and kidney function, bilirubin, serum osmolarity, blood ammonia, serum protein, acid/base balance, hematocrit, WBC, urinary glucose, and blood cultures when necessary.
When 20% ProSol (Amino Acid Injection 20% w/v) is combined with electrolytes, caution should be exercised against volume overload, particularly in patients with congestive heart failure, renal failure, edema, adrenal hyperactivity, acid base imbalance and those receiving diuretics or anti-hypertensive therapy. Serum electrolytes should be monitored daily.
Renal
Use with caution in patients with renal insufficiency. Fluid and electrolyte status should be closely monitored for water and/or electrolyte retention and managed appropriately.
Azotemia has been reported with parenteral administration of solutions containing amino acids, and may occur in particular in the presence of renal impairment.
Respiratory
Pulmonary vascular precipitates causing pulmonary vascular emboli and pulmonary distress have been reported in patients receiving parenteral nutrition. In some cases, fatal outcomes have occurred. Excessive addition of calcium and phosphate increases the risk of the formation of calcium phosphate precipitates. Precipitates have been reported even in the absence of phosphate salt in the solution. Precipitation distal to the in‐line filter and suspected in vivo precipitate formation has also been reported.
If signs of pulmonary distress occur, the infusion should be stopped and medical evaluation initiated.
For complete nutritional support, TPN regimens must also include multiple vitamins, electrolytes, and trace elements. Potentially incompatible ions such as calcium and phosphate may be added to alternate infusate containers to avoid precipitation.
6.1 Special Populations
6.1.1 Pregnant Women
There are no adequate data on use of 20% ProSol (Amino Acid Injection 20% w/v) in pregnant women. Healthcare professionals should carefully consider the potential risks and benefits for each specific patient before prescribing the product.
Animal reproduction studies have not been conducted with 20% ProSol (Amino Acid Injection 20% w/v). It is also not known whether 20% ProSol (Amino Acid Injection 20% w/v) can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. 20% ProSol ™ (Amino Acid) Injection 20% w/v) should be given to a pregnant woman only if clearly needed.
6.1.2 Breast-feeding
There are no adequate data on use of 20% ProSol (Amino Acid Injection 20% w/v) in lactating women. Healthcare professionals should carefully consider the potential risks and benefits for each specific patient before prescribing the product.
It is unknown if the drug is excreted in human milk. Because many drugs are excreted in human milk precaution should be exercised.
6.1.3 Pediatrics
There have been no studies performed by Baxter Healthcare Corporation in the pediatric population.
Hyperamonemia is of special significance in newborns and infants. In some patients, this may indicate the presence of a congenital disorder of amino acid metabolism or hepatic insufficiency (see Endocrine and Metabolism). Blood ammonia should be measured frequently in newborns and infants to detect hyperammonemia, which may indicate the presence of a congenital abnormality of amino acid metabolism (see Endocrine and Metabolism). Should symptoms of hyperammonemia develop, administration should be discontinued and the patient's clinical status re-assessed.
6.1.4 Geriatrics
In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or drug therapy.
7 ADVERSE REACTIONS
7.1 Adverse Reaction Overview
Adverse reaction information is based on post-marketing experiences with parenteral amino acid products.
7.2 Post-Market Adverse Reactions
Adverse reactions reported with parenteral amino acid products include:
IMMUNE SYSTEM DISORDERS:
- Anaphylactic/anaphylactoid reactions, including skin, gastrointestinal and severe circulatory (shock) and respiratory manifestations as well as other hypersensitivity/infusion reactions, including pyrexia, chills, hypotension, hypertension, arthralgia, myalgia, urticaria/rash, pruritus, erythema, and headache
METABOLISM AND NUTRITION DISORDERS:
- Hyperammonemia
RENAL AND URINARY DISORDERS:
- Azotemia
VASCULAR DISORDERS:
- Pulmonary vascular precipitates
Adverse reactions reported with parenteral nutrition to which the amino acid component may play a causal or contributory role include:
HEPATOBILIARY DISORDERS:
- Hepatic failure, Hepatic cirrhosis, Hepatic fibrosis, Cholestasis, Hepatic steatosis, Blood bilirubin increased, Hepatic enzyme increased; Cholecystitis, Cholelithiasis
GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS:
- Infusion site thrombophlebitis; Venous irritation (infusion site phlebitis, pain, erythema, warmth, swelling, induration)
8 DRUG INTERACTIONS
8.1 Overview
No interaction studies have been performed by Baxter Healthcare Corporation with 20% ProSol (Amino Acid Injection 20% w/v).
8.2 Drug-Drug Interactions
Caution must be exercised in administering these injections to patients receiving corticosteroids or corticotrophin.
Because of its antianabolic activity concurrent administration of tetracycline may reduce the protein-sparing effect of infused amino acids.
9 ACTION AND CLINICAL PHARMACOLOGY
9.1 Mechanism of Action
20% ProSol (Amino Acid Injection 20% w/v) when mixed with caloric source (such as dextrose and or fat emulsion) electrolytes, vitamins, and minerals administered parenterally (central IV or peripheral IV) will provide biologically utilizable source for protein synthesis.
9.2 Pharmacodynamics
There have been no pharmacodynamic studies performed by Baxter Healthcare Corporation.
9.3 Pharmacokinetics
There have been no pharmacokinetic studies performed by Baxter Healthcare Corporation.
Special Populations and Conditions
There have been no clinical pharmacology studies performed by Baxter Healthcare Corporation in special populations and conditions.
10 STORAGE, STABILITY AND DISPOSAL
Store between 15 - 25°C. Protect from light. Avoid excessive heat. Protect from freezing.
After initial entry, maintain contents at room temperature (25°C).
Any admixture storage should be under refrigeration and limited to a brief period of time, preferably less than 24 hours.
Extemporaneously prepared solutions should be used promptly after mixing.
11 SPECIAL HANDLING INSTRUCTIONS
Confirm the integrity of the container. Use only if the container is not damaged and if the solution is clear, colorless or slightly yellow.
To Open:
- 1. Do not remove unit from overwrap until ready for use.
- 2. Remove the protective overpouch.
- 3. Check for leaks.
Preparation for Admixing
- 1. The Pharmacy Bulk Package is to be used only in a suitable aseptic work area.
- 2. Suspend container.
- 3. Remove plastic protector from port.
- 4. Attach a suitable sterile transfer device or dispensing set which allows measured dispensing of the contents. Refer to complete directions accompanying device.
- 5. Viaflex® containers should not be written on directly since ink migration has not been investigated. Affix accompanying label for date and time of entry.
Administration of the infusion:
- For single use only.
- Do not reconnect any partially used container.
- Do not connect containers in series in order to avoid air embolism due to possible residual air contained in the primary container.
This Injection is for compounding only, not for direct infusion.
Once container closure has been penetrated, withdrawal of contents should be completed within 4 hours.
Additives
Additives may be incompatible.
Do not add other medicinal products or substances without first confirming their compatibility and the stability of the resulting preparation.
Excess addition of calcium and phosphate, especially in the form of mineral salts, may result in the formation of calcium phosphate precipitates which could lead to serious adverse reactions (see WARNINGS AND PRECAUTIONS, Respiratory and ADVERSE REACTIONS).
Discard the solution/emulsion if precipitates occur at any stage of the preparation for IV infusion of the product.
When compounding admixtures, use aseptic technique. Mix thoroughly. Do not store any unused portion of 20% ProSol (Amino Acid Injection 20% w/v).
PART II: SCIENTIFIC INFORMATION
12 PHARMACEUTICAL INFORMATION
Drug Substance
Essential Amino Acids
L-Histidine, L-Isoleucine, L-Leucine, L-Lysine, L-Methionine, L Phenylalanine, L-Threonine, L-Tryptophan, L-Valine
Non-Essential Amino Acids
L-Alanine, L-Arginine, L-Aspartic Acid, L-Glutamic Acid, Glycine, L-Proline, L-Tyrosine, L-Serine
Proper Name Chemical Name | Molecular Formula and Molecular Mass | Structural Formula | Physicochemical Properties |
|---|---|---|---|
L-Alanine (S)-2-aminopropionic acid | C3H7NO2 89.09 | 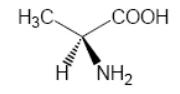 | White or almost white crystalline powder or colourless crystals, freely soluble in water, very slightly soluble in alcohol. |
L-Arginine (2S)-2-amino-5-guanidinopenta noic acid | C6H14N4O2 174.20 | 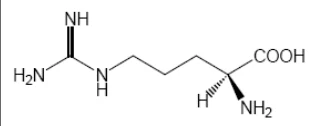 | White or almost white crystalline powder or colourless crystals, freely soluble in water, very slightly soluble in alcohol. |
L-Aspartic Acid (2S)-2-aminobutanedio ic acid | C4H7NO4 133.10 | 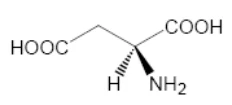 | White or almost white crystalline powder or colourless crystals, slightly soluble in water, practically insoluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. |
L-Glutamic Acid (2S)-2-aminopentanedi oic acid | C5H9NO4 147.13 | 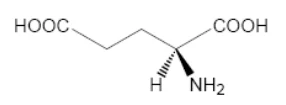 | White crystalline powder or colourless crystals, freely soluble in boiling water, slightly soluble in cold water, practically insoluble in acetic acid, in acetone and in alcohol. |
Glycine Aminoacetic acid | C2H5NO2 75.07 | 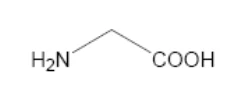 | White or almost white crystalline powder, freely soluble in water, very slightly soluble in alcohol. |
|---|---|---|---|
L-Histidine (S)-2-amino-1H-imidazole-4-propionic acid | C6H9N3O2 155.15 | 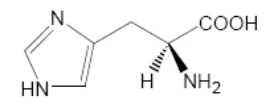 | White or almost white crystalline powder or colourless crystals, soluble in water, very slightly soluble in ethanol (96%). |
L-Isoleucine (2S, 3S)-2-amino-3-methylpentanoi c acid | C6H13NO2 131.17 | 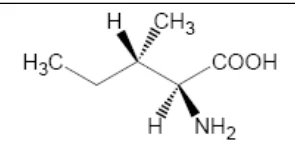 | White or almost white crystalline powder or flakes, sparingly soluble in water, slightly soluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. |
L-Leucine (2S)-2-amino-4-methylpentanoi c acid | C6H13NO2 131.17 | 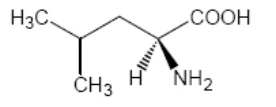 | White or almost white crystalline powder or shiny flakes, sparingly soluble in water, practically insoluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. |
L-Lysine (S)-2,6-diaminohexanoi c acid monohydrate | C6H14N2O2. H2O 164.21 | 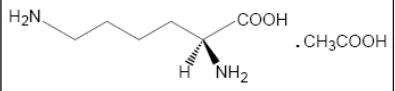 | White or almost white crystalline powder or colourless crystals, freely soluble in water, very slightly soluble in ethanol (96%). |
L-Methionine (2S)-2-amino-4-(methylsulfanyl) butanoic acid | C5H11NO2 S 149.21 | 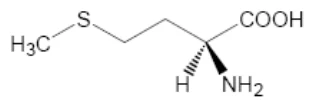 | White or almost white crystalline powder or colourless crystals, soluble in water, very slightly soluble in ethanol. |
L-Phenylalanine (2S)-2-amino-3-phenylpropanoi c acid | C9H11NO2 165.19 | 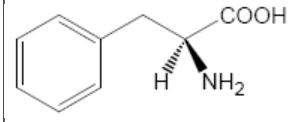 | White or almost white crystalline powder or shiny, white flakes, sparingly soluble in water, very slightly soluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. |
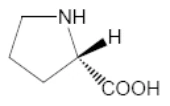
L-Proline (S)-2-pyrrolidinecarbo xylic acid | C5H9NO2 115.13 | White or almost white crystalline powder or colourless crystals, very soluble in water, freely soluble in alcohol. | |
|---|---|---|---|
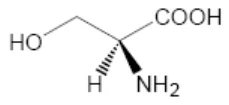
L-Serine (S)-2-amino-3-hydroxypropioni c acid | C3H7NO3 105.09 | White or almost white crystalline powder or colourless crystals, freely soluble in water, practically insoluble in alcohol. | |
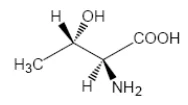
L-Threonine (2S, 3R)-2-amino-3-hydroxybutanoi c acid | C4H9NO3 119.12 | White crystalline powder or colourless crystals, soluble in water, practically insoluble in ethanol. | |
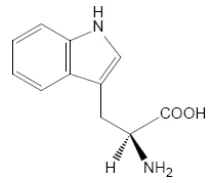
L-Tryptophan (2S)-2-amino-3-(indol-3-yl)propanoic acid | C11H12N2O2 204.23 | White or almost white crystalline or amorphous powder, sparingly soluble in water, slightly soluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. | |
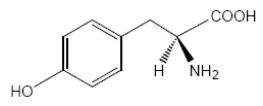
L-Tyrosine (S)-2-amino-3-(4-hydroxyphenyl) propionic acid | C9H11NO3 181.19 | White crystalline powder or colourless crystals, very slightly soluble in water, practically insoluble in alcohol. It dissolves in dilute mineral acids and in dilute solutions of alkali hydroxides. | |
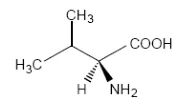
L-Valine (2S)-2-amino-3-methylbutanoic acid | C5H11NO2 117.15 | White or almost white crystalline powder or colourless crystals, soluble in water, very slightly soluble in ethanol. |
13 CLINICAL TRIALS
There have been no clinical trials of this product performed by Baxter Healthcare Corporation.
14 NON-CLINICAL TOXICOLOGY
There have been no pharmacology studies performed by Baxter Healthcare Corporation.
 | |||
|---|---|---|---|
 | |||
 | |||
 | |||
 | |||
 |