


Product Monograph - Aflivu
Recent Major Label Changes
| 4.4 Administration | 2025-09 |
|---|---|
| 7 Warnings and Precautions, Ophthalmologic | 2025-09 |
Table of Contents
Sections or subsections that are not applicable at the time of authorization are not listed.
Recent Major Label Changes ..................................................................................................................... 2
Table of Contents ...................................................................................................................................... 2
Part 1: Healthcare Professional Information .............................................................................................. 4
1 Indications ............................................................................................................................................. 4
1.1 Pediatrics.................................................................................................................................................... 4
1.2 Geriatrics .................................................................................................................................................... 4
2 Contraindications ................................................................................................................................... 4
4 Dosage and Administration .................................................................................................................... 4
4.1 Dosing Considerations ......................................................................................................................................4
4.2 Recommended Dose and Dosage Adjustment................................................................................................4
4.4 Administration ..................................................................................................................................................6
4.5 Missed Dose ................................................................................................................................................... 12
5 Overdose ............................................................................................................................................. 12
6 Dosage Forms, Strengths, Composition, and Packaging ......................................................................... 12
7 Warnings and Precautions .................................................................................................................... 13
General ................................................................................................................................................................. 13
Driving and Operating Machinery ....................................................................................................................... 13
Hepatic/Biliary/Pancreatic ................................................................................................................................... 13
Immune ................................................................................................................................................................ 13
Ophthalmologic .................................................................................................................................................... 13
Renal ..................................................................................................................................................................... 14
Reproductive Health ............................................................................................................................................ 14
7.1Special Populations ......................................................................................................................................... 15
7.1.1Pregnancy .......................................................................................................................................... 15
7.1.2 Breastfeeding ................................................................................................................................... 16
7.1.3 Pediatrics .......................................................................................................................................... 16
7.1.4 Geriatrics .......................................................................................................................................... 16
8 Adverse Reactions ................................................................................................................................ 16
8.1 Adverse Reaction Overview .......................................................................................................................... 16
8.2 Clinical Trial Adverse Reactions ..................................................................................................................... 18
8.3 Less Common Clinical Trial Adverse Reactions ............................................................................................ 35
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data Clinical Trial Findings ........................................................................................................................................................ 36
8.5 Post-Market Adverse Reactions .................................................................................................................... 36
9 Drug Interactions ................................................................................................................................. 36
9.2 Drug Interactions Overview .................................................................................................................... 36
9.4 Drug-Drug Interactions ............................................................................................................................ 36
9.5 Drug-Food Interactions ........................................................................................................................... 36
9.6 Drug-Herb Interactions ............................................................................................................................ 36
9.7 Drug-Laboratory Test Interactions ......................................................................................................... 36
10 Clinical Pharmacology .................................................................................................................... 36
10.1 Mechanism of Action ............................................................................................................................ 36
10.2 Pharmacodynamics ................................................................................................................................ 37
10.3 Pharmacokinetics ................................................................................................................................... 38
10.4 Immunogenicity .................................................................................................................................... 39
11 Storage, Stability, and Disposal ...................................................................................................... 39
12 Special handling Instructions .......................................................................................................... 39
Part 2: Scientific Information ................................................................................................................... 41
13 Pharmaceutical Information ................................................................................................................ 41
14 Clinical Trials .................................................................................................................................. 42
14.1 Clinical Trials by Indication – Reference Biologic Drug ......................................................................... 42
15 Microbiology .................................................................................................................................. 62
16 Non-Clinical Toxicology .................................................................................................................. 62
17 Supporting Product Monographs .................................................................................................... 64
Patient Medication Information .............................................................................................................. 65
Part 1: Healthcare Professional Information
AFLIVU (aflibercept injection) is a biosimilar biologic drug (biosimilar) to EYLEA (aflibercept injection). A biosimilar is a biologic drug that was granted authorization based on a demonstration of similarity to a version previously authorized in Canada, known as the reference biologic drug.
1 Indications
AFLIVU (aflibercept injection) is indicated for:
- the treatment of neovascular (wet) age-related macular degeneration (AMD)
- the treatment of visual impairment due to macular edema secondary to central retinal vein occlusion (CRVO)
- the treatment of visual impairment due to macular edema secondary to branch retinal vein occlusion (BRVO)
- the treatment of diabetic macular edema (DME)
- the treatment of myopic choroidal neovascularization (myopic CNV)
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of aflibercept injection in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Clinical studies of aflibercept injection include participants 65 years of age and older. No clinically significant differences in efficacy or safety were seen with increasing age in these studies.
2 Contraindications
- Patients who are hypersensitive to this drug, to any ingredient in the formulation, or to any component of the container. For a complete listing, see 6 Dosage Forms, Strengths, Composition, and Packaging section.
- Patients with ocular or periocular infection
- Patients with active intraocular inflammation
4 Dosage and Administration
4.1 Dosing Considerations
- FOR OPHTHALMIC INTRAVITREAL INJECTION ONLY.
- The AFLIVU pre-filled syringe or vial is for single-use only.
- The pre-filled syringe or vial contents should not be split or further compounded. Use of more than one injection from a pre-filled syringe or vial may increase the risk of contamination and subsequent infection.
- AFLIVU must only be administered by a qualified physician experienced in administering intravitreal injections.
4.2 Recommended Dose and Dosage Adjustment
Treatment of wet AMD
The recommended dose for AFLIVU is 2 mg (0.05 mL or 50 microliters) administered by intravitreal injection every month (4 weeks) for the first 3 doses followed by 2 mg (0.05 mL) via intravitreal injection every 2 months (8 weeks).
Based on the treating ophthalmologist’s judgement of visual and anatomic outcomes, the treatment interval may be maintained at two months or extended in 2-week increments if visual outcomes remain stable, no fluid is indicated by Optical Coherence Tomography and no hemorrhage is observed. If visual and/or anatomic outcomes deteriorate, the treatment interval should be shortened to two months accordingly (see 14.1 Clinical Trials by Indication – Reference Biologic Drug).
The maximum treatment interval between injections should not exceed 12 weeks in the first year of treatment and not exceed 16 weeks after the first year. Patients should be evaluated regularly. The schedule of monitoring visits may be more frequent than the injection visits.
In AMD clinical trials, aflibercept injection dosed every 4 weeks or every 8 weeks was shown to be non-inferior to ranibizumab. However, no additional efficacy was demonstrated when aflibercept injection was dosed every 4 weeks compared to every 8 weeks (see 14.1 Clinical Trials by Indication - Reference Biologic Drug). At the discretion of the treating ophthalmologist and based on the monitoring of visual and anatomic outcomes, dosing every month (4 weeks) after the first 3 months (12 weeks) may be considered on an individual patient basis.
Treatment of CRVO and BRVO
The recommended dose for AFLIVU is 2 mg (0.05 mL or 50 microliters) administered by intravitreal injection once every month (4 weeks). The interval between two doses should not be shorter than one month. The treatment interval may be extended up to 3 months (12 weeks) based on visual and anatomic outcomes. Prescribers are advised to periodically assess (every 1 to 2 months) the need for continued therapy.
Clinical trial experience of a monthly dosing regimen of 2 mg aflibercept beyond 6 months in the CRVO and BRVO indications is limited. The dosing regimen of once every 4 weeks changed at 24 weeks to a regimen that allowed for extension of the treatment interval based on visual and anatomic outcomes in the CRVO clinical trials and to once every 8 weeks in the BRVO clinical trial (see 14 Clinical Trials).
Treatment of DME
The recommended dose for AFLIVU is 2 mg aflibercept (equivalent to 50 microliters solution for injection) administered by intravitreal injection monthly (once every 4 weeks) for the first 5 consecutive doses, followed by one injection every 2 months (8 weeks).
Based on the treating ophthalmologist’s judgement of visual and/or anatomic outcomes, the treatment interval may be maintained at every two months or extended by up to 2-week increments at a time if visual and/or anatomic outcomes remain stable. There are limited data for treatment intervals longer than 4 months (16 weeks).
If visual and/or anatomic outcomes deteriorate, the treatment interval should be shortened, accordingly. Treatment intervals shorter than 4 weeks between injections have not been studied.
Patients should be evaluated regularly. The schedule for monitoring should be determined by the treating physician and may be more frequent than the schedule of injections.
Aflibercept injection dosed as frequently as 2 mg every month showed similar efficacy to aflibercept injection dosed 2 mg once every 2 months in the DME clinical trials (see 14.1 Clinical Trials by Indication -
Reference Biologic Drug). At the discretion of the treating ophthalmologist and based on the monitoring of visual and anatomic outcomes, dosing every month (4 weeks) after the first 5 months (20 weeks) may be considered on an individual patient basis (see 8.2 Clinical Trial Adverse Reactions).
Treatment of myopic CNV
The recommended dose for AFLIVU is a single intravitreal injection of 2 mg aflibercept (equivalent to 50 microliters solution for injection).
Additional doses should be administered only if visual and/or anatomic outcomes indicate that the disease persists. The interval between two doses should not be shorter than one month (4 weeks). Recurrences are treated like a new manifestation of the disease.
Special Populations
Hepatic and/or renal impairment: No specific studies in patients with hepatic and/or renal impairment were conducted with aflibercept injection.
Geriatrics (≥ 65 years of age): No special dosing considerations are needed in elderly populations.
Pediatrics (< 18 years of age): The safety and efficacy of aflibercept injection have not been studied in pediatric patients. Health Canada has not authorized an indication for pediatric use.
4.4 Administration
Intravitreal injections must be carried out by a qualified physician experienced in administering intravitreal injections, and according to medical standards and under controlled aseptic conditions, which include surgical hand disinfection and the use of sterile gloves, a sterile drape, and a sterile eyelid speculum (or equivalent). The peri-ocular skin, eyelid and ocular surface should be disinfected.
Adequate anesthesia and a topical broad spectrum microbicide should be used prior to the injection.
Prior to administration visually inspect the solution for injection. Do not use the pre-filled syringe or vial if particulates, cloudiness, or discoloration are visible. Do not use if any part of the pre-filled syringe is damaged or loose, or if the syringe cap is detached from the Luer-lock.
For the intravitreal injection a 30 G x ½ inch injection needle (not supplied) should be used.
Immediately following the intravitreal injection, patients should be monitored for elevation in intraocular pressure. Appropriate monitoring may consist of a check for perfusion of the optic nerve head or tonometry. If required, sterile equipment for paracentesis should be available.
Following intravitreal injection patients should be instructed to report any symptoms suggestive of endophthalmitis, retinal detachment or tear, cataract, scleritis or increased intraocular pressure (e.g., eye pain, redness/irritation of the eye, photophobia, blurring or loss of vision, ocular discharge, lid swelling) without delay.
THE PRE-FILLED SYRINGE OR VIAL IS FOR SINGLE-USE ONLY. EACH PRE-FILLED SYRINGE OR VIAL IS TO BE USED ONLY FOR THE TREATMENT OF ONE EYE WITH 50 microliters (2 mg) OF AFLIVU.
The pre-filled syringe contains more than the recommended dose of 2 mg aflibercept (equivalent to 50 microliters solution for injection). The excess volume must be expelled before injecting (see 12 Special Handling Instructions).
To expel the air bubbles along with excess drug, slowly depress the plunger to align the base of the plunger dome (not the tip of the dome) with the dosing line on the syringe (equivalent to 50 microliters i.e. 2 mg aflibercept) (see 5 Overdose and 12 Special Handling Instructions). AFTER INJECTION, ANY UNUSED PRODUCT MUST BE DISCARDED.
Prior to usage, the unopened blister pack or vial of AFLIVU may be stored at room temperature (25°C) for up to 24 hours. After opening the blister pack or vial, proceed under aseptic conditions.
To prepare AFLIVU for intravitreal injection, please adhere to the following instructions:
Filter needle:
Blunt filter (fill) needle, not for skin injection. Do not autoclave the blunt filter (fill) needle. The filter needle is non-pyrogenic. Do not use it if individual packaging is damaged. Discard the used blunt filter (fill) needle in approved sharps collector. Caution: Re-use of the filter needle may lead to infection or other illness/injury.
Vials:
1.
Remove the protective plastic cap from the vial (see
Figure 1).
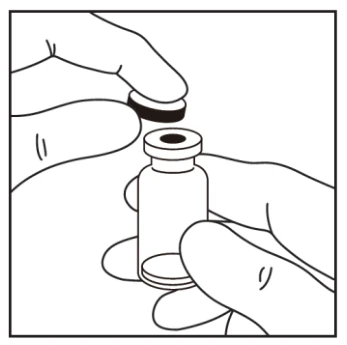
Figure 1
2.
Clean the top of the vial with an alcohol wipe (see Figure 2)
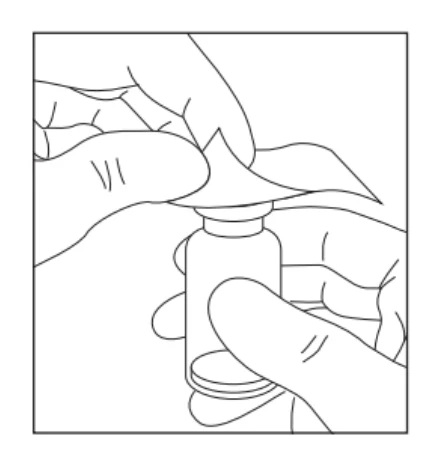
Figure 2
- 3.
Remove the 18 G, 5-micron filter needle supplied in the carton. Attach the filter needle to a 1-mL sterile, Luer-lock syringe (not supplied) by twisting it onto the Luer lock syringe tip (see Figure 3).
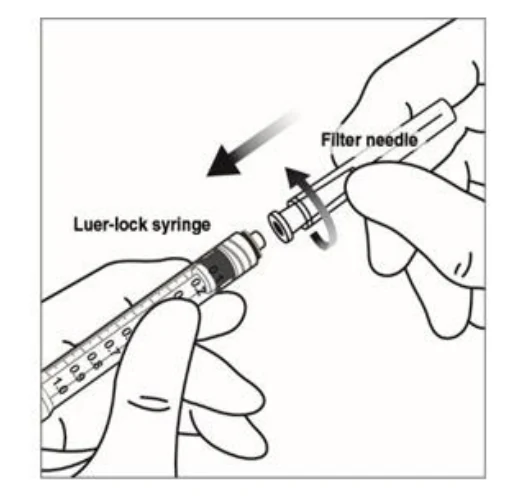
Figure 3
- 4. Push the filter needle into the centre of the vial stopper until the needle is completely inserted into the vial and the tip touches the bottom edge of the vial.
- 5. Using aseptic technique withdraw all of the AFLIVU vial contents into the syringe, keeping the vial in an upright position, slightly inclined to ease complete withdrawal. To deter the introduction of air, ensure the bevel of the filter needle is submerged into the liquid. Continue to tilt the vial during withdrawal keeping the bevel of the filter needle submerged in the liquid (see Figure 4 and Figure 5).
- 6.
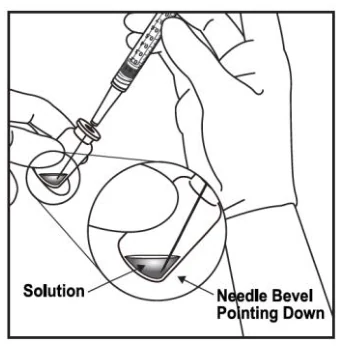
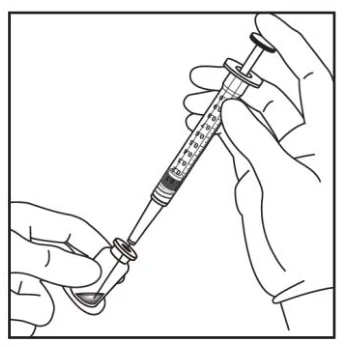
Figure 4 Figure 5
- 7. Ensure that the plunger rod is drawn sufficiently back when emptying the vial in order to completely empty the filter needle. After injection, any unused product must be discarded.
- 8.
Remove the filter needle from the syringe and properly dispose of the filter needle.
Note: Filter needle is not to be used for intravitreal injection.
8.
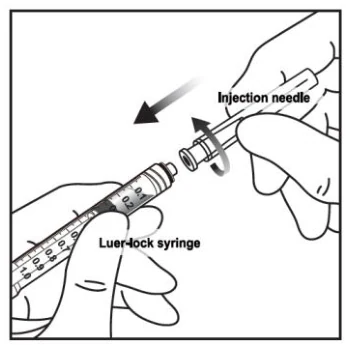
Using aseptic technique, attach a 30 G x ½ inch injection
needle (not supplied) to the syringe by firmly twisting the injection needle onto the Luer-lock syringe tip (see Figure 6).
Figure 6
9.
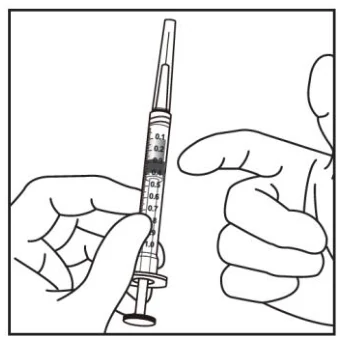
Holding the syringe with the needle pointing up, check
the syringe for bubbles. If there are bubbles, gently tap the syringe with your finger until the bubbles rise to the top (see Figure 7).
Figure 7
10.
To eliminate all of the bubbles and to expel excess drug, slowly depress the plunger so that the flat plunger edge aligns with the line that marks 0.05 mL on the syringe (see Figure 8 and Figure 9).
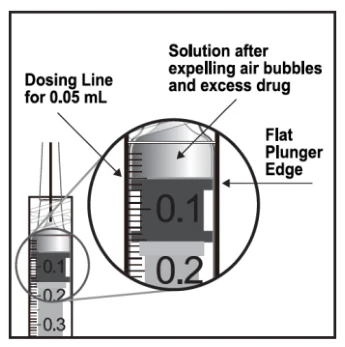
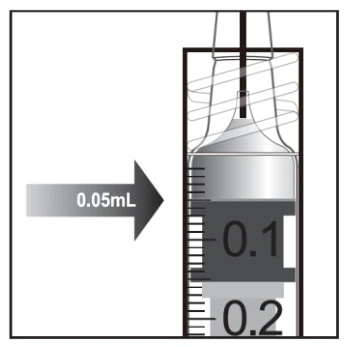
Figure 8
Figure 9
- 11. The vial is for single use only. Extraction of multiple doses from a pre-filled syringe may increase the risk of contamination and subsequent infection. After injection any unused product must be discarded in accordance with local regulations.
Pre-filled syringe:
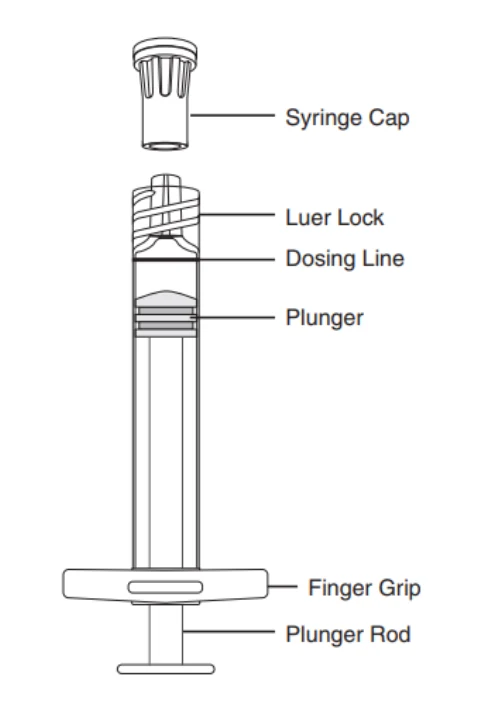
1.
When ready to administer AFLIVU, open the carton and remove the sterilized blister pack. Carefully peel open the blister pack ensuring the sterility of its contents. Keep the syringe in the sterile tray until you are ready for assembly.
2.
Using aseptic technique, remove the syringe from the sterilized blister pack.
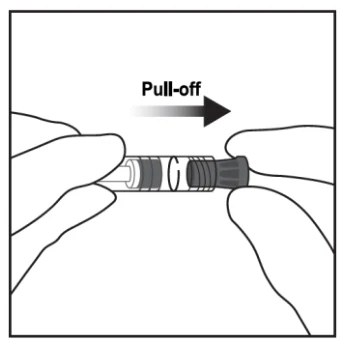
3.
To remove the syringe cap, hold the syringe in one hand while using your other hand to grasp the syringe cap with the thumb and fore finger. Please note: You should pull off the rubber tip cap with gentle force.
4.
To avoid compromising the sterility of the product, do not pull back on the plunger.
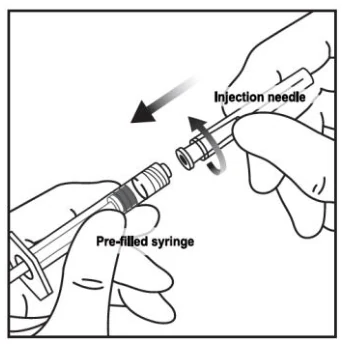
5.
Using aseptic technique, firmly twist a 30G x ½ inch injection needle onto the Luer-lock syringe tip.
6.
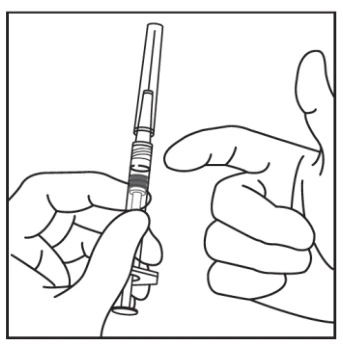
Holding the syringe with the needle pointing up, check the syringe for bubbles. If there are bubbles, gently tap the syringe with your finger until the bubbles rise to the top.
7.
To eliminate all bubbles and to expel excess drug, slowly depress the plunger to align the first rim line of the plunger stopper (not the tip of the dome, see Figure 7a) with the dosing line on the syringe (equivalent to 0.05 mL, i.e. 2 mg aflibercept, see Figure 7b).
Note: This accurate positioning of the plunger is very important, because incorrect plunger positioning can lead to delivering more or less than the labeled dose.
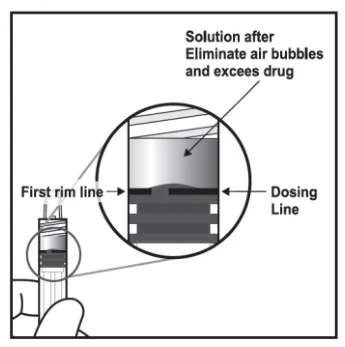
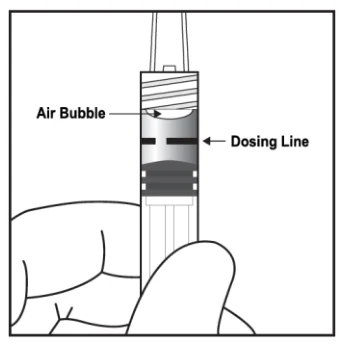
Figure 7a
Figure 7b
8.
Inject while pressing the plunger carefully and with constant pressure. Do not apply additional pressure once the plunger has reached the bottom of the syringe. Do not administer any residual solution observed in the syringe.
9.
The pre-filled syringe is for single use only.
Extraction of multiple doses from a pre-filled syringe may increase the risk of contamination and subsequent infection.
After injection any unused product must be discarded in accordance with local regulations.
4.5 Missed Dose
If a planned injection of AFLIVU is missed, reset a new appointment for an examination and injection as soon as possible. Reset the dose schedule to administer the next sequential dose after the missed dose is administered.
5 Overdose
Cases of accidental overdose have been reported from the clinical studies. Adverse reactions associated with these reported cases were intraocular pressure increased, corneal edema and eye pain.
Overdosing with increased injection volume may increase intraocular pressure. Therefore, in case of an overdose, intraocular pressure should be monitored and if deemed necessary by the treating physician, adequate treatment should be initiated (see 12 Special Handling Instructions).
6 Dosage Forms, Strengths, Composition, and Packaging
To help ensure the traceability of biologic products, including biosimilars, healthcare professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-Medicinal Ingredients |
|---|---|---|
| Intravitreal Injection | Solution / 2 mg / 0.05 mL | sodium acetate trihydrate, polysorbate 20, glacial acetic acid, sucrose, sodium chloride and water for injection |
Description
AFLIVU is provided as a sterile, clear, colourless to pale yellow, iso-osmotic, preservative-free aqueous solution containing sodium acetate trihydrate, polysorbate 20, glacial acetic acid, sucrose, sodium chloride and water for injection.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844-POISON-X (1-844-764-7669).
One millilitre solution for intravitreal injection contains 40 mg aflibercept. This medicinal product contains less than 1 mmol sodium (23 mg) per dose, i.e., essentially ‘sodium-free’.
Pre-filled Syringes
Each carton includes a pre-filled syringe containing a nominal fill volume of 165 microliters solution for intravitreal injection.
Each pre-filled syringe provides a usable amount to deliver a single dose of 50 microliters containing 2 mg aflibercept.
Vials
Each carton includes a type I glass vial containing a nominal fill volume of 278 microliters solution for intravitreal injection with an elastomeric rubber stopper, and an 18 G filter needle.
Each vial provides a usable amount to deliver a single dose of 50 microliters containing 2 mg aflibercept.
7 Warnings and Precautions
General
- Treatment with AFLIVU (aflibercept injection) is for intravitreal injection only.
Driving and Operating Machinery
Patients may experience temporary visual disturbances after an intravitreal injection with AFLIVU and the associated eye examinations. They should not drive or use machines until visual function has recovered sufficiently.
Hepatic/Biliary/Pancreatic
Aflibercept injection has not been studied in patients with hepatic impairment.
Immune
Hypersensitivity
As with all therapeutic proteins, there is a risk of hypersensitivity reactions including anaphylaxis. Hypersensitivity reactions may manifest as rash, pruritus, urticaria, severe anaphylactic/anaphylactoid reactions, or severe intraocular inflammation. Patients should be instructed to report any symptoms of anaphylaxis, allergic reactions or intraocular inflammation (e.g., pain, photophobia, or redness, which, although non-specific, should also be assessed as potential hypersensitivity reactions).
Ophthalmologic
Endophthalmitis, Retinal detachments and Cataracts
Intravitreal injections, including those with aflibercept injection, have been associated with endophthalmitis, retinal detachment, retinal tear, retinal pigment epithelium tear, cataract including traumatic cataract, vitreous hemorrhage and hyphema (see 8 Adverse Reactions). The proper aseptic injection technique must always be used when administering AFLIVU (see 4.4 Administration). Patients should be instructed to report any symptoms suggestive of any event listed above without delay and should be managed appropriately.
Retinal vasculitis and Retinal occlusive vasculitis
Retinal vasculitis and retinal occlusive vasculitis have been reported with the use of aflibercept injection, typically in the presence of intraocular inflammation or treatment with other intravitreal agents. Patients experiencing any change in vision following treatment should talk to their healthcare professional without delay to determine continuation of treatment.
Increase in Intraocular Pressure
Increases in intraocular pressure have been observed within 60 minutes of an intravitreal injection, including with aflibercept injection (see 8 Adverse reactions). Sustained (present at 2 or more consecutive visits) IOP increases > 21 mm Hg have also been reported in 34 (1.9%) patients treated with aflibercept and 30 (5.0%) patients treated with ranibizumab in wet AMD clinical trials, and in 5 (2.3%) patients treated with aflibercept injection and 9 (6.3%) patients treated with sham in CRVO clinical trials; and in 7 (7.7%) patients treated with aflibercept injection and 4 (4.3%) patients treated with laser in the BRVO clinical trial. In the DME Phase III clinical trials, sustained intraocular pressure increases have been reported in 3.6% (21/578) of patients initiated treatment with aflibercept and in 2.4% (7/287) of patients initiated treatment with laser. In all cases, both intraocular pressure and the perfusion of the optic nerve head must therefore be monitored and managed appropriately.
Aflibercept has not been tested in patients with poorly controlled glaucoma.
Other
As with other intravitreal anti-VEGF treatments, treatment should be withheld and resumed only when considered appropriate in cases of:
- An IOP of ≥ 30 mmHg
- Within the previous or next 28 days in the event of a performed or planned intraocular surgery
- A retinal break. The treatment should not be resumed until the break is adequately repaired
There is only limited experience in the treatment of subjects with DME due to type I diabetes or in diabetic patients with an HbA1c over 12% or with proliferative diabetic retinopathy.
Aflibercept injection has not been studied in patients with active systemic infections or in patients with concurrent eye conditions such as retinal detachment or macular hole. There is also no experience of treatment with aflibercept injection in diabetic patients with uncontrolled hypertension. This lack of information should be considered by the physician when treating such patients.
In myopic CNV, a clinical trial was conducted in Japan, South Korea, Singapore, Taiwan and Hong Kong. Thus, there is no clinical trial experience with aflibercept injection in the treatment of non-Asian patients for this indication. Furthermore, there is also no clinical trial experience in patients who have previously undergone treatment for myopic CNV, and in the patients with extrafoveal lesions. This lack of information should be considered by the physician before treating such patients.
In clinical trials of AMD, CRVO, BRVO and myopic CNV, only one eye per patient was treated with aflibercept injection. The safety and efficacy of aflibercept injection therapy administered to both eyes concurrently or consecutively have not been studied.
Renal
Aflibercept injection has not been studied in patients with renal impairment (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
Reproductive Health
Fertility
Women of childbearing potential have to use effective contraception during treatment and for at least 3 months after the last intravitreal injection of AFLIVU (see 7.1.1 Pregnancy).
Systemic Effects
Thromboembolic Events
Arterial thromboembolic events (ATEs) are adverse events potentially related to systemic VEGF inhibition. There is a potential risk of ATEs following intravitreal use of VEGF inhibitors, including AFLIVU.
ATEs, as defined by the Antiplatelet Trialists’ Collaboration (APTC) criteria, include nonfatal myocardial infarction, nonfatal stroke, or vascular death (including deaths of unknown cause). There are limited data on safety in the treatment of patients with CRVO, BRVO, DME or myopic CNV with a history of stroke or transient ischemic attacks or myocardial infarction within the last 6 months.
The incidence of APTC ATEs in the VIEW1 and VIEW2 wet AMD studies during the 96 weeks study duration was 3.3% (60 out of 1824) in the combined group of patients treated with aflibercept injection compared with 3.2% (19 out of 595) in patients treated with ranibizumab.
The incidence of APTC ATEs in the CRVO studies (GALILEO and COPERNICUS) during the 76/100 weeks study duration was 0.9% (2 out of 218) in patients treated with aflibercept injection +PRN compared to 1.4% (2 out of 142) in the group of patients receiving only sham treatment.
The incidence of APTC ATEs in the BRVO study (VIBRANT) during the 52 weeks study duration was 0% in the aflibercept injection treatment group patients and 2.2% (2 out of 92) in the laser + aflibercept injection control group through week 52. One of these patients in the laser group had received aflibercept injection rescue treatment.
The incidence of APTC ATEs in the DME studies (VISTADME and VIVIDDME) was 6.4% (37 out of 578) and 4.2% (12 out of 287) at Week 100; and 9.0% (52 out of 578) and 7.7% (22 out of 287) at Week 148 in the combined group of patients treated with aflibercept injection and in the control (laser) group, respectively. The incidence of adjudicated vascular deaths, as defined by APTC criteria in the DME studies (VISTADME and VIVIDDME), was 2.1 % (12 out of 578) and 1.0% (3 out of 287) at Week 100, and 2.9 % (17 out of 578) and 1.4% (4 out of 287) at Week 148 in the combined aflibercept injection groups and in the control (laser) group, respectively.
The incidence of APTC ATEs in the myopic CNV study (MYRROR) during the 48 weeks study duration was 1.1% (1 out of 91) in the group of patients treated with aflibercept injection compared to 0% (0 out of 31) in the group of patients in the control (sham) group.
Non-ocular Hemorrhages
Non-ocular hemorrhages have been reported following intravitreal injection of VEGF inhibitors, including aflibercept injection, and there is a theoretical risk that these may relate to VEGF inhibition.
7.1 Special Populations
7.1.1 Pregnancy
There are no data on the use of aflibercept in pregnant women. Studies in animals have shown reproductive toxicity after systemic administration including fetal loss and severe embryofetal malformations (see 16 Non-Clinical Toxicology). AFLIVU should not be used during pregnancy unless clearly indicated by medical need, and the potential benefit outweighs the potential risk to the fetus.
7.1.2 Breastfeeding
It is not known whether aflibercept is excreted in human milk. A risk to the breast -fed child cannot be excluded. AFLIVU is not recommended during breast-feeding. A decision must be made whether to discontinue breast-feeding or to postpone, if feasible, therapy with AFLIVU. The benefits of therapy should be weighed against potential risks to the child.
7.1.3 Pediatrics
Pediatric Use (< 18 years of age): The safety and efficacy of aflibercept injection in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
In the wet AMD Phase III clinical trials, 89% (1616/1817) of patients randomized to treatment with aflibercept injection were ≥65 years of age and 63% (1139/1817) were ≥75 years of age.
In CRVO studies, approximately 52% (112/217) of the patients randomized to treatment with aflibercept injection were ≥65 years of age, and approximately 18% (38/217) were ≥75 years of age.
In the BRVO study, approximately 58% (53/91) of the patients randomized to treatment with aflibercept injection were 65 years of age or older, and approximately 23% (21/91) were 75 years of age or older.
In the DME Phase III studies, approximately 47% (268/576) of the patients randomized to treatment with aflibercept injection were ≥65 years of age, and approximately 9% (52/576) were ≥75 years of age.
In the myopic CNV study, approximately 36% (33/91) of the patients randomized to treatment with aflibercept injection were ≥65 years of age, and approximately 10% (9/91) were ≥75 years of age.
No clinically significant differences in efficacy or safety were seen with increasing age in these studies.
8 Adverse Reactions
The adverse drug reaction profiles reported in clinical studies that compared AFLIVU to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
Treatment of wet AMD
A total of 1824 patients with up to 96 weeks exposure to aflibercept injection constituted the safety population in the 2 double-blind active-controlled clinical studies (VIEW1 and VIEW2); of these, 1223 patients were treated with the 2 mg dose (see 14 Clinical Trials).
Serious adverse reactions related to the injection procedure in the Phase III AMD trials have occurred in less than 1 in 1000 intravitreal injections (22 of 36206 injections) with either aflibercept injection or ranibizumab, and included endophthalmitis, cataract traumatic, increased intraocular pressure, retinal detachment, and vitreous detachment (see 7 Warnings and Precautions).
In patients randomized to the aflibercept injection 2mg every 8 weeks (2Q8) treatment group, fewer injection-related SAEs were observed in comparison to patients treated with aflibercept injection 2mg every 4 weeks and patients treated with ranibizumab 0.5 mg every 4 weeks (3 [0.5%] vs. 8 [1.3%] vs. 12 [2.0%]). The most common ocular serious adverse events in patients treated with aflibercept injection 2 mg every 8 weeks, aflibercept injection 2mg every 4 weeks and ranibizumab 0.5 mg every 4 weeks, respectively, included: visual acuity reduced (7 [1.1%], 7 [1.1%] vs. 7 [1.2%]), retinal hemorrhage (6 [1.0%], 3 [0.5%] vs. 6 [1.0%]), cataract (4 [0.7%], 5 [0.8%] vs. 5 [0.8%]), retinal pigment epithelial tear (3 [0.5%], 0 [0.0%] vs. 1 [0.2%]) and endophthalmitis (0 [0.0%], 4 [0.7%] vs. 6 [1.0%]).
The most common adverse reactions (in at least 5% of patients treated with aflibercept injection) were conjunctival hemorrhage (26.7%), eye pain (10.3%), vitreous detachment (8.4%), cataract (7.9%), vitreous floaters (7.6%), and increased intraocular pressure (7.2%). These adverse reactions occurred with a similar incidence in the ranibizumab treatment group.
Treatment of CRVO
Serious adverse reactions related to the injection procedure occurred in 3 out of 2,728 intravitreal injections with aflibercept injection and included endophthalmitis (see 7 Warnings and Precautions), cataract and vitreous detachment.
In CRVO clinical trials, the SAEs which occurred in ≥ 2 patients and occurred more frequently in the aflibercept injection +PRN group than in the Sham+PRN group in at least one clinical trial were (aflibercept injection +PRN vs. Sham+PRN): cataract (4 [2%] vs. 1 [1%]), macular edema (5 [2%] vs. 2 [1%]) and cystoid macular edema (2 [1%] vs. 0 [0%]) through week 76/100. The following ocular SAEs each occurred only in one patient receiving aflibercept injection treatment (1 [0.5%] subject), and in no patients who received sham treatment: endophthalmitis, corneal abrasion, vitreous detachment, retinal artery occlusion, and macular ischemia.
Through week 24, the most common ocular AEs (≥5% of patients treated with aflibercept injection and more frequently in the aflibercept injection group than in the Sham group) were (aflibercept injection vs. Sham): eye pain (13% vs. 5%), conjunctival hemorrhage (12% vs. 11%), intraocular pressure increased (8% vs. 6%), retinal exudates (6% vs. 4%), optic disc vascular disorders (6% vs. 3%) and vitreous floaters (5% vs. 1%). The most common non-ocular AE (≥5% of patients) that occurred more frequently in the aflibercept injection group than in the Sham group was hypertension (6% vs. 5%).
Through week 76/100, the most common AEs occurred more frequently in the aflibercept injection +PRN group than in the Sham+PRN group in at least one clinical trial were (aflibercept injection +PRN vs. Sham+PRN): macular edema (29% vs. 11%), cystoid macular edema (10% vs. 4%), vitreous floaters (7% vs. 4%), ocular hyperemia (7% vs. 4%), visual impairment (4% vs. 1%) and macular degeneration (4% vs. 1%).
Treatment of BRVO
Serious adverse reactions related to the injection procedure occurred in 1 out of 1,115 intravitreal injections with aflibercept injection: one case of traumatic cataract (see 7 Warnings and Precautions).
In the BRVO trial, one ocular SAE (traumatic cataract) was observed in the aflibercept injection group. The overall incidence of SAEs was 10% in the laser group and 10% in the aflibercept injection by week 24, 11% in the laser group and 15% in the aflibercept injection group by week 52. No drug-related SAEs were reported. After week 24, patients in the laser group could become eligible for aflibercept injection treatment.
The most common ocular AEs (≥5%) in the study eye were conjunctival hemorrhage (4% laser group and 20% aflibercept injection group through week 24, 15% laser group and 24% aflibercept injection group through week 52) and eye pain (5% laser group and 4% aflibercept injection group through week 24, 8% laser group and 5% aflibercept injection group through week 52, and eye irritation (1% laser group and 8% aflibercept injection group through week 52).
Treatment of DME
In the DME Phase III study, VISTADME, two patients experienced serious adverse reactions related to the injection procedure (vitreous hemorrhage and hyphema). In VIVIDDME, five patients experienced serious adverse reactions related to the injection procedure which included posterior capsule trauma, retinal detachment, cataract and vitreous hemorrhage (see 7 Warnings and Precautions).
Ocular serious adverse reactions in patients treated with aflibercept injection (2Q4 and 2Q8 treatment arms) and laser therapy, respectively, were: cataract (10 [1.7%] vs. 1 [0.3%]); vitreous hemorrhage (5 [0.9%] vs. 5 [1.7%]); retinal detachment (2 [0.3%] vs. 0 [0.0%]); cataract subcapsular (1 [0.2%] vs. 0 [0.0%]); punctate keratitis (1 [0.2%] vs. 0 [0.0%]); hyphema (1 [0.2%] vs. 0 [0.0%]); and increased intraocular pressure (1 [0.2%] vs. 0 [0.0%]).
The most common adverse reactions (in at least 5% of patients randomized to the aflibercept injection treatment arms (2Q4 and 2Q8) were conjunctival hemorrhage (31.1%), cataract (11.6%), eye pain (10.7%), intraocular pressure increased (9.2%), vitreous floaters (8.5%) and vitreous detachment (8.0%).
Through 100 weeks, the incidence of death (regardless of cause) in the aflibercept injection 2Q4, aflibercept injection 2Q8 and laser groups was 5.2%, 2.6%, and 1.9%, respectively, in VISTA, and 2.9%, 4.4%, and 0.8%, respectively, in VIVID. Through 148 weeks, the incidence of death (regardless of cause) in the aflibercept injection 2Q4, aflibercept injection 2Q8 and laser groups was 6.5% (19 out of 291), 4.5% (13 out of 287), and 2.9% (8 out of 287), respectively, in the DME studies (VISTADME and VIVIDDME). The overall rate was low and causes of death were consistent with the advanced diabetic complications and comorbidities present in this patient population. No evidence of dose response was demonstrated across these 2 studies.
Treatment of myopic CNV
In the myopic CNV Phase III study (MYRROR), one serious adverse reaction related to the injection procedure (macular hole) had occurred in 474 intravitreal injections with aflibercept injection.
One ocular serious adverse reaction (macular hole) occurred in patients treated with aflibercept injection.
The most common adverse reactions (in at least 5% of patients randomized to the aflibercept injection arm were: conjunctival hemorrhage (11.0%), eye pain (7.7%), punctate keratitis (6.6%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug. Treatment of wet AMD
The safety data include all adverse reactions (serious and non-serious) with a reasonable possibility of causality to the injection procedure or medicinal product (see Table 2 for baseline to week 52 data and Table 3 for week 52 to week 96 data).
Table 2: Adverse Reactions (Ocular and Non-Ocular) in VIEW1 and VIEW2 wet AMD Studies
Adverse Reactions Possibly Related to aflibercept injection with Incidence rate ≥1% (52-week data; safety population)
VIEW1
VIEW2
Primary system organ class
Preferred term
MedDRA Version 16.0
Ranibizumab
0.5 mg Q4
N=304 (100%)
aflibercept injection
2.0 mg Q4
N=304 (100%)
aflibercept injection
2.0 mg Q8
N=303 (100%)
Ranibizumab
0.5 mg Q4
N=291 (100%)
aflibercept injection
2.0 mg Q4
N=309 (100%)
aflibercept injection
2.0 mg Q8
N=307 (100%)
Eye disorders
Conjunctival hemorrhage
144 (47.4%)
109 (35.9%)
131 (43.2%)
24 (8.2%)
25 (8.1%)
29 (9.4%)
Eye pain
26 (8.6%)
33 (10.9%)
22 (7.3%)
27 (9.3%)
33 (10.7%)
21 (6.8%)
Vitreous detachment
24 (7.9%)
26 (8.6%)
21 (6.9%)
9 (3.1%)
20 (6.5%)
15 (4.9%)
Vitreous floaters
33 (10.9%)
40 (13.2%)
20 (6.6%)
10 (3.4%)
10 (3.2%)
8 (2.6%)
Foreign body sensation in eyes
9 (3.0%)
8 (2.6%)
16 (5.3%)
13 (4.5%)
13 (4.2%)
5 (1.6%)
Lacrimation increased
6 (2.0%)
9 (3.0%)
11 (3.6%)
2 (0.7%)
7 (2.3%)
5 (1.6%)
Retinal detachment
5 (1.6%)
4 (1.3%)
11 (3.6%)
5 (1.7%)
4 (1.3%)
11 (3.6%)
Retinal pigment epithelial tear
5 (1.6%)
1 (0.3%)
11 (3.6%)
2 (0.7%)
2 (0.6%)
7 (2.3%)
Cataract
6 (2.0%)
11 (3.6%)
8 (2.6%)
15 (5.2%)
16 (5.2%)
12 (3.9%)
Vision blurred
10 (3.3%)
11 (3.6%)
8 (2.6%)
2 (0.7%)
4 (1.3%)
3 (1.0%)
Cataract nuclear
7 (2.3%)
4 (1.3%)
6 (2.0%)
4 (1.4%)
5 (1.6%)
1 (0.3%)
Cataract subcapsular
2 (0.7%)
2 (0.7%)
6 (2.0%)
1 (0.3%)
3 (1.0%)
2 (0.7%)
Cataract cortical
2 (0.7%)
2 (0.7%)
4 (1.3%)
1 (0.3%)
0
2 (0.7%)
Corneal edema
3 (1.0%)
4 (1.3%)
4 (1.3%)
0
5 (1.6%)
2 (0.7%)
Detachment of retinal pigment epithelium
6 (2.0%)
5 (1.6%)
4 (1.3%)
14 (4.8%)
19 (6.1%)
12 (3.9%)
Anterior chamber flare
3 (1.0%)
0
3 (1.0%)
4 (1.4%)
2 (0.6%)
1 (0.3%)
Eyelid edema
5 (1.6%)
2 (0.7%)
3 (1.0%)
7 (2.4%)
7 (2.3%)
4 (1.3%)
Ocular hyperemia
11 (3.6%)
8 (2.6%)
3 (1.0%)
18 (6.2%)
13 (4.2%)
8 (2.6%)
Conjunctival hyperemia
4 (1.3%)
2 (0.7%)
2 (0.7%)
14 (4.8%)
6 (1.9%)
1 (0.3%)
Corneal epithelium defect
2 (0.7%)
1 (0.3%)
0
2 (0.7%)
4 (1.3%)
3 (1.0%)
Corneal erosion
0
0
0
7 (2.4%)
3 (1.0%)
7 (2.3%)
General disorders and administration site conditions
Injection site pain
11 (3.6%)
9 (3.0%)
12 (4.0%)
9 (3.1%)
11 (3.6%)
8 (2.6%)
Injection site hemorrhage
5 (1.6%)
6 (2.0%)
6 (2.0%)
5 (1.7%)
5 (1.6%)
4 (1.3%)
Injection site irritation
2 (0.7%)
0
4 (1.3%)
0
0
0
VIEW1
VIEW2
Primary system organ class
Preferred term
MedDRA Version 16.0
Ranibizumab
0.5 mg Q4
N=304 (100%)
aflibercept injection
2.0 mg Q4
N=304 (100%)
aflibercept injection
2.0 mg Q8
N=303 (100%)
Ranibizumab
0.5 mg Q4
N=291 (100%)
aflibercept injection
2.0 mg Q4
N=309 (100%)
aflibercept injection
2.0 mg Q8
N=307 (100%)
Infections and infestations
Endophthalmitis
3 (1.0%)
3 (1.0%)
0
0
0
0
Injury, poisoning and procedural complications
Corneal abrasion
4 (1.3%)
3 (1.0%)
4 (1.3%)
1 (0.3%)
2 (0.6%)
1 (0.3%)
Investigations
Intraocular pressure increased
21 (6.9%)
14 (4.6%)
15 (5.0%)
20 (6.9%)
24 (7.8%)
16 (5.2%)
Note: Patients are only counted once in each row but may appear in more than one row.
Table 3: Adverse Reactions (Ocular and Non-Ocular) in VIEW1 and VIEW2 wet AMD Studies
Adverse Reactions Possibly Related to aflibercept injection with Incidence rate ≥1% (from week 52 to week 96 dataa; safety population)
VIEW1
VIEW2
Primary system organ class
Preferred term
MedDRA Version 16.0
Ranibizumab
0.5 mg Q4
N=280 (100%)
aflibercept injection
2.0 mg Q4
N=290 (100%)
aflibercept injection
2.0 mg Q8
N=274 (100%)
Ranibizumab
0.5 mg Q4
N=276 (100%)
aflibercept injection
2.0 mg Q4
N=281 (100%)
aflibercept injection
2.0 mg Q8
N=284 (100%)
Eye Disorders
Conjunctival hemorrhage
52 (18.6%)
37 (12.8%)
41 (15.0%)
9 (3.3%)
4 (1.4%)
3 (1.1%)
Vitreous floaters
16 (5.7%)
13 (4.5%)
12 (4.4%)
1 (0.4%)
0
3 (1.1%)
Eye pain
11 (3.9%)
12 (4.1%)
11 (4.0%)
2 (0.7%)
6 (2.1%)
6 (2.1%)
Detachment of retinal pigment
epithelium
1 (0.4%)
2 (0.7%)
8 (2.9%)
7 (2.5%)
3 (1.1%)
4 (1.4%)
Foreign body sensation in eyes
4 (1.4%)
4 (1.4%)
8 (2.9%)
1 (0.4%)
1 (0.4%)
2 (0.7%)
Vision blurred
4 (1.4%)
8 (2.8%)
7 (2.6%)
3 (1.1%)
2 (0.7%)
2 (0.7%)
Vitreous detachment
9 (3.2%)
10 (3.4%)
7 (2.6%)
7 (2.5%)
6 (2.1%)
4 (1.4%)
Lacrimation increased
5 (1.8%)
3 (1.0%)
6 (2.2%)
0
5 (1.8%)
4 (1.4%)
Cataract
7 (2.5%)
12 (4.1%)
5 (1.8%)
13 (4.7%)
15 (5.3%)
18 (6.3%)
Cataract nuclear
2 (0.7%)
4 (1.4%)
4 (1.5%)
2 (0.7%)
5 (1.8%)
1 (0.4%)
Eyelid edema
2 (0.7%)
0
4 (1.5%)
1 (0.4%)
0
1 (0.4%)
Punctate keratitis
2 (0.7%)
3 (1.0%)
4 (1.5%)
3 (1.1%)
1 (0.4%)
2 (0.7%)
Cataract cortical
3 (1.1%)
1 (0.3%)
3 (1.1%)
1 (0.4%)
1 (0.4%)
2 (0.7%)
Cataract subcapsular
2 (0.7%)
4 (1.4%)
3 (1.1%)
0
2 (0.7%)
2 (0.7%)
Corneal edema
1 (0.4%)
2 (0.7%)
3 (1.1%)
0
3 (1.1%)
0
Ocular hyperemia
2 (0.7%)
0
2 (0.7%)
2 (0.7%)
5 (1.8%)
1 (0.4%)
Conjunctival hyperemia
6 (2.1%)
0
1 (0.4%)
6 (2.2%)
2 (0.7%)
3 (1.1%)
Retinal detachment
0
1 (0.3%)
0
1 (0.4%)
2 (0.7%)
5 (1.8%)
Investigations
Intraocular pressure increased
15 (5.4%)
4 (1.4%)
8 (2.9%)
18 (6.5%)
13 (4.6%)
15 (5.3%)
a During this period (weeks 52 to 96), patients continued to receive the dosage strength to which they were initially randomized but on a modified dosing schedule guided by assessment of visual and anatomic outcomes with a protocol-defined maximum dosing interval of 12 weeks
Note: Patients are only counted once in each row but may appear in more than one row.
In addition, 157 wet AMD patients were treated for up to 44 months in a long term extension of the Phase I and Phase II studies. The safety profile was consistent with that seen in the Phase III wet AMD studies.
Treatment of CRVO
A total of 317 patients treated with at least one dose of aflibercept injection constituted the safety population in the two Phase III CRVO studies (COPERNICUS and GALILEO).
Patients in the aflibercept injection groups (n=218) received aflibercept injection 2 mg, monthly for 6 months and then received aflibercept injection only if they met prespecified treatment criteria to Week 76 (Study GALILEO) or Week 100 (Study COPERNICUS). Patients in the Control groups received sham injections monthly from baseline to Week 24 (Study COPERNICUS, n=74) or to Week 52 (Study GALILEO, n=68) and then received aflibercept injection if they met prespecified treatment criteria.
The most common adverse reactions (≥1%) which have been assessed as having reasonable or suspected relationship to either the study drug or the injection procedure in the CRVO studies (COPERNICUS and GALILEO) are presented in Table 4.
Table 4: Adverse Reactions (≥1%) in CRVO Studies (COPERNICUS and GALILEO, up to 76/100 weeks)
Preferred term MedDRA Version 14.1
aflibercept injection a
(N=218)
Control (sham) a (N=142)
aflibercept injection a
+ PRN (N=218)
Control (sham) a
+ PRN
(N=142)
aflibercept injection Totalb (N= 317)
Baseline to Week 24
Baseline to Week 76/100
Conjunctival hemorrhage
11.9%
11.3%
18.3%
14.1%
15.8%
Intraocular pressure increased
7.8%
6.3%
14.7%
12.0%
12.9%
Eye pain
12.8%
4.9%
16.5%
7.7%
12.6%
Vitreous detachment
2.8%
4.2%
9.2%
5.6%
6.9%
Vitreous floaters
5.0%
1.4%
7.3%
3.5%
5.7%
Lacrimation increased
2.8%
3.5%
4.6%
7.0%
5.0%
Ocular hyperemia
4.1%
2.8%
6.9%
2.8%
5.0%
Cataract
0%
0.7%
5.0%
3.5%
4.4%
Foreign body sensation in eyes
3.2%
4.9%
4.1%
5.6%
3.5%
Injection site pain
2.8%
1.4%
4.1%
2.1%
3.2%
Corneal abrasion
1.8%
0.7%
2.8%
1.4%
2.2%
Vision blurred
1.4%
0.7%
2.3%
1.4%
1.9%
Cataract nuclear
0%
0.7%
1.8%
0.7%
1.6%
Injection site hemorrhage
0%
0%
1.4%
1.4%
1.6%
Lenticular opacities
0.9%
0.7%
1.8%
0.7%
1.3%
Corneal erosion
1.4%
0.7%
1.4%
2.1%
1.3%
Retinal tear
0.5%
0.7%
1.4%
1.4%
1.3%
PRN: As needed (pro re nata)
- a As randomized in the GALILEO or COPERNICUS study
- b Aflibercept injection Total = all patients who received at least one active aflibercept injection including patients who were previously in the Control arm.
Note: Patients are only counted once in each row but may appear in more than one row.
Table 5: Ocular and non-ocular adverse events, regardless of relationship to treatment (treatment emergent adverse events with incidence rate ≥1% in any treatment arm), with a difference of ≥2% between aflibercept injection and Sham (COPERNICUS and GALILEO Studies, 24 weeks)
Primary system organ class
Preferred term
MedDRA Version 14.1
aflibercept injection 2Q4 N=218
Control (Sham Injection)
N=142
Eye disorders
Eye irritation
9 (4.1%)
10 (7.0%)
Eye pain
28 (12.8%)
7 (4.9%)
Iris neovascularisation
2 (0.9%)
7 (4.9%)
Macular degeneration
5 (2.3%)
0
Macular edema
6 (2.8%)
12 (8.5%)
Maculopathy
13 (6.0%)
3 (2.1%)
Optic disc vascular disorder
12 (5.5%)
4 (2.8%)
Retinal exudates
14 (6.4%)
6 (4.2%)
Retinal hemorrhage
10 (4.6%)
11 (7.7%)
Retinal neovascularisation
1 (0.5%)
4 (2.8%)
Retinal vascular disorder
12 (5.5%)
12 (8.5%)
Visual acuity reduced
9 (4.1%)
20 (14.1%)
Vitreous floaters
13 (6.0%)
2 (1.4%)
Vitreous hemorrhage
5 (2.3%)
8 (5.6%)
Gastrointestinal disorders
Nausea
0
4 (2.8%)
Investigations
Intraocular pressure increased
18 (8.3%)
9 (6.3%)
Injury, poisoning and procedural complications
Fall
0
3 (2.1%)
Musculoskeletal and connective tissue disorders
Arthralgia
2 (0.9%)
6 (4.2%)
Respiratory, thoracic and mediastinal disorders
Cough
1 (0.5%)
4 (2.8%)
Note: Patients are only counted once in each row but may appear in more than one row.
Table 6: Ocular and non-ocular adverse events, regardless of relationship to treatment (treatment emergent adverse events with incidence rate ≥1% in any treatment arm), with a difference of ≥2% between aflibercept injection and Sham in at least one study (COPERNICUS and GALILEO Studies, Week 24 to Week 76/100)
System organ class, Preferred term MedDRA Version 14.1
COPERNICUS
GALILEO
Week 24 to Week 100
Week 24 to Week 52
Week 52 to Week 76 aflibercept injection +PRN N=110
SHAM+PRN N=60
aflibercept injection +PRN N=97
SHAM N=57
aflibercept injection +PRN N= 91
SHAM+PRN N= 52
Blood and Lymphatic Disorders
Anemia
5 (4.5%)
2 (3.3%)
0
2 (3.5%)
0
1 (1.9%)
Cardiac Disorders
Cardiac failure congestive
1 (0.9%)
2 (3.3%)
0
0
0
0
Coronary artery disease
3 (2.7%)
0
0
0
0
1 (1.9%)
Eye Disorders
Anterior chamber angle
neovascularization
0
0
2 (2.1%)
0
1 (1.1%)
0
Blepharitis
3 (2.7%)
0
2 (2.1%)
0
0
1 (1.9%)
Conjunctival hemorrhage
16 (14.5%)
9 (15.0%)
5 (5.2%)
1 (1.8%)
6 (6.6%)
1 (1.9%)
Corneal erosion
0
1 (1.7%)
1 (1.0%)
2 (3.5%)
0
0
Cystoid macular edema
16 (14.5%)
4 (6.7%)
3 (3.1%)
0
4 (4.4%)
1 (1.9%)
Diabetic retinopathy
1 (0.9%)
3 (5.0%)
0
0
0
0
Dry Eye
1 (0.9%)
4 (6.7%)
2 (2.1%)
0
0
1 (1.9%)
Eye irritation
5 (4.5%)
2 (3.3%)
4 (4.1%)
1 (1.8%)
0
2 (3.8%)
Eye pain
10 (9.1%)
5 (8.3%)
6 (6.2%)
2 (3.5%)
1 (1.1%)
0
Foreign body sensation in eyes
1 (0.9%)
2 (3.3%)
2 (2.1%)
0
1 (1.1%)
0
Iris neovascularisation
1 (0.9%)
2 (3.3%)
3 (3.1%)
0
2 (2.2%)
0
Lacrimation increased
4 (3.6%)
4 (6.7%)
3 (3.1%)
4 (7.0%)
1 (1.1%)
2 (3.8%)
Macular cyst
2 (1.8%)
1 (1.7%)
1 (1.0%)
2 (3.5%)
1 (1.1%)
0
Macular degeneration
2 (1.8%)
2 (3.3%)
3 (3.1%)
0
0
0
Macular fibrosis
8 (7.3%)
6 (10.0%)
4 (4.1%)
3 (5.3%)
2 (2.2%)
4 (7.7%)
Macular edema
21 (19.1%)
2 (3.3%)
33 (34.0%)
7 (12.3%)
21 (23.1%)
2 (3.8%)
Maculopathy
6 (5.5%)
2 (3.3%)
1 (1.0%)
0
0
0
Ocular hyperemia
4 (3.6%)
0
2 (2.1%)
1 (1.8%)
4 (4.4%)
1 (1.9%)
Optic disc hemorrhage
3 (2.7%)
0
2 (2.1%)
0
1 (1.1%)
0
Optic disc hyperemia
1 (0.9%)
0
2 (2.1%)
0
0
0
Optic disc vascular disorder
8 (7.3%)
5 (8.3%)
2 (2.1%)
3 (5.3%)
0
0
System organ class,
Preferred term
MedDRA Version 14.1
COPERNICUS
GALILEO
Week 24 to Week 100
Week 24 to Week 52
Week 52 to Week 76 aflibercept injection +PRN N=110
SHAM+PRN N=60
aflibercept injection +PRN N=97
SHAM N=57
aflibercept injection +PRN N= 91
SHAM+PRN N= 52
Posterior capsule opacification
3 (2.7%)
0
0
0
0
1 (1.9%)
Punctate keratitis
2 (1.8%)
3 (5.0%)
1 (1.0%)
0
1 (1.1%)
1 (1.9%)
Retinal aneurysm
4 (3.6%)
3 (5.0%)
(%)
(%)
2 (2.2%)
0
Retinal degeneration
3 (2.7%)
4 (6.7%)
3 (3.5%)
2 (3.5%)
0
1 (1.9%)
Retinal exudates
7 (6.4%)
5 (8.3%)
3 (3.1%)
4 (7.0%)
1 (1.1%)
0
Retinal hemorrhage
15 (13.6%)
8 (13.3%)
7 (7.2%)
4 (7.0%)
7 (7.7%)
3 (5.8%)
Retinal ischemia
0
0
3 (3.1%)
3 (5.3%)
1 (1.1%)
0
Retinal edema
3 (2.7%)
0
0
1 (1.8%)
0
0
Retinal pigment epitheliopathy
4 (3.6%)
12 (20.0%)
1 (1.0%)
0
0
2 (3.8%)
Retinal vascular disorder
9 (8.2%)
3 (5.0%)
9 (9.3%)
3 (5.3%)
1 (1.1%)
3 (5.8%)
Retinal vein occlusion
5 (4.5%)
0
5 (5.2%)
0
2 (2.2%)
0
Visual acuity reduced
30 (27.3%)
8 (13.3%)
11 (11.3%)
2 (3.5%)
9 (9.9%)
1 (1.9%)
Visual impairment
2 (1.8%)
0
4 (4.1%)
0
1 (1.1%)
0
Vitreous detachment
8 (7.3%)
3 (5.0%)
2 (2.1%)
0
3 (3.3%)
0
Vitreous hemorrhage
2 (1.8%)
4 (6.7%)
2 (2.1%)
1 (1.8%)
0
1 (1.9%)
Gastrointestinal Disorders
Abdominal pain
0
2 (3.3%)
0
0
0
0
Constipation
1 (0.9%)
2 (3.3%)
0
0
0
0
Diarrhea
2 (1.8%)
2 (3.3%)
1 (1.0%)
1 (1.8%)
0
2 (3.8%)
Dyspepsia
1 (0.9%)
2 (3.3%)
1 (1.0%)
0
0
0
Dysphagia
0
2 (3.3%)
0
0
0
0
Gastritis
0
2 (3.3%)
0
0
0
0
Nausea
5 (4.5%)
0
0
3 (5.3%)
0
0
Toothache
1 (0.9%)
0
1 (1.0%)
0
2 (2.2%)
0
Vomiting
1 (0.9%)
1 (1.7%)
0
3 (5.3%)
1 (1.1%)
0
General Disorders and Administration Site Conditions
Pyrexia
2 (1.8%)
3 (5.0%)
0
2 (3.5%)
0
0
Immune System Disorders
Drug hypersensitivity
0
4 (6.7%)
1 (1.0%)
0
0
0
Seasonal allergy
3 (2.7%)
3 (5.0%)
0
1 (1.8%)
0
0
System organ class,
Preferred term
MedDRA Version 14.1
COPERNICUS
GALILEO
Week 24 to Week 100
Week 24 to Week 52
Week 52 to Week 76 aflibercept injection +PRN N=110
SHAM+PRN N=60
aflibercept injection +PRN N=97
SHAM N=57
aflibercept injection +PRN N= 91
SHAM+PRN N= 52
Infections and Infestations
Bronchitis
5 (4.5%)
3 (5.0%)
4 (4.1%)
0
0
1 (1.9%)
Herpes zoster
1 (0.9%)
2 (3.3%)
0
1 (1.8%)
0
0
Influenza
7 (6.4%)
3 (5.0%)
5 (5.2%)
1 (1.8%)
1 (1.1%)
1 (1.9%)
Nasopharyngitis
6 (5.5%)
3 (5.0%)
10 (10.3%)
11 (19.3%)
4 (4.4%)
2 (3.8%)
Pharyngitis
3 (2.7%)
0
0
0
0
0
Pneumonia
3 (2.7%)
5 (8.3%)
1 (1.0%)
1 (1.8%)
0
0
Tooth infection
3 (2.7%)
0
0
0
1 (1.1%)
0
Upper respiratory tract infection
6 (5.5%)
2 (3.3%)
0
0
1 (1.1%)
0
Urinary tract infection
5 (4.5%)
1 (1.7%)
1 (1.0%)
1 (1.8%)
0
0
Injury, Poisoning and Procedural Complications
Accident
1 (0.9%)
3 (5.0%)
0
0
0
0
Contusion
1 (0.9%)
1 (1.7%)
0
2 (3.5%)
0
1 (1.9%)
Fall
3 (2.7%)
4 (6.7%)
1 (1.0%)
1 (1.8%)
0
0
Investigations
Blood glucose increased
3 (2.7%)
3 (5.0%)
0
0
0
0
Blood pressure increased
1 (0.9%)
3 (5.0%)
0
0
0
0
Blood pressure systolic increased
1 (0.9%)
4 (6.7%)
0
0
0
0
Blood urine present
2 (1.8%)
4 (6.7%)
0
0
0
0
Glucose urine present
2 (1.8%)
3 (5.0%)
0
0
0
0
Intraocular pressure increased
10 (9.1%)
11 (18.3%)
13 (13.4%)
2 (3.5%)
0
0
Lymphocyte count decreased
1 (0.9%)
2 (3.3%)
0
0
0
0
Protein urine present
4 (3.6%)
5 (8.3%)
0
1 (1.8%)
0
0
Visual acuity tests abnormal
4 (3.6%)
2 (3.3%)
5 (5.2%)
0
0
0
Metabolism and Nutrition Disorders
Diabetes mellitus
3 (2.7%)
0
1 (1.0%)
0
0
0
Hypercholesterolemia
1 (0.9%)
3 (5.0%)
1 (1.0%)
0
0
2 (3.8%)
Hypokalemia
0
3 (5.0%)
0
0
0
0
System organ class,
Preferred term
MedDRA Version 14.1
COPERNICUS
GALILEO
Week 24 to Week 100
Week 24 to Week 52
Week 52 to Week 76 aflibercept injection +PRN N=110
SHAM+PRN N=60
aflibercept injection +PRN N=97
SHAM N=57
aflibercept injection +PRN N= 91
SHAM+PRN N= 52
Musculoskeletal and Connective Tissue Disorders
Arthralgia
4 (3.6%)
2 (3.3%)
2 (2.1%)
1 (1.8%)
2 (2.2%)
0
Back pain
4 (3.6%)
0
3 (3.1%)
0
1 (1.1%)
0
Bursitis
1 (0.9%)
2 (3.3%)
0
0
0
0
Osteoarthritis
3 (2.7%)
4 (6.7%)
1 (1.0%)
0
2 (2.2%)
0
Pain in extremity
1 (0.9%)
2 (3.3%)
1 (1.0%)
0
0
0
Nervous System Disorders
Syncope
1 (0.9%)
2 (3.3%)
1 (1.0%)
2 (3.5%)
0
0
Psychiatric Disorders
Anxiety
1 (0.9%)
2 (3.3%)
0
0
0
0
Renal and Urinary Disorders
Renal failure acute
1 (0.9%)
2 (3.3%)
0
0
0
0
Respiratory, Thoracic and Mediastinal Disorders
Hypoxia
0
2 (3.3%)
0
0
0
0
Vascular Disorders
Hypertension
13 (11.8%)
9 (15.0%)
4 (4.1%)
4 (7.0%)
3 (3.3%)
2 (3.8%)
PRN: As needed (pro re nata)
Note: Patients are only counted once in each row but may appear in more than one row.
Treatment of BRVO
A total of 183 patients constituted the safety population in the aflibercept injection BRVO study (VIBRANT).
Patients in the aflibercept injection group (n=91) received aflibercept injection 2 mg, monthly up to week 24 and then received aflibercept injection every 2 months up to week 52. Patients in the laser control group received grid laser photocoagulation treatment at day 1 followed by sham injections monthly up to Week 24. Subjects in the laser arm became eligible for rescue treatment with aflibercept injection at week 24, and if pre-specified criteria were met, received 3 monthly 2 mg aflibercept injection injections, followed by 2 mg every two months. 67 patients in the laser control group received aflibercept injection rescue treatment after week 24.
The most common adverse reactions (≥1%) which have been assessed as having reasonable or suspected relationship to either the study drug or the injection procedure in the BRVO study (VIBRANT) are presented in Table 7.
Table 7: Adverse Reactions (≥1%) in BRVO Study (VIBRANT; Baseline to Week 24 and Week 24 to
Week 52 weeks)
Preferred term MedDRA version 17.0
aflibercept injection
(N=91)
Laser (N=92)
aflibercept injection (N=85)
Laser (N=83)
aflibercept injection Totalb
(N=152)
Baseline to Week 24
Week 24 to Week 52a
Conjunctival hemorrhage
19.8%
4.3%
10.6%
13.3%
11.2%
Eye pain
4.4%
5.4%
1.2%
3.6%
2.0%
Foreign body sensation in eyes
3.3%
0%
1.2%
0%
0.7%
Lacrimation increased
3.3%
0%
1.2%
0%
0.7%
Cataract
2.2%
0%
1.2%
0%
0.7%
Corneal epithelium defect
2.2%
0%
0%
0%
0%
Intraocular pressure increased
2.2%
0%
2.4%
1.2%
2.0%
Ocular hyperemia
2.2%
2.2%
0%
1.2%
0%
Vitreous detachment
2.2%
0%
0%
2.4%
1.3%
Vitreous floaters
1.1%
0%
0%
0%
0%
Vision blurred
1.1%
1.1%
1.2%
2.4%
2.0%
Eyelid edema
1.1%
0%
1.2%
0%
0.7%
Cataract cortical
1.1%
0%
1.2%
0%
0.7%
Cataract subcapsular
1.1%
0%
0%
0%
0%
Cataract traumatic
1.1%
0%
0%
0%
0%
Injection site pain
1.1%
0%
0%
0%
0%
Corneal abrasion
0%
0%
2.4%
1.2%
2.0%
Punctate keratitis
0%
0%
1.2%
0%
0.7%
Hypersensitivity
0%
1.1%
1.2%
0%
0.7% a As randomized in the BRVO (VIBRANT) study. Due to the study design, patients in the control (laser) arm may have received aflibercept injections and patients randomized to the aflibercept arm may have received laser treatment.
b Aflibercept Total = all patients who received at least one active aflibercept injection including patients who were previously in the laser control arm.
Note: Ocular ADR consider TEAE in study eye only. Patients are only counted once in each row but may appear in more than one row.
Treatment of DME
The data described in Table 8 reflect exposure to aflibercept injection in two randomized, double-blind, laser controlled Phase III studies in (2Q4 n =291, 2Q8 n=287; laser: n=287) patients with up to 52 weeks of exposure to aflibercept injection.
The data described in Table 9 reflect ADRs in two randomized, double blind, laser-controlled Phase III studies in patients with up to 100 weeks of exposure to aflibercept injection. 687 patients were treated at least once with 2mg aflibercept injection.
Table 8: Adverse Reactions with Incidence rate ≥1% in either aflibercept injection treatment arms in at least one study (VIVIDDME and VISTADME Studies; 52-week data)a
System/Organ Class Preferred Term (MedDRA Version 17.0)
VIVIDDME
VISTADME
Control (laser)
(N=133)
aflibercept injection 2Q4 (N=136)
aflibercept injection 2Q8 (N=135)
Control (laser)
(N=154)
aflibercept injection 2Q4 (N=155)
aflibercept injection 2Q8 (N=152)
Eye Disorders
Conjunctival hemorrhage
2.3%
22.8%
23.0%
30.5%
37.4%
27.6%
Eye pain
2.3%
6.6%
2.2%
9.7%
14.2%
11.8%
Vitreous floaters
0.8%
4.4%
1.5%
5.2%
9.7%
7.2%
Vitreous detachment
1.5%
1.5%
1.5%
5.2%
4.5%
5.9%
Cataract
3.8%
2.9%
5.9%
6.5%
7.1%
3.9%
Foreign body sensation in eyes
1.5%
0.7%
3.0%
4.5%
5.2%
3.3%
Ocular hyperemia
0.8%
1.5%
4.4%
7.1%
3.9%
3.3%
Cataract cortical
0
2.2%
2.2%
1.9%
0.6%
2.6%
Cataract subcapsular
0
1.5%
0.7%
2.6%
1.3%
2.6%
Lacrimation increased
0
3.7%
2.2%
3.2%
4.5%
2.0%
Vision blurred
0.8%
0
1.5%
3.2%
5.2%
2.0%
Eyelid edema
1.5%
0
0.7%
0.6%
0
1.3%
Punctate keratitis
1.5%
3.7%
4.4%
0.6%
2.6%
1.3%
Conjunctival hyperemia
3.0%
2.2%
0.7%
0
1.9%
0.7%
Vitreous hemorrhage
2.3%
2.2%
2.2%
5.2%
4.5%
0.7%
Cataract nuclear
1.5%
0
1.5%
2.6%
1.3%
0
Corneal erosion
1.5%
2.2%
3.7%
0
0
0
Retinal detachment
0.8%
0
1.5%
0
0
0
General Disorders and Administration Site Conditions
Injection site pain
0.8%
1.5%
1.5%
0
2.6%
1.3%
System/Organ Class Preferred Term (MedDRA Version 17.0)
VIVIDDME
VISTADME
Control
(laser) (N=133)
aflibercept injection 2Q4 (N=136)
aflibercept injection 2Q8 (N=135)
Control
(laser) (N=154)
aflibercept injection 2Q4 (N=155)
aflibercept injection 2Q8 (N=152)
Immune system disorders
Hypersensitivity
0
2.6%
0
0
0
0
Injury, Poisoning and Procedural Complications
Corneal abrasion
0
0
0
2.6%
1.9%
2.6%
Investigations
Intraocular pressure increased
6.8%
8.8%
4.4%
0.6%
3.2%
3.9% a As randomized in the VIVIDDME and VISTADME study. Due to the study design, beginning at week 24, if criteria were met, patients in the control (laser) arm may have received aflibercept injections (2Q8) and patients randomized to the aflibercept injection arm may have received laser treatment
Note: Patients are only counted once in each row but may appear in more than one row.
Table 9: Adverse Reactions with Incidence rate ≥1% reported in the DME Phase III studies (VISTADME and VIVIDDME, 100 weeks)a
System/Organ Class Preferred Term (MedDRA Version 17.0)
VIVIDDME
VISTADME
Control
(laser) (N=133)
aflibercept injection 2Q4
(N=136)
aflibercept injection 2Q8
(N=135)
Control
(laser) (N=154)
aflibercept injection 2Q4
(N=155)
aflibercept injection 2Q8
(N=152)
Eye Disorders
Conjunctival hemorrhage
5.3%
26.5%
24.4%
34.4%
40.6%
31.6%
Vitreous detachment
2.3%
2.9%
4.4%
9.7%
9.0%
14.5%
Eye pain
4.5%
8.1%
5.2%
13.0%
14.8%
13.8%
Vitreous floaters
1.5%
6.6%
1.5%
9.1%
13.5%
11.2%
Cataract
6.0%
11.0%
13.3 %
11.0%
13.5%
8.6%
Cataract subcapsular
0.8%
5.1%
2.2%
4.5%
3.9%
5.3%
Punctate keratitis
3.0%
4.4%
5.2%
0.6%
3.2%
4.6%
Cataract cortical
0
4.4%
3.7%
5.2%
1.3%
4.6%
Lacrimation increased
0
4.4%
2.2%
3.9%
4.5%
3.9%
Ocular hyperemia
1.5%
2.2%
4.4%
7.8%
3.9%
3.9%
Vision blurred
1.5%
0.7%
1.5%
6.5%
7.1%
3.9%
Foreign body sensation in eyes
1.5%
1.5%
3.0%
5.2%
5.2%
3.3%
Eyelid edema
2.3%
2.2%
2.2%
0.6%
0
2.0%
Vitreous hemorrhage
4.5%
2.9%
3.0%
9.1%
6.5%
2.0%
Cataract nuclear
3.0%
1.5%
3.0%
3.9%
3.2%
1.3%
Corneal epithelium defect
0
0
0
0.6%
0
1.3%
Conjunctival hyperemia
3.8%
3.7%
0.7%
0.6%
1.9%
0.7%
Corneal erosion
3.0%
2.2%
3.7%
0
0.6%
0
Iridocyclitis
0
0
0.7%
0
1.3%
0
Lentricular opacities
1.5%
1.5%
0.7%
0.6%
0
0
Retinal detachment
0.8%
0
1.5%
0
0.6%
0
General Disorders and Administration Site Conditions
Injection site pain
0.8%
1.5%
2.2%
0.6%
2.6%
1.3%
System/Organ Class Preferred Term (MedDRA Version 17.0)
VIVIDDME
VISTADME
Control
(laser)
(N=133)
aflibercept injection 2Q4
(N=136)
aflibercept injection 2Q8
(N=135)
Control
(laser)
(N=154)
aflibercept injection 2Q4
(N=155)
aflibercept injection 2Q8
(N=152)
Immune system disorders
Hypersensitivity
0
0
0
0
2.6%
0.7%
Injury, Poisoning and Procedural Complications
Corneal abrasion
0
0
0
3.9%
2.6%
3.9%
Investigations
Intraocular pressure increased
8.3%
15.4%
7.4%
1.3%
7.7%
6.6% a As randomized in the VIVIDDME and VISTADME study. Due to the study design, beginning at week 24, if criteria were met, patients in the control (laser) arm may have received aflibercept injections (2Q8) and patients randomized to the aflibercept arm may have received laser treatment
Note: Patients are only counted once in each row but may appear in more than one row.
Treatment of myopic CNV
A total of 122 patients from Japan, South Korea, Singapore, Taiwan and Hong Kong constituted the safety population in the aflibercept injection myopic CNV study (MYRROR).
Patients in the aflibercept injection group (n=91) received aflibercept injection 2 mg administered once at study start and then as needed (PRN) up to week 44.
Patients in the sham arm (n=31) received sham injections every 4 weeks through Week 20. Patients in the sham arm received a mandatory first dose of aflibercept injection at week 24, followed by additional aflibercept injection injections, if pre-specified criteria were met, up to Week 44.
The most common adverse reactions (≥1%) in the MYRROR study are presented in Table 10.
Table 10: Adverse Reactions with Incidence Rate ≥1% in Patients Treated with aflibercept injection or Sham (MYRROR, baseline up to 48 weeks)
System/Organ Class Preferred Term
MedDRA Version 16.0
aflibercept injectiona (n=91) %
Shamb (n=31) %
aflibercept injectiona (n=91) %
Sham+aflibercept injectionc
(n=31) %
Baseline to Week 24
Baseline to Week 48
Eye disorders
Cataract subcapsular
0
0
1 (1.1%)
0
Conjunctival haemorrhage
6 (6.6%)
1 (3.2%)
10 (11.0%)
1 (3.2%)
Corneal erosion
2 (2.2%)
1 (3.2%)
2 (2.2%)
1 (3.2%)
Eye pain
6 (6.6%)
1 (3.2%)
7 (7.7%)
1 (3.2%)
Ocular hyperaemia
2 (2.2%)
1 (3.2%)
2 (2.2%)
1 (3.2%)
Punctate keratitis
4 (4.4%)
3 (9.7%)
6 (6.6%)
3 (9.7%)
Retinal detachment excluding LLT
subretinal fluid
0
1 (3.2%)
0
1 (3.2%)
Retinal detachment including LLT
subretinal fluid
0
1 (3.2%)
0
1 (3.2%)
Retinal tear
1 (1.1%)
0
1 (1.1%)
0
Vitreous floaters
0
0
1 (1.1%)
0 a Aflibercept injection administered at baseline and additional injection in case of disease persistence or reoccurrence
b Received sham injections every 4 weeks through Week 20
c Mandatory injection of aflibercept injection at Week 24, thereafter additional injection in case of disease persistence or reoccurrence
Note: Patients are only counted once in each row but may appear in more than one row.
8.3 Less Common Clinical Trial Adverse Reactions
Less common adverse reactions reported in <1% of the patients treated with aflibercept injection in the Phase III studies (pooled data of the Phase III studies for wet AMD (96 weeks), CRVO (100 weeks), BRVO (52 weeks) and DME (100 weeks)) are listed below.
Eye Disorders: abnormal sensation in eye, anterior chamber flare, cataract traumatic, corneal edema, corneal epithelium defect, eyelid irritation, iridocyclitis, iritis, lenticular opacities, retinal detachment, retinal tear, uveitis, vitritis.
General Disorders and Administration Site Conditions: injection site irritation
Immune System Disorders: hypersensitivity
Infections and Infestations: endophthalmitis1, hypopyon
There were no less common adverse reactions reported in <1% of patients treated with aflibercept injection in the myopic CNV Phase III study (48 weeks).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data Clinical Trial Findings
There were no hematologic or clinical chemistry ADRs seen in Phase III wet AMD and DME studies.
There were no trends indicating an association with aflibercept injection and the development of clinically significant abnormal hematologic and clinical chemistry in the Phase III CRVO, BRVO, and myopic CNV studies.
8.5 Post-Market Adverse Reactions
- Eye disorder: scleritis, episcleritis, blindness
- Immune system disorders: severe anaphylactic/anaphylactoid reactions
- Skin and subcutaneous tissue disorders: pruritus, rash, urticaria
9 Drug Interactions
9.2 Drug Interactions Overview
No formal drug interaction studies have been performed with aflibercept injection. AFLIVU must not be mixed with other medicinal products.
Adjunctive use of verteporfin photodynamic therapy (PDT) and aflibercept injection has not been studied.
The safety and efficacy of wet AMD patients who were previously treated with laser photocoagulation have not been studied.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Vascular endothelial growth factor-A (VEGF-A) and placental growth factor (PlGF) are members of the VEGF family of pro-angiogenic factors that can act as potent mitogenic, chemotactic, and vascular
1 Culture positive and culture negative endophthalmitis
permeability factors for endothelial cells. VEGF acts via 2 receptor tyrosine kinases, VEGFR-1 and VEGFR- 2, present on the surface of endothelial cells. PlGF binds only to VEGFR-1, which is also present on the surface of leukocytes. Excessive activation of these receptors by VEGF-A can result in pathological neovascularization and excessive vascular permeability which is believed to contribute to vision loss in a variety of ocular diseases.
Aflibercept acts as a soluble decoy receptor that binds VEGF-A and PlGF with higher affinity than their natural receptors, and thereby can inhibit the binding and activation of these cognate VEGF receptor s.
10.2 Pharmacodynamics
Treatment of wet AMD
Data on pharmacodynamics effect of aflibercept, measured by central retinal thickness (CRT) and change in choroidal neovascularization (CNV) area, showed variable results across Phase I and Phase II studies. In the Phase III studies (VIEW1 and VIEW2), similar results on decrease in mean CNV area and CRT from baseline to Week 52 were reported for all 3 aflibercept treatment groups (0.5Q4, 2Q4, 2Q8). At Week 52 in VIEW 1, the mean change from baseline in CRT (aflibercept injection 2Q8 and aflibercept injection 2Q4 vs. ranibizumab 0.5Q4) was -130 and -121 microns vs. -129 microns, and at Week 96, was -121 and -108 microns vs. -114 microns, respectively. At Week 52 in VIEW 2, the mean change from baseline in CRT (aflibercept injection 2Q8 and aflibercept injection 2Q4 vs. ranibizumab 0.5Q4) was -149 and -157 microns vs. -139 microns, and at Week 96/100, was -145 and -146 microns vs. -121 microns, respectively.
Treatment of CRVO
Reductions in mean retinal thickness (microns, aflibercept injection vs. Sham) were observed in GALILEO (-449 vs. -169) and COPERNICUS (-457 vs. -145) at week 24 compared to baseline. However, the clinical relevance of these data is yet to be determined.
Treatment of BRVO
At week 24 the mean changes in retinal thickness in the aflibercept injection vs. the laser group were -280 microns vs. -128 microns.
Treatment of DME
VIVIDDME and VISTADME Studies
A reduction in CRT was observed in patients treated with aflibercept injection in the VIVIDDME and VISTADME DME clinical trials. At Week 52 in VIVIDDME, the mean change from baseline in CRT (aflibercept injection 2Q8 and aflibercept injection 2Q4 vs. Control) was -192.4 microns and -195.0 microns vs. -66.2 microns, and at Week 100, was -195.8 microns and -211.8 microns vs. -85.7 microns. At Week 52 in VISTADME, the mean change from baseline in CRT (aflibercept injection 2Q8 and aflibercept injection 2Q4 vs. Control) was -183.1 microns and -185.9 microns vs. -73.3 microns, and at Week 100, was -191.1 microns and -191.4 microns vs. -83.9 microns.
VIOLET Study
At week 52 of the study, i.e. second year of treatment, the mean changes in CRT for treat -and-extend (2T&E), pro re nata (2PRN) and 2Q8 were -2.1, 2.2 and -18.8 microns, respectively.
At week 100 of the study, i.e. third year of treatment, the mean changes in CRT for 2T&E, 2PRN and 2Q8 were 2.3, -13.9 and -15.5 microns, respectively.
Treatment of myopic CNV
In patients treated with aflibercept injection (one injection given at start of therapy, additional injection given in case of disease persistence or recurrence) retinal thickness was assessed by Optical Coherence Tomography (OCT). The mean change in CRT (microns, aflibercept injection vs. Sham) from baseline to week 24 was -79 vs. -4. The mean change in CRT through Week 48 was -83 vs. -57.
10.3 Pharmacokinetics
AFLIVU is administered directly into the vitreous to exert local effects in the eye.
Absorption:
Following intravitreal administration of aflibercept, a fraction of the administered dose is expected to bind with free endogenous VEGF to form an inactive VEGF: aflibercept complex in the eye. From the ocular space, free and bound aflibercept are slowly absorbed into the systemic circulation where it is predominately observed as the inactive stable complex with VEGF; however, only "free aflibercept" is able to bind endogenous VEGF. Peak plasma concentrations (Cmax) of free aflibercept are reached within 1 to 3 days after administration.
Distribution:
In a pharmacokinetic substudy with frequent sampling in wAMD patients, maximum plasma concentrations of free aflibercept (systemic Cmax) were low, with a mean of approximately 0.02 microgram/mL (range 0 to 0.054 microgram/mL) within 1 to 3 days after a 2 mg intravitreal injection, and were undetectable 2 weeks following dosage in almost all patients. Aflibercept does not accumulate in the plasma when administered intravitreally every 4 weeks.
It is estimated that after intravitreal administration of 2 mg to patients, the mean maximum plasma concentration of free aflibercept is more than a 100 fold lower than the concentration of aflibercept required to half-maximally bind systemic VEGF (2.91 microgram/mL) in a study of healthy volunteers.
These pharmacokinetic results were consistent in pharmacokinetic sub-studies in patients with CRVO, BRVO, DME, and myopic CNV with mean Cmax of free aflibercept in plasma in the range of 0.03 to
0.05 microgram/mL. Plasma concentrations of free aflibercept declined to values below or close to the lower limit of quantitation generally within one week; undetectable concentrations were reached after two weeks in all patients.
Metabolism:
As aflibercept injection is a protein-based therapeutic, no metabolism studies have been conducted.
Elimination:
Aflibercept is expected to be eliminated through both binding to endogenous VEGF and a slower non- saturable clearance (e.g., proteolysis) mechanism.
Special populations and conditions
- Pediatrics (< 18 years of age) Wet AMD does not occur in children or adolescents. The safety and efficacy of aflibercept injection have not been studied in pediatric patients in the indications wet AMD, CRVO, BRVO, DME, and myopic CNV.
- Geriatrics (≥ 65 years of age): No special considerations are needed.
- Hepatic Insufficiency: No specific studies in patients with hepatic impairment were conducted with aflibercept injection.
Renal Insufficiency No special studies in patients with renal impairment were conducted with aflibercept injection. Pharmacokinetic analysis of wet AMD patients in the VIEW2 study, of which 40% had renal impairment (24% mild, 15% moderate, and 1% severe), revealed no differences with respect to plasma concentrations of active drug after intravitreal administration every 4 or 8 weeks.
Similar results were seen in patients with CRVO in the GALILEO study.
Pharmacokinetic analysis of DME patients in the VIVIDDME study, of which 47% had renal impairment (35% mild, 10% moderate, and 2% severe), detected no difference in free aflibercept concentrations in patients with different renal function.
Similar results were seen in patients with myopic CNV in the MYRROR study.
10.4 Immunogenicity
As with all therapeutic proteins, there is a potential for immunogenicity with AFLIVU.
Immunogenicity was measured in serum samples. The immunogenicity data reflect the percentage of patients whose test results were considered positive for antibodies to aflibercept in immunoassays, and are highly dependent on the sensitivity and specificity of the assays.
In Phase III studies, the pre-treatment incidence of immune reactivity to aflibercept was approximately 1% to 3% in all treatment groups. After dosing with aflibercept for up to 96 weeks (wet AMD), 52 weeks (CRVO and BRVO), 100 weeks (DME), and 48 weeks (myopic CNV), antibodies to aflibercept were detected in a similar percentage range of patients. In the wet AMD, CRVO, BRVO, DME, and myopic CNV studies, there were no differences in efficacy or safety between patients with or without immune reactivity.
Overall, the risk of significant immunogenicity with aflibercept injection appears to be very low.
11 Storage, Stability, and Disposal
Vial
Store in a refrigerator (2°C to 8°C). Do not freeze.
Keep the vial in the outer carton in order to protect from light.
Pre-filled syringe
Store in a refrigerator (2°C to 8°C). Do not freeze.
Keep the pre-filled syringe in its blister pack and in the outer carton in order to protect from light.
12 Special handling Instructions
For the intravitreal injection, a 30 G x ½ inch injection needle should be used.
Vial
THE VIAL IS FOR SINGLE USE IN ONE EYE ONLY.
Prior to administration visually inspect the solution for injection. Do not use the vial if particulates, cloudiness, or discoloration are visible.
Prior to usage, unopened vial of AFLIVU may be stored at room temperature (25°C) for up to 24 hours. After opening the vial, proceed under aseptic conditions.
Pre-filled syringe
THE PRE-FILLED SYRINGE IS FOR SINGLE USE IN ONE EYE ONLY.
The pre-filled syringe contains more than the recommended dose of 2 mg aflibercept (equivalent to 50 microliters). The excess volume must be discarded prior to the administration.
Prior to administration visually inspect the solution for injection. Do not use the pre-filled syringe if particulates, cloudiness, or discoloration are visible.
Prior to usage, the blister pack of AFLIVU may be stored at room temperature (25°C) for up to 24 hours. After opening the blister pack, proceed under aseptic conditions.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance:
Aflibercept
Chemical name:
des-432-lysine-[human vascular endothelial growth factor receptor 1-(103-204)-peptide (containing Ig-like C2-type 2 domain) fusion protein with human vascular endothelial growth factor receptor 2-(206-308)-peptide (containing Ig-like C2-type 3 domain fragment) fusion protein with human
immunoglobulin G1-(227 C-terminal residues)-peptide (Fc fragment)], (211-211’:214-214’)-bisdisulfide dimer
Molecular formula:
C4318H6788N1164O1304S32
Molecular weight:
Without glycolysation: 97 kDa With glycolysation: 115 kDa
Structure:
VEGFR1 VEGFR2 Aflibercept
1 1
2 2
2 2
3 3
3 3
- 4 4 IgG1 Fc
- 5 5
- 6 6
- 7 7
Physicochemical properties:
Aflibercept is a dimeric glycoprotein.
pH:
5.5
Product Characteristics:
AFLIVU (aflibercept injection) is a recombinant fusion protein consisting of portions of human Vascular Endothelial Growth Factor (VEGF) receptor 1 and 2 extracellular domains fused to the Fc portion of human IgG1 and formulated as an iso-osmotic solution for intravitreal administration. Aflibercept is produced in Chinese hamster ovary (CHO) K1 cells by recombinant DNA technology.
14 Clinical Trials
14.1 Clinical Trials by Indication – Reference Biologic Drug
Treatment of Wet AMD
VIEW1 and VIEW2 Studies
The safety and efficacy of aflibercept injection were assessed in 2 randomized, multi-center, double-blind, active-controlled studies in patients with wet AMD. VIEW1 was conducted in Canada and the United States of America. VIEW2 was conducted in Europe, Latin America and Asia. A total of 2412 patients were treated and evaluable for efficacy (1817 with aflibercept injection) in the 2 Phase III studies (VIEW1 and VIEW2). In each study, patients were randomly assigned in a 1:1:1:1 ratio to 1 of 4 dosing regimens.
Administration in 2 of the aflibercept injection arms was every 4 weeks, and in the third arm, administration was extended to a longer dosing interval of every 8 weeks:
- 1) aflibercept injection administered at 2 mg every 8 weeks following 3 initial monthly doses (aflibercept injection 2Q8),
- 2) aflibercept injection administered at 2 mg every 4 weeks (aflibercept injection 2Q4),
- 3) aflibercept injection administered at 0.5 mg every 4 weeks (aflibercept injection 0.5Q4), and
- 4) Ranibizumab administered at 0.5 mg every 4 weeks (ranibizumab 0.5Q4)
In the second year of the studies, patients continued to receive the dosage strength to which they were initially randomized but on a modified dosing schedule guided by pre-specified retreatment criteria with a protocol-defined maximum dosing interval of 12 weeks:
- Increase in central retinal thickness (CRT) of ≥100 μm compared to the lowest previous value as measured by optical coherence tomography (OCT), or
A loss from the best previous letter score of ≥5 Early Treatment Diabetic Retinopathy Study
(ETDRS) letters in conjunction with recurrent fluid as indicated by OCT, or
- New or persistent fluid as indicated by OCT, or
- New onset classic neovascularization, or
- New or persistent leak on fluorescein angiography (FA), or
- New macular hemorrhage, or
- 12 weeks have elapsed since the previous injection.
The primary efficacy endpoint was the proportion of patients who maintained vision (i.e., loss of fewer than 15 letters of BCVA compared to Baseline) at Week 52. The non-inferiority margin was 10%. The secondary efficacy variables included changes from Baseline to Week 52 in (1) BCVA (ETDRS letter score); (2) the proportion of patients who gained 15 or more letters; (3) total NEI VFQ-25 (National Eye Institute 25-item Visual Function Questionnaire) score; and (4) CNV (choroidal neovascularisation) area as assessed by fluorescein angiography (FA).
Patients ranged in age from 49 to 99 years (with a mean of 76 years) with primarily active subfoveal CNV lesions secondary to wet AMD, also including juxtafoveal lesions, as seen on FA. In the clinical studies, approximately 89% (1616/1817) of the patients randomized to treatment with aflibercept injection were 65 years of age or older and approximately 63% (1139/1817) were 75 years of age or older.
Table 11 – Summary of Patient Demographics for Clinical Trials in wet AMD
Study#
Trial Design
Dosage, route of administration, and duration
Study Subjects (n)
Mean Age (Range)
Sex
VIEW1
Intravitreal injection
aflibercept injection administered at 2
aflibercept injection 2Q8: n= 303
78.1
(49-99 years)
Male: 41.2% mg every 8 weeks following 3 initial
aflibercept injection 2Q4: n= 304
Female: 58.8% randomized, multi-center, double-blind, active- controlled
monthly doses (aflibercept injection
2Q8),
- aflibercept injection administered at 2 mg every 4 weeks (aflibercept injection 2Q4),
- aflibercept injection administered at 0.5 mg every 4 weeks (aflibercept injection 0.5Q4), and
- Ranibizumab administered at 0.5 mg every 4 weeks (ranibizumab 0.5Q4)
96-week study
aflibercept injection 0.5Q4: n=304
ranibizumab 0.5mgQ4: n=306
VIEW2 aflibercept injection 2Q8: n=313
aflibercept injection 2Q4: n= 313
aflibercept injection 0.5Q4: n=311
ranibizumab 0.5mg Q4: n=303
73.9
(50-93 years)
Male: 44.5%
Female: 55.5%
Table 12: Efficacy Outcomes at Week 52; VIEW1 and VIEW2 Studies (wet AMD)
VIEW1
VIEW2 aflibercept injection
2 mg Q8a
aflibercept injection 2 mg Q4
ranibizumab
0.5 mg Q4
aflibercep t injection
2 mg Q8a
aflibercept injection 2 mg Q4
ranibizumab
0.5 mg Q4
Efficacy Outcomes
Per Protocol Set
N=265
N=285
N=269
N=270
N=274
N=269
Proportion of patients who maintained visual acuity (%)
(<15 letters of BCVA loss)
95.1%
95.1
94.4%
95.6%
95.6
94.4%
Difference b (%) (95% CI) c
0.7
(-3.1, 4.5) d
0.7
(-3.1, 4.4) d
1.1
(-2.6, 4.8)d
1.2
(-2.5, 4.9)d
Full Analysis Set (FAS)
N=301
N=304
N=304
N=306
N=309
N=291
Mean number of active injections over 52 weeks
7.6
12.5
12.1
7.7
12.6
12.7
Mean change in BCVA as measured by ETDRS letter score from Baseline
7.9
10.9
8.1
8.9
7.6
9.4
Difference b in LS mean (95% CI) c
0.3
(-2.0, 2.5)
3.2
(0.9, 5.4)
-0.9
(-3.1, 1.3)
-1.9
(-4.1, 0.2)
Patients who gained at least 15 letters of vision from baseline (%)
92
(30.6%)
114
(37.5%)
94
(30.9%)
96
(31.4%)
91
(29.5%)
99
(34.0%)
Difference b (%) (95% CI) c
-0.4
(-7.7, 7.0)
6.6
(-1, 14.1)
-2.7
(-10.2, 4.9)
-4.6
(-12.2, 2.9)
BCVA= Best Corrected Visual Acuity; CI= Confidence Interval; ETDRS= Early Treatment Diabetic Retinopathy Study; LOCF= Last Observation Carried Forward (baseline values are not carried forward)
- a After treatment initiation with 3 monthly doses
- b Aflibercept injection group minus the ranibizumab group.
- c 95.1% CI for VIEW1; the CI reflected an alpha adjustment of 0.1% to account for safety assessments of the data by an Independent Data Monitoring Committee
- d A confidence interval lying entirely above -10% indicates a non-inferiority of aflibercept injection to ranibizumab.
52 Week Analyses
In a sensitivity analysis where dropouts were counted as non-responders (regardless of the time of when the dropouts occurred and the patient’s visual acuity outcome at the time of dropout), the proportion of patients who maintained visual acuity for the aflibercept injection 2Q8, aflibercept injection 2Q4 and ranibizumab 0.5Q4 arms were 88.0%, 91.8%, and 87.8%, respectively, in VIEW1, and 88.6%, 86.1%, and 89.4%, respectively, in VIEW2.
Across both Phase III studies, the aflibercept injection 2 Q8 treatment group received less injections than the aflibercept injection 2Q4 and ranibizumab 0.5Q4 treatment groups (i.e., mean [SD] of 7.6 [1.1], 12.3 [1.8] and 12.3 [1.9], respectively).
The proportion of patients who maintained vision in the aflibercept injection 2Q8 and in the aflibercept injection 2Q4 treatment arms were both shown to be non-inferior to ranibizumab 0.5 mg every 4 weeks.
96 Week Analyses
In the second year, the mean numbers of active injections in VIEW 1 were 4.3, 4.1 and 4.6 for the groups receiving aflibercept injection 2Q8, aflibercept injection 2Q4, and ranibizumab 0.5Q4, respectively. In VIEW2, the corresponding mean number of active injections was 4.0, 4.0, and 4.9, respectively. Ninety percent (90%) of patients originally treated with aflibercept injection 2Q8 or aflibercept 2Q4 received 6 doses or less. 72% and 78% respectively received 4 doses or less among those patients completing the second year of the studies. In VIEW1, the proportion of patients who maintained visual acuity was 91.4%, 93.1%, and 89.8% in the aflibercept injection 2Q8, aflibercept injection 2Q4 and ranibizumab 0.5Q4 treatment groups, respectively. In VIEW2, the corresponding results were 93.5%, 91.3% and 93.5%, respectively. In VIEW1, the mean change from baseline in BCVA was +7.1, +9.3, and +7.3 letters in the aflibercept injection 2Q8, aflibercept injection 2Q4, and ranibizumab 0.5Q4 groups, respectively; and +8.1 letters, +6.0 and +8.5 letters in VIEW2. In VIEW1, the proportion of patients who gained at least 15 letters of vision from baseline was 32.9%, 35.5%, and 30.6% in the aflibercept injection 2Q8, aflibercept injection 2Q4 and ranibizumab 0.5Q4 treatment groups, respectively; and 34.0%, 26.9%, and 32.7% in VIEW2.
Figure 10: Mean Change in Visual Acuity from Baseline to Week 52; Data from the VIEW1 and VIEW2 studies
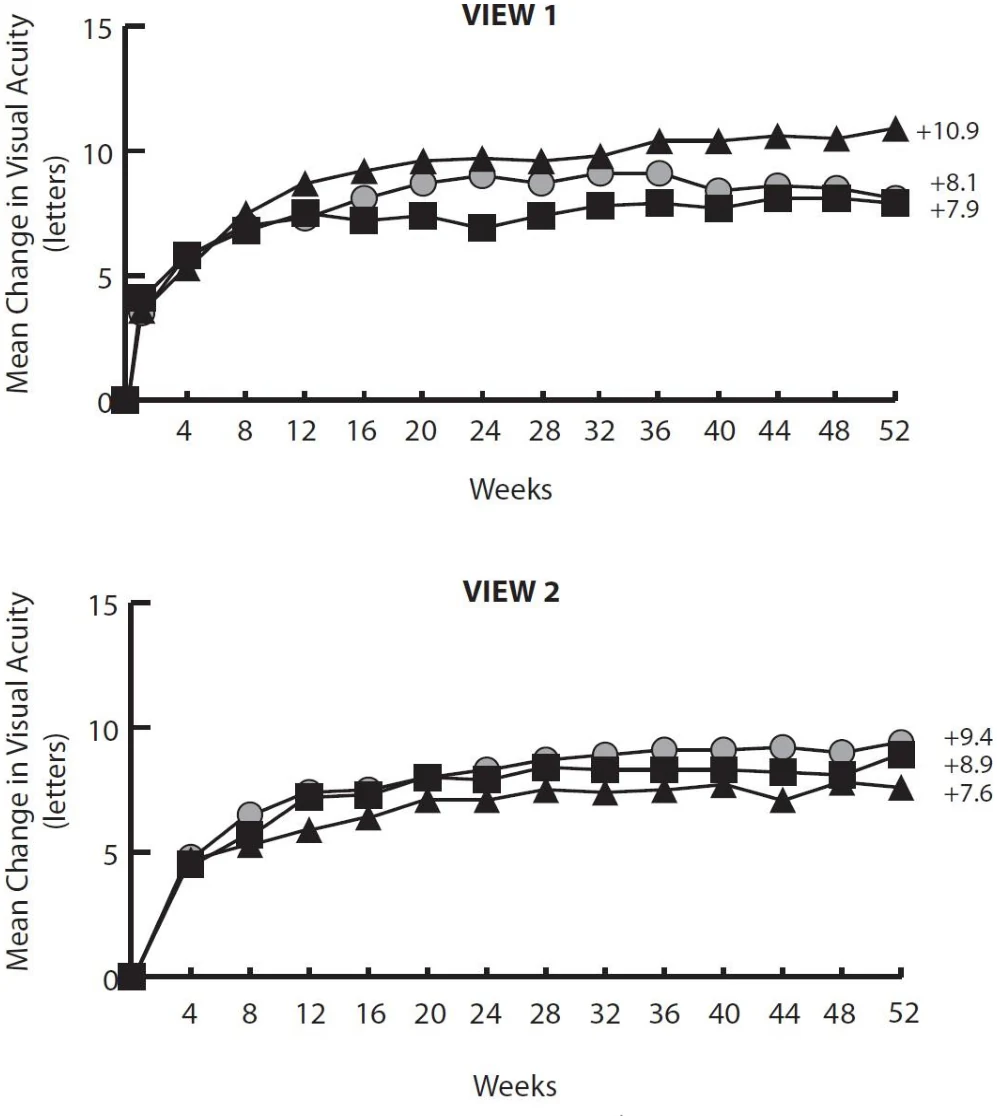


aflibercept injection 2mg Q8 weeks
aflibercept injection 2mg Q4 weeks

Ranibizumab 0.5mg Q4 weeks
ALTAIR Study
ALTAIR was a 96-week exploratory open-label phase 4 study in 247 Japanese patients with treatment naïve wet AMD, designed to assess the efficacy and safety of aflibercept injection following two different adjustment intervals (2 weeks and 4 weeks) of a treat-and-extend dosing regimen.
All patients received 3 monthly doses of aflibercept injection 2 mg, followed by one injection after a 2-month interval. At week 16, patients were randomized 1:1 into two treatment groups:
- 1) Aflibercept injection treat-and-extend with 2-week adjustments and
- 2) Aflibercept injection treat-and-extend with 4-week adjustments.
Extension or shortening of the interval was decided based on visual and/or anatomic criteria defined by protocol.
The primary efficacy endpoint was mean change in BCVA from baseline to week 52.
At week 52, patients in the treat-and-extend arm with 2-week adjustments gained a mean of 9.0 ± 14.6 (range: -62 to 46) letters from baseline.
ARIES Study
ARIES was a 104-week multi-center, randomized, open-label, active-controlled study in patients in several countries including Canada, with treatment naïve wet AMD. Two hundred and eighty-seven (287) patients were treated with the 3 consecutive monthly doses followed by a dose after 8 weeks. At the 16 week timepoint, 271 patients were randomized into two arms: patients randomized to the first arm were treated using treat-and-extend with 2-week adjustments to the end of 2 years (Early start), and patients randomized to the second arm continued with dosing every 8 weeks for the remainder of the first year, and then were treated using treat-and-extend with 2-week adjustments in the second year (Late start). The primary efficacy endpoint was the change in BCVA from week 16 (randomization) to week 104.
The change in mean BCVA from week 16 to week 104 was -2.1 ± 11.4 (range: -44 to 23) letters in the Early start treat-and-extend group and -0.4 ± 8.4 (range: -25 to 17) letters in the Late start treat-and- extend group.
Treatment of CRVO
The safety and efficacy of aflibercept injection (aflibercept) were assessed in two randomized, multi-center, double- masked, sham-controlled studies in patients with macular edema secondary to CRVO. A total of 358 patients were treated and evaluable for efficacy (217 with aflibercept injection) in the two studies COPERNICUS and GALILEO. In both studies, patients were randomly assigned in a 3:2 ratio to either 2 mg aflibercept injection administered every 4 weeks (2Q4) or the control group receiving sham injections every 4 weeks for a total of 6 injections for the first 24 weeks.
After 6 monthly injections, patients received treatment only if they met pre-specified retreatment criteria, except for patients in the control group in the GALILEO study who continued to receive sham (control to control) (see Table 13).
The pre-specified retreatment criteria were as follows:
- Greater than 50 micron increase in CRT compared to the lowest previous measurement as assessed by OCT
- New or persistent cystic retinal changes or subretinal fluid as assessed by OCT
- Persistent diffuse edema ≥ 250 microns in the central subfield as assessed by OCT
- Loss of five or more letters in BCVA compared to the best previous measurement in conjunction with any increase in CRT as assessed by OCT
- Increase of five or more letters in BCVA compared to the most recent previous assessment.
After 52 weeks, all patients received the treatment if they met pre-specified visual or anatomic retreatment criteria until week 76 (GALILEO study) or week 100 (COPERNICUS study).
In both studies, the primary efficacy endpoint was the proportion of patients who gained at least 15 letters in Best Corrected Visual Acuity (BCVA) at Week 24 compared to baseline. Secondary endpoints included change in visual acuity at Week 24 compared to baseline, the mean change in baseline central retinal thickness, the mean change in the baseline NEI VFQ-25 total score at Week 24 and the proportion of patients progressing to anterior segment neovascularization.
Patient ages ranged from 22 to 89 years with a mean of 64 years. In the CRVO studies, approximately 52% (112/217) of the patients randomized to treatment with aflibercept injection were 65 years of age or older, and approximately 18% (38/217) were 75 years of age or older.
Table 13 – Summary of Patient Demographics for Clinical Trials in CRVO
Study#
Trial Design
Dosage, route of administration, and duration
Study Patients (n)
Mean Age (Range)
Sex
COPERNICUS
Intravitreal injection
aflibercept injection: n= 114
66.3
Male: 57%
•
randomized, multi-center, double- masked, sham- controlled
- Sham injections every 4 weeks up to week 24; then aflibercept injection 2 mg PRN
100-week study
GALILEO Intravitreal injection
- aflibercept injection administered at 2 mg aflibercept injection 4 weeks (aflibercept injection 2Q4), up to week 24; then aflibercept injection 2 mg PRN
- Sham injections every 4 weeks up to week 52; then aflibercept injection 2 mg PRN
76-week study
aflibercept injection: n= 104 Sham: n=68
61.5
(29-88 years)
Male: 55.6%
Female: 44.4%
PRN=pro re nata (as needed)
Superiority of treatment with aflibercept injection versus treatment with sham injection was shown for the primary endpoint at 24 weeks in both the COPERNICUS and GALILEO studies. Rapid improvements in visual acuity were observed with aflibercept injection treatment as early as 4 weeks after the first aflibercept injection.
Results from the analysis of the COPERNICUS and GALILEO studies are shown in Table 14 and Figure 11 below:
| aflibercept injection administered at 2 mg every 4 weeks (aflibercept injection | Sham: n=74 (22- | 89 years) Female: 43% |
|---|---|---|
2Q4) up to week 24; then aflibercept injection 2 mg PRN |
Table 14: Efficacy Outcomes at Week 24 (Full Analysis Set with LOCF) in COPERNICUS and GALILEO Studies
Efficacy Outcomes
COPERNICUS
GALILEO aflibercept injection 2 mg Q4
Control
(Sham)a
aflibercept injection 2 mg Q4
Control
(Sham) a
(N = 114)
(N = 73)
(N = 103)
(N = 68)
Proportion of patients who gained at least 15
letters in BCVA from baselineb
56%
12%
60%
22%
Weighted difference (%)c,d
44.8%
38.3%
(95% CI)
(33.0, 56.6)
(24.4, 52.1)
p-value
p < 0.0001
p < 0.0001
Mean change in BCVA as measured by ETDRS
letter score from baseline (SD)
17.3 (12.8)
-4.0 (18.0)
18.0 (12.2)
3.3 (14.1)
Difference in LS meanc,e
21.7
14.7
(95% CI)
(17.4, 26.0)
(10.8, 18.7)
p-value
p<0.0001
p<0.0001
- a Control group received sham injections every 4 weeks (Q4)
- b Subjects who discontinued prior to week 24 and had less than 5 injections of study drug or sham were evaluated as non - responders; otherwise, missing values were imputed using LOCF analyses in COPERNICUS study. Subjects who discontinued from the study prior to Week 24 were judged as non-responders in GALILEO study.
- c Difference is aflibercept injection 2 mg Q4 weeks minus control
- d Difference and confidence interval (CI) are calculated using Cochran-Mantel-Haenszel (CMH) test adjusted for region (America vs. rest of the world for COPERNICUS and Europe vs. Asia/Pacific for GALILEO) and baseline BCVA category (> 20/200 and ≤ 20/200)
- e
LS mean difference and confidence interval based on an ANCOVA model with factors treatment group, region (America vs. rest of the world for COPERNICUS and Europe vs. Asia/Pacific for GALILEO) and baseline BCVA category (> 20/200 and
≤ 20/200)
BCVA: Best Corrected Visual Acuity; ETDRS: Early Treatment Diabetic Retinopathy Study; LOCF: Last Observation Carried Forward; SD: Standard deviation; LS: Least square means derived from ANCOVA
In the COPERNICUS study, at Week 52, the proportion of patients gaining at least 15 letters in BCVA from baseline was 55% for the group receiving aflibercept injection and 30% for the group initially receiving sham treatment, and at Week 100, the proportions were 49.1% and 23.3% for the group receiving aflibercept injection and for the group initially receiving sham treatment, respectively. At Week 52, the mean improvement from baseline in BCVA was +16.2 letters for the group receiving aflibercept injection and +3.8 letters for the group initially receiving sham treatment, and at Week 100, the mean improvement were 13.0 and 1.5 letters for the group receiving aflibercept injection and for the group initially receiving sham treatment, respectively.
At Week 52 in the GALILEO study, the proportion of patients gaining at least 15 letters in BCVA from baseline was 60% for the group receiving aflibercept injection and 32% for the group initially receiving sham treatment, and at Week 76, the proportions were 57.3% and 29.4% for the group receiving aflibercept injection and for the group initially receiving sham treatment, respectively. At Week 52, the mean improvement from baseline in BCVA was +16.9 letters for the group receiving aflibercept injection and +3.8 letters for the group initially receiving sham treatment, and at Week 76, the mean improvement were 13.7 and 6.2 letters for the group receiving aflibercept injection and for the group initially receiving sham treatment, respectively.
Treatment effects in evaluable subgroups (e.g., age, gender, race, baseline visual acuity, retinal perfusion status, and CRVO duration) in each study were in general consistent with the results in the overall populations.
Figure 11: Mean change from baseline to Week 24 in best corrected visual acuity by treatment group for the COPERNICUS and GALILEO studies (Full Analysis Set, LOCF)
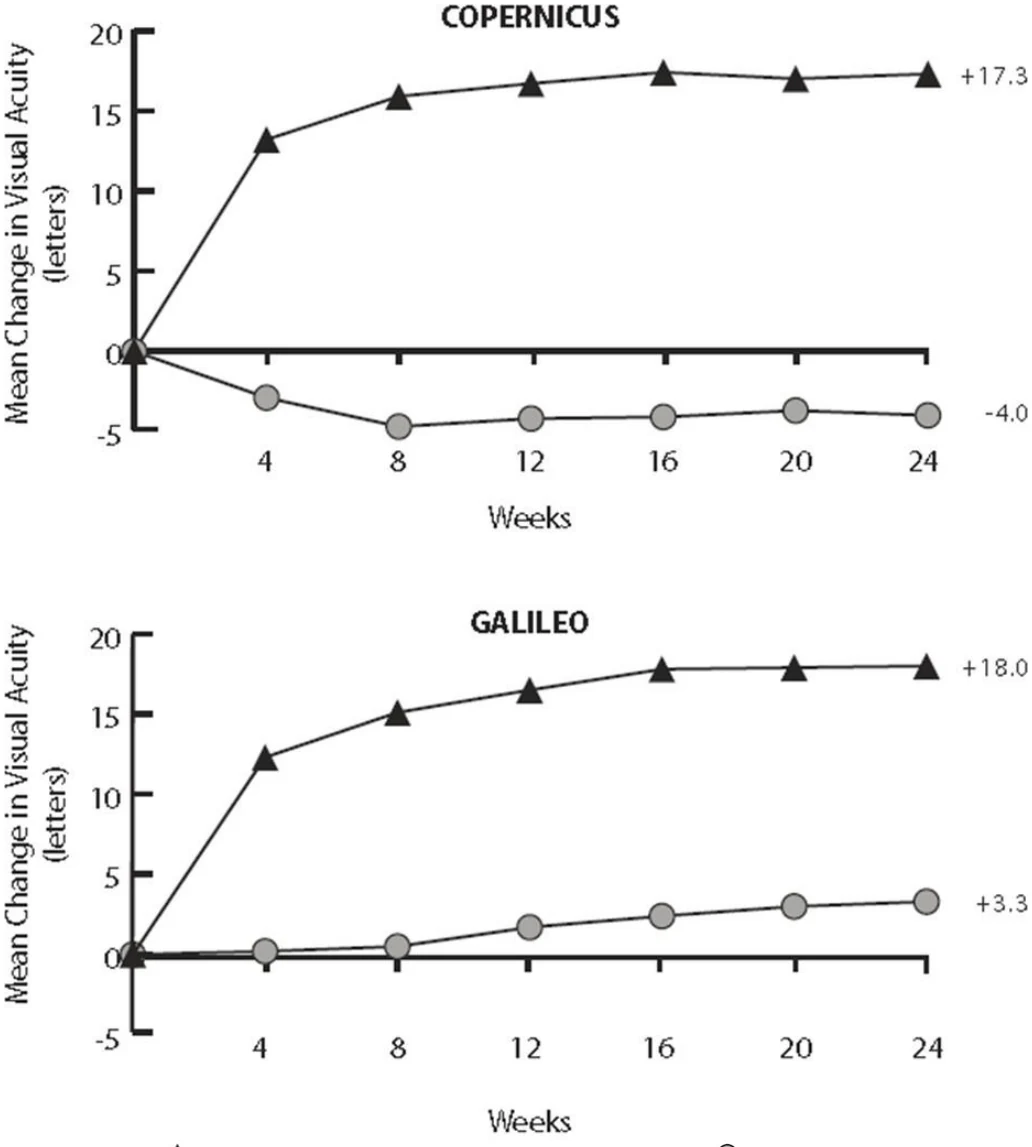

aflibercept injection 2 mg Q4 weeks
Control Group
Treatment of BRVO
The safety and efficacy of aflibercept, solution for intravitreal injection were assessed in a randomized, multi-center, double-masked, active-controlled study in patients with macular edema secondary to BRVO. A total of 181 patients were treated and evaluable for efficacy (91 with aflibercept injection) in the VIBRANT study. In the study, patients were randomly assigned in a 1:1 ratio to either 2 mg aflibercept injection administered every 4 weeks (2Q4) with a total of 6 injections or laser photocoagulation administered at baseline and subsequently as needed at and after week 12 (laser control group) (see Table 15).
After 6 monthly injections (week 24), patients in the aflibercept injection group received an injection every 2 months (8 weeks) up to week 52. Rescue laser treatment was permitted at week 36 if at least 1 rescue treatment criterion was met:
- >50 micron increase in CRT on OCT compared to the lowest previous measurement
- new or persistent cystic retinal changes or sub-retinal fluid on OCT or persistent diffuse edema in the central subfield on OCT
- a loss of ≥5 letters from the best previous measurement due to BRVO, in conjunction with any increase in retinal thickness in the central subfield on OCT from the best previous measurement.
For patients randomized to the laser control group, additional rescue laser treatment and rescue treatment with aflibercept injection starting at week 24 (3 monthly injections followed by an injection every 2 months) were also permitted if specific criteria (above) were met.
9 of 91 patients in the aflibercept injection group received laser therapy at week 36 and 67 of 90 patients in the laser group received aflibercept injection treatment after week 24.
Patient ages ranged from 42 to 94 years with a mean of 65 years. At baseline, 22% (20/91) of the patients randomized to treatment with aflibercept injection had a retinal perfusion status classified as non-perfused. 19.8% patients in the aflibercept injection group and 16.3% of patients in the laser + aflibercept injection group discontinued the study prior to week 52.
In the VIBRANT study, the primary efficacy endpoint was the proportion of patients who gained at least 15 letters in BCVA at Week 24 compared to baseline. Secondary endpoints efficacy analyses included change from baseline in BCVA score and change from baseline in CRT.
Table 15 – Summary of Patient Demographics for Clinical Trial in BRVO
Study#
Trial Design
Dosage, route of administration, and duration
Study Patients (n)
Mean Age (Range)
Sex
VIBRANT
randomized, multi-center, double- masked, active- controlled
Intravitreal injection
- aflibercept injection administered at 2 mg every 4 weeks (aflibercept injection 2Q4) up to week 24; then aflibercept injection 2 mg every 8 weeks (aflibercept injection 2Q8). Rescue laser treatment was permitted at week 36 if rescue treatment criteria were met.
Laser treatment at day 1 and sham injections every 4 weeks up to week 48
Rescue treatment with aflibercept injection starting at week 24 was permitted if rescue treatment criteria were met.
52-week study
aflibercept injection: n= 91 Sham: n=92
65.5
(42-94 years)
Male: 54.1%
Female: 45.9%
At week 24, the results of patients in the aflibercept injection group were shown superior to the laser control for the primary endpoint (the proportion of patients who gained at least 15 letters in BCVA at week 24) and secondary endpoints of visual acuity (mean change from baseline in BCVA at week 24). A rapid gain in visual acuity was observed as early as one week after treatment initiation with aflibercept injection.
Results from the analysis of the VIBRANT study are shown in Table 16 and Figure 12 below:
Table 16: Efficacy Outcomes at Week 24 (Full Analysis Set with LOCF) in BRVO (VIBRANT study)
Efficacy Outcomes
Week 24
aflibercept injection
2 mg Q4
Control (Laser)a
(N = 91)
(N = 90)
Proportion of patients who gained at least 15
letters in BCVA from baseline
52.7%
26.7%
Adjusted difference (%)b,c
26.6%
(95% CI)
(13.0, 40.1)
p-valued
p= 0.0003
Mean change in BCVA as measured by ETDRS
letter score from baseline (SD)
17.0 (11.9)
6.9 (12.9)
Difference in LS meanb,e
10.5
(95% CI)
(7.1, 14.0)
p-valuee
p< 0.0001
a Control group received sham injections every 4 weeks (Q4)
b Difference is aflibercept injection 2 mg Q4 weeks minus laser group
c Difference and confidence interval (CI) were calculated using Mantel-Haenszel weighting scheme adjusted by regions
(Japan vs North America) and baseline Best Corrected Visual Acuity (BCVA) (BCVA ≤20/200 and BCVA >20/200).
d P-value was calculated using 2-sided Cochran-Mantel-Haenszel test adjusted by regions (Japan vs North America) and baseline BCVA (BCVA ≤20/200 and BCVA >20/200).
e LS mean difference and confidence interval (CI) and p-value were based on an analysis of covariance (ANCOVA) model with baseline measurement as covariate and treatment group, region, and baseline Best Corrected Visual Acuity (BCVA) (BCVA ≤20/200 and BCVA >20/200) as fixed factors.
BCVA: Best Corrected Visual Acuity; ETDRS: Early Treatment Diabetic Retinopathy Study; LOCF: Last Observation Carried
Forward; SD: Standard deviation; LS: Least square means derived from ANCOVA
In the VIBRANT study, at week 52, the proportion of patients gaining at least 15 letters in BCVA from baseline was 57.1% for the group receiving aflibercept injection and 41.1% for the group initially receiving laser treatment. At week 52, the mean improvement from baseline in BCVA was +17.1 letters for the group receiving aflibercept injection and +12.2 letters for the group initially receiving laser treatment. At week 52, the mean change in CRT was -284 microns for the group receiving aflibercept injection and -249 microns for the group initially receiving laser treatment.
Treatment effects in evaluable subgroups (e.g., age, gender, and baseline retinal perfusion status) in the study were in general consistent with the results in the overall populations.
Figure 12: Change From Baseline to Week 24 in Mean BCVA Score in BRVO (VIBRANT study) (LOCF) (Full Analysis Set)
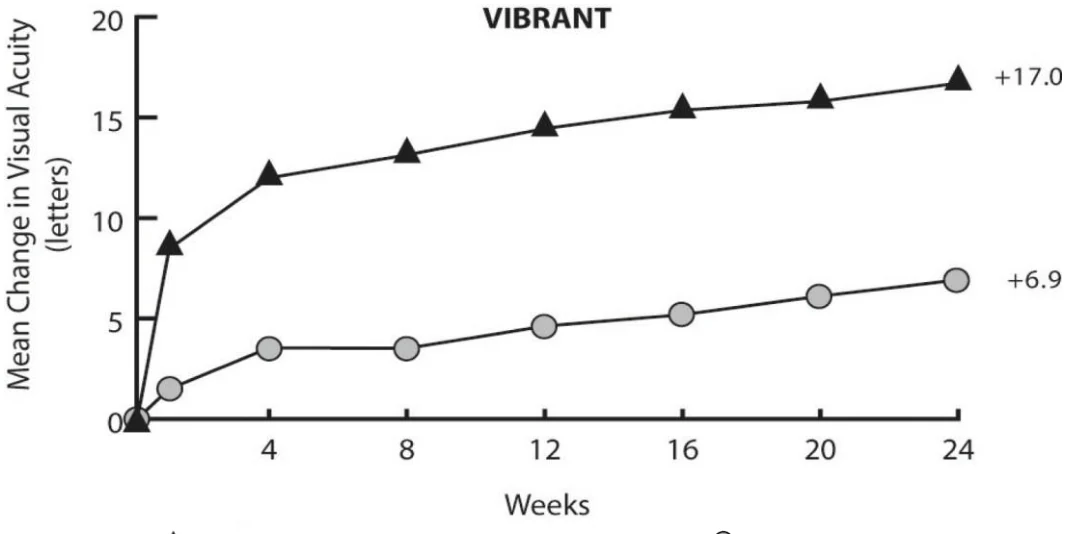

aflibercept injection 2 mg Q4 weeks
Control Group
Treatment of DME
VIVIDDME and VISTADME Studies
The safety and efficacy of aflibercept injection were assessed in two randomized, multi-center, double-blind, active- controlled studies in patients with DME (VIVIDDME and VISTADME). The VIVIDDME study was conducted in Europe, Australia and Japan and the VISTADME study was conducted in the US. A total of 862 randomized and treated patients were evaluable for efficacy. Of those, 576 were randomized to the aflibercept injection groups in the two studies (see Table 17). In each study, patients were randomly assigned in a 1:1:1 ratio to 1 of 3 treatment regimens:
- 1) Aflibercept injection administered 2 mg every 8 weeks following 5 initial monthly injections (aflibercept injection 2Q8);
- 2) Aflibercept injection administered 2 mg every 4 weeks (aflibercept injection 2Q4); and
- 3) Macular laser photocoagulation (active control laser).
Beginning at week 24, patients meeting a pre-specified threshold of vision loss were eligible to receive additional treatment: patients in the aflibercept injection groups could receive laser and patients in the control (laser) group could receive aflibercept injection.
In both studies, the primary efficacy endpoint was the mean change from baseline in BCVA at Week 52 as measured by ETDRS letter score. The key secondary efficacy endpoints included proportion of patients who gained ≥10 or ≥15 ETDRS letters from baseline to week 52, the proportion of patients who achieved a ≥2 step improvement in the ETDRS Diabetic Retinopathy Severity Score (DRSS), and the mean change from baseline in CRT.
Patient ages ranged from 23 to 87 years with a mean of 63 years. In the DME Phase III studies, approximately 47% (268/576) of the patients randomized to treatment with aflibercept injection were 65 years of age or older, and approximately 9% (52/576) were 75 years of age or older.
Overall, half of the patients in the VIVIDDME and VISTADME studies had poorly controlled diabetes at baseline.
In the VIVIDDME study, the mean numbers of injections in the 2Q8 and 2Q4 groups were 8.7 and 12.2, respectively, and the mean numbers of laser treatments in the laser group was 2.1. In the VISTADME study, the mean numbers of injections in the 2Q8 and 2Q4 groups were 8.4 and 11.8, respectively, and the mean number of laser treatments in the laser group was 2.7.
In the VIVIDDME and VISTADME studies, 36 (8.9%) and 197 (42.9%) of the patients received prior anti- VEGF therapy, respectively, with a 3-month or longer washout period. Treatment effects in the subgroup of patients who had previously been treated with a VEGF inhibitor prior to study participation were similar to those seen in patients who were VEGF inhibitor naïve prior to study participation.
More than 80% of patients in all treatment groups in VIVIDDME and VISTADME had a DRSS at baseline of mild to severe non-proliferative diabetic retinopathy.
In the VISTADME study, >60% of patients in the aflibercept injection groups received bilateral aflibercept injection injections.
Table 17: Summary of Patient Demographics for Clinical Trials in DME
Study#
Trial Design
Dosage, route of administration, and duration
Study Subjects (n)
Mean Age (Range)
Sex
VIVIDDME
Intravitreal injection
aflibercept injection administered at 2 mg every 8 weeks following 5 initial monthly injections (aflibercept injection
2Q8),
aflibercept injection administered at 2 mg every 4 weeks (aflibercept injection 2Q4)
aflibercept injection 2Q8: n= 135
aflibercept injection 2Q4: n= 136
aflibercept injection laser: n= 135
63.6
(32-84 years)
Male: 61.8%
Female: 38.2% randomized, multi-center, double-blind, active- controlled
Laser photocoagulation (with sham intraocular injections)
100-week study
VISTADME
aflibercept injection 2Q8: n=154
aflibercept injection 2Q4: n= 156
aflibercept injection laser: n= 156
62.2
(23-87 years)
Male: 54.5%
Female: 45.5%
In both VIVIDDME and VISTADME studies, the 52-week results demonstrate statistically significant superiority of aflibercept injection 2Q8 and 2Q4 treatment groups as compared to laser control on both primary and secondary endpoints.
A rapid improvement in BCVA was observed as early as one week in the aflibercept injection -treated patients. In the VIVIDDME study, the mean change in BCVA after the initial 4-week period was a gain of +5.4 (2Q8), +5.7 (2Q4) and +0.9 (laser) letters. In the VISTADME study, the mean change in BCVA after the initial 4 week period was a gain of +6.6 (2Q8), +7.0 (2Q4) and +2.6 (laser) letters.
Detailed results from the analysis of the VIVIDDME and VISTADME studies at week 52 are shown in Table 18 and Figure 13 below.
Table 18: Efficacy Outcomes at Week 52 (Full Analysis Set with LOCF) in VIVIDDME and VISTADME Studiese
Efficacy Outcomes
VIVIDDME
VISTADME
52 Weeks
52 Weeks aflibercept injection 2Q8a
(n = 135)
afliberce pt injection 2Q4
(n = 136)
Control
(laser) (n = 132)
aflibercept injection 2Q8a
(n = 151)
aflibercept injection
2Q4 (n = 154)
Control
(laser) (n = 154)
Mean change in BCVA as
measured by ETDRS letter score from Baseline (SD)
10.7
(9.3)
10.5
(9.6)
1.2
(10.7)
10.7
(8.2)
12.5
(9.5)
0.2
(12.5)
Difference in LS meanb,c (97.5% CI)
p-value
9.1
(6.3, 11.8)
p < 0.0001
9.3
(6.5, 12.0)
p < 0.0001
10.5
(7.7, 13.2)
p < 0.0001
12.2
(9.4, 15.0)
p < 0.0001
Proportion of patients who
gained at least 15 letters in BCVA from Baseline
33.3%
32.4%
9.1%
31.1%
41.6%
7.8%
Adjusted Differencec, d
(97.5% CI)
p-value
24.2%
(13.5, 34.9)
p < 0.0001
23.3%
(12.6, 33.9)
p < 0.0001
23.3%
(13.5, 33.1)
p < 0.0001
34.2%
(24.1, 44.4)
p < 0.0001
- a After treatment initiation with 5 monthly injections
- b LS mean and CI based on an ANCOVA model with baseline BCVA measurement as a covariate and a factor for treatment group. Additionally, region (Europe/Australia vs. Japan) had been included as a factor for VIVIDDME, and history of MI and/or CVA as a factor for VISTADME.
- c Difference is aflibercept injection group minus active control (laser) group
- d Difference with confidence interval (CI) and statistical test is calculated using Mantel -Haenszel weighting scheme adjusted by region (Europe/Australia vs. Japan) for VIVIDDME and medical history of MI or CVA for VISTADME
- e For both studies, VIVIDDME and VISTADME, beginning at week 24, if criteria were met, patients in the control (laser) arm may have received aflibercept injection injections (2Q8) and patients randomized to the aflibercept injection arm may have received laser treatment.
BCVA: Best Corrected Visual Acuity; ETDRS: Early Treatment Diabetic Retinopathy Study; LOCF: Last Observation Carried Forward; SD: Standard deviation; LS: Least square means derived from ANCOVA; CI: Confidence interval; MI: Myocardial Infarction; CVA: cerebrovascular accident
52-Week Analysis
In the VIVIDDME study, at Week 52, the proportion of patients gaining ≥10 letters in BCVA from baseline was 53.3%, 54.4% and 25.8% for the groups receiving aflibercept injection 2Q8, aflibercept injection 2Q4, and control (laser), respectively. In the VISTADME study, the corresponding results at Week 52 were 58.3%, 64.9% and 19.5%, respectively.
The proportion of patients with improvement of ≥2 steps on the ETDRS DRSS from baseline was 27.7%, 33.3% and 7.5% for the groups receiving aflibercept injection 2Q8, aflibercept injection 2Q4, and control (laser), respectively, at Week 52 in the VIVIDDME study. In the VISTADME study, the corresponding results at Week 52 were 29.1%, 33.8% and 14.3%, respectively.
100-Week Analysis
There were 82% of patients who completed the 100 weeks study. The mean number of injections for aflibercept injection treatment group was 21.9 injections (aflibercept injection 2Q4) and 13.6 injections (aflibercept injection 2Q8). Due to the study design, beginning at week 24, 5.2% and 9.8% of patients received 1.8 and 1.5 additional laser treatments in aflibercept injection 2Q4 and aflibercept injection 2Q8, respectively; 38.0% of patients in the laser group received 8.8 additional aflibercept injection injections (2Q8) on average.
The mean change from baseline in BCVA was +9.4 letters in the aflibercept injection 2Q8 group vs. +11.4 letters in the aflibercept injection 2Q4 group vs. +0.7 letters in the control (laser) group in VIVIDDME, and +11.1 letters vs. +11.5 letters vs. +0.9 letters in VISTADME. The proportion of patients who gained at least 15 letters of vision from baseline was 31.1% in the aflibercept injection 2Q8 treatment group vs. 38.2% in the aflibercept injection 2Q4 treatment group vs. 12.1% in the control (laser) group in VIVIDDME, and 33.1% vs. 38.3% vs. 13.0% in VISTADME.
In the VIVIDDME study, at Week 100, the proportion of patients gaining ≥10 letters in BCVA from baseline was 49.6%, 58.1% and 25.0% for the groups receiving aflibercept injection 2Q8, aflibercept injection 2Q4, and control (laser), respectively. In the VISTADME study, the corresponding results at Week 100 were 59.6%, 63.6% and 27.9%, respectively.
At Week 100 in the VIVIDDME study, the proportion of patients with improvement of ≥2 steps on the ETDRS DRSS from baseline was 32.6%, 29.3% and 8.2% for the groups receiving aflibercept 2Q8, aflibercept injection 2Q4, and control (laser), respectively. In the VISTADME study, the corresponding results at Week 100 were 37.1%, 37.0% and 15.6%, respectively.
Figure 13: Mean change in BCVA as Measured ETDRS Letter Score from Baseline to Week 52 in VIVIDDME and VISTADME Studies
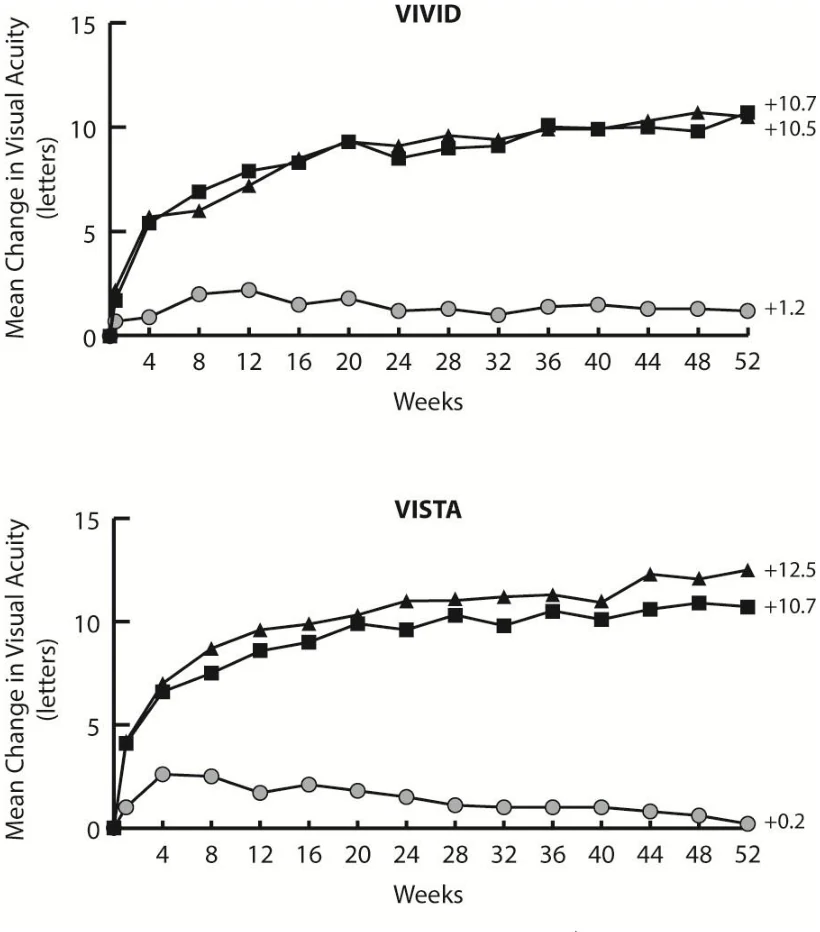


aflibercept injection 2mg Q8 weeks
aflibercept injection 2mg Q4 weeks

Active Control (laser)
Treatment effects in evaluable subgroups (e.g., age, gender, race, baseline HbA1c, baseline visual acuity, prior anti-VEGF therapy) in each study and in the combined analysis were consistent with the results in the overall populations.
A patient-level-data comparison using propensity score matching (PSM) methodology was performed on data from three independent studies. Based on PSM, subsets of 179 matched patients were identified from pooled VIVIDDME and VISTADME (utilizing a fixed aflibercept dosing regimen) and Protocol T (utilizing a flexible dosing regimen based on strict OCT and vision re-treatment criteria). The PSM analysis showed that mean change in BCVA from baseline at week 52 was 10.9 letters in the 2 mg aflibercept 2Q8 fixed dosing regimen (VIVIDDME and VISTADME) and 13.7 letters in the 2 mg aflibercept flexible dosing regimen (Protocol T).
VIOLET Study
VIOLET was a 100-week multicenter, randomized, open-label, active controlled study designed to compare three different dosing regimens of aflibercept injection 2 mg for the treatment of DME in 463 patients after at least one year of treatment at fixed intervals, where treatment was initiated with 5 consecutive monthly doses followed by dosing every 2 months. Eligible patients were randomized (1:1:1 ratio) to aflibercept injection 2 mg dosed according to a treat-and-extend regimen (2T&E), where injections intervals were kept at a minimum of 8 weeks and gradually extended based on clinical and anatomical outcomes , aflibercept injection 2 mg dosed as needed (2PRN), where patients were observed every 4 weeks and injected when needed based on clinical and anatomical outcomes, or aflibercept injection 2 mg dosed every 8 weeks (2Q8) for the second and third year of treatment. In the 2T&E arm, modifications of the injection intervals were at the investigator’s discretion, based on visual and anatomic outcomes; increments of 2 weeks were typically recommended.
The primary efficacy endpoint was the change in BCVA from study baseline to week 52.
The change in BCVA from study baseline to week 52 was 0.5 ± 6.7 letters in the 2T&E group and 1.7 ±
6.8 letters in the 2PRN group compared to 0.4 ± 6.7 letters in the 2Q8 group. The changes in BCVA from study baseline to week 100 were -0.1 ± 9.1 letters in the 2T&E group and 1.8 ± 9.0 letters in the 2PRN group compared to 0.1 ± 7.2 letters in the 2Q8 group. The mean number of injections over 100 weeks were 10.0, 11.5 and 12.3 for 2T&E, 2PRN and 2Q8, respectively.
Treatment of myopic CNV
The safety and efficacy of aflibercept injection in subjects with choroidal neovascularization secondary to pathologic myopia (myopic CNV) were assessed in a randomized, parallel-group, multi-center, double-masked, sham-controlled Phase 3 study conducted in Japan, Hong Kong, Singapore, Taiwan and South Korea (see Table 19).
122 subjects (91 aflibercept injection and 31 Sham) were randomized 3:1 to the aflibercept injection or Sham groups. Patients randomized to the aflibercept injection group received 1 injection at baseline. Additional injections were performed in case of CNV persistence or recurrence at monthly visits through week 44. Patients randomized to the Sham group received a sham injection at baseline. Although subjects randomized to the Sham group underwent assessment of re-treatment criteria for masking purposes, an injection of active drug was not given regardless of the outcome of this assessment. Patients were evaluated at 4-week intervals for BCVA using the ETDRS chart at 4 meters. At week 24, after assessment of the primary efficacy end point, patients in the Sham group received a mandatory aflibercept injection followed by aflibercept injection (if disease persisted/recurred) or sham injection every 4 weeks.
A total of 14 subjects discontinued the study treatment prior to Week 24; 8 (8.8%) in the aflibercept injection group and 6 (19.4%) in the Sham group. Between Week 24 and Week 48, treatment was discontinued in 5 subjects (5.5%) in the aflibercept injection group and in one subject (3.2%) in the Sham+ aflibercept injection group.
The majority of patients were female (76.0%) and Japanese (74.4%), and the mean age was 58.2 years (range 27-83). Most patients had classic CNV (98.3%) and a disease duration of <2 months (80.2%). The mean axial length was 28.7 (SD 1.6) mm. Approximately 97% of patients had a baseline BCVA of
>20/200 (≥35 letters) and, in both groups, the mean baseline BCVA letter score was approximately 56.5 letters.
Overall, patients in the aflibercept injection group received a median of 3.0 (range 1-12) injections over the study period of 48 weeks.
The primary efficacy endpoint was the mean change in visual acuity at week 24 compared to baseline.
The confirmatory secondary efficacy endpoint was the proportion of patients who gained at least 15 letters in BCVA at week 24 compared to baseline.
Table 19 – Summary of Patient Demographics for Clinical Trial in myopic CNV
Study#
Trial Design
Dosage, route of administration, and duration
Study Subjects (n)
Mean Age (Range)
Sex
MYRROR
randomized, parallel- group, multi- center, double- masked, sham- controlled
Intravitreal injection
- aflibercept injection 2 mg administered on day 1; then aflibercept injection 2 mg or sham administered depending on whether study re-treatment criteria were met
- Sham injections every 4 weeks up to week 20, aflibercept injection 2 mg at week 24; then aflibercept injection 2 mg or sham administered depending on whether study re- treatment criteria were met
48-week study
aflibercept injection: n= 91
Sham: n= 31
58.2 (27-83 years)
Male: 24.6%
Female: 75.4%
In the MYRROR study, the 24-weeks results demonstrated statistical superiority of aflibercept injection as compared to sham injections on both primary and confirmatory secondary endpoints (Table 20). In the aflibercept injection group, the mean change in BCVA was maintained until Week 48 (Figure 14).
Table 20: Efficacy Outcomes at Week 24 (primary analysis) in MYRROR study (Full Analysis Set with LOCF)
Efficacy Outcomes
24 Weeks
aflibercept injection 2mg
(N = 90)
Sham
(N = 31)
Mean change in BCVA letter score as measured by ETDRS from baseline (SD)
12.1 (8.3)
-2.0 (9.7)
Difference in LS mean a,b
14.1
(95% CI)
(10.8, 17.4)
p-valued
p < 0.0001
Proportion of patients who gained at least 15 letters in
BCVA from baseline
38.9%
9.7%
Weighted difference a,c
29.2%
(95% CI)
(14.4, 44.0)
p-valued
p = 0.0001
- a Difference is aflibercept injection 2mg minus sham at Week 24.
- b
LS mean difference and 95% CI based on an ANCOVA model with treatment group and country (country designations) as
- fixed effects, and baseline BCVA as covariant.
- c Difference and 95% CI are calculated using Cochran-Mantel-Haenszel (CMH) test adjusted for country (country designations)
- d To control the type I error rate for multiple testing, the confirmatory secondary endpoint was only tested if the null hypothesis for the primary endpoint could be rejected
LOCF: Last Observation Carried Forward; BCVA: Best Corrected Visual Acuity; ETDRS: Early Treatment Diabetic Retinopathy Study; SD: Standard Deviation; LS mean: Least square means; CI: Confidence Interval
At week 48, the mean improvement from baseline in BCVA was +13.5 letters for the group receiving aflibercept injection and +3.9 letters for the Sham+ aflibercept injection group. At week 48, the proportion of patients gaining at least 15 letters in BCVA from baseline was 50.0% for the group receiving aflibercept injection and 29.0% for the group initially receiving sham injections.
Figure 14: Mean change from baseline to week 48 in visual acuity by treatment group for the MYRROR study (Full Analysis Set, LOCF)
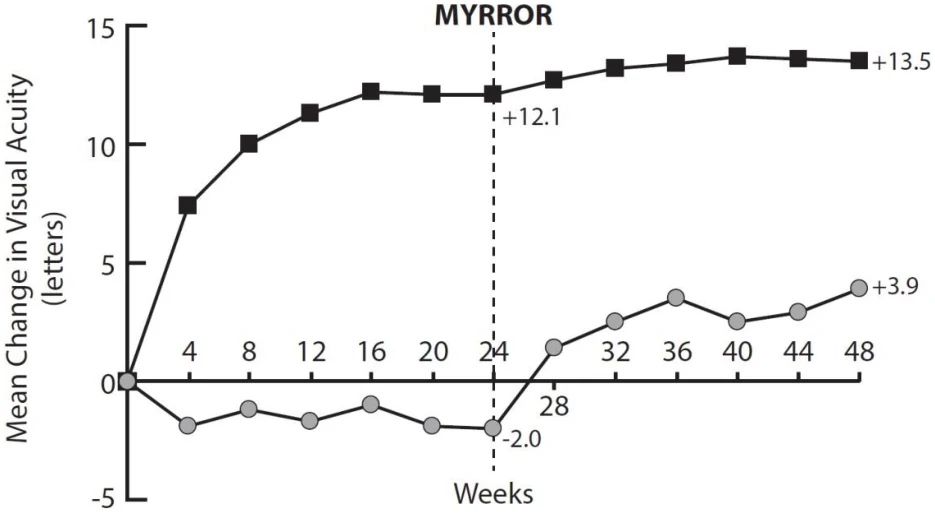


aflibercept injection 2mg
Control Group
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General toxicology: The toxicology profile of aflibercept was assessed in several repeated dose studies in monkeys. In brief, the following pivotal studies were performed:
- 1) a 9-week or 6-month repeat-dose intravitreal study with 12 weeks of recovery, where monkeys were administered aflibercept doses of 0, 4, or 7 mg/eye bilaterally every 4 weeks. Erosions and ulcerations of the respiratory epithelium in nasal turbinates in monkeys treated with aflibercept at all doses. A No Observed Adverse Effect Level (NOAEL) was not identified. At the Lowest Observed Adverse Effect Level (LOAEL) of 4 mg/eye in monkeys, the systemic exposure was 637- and 1143-fold higher based on Cmax and AUC when compared to corresponding values observed in adult patients with neovascular AMD given a single unilateral intravitreal dose of 2 mg. Systemic toxicity was not fully assessed in this study. .
- 2) an 8-month repeat-dose intravitreal study with 4-months of recovery, where monkeys were administered aflibercept bilaterally every 4 weeks at doses of 0, 0.5, 2, or 4 mg/eye. Systemic effects were limited to erosions and ulcerations of the respiratory epithelium in nasal turbinates in monkeys treated with aflibercept at doses of 2 or 4 mg/eye. At the NOAEL of 0.5 mg/eye in monkeys, the systemic exposure was 42- and 56-fold higher based on Cmax and AUC when compared to corresponding values observed in adult patients with neovascular AMD given a single unilateral intravitreal dose of 2 mg.
- 3) a 6-month repeat-dose intravenous study with 5-months of recovery, where monkeys were administered aflibercept intravenously once weekly for 15 weeks; then once every 2 weeks for 12 weeks at doses of 0, 3, 10, or 30 mg/kg. No NOAEL was identified. At the Lowest Observed Adverse Effect Level (LOAEL) of 3 mg/eye in monkeys, the systemic exposure was 1546-fold higher based on AUC when compared to corresponding values observed in adult patients with neovascular AMD given a single unilateral intravitreal dose of 2 mg. Under these conditions and high systemic exposure, aflibercept can cause system-wide organ effects. Monkeys given aflibercept had reduced body weight and developed erosion/ulceration of the nasal turbinate epithelia leading to hemorrhage. Anemia related to bleeding as a result of lesions in the nasal cavity resulted in the premature euthanization of one monkey in the low-dose group. Monkeys administered doses ≥ 3 mg/kg developed deformity or abnormal bone growth of spinal vertebrae or bones of the limbs, along with muscular atrophy, and joint degeneration. Monkeys also developed renal inflammation and glomerulopathy accompanied by proteinuria and albuminuria. At doses ≥ 10 mg/kg, monkeys showed vascular degeneration/proliferation in tissues of the GI tract, heart, joints, and nervous system, as well as liver inflammation and necrosis.
Carcinogenicity: No studies have been conducted on the carcinogenic potential of aflibercept.
Genotoxicity No studies have been conducted on the mutagenic potential of aflibercept.
Reproductive and developmental toxicology: Effects on male and female fertility were assessed as part of a 6-month repeat-dose intravenous study with 5-months of recovery, where monkeys were administered aflibercept intravenously once weekly for 15 weeks; then once every 2 weeks for 12 weeks at doses of 0, 3, 10, or 30 mg/kg. Absent or irregular menses associated with alterations in female reproductive hormone levels and changes in sperm morphology and motility were observed at all dose levels. In addition, females showed decreased ovarian and uterine weight accompanied by compromised luteal development and reduction of maturing follicles. These changes correlated with uterine and vaginal atrophy. A NOAEL was not identified.
Intravenous administration of the lowest dose of aflibercept assessed in monkeys (3 mg/kg) resulted in systemic exposure (AUC) that was approximately 1500-fold higher than the exposure observed in adult patients with neovascular AMD given a single intravitreal dose of 2 mg. All changes were reversible within 20 weeks after cessation of treatment.
Aflibercept produced embryo-fetal toxicity in an embryo-fetal development study in pregnant rabbits with intravenous administration (3 to 60 mg/kg on gestation Days 6, 9, 12, 15, and 18). The maternal NOAEL was at the dose of 3 mg/kg. At this dose, the systemic exposures based on Cmax and AUC for free aflibercept were approximately 2000- and 600-fold higher, respectively, when compared to corresponding values observed in adult patients with neovascular AMD given a single unilateral intravitreal dose of 2 mg.
In an embryo-fetal development study in pregnant rabbits, aflibercept produced embryo-fetal toxicity when administered every three days during organogenesis to pregnant rabbits at intravenous doses ≥3 mg per kg (3 to 60 mg/kg), or every six days at subcutaneous doses ≥0.1 mg per kg. Adverse embryo- fetal effects included increased incidences of post implantation loss and fetal malformations, including anasarca, umbilical hernia, diaphragmatic hernia, gastroschisis, cleft palate, ectrodactyly, intestinal atresia, spina bifida, encephalomeningocele, heart and major vessel defects, and skeletal malformations (fused vertebrae, sternebrae, and ribs; supernumerary vertebral arches and ribs; and incomplete ossification). The maternal No Observed Adverse Effect Level (NOAEL) in these studies was 3 mg per kg. Aflibercept produced fetal malformations at all doses assessed in rabbits and the fetal NOAEL was less than 0.1 mg per kg. Administration of the lowest dose assessed in rabbits (0.1 mg per kg) resulted in systemic exposure (AUC) that was approximately 10 times the systemic exposure observed in adult patients with neovascular AMD given a single unilateral intravitreal dose of 2 mg. A pre- and postnatal development study was not conducted with aflibercept.
Juvenile toxicity: No juvenile toxicity studies have been conducted with aflibercept.
17 Supporting Product Monographs
- 1. EYLEA® (2 mg / 0.5 mL), control no. 278211, product monograph, Bayer Inc. (2025-05-02)