


Product Monograph - Apo-Ciclesonide
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Nonmedicinal Ingredients |
| Nasal | Spray 50 mcg/spray | Edetate disodium dihydrate, hypromellose, microcrystalline cellulose and carboxymethylcellulose sodium, potassium sorbate and purified water; hydrochloric acid may be added to adjust the pH to a target 4.5 |
INDICATIONS AND CLINICAL USE
APO-CICLESONIDE (ciclesonide nasal spray) is indicated for:
- the treatment of seasonal allergic rhinitis, including hayfever, and perennial allergic rhinitis in adults and adolescents 12 years of age and older.
Geriatrics (> 65 years of age)
A total of 31 patients 65 years of age and older (age range 65 to 75 years) have been treated with ciclesonide nasal spray 200 mcg/day for up to 1 year. The adverse reactions reported in this population were similar in type and incidence to those reported by younger patients, but greater sensitivity of some older individuals cannot be ruled out. Based on available data for ciclesonide nasal spray, no adjustment of dosage of APO-CICLESONIDE in geriatric patients is warranted.
Pediatrics
APO-CICLESONIDE is not presently approved for use in patients younger than 12 years of age. A total of 91 patients 12-17 years of age were treated with ciclesonide nasal spray for up to one year. No differences in the rate or incidence of adverse events were observed.
CONTRAINDICATIONS
- APO-CICLESONIDE is contraindicated in patients with a hypersensitivity to any of the ingredients. For a complete listing see DOSAGE FORMS, COMPOSITION AND PACKAGING section of the Product Monograph.
- APO-CICLESONIDE should be used with caution, if at all, in patients with active or quiescent tuberculosis infections of the respiratory tract.
WARNINGS AND PRECAUTIONS
Carcinogenesis and Mutagenesis
See TOXICOLOGY.
Ear/Nose/Throat
As with other corticosteroids, rare instances of nasal septal perforation have been reported post-market in patients following the intranasal application of ciclesonide (See ADVERSE REACTIONS, Post-Market Adverse Drug Reactions).
Because of the inhibitory effect of corticosteroids on wound healing, patients who have experienced recent nasal septal ulcers, nasal surgery, or nasal trauma should not use a nasal corticosteroid until healing has occurred.
Immune
Patients who are on drugs that suppress the immune system are more susceptible to infections than healthy individuals. Chickenpox and measles, for example, can have a more serious or even fatal course in children or adults on corticosteroids. In children or adults who have not had these diseases, particular care should be taken to avoid exposure. How the dose, route, and duration of corticosteroid administration affects the risk of developing a disseminated infection is not known. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known. If exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) may be indicated. If exposed to measles, prophylaxis with pooled intramuscular immunoglobulin (IG) may be indicated. If chickenpox develops, treatment with antiviral agents may be considered.
Infection
In clinical studies with corticosteroids administered intranasally, the development of localized infections of the nose and pharynx with Candida albicans have been reported only rarely.
When such an infection develops, it may require treatment with appropriate local therapy and discontinuation of treatment with the intranasal steroid. Therefore, patients using intranasal corticosteroids over several months or longer should be examined periodically for evidence of Candida infection or other signs of adverse effects on the nasal mucosa.
Ciclesonide nasal spray should be used with caution, if at all, in patients with untreated local or systemic fungal or bacterial infections; systemic viral or parasitic infections; or ocular herpes simplex because of the potential for worsening of these infections.
Systemic Effects
Rarely, immediate hypersensitivity reactions or contact dermatitis may occur after the administration of intranasal corticosteroids. Patients with a known hypersensitivity reaction to other corticosteroid preparations should use caution when using ciclesonide nasal spray since cross-reactivity to other corticosteroids including ciclesonide may occur. Rare instances of wheezing, nasal septum perforation, cataracts, glaucoma, and increased intraocular pressure have been reported following the intranasal application of corticosteroids. The risk of glaucoma was evaluated by assessments of intraocular pressure in 390 adolescent or adult patients receiving treatment with ciclesonide nasal spray 200 mcg daily for up to 52 weeks. In this trial, no significant differences in intraocular pressure changes were observed between ciclesonide nasal spray and placebo-treated patients. Additionally, no significant differences between ciclesonide nasal spray 200 mcg and placebo-treated patients were noted during the 52-week study of 577 patients in which thorough ophthalmologic assessments were performed including evaluation of cataract formation using slit lamp examinations.
Although systemic effects have been minimal with recommended doses of ciclesonide nasal spray, any such effect is likely to be dose dependent. Therefore, larger than recommended doses of ciclesonide nasal spray should be avoided. When used at excessive doses, systemic corticosteroid effects such as hypercorticism and adrenal suppression may occur. If such changes occur, the dosage of ciclesonide nasal spray should be discontinued slowly, consistent with accepted procedures for discontinuing oral corticosteroid therapy.
Physicians should closely follow the growth of children and adolescents taking corticosteroids by any route, and weigh the benefits of corticosteroid therapy against the possibility of growth suppression if growth appears slowed. To minimize the systemic effects of intranasal corticosteroids each patient should be titrated to his/her lowest effective dose.
Systemic Steroid Replacement by a Topical Steroid
The replacement of a systemic corticosteroid with a topical corticosteroid can be accompanied by signs of adrenal insufficiency. In addition, some patients may experience symptoms of corticosteroid withdrawal, e.g., joint and/or muscular pain, lassitude, and depression. Patients previously treated for prolonged periods with systemic corticosteroids and transferred to topical corticosteroids should be carefully monitored for acute adrenal insufficiency in response to stress. In those patients who have asthma or other clinical conditions requiring long-term systemic corticosteroid treatment, rapid decreases in systemic corticosteroid dosages may cause a severe exacerbation of their symptoms.
Special Populations
Pregnant Women: There are no clinical studies with ciclesonide nasal spray in pregnant women. As with other corticosteroids, ciclesonide should only be used during pregnancy when the potential benefit to the mother justifies the potential risk to the mother, fetus or infant. Infants born to mothers who received corticosteroids during pregnancy should be observed carefully for hypoadrenalism.
Nursing Women: It is unknown if ciclesonide is excreted in human milk. As with other corticosteroids, ciclesonide nasal spray should only be used in nursing women when the potential benefit to the mother justifies the potential risk to the mother and/or infant.
Pediatrics: Ciclesonide nasal spray is not presently approved for use in patients younger than 12 years of age. A total of 91 patients 12-17 years of age were treated with ciclesonide nasal spray for up to one year. No differences in the rate or incidence of adverse events were observed.
Geriatrics (> 65 years of age): A total of 31 patients above 65 years of age (age range 65 to 75 years) have been treated with ciclesonide nasal spray 200 mcg/day for up to 1 year. The adverse reactions reported in this population were similar in type and incidence to those reported by younger patients, but greater sensitivity of some older individuals cannot be ruled out. Based on available data for ciclesonide nasal spray, no adjustment of dosage of ciclesonide nasal spray in geriatric patients is warranted.
Monitoring and Laboratory Tests
As with any long-term treatment, patients using ciclesonide nasal spray over several months or longer should be examined periodically for possible changes in the nasal mucosa.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
In controlled clinical studies, a total of 2013 patients ages 12 years and older received treatment with ciclesonide nasal spray. In studies of 2 to 6-weeks duration, 677 patients were treated with ciclesonide nasal spray 200 mcg daily, and in a study of up to one year in duration, 441 patients were treated with ciclesonide nasal spray 200 mcg daily. The overall incidence of adverse events for patients treated with ciclesonide nasal spray was comparable to that in patients treated with the placebo. Approximately 2% of patients treated with ciclesonide nasal spray
200 mcg in clinical trials discontinued because of adverse events; this rate was similar for patients treated with placebo.
The table below displays adverse events, assessed as likely or definitely related to treatment by the investigator, that occurred with an incidence of 1% or greater in clinical trials of 2 to 6-weeks in duration.
Table 1: Common Adverse Reactions1 (1-10%) in Controlled Clinical Trials 2 to 6-weeks in Duration in Patients 12 Years of Age and Older with Seasonal or Perennial Allergic Rhinitis
| Adverse Reaction | Ciclesonide Nasal Spray 200 mcg n=677 (%) | Placebo n=674 (%) |
| Epistaxis2 | 2.7 | 2.1 |
| Nasal Passage Irritation3 | 2.4 | 2.2 |
| Headache | 1.3 | 0.7 |
1 assessed as likely or definitely related to the treatment by investigator
2 epistaxis (e.g. frank bleeding, blood-tinged mucus and blood flecks)
3 nasal passage irritation includes nasal discomfort
In a 52-week long-term safety trial that included 663 adolescent and adult patients (227 males and 436 females) with perennial allergic rhinitis, the adverse event profile over the treatment period was similar to the adverse event profile in trials of shorter duration. Adverse events considered likely or definitely related to ciclesonide nasal spray that were reported at an incidence of 1% or greater are presented in Table 2. No patient experienced a nasal septal perforation or nasal ulcer during long-term use of ciclesonide nasal spray nor was there any evidence of HPA-axis suppression in this study.
Table 2: Common Adverse Reactions1 (1-10%) in a 52-week Study in Adult and Adolescent Patients with Perennial Allergic Rhinitis
| Adverse Reaction | Ciclesonide Nasal Spray 200 mcg n=441 (%) | Placebo n=222 (%) |
| Epistaxis2 | 8.4 | 6.3 |
| Nasal Passage Irritation3 | 4.3 | 3.6 |
| Headache | 1.6 | 0.5 |
1 assessed as likely or definitely related to the treatment by investigator
2 epistaxis (e.g. frank bleeding, blood-tinged mucus and blood flecks)
3 nasal passage irritation includes nasal discomfort
The following less common adverse reactions (assessed as possibly related to treatment by the investigator) were reported in controlled clinical trials 2 to 52 weeks in duration in patients 12 years of age and older with Seasonal Allergic or Perennial Allergic Rhinitis treated with ciclesonide nasal spray 200 mcg:
Less Common Clinical Trial Adverse Drug Reactions (≥0.1% to <1%)
Gastrointestinal: dry mouth (0.2%), dyspepsia (0.2%)
Infections: candidiasis (0.2%), rhinitis (0.2%),
Investigations: laboratory test abnormal NOS (0.2%), white blood cell count increased (0.3%),
Nervous System: dysgeusia (0.2%)
Respiratory, Thoracic and Mediastinal: nasal dryness (0.4%), pharyngolaryngeal pain (0.4%), rhinorrhoea* (0.3%), nasal septum disorder (0.2%), throat irritation* (0.2%)
*occurred at rates ≤ placebo
Other Clinical Trial Adverse Drug Reactions
In all allergic rhinitis clinical trials, a total of 3954 patients received treatment with ciclesonide nasal spray, and 2544 received treatment with ciclesonide nasal spray 200 mcg. The following common treatment-emergent adverse events were reported with ciclesonide nasal spray
200 mcg:
Respiratory, Thoracic and Mediastinal: nasopharyngitis (4.6%), sinusitis (2.3%)
Post-Market Adverse Drug Reactions
The following adverse events were reported in post-marketing use of ciclesonide and causal relation to ciclesonide treatment could not be ruled out. As the events were reported spontaneously, no exact incidences can be provided:
Respiratory, Thoracic and Mediastinal: nasal septum perforation
Special Populations
The incidence of adverse events did not differ appreciably based on age, gender or race.
Abnormal Hematologic and Clinical Chemistry Findings
Examination of the percentage of patients with normal values at baseline and values above or below the normal range at the end of treatment did not demonstrate any trends with respect to changes in hematology and biochemistry values, see Less Common Clinical Trial Adverse Drug Reactions above.
DRUG INTERACTIONS
Overview
In vitro data indicate that cytochrome P 450 3A4 is the major enzyme involved in the metabolism of the active metabolite of des-ciclesonide (M1) in man.
Based on in vitro studies in human liver microsomes, the active metabolite des-ciclesonide (M1) did not significantly inhibit or induce the metabolism of other drugs metabolized by cytochrome P 450 enzymes. The inhibitory potential of ciclesonide on cytochrome P 450 isoenzymes has not been studied. Based on in vitro human hepatocyte studies, ciclesonide and des-ciclesonide (M1) had no significant effect on the induction of major cytochrome P 450 isoenzymes. In vitro studies also demonstrated that the plasma protein binding of des-ciclesonide was not affected by warfarin or salicylic acid, indicating that protein binding-based drug interactions are unlikely.
The serum levels of ciclesonide and des-ciclesonide, its active metabolite M1, are negligible following administration of ciclesonide nasal spray. Therefore, the potential for clinically relevant drug-drug interactions is very low. However, co-administration with potent inhibitors of the cytochrome P 450 3A4 system (e.g. protease inhibitors for the treatment of HIV infections such as, ritonavir or nelfinavir) should be considered with caution because there might be an increase in systemic drug levels of the active metabolite M1, des-ciclesonide.
Drug-Drug Interactions
A drug interaction study with orally inhaled ciclesonide and oral erythromycin, a substrate and weak inhibitor of cytochrome P 450 3A4, had no relevant effect on the pharmacokinetics of either M1 or erythromycin. In a drug interaction study at steady state with orally inhaled ciclesonide and oral ketoconazole, a potent cytochrome P 450 3A4 inhibitor, the exposure of the active metabolite M1 increased approximately 3.5-fold, while levels of ciclesonide remained unchanged. Due to the low systemic exposure of intranasal ciclesonide relative to orally inhaled ciclesonide, clinically relevant drug interactions with ciclesonide nasal spray, except with very potent inhibitors of the cytochrome P450 3A4 system, are not expected.
Drug-Food Interactions
Interactions with food have not been established. Drug-food interactions are unlikely for intranasal corticosteroids.
Drug-Herb Interactions
Interactions with herbal products have not been established.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established. Drug-laboratory interactions are unlikely for intranasal corticosteroids.
DOSAGE AND ADMINISTRATION
Dosing Considerations
The therapeutic effects of corticosteroids, unlike those of decongestants, are not immediate. Since the effect of ciclesonide nasal spray depends on its regular use, patients should be instructed to use the nasal inhalation at regular intervals and not, as with other nasal sprays, as they feel necessary.
Recommended Dose and Dosage Adjustment
Adults and Adolescents (12 Years of Age and Older): The recommended dose of APO-CICLESONIDE is 200 mcg per day administered as 2 sprays (50 mcg/spray) in each nostril once daily. The maximum total daily dosage should not exceed 2 sprays in each nostril (200 mcg/day).
Missed Dose
It is very important that APO-CICLESONIDE is used regularly. If a dose is missed, the next dose should be taken when it is due and patients should not exceed the prescribed daily dosage.
Administration
Prior to initial use, APO-CICLESONIDE must be shaken gently and then the pump must be primed by actuating 8 times. If not used for 4 or more consecutive days, it should be shaken gently and reprimed with 1 spray or until a fine spray appears. It is recommended that the applicator tip be wiped with a clean tissue following daily use. It is also recommended that the applicator be cleaned weekly using warm water and reprimed with one spray or until a fine mist appears.
APO-CICLESONIDE delivers 50 mcg of ciclesonide per spray. Each bottle of APO-CICLESONIDE contains 120 metered sprays after initial priming. The bottle should be discarded after 120 sprays following initial priming, since the amount of ciclesonide delivered per spray thereafter may be substantially less than the labeled dose. If more than 6 months have elapsed since the bottle was removed from the foil pouch, it should be discarded.
Do not spray in eyes. Avoid spraying APO-CICLESONIDE directly onto the nasal septum.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional poison control centre.
Acute overdosage with this dosage form is unlikely since one 120 spray bottle of ciclesonide nasal spray only contains approximately 9.6 mg of ciclesonide. A single oral dose of up to
10 mg of ciclesonide in healthy volunteers was well tolerated and serum cortisol levels were virtually unchanged in comparison with placebo treatment. Considering the low systemic availability of ciclesonide administered intranasally or orally, systemic effects following an overdose are unlikely.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Ciclesonide is a pro-drug with a low glucocorticoid receptor affinity and is pharmacologically inactive. Following intranasal application, ciclesonide is enzymatically converted by esterases in the nasal mucosa to the pharmacologically active metabolite, 21 des-methylpropionyl-ciclesonide (des-ciclesonide, des-CIC, M1). M1 has potent anti-inflammatory activity with affinity for the glucocorticoid receptor that is 120 times higher than the parent compound and 12 times higher than dexamethasone.
The primary mechanism of corticosteroid action in allergic rhinitis is considered due to anti-inflammation. Corticosteroids have been shown to have a wide range of effects on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in allergic inflammation. The anti-inflammatory properties of ciclesonide and des-ciclesonide (M1) were shown in several in vitro and in vivo investigations, including experiments using a guinea pig model of allergic rhinitis and several investigations in primary human nasal epithelial cells, bronchial epithelial and smooth muscle cells (see DETAILED PHARMACOLOGY).
Pharmacodynamics
Ciclesonide is a topical glucocorticosteroid delivered as a unique hypotonic suspension that has local anti-inflammatory properties at doses that are minimally systemically active. The effects of ciclesonide nasal spray on the HPA (hypothalamic-pituitary-adrenal) axis were investigated in several Phase III clinical trials up to one-year in duration and no appreciable effects of intranasally administered ciclesonide on serum or urinary cortisol levels were detected (see DETAILED PHARMACOLOGY). This pharmacodynamic finding is consistent with the negligible systemic bioavailability of ciclesonide following intranasal administration.
Pharmacokinetics
Absorption: Ciclesonide and des-ciclesonide (M1) have negligible oral bioavailability (both less than 1%) due to low gastrointestinal absorption and high first-pass metabolism. The intranasal administration of ciclesonide at recommended doses results in negligible serum concentrations of ciclesonide and its active metabolite (M1) in adult and pediatric subjects using a sensitive bioanalytical assay with a lower limit of quantification of 25 pg/mL and 10 pg/mL for ciclesonide and M1, respectively. Due to the negligible serum concentrations following intranasal administration of ciclesonide, pharmacokinetic calculations could not be performed.
Distribution: The volumes of distribution of ciclesonide and des-ciclesonide (M1) following i.v. administration were approximately 2.9 L/kg and 12.1 L/kg, respectively. The percentage of ciclesonide and the active metabolite M1 bound to human plasma proteins averaged ≥ 99% each. Only the unbound drug in the systemic circulation (approximately 1%) is available for further systemic pharmacodynamic effect; des-ciclesonide (M1) is not significantly bound to human transcortin.
Metabolism: Intranasal ciclesonide is primarily hydrolyzed to its biologically active metabolite, des-ciclesonide (M1), by esterases in the nasal mucosa (primarily by carboxylesterases and cholinesterases). M1 is metabolized in the liver to inactive metabolites mainly by the CYP 3A4 isozyme. Furthermore, inactive fatty acid ester conjugates of M1 in human nasal epithelial cells were detected in vitro for up to 24 hours, providing a reversible depot of M1 due to gradual hydrolysis by lipases.
Elimination: After oral and intravenous administration, ciclesonide is predominantly excreted via the feces (66%), indicating that excretion via the bile is the major route of elimination.
Special Populations and Conditions
The pharmacokinetics of intranasally administered ciclesonide have not been assessed in patient subpopulations because the resulting blood levels are insufficient for pharmacokinetic calculations. However, the pharmacokinetic characteristics of M1 after oral inhalation of ciclesonide were not appreciably influenced by a variety of subject/patient characteristics such as body weight, advanced age, race, gender and liver impairment. Studies in renal impaired patients were not conducted since renal excretion of des-ciclesonide (M1) is a minor route of elimination (≤ 20%). Because the systemic exposure of intranasally administered ciclesonide is much lower than that of orally inhaled ciclesonide, it is not likely that these special populations will experience clinically relevant changes in the pharmacokinetics of intranasally administered ciclesonide.
STORAGE AND STABILITY
Store at room temperature 15°C – 30°C. Do not freeze. Shake gently. Protect from light. APO-CICLESONIDE should be discarded 6 months after opening of the aluminum foil pouch.
SPECIAL HANDLING INSTRUCTIONS
The ciclesonide nasal spray device is packaged within a tamper resistant aluminum foil pouch to protect the product from oxygen absorption. In addition, an oxygen absorber sachet is contained within the overwrap to absorb atmospheric oxygen. Ciclesonide nasal spray should be stored in the aluminum foil pouch and only removed immediately before first use. Ciclesonide nasal spray should be discarded 6 months after removal from the aluminum foil pouch.
DOSAGE FORMS, COMPOSITION AND PACKAGING
APO-CICLESONIDE is an unscented, metered-dose, manual-pump spray formulation containing a hypotonic aqueous suspension of ciclesonide. APO-CICLESONIDE also contains edetate disodium dihydrate, hypromellose, microcrystalline cellulose and carboxymethylcellulose sodium, potassium sorbate and purified water; hydrochloric acid may be added to adjust the pH to a target 4.5.
APO-CICLESONIDE is contained within an amber glass bottle and provides for nasal delivery with a manual metered pump. The bottle is enclosed in an aluminum foil pouch with an oxygen absorber. APO-CICLESONIDE provides 120-metered sprays after initial priming; net fill weight 12.5 g. The APO-CICLESONIDE bottle has been filled with an excess to accommodate the priming activity. The bottle should be discarded after 120 sprays following initial priming, since the amount of ciclesonide delivered per spray thereafter may be substantially less than the labeled dose. Each spray delivers 50 mcg of ciclesonide to the patient.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
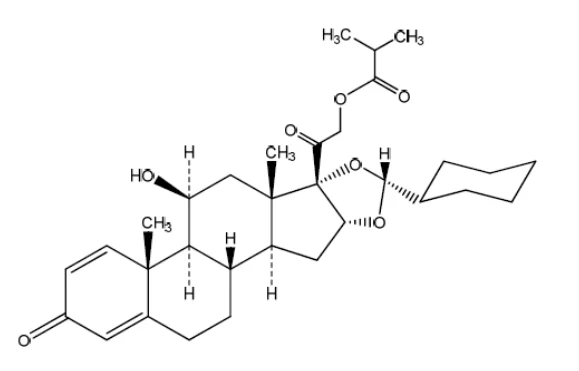
Common Name: Ciclesonide
Chemical Name: (11β,16α)-16,17-[[(R)-cyclohexylmethylene]bis(oxy)]-11-hydroxy-21-(2-methyl-1-oxo-propoxy)pregna-1,4-diene-3,20-dione
Molecular formula and molecular weight: C32H44O7, 540.69 g/mol
Structural Formula:
Physical Form: White to off-white powder
Solubility: Practically insoluble in water; freely soluble in ethanol and acetone
CLINICAL TRIALS
Clinical Efficacy and Comparative Bioavailability Studies
A clinical efficacy study was conducted between March and August 2011 to demonstrate efficacy and bioequivalence. The study consisted of a double blind, multi-center, placebo controlled, parallel group, randomized clinical study. Of the 580 subjects (male and female) who completed the placebo run-in period and were randomized to one of the three treatments (Apo-Ciclesonide, Omnaris™ and placebo), 502 subjects met the criteria for clinical equivalency analysis and 527 subjects were eligible for the clinical efficacy analysis. Each eligible subject received a dose of 200 mcg per day (50 mcg per actuation, 2 actuations in each nostril once daily) for 14 days. Drug concentration/time profiles and pharmacokinetic parameters were not determined in this study.
The primary efficacy and equivalence measures were based on the average morning and evening Reflective total nasal symptom scores (TNSS) of rhinorrhea, nasal congestion, nasal itchiness and sneezing. The primary endpoint was the change in Reflective TNSS from baseline to the average of the data from the 14 days of treatment.
A secondary efficacy analysis on the ITT and the PP populations was conducted in an identical manner to the primary efficacy analysis, except using the secondary efficacy measure of instantaneous TNSS (morning and evening instantaneous scores on runny nose, nasal congestion, nasal itchiness, and sneezing).
The efficacy and bioequivalence results for the seasonal allergic rhinitis study are shown in the table below:
Mean ± SD Changes from Baseline in Reflective Total Nasal Symptom Scores (rTNSS) and Instantaneous Total Nasal Symptom Score (iTNSS) in Seasonal Allergic Rhinitis Trial
| Measures | Statistics1 | Ciclesonide (50 mcg/spray; 2 sprays per nostril daily) | Equivalence Assessment2 | ||||||||||||||||
| Based on Untransformed Data | Based on Log-transformed Data | ||||||||||||||||||
| Test# | Reference† | Placebo | Ratio (Test/Ref) of Means (%) | 90% Confidence Interval | Ratio (Test/Ref) of Means (%) | 90% Confidence Interval | |||||||||||||
| N | (N=209) | (N=207) | (N=111) | ||||||||||||||||
| rTNSS | Mean ± SD | -1.67* ± 2.04 | -1.56* ± 2.05 | -0.89 ± 1.75 | 103.31 | 84.55 -122.07 | 106.78 | 101.81 -112.00 | |||||||||||
| iTNSS | Mean ± SD | -1.61* ± 1.99 | -1.42* ± 1.98 | -0.83 ± 1.77 | 107.96 | 87.62 -128.31 | 115.82 | 110.09 - 121.85 | |||||||||||
# Apo-Ciclesonide 50 mcg/metered nasal spray (Apotex Inc.) † Omnaris™ Nasal Spray, 50 mcg/spray (Sepracor, Inc.) was purchased in the USA 1 Based on the Intent-To-Treat population 2 Based on the Per-Protocol population * Significantly different from placebo (p<0.001) | |||||||||||||||||||
A randomized, single dose, 2-way crossover comparative bioavailability study, conducted under fasting conditions, was performed on healthy male and female (93 male and 53 female) volunteers. The rate and extent of absorption of des-ciclesonide was measured and compared following a 200 mcg (4 x 50 mcg/spray, administered as 2 sprays per nostril) of Omnaris® (ciclesonide) Nasal Spray, 50 mcg (Sepracor Inc., USA) and Apo-Ciclesonide Nasal Spray,
50 mcg (Apotex Inc.) in 146 volunteers. The results from measured data are summarized in the following table:
Summary Table of the Comparative Bioavailability Data Des-Ciclesonide 200 mcg (4 x 50 mcg/spray, administered as 2 sprays per nostril) From Measured Data/Fasting Conditions Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Apo–Ciclesonide Nasal Spray (Apotex Inc.) (Canada) | Omnaris® Nasal Spray€ (Sepracor Inc.) (USA) | Ratio of Geometric Means (%) | 90% Confidence Interval (%) |
AUCt (pg•h/mL) | 62.2 77.1 (70) | 62.1 73.3 (54) | 100.1 | 93.7 – 107.0 |
AUCinf (pg•h/mL) | 93.5 124.4 (106) | 93.7 119.8 (75) | 99.8 | 88.9 – 112.1 |
Cmax (pg/mL) | 5.9 6.9 (63) | 5.9 6.6 (49) | 100.7 | 95.5 – 106.1 |
| Tmax§ (h) | 3.0 (0.8 – 30.0) | 2.5 (1.5 – 18.0) | ||
| Thalf† (h) | 15.1 (93) | 19.6 (186) | ||
§ Expressed as median (range) only. † Expressed as arithmetic mean (CV%) only. € Omnaris® Nasal Spray is manufactured for Sepracor Inc. and was purchased in the USA. For the Cmax and Tmax parameters, N = 145 for the Test product and N = 146 for the Reference Product. For the AUCinf and Thalf parameters, N = 116 for the Test product and N = 102 for the Reference Product. | ||||
Study Demographics and Trial Design
The efficacy and safety of ciclesonide nasal spray in adolescents and adults 12 years and older with seasonal allergic rhinitis (SAR) or perennial allergic rhinitis (PAR) have been evaluated in double-blind, placebo-controlled clinical trials up to 1 year in duration. The number of patients treated with ciclesonide nasal spray in these studies was 2013 (737 males and 1276 females) and included a total of 158 adolescent patients. The age of patients ranged from 12 – 75 years of age and the median age was 36 years. In all treatment groups, the majority of patients were Caucasian. All studies included ciclesonide 200 mcg and placebo once daily dose groups.
These trials evaluated total nasal symptoms scores that included runny nose, nasal itching, sneezing and nasal congestion using a 0 to 12 scale.
Study Results
Efficacy in Seasonal and Perennial Allergic Rhinitis in Adolescents and Adults:
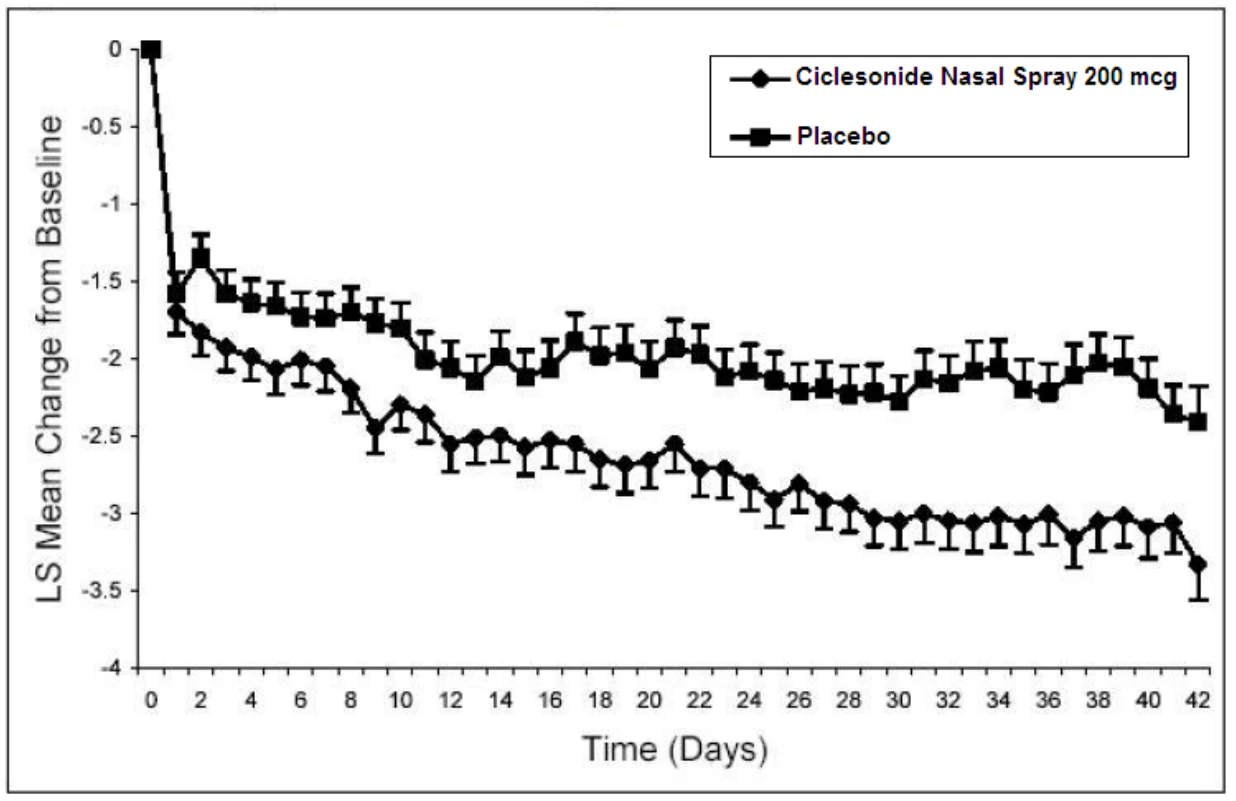
The efficacy of ciclesonide nasal spray 200 mcg administered once daily was evaluated in two pivotal studies; a 4-week study in patients with SAR and a 6-week study in patients with PAR. The primary endpoint for these studies was change from baseline in patient-assessed total nasal symptom score (TNSS) ratings vs. placebo. The changes from baseline in TNSS over the 14 and 42 day primary efficacy assessment periods for the pivotal SAR and PAR studies in patients 12 years and older are displayed in Table 3 and Figure 1 and Figure 2 below. The mean baseline symptom scores for ciclesonide nasal spray and placebo were 8.96 and 8.83 in SAR and 7.59 and 7.71 in PAR. In both studies, patients treated with ciclesonide nasal spray 200 mcg once daily had a significant decrease in total nasal symptom scores compared to placebo-treated patients, and the improvement in TNSS was maintained over the full 24-hour dosing interval.
Table 3: Mean Change from Baseline in Average Reflective AM and PM TNSS in Pivotal Efficacy Trials with Ciclesonide Nasal Spray
| Study | Inclusion | Treatment arms / dosage (mcg) | # of patients (ITT) | Duration of Study | Total Nasal Symptom Score (TNSS) | |||||
| LS Mean Change from baseline in Average Reflective AM and PM TNSS | p value vs. placebo | |||||||||
| 1 | History of SAR for a min. of 2 years preceding study season. | CIC 200 OD PLACEBO | 162 162 | 4 weeks1 | -2.40 -1.50 | p<0.001 | ||||
| 2 | History of PAR for a min. of 2 years preceding study start. | CIC 200 OD PLACEBO | 232 229 | 6 weeks | -2.51 -1.89 | p<0.001 | ||||
1 primary efficacy endpoint was change from baseline over the first two weeks of the treatment period.
CIC = ciclesonide
Figure 1: Change from Baseline in Average AM and PM Reflective TNSS in Seasonal Allergic Rhinitis
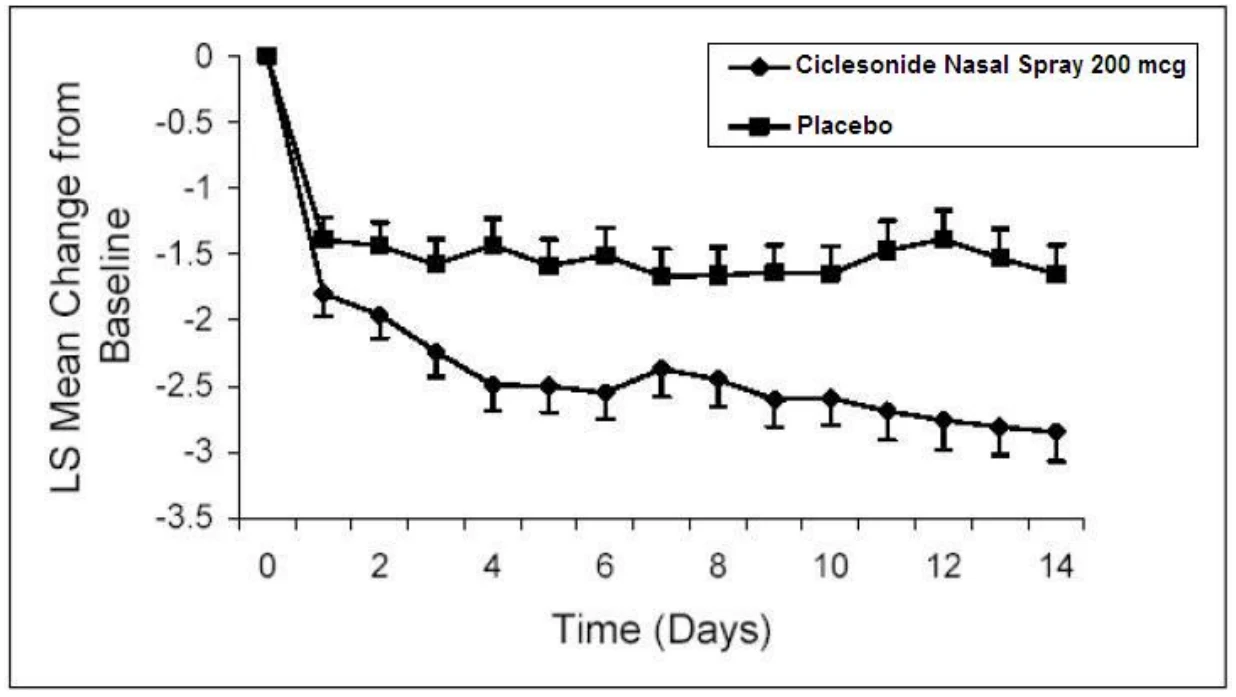
Figure 2: Change from Baseline in Average AM and PM Reflective TNSS in Perennial Allergic Rhinitis
The long-term effectiveness of ciclesonide nasal spray was demonstrated in a 52-week safety study. Over the full course of the study (Days 2-365), the mean decrease in TNSS (24-hour reflective) from baseline was greater in the ciclesonide nasal spray group vs. placebo (p<0.001) with no evidence of tachyphylaxis.
In addition to the two pivotal efficacy studies, two Environmental Exposure Unit (EEU) studies were conducted in patients with SAR to investigate the onset of effect of ciclesonide nasal spray. In the first EEU study a statistically significant improvement in nasal symptoms compared to placebo was noted within 1 hour of first using ciclesonide nasal spray. In a second EEU study in seasonal allergic rhinitis patients, statistically significant improvement in nasal symptoms was observed at one time point of 6 hours, however, a second statistically significant confirmatory time point was not observed.
DETAILED PHARMACOLOGY
Human Pharmacology
Pharmacokinetics: Ciclesonide, administered as a nasal spray, at recommended doses results in negligible serum concentrations of ciclesonide and its active metabolite des-ciclesonide (M1), despite the use of a sensitive assay with a lower quantitation limit of 25 pg/mL for ciclesonide and 10 pg/mL for the M1. Thus, no pharmacokinetic data for this dosage form could be calculated.
Investigations in primary human nasal epithelial cells (HNEC), bronchial epithelial and smooth muscle cells have shown rapid cell penetration of ciclesonide, conversion to active metabolite M1, and a long duration of anti-inflammatory action in vitro.
In studies in HNEC it was demonstrated that the pharmacological active metabolite des-ciclesonide (M1) can reversibly form fatty acid conjugates (primary oleate) which can serve as a slow release pool for the active metabolite in nasal tissue. The long-term retention of M1 at relatively stable levels for up to 24 hours was demonstrated. These properties contribute to long-term retention of M1 in the cells.
Pharmacodynamics: The effects of ciclesonide nasal spray on adrenal function have been evaluated in several clinical trials. In a study of 40 healthy adult volunteers and 8 asymptomatic seasonal allergic rhinitis patients, no significant differences between the active and placebo groups were observed in 24-hour plasma or urine cortisol after administration of 50-800 mcg daily of ciclesonide for 14 days. In a 1 year safety study including 174 patients treated with
200 mcg once daily of ciclesonide nasal spray and 92 patients treated with placebo who had cortisol assessments, no significant differences in morning plasma and 24-hour urine cortisol levels were observed with ciclesonide versus placebo treatment.
As asthma and allergic rhinitis are often co-morbid conditions, the concomitant use of intranasal and inhaled corticosteroids was studied. Two pharmacodynamic studies were conducted in patients with perennial allergic rhinitis to assess the effect of ciclesonide nasal spray on adrenal function when combined with inhaled corticosteroid-containing products. One study evaluated the addition of ciclesonide nasal spray to inhaled beclomethasone diproprionate HFA (320 mcg BID) in 111 patients. A second study evaluated the addition of ciclesonide nasal spray to inhaled fluticasone propionate and salmeterol (500/50 mcg BID) combination therapy in 150 patients. Orally inhaled corticosteroid treatment was administered for a ten-day run-in period and was continued throughout a 43-day treatment period. Patients were randomized to concomitant ciclesonide (200 mcg/day) or placebo nasal spray at the end of the run-in period. As a positive control on the last treatment day, all patients additionally received 2 mg dexamethasone orally.
Both 24-hour plasma and urine cortisol levels significantly decreased over the 10-day run-in period due to the inhaled corticosteroid therapy. After six weeks of treatment, ciclesonide nasal spray, when co-administered with inhaled corticosteroid therapy, was shown to have no additional inhibitory effect on plasma or urine cortisol when compared to placebo. In both studies, further cortisol suppression was observed on the last treatment day when oral dexamethasone was added, indicating that additional suppression of the HPA-axis was possible. These studies indicate that the addition of ciclesonide nasal spray is unlikely to impact the HPA-axis in patients concurrently receiving inhaled corticosteroids.
Animal Pharmacology
The main mechanism of corticosteroid action in allergic rhinitis is considered due to anti-inflammation. The anti-inflammatory properties of ciclesonide and des-ciclesonide (M1) were shown in several in vitro and in vivo experiments. In a guinea pig model of allergic rhinitis, it was demonstrated that the repeated treatment with ciclesonide could prevent the immediate (increase in nasal resistance) and late response (influx of inflammatory cells) following allergen challenge.
Ciclesonide nasal spray is formulated as a hypotonic suspension. In a preclinical study conducted in rabbits, there was an enhanced uptake of ciclesonide into the nasal mucosa, a significantly higher intracellular concentration of des-ciclesonide (M1) and longer retention of the active metabolite when a hypotonic suspension of ciclesonide was administered compared to administration of an isotonic formulation.
TOXICOLOGY
Toxicology studies conducted with ciclesonide showed effects typically associated with administering high doses of glucocorticoids; no unexpected effects were found in the toxicology studies conducted with ciclesonide.
Acute toxicity
Oral and intraperitoneal acute toxicity studies were performed in rats and mice. The approximate LD50 values are significantly higher than doses that would be administered to humans:
Table 4: LD50 Values in Oral and Intraperitoneal Acute Toxicity Studies
| Species | Route | Doses (mg/kg) | LD50 (mg/kg) |
| Mouse | Intraperitoneal | 0, 50, 100, 200 | >200 |
| Mouse | Oral | 0, 2000 | >2000 |
| Rat | Intraperitoneal | 0, 50, 100, 200 | >200 |
| Rat | Oral | 0, 2000 | >2000 |
Chronic Toxicity
In all toxicity studies, ciclesonide was well tolerated by animals of all investigated species with adverse effects limited to those associated with glucocorticoid activity that were either completely or mostly reversible after cessation of treatment. There was no indication of clinically relevant effects in the respiratory tract.
Table 5: No Observed Adverse Effect Level in Chronic Toxicity Studies with Intranasal Application of Ciclesonide
| Species | Duration | Application form | NOAEL (mcg/kg/day) |
| Rat | 4 weeks | Intranasal (hypotonic suspension) | 429 |
| Rat | 4 weeks | Intranasal (hypotonic suspension) | 429 |
| Dog | 4 weeks | Intranasal (hypotonic suspension) | 480 |
| Dog | 6 months | Intranasal (hypotonic suspension) | 4800 mcg/body/day |
In both rat studies, a reduction in weight gain, slight deviations in clinical chemistry parameters, and a reduction in thymus weight reflected the pharmacological activity of ciclesonide. All findings were reversible.
The 4-week study in dogs revealed a reduction in body weight gain, elevation of clinical chemistry parameters, and low thymus and adrenal weights correlating with thymus and adrenal atrophy. The lymphoid aggregates associated with the respiratory mucosa tended to be smaller. All findings were attributed to the glucocorticoid pharmacology of ciclesonide and showed reversibility after the treatment-free period.
In the 6-month dog study, substance-related findings included a slight decrease in leukocyte and lymphocyte count, low adrenal weights, cortical and thymus atrophy and atrophy of the mucosal-associated lymphoid tissue in the respiratory mucosa of the nasal cavity. All these findings were very slight or slight, showed complete reversibility after the recovery period and are considered to be due to the glucocorticoid pharmacological action of ciclesonide.
Inhalation administration of ciclesonide was evaluated in a series of studies of up to 6-months duration in rats and 12-months duration in dogs, and the no observed adverse effect levels (NOAEL) were determined.
Table 6: No Observed Adverse Effect Level in Chronic Toxicity Studies with Inhalation Administration of Ciclesonide
| Species | Duration | Application form | NOAEL (mcg/kg/day) |
| Rat | 4 week | Powder | 50.5 |
| Rat | 4 week | MDI | Males: 50.3; Females 55.2 |
| Rat | 6 months | Powder | Males: 44.5; Females 49.6 |
| Dog | 4 week | Powder | 50 |
| Dog | 4 week | MDI | 61 |
| Dog | 4 week | MDI | 15 (highest dose studied) |
| Dog | 13 week | MDI | 53 |
| Dog | 12 month | Powder | 47 |
In the rat, comparable and typical glucocorticoid-like effects were observed which were completely or partially reversible during the recovery periods – slight reductions in body, spleen and thymus weights and minor alterations in erythrocytes, lymphocytes, differential blood cell picture, serum urea, serum creatinine, serum corticosterone and urine electrolyte levels, increased development of alveolar structures in the mammary gland, atrophy of lymphocytic components in thymus, spleen, and lymph nodes, atrophy of adrenal cortex.
Dogs similarly showed only exaggerated glucocorticoid-like effects – atrophy of lymphocytic components in thymus, spleen and lymph nodes, suppression of serum cortisol levels, atrophy of adrenal cortex.
The initial effects seen in toxicity studies – decrease of body-weight gain, lymphoid tissue depletion, adrenal atrophy, and, in rats, activation of erythrocyte parameters - result from pronounced pharmacological glucocorticoid activity, demonstrating the continuum of actions recognized for corticosteroids and seen with other glucocorticoids. Because of the need for the enzymatic conversion of ciclesonide ester to its active metabolite and the high plasma protein binding of both ciclesonide and its metabolite, the results suggest that ciclesonide can be used in humans at therapeutic doses that are expected to be devoid of both local (upper and lower respiratory tract, mouth, esophagus, stomach) and systemic glucocorticoid effects.
Local Tolerance
In a primary eye irritation study, ciclesonide nasal spray with the concentrations 25 and
100 mcg/actuation was categorized as non-irritant. The formulation of the nasal spray showed no primary irritating potential in an intranasal irritation study in rabbits.
Mutagenicity
Ciclesonide was negative in the conducted in vitro test for genotoxicity:
- in the Ames test for gene mutation in bacteria;
- in the HPRT test for gene mutation in bacteria;
- in the test for chromosome aberrations in human lymphocytes and the in vitro micronucleus test in Chinese hamster V79 cells.
Moreover, racemic ciclesonide was also negative in an Ames test.
Four independent in vivo micronucleus tests were performed in mice covering a range of orally administered doses of glucocorticoids including ciclesonide. Threshold doses were found for all glucocorticoids tests at a dose which induced micronuclei in vivo. This induction of micronuclei is known from the literature. A positive response at high doses of glucocorticoids in the in vivo micronucleus assays is not indicative for a genotoxic potential.
Carcinogenicity
Two carcinogenicity studies were performed with ciclesonide; one study was conducted in mice (2-year study, oral gavage) and the other in rats (2-year study, inhalation).
Doses in the mouse study were 150, 450, and 900 mcg/kg/day administered by oral gavage. No compound related malignant tumors were reported. However, histology showed small, focal and solitary gastric adenomas at a very low incidence (one male and three females in the high dose group, one male each in the low and mid dose group). The adenoma were small, focal, solitary, and incidentally observed at the end of the 2-year study. They did not affect survival rate and only reached statistical significance by trend analysis in high dose females. There were also non-neoplastic changes consisting of a slightly increased incidence of hyperplastic changes in the epithelium of the antrum, mainly at the junction with the duodenum (mainly in males), and focal squamous metaplasia at the junction of the antrum and duodenum were detected for mice receiving 900 or 450 mcg/kg/day. The benign gastric adenomas in mice were only present in one species (mouse), only in one site (the antrum of the stomach), and only by one route of administration (oral gavage). For the oral gavage in the mouse, polyethylene glycol 400 (PEG 400) was used as the vehicle. PEG 400 has been reported to be a digestive tract irritant and to potentiate the activity of drugs. There is no PEG in the clinical nasal spray formulation. Hyperplastic and neoplastic changes in the stomach of the mice should be seen together as the result of response processes to irritating action. The benign neoplastic findings in the antrum are unlikely to present a safety concern for humans.
Inhalation doses in the rat carcinogenicity study were for males/females, 14/16.2, 34.9/40.4, and 89.3/103.6 mcg/kg/day administered by MDI over one hour. After 2 years of daily exposure, the results of the rat inhalation carcinogenicity study indicate the absence of a tumorigenic potential of inhaled ciclesonide.
Reproduction and Teratology
No effects were observed in rats on fertility, embryofoetal development, or pre/post natal studies apart from a reduction in body weight or body weight gain in animals receiving 300 mcg/kg/day and 900 mcg/kg/day orally (all studies were conducted with 100/300/900 mcg/kg/day). In rabbits, embryotoxic effects (reduced litter weight, incomplete ossification) and teratogenic effects (like cleft palate, flexure of paw, enlarged fontanelle, parchment-like skin) were observed over the dose range of 5 to 100 mcg/kg/day given subcutaneously. The effects observed with ciclesonide in rabbits are those reported for other glucocorticosteroids. The no-effect for maternal toxicity in rabbits was established at 25 mcg/kg/day and for embryofoetal development at 1 mcg/kg/day.
REFERENCES
- 1) Nave R, Bethke TD, van Marle SP, Zech K. Pharmacokinetics of [14C] ciclesonide after oral and intravenous administration to healthy subjects. Clin Pharmacokinet 2004; 43(7): 479- 486.
- 2) Nave R, Drollman A, Steinijans VW, Zech K, Bethke TD. Lack of pharmacokinetic drug-drug interaction between ciclesonide and erythromycin. Int J of Clin Pharmacol Ther 2005; 43(6): 264-270.
- 3) Nave R, Meyer W, Fuhst R, Zech K. Formation of fatty acid conjugates of ciclesonide active metabolite in the rat lung after 4-week inhalation of ciclesonide. Pulm Pharmacol Ther 2005; 18 (2005) 390-396.
- 4) Ratner P, Darken P, Wingertzahn M, Shah T. Ciclesonide and beclomethasone dipropionate coadministration: effect on cortisol in perennial allergic rhinitis. J Asthma 2007; 44:629-633.
- 5) Rohatagi S, Arya V, Zech K, Nave R, Hochhaus G, Jensen BK, Barrett JS. Population pharmacokinetics and pharmacodynamics of ciclesonide. J Clin Pharmacol 2003; 43: 365- 378.
- 6) Product Monograph – Omnaris® (ciclesonide nasal spray) 50 mcg/metered spray. AstraZeneca Canada Inc. Date of Revision: January 19, 2017.