


Product Monograph - Atriance
RECENT MAJOR LABEL CHANGES
| 11 STORAGE, STABILITY AND DISPOSAL | [01/2021] |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics ................................................................................................................. 4
1.2 Geriatrics ................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.3 Administration ......................................................................................................... 6
5 OVERDOSAGE ............................................................................................................ 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 6
7 WARNINGS AND PRECAUTIONS ................................................................................. 7
7.1 Special Populations .................................................................................................. 9
7.1.1 Pregnant Women ............................................................................................... 9
7.1.2 Breast-feeding .................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................ 9
7.1.4 Geriatrics ............................................................................................................ 9
8 ADVERSE REACTIONS............................................................................................... 10
8.2 Clinical Trial Adverse Reactions ............................................................................. 10
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................... 15
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 17
8.5 Post-Market Adverse Reactions ............................................................................. 18
9 DRUG INTERACTIONS .............................................................................................. 18
9.1 Serious Drug Interactions ...................................................................................... 18
9.2 Drug Interactions Overview ................................................................................... 18
9.3 Drug-Behavioural Interactions ............................................................................... 19
9.4 Drug-Drug Interactions .......................................................................................... 19
10 CLINICAL PHARMACOLOGY ...................................................................................... 20
10.1 Mechanism of Action ....................................................................................... 20
10.2 Pharmacokinetics ............................................................................................. 20
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 22
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 23
PART II: SCIENTIFIC INFORMATION ..................................................................................... 24
13 PHARMACEUTICAL INFORMATION .......................................................................... 24
14 CLINICAL TRIALS ...................................................................................................... 24
14.1 Trial Design and Study Demographics ............................................................. 24
14.2 Study Results .................................................................................................... 25
15 MICROBIOLOGY ...................................................................................................... 27
16 NON-CLINICAL TOXICOLOGY .................................................................................... 27
PATIENT MEDICATION INFORMATION ................................................................................ 30
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
ATRIANCE® (nelarabine) is indicated for the treatment of patients with T-cell acute lymphoblastic leukemia and T-cell lymphoblastic lymphoma whose disease has not responded to or has relapsed following treatment with at least two chemotherapy regimens.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of ATRIANCE in pediatric patients has been established; therefore, Health Canada has authorized an indication for pediatric use. See 4.2 Recommended Dose and Dosage Adjustment and 14 CLINICAL TRIALS.
1.2 Geriatrics
Geriatrics (65 years or older): Clinical studies of ATRIANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently than younger patients.
In an exploratory analysis, increasing age, especially aged 65 years and older, appeared to be associated with increased rates of neurologic adverse events. See 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
ATRIANCE is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
ATRIANCE (nelarabine) Injection should be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents. This product is for intravenous use only. Severe Neurologic Events: These events included:
|
Some of these neurologic adverse events are irreversible and fatal. ATRIANCE should be discontinued at the first sign of neurologic events of NCI Common Toxicity Criteria grade 2 or greater (See 7 WARNINGS and PRECAUTIONS, Neurologic, 8 ADVERSE REACTIONS, 4 DOSAGE and ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment). Close monitoring for neurological events is strongly recommended. |
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Appropriate measures (e.g. hydration, urine alkalinization, and prophylaxis with allopurinol) must be taken to prevent hyperuricemia associated with tumour lysis syndrome.
Supportive measures (e.g. antiemetic agents) and medical care (e.g. antibiotics, blood and platelet transfusions) are recommended, as clinically indicated.
4.2 Recommended Dose and Dosage Adjustment
Adults: The recommended adult dose of ATRIANCE is 1,500 mg/m²/day administered intravenously over 2 hours on days 1, 3, and 5, repeated every 21 days.
Children : The recommended pediatric dose of ATRIANCE for children 15 years and younger is 650 mg/m²/day administered intravenously over 1 hour on days 1 to 5, repeated every 21 days.
The optimal dosing regimen for patients between the ages of 16 and 21 years of age has not been determined.
The recommended duration of treatment has not been clearly established. In clinical trials, treatment was generally continued until there was evidence of disease progression, the patient experienced unacceptable toxicity, the patient became a candidate for bone marrow transplant, or the patient no longer continued to benefit from treatment.
The optimal schedule of concurrently administered nelarabine with intrathecal therapy and/or craniospinal irradiation has not been studied and is therefore not recommended (see 7 WARNINGS AND PRECAUTIONS, Neurologic; and 9 DRUG INTERACTIONS).
ATRIANCE has not been studied in patients with hepatic or renal dysfunction. No dose adjustment is recommended for CrCl≥50 mL/min. There are insufficient data to support a dose recommendation for CrCl < 50 mL/min (see 10 CLINICAL PHARMACOLOGY, Special Populations and Conditions, Renal Insufficiency).).
ATRIANCE (nelarabine) should be discontinued at the first sign of neurologic events of NCI Common Toxicity Criteria grade 2 or greater. Administration of the next treatment cycle may be delayed for other toxicity including hematologic toxicity (See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Neurologic, 8 ADVERSE REACTIONS).
4.3 Administration
Nelarabine Injection is intended to be used without further dilution.
Nelarabine Injection is stable in polyvinylchloride (PVC) infusion bags and glass containers for up to 8 hours at up to 30°C.
ATRIANCE solution should be inspected visually before use. Do not use if solution shows haziness, particulate matter, discolouration, or leakage.
5 OVERDOSAGE
There is no known antidote for overdoses of ATRIANCE (nelarabine). It is anticipated that overdosage would result in severe neurotoxicity (possibly including paralysis, coma), myelosuppression, and potentially death. In the event of overdose, supportive care consistent with good clinical practice should be provided.
Nelarabine has been administered in clinical trials up to a dose of 75 mg/kg (approximately 2,250 mg/m2) daily for 5 days to 1 pediatric subject and up to a dose of 60 mg/kg (approximately 2,400 mg/m2) daily for 5 days to 5 adult patients.
Nelarabine has been administered in clinical trials up to a dose of 2,900 mg/m2 on days 1, 3, and 5 to 2 adult patients. At a dose of 2,200 mg/m2 given on days 1, 3, and 5 every 21 days, 2 patients developed a significant grade 3 ascending sensory neuropathy. MRI evaluations of the 2 patients demonstrated findings consistent with a demyelinating process in the cervical spine.
Because strategies for the management of overdose are continually evolving, it is advisable to contact a poison control center to determine the latest recommendations for the management of an overdose of any drug.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
ATRIANCE (nelarabine) Injection is a clear, colorless solution containing 5 mg nelarabine and 4.5 mg sodium chloride per mL in Water for Injection, USP. Hydrochloric acid and sodium hydroxide may have been used to adjust the pH. The solution pH ranges from 5.0 to 7.0.
ATRIANCE Injection is supplied in Type I, clear glass, single use vials with a gray bromobutyl rubber (latex-free) stopper and a red snap-off aluminum seal containing 250 mg nelarabine in 50 mL Water for Injection, USP.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Solution for intravenous infusion | injection 5 mg/mL nelarabine | Sodium chloride, water for injection, USP. Hydrochloric acid and sodium hydroxide may have been used to adjust the pH. |
Available in cartons of 1 single use vial.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Patients receiving ATRIANCE should receive intravenous hydration according to standard medical practice for the management of hyperuricemia in patients at risk for tumour lysis syndrome. Consideration should be given to the use of allopurinol in patients at risk of hyperuricemia (See 4 DOSAGE AND ADMINISTRATION).).
Administration of live vaccines to immunocompromised patients should be avoided.
Carcinogenesis and Mutagenesis
Carcinogenicity testing of nelarabine has not been performed. Nelarabine, however, is known to be genotoxic to mammalian cells (see 16 NON-CLINICAL TOXICOLOGY).
Cardiovascular
The effect of nelarabine on QT interval prolongation has not been investigated.
Driving and Operating Machinery
No studies on the effects of nelarabine on the ability to drive and operate machines have been performed. Patients experiencing somnolence, dizziness, neurologic disorders, or any other undesirable effects with a potential impact on the ability to safely drive or use machines should refrain from these activities as long as these undesirable effects persist (see 8 ADVERSE REACTIONS, 9 DRUG INTERACTIONS, 99.3 Drug-Behavioural Interactions).
Hematologic
Leukopenia, thrombocytopenia, anemia (including Grade 3 and 4), and neutropenia, including febrile neutropenia (Grade 3 or 4) have been associated with nelarabine therapy. Complete blood counts including platelets should be monitored regularly (see 8 ADVERSE REACTIONS, and 4 DOSAGE AND ADMINISTRATION).
Hepatic/Biliary/Pancreatic
Hepatobiliary: In clinical trials, Grade 3 and 4 elevations in transaminases and bilirubin have occurred. In the post-marketing setting, cases of acute hepatic failure (including fatal toxic hepatitis) have been reported although causality has not been established.
Hepatically Impaired Patients: The influence of hepatic impairment on the pharmacokinetics of nelarabine has not been evaluated. Because the risk of adverse reactions to this drug may be greater in patients with severe hepatic impairment, these patients should be closely monitored for toxicities when treated with ATRIANCE.
Musculoskeletal
Nelarabine is associated with cases of rhabdomyolysis and creatine phosphokinase increased. Discontinuation of nelarabine therapy should be considered if rhabdomyolysis and creatine phosphokinase increased is suspected to be associated with the use of nelarabine.
Neurologic
Neurotoxicity is the dose-limiting toxicity of nelarabine. Patients undergoing therapy with ATRIANCE should be closely observed for signs and symptoms of neurologic toxicity.
Some of these neurologic adverse events are irreversible and fatal.
ATRIANCE should be discontinued at the first sign of neurologic events of NCI Common Toxicity Criteria grade 2 or greater. (See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 8 ADVERSE REACTIONS, 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment).
Close monitoring for neurological events is strongly recommended.
Patients treated previously or concurrently with intrathecal chemotherapy or previously with craniospinal irradiation may be at increased risk for neurologic adverse events (see 4 DOSAGE AND ADMINISTRATION). Case reports describing fatal neurologic outcomes following concurrent intrathecal chemotherapy and intravenous nelarabine have been received (see 9 DRUG INTERACTIONS). The optimal schedule of concurrently administered nelarabine with intrathecal therapy and/or craniospinal irradiation has not been studied and is therefore not recommended. Patients with CNS disease at baseline may have an increased risk of experiencing more severe (grade ≥ 3) neurological events.
Common signs and symptoms of nelarabine-related neurotoxicity include somnolence, confusion, altered level of consciousness, convulsions, ataxia, paraesthesias and hypoesthesia. Severe neurologic toxicity can manifest as coma, status epilepticus, myelopathy, craniospinal demyelination, or ascending neuropathy similar in presentation to Guillain-Barré syndrome (see 8 ADVERSE REACTIONS).
Renal
Renally Impaired Patients: Nelarabine has not been studied in individuals with renal impairment. Nelarabine and ara-G are partially renally excreted. Because the risk of adverse reactions to this drug may be greater in patients with decreased renal function (CrCl <50 mL/min), these patients should be closely monitored for toxicities when treated with ATRIANCE (see 4 DOSAGE AND ADMINISTRATION).
Reproductive Health: Female and Male Potential
Fertility
The effects of nelarabine on human fertility are not known (see 16 NON-CLINICAL TOXICOLOGY).
Teratogenic Risk
Females of Childbearing Potential: Females of childbearing potential (i.e. females who are menstruating or who are physiologically capable of becoming pregnant) should be advised to avoid becoming pregnant during treatment with ATRIANCE.
Females of childbearing potential must be advised to use highly effective contraception while receiving ATRIANCE. Highly effective contraception is a method of birth control which, when used alone or in combination, results in a low failure rate (i.e. less than 1% per year) when used consistently and correctly.
There are no clinical data on drug-drug interaction between ATRIANCE and hormonal contraceptives. The effect of ATRIANCE on hormonal contraceptives in humans is not known.
Male Patients: Sexually active male patients must use highly effective contraception during treatment with ATRIANCE.
Male patients with partners who are pregnant, possibly pregnant, or who could become pregnant should use condoms during sexual intercourse while receiving ATRIANCE and for 3 months following completion of therapy.
Male patients must be advised to inform their female sexual partners that they are taking ATRIANCE. Male patients must also advise their female partners of the potential serious risks to a developing fetus should pregnancy occur during her partner’s treatment with ATRIANCE (See 16 NON-CLINICAL TOXICOLOGY).
7.1 Special Populations
7.1.1 Pregnant Women
ATRIANCE may cause fetal harm when administered to a pregnant woman. There are no studies of ATRIANCE in pregnant women. Animal studies have reported increased incidences of fetal malformations and abnormalities following administration of nelarabine during pregnancy compared to controls (see 16 NON-CLINICAL TOXICOLOGY). One case of pregnancy was reported in a clinical trial with the outcome of fetal death. Causality could not be established due to the fact that the patient received multiple other chemotherapeutic drugs which can contribute to this outcome.
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be warned of the potential hazard to the fetus.
7.1.2 Breast-feeding
Nelarabine is a pro-drug of the deoxyguanosine analogue 9-β-D-arabinofuranosylguanine (ara-G) (see 10 CLINICAL PHARMACOLOGY). It is not known whether nelarabine or ara-G is excreted in human milk. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants from ATRIANCE, it is recommended that nursing be discontinued in women who are receiving therapy with ATRIANCE.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): In a phase III study including 685 patients aged < 16 with newly diagnosed T-ALL or T-LBL, the safety profile was consistent with that seen in the Phase I and Phase II studies. See 14 CLINICAL TRIALS.
Nelarabine pharmacology has not been studied in children under four years of age.
7.1.4 Geriatrics
Geriatrics (65 years or older): Clinical studies of ATRIANCE did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently than younger patients. In an exploratory analysis, increasing age, especially aged 65 years and older, appeared to be associated with increased rates of neurologic adverse events.
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Relapsed or Refractory T-ALL and T-LBL
Adults: ATRIANCE (nelarabine) was studied in 459 patients in Phase I and Phase II clinical trials. The safety profile for the recommended dosages of ATRIANCE is based on data from 103 adult patients enrolled and treated in the CALGB19801 Study and an adult chronic lymphocytic leukemia study (PGAA2003) who were treated with the recommended dose and schedule.
The most common adverse events in adults, regardless of causality, were fatigue; gastrointestinal (GI) disorders (nausea, diarrhea, vomiting, and constipation); hematologic disorders (severe anemia, leukopenia, neutropenia and thrombocytopenia); respiratory disorders (cough and dyspnea); nervous system disorders (somnolence and dizziness); and pyrexia.
The most common adverse events by System Organ Class, regardless of causality, including severe or life threatening events (NCI Common Toxicity Criteria grade 3 or grade 4) and fatal events (grade 5) are shown in Table 4 for pediatric patients and Table 2 for adult patients.
Table 2 Most Commonly Reported (≥5% Overall) Adverse Events Regardless of Causality in ADULT Patients Treated with 1,500 mg/m2 of ATRIANCE Administered Intravenously Over 2 Hours on Days 1, 3, and 5 Repeated Every 21 Days
System Organ Class Preferred Term | Percentage of Patients; N = 103 | ||
|---|---|---|---|
| Toxicity Grade | |||
Grade 3 % | Grade 4+ % | All Grades % | |
| Blood and Lymphatic System Disorders | |||
| Anemia | 20 | 14 | 99 |
| Thrombocytopenia | 37 | 22 | 86 |
| Neutropenia | 14 | 49 | 81 |
| Febrile neutropenia | 9 | 1 | 12 |
| Cardiac Disorders | |||
| Sinus tachycardia | 1 | 0 | 8 |
| Gastrointestinal Disorders | |||
System Organ Class Preferred Term | Percentage of Patients; N = 103 |
|---|
| Toxicity Grade |
|---|
Grade 3 % | Grade 4+ % | All Grades % | |
|---|---|---|---|
| Nausea | 0 | 0 | 41 |
| Diarrhea | 1 | 0 | 22 |
| Vomiting | 1 | 0 | 22 |
| Constipation | 1 | 0 | 21 |
| Abdominal pain | 1 | 0 | 9 |
| Stomatitis | 1 | 0 | 8 |
| Abdominal distension | 0 | 0 | 6 |
| General Disorders and Administration Site Conditions | |||
| Fatigue | 10 | 2 | 50 |
| Pyrexia | 5 | 0 | 23 |
| Asthenia | 0 | 1 | 17 |
| Edema, peripheral | 0 | 0 | 15 |
| Edema | 0 | 0 | 11 |
| Pain | 3 | 0 | 11 |
| Rigors | 0 | 0 | 8 |
| Gait, abnormal | 0 | 0 | 6 |
| Chest pain | 0 | 0 | 5 |
| Non-cardiac chest pain | 0 | 1 | 5 |
| Infections | |||
| Infection | 2 | 1 | 9 |
| Pneumonia | 4 | 1 | 8 |
| Hepatobiliary Disorders | |||
| AST increased | 1 | 1 | 6 |
System Organ Class Preferred Term | Percentage of Patients; N = 103 |
|---|
| Toxicity Grade |
|---|
Grade 3 % | Grade 4+ % | All Grades % | |
|---|---|---|---|
| Blood bilirubin increased | 2 | 0 | 3 |
| Metabolism and Nutrition Disorders | |||
| Anorexia | 0 | 0 | 9 |
| Dehydration | 3 | 1 | 7 |
| Hyperglycemia | 1 | 0 | 6 |
| Musculoskeletal and Connective Tissue Disorders | |||
| Myalgia | 1 | 0 | 13 |
| Arthralgia | 1 | 0 | 9 |
| Back pain | 0 | 0 | 8 |
| Muscular weakness | 5 | 0 | 8 |
| Pain in extremity | 1 | 0 | 7 |
| Nervous System Disorders (see Table 3) | |||
| Psychiatric Disorders | |||
| Confusional state | 2 | 0 | 8 |
| Insomnia | 0 | 0 | 7 |
| Depression | 1 | 0 | 6 |
| Respiratory, Thoracic, and Mediastinal Disorders | |||
| Cough | 0 | 0 | 25 |
| Dyspnea | 4 | 2 | 20 |
| Pleural effusion | 5 | 1 | 10 |
| Epistaxis | 0 | 0 | 8 |
| Dyspnea, exertional | 0 | 0 | 7 |
| Wheezing | 0 | 0 | 5 |
System Organ Class Preferred Term | Percentage of Patients; N = 103 |
|---|
| Toxicity Grade |
|---|
Grade 3 % | Grade 4+ % | All Grades % | |
|---|---|---|---|
| Vascular Disorders | |||
| Petechiae | 2 | 0 | 12 |
| Hypotension | 1 | 1 | 8 |
Grade 4+ = Grade 4 and Grade 5 Five (5) patients had a fatal event. Fatal events included hypotension (n = 1), respiratory arrest (n = 1), pleural effusion/pneumothorax (n = 1), pneumonia (n = 1), and cerebral hemorrhage/coma/ leukoencephalopathy (n = 1). The cerebral hemorrhage/coma/leukoencephalopathy was thought to be related to treatment with ATRIANCE. All other fatal events were unrelated to treatment with ATRIANCE. | |||
Other Adverse Events: Blurred vision was also reported in 4% of adult patients. There was a single report of biopsy confirmed progressive multifocal leukoencephalopathy in the adult patient population. Blindness unilateral was reported in 1% of adult patients. Reduced visual acuity was reported in 2% of adult patients and visual disturbance was reported in 1% of adult patients. Grade 3, Grade 4 and Grade 5 ALT increases have been reported in 1% of adults. Hallucination was reported in 1% of adult patients. In addition to the safety data from the pivotal clinical trials, tumour lysis syndrome has been observed (see 7 WARNINGS and PRECAUTIONS, General). Infection (including but not limited to; sepsis, bacteremia, pneumonia, fungal infection) were reported in adult patients and pediatric patients in clinical trials. There have been reports of sometimes fatal opportunistic infections in patients receiving nelarabine therapy.
Neurologic Adverse Events: Nervous system events, regardless of drug relationship, were reported for 64% of patients across the Phase I and Phase II studies.
Most patients in clinical studies with ATRIANCE had no apparent CNS involvement of their disease at the time of therapy initiation with ATRIANCE. However, in an exploratory analysis of 459 nelarabine treated patients across multiple dose levels and regimens, the presence of CNS involvement with malignancy at baseline was associated with an increased risk (odds ratio 3.35 in regression analysis, p = 0.0002) of grade ≥ 3 neurologic toxicity during therapy with ATRIANCE.
Adults: The most common neurologic adverse events, regardless of causality, including all grades (NCI Common Toxicity Criteria) are shown in Table 3 for adult patients.
| Table 3 Neurologic Adverse Events (≥1%) Regardless of Causality in ADULT Patients Treated with 1,500 mg/m2 of ATRIANCE Administered Intravenously Over 2 Hours on Days 1, 3, and 5 Repeated Every 21 Days | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
System Organ Class Preferred Term | Percentage of Patients; N =103 | |||||||||||
Grade 1 % | Grade 2 % | Grade 3 % | Grade 4 % | All Grades % | ||||||||
| Somnolence | 20 | 3 | 0 | 0 | 23 | |||||||
| Dizziness | 14 | 8 | 0 | 0 | 21 | |||||||
| Peripheral neurologic disorders, any event | 8 | 12 | 2 | 0 | 21 | |||||||
| Neuropathy | 0 | 4 | 0 | 0 | 4 | |||||||
| Peripheral neuropathy | 2 | 2 | 1 | 0 | 5 | |||||||
| Peripheral motor neuropathy | 3 | 3 | 1 | 0 | 7 | |||||||
| Peripheral sensory neuropathy | 7 | 6 | 0 | 0 | 13 | |||||||
| Hypoesthesia | 5 | 10 | 2 | 0 | 17 | |||||||
| Headache | 11 | 3 | 1 | 0 | 15 | |||||||
| Paresthesia | 11 | 4 | 0 | 0 | 15 | |||||||
| Ataxia | 1 | 6 | 2 | 0 | 9 | |||||||
| Depressed level of consciousness | 4 | 1 | 0 | 1 | 6 | |||||||
| Tremor | 2 | 3 | 0 | 0 | 5 | |||||||
| Amnesia | 2 | 1 | 0 | 0 | 3 | |||||||
| Dysgeusia | 2 | 1 | 0 | 0 | 3 | |||||||
| Balance disorder | 1 | 1 | 0 | 0 | 2 | |||||||
| Sensory loss | 0 | 2 | 0 | 0 | 2 | |||||||
| One (1) patient had a fatal neurologic event, cerebral hemorrhage/coma/leukoencephalopathy. This event was thought to be related to treatment with ATRIANCE. | ||||||||||||
Most nervous system events in the adult patients were evaluated as grade 1 or 2. The additional grade
3 events in adult patients, regardless of causality, were aphasia, convulsion, hemiparesis, and loss of consciousness, each reported in 1 patient (1%). The additional grade 4 events, regardless of causality, were cerebral hemorrhage, coma, intracranial hemorrhage, leukoencephalopathy, and metabolic encephalopathy, each reported in one patient (1%).
The other neurologic adverse events, regardless of causality, reported as grade 1, 2, or unknown in adult patients were abnormal coordination, burning sensation, disturbance in attention, dysarthria, hyporeflexia, neuropathic pain, nystagmus, peroneal nerve palsy, sciatica, sensory disturbance, sinus headache, and speech disorder, each reported in one patient (1%).
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Relapsed or Refractory T-ALL and T-LBL
Pediatrics: The safety profile for children is based on data from 84 pediatric patients enrolled and treated in the COGP9673 study who were treated with the recommended dose and schedule. The most common adverse events in pediatric patients, regardless of causality, were hematologic disorders (anemia, leukopenia, neutropenia and thrombocytopenia). Of the non-hematologic adverse events in pediatric patients, the most frequent events reported were headache, increased transaminase levels, decreased blood potassium, decreased blood albumin, increased blood bilirubin and vomiting.
| Table 4 Most Commonly Reported (≥5% Overall) Adverse Events Regardless of Causality in PEDIATRIC Patients Treated with 650 mg/m2 of ATRIANCE Administered Intravenously Over 1 Hour Daily for 5 Consecutive Days Repeated Every 21 Days | |||||||||
System Organ Class Preferred Term | Percentage of Patients: 650 mg/m2; N = 84 | ||||||||
| Toxicity Grade | |||||||||
Grade 3 % | Grade 4+ % | All Grades % | |||||||
| Blood and Lymphatic System Disorders | |||||||||
| Anemia | 45 | 10 | 95 | ||||||
| Neutropenia | 17 | 62 | 94 | ||||||
| Thrombocytopenia | 27 | 32 | 88 | ||||||
| Leukopenia | 14 | 7 | 38 | ||||||
| Hepatobiliary Disorders | |||||||||
| Transaminases increased | 4 | 0 | 12 | ||||||
| Blood albumin decreased | 5 | 1 | 10 | ||||||
| Blood bilirubin increased | 7 | 2 | 10 | ||||||
| Metabolic/Laboratory | |||||||||
| Blood potassium decreased | 4 | 2 | 11 |
| Blood calcium decreased | 1 | 1 | 8 |
| Blood creatinine increased | 0 | 0 | 6 |
| Blood glucose decreased | 4 | 0 | 6 |
| Blood magnesium decreased | 2 | 0 | 6 |
| Nervous System Disorders (see Table 5) | |||
| Gastrointestinal Disorders | |||
| Vomiting | 0 | 0 | 10 |
| General Disorders & Administration Site Conditions | |||
| Asthenia | 1 | 0 | 6 |
| Infections & Infestations | |||
| Infection | 2 | 1 | 5 |
Grade 4+ = Grade 4 and Grade 5 Three (3) patients had a fatal event. Fatal events included neutropenia and pyrexia (n = 1), status epilepticus/seizure (n = 1), and fungal pneumonia (n = 1). The status epilepticus was thought to be related to treatment with ATRIANCE. All other fatal events were unrelated to treatment with ATRIANCE. | |||
Neurologic Adverse Events
Pediatric: The most common neurologic adverse events regardless of causality, including all grades (NCI Common Toxicity Criteria) are shown in Table for pediatric patients.
| Table 5 Neurologic Adverse Events (≥1%) Regardless of Causality in PEDIATRIC Patients Treated with 650 mg/m2 of ATRIANCE Administered Intravenously Over 1 Hour Daily for 5 Consecutive Days Repeated Every 21 Days | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
Nervous System Disorders Preferred Term | Percentage of Patients; N = 84 | |||||||||||
Grade 1 % | Grade 2 % | Grade 3 % | Grade 4+ % | All Grades % | ||||||||
| Headache | 8 | 2 | 4 | 2 | 17 | |||||||
| Peripheral neurologic disorders, any event | 1 | 4 | 7 | 0 | 12 | |||||||
| Peripheral neuropathy | 0 | 4 | 2 | 0 | 6 | |||||||
| Peripheral motor neuropathy | 1 | 0 | 2 | 0 | 4 | |||||||
| Table 5 Neurologic Adverse Events (≥1%) Regardless of Causality in PEDIATRIC Patients Treated with 650 mg/m2 of ATRIANCE Administered Intravenously Over 1 Hour Daily for 5 Consecutive Days Repeated Every 21 Days |
|---|
Nervous System Disorders Preferred Term | Percentage of Patients; N = 84 |
|---|
Grade 1 % | Grade 2 % | Grade 3 % | Grade 4+ % | All Grades % | |
|---|---|---|---|---|---|
| Peripheral sensory neuropathy | 0 | 0 | 6 | 0 | 6 |
| Somnolence | 1 | 4 | 1 | 1 | 7 |
| Hypoesthesia | 1 | 1 | 4 | 0 | 6 |
| Seizures | 0 | 0 | 0 | 6 | 6 |
| Convulsions | 0 | 0 | 0 | 3 | 4 |
| Grand mal convulsions | 0 | 0 | 0 | 1 | 1 |
| Status epilepticus | 0 | 0 | 0 | 1 | 1 |
| Motor dysfunction | 1 | 1 | 1 | 0 | 4 |
| Nervous system disorder | 1 | 2 | 0 | 0 | 4 |
| Paresthesia | 0 | 2 | 1 | 0 | 4 |
| Tremor | 1 | 2 | 0 | 0 | 4 |
| Ataxia | 1 | 0 | 1 | 0 | 2 |
Grade 4+ = Grade 4 and Grade 5 One (1) patient had a fatal neurologic event, status epilepticus. This event was thought to be related to treatment with ATRIANCE. | |||||
The other grade 3 event in pediatric patients, regardless of causality, was hypertonia reported in 1 patient (1%). The additional grade 4+ events, regardless of causality, were 3rd nerve paralysis, and 6th nerve paralysis, each reported in 1 patient (1%).
The other neurologic adverse events, regardless of causality, reported as grade 1, 2, or unknown in pediatric patients were dysarthria, encephalopathy, hydrocephalus, hyporeflexia, lethargy, mental impairment, paralysis, and sensory loss, each reported in 1 patient (1%).
8.3 Less Common Clinical Trial Adverse Reactions
Other Neurologic Events: There have also been reports of events associated with demyelination and ascending peripheral neuropathies similar in appearance to Guillain-Barré syndrome.
Supportive Data in Newly Diagnosed T-ALL and T-LBL
Adults and pediatrics: ATRIANCE (nelarabine) was studied in newly diagnosed patients with T-ALL and T-LBL in a Phase III clinical trial.
In this Phase III clinical study of patients between 1 and 30 years of age (N=825) with newly diagnosed T-ALL or T-LBL, patients received augmented Berlin-Frankfurt-Münster regimen (aBFM) with or without nelarabine. The safety profile of the treatment groups was consistent with that known for the individual medicinal products. The addition of nelarabine to the aBFM chemotherapy regimen in the T-ALL and T-LBL populations did not significantly alter the safety profile of the aBFM chemotherapy regimen.
8.5 Post-Market Adverse Reactions
The following adverse events have been reported from worldwide marketing experience with Nelarabine. Because these events are reported voluntarily from a population of uncertain size, are associated with concomitant diseases and multiple drug therapies, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Decisions to include these events in labeling are typically based on one or more of the following factors: (1) seriousness of the event, (2) frequency of the reporting, or (3) strength of causal connection to the drug:
Nervous system: Several cases of serious spinal cord disorders including myelopathy, spinal cord ischaemia and myelitis transverse have been reported. These events presented with symptoms including leg weakness, numbness, quadriplegia, fecal incontinence and urinary incontinence.
Cases of leukoencephalopathy have been reported.
Musculoskeletal: Cases of rhabdomyolysis and creatine phosphokinase increased have been reported.
Hepatobiliary: In clinical trials, Grade 3 and 4 elevations in transaminases and bilirubin have occurred. Cases of acute hepatic failure have been reported (including fatal toxic hepatitis), although causality has not been established.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions Fatal neurologic outcomes following concurrent intrathecal chemotherapy and intravenous nelarabine (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, 7 WARNINGS AND PRECAUTIONS, Neurologic). |
9.2 Drug Interactions Overview
No formal drug interaction studies have been carried out with nelarabine.
In a pharmacokinetic study in 13 adult patients receiving 1,200 mg/m2 of nelarabine, fludarabine administration at 30 mg/m2 4 hours prior to nelarabine administration did not affect the plasma pharmacokinetics of nelarabine and ara-G or the intracellular accumulation of ara-GTP in leukemic blasts.
In-vitro studies in human liver microsomes suggest that nelarabine and ara-G did not significantly inhibit the activities of the major hepatic cytochrome P450 (CYP) enzymes CYP1A2, CYP2A6, CYP2B6,
CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4 in vitro at concentrations of nelarabine and ara-G up to 100 μM.
9.3 Drug-Behavioural Interactions
Effects on ability to drive and use machinery
No studies on the effects of nelarabine on the ability to drive and operate machines have been performed. Patients experiencing somnolence, dizziness, neurologic disorders, or any other undesirable effects with a potential impact on the ability to safely drive or use machines should refrain from these activities as long as these undesirable effects persist (see 7 WARNINGS and PRECAUTIONS, 8 ADVERSE REACTIONS).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions.
Table 6 - Established or Potential Drug-Drug Interactions
| Proper/ Common name | Source of Evidence | Effect | Clinical comment | |||
| Drugs that may affect the exposure to nelarabine | ||||||
| Pentostatin | T | There is in vitro evidence that pentostatin is a strong inhibitor of adenosine deaminase. This may result in a reduction in the conversion of the prodrug nelarabine to its active moiety and consequently in a reduction in efficacy of nelarabine and/or change in the adverse event profile of either drug. | Administration of nelarabine in combination with adenosine deaminase inhibitors, such as pentostatin, is not recommended. | |||
Legend: T = Theoretical
No clinical data on drug interactions between ATRIANCE and chemotherapy are available, however there are reports of fatal neurologic outcomes following nelarabine with intrathecal chemotherapy.
In one pharmacokinetic study, fludarabine administered prior to nelarabine did not affect the plasma pharmacokinetics of nelarabine and ara-G or ara-GTP (see 9 DRUG INTERACTIONS, 9.2. Drug Interactions Overview).).
The involvement of cytochrome P450 enzymes in the metabolism of nelarabine has not been investigated.
There are no clinical data on drug-drug interaction between ATRIANCE and hormonal contraceptives. The effect of ATRIANCE on hormonal contraceptives in humans is not known.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Nelarabine is a pro-drug of the deoxyguanosine analogue antimetabolite, 9-β-D-arabinofuranosylguanine (ara-G). Nelarabine is rapidly demethylated by adenosine deaminase (ADA) to ara-G and then phosphorylated intracellularly by deoxyguanosine kinase and deoxycytidine kinase to its 5’-monophosphate. The monophosphate is subsequently converted intracellularly to the active 5’-triphosphate, ara-GTP. Accumulation of ara-GTP in leukemic cells allows for incorporation of ara-GTP into deoxyribonucleic acid (DNA) leading to inhibition of DNA synthesis which results in cell death. Other mechanisms may contribute to the cytotoxic effects of nelarabine. In vitro, T-cells are more sensitive than B-cells to the cytotoxic effects of nelarabine.
10.2 Pharmacokinetics
In a cross-study analysis using data from four Phase I studies, the pharmacokinetics of nelarabine and ara-G were characterized in patients aged less than 18 years and adult patients with refractory leukemia or lymphoma.
Absorption
Plasma ara-G Cmax values generally occurred at the end of the nelarabine infusion and were generally higher than nelarabine Cmax values, suggesting rapid and extensive conversion of nelarabine to ara-G. After infusion of 1,500 mg/m2 nelarabine over two hours in adult patients, mean plasma nelarabine and ara-G Cmax values were 13.9 µM and 115 µM), respectively. Mean plasma nelarabine and ara-G AUC values were 13.5 µM.h and 571 µM.h, respectively, after infusion of 1500 mg/m2. Intracellular Cmax for ara-GTP appeared within 3 to 25 hours on Day 1. Mean intracellular ara-GTP Cmax and AUC values were 95.6 µM and 2214 µM.h at this dose. No pharmacokinetic data are available in pediatric patients at the once daily 650 mg/m2 nelarabine dose.
Distribution:
Nelarabine and ara-G are extensively distributed throughout the body based on combined Phase I pharmacokinetic data at nelarabine doses of 104 to 2,900 mg/m2 in 135 patients with refractory leukemia or lymphoma in four Phase I studies. Specifically, for nelarabine, Vss values were 115 L/m2 and 89.4 L/m2 in adult and pediatric patients, respectively. For ara-G, Vss/F values were 44.8 L/m2 and 32.1 L/m2 in adult and pediatric patients, respectively. Nelarabine volume of distribution (Vss) and ara-G Vss/F were influenced by body surface area (BSA), which supports dosing based on BSA.
Nelarabine and ara-G are not substantially bound to human plasma proteins (less than 25%) in vitro, and binding is independent of nelarabine or ara-G concentrations up to 600 µM.
Metabolism:
The principal route of metabolism for nelarabine is O-demethylation by adenosine deaminase to form ara-G, which undergoes hydrolysis to form guanine. In addition, some nelarabine is hydrolyzed to form methylguanine, which is O-demethylated to form guanine. Guanine is N-deaminated to form xanthine, which is further oxidized to yield uric acid.
Elimination
Pharmacokinetic studies in adult patients with refractory leukemia or lymphoma have demonstrated that nelarabine is rapidly eliminated from plasma with a half-life of approximately 30 minutes. Ara-G is eliminated from plasma at a slower rate than nelarabine, with a half-life of 2.0 and 3.2 hours for pediatric and adult patients, respectively.
Combined Phase 1 pharmacokinetic data at nelarabine doses of 104 to 2900 mg/m2 on Day 1 indicate that geometric mean clearance (CL) values for nelarabine are 138 L/h/m2 and 125 L/h/m2 in adult and pediatric patients, respectively, on Day 1 (n = 65 adults, n = 1 pediatric patients). The apparent clearance of ara-G (CL/F) is comparable between the two groups (9.5 L/h/m2 in adult patients and 10.8 L/h/m2 in pediatric patients) on Day 1. Ara-G CL/F was influenced by body surface area (BSA), which supports dosing based on BSA.
Nelarabine and ara-G are partially eliminated by the kidneys. Mean urinary excretion of nelarabine and ara-G was 5.3% and 23.2% of the administered dose, respectively, in 28 adult patients over the 24 hours after nelarabine infusion on Day 1. Renal clearance averaged 16.4 L/h for nelarabine and 4.9 L/h for ara-G in 21 adult patients. Ara-G clearance (CL/F) was influenced by baseline calculated creatinine clearance (CLcr).
No accumulation of nelarabine or ara-G was observed in plasma after nelarabine administration on either a daily or a day 1, 3, 5 schedule.
Duration of Effect
Intracellular ara-GTP concentrations in leukemic blasts were quantifiable for a prolonged period after nelarabine administration, and the elimination half-life could not be accurately estimated. Intracellular ara-GTP accumulated with repeated administration of nelarabine; on the Day 1, 3, and 5 schedule, Cmax and AUC(0-t) values on Day 3 were approximately 50% and 30%, respectively, greater than Cmax and AUC(0-t) values on Day 1. There is substantial intersubject variability in nelarabine, ara-G, and intracellular ara-GTP pharmacokinetics. Intracellular ara-GTP AUC and Cmax values were higher in patients who responded to treatment with nelarabine than in patients who did not respond. Nelarabine and ara-G exposure were not associated with response.
Special Populations and Conditions
Pediatrics (< 18 years of age): No pharmacokinetic data are available in pediatric patients at the once daily 650 mg/m2 nelarabine dosage. Combined Phase 1 pharmacokinetic data at nelarabine doses of 104 to 2,900 mg/m2 on Day 1 indicate that the geometric mean clearance (CL) values for nelarabine are 138 L/h/m2 and 125 L/h/m2 in adult and pediatric patients, respectively, on Day 1 (n = 65 adults, n = 21 pediatric patients). The apparent clearance of ara-G (CL/F) is comparable between the two groups (9.5 L/h/m2 in adult patients and 10.8 L/h/m2 in pediatric patients) on Day 1.
Nelarabine and ara-G are extensively distributed throughout the body. Specifically, for nelarabine, Vss values were 115 L/m2 and 89.4 L/m2 in adult and pediatric patients, respectively. The volume of distribution of ara-G (Vss/F) is 44.8 L/m2 and 32.1 L/m2 in adult and pediatric patients, respectively.
Geriatrics (≥ 65 years of age):Nelarabine and ara-G pharmacokinetics have not been specifically studied in an elderly population. Age has no effect on the pharmacokinetics of
- nelarabine or ara-G. Decreased renal function, which is more common in the elderly, may reduce ara-G clearance (see 7 WARNINGS AND PRECAUTIONS).
- Sex: The effect of gender on nelarabine and ara-G pharmacokinetics has not been specifically studied. In a pharmacokinetic/pharmacodynamic cross-study analysis, nelarabine and ara-G pharmacokinetics were not different between adult male and female patients; however, intracellular ara-GTP Cmax and AUC(0-t) values at the same dose level were 2- to 3- fold greater on average in adult female than in adult male patients. There was no apparent difference in safety or efficacy parameters were observed by gender in clinical trials.
- Ethnic Origin: The effect of race on nelarabine and ara-G pharmacokinetics has not been specifically studied. In a pharmacokinetic/pharmacodynamic cross-study analysis, race (Caucasian/other) had no apparent effect on nelarabine, ara-G, or intracellular ara-GTP pharmacokinetics.
- Hepatic Insufficiency: The influence of hepatic impairment on the pharmacokinetics of nelarabine has not been evaluated.
- Renal Insufficiency: The pharmacokinetics of nelarabine and ara-G have not been specifically studied in renally impaired or hemodialyzed patients. Nelarabine is excreted by the kidney to a small extent (5 to 10% of the administered dose). Ara-G is excreted by the kidney to a greater extent (20 to 30% of the administered nelarabine dose). In a pharmacokinetic/pharmacodynamic cross-study analysis with a limited number of renally impaired patients (n = 2 with CLcr <50 mL/min), baseline calculated creatinine clearance (CLcr) was a significant predictor of ara-G apparent clearance (CL/F). The mean apparent clearance (CL/F) of ara-G was about 7% lower in patients with mild renal impairment (CLcr 50 to 80 mL/min) than in patients with normal renal function (>80 mL/min). Because the risk of adverse reactions to this drug may be greater in patients with decreased renal function (CLcr <50 mL/min), these patients should be closely monitored for toxicities when treated with ATRIANCE (see 4 DOSAGE AND ADMINISTRATION).
11 STORAGE, STABILITY AND DISPOSAL
Store between 15° to 25°C.
12 SPECIAL HANDLING INSTRUCTIONS
Caution should be used during handling, preparation and disposal of nelarabine. Use of gloves and other protective clothing to prevent skin contact is recommended. Proper aseptic technique should be used.
Guidelines on the proper handling and disposal of anticancer drugs should be consulted.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: nelarabine
Chemical name: 2-amino-9-β-D-arabinofuranosyl-6-methoxy-9H-purine
Molecular formula and molecular mass: C11H15N5O5 and 297.27
Structural formula:
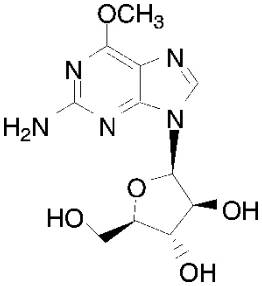
Physicochemical properties: Nelarabine is slightly soluble to soluble in water and melts with decomposition between 209° and 217°C.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The safety and efficacy of ATRIANCE (nelarabine) were evaluated in three open-label, multicentre studies conducted under the sponsorship of the National Cancer Institute of the U.S. National Institutes of Health.
Pediatric clinical study in relapsed or refractory T-ALL and T-LBL
The safety and efficacy of ATRIANCE in pediatric patients were studied in a clinical trial conducted by the Children’s Oncology Group (COG). This study included 151 treated patients 21 years of age and younger, 149 of whom had relapsed or refractory T-cell acute lymphoblastic leukemia (T-ALL) or T-cell lymphoblastic lymphoma (T-LBL). Eighty-four (84) patients, 39 of whom had received two or more prior induction regimens, were treated with 650 mg/m2/day of ATRIANCE administered intravenously over 1 hour daily for 5 consecutive days repeated every 21 days (see Table 7). Patients who experienced signs or symptoms of peripheral neuropathy on therapy were to be evaluated for discontinuation of further therapy with ATRIANCE.
| Table 7 Pediatric Clinical Study - Patient Allocation | |
| Patient Population | N |
| Patients treated at 650 mg/m2/day for 5 days every 21 days | 84 |
| Patients with T-ALL or T-LBL with two or more prior inductions treated at 650 mg/m2/day for 5 days every 21 days | 39 |
Baseline patient and disease characteristics of the 84 patients treated with 650 mg/m2/day of ATRIANCE were consistent with those generally observed for patients with these diseases. Patients ranged in age from 2.5-21.7 years (overall mean, 11.9 years), 52% were 3 to 12 years of age and most were male (74%) and Caucasian (62%). The majority (77%) of patients had a diagnosis of T-ALL.
Adult clinical study in relapsed or refractory T-ALL and T-LBL
The safety and efficacy of ATRIANCE in adult patients were studied in a clinical trial conducted by the Cancer and Leukemia Group B (CALGB). This study included 39 treated patients, 28 of whom were with T-cell acute lymphoblastic leukemia (T-ALL) or T-cell lymphoblastic lymphoma (T-LBL) that had relapsed following or was refractory to at least two prior induction regimens. ATRIANCE 1,500 mg/m2 was administered intravenously over 2 hours on days 1, 3 and 5 repeated every 21 day treatment cycle. Seventeen patients had a diagnosis of T-ALL and 11 had a diagnosis of T-LBL. For patients with ≥2 prior inductions, the age range was 16-65 years (mean 34 years) and most patients were male (82%) and Caucasian (61%). Patients with central nervous system (CNS) disease were not eligible. Patients who experienced grade 2 or greater peripheral neuropathy on therapy were typically discontinued from further therapy with ATRIANCE.
Adult and pediatric clinical study in newly diagnosed T-ALL and T-LBL
The efficacy and safety of ATRIANCE, in combination with an aBFM regimen, were assessed in a randomised Phase III study. Newly diagnosed T-ALL or T-LBL patients between 1 and 30 years of age were enrolled. A total of 825 patients were randomised or assigned to treatment arms with or without ATRIANCE based on risk categorisation following induction treatment and type of disease (T ALL or T-LBL). Out of 702 T-ALL patients, 659 patients were randomised to receive an aBFM regimen with ATRIANCE (N=323) or without ATRIANCE (N=336).
Patients in the ATRIANCE arms received ATRIANCE in 5-day cycles of 650 mg/m2/day added to an aBFM backbone chemotherapy; two cycles were administered during Consolidation, one cycle during Delayed Intensification, and one cycle in each of the first 3 Maintenance treatment phases.
The study was designed to evaluate the potential clinical benefit in event-free survival (EFS) when ATRIANCE is added to an aBFM regimen to treat T-ALL patients following initial remission after Induction phase treatment. EFS in this trial for T-ALL patients was defined as the time to the EFS events. EFS events include any type of relapse, death in remission or second malignant neoplasm.
The median age of T-ALL patients analysed for EFS was 9 to 10 years of age (range: 1 to 29 years). The majority of patients were: between 3 to 12 years of age (~60%), male (~75%) and Caucasian (~70%).
14.2 Study Results
Pediatric clinical study in relapsed or refractory T-ALL and T-LBL
Complete response (CR) in the pediatric clinical study was defined as bone marrow blast counts ≤5%, no other evidence of disease, and full recovery of peripheral blood counts. Complete response with or without full hematologic recovery (CR*) was also assessed as a meaningful outcome in this heavily pretreated population. Duration of CR is reported from date of response to date of relapse, and may include subsequent stem cell transplant. Efficacy results, including survival at one year, are presented in Table 8.
| Table 8 Efficacy Results in Patients 21 Years of Age and Younger at Diagnosis With ≥2 Prior Inductions Treated with 650 mg/m2 of ATRIANCE Administered Intravenously Over 1 Hour Daily for 5 Consecutive Days Repeated Every 21 Days | ||||
| N = 39 | ||||
| CR n (%) [95% CI] | 5 (13%) [4%, 27%] | |||
| CR* n (%) [95% CI] | 9 (23%) [11%, 39%] | |||
| Duration of complete response (range in weeks) ** | 3.3 to 9.3 | |||
| Median overall survival (weeks) [95% CI] | 13.1 [8.7, 17.4] | |||
| Kaplan-Meier Survival estimate at 1 year [95% CI] | 14% [3%, 26%] | |||
CR = Complete response
CR* = Complete response with or without hematologic recovery (includes patients who achieved a CR) ** Does not include 5 patients who were transplanted or had subsequent systemic chemotherapy) duration of response in these 5 patients was 4.7 to 42.1 weeks).
The mean number of days on therapy was 46 days (range of 7 to 129 days). Time to complete response ranged from 3.4 to 12 weeks and median time to CR* was 3.4 weeks (95% CI: 3.0, 3.7).
Adult clinical study in relapsed or refractory T-ALL and T-LBL
Complete response (CR) in the adult clinical study was defined as bone marrow blast counts ≤5%, no other evidence of disease, and full recovery of peripheral blood counts. Complete response with or without complete hematologic recovery (CR*) was also assessed as a meaningful outcome in this heavily pretreated population. The results of the study for patients who had received ≥2 prior inductions are shown in Table 9.
| Table 9 Efficacy Results in Adult Patients With ≥2 Prior Inductions Treated with 1,500 mg/m2 of ATRIANCE Administered Intravenously Over 2 Hours on Days 1, 3, and 5 Repeated Every 21 Days | |||||
| N = 28 | |||||
| CR n (%) [95% CI] | 5 (18%) [6%, 37%] | ||||
| CR* n (%) [95% CI] | 6 (21%) [8%, 41%] | ||||
| Duration of complete response (range in weeks)** | 15 to 195+ | ||||
| Median overall survival (weeks) [95% CI] | 20.6 weeks [10.4, 36.4] | ||||
| Kaplan-Meier Survival estimate at 1 year [95% CI] | 29% [12%, 45%] | ||||
CR = Complete response
CR* = Complete response with or without hematologic recovery (includes patients who achieved a CR)
** Does not include 1 patient who was transplanted (duration of response was 156+ weeks)
The mean number of days on therapy was 56 days (range of 10 to 136 days). Time to complete response and time to CR* ranged from 2.9 to 11.7 weeks.
Adult and pediatric clinical study in newly diagnosed T-ALL and T-LBL
The addition of ATRIANCE to an aBFM regimen resulted in a 31% reduction in the risk of having an event (i.e. death, secondary malignancy or relapse) in the T-ALL population, with a HR of 0.691 (90% CI: 0.486, 0.981), p=0.081. Median EFS was not reached in either treatment group. The 4-year EFS rate was 88.9% in the ATRIANCE with aBFM treatment group and 83.5% in the aBFM treatment group.
EFS in T-LBL patients was an exploratory objective. The study was not powered to detect a difference in EFS between the ATRIANCE and no-ATRIANCE treatment groups in T-LBL patients. Nine patients (15.0%) in the ATRIANCE treatment group and 10 patients (16.4%) in the no-ATRIANCE treatment group had an EFS event (HR of 0.947, 90% CI: 0.445, 2.016). Median EFS was not reached in either treatment group. The 4-year EFS rate was 86.5% in the ATRIANCE with aBFM treatment group and 86.6% in the aBFM treatment group.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
No pre-clinical safety pharmacology studies were performed to investigate the effects of nelarabine on vital organ systems (cardiovascular, respiratory, central nervous system).
General Toxicology:
Repeat Dose Toxicity: The potential toxicity of nelarabine was investigated in repeat dose intravenous studies of 5 days duration in mice at doses of 600 to 1800 mg/m2/day and ketamine-sedated cynomolgus monkeys at doses of 720 to 3600 mg/m2/day and for 30 days duration in the non-sedated monkey at doses of 120 to 480 mg/m2/day.
In the mouse, no clinical signs of neurotoxicity were seen. Furthermore, no macroscopic changes were observed at necropsy.
A dose limiting neurotoxicity characterized by seizures, muscle tremor and weakness, incoordination, ataxia, depth perception deficits, and unresponsiveness occurred in male and female cynomolgus monkeys given ≥720 mg/m2/day for 5 days or at ≥240 mg/m2/day for up to 30 days. No neurotoxicity occurred in monkeys given 120 mg/m2/day for 30 days.
The onset of clinical neurotoxicity was dose-dependent, beginning immediately after the dosing period in individual monkeys given 3600 mg/m2/day for 5 days, as late as post dose day 10 and 13, in monkeys given 720 or 1800 mg/m2/day, respectively for 5 days, and on Day 19, in monkeys given 240 or 480 mg/m2/day for 30 days. Clinical neurotoxicity was completely reversible after 5 days of dosing and after 30 days of dosing at 240 mg/m2/day, but only partially reversible at 480 mg/m2/day given for 23 days. Within 3 weeks after dosing was stopped, in monkeys given 480 mg/m2/day for 23 days, muscle tremors lessened and general body condition improved; however, clinical neurotoxicity had not completely resolved by the end of the two month recovery period. No histopathologic lesions were observed in central or peripheral nervous system tissues of monkeys given nelarabine for 5 days. Histopathologic changes evident as white matter degeneration and vacuolation in brain and spinal cord were noted in 3 of 10 monkeys dosed at 480 mg/m2/day for 23 days. These CNS lesions occurred only at 480 mg/m2/day and were still present two months after dosing was stopped. Neurotoxicity generally correlated with greater systemic exposure to ara-G.
The clinical neurotoxicity seen in monkeys given nelarabine for 5 or 30 days was qualitatively similar to that seen in humans at therapeutic doses.
The major findings from 5 and 30 day repeat dose studies in monkeys indicate that nelarabine targeted the mitotically active cells in bone marrow, lymphoid organs, and intestinal tract. The incidence and severity of the toxicity was dose-and time-dependent and all effects reversed during recovery.
Decreases in total white blood cell values, chiefly due to a neutropenia and monocytopenia, occurred at all doses in monkeys given nelarabine at ≥720 mg/m2/day for 5 or ≥120 mg/m2/day for 30 days. Decreases in red blood cell counts and platelet counts also occurred but at higher doses. No clinically detectable bleeding accompanied the decrease in platelet count. Hypocellular bone marrow was seen only in monkeys given 3600 mg/m2/day over 5 days. All changes reversed during the recovery period with a rebound leukocytosis seen in individual monkeys.
Thymus weights were reduced at 30 days in females at ≥120 mg/m2/day and at ≥240 mg/m2/day in males. This effect was reversible, as thymus weights had returned to normal by the time of the recovery necropsy. Monkeys with low thymus weights had normal peripheral lymphocyte counts.
Histopathologic changes in mitotically active tissues were seen in three (of four) monkeys given 3600 mg/m2/day for 5 days. Findings included lymphoid depletion of cervical and mesenteric lymph nodes, splenic involution, thymic atrophy, hypocellular bone marrow, and intestinal epithelial cell maturation arrest. Another female monkey dosed at 3600 mg/m2/day had no histopathologic abnormalities after a 60 day recovery period, indicating these lesions were reversible.
Effects on mitotically active tissues in monkeys, as evidenced by decreased RBC, WBC, neutrophils, and platelets, were qualitatively similar to those observed in humans at therapeutic dose levels.
Genotoxicity:
Like other drugs in the nucleoside analogue class, nelarabine was mutagenic in the microtiter version of the L5178Y/TK+/- mouse lymphoma mutagenesis assay in the presence and absence of rat liver S9 metabolic activation. Significant increases in mutant frequency were observed when cells were treated for (i) three hours in the absence of S9 metabolic activation and (ii) three hours in the presence of S9 metabolic activation at concentrations up to 5000 mcg/mL nelarabine. Since nelarabine and other nucleoside analogs are known genotoxic agents, administration of nelarabine to patients should be considered on an individual case basis, following a risk-benefit evaluation.
Reproductive and Developmental Toxicology:
Compared to controls, nelarabine caused increased incidences of fetal malformations, anomalies, and variations in rabbits when given via 8-hour intravenous infusions at doses ≥354 mg/m2/day (approximately 24% of the adult dose on a mg/m2 basis) during days 7 to 19 of gestation. Cleft palate was seen in rabbits given 3,540 mg/m2/day (approximately 2-fold the adult dose), absent pollices in rabbits given ≥1,180 mg/m2/day (approximately 79% of the adult dose) while absent gall bladder, absent accessory lung lobes, fused or extra sternebrae and delayed ossification was seen at all doses. Maternal body weight gain and fetal body weights were reduced in rabbits given 3,540 mg/m2/day (approximately 2-fold the adult dose). The number of corpora lutea, implantation sites, live fetuses, dead fetuses, sex ratio, and pre implantation losses were unaffected by the administration of nelarabine.
No studies have been conducted in animals to assess effects on fertility. However, no adverse effects were seen in the testes or ovaries of monkeys given nelarabine intravenously at doses up to 480 mg/m2/day (approximately 32% of the adult dose on a mg/m2 basis) for 30 consecutive days. The effect on human fertility is unknown.