


Product Monograph - Benlysta (Glaxosmithkline, 120 mg, 400 mg, 200 mg)
Recent Major Label Changes
| Section | Date |
|---|---|
| 2025- |
| 2025- |
| 2025- |
| 2025- |
| 2025- |
| 2025- |
| 2025- |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................... 2
Table of Contents .................................................................................................................... 2
Part 1: Health Professional Information ................................................................................... 5
- 1.
Indications ................................................................................................................... 5
1.1. Pediatrics ................................................................................................................. 5
1.2. Geriatrics ................................................................................................................. 5
- 2. Contraindications ......................................................................................................... 5
- 3. Serious Warnings and Precautions Box ........................................................................ 5
- 4.
Dosage and Administration .......................................................................................... 6
4.1. Dosing Considerations ............................................................................................. 6
4.2. Recommended Dose and Dosage Adjustment ........................................................ 6
4.3. Reconstitution ......................................................................................................... 8
4.4. Administration ......................................................................................................... 9
4.5. Missed Dose .......................................................................................................... 10
- 5. Overdosage ................................................................................................................ 10
- 6. Dosage Forms, Strengths, Composition and Packaging ............................................... 10
- 7.
Warnings and Precautions .......................................................................................... 11
General ............................................................................................................................ 12
Carcinogenesis and Mutagenesis .................................................................................... 12
Driving and Operating Machinery ................................................................................... 12
Immune ........................................................................................................................... 12
Neurologic ....................................................................................................................... 13
Psychiatric ....................................................................................................................... 13
Sensitivity ........................................................................................................................ 13
7.1. Special Populations ............................................................................................... 14
7.1.1. Pregnant Women .................................................................................................. 14
7.1.2. Breast-feeding ....................................................................................................... 14
7.1.3. Pediatrics ............................................................................................................... 15
7.1.4. Geriatrics ............................................................................................................... 15
- 8.
Adverse Reactions ...................................................................................................... 15
8.1. Adverse Reaction Overview ................................................................................... 15
8.2. Clinical Trial Adverse Reactions ............................................................................. 15
8.2.1. Clinical Trial Adverse Reactions – pediatrics .......................................................... 21
8.3. Less Common Clinical Trial Adverse Reactions ...................................................... 22
8.5. Post-Market Adverse Reactions ............................................................................ 22
- 9.
Drug Interactions ....................................................................................................... 22
9.2. Drug Interactions Overview .................................................................................. 22
- 10.
Clinical Pharmacology ................................................................................................ 22
10.1. Mechanism of Action............................................................................................. 22
10.2. Pharmacodynamics ............................................................................................... 22
10.3. Pharmacokinetics .................................................................................................. 23
10.4. Immunogenicity .................................................................................................... 28
- 11. Storage, Stability and Disposal ................................................................................... 29
- 12. Special Handling Instructions ..................................................................................... 29
Part 2: Scientific Information ................................................................................................. 30
- 13. Pharmaceutical Information ....................................................................................... 30
- 14.
Clinical Trials .............................................................................................................. 31
14.1. Clinical Trials by Indication .................................................................................... 31
Systemic Lupus Erythematosus (SLE) .............................................................................. 31
Lupus Nephritis ............................................................................................................... 43
- 15. Microbiology .............................................................................................................. 48
- 16. Non-Clinical Toxicology .............................................................................................. 48
Patient Medication Information - Intravenous ...................................................................... 52
Patient Medication Information - Autoinjector ...................................................................... 59
INSTRUCTIONS FOR USE – Autoinjector ................................................................................. 67
Part 1: Health Professional Information
1. Indications
BENLYSTA is indicated in addition to standard therapy for:
- reducing disease activity in adult and pediatric patients aged 5 years and older with active, autoantibody-positive, systemic lupus erythematosus (SLE).
- treatment of active lupus nephritis in adult and pediatric patients aged 5 years and older.
The safety and efficacy of BENLYSTA have not been evaluated in patients with severe active central nervous system lupus.
The efficacy of BENLYSTA in SLE patients of Black African heritage has not been clearly established.
1.1. Pediatrics
Pediatrics (< 5 years of age): BENLYSTA is not indicated in patients under 5 years of age [see 14. Clinical Trials]. The use of intravenous BENLYSTA in pediatric lupus nephritis patients 5 to 17 years of age and the use of subcutaneous BENLYSTA in SLE patients 5 to 17 years of age and from > 15 kg bodyweight is supported by model-based extrapolation.
1.2. Geriatrics
Although data are limited, dosage adjustment is not recommended in patients > 65 years of age (see 10.3. Pharmacokinetics).
2. Contraindications
BENLYSTA is contraindicated in patients who are hypersensitive to belimumab (e.g., have demonstrated anaphylaxis) or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing see 6. Dosage Forms, Strengths, Composition and Packaging.
- 3. Serious Warnings and Precautions Box
Serious Warnings and Precautions
Infusion/Injection-Related Systemic Reactions and Hypersensitivity, including Anaphylaxis
Administration of BENLYSTA may result in infusion or injection-related systemic reactions and hypersensitivity reactions, which can be severe or fatal. Serious infusion reactions and serious anaphylaxis/hypersensitivity have been observed uncommonly (see 7. Warnings and Precautions, General, Infusion/Injection-Related Systemic Reactions and Hypersensitivity).
Severe and sometimes fatal Infections, including Progressive Multifocal Leukoencephalopathy (PML)
Severe infections, including PML have been reported in patients receiving BENLYSTA, and other immune-modulating therapies for the treatment of SLE. Some cases were fatal (see7. Warnings and Precautions, Immune, and 8. Adverse Reactions, Infections, and 8.5 Post-Market Adverse Drug Reactions).
Psychiatric Disorders: Depression and suicidality have been reported in trials with BENLYSTA. Patients should be instructed to contact their healthcare provider if they experience new or worsening depression, or suicidal thoughts/behaviour (See 7. Warnings and Precautions, Psychiatric, and 8. Adverse Reactions, Clinical Trial Adverse Reactions, Psychiatric Disorders).
4. Dosage and Administration
Where instructions are specific to either the intravenous infusion or subcutaneous injection, this administration route is specifically named under each subheading below.
4.1. Dosing Considerations
Discontinuation of treatment with BENLYSTA in SLE should be considered if there is no improvement in disease control after 6 months of treatment.
In active lupus nephritis, BENLYSTA should be used in combination with corticosteroids and mycophenolate or cyclophosphamide for induction, or mycophenolate or azathioprine for maintenance. The patient’s condition should be evaluated continuously.
4.2. Recommended Dose and Dosage Adjustment
Intravenous Administration
Systemic Lupus Erythematosus or Lupus Nephritis
Adults and Children (5 to 17 years of age):
The recommended dosage regimen is 10 mg/kg at 2-week intervals for the first three doses and at 4-week intervals thereafter. BENLYSTA should be infused over a 1-hour period. The infusion rate may be slowed or interrupted if the patient develops an infusion reaction. The infusion must be discontinued immediately if the patient experiences a potentially life-threatening infusion reaction (see 2. Contraindications and 7. Warnings and Precautions).
The use of BENLYSTA in pediatric lupus nephritis patients 5 to 17 years of age and > 15 kg bodyweight is supported by model-based extrapolation (see 10.3. Pharmacokinetics).
The safety and efficacy of BENLYSTA in children below 5 years of age have not been established. Therefore, BENLYSTA is not indicated in patients under 5 years of age.
Premedication Recommendations
Premedication with an oral antihistamine, with or without an antipyretic, may be administered before the infusion of BENLYSTA (see 7. Warnings and Precautions).
Subcutaneous injection
Systemic Lupus Erythematosus
Adults:
The recommended dosage is 200 mg once weekly. Subcutaneous dosing in adults is not based on weight.
Children (5 to 17 years of age):
The recommended dosage regimen for children aged 5 to 17 years of age is based on the patient’s weight as shown below. For patients under 10 years of age, BENLYSTA must be administered by a healthcare professional or trained caregiver.
Body Weight
Recommended Dosage
≥ 50 kg
200 mg subcutaneous injection once weekly
30 to < 50 kg
200 mg subcutaneous injection once every 10 days
15 to < 30 kg
200 mg subcutaneous injection once every 2 weeks
The safety and efficacy of subcutaneous BENLYSTA in children below 5 years of age or less than 15 kg have not been established. Therefore, subcutaneous belimumab is not indicated for use in children under 5 years old or less than 15 kg with SLE.
Lupus Nephritis
Adults:
In adult patients initiating therapy for lupus nephritis (see 14. Clinical Trials), the recommended dosage regimen is a 400 mg dose (two 200 mg injections) once weekly for 4 doses, then 200 mg once weekly thereafter. In patients not requiring induction therapy for lupus nephritis, the recommended dosage is 200 mg once weekly.
The efficacy and safety of 200 mg administered subcutaneously in patients with active lupus nephritis is based on data from administration of 10 mg/kg intravenously (see Intravenous Administration) and pharmacokinetic modelling and simulation (see 10. Clinical Pharmacology).
Children (5 to 17 years of age):
The safety and efficacy of subcutaneous BENLYSTA in children below 18 years of age have not been established. Therefore, subcutaneous BENLYSTA is not indicated for use in children under 18 years old with active lupus nephritis.
Transitioning from Intravenous Therapy to Subcutaneous Therapy
If a patient with SLE is being transitioned from BENLYSTA intravenous therapy to BENLYSTA subcutaneous therapy, administer the first subcutaneous dose of 200 mg 1 to 4 weeks after the last intravenous dose (see 10.3. Pharmacokinetics).
If a patient with lupus nephritis is being transitioned from BENLYSTA intravenous therapy to BENLYSTA subcutaneous therapy, administer the first subcutaneous dose 1 to 2 weeks after the last intravenous dose. This transition can or may occur any time after the patient completes the first 2 intravenous doses (see 10.3. Pharmacokinetics).
4.3. Reconstitution
Table 1 Reconstitution of lyophilized powder for intravenous infusion
| Vial Size | Volume of Diluent to be Added to Vial | Nominal Concentration per mL Upon Reconstitution | Volume Upon Final Dilution | |
| 120 mg as lyophilized powder in 5 mL vial | 1.5 mL Sterile Water for Injection, USP | 80 mg/mL* | Patients with bodyweight > 40 kg: 250 mL Patients with bodyweight < 40 kg: 100 mL | |
| 400 mg as lyophilized powder in 20 mL vial | 4.8 mL Sterile Water for Injection, USP | |||
*The reconstituted solution must be further diluted to 250 mL or 100 mL in 0.9% Sodium Chloride Injection, USP (normal saline), depending on patient’s bodyweight. See instructions provided below in Preparation of Solutions for details.
Preparation of Solutions
BENLYSTA is provided as a lyophilized powder in a single-use vial for intravenous infusion after reconstitution and dilution. BENLYSTA does not contain a preservative; therefore reconstitution and dilution must be carried out under aseptic conditions as follows:
- 1. Allow 10 to 15 minutes for the vial to warm to room temperature.
- 2.
Reconstitute the BENLYSTA powder with Sterile Water for Injection, USP (sterile water), as follows. The reconstituted solution will contain a concentration of 80 mg/mL belimumab.
- • Reconstitute 120 mg in 5 mL vial with 1.5 mL sterile water.
- • Reconstitute 400 mg in 20 mL vial with 4.8 mL sterile water.
- 3. The stream of sterile water should be directed toward the side of the vial to minimize foaming. Gently swirl the vial for 60 seconds. Allow the vial to sit at room temperature during reconstitution, gently swirling the vial for 60 seconds every 5 minutes until the powder is dissolved. DO NOT SHAKE. Reconstitution is typically complete within 10 to 15 minutes after the sterile water has been added, but it may take up to 30 minutes. Protect the reconstituted solution from direct sunlight.
- 4. If a mechanical reconstitution device (swirler) is used to reconstitute BENLYSTA, it should not exceed 500 rpm and the vial swirled for no longer than 30 minutes.
- 5. Once reconstitution is complete, the solution should be opalescent and colourless to pale yellow, and without particles. Small air bubbles, however, are expected and acceptable.
- 6.
Dilute the reconstituted product to 250 mL in 0.9% Sodium Chloride Injection, USP (normal saline) for IV infusion. For patients whose body weight is less than or equal to 40 kg, dilute the reconstituted product to 100 mL in 0.9% Sodium Chloride Injection, USP (normal saline) for IV infusion providing that the resulting BENLYSTA concentration in the infusion bag does not exceed 4 mg/mL. 5% Dextrose IV solutions are incompatible with BENLYSTA and should not be used. From a 250-mL (or 100 mL) infusion bag or bottle of normal saline, withdraw and discard a volume equal to the volume of the reconstituted solution of BENLYSTA required for the patient’s dose. Then add the required volume of the reconstituted solution of BENLYSTA into the infusion bag or bottle. Gently invert the bag or bottle to mix the solution. Any unused solution in the
- vials must be discarded.
- 7. Inspect the solution of BENLYSTA visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Discard the solution if any particulate matter or discoloration is observed.
- 8. The reconstituted solution of BENLYSTA, if not used immediately, should be stored protected from direct sunlight and refrigerated at 2° to 8°C. Solutions of BENLYSTA diluted in normal saline may be stored at 2° to 8°C or room temperature. The total time from reconstitution of BENLYSTA to completion of infusion should not exceed 8 hours.
- 9. No incompatibilities between BENLYSTA and polyvinylchloride or polyolefin bags have been observed.
4.4. Administration
Intravenous Administration
BENLYSTA vials for intravenous infusion must be reconstituted and diluted prior to administration (see Preparation of Solutions). Do not administer as an intravenous push or bolus.
BENLYSTA should be administered in an appropriate setting by qualified healthcare providers trained to give infusion therapy and prepared to treat hypersensitivity, including anaphylaxis. Monitor patients during and for an appropriate amount of time after administration of BENLYSTA (see 7. Warnings and Precautions).
The intravenous infusion of the diluted solution of BENLYSTA should be administered over a period of 1 hour.
It is recommended that a 21-25 gauge needle be used when piercing the vial stopper for reconstitution and dilution.
BENLYSTA should not be infused concomitantly in the same intravenous line with other agents. No physical or biochemical compatibility studies have been conducted to evaluate the co-administration of BENLYSTA with other agents.
Subcutaneous injection
Autoinjectors must NOT be used for intravenous injection.
It is recommended that the first subcutaneous injection of BENLYSTA should be under the supervision of a healthcare professional. After an initial training in proper subcutaneous injection technique and education about signs and symptoms of hypersensitivity reactions (see 7. Warnings and Precautions, Infusion/Injection-Related Systemic Reactions and Hypersensitivity), a patient with SLE may self-inject (or the patient caregiver may administer) BENLYSTA if a physician determines that it is appropriate and with medical follow-up as necessary. See also PATIENT MEDICATION INFORMATION and INSTRUCTIONS FOR USE.
- Instruct the patient or patient caregiver to follow the directions for administration provided in the PATIENT MEDICATION INFORMATION and INSTRUCTIONS FOR USE.
- Instruct the patient to remove the autoinjector from the refrigerator and allow it to sit at room temperature for 30 minutes prior to the subcutaneous injection. Do not warm BENLYSTA in any other way.
Prior to administration, instruct the patient or patient caregiver to visually inspect the window of
- autoinjector for particulate matter or discoloration, whenever solution and container permit. BENLYSTA should be clear to opalescent and colorless to pale yellow. Do not use BENLYSTA if the product exhibits discoloration or particulate matter.
- BENLYSTA may be given as a subcutaneous injection in the abdomen or thigh. When injecting in the same body region, advise the patient to use a different injection site for each injection; never give injections into areas where the skin is tender, bruised, red, or hard. When a 400 mg dose is administered at the same site, it is recommended that the 2 individual 200 mg injections be administered at least 5 cm (approximately 2 inches) apart.
- Instruct the patient to administer BENLYSTA as prescribed (once weekly, once every 10 days or once every two weeks), preferably on the same scheduled day of the week (see 4.2. Recommended Dose and Dosage Adjustment).
4.5. Missed Dose
Intravenous Administration
If a dose is missed or the patient is unable to attend appointment for one of the infusions, the missed dose should be administered as soon as possible.
Subcutaneous injection
If a dose is missed, it should be administered as soon as possible. Thereafter, patients can resume dosing on their usual day of administration, or start a new schedule from the day that the missed dose was administered.
5. Overdosage
There is limited experience with overdosage of BENLYSTA. Two doses of up to 20 mg/kg have been given 21 days apart by intravenous infusion to humans with no increase in incidence or severity of adverse reactions compared with doses of 1, 4, or 10 mg/kg.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6. Dosage Forms, Strengths, Composition and Packaging
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number (DIN) and the batch/lot number of the product supplied.
Table 2 – Dosage Forms, Strengths, Composition and Packaging
Dosage Forms
BENLYSTA for intravenous infusion is supplied as a sterile, white to off-white, preservative-free, lyophilized powder for reconstitution, dilution, and intravenous infusion.
BENLYSTA for subcutaneous injection is supplied as a clear to opalescent, colourless to pale yellow solution in the following format:
- A single-dose, 1 mL, pre-filled autoinjector
Packaging
BENLYSTA for intravenous infusion is supplied in single-use glass vials with a latex-free, siliconised rubber stopper and a flip-off aluminium seal, as follows:
- 120 mg belimumab in a 5 mL single-use vial
- 400 mg belimumab in a 20 mL single-use vial
BENLYSTA for subcutaneous injection is supplied as follows:
- 200 mg in a 1-mL single-dose autoinjector with 27-gauge, 12.7 mm needle. Available in packages of 4.
Description
BENLYSTA (belimumab) is a human IgG1λ monoclonal antibody specific for soluble human B Lymphocyte Stimulator protein (BLyS, also referred to as BAFF and TNFSF13B). Belimumab has a molecular weight of approximately 147 kDa. Belimumab is produced by recombinant DNA technology in a mammalian cell expression system.
7. Warnings and Precautions
Please see 3. Serious Warnings and Precautions Box.
Route of Administration (Common Name) | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
Intravenous Infusion (belimumab for injection) | Lyophilized powder for intravenous infusion 120 mg in 5 mL vial 400 mg in 20 mL vial (80 mg/mL after reconstitution) | citric acid monohydrate, polysorbate 80, sodium citrate dihydrate, sucrose |
Subcutaneous Injection (belimumab injection) | Solution for subcutaneous injection 200 mg in 1 mL | L-arginine hydrochloride, L-histidine, L-histidine monohydrochloride, polysorbate 80, sodium chloride, water for injections |
General
BENLYSTA treatment should be initiated and supervised by a qualified physician experienced in the diagnosis and treatment of SLE or lupus nephritis.
Concomitant Use with Other Biologic Therapies
Available data do not support the co-administration of rituximab with BENLYSTA in patients with SLE (see 8. Adverse Reactions, Concomitant Use with Other Biologic Therapies). The safety and efficacy of BENLYSTA in combination with other biologic therapies, including B-cell targeted therapies, have not been established. Therefore, the use of Benlysta is not recommended in combination with biologic therapies.
Carcinogenesis and Mutagenesis
As with other immunomodulating agents, the mechanism of action of BENLYSTA could increase the risk for the development of malignancies. The effect of treatment with Benlysta on the development of malignancies is not known (see 8. Adverse Reactions, Clinical Trial Adverse Reactions).
Driving and Operating Machinery
There have been no studies to investigate the effect of BENLYSTA on driving performance or the ability to operate machinery. No detrimental effects on such activities are predicted from the pharmacology of belimumab. Exercise caution when driving or operating a vehicle or potentially dangerous machinery. The clinical status of the patient and the safety profile of BENLYSTA should be borne in mind when considering the patient's ability to perform tasks that require judgement, motor or cognitive skills.
Immune
Immunization
Live vaccines should not be given for 30 days before, or concurrently with BENLYSTA as clinical safety has not been established. No data are available on the secondary transmission of infection from persons receiving live vaccines to patients receiving BENLYSTA.
Because of its mechanism of action, BENLYSTA may interfere with the response to immunizations. However, in a study evaluating the response to a 23-valent pneumococcal vaccine, overall immune responses to the different serotypes were similar in SLE patients receiving BENLYSTA compared with those not receiving treatment at the time of vaccination. Limited data suggest that BENLYSTA does not significantly affect the ability to maintain a protective immune response to immunizations received prior to administration of BENLYSTA.
Infections
As with other immunomodulating agents, the mechanism of action of belimumab may increase the risk for the development of infections. In controlled clinical studies, fatal infections were uncommon, but occurred more frequently in patients receiving belimumab compared with placebo. Overall, the incidence of serious infections was similar across the belimumab and placebo groups (see 8. Adverse Reactions). Patients who develop an infection while undergoing treatment with belimumab should be monitored closely, and consideration should be given to stopping immunosuppressant therapy. Physicians should exercise caution when considering the use of BENLYSTA in patients with severe or chronic infections.
Progressive Multifocal Leukoencephalopathy (PML)
Progressive multifocal leukoencephalopathy (PML) resulting in neurological deficits, including fatal cases, has been reported in SLE patients receiving immunosuppressant pharmacotherapy, including belimumab. A diagnosis of PML should be considered in any patient presenting with new onset deficits or deterioration in cognition, speech or ocular functions, and/or motor and gait disturbances, and/or seizures. If PML is suspected it should be urgently investigated by a neurologist or other appropriate specialist, considering also CNS lupus in the differential diagnosis. If PML is suspected, immunosuppressant therapy, including BENLYSTA, must be suspended until PML has been excluded. If PML is confirmed, immunosuppressant therapy, including BENLYSTA, must be discontinued.
Neurologic
The safety and efficacy of BENLYSTA have not been evaluated in patients with severe active central nervous system lupus.
Psychiatric
In controlled clinical intravenous and subcutaneous studies, psychiatric disorders (depression, suicidal ideation and behaviour, and self-injury) have been reported more frequently in patients receiving BENLYSTA, including one suicide in a patient receiving 10 mg/kg and one suicide in a patient receiving 1 mg/kg (see 8. Adverse Reactions, Psychiatric Disorders).
Physicians should carefully assess the risk of depression, suicide and self-injury considering the patient’s medical history and current psychiatric status before treatment with BENLYSTA, and continue to monitor patients during treatment. Health professionals should advise patients (and caregivers where appropriate) to contact their healthcare provider in a timely manner if they experience new or worsening psychiatric symptoms. The risk and benefit of continued treatment with BENLYSTA should be carefully assessed for patients who develop such symptoms.
Sensitivity
Infusion/Injection-Related Systemic Reactions and Hypersensitivity
Administration of BENLYSTA may result in infusion or injection-related systemic reactions and hypersensitivity reactions, which can be severe or fatal. In the event of a severe reaction, BENLYSTA administration must be interrupted and appropriate medical therapy administered. Patients with a history of multiple drug allergies or significant hypersensitivity may be at increased risk (see 8. Adverse Reactions).
Infusion or injection-related systemic reactions and hypersensitivity reactions occurred more frequently with the first two doses and tended to decrease with subsequent doses (see 8. Adverse Reactions). Delay in the onset of acute hypersensitivity reactions and recurrence of clinically significant reactions after initial resolution of symptoms following appropriate treatment, have been observed. Patients treated with BENLYSTA should be made aware of these potential risks, the signs and symptoms of such reactions, and the importance of immediately seeking medical attention. Symptoms may include anaphylactic reaction, bradycardia, hypotension, angioedema, and dyspnea. Delayed-type, non-acute hypersensitivity reactions may also occur and include symptoms such as rash, nausea, fatigue, myalgia, headache, and facial edema.
Additional information for intravenous infusion
If administered intravenously, BENLYSTA should be administered in an appropriate setting by qualified healthcare providers trained to give infusion therapy and prepared to treat hypersensitivity, including anaphylaxis. In clinical trials, serious infusion and hypersensitivity reactions affected less than 1% of patients. Delay in the onset of hypersensitivity reactions has been observed. Therefore, patients should be monitored during and for an appropriate period of time after intravenous infusion of BENLYSTA. Premedication with an oral antihistamine, with or without an antipyretic, may be administered before the infusion of belimumab. There is insufficient evidence to determine whether premedication diminishes the frequency or severity of infusion reactions (see 4.1. Dosing Considerations).
The BENLYSTA MONARCH PROGRAM has been established to facilitate the administration of BENLYSTA. The BENLYSTA MONARCH PROGRAM clinics are staffed by qualified healthcare professionals that have been trained in the administration of BENLYSTA. These clinics are available throughout Canada. Information about these clinics and the location of these clinics can be obtained by calling GSK Medical information at: 1-800-387-7374.
7.1. Special Populations
7.1.1. Pregnant Women
There are limited data on the use of BENLYSTA in pregnant women. Post-marketing data from a prospective pregnancy registry have collected pregnancy information in women exposed to BENLYSTA. Due to the small sample size achieved, no definitive conclusions form this registry can be made regarding a potential risk of birth defects following exposure to BENLYSTA.
Immunoglobulin G (IgG) antibodies, including belimumab, can cross the placenta. BENLYSTA should not be used during pregnancy unless the potential benefit justifies the potential risk to the fetus.
If prevention of pregnancy is warranted, women of childbearing potential should use adequate contraception while using BENLYSTA and for at least 4 months after the last BENLYSTA treatment.
Animal studies did not indicate direct or indirect harmful effects with respect to maternal toxicity, pregnancy or embryofetal and post-natal development except for reductions in B-cells in monkey fetuses and reductions in B-cells and IgM in infant monkeys exposed in utero, indicating that belimumab crosses the placental barrier and has a pharmacological effect in fetuses and infants. In infant monkeys, the reductions in B-cells and IgM lasted 3-6 months post-partum (see 16. Non-Clinical Toxicology).
Monitor infants of treated mothers for B-cell reduction and depending upon the results, consider delaying infant vaccination with live viral vaccines. B-cell reduction in infants may also interfere with the response to immunisations (see 7. Warnings and Precautions).
Pregnancy Registry: To monitor maternal-fetal outcomes of pregnant women with lupus exposed to BENLYSTA, a pregnancy registry has been established. Healthcare professionals are encouraged to refer patients, and pregnant women are encouraged to enrol themselves by calling 1-877-311-8972 or visiting https://mothertobaby.org/ongoing-study/benlysta-belimumab/.
7.1.2. Breast-feeding
The safety of BENLYSTA for use during lactation has not been established. There are no data regarding the excretion of belimumab in human milk, or systemic absorption of belimumab after ingestion. Although belimumab was excreted into the milk of cynomolgus monkeys, published literature suggests that human neonatal and infant consumption of breast milk does not result in clinically significant absorption of maternal IgG antibodies into circulation.
It is recommended that a decision should be made about BENLYSTA therapy in breast-feeding mothers, taking into account the importance of breast-feeding to the infant and the importance of the drug to the mother, and any potential adverse effects on the breastfed child from BENLYSTA or from the underlying maternal condition.
7.1.3. Pediatrics
Pediatrics (less than 5 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in this age group [see 14 CLINICAL TRIALS].
7.1.4. Geriatrics
Although data are limited, dosage adjustment is not recommended in patients >65 years of age (see 10.3. Pharmacokinetics).
8. Adverse Reactions
8.1. Adverse Reaction Overview
Clinical trials have been conducted in SLE patients treated with intravenous and subcutaneous BENLYSTA, plus standard therapy. The overall safety profile for patients receiving BENLYSTA intravenously and subcutaneously was similar, with the exception of injection site reaction.
In pre-registration trials, the most common serious adverse events were serious infections (5.7% and 5.2% in the groups receiving intravenous BENLYSTA and placebo, respectively, and 4.1% and 5.4% in the groups receiving subcutaneous BENLYSTA and placebo, respectively). Serious opportunistic infections occurred in <1% of patients receiving intravenous or subcutaneous BENLYSTA, and no patients receiving placebo. Some infections were severe or fatal (see 7. Warnings and Precautions and 8.2. Clinical Trial Adverse Reactions).
The safety of BENLYSTA 10 mg/kg administered intravenously plus standard therapy (n = 224) compared with placebo plus standard therapy (n = 224) was also evaluated in adults with lupus nephritis for up to 104 weeks (see 14. Clinical Trials). The adverse reactions observed were consistent with the known safety profile of intravenous or subcutaneous BENLYSTA plus standard therapy in patients with SLE.
The data presented within Clinical Trial Adverse Reactions therefore reflects the known safety profile as defined in SLE studies, and data from lupus nephritis studies is also presented, where differences exist.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
In three placebo-controlled pre-registration intravenous SLE trials, 674 adult patients received BENLYSTA (10 mg/kg intravenously over a 1-hour period on Days 0, 14, 28, and then every 28 days up to 52 weeks) plus standard therapy, and 675 adult patients received placebo plus standard therapy. In the 674 patients receiving BENLYSTA, treatment was received for up to 52 weeks in 401 patients and up to 76 weeks in 273 patients.
In the intravenous SLE trials, the population receiving BENLYSTA was aged 18 to 71 years, 96% female, and the race distribution was 50% white/Caucasian, 19% Asian, 19% Alaska native/American Indian, and 12% Black/African American; 32% of subjects were Hispanic/Latino ethnicity. The majority of patients were also receiving one or more of the following concomitant treatments for SLE: corticosteroids (83%), antimalarials (66%), immunosuppressives (49%), nonsteroidal anti-inflammatory drugs (NSAIDS, 34%), and angiotensin pathway antihypertensives (24%). More than half of the patients were receiving systemic corticosteroids at doses equivalent to >7.5 mg/day of prednisone (54% of patients receiving BENLYSTA 10 mg/kg and 55% of patients receiving placebo). The proportion of patients who discontinued treatment due to any adverse events was 6.7% for patients receiving BENLYSTA 10 mg/kg and 7.1% for patients receiving placebo. The most common adverse events resulting in discontinuation of treatment (>2 subjects in either treatment group) were lupus nephritis (0.9% BENLYSTA and 1.2% placebo), infections (0.6% BENLYSTA and 1.0% placebo), and infusion reactions (1% BENLYSTA and 0.3% placebo).
In the placebo-controlled pre-registration subcutaneous SLE trial, 556 patients received 200 mg BENLYSTA plus standard therapy once weekly up to 52 weeks, and 280 patients received placebo plus standard therapy (see 14. Clinical Trials). The overall population had a mean age of 39 years (range: 18 to 77), 94% were female, and 60% were white. The majority of subjects were also receiving one or more of the following concomitant treatments for SLE: corticosteroids (87%), antimalarials (70%), immunosuppressants (46%), aspirin (17%), NSAIDs (23%). For subjects who were using steroids, the average prednisone dose was >7.5 mg/day for 60.2% of subjects. The proportion of patients who discontinued treatment due to any adverse reaction during the controlled clinical trial was 7.2% of patients receiving BENLYSTA and 8.9% of patients receiving placebo. The most common adverse reactions resulting in discontinuation of treatment (>2 subjects in either treatment group) were lupus nephritis (0.7% in both arms) and thrombocytopenia (0% for BENLYSTA and 1.1% for placebo).
Table 3 and Table 4 list adverse events, regardless of causality, occurring in at least 1% of patients who received BENLYSTA, and at an incidence at least 1% greater than that observed with placebo, in the three intravenous studies and one subcutaneous SLE controlled clinical study, respectively.
Table 3 Incidence of Adverse Events Occurring in at Least 1% of Adult Patients Treated with BENLYSTA IV Plus Standard therapy and at Least 1% More Frequently Than in Patients Receiving Placebo Plus Standard therapy, in Three Controlled SLE IV Studies*.
| Intravenous Infusion | |||||
| Preferred Term | BENLYSTA 10 mg/kg IV + Standard therapy n= 674 (%) | Placebo IV + Standard therapy n= 675 (%) | |||
| Nausea | 15 | 12 | |||
| Diarrhea | 12 | 9 | |||
| Pyrexia | 10 | 8 | |||
| Nasopharyngitis | 9 | 7 | |||
| Bronchitis | 9 | 5 | |||
| Insomnia | 7 | 5 | |||
| Pain in extremity | 6 | 4 | |||
| Depression | 5 | 4 | |||
| Migraine | 5 | 4 | |||
| Pharyngitis | 5 | 3 | |||
| Cystitis | 4 | 3 | |||
| Leukopenia | 4 | 2 | |||
| Gastroenteritis | 3 | 1 | |||
| Hypokalemia | 3 | 2 | |||
| Dysuria | 3 | 1 | |||
| Neutropenia | 3 | 1 | |||
| Toothache | 3 | 1 | |||
| Pain | 2 | 1 | |||
| Infusion related reaction | 2 | 1 | |||
| Hypertensive crisis | 1 | <1 | |||
| Dysphonia | 1 | 0 | |||
*up to 76 weeks duration
In open-label, single arm, long-term extensions of the three IV studies listed above (see also Table 8), incidences of AEs, related AEs, SAEs, severe AEs, AESI, and AEs that led to study agent discontinuation either declined overall or were generally stable overall from Year 0-1 to Year 10+.
Table 4 Incidence of Adverse Events Occurring in at Least 1% of Adult Patients Treated with BENLYSTA SC Plus Standard therapy and at Least 1% More Frequently Than in Patients Receiving Placebo Plus Standard therapy, in One Controlled SC SLE Study*
| Subcutaneous Injection | |||||
| Preferred Term | BENLYSTA 200 mg SC + Standard therapy n= 556 (%) | Placebo SC + Standard therapy n= 280 (%) | |||
| Headache | 10 | 9 | |||
| Urinary tract infection (bacterial) | 8 | 6 | |||
| Arthralgia | 6 | 4 | |||
| Vulvovaginal mycotic infection | 3 | 1 | |||
| Leukopenia | 2 | 0 | |||
| Leukocyturia | 1 | 0 | |||
| Palpitations | 1 | 0 | |||
| Abdominal pain | 3 | 2 | |||
| Abdominal pain upper | 3 | 2 | |||
| Hepatic steatosis | 1 | 0 | |||
| Dyspepsia | 2 | 1 | |||
| Injection site pain | 2 | <1 | |||
| Injection site erythema | 2 | 0 | |||
| Contusion | 2 | <1 | |||
| Weight increased | 2 | <1 | |||
| Dry eye | 2 | 1 | |||
* Up to 52 weeks duration
Infections
In controlled studies, fatal infections occurred more frequently in patients receiving BENLYSTA compared with placebo. Overall, the incidence of serious infections was similar in patients receiving BENLYSTA compared with placebo. Physicians should exercise caution when considering the use of BENLYSTA in patients with severe or chronic infections. Consider interrupting BENLYSTA therapy in patients who develop a new infection while undergoing treatment with BENLYSTA and monitor these patients closely.
In the three controlled intravenous SLE pre-registration clinical trials, the overall incidence of infections was 70% in patients receiving BENLYSTA compared with 67% in patients receiving placebo. The most frequent infections (>5% of patients receiving BENLYSTA) were upper respiratory tract infection, urinary tract infection, nasopharyngitis, sinusitis, bronchitis, and influenza. Serious infections occurred in 6.0% of patients receiving BENLYSTA and in 5.2% of patients receiving placebo. The most frequent serious infections included pneumonia, urinary tract infection, cellulitis and bronchitis. Infections leading to discontinuation of treatment occurred in 0.7% of patients receiving BENLYSTA and 1.0% of patients receiving placebo. Infections resulting in death occurred in 0.3% (4/1458) of patients receiving BENLYSTA and in 0.1% (1/675) of patients receiving placebo.
In the controlled subcutaneous SLE clinical study (N = 836), the overall incidence of infections was 55% in the group receiving BENLYSTA and 57% in the group receiving placebo. Only bacterial urinary tract infection occurred in at least 3% of patients receiving BENLYSTA and at least 1% more frequently than patients receiving placebo. Serious infections occurred in 4.1% of patients receiving BENLYSTA and 5.4% of patients receiving placebo; serious opportunistic infections accounted for 0.2% and 0% of these, respectively. Infections resulting in death occurred in 0.5% (3/556) of patients receiving BENLYSTA and in no patients receiving placebo (0/280).
In a randomized, double-blind, placebo-controlled, 52-week, post-marketing SLE safety study (BEL115467) of BENLYSTA 10 mg/kg administered intravenously (N = 4,003), serious infections occurred in 3.7% of patients receiving BENLYSTA and in 4.1% of patients receiving placebo. Serious infections leading to discontinuation of treatment occurred in 1.0% of patients receiving BENLYSTA and in 0.9% of patients receiving placebo. Fatal infections occurred in 0.45% (9/2002) of patients receiving BENLYSTA and in 0.15% (3/2001) of patients receiving placebo, while the incidence of all-cause mortality was 0.50% (10/2002) in patients receiving BENLYSTA and 0.40% (8/2001) in patients receiving placebo.
In the randomized, double-blind, placebo-controlled, 104-week trial of active lupus nephritis, adult patients were receiving standard therapy in addition to BENLYSTA administered intravenously (N = 448) (see 14. Clinical Trials). The overall incidence of infections was 82.1% (184/224) in patients receiving BENLYSTA compared with 76.3% (171/224) in patients receiving placebo. Serious infections occurred in 13.8% (31/224) of patients receiving BENLYSTA and in 17.0% (38/224) of patients receiving placebo. Fatal infections occurred in 0.9% (2/224) of patients receiving BENLYSTA and in 0.9% (2/224) of patients receiving placebo.
Infusion/Injection-Related Systemic Reactions and Hypersensitivity
Hypersensitivity reactions and infusion- or injection-related systemic reactions were observed in clinical trials. ‘Hypersensitivity reaction’ covers a group of terms, including anaphylaxis, and can manifest as a range of symptoms including hypotension, angioedema, urticaria or other rash, pruritus, and dyspnea. ‘Infusion/injection-related systemic reaction’ covers a group of terms and can manifest as a range of symptoms including bradycardia, myalgia, headache, rash, urticaria, pyrexia, hypotension, hypertension, dizziness, and arthralgia. Due to overlap in signs and symptoms, it is not possible to distinguish between hypersensitivity reactions and infusion/injection-related systemic reactions in all cases.
Intravenous Infusion
The incidence of infusion reactions, including hypersensitivity reactions, in the three pre-registration intravenous SLE trials was 17% and 15% in the groups receiving intravenous BENLYSTA 10 mg/kg and placebo, respectively. The most common infusion reactions (≥1% of patients receiving intravenous BENLYSTA 10 mg/kg) were headache, nausea, infusion-related reaction (not specified), arthralgia, hypotension, hypertension, and pyrexia. Dermatologic manifestations were reported in 1.8% of patients receiving intravenous BENLYSTA and 1.5% of patients receiving placebo and included events such as urticaria, other rashes, and pruritus. Severe and/or serious infusion or hypersensitivity reactions were reported in 1.2% and 0.6% of subjects receiving intravenous BENLYSTA 10 mg/kg and placebo, respectively. Reactions that led to discontinuation of treatment occurred in 1% and 0.3% of subjects receiving intravenous BENLYSTA 10 mg/kg and placebo, respectively. Infusion reactions were generally observed on the day of the infusion, and occurred more frequently with the first two infusions and tended to decrease with subsequent infusions. Delayed-type, non-acute hypersensitivity reactions have also been observed and included symptoms such as rash, nausea, fatigue, myalgia, headache, and facial oedema. Patients with a history of multiple drug allergies or significant hypersensitivity reactions may be at increased risk. Serious and/or severe hypersensitivity reactions included drug hypersensitivity (not specified), anaphylactic reaction, and angioedema (see 7. Warnings and Precautions). There is insufficient evidence to determine whether premedication diminishes the frequency or severity of infusion reactions. Over 15,000 belimumab infusions were administered in the Phase III clinical studies, with approximately 800 belimumab infusions administered to patients who had been premedicated with an antihistamine and antipyretic at the investigator’s discretion. In these trials, subjects with a history of allergies were more likely to have been premedicated (22%) than subjects without a history of allergies (9%). The proportion of infusions with infusion reactions was numerically greater for premedicated infusions than non-premedicated infusions (3% vs 2%, respectively). However, the incidence of serious and/or severe infusion reactions was 0.1% for non-premedicated infusions while none occurred with premedicated infusions.
Subcutaneous Injection
In the subcutaneous SLE clinical study, the frequency of injection site reactions was 6.1% (34/556) and 2.5% (7/280) for adult patients receiving BENLYSTA and placebo, respectively. These injection site reactions (including pain, erythema, hematoma, pruritus, and induration) were mild to moderate in severity. The majority did not necessitate drug discontinuation. Clinically significant hypersensitivity reactions associated with BENLYSTA administered subcutaneously and requiring permanent treatment discontinuation were reported in 0.2% (1/556) of patients.
Malignancies
The effect of treatment with BENLYSTA on the development of malignancies is not known. In the controlled SLE clinical trials (N=2969) of BENLYSTA administered intravenously (1 mg/kg, 4 mg/kg, 10 mg/kg) or subcutaneously (200 mg) for 52 weeks, malignancies (including non-melanoma skin cancers) were reported in 0.3% (7/2014) of patients receiving BENLYSTA and 0.3% (3/955) of patients receiving placebo. In the controlled clinical trials, malignancies, excluding non-melanoma skin cancers, were observed in 0.2% (4/2014) and 0.2% (2/955) of patients receiving BENLYSTA and placebo, respectively. As with other immunomodulating agents, the mechanism of action of BENLYSTA could increase the risk for the development of malignancies.
Psychiatric Disorders
In the three pre-registration intravenous SLE clinical studies, serious psychiatric events were reported in 1.2% (8/674) of patients receiving belimumab 10 mg/kg and 0.4% (3/675) of patients receiving placebo. Serious depression was reported in 0.6% (4/674) of patients receiving belimumab 10 mg/kg and 0.3% (2/675) of patients receiving placebo. One suicide was reported in a patient receiving belimumab 10 mg/kg (and one was reported in a patient receiving belimumab 1 mg/kg); there were no reports in patients receiving placebo.
In a large post-marketing SLE study (BEL115467) with belimumab 10 mg/kg administered intravenously, serious psychiatric events were reported in 1.0% (20/2002) of patients receiving belimumab and 0.3% (6/2001) of patients receiving placebo. Serious depression was reported in 0.3% (7/2002) of patients receiving belimumab and <0.1% (1/2001) receiving placebo. The overall incidence of serious suicidal ideation or behaviour or self-injury without suicidal intent was 0.7% (15/2002) in the belimumab group and 0.2% (5/2001) in the placebo group. On the Columbia-Suicide Severity Rating Scale (C-SSRS), 2.4% (48/1974) of patients receiving belimumab reported suicidal ideation or behaviour compared with 2.0% (39/1988) of patients receiving placebo. No suicide was reported in either group.
The SLE intravenous studies above did not exclude patients with a history of psychiatric disorders.
In the pre-registration subcutaneous SLE clinical study, which excluded patients with a history of psychiatric disorders, serious psychiatric events were reported in 0.2% (1/556) of patients receiving belimumab and in no patients receiving placebo. There were no serious depression related events or suicides reported in either group. On the C-SSRS, 1.3% (7/554) of patients receiving belimumab reported suicidal ideation or behaviour and 0.7% (2/277) of patients receiving placebo.
Concomitant Use with Other Biologic Therapies
Concomitant Use of Rituximab in Adults: BENLYSTA administered subcutaneously in combination with a single cycle of rituximab was studied in a Phase III, randomized, double-blind, placebo-controlled, 104-week study in adult patients (n=292) with SLE (Study 205646). A higher frequency of adverse events (91.7 % vs. 87.5 %), serious adverse events (22.2 % vs. 13.9 %), serious infections (9.0 % vs. 2.8 %) and post-injection systemic reactions (13.2% vs. 9.7%) were observed in patients treated with BENLYSTA in combination with rituximab as compared to BENLYSTA in combination with placebo.
8.2.1. Clinical Trial Adverse Reactions – pediatrics
Safety data for pediatric patients receiving BENLYSTA intravenously were derived from a 52-week placebo-controlled study in which 53 patients with SLE received intravenous BENLYSTA 10 mg/kg on Days 0, 14, 28, and then every 28 days, on a background of concomitant treatments. The safety profile in pediatric patients receiving BENLYSTA intravenously was consistent with that observed in clinical studies in adult patients.
Infections: Amongst the 5- to 11-year old group, infections were reported in 8 of 10 patients receiving BENLYSTA intravenously and 3 of 3 receiving placebo. Serious infections were reported in 1 of 10 patients receiving BENLYSTA intravenously, and 2 of 3 patients receiving placebo. Amongst the 12- to 17-year old age group, infections were reported in 22 of 43 patients receiving BENLYSTA intravenously and 25 of 37 patients receiving placebo. Serious infections were reported in 3 of 43 patients receiving BENLYSTA intravenously, and 3 of 37 patients receiving placebo, respectively.
Safety data for pediatric patients receiving BENLYSTA subcutaneously were derived from a 52-week open-label study in which 25 patients with SLE received subcutaneous BENLYSTA 200 mg at a set dosing interval based on weight (to achieve comparable exposure to adults), on a background of concomitant treatments. The safety profile in pediatric patients receiving BENLYSTA subcutaneously was consistent with the known safety profile for BENLYSTA.
No clinical trial was conducted in pediatric patients with lupus nephritis. Very limited clinical data was collected in patients who developed lupus nephritis while receiving BENLYSTA intravenously or placebo.
8.3. Less Common Clinical Trial Adverse Reactions
The uncommon adverse reactions are related to infusion reactions, which include: anaphylactic reactions, angioedema, rash, and urticaria.
See 8. Adverse Reactions, Clinical Trial Adverse Reactions, Infusion / Injection-Related Systemic Reactions and Hypersensitivity.
8.5. Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of BENLYSTA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Fatal anaphylaxis (see 7. Warnings and Precautions, Infusion/ Injection-Related Systemic Reactions and Hypersensitivity).
Fatal progressive multifocal leukoencephalopathy (see 7. Warnings and Precautions, Immune).
9. Drug Interactions
9.2. Drug Interactions Overview
Formal drug interaction studies have not been performed with BENLYSTA. Co-administration of steroids and angiotensin-converting enzyme (ACE) inhibitors increased mean clearance of BENLYSTA but the magnitude was within the range of normal variability of clearance.
In clinical trials, concomitant use of mycophenolate, cyclophosphamide, azathioprine, methotrexate, antimalarials, NSAIDs, aspirin, and HMG-CoA reductase inhibitors did not significantly influence the pharmacokinetics of BENLYSTA.
The effect of other biologic therapies, including B-cell targeted therapies, on the pharmacokinetics of BENLYSTA has not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
Belimumab is a B Lymphocyte Stimulator (BLyS)-specific inhibitor that blocks the binding of soluble BLyS, a B-cell survival factor, to its receptor on B-cells. Belimumab does not bind B-cells directly, but by binding BLyS, belimumab inhibits the survival of B-cells, including autoreactive B-cells, and reduces the differentiation of B-cells into immunoglobulin producing plasma cells.
10.2. Pharmacodynamics
In adult patients, in the controlled clinical SLE studies, treatment with either IV or SC formulations of BENLYSTA provided similar results, including effects such as reduced circulating CD19+, CD20+, naïve, transitional, and activated B-cells, plasma cells, plasmacytoid cells, and the SLE B-cell subset at Week 52. Reductions in naïve, plasma and short lived plasma cells as well as the SLE B-cell subset were observed as early as Week 8 and were sustained to Week 52. Memory cells increased initially and slowly declined toward baseline levels by Week 52. The clinical relevance of these effects has not been established.
Treatment of SLE with BENLYSTA also led to reductions in IgG and anti-dsDNA, and increases in complement (C3 and C4). These changes were observed as early as Week 8 and were sustained through Week 52. The clinical relevance of these effects has not been established.
In a long-term uncontrolled SLE extension study, B-cells (including naïve, activated, plasma cells and the SLE B-cell subset) and IgG levels were followed for more than 7 years. A substantial and sustained decrease in various B-cell subsets was observed. A reduction in IgG levels was also observed. Over the course of the study, the reported incidence of AEs generally remained stable or declined.
In adult patients with lupus nephritis, following treatment with BENLYSTA or placebo, there was an increase in serum IgG levels which was associated with decreased proteinuria. Relative to placebo, smaller increases in serum IgG levels were observed with BENLYSTA group as expected with the known mechanism of belimumab. At Week 104, the median percent increase from baseline in IgG was 17% for belimumab and 37% for placebo. Reductions in autoantibodies, increases in complement, and reductions in circulating total B cells and B-cell subsets observed were consistent with the SLE studies.
In Phase II intravenous and subcutaneous SLE clinical studies in pediatric patients, the pharmacodynamic response was consistent with the adult data.
10.3. Pharmacokinetics
SLE
The pharmacokinetic parameters displayed in Table 5 are based on population parameter estimates from 1122 SLE adult patients who received intravenous infusions of belimumab 1 mg/kg (N=559) or 10 mg/kg (N=563); and from 661 adult subjects, comprised of 554 SLE patients and 107 healthy subjects, who received belimumab injected subcutaneously (see 14. Clinical Trials).
Table 5 Population Pharmacokinetic Parameters in Adult Patients After Intravenous Infusion of BENLYSTA 1 mg/kg and 10 mg/kg, or Subcutaneous Administration of BENLYSTA 200 mg weekly
| Pharmacokinetic Parameter | Intravenousa, b BENLYSTA 1 mg/kgc (n = 559) | Intravenousa, b BENLYSTA 10 mg/kg (n = 563) | Subcutaneousa BENLYSTA 200 mg weekly (n= 661) |
|---|---|---|---|
| Peak concentration (Cmax, μg/mL) | 30.1 | 313 | 108 |
| Area under the curve (AUC0-∞, day●μg/mL) | 308 | 3,083 | 726 |
| Distribution half-life (t½, days) | 1.14 | 1.75 | 1.1 |
| Terminal half-life (t½, days) | 12.5 | 19.4 | 18.3 |
| Systemic clearance (CL, mL/day) | 215 | 215 | 204 |
| Volume of distribution (Vss, L) | 3.70 | 5.29 | 4.95 |
a IV population: SLE patients. SC population: 554 SLE, 107 healthy.
b Intravenous infusions were administered at 2-week intervals for the first 3 doses and at 4-week intervals thereafter.
c The 1 mg/kg dose is not recommended
Lupus Nephritis
A population pharmacokinetic analysis was conducted in 224 adult patients with lupus nephritis who received belimumab 10 mg/kg intravenously (Days 0, 14, 28, and then every 28 days up to 104 weeks) plus standard therapy (see 14. Clinical Trials). In patients with lupus nephritis, due to renal disease activity, belimumab clearance was initially higher than observed in SLE studies. After 24 weeks of treatment and throughout the remainder of the trial, belimumab clearance and exposure were similar to that observed in patients with SLE who received belimumab 10 mg/kg intravenously.
Based on population pharmacokinetic modelling and simulation, the average belimumab concentration during the first 12 weeks was predicted to be 78 µg/mL following the subcutaneous 400 mg weekly loading doses for the first 4 doses then 200 mg weekly thereafter, which is similar to the estimated concentration of 89 µg/mL following intravenous administration. In addition, the steady-state average concentrations of subcutaneous administration of belimumab 200 mg once weekly in adults with lupus nephritis are predicted to be similar to those observed in adults with lupus nephritis receiving belimumab 10 mg/kg intravenously every 4 weeks.
Absorption
Following belimumab intravenous infusion over 1 hour, maximum serum concentrations (Cmax) were reached shortly after the completion of infusion. The Cmax was 30.1 µg/mL and 313 µg/mL for 1 mg/kg and 10 mg/kg doses, respectively. AUC0-∞ was 308 µg·day/mL and 3083 µg·day/mL for 1 mg/kg and 10 mg/kg doses, respectively.
Following belimumab weekly subcutaneous administration, the time (Tmax) to reach maximum serum concentration (Cmax) at steady-state was 2.6 days after administration. There were minor fluctuations around the average concentration (Cavg 104 mcg/mL), with Cmax 108 μg/mL and Cmin 97 mcg/mL at steady state. The bioavailability of belimumab was approximately 74%.
Distribution
Belimumab, as a macromolecule, is expected to distribute to plasma and intracellular compartments and have limited distribution to tissues. The volume of distribution of belimumab at steady-state was 56-80 mL/kg based on median body weight of the population (66.3 kg).
Metabolism
Belimumab is a protein for which the expected metabolic pathway is degradation to small peptides and individual amino acids by widely distributed proteolytic enzymes. Classical biotransformation studies have not been conducted.
Elimination
Serum belimumab concentrations declined in a bi-exponential manner. Although increases in creatinine clearance and proteinuria (>2 g/day) increased belimumab clearance, these effects were within the expected range of variability. The effect of renal disease on elimination of belimumab is otherwise unknown.
Transitioning from Intravenous to Subcutaneous Administration
SLE
Based on population pharmacokinetic modelling and simulation, adult and pediatric patients with SLE transitioning from the 10 mg/kg intravenous (IV) dose every 4 weeks to 200 mg subcutaneous (SC) dosing (see 4. Dosage and Administration), using a 1 to 4 week switching interval had steady-state average belimumab concentrations similar to adult and pediatric patients dosed with 10 mg/kg intravenous every 4 weeks.
Lupus Nephritis
Based on population pharmacokinetic modelling and simulation, 1 to 2 weeks after completing the first 2 intravenous doses, adult patients with lupus nephritis transitioning from 10 mg/kg IV to 200 mg SC weekly, are predicted to have steady-state average belimumab serum concentrations similar to patients dosed with 10 mg/kg intravenously every 4 weeks (see 4. Dosage Administration). The safety and efficacy of subcutaneous BENLYSTA in children below 18 years of age with lupus nephritis have not been established.
Special Populations and Conditions
- Pediatrics (5 to 17 years of age): The pharmacokinetic parameters of belimumab administered intravenously are based on population parameter estimates of 53 patients from a Phase II intravenous SLE study in pediatric patients. Following intravenous administration of 10 mg/kg at 2-week intervals for the first three doses and at 4-week intervals thereafter, belimumab exposures were similar between pediatric and adult SLE subjects. A summary of pharmacokinetic parameters in pediatric and adult SLE patients receiving belimumab intravenously are included in Table 6.
- The pharmacokinetic parameters of belimumab administered subcutaneously are based on a population pharmacokinetic analysis of 25 patients from a Phase II pharmacokinetic study in pediatric patients with SLE receiving belimumab subcutaneously and the Phase II study in pediatric patients with SLE receiving belimumab intravenously. Following subcutaneous administration of 200 mg of belimumab in pediatric patients 5 to less than 18 years of age, either weekly (patients weighing ≥ 50 kg), every 10 days (patients weighing 30 to <50 kg) or every 2 weeks (patients weighing 15 to < 30 kg), the steady state average belimumab concentration is estimated to be similar to that of adult SLE subjects following subcutaneous administration of 200 mg belimumab weekly, and similar to that of pediatric SLE subjects following intravenous administration of 10 mg/kg belimumab on Days 0, 14 and 28, and at 4-week intervals thereafter. A summary of pharmacokinetic parameters in pediatric and adult SLE patients receiving belimumab subcutaneously are included in Table 6.
Table 6: Summary of Pharmacokinetic Parameters for Adult and Pediatric SLE Patients
| SLE Population | Dose | Cmax at steady state (µg/mL) | AUC over a dosing interval at steady state (day µg/mL) |
|---|---|---|---|
| Adult IVa | 10 mg/kg on days 0, 14, 28 then Q4W | 313 | 3083 |
| Adult SCa | 200 mg QW | 108 | 726 |
Pediatric IVb 5-11 Years 12-17 Years | 10 mg/kg on days 0, 14, 28 then Q4W | 305 317 | 2569 3126 |
Pediatric SCc 15 kg to <30 kg 30 kg to <50 kg ≥50 kg | 200 mg Q2W 200 mg Q10d 200 mg QW | 119 114 124 | 1438 1051 834 |
aAdult IV and SC values are the population median estimates derived from population PK analyses, and reported in Table 5 bPediatric IV values are the geometric means of the individual exposures estimated for each paediatric patient of study BEL114055, derived from a population PK analysis cPediatric SC values are the geometric means of a simulated pediatric SLE population derived from a population PK analysis | |||
The pharmacokinetics of belimumab in pediatric patients with active lupus nephritis were extrapolated based on a population pharmacokinetic model developed from 224 adults with active lupus nephritis and validated using data from 53 pediatric patients with SLE. With intravenous administration of 10 mg/kg at 2-week intervals for the first three doses and at 4-week intervals thereafter, the simulated belimumab exposures for both the 5 to 11 year old group and the 12 to 17 year old group were comparable to adults with active lupus nephritis. A summary of pharmacokinetic parameters in pediatric and adult LN patients receiving belimumab are included in Table 7.
Table 7: Summary of Pharmacokinetic Parameters for Adult and Pediatric LN Patients
| Lupus-Nephritis Population | Dose | Cmax over the first 12 weeks (µg/mL) | Cavg over the first 12 weeks (µg/mL) |
|---|---|---|---|
| Adult IVa | 10 mg/kg on days 0, 14, 28 then Q4W | 276 | 87 |
| Adult SCb | 400 mg QW for the first 4 doses then 200 mg QW | 104 | 77 |
Pediatric IVa 5-11 Years 12-17 Years | 10 mg/kg on days 0, 14, 28 then Q4W | 201 263 | 61 83 |
aAdult and pediatric IV values are the geometric means of simulated adult and pediatric LN populations derived from a population PK model analysis in adults and extrapolated to children. bAdult SC values are the geometric means of simulated adult LN populations derived from a population PK model-based extrapolation. | |||
The following information is based on the population pharmacokinetic analyses of intravenous and subcutaneous administration of BENLYSTA in adults.
- Geriatrics: Age did not affect belimumab exposure within the overall SLE patients studied; while the majority of subjects were between 18 and 45 years (70% with intravenous dosing; 74% with subcutaneous dosing), limited pharmacokinetic data are available on elderly patients. Less than 2% of the subjects were 65 years or older in the pharmacokinetic analyses.
- Gender: Gender did not significantly influence belimumab pharmacokinetics in the largely female study population (94% with intravenous dosing; 85% with subcutaneous dosing).
- Ethnic Origin: Race did not significantly influence belimumab pharmacokinetics. The racial distribution with intravenous administration was 53% white/Caucasian, 16% Asian, 16% Alaska native/American Indian, and 14% Black/African American. The racial distribution with subcutaneous administration was 61% White, 20% Asian, 11% Black/African American, and 6% Alaska native/American Indian.
- Hepatic Insufficiency: No formal studies were conducted to examine the effects of hepatic impairment on the pharmacokinetics of belimumab. Belimumab has not been studied in patients with severe hepatic impairment. Baseline ALT and AST levels did not significantly influence belimumab pharmacokinetics.
Renal Insufficiency: No formal studies were conducted to examine the effects of renal impairment on the pharmacokinetics of belimumab. During clinical development, belimumab administered intravenously and subcutaneously was studied in a limited number of SLE patients with mild (creatinine clearance ≥60 and <90 mL/min), moderate (creatinine clearance ≥30 and <60 mL/min), or severe (creatinine clearance ≥15 and <30 mL/min) renal impairment: 770 patients with mild renal impairment, 261 patients with moderate renal impairment, and 14 patients with severe renal impairment received belimumab intravenously; 121 patients with
- mild renal impairment and 30 patients with moderate renal impairment received belimumab subcutaneously.
- Body Weight: Following belimumab subcutaneous administration at fixed dose of 200 mg once weekly in adults, subjects with higher body weight had lower systemic belimumab exposure. However, no clinically relevant effect of body weight or body mass index (BMI) on the pharmacokinetics of belimumab was observed. Therefore, no dose adjustment is recommended based on weight or BMI for subcutaneous administration in adult patients. Pediatric SLE patients with lower body weight have lower belimumab clearance and volume of distribution resulting in increased exposure. Therefore, pediatric patients with lower body weight are dosed less frequently (see 4. Dosage and Administration). The safety and efficacy of subcutaneous BENLYSTA in children below 18 years of age with lupus nephritis have not been established.
10.4. Immunogenicity
In the two controlled Phase III intravenous SLE clinical studies (BLISS-76 and BLISS-52), anti-belimumab antibodies were detected in 4 of 563 (0.7%) adult patients receiving BENLYSTA 10 mg/kg and in 27 of 559 (4.8%) patients receiving BENLYSTA 1 mg/kg. The reported frequency for the group receiving 10 mg/kg may underestimate the actual frequency due to lower assay sensitivity in the presence of high drug concentrations. Neutralizing antibodies were detected in three patients receiving BENLYSTA 1 mg/kg. Three patients with anti-belimumab antibodies experienced mild infusion reactions of nausea, erythematous rash, pruritus, eyelid edema, headache, and dyspnea; none of the reactions were serious. The clinical relevance of the presence of anti-belimumab antibodies is not known.
In the subcutaneous SLE study (BLISS-SC), there was no formation of anti-belimumab antibodies in 553 adult patients who received BENLYSTA 200 mg SC once weekly dose during the 52-week placebo-controlled period.
In the Phase III lupus nephritis study with BENLYSTA 10 mg/kg administered intravenously (BEL114054), none of the 224 adult patients developed anti-belimumab antibodies during the 104 week, placebo-controlled period.
In a Phase II intravenous SLE clinical study in pediatric patients, none of the 53 patients developed anti-belimumab antibodies.
In a Phase II subcutaneous SLE clinical study in pediatric patients, none of the 25 patients developed anti-belimumab antibodies.
The data reflect the percentage of patients whose test results were positive for antibodies to belimumab in specific assays. The observed incidence of antibody positivity in an assay is highly dependent on several factors, including assay sensitivity and specificity, assay methodology, sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies to belimumab with the incidence of antibodies to other products may be misleading.
11. Storage, Stability and Disposal
Lyophilized powder for intravenous infusion
Store vials of BENLYSTA refrigerated between 2° to 8°C. Vials should be protected from direct sunlight and stored in the original carton until use. Do not freeze. Avoid exposure to heat. Do not use beyond the expiration date.
Reconstituted solution
After reconstitution with sterile Water for Injection, the reconstituted solution, if not used immediately, should be protected from direct sunlight, and stored refrigerated at 2° to 8°C.
Reconstituted and diluted solution for infusion
Solutions of BENLYSTA diluted in normal saline may be stored at 2° to 8°C or room temperature.
The total time from reconstitution of BENLYSTA to completion of infusion should not exceed 8 hours.
Solution for subcutaneous injection in autoinjector
Store between 2°C and 8°C.
Do not freeze.
Protect from light. Store in the original carton until use. Keep out of sight and reach of children.
The pre-filled autoinjector must be administered within 12 hours once the pack is opened. Discard if not administered within 12 hours.
12. Special Handling Instructions
There are no special handling instructions.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Proper name: belimumab
Chemical name: immunoglobulin G1, anti-(human cytokine BAFF) (human monoclonal LymphoStat-B heavy chain) disulfide with human monoclonal LymphoStat B light-chain, dimer
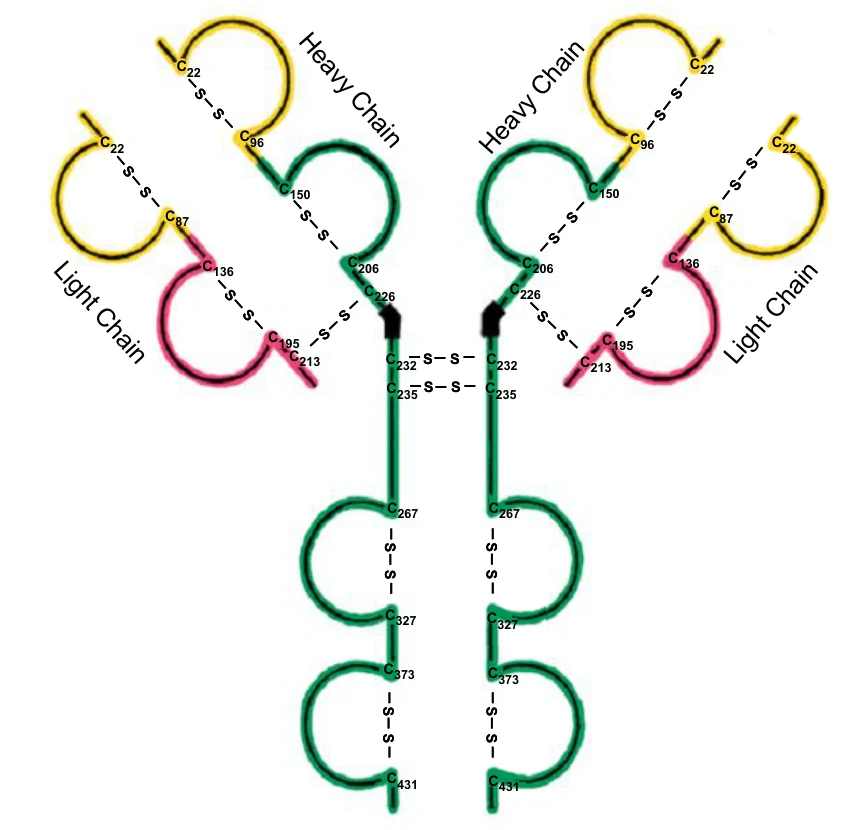
Molecular formula and molecular mass: Belimumab has a molecular formula of C6358H9904N1728O2010S44 prior to post-translational modifications and disulfide bond formation. It contains 1332 amino acid residues and has an approximate molecular weight of 147 kilodaltons.
Structural formula: Belimumab is a human IgG1λ immunoglobulin and consists of two heavy chains of 452 amino acids and two light chains of 214 amino acids.
Physicochemical properties: Belimumab bulk drug substance is clear to opalescent, colorless to pale yellow solution with a concentration of approximately 105 mg/mL (for IV infusion) / 225 mg/mL (for SC injection) and an osmolality of approximately 333 mOsm/kg (for IV infusion) / 307 mOsm/kg (for SC injection) in a formulation buffer of pH 6.5(for IV infusion) / pH 6 (for SC injection).
Product Characteristics
Belimumab is produced by mammalian cells (NS0 mouse myeloma) in serum-free cell culture production medium. Belimumab is secreted into cell culture medium during cell culture production, recovered from the medium and purified using a series of chromatographic and filtration steps.
BENLYSTA for intravenous infusion consists of a sterile, lyophilized formulation in single-use vials to be reconstituted with sterile Water for Injection (WFI not supplied) for intravenous infusion. Upon reconstitution with sterile WFI, each vial contains 80 mg/mL solution of belimumab with formulation buffer (citric acid, sodium citrate, sucrose, polysorbate 80) in either 120 mg (5 mL) or 400 mg (20 mL) single-use vials.
BENLYSTA for subcutaneous injection consists of a clear to opalescent, colourless to pale yellow solution in a single-use autoinjector with 12.7 mm 27G stainless steel needle. Each autoinjector delivers 200 mg belimumab (with L-arginine hydrochloride, L-histidine, L-histidine monohydrochloride, polysorbate 80, sodium chloride, water for injection) in 1 mL (200 mg/mL).
14. Clinical Trials
14.1. Clinical Trials by Indication
Systemic Lupus Erythematosus (SLE)
Study Design
A summary of clinical trials conducted in patients with SLE is presented in Table 8.
Table 8 Summary of Patient Demographics for Clinical Trials in Adult and Pediatric Patients with SLE
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age ± SD (Range) | Gender |
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age ± SD (Range) | Gender |
| LBSL02 | Dose ranging, multicentre, double-blind, parallel-group, placebo-controlled, randomized study | Treatment period (52 weeks): Belimumab 1 mg/kg 4 mg/kg 10 mg/kg or placebo Extension period (24 weeks): Placebo to 10 mg/kg 1 to 1 mg/kg 1 to 10 mg/kg 4 to 4 mg/kg 4 to 10 mg/kg 10 to 10 mg/kg (every 28 days) | Treatment period N=114 N=111 N=111 N=113 Extension period N=88 N=19 N=65 N=24 N=64 N=85 | 42.2±11.2 (20-75) | Female: 419 (93.3%) |
| BEL112626/ LBSL99 | Multi-centre, open-label, continuation study | Belimumab 10 mg/kg (every 28 days); for up to 3970 days | N=298 10 mg/kg | 43 ± 11.6 (20-75) | Female: 276 (93.2%) |
| (median 3303 days) | |||||
BLISS-76 HGS1006-C1056 | Multicentre, double-blind, placebo-controlled, randomized study | Belimumab 1 mg/kg or 10 mg/kg, or placebo on days 0, 14, 28, and then every 28 days); primary endpoint assessed at 52 weeks, trial continued to 76 weeks | 1 mg/kg: N=271 10 mg/kg: N=273 Placebo: N=275 | 40.2 ± 11.5 (18-73) | Female: 764 (93.3%) |
BEL112233 HGS1006-C1066 | Multi-centre, open-label continuation trial | Belimumab 1 mg/kg and/or 10 mg/kg (every 28 days); for up to 2908 days (median 2167 days) | N=268 1 mg/kg and/or 10 mg/kg | 43 ± 11.33 (21-72) | Female: 250 (93%) |
BLISS-52 HGS1006-C1057 | Multicentre, double-blind, placebo-controlled, randomized study | Belimumab 1 mg/kg and/or 10 mg/kg (on days 0, 14, 28, and then every 28 days) up to 52 weeks | 1 mg/kg: N=288 10 mg/kg: N=290 Placebo: N=287 | 35.5 ± 11.1 (18-71) | Female: 821 (94.9%) |
BEL112234 HGS1006-C1074 | Multi-centre, open-label, continuation study | Belimumab 1 mg/kg and/or 10 mg/kg (every 28 days); for up to 2674 days (median 1740days) | N=504, 1 mg/kg and/or 10 mg/kg | 37.2 ± 11.2 (18-75) | Female: 695 (94.6%) |
BLISS-SC HGS1006-C1115; BEL112341 | Multicentre, double-blind, placebo-controlled, randomized study | 200 mg in 1mL pre-filled syringe, weekly subcutaneous dosing, 52 weeks. | N=836 BENLYSTA: n=556 Placebo: n=280 | 39± (12.29) (18-77) | Female: 789 (94.4%) |
BEL114055 (pediatrics) PLUTO | Multi-centre, double-blind, placebo-controlled, | Belimumab IV 10 mg/kg on days 0, 14, 28, and then every 28 days) up | 10 mg/kg: N=53 Placebo: N=40 | 14.0 ± 2.49 (6-17) | Female: 88 (94.6%) |
Adults – Intravenous Infusion
The safety and efficacy of BENLYSTA administered intravenously were evaluated in three randomized, double-blind, placebo-controlled studies including 2133 adult patients with SLE according to the American College of Rheumatology criteria (Study LBSL02, BLISS-76, and BLISS-52 see Table 8); those patients with severe active lupus nephritis and severe active CNS lupus were excluded. Patients were stable on a standard therapy SLE treatment regimen including any of the following (alone or in combination): corticosteroids, antimalarials, NSAIDS, and immunosuppressives. Use of other biologics and intravenous cyclophosphamide were not permitted.
LBSL02 enrolled 499 patients and evaluated doses of 1, 4, and 10 mg/kg BENLYSTA plus standard therapy compared with placebo plus standard therapy over 52 weeks in patients with SLE. Patients had to have a SELENA-SLEDAI score >4 at baseline and a history of autoantibodies (anti-nuclear antibody (ANA) and/or anti-double-stranded DNA (anti-dsDNA), but 28% of the population was autoantibody negative at baseline. The co-primary endpoints were percent change in SELENA-SLEDAI score at week 24 and time to first flare over 52 weeks. No significant differences between any of the BENLYSTA groups and the placebo group were observed. Exploratory analysis of this study identified a group of patients (72%), who were autoantibody positive, and in whom BENLYSTA appeared to offer benefit. The results of this study informed the design of studies BLISS-76 and BLISS-52 and led to the selection of a target population and indication that is limited to autoantibody-positive SLE patients.
In BLISS-76 and BLISS-52 eligible patients had active SLE disease, defined as a SELENA-SLEDAI score ≥6 and positive anti-nuclear antibody (ANA or anti-dsDNA) test results (ANA titre ≥1:80 and/or a positive anti-dsDNA [≥30 units/mL]) at screening. Patients were on a stable standard therapy SLE treatment regimen consisting of any of the following (alone or in combination): corticosteroids, antimalarials, NSAIDs, and/or immunosuppressives. In the studies, patients were not required to be treated with each of these drugs; the choice of agent or agents was based on clinical judgment. Patients were excluded from the study if they had ever received treatment with any B-cell targeted agent; if they had received another biologic investigational agent in the previous year; or if they had a positive response to testing for HIV antibody, hepatitis B surface antigen, or hepatitis C antibody. The two studies were similar in design except that BLISS-76 was a 76-week study and BLISS-52 was a 52-week study, but in both studies the primary efficacy endpoint was determined at 52 weeks. 268 subjects from BLISS-76 entered an open label extension study for a median of 2167 days, receiving a median of 67 (± 26.4) BENLYSTA infusions.
BLISS-76 was conducted primarily in North America and Western Europe. The racial distribution was 70% white/Caucasian, 14% Black/African American, 13% Alaska native/American Indian, and 3% Asian; 21% of subjects were of Hispanic/Latino ethnicity.
BLISS-52 was conducted in South America, Eastern Europe, Asia, and Australia. The racial distribution was 38% Asian, 26% white/Caucasian, 32% Alaska native/American Indian, and 4% Black/African American; 49% of subjects were of Hispanic/Latino ethnicity.
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age ± SD (Range) | Gender |
| randomised, 52-week Phase II study | to 52 weeks | ||||
The concurrent SLE medications allowed were controlled with provision for adjustments early in the trial and protocol outlined restrictions or prohibitions after specified study visits for each category of medication. This provision permitted subjects an opportunity to have their disease activity managed with medication adjustments optimized while minimizing unnecessary subject requests for withdrawal for lack of efficacy or mild disease flares.
Patient mean age across both studies was 38 years (range: 18 to 73 years), and the majority (94%) were female. Baseline concomitant medications included corticosteroids (BLISS-76:76%, BLISS-52: 96%), immunosuppressives (BLISS-76: 56%, BLISS-52: 42%; including azathioprine, methotrexate and mycophenolate), and antimalarials (BLISS-76: 63%, BLISS-52: 67%). Most patients (>70%) were receiving 2 or more classes of SLE medications.
In BLISS-76 and BLISS-52, more than 50% of patients had 3 or more active organ systems at baseline. The most common active organ systems at baseline based on SELENA SLEDAI were mucocutaneous (82% in both studies); immunologic (BLISS-76: 74%, BLISS-52: 85%); and musculoskeletal (BLISS-76: 73%, BLISS-52: 59%). Less than 16% of patients had some degree of renal activity and less than 7% of patients had activity in the vascular, cardio-respiratory, or CNS systems.
At screening, patients were stratified by disease severity based on their SELENA-SLEDAI score (<9 vs ≥10), proteinuria level (<2 g/24 hr vs ≥2 g/24 hr), and race (African or Indigenous-American descent versus other), and then randomly assigned to receive BENLYSTA 1 mg/kg, BENLYSTA 10 mg/kg, or placebo in addition to standard therapy. The patients were administered study medication intravenously over a 1-hour period on Days 0, 14, 28, and then every 28 days for 48 weeks in BLISS-52 and for 72 weeks in BLISS-76.
The primary efficacy endpoint was a composite endpoint (SLE Responder Index) that defined response as meeting each of the following clinically relevant criteria at Week 52 compared with baseline:
- ≥4-point reduction in the SELENA-SLEDAI score, and
- no new British Isles Lupus Assessment Group (BILAG) A organ domain score or 2 new BILAG B organ domain scores, and
- no worsening (<0.30-point increase) in Physician’s Global Assessment (PGA) score.
The SLE Responder Index uses the SELENA-SLEDAI score as an objective measure of reduction in global disease activity; the BILAG index to ensure no significant worsening in any specific organ system; and the PGA to ensure that improvements in disease activity are not accompanied by worsening of the subject’s condition overall.
Adults - Subcutaneous Injection
The safety and efficacy of BENLYSTA administered subcutaneously were evaluated in a randomized, double-blind, placebo-controlled study including 836 adult patients with SLE according to the American College of Rheumatology criteria. Patients were randomised in a 2:1 ratio to receive BENLYSTA 200 mg or placebo subcutaneously once weekly for 52 weeks (BLISS-SC, see Table 8).
The trial was conducted in the US, South America, Europe and Asia.
Patients were stable on a standard therapy SLE treatment regimen including any of the following (alone or in combination): corticosteroids (86%), antimalarials (69%), NSAIDS, and immunosuppressives (46%; including azathioprine, methotrexate, and mycophenolate). In some countries, treatment with a B-cell-targeted agent was permitted if received a year or more prior to baseline, otherwise, treatment with a B-cell-targeted agent was not permitted. Patients were excluded from the trial if they were currently receiving other biologic agents. Anti-tumor necrosis factor therapy, intravenous cyclophosphamide, interleukin-1 receptor antagonist, intravenous immunoglobulin (IVIG), prednisone >100 mg/day, and plasmapheresis were not permitted within the previous 3 months or during the trial.
Patients had to have a Safety of Estrogens in Lupus Erythematosus National Assessment-Systemic Lupus Erythematosus Disease Activity Index (SELENA-SLEDAI) score of ≥8 and positive autoantibody test (anti-nuclear antibody [ANA] and/or anti-double-stranded DNA [anti-dsDNA]) results at screening.
Patients were excluded from the study if they had severe active central nervous system lupus or severe active lupus nephritis, or if they had a positive response to testing for HIV antibody, hepatitis B surface antigen, or hepatitis C antibody. The primary efficacy endpoint was a composite endpoint (SLE Responder Index or SRI) that defined response as meeting each of three criteria (SELENA-SLEDAI, Physician’s Global Assessment, BILAG) at Week 52 compared with baseline (see detail presented in the intravenous section above).
Secondary efficacy endpoints included time to first severe flare (as measured by the modified SLE Flare Index) and the proportion of subjects whose average prednisone dose has been reduced by ≥25% from baseline to ≤7.5 mg/day during weeks 40 through 52. A health outcomes endpoint included mean change in the Functional Assessment of Chronic Illness Therapy (FACIT)-Fatigue Scale score at week 52.
Patient median age was 37 years (range: 18 to 77 years), and the majority (94.4%) were female. More than 50% of patients had 3 or more active organ systems at baseline. The most common active organ systems at baseline based on SELENA-SLEDAI were mucocutaneous (87.9%), musculoskeletal (78.5%), and immunologic (75.7%). Overall, 11.8% of patients had some degree of renal activity and less than 15% of patients had activity in the vascular (7.7%), cardio-respiratory (5.6%), or CNS systems (1.1%). Patients were stratified by disease severity based on their SELENA-SLEDAI score (≤9 and ≥10), complement level (C3 and/or C4 low vs. other), and race (black vs. other), and then randomly assigned to receive BENLYSTA 200 mg subcutaneously weekly or placebo in addition to standard therapy. Baseline concomitant medications included corticosteroids (86%), antimalarials (69%), and immunosuppressives (46% including azathioprine, methotrexate, and mycophenolate). Most patients (approximately 80%) were receiving 2 or more classes of SLE medications.
Pediatrics - Intravenous Infusion
The safety and efficacy of BENLYSTA was evaluated in a randomised, double-blind, placebo-controlled 52-week Phase II study (BEL114055) in 93 pediatric patients. Eligible patients were aged 5-17 years with a clinical diagnosis of SLE according to the American College of Rheumatology classification criteria (see Table 8). Patients had active SLE disease, defined as a SELENA-SLEDAI score greater than or equal to 6 and positive anti-auto antibodies at screening as defined in the adult trials. Patients were on a stable SLE treatment regimen (standard of care) and had similar inclusion and exclusion criteria as the adult studies. This study was conducted in the US, South America, Europe, and Asia.
Pediatrics - Subcutaneous Injection
The safety and efficacy of BENLYSTA administered subcutaneously to paediatric patients 5 to < 18 years of age with active SLE is supported by a population pharmacokinetic model and simulation integrating data from an open-label pharmacokinetic study of 25 paediatric patients with active SLE administered BENLYSTA subcutaneously (200908), and a study of paediatric patients with active SLE administered BENLYSTA intravenously (PLUTO) (See 10.3. Pharmacokinetics, Special Populations and Conditions).
Study Results
Adults - Intravenous Infusion
In both BLISS-76 and BLISS-52, the proportion of SLE patients achieving an SRI response, as defined for the primary endpoint, was significantly higher in the BENLYSTA 10 mg/kg group than in the placebo group. The effect on the SRI was not consistently significantly different for the BENLYSTA 1 mg/kg group relative to placebo in both trials. The 1 mg/kg dose is not recommended. The trends in comparisons between the treatment groups for the rates of response for the individual components of the endpoint were generally consistent with that of the SRI (Table 9). At week 76 in BLISS-76, the SRI response rate with BENLYSTA 10 mg/kg was not significantly different from that of placebo (39% and 32%, respectively).
The reduction in disease activity seen in the SRI was related primarily to improvement in the most commonly involved organ systems namely, mucocutaneous, musculoskeletal, and immunology.
Table 9 Clinical Response Rate in Patients with SLE After 52 Weeks of Treatment
| Response1 | BLISS-76 | BLISS-52 | ||||
|---|---|---|---|---|---|---|
Placebo + Standard therapy (n = 275) | BENLYSTA 1 mg/kg + Standard therapy2 (n = 271) | BENLYSTA 10 mg/kg + Standard therapy (n = 273) | Placebo + Standard therapy (n = 287) | BENLYSTA 1 mg/kg + Standard therapy2 (n = 288) | BENLYSTA 10 mg/kg + Standard therapy (n = 290) | |
| SLE Responder Index | 34% | 41% (p = 0.104) | 43% (p = 0.021) | 44% | 51% (p = 0.013) | 58% (p < 0.001) |
| Odds Ratio (95% CI) vs. placebo | 1.3 (0.9, 1.9) | 1.5 (1.1, 2.2) | 1.6 (1.1, 2.2) | 1.8 (1.3, 2.6) | ||
| Components of SLE Responder Index | ||||||
| Percent of patients with reduction in SELENA-SLEDAI ≥4 | 36% | 43% | 47% | 46% | 53% | 58% |
| Percent of patients with no worsening by BILAG index | 65% | 75% | 69% | 73% | 79% | 81% |
| Percent of patients with no worsening by PGA | 63% | 73% | 69% | 69% | 79% | 80% |
1Patients dropping out of the study early or experiencing certain increases in background medication were considered as failures in these analyses. In both studies, a higher proportion of placebo patients were considered as failures for this reason as compared to the BENLYSTA groups.
2The 1 mg/kg dose is not recommended.
There were too few males or patients over 65 years of age enrolled in the controlled clinical trials to draw meaningful conclusions about the effects of gender or age, on clinical outcomes.
Effect in Black/African Patients: Exploratory subgroup analyses of SRI response rate in patients of Black race were performed. In BLISS-76 and BLISS-52 combined, the SRI response rate in Black patients (N=148) in the BENLYSTA groups was less than that in the placebo group (22/50 or 44% for placebo, 15/48 or 31% for BENLYSTA 1 mg/kg, and 18/50 or 36% for BENLYSTA 10 mg/kg). In LBSL02, Black patients (N=106) in the BENLYSTA groups did not appear to have a different response than the rest of the study population. Although no definitive conclusions can be drawn from these subgroup analyses, caution should be used when considering BENLYSTA treatment in SLE patients of Black African heritage since efficacy has not been clearly established.
Effect on Concomitant Steroid Treatment: In BLISS-76 and BLISS-52, 46% and 69% of patients, respectively, were receiving prednisone at doses > 7.5 mg/day at baseline. The proportion of patients able to reduce their average prednisone dose by at least 25% to ≤7.5 mg/day during Weeks 40 through 52 was not consistently significantly different for BENLYSTA relative to placebo in both studies. In BLISS-76, 17% of patients receiving BENLYSTA 10 mg/kg and 19% of patients receiving BENLYSTA 1 mg/kg achieved this level of steroid reduction compared with 13% of patients receiving placebo. In BLISS-52, 19%, 21%, and 12% of patients receiving BENLYSTA 10 mg/kg, BENLYSTA 1 mg/kg, and placebo, respectively, achieved this level of steroid reduction.
Effect on Severe SLE Flares: The probability of experiencing a severe SLE flare, as defined by a modification of the SELENA Trial flare criteria which excluded severe flares triggered only by an increase of the SELENA-SLEDAI score to >12, was calculated for both BLISS-76 and BLISS-52. The proportion of patients having at least 1 severe flare over 52 weeks was not consistently significantly different for BENLYSTA relative to placebo in both studies. In BLISS-76, 18% of patients receiving BENLYSTA 10 mg/kg and 16% of patients receiving BENLYSTA 1 mg/kg had a severe flare compared with 24% of patients receiving placebo. In BLISS-52, 14%, 18%, and 23% of patients receiving BENLYSTA 10 mg/kg, BENLYSTA 1 mg/kg and placebo, respectively, had a severe flare.
Effect in Higher Disease Activity: Univariate and multivariate analysis of the primary endpoint in pre-specified subgroups demonstrated that the greatest benefit was observed in patients with higher disease activity including patients with SELENA SLEDAI scores ≥ 10, patients requiring steroids to control their disease, and patients with low complement levels.
Post-hoc analysis has identified high responding subgroups such as those patients with low complement and positive anti-dsDNA at baseline, see Table 10. Of these patients, 64.5% had SELENA SLEDAI scores ≥ 10 at baseline.
Table 10 Patients with low complement and positive anti-dsDNA at baseline
| Subgroup | Anti-dsDNA positive AND low complement | ||||
|---|---|---|---|---|---|
| BLISS-76 and BLISS-52 pooled data | Placebo (n=287) | BENLYSTA 10 mg/kg (n=305) | |||
SRI response rate at Week 52 (%) Observed treatment difference vs placebo (%) | 31.7 | 51.5 (p<0.0001) 19.8 | |||
SRI response rate (excluding complement and anti-dsDNA changes) at Week 52 (%) Observed treatment difference vs placebo (%) | 28.9 | 46.2 (p<0.0001) 17.3 | |||
Severe flares over 52 weeks Patients experiencing a severe flare (%) Observed treatment difference vs placebo (%) Time to severe flare [Hazard ratio (95% CI)] | 29.6 | 19.0 10.6 0.61 (0.44, 0.85) (p=0.0038) | |||
FACIT-fatigue score improvement from baseline at Week-52 (mean) Observed treatment difference vs placebo (mean difference) | 1.99 | 4.21(p=0.0048) 2.21 | |||
| BLISS-76 Study only | Placebo (n=131) | BENLYSTA 10 mg/kg (n=134) | |||
SRI response rate at Week-76 (%) Observed treatment difference vs placebo (%) | 27.5 | 39.6 (p=0.0160) 12.1 | |||
Adults - Subcutaneous Injection
The proportion of patients achieving an SRI response was statistically significantly higher in patients receiving BENLYSTA subcutaneously compared with placebo. The rates of response for the individual components of the endpoint were consistent with that of the SRI and all 3 were statistically significantly higher in patients receiving BENLYSTA (Table 11).
Table 11 Clinical Response Rate in Patients with SLE after 52 Weeks of Treatment
| Responsea | Placebo + Standard therapy (n = 279) | BENLYSTA + Standard therapy (n = 554) |
|---|---|---|
| SLE Responder Indexb | 48.4 | 61.4 P = 0.0006 |
Odds Ratio (95% CI) vs. placebo | 1.68 (1.25, 2.25) | |
| Components of SLE Responder Index | ||
| Percent of patients with reduction in SELENA-SLEDAI ≥4 | 49.1% | 62.3% P = 0.0005 |
Odds Ratio (95% CI) vs. placebo | 1.69 (1.26, 2.27) | |
| Percent of patients with no worsening by PGA | 72.8% | 81.2% P = 0.0061 |
Odds Ratio (95% CI) vs. placebo | 1.61 (1.15, 2.27) | |
| Percent of patients with no worsening by BILAG index | 74.2% | 80.9% P = 0.0305 |
Odds Ratio (95% CI) vs. placebo | 1.46 (1.04, 2.07) | |
a Analyses excluded any subject missing a baseline assessment for any of the components (1 for placebo; 2 for BENLYSTA).
b Patients dropping out of the trial early or experiencing certain increases in background medication were considered as failures in these analyses. A higher proportion of placebo patients were considered as failures for this reason as compared with the groups receiving BENLYSTA.
The reduction in disease activity seen in the SRI was related primarily to improvement in the most commonly involved organ systems namely, mucocutaneous, musculoskeletal, immunologic, and vascular. Statistically significant differences in the SRI response were observed by week 16 and sustained through week 52 (Figure 1).
Figure 1 Proportion of SRI Responders by Visit
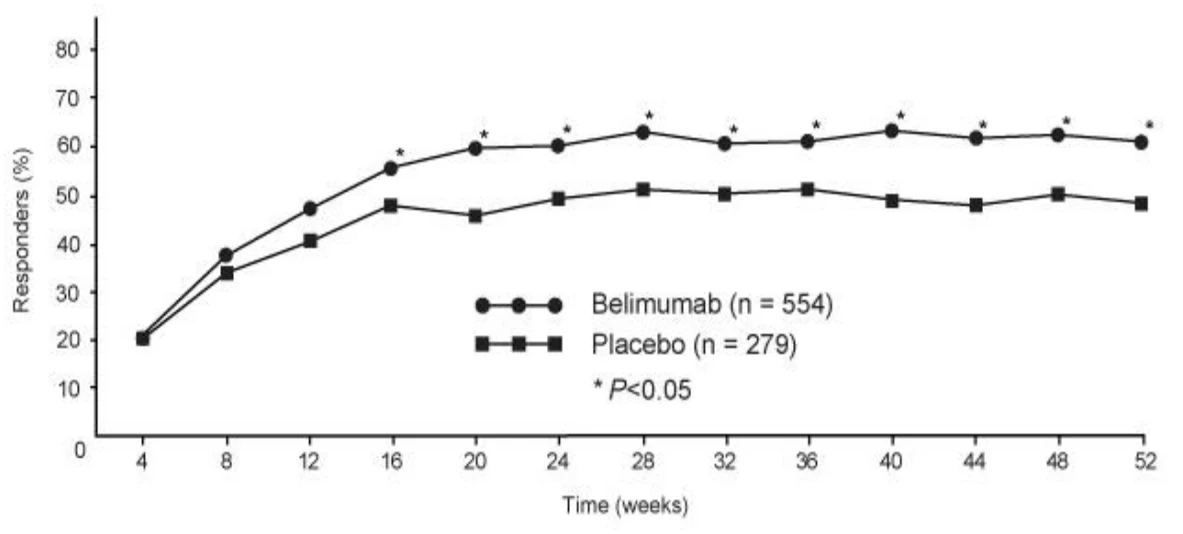
Effect on Severe SLE Flares: A severe flare in SLE was defined by the modified SELENA SLEDAI SLE Flare Index where the modification excludes severe flares that are triggered only by an increase of the SELENA SLEDAI score to >12. The proportion of patients reporting at least 1 severe flare during the study was lower in patients treated with BENLYSTA (10.6%) compared with those receiving placebo (18.2%). Patients treated with BENLYSTA had a 49% lower risk of experiencing at least 1 severe flare during the 52 weeks of observation, relative to the patients receiving placebo (HR = 0.51 [95% CI: 0.35, 0.74]; P =0.0004). Of the patients experiencing a severe flare, the median time to the first severe flare was delayed in patients receiving BENLYSTA compared with placebo (171 days vs.118 days).
Effect on Concomitant Steroid Treatment: At baseline, 60% of patients in both groups were receiving prednisone at doses >7.5 mg/day (or equivalent). Among these patients, 18.2% of patients receiving BENLYSTA were able to reduce their average prednisone dose by at least 25% to ≤7.5 mg/day during Weeks 40 through 52 compared with 11.9% of patients on placebo (OR = 1.65 [95% CI: 0.95, 2.84]; P = 0.0732). Regardless of baseline prednisone dose, fewer patients in the BENLYSTA treatment group than the placebo group had increases in prednisone at week 52 (OR=0.55 [95% CI: 0.34-0.87]; P = 0.0117); this difference was statistically significant starting from Week 20 to Week 52, with the exception of Week 32.
Effect on Fatigue: BENLYSTA demonstrated improvement in fatigue compared with placebo as measured by the FACIT Fatigue Scale score. The mean improvement in FACIT-Fatigue Scale score from baseline to week 52 was significantly greater with BENLYSTA (4.4) compared with placebo (2.7); (P=0.0130). Among patients receiving BENLYSTA, 44.4% of patients experienced improvement in FACIT-Fatigue Scale score exceeding the minimally important clinical difference (improvement greater than or equal to 4) at week 52 compared with 36.1% of patients receiving placebo (P=0.0245).
Effect in Higher Disease Activity: Subgroup analysis of the primary endpoint demonstrated that the greatest benefit was observed in patients with higher disease activity at baseline, including patients with SELENA SLEDAI scores greater than or equal to 10 or patients requiring steroids to control their disease or patients with low complement levels.
An additional, previously identified serologically active group, those patients with low complement and positive anti-dsDNA at baseline, also demonstrated a greater relative response to BENLYSTA, see Table 12.
Table 12 Patients with low complement and positive anti-dsDNA at baseline
| Subgroup | Anti-dsDNA positive AND low complement | |||
|---|---|---|---|---|
| Subcutaneous Trial Data | Placebo | BENLYSTA 200 mg SC weekly | ||
SRI response rate at Week 52a (%) Observed treatment difference vs placebo (%) | n=108 47.2 | n=246 64.6 (P=0.0014) 17.41 | ||
Severe flares over 52 weeks: Patients experiencing a severe flare (%) Observed treatment difference vs placebo (%) Time to severe flare [Hazard ratio (95% CI)] | (n=108) 31.5 | (n=248) 14.1 17.4 0.38 (0.24, 0.61) (P=< 0.0001) | ||
FACIT-fatigue score improvement from baseline at Week-52 (mean): Observed treatment difference vs placebo (median difference) | (n=108) 2.4 | (n=248) 4.6 (P=0.0324) 2.1 | ||
a Analysis of SRI response rate at Week 52 excluded any subject missing a baseline assessment (2 for BENLYSTA)
Pediatrics – Intravenous Infusion
The primary efficacy endpoint in the pediatric trial (BEL114055) of IV infusion was the SLE Responder Index (SRI) at Week 52 as described in the adult intravenous trials. Due to the rarity of childhood-onset SLE, the sample size in Study BEL114055 was limited, and as a result the study was not statistically powered to detect differences between treatment groups. There was a higher proportion of pediatric patients achieving an SRI response in patients receiving BENLYSTA compared with placebo. The response for the individual components of the endpoint were consistent with that of the SRI (Table 13).
Table 13 Clinical Response Rate in Pediatric Patients with SLE after 52 Weeks of Treatment
| Response | Placebo (n=40) | Belimumab 10 mg/kg (n=53) |
|---|---|---|
| Primary endpoint | ||
SLE Responder Index Odds ratio (95% CI) vs placebo | 43.6% | 52.8% 1.49 (0.64, 3.46) |
| Components of SLE Responder Index | ||
Percent of patients with reduction in SELENA-SLEDAI ³4 Odds ratio (95% CI) vs placebo | 43.6% | 54.7% 1.62 (0.69, 3.78) |
Percent of patients with no worsening by BILAG index Odds ratio (95% CI) vs placebo | 61.5% | 73.6% 1.96 (0.77, 4.97) |
Percent of patients with no worsening by PGA Odds ratio (95% CI) vs placebo | 66.7% | 75.5% 1.70 (0.66, 4.39) |
The estimated hazard ratio for time to first severe flare for BENLYSTA 10 mg/kg compared with placebo was 0.36 (95% CI: 0.15, 0.86). Among patients experiencing a severe flare, the median study day of the first severe flare was Day 113 in the placebo group and Day 150 in the BENLYSTA group. This was consistent with the findings from the adult intravenous clinical trials.
Using the Pediatric Rheumatology International Trials Organisation/American College of Rheumatology (PRINTO/ACR) Juvenile SLE Response Evaluation Criteria, a higher proportion of pediatric patients demonstrated improvement in patients receiving BENLYSTA compared with placebo.
The proportion of patients with at least 50% improvement in any 2 of 5 components and no more than one of the remaining worsening by more than 30% at Week 52 was 32/53 (60.4%) in the BENLYSTA group compared with 14/40 (35.0%) in the placebo group [Observed difference: 25.38; Odds ratio (95% CI) vs Placebo: 2.74 (1.15, 6.54)].
The proportion of patients with at least 30% improvement in 3 of 5 components and no more than one of the remaining worsening by more than 30% at Week 52 was 28/53 (52.8%) in the BENLYSTA group compared with 11/40 (27.5%) in the placebo group [Observed difference: 25.33; Odds ratio (95% CI) vs Placebo: 2.92 (1.19, 7.17)].
The five PRINTO/ACR components were percent change at Week 52 in: Parent’s Global Assessment (Parent GA), PGA, SELENA SLEDAI score, 24-hour proteinuria, and Pediatric Quality of Life Inventory – Generic Core Scale (PedsQL GC) physical functioning domain score.
Lupus Nephritis
Adults
The efficacy and safety of BENLYSTA 10 mg/kg administered intravenously over a 1 hour period on Days 0, 14, 28, and then every 28 days, were evaluated in a 104-week randomized (1:1), double-blind, placebo-controlled, Phase III study (BEL114054) in adult 448 patients with active lupus nephritis (see Table 14).
The patients had a clinical diagnosis of SLE according to American College of Rheumatology (ACR) classification criteria, biopsy proven lupus nephritis Class III, IV, and/or V and had active renal disease at screening requiring standard therapy (corticosteroids with 1) mycophenolate mofetil for induction and maintenance, or 2) cyclophosphamide for induction followed by azathioprine for maintenance). This study was conducted in Asia, North America, South America, and Europe. Patient median age was 31 years (range: 18 to 77 years); the majority (88%) of patients were female.
Table 14 Summary of Patient Demographics for Clinical Trial in Adult Patients with Lupus Nephritis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age ± SD (Range) | Gender |
BLISS-LN BEL114054 Lupus Nephritis | Randomized, double-blind, placebo-controlled trial | Belimumab 10 mg/kg IV on days 0, 14, 28 and then every 28 days for 104-weeks | N=223, 10 mg/kg N=223, placebo | 31 (range: 18 to 77) | Female (88%) |
The primary efficacy endpoint was Primary Efficacy Renal Response (PERR) at Week 104 defined as a response at Week 100 confirmed by a repeat measurement at Week 104 of the following parameters: urinary protein:creatinine ratio (uPCR) ≤0.7 and estimated glomerular filtration rate (eGFR) ≥60 mL/min/1.73m2 or no decrease in eGFR of >20% from pre-flare value.
The major secondary endpoints included:
- Complete Renal Response (CRR) defined as a response at Week 100 confirmed by a repeat measurement at Week 104 of the following parameters: uPCR <0.5 and eGFR ≥90 mL/min/1.73m2 or no decrease in eGFR of >10% from pre-flare value.
- PERR at Week 52.
- Time to renal-related event or death (renal-related event defined as first event of end stage renal disease, doubling of serum creatinine, renal worsening [defined as increased proteinuria and/or impaired renal function], or receipt of renal disease related prohibited therapy).
For PERR and CRR endpoints, patients dropping out of the study early or receiving prohibited medications were considered as failures. For these endpoints, in order to be considered a responder, steroid treatment had to be reduced to ≤10 mg/day from Week 24.
Study Results
In BLISS-LN, the proportion of lupus nephritis patients achieving PERR at Week 104 was statistically significantly higher in patients receiving BENLYSTA 10 mg/kg compared with placebo (Table 15). The major secondary endpoints also showed statistically significant improvement with BENLYSTA plus standard therapy compared with placebo plus standard therapy (Table 15).
Table 15 Efficacy Results in Patients with Lupus Nephritis
| Efficacy Endpoint1 | Placebo _+ Standard therapy n=223 | BENLYSTA _+ Standard therapy 10 mg/kg n=223 | Observed difference vs Placebo _+ Standard therapy | Odds/ Hazard ratio vs. Placebo _+ Standard therapy (95% CI) P-value | ||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Efficacy Endpoint1 | Placebo _+ Standard therapy n=223 | BENLYSTA _+ Standard therapy 10 mg/kg n=223 | Observed difference vs Placebo _+ Standard therapy | Odds/ Hazard ratio vs. Placebo _+ Standard therapy (95% CI) P-value | ||||||
Primary Efficacy Renal Response (PERR) at Week 1042, 3 Responders | 32% | 43% | 11% | OR 1.55 (1.04, 2.32) P=0.031 | ||||||
| Components of PERR | ||||||||||
| Urine protein:creatinine ratio ≤0.7 g/g | 34% | 44% | 11% | OR 1.54 (1.04, 2.29) | ||||||
eGFR≥60 mL/min/1.73m2 or no decrease in eGFR from pre-flare value of >20% | 50% | 57% | 7% | OR 1.32 (0.90, 1.94) | ||||||
Complete Renal Response (CRR) at Week 1042, 3 Responders | 20% | 30% | 10% | OR 1.74 (1.11, 2.74) P=0.017 | ||||||
| Components of CRR | ||||||||||
| Urine protein:creatinine ratio <0.5 | 29% | 39% | 11% | OR 1.58 (1.05, 2.38) | ||||||
| eGFR≥90 mL/min/1.73m2 or no decrease in eGFR from pre-flare value of >10% | 40% | 47% | 7% | OR 1.33 (0.90, 1.96) | ||||||
PERR at Week 522, 3 Responders | 35% | 47% | 11% | OR 1.59 (1.06, 2.38) P=0.025 | ||||||
Time to Renal-Related Event or Death Percentage of patients with event4 Time to event [Hazard ratio (95% CI)] | 28% | 16% | - - | HR 0.51 (0.34, 0.77) P=0.001 | ||||||
eGRF = Estimated glomerular filtration rate. 1PERR at Week 104 was the primary efficacy analysis; CRR at Week 104, PERR at Week 52 and time to renal-related event or death were included in the pre-specified testing hierarchy. 2In order to be considered a responder, steroid treatment had to be reduced to ≤10 mg/day from Week 24. Patients who discontinued treatment early, received prohibited medication or increases in background standard therapy, or withdrew from the study were considered non-responders. Prohibited medications and increases in background standard therapy were defined as: 1) use of corticosteroids above that allowed by protocol; 2) additional immunosuppressive agents (except topicals) beyond their induction/maintenance regimens; 3) angiotensin converting enzyme inhibitors (ACE) inhibitors, angiotensin II receptor blockers (ARBs), or antimalarials initiated after Week 24; 4) exceeding protocol-permitted doses for standard therapy (cyclophosphamide, azathioprine, mycophenolate); or 5) other biologics, IV immunoglobulin, or plasmapheresis. 3The percentage of patients who did not take prohibited medications or have an increase in background standard therapy at Week 104 was 83% for BENLYSTA and 74% for placebo. 4When excluding deaths from the analysis (1 for belimumab; 2 for placebo), the percentage of patients with a renal-related event was 15% for belimumab compared with 27% for placebo (HR = 0.51; 95% CI: 0.34, 0.78). | ||||||||||
A numerically greater percentage of patients receiving BENLYSTA achieved the Primary Efficacy Renal Response beginning at Week 24 compared with placebo, and this treatment difference was maintained through Week 104. Beginning at Week 12, a numerically greater percentage of patients receiving BENLYSTA achieved Complete Renal Response compared with placebo and this numerical difference was maintained through Week 104.
The proportion of responders for PERR and CRR by visit through Week 104 is shown in Figure 2.
Figure 2 Response Rates in Adults with Lupus Nephritis (+/- Standard Error) by Visita
Primary Efficacy Renal Response (PERR)
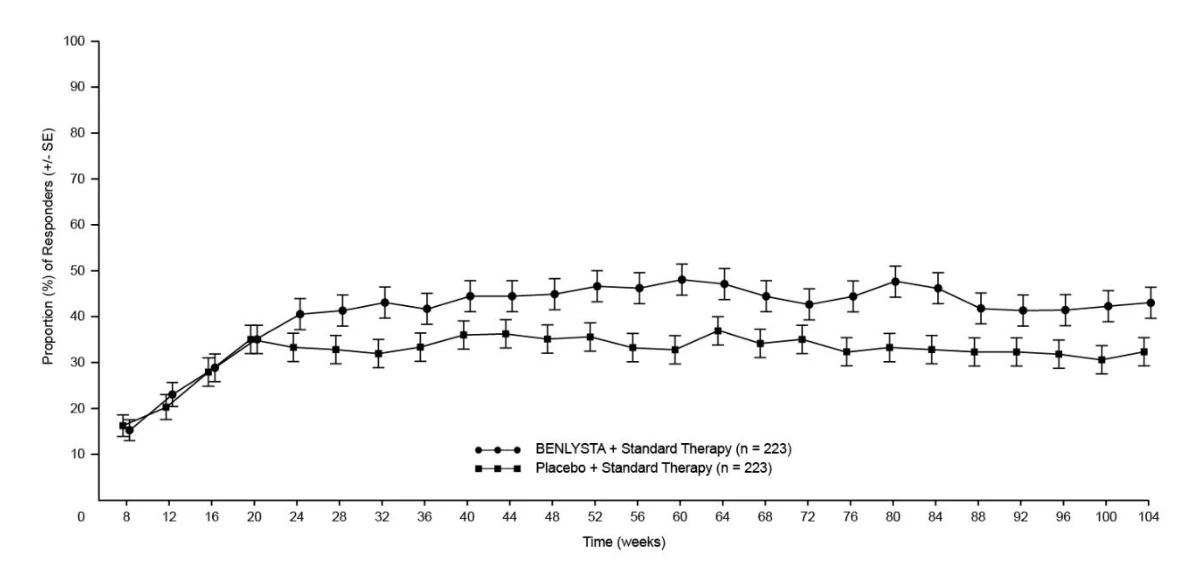
a The same patients may not have responded at each timepoint.
Complete Renal Response (CRR)
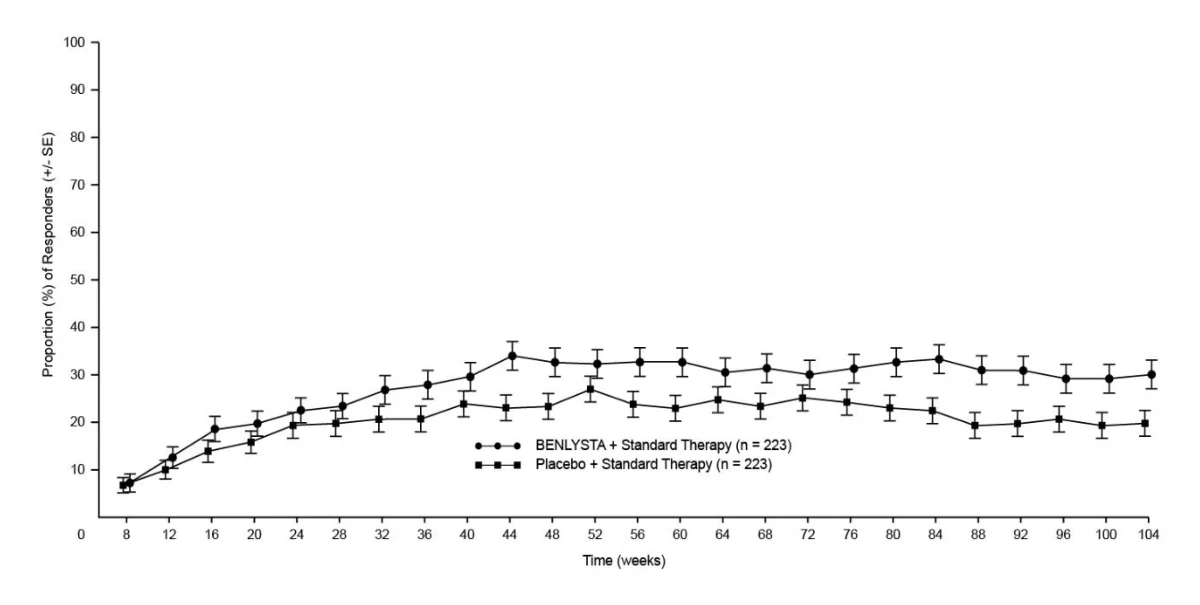
a The same patients may not have responded at each timepoint.
In descriptive subgroup analyses, the PERR and CRR rates were examined by induction therapy (mycophenolate or cyclophosphamide), biopsy class (Class III or IV, Class III + V or Class IV + V, or Class V), and uPCR levels at baseline (<3 g/g or ≥3 g/g; post-hoc analysis) (Figure 3).
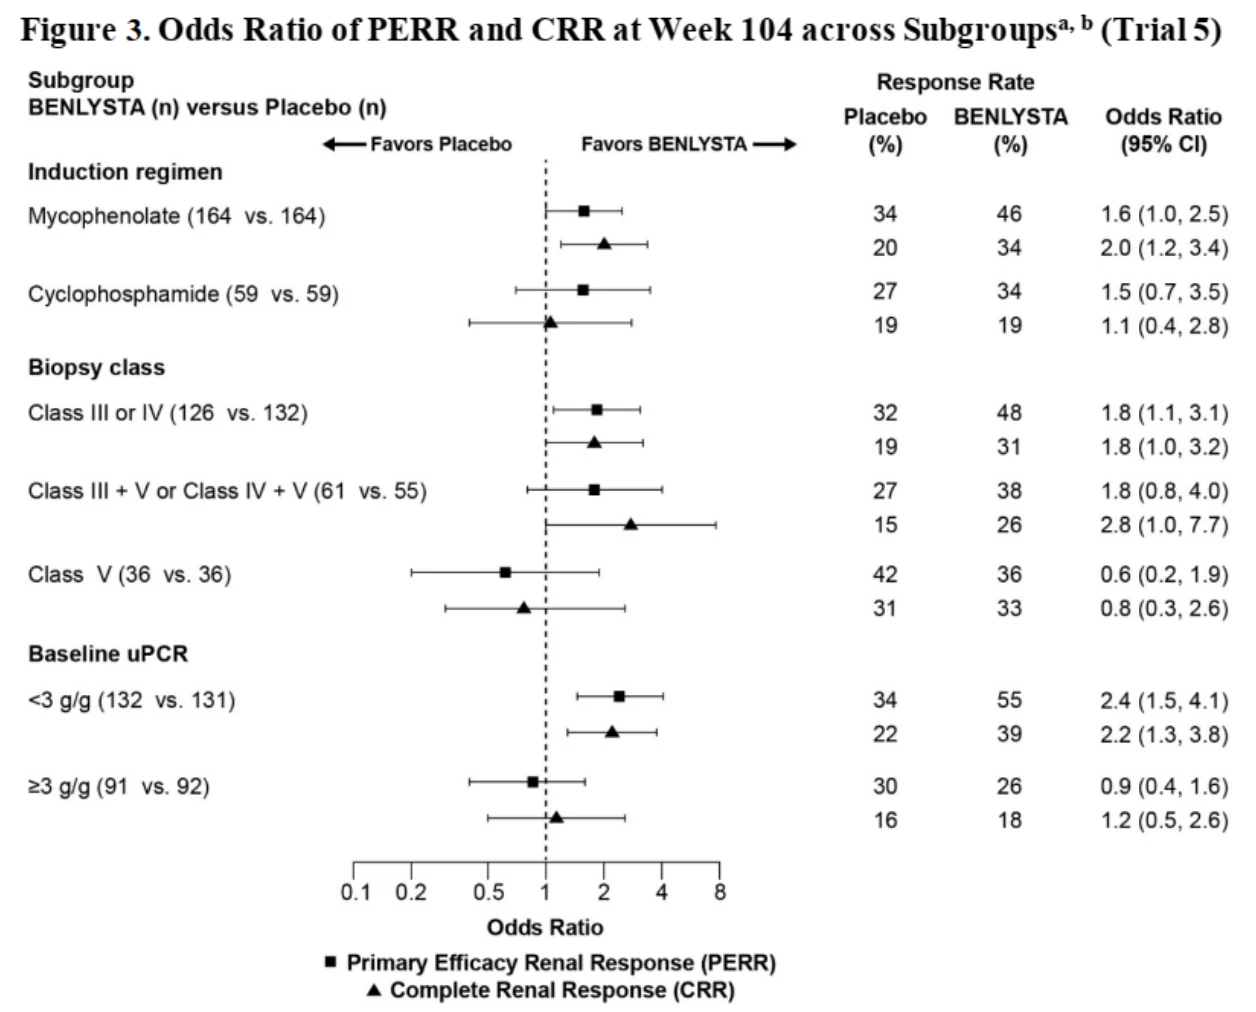
a Class III = Focal proliferative lupus nephritis; Class IV = Diffuse proliferative lupus nephritis; Class V = Membranous lupus nephritis; Class III + V = Mixed membranous-focal proliferative lupus nephritis; Class IV + V = Mixed membranous-diffuse proliferative lupus nephritis.
b Baseline urine protein:creatinine ratio (uPCR) was a post-hoc analysis.
In descriptive subgroup analyses of time to renal-related event or death, results were consistent with the overall endpoint regardless of induction therapy (mycophenolate or cyclophosphamide), biopsy class (Class III or IV, Class III + V or Class IV + V, or Class V; post-hoc analysis), and baseline proteinuria (<3 g/g or ≥3 g/g; post-hoc analysis). The treatment difference was primarily driven by the renal worsening and renal-related treatment failure components of the endpoint.
Pediatrics
No clinical study was conducted to evaluate the efficacy of BENLYSTA in pediatric patients aged 5 years and older with active lupus nephritis.
Use of intravenous administration of BENLYSTA in these patients is based on the extrapolation of efficacy from the intravenous study in adults with active lupus nephritis (n = 224), and supported by pharmacokinetic data from that study together with pharmacokinetic data from pediatric patients (n = 53) with SLE dosed intravenously (see 10.3. Pharmacokinetics).
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology: Nonclinical data revealed no special hazard for humans based on studies of repeat dose toxicity and reproductive toxicology.
Intravenous and subcutaneous administration to monkeys resulted in the expected reduction in number of peripheral and lymphoid tissue B-cell counts with no associated toxicological findings (see Table 16).
Safety pharmacology endpoints were included in the 4 week and 6 month toxicology studies in cynomolgus monkeys. No belimumab related adverse effects were noted on cardiovascular or renal endpoints at doses up to 50 mg/kg. Although no formal assessments of effects on central nervous or respiratory systems were undertaken, no treatment-related changes in these parameters were noted at repeated doses up to 50 mg/kg.
Carcinogenicity: No carcinogenicity studies have been conducted with belimumab.
Genotoxicity: No genotoxicity studies have been conducted with belimumab.
Reproductive and Developmental Toxicology: Reproductive studies have been performed in pregnant cynomolgus monkeys receiving belimumab 150 mg/kg by intravenous infusion (approximately 9 times the anticipated maximum human clinical exposure based on AUC) every 2 weeks for up to 21 weeks, and belimumab treatment was not associated with direct or indirect harmful effects with respect to maternal toxicity, developmental toxicity, or teratogenicity. Treatment-related findings were limited to the expected reversible reduction of B-cells in both dams and infants and reversible reduction of IgM in infant monkeys. B-cell numbers recovered after the cessation of belimumab treatment by about 1 year post-partum in adult monkeys and by 3 months of life in infant monkeys; IgM levels in infants exposed to belimumab in utero recovered by 6 months of age (see Table 16 ). Neurobehavioural assessments were conducted in infants, and no changes were noted at maternal doses up to 150 mg/kg.
Table 16 Summary of Toxicology Findings with belimumab
| Study ID | Species/ Dose/(mg/kg)/ Route | Study Design | Findings / Conclusion |
| Study ID | Species/ Dose/(mg/kg)/ Route | Study Design | Findings / Conclusion |
| Study ID | Species/ Dose/(mg/kg)/ Route | Study Design | Findings / Conclusion |
| Short Term Repeat Dose Studies | |||
| A 4 Week Repeat Dose Toxicity Study of belimumab Administered by Intravenous Injection to Cynomolgus Monkeys, with a 4 Week Recovery Period | Cynomolgus monkey Doses: 0 (vehicle control), 5, 15, 50 mg/kg Dosing: Weekly Route: IV (bolus) | 5/sex/dose group 3/sex/group necropsied 4 weeks after treatment; remaining 2/sex/group necropsied after 4 weeks of treatment followed by 4 weeks of recovery period | In all belimumab-treated dose groups: A reduction of B cells in spleen and/or mesenteric lymph node, the expected pharmacological effect of treatment with belimumab, was noted. There was no significant difference in the absolute numbers of peripheral blood mononuclear cell (PBMC) populations (total lymphocytes, B lymphocyte subsets, T lymphocyte subsets or monocytes) at the end of treatment or at the end of the recovery phase. An increase in T cells was observed and is considered to be secondary to the decreases in B lymphocyte populations. Minimal to mild thyroid follicular epithelial degeneration was noted in 1 out of 10 and 5 out of 10 belimumab-treated monkeys at 5 and 50 mg/kg, respectively. A possible treatment relationship could not be excluded; however, similar findings were not observed in the 6 month repeat dose study. At 50 mg/kg belimumab dose group: Splenic abscess (1 out of 10) and necrotizing granuloma (1 out of 10) were noted. These findings may have been associated with infection, and possible treatment relationship could not be excluded. In the subsequent 6 month repeat dose study, similar findings were not observed, confirming the view that the observations in the 4 week study were not treatment-related. The NOAEL is 50 mg/kg (12-fold human exposure based on AUC). |
| Long Term Repeat Dose Study | |||
| A 6 Month Toxicity Study of belimumab Administered Bi-Weekly by Intravenous Injection to Cynomolgus Monkeys, with an 8 Month Recovery Period | Cynomolgus monkey Doses: 0 (vehicle control), 5, 15, 50 mg/kg Dosing: Every 14 days Route: IV (bolus) | 6/sex at 0 mg/kg and 8/sex/dose group at all belimumab treatment groups; 2/sex/group at 0 mg/kg and 3/sex/group at all belimumab dose groups necropsied 13 weeks after treatment initiation; 2/sex/group at 0 mg/kg and 3/sex/group at all belimumab dose groups necropsied 26 weeks after treatment initiation; 2/sex/group at 0 mg/kg and 3/sex/group at all belimumab dose groups necropsied after 26 weeks of treatment followed by 8 month (Week 60) recovery period | In all belimumab-treated dose groups: A reduction of B cells in spleen and/or mesenteric lymph node (MLN), the expected pharmacological effect of treatment with belimumab, was noted at Weeks 13 and 26. The B lymphocyte reductions in the spleen and MLN resolved by the end of the recovery period. Also, a reduction in peripheral blood B cells was noted after 13 weeks of treatment in the 15 and 50 mg/kg groups and in all groups by Week 26. The reduction in B cells persisted into the recovery period through Week 39 followed by a trend for recovery of peripheral blood B lymphocytes back to baseline levels at Week 45, which continued through to the end of the recovery period. Consistent with the pharmacologic effect of belimumab, there was a reduction in spleen weights at Week 26. In addition, at Week 13, microscopic changes attributed to belimumab administration consisted of decreased lymphoid follicle size and/or number in the spleen. A reduction in the size and/or number of lymphoid follicles in the spleen and mesenteric lymph node was also evident in the belimumab-treated animals at Week 26. These effects correlated with decreases in splenic and MLN B lymphocytes at Weeks 13 and 26, as well as reduced splenic weights at Week 26. These changes, as well as splenic mesenteric B lymphocyte reductions, resolved by the end of the recovery period. The NOAEL is 50 mg/kg (5-fold human dose on a mg/kg basis). |
| Reproductive and Developmental Toxicity Studies | |||
| Maternal, Fetal and Neonatal Toxicity Study of belimumab Administered Bi-Weekly by Intravenous (Bolus) Injection to Pregnant Cynomolgus Monkeys, Including a One Year Postnatal Evaluation | Cynomolgus monkey Doses: 0 (vehicle control), 5, 150 mg/kg Dosing: within 2 days of confirmed pregnancy by ultrasound [Gestation Day 20 (GD20) to GD22], on GD34 and every 14 days throughout pregnancy (GD150) Route: IV (bolus) | 0 (vehicle control) mg/kg: Total 21 females of which 11 females were C-sectioned at GD150, and 10 females were followed out to 1 year postpartum 5 mg/kg: Total 25 females of which 13 females were C-sectioned at GD150, and 12 females were followed out to 1 year postpartum 150 mg/kg: Total 20 females of which 9 females were C-sectioned at GD150, and 11 females were followed out to 1 year postpartum | In all belimumab treated dose groups: No maternal toxicity and no adverse effects on embryofetal development or teratogenicity were noted. As expected, there were decreases in total and mature B lymphocytes in maternal peripheral blood during dosing and in fetal lymphoid tissues. Recovery of the total and mature B lymphocytes was observed in maternal blood and in infant blood and tissues after the cessation of dosing. Infant serum immunoglobulin M (IgM) levels were decreased in the first 3 months of life but recovered to control levels by 6 months after birth. In addition, it was confirmed that belimumab, like other antibodies of the immunoglobulin G1 (IgG1) subclass, is able to cross the placenta and can be secreted into milk. After cessation of dosing and clearance of belimumab and just prior to (or concomitant with) B cell recovery, BLyS levels, which pre-dose were very low in adult females, transiently increased in both mothers and infants prior to returning to baseline levels. There were a total of 12 fetal losses (12 out of 66 or 18.2%); overall incidence of fetal losses and stillbirths was 3 out of 21 (14.3%) in the 0 (vehicle control), 6 out of 25 (24.0%) at 5 mg/kg dose and 3 out of 20 (15.0%) at the 150 mg/kg dose of belimumab. There were a total of 3 neonatal deaths (3 out of 43 or 7.0%); overall incidence was 0 out of 10 in the 0 (vehicle control), 2 out of 12 (16.7%) at 5 mg/kg dose and 1 out of 11 (9.0%) at the 150 mg/kg dose of belimumab. No belimumab-related adverse effects were seen on embryofetal development in fetuses examined following C-section (GD150) or in the aborted or stillborn fetuses. No abnormalities were noted in the 3 neonates lost within the first few weeks, confirming that the deaths were not related to belimumab treatment. Reproductive failure through abortions and stillbirths in early and late pregnancy and neonatal losses within the first few weeks is significant and common among non-human primates. The NOAEL is 150 mg/kg (9-fold human exposure based on AUC). |