


Product Monograph - Cysklar
RECENT MAJOR LABEL CHANGES
None at time of authorization.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.1 Dosing Considerations .......................................................................................... 4
4.2 Recommended Dose and Dosage Adjustment ..................................................... 4
4.4 Administration ...................................................................................................... 4
4.5 Missed Dose ......................................................................................................... 5
5 OVERDOSE .................................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 5
7 WARNINGS AND PRECAUTIONS .................................................................................. 5
General ............................................................................................................................. 5
Driving and Operating Machinery .................................................................................... 5
Neurologic ........................................................................................................................ 6
Ophthalmologic ................................................................................................................ 6
Reproductive Health ........................................................................................................ 6
7.1 Special Populations ............................................................................................... 6
7.1.1 Pregnant Women ............................................................................................. 6
7.1.2 Breastfeeding ................................................................................................... 6
7.1.3 Pediatrics .......................................................................................................... 7
7.1.4 Geriatrics .......................................................................................................... 7
8 ADVERSE REACTIONS .................................................................................................. 7
8.1 Adverse Reaction Overview .................................................................................. 7
8.2 Clinical Trial Adverse Reactions ............................................................................ 7
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ...................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 10
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................... 10
8.5 Post-Market Adverse Reactions ......................................................................... 10
9 DRUG INTERACTIONS ................................................................................................ 10
9.2 Drug Interactions Overview ................................................................................ 10
9.3 Drug-behaviour interactions ............................................................................... 10
9.4 Drug-Drug Interactions ....................................................................................... 10
9.5 Drug-Food Interactions ....................................................................................... 11
9.6 Drug-Herb Interactions ....................................................................................... 11
9.7 Drug-Laboratory Test Interactions ...................................................................... 11
10 CLINICAL PHARMACOLOGY ....................................................................................... 11
10.1 Mechanism of Action .......................................................................................... 11
10.2 Pharmacodynamics ............................................................................................ 11
10.3 Pharmacokinetics ............................................................................................... 11
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 11
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 12
PART II: SCIENTIFIC INFORMATION ....................................................................................... 12
13 PHARMACEUTICAL INFORMATION ............................................................................ 12
14 CLINICAL TRIALS ........................................................................................................ 13
14.1 Clinical Trials by Indication ................................................................................... 13
15 MICROBIOLOGY ........................................................................................................ 15
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 16
PATIENT MEDICATION INFORMATION .................................................................................. 17
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
CYSKLARTM (cysteamine ophthalmic solution) is indicated for:
- the treatment of corneal cystine crystal accumulation in patients with cystinosis.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of CYSKLAR in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use. (see 14 CLINICAL TRIALS)
1.2 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada; therefore, the safety and efficacy are not established for geriatric use.
2 CONTRAINDICATIONS
CYSKLAR is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Treatment with CYSKLAR should be initiated under the supervision of a physician experienced in the management of cystinosis.
4.2 Recommended Dose and Dosage Adjustment
- The recommended dose is one drop of CYSKLAR in each eye, every waking hour.
- CYSKLAR may be used in pediatric (< 18 years of age) patients at the same dose as in adults (see 14 CLINICAL TRIALS).
4.4 Administration
- For ophthalmic use.
- Before opening, the patient should be advised to store CYSKLAR in the refrigerator in the original carton and unopened foil.
- The patient should be advised to open the carton and foil only when starting a new bottle. After opening, store bottle at room temperature. The bottle does not require refrigeration between use (see 11 STORAGE, STABILITY, AND DISPOSAL).
- The patient should be advised not to touch the eyelid or surrounding areas with the dropper tip of the bottle, as this may contaminate the solution. The cap should remain on the bottle when not in use.
- Patients should be advised that contact lenses should be removed prior to application of CYSKLAR. Contact lenses may be inserted 15 minutes following administration.
- The patient should be advised to discard the bottle after 1 week of use.
4.5 Missed Dose
If a dose is missed, the patient should be advised to continue the treatment with the next instillation.
5 OVERDOSE
If the patient administers too much CYSKLAR, allow a few minutes for blinking of the eyes. If irritation or pain persists, instruct patient to rinse out the eye(s) with an ophthalmic saline or buffered solution. No further drops should be administered until it is time for the next regular dose.
Systemic overdose is unlikely to occur with ocular administration.
In case of accidental ingestion, patient should contact their physician. Monitoring and symptomatic management of the patient should be implemented.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths and Composition
Fifteen (15) mL of CYSKLAR is supplied as a sterile, clear, colorless solution in a 23.24 mL, opaque, white, low-density polyethylene (LDPE) 88.2 mm tall, multi-use bottle, with a 1.6 mm blue, silicone rubber flow-controlled dropper tip and closed with a white, high-density polyethylene (HDPE) screw cap. The bottle is foil-wrapped and stored in a carton.
7 WARNINGS AND PRECAUTIONS
General
For ophthalmic use only.
To minimize contaminating the dropper tip and solution, care should be taken not to touch the eyelids or surrounding areas with the dropper tip of the bottle. Keep bottle tightly closed when not in use.
Driving and Operating Machinery
Temporary blurred vision or other visual disturbances may affect the ability to drive or use machines.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Ophthalmic | Solution containing 6.5 mg/mL cysteamine hydrochloride equivalent to 4.4 mg/mL of cysteamine (0.44% w/v) | benzalkonium chloride hydrochloric acid sodium chloride sodium hydroxide water for injection |
If blurred vision occurs after administration, the patient must wait until their vision clears before driving or using dangerous machinery.
Neurologic
Benign Intracranial Hypertension
There have been reports of benign intracranial hypertension (or pseudotumor cerebri) associated with oral cysteamine treatment that has resolved with the addition of diuretic therapy.
There have also been reports associated with ophthalmic use of cysteamine; however, all of these patients were on concurrent oral cysteamine.
Ophthalmologic
CYSKLAR contains benzalkonium chloride which may cause eye irritation.
Benzalkonium chloride, which is commonly used as a preservative in ophthalmic products has also been reported to cause punctate keratopathy and/or toxic ulcerative keratopathy. Monitoring is required.
Contact Lens Use
CYSKLAR contains benzalkonium chloride, which may be absorbed by soft contact lenses. Benzalkonium chloride is known to discolour soft contact lenses. Contact with soft contact lenses should be avoided. Contact lenses should be removed prior to application of solution and may be reinserted 15 minutes following its administration.
Reproductive Health
Fertility
No data on the effect of cysteamine on human fertility are available. Studies in animals with cysteamine administered orally have shown a reduction of fertility (see 16 NON-CLINICAL TOXICOLOGY).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well controlled studies of ophthalmic cysteamine in pregnant women to inform any drug associated risks. CYSKLAR should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus and should be discussed with the primary provider.
The recommended total daily ophthalmic dose of CYSKLAR is less than 2% of the recommended oral daily dose of cysteamine. Systemic exposure of cysteamine following ophthalmic administration is expected to be very low.
Studies in animals with oral cysteamine have shown reproductive toxicity, including teratogenesis. The potential risk in humans is unknown (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breastfeeding
There is no information regarding the presence of cysteamine in human milk, the effects on the breastfed infants, or the effects on milk production.
Cysteamine administered orally is present in milk of lactating rats. It is not known whether measurable levels of cysteamine would be present in maternal milk following topical ocular administration of cysteamine ophthalmic solution. Oral administration of cysteamine to breast-feeding mother rats reduced growth and increased mortality rates among their neonates (see 16 NON-CLINICAL TOXICOLOGY).
It is unknown if CYSKLAR is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk.
7.1.3 Pediatrics
The safety and effectiveness of CYSKLAR have been established in pediatric patients (< 18 years of age) at the same dose as adults (see 14 CLINICAL TRIALS).
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada; therefore, the safety and efficacy are not established for geriatric use.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Safety data was collected from 3 controlled clinical studies in adult and pediatric patients. The mean study duration was approximately 6 years in Study 1. Study 2 and 3 had a duration of 1 year and 6 months, respectively.
The most frequently reported adverse reactions occurring in ≥10% of patients from clinical studies were sensitivity to light, eye redness, eye pain/irritation, instillation site redness/irritation/pain, headache and visual field defects.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Study 1 is a combined analysis of three smaller controlled clinical studies which evaluated several formulations of ophthalmic cysteamine solution. Table 2 outlines the incidence of the most common (≥1%) adverse events in the safety population in Study 1. The safety population consisted of 247 patients (adult and pediatric patients ranged in age from <1 year to 49.6 years). The mean (±SD) treatment duration was 5.8 ± 5.5 years.
| Table 2 Summary of the Incidence of the Most Common (≥1%) Adverse Events (AE) (n and %) for the Treatment Period – Safety Population (Study 1) | |||
|---|---|---|---|
| Table 2 Summary of the Incidence of the Most Common (≥1%) Adverse Events (AE) (n and %) for the Treatment Period – Safety Population (Study 1) | |||
System Organ Classa Preferred Terma | Total (N = 247) n (%) | ||
System Organ Classa Preferred Terma | Total (N = 247) n (%) | ||
| Number of Patients With at Least One AE | 169 (68.4) | ||
| Eye Disorders | 166 (67.2) | ||
| Photophobia | 157 (63.6) | ||
| Conjunctival Hyperaemia | 69 (27.9) | ||
| Eye Pain | 48 (19.4) | ||
| Ocular Hyperaemia | 43 (17.4) | ||
| Eye Irritation | 42 (17.0) | ||
| Lacrimation Increased | 21 (8.5) | ||
| Keratitis | 19 (7.7) | ||
| Optic Disc Disorder | 18 (7.3) | ||
| Vision Blurred | 17 (6.9) | ||
| Dry Eye | 13 (5.3) | ||
| Eyelid Oedema | 12 (4.9) | ||
| Retinal Disorder | 11 (4.5) | ||
| Conjunctivitis | 10 (4.0) | ||
| Eye Pruritus | 10 (4.0) | ||
| Blindness | 7 (2.8) | ||
| Corneal Epithelium Disorder | 6 (2.4) | ||
| Blepharitis | 5 (2.0) | ||
| Erythema of Eyelid | 5 (2.0) | ||
| Eye Swelling | 3 (1.2) | ||
| Nervous System Disorders | 63 (25.5) | ||
| Headache | 34 (13.8) | ||
| Visual Field Defect | 32 (13.0) | ||
| Benign Intracranial Hypertension | 8 (3.2) | ||
| General Disorders and Administration Site Conditions | 45 (18.2) | ||
| Instillation Site Irritation | 30 (12.1) | ||
| Instillation Site Pain | 17 (6.9) | ||
| Adverse Drug Reaction | 7 (2.8) | ||
| Instillation Site Erythema | 5 (2.0) | ||
| Infections and Infestations | 11 (4.5) | ||
| Eye Infection | 5 (2.0) | ||
| Conjunctivitis Infective | 3 (1.2) | ||
| Hordeolum | 3 (1.2) | ||
| Gastrointestinal Disorders | 8 (3.2) | ||
| Vomiting | 8 (3.2) | ||
aAll AE terms were coded using MedDRA Dictionary Version 9.0. Note: A patient experiencing multiple occurrences of an AE is counted only once within each system organ class and within each preferred term. | |||
Study 2 was a multicenter, randomized, double masked, comparative safety and efficacy trial comparing two formulations of the cysteamine ophthalmic solution over a 12-month treatment period. Safety population consisted of 16 pediatric patients.
Study 3 was a single center, randomized, double masked, comparative safety and efficacy trial comparing 2 formulations of the cysteamine ophthalmic solution over a 6-month treatment period. The safety population consisted of 20 adult and pediatric patients.
The safety profile of CYSKLAR in supportive Studies 2 and 3 is consistent with Study 1.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Pediatric patients are included in the clinical trials noted above. Table 3 outlines age distribution of pediatric patients in the clinical trials.
Table 3 Age Distribution of Pediatric Patients in the Clinical Trials
| Study | Number of Pediatric Patients | ||
|---|---|---|---|
| Age 0 - <2 Years | Age 2 - <12 Years | 12 - <18 Years | |
| Study 1 | 23 | 93 | 60 |
| Study 2 | 0 | 15 | 1 |
| Study 3 | 0 | 9 | 9 |
8.3 Less Common Clinical Trial Adverse Reactions
The list includes less common clinical trial adverse reactions reported for adult and pediatric patients:
Eye Disorders: Conjunctival oedema, eye oedema, eyelid cyst, eyelid irritation, ulcerative keratitis
General Disorders and Administration Site Conditions: Drug ineffective, instillation site lacrimation, instillation site reaction
Immune System Disorders: Drug hypersensitivity
Investigations: Visual evoked potentials abnormal
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
No clinically relevant changes in laboratory findings were observed.
Post-Market Findings
No clinically relevant changes in laboratory findings were observed.
8.5 Post-Market Adverse Reactions
In the post-market setting CYSKLAR demonstrates an adverse event profile consistent with what was reported in the clinical trials.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
No clinical drug interaction studies with CYSKLAR have been performed.
9.3 Drug-behaviour interactions
The interaction of CYSKLAR with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4 Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Cysteamine acts as a cystine-depleting agent by converting cystine to cysteine and cysteine-cysteamine mixed disulfides and thereby reducing corneal cystine crystal accumulation.
10.2 Pharmacodynamics
Conventional pharmacodynamic studies using topically administered cysteamine have not been conducted.
10.3 Pharmacokinetics
Human pharmacokinetic studies were not conducted with cysteamine ophthalmic solution 0.44%.
The peak plasma concentration of cysteamine following ocular administration of cysteamine ophthalmic solution in humans is unknown, but it is expected to be substantially less than the peak plasma concentration following oral administration of cysteamine bitartrate.
Cysteamine distribution, metabolism and excretion data were based on mode of administration that were not ophthalmic. Cysteamine that reach the systemic circulation upon ophthalmic administration is expected to be rapidly absorbed, distributed, metabolised and excreted in a similar manner, but tissue concentrations is expected to be low based on the low dose administered.
Special Populations and Conditions
Renal impairment: The effect of renal impairment on the pharmacokinetics of cysteamine following ophthalmic administration of cysteamine ophthalmic solution has not been evaluated in a dedicated renal impairment study.
The majority of the patients in the ophthalmic clinical studies are assumed to have had some degree of renal impairment due to their underlying systemic disease.
The total daily ophthalmic dose is less than 2% of the recommended oral daily dose of cysteamine; thus, the systemic exposure following ophthalmic administration is expected to be negligible compared to oral administration.
11 STORAGE, STABILITY AND DISPOSAL
Before Opening: Store unopened bottle in a refrigerator (2°C to 8°C) in the original packaging including unopened foil.
Open the carton and the foil only when starting a new bottle.
After Opening: Record opening date on the bottle. During the week of use, store bottle at room temperature, 20°C to 25°C. Discard 1 week after the foil and bottle were opened even if there is medication left in the bottle.
12 SPECIAL HANDLING INSTRUCTIONS
Patients should be advised not to touch the eyelid or surrounding areas with the dropper tip of the bottle. The cap should remain on the bottle when not in use.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Non-proprietary name of the drug substance: Cysteamine Hydrochloride
Chemical name: 2-Amino-ethanethiol hydrochloride/2-Mercaptoethylamine hydrochloride
Molecular formula and molecular mass: C2H7NS, HCl; 113.61
Structural formula:
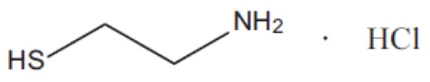
Physicochemical properties:
Appearance: White to off-white solid.
Solubility: Freely soluble in water and soluble in 2-propanol at 20 °C.
pH: The pH of a 1% solution of Cysteamine HCl in water is 4.2 - 4.7.
Melting Point: 71.8°C.
Hygroscopicity: Cysteamine HCl will deliquesce at standard temperature and humidity conditions.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
| Table 4 - Summary of patient demographics for clinical trials in the treatment of corneal cystine crystal accumulation in patients with cystinosis | |||||||||
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Average age (Range) | Sex | ||||
| Study 1 | Randomized, Double-Masked | Placebo (saline) Formulation 1a Formulation 2b Formulation 3c (CYSKLAR) Formulation 4d One drop of cysteamine was administered to one eye and one drop placebo administered to companion eye, every waking hour; the administration was later amended to apply active treatment to both eyes. Duration of treatment: up to 19 years. | 247 patients | 13.8 years (< 1 to 49.6 years) | 130 (52.6%) patients were male | ||||
| Study 2 | A Multicenter, Randomized, Double-Masked, Comparative Efficacy Trial | Formulation 3c (CYSKLAR) Formulation 5e One drop of Formulation 3 was administered to one eye and one drop of Formulation 5 was administered to the companion eye, every waking hour. Duration of treatment: up to 1 year. | 16 patients | 6.5 years (2.7-12.0 years)f | 8 (50%) patients were male | ||||
| Study 3 | A Single-Center, Randomized, Double-Masked, Comparative Safety and Efficacy Trial | Formulation 3c (CYSKLAR) Formulation 5e One drop of Formulation 3 was administered to one eye and one drop of Formulation 5 was administered to the companion eye, every waking hour for 6 months | 20 patients | 13.4 years (5.9-27.8 years)f | 13 (65.0%) patients were male | ||||
BAK = Benzalkonium chloride aFormulation 1: 0.07% cysteamine (equivalent to 1.1 mg/mL cysteamine hydrochloride) bFormulation 2: 0.44% cysteamine (equivalent to 6.5 mg/mL cysteamine hydrochloride) cFormulation 3: 0.44% cysteamine (equivalent to 6.5 mg/mL cysteamine hydrochloride), 0.01% BAK dFormulation 4: 0.55% cystamine , 0.01% BAK eFormulation 5: 0.37% cysteamine (equivalent to 5.5 mg/mL cysteamine hydrochloride), BAK, monobasic sodium phosphate, EDTA f All patients were of white, non-Hispanic origin | |||||||||
Study 1 combined data from three protocols and evaluated three (3) formulations of ophthalmic cysteamine solution (Formulations 1, 2 and 3) and one formulation of ophthalmic cystamine solution (Formulation 4). All patients who continued to participate in the study eventually switched to receiving Formulation 3 (CYSKLAR) in both eyes until the end of study. Of the 247 patients enrolled in the study, 161 (65.2%) were included in the efficacy analysis. Patients in the study ranged in age from < 1 year to 49 years with a mean (±SD) exposure to treatment of 5.8 ± 5.5 years. Mean (±SD) study duration for the analysis population was 8.5 ± 4.9 years. Patients were randomly assigned to treatment; all study participants and study staff were masked to the treatment administered. Patients received one drop of the assigned ophthalmic solution (Formulation 1, 2, 3, 4, or placebo) in the appropriate eye every waking hour. The primary endpoint was the reduction of corneal cystine crystal score (CCCS) in eyes with high CCCS (≥1) at baseline, and lack of increase in CCCS in eyes with low CCCS (<1) at baseline. A response was defined as a decrease from baseline of at least 1 unit in CCCS at any time on study when baseline CCCS was ≥1, or CCCS did not increase at least 1 unit at any time on study when baseline CCCS was <1.
For eyes with baseline CCCS ≥1, the response rate was 32% [95% CI: (27, 38)]. For eyes with baseline CCCS <1, the response rate was 13% [95% CI: (4, 31)]. For eyes with baseline CCCS ≥1, mean baseline CCCS score was 2.7 ± 0.5 (mean ± SD) with mean change of -0.2 ± 0.8 at Year 1. For eyes with baseline CCCS <1, mean baseline CCCS score was 0.3 ± 0.2 (mean ± SD) with mean change of 0.3 ± 0.5 at Year 1.
Study 2 was a multi-center, double masked, clinical trial. A total of 16 patients were randomized to receive one drop of Formulation 3 (CYSKLAR) in one eye and one drop of Formulation 5 (0.37% cysteamine, EDTA and BAK) in the companion eye every waking hour. Study investigators and all clinic staff were to be masked to treatment assignments. Patients enrolled were ranged from 2 to12 years of age (inclusive) who had never used cysteamine eye drops. The treatment duration was 1 year. All eyes evaluated in the study had CCCS baseline value ≥1.00. The primary efficacy end point was defined as the estimated proportion of eyes with a reduction of 1.00 unit or more in CCCS relative to at any time during the treatment period (up to Month 12) and at the specified time points of Months 3, 6, 9, and 12.
CYSKLAR response rate was 67% [95% CI: (38, 88)] at any time during the study. Mean baseline CCCS score for eyes receiving CYSKLAR was 2.7 ± 0.4 (mean ± SD) with mean change of -0.6 ± 0.7, -1.0 ± 0.9, -1.2 ± 1.0, and -0.9 ± 0.9 at Months 3, 6, 9, and 12, respectively.
Study 3 was a single-centre, double masked, randomized, comparative safety and efficacy study in, pediatric (≥ 1 year of age) and adult patients diagnosed with cystinosis. A total of 20 patients were randomized to receive one drop of Formulation 3 (CYSKLAR) in one eye and one drop of Formulation 5 in the companion eye every waking hour. Safety and efficacy assessments were done at baseline and at 6 months. The study duration was 6 months and the efficacy analysis was conducted at 6 months in the per protocol population. The efficacy analysis included the estimated proportion of eyes with a reduction of 1.00 unit or more in the CCCS relative to baseline (where CCCS baseline value was ≥1.00) or a lack of increase by at least 1 unit (where baseline CCCS <1.00).
For eyes with baseline CCCS ≥1, the response rate was 33% [95% CI: (8, 70)]. For eyes with baseline CCCS <1, the response rate was 89% [95% CI: (52, 100)]. For eyes with baseline CCCS ≥1, mean baseline CCCS score was 1.9 ± 0.6 (mean ± SD) with mean change of -0.5 ± 0.6 at 6 months. For eyes with baseline CCCS <1, mean baseline CCCS score was 0.2 ± 0.1 (mean ± SD) with mean change of 0.1 ± 0.4 at 6 months.
Details on the patient demographics for the three clinical studies are provided in Table 4. Efficacy results from the three clinical studies for treatment of corneal cystine crystal accumulation in patients with cystinosis are summarized in Table 5.
| Table 5 : Results of proportion of eyes with corneal cystine crystal score (CCCS) response across Studies 1 to 3 | |||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study 1 | Study 2 | Study 3 | |||||||||||||||||||||
| STUDY DETAILS | |||||||||||||||||||||||
| Number of patients enrolled | 247 | 16 | 20 | ||||||||||||||||||||
| Treatment duration | 5.8 ± 5.5 years (Mean ± SD) | 1 year | 6 months | ||||||||||||||||||||
| Mean age (range) | 13.8 years (0.2 – 49.6) | 6.5 years (2.7 – 12.0) | 13.4 years (5.9 – 27.8) | ||||||||||||||||||||
| PROPORTION OF EYES WITH CORNEAL CYSTINE CRYSTAL SCORE (CCCS) RESPONSE | |||||||||||||||||||||||
| Number of eyes evaluated | Number of responders (%) [95% CI] | Number of eyes evaluated | Number of responders (%) [95% CI] | Number of eyes evaluated | Number of responders (%) [95% CI] | ||||||||||||||||||
| Eyes with Baseline CCCS ≥1.00 | |||||||||||||||||||||||
| Any Time During Study | 291 | 94 (32%) [27-38] | 15 | 10 (67%) [38-88] | - | NS* | |||||||||||||||||
| Month 3 | - | NS* | 14 | 4 (29%) [8-58] | - | NS | |||||||||||||||||
| Month 6 | - | NS* | 14 | 7 (50%) [23-77] | 9 | 3 (33%) [7-70] | |||||||||||||||||
| Month 9 | - | NS* | 14 | 8 (57%) [29-82] | - | NS* | |||||||||||||||||
| Month 12 | 291 | 27 (9%) [6, 13] | 15 | 7 (47%) [21-73] | - | NS* | |||||||||||||||||
| Eyes with Baseline CCCS <1.00 | |||||||||||||||||||||||
| At the end of study | 30 | 4 (13%) [95% CI: (4, 31)] | - | NS | 9 | 8 (89%) [52-100] | |||||||||||||||||
| *NS = Not Summarized | |||||||||||||||||||||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Topical, ocular administration of CYSKLAR is expected to result in low systemic exposure.
General Toxicology
Oral and Intraperitoneal Toxicity Studies
Acute toxicity data are available following systemic administration of cysteamine hydrochloride to rodents. Gastrointestinal ulcers and necrosis of the adrenal gland have been associated with high doses in rats, and depletion of somatostatin was also observed, although the interpretation of these findings in relation to the clinical use are not known.
Ocular Toxicity Studies
Three studies ranging from 3 weeks to 3 months duration were conducted in rabbits where either 0.55% or 0.5% cysteamine HCl eye drop solutions were applied every hour for 8 hours daily. No adverse findings were reported at these concentrations.
Safety Pharmacology
No standard safety pharmacology studies have been performed as these were not considered relevant following topical application.
Genotoxicity
The genotoxic activity of cysteamine has been investigated in in vitro studies. Cysteamine was not mutagenic in the Ames test. It produced a negative response in an in vitro sister chromatid exchange (SCE) assay in human lymphocytes but a positive response in a similar assay in hamster ovarian cells.
Carcinogenicity
Cysteamine has not been tested for its carcinogenic potential in long-term animal studies.
Reproductive and Developmental Toxicology
Repeat breeding reproduction studies were conducted in male and female rats. Cysteamine was found to have no effect on fertility and reproductive performance at an oral dose of 75 mg/kg/day. At an oral dose of 375 mg/kg/day, it reduced the fertility of the adult rats and the survival of their offspring.
Reproductive studies in animals with oral cysteamine were conducted at doses ranging from 37.5 mg/kg/day to 150 mg/kg/day. At doses ≥100 mg/kg/day, teratogenesis were shown. Observed teratogenic findings were intrauterine death, cleft palate, kyphosis, heart ventricular septal defects, microcephaly, exencephaly, and growth deficits. Growth was reduced and mortality increased in rat neonates when mothers received 375 mg/kg/day cysteamine during lactation.