


Product Monograph - Dovobet Ointment
Recent Major Label Changes
| None at time of the most recent authorization |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes….…………………………………………………………………………………………..2
Table of Contents .............................................................................................................. 2
Part 1: Healthcare Professional Information....................................................................... 4
- 1.
Indications.................................................................................................................. 4
1.1. Pediatrics .................................................................................................................. 4
1.2. Geriatrics .................................................................................................................. 4
- 2. Contraindications ....................................................................................................... 4
- 4.
Dosage and Administration ........................................................................................ 4
4.2. Recommended Dose and Dosage Adjustment ............................................................. 4
4.4. Administration .............................................................................................................. 4
4.5. Missed Dose ................................................................................................................. 5
- 5. Overdose .................................................................................................................... 5
- 6. Dosage Forms, Strengths, Composition, and Packaging ................................................ 5
- 7.
Warnings and Precautions ........................................................................................... 6
General ................................................................................................................................ 6
Carcinogenesis and Genotoxicity ........................................................................................ 6
Endocrine and Metabolism ................................................................................................. 6
Monitoring and Laboratory Tests ........................................................................................ 7
Ophthalmologic ................................................................................................................... 7
Skin ...................................................................................................................................... 7
7.1. Special Populations....................................................................................................... 8
- 8.
Adverse Reactions ...................................................................................................... 8
8.2. Clinical Trial Adverse Reactions .................................................................................... 8
- 9.
Drug Interactions ........................................................................................................ 9
9.2. Drug Interactions Overview.......................................................................................... 9
9.3. Drug-Behaviour Interactions ........................................................................................ 9
9.4. Drug-Drug Interactions ................................................................................................. 9
9.5. Drug-Food Interactions ................................................................................................ 9
9.6. Drug-Herb Interactions ................................................................................................. 9
9.7. Drug-Laboratory Test Interactions ............................................................................. 10
- 10.
Clinical Pharmacology ............................................................................................... 10
10.1. Mechanism of Action................................................................................................ 10
10.2. Pharmacodynamics .................................................................................................. 10
10.3. Pharmacokinetics ..................................................................................................... 10
- 11. Storage, Stability, and Disposal ................................................................................. 11
Part 2: Scientific Information ........................................................................................... 12
- 13. Pharmaceutical Information ...................................................................................... 12
- 14. Clinical Trials ............................................................................................................. 13
- 16. Non-Clinical Toxicology ............................................................................................. 23
Patient Medication Information ...................................................................................... 25
Part 1: Healthcare Professional Information
1. Indications
DOVOBET (calcipotriol and betamethasone dipropionate) ointment is indicated for:
- the topical treatment of psoriasis vulgaris for up to 4 weeks.
1.1. Pediatrics
Pediatrics (< 18 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2. Geriatrics
Geriatrics (≥ 65 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2. Contraindications
- DOVOBET is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6. Dosage Forms, Strengths, Composition, and Packaging.
- Ophthalmic use
- Patients with known disorders of calcium metabolism
- Viral (e.g. herpes or varicella) lesions of the skin, fungal or bacterial skin infections, parasitic infections, skin manifestations in relation to tuberculosis or syphilis
- Perioral dermatitis, atrophic skin, striae atrophicae, fragility of skin veins, ichtyosis, acne vulgaris, acne rosacea, rosacea, ulcers and wounds, chicken pox and eruptions following vaccinations
- Erythrodermic, exfoliative and pustular psoriasis
4. Dosage and Administration
4.2. Recommended Dose and Dosage Adjustment
DOVOBET should be applied topically to the affected areas once daily for up to 4 weeks. After satisfactory improvement has occurred, the drug can be discontinued. If recurrence takes place after discontinuation, treatment may be reinstituted.
The maximum daily dose should not exceed 15 g and the maximum weekly dose should not exceed 100 g of DOVOBET and/or other products containing calcipotriol. The total body surface area treated should not exceed 30%.
DOVOBET ointment is not recommended for use in children and adolescents below the age of 18 years.
4.4. Administration
Application under occlusive dressings should be avoided since it increases systemic absorption of corticosteroids.
DOVOBET ointment should not be applied directly to the face, eyes, flexures, groin or genitals (see 7. Warnings and Precautions, Ophthalmologic, and 7. Warnings and Precautions, Skin).
DOVOBET ointment should be gently rubbed on the areas of your skin affected by psoriasis. Wash your hands after using DOVOBET ointment to prevent getting any on your face. No special dressing or cover is needed.
4.5. Missed Dose
If a dose is missed, the patient should apply DOVOBET as soon as he/she remembers and then continue on as usual.
5. Overdose
Due to the calcipotriol component of DOVOBET (calcipotriol and betamethasone dipropionate), excessive administration (i.e. more than the recommended weekly amount of 100 g) may cause elevated serum calcium, which should subside when treatment is discontinued. In such cases, it is recommended to monitor serum calcium levels once weekly until they return to normal. The symptoms of hypercalcemia include polyuria, constipation, muscle weakness, confusion and coma.
Excessive prolonged use of topical corticosteroid containing products, including DOVOBET ointment, may suppress pituitary-adrenal functions, resulting in secondary adrenal insufficiency which is usually reversible. If this occurs, symptomatic treatment is indicated. In cases of chronic toxicity, treatment with DOVOBET ointment must be discontinued gradually.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
Dosage Form: Ointment (faintly translucent white to yellowish ointment)
Packaging: Available in 30 g, 60 g, and 120 g lacquered aluminium tubes (equipped with an aluminium membrane).
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| topical | Ointment, 50 mcg/g calcipotriol (as monohydrate) and 0.5 mg/g betamethasone (as dipropionate) | -α-Tocopherol, butylhydroxytoluene, white soft paraffin, liquid paraffin and polyoxypropylene stearyl ether |
7. Warnings and Precautions
General
DOVOBET ointment should not be used on the face, axillae, flexures, groin, or genitals (see 7. Warnings and Precautions, Skin).
Hypercalcemia, hypercalciuria and hypothalamic-pituitary-adrenal (HPA) axis suppression have been observed with the use of DOVOBET (see 7. Warnings and Precautions, Skin).
Carcinogenesis and Genotoxicity
Calcipotriol when used in combination with ultraviolet radiation (UVR) may enhance the known skin carcinogenic effect of UVR. This potential risk is based on the pre-clinical finding in mice of a reduced time to tumour formation from long term exposure of UVR and topically applied calcipotriol (see 16. Non-Clinical Toxicology, Carcinogenicity).
Patients who apply DOVOBET ointment to exposed skin should avoid excessive exposure to both natural and artificial sunlight (e.g. phototherapy, tanning beds, sun lamps, etc.)
Endocrine and Metabolism
Systemic absorption of topical corticosteroids can produce reversible hypothalamic-pituitary-adrenal (HPA) axis suppression with the potential for clinical glucocorticoid insufficiency. This may occur during treatment or upon withdrawal of the topical corticosteroid.
Factors that predispose a patient using a topical corticosteroid to HPA axis suppression include the use of more potent steroids, use over large surface areas, use over prolonged periods, use under occlusion, use on an altered skin barrier, and use in patients with liver failure.
Application of topical corticosteroid products including DOVOBET ointment on large areas of broken skin (i.e. open sores), on mucous membranes, in skin folds or under occlusive dressings should therefore be avoided. The use of occlusion may increase penetration of the drug into the stratum corneum, increasing the risk of adverse events. Manifestations of Cushing’s syndrome, effects on the metabolic control of diabetes mellitus (e.g. hyperglycaemia, glucosuria) and unmasking of latent diabetes mellitus can also be produced in some patients by systemic absorption of topical corticosteroids. Occlusive dressings should not be applied if body temperature is elevated.
Because of the potential for systemic absorption, use of topical corticosteroids may require that patients be periodically evaluated for HPA axis suppression. An ACTH stimulation test may be helpful in evaluating patients for HPA axis suppression (see 7. Warnings and Precautions, Monitoring and Laboratory Tests).
Hypercalcemia and hypercalciuria have been observed with the use of DOVOBET ointment. If hypercalemia or hypercalciuria develop, treatment should be discontinued until parameters of calcium metabolism have normalized (see 7. Warnings and Precautions, Monitoring and Laboratory Tests).
All of the adverse effects associated with systemic use of corticosteroids, including adrenal suppression, may also occur following topical administration of corticosteroid containing products such as DOVOBET, especially in children.
Monitoring and Laboratory Tests
Treatment with DOVOBET in the recommended amounts (See 4. Dosage and Administration) does not generally result in changes in laboratory values. However, in patients at risk for hypercalcaemia it is recommended that baseline serum calcium levels be obtained before starting treatment with subsequent monitoring of serum calcium levels at suitable intervals. If serum calcium becomes elevated, DOVOBET administration should be discontinued and serum calcium levels should be measured once weekly until they return to normal. Patients with marginally elevated serum calcium may be treated with DOVOBET, provided that serum calcium is monitored at suitable intervals.
An ACTH stimulation test may be helpful in evaluating patients for HPA axis suppression. If HPA axis suppression is documented, an attempt should be made to gradually withdraw the drug, reduce the frequency of application, or substitute a less potent steroid. Manifestations of adrenal insufficiency may require supplemental systemic corticosteroids. Recovery of HPA Axis function is generally prompt and complete upon discontinuation of topical corticosteroids (see 7. Warnings and Precautions, Endocrine and Metabolism and 10. Clinical Pharmacology).
Ophthalmologic
DOVOBET ointment is not for ophthalmic use. DOVOBET ointment may cause eye irritation. Avoid contact with the eyes or conjunctiva.
Skin
DOVOBET ointment contains a potent World Health Organization (WHO) group III steroid and concurrent treatment with other corticosteroids on the same treatment area must be avoided.
DOVOBET ointment should not be used on the face, axillae, flexures, groin or genitals. The patient must be instructed in the correct use of DOVOBET ointment (e.g. washing their hands after each application) to avoid accidental transfer or application to these regions or to the mouth, mucous membranes or eyes (see 4. Dosage and Administration). Should facial dermatitis develop, treatment with DOVOBET ointment should be discontinued.
With long-term use, there is an increased risk of local and systemic corticosteroid adverse reactions. Treatment should be discontinued in case of corticosteroid adverse reactions related to long-term use of DOVOBET ointment (see 8. Adverse Reactions).
When treating psoriasis with topical corticosteroid containing products, including DOVOBET ointment for a prolonged period of time, it is recommended that treatment be interrupted periodically. There may be a risk of generalised pustular psoriasis or rebound psoriasis when discontinuing corticosteroids (see 8. Adverse Reactions). Medical supervision should therefore continue in the post-treatment period.
Concomitant skin infections should be treated with an appropriate antimicrobial agent. If the infection worsens, DOVOBET ointment should be discontinued until the infection has been adequately treated.
7.1. Special Populations
7.1.1. Pregnancy
The safety of calcipotriol and/or topical corticosteroids for use during pregnancy has not been established. Although studies in experimental animals have not shown teratogenic effects with calcipotriol, studies with corticosteroids have shown teratogenic effects. The use of DOVOBET is not recommended in pregnant women.
7.1.2. Breastfeeding
The safety of calcipotriol and/or topical corticosteroids for use in nursing women has not been established. It is not known whether calcipotriol can be excreted in breast milk. Batamethasone passes into breast milk, but it is not known if topical application of corticosteroid containing products, including DOVOBET, can lead to sufficient systemic absorption to produce detectable quantities in breast milk. Caution should be exercised when prescribing DOVOBET to women who breastfeed. The patient should be instructed not to use DOVOBET on the breast when breastfeeding.
7.1.3. Pediatrics
Pediatrics (<18 years of age): There is no clinical trial experience with the use of DOVOBET in children. Children may demonstrate greater susceptibility to systemic steroid related adverse effects due to a larger skin surface area to body weight ratio as compared to adults.
7.1.4. Geriatrics
Geriatrics (≥ 65 years): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
8. Adverse Reactions
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
In clinical trials, the most common adverse reaction associated with DOVOBET (calcipotriol and betamethasone dipropionate) was pruritus. Pruritus was usually mild and no patients were withdrawn from treatment.
In a randomized, double-blind, parallel group, safety study of psoriasis patients with at least moderate disease severity, DOVOBET ointment was used intermittently on an 'as needed' basis under medical supervision (N=207). Patients were followed for up to 52 weeks. The median amount of study drug used was 15.4 g/week. The effects of DOVOBET ointment on calcium metabolism were not studied and the effects on adrenal suppression were not adequately studied. The following adverse drug reactions were reported in 1% or more of patients: pruritus (5.8%), psoriasis (5.3%), skin atrophy (based on a dermatologist’s visual assessment) (1.9%), folliculitis (1.9%), skin burning sensation (1.4%), application site skin depigmentation (1.4%), and erythema (1.0%). One case of serious flare-up of psoriasis was reported.
Other Adverse Drug Reactions
Adverse reactions observed for the individual drug substances calcipotriol and betamethasone dipropionate are described below.
Calcipotriol
Adverse reactions include application site reactions, pruritus, skin irritation, burning and stinging sensation, dry skin, erythema, rash, dermatitis, eczema, aggravated psoriasis, photosensitivity and hypersensitivity reactions including very rare cases of angioedema and facial oedema. Very rare cases of hypercalcaemia or hypercalciuria have been reported (see 7. Warnings and Precautions).
Betamethasone dipropionate
Local reactions can occur after topical use especially during prolonged application. These include dryness, itching, burning, local irritation, skin atrophy, telangiectasia, striae, folliculitis, hypertrichosis, perioral dermatitis, allergic contact dermatitis, depigmentation, colloid milia, maceration of the skin and secondary infection. When treating psoriasis with topical corticosteroids and following reduction or discontinuation of treatment, there are reports of the development of pustular psoriasis from chronic plaque psoriasis.
Systemic reactions due to topical use of corticosteroid containing products, including DOVOBET in adults occur infrequently but can be severe. Adrenocortical suppression, cataract, infections, impact on the metabolic control of diabetes mellitus and increase of intra-ocular pressure can occur, especially after long-term treatment. Application of DOVOBET under occlusion, on large areas or for prolonged treatment periods may result in an increased risk of systemic adverse events and is therefore not recommended (see 7. Warnings and Precautions).
9. Drug Interactions
9.2. Drug Interactions Overview
No drug interaction studies have been performed with DOVOBET.
9.3. Drug-Behaviour Interactions
The interaction of DOVOBET with individual behavioural risks (e.g. cigarette smoking, cannabis use, and/or alcohol consumption) has not been studied.
9.4. Drug-Drug Interactions
Interactions with other drugs have not been established.
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
DOVOBET is a combination of the vitamin D analogue calcipotriol and the corticosteroid betamethasone dipropionate.
Calcipotriol is a non-steroidal antipsoriatic agent, derived from the naturally occurring vitamin D. Calcipotriol exhibits a vitamin D-like effect by competing for the 1,25(OH)2D3 receptor. Calcipotriol is as potent as 1,25(OH)2D3, the naturally occurring active form of vitamin D, in regulating cell proliferation and cell differentiation, but much less active than 1,25(OH)2D3 in its effect on calcium metabolism. Calcipotriol induces differentiation and suppresses proliferation of keratinocytes (without any evidence of a cytotoxic effect), thus reversing the abnormal keratinocyte changes in psoriasis. The therapeutic goal envisaged with calcipotriol is thus a normalization of epidermal growth.
Topical corticosteroids such as betamethasone dipropionate have anti-inflammatory, anti-pruritic, and vasoconstrictive properties. The mechanism of the anti-inflammatory activity is generally unclear. However, corticosteroids are thought to induce phospholipase A2 inhibitor proteins, preventing arachidonic acid release and the biosynthesis of potent mediators of inflammation.
10.2. Pharmacodynamics
Adrenal response to ACTH was determined by measuring serum cortisol levels in patients with both extensive scalp and body psoriasis, using up to 106 g per week combined DOVOBET gel (on the scalp) and DOVOBET ointment (on the body) (study A). A borderline decrease in cortisol response at 30 minutes post ACTH challenge was seen in 5 of 32 patients (15.6%) after 4 weeks of treatment and in 2 of 11 patients (18.2%) who continued treatment until 8 weeks. In all cases, the serum cortisol levels were normal at 60 minutes post ACTH challenge. There was no evidence of change of calcium metabolism observed in these patients.
In addition, HPA axis suppression was evaluated in adult patients (n=43) with extensive psoriasis involving 15-30% of the body surface area (including the scalp) (study B). Treatment consisted of once daily application of DOVOBET gel on the body and the scalp for up to 8 weeks. Adrenal suppression, as indicated by a 30-minute post-stimulation cortisol level ≤18 mcg/dL, was observed in 3 of 43 patients (7%) after 4 weeks of treatment and in 0 of the 36 patients who provided data after 8 weeks treatment.
10.3. Pharmacokinetics
A pharmacokinetic study of calcipotriol ointment demonstrated that the apparent systemic absorption over 12 hours is approximately 5.5% of the dose in normal subjects and in psoriatic patients. Topical application of corticosteroids to normal skin results in minimal absorption. Only small amounts of drug reach the dermis and are then absorbed into the systemic circulation. However, absorption may be greater when corticosteroids are applied to certain areas of the body (such as the axilla and scrotum) or if the epidermis is damaged by disease or inflammation. Continued absorption of corticosteroids may occur, even after washing, due to retention of the drug in the stratum corneum. The individual pharmacokinetics of calcipotriol and betamethasone dipropionate, are not affected by their combined presence in DOVOBET ointment. Under normal conditions of use, systemic absorption of calcipotriol and/or betamethasone dipropionate from DOVOBET is not expected to have any effects.
- 11. Storage, Stability, and Disposal
Store at 5 to 25°C. Use within 12 months of first opening the tube.
For easy application do not refrigerate, this is to prevent pulling of delicate skin.
Part 2: Scientific Information
13. Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance(s):
Calcipotriol monohydrate
Betamethasone dipropionate
Chemical name:
9,10-Secochola-5,7,10(19),22-tetraene-1,3,24-triol, 24-cyclo-propyl-, monohydrate, (1α,3β,5Z,7E,22E,24S)
Pregna-1,4-diene-3,20-dione,9-fluoro-11-hydroxy-16-methyl-17,21-bis(1-oxopropoxy)-(11β,16β)
Alternative chemical
20(R)-(3'(S)-Cyclopropyl-3'-hydroxyprop-1'(E)-enyl)-1(S),3(R)-dihydroxy-9-10-Secopregna-5(Z),7(E),10(19)-triene, hydrate
9-fluoro-11β,17,21-trihydroxy-16β-methylpregna-1,4-diene-3,20-dione 17,21-dipropionate
Laboratory code name:
MC 903 monohydrate
MC 903, H20
433 or 433/M
Molecular formula and molecular mass:
C27H40O3, H2O
430.6
C28H37FO7
504.6
Chirality:
The calcipotriol molecule is one single stereoisomer. The absolute configuration of the chiral centres at carbon atoms nos. 1, 3, 13, 14, 17, 20 and 24 is indicated in the structural formula below.
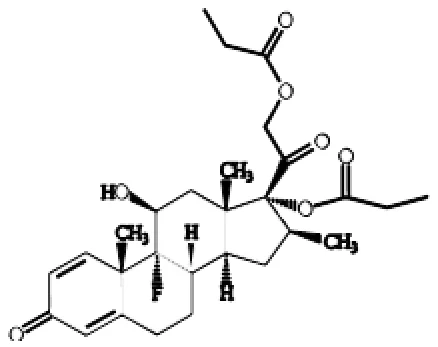
Structural formula:
Physicochemical properties:
Physical form:
White or almost white crystalline substance.
White or almost white crystalline powder.
Solubility at room temperature:
Freely soluble in ethanol, soluble in chloroform and propylene glycol, practically insoluble in liquid paraffin. Solubility in water is 0.6 mcg/ml.
Freely soluble in acetone, in dioxane, in dichloromethane and in chloroform; soluble in methanol; sparingly soluble in alcohol; slightly soluble in ether; insoluble in water and in hexane.
Melting point:
166-168 °C
176-180 °C
Polymorphism:
So far no signs have indicated the existence of polymorphic
forms.
Other characteristics:
Calcipotriol is a vitamin D derivative. It is well-known that vitamin D in solution forms a reversible temperature dependent equilibrium between vitamin D and pre-vitamin D (described in (i.e.) J Pharm Sci 1968; 57:1326). In the same way, solutions of calcipotriol establish an equilibrium with “pre-calcipotriol”. The structural formula of “pre-calcipotriol” is shown below.
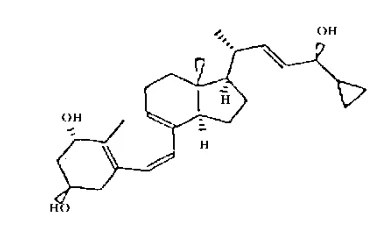
14. Clinical Trials
A large multicentre, randomized, double-blind clinical trial has shown DOVOBET ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg/g betamethasone (as dipropionate)) administered twice daily to be more efficacious and to provide faster onset of action than either of the individual components alone (calcipotriol or betamethasone dipropionate) for the treatment of plaque psoriasis. These findings were supported by a second large, multicentre, randomised, double-blind trial comparing DOVOBET twice daily to calcipotriol and betamethasone dipropionate, each in their currently marketed formulations. A third large, multicentre, randomised, double-blind trial found DOVOBET once daily to be more efficacious than vehicle alone and calcipotriol twice daily (betamethasone dipropionate alone was not evaluated). It was also demonstrated that once daily DOVOBET was similar to twice daily DOVOBET for most of the efficacy measures. In all three studies, DOVOBET was effective in terms of reducing PASI (Psoriasis Area and Severity Index) score and thickness of target lesions. Furthermore, a significant proportion of patients on DOVOBET achieved marked improvement or clearance at the end of 4 weeks of treatment. Clinical improvement occurred rapidly and a significant improvement was evident within 1 week of treatment. DOVOBET was well tolerated with the most common adverse reaction being mild pruritus. In one additional study, patients were treated with DOVOBET once daily for 8 weeks. Optimal population results in this study were seen between 4 and 5 weeks of treatment. The therapeutic goal envisioned with DOVOBET is to provide an effective, rapid acting topical agent for initial treatment of psoriasis and/or for treatment of flare-ups of psoriasis.
In a randomized, double-blind, parallel group, safety study, patients with at least moderate disease severity were given DOVOBET ointment intermittently on an 'as needed' basis under medical supervision (N=207). Patients were followed for up to 52 weeks. The median amount of study drug used was 15.4 g/week. The effects of DOVOBET ointment on calcium metabolism were not studied and the effects on adrenal suppression were not adequately studied. The following adverse drug reactions were reported in 1% or more of patients: pruritus (5.8%), psoriasis (5.3%), skin atrophy (based on a dermatologist’s visual assessment) (1.9%), folliculitis (1.9%), burning sensation (1.4%), skin depigmentation (1.4%), and erythema (1.0%). One case of serious flare-up of psoriasis was reported.
Special Studies
Effects on adrenal function and calcium metabolism were investigated in an open-label study in 35 patients with extensive psoriasis on both scalp (at least 30% of scalp area) and body (15-30% of body surface area). Patients used an average of 23.7 g/week DOVOBET gel on the scalp and an average of 40.2 g/week DOVOBET ointment on the body. Adrenal response to ACTH was determined by measuring serum cortisol levels 30 and 60 minutes after ACTH challenge. A borderline decrease in cortisol response at 30 minutes post ACTH challenge was seen in 5 of the 32 evaluable patients (15.6%) after 4 weeks of treatment and in 2 of 11 patients (18.2%) who continued treatment until 8 weeks. In all cases, the serum cortisol levels were normal at 60 minutes post ACTH challenge. There was no evidence of a change in calcium metabolism observed in these patients.
Effects on adrenal function and calcium metabolism were also investigated using only DOVOBET gel in an open-label study in 43 adult patients with extensive psoriasis involving 15-30% of the body surface area (including the scalp). Treatment consisted of once daily application of DOVOBET gel on the body and the scalp for up to 8 weeks. Adrenal response to ACTH was determined by measuring serum cortisol levels 30 and 60 minutes after ACTH challenge. The mean baseline extent of psoriasis was 20.6% of body surface area. The mean amount of study drug used over the total treatment period was 52.3 g/week (range 7.6 g/week to 92.9 g/week).
Three (7.0%) subjects had a serum cortisol ≤18 mcg/dL 30 minutes after the ACTH stimulation test at week 4. None of the 36 subjects who continued to week 8 and had samples with data had a 30 minute serum cortisol ≤18 mcg/dL. The adrenal suppression was considered borderline in two of these subjects because the 30 minute value was only slightly below the defined cut off level and the 60 minute value showed adequate response. One subject showed clear signs of adrenal suppression with a cortisol level lower than the cut off level at both 30 and 60 minutes. There were no clinically relevant changes in mean serum or urinary calcium levels. Elevated urinary calcium levels outside the normal range were observed in 2 patients (1 at 4 weeks and 1 at 8 weeks).
SUMMARY OF CLINICAL TRIALS
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9903 DE | Design: Randomised, double-blind, right/left comparison on the forearm. Inclusion Criteria: Healthy volunteers. Treatment Period: Twice daily topical application for 4 weeks (28 days). Treatment Groups: Phase I: (1) Dovobet ointment (50 mcg/g calcipotriol ( as monohydrate) plus 0.5 mg betamethasone (as dipropionate); (2) Betamethasone dipropionate ointment (0.5 mg/g). (n=30) Phase II: (1) Dovobet ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg betamethasone (as dipropionate); (2) Placebo ointment. (n=15) | Evaluation Criteria: Sonography was performed on day 1. Sonography and clinical assessments of atrophy, telangiectasia and erythema) were performed on days 8, 15, 22 and 29. Skin biopsies were taken from 10 subjects on day 29 for morphometric determination of epidermal and dermal thickness and epidermal cell layers. Sonography and clinical assessments were repeated 2 weeks after treatment (day 43) in subjects who did not have a biopsy taken. Results: There were no clinical signs of atrophy, telangiectasia or irritation (erythema). Sonography demonstrated skin thinning with Dovobet relative to placebo ointment but similar to betamethasone dipropionate (12.3% and 13.2% respectively) after 4 weeks of treatment. There were no histological differences in epidermal or dermal thickness between Dovobet and betamethasone dipropionate. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9902 FR | Design: Single centre, randomised, double-blind, bioequivalence study according to FDA guideline for vasoconstrictor assays. Inclusion Criteria: Healthy volunteers. Treatment Period: Pilot Phase: Single 10 mcl application on the ventral forearm for 0.25, 0.5, 0.75, 1, 1.5, 2, 4, and 6 hours followed up to 24 hours. Pivotal Phase: (1) Single 10 mcl application of Dovobet and betamethasone dipropionate ointment (Diprosone*) at a dose-duration corresponding to ED50 (1h04min) on two sites each per forearm. (2) Betamethasone dipropionate was also applied on two sites per forearm at dose-durations corresponding to 0.5 times ED50 (32 min.) and 2 times ED50 (2h08min.) Treatment: Pilot Phase: Diprosone* (0.5 mg/g betamethasone (as dipropionate)). (n=12) Pivotal Phase: (1) Dovobet (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg/g betamethasone (as dipropionate)) ointment; (2) Diprosone* (0.5 mg/g betamethasone (as dipropionate)). (n=90) | Evaluation Criteria: Skin blanching (vasoconstrictor) assessed using the chromametric a value and visual scoring. Results: Pilot Part: Betamethasone dipropionate ointment (Diprosone*) produced a dose-duration dependent vasoconstriction with an ED50 (half maximal response) of 1h04min., D1 (0.5 times ED50) of 32 min and D2 (2 times ED50) of 2h08 min. 67% of the included subjects were ‘detectors’ (AUC at D1 was at least 1.25 time the AUC at D2). Pivotal Part: Betamethasone dipropionate in Dovobet ointment is bioequivalent to the reference product, Diprosone* ointment, as the 90% confidence interval for the skin blanching response ratio (test to reference) is [0.81; 1.04] and within the interval [0.80; 1.25] as defined by the applicable FDA guideline. * registered trademark of Schering-Plough Ltd. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9801 NL | Design: Single centre, open, randomised, multiple (2 application sites on the thigh) topical absorption study. Inclusion Criteria: Healthy volunteers. Treatment Period: Single 12 hour application. Treatment: Dovobet (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg/g betamethasone (as dipropionate)) ointment containing 3H-labelled calcipotriol. (n=4) | Evaluation Criteria: Pharmacokinetic parameters: Recovery of 3H-radioactivity from gauzes, gloves, swabs and shorts; excretion of 3H-radioactivity in urine and faeces; 3H-radioactivity levels in serum. Safety parameters: adverse events, local tolerability results, vital signs, ECG parameters and clinical laboratory parameters. Results: Excretion and recovery data suggest that there is only minimal systemic absorption of calcipotriol. The ointment was well tolerated. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9901 NL | Design: Single centre, open, randomised, multiple (2 application sites on the thigh) topical absorption study. Inclusion Criteria: Healthy volunteers. Treatment Period: Single 12 hour application of 3H labelled ointment and single 12 hour application after 4 weeks of twice daily topical application of unlabelled ointment. Treatment Groups: Group I: Single 12 hour application of 2.5 g Dovonex (50 mcg/g calcipotriol) ointment containing 3H labelled calcipotriol. Four weeks (28 days) of twice daily treatment with unlabelled Dovonex. On day 36, another single 12 hour application of Dovonex containing 3H labelled calcipotriol. (n=6) Group II: Single 12 hour application of 2.5 g Dovobet (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg/g betamethasone (as dipropionate) ointment containing 3H labelled calcipotriol. Four weeks (28 days) of twice daily treatment with unlabelled Dovobet. On day 36, another single 12 hour application of Dovobet containing 3H labelled calcipotriol. (n=6) Group III: Single 12 hour application of 2.5 g Dovobet ointment vehicle containing 3H labelled calcipotriol. Group IV: Single 12 hour application of 2.5 g Dovobet ointment containing 3H labelled betamethasone dipropionate. Group V: Single 12 hour application of 2.5 g Dovobet ointment vehicle containing 3H labelled betamethasone dipropionate. | Evaluation Criteria: Pharmacokinetic parameters: Recovery of 3H radioactivity from gauzes, gloves, swabs and shorts; excretion of 3H radioactivity in urine and faeces; 3H radioactivity levels in serum. Safety parameters: adverse events, local tolerability results, vital signs, ECG parameters and clinical laboratory parameters. Results: The absorption of calcipotriol after a single application of Dovobet is similar to absorption after application of the other marketed formulation of calcipotriol (i.e. Dovonex®; 50 mcg/g calcipotriol (as monohydrate)). Thus, the safety profile of Dovonex is applicable to Dovobet. Betamethasone dipropionate in Dovobet does not influence the absorption rate of calcipotriol and vice versa calcipotriol does not affect the absorption of betamethasone dipropionate. Absorption of calcipotriol is similar after 4 weeks of treatment with Dovobet as it is after a single application. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9802 INT | Design: Multi-centre, randomised, double-blind, vehicle-controlled, parallel-group study. Inclusion Criteria: Plaque psoriasis amenable to topical treatment. Treatment Period: Twice daily topical application for 4 weeks of active treatment. Treatment Groups: (1) Combination ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg betamethasone (as dipropionate); Dovobet), (n=301); (2) Calcipotriol ointment (50 mcg/g), (n=308); (3) Betamethasone dipropionate ointment (0.5 mg/g), (n=313); (4) Ointment vehicle, (n=108) | Evaluation Criteria: Change in PASI score after 4 weeks of treatment, speed of response (change in PASI score after 1 week of treatment), change in plaque thickness of a target lesion, investigators’ overall assessment of treatment response (clearance or marked improvement) at the end of treatment, patient assessment of overall treatment response, patient assessment of treatment acceptability, adverse events, and serum biochemistry. Results: Dovobet combination treatment was effective and provided a more rapid onset of action than either of the individual components (calcipotriol or betamethasone dipropionate). At the end of 4 weeks treatment, PASI score was reduced by 73% with Dovobet, 49% with calcipotriol, 63% with betamethasone dipropionate and 29% with vehicle (p<0.001). After 1 week of treatment PASI score was reduced by 48% with Dovobet, 28% with calcipotriol, 41% with betamethasone dipropionate and 22% with vehicle (p<0.001). The greatest reduction in target lesion thickness was observed with Dovobet. Plaque thickness was reduced by 79% with Dovobet compared to 54% with calcipotriol, 67% with betamethasone dipropionate and 27% with vehicle (p<0.001). The greatest treatment response according to the investigators’ overall assessment was also observed in the Dovobet group. With Dovobet combination treatment 76% of patients achieved clearance or marked improvement compared to 33% with calcipotriol, 56% with betamethasone dipropionate and 8% with vehicle (p<0.001). Adverse reactions associated with Dovobet were similar to reactions with betamethasone dipropionate. Mild pruritus was the most common adverse reaction. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9904 INT | Design: Multi-centre, randomised, double-blind, vehicle-controlled, parallel-group study. Inclusion Criteria: Plaque psoriasis amenable to topical treatment. Treatment Period: Phase 1: Twice daily topical application of active treatment (double-blind) for 4 weeks. Phase 2: twice daily maintenance therapy with Dovonex® (open-label) for 4 weeks. Treatment Groups: Phase 1: (1) Dovobet ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg betamethasone (as dipropionate)), (n=369); (2) Dovonex® ointment (50 mcg/g calcipotriol, Leo Pharmaceutical Products), (n=365); (3) Diprosone* ointment (0.5 mg/g betamethasone (as dipropionate), Schering-Plough Ltd.), (n=363) Phase 2: Patients from each of the above groups (n=344, 332, and 344, respectively) transferred to Dovonex® ointment. | Evaluation Criteria: Phase 1: Change in PASI score after 4 weeks of treatment, speed of response (change in PASI score after 1 week of treatment), change in plaque thickness of a target lesion, investigators’ overall assessment of treatment response (clearance or marked improvement) at the end of treatment, patient assessment of overall treatment response, change in redness and scaliness of a target lesion, adverse events, and serum biochemistry. Phase 2: general evaluation of transfer to Dovonex® maintenance therapy. Results: Dovobet combination treatment was effective and provided a more rapid onset of action than either of the individual components in their currently marketed formulations (Dovonex® and Diprosone*). At the end of 4 weeks treatment, PASI score was reduced by 74% with Dovobet, 55% with Dovonex®, and 61% with Diprosone* (p<0.001). After 1 week of treatment PASI score was reduced by 47% with Dovobet, 31% with Dovonex®, and 40% with Diprosone* (p<0.001). The greatest reduction in target lesion thickness was observed with Dovobet. Plaque thickness was reduced by 79% with Dovobet compared to 63% with Dovonex®, and 62% with Diprosone* (p<0.001). The greatest treatment response according to the investigators’ overall assessment was also observed in the Dovobet group. With Dovobet combination treatment 68% of patients achieved clearance or marked improvement compared to 39% with Dovonex®, and 47% with Diprosone* (p<0.001). Adverse reactions associated with Dovobet were predictable based on the individual components with mild pruritus being the most common adverse reaction. Patients were safely transferred to maintenance therapy with Dovonex®. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 9905 INT | Design: Multi-centre, randomised, double-blind, vehicle-controlled, parallel-group study. Inclusion Criteria: Plaque psoriasis amenable to topical treatment. Treatment Period: Active topical treatment once or twice daily for 4 weeks. To maintain blinding, the once daily group received vehicle in the morning and study medication in the evening. Treatment Groups: (1) Dovobet combination ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg betamethasone (as dipropionate)) once daily, (n=150); (2) Dovobet ointment twice daily, (n=234); (3) Dovonex ® ointment (50 mcg/g calcipotriol) twice daily, (n=227); (4) Ointment vehicle twice daily, (n=207). | Evaluation Criteria: Change in PASI score after 4 weeks of treatment, speed of response (change in PASI score after 1 week of treatment), change in plaque thickness of a target lesion, investigators’ overall assessment of treatment response (clearance or marked improvement) at the end of treatment, patient assessment of overall treatment response, patient assessment of treatment acceptability, change in redness and scaliness of target lesion, adverse events, and serum biochemistry. Results: Once daily Dovobet combination treatment was as effective as twice daily Dovobet treatment but more effective than twice daily Dovonex® treatment. At the end of 4 weeks, PASI score was reduced by 69% with Dovobet once daily, 59% with Dovonex® twice daily, and 27% with vehicle twice daily (p<0.001). Reduction in PASI after 4 weeks of twice daily Dovobet treatment (74%) was similar to that after once daily Dovobet treatment (p=0.052). After 1 week of treatment PASI score was reduced by 46% with Dovobet once daily, 34% with Dovonex® twice daily, and 20% with vehicle twice daily (p<0.001). The speed of response to Dovobet twice daily treatment was similar to that after Dovobet once daily treatment, with the reduction in PASI after one week being 48%. The greatest reduction in target lesion thickness was observed with Dovobet, with similar reductions occurring after once daily (74%) and twice daily (78%) treatment. The greatest treatment response according to the investigators’ overall assessment was also observed in the Dovobet groups, with twice daily treatment favoured over once daily. Adverse reactions associated with Dovobet were predictable based on the individual components with mild pruritus being the most common adverse reaction. |
SUMMARY OF CLINICAL TRIALS (continued)
| STUDY CODE | STUDY DESIGN | EVALUATION CRITERIA AND RESULTS |
| MCB 0003 INT | Design: Multi-centre, randomised, double-blind, vehicle-controlled, parallel-group study. Inclusion Criteria: Plaque psoriasis amenable to topical treatment. Treatment Period: Active topical treatment once daily for 4 weeks. Treatment Groups: (1) Dovobet combination ointment (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg betamethasone (as dipropionate) once daily, (n=490); (2) Calcipotriol ointment (50 mcg/g calcipotriol) once daily, (n=480); (3) Betamethasone dipropionate ointment (0.5 mg/g betamethasone (as dipropionate)) once daily, (n=476); (4) Vehicle ointment once daily, (n=157). | Evaluation Criteria: Change in PASI score after 4 weeks of treatment, controlled disease after 4 weeks of treatment, speed of response (change in PASI score after 1 week of treatment), treatment success, and adverse events. Results: Once daily Dovobet combination treatment was more effective than once daily application of its individual components or vehicle. At the end of 4 weeks, PASI score was reduced by 71% with Dovobet, 46% with calcipotriol, 57% with betamethasone dipropionate and 23% with vehicle (p<0.001). The percentage of patients with controlled disease at the end of treatment was 56% for Dovobet, 22% for calcipotriol, 37% for betamethasone dipropionate and 10% for vehicle (p<0.001). After 1 week of treatment PASI score was reduced by 39% with Dovobet, 23% with calcipotriol, 33% with betamethasone dipropionate and 18% with vehicle ((p0.001). The proportion of patients with treatment success was 65% with Dovobet, 29% with calcipotriol, 46% with betamethasone dipropionate, and 10% with vehicle (p<0.001). Adverse reactions associated with Dovobet were predictable based on the individual components with mild pruritus being the most common adverse reaction. |
16. Non-Clinical Toxicology
General toxicology
Systemic Toxicity of Calcipotriol
Despite the intended topical use of calcipotriol in the treatment of psoriasis, most of the toxicological studies were performed using the oral route of administration. This was done to assure maximum exposure to the compound. From these studies it was evident that toxicity associated with the administration of pharmacologically excessive doses of calcipotriol was due to the calcitropic activity of the compound. The maximum doses were 54 mcg/kg/day in rats, 18 mcg/kg/day in minipigs and 3.6 mcg/kg/day in dogs. In the acute, subacute and chronic toxicity studies the main signs of toxicity were loss of bodyweight, increases in plasma or serum calcium, creatinine and urea, renal toxicity and soft tissue calcifications. These changes resulted from the exaggerated absorption of calcium and phosphorous from the intestine and are characteristic of vitamin D overdosage. The kidney was the main target organ of toxicity and tubular lesions and calcifications were apparent after prolonged hypercalcemia in all species investigated. These types of changes, however, are not considered indicative of a human risk, since less than 1% of calcipotriol is absorbed through the skin in man and there is no evidence of calcitropic effects in man with the prescribed dose.
Dermal Toxicity of Calcipotriol
Dermal toxicity of calcipotriol was limited to a slight-to-moderate skin irritative effect. The studies performed with calcipotriol ointment showed that the incidence and severity of skin irritation was slightly less in the calcipotriol-treated group than in the placebo ointment group. The formulation of the ointment base is analogous to that employed for a number of steroids available for the treatment of psoriasis. Skin thinning, as seen with steroid application, was not observed with the calcipotriol ointment.
Dermal Tolerability of DOVOBET (50 mcg/g calcipotriol (as monohydrate) plus 0.5 mg/g betamethasone (as dipropionate)): Two dermal tolerability studies were conducted in rabbits. In the first study, no skin irritation was observed and only slight irritation attributed primarily to calcipotriol was observed in the second study. A gradual reduction in skin thickness was observed over 6 weeks which was attributed to betamethasone dipropionate. However, the stratum corneum of rabbit skin is much thinner than that of humans and rabbits are very sensitive to skin irritants.
Carcinogenicity
Calcipotriol: A dermal carcinogenicity study in mice showed no indications of increased carcinogenic risks. Calcipotriol solution was applied topically for up to 24 months at doses of 3, 10 and 30 mcg/kg/day (corresponding to 9, 30 and 90 mcg/m2/day). The high-dose was considered to be the Maximum Tolerated Dose for dermal treatment of mice with calcipotriol. Survival was decreased at 10 and 30 mcg/kg/day; particularly in the males. The reduced survival was associated with an increased incidence of obstructive uropathy, most probably caused by treatment-related changes in the urinary composition. This is an expectable effect of treatment with high doses of calcipotriol or other vitamin D analogues. There were no dermal effects and no dermal or systemic carcinogenicity.
Photo(co)carcinogenicity:
Calcipotriol: In a study where albino hairless mice were repeatedly exposed to both ultraviolet radiation (UVR) and topically applied calcipotriol for 40 weeks at the same dose levels as in the dermal carcinogenicity study (see above), a reduction in the time required for UVR light to induce the formation of skin tumours was observed (statistically significant in males only), suggesting that calcipotriol may enhance the effect of UVR to induce skin tumours. The clinical relevance of these findings is unknown.
Betamethasone dipropionate: No carcinogenicity or photocarcinogenicity studies have been performed with betamethasone dipropionate.
Reproductive and developmental toxicology
Reproduction studies have shown that calcipotriol has no effect on fertility in male and female rats nor on their F1 generation progeny. Fetal toxicity and teratogenicity studies showed no evidence of embryotoxic or teratogenic effects in rats and rabbits. Peri- and post-natal development studies indicated that calcipotriol had no toxic effects on the F1 or F2 generation. There was also no evidence for a mutagenic or clastogenic potential with calcipotriol.