


Patient Medication Information: uses, side effects, how to take - Estraderm-50
ABOUT THIS MEDICATION
What the medication is used for:
ESTRADERM* should not be used by women with intact uteri unless taken with an appropriate dosage of a progestin.
The relief of menopausal and
postmenopausal symptoms
- To prevent osteoporosis
Some women are more likely to develop osteoporosis after menopause than others. If you have been prescribed ESTRADERM* only for the prevention of osteoporosis you should discuss other alternative therapies with your doctor. In addition, you should discuss adequate diet, calcium and vitamin D intake, cessation of smoking and regular physical weight-bearing exercise with your doctor or pharmacist.
If you have not had a hysterectomy (operation to remove the womb), estrogens should be prescribed in association with a progestin
ESTRADERM* should be used only under the supervision of a doctor, with regular follow-up at least once a year to identify side effects associated with its use. Your first follow-up visit should be within 3 to 6 months of starting treatment. Your visit may include a blood pressure check, a breast exam, a Pap smear and pelvic exam. You should have a mammogram before starting treatment and at regular intervals as recommended by your doctor. Your doctor may recommend some blood tests.
You should carefully discuss the risks and benefits of hormone replacement therapy (HRT) with your doctor. You should regularly talk with your doctor about whether you still need treatment with HRT.
What it does:
The main estrogen produced by your ovaries prior to menopause is estradiol, and this is the same estrogen that is in ESTRADERM*. When applied to the skin, the ESTRADERM* patch continually releases small, controlled quantities of estradiol, which pass through your skin and into your bloodstream. The amount of estrogen prescribed depends on your body's needs. Your doctor may adjust the amount you get by prescribing another (different) patch size.
By providing estradiol, ESTRADERM* offers relief from menopausal symptoms, slows down bone loss and may prevent bones from breaking.
Your body normally makes estrogens and progesterone (female hormones) mainly in the ovaries. Between ages 45 and 55, the ovaries gradually stop making estrogens. This leads to a decrease in body estrogen levels and a natural menopause (the end of monthly menstrual periods). If both ovaries are removed during an operation before natural menopause takes place, the sudden decrease in estrogen levels causes "surgical menopause".
Menopause is not a disease - it is a natural life event and different women experience menopause and its symptoms differently. Not all women suffer obvious symptoms of estrogen deficiency. When the estrogen levels begin decreasing, some women develop very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest, or sudden intense episodes of heat and sweating ("hot flashes" or "hot flushes"). Using estrogen drugs can help the body adjust to lower estrogen levels and reduce these symptoms.
Osteoporosis is a thinning of the bones that makes them weaker and allows them to break more easily. In osteoporosis, the bones of the spine, wrists and hips break most often. The bones of both men and women start to thin after about age 40, but women lose bone faster after menopause. Using estrogens after menopause slows down bone thinning and may prevent bones from breaking.
When it should not be used
Certain medical conditions may be aggravated by estrogens, therefore estrogens should not be used at all under these conditions.
ESTRADERM* should not be used under these conditions:
if you are pregnant or think you may be
pregnant. Since pregnancy may be possible early in menopause while you are still having spontaneous periods, the use of non-hormonal birth control should be discussed with your physician at this time. If you take estrogen during pregnancy, there is a small risk of your unborn child having birth defects.
if you are breast-feeding. Ask your doctor
or pharmacist for advice
if you currently have or have ever had
cancer of the breast, or uterus or endometrium (lining of the womb) or any other cancer which is sensitive to estrogens
if you have been diagnosed with endometrial
hyperplasia (overgrowth of the lining of the uterus)
if you have unexplained changes in
unexpected or unusual genital bleeding
if you have active thrombophlebitis
(inflamed varicose veins)
if you currently have a problem with
abnormal blood clots forming in your blood vessels. or have ever had such a problem in the past. This may cause painful inflammation of the veins (thrombophlebitis) or blockage of a blood vessel in the legs (deep vein thrombosis), lungs (pulmonary embolism) or other organs
if you have ever had coronary heart disease,
a heart attack or stroke
- if you currently have a serious liver disease
- if you have migraine
if you have had partial or complete loss of
vision due to blood vessel disease in the eye
if you have a disease of blood pigment
called porphyria
if you have ever had any unusual allergic
reaction to estrogens or any other component of the patch (see What the medicinal ingredient is and What the nonmedicinal ingredients are)
ESTRADERM* is not a contraceptive, nor will it restore fertility.
Talk to your doctor if you have any further questions or if you think that any of the above may apply to you.
What the medicinal ingredient is:
Estradiol-17 ß
What the nonmedicinal ingredients are:
cellulose compounds, ethanol, ethylene-vinyl acetate copolymer, light mineral oil, polyester and polyisobutylene.
What dosage forms it comes in:
ESTRADERM* is a transdermal patch available in three strengths: ESTRADERM* 25, ESTRADERM* 50 and ESTRADERM* 100, containing respectively 2, 4 and 8 mg of estradiol.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
The Women’s Health Initiative (WHI) trial is a large clinical study that assessed the benefits and risks of oral combined estrogen plus progestin therapy and oral estrogen-alone therapy compared with placebo (a pill with no active ingredients) in postmenopausal women.
The WHI trial indicated an increased risk of myocardial infarction (heart attack), stroke, breast cancer, pulmonary emboli (blood clots in the lungs) and deep vein thrombosis (blood clots in the large veins) in postmenopausal women taking oral combined estrogen plus progestin.
The WHI trial indicated an increased risk of stroke and deep vein thrombosis in postmenopausal women with prior hysterectomy (surgical removal of the uterus) taking oral estrogen-alone. Therefore, you should highly consider the following:
- There is an increased risk of developing invasive breast cancer, heart attack, stroke and blood clots in both lungs and large veins with the use of estrogen plus progestin therapy.
- There is an increased risk of stroke and blood clots in the large veins with the use of estrogen-alone therapy.
- Estrogens with or without progestins should not be used for the prevention of heart disease or stroke.
- Estrogens with or without progestins should be used at the lowest effective dose and for the shortest period of time possible. Regular medical follow-up is advised.
- Breast cancer
The results of the WHI trial indicated an increased risk of breast cancer in post-menopausal women taking combined estrogen plus progestin compared to women taking placebo.
The results of the WHI trial indicated no difference in the risk of breast cancer in postmenopausal women with prior hysterectomy taking estrogen-alone compared to women taking placebo.
Estrogens should not be taken by women who have a personal history of breast cancer.
In addition, women with a family history of breast cancer or women with a history of breast lump, breast biopsies or abnormal mammograms (breast x-rays) should consult with their doctor before starting hormone replacement therapy.
Women should have a mammogram before starting HRT and at regular intervals during treatment as recommended by their doctor.
Regular breast examinations by a doctor and regular breast self-examination are recommended for all women. You should review technique for breast self-examination with your doctor.
- Overgrowth of the lining of the uterus and cancer of the uterus
The use of estrogen-alone therapy by post menopausal women who still have a uterus increases the risk of developing endometrial hyperplasia (overgrowth of the lining of the uterus), which increases the risk of endometrial cancer (cancer of the lining of the uterus).
If you still have your uterus, you should take a progestin medication (another hormone drug) regularly for a certain number of days of each month to reduce the risk of endometrial hyperplasia.
You should discuss progestin therapy and risk factors for endometrial hyperplasia and endometrial carcinoma with your doctor. You should also report any unexpected or unusual vaginal bleeding to your doctor.
If you have had your uterus removed, you are not at risk of developing endometrial hyperplasia or endometrial carcinoma. Progestin therapy is
therefore not generally required in women who have had a hysterectomy.
- Ovarian cancer
In some studies, the use of estrogen-alone and estrogen plus progestin therapies for 5 or more years has been associated with an increased risk of ovarian cancer.
- Heart disease and Stroke
The results of the WHI trial indicated an increased risk of stroke and coronary heart disease in post-menopausal women taking combined estrogen plus progestin compared to women taking placebo.
The results of the WHI trial indicated an increased risk of stroke, but no difference in the risk of coronary heart disease in post-menopausal women with prior hysterectomy taking estrogen alone compared to women taking placebo.
- Abnormal Blood Clotting
The results of the WHI trial indicated an increased risk of blood clots in the lungs and large veins in post menopausal women taking combined estrogen plus progestin compared to women taking placebo.
The results of the WHI trial indicated an increased risk of blood clots in the large veins, but no difference in the risk of blood clots in the lungs in post-menopausal women with prior hysterectomy taking estrogen-alone compared to women taking placebo.
The risk of blood clots increases with age, if you or a family member has had blood clots, if you smoke or if you are severely overweight. The risk of blood clots is also temporarily increased if you are immobilized for long periods of time and following major surgery. You should discuss risk factors for blood clots with your doctor since blood clots can be life-threatening or cause serious disability.
- Gallbladder disease
The use of estrogens by postmenopausal women has been associated with an increased risk of gallbladder disease requiring surgery.
- Dementia
The Women’s Health Initiative Memory Study (WHIMS) was a substudy of the WHI trial and indicated an increased risk of dementia (loss of memory and intellectual function) in post-
menopausal women age 65 and over taking oral combined estrogen plus progestin compared to women taking placebo.
The WHIMS indicated no difference in the risk of dementia in post-menopausal women age 65 and over with prior hysterectomy taking oral estrogen-alone compared to women taking placebo.
Before you use ESTRADERM* talk to your doctor or pharmacist if you:
have a history of allergy or intolerance to
any medications or other substances
have been told that you have a condition
called hereditary angioedema of if you have had episodes of rapid swelling of the hands, feet, face, lips, eyes, tongue, throat (airway blockage) or digestive tract
have a personal history of breast disease
(including breast lumps) and/or breast biopsies, or a family history of breast cancer
have experienced any unusual or
undiagnosed vaginal bleeding
have a history of uterine fibroids or
endometriosis
have a history of liver disease or liver
tumours, jaundice (yellowing of the eyes and/or skin) or itching related to estrogen use or during pregnancy
- have a history of migraine headache
- have a history of high blood pressure
have a personal or family history of blood
clots, or a personal history of heart disease or stroke
- phlebitis (inflamed varicose veins)
have a history of kidney disease, asthma or
epilepsy (seizures)
have a history of bone disease (this includes
certain metabolic conditions or cancers that can affect blood levels of calcium and phosphorus)
- have been diagnosed with diabetes
have been diagnosed with porphyria (a
disease of blood pigment)
- have been diagnosed with lupus
- gall bladder disease
- depression
have been diagnosed with hearing loss due
to otosclerosis
have a history of high cholesterol or high
triglycerides
- are pregnant or may be pregnant
- are breastfeeding
have had a hysterectomy (surgical removal
of the uterus)
- smoke
- are undergoing surgery or need long bed rest.
Ask your doctor and pharmacist to answer any questions you may have.
Tell your doctor or pharmacist if you are taking or have recently taken any other other medications, including prescription medications, over-the-counter medications, vitamins or herbal products.
This particularly includes the following: anti-anxiety medicines (e.g.barbiturates, meprobamate), anti-epileptic medicines (e.g. pheno barbital, phenytoin or carbamazepine), an anti-inflammatory medicine called phenylbutazone, antibiotics and other anti-infective medicines (e.g. rifampicin, rifabutin, nevirapine, efavirenz), and herbal medicines (e.g. St John’s wort).
These medicines may be affected by ESTRADERM* or, conversely, they may affect how well ESTRADERM* works. Your doctor may need to adjust the dose of your treatment.
Usual dose:
Follow all instructions given to you by your doctor or pharmacist carefully. Your doctor will explain when to start using ESTRADERM*. ESTRADERM* is used as continuous therapy. You will need to wear a patch all the time. The ESTRADERM* patches are applied twice weekly on the same days of each week. Each patch should be worn continuously for 3 to 4 days.
Each box contains eight ESTRADERM* patches. If your treatment is for less than 28 days of estrogen (cyclical therapy), you will have one or two patches left over which can be used for the next month.
It is important that you take your medication as your physician has prescribed. Do not discontinue or change your therapy without consulting your physician first.
How And Where To Apply ESTRADERM*
INTERACTIONS WITH THIS MEDICATION
PROPER USE OF THIS MEDICATION
It is recommended that you change the site of application each time the patch is applied. However, each time you apply a patch you should always apply it to the same area of your body (i.e., if the patch is applied to the buttocks, move the patch from right side to left side, twice a week or more if there is any redness under the patch).
- 1. Preparing The Skin
In order for the patch to stick, the skin should be clean, dry and free of creams, lotions or oils. If you wish, you may use body lotion after the patch has been properly applied to the skin. The skin should not be irritated or broken, since this may alter the amount of hormone you get. Contact with water (bath, pool, or shower) won't affect the patch, although very hot water or steam may loosen it and therefore should be avoided (see Helpful Hints).

- 2. Where to apply the ESTRADERM* patch
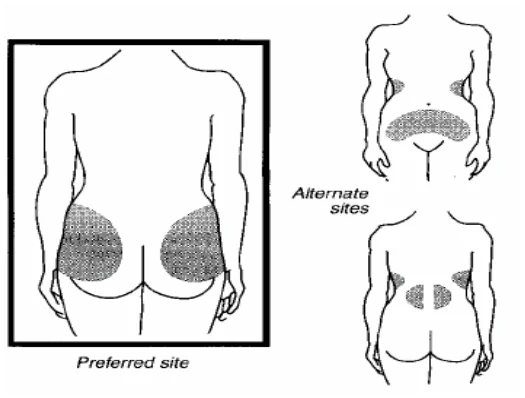
The buttock is the preferred place to apply the patch. Other suitable application sites are the sides, hip, lower back or lower abdomen (see Figure 1). Change the site of application each time you put a patch on. You can use the same spot more than once but not twice in a row.
Figure 1
Avoid areas of the skin where clothing may rub the patch off or areas where the skin is very hairy or folded. Also avoid areas where the patch is likely to be exposed to the sun since this may affect how the patch works.
DO NOT APPLY ESTRADERM* TO YOUR BREAST, since this may cause unwanted effects and discomfort.
- 3. Opening the Pouch
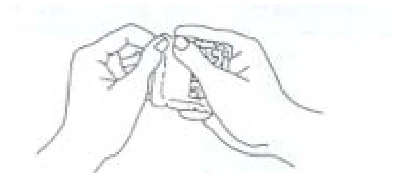
Each ESTRADERM* patch is individually sealed in a protective pouch. Tear open this pouch at the indented notch and remove the patch (see Figures 2a and 2b). Do not use scissors, as you may accidentally cut and destroy the patch. There may or may not be bubbles in the patch, but this is normal.
Figure 2a
Figure 2b
- 4. Removing The Liner
One side of the patch has the adhesive that sticks to your skin. The adhesive is covered by a protective liner that must be removed.
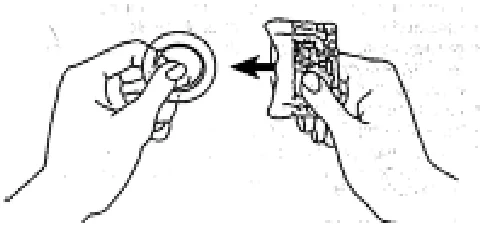
To separate the patch from the liner, hold the patch with your thumb on the smooth liner, your other fingers on the patch. See positioning in Figure 3. Press your thumb against your other fingers by using the motion of snapping your fingers slowly.
Figure 3
This will allow you to easily separate the patch and liner. Holding the edge of the patch you can now peel away the liner (see Figure 4). Avoid touching the adhesive.
Figure 4
Don't worry if the patch buckles slightly because you can flatten it out after the liner has been removed. Apply the patch soon after opening the pouch and removing the liner.
- 5. Applying the ESTRADERM* Patch
Apply the adhesive side to the spot you have chosen. Press it firmly in place with the palm of your hand for about 10 seconds, then run your finger around the edge, making sure there is good contact with the skin.
- 6. When And How To Remove The Patch
The ESTRADERM* patch should be changed twice weekly. Always change it on the same 2 days of the week. If you forget to change it at the scheduled time, there is no cause for alarm. Just change it as soon as possible and continue to follow your usual schedule.
After you remove the patch fold it in half with the adhesive sides inwards. Throw it away, safely out of the reach of children or pets.
Any adhesive left on your skin should rub off easily. You can also use mineral oil, baby oil or rubbing alcohol to remove adhesive from the skin. Apply a new ESTRADERM* patch on a different spot of clean, dry skin.
Helpful Hints
What to do if the patch falls off
Should a patch fall off in a very hot bath or shower, shake the water off the patch. Dry your skin completely and reapply the patch (to a different area of skin) and continue your regular schedule. Make sure you choose a clean, lotion-free area of the skin). If it still does not stick completely to your skin, then use a new patch. No matter what day this happens, go back to changing the patch on the same days as the initial schedule.
If hot baths, saunas or whirlpools are something you enjoy and you find that the patch is falling off, you may consider removing the patch temporarily while
you are in the water. If you do remove the patch temporarily, the adhesive side of the patch should be placed on the protective liner that was removed when originally applying the patch. Wax paper may be used as an alternate to the liner. This prevents the contents of the patch from emptying by evaporation while you are not wearing it.
In addition to exposure to very hot water, there are some other causes for the patch failing to stick. If you are having patches fall off regularly, this could be happening as a result of:
- using any type of bath oil
- using soaps with a high cream content
- using skin moisturizers before applying the patch
Patch adhesion may be improved if you avoid using these products, and by cleansing the site of application with rubbing alcohol before you apply the patch.
What to do if your skin becomes red or irritated under or around the patch
As with any product that covers the skin for a period of time (such as bandages), the ESTRADERM* patch can produce some skin irritation in some women. This varies according to the sensitivity of each woman.
Usually this redness does not pose any health concern to you, but to reduce this problem, there are some things that you may do:
- Choose the buttock as the site of application
Change the site of application of the
ESTRADERM* patch every time a new patch is applied, usually twice weekly
Experience with ESTRADERM* has shown that if you allow the patch to be exposed to the air for approximately 10 seconds after the protective liner has been removed, skin redness may not occur.
If redness and/or itching continues, you should consult your physician.
Overdose:
If more medication has been taken than what has been prescribed, remove the patch and contact either your doctor, hospital or emergency department immediately.
For management of a suspected drug overdose, contact your regional Poison Control Center.
Missed Dose:
If you miss applying a patch, apply a new patch as soon as you remember. No matter what day that happens, go back to changing this patch on the same day as your initial schedule.
SSIDE EFFECTS AND WHAT TO DO ABOUT THEM
All medicines can have side effects. Sometimes they are serious, most of the time they are not.
Check with your doctor as soon as possible if any of the following occur: swelling of the lower legs, ankles, fingers or abdomen due to fluid retention (oedema) persisting for more than 6 weeks, change in weight, change in your sex drive, easy bruising, excessive nose bleedspainful and/or heavy periods (may be signs of growth of fibroids in the uterus), change in vaginal discharge (may be a sign that too much estrogen is taken), vaginal thrush (vaginal fungal infection with severe itching, vaginal discharge), intolerable breast tenderness, persistent or severe skin irritation, itching under the patch, reddening of the skin after the patch has been removed; hair loss, excessive hairiness, spotty darkening of the skin, particularly on the face or abdomen (chloasma), rash, itching, acne, dryness or discoloration of the skin, purple skin patches, decline of memory or mental ability, contact lens discomfort, gall bladder disease (tendency to form gall stones),
| SERIOUS SIDE EFFECTS, HOW OFTEN THEY | ||||||
| HAPPEN AND WHAT TO DO ABOUT THEM | ||||||
| Symptom/possi ble side effect | Talk to your doctor or pharmacist | Stop taking drug and call your doctor or pharma-cist | ||||
| Only if severe | In all cases | |||||
| Abdominal pain, nausea or vomiting | x | |||||
| Breast lump | x | |||||
| Crushing chest pain or chest heaviness | x | |||||
| Pain or swelling in the leg | x | |||||
| Persistent sad mood | x | |||||
| Sharp pain in the chest, coughing blood or sudden shortness of breath | x | |||||
| Sudden partial or complete loss of vision | x | |||||
| Sudden severe headache or worsening of headache, vomiting, dizziness, fainting, disturbance of vision or speech or weakness or numbness in an arm or leg | x | |||||
| Migraine | x | |||||
| Unexpected or excessively heavy vaginal bleeding | x | |||||
| Yellowing of the skin or eyes (jaundice) | x | |||||
Signs of allergic reaction: sudden troubled breathing, tightness of the chest, general rash, swelling or itching | x | ||
Increase in blood pressure, | x |
This is not a complete list of side effects. For any unexpected effects while taking ESTRADERM*, contact your doctor or pharmacist.
ESTRADERM* should be stored at room temperature (below 25◦C) and away from direct sunlight. Do not freeze. Store in the original package.
ESTRADERM* patches should be kept out of the reach and sight of children and pets.
Do not use ESTRADERM* after the expiry date shown on the pack.
Do not use ESTRADERM* pack that is damaged or shows signs of tampering.
REPORTING SUSPECTED SIDE EFFECTS
To monitor drug safety, Health Canada through Canada Vigilance Program collects information on serious and unexpected side effects of drugs. If you suspect you have had a serious or unexpected reaction to this drug you may notify Canada Vigilance:
Online: www.healthcanada.gc.ca/medeffect
Toll-free telephone: 1-866-234-2345 toll-free fax 1-866-678-6789 Postage Paid mail:
Canada Vigilance Program
Health Canada
AL 0701C
Ottawa ON K1A 0K9
NOTE: Should you require information related to the management of the side effect, please contact your health care provide. The Canada Vigilance Program does not provide medical advice.
MORE INFORMATION
Please consult your doctor or pharmacist with any questions or concerns you may have regarding your individual condition.
This document plus the full product monograph, prepared for health professionals can be found at: http://www.novatis.ca
or by contacting the sponsor, Novartis Pharmaceuticals Canada Inc., at:
1-800-363-8883
Last revised: January 23, 2009
Novartis Pharmaceuticals Canada Inc. 385 Bouchard Blvd
Dorval, Quebec H9S 1A9
* Registered trademark