


Product Monograph - Prevymis
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS | 09/2023 |
|---|---|
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 03/2024 |
| 7 WARNINGS AND PRECAUTIONS | 09/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.3 Reconstitution ........................................................................................................ 6
4.4 Administration ........................................................................................................ 8
4.5 Missed Dose ........................................................................................................... 9
5 OVERDOSAGE .............................................................................................................. 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
7.1 Special Populations............................................................................................... 12
7.1.1 Pregnant Women ........................................................................................... 12
7.1.2 Breast-feeding ................................................................................................ 12
7.1.3 Pediatrics ........................................................................................................ 12
7.1.4 Geriatrics ........................................................................................................ 12
8 ADVERSE REACTIONS ................................................................................................ 12
8.1 Adverse Reaction Overview .................................................................................. 12
8.2 Clinical Trial Adverse Reactions ............................................................................ 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ........................................................................................................... 15
8.5 Post-Market Adverse Reactions ........................................................................... 16
9 DRUG INTERACTIONS ................................................................................................ 16
9.1 Serious Drug Interactions ..................................................................................... 16
9.2 Drug Interactions Overview .................................................................................. 16
9.4 Drug-Drug Interactions ......................................................................................... 17
9.5 Drug-Food Interactions ......................................................................................... 27
9.6 Drug-Herb Interactions ......................................................................................... 27
9.7 Drug-Laboratory Test Interactions ........................................................................ 27
10 CLINICAL PHARMACOLOGY ....................................................................................... 27
10.1 Mechanism of Action ...................................................................................... 27
10.2 Pharmacodynamics ........................................................................................ 27
10.3 Pharmacokinetics ........................................................................................... 27
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 31
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 31
PART II: SCIENTIFIC INFORMATION ....................................................................................... 32
13 PHARMACEUTICAL INFORMATION ............................................................................ 32
14 CLINICAL TRIALS ........................................................................................................ 32
14.1 Clinical Trials by Indication ............................................................................. 32
Adult CMV-seropositive Recipients [R+] of an Allogeneic Hematopoietic Stem Cell Transplant (HSCT): .......................................................................................................... 32
Adult CMV-seronegative Recipients of a Kidney Transplant from a CMV-seropositive Donor [D+/R-] ................................................................................................................. 38
15 MICROBIOLOGY ........................................................................................................ 42
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 43
PATIENT MEDICATION INFORMATION .................................................................................. 45
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
PREVYMIS® (letermovir) is indicated for:
- the prophylaxis of cytomegalovirus (CMV) infection in adult CMV-seropositive recipients [R+] of an allogeneic hematopoietic stem cell transplant (HSCT).
- the prophylaxis of CMV disease in adult kidney transplant recipients who are at high risk (donor CMV-seropositive [D+]/recipient CMV-seronegative [R-]).
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Safety and efficacy were similar across older and younger subjects in the Phase 3 trials in HSCT recipients and in the Phase 3 trial in kidney transplant recipients.
2 CONTRAINDICATIONS
PREVYMIS® is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Pimozide
Concomitant administration of PREVYMIS® may result in increased concentrations of pimozide due to inhibition of cytochrome P450 3A (CYP3A) by letermovir, leading to QT prolongation and torsades de pointes (see 7 WARNINGS AND PRECAUTIONS and 9.2 Drug Interactions Overview).
Ergot Alkaloids
Concomitant administration of PREVYMIS® may result in increased concentrations of ergot alkaloids (ergotamine and dihydroergotamine) due to inhibition of CYP3A by letermovir, which may lead to ergotism (see 7 WARNINGS AND PRECAUTIONS and 9.2 Drug Interactions Overview).
Cyclosporine with lovastatin, rosuvastatin or simvastatin
Concomitant administration of PREVYMIS® when used in combination with cyclosporine is contraindicated as it may result in significantly increased lovastatin, rosuvastatin or simvastatin concentrations, which may lead to myopathy or rhabdomyolysis (see 7 WARNINGS AND PRECAUTIONS and 9.2 Drug Interactions Overview).
Cyclosporine with bosentan
Concomitant administration of PREVYMIS® when used in combination with cyclosporine is contraindicated as it may result in significantly increased concentrations of bosentan (see 7 WARNINGS AND PRECAUTIONS and 9.2 Drug Interactions Overview).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
PREVYMIS® Tablets
- Administer with or without food.
- Swallow tablets whole. Do not divide, crush or chew.
PREVYMIS® Injection
- PREVYMIS® injection must be administered through a sterile 0.2 micron or 0.22 micron polyethersulfone (PES) in-line filter.
- Do not administer as an IV bolus injection.
- Administer by intravenous (IV) infusion upon dilution via a peripheral catheter or central venous line over approximately 60 minutes.
PREVYMIS® tablet and injection may be used interchangeably at the discretion of the physician, and no dose adjustment is necessary.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dosage
Adults:
The recommended dosage of PREVYMIS® is 480 mg administered once daily.
If PREVYMIS® is co-administered with cyclosporine, the dosage of PREVYMIS® should be decreased to 240 mg once daily (see Dosage Adjustment in Adults section below).
HSCT
PREVYMIS® should be started after HSCT. PREVYMIS® may be started on the day of transplant and no later than 28 days post-HSCT. PREVYMIS® may be started before or after engraftment. Continue PREVYMIS® through 100 days post-HSCT. In patients at risk for late CMV infection and disease, PREVYMIS® may be continued through 200 days post-HSCT.
Following completion of PREVYMIS® prophylaxis, monitoring for CMV reactivation in HSCT recipients is recommended.
Kidney Transplant
PREVYMIS® should be started on the day of transplant and no later than 7 days post-kidney transplant and continued through 200 days post-transplant.
Pediatrics (< 18 years of age):
Safety and efficacy of PREVYMIS® have not been established in pediatric patients less than 18 years of age.
Geriatrics (≥ 65 years of age):
No dose adjustment of PREVYMIS® is required based on age (see 10.3 Pharmacokinetics).
Dosage Adjustment in Adults
If PREVYMIS® is co-administered with cyclosporine, the dosage of PREVYMIS® should be decreased to 240 mg once daily (see 4.3 Reconstitution, 9 DRUG INTERACTIONS and 10.3 Pharmacokinetics).
- If cyclosporine is initiated after starting PREVYMIS®, the next dose of PREVYMIS® should be decreased to 240 mg once daily.
- If cyclosporine is discontinued after starting PREVYMIS®, the next dose of PREVYMIS® should be increased to 480 mg once daily.
- If cyclosporine dosing is temporarily interrupted due to high cyclosporine levels, no dose adjustment of PREVYMIS® is needed.
Renal Impairment
No dose adjustment of PREVYMIS® is required based on renal impairment (see Renal, Combined Renal and Hepatic Insufficiency and 10.3 Pharmacokinetics). There are no data in patients with end-stage renal disease (CrCl less than 10 mL/min), including patients on dialysis.
Hepatic Impairment
No dose adjustment of PREVYMIS® is required based on mild (Child-Pugh Class A) to moderate (Child-Pugh Class B) hepatic impairment. PREVYMIS® is not recommended for patients with severe (Child-Pugh Class C) hepatic impairment (see Hepatic/Biliary/Pancreatic, Combined Renal and Hepatic Insufficiency and 10.3 Pharmacokinetics).
Combined Renal and Hepatic Impairment
PREVYMIS® is not recommended in patients with moderate hepatic impairment combined with moderate or severe renal impairment (CrCl less than 50 mL/min) (see Combined Renal and Hepatic Insufficiency and 10.3 Pharmacokinetics).
4.3 Reconstitution
Parenteral Products:
- Add one single-dose vial of PREVYMIS® injection to a 250 mL pre-filled IV bag containing either 0.9% sodium chloride injection or 5% dextrose injection and mix bag gently. Do not shake.
- Once diluted, the solution of PREVYMIS® is clear, and ranges from colorless to yellow. Variations of color within this range do not affect the quality of the product. The diluted solution should be inspected visually for particulate matter and discoloration prior to administration.
- Discard if the diluted solution is cloudy, discolored, or contains matter other than a few small translucent or white particles.
Storage of Diluted Solution
- The diluted solution can be stored for up to 24 hours at room temperature or up to 48 hours under refrigeration at 2°C to 8°C.
- This time includes storage of the diluted solution in the IV bag through the duration of infusion.
Compatible Diluents, Drug Products, and Other Materials Used for Intravenous Administration
Compatible Diluents
PREVYMIS® injection is compatible with 0.9% sodium chloride injection and 5% dextrose injection.
Compatible Drug Products
A study was conducted to evaluate physical compatibility of PREVYMIS® injection with injectable drug products. Compatibility was determined through visual observations, turbidity, and measurement of particulate matter. Compatible drug products are listed below.
PREVYMIS® should not be co-administered through the same IV line (or cannula) with other drug products and diluent combinations except those listed below.
The following compatible drug products† may be co-administered with PREVYMIS® for injection when both drug products are in 0.9% Sodium Chloride via Y tubing only, as per the approved instructions of the respective drug products.
- Ampicillin sodium
- Anti-thymocyte globulin
- Caspofungin
- Daptomycin
- Fentanyl citrate
- Fluconazole
- Furosemide
- Human insulin
- Magnesium sulfate
- Methotrexate
- Micafungin
† These injectable drug products are available in Canada
The following compatible drug products† may be co-administered with PREVYMIS® for injection when both drug products are in 5% Dextrose via Y tubing only, as per the approved instructions of the respective drug products.
- Amphotericin B (lipid complex)#
- Anidulafungin
- Cefazolin sodium
- Ceftriaxone sodium
- Famotidine
- Folic acid
- Ganciclovir sodium
- Hydrocortisone sodium succinate
- Morphine sulfate
- Norepinephrine bitartrate
- Pantoprazole sodium
- Potassium chloride
- Potassium phosphate
- Tacrolimus
- Telavancin
- Tigecycline
† These injectable drug products are available in Canada
# Amphotericin B (lipid complex) is compatible with PREVYMIS®. However, Amphotericin B (liposomal) is incompatible (see below Incompatible Drug Products and Other Materials Used for Intravenous Administration).
Compatible IV Bags and Infusion Set Materials
PREVYMIS® is compatible with the following IV bags and infusion set materials. Any IV bags or infusion set materials not listed below should not be used.
IV Bags Materials:
Polyvinyl chloride (PVC), ethylene vinyl acetate (EVA) and polyolefin (polypropylene and polyethylene)
Infusion Sets Materials:
PVC, polyethylene (PE), polybutadiene (PBD), silicone rubber (SR), styrene–butadiene copolymer (SBC), styrene-butadiene-styrene copolymer (SBS), polystyrene (PS)
Plasticizers:
Tris (2-ethylhexyl) trimellitate (TOTM), butyl benzyl phthalate (BBP)
Catheters:
Radiopaque polyurethane
Incompatible Drug Products and Other Materials Used for Intravenous Administration
Incompatible Drug Products
PREVYMIS® injection is physically incompatible with amiodarone HCl, amphotericin B (liposomal), aztreonam, cefepime HCl, ciprofloxacin, cyclosporine, diltiazem HCl, filgrastim, gentamicin sulfate, levofloxacin, linezolid, lorazepam, midazolam HCl, mycophenolate mofetil HCl, ondansetron, and palonosetron.
Incompatible IV Bags and Infusion Set Materials
PREVYMIS® injection is incompatible with diethylhexyl phthalate (DEHP) plasticizers and polyurethane-containing IV administration set tubing.
4.4 Administration
PREVYMIS® injection is supplied in 30 mL single-dose vials containing either 240 mg (12 mL per vial) or 480 mg (24 mL per vial). The preparation and administration instructions are the same for either dose.
PREVYMIS® vials are for single use only. Discard any unused portion.
- The diluted solution must be administered through a sterile 0.2 micron or 0.22 micron PES in-line filter.
- Do not administer the diluted solution through a filter other than a sterile 0.2 micron or 0.22 micron PES in-line filter.
- Administer as an IV infusion upon dilution only. Do not administer as an IV push or bolus.
- After dilution, administer PREVYMIS® via IV infusion via peripheral or central venous catheter using a total time of approximately 60 minutes. Administer the entire contents of the IV bag.
Preparation
- PREVYMIS® must be diluted prior to IV use.
- Inspect vial contents for discoloration and particulate matter prior to dilution. PREVYMIS® injection is a clear colorless solution and may contain a few product-related small translucent or white particles.
- Do not use the vial if the solution is cloudy, discolored, or contains matter other than a few small translucent or white particles.
- Do not use PREVYMIS® injection with IV bags and infusion set materials containing polyurethane or the plasticizer diethylhexyl phthalate (DEHP). Materials that are phthalate-free are also DEHP-free.
- Do not shake PREVYMIS® vial.
4.5 Missed Dose
Instruct patients that if they miss a dose of PREVYMIS®, they should take it as soon as they remember. If they do not remember until it is time for the next dose, instruct them to skip the missed dose and go back to the regular schedule. Instruct patients not to double their next dose or take more than the prescribed dose.
5 OVERDOSAGE
During Phase 1 clinical trials, 86 healthy subjects received doses ranging from 720 mg/day to 1440 mg/day of PREVYMIS® for up to 14 days. The adverse reaction profile was similar to that of the clinical dose of 480 mg/day. There is no specific antidote for overdose with PREVYMIS®. In case of overdose, it is recommended that the patient be monitored for adverse reactions and appropriate symptomatic treatment instituted.
It is unknown whether dialysis will result in meaningful removal of PREVYMIS® from systemic circulation.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 240 mg, 480 mg | Colloidal silicon dioxide, croscarmellose sodium, |
Tablet:
PREVYMIS® 240 mg tablet is a yellow oval tablet. Each tablet is debossed with “591” on one side and Corporate logo on the other side. The 240 mg tablets are packaged in aluminum foil blister and lidding in cartons of 28 tablets.
PREVYMIS® 480 mg tablet is a pink oval, bi-convex tablet. Each tablet is debossed with “595” on one side and Corporate logo on the other side. The 480 mg tablets are packaged in aluminum foil blister and lidding in cartons of 28 tablets.
Solution for Injection:
PREVYMIS® for injection 240 mg/12 mL (20 mg/mL) is supplied in a single-dose vial.
PREVYMIS® for injection 480 mg/24 mL (20 mg/mL) is supplied in a single-dose vial.
7 WARNINGS AND PRECAUTIONS
General
Risk of Adverse Reactions or Reduced Therapeutic Effect Due to Drug Interactions
The concomitant use of PREVYMIS® and certain drugs may result in known or potentially significant drug interactions, some of which may lead to:
- Possible clinically significant adverse reactions from greater exposure of concomitant drugs or PREVYMIS®.
- Significant decrease of concomitant drug plasma concentrations which may lead to reduced therapeutic effect of the concomitant drug.
See Table 5 for steps to prevent or manage these known or potentially significant drug interactions, including dosing recommendations (see 2 CONTRAINDICATIONS, 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions). Consider the potential for drug interactions prior to and during PREVYMIS® therapy; review concomitant medications during PREVYMIS® therapy; and monitor for the adverse reactions associated with the concomitant drugs.
magnesium stearate, microcrystalline cellulose and povidone 25. Film-coating: hypromellose 2910, iron oxide yellow, and (only for 480 mg tablets) iron oxide red, lactose monohydrate, titanium dioxide and triacetin. Carnauba wax is added as a polishing agent. | ||
| Intravenous infusion | Solution for Injection 20 mg / mL | Preservative-free sterile solution in single-dose vials of either 240 mg or 480 mg per vial. Each 1 mL of solution contains hydroxypropyl betadex (150 mg), sodium chloride (3.1 mg), sodium hydroxide (1.2 mg), and Water for Injection. The amount of sodium hydroxide may be adjusted to achieve a pH of approximately 7.5. |
PREVYMIS® should be used with caution with drugs that are CYP3A substrates with narrow therapeutic ranges (e.g., alfentanil, fentanyl, and quinidine1) as co-administration may result in increases in the plasma concentrations of CYP3A substrates. Close monitoring and/or dose adjustment of co-administered CYP3A substrates is recommended (see Table 5, 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions).
1 Not marketed in Canada.
Co-administration of PREVYMIS® with strong and moderate inducers of transporters (e.g., P-gp) and/or enzymes (e.g. UGTs) is not recommended due to the potential for a decrease in letermovir plasma concentrations.
Rifampin co-administration resulted in an initial increase in letermovir plasma concentrations
(due to OATP1B1/3 inhibition) that is not clinically significant, followed by clinically relevant decreases in letermovir plasma concentrations with continued rifampin co-administration. This may result in loss of prophylactic efficacy and necessitate initiation of anti-CMV therapy for CMV reactivation and/or disease.
Co-administration of PREVYMIS® may result in increases in the plasma concentrations of cyclosporine, tacrolimus, and sirolimus. Close monitoring and/or dose adjustment of cyclosporine, tacrolimus, and sirolimus is recommended when co-administered with PREVYMIS®.
Hepatic/Biliary/Pancreatic
Hepatic Insufficiency
Exposure to PREVYMIS® is increased 1.6- to 3.8-fold in subjects with moderate and severe hepatic impairment. No dose adjustment of PREVYMIS® is required based on mild (Child-Pugh Class A) to moderate (Child-Pugh Class B) hepatic impairment. PREVYMIS® is not recommended for patients with severe (Child-Pugh Class C) hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment, Combined Renal and Hepatic Insufficiency and 10.3 Pharmacokinetics).
Renal
Renal Insufficiency
Exposure to PREVYMIS® is increased 1.4- to 1.9-fold in subjects with moderate and severe renal impairment. No dose adjustment of PREVYMIS® is required based on renal impairment (see 4.2 Recommended Dose and Dosage Adjustment, Combined Renal and Hepatic Insufficiency and 10.3 Pharmacokinetics). There are no data in patients with end-stage renal disease (CrCl less than 10 mL/min), including patients on dialysis.
In patients with moderate or severe renal impairment (CrCl less than 50 mL/min) receiving
PREVYMIS® injection, accumulation of the IV vehicle, hydroxypropyl betadex, could occur. Serum creatinine levels should be closely monitored in these patients.
Combined Renal and Hepatic Insufficiency
PREVYMIS® is not recommended in patients with moderate hepatic impairment combined with moderate or severe renal impairment (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics).
Reproductive Health: Female and Male Potential
- Fertility
There were no effects on female fertility in rats. Impairment of fertility was observed in male rats, but not in male mice or male monkeys (see 16 NON-CLINICAL TOXICOLOGY). Testicular toxicity in rats appears to be species-specific, and the relevance to humans is unknown. In the Phase 3 trials in HSCT and kidney transplant recipients, there was no evidence of letermovir-related testicular toxicity (see 8.2 Clinical Trials Adverse Reactions, 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data).
7.1 Special Populations
7.1.1 Pregnant Women
No human data are available to establish whether or not PREVYMIS® poses a risk to pregnancy outcomes, therefore, the potential risk to humans is unknown. PREVYMIS® should not be used in pregnancy unless benefit outweighs the risk.
Embryofetal toxicity was observed in rats and rabbits at maternally toxic systemic AUC exposures of approximately 11- and 2-fold, respectively, the AUC at the recommended human dose (RHD). In the rat pre-and postnatal development study, no developmental toxicity was observed up to the highest maternal systemic AUC exposure (approximately 2-fold the AUC at the RHD).
In pregnant rats, letermovir was able to cross the placenta (see 10.3 Pharmacokinetics).
7.1.2 Breast-feeding
It is not known whether letermovir is present in human breast milk, affects human milk production, or has effects on the breastfed child.
When administered to lactating rats, letermovir was present in milk, without effects on growth and development in nursing pups.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for PREVYMIS® and any potential adverse effects on the breastfed child from PREVYMIS® or from the underlying maternal condition.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Safety and efficacy were similar across older and younger subjects in the Phase 3 trials in HSCT recipients and in the Phase 3 trial in kidney transplant recipients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety summary for PREVYMIS® in HSCT recipients was based on data from a randomized, placebo-controlled Phase 3 clinical trials (P001 and P040) in which CMV seropositive HSCT recipients received letermovir or placebo. The safety summary for PREVYMIS® in kidney transplant recipients was based on data from a randomized, active comparator-controlled Phase 3 clinical trial P002 in which kidney transplant recipients [D+/R-] received letermovir or valganciclovir.
In P001, the most commonly reported adverse reactions in subjects treated with PREVYMIS® through Week 14 post-HSCT and followed for safety through Week 24 post-HSCT were nausea, diarrhea, and vomiting. In P002, the most commonly reported adverse reactions in subjects treated with PREVYMIS® or valganciclovir through Week 28 post-kidney transplant were leukopenia, neutropenia, and white blood cell count decreased. In P040, the most commonly reported adverse reactions in subjects treated with PREVYMIS® from Week 14 post-HSCT through Week 28 post-HSCT were nausea and vomiting.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adult CMV-seropositive Recipients [R+] of an Allogeneic HSCT
Prophylaxis Through Week 14 (~100 days) Post-HSCT
The safety of PREVYMIS® was evaluated in a Phase 3 randomized, double-blind, placebo-controlled trial (P001) through Week 14 post-HSCT and were followed for safety through Week 24 post-HSCT (see 14 CLINICAL TRIALS).
The most commonly reported adverse reactions occurring in at least 1% of subjects in the PREVYMIS® group through Week 24 post-HSCT and at a frequency greater than placebo were: nausea, diarrhea, and vomiting (see Table 2).
Table 2 - P001 Adverse Reactions Reported in ≥1% HSCT Recipients in the PREVYMIS® Group and at a Frequency Greater than Placebo Through Week 24 Post-Transplant
PREVYMIS® n = 373 (%) | Placebo n = 192 (%) | |
Gastrointestinal Nausea Diarrhea Vomiting | 27 (7.2) 9 (2.4) 7 (1.9) | 7 (3.6) 2 (1.0) 1 (1.0) |
Serious adverse reactions through week 24 post-HSCT were reported in 6 (1.1%) subjects with 3 (0.8%) in the PREVYMIS® group and 3 (1.6%) in the placebo group. The reported serious adverse reactions, which had a temporal association but no other plausible causal relationship to study treatment, were pancytopenia, thrombocytopenia, and delayed engraftment in the letermovir group and Bowen’s disease, mental status changes, and acute kidney injury in the placebo group.
Cardiac Adverse Events:
Cardiac adverse events were more common in subjects receiving PREVYMIS® (13%) compared to subjects receiving placebo (6%). The most common cardiac adverse events were tachycardia (reported in 4% of PREVYMIS® subjects and in 2% of placebo subjects) and atrial fibrillation (reported in 3.5% of PREVYMIS® subjects and in 1% of placebo subjects). These adverse events were mostly considered mild or moderate in severity.
Hypersensitivity was reported with PREVYMIS® in one subject.
Overall, similar proportions of subjects in each group discontinued study medication due to an adverse reaction (4.8% PREVYMIS® vs. 3.6% placebo). The most frequently reported adverse reactions that led to discontinuation of PREVYMIS® were nausea (1.6%), vomiting (0.8%), and abdominal pain (0.5%).
Prophylaxis From Week 14 (~100 days) Through Week 28 (~200 days) Post-HSCT
The safety of PREVYMIS® was evaluated in a Phase 3 randomized, double-blind, placebo-controlled trial (P040) in which 218 subjects who completed PREVYMIS® prophylaxis through ~100 days post-HSCT were randomized to treatment with PREVYMIS® (N=144) or placebo (N=74) through Week 28 (~200 days) post-HSCT and were followed for safety through Week 48 post-HSCT.
The adverse reactions observed were consistent with those observed in P001. The most commonly reported adverse reactions occurring in at least 1% of subjects in the PREVYMIS® group and at a frequency greater than placebo were: nausea (2.1%) and vomiting (1.4%). A total of 5% of subjects in the PREVYMIS® group and 1% of subjects in the placebo group discontinued due to adverse events; none of the adverse events were considered to be related to study medication (PREVYMIS® or placebo).
The cardiac adverse event rate (regardless of investigator-assessed causality) was 4% in the PREVYMIS® and placebo groups; no cardiac adverse event was reported more than once in either group.
Adult Kidney Transplant Recipients [D+/R-]
The safety of PREVYMIS® was evaluated in a Phase 3 randomized, double-blind, active comparator-controlled trial (P002) in which 589 subjects were treated with PREVYMIS® (N=292) or valganciclovir (N=297) through Week 28 post-transplant.
The most commonly reported adverse reactions occurring in at least 2% of subjects in the PREVYMIS® group or valganciclovir group are shown in Table 3.
Table 3- P002 Adverse Reactions Reported in ≥2% Kidney Transplant Recipients in the PREVYMIS® Group or Valganciclovir Group Through Week 28 Post-Transplant
| Adverse Reaction | PREVYMIS® (n=292) (%) | Valganciclovir (n=297) (%) |
|---|---|---|
| Leukopenia | 20 (6.8) | 68 (22.9) |
| Neutropenia | 6 (2.1) | 24 (8.1) |
| White blood cell count decreased | 3 (1.0) | 12 (4.0) |
Study medication was discontinued due to an adverse reaction in 2.7% of subjects in the PREVYMIS® group and 8.8% of subjects in the valganciclovir group. The most frequently reported adverse reactions that led to study medication discontinuation were neutropenia (PREVYMIS®, 1.4%; valganciclovir, 1.3%) and leukopenia (PREVYMIS®, 1.0%; valganciclovir, 5.4%).
The proportion of subjects with leukopenia or neutropenia (adverse events of leukopenia or neutropenia, total white blood cell count <3500 cells/μL, or absolute neutrophil count <1000 cells/μL) through Week 28 post-transplant was lower in the PREVYMIS® group compared with the valganciclovir group (PREVYMIS®, 26%; valganciclovir, 64%).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Adult CMV-seropositive Recipients [R+] of an Allogeneic HSCT
Overall, the percentage of subjects with potentially clinically significant changes in laboratory values (e.g., hematology, chemistry, renal, and hepatic function) was similar in the PREVYMIS® and placebo groups. In P001, there were no differences in the incidence of or time to engraftment (defined as absolute neutrophil count ≥ 500/mm3 on 3 consecutive days after transplantation) between the PREVYMIS® and placebo groups. In Study P040 serum creatinine abnormalities > 1.5 mg/dL occurred in 15% of PREVYMIS and 8% of placebo subjects.
Biomarkers of testicular toxicity were evaluated in male subjects in P001 (see 16 NON-CLINICAL TOXICOLOGY). The changes from baseline in male sex hormones (serum inhibin B, luteinizing hormone (LH), follicle-stimulating hormone (FSH), and testosterone) were similar in the PREVYMIS® and placebo groups.
Adult Kidney Transplant Recipients [D+/R-]
Selected laboratory abnormalities reported through Week 28 post-transplant are presented in the table below.
Table 4 - P002 Selected Laboratory Abnormalities
PREVYMIS® n=292 | Valganciclovir n=297 | |
|---|---|---|
| Absolute neutrophil count (cells/μL) | ||
| < 500 | 2.1% | 6.7% |
| 500 – < 750 | 1.4% | 2.4% |
| 750 – < 1000 | 1.4% | 6.7% |
| Hemoglobin (g/dL) | ||
| < 6.5 | 0.7% | 0.0% |
| 6.5 – < 8.0 | 3.8% | 4.0% |
| 8.0 – < 9.5 | 29.5% | 32.0% |
| Platelets (cells/μL) | ||
| < 25000 | 0.0% | 0.0% |
| 25000 – < 50000 | 0.3% | 0.0% |
| 50000 – < 100000 | 0.7% | 2.7% |
| Leukocytes (cells/μL) | ||
| < 1000 | 1.0% | 2.0% |
| 1000 – < 2000 | 4.5% | 16.2% |
| 2000 – < 3500 | 16.4% | 36.4% |
| Serum creatinine (mg/dL) | ||
| > 2.5 | 21.6% | 21.2% |
| > 1.5 – 2.5 | 50.7% | 51.5% |
|---|
8.5 Post-Market Adverse Reactions
Not Applicable.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Effect of Other Drugs on PREVYMIS®
Letermovir is a substrate of organic anion-transporting polypeptide 1B1/3 (OATP1B1/3) and P-glycoprotein (P-gp) transporters and UDP-glucuronosyltransferase 1A1/3 (UGT1A1/3) enzymes. Co-administration of PREVYMIS® with drugs that are inhibitors of OATP1B1/3 transporters may result in increases in letermovir plasma concentrations. If PREVYMIS® is co-administered with cyclosporine (a potent OATP1B1/3 inhibitor), the recommended dose of PREVYMIS® is 240 mg once daily (see 4.2 Recommended Dose and Dosage Adjustment, 10.3 Pharmacokinetics, and Table 5).
Co-administration of PREVYMIS® with strong and moderate inducers of transporters (e.g., P-gp) and/or enzymes (e.g., UGTs) is not recommended due to the potential for a decrease in letermovir plasma concentrations (see 7 WARNINGS AND PRECAUTIONS).
Rifampin co-administration resulted in an initial increase in letermovir plasma concentrations (due to OATP1B1/3 inhibition) that is not clinically significant, followed by clinically relevant decreases in letermovir plasma concentrations with continued rifampin co-administration. This may result in loss of prophylactic efficacy and necessitate initiation of anti-CMV therapy for CMV reactivation and/or disease (see 7 WARNINGS AND PRECAUTIONS).
Effect of PREVYMIS® on Other Drugs
Letermovir is a moderate inhibitor of CYP3A, based on clinical studies using midazolam as probe. Co-administration of PREVYMIS® with drugs that are CYP3A substrates may result in clinically relevant increases in the plasma concentrations of co-administered CYP3A substrates. PREVYMIS® is contraindicated with drugs that are highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening reactions. PREVYMIS® should be used with caution with other CYP3A substrates and adverse reactions to these drugs monitored as appropriate (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS, and Table 5)
Letermovir is an inhibitor of OATP1B1/3 transporters BCRP, BSEP, MRP2, and UGT1A1. Co-administration of PREVYMIS® with drugs that are substrates of OATP1B1/3 transporters may result in a clinically relevant increase in plasma concentrations of co-administered OATP1B1/3 substrates (see Table 5).
The magnitude of CYP3A- and OATP1B1/3-mediated drug interactions on co-administered drugs may be different when PREVYMIS® is co-administered with cyclosporine. See the product monograph for cyclosporine for information on drug interactions with cyclosporine.
9.4 Drug-Drug Interactions
Established and Other Potentially Significant Drug Interactions
If dose adjustments of concomitant medications are made due to treatment with PREVYMIS®, doses should be readjusted after treatment with PREVYMIS® is completed.
Table 5 provides a listing of established or potentially clinically significant drug interactions. The drug interactions described are based on studies conducted with PREVYMIS® or are predicted drug interactions that may occur with PREVYMIS® (see 7 WARNINGS AND PRECAUTIONS and 10.3 Pharmacokinetics).
Table 5 - Potentially Significant Drug Interactions: Alteration in Dose May Be Recommended Based on Results from Drug Interaction Studies or Predicted Interactionsβ (Information in the Table Applies to Co-administration of PREVYMIS® and the Concomitant Drug without Cyclosporine, Unless Otherwise Indicated)
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| Anti-arrhythmic Agents | |||
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| amiodarone | T | ↑ amiodarone | Co-administration of PREVYMIS® with amiodarone increases plasma concentrations of amiodarone. Close clinical monitoring for adverse events related to amiodarone is recommended during co-administration. Frequently monitor amiodarone concentrations when amiodarone is co-administered with PREVYMIS®. When PREVYMIS® is co-administered with cyclosporine, use of amiodarone is not recommended. |
| Anticoagulants | |||
| warfarin | T | ↓ concentrations of warfarin | Co-administration of PREVYMIS® with warfarin may decrease the plasma concentrations of warfarin. Frequent monitoring of INR should be performed while warfarin is co-administered with PREVYMIS®§. |
| Anticonvulsants | |||
| carbamazepine | T | ↓ letermovir | Co-administration of PREVYMIS® with carbamazepine may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and carbamazepine is not recommended. |
| phenobarbital | T | ↓ letermovir | Co-administration of PREVYMIS® with phenobarbital may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and phenobarbital is not recommended. |
| phenytoin | T | ↓ letermovir ↓ phenytoin | Co-administration of PREVYMIS® with phenytoin may decrease plasma concentrations of letermovir. PREVYMIS® may decrease the plasma concentrations of phenytoin. Frequent monitoring of phenytoin concentrations should be performed when phenytoin is co-administered with PREVYMIS®. Co-administration of PREVYMIS® and phenytoin is not recommended. |
| Antidiabetic Agents | |||
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
Examples: glyburide, repaglinide, rosiglitazone | T¶ | ↑glyburide ↑repaglinide ↑rosiglitazone | Co-administration of PREVYMIS® with glyburide, repaglinide, or rosiglitazone may increase the plasma concentrations of these drugs. Frequent monitoring of glucose concentrations is recommended during co-administration of glyburide, repaglinide, and rosiglitazone§. When PREVYMIS® is co-administered with cyclosporine, use of repaglinide is not recommended. |
| Antifungals | |||
| voriconazole | CT | ↓ voriconazole | Co-administration of PREVYMIS® with voriconazole decreases plasma concentrations of voriconazole. If concomitant administration is necessary, close monitoring for reduced effectiveness of voriconazole is recommended§. |
| Antimycobacterials | |||
| rifabutin | T | ↓ letermovir | Co-administration of PREVYMIS® with rifabutin may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and rifabutin is not recommended. |
| rifampin | CT | ↓ letermovir | Co-administration of PREVYMIS® with rifampin decreases plasma concentrations of letermovir. which may result in loss of prophylactic efficacy and necessitate initiation of anti-CMV therapy for CMV reactivation and/or disease. Co-administration of PREVYMIS® and rifampin is not recommended. |
| Endothelin Antagonists | |||
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| bosentan | T | ↓ letermovir | When PREVYMIS® is co-administered with cyclosporine, the use of bosentan is contraindicated (see 2 CONTRAINDICATIONS). Co-administration of PREVYMIS® with bosentan may decrease plasma concentrations of letermovir. Co-administration of bosentan with PREVYMIS® is not recommended. |
| Herbal Products | |||
| St. John’s wort (Hypericum perforatum) | T | ↓ letermovir | Co-administration of PREVYMIS® with St. John’s wort may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and St. John’s wort is not recommended. |
| HIV Medications | |||
| efavirenz | T | ↓ letermovir | Co-administration of PREVYMIS® with efavirenz may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and efavirenz is not recommended. |
| etravirine | T | ↓ letermovir | Co-administration of PREVYMIS® with etravirine may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and etravirine is not recommended. |
| nevirapine | T | ↓ letermovir | Co-administration of PREVYMIS® with nevirapine may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and nevirapine is not recommended. |
| HMG-CoA Reductase Inhibitors | |||
| atorvastatin | CT | ↑ atorvastatin | Co-administration of PREVYMIS® with atorvastatin increases plasma concentrations of atorvastatin. The dose of atorvastatin should not exceed 20 mg daily when co-administered with PREVYMIS®§. Closely monitor patients for adverse reactions such as myopathy. When PREVYMIS® is co-administered with cyclosporine, use of atorvastatin is not recommended. |
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| Simvastatin, lovastatin, rosuvastatin | T | ↑ simvastatin lovastatin rosuvastatin | When PREVYMIS® is co-administered with cyclosporine, the use of lovastatin or rosuvastatin or simvastatin is contraindicated (see 2 CONTRAINDICATIONS). Concomitant use with PREVYMIS® is not recommended. |
fluvastatin, pravastatin | T | ↑ fluvastatin, pravastatin | When PREVYMIS® is co-administered with these statins, a statin dosage reduction may be necessary§. Closely monitor patients for adverse reactions such as myopathy. When PREVYMIS® is co-administered with cyclosporine, refer to the statin product monograph for specific statin dosing recommendations§. |
| Immunosuppressants | |||
| cyclosporine | CT | ↑ cyclosporine ↑ letermovir | Co-administration of PREVYMIS® with cyclosporine increases concentrations of both letermovir and cyclosporine. When PREVYMIS® is co-administered with cyclosporine (a potent OATP1B1/3 inhibitor), the dosage of PREVYMIS® should be decreased to 240 mg once daily (see 4.2 Recommended Dose and Dosage adjustment and 10.3 Pharmacokinetics). Frequent monitoring of cyclosporine whole blood concentrations should be performed during and at discontinuation of PREVYMIS® and the dose of cyclosporine adjusted accordingly§. |
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| sirolimus | CT | ↑ sirolimus | Co-administration of PREVYMIS® with sirolimus increases concentrations of sirolimus. Frequent monitoring of sirolimus whole blood concentrations should be performed during and at discontinuation of PREVYMIS® and the dose of sirolimus adjusted accordingly §. When PREVYMIS® is co-administered with cyclosporine, refer to the sirolimus product monograph for specific sirolimus dosing recommendations§. |
| tacrolimus | CT | ↑ tacrolimus | Co-administration of PREVYMIS® with tacrolimus increases tacrolimus plasma concentrations. Frequent monitoring of tacrolimus whole blood concentrations should be performed during and at discontinuation of PREVYMIS® and the dose of tacrolimus adjusted accordingly§. |
| Proton Pump Inhibitors | |||
omeprazole pantoprazole | T | ↓omeprazole ↓pantoprazole | Co-administration of PREVYMIS® with these proton pump inhibitors (PPI) may decrease plasma concentrations of the PPIs. Clinical monitoring and dose adjustment may be needed when co-administered with PREVYMIS®§. |
| Wakefulness-Promoting Agents | |||
| modafinil | T | ↓ letermovir | Co-administration of PREVYMIS® with modafinil may decrease plasma concentrations of letermovir. Co-administration of PREVYMIS® and modafinil is not recommended. |
| CYP3A Substrates | |||
| [Proper/Common name] | Source of Evidence | Effect† | Clinical comment |
| Examples: alfentanil, fentanyl, midazolam, quinidine | T, CT | ↑concentrations of CYP3A substrate | PREVYMIS® may increase the plasma concentrations of CYP3A substrates. Frequent monitoring for adverse reactions related to CYP3A substrates is recommended during co-administration. Dose adjustment of CYP3A substrates may be needed§ (see 7 WARNINGS AND PRECAUTIONS). When PREVYMIS® is co-administered with a CYP3A substrate, refer to the product monograph for dosing of the CYP3A substrate with a moderate CYP3A inhibitor§. When PREVYMIS® is co-administered with alfentanil, fentanyl, and midazolam, closely monitor patients for adverse reactions such as respiratory depression and prolonged sedation. When PREVYMIS® is co-administered with quinidine, closely monitor patients for adverse reactions such as ventricular arrhythmia and hypotension. When PREVYMIS® is co-administered with cyclosporine, the combined effect on CYP3A substrates may be similar to a strong CYP3A inhibitor. Refer to the CYP3A substrate product monograph for dosing of the CYP3A substrate with a strong CYP3A inhibitor§. |
β This table is not all inclusive. † ↓ =decrease, ↑=increase § Refer to the respective product monograph. ¶ Effect on concentration for repaglinide and rosiglitazone is based on physiologically based pharmacokinetic modeling. | |||
Legend: CT = Clinical Trial; T = Theoretical
Drugs without Clinically Significant Interactions with PREVYMIS®
There was no clinically relevant interaction when PREVYMIS® was co-administered with itraconazole, a P-gp/BCRP inhibitor.
There were no clinically relevant changes in plasma concentrations of digoxin, a P-gp substrate, and acyclovir, an OAT3 substrate, following co-administration with PREVYMIS® in clinical studies (see below).
The interaction between letermovir and the following drugs was evaluated in clinical studies: mycophenolate mofetil, fluconazole, posaconazole, and oral combinations of ethinyl estradiol/levonorgestrel. No dose adjustments are needed when PREVYMIS® is used with these drugs.
Drug Interaction Studies
Drug interaction studies were performed in healthy subjects with PREVYMIS® and drugs likely to be co-administered or drugs commonly used as probes for pharmacokinetic interactions (see Table 6 and Table 7).
In vitro results indicate that letermovir is a substrate of OATP1B1/3, P-gp, UGT1A1, and UGT1A3. Inhibitors of OATP1B1/3 transporters may result in increases in letermovir plasma concentrations. If PREVYMIS® is co-administered with cyclosporine (a potent OATP1B1/3 inhibitor), the recommended dose of PREVYMIS® is 240 mg once daily (see 4.2 Recommended Dose and Dosage Adjustment). Changes in letermovir plasma concentrations due to inhibition of P-gp/BCRP by itraconazole were not clinically relevant. Inhibition of UGTs is not anticipated to have a clinically relevant effect on letermovir plasma concentrations. Induction of drug enzymes (e.g., UGTs) and/or transporters (e.g., P-gp) by rifampin may result in clinically relevant decreases in letermovir plasma concentrations; therefore, co-administration of strong and moderate inducers with letermovir is not recommended (see Effect of Other Drugs on PREVYMIS®, Table 5, and Table 6). Although CYP3A, CYP2D6 and CYP2J2 were identified as enzymes capable of mediating the metabolism of letermovir in vitro, oxidative metabolism is considered to be a minor elimination pathway based on in vivo human data.
Letermovir is a time-dependent inhibitor and inducer of CYP3A in vitro. Co-administration of PREVYMIS® with midazolam resulted in increased exposure of midazolam, indicating that the net effect of letermovir on CYP3A is moderate inhibition (see Table 5). Based on these results, co-administration of PREVYMIS® with CYP3A substrates may increase the plasma concentrations of the CYP3A substrates (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS, 9.4 Drug-Drug Interactions, and Table 5). Letermovir is a reversible inhibitor of CYP2C8 in vitro. Physiologically based pharmacokinetic modeling predicts an increase in plasma concentrations of CYP2C8 substrates when co-administered with PREVYMIS® (see Table 5 in 9.4 Drug-Drug Interactions). Co-administration of PREVYMIS® reduced the exposure of voriconazole, most likely due to the induction of voriconazole elimination pathways, CYP2C9 and CYP2C19. Co-administration of PREVYMIS® with CYP2C9 and CYP2C19 substrates may decrease the plasma concentrations of the CYP2C9 and CYP2C19 substrates (see Table 5 in 9.4 Drug-Drug Interactions). Letermovir is an inducer of CYP2B6 in vitro; the clinical relevance is unknown.
Letermovir inhibited efflux transporters P-gp, breast cancer resistance protein (BCRP), bile salt export pump (BSEP), multidrug resistance-associated protein 2 (MRP2), OAT3, and hepatic uptake transporter OATP1B1/3 in vitro. Co-administration of PREVYMIS® with substrates of OATP1B1/3 transporters (e.g., atorvastatin, a known substrate of CYP3A, OATP1B1/3, and potentially BCRP) may result in a clinically relevant increase in plasma concentrations of OATP1B1/3 substrates (see Table 5 in 9.4 Drug-Drug Interactions). There were no clinically relevant changes in plasma concentrations of digoxin, a P-gp substrate, or acyclovir, an OAT3 substrate, following co-administration with PREVYMIS® in clinical studies (see Table 7). The effect of letermovir on BCRP, BSEP, and MRP2 substrates was not evaluated in clinical studies; the clinical relevance is unknown.
Table 6 - Drug Interactions: Changes in Pharmacokinetics of Letermovir in the Presence of Co-Administered Drug
| Co-administered Drug | Regimen of Co-administered Drug | Letermovir Regimen | N | Geometric Mean Ratio [90% CI] of Letermovir PK with/without Co-administered Drug (No Effect=1.00) | |
|---|---|---|---|---|---|
| AUC | Cmax | ||||
| Antifungals | |||||
| fluconazole | 400 mg single dose PO | 480 mg single dose PO | 14 | 1.11 (1.01, 1.23) | 1.06 (0.93, 1.21) |
| itraconazole | 200 mg once daily PO | 480 mg once daily PO | 14 | 1.33 (1.17, 1.51) | 1.21 (1.05, 1.39) |
| Antimycobacterials | |||||
| rifampin | 600 mg single dose PO | 480 mg single dose PO | 16 | 2.03 (1.84, 2.26) | 1.59 (1.46, 1.74) |
| 600 mg single dose IV | 480 mg single dose PO | 16 | 1.58 (1.38, 1.81) | 1.37 (1.16, 1.61) | |
| 600 mg once daily PO** | 480 mg once daily PO | 14 | 0.81 (0.67, 0.98) | 1.01 (0.79, 1.28) | |
| 600 mg once daily PO (24 hours after rifampin)† | 480 mg once daily PO | 14 | 0.15 (0.13, 0.17) | 0.27 (0.22, 0.31) | |
| Immunosuppressants | |||||
| cyclosporine | 200 mg single dose PO | 240 mg once daily PO | 12 | 2.11 (1.97, 2.26) | 1.48 (1.33, 1.65) |
mycophenolate mofetil | 1 g single dose PO | 480 mg once daily PO | 14 | 1.18 (1.04, 1.32) | 1.11 (0.92, 1.34) |
| tacrolimus | 5 mg single dose PO | 80 mg twice daily PO | 14 | 1.02 (0.97, 1.07) | 0.92 (0.84, 1.00) |
Abbreviations: PO= oral ** C24 GMR [90%] is 0.14 (0.11, 0.19) † These data are the effect of rifampin on letermovir 24 hours after final rifampin dose. C24 GMR [90%] is 0.09 (0.06, 0.12). | |||||
Table 7 - Drug Interactions: Changes in Pharmacokinetics for Co-Administered Drug in the Presence of Letermovir or Co-Administered Letermovir
| Co-administered Drug | Regimen of Co-administered Drug | Letermovir Regimen | N | Geometric Mean Ratio [90% CI] of Co-administered Drug PK with/without Letermovir (No Effect=1.00) | |
|---|---|---|---|---|---|
| AUC | Cmax | ||||
| CYP3A Substrates | |||||
| midazolam | 1 mg single dose IV | 240 mg once daily PO | 16 | 1.47 (1.37, 1.58) | 1.05 (0.94, 1.17) |
| 2 mg single dose PO | 240 mg once daily PO | 16 | 2.25 (2.04, 2.48) | 1.72 (1.55, 1.92) | |
| P-gp Substrates | |||||
| digoxin | 0.5 mg single dose PO | 240 mg twice daily PO | 22 | 0.88 (0.80, 0.96) | 0.75 (0.63, 0.89) |
| Immunosuppressants | |||||
| cyclosporine | 50 mg single dose PO | 240 mg once daily PO | 14 | 1.66 (1.51, 1.82) | 1.08 (0.97, 1.19) |
mycophenolate mofetil | 1 g single dose PO | 480 mg once daily PO | 14 | 1.08 (0.97, 1.20) | 0.96 (0.82, 1.12) |
| tacrolimus | 5 mg single dose PO | 480 mg once daily PO | 13 | 2.42 (2.04, 2.88) | 1.57 (1.32, 1.86) |
| sirolimus | 2 mg single dose PO | 480 mg once daily PO | 13 | 3.40 (3.01, 3.85) | 2.76 (2.48, 3.06) |
| Antifungals and Antivirals | |||||
| acyclovir | 400 mg single dose PO | 480 mg once daily PO | 13 | 1.02 (0.87, 1.2) | 0.82 (0.71, 0.93) |
| fluconazole | 400 mg single dose PO | 480 mg single dose PO | 14 | 1.03 (0.99, 1.08) | 0.95 (0.92, 0.99) |
| itraconazole | 200 mg once daily PO | 480 mg once daily PO | 14 | 0.76 (0.71, 0.81) | 0.84 (0.76, 0.92) |
| posaconazole | 300 mg single dose PO | 480 mg once daily PO | 13 | 0.98 (0.82, 1.17) | 1.11 (0.95, 1.29) |
| voriconazole | 200 mg twice daily PO | 480 mg once daily PO | 12 | 0.56 (0.51,0.62) | 0.61 (0.53, 0.71) |
| HMG-CoA Reductase Inhibitors | |||||
| atorvastatin | 20 mg single dose PO | 480 mg once daily PO | 14 | 3.29 (2.84, 3.82) | 2.17 (1.76, 2.67) |
| Oral Contraceptives | |||||
| Co-administered Drug | Regimen of Co-administered Drug | Letermovir Regimen | N | Geometric Mean Ratio [90% CI] of Co-administered Drug PK with/without Letermovir (No Effect=1.00) | |
|---|---|---|---|---|---|
| AUC | Cmax | ||||
| ethinyl estradiol (EE) /levonorgestrel (LNG) | 0.03 mg EE single dose PO | 480 mg once daily PO | 22 | 1.42 (1.32, 1.52) | 0.89 (0.83, 0.96) |
| 0.15 mg LNG single dose PO | 22 | 1.36 (1.30, 1.43) | 0.95 (0.86, 1.04) | ||
| Abbreviations: PO=oral | |||||
9.5 Drug-Food Interactions
Food increases peak levels (Cmax) but not exposure (AUCT) of PREVYMIS® following administration with a high fat, high calorie meal (see 4.1 Dosing Considerations and 10.3 Pharmacokinetics, Absorption, Effect of Food).
9.6 Drug-Herb Interactions
Co-administration of PREVYMIS® with St. John’s wort (Hypericum perforatum) may decrease plasma concentrations of letermovir.
Co-administration of PREVYMIS® and St. John’s wort is not recommended (see Table 5 in 9.4 Drug-Drug Interactions).
9.7 Drug-Laboratory Test Interactions
Interactions with clinical laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
PREVYMIS® is an antiviral drug against CMV (see 15 MICROBIOLOGY).
10.2 Pharmacodynamics
Cardiac Electrophysiology
The effect of letermovir on doses up to 960 mg given IV on the QTc interval was evaluated in a randomized, single-dose, placebo- and active-controlled (moxifloxacin 400 mg oral) 4-period crossover thorough QT trial in 38 healthy subjects. Letermovir did not prolong QTc to any clinically relevant extent following the 960 mg IV dose with plasma concentrations approximately 2-fold higher than the 480 mg IV dose.
10.3 Pharmacokinetics
The pharmacokinetics of letermovir have been characterized following oral and IV administration in healthy subjects and HSCT recipients and following oral administration in kidney transplant recipients.
Healthy Subjects
Letermovir exposure increased in a greater than dose-proportional manner with both oral or IV administration following single and multiple doses of 240 mg and 480 mg. Letermovir was absorbed rapidly with a median time to maximum plasma concentration (Tmax) of 1.5 to 3.0 hours and declined in a biphasic manner. The geometric mean steady-state AUC and Cmax values were 71,500 ng•hr/mL and 13,000 ng/mL, respectively, with 480 mg once daily oral PREVYMIS®. The post-absorption plasma concentration-time profile of letermovir following oral administration was similar to the profile observed with IV dosing. Letermovir clearance (CL) reached steady-state in 9 to 10 days with an accumulation ratio of 1.22 for AUC and 1.03 for Cmax.
HSCT Recipients
Letermovir AUC was estimated using population pharmacokinetic analyses using Phase 3 data (see Table 8). Differences in exposure across treatment regimens are not clinically relevant; efficacy was consistent across the range of exposures observed in P001.
Table 8 - Letermovir AUC (ng•hr/mL) Values in HSCT Recipients
| Treatment Regimen | Median (90% Prediction Interval)β |
|---|---|
| 480 mg Oral, no cyclosporine | 34,400 (16,900, 73,700) |
| 480 mg IV, no cyclosporine | 100,000 (65,300, 148,000) |
| 240 mg Oral, with cyclosporine | 60,800 (28,700, 122,000) |
| 240 mg IV, with cyclosporine | 70,300 (46,200, 106,000) |
| β Medians and 90% prediction intervals are based on simulations using the Phase 3 population PK model with inter-individual variability. | |
Kidney Transplant Recipients
Letermovir AUC was estimated using population pharmacokinetic analysis using Phase 3 data (see Table 9). Efficacy was consistent across the range of exposures observed in P002.
Table 9 - Letermovir AUC (ng•hr/mL) Values in Kidney Transplant Recipients
| Treatment Regimen | Median (90% Prediction Interval)β |
|---|---|
| 480 mg Oral, no cyclosporine | 62,200 (28,900, 145,000) |
| 240 mg Oral, with cyclosporine | 57,700 (26,900, 135,000) |
| β Medians and 90% prediction intervals are based on simulations using the Phase 3 population PK model with inter-individual variability. | |
Absorption
In healthy subjects, absolute bioavailability of letermovir was estimated to be approximately 94% over the dose range 240 mg to 480 mg based on population pharmacokinetic analyses. In HSCT recipients, bioavailability of letermovir was estimated to be approximately 35% with 480 mg once daily oral PREVYMIS® administered without cyclosporine. The inter-individual variability for bioavailability was estimated to be approximately 37%. In kidney transplant recipients, bioavailability of letermovir was estimated to be approximately 60% with 480 mg once daily oral PREVYMIS® administered without cyclosporine.
Effect of Cyclosporine
In HSCT recipients, co-administration of cyclosporine increased plasma concentrations of letermovir. Bioavailability of letermovir was estimated to be approximately 85% with 240 mg once daily oral PREVYMIS® co-administered with cyclosporine. If PREVYMIS® is co-administered with cyclosporine, the recommended dose of PREVYMIS® is 240 mg once daily (see 4.2 Recommended Dose and Dosage Adjustment).
Effect of Food
Relative to administration under fasting conditions, oral administration of a single 480 mg dose of PREVYMIS® 480 mg tablets with a standard high fat, high calorie meal resulted in no significant effect on overall exposure (AUCT) of letermovir and an increase in peak levels (Cmax) of approximately 30%. The increase in Cmax is not clinically relevant (see 4.1 Dosing Considerations and 9.5 Drug-Food Interactions).
Distribution:
Based on population pharmacokinetic analyses, the mean steady-state volume of distribution is estimated to be 45.5 L following IV administration in HSCT recipients.
Letermovir is extensively bound (98.7%) to human plasma proteins in vitro. Blood to plasma partitioning of letermovir is 0.56 and independent of the concentration range (0.1 to 10 mg/L) evaluated in vitro.
In preclinical distribution studies, letermovir is distributed to organs and tissues with the highest concentrations observed in the gastrointestinal tract, bile duct and liver and low concentrations in the brain.
In pregnant rats, letermovir was able to cross the placenta (see 7.1 Special Populations, Pregnant Women).
Metabolism:
The majority of drug-related component in plasma is unchanged parent (96.6%). No major metabolites are detected in plasma. Letermovir is partly eliminated by glucuronidation mediated by UGT1A1/1A3.
Elimination
The mean apparent terminal half-life for letermovir is approximately 12 hours with 480 mg IV PREVYMIS® in healthy subjects.
Excretion
Based on population pharmacokinetic analyses, letermovir steady-state CL is estimated to be 4.84 L/hr following IV administration in HSCT recipients. The inter-individual variability for CL is estimated to be 24.6%.
After oral administration of radio-labeled letermovir, 93.3% of radioactivity was recovered in feces. The majority of drug was excreted as unchanged parent with a minor amount (6% of dose) as an acyl-glucuronide metabolite in feces. Urinary excretion of letermovir was negligible (<2% of dose).
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of letermovir in pediatric patients less than 18 years of age have not been evaluated.
- Geriatrics: Based on population pharmacokinetic analyses, there is no effect of age on letermovir pharmacokinetics. No dose adjustment is required based on age.
- Sex: Based on population pharmacokinetic analyses, there is no difference in letermovir pharmacokinetics in females compared to males.
- Genetic Polymorphism: The impact of genetic variants in the OATP1B1 gene SLCO1B1 (rs4149056, rs2306283, rs4149032) and UGT1A1 (rs4148323 and the promoter TA repeat variants) on the pharmacokinetics of letermovir was evaluated in 299 study participants. There was no clinically relevant impact of these variants on letermovir exposures.
- Ethnic Origin: Based on Phase 1 population pharmacokinetic analyses in HSCT recipients, letermovir AUC is estimated to be 33.2% higher in Asians compared to Whites. This change is not clinically relevant.
Hepatic Insufficiency: Letermovir AUC was approximately 1.6- and 3.8-fold higher in subjects with moderate (Child-Pugh Class B [CP-B], score of 7-9) and severe (Child-Pugh Class C [CP-C], score of 10-15) hepatic impairment, respectively, compared to healthy subjects. The changes in letermovir exposure in subjects with moderate hepatic impairment are not clinically relevant.
Clinically relevant increases in letermovir exposure are anticipated in patients with severe hepatic impairment.
Renal Insufficiency:
- Clinical Study in a Renally Impaired Population
Letermovir AUC was approximately 1.9- and 1.4-fold higher in subjects with moderate (eGFR greater than or equal to 30 to 59 mL/min/1.73m2) and severe (eGFR less than 30 mL/min/1.73m2) renal impairment, respectively, compared to healthy subjects. The changes in letermovir exposure due to renal impairment are not clinically relevant.
- Post-kidney Transplant
Based on population pharmacokinetic analysis, letermovir AUC was approximately 1.1-, 1.3- and 1.4-fold higher in subjects with mild (CrCl greater than or equal to 60 to less than 90 mL/min), moderate (CrCl greater than or equal to 30 to less than 60 mL/min) and severe (CrCl greater than or equal to 15 to less than 30 mL/min) renal impairment, respectively, compared to subjects with CrCl greater than or equal to 90 mL/min. These changes are not clinically relevant.
- Combined Renal and Hepatic Insufficiency: Clinically relevant increases in letermovir exposure are anticipated in patients with moderate hepatic impairment combined with moderate or severe renal impairment.
- Obesity: Based on Phase 1 population pharmacokinetic analyses, letermovir AUC is estimated to be 18.7% lower in subjects weighing 80-100 kg compared to subjects weighing 67 kg. Based on population pharmacokinetic analysis in kidney transplant recipients, letermovir AUC is estimated to be 26% lower in subjects weighing greater than 80 kg compared to subjects weighing less than or equal to 80 kg. These changes are not clinically relevant.
11 STORAGE, STABILITY AND DISPOSAL
Tablets and solution for injection:
Store PREVYMIS® tablets in the original package until use.
Store PREVYMIS® tablets at room temperature (15°C to 30°C).
Store PREVYMIS® for injection vials at 15°C to 25°C. Store in the original carton to protect from exposure to light.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: letermovir
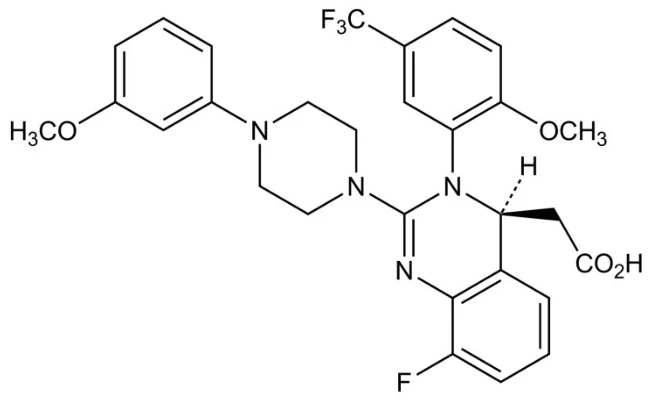
Chemical name: (4S)-2-{8-Fluoro-2-[4-(3- methoxyphenyl)piperazin-1-yl]-3-[2-methoxy-5- (trifluoromethyl)phenyl]-3,4-dihydroquinazolin-4-yl}acetic acid
Molecular formula and molecular mass: C29H28F4N4O4, 572.55
Structural formula:
Physicochemical properties: Letermovir drug substance (DS) is amorphous powder, with two pKa values at 3.6 and 7.1. Letermovir exists predominantly in the zwitterion form between pH 4 and pH 7 with a low intrinsic solubility of approximately 0.3 mg/mL. Solubility increases above pH 7 to 7.7 mg/mL and 25.5 mg/mL at pH 8 and pH 9, respectively.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Adult CMV-seropositive Recipients [R+] of an Allogeneic Hematopoietic Stem Cell Transplant (HSCT):
A phase III study to evaluate the safety and efficacy of PREVYMIS® in the prevention of clinically significant CMV infection in adult CMV-seropositive recipients [R+] of an allogeneic HSCT. A summary of trial design and demographics is presented in Table 10:
Table 10 - Summary of Trial Design and Patient Demographics for the Phase III Trial in HSCT Recipients (P001)
| Study # | Study design | Dosage, route of administratio n and duration | Study subjects (n) | Mean age (Range) | Other Demographic Characteristic s | Baseline Patient Characteristics |
P001 Prophylaxi s Through Week 14 (~100 days) Post-HSCT | Randomize d, double-blind, placebo-controlled, multi-site | PREVYMIS®: 480 mg QD or 240 mg QD dose, if given concomitantly with CsA, through Week 14 (~100 days) post-HSCT; dose is the same for both oral tablets and IV formulation. Placebo: matching placebo oral tablets for letermovir oral tablets; normal saline or 5% dextrose as placebo comparator for IV letermovir formulation | Total: 565 PREVYMIS® : 373 Placebo: 192 | Mean: 50.8 years Median : 54 years Range: (18 - 78 years) | Male: 58% Female: 42% 10% were Asian; 2% were Black or African; and 7% were Hispanic or Latino | The most common primary reasons for HCST were acute myeloid leukemia (38%), myeloblastic syndrome (15%), and lymphoma (13%). 50% of subjects received a myeloablative regimen, 52% were receiving cyclosporine, and 42% were receiving tacrolimus. Twelve percent (12%) of subjects were positive for CMV DNA at baseline. |
P040 Prophylaxi s From Week 14 (~100 days) Through Week 28 (~200 days) Post-HSCT | Randomize d, double-blind, placebo-controlled, multi-site | PREVYMIS®: 480 mg QD or 240 mg QD dose, if given concomitantly with CsA, from Week 14 through Week 28 (~200 days) post-HSCT; dose is the same for both oral tablets and IV formulation. Placebo: matching placebo oral tablets for letermovir oral tablets; normal saline or 5% dextrose as placebo comparator for IV letermovir formulation | Total: 218 PREVYMIS® : 144 Placebo: 74 | Mean: 52.2 years Median : 55 years Range: (20 - 74 years) | Male: 62% Female: 38% 11% were Asian; 2% were Black or African; and 10% were Hispanic or Latino | The most common primary reasons for HCST were acute myeloid leukemia (42%), acute lymphocytic leukemia (15%), and myelodysplasti c syndrome (11%). |
Prophylaxis Through Week 14 (~100 days) Post-HSCT
Subjects were randomized (2:1) to receive either PREVYMIS® or placebo. Randomization was stratified by investigational site and risk level for CMV reactivation at the time of study entry. Study drug was initiated after HSCT (Day 0-28 post-HSCT) and continued through Week 14 post-HSCT. Subjects were monitored through Week 24 post-HSCT for the primary efficacy endpoint.
At baseline, 31% of subjects were in the high risk stratum as defined by one or more of the following criteria: Human Leukocyte Antigen (HLA)-related (sibling) donor with at least one mismatch at one of the following three HLA-gene loci: HLA-A, -B or –DR, haploidentical donor; unrelated donor with at least one mismatch at one of the following four HLA-gene loci: HLA-A, -B, -C and -DRB1; use of umbilical cord blood as stem cell source; use of ex vivo T-cell-depleted grafts; Grade 2 or greater Graft-Versus-Host Disease (GVHD), requiring systemic corticosteroids. The remaining 69% of subjects did not meet any of these high risk stratum criteria and were therefore included in the low risk stratum.
Clinically Significant CMV Infection
The primary efficacy endpoint of P001 was the incidence of clinically significant CMV infection through Week 24 post-HSCT. Clinically significant CMV infection was defined as the occurrence of either CMV end-organ disease, or initiation of anti-CMV pre-emptive therapy (PET) based on documented CMV viremia (using the Roche COBAS* AmpliPrep/COBAS TaqMan* assay, Lower Limit of Quantification (LLoQ) is 137 IU/mL, which is approximately 150 copies/mL) and the clinical condition of the subject. The Non-Completer=Failure (NC=F) approach was used, where subjects who discontinued from the study prior to Week 24 post-HSCT or had a missing outcome at Week 24 post-HSCT were counted as failures.
PREVYMIS® demonstrated superior efficacy over placebo in the analysis of the primary endpoint, as shown in Table 11. The estimated treatment difference of -23.5% was statistically significant (one-sided p-value <0.0001).
Table 11- P001 Efficacy Results in HSCT Recipients (NC=F Approach, FAS Population)
| Parameter | PREVYMIS® (N=325) n (%) | Placebo (N=170) n (%) | ||||||
|---|---|---|---|---|---|---|---|---|
| Primary Endpoint | 122 (37.5) | 103 (60.6) | ||||||
| (Proportion of subjects who failed prophylaxis) | ||||||||
| Reasons for Failuresβ | ||||||||
| Clinically significant CMV infection by Week 24† | 57 (17.5) | 71 (41.8) | ||||||
| Initiation of PET based on documented CMV viremia | 52 (16.0) | 68 (40.0) | ||||||
| CMV end-organ disease | 5 (1.5) | 3 (1.8) | ||||||
| Discontinued from study before Week 24 | 56 (17.2) | 27 (15.9) | ||||||
| Missing outcome in Week 24 visit window | 9 (2.8) | 5 (2.9) | ||||||
| Stratum-adjusted treatment difference (PREVYMIS®-Placebo)‡ | ||||||||
| Difference (95% CI) | -23.5 (-32.5, -14.6) | |||||||
| p-value | <0.0001 | |||||||
β The categories of failure are mutually exclusive and based on the hierarchy of categories in the order listed. † Clinically significant CMV infection was defined as CMV end organ disease or initiation of PET based on documented CMV viremia and the clinical condition of the subject. ‡ 95% CIs and p-value for the treatment differences in percent response were calculated using stratum-adjusted Mantel-Haenszel method with the difference weighted by the harmonic mean of sample size per arm for each stratum (high or low risk). A 1-sided p-value ≤0.0249 was used for declaring statistical significance. Note: FAS=Full analysis set; FAS includes randomized subjects who received at least one dose of study medication, and excludes subjects with detectable CMV DNA at baseline. Approach to handling missing values: Non-Completer=Failure (NC=F) approach. With NC=F approach, failure was defined as all subjects who developed clinically significant CMV infection or prematurely discontinued from the study or had a missing outcome through Week 24 post-HSCT visit window. N = number of subjects in each treatment group. n (%) = Number (percent) of subjects in each sub-category. | ||||||||
At Week 14 post-HSCT, the Kaplan-Meier (K-M) event rate for clinically significant CMV infection was 6.8% in the PREVYMIS® group compared to 41.3% in the placebo group. At Week 24 post-HSCT, the K-M event rate for clinically significant CMV infection was 18.9% in the PREVYMIS® group compared to 44.3% in the placebo group (nominal two-sided stratified log-rank p-value<0.0001). Factors associated with clinically significant CMV infection between Week 14 and Week 24 post-HSCT among PREVYMIS®-treated subjects included high risk for CMV reactivation at baseline, having GVHD, and steroid use at any time after randomization.
Of the 373 subjects treated with PREVYMIS® in P001, 56 (15.0%) subjects were 65 years of age or older. Safety and efficacy were similar across older and younger subjects.
Efficacy consistently favored PREVYMIS® across subgroups including low and high risk strata for CMV reactivation, stem cell source, donor mismatch, haploidentical transplant, conditioning regimens, and concomitant immunosuppressive regimens.
Mortality
The K-M event rate for all-cause mortality in the letermovir vs. placebo groups was 12.1% vs. 17.2% at Week 24 post-HSCT, and 23.8% vs. 27.6% at Week 48 post-HSCT.
The K-M event rate for CMV-related mortality (defined as death due to any reason in patients with clinically significant CMV infection [primary endpoint]) in the letermovir vs. placebo group was 0.7% vs. 9.1% at Week 24 post-HSCT (nominal two-sided stratified log-rank p-value < 0.0001), and 3.6% vs. 16.0% at Week 48 post-HSCT (nominal two-sided stratified log rank p-value < 0.0001).
Prophylaxis From Week 14 (~100 days) Through Week 28 (~200 days) Post-HSCT
The efficacy of extending PREVYMIS® prophylaxis from Week 14 (~100 days) through Week 28 (~200 days) post-HSCT in patients at risk for late CMV infection and disease was assessed in adult CMV-seropositive recipients [R+] of an allogeneic HSCT. Eligible subjects who completed PREVYMIS® prophylaxis through ~100 days post-HSCT were randomized (2:1) to receive PREVYMIS® or placebo from Week 14 through Week 28 post-HSCT. Subjects were monitored through Week 28 post-HSCT for the primary efficacy endpoint with continued off-treatment follow-up through Week 48 post-HSCT.
At study entry, all subjects had risk factors for late CMV infection and disease, with 64% having two or more risk factors. The risk factors included: HLA-related (sibling) donor with at least one mismatch at one of the following three HLA-gene loci: HLA-A, -B or –DR; haploidentical donor; unrelated donor with at least one mismatch at one of the following four HLA-gene loci: HLA-A, -B, -C and -DRB1; use of umbilical cord blood as stem cell source; use of ex vivo T-cell-depleted grafts; receipt of anti-thymocyte globulin; receipt of alemtuzumab; use of systemic prednisone (or equivalent) at a dose of ≥1 mg/kg of body weight per day.
Clinically Significant CMV Infection
The primary efficacy endpoint of P040 was the incidence of clinically significant CMV infection through Week 28 post-HSCT. Clinically significant CMV infection was defined as the occurrence of either CMV end-organ disease, or initiation of anti-CMV PET based on documented CMV viremia and the clinical condition of the subject.
The Observed Failure (OF) approach was used, where subjects who discontinued prematurely from the study without viremia or were missing data at the timepoint were not counted as failures. The number of subjects who discontinued from the study before Week 28 without viremia was 14 (9.7%) in the PREVYMIS arm and 0 in the placebo arm. The number of subjects with a missing outcome in the Week 28 visit window was 3 (2.1%) in the PREVYMIS arm and 4 (5.4%) in the placebo arm, none had prior viremia.
PREVYMIS® demonstrated superior efficacy over placebo in the analysis of the primary endpoint, as shown in Table 12. The estimated treatment difference of -16.1% was statistically significant (one-sided p-value=0.0005). Efficacy consistently favored PREVYMIS® across subgroups based on subject characteristics (age, gender, race) and risk factors for late CMV infection and disease.
Table 12. P040 Efficacy Results in HSCT Recipients at Risk for Late CMV Infection and Disease (OF Approach, FAS Population)
| Parameter | PREVYMIS® (~200 days PREVYMIS®) (N=144) n (%) | Placebo (~100 days PREVYMIS®) (N=74) n (%) |
|---|---|---|
| Failures β | 4 (2.8) | 14 (18.9) |
| Clinically significant CMV infection through Week 28† | 2 (1.4) | 13 (17.6) |
| Initiation of PET based on documented CMV viremia | 1 (0.7) | 11 (14.9) |
| CMV end-organ disease | 1 (0.7) | 2 (2.7) |
| Discontinued from study with CMV viremia before Week 28 | 2 (1.4) | 1 (1.4) |
| Stratum-adjusted treatment difference (PREVYMIS® (~200 days PREVYMIS®)-Placebo (~100 days PREVYMIS®)) ‡ | ||
| Difference (95% CI) | -16.1 (-25.8, -6.5) 0.0005 | |
| p-value | ||
β The categories of failure are mutually exclusive and based on the hierarchy of categories in the order listed. † Clinically significant CMV infection was defined as CMV end-organ disease (proven or probable) or initiation of PET based on documented CMV viremia and the clinical condition of the subject. ‡ 95% CIs and p-value for the treatment differences in percent response were calculated using stratum-adjusted Mantel-Haenszel method with the difference weighted by the harmonic mean of sample size per arm for each stratum (haploidentical donor yes or no). A one-sided p-value ≤0.0249 was used for declaring statistical significance. | ||
Approach to handling missing values: Observed Failure (OF) approach. With the OF approach, failure was defined as all subjects who developed clinically significant CMV infection or discontinued prematurely from the study with CMV viremia from Week 14 (~100 days) through Week 28 (~200 days) post-HSCT. N = Number of subjects in each treatment group. n (%) = Number (percent) of subjects in each sub-category. |
|---|
Among subjects in the PREVYMIS group, the cumulative rate of clinically significant CMV infection increased from 1.6% at the end of prophylaxis (Week 28) to 15.6% at Week 38. In the placebo group, the cumulative rate of clinically significant CMV infection increased from 17.6% at Week 28 to 19.0% at Week 38. There were no additional cases of clinically significant CMV infection in either group between Weeks 38 and 48.
Adult CMV-seronegative Recipients of a Kidney Transplant from a CMV-seropositive Donor [D+/R-]
A phase III study to evaluate the efficacy of PREVYMIS® prophylaxis as a preventive strategy for CMV disease in adult kidney transplant recipients at high risk [D+/R-]. A summary of trial design and demographics is presented in Table 13:
Table 13 - Summary of Trial Design and Patient Demographics for the Phase III Trial in Kidney Transplant Recipients (P002)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Other Demographic Characteristic s | Baseline Patient Characteristics |
| P002 | Randomized , double-blind, active comparator-controlled, non-inferiority, multi-site | PREVYMIS®: 480 mg QD or 240 mg QD dose, if given concomitantly with CsA, through Week 28 (~200 days) post-kidney transplant; dose is the same for both oral tablets and IV formulation. Acyclovir 400 mg twice daily was given concomitantly. Valganciclovir: 900 mg QD (oral) or ganciclovir 5 mg/kg QD (IV); adjusted based on renal function | Total: 589 PREVYMIS®: 292 Valganciclovi r: 297 | Mean: 49.6 years Median: 51 years Range: (18 - 82 years) | Male: 72% Female: 28% 2% were Asian; 9% were Black or African; and 17% were Hispanic or Latino 60% received a kidney from a deceased donor | The most common primary reasons for transplant were congenital cystic kidney disease (17%), hypertension (16%), and diabetes/diabeti c nephropathy (14%). |
Subjects were randomized (1:1) to receive either PREVYMIS® or valganciclovir. PREVYMIS® was given concomitantly with acyclovir for herpes simplex virus (HSV) and varicella zoster virus (VZV) prophylaxis. Subjects randomized to the valganciclovir group were given a placebo to acyclovir. Randomization was stratified by the use or nonuse of highly cytolytic, anti-lymphocyte immunotherapy during induction. Study drug was initiated between Day 0 and Day 7 post-kidney transplant and continued through Week 28 (~200 days) post-transplant. Subjects were monitored through Week 52 post-transplant.
CMV Disease
The primary efficacy endpoint of P002 was the incidence of CMV disease (CMV end-organ disease or CMV syndrome, confirmed by an independent adjudication committee) through Week 52 post-transplant. The Observed Failure (OF) approach was used, where subjects who discontinued prematurely from the study for any reason or were missing data at the timepoint were not considered failures. The number of subjects who discontinued from the study before Week 52 was 32 (11.1%) in the PREVYMIS® group and 28 (9.4%) in the valganciclovir group. The number of subjects with a missing outcome in the Week 52 visit window was 24 (8.3%) in the PREVYMIS® group and 25 (8.4%) in the valganciclovir group.
Based on a non-inferiority margin of 10%, PREVYMIS® demonstrated non-inferiority to valganciclovir in the analysis of the primary endpoint, as shown in Table 14.
Table 14: P002 Efficacy Results in Kidney Transplant Recipients (OF Approach, FAS Population)
| Parameter | PREVYMIS® (N=289) n (%) | Valganciclovir (N=297) n (%) |
|---|---|---|
CMV diseaseβ through Week 52 CMV Syndrome§ CMV End-Organ Disease | 30 (10.4) 24 (8.3) 6 (2.1) | 35 (11.8) 34 (11.4) 1 (0.3) |
Stratum-adjusted treatment difference (PREVYMIS®-Valganciclovir)† Difference (95% CI) | -1.4 (-6.5, 3.8)‡ | |
β CMV disease cases confirmed by an independent adjudication committee. § CMV syndrome was defined as evidence of CMV in blood by viral isolation, rapid culture, antigenemia, or nucleic acid testing, and two or more of the following: fever ≥38oC for at least 2 days, new or increased malaise/fatigue, leukopenia or neutropenia on two separate measurements at least 24 hours apart, ≥5% atypical lymphocytes, thrombocytopenia, elevation of ALT or AST to 2x ULN. † The 95% CIs for the treatment differences in percent response were calculated using stratum-adjusted Mantel-Haenszel method with the difference weighted by the harmonic mean of sample size per arm for each stratum (use/nonuse of highly cytolytic, anti-lymphocyte immunotherapy during induction). ‡ Based on a non-inferiority margin of 10%, PREVYMIS® is non-inferior to valganciclovir. Approach to handling missing values: Observed Failure (OF) approach. With OF approach, subjects who discontinued prematurely from the study for any reason are not considered failures. N = number of subjects in each treatment group. n (%) = number (percent) of subjects in each sub-category. | ||
Efficacy was comparable across all subgroups, including the use/nonuse of highly cytolytic, anti-lymphocyte immunotherapy during induction.
No subjects in the PREVYMIS® group experienced CMV disease through Week 28 post-transplant compared with 5 subjects in the valganciclovir group.
15 MICROBIOLOGY
Mechanism of Action
Letermovir inhibits the CMV DNA terminase complex, which is required for viral DNA replication. Biochemical characterization and electron microscopy demonstrated that letermovir affects the formation of proper unit length genomes and interferes with virion maturation.
Antiviral Activity
The median EC50 value of letermovir against a collection of clinical CMV isolates in a cell-culture model of infection was 2.1 nM (range = 0.7 nM to 6.1 nM, n = 74). There was no significant difference in EC50 value by CMV gB genotype (n=70).
Viral Resistance
In Cell Culture
The CMV genes UL51, UL56, and UL89 encode subunits of CMV DNA terminase. CMV mutants with reduced susceptibility to letermovir have been selected in cell culture, and the substitutions map to pUL51 (P91S, A95V), pUL56 (C25F, S229F,V231A, V231L, N232Y, V236A, V236L, V236M, E237D, L241P, T244K, T244R, L254F, L257F, L257I, K258E, F261C, F261L, F261S, Y321C, C325F, C325R, C325W, C325Y, L328V, M329T, A365S, N368D, R369G, R369M, R369S), and pUL89 (N320H, D344E). EC50 values for recombinant CMV mutants expressing these substitutions are 1.6- to 9300-fold higher than those for the wild-type reference virus. EC50 ratios of >3000 are interpreted as absolute letermovir resistance, because viral yield reduction occurs at visibly cytotoxic letermovir concentrations.
In Clinical Studies
In a Phase 2b trial evaluating letermovir doses of 60, 120, or 240 mg/day or placebo for up to 84 days in 131 HSCT recipients, DNA sequence analysis of a select region of UL56 (amino acids 231 to 369) was performed on samples obtained from 12 letermovir-treated subjects who experienced prophylaxis failure and for whom samples were available for analysis. One subject (who received 60 mg/day) had a letermovir resistant genotypic variant (GV) (V236M).
In a Phase 3 trial (P001), DNA sequence analysis of the entire coding regions of UL56 and UL89 was performed on samples obtained from 50 letermovir-treated subjects who experienced prophylaxis failure and for whom samples were available for analysis. A total of 4 letermovir resistance-associated substitutions all mapping to pUL56 were detected in 3 subjects as follows: V236M, C325W and R369T, and E237G, respectively.
In a Phase 3 trial (P002), DNA sequence analysis of the entire coding regions of UL51, UL56 and UL89 was performed on samples obtained from 52 letermovir-treated subjects who experienced CMV disease or who discontinued early with CMV viremia. There were no letermovir resistance-associated substitutions detected above the validated assay limit of 5%.
In a Phase 3 trial (P040), DNA sequence analysis of the entire coding regions of UL51, UL56 and UL89 was performed on samples obtained from 32 subjects (regardless of treatment group) who experienced prophylaxis failure or who discontinued early with CMV viremia. There were no letermovir resistance-associated substitutions detected above the validated assay limit.
Cross Resistance
Cross resistance is not likely with drugs outside of this class. Letermovir is fully active against viral populations with substitutions conferring resistance to CMV DNA polymerase inhibitors (ganciclovir, cidofovir, and foscarnet). A panel of recombinant CMV strains with substitutions conferring resistance to letermovir was fully susceptible to cidofovir, foscarnet and ganciclovir with the exception of a recombinant strain with the pUL56 E237G substitution which confers a 2.1-fold reduction in ganciclovir susceptibility relative to wild-type.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Testicular toxicity was noted only in rats at systemic exposures (AUC) ≥3-fold the exposures in humans at the recommended human dose (RHD). This toxicity was characterized by seminiferous tubular degeneration, and oligospermia and cell debris in the epididymides, with decreased testicular and epididymides weights. The No-Observed Adverse Effect Level (NOAEL) for testicular toxicity in rats was observed at exposures (AUC) in rats similar to the exposures in humans at the RHD. This testicular toxicity appears to be species-specific; testicular toxicity was not observed in mice and monkeys at the highest doses tested at exposures up to 4-fold and 2-fold, respectively, the exposures in humans at the RHD. The relevance to humans is unknown (see 8.3 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data).
Carcinogenicity: A 6-month oral carcinogenicity study in rasH2 transgenic (Tg.rasH2) mice showed no evidence of human-relevant tumorigenesis up to the highest doses tested, 150 mg/kg/day approximately the same AUC in humans at the RHD) and 300 mg/kg/day (approximately 2-fold the AUC in humans at the RHD) in males and females, respectively.
Genotoxicity: Letermovir was not genotoxic in a battery of in vitro or in vivo assays, including microbial mutagenesis assays, chromosomal aberration in Chinese Hamster Ovary cells, and in an in vivo mouse micronucleus study.
Reproductive and Developmental Toxicology:
Reproduction
In the fertility and early embryonic development studies in the rat, there were no effects of letermovir on female fertility at the highest dose tested, 240 mg/kg/day (approximately 5-fold the AUC in humans at the RHD). In male rats, reduced sperm concentration, reduced sperm motility, and decreased fertility were observed at systemic exposures ≥ 3-fold the AUC in humans at the RHD (see General Toxicity).
Development
In pregnant rats, maternal toxicity (including decrease in body weight gain) was noted at the highest dose of 250 mg/kg/day (approximately 11-fold the AUC at the RHD); in the offspring, decreased fetal weight with delayed ossification, slightly edematous fetuses, and increased incidence of shortened umbilical cords and of variations and malformations in the vertebrae, ribs, and pelvis were observed. No maternal or developmental effects were noted up to the dose of 50 mg/kg/day (approximately 2.5-fold the AUC at the RHD).
In pregnant rabbits, maternal toxicity (including mortality and abortions) was noted at the highest dose of 225 mg/kg/day (approximately 2-fold the AUC at the RHD); in the offspring, an increased incidence of malformations and variations in the vertebrae and ribs were observed. No maternal or developmental effects were noted up to the dose of 75 mg/kg/day (at less than the AUC at the RHD).
In the pre- and post-natal developmental study, no developmental toxicity was observed up to the highest exposure of 180 mg/kg/day (2-fold the AUC at the RHD).
Lactation
No effects of letermovir on growth and postnatal development were observed in nursing rat pups at the highest dose tested (at 2-fold the AUC at the RHD) (see 7.1 Special Populations, Pregnant Women).