


Product Monograph - Seacalphyx
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form/Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intravenous | Solution/25% | Sodium metabisulfite For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Seacalphyx (Sodium thiosulfate pentahydrate injection BP), is indicated for sequential use with sodium nitrite for the treatment of acute cyanide poisoning that is judged to be life-threatening. When the diagnosis of cyanide poisoning is uncertain, the potential risks associated with Seacalphyx, should be carefully weighed against the potential benefits, especially if the patient is not in extremis.
Identifying Patients with Cyanide Poisoning
Cyanide poisoning may result from inhalation, ingestion, or dermal exposure to various cyanide-containing compounds, including smoke from closed-space fires. Sources of cyanide poisoning include hydrogen cyanide and its salts, cyanogenic plants, aliphatic nitriles, and prolonged exposure to sodium nitroprusside.
The presence and extent of cyanide poisoning are often initially unknown. There is no widely available, rapid, confirmatory cyanide blood test. Treatment decisions must be made on the basis of clinical history and signs and symptoms of cyanide intoxication. If clinical suspicion of cyanide poisoning is high, sodium thiosulfate pentahydrate injection and Sodium Nitrite Injection should be administered without delay.
Table 1. Common Signs and Symptoms of Cyanide Poisoning
Symptoms
| Signs
(e.g., confusion, disorientation)
|
In some settings, panic symptoms including tachypnea and vomiting may mimic early cyanide poisoning signs. The presence of altered mental status (e.g., confusion and disorientation) and/or mydriasis is suggestive of true cyanide poisoning although these signs can occur with other toxic exposures as well.
The expert advice of a provincial poison control center may be obtained. Details can be found at this website:
http://www.safetyxchange.org/health-safety/canadian-poison-control-centres-contact-information
Smoke Inhalation
Not all smoke inhalation victims will have cyanide poisoning and may present with burns, trauma, and exposure to other toxic substances making a diagnosis of cyanide poisoning particularly difficult. Prior to administration of sodium thiosulfate pentahydrate injection, smoke-inhalation victims should be assessed for the following:
- Exposure to fire or smoke in an enclosed area
- Presence of soot around the mouth, nose, or oropharynx
- Altered mental status.
Although hypotension is highly suggestive of cyanide poisoning, it is only present in a small percentage of cyanide-poisoned smoke inhalation victims. Also indicative of cyanide poisoning is a plasma lactate concentration greater than or equal to 10 mmol/L (a value higher than that typically listed in the table of signs and symptoms of isolated cyanide poisoning because carbon monoxide associated with smoke inhalation also contributes to lactic acidemia). If cyanide poisoning is suspected, treatment should not be delayed to obtain a plasma lactate concentration.
CONTRAINDICATIONS
Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see the Dosage Forms, Composition and Packaging section of the prescribing information.
WARNINGS AND PRECAUTIONS
Use with Other Cyanide Antidotes
Caution should be exercised when administering cyanide antidotes, other than sodium nitrite, simultaneously with sodium thiosulfate pentahydrate injection as the safety of co-administration has not been established. If a decision is made to administer another cyanide antidote, other than sodium nitrite, with sodium thiosulfate pentahydrate injection, these drugs should not be administered concurrently in the same IV line.
Sulfites
Sodium thiosulfate drug product may contain trace impurities of sodium sulfite. The presence of a trace amount of sulfites in this product should not deter administration of the drug for treatment of emergency situations, even if the patient is sulfite-sensitive.
Special Populations
Pregnant Women:
Teratogenic Effects. Pregnancy Category C.
There are no adequate and well-controlled studies in pregnant women. Sodium thiosulfate pentahydrate injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
There are no reported epidemiological studies of congenital anomalies in infants born to women treated with sodium thiosulfate during pregnancy. In animal studies, there are no teratogenic effects in offspring of hamsters treated during pregnancy with sodium thiosulfate in doses similar to those given intravenously to treat cyanide poisoning in humans. Other studies suggest that treatment with sodium thiosulfate ameliorates the teratogenic effects of maternal cyanide poisoning in hamsters. In other studies, sodium thiosulfate was not embryotoxic or teratogenic in mice, rats, hamsters, or rabbits at maternal doses of up to 550, 400, 400 and 580 mg/kg/day, respectively.
Nursing Women:
It is not known whether sodium thiosulfate is excreted in human milk. Because sodium thiosulfate pentahydrate injection may be administered in life-threatening situations, breast-feeding is not a contraindication to its use. Because many drugs are excreted in human milk, caution should be exercised following sodium thiosulfate pentahydrate injection administration to a nursing woman. There are no data to determine when breastfeeding may be safely restarted following administration of sodium thiosulfate.
Pediatrics (< 18 years of age):
There are case reports in the medical literature of sodium nitrite in conjunction with sodium thiosulfate being administered to pediatric patients with cyanide poisoning; however, there have been no clinical studies to evaluate the safety or efficacy of sodium thiosulfate in the pediatric population. As for adult patients, dosing recommendations for pediatric patients have been based on theoretical calculations of antidote detoxifying potential, extrapolation from animal experiments, and a small number of human case reports.
Geriatrics (> 65 years of age):
Sodium thiosulfate is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
Decreased Renal Function:
Sodium thiosulfate is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function.
Monitoring and Laboratory Tests
Patients should be monitored for at least 24-48 hours after sodium thiosulfate pentahydrate injection administration for adequacy of oxygenation and perfusion and for recurrent signs and symptoms of cyanide toxicity. When possible, hemoglobin/hematocrit should be obtained when treatment is initiated.
Measurements of oxygen saturation using standard pulse oximetry and calculated oxygen saturation values based on measured PO2 are unreliable in the presence of methemoglobinemia.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
There have been no controlled clinical trials conducted to systematically assess the adverse events profile of sodium thiosulfate. The medical literature has reported the following adverse events in association with sodium thiosulfate administration. These adverse events were not reported in the context of controlled trials or with consistent monitoring and reporting methodologies for adverse events. Therefore, frequency of occurrence of these adverse events cannot be assessed.
Cardiovascular system: hypotension
Central nervous system: headache, disorientation
Gastrointestinal system: nausea, vomiting
Hematological: prolonged bleeding time
Body as a Whole: salty taste in mouth, warm sensation over body
In humans, rapid administration of concentrated solutions or solutions not freshly prepared, and administration of large doses of sodium thiosulfate have been associated with a higher incidence of nausea and vomiting. However, administration of 0.1 g sodium thiosulfate per pound up to a maximum of 15 g in a 10-15% solution over 10-15 minutes was associated with nausea and vomiting in 7 of 26 patients without concomitant cyanide intoxication.
In a series of 11 human subjects, a single intravenous infusion of 50 mL of 50% sodium thiosulfate was associated with increases in clotting time 1-3 days after administration. However, no significant changes were observed in other hematological parameters.
DRUG INTERACTIONS
Formal drug interaction studies have not been conducted with sodium thiosulfate pentahydrate injection.
DOSAGE AND ADMINISTRATION
Comprehensive treatment of acute cyanide intoxication requires support of vital functions. Administration of sodium nitrite and sodium thiosulfate should be considered adjunctive to appropriate supportive therapies. Airway, ventilatory and circulatory support, and oxygen administration should not be delayed to administer sodium nitrite and sodium thiosulfate.
Recommended Dose and Dosage Adjustment
| Population | Intravenous Dose of Sodium thiosulfate and Sodium Nitrite |
| Adults (>18 years of age) | 1.) Sodium Nitrite -10 mL of sodium nitrite at the rate of 2.5 to 5 mL/minute. 2.) Sodium thiosulfate, - 50 mL of sodium thiosulfate immediately following administration of sodium nitrite. |
| Children (<18 years of age) | 1.) Sodium Nitrite -0.2 mL/kg (6 mg/kg or 6-8 mL/m2 BSA) of sodium nitrite at the rate of 2.5 to 5 mL/minute not to exceed 10 mL 2.) Sodium thiosulfate - 1 mL/kg of body weight (250 mg/kg or approximately 30-40 mL/m2 of BSA) not to exceed 50 mL total dose immediately following administration of sodium nitrite. |
REPORTING SUSPECTED SIDE EFFECTS
You can report any suspected adverse reactions associated with the use of Seacalphyx to the Canada Vigilance Program by one of the following 3 ways:
- Report online at www.healthcanada.gc.ca/medeffect
Call toll-free at 1-866-234-2345
Complete a Canada Vigilance Reporting Form and:
- Fax toll free to 1-866-678-6789
Mail to:
Canada Vigilance Program Health Canada
Postal Locator 0701E Ottawa, Ontario
K1A 0K9
Postage paid labels, Canada Vigilance Reporting Form and the adverse reaction reporting guidelines are available on the MedEffect™ Canada Web site at www.healthcanada.gc.ca/medeffect.
NOTE: Should you require information related to the management of side effects, contact your health professional. The Canada Vigilance Program does not provide medical advice.
NOTE: If signs of poisoning reappear, repeat treatment using one-half the original dose of both sodium nitrite and sodium thiosulfate.
In adult and pediatric patients with known anemia, it is recommended that the dosage of sodium nitrite should be reduced proportionately to the hemoglobin concentration.
Administration
Sodium nitrite injection and sodium thiosulfate pentahydrate injection are administered by slow intravenous injection. They should be given as early as possible after a diagnosis of acute life-threatening cyanide poisoning has been established. Sodium nitrite should be administered first, followed immediately by sodium thiosulfate. Blood pressure must be monitored during infusion in both adults and children. The rate of infusion should be decreased if significant hypotension is noted.
All parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Incompatibility Information
Chemical incompatibility has been reported between sodium thiosulfate pentahydrate injection and hydroxocobalamin and these drugs should not be administered simultaneously through the same IV line. No chemical incompatibility has been reported between sodium thiosulfate and sodium nitrite, when administered sequentially through the same IV line as described in Dosage and Administration.
OVERDOSAGE
There is limited information about the effects of large doses of sodium thiosulfate in humans. Oral administration of 3 g sodium thiosulfate per day for 1-2 weeks in humans resulted in reductions in room air arterial oxygen saturation to as low as 75%, which was due to a rightward shift in the oxygen hemoglobin dissociation curve. The subjects returned to baseline oxygen saturations 1 week after discontinuation of sodium thiosulfate. A single intravenous administration of 20 mL of 10% sodium thiosulfate reportedly did not change oxygen saturations.
| For management of a suspected overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Exposure to a high dose of cyanide can result in death within minutes due to the inhibition of cytochrome oxidase resulting in arrest of cellular respiration. Specifically, cyanide binds rapidly with cytochrome a3, a component of the cytochrome c oxidase complex in mitochondria. Inhibition of cytochrome a3 prevents the cell from using oxygen and forces anaerobic metabolism, resulting in lactate production, cellular hypoxia and metabolic acidosis. In massive acute cyanide poisoning, the mechanism of toxicity may involve other enzyme systems as well.
The synergy resulting from treatment of cyanide poisoning with the combination of sodium nitrite and sodium thiosulfate is the result of differences in their primary mechanisms of action as antidotes for cyanide poisoning.
Sodium Nitrite
Sodium nitrite is thought to exert its therapeutic effect by reacting with hemoglobin to form methemoglobin, an oxidized form of hemoglobin incapable of oxygen transport but with high affinity for cyanide. Cyanide preferentially binds to methemoglobin over cytochrome a3, forming the nontoxic cyanomethemoglobin. Methemoglobin displaces cyanide from cytochrome oxidase, allowing resumption of aerobic metabolism. The chemical reaction is as follows:
NaNO2 + Hemoglobin → Methemoglobin
HCN + Methemoglobin → Cyanomethemoglobin
Vasodilation has also been cited to account for at least part of the therapeutic effect of sodium nitrite. It has been suggested that sodium nitrite-induced methemoglobinemia may be more efficacious against cyanide poisoning than comparable levels of methemoglobinemia induced by other oxidants. Also, sodium nitrite appears to retain some efficacy even when the formation of methemoglobin is inhibited by methylene blue.
Sodium Thiosulfate
The primary route of endogenous cyanide detoxification is by enzymatic transulfuration to thiocyanate (SCN-), which is relatively nontoxic and readily excreted in the urine. Sodium thiosulfate is thought to serve as a sulfur donor in the reaction catalyzed by the enzyme rhodanese, thus enhancing the endogenous detoxification of cyanide in the following chemical reaction:
Rhodanese
Na2S2O3 + CN ---→ SCN+ Na2SO3.
Pharmacodynamics
In dogs, pre-treatment with sodium thiosulfate to achieve a steady state level of 2 μmol/mL increased the rate of conversion of cyanide to thiocyanate over 30-fold.
Pharmacokinetics
Sodium Thiosulfate
Thiosulfate taken orally is not systemically absorbed. Most of the thiosulfate is oxidized to sulfate or is incorporated into endogenous sulphur compounds; a small proportion is excreted through the kidneys. Approximately 20-50% of exogenously administered thiosulfate is eliminated unchanged via the kidneys. After an intravenous injection of 1 g sodium thiosulfate in patients, the reported serum thiosulfate half-life was approximately 20 minutes. However, after an intravenous injection of a substantially higher dose of sodium thiosulfate (150 mg/kg, that is, 9 g for 60 kg body weight) in normal healthy men, the reported elimination half-life was 182 minutes.
Cyanide
The apparent terminal elimination half-life and volume of distribution of cyanide, in a patient treated for an acute cyanide poisoning with sodium nitrite and sodium thiosulfate administration, have been reported to be 19 hours and 0.41 L/kg, respectively. Additionally, an initial elimination half-life of cyanide has been reported to be approximately 1-3 hours.
Thiocyanate
After detoxification, in healthy subjects, thiocyanate is excreted mainly in the urine at a rate inversely proportional to creatinine clearance. In healthy subjects, the elimination half-life and volume of distribution of thiocyanate have been reported to be 2.7 days and 0.25 L/kg, respectively. However, in subjects with renal insufficiency the reported elimination half-life is approximately 9 days.
STORAGE AND STABILITY
Store at room (15⁰C to 30⁰ C) Protect from direct light. Do not freeze.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Seacalphyx (sodium thiosulfate pentahydrate injection BP) 25% is a preservative-free, sterile solution supplied in 100 mL vials.
Each vial of Seacalphyx contains 25 grams sodium thiosulfate pentahydrate, sodium monohydrogen phosphate-dodecahydrate, glycine, sodium hydroxide, sodium chloride, sodium metabisulfite, disodium edentate and water for injection.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Sodium thiosulfate pentahydrate
Chemical Name: Thiosulfuric acid disodium salt, pentahydrate
Molecular Formula and Mass: Na2S2O3· 5H2O 248.17 g/mol
Structural Formula:
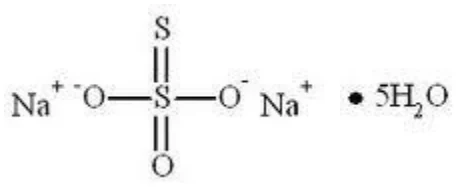
Physiochemical properties: Sodium thiosulfate pentahydrate is odourless and soluble in water. Insoluble in alcohol.