


Product Monograph - ACH-Capecitabine
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 04/2026 |
|---|---|
| 3 SERIOUS WARNING AND PRECAUTIONS BOX | 04/2026 |
| 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Dihydropyrimidine dehydrogenase (DPD) deficiency | 04/2026 |
| 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests | 04/2026 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS .................................................................................................................... 4
1.1 Pediatrics ................................................................................................................................. 5
1.2 Geriatrics ................................................................................................................................. 5
2 CONTRAINDICATIONS ....................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................. 6
4 DOSAGE AND ADMINISTRATION ...................................................................................... 6
4.1 Dosing Considerations ............................................................................................................. 6
4.2 Recommended Dose and Dosage Adjustment ........................................................................ 7
4.5 Missed Dose .......................................................................................................................... 11
5 OVERDOSAGE ................................................................................................................. 11
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................... 11
7 WARNINGS AND PRECAUTIONS ...................................................................................... 12
7.1 Special Populations ............................................................................................................... 18
7.1.1 Pregnant Women .................................................................................................................. 18
7.1.2 Breast-feeding ....................................................................................................................... 18
7.1.3 Pediatrics ............................................................................................................................... 18
7.1.4 Geriatrics ............................................................................................................................... 18
8 ADVERSE REACTIONS ...................................................................................................... 19
8.1 Adverse Reaction Overview .................................................................................................. 19
8.2 Clinical Trial Adverse Reactions ............................................................................................. 19
8.3 Less Common Clinical Trial Adverse Reactions ..................................................................... 20
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data……………………………………………………………………………………………………………………………………………….27
8.5 Post-Market Adverse Reactions ............................................................................................ 31
9 DRUG INTERACTIONS ..................................................................................................... 32
9.4 Drug-Drug Interactions .......................................................................................................... 32
9.5 Drug-Food Interactions ......................................................................................................... 34
10 CLINICAL PHARMACOLOGY ........................................................................................ 34
10.1 Mechanism of Action ............................................................................................................ 34
10.3 Pharmacokinetics .................................................................................................................. 35
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 37
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 37
PART II: SCIENTIFIC INFORMATION ....................................................................................... 39
13 PHARMACEUTICAL INFORMATION ............................................................................. 39
14 CLINICAL TRIALS ......................................................................................................... 40
14.1 Trial Design and Study Demographics ................................................................................... 40
14.2 Study Results ......................................................................................................................... 40
14.3 Comparative Bioavailability Studies ...................................................................................... 47
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 49
17 SUPPORTING PRODUCT MONOGRAPHS ..................................................................... 58
PATIENT MEDICATION INFORMATION ................................................................................... 59
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Caution: ACH-CAPECITABINE (capecitabine) is a potent drug and should be prescribed only by physicians experienced with cancer chemotherapeutic drugs.
ACH-CAPECITABINE (capecitabine) is indicated for:
Colorectal Cancer
Monotherapy
- ACH-CAPECITABINE (capecitabine) is indicated for the adjuvant treatment of patients with stage III (Dukes’ stage C) colon cancer.
- ACH-CAPECITABINE is also indicated for the first-line treatment of patients with metastatic colorectal cancer.
Combination Therapy
ACH-CAPECITABINE in combination with oxaliplatin is indicated for the treatment of metastatic colorectal cancer following failure of irinotecan-containing combination chemotherapy.
In second-line metastatic disease, subgroup analyses for PFS and OS for age suggest that ACH-CAPECITABINE in combination with oxaliplatin may be less effective in patients over the age of 65. Clinical studies suggest an increase in the incidence of adverse events. (See 14 CLINICAL TRIALS and 7 WARNINGS AND PRECAUTIONS).
Breast Cancer
Monotherapy
ACH-CAPECITABINE is also indicated for the treatment of advanced or metastatic breast cancer after failure of standard therapy including a taxane, unless therapy with a taxane is clinically contraindicated.
Combination Therapy
ACH-CAPECITABINE in combination with docetaxel is indicated for the treatment of patients with advanced or metastatic breast cancer after failure of prior anthracycline containing chemotherapy.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of capecitabine in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. (See 14 CLINICAL TRIALS, 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions).
1.2 Geriatrics
Geriatrics (≥ 65 years of age): Based on the population pharmacokinetic analysis which included patients with a wide range of ages (27 to 86 years) and included 234 (46%) patients greater or equal to 65, age has no influence on the pharmacokinetics of 5'-DFUR and 5-FU. However, the elderly may be pharmacodynamically more sensitive to the toxic effects of 5-FU (see 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics and 4 DOSAGE AND ADMINISTRATION).
2 CONTRAINDICATIONS
Capecitabine is contraindicated in patients who are hypersensitive to this drug, or 5-fluorouracil or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Capecitabine is contraindicated in patients who have:
- Severe renal impairment (calculated creatinine clearance below 30 mL/min, or 0.5 mL/s)
- Complete absence of dihydropyrimidine dehydrogenase (DPD) activity. Testing for DPD deficiency should be performed prior to initiating ACH-CAPECITABINE unless immediate treatment is necessary, based on the local availability and current guidelines (see 7 WARNINGS AND PRECAUTIONS, Dihydropyrimidine dehydrogenase (DPD) deficiency and Monitoring and Laboratory Tests).
Due to potentially fatal drug interaction, ACH-CAPECITABINE should not be administered concomitantly with sorivudine1 or its chemically related analogues, such as brivudine.
If contraindications exist to any of the agents in a combination regimen, that agent should not be used.
1 sorivudine and its chemically related analogues, such as brivudine are not authorized for sale in Canada.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
- Acute renal failure secondary to dehydration can be fatal. If Grade 2 (or higher) dehydration occurs, ACH-CAPECITABINE treatment should be immediately interrupted and the dehydration corrected (see 7 WARNINGS AND PRECAUTIONS, Dehydration below).
- Similar to that of other fluorinated pyrimidines sudden death due to cardiotoxicity has been observed with capecitabine (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular below).
- Capecitabine can induce severe skin reactions such as hand-and-foot syndrome, Stevens- Johnson syndrome and Toxic Epidermal Necrolysis. If grade 2 (or higher) event occurs, administration of ACH-CAPECITABINE should be immediately interrupted (see 7 WARNINGS AND PRECAUTIONS, Immune and Skin below).
- Severe toxicity (e.g. stomatitis, diarrhea, mucosal inflammation, neutropenia and neurotoxicity) associated with 5-fluorouracil has been attributed to a deficiency of DPD activity, an enzyme involved in fluorouracil degradation. Fatalities have been reported. Testing for DPD deficiency should be performed prior to initiating ACH-CAPECITABINE unless immediate treatment is necessary, based on the local availability and current guidelines. (see 7 WARNINGS AND PRECAUTIONS, Dihydropyrimidine dehydrogenase (DPD) deficiency below).
- Altered coagulation parameters and/or bleeding have been reported in patients taking capecitabine concomitantly with coumarin-derived anticoagulants such as warfarin. Patients taking coumarin-derivative anticoagulants concomitantly with ACH-CAPECITABINE should be monitored regularly for alterations in their coagulation parameters (PT or INR) and the anticoagulant dose adjusted accordingly (see 7 WARNINGS AND PRECAUTIONS, Hematologic below).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- ACH-CAPECITABINE is intended for long-term administration unless clinically inappropriate.
- ACH-CAPECITABINE tablets should be swallowed whole with water within 30 minutes after a meal.
- ACH-CAPECITABINE tablets should not be crushed or cut (see 8 ADVERSE REACTIONS, 8.5 Post-Market Adverse Reactions).
- If patients cannot swallow ACH-CAPECITABINE tablets whole and tablets must be crushed or cut, this should be done by a professional trained in the safe handling of cytotoxic drugs (see 12 SPECIAL HANDLING INSTRUCTIONS).
4.2 Recommended Dose and Dosage Adjustment
Monotherapy: The recommended dose of ACH-CAPECITABINE (capecitabine) is 1250 mg/m2 administered twice daily (morning and evening; equivalent to 2500 mg/m2 total daily dose) for 14 days followed by a seven day rest period.
For adjuvant treatment of stage III colon cancer, ACH-CAPECITABINE is intended to be given for a total of 8 cycles (or 24 weeks).
Colorectal Cancer, Combination Therapy with Oxaliplatin: In combination with oxaliplatin, the recommended dose of ACH-CAPECITABINE is 1000 mg/m2 twice daily for 2 weeks followed by a 7-day rest period. The first dose of ACH-CAPECITABINE is given on the evening of day 1 and the last dose is given on the morning of day 15. Given as a 3-weekly schedule, oxaliplatin is administered as a 130 mg/m2 intravenous infusion over 2 hours.
Premedication to maintain adequate anti-emesis according to the oxaliplatin Product Monograph should be started prior to oxaliplatin administration for patients receiving the ACH-CAPECITABINE plus oxaliplatin combination.
- Locally advanced and/or Metastatic Breast Cancer, Combination Therapy with Docetaxel: In combination with docetaxel, the recommended starting dose of ACH-CAPECITABINE is 1250 mg/m2 twice daily for 2 weeks followed by a 7-day rest period combined with docetaxel 75 mg/m2 administered as a 1-hour intravenous infusion every 3 weeks (see 14 CLINICAL TRIALS, 14.2 Study Results, Breast Carcinoma). Premedication according to the docetaxel labelling, should be started prior to docetaxel administration for patients receiving the ACH-CAPECITABINE plus docetaxel combination.
Dose calculation
ACH-CAPECITABINE dose is calculated according to body surface area. Tables 1 and 2 show examples of the standard and reduced dose calculations for a ACH-CAPECITABINE starting dose of either 1250 mg/m2 or 1000 mg/m2.
Table 1 Standard and reduced dose calculations according to body surface area for a starting ACH-CAPECITABINE dose of 1250 mg/m2
| Dose level 1250 mg/m2 (twice daily) | |||||||||||
Full dose 1250 mg/m2 | Number of 150 mg tablets and/or 500 mg tablets per administration (each administration to be given morning and evening) | Reduced dose (75%) 950 mg/m2 | Reduced dose (50%) 625 mg/m2 | ||||||||
Body Surface Area (m2) | Dose per administration (mg) | 150 mg | 500 mg | Dose per administration (mg) | Dose per administration (mg) | ||||||
| ≤ 1.26 | 1500 | - | 3 | 1150 | 800 | ||||||
| 1.27 - 1.38 | 1650 | 1 | 3 | 1300 | 800 | ||||||
| 1.39 - 1.52 | 1800 | 2 | 3 | 1450 | 950 | ||||||
| 1.53 - 1.66 | 2000 | - | 4 | 1500 | 1000 | ||||||
| 1.67 - 1.78 | 2150 | 1 | 4 | 1650 | 1000 | ||||||
| 1.79 - 1.92 | 2300 | 2 | 4 | 1800 | 1150 | ||||||
| 1.93 - 2.06 | 2500 | - | 5 | 1950 | 1300 | ||||||
| 2.07 - 2.18 | 2650 | 1 | 5 | 2000 | 1300 | ||||||
| ≥ 2.19 | 2800 | 2 | 5 | 2150 | 1450 | ||||||
Table 2 Standard and reduced dose calculations according to body surface area for a starting ACH-CAPECITABINE dose of 1000 mg/m2
| Dose level 1000 mg/m2 (twice daily) | ||||||||||||
Full dose 1000 mg/m2 | Number of 150 mg tablets and/or 500 mg tablets per administration (each administration to be given morning and evening) | Reduced dose (75%) 750 mg/m2 | Reduced dose (50%) 500 mg/m2 | |||||||||
Body Surface Area (m2 ) | Dose per administration (mg) | 150 mg | 500 mg | Dose per administration (mg) | Dose per administration (mg) | |||||||
| ≤ 1.26 | 1150 | 1 | 2 | 800 | 600 | |||||||
| 1.27 - 1.38 | 1300 | 2 | 2 | 1000 | 600 | |||||||
| 1.39 - 1.52 | 1450 | 3 | 2 | 1100 | 750 | |||||||
| 1.53 - 1.66 | 1600 | 4 | 2 | 1200 | 800 | |||||||
| 1.67 - 1.78 | 1750 | 5 | 2 | 1300 | 800 | |||||||
| 1.79 - 1.92 | 1800 | 2 | 3 | 1400 | 900 | |||||||
| 1.93 - 2.06 | 2000 | - | 4 | 1500 | 1000 | |||||||
| 2.07 - 2.18 | 2150 | 1 | 4 | 1600 | 1050 | |||||||
| ≥ 2.19 | 2300 | 2 | 4 | 1750 | 1100 | |||||||
Dose Modification Guidelines
Patients should be carefully monitored for toxicity. Toxicity due to ACH-CAPECITABINE administration may be managed by symptomatic treatment, dose interruptions and adjustment of ACH-CAPECITABINE dose. Once the dose has been reduced, it should not be increased at a later time.
For those toxicities considered by the treating physician to be unlikely to become serious or life- threatening, treatment can be continued at the same dose without reduction or interruption.
Dose modifications for the use of ACH-CAPECITABINE are shown in Table 3.
Table 3 Recommended Dose Modifications for ACH-CAPECITABINE
| Toxicity NCIC Grade* | During a Course of Therapy | Dose Adjustment for Next Cycle (% of starting dose) |
| Grade 1 | Maintain dose level | Maintain dose level |
| Grade 2 | ||
| -1st appearance | Interrupt until resolved to grade 0-1 | 100% |
| -2nd appearance | Interrupt until resolved to grade 0-1 | 75% |
| -3rd appearance | Interrupt until resolved to grade 0-1 | 50% |
| -4th appearance | Discontinue treatment permanently | |
| Grade 3 | ||
| -1st appearance | Interrupt until resolved to grade 0-1 | 75% |
| -2nd appearance | Interrupt until resolved to grade 0-1 | 50% |
| -3rd appearance | Discontinue treatment permanently | |
| Grade 4 | ||
| -1st appearance | Discontinue permanently or If physician deems it to be in the patient’s best interest to continue, interrupt until resolved to grade 0-1 | 50% |
| -2nd appearance | Discontinue permanently | |
*According to the National Cancer Institute of Canada Clinical Trial Group (NCIC CTG) Common Toxicity Criteria (Version 1 or the Common Terminology Criteria for Adverse Events (CTCAE) of the Cancer Therapy Evaluation Program, US National Cancer Institute, version 3.0. For Hand-and-Foot Syndrome and hyperbilirubinemia (see 7 WARNINGS AND PRECAUTIONS).
Dosage modifications are not recommended for grade 1 events. Therapy with ACH-CAPECITABINE should be interrupted upon the occurrence of a grade 2 or 3 adverse experience. Once the adverse event has resolved or decreased in intensity to grade 1, then ACH-CAPECITABINE therapy may be restarted at full dose or as adjusted according to Table 3 for ACH-CAPECITABINE monotherapy. If a grade 4 event occurs, therapy should be discontinued or interrupted until resolved or decreased to grade 1, and therapy should be restarted at 50% of the original dose. Patients taking ACH-CAPECITABINE should be informed of the need to interrupt treatment immediately if moderate or severe toxicity occurs. Doses of ACH-CAPECITABINE omitted for toxicity are not replaced.
Haematology: Patients with baseline neutrophil counts of <1.5 x 10⁹/L and/or thrombocyte counts of <100 x 109/L should not be treated with ACH-CAPECITABINE. If unscheduled laboratory assessments during a treatment cycle show grade 3 or 4 haematologic toxicity, treatment with ACH-CAPECITABINE should be interrupted.
Combination Therapy: Dose modifications for toxicity when ACH-CAPECITABINE is used in combination with other therapies should be made according to Table 3 above for ACH-CAPECITABINE and according to the appropriate Product Monograph for the other agent(s).
At the beginning of a treatment cycle, if a treatment delay is indicated for either ACH-CAPECITABINE or the other agent(s), then administration of all agents should be delayed until the requirements for restarting all drugs are met.
During a treatment cycle for those toxicities considered by the treating physician not to be related to ACH-CAPECITABINE, ACH-CAPECITABINE should be continued and the dose of the other agent adjusted according to the appropriate Product Monograph.
If the other agent(s) have to be discontinued permanently, ACH-CAPECITABINE treatment can be resumed when the requirements for restarting ACH-CAPECITABINE are met.
This advice is applicable to all indications and to all special populations.
Adjustment of Starting Dose in Special Populations
Hepatic Impairment: In patients with mild to moderate hepatic dysfunction due to liver metastases, no dose adjustment is necessary. Patients with severe hepatic dysfunction have not been studied (see 7 WARNINGS AND PRECAUTIONS).
Renal Impairment: In patients with moderate renal impairment (calculated creatinine clearance 30-50 mL/min [Cockroft and Gault]) at baseline, a dose reduction to 75% from a starting dose of 1250 mg/m2 is recommended based upon pharmacokinetic and safety data (see 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency, and 7 WARNINGS AND PRECAUTIONS). In patients with mild renal impairment (calculated creatinine clearance 51-80 mL/min) no adjustment in starting dose is recommended. In patients with severe renal impairment, ACH-CAPECITABINE should not be administered (see 2 CONTRAINDICATIONS). Careful monitoring and prompt treatment interruption is recommended if the patient develops a grade 2, 3, or 4 adverse event, with subsequent dose adjustment as outlined in the tables above. If the calculated creatinine clearance decreases during treatment to a value below 30 mL/min, ACH-CAPECITABINE should be discontinued. The dose adjustment recommendation for patients with moderate renal impairment applies both to monotherapy and combination use. For dosage calculations, see Table 1.
Geriatrics: No adjustment of the starting dose is needed for ACH-CAPECITABINE. However for ACH-CAPECITABINE monotherapy in the metastatic setting, severe Grade 3 or 4 treatment-related adverse events were more frequent in patients over 80 years of age compared to younger patients. Careful monitoring of elderly patients is advisable.
When ACH-CAPECITABINE was used in combination with other agents, elderly patients (≥ 65 years) experienced more grade 3 and grade 4 adverse drug reactions (ADRs) and ADRs that led to discontinuation, than younger patients. Careful monitoring of elderly patients is advisable.
For treatment with ACH-CAPECITABINE in combination with docetaxel, an increased incidence of Grade 3 or 4 treatment-related adverse events and treatment-related serious adverse events was observed in patients 60 years of age or more.
4.5 Missed Dose
If you forget a dose of ACH-CAPECITABINE do not take the missed dose at all. Take your next dose at the usual time and check with your doctor. Do not take a double dose.
5 OVERDOSAGE
The manifestations of acute overdose include: nausea, vomiting, diarrhea, mucositis, GI irritation and bleeding, and bone marrow depression. Management of overdose should include customary therapeutic and supportive medical interventions aimed at correcting the presenting clinical manifestations and preventing their possible complications.
Administer uridine triacetate within 96 hours for management of ACH-CAPECITABINE overdose. Although no clinical experience using dialysis as a treatment for ACH-CAPECITABINE overdose has been reported, dialysis may be of benefit in reducing circulating concentrations of 5’-DFUR, a low-molecular-weight metabolite of the parent compound.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 4 - Dosage Forms, Strengths, Composition and Packaging
Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Oral | Tablets 150 mg and 500 mg | croscarmellose sodium, ferric oxide red, ferric oxide yellow, hypromellose, lactose anhydrous, magnesium stearate, microcrystalline cellulose, talc, titanium dioxide. |
Composition:
Each ACH-CAPECITABINE 150 mg and 500 mg tablet contains either 150 mg or 500 mg capecitabine, respectively. Non-medicinal ingredients (alphabetical order): croscarmellose sodium, ferric oxide red, ferric oxide yellow, hypromellose, lactose anhydrous, magnesium stearate, microcrystalline cellulose, talc, titanium dioxide.
Packaging:
ACH-CAPECITABINE is available as a film-coated tablet in strengths of either 150 mg or 500 mg.
ACH-CAPECITABINE 150 mg tablets are light peach coloured, oblong shaped, biconvex, film coated tablets, debossed with ‘150’ on one side and plain on other side. ACH-CAPECITABINE 150 mg tablets are available in HDPE bottles containing 60 tablets and blister packs of 60 tablets (carton box containing 6 blisters of 10 tablets each).
ACH-CAPECITABINE 500 mg tablets are peach coloured, oblong shaped, biconvex, film coated tablets, debossed with ‘500’ on one side and plain on other side. ACH-CAPECITABINE 500 mg tablets are available in HDPE bottles containing 120 tablets and blister packs of 120 tablets (carton box containing 12 blisters of 10 tablets each).
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
If toxicity on therapy occurs, ACH-CAPECITABINE should be interrupted until the event resolves, or the severity decreases when the following toxicities occur at a severity of grade 2 or greater: diarrhea, hand-foot syndrome, nausea, hyperbilirubinemia, vomiting or stomatitis (see 4 DOSAGE AND ADMINISTRATION).
Patients and patients’ caregivers should be informed of the expected adverse effects of ACH-CAPECITABINE, particularly of diarrhea, nausea, vomiting, and hand-and-foot syndrome and stomatitis. The frequent oral administration of ACH-CAPECITABINE allows patient specific dose adaptations during therapy (see 4 DOSAGE AND ADMINISTRATION). Most adverse reactions are reversible and do not require discontinuation, although doses may need to be withheld or reduced (see 4 DOSAGE AND ADMINISTRATION). Patients should be taught to recognize and report the common grade 2 toxicities associated with capecitabine treatment (please refer to PATIENT MEDICATION INFORMATION).
If ACH-CAPECITABINE is prescribed in combination with docetaxel, patients and patients’ caregivers should be informed of the expected adverse effects of the combination of ACH-CAPECITABINE and docetaxel (see Table 3).
Diarrhea: Patients experiencing grade 2 diarrhea (an increase of 4 to 6 stools/day or nocturnal stools) or greater should be instructed to stop taking ACH-CAPECITABINE immediately. Standard antidiarrheal agents (e.g. loperamide) should be prescribed for symptom control (see 4 DOSAGE AND ADMINISTRATION).
Nausea: Patients experiencing grade 2 nausea (food intake significantly decreased but able to eat intermittently) or greater should be instructed to stop taking ACH-CAPECITABINE immediately. Standard anti-nausea agents should be prescribed for symptom control (see 4 DOSAGE AND ADMINISTRATION).
Vomiting: Patients experiencing grade 2 vomiting (2 to 5 episodes in a 24-hour period) or greater should be instructed to stop taking ACH-CAPECITABINE immediately. Standard anti-emetic agents should be prescribed for symptom control (see 4 DOSAGE AND ADMINISTRATION).
Hand-and-Foot Syndrome: Patients experiencing grade 2 hand-and-foot syndrome (painful erythema and swelling of the hands and/or feet and/or discomfort affecting the patients’ activities of daily living) or greater should be instructed to stop taking ACH-CAPECITABINE immediately.
Stomatitis: Patients experiencing grade 2 stomatitis or greater (painful erythema, edema or ulcers, but are able to eat) should be instructed to stop taking ACH-CAPECITABINE immediately. Symptomatic treatment should be prescribed (see 4 DOSAGE AND ADMINISTRATION).
Carcinogenesis and Mutagenesis
Although there was no evidence for oncogenic potential of capecitabine in a two-year carcinogenicity study in mice, capecitabine was clastogenic in vitro in human lymphocytes (similar to other nucleoside analogues such as 5-FU). There was also a positive trend in the in vivo mouse micronucleus assay (see 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity Study, and Mutagenicity and Genotoxicity Studies).
Women of childbearing potential should be advised to avoid becoming pregnant while receiving treatment with ACH-CAPECITABINE (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations below) and be provided with appropriate counselling if not currently using contraceptives. Males are advised not to father a child during treatment.
Cardiovascular
The spectrum of cardiotoxicity observed with capecitabine is similar to that of other fluorinated pyrimidines. This includes myocardial infarction, angina, dysrhythmias, cardiac arrest, sudden death, cardiomyopathy, cardiac failure, and electrocardiographic changes. These adverse events may be more common in patients with a prior history of coronary artery disease. A thorough QT interval prolongation assessment study of capecitabine has not been conducted.
Driving and Operating Machinery
Capecitabine has moderate influence on the ability to drive and use machines. Patients should be advised to use caution when driving or using machines if they experience ADRs such as dizziness, fatigue, and or nausea during treatment with ACH-CAPECITABINE.
Endocrine and Metabolism
Dehydration
Dehydration should be prevented or corrected at the onset. Patients with anorexia, asthenia, nausea, vomiting or diarrhea may rapidly become dehydrated. If Grade 2 (or higher) dehydration occurs, ACH-CAPECITABINE treatment should be immediately interrupted and the dehydration corrected.2 Treatment should not be restarted until the patient is rehydrated and any precipitating causes have been corrected or controlled. Dose modifications applied should be applied for the precipitating adverse event as necessary (see 4 DOSAGE AND ADMINISTRATION).
Dehydration may cause acute renal failure, especially in patients with pre-existing compromised renal function or when capecitabine is given concomitantly with known nephrotoxic agents. Fatal outcome of renal failure has been reported in these situations (see 8 ADVERSE REACTIONS).
Dihydropyrimidine dehydrogenase (DPD) deficiency
Patients with certain homozygous or certain compound heterozygous mutations in the DPYD gene locus that cause complete or near complete absence of DPD activity, are at the highest risk for severe, life-threatening or fatal adverse reactions caused by fluorouracil. These patients should not be treated with ACH-CAPECITABINE . No dose has been proven safe for patients with complete absence of DPD activity (see 2 CONTRAINDICATIONS).
Patients with certain heterozygous DPYD variants (eg. DPYD*2A variant) that may cause partial DPD deficiency have been shown to have increased risk of severe toxicity when treated with capecitabine. For patients with partial DPD deficiency where the benefits of capecitabine are considered to outweigh the risks (taking into account the suitability of an alternative non-fluoropyrimidine chemotherapeutic regimen), these patients must be treated with extreme caution, initially with a substantial dose reduction and frequent subsequent monitoring and dose adjustment according to toxicity.
Testing for DPD deficiency should be performed prior to initiating ACH-CAPECITABINE unless immediate treatment is necessary, based on the local availability and current guidelines.
In patients with unrecognised DPD deficiency treated with capecitabine as well as patients who test negative for specific DPYD variations, life-threatening toxicities manifesting as acute overdose may occur. In the event of grade 2-4 acute toxicity, treatment must be discontinued immediately. Permanent discontinuation should be considered based on clinical assessment of the onset, duration and severity of the observed toxicities (see 4 DOSAGE AND ADMINISTRATION).
2 NCIC grade 2 dehydration is defined as IV fluids indicated <24 hours, grade 3 dehydration is defined as IV fluids indicated ≥24 hours, grade 4 dehydration is defined as life-threatening consequences (e.g. hemodynamic collapse), and grade 5 dehydration as death.
Gastrointestinal
Diarrhea
Capecitabine very frequently induces diarrhea, which can sometimes be severe. Patients with severe diarrhea should be carefully monitored and, if they become dehydrated, should be given fluid and electrolyte replacement (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). If grade 2 (or higher) diarrhea occurs, administration of ACH-CAPECITABINE should be immediately interrupted until diarrhea resolves or decreases in intensity to grade 13. Standard antidiarrheal agents (e.g. loperamide) should be initiated, as medically appropriate, as early as possible. Dose reduction should be applied as necessary (see 4 DOSAGE AND ADMINISTRATION). Necrotizing enterocolitis (typhlitis) has been reported.
Hematologic
In 251 patients with metastatic breast cancer who received capecitabine in combination with docetaxel, 68% had grade 3 or 4 neutropenia, 2.8% had grade 3 or 4 thrombocytopenia and 9.6% had grade 3 or 4 anemia.
In 875 patients with either metastatic breast or colorectal cancer who received capecitabine monotherapy, 3.2%, 1.7%, and 2.4% of patients had grade 3/4 neutropenia, thrombocytopenia and decreases in hemoglobin, respectively.
Patients with baseline neutrophil counts of <1.5 x 10⁹/L and/or thrombocyte counts of <100 x 109/L should not be treated with ACH-CAPECITABINE (see 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Haematology).
Altered coagulation parameters and/or bleeding have been reported in patients taking capecitabine concomitantly with coumarin-derived anticoagulants such as warfarin. These events occurred within several days and up to several months after initiating capecitabine therapy, and, in a few cases, within one month after stopping capecitabine. These events occurred in patients with and without liver metastases (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Coumarin Anticoagulants).
Hepatic/Biliary/Pancreatic
Hepatic Insufficiency
Patients with hepatic impairment should be carefully monitored when ACH-CAPECITABINE is administered (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). However, the effect of hepatic impairment not due to liver metastases or of severe hepatic impairment on the disposition of ACH-CAPECITABINE is not known.
3 National Cancer Institute of Canada (NCIC) grade 1 diarrhea is defined as an increase of < 4 stools per day over baseline, mild increase in ostomy output compared to baseline, grade 2 diarrhea is defined as an increase of 4 to 6 stools/day or nocturnal stools, grade 3 diarrhea as an increase of 7 to 9 stools/day or incontinence and malabsorption, grade 4 diarrhea as an increase of 10 stools/day or grossly bloody diarrhea or the need for parenteral support, and grade 5 diarrhea as death.
Hyperbilirubinemia
In 251 patients with metastatic breast cancer who received a combination of capecitabine and docetaxel, grade 3 and 4 hyperbilirubinemia occurred in 6.8% (n=17) and 2% (n=5), respectively.
In 875 patients with either metastatic breast or colorectal cancer treated with capecitabine monotherapy, grade 3 hyperbilirubinemia occurred in 133 (15.2%) and grade 4 hyperbilirubinemia occurred in 34 (3.9%) patients with either metastatic breast or colorectal cancer. If drug related grade 2, 3 or 4 elevations in bilirubin occur, administration of ACH-CAPECITABINE should be immediately interrupted until the hyperbilirubinemia resolves or decreases in intensity to grade 1. Following grade 3 or 4 hyperbilirubinemia, subsequent doses of ACH-CAPECITABINE should be decreased (see 4 DOSAGE AND ADMINISTRATION).
Immune
ACH-CAPECITABINE can induce severe skin reactions such as Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN) (see 8 ADVERSE REACTIONS). Capecitabine should be permanently discontinued in patients who experience a severe skin reaction possibly attributable to capecitabine treatment.
Rarely, unexpected and potentially fatal severe toxicities including neutropenia leading to local and fatal systemic infections following exposure to capecitabine have been observed.
Monitoring and Laboratory Tests
- Testing for DPD deficiency should be performed prior to initiating ACH-CAPECITABINE unless immediate treatment is necessary, based on the local availability and current guidelines. (See 7 WARNINGS AND PRECAUTIONS, Dihydropyrimidine dehydrogenase (DPD) deficiency).
- Patients taking coumarin-derivative anticoagulants concomitantly with ACH-CAPECITABINE should be monitored regularly for alterations in their coagulation parameters (PT or INR) and the anticoagulant dose adjusted accordingly (see 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Coumarin Anticoagulants).
- Careful monitoring of patients ≥60 years of age is advisable (see 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics).
- Patients with severe diarrhea should be monitored for symptoms of dehydration (see 7 WARNINGS AND PRECAUTIONS, Gastrointestinal and Endocrine and Metabolism).
- Patients with hepatic impairment or renal insufficiency should be carefully monitored when ACH-CAPECITABINE is administered (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Hepatic Impairment).
- Patients should be carefully monitored for toxicity (see 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Dose Modification Guidelines).
- Pregnancy testing is recommended for females of reproductive potential prior initiating ACH-CAPECITABINE. (See 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations).
- Patients taking phenytoin concomitantly with ACH-CAPECITABINE should be regularly monitored for increased phenytoin plasma concentrations. (See 9 DRUG INTERACTIONS).
Neurologic
Very rare adverse drug reaction leukoencephalopathy has been identified during post-marketing exposure.
Renal
Renal Insufficiency
Physicians should exercise caution when ACH-CAPECITABINE is administered to patients with impaired renal function. As seen with 5-FU, the incidence of treatment-related grade 3 or 4 adverse events was higher in patients with moderate renal impairment (calculated creatinine clearance 30-50 mL/min).
Reproductive Health: Female and Male Potential
- Fertility: Based on evidence from animal studies, capecitabine may impair fertility in females and males of reproductive potential (see 16 NON-CLINICAL TOXICOLOGY).
- Females: Women of childbearing potential should be advised to avoid becoming pregnant while receiving treatment with capecitabine and be provided with appropriate counselling if not currently using contraceptives. An effective method of contraception should be used during treatment and for 6 months after the last dose of capecitabine. If the patient becomes pregnant while receiving capecitabine, the potential hazard to the fetus must be explained. Pregnancy testing is recommended for females of reproductive potential prior initiating capecitabine. (See 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
- Males: Based on genetic toxicity findings, male patients with female partners of reproductive potential should use effective contraception during treatment and for 3 months following the last dose of capecitabine.
Skin
Hand-and-Foot Syndrome
Hand-and-foot syndrome (palmar-plantar erythrodysesthesia or chemotherapy induced acral erythema) can occur in patients receiving capecitabine either as monotherapy or in combination therapy. Persistent or severe hand-foot syndrome (grade 2 and above) can eventually lead to loss of fingerprints, which could impact patient identification. For patients receiving capecitabine monotherapy in the metastatic setting, median time to onset was 79 days (range from 11 to 360 days) with a severity range of grades 1 to 31. If grade 2 or 3 hand-and-foot syndrome occurs, administration of ACH-CAPECITABINE should be interrupted until the event resolves or decreases in intensity to grade 1. Following grade 3 hand-and-foot syndrome, subsequent doses of capecitabine should be decreased (see 4 DOSAGE AND ADMINISTRATION). For ACH-CAPECITABINE in combination with docetaxel, hand-and-foot syndrome was more common in patients in the combination therapy arm than in the monotherapy arm (63% vs. 8%).
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women using capecitabine. If the drug is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus (see 7 WARNINGS AND PRECAUTIONS, Carcinogenesis and Mutagenesis above). Capecitabine was found to be teratogenic and embryolethal in mice and embryolethal in monkeys (see 16 NON-CLINICAL TOXICOLOGY).
7.1.2 Breast-feeding
No studies have been conducted to assess the impact of capecitabine on milk production or its presence in human breast milk. In a study of single oral administration of capecitabine in lactating mice, it was found that a significant amount of the capecitabine metabolites is transferred to the milk. Because of the potential for serious adverse reactions in nursing infants, it is recommended that nursing be discontinued when receiving capecitabine therapy and for 2 weeks after the final dose.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The safety and effectiveness of capecitabine in persons <18 years of age has not been established.
7.1.4 Geriatrics
Capecitabine in Combination with Docetaxel: An analysis of safety data in patients equal to or greater than 60 years of age showed an increase in the incidence of treatment-related Grade 3 and 4 adverse events, treatment-related serious adverse events and early withdrawals from treatment due to adverse events compared to patients less than 60 years of age. The incidence of grade 3 or 4 stomatitis was greater in the 60 to 70 year old patient group (30%) than the
1 Grade 1 hand-and-foot syndrome is defined by numbness, dysesthesia/paresthesia, tingling, or erythema of the hands and/or feet and/or discomfort which does not disrupt normal activities. Grade 2 hand-and-foot syndrome is defined as painful erythema and swelling of the hands and/or feet that results in discomfort affecting the patient’s activities of daily living and grade 3 hand-and- foot syndrome is defined as moist desquamation, ulceration, blistering or severe pain of the hands and/or feet that results in severe discomfort that causes the patient to be unable to work or perform activities of daily living.
general population (13%) (see 4 DOSAGE AND ADMINISTRATION).
Capecitabine in Combination with Oxaliplatin: In the second-line setting, subgroup analyses for PFS (EP population) and OS (ITT population) for age suggest that XELOX may be less effective than FOLFOX-4 in patients ≥ 65 years of age (HR 1.32, 95% CI, 0.98-1.78 and HR 1.34, 95% CI, 1.00-1.80, respectively). Physicians are advised to assess risks and benefits in these patients.
In the second-line setting, an analysis of safety data in patients equal to or greater than 65 years of age showed an increase in the incidence of treatment related serious adverse events, treatment related Grade 3 and 4 adverse events, gastrointestinal grade 3/4 events (particularly diarrhea), and patients who discontinued trial treatment. In addition, deaths up to 60 days after treatment start and deaths up to 28 days after last dose were slightly higher in older patients (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Capecitabine Monotherapy: Patients ≥80 years old may experience a greater incidence of gastrointestinal grade 3/4 events (see 4 DOSAGE AND ADMINISTRATION).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse drug reactions (ADRs) considered by the investigator to be possibly, probably, or remotely related to the administration of capecitabine have been obtained from clinical studies conducted with capecitabine monotherapy (in adjuvant therapy of colon cancer, in metastatic colorectal cancer and metastatic breast cancer), and clinical studies conducted with capecitabine in combination with docetaxel (metastatic breast cancer) or in combination with oxaliplatin (metastatic colorectal cancer).
8.2 Clinical Trial Adverse Reactions
Colorectal Cancer, Monotherapy
Adjuvant Colon Cancer
Safety data of capecitabine monotherapy were reported from one phase III trial in adjuvant colon cancer (995 patients treated with capecitabine and 974 treated with i.v. 5FU/LV). The most frequently reported treatment related adverse events (≥ 10%) for capecitabine in this trial were gastrointestinal disorders, especially diarrhea, stomatitis, nausea, vomiting, hand-foot syndrome, fatigue and lethargy. The most frequent treatment-related undesirable effects (≥ 5%) reported in this trial are presented in the following table (Table 5).
Table 5 Summary of ADRs Reported in ≥ 5% of Patients with Colon Cancer Treated with Capecitabine Monotherapy or i.v. 5-FU/LV in the Adjuvant Setting
| Adverse Event | Capecitabine 1250 mg/m2/bid (n=995) | i.v. 5-FU/LV* (n= 974) | ||||||||
| Body System/Adverse Event | Total % | Grade 3/4 % | Total % | Grade 3/4 % | ||||||
Gastrointestinal Diarrhea Stomatitis Nausea Vomiting Abdominal pain Constipation Abdominal pain upper Dyspepsia | 46 22 33 14 10 6 6 5 | 11 2 2 2 2 - <1 <1 | 64 60 47 20 13 7 5 4 | 13 14 2 1 1 <1 <1 - | ||||||
Skin and Subcutaneous Hand-foot Syndrome** Alopecia Rash Erythema | 60 6 6 6 | 17 - - 1 | 9 22 8 5 | <1 <1 - <1 | ||||||
General Disorders Fatigue Lethargy Asthenia Pyrexia | 15 10 9 4 | <1 <1 <1 <1 | 15 9 9 6 | 1 <1 1 <1 | ||||||
Nervous System Disorders Dysgeusia Dizziness | 6 5 | - <1 | 9 4 | - - | ||||||
Metabolism and Nutrition Disorders Anorexia | 9 | <1 | 10 | <1 | ||||||
Eye Conjunctivitis | 5 | <1 | 5 | <1 | ||||||
Blood and Lymphatic System Neutropenia | 2 | <1 | 8 | 5 | ||||||
*Mayo Clinic regimen
** Based on the post-marketing experience, persistent or severe palmar-plantar erythrodysaesthesia syndrome (grade 2 and above) can eventually lead to loss of fingerprints (see 7 WARNINGS AND PRECAUTIONS).
8.3 Less Common Clinical Trial Adverse Reactions
Rare or uncommon clinically relevant adverse reactions reported in <5% of metastatic colorectal cancer patients treated with capecitabine in combination with oxaliplatin (second-line), that were considered at least remotely related to treatment are shown below. Occurrences of each grade 3 and 4 adverse event are provided in parentheses.
Gastrointestinal: intestinal obstruction (2%)
Nervous: peripheral motor neuropathy (<1%), encephalopathy (<1%)
Blood & Lymphatic: febrile neutropenia (<1%), pancytopenia (<1%)
Respiratory: pulmonary embolism (<1%), laryngospasm (<1%), bronchospasm (<1%)
Vascular: thrombosis (<1%), deep vein thrombosis (<1%), embolism (<1%)
Psychiatric: anxiety (<1%)
Renal & urinary: renal failure acute (<1%)
Hepatobiliary: hepatic failure (<1%)
Cardiac: myocardial infarction (<1%)
Breast Cancer, Capecitabine Monotherapy
The following data (Table 6) are for the study in stage IV breast cancer patients who received a dose of 2500 mg/m2 administered daily for 2 weeks followed by a 1-week rest period. The mean duration of treatment was 121 days. A total of 71 patients (13%) discontinued treatment because of adverse events/intercurrent illness.
Table 6 Capecitabine Monotherapy: Percent Incidence of Adverse Reactions in ≥5% of Patients Participating in the Phase II Trial in Stage IV Breast Cancer
| Body System/ Adverse Event | NCIC Grade | ||||
| Body System/ Adverse Event | NCIC Grade | ||||
| 1 to 4 | 3 | 4 | |||
| 1 to 4 | 3 | 4 | |||
GI Diarrhea Nausea Vomiting Stomatitis Abdominal pain Constipation Dyspepsia | 57 53 37 24 20 15 8 | 12 4 4 7 4 1 - | 3 - - - - - - | ||
Skin and Subcutaneous Hand-and-Foot Syndrome * Dermatitis Nail disorder | 57 37 7 | 11 1 - | - - - | ||
General Fatigue Pyrexia Pain in limb | 41 12 6 | 8 1 1 | - - - | ||
| Neurological Paraesthesia Headache Dizziness Insomnia | 21 9 8 8 | 1 1 - - | - - - - | ||
Metabolism Anorexia Dehydration | 23 7 | 3 4 | - 1 | ||
Eye Eye irritation | 15 | - | - | ||
Musculoskeletal Myalgia | 9 | - | - | ||
Cardiac Edema | 9 | 1 | - | ||
| Blood | |||||
Neutropenia Thrombocytopenia Anemia Lymphopenia | 26 24 72 94 | 2 3 3 44 | 2 1 1 15 | ||
Hepatobiliary Hyperbilirubinemia | 22 | 9 | 2 | ||
* Based on the post-marketing experience, persistent or severe palmar-plantar erythrodysaesthesia syndrome (grade 2 and above) can eventually lead to loss of fingerprints (see 7 WARNINGS AND PRECAUTIONS).
Locally advanced and/or Metastatic Breast Cancer, Combination with Docetaxel
The following data (Table 7) are for the combination study with capecitabine and docetaxel in patients with locally advanced and/or metastatic breast cancer. In the Capecitabine-Docetaxel combination arm, the treatment was capecitabine administered orally 1250 mg/m2 twice daily as intermittent therapy (2 weeks of treatment followed by one week without treatment) for at least 6 weeks and docetaxel administered as a 1 hour intravenous infusion at a dose of 75 mg/m2 on the first day of each 3 week cycle for at least 6 weeks. In the monotherapy arm, docetaxel was administered as a 1 hour intravenous infusion at a dose of 100 mg/m2 on the first day of each 3 week cycle for at least 6 weeks. The mean duration of treatment was 129 days in the combination arm and 98 days in the monotherapy arm. A total of 66 patients (26%) in the combination arm and 49 (19%) in the monotherapy arm withdrew from the study because of adverse events. The percentage of patients requiring dose reductions due to adverse events were 65% in the combination arm and 36% in the monotherapy arm. The hospitalization rate for treatment-related adverse events was 28.7% in the combination arm and 26.3% in the monotherapy arm.
Table 7 Per Cent Incidence of Adverse Reactions in ≥5% of Patients Participating in the Combination Study of Capecitabine and Docetaxel in Metastatic Breast Cancer
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen)with Docetaxel 75 mg/m2/3 weeks (n=251) | Docetaxel 100 mg/m2/3 weeks (n=255) | ||||||||||||||||
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen)with Docetaxel 75 mg/m2/3 weeks (n=251) | Docetaxel 100 mg/m2/3 weeks (n=255) | ||||||||||||||||
| Adverse Event | Capecitabine 1250 mg/m2/bid (Intermittent Regimen)with Docetaxel 75 mg/m2/3 weeks (n=251) | Docetaxel 100 mg/m2/3 weeks (n=255) | ||||||||||||||||
| Body System/Adverse Event | NCIC Grade | |||||||||||||||||
| Body System/Adverse Event | NCIC Grade | |||||||||||||||||
| Body System/Adverse Event | NCIC Grade | |||||||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||||||||
Total % | Grade 3 % | Grade 4 % | Total % | Grade 3 % | Grade 4 % | |||||||||||||
GI Stomatitis Diarrhea Nausea Vomiting Constipation Abdominal pain Dyspepsia Abdominal Pain Upper Dry mouth | 67 64 43 33 14 14 12 9 5 | 17.1 13.5 6.4 3.6 1.2 2.0 - - 0.4 | 0.4 0.4 - 0.8 - - - - - | 43 45 35 22 12 9 5 6 4 | 4.7 5.4 2.0 0.8 - 0.8 0.4 - - | - 0.4 - - - - - - - | ||||||||||||
Skin and Subcutaneous Hand-and-Foot Syndrome Alopecia Nail disorder Dermatitis Rash erythematous Nail discolouration Onycholysis Pruritis | 63 41 14 8 8 6 5 2 | 24.3 6.0 2.0 - 0.4 - 1.2 - | - - - - - - - - | 8 42 15 9 4 4 5 5 | 1.2 6.7 - 0.8 - 0.4 0.8 - | - - - - - - - - | ||||||||||||
General Pyrexia Asthenia Fatigue Weakness Pain in limb Lethargy Pain | 21 23 21 13 9 6 6 | 0.8 3.2 4.4 1.2 0.4 - - | - 0.4 - - - - - | 29 22 25 9 8 5 2 | 0.4 5.5 5.1 2.0 0.4 1.2 - | - - - - - - - | ||||||||||||
Neurological Dysgeusia Headache Paraesthesia Dizziness* Insomnia Peripheral Neuropathy Hypoaesthesia | 15 7 11 9 4 5 4 | 0.4 0.4 0.4 - - - - | - - - - - - - | 14 8 15 6 5 10 7 | 0.4 - 0.8 0.4 0.4 0.8 0.4 | - - - - - - - | ||||||||||||
Metabolism Anorexia Appetite Decreased Dehydration | 12 10 8 | 0.8 - 2.0 | - - - | 10 4 5 | 0.8 - 0.4 | - - 0.4 | ||||||||||||
Eye Lacrimation increased | 12 | - | - | 5 | - | - | ||||||||||||
Musculoskeletal Arthralgia Myalgia Back pain | 11 14 7 | 1.2 1.6 0.8 | - - - | 18 24 6 | 2.4 2.0 0.8 | - - - | ||||||||||||
Cardiac Edema lower limb Edema NOS Edema peripheral | 14 4 4 | 0.8 - - | - - - | 12 5 5 | 1.2 - 0.4 | - 0.8 - | ||||||||||||
Hematologic Neutropenia Neutropenic fever Anaemia | 17 16 13 | 4.8 2.8 2.8 | 10.8 13.1 0.8 | 16 21 11 | 2.7 4.7 3.9 | 11.8 16.1 - | ||||||||||||
| Respiratory | ||||||||||||||||||
Dyspnea Cough Sore throat Epistaxis | 7 6 11 5 | 0.8 0.4 1.6 0.4 | - - - - | 9 9 7 5 | 0.4 - 0.4 - | - - - - | ||||||||||||
Infections and Infestations Oral Candidiasis | 6 | 0.4 | - | 7 | 0.4 | - | ||||||||||||
- Not observed or applicable.
* Excluding vertigo
Listed below by body system are the adverse events in <5% of patients in the overall clinical trial safety database of 251 patients reported as related to the administration of capecitabine in combination with docetaxel and that were clinically at least remotely relevant. In parentheses is the incidence of grade 3 and 4 occurrences of each adverse event.
Gastrointestinal: hemorrhoids (0.39), ileus (0.39), necrotizing enterocolitis (0.39), esophageal ulcer (0.39), hemorrhagic diarrhea (0.80)
General: rigors (0.39), injection site infection (0.39), neuralgia (0.39)
Neurological: ataxia (0.39), syncope (1.20), taste loss (0.80), polyneuropathy (0.39), migraine (0.39)
Cardiac: supraventricular tachycardia (0.39)
Infection: neutropenic sepsis (2.39), lower respiratory tract infection NOS (0.39), pharyngitis (0.39), otitis media (0.39), sepsis (0.39), bronchopneumonia (0.39)
Blood and Lymphatic: agranulocytosis (0.39), prothrombin decreased (0.39)
Vascular: hypotension (1.20), venous phlebitis & thrombophlebitis (0.39), blood pressure increase (0.39), postural hypotension (0.80)
Renal: renal failure (0.39)
Hepatobiliary: jaundice (0.39), abnormal liver function tests (0.39), hepatic failure (0.39), hepatic coma (0.39), hepatotoxicity (0.39)
Immune System: hypersensitivity (1.20)
Capecitabine Monotherapy Metastatic Breast and Colorectal Cancer
Listed below by body system are the clinical adverse events in <5% of 875 patients (phase III colorectal studies - 596 patients, phase II colorectal study - 34 patients, phase II breast cancer monotherapy studies - 245 patients) reported as related to the administration of capecitabine and that were clinically at least remotely relevant.
In parentheses is the incidence of grade 3 or 4 occurrences of each adverse event.
Gastrointestinal: abdominal distension, esophagitis (0.2), intestinal obstruction (0.3), dysphagia, proctalgia, hemorrhoids, fecal abnormality, tongue disorder, ascites (0.1), gastric ulcer (0.1), gastrointestinal hemorrhage (0.2), ileus (0.3), incisional hernia, rectal disorder, swallowing painful, toxic dilation of intestine, melena, gastroenteritis (0.1) , flatulence, gastritis, duodenitis, colitis
Skin and Subcutaneous: nail disorder (0.1), sweating increased (0.1), face edema, photosensitivity reaction (0.1), urticaria, skin ulcer, genital pruritus, skin lesion, ecchymoses, hyperkeratosis, intertrigo, leg ulcer (excluding varicose), localized skin reaction, red face, rosacea, scab, foot ulcer (0.1), dry skin (<0.01), localized exfoliation, skin hyperpigmentation, skin fissures (< 0.02).
General: shivering, chest pain (0.2), influenza-like illness, hot flushes, palmar erythema, hiccups, pain (0.1), hoarseness, fluid retention, irritability, difficulty in walking, thirst, chest mass, collapse, fibrosis (0.1), hemorrhage, neck edema, sedation, sudden death unexplained (0.1), swelling, ulcer (0.1)
Neurological: insomnia, ataxia (0.5), sedation, syncope (0.1), tremor, dysphasia, encephalopathy (0.1), coordination abnormal, dysarthria, facial palsy, loss of consciousness (0.2), mental impairment, myoclonic jerks, peroneal nerve palsy (0.1), headache (0.5)
Metabolism: weight increase, malnutrition (0.2), appetite increased, food intolerance (0.1), hypertriglyceridemia (0.1), hypokalemia, diabetes control impaired (0.1), hypomagnesemia
Eye: vision abnormal, cataract
Respiratory: cough (0.1), epistaxis (0.1), sore throat, chest tightness, rhinitis, increased sputum production, bronchospasm (0.2), hemoptysis, nasal ulcer, pneumothorax, crackles, orthopnea, pharyngeal disorder, pleural disorder, respiratory distress (0.1), sneezing
Cardiac: tachycardia (0.1), bradycardia, arrhythmia, chest pain (cardiac) (0.2), atrial fibrillation, cardiac failure, cardiomyopathy, extrasystoles, myocardial/infarction (0.1), myocarditis (0.1), pericardial effusion
Infection: herpes simplex, upper respiratory tract infection (0.1), urinary tract infection (0.2), localized infection, sepsis (0.3), bronchitis (0.1), lower respiratory tract infection, cellulitis, fungal infection (0.3), pneumonia (0.1), bronchopneumonia (0.1), herpes zoster, infection (0.1), influenza, keratoconjunctivitis, laryngitis (0.1), superinfection , immune system compromise, and/or disruption of mucous membranes, such as local and fatal systemic infections (including bacterial, viral, fungal etiologies) and sepsis
Musculoskeletal: myalgia, back pain, arthralgia (0.1), bone pain (0.1), neck pain, arthritis (0.1), calcaneal spur, muscle weakness
Blood and Lymphatic: leucopenia (0.2), coagulation disorder (0.1), bone marrow depression (0.1), idiopathic thrombocytopenia purpura (1.0), pancytopenia (0.1)
Vascular: hypotension (0.2), hypertension (0.1), flushing, lymphoedema (0.1), hematoma, pulmonary embolism (0.2), cerebrovascular accident (0.1), transient ischemic attack, varicose veins, venous thrombosis (0.8)
Psychiatric: depression, confusion (0.1), amnesia, libido decreased, loss of confidence, mood alteration, personality change, psychogenic disorder
Renal: dysuria, urinary incontinence, hematuria, hydronephrosis (0.1), nocturia (0.1), urinary tract disorder, urine discolouration, polyuria, renal impairment (0.1), urinary retention
Reproductive System: intermenstrual bleeding, balanoposthitis, vaginal pain, nipple disorder, premenstrual tension syndrome
Ear: vertigo, earache, deafness, sensation of block in ear
Hepatobiliary: jaundice (0.3), hepatomegaly, hepatic pain, fatty liver, bile duct stone (0.1), hepatic fibrosis (0.1), hepatitis (0.1), hepatic cholestatic (0.1)
Injury and Poisoning: radiation recall syndrome (0.1), bruising, overdose, scratch
Surgical: paronychia drainage, postoperative complications, wound drainage increased
Immune System: food allergy, hypersensitivity (0.1)
Endocrine: cushingoid, hypothyroidism, hirsutism
Neoplasms: lipoma, solar keratosis (0.1)
The following table (Table 8) displays laboratory abnormalities observed in 949 patients, regardless of relationship to treatment with capecitabine in metastatic breast and colorectal cancer.
Table 8 Laboratory Abnormalitiesa: Capecitabine Monotherapy in Metastatic Breast and Colorectal Cancer.
| Capecitabine 1250 mg/m2 twice daily intermittent N=949 | ||||||||
| Parametera | Patients with Grade 3 / 4 abnormality (%) | Patients with worsening from baseline of any grade (%) | worsening from baseline by 1 or 2 grades (%) | worsening from baseline by 3 or 4 grades (%) | ||||
| Patients with | Patients with | |||||||
| Decreased hemoglobin | 3.1 | 41.4 | 40.7 | 0.7 | ||||
| Decreased neutrophils | 3.6 | 18.7 | 15.6 | 3.1 | ||||
| Decreased granulocytes | 0.2 | 1.9 | 1.7 | 0.2 | ||||
| Decreased lymphocytes | 44.4 | 58.2 | 53.1 | 5.1 | ||||
| Decreased platelets | 2.0 | 20.4 | 18.8 | 1.6 | ||||
| Increased bilirubin | 17.7 | 36.9 | 21.6 | 15.3 | ||||
| Increased ALAT (SGPT) | 0.5 | 16.7 | 16.3 | 0.4 | ||||
| Increased ASAT (SGOT) | 1.1 | 25.1 | 24.8 | 0.3 | ||||
| Increased serum creatinine | 0.5 | 9.8 | 9.4 | 0.4 | ||||
| Increased alkaline phosphatase | 3.5 | 27.2 | 27.2 | 0.0 | ||||
| Hyperglycemia | 4.4 | 40.1 | 39.2 | 0.9 | ||||
a Laboratory abnormalities were graded according to the categories of the NCIC CTC Grading System
Adverse Events Occurring in Special Patient Populations in Clinical Trials with Capecitabine Monotherapy in the Metastatic Setting
Geriatrics: Among the 21 patients (80 years of age and greater) with either metastatic breast or colorectal cancer who received capecitabine monotherapy (N=875), 6 (28.6%), 3 (14.3%), and 2 (9.5%) patients experienced reversible grade 3/4 diarrhea, nausea and vomiting, respectively. Among the 496 patients aged 60 to 79 years old, the incidence of gastrointestinal toxicity was similar to that in the overall population. Patients 70 to 79 years old (22%) had a higher incidence of hand-and-foot syndrome.
Hyperbilirubinemia: In 875 patients with either metastatic breast or colorectal cancer who received at least one dose of capecitabine 2500 mg/m2 daily for 2 weeks followed by a 1-week rest period, grade 3 hyperbilirubinemia occurred in 133 (15.2%) and grade 4 hyperbilirubinemia occurred in 34 (3.9%) patients. Grade 3/4 hyperbilirubinemia occurred in 22.8% of the 566 patients with hepatic metastases and in 12.3% of the 309 patients without hepatic metastases at baseline. Of the 167 patients with grade 3 or 4 hyperbilirubinemia, 31 (18.6%) also had post- baseline elevations (grades 1 to 4, without elevations at baseline) in alkaline phosphatase and 46 (27.5%) had post-baseline elevations in transaminases at any time (not necessarily concurrent). The majority of these patients, 20 (64.5%) and 33 (71.7%), had liver metastases at baseline. In addition, 96 (57.5%) and 59 (35.3%) of the 167 patients had elevations (grades 1 to 4) at both pre- and post-baseline in alkaline phosphatase or transaminases, respectively. Only 13 (7.8%) and 5 (3.0%) had grade 3 or 4 elevations in alkaline phosphatase or transaminases.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
The following table (Table 9) displays laboratory abnormalities observed in 995 patients, regardless of relationship to treatment, with capecitabine in the adjuvant treatment of colon cancer.
Table 9 Laboratory Abnormalitiesa: Capecitabine Monotherapy in Adjuvant Colon Cancer
| Parameter | Capecitabine 1250 mg/m2 twice daily intermittent N=995 | |||
Patients with Grade 3/4 abnormality (%) | Patients with worsening from baseline of any grade (%) | Patients with worsening from baseline by 1 or 2 grades (%) | Patients with worsening from baseline by 3 or 4 grades (%) | |
| Increased ALAT (SGPT) | 1.6 | 27.2 | 25.9 | 1.3 |
| Increased ASAT (SGOT) | 0.7 | 28.7 | 28 | 0.7 |
| Increased alkaline phosphatase | 0.1 | 26.0 | 25.9 | 0.1 |
| Increased calcium | 1.1 | 5.2 | 4.8 | 0.4 |
| Decreased calcium | 2.3 | 13.2 | 12.4 | 0.8 |
| Decreased granulocytes | 0.3 | 2.0 | 1.7 | 0.3 |
| Decreased hemoglobin | 1.1 | 27.8 | 27.7 | 0.1 |
| Decreased lymphocytes | 13 | 51.3 | 49.2 | 2.1 |
| Decreased neutrophils | 2.2 | 30.3 | 28.4 | 1.9 |
| Decreased neutrophils/granulocytes | 2.4 | 31.0 | 28.9 | 2.1 |
| Decreased platelets | 1.0 | 17.3 | 16.8 | 0.5 |
| Decreased Potassium | 0.3 | 19.9 | 19.7 | 0.2 |
| Increased serum creatinine | 0.1 | 13.8 | 13.8 | 0 |
| Decreased Sodium | 0.4 | 17.5 | 17.1 | 0.4 |
| Increased bilirubin | 20 | 50.3 | 31.7 | 18.6 |
*The incidence of grade 3/4 white blood cell abnormalities was 1.3% in the capecitabine arm and 4.9% in the I.V. 5 -FU/LV arm.
a Laboratory abnormalities were graded according to the categories of the NCIC CTC Grading System.
Metastatic Colorectal Cancer
Presented in the following table (Table 10) are the most frequent adverse reactions (≥5%) with intensity reported as related (remotely, possibly or probably) to the administration of capecitabine (capecitabine) or 5-FU/leucovorin (LV). Rates are rounded to the nearest whole number. The data shown are from pooled phase III metastatic colorectal cancer trials, in which a total of 605 patients with metastatic colorectal cancer were treated with 2500 mg/m2/day of capecitabine administered for 2 weeks followed by a 1-week rest period and 604 patients were administered 5-FU and leucovorin in the Mayo regimen (20 mg/m2 leucovorin I.V. followed by 425 mg/m2 I.V. bolus 5-FU, on days 1 to 5, every 28 days. The adverse event profile of 5-FU/LV in this study was consistent with the published literature. In the pooled colorectal database the median duration of treatment was 139 days for capecitabine treated patients and 140 days for 5-FU/LV treated patients. A total of 78 (13%) and 63 (11%) capecitabine and 5-FU/LV-treated patients, respectively, discontinued treatment because of adverse event/intercurrent illness.
Table 10 Pooled Phase III Metastatic Colorectal Trials of Capecitabine Monotherapy vs. 5- FU/LV: Percent Incidence of Adverse Reactions in ≥5% of Patients
| Adverse Event | Capecitabine (n=596) | 5-FU/LV (n=593) | ||||||||||||
| Body System/ Adverse Event | NCIC Grade | |||||||||||||
| 1 to 4 | 3 | 4 | 1 to 4 | 3 | 4 | |||||||||
GI Diarrhea All Nausea Vomiting Stomatitis All Abdominal Pain Gastrointestinal Motility Disorder Constipation Oral Discomfort | 49 38 23 25 17 10 7 9 | 12 3 3 2 4 - - - | 2 - - - - - - - | 59 47 27 62 16 11 8 9 | 10 2 3 14 2 1 - - | 2 - - 1 - - - - | ||||||||
Skin and Subcutaneous Hand-and-Foot Syndrome** Dermatitis Skin Discoloration Alopecia | 53 24 7 6 | 17 1 - - | - - - - | 6 23 5 21 | 1 1 - - | - - - - | ||||||||
General Fatigue/Weakness Pyrexia | 32 9 | 3 - | - - | 38 12 | 3 1 | - - | ||||||||
Neurological Paresthesia Sensory Disturbance Dizziness* | 9 6 5 | - - - | - - - | 5 11 5 | - - - | - - - | ||||||||
Metabolism Appetite decreased Dehydration | 20 4 | 1 2 | - - | 25 6 | 2 2 | - - | ||||||||
Eye Eye Irritation | 11 | - | - | 8 | - | - | ||||||||
Respiratory Dyspnea | 6 | - | - | 4 | - | - | ||||||||
Cardiac Edema | 5 | - | - | 3 | - | - | ||||||||
Blood and Lymphatic Neutropenia Thrombocytopenia Anemia Lymphopenia | 21 20 80 93 | 0.7 0.5 2 29 | 2 0.5 0.2 8 | 55 28 82 92 | 8 0.2 1 30 | 13 0.2 0.3 8 | ||||||||
Hepatobiliary Hyperbilirubinemia | 49 | 18 | 5 | 25 | 3 | 3 | ||||||||
- Not observed or applicable.
* Excluding vertigo
** Based on the post-marketing experience, persistent or severe palmar-plantar erythrodysaesthesia syndrome (grade 2 and above) can eventually lead to loss of fingerprints (see 7 WARNINGS AND PRECAUTIONS).
In the pooled phase III metastatic colorectal studies, dose reductions occurred in 34% of patients treated with capecitabine and in 42% with 5-FU. Dose reductions also occurred later with capecitabine than 5-FU/LV (median time to dose reduction was 76 and 36 days, respectively).
The hospitalization rate for the treatment-related adverse events was 11.6% for capecitabine treated patients and 18.0% for 5-FU/LV-treated patients. The predominant treatment-related adverse events leading to hospitalization in capecitabine and 5-FU/LV-treated patients, respectively, were diarrhea (4.2% vs. 3.7%), dehydration (2.2% vs. 1.5%), and stomatitis (0.2% vs. 3.7%).
Metastatic Colorectal Cancer, Combination Therapy
Capecitabine in combination with oxaliplatin
The following table (Table 11) shows the most frequent ADRs (≥5%) reported in patients with metastatic colorectal cancer who received second-line (Study NO16967) treatment with capecitabine in combination with oxaliplatin (XELOX). The intensity of adverse events was graded according to the toxicity categories of the NCI CTCAE Grading System Version 3.0.
Table 11 Summary of ADRs in ≥5% of Patients who Received Second-line Treatment with Capecitabine and Oxaliplatin for Metastatic Colorectal Cancer (Study NO16967)
XELOXa (N=311) | FOLFOX-4b (N=308) | |||||||
XELOXa (N=311) | FOLFOX-4b (N=308) | |||||||
| Body system | All | Grade 3/4 | All | Grade 3/4 | ||||
| Body system | All | Grade 3/4 | All | Grade 3/4 | ||||
| Adverse drug reaction | % | % | % | % | ||||
| Adverse drug reaction | % | % | % | % | ||||
Gastrointestinal Disorders Nausea Diarrhea Vomiting Stomatitis Abdominal pain Constipation Dyspepsia Abdominal pain upper | 60 57 43 14 30 16 11 6 | 4 20 3 <1 5 2 <1 <1 | 56 49 34 30 24 26 7 6 | 3 5 3 1 5 3 - <1 | ||||
Nervous system disorders Paraesthesia Neuropathy peripheral Peripheral sensory neuropathy Dysgeusia Neuropathy Dysaesthesia Dizziness Headache Lethargy Hypoaesthesia | 33 13 13 7 12 10 10 10 6 7 | 4 <1 <1 <1 <1 <1 <1 <1 2 <1 | 32 10 16 11 9 11 9 11 6 6 | 3 - 2 - <1 2 - <1 <1 <1 | ||||
General disorders and administration site conditions Fatigue Asthenia Oedema Peripheral Pyrexia | 41 19 5 21 | 7 3 <1 - | 42 18 9 23 | 9 5 <1 <1 | ||||
Temperature intolerance Chills | 5 3 | - - | 6 6 | - - | ||||
Blood and lymphatic system disorders Neutropenia Thrombocytopenia Anaemia | 18 13 6 | 5 3 1 | 48 17 8 | 35 2 2 | ||||
Metabolism and nutrition disorders Anorexia Hypokalemia Dehydration | 32 8 6 | 4 4 3 | 27 5 5 | 2 3 2 | ||||
Skin and subcutaneous tissue disorders Palmar-plantar erythrodysaesthesia syndrome Rash Alopecia | 23 10 1 | 4 - - | 6 7 6 | <1 <1 - | ||||
Respiratory, thoracic and mediastinal disorders Cough Dysaesthesia pharynx Epistaxis Dyspnea Pharyngolaryngeal pain | 7 11 3 9 3 | <1 2 - 1 - | 15 4 7 10 5 | - <1 <1 2 - | ||||
Musculoskeletal and connective tissue disorders Pain in extremity Pain in jaw Pain in back Myalgia | 6 5 10 4 | <1 <1 2 - | 5 4 14 7 | <1 - 3 <1 | ||||
Investigations Weight decreased | 6 | <1 | 6 | <1 | ||||
Psychiatric disorders Insomnia | 7 | <1 | 12 | - | ||||
Infections and Infestations Nasopharyngitis | 4 | - | 6 | <1 | ||||
Vascular Disorders Flushing | 3 | - | 6 | - | ||||
Immune System Disorders Hypersensitivity | 2 | <1 | 6 | 4 | ||||
aXELOX: Capecitabine (1000 mg/m2 twice daily for 2 weeks followed by a 7-day rest period) and oxaliplatin (130 mg/m2 as a 2- hour infusion on day 1 every three weeks).
bFOLFOX-4: leucovorin (200 mg/m2 as a 2-hour infusion on days 1 and 2 every two weeks), 5-FU (400 mg/m2 as a bolus injection, 600 mg/m2 as a 22 hour infusion on days 1 and 2 every two weeks), and oxaliplatin (85 mg/m2 as a 2 hour infusion on day 1 every two weeks).
8.5 Post-Market Adverse Reactions
The following additional adverse events have been identified during post-marketing use of capecitabine. Because these events are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to capecitabine exposure.
Table 12 Adverse Drug Reactions Reported in the Post Marketing Setting
| System Organ Class (SOC) | ADR(s) |
| Gastrointestinal | Serious gastro-intestinal disorders have been reported in patients exposed to capecitabine and include but are not limited to: necrotizing enterocolitis, ileus paralytic, gastrointestinal perforation and intestinal obstruction. |
| Cardiovascular | Thromboembolic events such as deep vein thrombosis, thrombophlebitis and pulmonary embolism have been reported. |
| Hepatobiliary disorders | Hepatic failure, Cholestatic hepatitis. |
| Renal and urinary disorders | Acute renal failure secondary to dehydration including fatal outcome (see 7 WARNINGS AND PRECAUTIONS). |
| Immune | Angioedema, Cutaneous lupus erythematosus, severe skin reactions such as Stevens-Johnson Syndrome (SJS) and Toxic Epidermal Necrolysis (TEN) (see 7 WARNINGS AND PRECAUTIONS). |
| Eye disorders | Lacrimal duct stenosis NOS, Corneal disorders including keratitis. |
| Nervous system disorders | Toxic leukoencephalopathy (see 7 WARNINGS AND PRECAUTIONS). |
Exposure to crushed or cut Capecitabine tablets
In the instance of exposure to crushed or cut Capecitabine tablets, the following ADRs have been reported: eye irritation, eye swelling, skin rash, headache, paresthesia, diarrhea, nausea, gastric irritation, and vomiting.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Sorivudine and analogues25: A clinically significant drug-drug interaction between sorivudine and 5-FU, resulting from the inhibition of dihydropyrimidine dehydrogenase by sorivudine, has been described. This interaction, which leads to increased fluoropyrimidine toxicity, is potentially fatal. Therefore, capecitabine must not be administered concomitantly with sorivudine or its
52 sorivudine and its chemically related analogues, such as brivudine are not authorized for sale in Canada.
chemically related analogues, such as brivudine. There must be at least a 4- week waiting period between end of treatment with sorivudine or its chemically related analogues such as brivudine and start of capecitabine therapy.
Phenytoin and Fosphenytoin: Increased phenytoin plasma concentrations have been reported during concomitant use of capecitabine with phenytoin, suggesting a potential interaction. Formal drug-drug interactions studies with phenytoin have not been conducted, but the mechanism of interaction is presumed to be inhibition of the CYP 2C9 isoenzyme system by capecitabine (see 9 DRUG INTERACTIONS, 9.4 Drug-Drug Interactions, Cytochrome P450 2C9 Substrates below). Patients taking phenytoin or fosphenytoin concomitantly with capecitabine should be regularly monitored for increased phenytoin plasma concentrations and associated clinical symptoms.
Coumarin Anticoagulants: Altered coagulation parameters and/or bleeding have been reported in patients taking capecitabine concomitantly with coumarin-derivative anticoagulants such as warfarin and phenprocoumon. These events occurred within several days and up to several months after initiating capecitabine therapy and, in a few cases, within one month after stopping capecitabine. In a drug interaction study with single-dose warfarin administration, there was a significant increase in the mean AUC (+57%) of S-warfarin. These results suggest an interaction, probably due to an inhibition of the cytochrome P450 2C9 isoenzyme system by capecitabine. In a clinical interaction study, after a single 20 mg dose of warfarin, capecitabine treatment increased the AUC of S-warfarin by 57% with a 91% increase in INR value. Patients taking coumarin- derivative anticoagulants concomitantly with capecitabine should be monitored regularly for alterations in their coagulation parameters (PT or INR) and the anticoagulant dose adjusted accordingly.
Cytochrome P450 2C9 Substrates: No formal drug-drug interaction studies with capecitabine and other drugs known to be metabolized by the cytochrome P450 2C9 isoenzyme have been conducted. Care should be exercised when capecitabine is co-administered with these drugs, which are metabolized by cytochrome P450 2C9 such as for example warfarin or phenytoin. Patients receiving concomitant capecitabine and oral coumarin-derivative anticoagulant therapy should have their anticoagulant response (INR or prothrombin time) monitored closely and the anticoagulant dose adjusted accordingly. Patients taking phenytoin concomitantly with capecitabine should be regularly monitored for increased phenytoin plasma concentrations.
Antacid: The effect of an aluminum hydroxide and magnesium hydroxide-containing antacid (Maalox ®) on the pharmacokinetics of capecitabine was investigated in 12 cancer patients. There was a small increase in plasma concentrations of capecitabine and one metabolite (5’DFCR); there was no effect on the 3 major metabolites (5’DFUR, 5-FU and FBAL).
Leucovorin: A phase I study evaluating the effect of leucovorin on the pharmacokinetics of capecitabine was conducted in 22 cancer patients. Leucovorin has no effect on the pharmacokinetics of capecitabine and its metabolites; however, the toxicity of capecitabine may be enhanced by leucovorin.
Oxaliplatin: No clinically significant differences in exposure to capecitabine or its metabolites, free platinum or total platinum occurred when capecitabine and oxaliplatin were administered in combination.
9.5 Drug-Food Interactions
The effect of food on the pharmacokinetics of capecitabine was investigated in 11 cancer patients. The rate and extent of absorption of capecitabine is decreased when administered with food. The effect on AUC0-∞ of the 3 main metabolites in plasma (5’DFUR, 5-FU, FBAL) is minor. In all clinical trials, patients were instructed to take capecitabine within 30 minutes after a meal. Therefore, since current safety and efficacy data are based upon administration with food, it is recommended ACH-CAPECITABINE be administered with food.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Capecitabine is a tumour- activated antineoplastic agent (antimetabolite) belonging to the novel fluoropyrimidine carbamate class. It was rationally designed as an orally administered precursor of 5'-deoxy-5-fluorouridine (5'-DFUR). Capecitabine is selectively activated to the cytotoxic moiety, 5-fluorouracil (5-FU), by thymidine phosphorylase in tumours.
Within normal and tumour cells, 5-FU is further metabolized to 5-fluoro-2'-deoxyuridine monophosphate (FdUMP) and 5-fluorouridine triphosphate (FUTP) which cause cell injury by both DNA and RNA-derived mechanisms (see 14 CLINICAL TRIALS, 14.3 Comparative Bioavailability Studies, Detailed Pharmacology section for more information).
Bioactivation: Capecitabine is absorbed unchanged from the gastrointestinal tract, metabolized primarily in the liver by the 60kDa carboxylesterase to 5’-Deoxy-5-fluorocytidine (5’-DFCR) which is then converted to 5’-DFUR by cytidine deaminase, principally located in the liver and tumour tissue. Further metabolism of 5’-DFUR to the pharmacologically-active agent 5-FU occurs mainly at the site of the tumour by thymidine phosphorylase (dThdPase), which has levels considerably higher in tumour tissues compared to normal tissues (see the following figure for the metabolic pathway of capecitabine). Healthy liver tissues also contain a relatively high activity of dThdPase. In human cancer xenograft models, capecitabine demonstrated a synergistic effect in combination with docetaxel which may be related to the upregulation of thymidine phosphorylase by docetaxel.
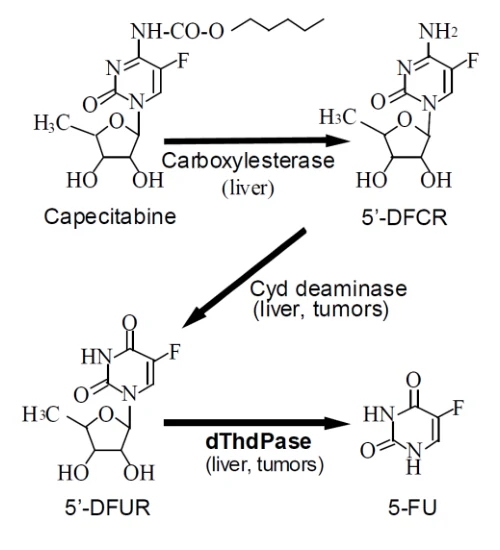
10.3 Pharmacokinetics
Pharmacokinetic Parameters: Table 13 below shows the pharmacokinetic parameters of capecitabine, 5’-DFCR, 5’-DFUR and 5-FU in plasma at steady-state (day 14) following administration of the recommended dose (1255 mg/m2 b.i.d.) in 8 cancer patients. The peak of plasma concentrations of intact drug, 5’-DFCR, 5’-DFUR and 5-FU is reached rapidly and then concentrations decline with a short half-life for all species.
Table 13 Descriptive Statistics on the Pharmacokinetic Parameters Estimated on Day 14 after Administration of Capecitabine (1255 mg/m2) in 8 Cancer Patients
| Parameter | Capecitabine | 5'-DFCR | 5'-DFUR | 5-FU | FUH2 | FBAL |
Cmax (mcg/mL) | 3.99 (56%) | 1.71 (236%) | 9.37 (94%) | 0.709 (87%) | 0.442 (103%) | 5.32 (26%) |
tmax (h) | 1.50 (0.78-2.17) | 2.00 (0.78-4.08) | 2.00 (1.28-4.08) | 2.00 (1.28-4.08) | 2.28 (2.00-4.08) | 3.34 (3.00-5.58) |
AUC0-t (mcg.h/mL) | 7.29 (32%) | 3.97 (175%) | 19.9 (57%) | 1.62 (62%) | 1.20 (153%) | 30.0 (20%) |
AUC0-∞ (mcg.h/mL) | 7.40 (34%) | 5.21 (140%) | 21.7 (63%) | 1.63 (74%) | 2.15 (67%) | 35.2 (27%) |
t1/2 (h) | 0.85 (88%) | 1.11 (80%) | 0.66 (17%) | 0.76 (25%) | 1.14 (26%) | 3.23 (40%) |
Geometric means (CV) are reported for Cmax, AUC0-t and AUC0-∞. Median values (min-max) are reported for tmax. Arithmetic means (CV) are reported for t1/2.
After oral administration, plasma data indicate an extensive and rapid conversion to the first two metabolites in plasma, 5'-DFCR and 5'-DFUR. The peak plasma concentrations for the drug and its two first metabolites occurs shortly (median tmax of 1.50 to 2.0 h) after capecitabine administration. Concentrations then decline exponentially with half-lives of 0.85 h (arithmetic mean), 1.11 h and 0.66 h for intact drug, 5’-DFCR and 5’-DFUR, respectively. Following administration of 1255 mg/m2, a high AUC0-∞ is obtained for 5'-DFUR (geometric mean = 21.7

mcg h/mL, CV = 63%, n = 8). On day 14, the systemic exposure (AUC) to 5-FU is approximately 13 times lower than the systemic exposure to 5’-DFUR.
In plasma, the peak of FBAL concentration occurred approximately 3 h after drug intake. The decline in FBAL concentration is characterized by a half-life of 3.23±1.29 h. Plasma concentrations of FBAL are high (1.6 times those of 5’-DFUR and 22 times those of 5-FU), which probably reflects the extensive formation of 5-FU in the tumour and other tissues.
Absorption, Distribution, Metabolism and Excretion: Capecitabine reached peak blood levels in about 1.5 hours (Tmax) with peak 5-FU blood levels occurring slightly later, at 2 hours. Administration with food decreases the rate of capecitabine absorption but only results in a minor decrease in the AUC’s of 5'-DFUR and 5-FU (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION). Plasma protein binding of capecitabine and its metabolites is low (less than 60%) and is not concentration dependent. Capecitabine was primarily bound to human albumin (approximately 35%). Capecitabine is extensively metabolized to 5-FU. The enzyme dihydropyrimidine dehydrogenase hydrogenates 5-FU, the product of capecitabine metabolism, to the much less toxic, 5-fluoro-5, 6-dihydro-fluorouracil (FUH2). Dihydropyrimidinase cleaves the pyrimidine ring to yield 5-fluoro-ureido-propionic acid (FUPA). Finally, β-ureido-propionase cleaves FUPA to α-fluoro-β-alanine (FBAL) which is cleared in the urine. Over 70% of the administered capecitabine dose is recovered in urine as drug-related material, about 50% of it as FBAL.
Phase I studies evaluating the effect of capecitabine on the pharmacokinetics of either docetaxel or paclitaxel and vice versa showed no effect by capecitabine on the pharmacokinetics of docetaxel or paclitaxel (Cmax and AUC) and no effect by docetaxel or paclitaxel on the pharmacokinetics of 5’-DFUR (the most important metabolite of capecitabine).
Pharmacokinetics in Colorectal Tumours and Adjacent Healthy Tissue: Following oral administration of capecitabine (1255 mg/m2 b.i.d. 5 to 7 days) in patients with colorectal cancer, concentrations of 5-FU were significantly greater in primary tumour than in adjacent healthy tissue (geometric mean ratio 2.5; CI:1.5 to 4.1) and in plasma (geometric mean ratio 14).
Special Populations and Conditions
A population pharmacokinetic analysis was carried out after capecitabine treatment of 505 patients with metastatic colorectal cancer dosed at 2500 mg/m2/day. Gender, race, presence or absence of liver metastasis at baseline, Karnofsky Performance Status, total bilirubin, serum albumin, ASAT and ALAT had no statistically-significant effect on the pharmacokinetics of 5'-DFUR, 5- FU and FBAL.
Geriatrics: Based on the population pharmacokinetic analysis which included patients with a wide range of ages (27 to 86 years) and included 234 (46%) patients greater or equal to 65, age has no influence on the pharmacokinetics of 5'-DFUR and 5-FU. The AUC of FBAL increased with age (20% increase in age results in a 15% increase in the AUC of FBAL). This increase is likely due to a change in renal function (see 10 CLINICAL PHARMACOLOGY, 10.3
- Pharmacokinetics, Renal Insufficiency). However, the elderly may be pharmacodynamically more sensitive to the toxic effects of 5-FU (see 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics and 4 DOSAGE AND ADMINISTRATION).
Sex: Based on population pharmacokinetic analysis including 202 females (40%) and 303 males (60%), gender has no influence on the pharmacokinetics of 5'-DFUR, 5-FU and FBAL.
Ethnic Origin: Based on population pharmacokinetic analysis of 455 white patients (90.1%), 22 black patients (4.4%) and 28 patients of other race or ethnicity (5.5%), the pharmacokinetics of black patients were not different compared to white patients. For the other minority groups the numbers were too small to draw a conclusion.
- Hepatic Insufficiency: Capecitabine has been evaluated in patients with mild to moderate hepatic dysfunction due to liver metastases. Both Cmax and AUC0-∞ of capecitabine, 5’-DFUR and 5-FU were increased by 49%, 33% and 28% and by 48%, 20% and 15%, respectively. Conversely, Cmax and AUC of 5’-DFCR decreased by 29% and 35%, respectively. Therefore, bioactivation of capecitabine is not affected. There are no pharmacokinetic data on patients with severe hepatic impairment (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
Renal Insufficiency: Based on a pharmacokinetic study in cancer patients with mild to severe renal impairment, there is no evidence for an effect of creatinine clearance on the pharmacokinetics of intact drug and 5-FU. Creatinine clearance was found to influence the systemic exposure to 5'-DFUR (35% increase in AUC when creatinine clearance decreases by 50%) and to FBAL (114% increase in AUC when creatinine clearance decreases by 50%). FBAL is a metabolite without antiproliferative activity; 5’-DFUR is the direct precursor of 5-FU.
As seen with 5-FU, the incidence of related grade 3 or 4 adverse events is higher in patients with moderate renal impairment (creatinine clearance 30-50 mL/min) (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
For more detailed information on the pharmacokinetics of capecitabine, please refer to 14 CLINICAL TRIALS, 14.3 Comparative Bioavailability Studies, Detailed Pharmacology.
11 STORAGE, STABILITY AND DISPOSAL
ACH-CAPECITABINE tablets should be stored at 15-30ºC and in the original package.
12 SPECIAL HANDLING INSTRUCTIONS
Disposal of unused/expired medicines
The release of pharmaceuticals in the environment should be minimized. Medicines should not be disposed of via wastewater and disposal through household waste should be avoided. Use established “collection systems”, if available in your location.
Special handling using appropriate equipment and disposal procedures, should be taken as ACH-CAPECITABINE is a cytotoxic drug. Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: capecitabine
Chemical name: 5'-Deoxy-5-fluoro-N-[(pentyloxy)carbonyl]-cytidine
Molecular formula and molecular weight: C15H22FN3O6 ; 359.35 g / mol
Structural formula:
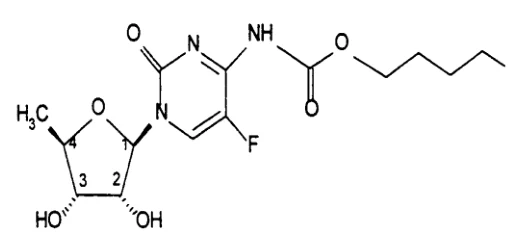
Physicochemical properties:
Physical Form: white to off-white crystalline powder
Solubility: Water 2.6 g/100 mL
pKa: 8.8 (in water and titrated with 0.1 N KOH with bubbling N2)
Partition co-efficient: octanol/buffer: log P =4.4-0.98 (range for pH 5.0-9.5)
Melting Point: 120ºC with decomposition
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
In a phase I study with capecitabine, the maximum-tolerated dose as a single agent in the treatment of patients with solid tumours was 3000 mg/m2 when administered daily for 2 weeks, followed by a 1-week rest period. The dose-limiting toxicities were diarrhea and leucopenia.
14.2 Study Results
Colorectal Carcinoma
Adjuvant Colon Cancer
Data from one open-label, multicenter, randomized, controlled, non-inferiority, phase III clinical trial in patients with stage III (Dukes C) colon cancer supports the use of capecitabine for the adjuvant treatment of patients with stage III colon cancer (X-ACT Study: M66001). In this trial, 1987 patients were randomized to treatment with monotherapy capecitabine (1250 mg/m2 twice daily for 2 weeks followed by a 1-week rest period and given as 3-week cycles for 24 weeks) (N=1004) or 5-FU and leucovorin (Mayo regimen: 20 mg/m2 leucovorin i.v. followed by 425 mg/m2 i.v. bolus 5-FU, on days 1 to 5, every 28 days for 24 weeks) (N=983). Although this trial used bolus 5-FU in the control arm, infusional 5-FU has been shown to be superior to bolus 5- FU.
The primary efficacy endpoint was disease-free survival. The original conditional approval was based on primary analysis at a median follow-up time of 3.8 years which showed. Capecitabine was at least equivalent to i.v. 5-FU/LV in disease-free survival (p=0.0001, non-inferiority margin 1.2) with a trend towards superiority in disease-free survival. The full approval was based on an updated analysis at a median follow-up time of 6.9 years which confirmed capecitabine to be at least equivalent to 5-FU/LV in disease-free survival although there was no longer a trend toward superiority in disease-free survival (p=0.06). A summary of the results is provided in Table 14. Compared with 5-FU/LV, capecitabine was associated with lower incidence of stomatitis, neutropenia and febrile neutropenia but with a considerably higher incidence of hand-and-foot syndrome and hyperbilirubinemia in the adjuvant treatment of patients with Dukes Stage C colon cancer.
Figure 1: Kaplan-Meier Estimates of Disease-free Survival (All Randomized Population)
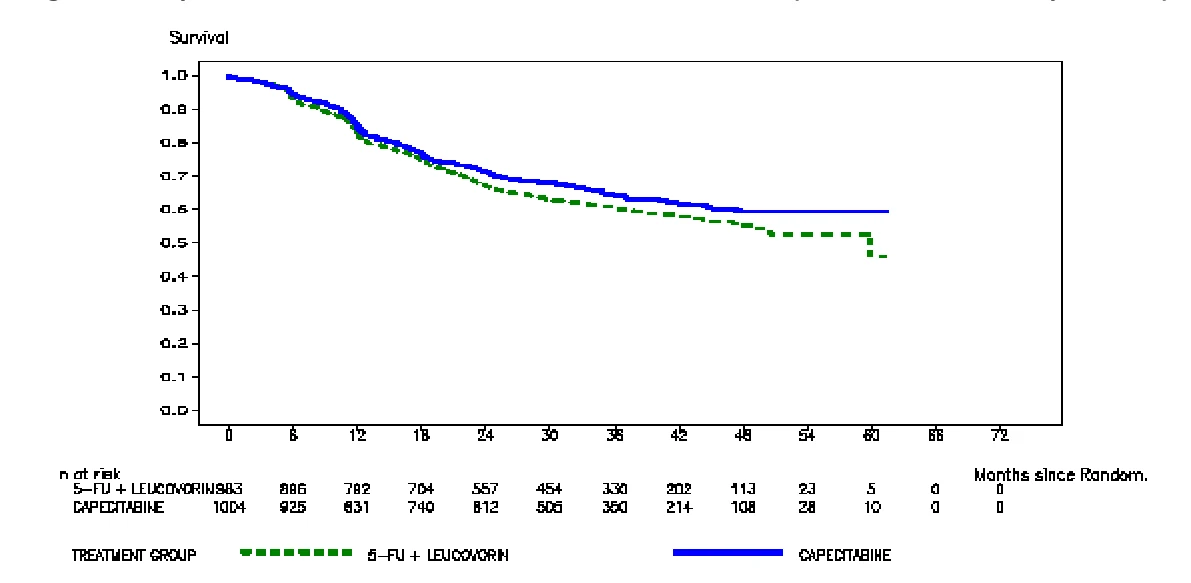
Table 14 Efficacy of Capecitabine vs 5-FU/LV in Adjuvant Treatment of stage III (Dukes Stage C) Colon Cancer
| Design | Drug/Dosage | No. of Patients Enrolled -Demographic Data | Results of Primary Analysis – median follow-up 3.8 years | Results of Updated Analysis –median follow-up 6.9 years |
PIVOTAL PHASE III STUDY (X-ACT Study) randomized, controlled, multicenter patients with stage III (Dukes’ stage C) colon cancer | capecitabine 2500 mg/m2/day for 2 weeks with a 1 week rest period [given as 3 week cycles for a total of 8 cycles (24 weeks)] 5-FU/leucovorin (LV) Mayo regimen - 20 mg/m2 leucovorin I.V. followed by 425 mg/m2 I.V. bolus 5-FU on days 1 to 5, every 28 days [given as 4 week cycles for a total of 6 cycles (24 weeks)] | N=1004 Age (yrs) - Md: 62; range: 25 - 80 M/F: 542(54%)/ 461(46%) ECOG Score: 0 (%) 849 (85) 1 (%) 152 (15) Node Statusa : N1 (%) 695 (69) N2 (%) 305 (30) Other (%) 4 (0.4) N=983 Age (yrs) - Md: 63; range: 22 - 82 M/F: 532(54%)/ 451 (46%) ECOG Score: 0 (%) 830 (85) 1 (%) 147 (15) Node Statusa: N1 (%) 694 (71) N2 (%) 288 (29) Other (%) 1 (0.1) | All Randomized Population: Disease-Free Survival Hazard Ratiob = 0.87 (95% C.I. 0.75-1.00); pc = 0.053 3-year disease-free survival rate capecitabine - 64% 5-FU/LV - 61% Overall Survival Hazard Ratiob = 0.84 (95% C.I. 0.69-1.01; pc = 0.071) 3-year overall survival rate capecitabine - 81% 5-FU/LV - 78% Per Protocol Population: Disease-Free Survival Hazard Ratiob = 0.89 (95% C.I. 0.76-1.04); | All Randomized Population: Disease-Free Survival Hazard Ratiob = 0.88 (95% C.I. 0.77-1.01); pc = 0.068 5-year disease-free survival rate capecitabine – 60.8% 5-FU/LV – 56.7% Overall Survival Hazard Ratiob = 0.86 (95% C.I. 0.69-1.01; pc = 0.060) 5-year overall survival rate capecitabine – 71.4% 5-FU/LV – 68.4% Per Protocol Population: Disease-Free Survival Hazard Ratiob = 0.92 (95% C.I. 0.80-1.06); |
pc = 0.157 3-year disease free survival rate capecitabine - 65% 5-FU/LV - 63% Overall Survival Hazard Ratiob = 0.90 (95% C.I. 0.73-1.10); pc = 0.298 3-year overall survival rate capecitabine – 83% 5-FU/LV – 80% | pc = 0.2743 5-year disease free- survival rate capecitabine – 60.9% 5-FU/LV – 58.4% Overall Survival Hazard Ratiob = 0.93 (95% C.I. 0.73-1.09); pc = 0.357 5-year overall survival rate capecitabine – 72% 5-FU/LV – 70.5% |
aN1- tumor in 1-3 regional lymph nodes; N2- tumor in ≥ 4 regional lymph nodes
b Capecitabine versus 5-FU/LV; Non-inferiority margin of 1.20 corresponds to the retention by capecitabine of approx. 75% of the 5-FU/LV effect on DFS
c Wald chi square test for differences of capecitabine vs 5-FU/LV
Metastatic Colorectal Cancer
Data from two multicenter, randomized, controlled phase III clinical trials involving 603 patients and one randomized phase II trial of 34 patients support the use of capecitabine in the first-line treatment of patients with metastatic colorectal carcinoma (refer to Table 15).
Table 15 Clinical Studies in Metastatic Colorectal Carcinoma - Monotherapy
-Design -Diagnosis | Drug/Dosage | No. of Patients Enrolled -Demographic Data | Results |
-Design -Diagnosis | Drug/Dosage | No. of Patients Enrolled -Demographic Data | Results |
PIVOTAL PHASE III STUDIES Study 1: randomized, controlled, multicenter | -capecitabine 2500 mg/m2/day for 2 weeks with a 1 week rest period (given as 3 week cycles) -5-FU/leucovorin (LV) Mayo regimen* | N=302 Age (yrs) - Md: 64; range: 23 -86 M/F: 181(60%)/ 121(40%) Karnofsky PS- Md: 90%; range: 70 - 100 Colon /Rectum: 222 (74%)/ 79 (26%) Prior radiation therapy: 52 (17%) Prior adjuvant 5-FU: 84 (28%) N=303 Age (yrs) - Md: 63; range: 24 - 87 M/F: 197(65%)/ 106(35%) Karnofsky PS- Md: 90%; range: 70 - 100 Colon /Rectum: 232 (77%)/ 70 (23%) Prior radiation therapy: 62 (21%) Prior adjuvant 5-FU: 110 (36%) | -overall response rate: capecitabine - 21% 5-FU/LV - 11% (p=0.0014) -median time to progression: capecitabine - 128 days 5-FU/LV - 131 days (p=0.90) -median survival: capecitabine - 380 days 5-FU/LV - 407days (p=0.24) |
Study 2: randomized, controlled, multicenter | -capecitabine 2500 mg/m2/day for 2 weeks with a 1 week rest period (given as 3 week cycles) -5-FU/leucovorin (LV) Mayo regimen* | N=301 Age (yrs) - Md: 64; range: 29 - 84 M/F: 172(57%)/ 129(43%) Karnofsky PS- Md: 90%; range: 70 - 100 Colon /Rectum: 199 (66%)/ 101 (34%) Prior radiation therapy: 42 (14%) Prior adjuvant 5-FU: 56 (19%) N=301 Age (yrs) - Md: 64; range: 36 - 86 M/F: 173(57%)/ 128(43%) Karnofsky PS- Md: 90%; range: 70 - 100 Colon /Rectum: 196 (65%)/ 105 (35%) Prior radiation therapy: 42 (14%) Prior adjuvant 5-FU: 41 (14%) | -overall response rate: capecitabine - 21% 5-FU/LV - 14% (p=0.027) -median time to progression: capecitabine - 137 days 5-FU/LV - 131 days (p=0.68) -median survival: capecitabine - 404 days 5-FU/LV - 379 days (p=0.30) |
PHASE II STUDY randomized, open label | -capecitabine 1331 mg/m2/day (continuous) -capecitabine 2510 mg/m2/day (intermittent) -capecitabine 1657 mg/m2/day/ leucovorin 60 mg/day (intermittent) | 39 34 35 Patients with advanced and/or metastatic colorectal carcinoma | -objective response rate: 22% 25% 24% |
*20 mg/m2 leucovorin I.V. followed by 425 mg/m2 I.V. bolus 5-FU on days 1 to 5, every 28 days.
Capecitabine was superior to 5-FU/LV for objective response rate in Study 1 and Study 2. The response rate observed in patients receiving the Mayo regimen was consistent with the published literature. It was also observed that in patients who received prior adjuvant chemotherapy the objective response rate was 15.3% and 14.5% for capecitabine and 5.5% and 4.4% (Study 1 and 2, respectively) for 5-FU/LV. There was no difference in time to disease progression and survival as compared to 5-FU/LV for both studies.
Combination therapy – Second-line treatment of metastatic colorectal cancer
Data from a multicenter, randomized, controlled phase III clinical study (NO16967) support the use of capecitabine in combination with oxaliplatin for the second-line treatment of metastatic colorectal cancer. In this trial, 627 patients with metastatic colorectal carcinoma who have received prior treatment with irinotecan in combination with a fluoropyrimidine regimen as first- line therapy were randomized to treatment with XELOX or FOLFOX-4. For the dosing schedule of capecitabine and FOLFOX-4, refer to Table 16 below.
Table 16 Treatment Regimens in Study NO16967
| Treatment | Starting Dose | Schedule | |||||
| FOLFOX-4 | Oxaliplatin | 85 mg/m2 IV 2 h | Oxaliplatin on Day 1, every 2 weeks | ||||
| Leucovorin | 200 mg/m2 IV 2 h | Leucovorin on Day 1 and 2, every 2 weeks | |||||
| 5-Fluorouracil | 400 mg/m2 IV bolus, 600 mg/ m2 IV 22 h | 5-fluorouracil IV bolus/infusion, each on Days 1 and 2 , every 2 weeks | |||||
| XELOX | Oxaliplatin Capecitabine | 130 mg/m2 IV 2 h 1000 mg/m2 oral bid | Oxaliplatin on Day 1, every 3 weeks Capecitabine oral bid for 2 weeks (followed by 1 week off treatment) | ||||
5-Fluorouracil: IV bolus injection immediately after leucovorin
XELOX is at least equivalent to FOLFOX-4 in terms of progression-free survival in the per protocol population and intent-to-treat population in the investigator assessments. Progression- free survival by the IRC assessment also met the NI margin of 1.23 (HR = 0.93; 95% CI [0.74; 1.17]). Exploratory subgroup analyses for PFS (EP population) and OS (ITT population) for age suggest that XELOX may be less effective than FOLFOX-4 in patients ≥ 65 years of age (HR 1.32, 95% CI, 0.98-1.78 and HR 1.34, 95% CI, 1.00-1.80, respectively).
No quality of life data was collected. The median follow up at the time of the primary analyses in the intent-to-treat population was 2.1 years; data from analyses following an additional 6 months of follow up are also included in the table below.
Table 17 Key Non-Inferiority Efficacy Results for the Primary Analysis and 6-month Follow-up Data (PPP and ITT Populations, Study NO16967)
PRIMARY ANALYSIS PFS by Investigator Assessment* | |||||
| XELOX | FOLFOX-4 | ||||
| Population | # events | Median Time to Event (Days) | # events | Median Time to Event (Days) | HR (97.5% CI) |
| PPP ITT | 244 301 | 154 144 | 247 301 | 168 146 | 1.03 (0.87; 1.24) 0.97 (0.83; 1.14) |
OS ADDITIONAL 6-MONTHS OF FOLLOW UP | |||||
| ITT | 270 | 363 | 270 | 382 | 1.02 (0.86; 1.21) |
*PFS by IRC assessment (PPP) met the NI margin of 1.23 (HR = 0.93; 95% CI [0.74; 1.17])
Breast Carcinoma:
Capecitabine has been evaluated in breast cancer clinical trials in combination with docetaxel and as monotherapy. Table 18 summarizes data from a pivotal combination trial as well as from one pivotal and two supportive monotherapy phase II clinical trials.
Capecitabine in Combination with Docetaxel: The dose of capecitabine used in combination with docetaxel in the phase III clinical trial was based on the results of a phase I study, where a range of doses of docetaxel given every 3 weeks in combination with an intermittent regimen of capecitabine were evaluated. The combination dose regimen was selected based on the tolerability profile of the 75 mg/m2 every 3 weeks of docetaxel in combination with 1250 mg/m2 twice daily for 14 days of capecitabine administered every 3 weeks. The approved dose of 100 mg/m2 of docetaxel administered every 3 weeks was the control arm of the phase III study.
As shown in Table 18, capecitabine in combination with docetaxel resulted in statistically significant improvement in time to disease progression, overall survival and objective response rate compared to monotherapy with docetaxel.
Health Related Quality of Life (HRQoL) was assessed using EORTC QLQ-C30 (version 2) and Breast Cancer Module of the EORTC (BR23). HRQoL was similar in the two treatment groups. Approximately 11% of patients in the combination arm and 10% in the monotherapy arm did not complete a quality of life questionnaire at least once either at baseline or during the treatment phase.
Table 18 Clinical Studies in Breast Carcinoma
-Design -Diagnosis | Drug/Dosage | No. Women Enrolled | Results | |
-Design -Diagnosis | Drug/Dosage | No. Women Enrolled | Results | |
| PIVOTAL STUDY - MONOTHERAPY | ||||
-open label -females with advanced or metastatic breast cancer refractory to previous paclitaxel therapy: (77% resistant, 23% failed paclitaxel; 41% resistant, 26% failed anthracycline therapy; 82% prior 5-FU exposure). | -capecitabine 2510 mg/m2/day for 2 weeks with a 1 week rest period (given as 3 week cycles) | 162 (135 measurable disease) | -overall response rate (ORR) intent- to-treat (n=135): 20% (95% CI:13.6- 27.8); 3 complete responses -ORR (standard population, n=117): 23% (min. 6 weeks therapy) -median duration of response: 241 days -median time to progression: 93 days -median survival: 384 days -clinical benefit response: positive 29 pts. (20%); stable 45 pts. (31%). In 51 pts. with baseline pain ≥20 mm (visual analogue scale), 24 pts. (47%) positive response in pain intensity (≥50% decrease) | |
| SUPPORTIVE STUDIES - MONOTHERAPY | ||||
-open label, randomized, parallel group -females ≥55 with advanced or metastatic breast cancer without previous chemotherapy (other than adjuvant treatment) | -capecitabine 2510 mg/m2/day for 2 weeks with a 1 week rest period (given as 3 week cycles) -Cytoxan, methotrexate, 5FU (CMF) 600/40/600 mg/m2 iv q3 weeks. | 95 | -capecitabine response rate: 25% (95%CI: 14%-37%) -CMF response rate: 16% (95% CI: 5%-33%) -median time to disease progression: capecitabine-132 days; CMF-94 days | |
-open-label, randomized parallel group -females with disease progression within 12 months of previous anthracycline treatment | -capecitabine 1331 mg/m2/day (continuous) for 6 weeks -capecitabine 2510 mg/m2/day for 2 weeks with a 1 week rest period (given as 3 week cycles) (intermittent) -paclitaxel 175 mg/m2/q 3weeks | 44 | -capecitabine response rate (intermittent arm): 36% (95%CI: 17- 59%); 3 complete responses -paclitaxel response rate: 21% (95% CI: 6-46%). -median time to disease progression: capecitabine 92 days; paclitaxel 95 days. | |
| PIVOTAL STUDY – COMBINATION THERAPY | ||||
-open label, randomized, parallel group -females with advanced and/or metastatic breast cancer resistant to or recurring during or after anthracycline-containing therapy or relapsing during or recurring within 2 years of completing anthracycline- containing adjuvant therapy | -capecitabine 2500 mg/m2/day for 2 weeks with a 1 week rest period in combination with docetaxel 75 mg/m2 every 3 weeks -docetaxel 100 mg/m2 every 3 weeks | 255 256 | Response Rate Combination therapy: 41.6% Docetaxel monotherapy: 29.7% (p=0.0058) Time to Disease Progression Combination therapy: 186 days Docetaxel monotherapy: 128 days (p=0.0001) Hazard Ratio: 0.643 Overall Survival Combination therapy: 442 days Docetaxel monotherapy: 352 days (p= 0.0126) Hazard Ratio: 0.775 | |
14.3 Comparative Bioavailability Studies
Summary of studies establishing bioequivalence of ACH-CAPECITABINE 500 mg tablets to Xeloda® (Capecitabine) Tablets 500 mg (Reference Listed Drug)
Statistical summary of the comparative Bioavailability data:
A multicentre, randomized, double blind, two-period, two-treatment, two-way crossover, bioequivalence study of ACH-CAPECITABINE 500 mg tablets (Accord Healthcare Inc.) and Xeloda® (capecitabine) tablets 500 mg (Hoffmann-La Roche Limited, Canada) was conducted in 43 male and female patients with metastatic breast cancer or colorectal cancer. The dose of the study medication was scaled to the body surface area of the study subjects (1250 mg/m2), and was administered as single doses of 3 x 500 mg or 4 x 500 mg tablets, under fed conditions.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Capecitabine (3 x 500 mg or 4 x 500 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90 % Confidence Interval |
AUCT ( ng.h / mL) | 7799.93 8217.56 (34.8) | 8025.27 8507.35 (38.6) | 97.1 | 93.07-101.25% |
AUCI (ng.h / mL) | 7848.97 8267.56 (34.7) | 8056.97 8550.08 (38.9) | 97.4 | 93.35-101.52% |
| Cmax (ng / mL) | 4998.75 5460.60 (45.7) | 5453.35 6324.09 (59.1) | 92.3 | 81.18-105.06% |
| Tmax§ (h) | 2.000 (0.500-5.000) | 1.667 (0.500-5.000) | ||
| T½# (h) | 0.571(35.2%) | 0.591(35.4%) | ||
* ACH-CAPECITABINE 500 mg tablets-manufactured by Intas Pharmaceuticals Ltd., India for Accord Healthcare Inc., Canada.
† Xeloda® (Capecitabine) Tablets 500 mg - Distributed by Hoffmann-La Roche Limited, Canada, were purchased in Canada.
§ Expressed as the median (range) only
# Expressed as the arithmetic mean (CV%) only
Detailed Pharmacology
Animal Pharmacology:
Capecitabine administration of doses up to 300 mg/kg (p.o.) in mice and rats and up to 30 mg/kg (i.v.) in anesthetized dogs, produced no biologically significant pharmacodynamic effects on the mammalian nervous, cardiovascular, respiratory, and gastrointestinal systems. At the highest doses [1,000 mg/kg (p.o.) in mice and rats and 100 mg/kg (i.v.) in dogs], capecitabine caused minimal changes in some of the above parameters. In anaesthetized cynomolgus monkeys, capecitabine infused i.v. at 10 and 30 mg/kg did not affect the parameters relating to cardiovascular and respiratory function. At 100 mg/kg (i.v.), it caused slight and transient hypotension and suppressed cardiac function. These effects were not considered critical.
Metabolic Conversion of Capecitabine in Animals: The cynomolgus monkey is the most predictive model of the toxicity that may occur in humans as the activity and distribution of the metabolizing enzymes carboxylesterase and cytidine deaminase are similar in this species to those seen in humans. In the mouse, as in humans and monkeys, conversion of the parent drug occurs via 5'-DFCR to 5'-DFUR. However, the efficiency of this conversion is less than that of the monkey. In contrast to monkey and mouse, the rat has minimal cytidine deaminase activity in major organs. Therefore, in the latter species, capecitabine is metabolized to 5'-DFCR; however, its subsequent conversion to 5'-DFUR is poor. The low activity of cytidine deaminase in the rat, which results in high plasma levels of 5'-DFCR relative to monkey and man, allowed the toxicity of 5'-DFCR to be investigated. For these reasons, the teratology and reproductive toxicity studies were conducted in the mouse and the monkey.
Mechanism of Action: 5-FU is further metabolized to 5-fluoro-2'-deoxyuridine monophosphate (FdUMP) and 5-fluorouridine triphosphate (FUTP) and causes cell injury by two primary mechanisms. First, FdUMP binds covalently to thymidylate synthase (TS) and prevents formation of thymidylate, the precursor of thymidine triphosphate that is required for DNA synthesis, thereby inhibiting cell proliferation. The second mechanism results from the incorporation of FUTP into RNA in place of UTP, thereby preventing the correct nuclear processing of ribosomal RNA and messenger RNA. These effects are most marked on rapidly proliferating cells, such as tumour cells, which utilize 5-FU at a higher rate.
Clinical Pharmacokinetics:
The pharmacokinetics of capecitabine and its metabolites have been evaluated in 11 studies in a total of 213 cancer patients at a dosage range of 502 to 3514 mg/m2/day. The parameters of capecitabine, 5’DFCR and 5’DFUR measured on days 1 and 14 were similar. AUC of 5-FU was 30% higher on day 14, but did not increase subsequently (day 22). At therapeutic doses, the pharmacokinetics of capecitabine and its metabolites were dose proportional, except for 5-FU. The elimination half-life of both capecitabine and 5-FU were about 45 minutes.
Absorption: The gastrointestinal absorption of capecitabine and its metabolites (5’-DFCR, 5’- DFUR and 5-FU) was rapid (median 2 hours; range 0.5 to 5 hours). Capecitabine is extensively absorbed since at least 70% of the dose was recovered in urine with low variability (CV of 30%).
Distribution: Binding of 14C-capecitabine, 14C-5’-DFCR and 3H-5’-DFUR to human plasma proteins were determined in vitro by ultrafiltration. The concentration ranges used (0.2/0.5 to 200/500 mcgmL) encompassed the concentrations observed in plasma species in vivo. Plasma protein binding of capecitabine is low (54%, 10% and 60% for capecitabine, 5’-DFCR and 5’- DFUR, respectively) and is not concentration-dependent. Capecitabine was primarily bound to human albumin (approximately 35%).
Excretion: In three studies, concentrations of capecitabine and its metabolites (5’-DFCR, 5’- DFUR, 5-FU, FUH2, FUPA and FBAL) were measured in urine. Over 70% of the capecitabine dose was recovered in urine as drug-related material. The majority of the dose was recovered as FBAL (approximately 50%).
16 NON-CLINICAL TOXICOLOGY
The tables presented on the following pages provide the findings of the main toxicology, mutagenicity/genotoxicity and reproduction/teratology studies performed with capecitabine:
Acute Toxicity:
| Title | Species/ Strain | No./Sex / Dose | Dose (mg/kg) | Duration of Observations/ Route of Administration | Maximum Non-Lethal Dose | Target Organs/Systems of Toxicity |
| Mouse Acute Study | Mouse / BDF1 | 5 | 250, 375, 500 | 14 days Intravenous | > 250 - < 375 mg/kg for males > 375 - < 500 mg/kg for females | High-Dose: 3 males and 2 females died. Transient ↓ spontaneous motor activity immediately after to 1 hour after dosing. Mid-Dose: One male died. Transient ↓ spontaneous motor activity immediately after to 1 hour after dosing. Low-Dose: No adverse effects observed. |
| Mouse Acute Study | Mouse / BDF1 | 5 | 1000, 2000 | 14 days Oral (gavage) | > 2000 mg/kg (limit dose) | Low & High Doses: Transient ↓ spontaneous motor activity from 15 minutes after dosing to 1 hour at 1000 mg/kg and 2-4 hours at 2000 mg/kg (↓ respiratory rate & prostration at high dose only). Transient ↓ food consumption, males, on day of dosing. |
| Rat Acute Study | Rat / (SD-Slc) | 5 | 1000, 2000 | 14 days Oral (gavage) | > 2000 mg/kg (limit dose) | Low Dose: ↓ spontaneous motor activity and muscle relaxation (1 female) from 15-30 minutes after dosing. High Dose: ↓ spontaneous motor activity, muscle relaxation, and immobility in males and females, and slight salivation in 1 female from 15 minutes-4 hours after dosing |
| Monkey Pyramiding Study | Monkeys / Cynomolgus | 2 males only | 500, 1000, 20001 | 14 days after final dosing Oral (naso-gastric) | > 2000 mg/kg (limit dose) | Low Dose: Emesis within 15 minutes of dosing; loose feces/diarrhea in 1 monkey the day after dosing. Mid-Dose: Emesis 1.5 or 6 hours post-dosing; loose feces/diarrhea in 1 monkey 6 hours after dosing. High Dose: Emesis within 15 minutes of dosing; salivation immediately after dosing; loose feces/diarrhea for approximately 1 week after dosing. |
1 500 mg/kg (day 1), 1000 mg/kg (day 4), 2000 mg/kg (day 7)
Subchronic and Chronic (Long-Term) Toxicology Studies:
| Title | Species/ Strain | No./ Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
| 4-Week Mouse Study | Mouse / BDF1 | 6 | 0 198 395 791 | 4 weeks Oral (gavage) | Mid & High Doses: Slight anemia,↑BUN (slight); ↑spleen weight (slight); enlarged nuclei and degenerated crypt cells in small intestine, ↑extramedullary hematopoiesis in spleen High Dose: ↓BMC (slight); ↓thymus weight (slight); slight atrophic changes in thymus and spleen, degeneration of hematopoietic cells in bone marrow |
| 13-Week Mouse Study | Mouse / BDF1 | 1511 | 0 198 395 791/5932 | 13 Weeks + 4 weeks Recovery Oral (gavage) | Mid & High Dose: ↓RBC, ↑MCV, MCH, PLT; ↑spleen weight, ↓ovary weight; splenic extramedullary hematopoiesis, increased ratio of neutrophil myelocytes & degenerated erythroblasts in bone marrow, changes in female reproductive organs, regressive change of gastrointestinal tract High Dose: Mortality (11/30); ↓body weight, food intake; emaciation, ↓spontaneous motor activity, loose feces; ↓HCT, Hb, BMC; ↓testis & epididymis weights; atrophy of lymph node nodules and of thymus, ↓erythroblasts in bone marrow, changes in male reproductive organs. Found dead & moribund sacrificed mice also showed hyposthenia, hypothermia, bradypnea, or convulsion; ↓WBC, ↑reticulocytes; ↓thymus & uterus weights, ↑relative adrenal weight; atrophy of epidermis/sebaceous glands/hair follicles in skin. Recovery High Dose: ↑PLT, reticulocyte, BMC; enlarged spleen with increased weight; extramedullary hematopoiesis in spleen, ↑neutrophil myelocytes in bone marrow |
4-Week Rat Study | Rat / (SD-Slc) | 5 | 0 179.5 359 538.5 | 4 Weeks Oral (gavage) | High Dose: Slight ↓body weight gain and food intake (males); slight degeneration of rectal crypt cells |
26-Week Rat Study | Rat / (SD-Slc) | 20 | 0 179.5 359 538.5 | 26 Weeks Oral (gavage) | High and Mid Doses: ↓Body weight gain and food intake (males); ↑MCH, MCV (very slight), ↓serum total protein (very slight/males); proteinuria High Dose: (males only) ↓RBC (very slight); ↓urine volume and ↑specific gravity (slight); slight histopathologic changes in rectum (degenerated crypt cells, dilatation of glandular lumina, enlarged nuclei of crypt cells or epithelium) |
1 10 for 13 week dosing, 5 for recovery.
2 The high dose was changed from 791 mg/kg/day to 593 mg/kg/day on day 37.
| Title | Species/ Strain | No./ Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Adminis- tration | Target Organs / Systems of Toxicity |
| 4-Week Monkey Study & Toxico- kinetics | Monkey/ Cynomolgus (Macaca fascicularis) | 3 (High dose: males only) | 0 35.9 179.5 359 | 4 Weeks Oral (gavage) | Mid Dose: Decrease in duodenal and ileal mucosal folds Mid & High Doses: Loose feces, diarrhea; ↓body weight & food intake; ↓WBC, BMC; ↓thymus weight; gastrointestinal changes (dilated glandular lumina, enlarged nuclei of epithelial cells and crypt cells, atrophic glands), atrophic acinar cells in pancreas, atrophic lymph follicles in lymph nodes, spleen and tonsils, atrophic thymus, hypoplasia of hematopoietic cells in bone marrow, atrophy of acinar cells in salivary glands High Dose: Mortality - 2 males sacrificed moribund; emesis; in addition, 2 males sacrificed moribund showed ↓spontaneous motor activity, emaciation, hypothermia, lying on the side, staggering gait; atrophic mucosa and glands, enlarged glandular lumina, enlarged nuclei of mucosal epithelial cells and crypt cells in stomach and small intestine, atrophy of mucosal epithelium of tongue and esophagus, degeneration and hypertrophy of cortical cells, and hemorrhage in cortex of adrenals |
13-week Monkey Study & Toxico- kinetics | Monkey / Cynomolgus (Macaca fascicularis) | 4 | 0 54 108 215/1621 | 13 Weeks + 4 Weeks Recovery Oral (gavage) | Mid & High Doses: Loose feces; ↓RBC, WBC, HCT, Hb; small thymus and spleen, atrophied splenic nodules, decrease of lymphocyte in thymic cortex. High Dose: Mortality - 1 male died, 1 female sacrificed moribund; ↓food intake; ↓thymus & spleen weights; atrophied lymph nodules in tonsil. In addition, monkeys that died or were sacrificed moribund showed poor appetite, diarrhea, staggering gait, emesis, lying on the belly, ↓spontaneous motor activity, emaciation, hypothermia, pale oral mucosa; ↓body weight; ↓BMC, ↑platelet; enlarged adrenal & ↑weight; ↓adipose tissue, atrophy of thymus, regressive degeneration of gastrointestinal tract, lymphatic, & hematopoietic organs. No findings after recovery period. |
1Days 0-31:215 mg/kg/day; days 32-34: cessation of administration; days 35-90: 162 mg/kg/day
| Title | Species/ Strain | No./ Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
| 26-Week Monkey Study | Monkey / Cynomolgus (Macaca fascicularis) | 3 | 0 18 54 144 | 26 Weeks Oral (gavage) | High Dose: Mortality (1 female sacrificed moribund); loose feces; ↓WBC (segmented neutrophils, lymphocytes), RBC, HCT and Hb; atrophy of thymus & lymphoid follicle of spleen. In addition, female monkey sacrificed moribund showed diarrhea, ↓spontaneous motor activity, loss of appetite, pale oral mucosa, emaciation, prone position, hypothermia, bradypnea; ↓body weight & food intake; ↓BMC, ↑relative lymphocytes, ↓total cholesterol, glucose, Ca, Na, K, Cl, ↑creatinine, BUN, α-1 globulin; enlarged adrenals, small thymus, liquid feces in large intestine, no contents in stomach or small intestine; ↓absolute weights of heart, liver, kidney, thymus, ↑relative weights of brain, lung, adrenals; histopathologic changes in digestive system (degeneration or hyperplasia of mucosal epithelium, hyperplasia of muscularis mucosa, fibroplasia of submucosa, blunting and fusing of villi); atrophy of lymphoid follicles of spleen; atrophic thymus; lymphocyte depletion of mesenteric lymph node; decreased cellularity of bone marrow; hypoplasia of squamous epithelium in skin, mammary gland, tongue, esophagus, vagina; atrophy of hair follicle of skin; degranulation of acinar cell in pancreas (islet cells of the pancreas were unaffected). |
52-Week Monkey Study & Toxico- kinetics | Monkey / Cynomolgus (Macaca fascicularis) | 4 | 0 36 72 108 | 52 weeks Oral (gavage) | All treated groups: Dose-related increase of post-dosing salivation, slight ↓WBC, dosage-related ↑myeloid left shift. High Dose: Regurgitation, ↓relative thymus weight (marginal) with ↓lymphocytes in thymic cortex and proliferated hematopoietic cells in bone marrow. |
Carcinogenicity Study:
| Title | Species/ Strain | No./ Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
| 24-Month Mouse Carcinogenicity Study | Mouse / BDF1 | 50/ sex/ group | 0 - Control -1 0 - Control - 2 30, 60, 90 | 24-Month Oral (dietary admixture) | Low Dose: ↑ MCV, MCH (females only) Mid Dose: ↑ MCV, MCH, ↓ RBC, ↓ testes weights High Dose: ↓RBC, Hb, HCT, ↑ MCV, MCH, platelets ↓ Thymus and testes weight (males only) There was no evidence of an oncogenic potential |
Mutagenicity and Genotoxicity Studies:
| Title | Assay System | Concentration of Capecitabine Assayed | Duration of Exposure | Genotoxic and Other Findings |
| Bacterial Cell Gene Mutation (Exploratory) | Ames Test: standard plate incorporation method using strains TA98 & TA100 of Salmonella typhimurium with & without metabolic activation (S9 mix) (S9 mix) | 4 to 1000 mcg/plate | 48 hrs | No mutagenic activity observed with or without metabolic activation. |
| Gene mutation test in Cultured Mammalian Cells | Chinese hamster lung cells V79/HPRT with and without metabolic activation | 100 to 4000 mcg/mL (without metabolic activation) 100 to 5000 mcg/mL (with metabolic activation) | 16 hrs (without metabolic activation) 5 hrs (with metabolic activation) | No mutagenic activity observed with or without metabolic activation. Cytotoxicity Relative cell viability: 42-51% at 4000 mcg/mL without metabolic activation 50-92% at 5000 mcg/mL with metabolic activation |
Chromosome Aberration (in vitro) | Human peripheral blood lymphocytes with and without metabolic activation | 50 to 500 mcg/mL (without metabolic activation) 250 to 3600 mcg/mL (with metabolic activation) | 24 & 48 hrs (without metabolic activation) 3 hrs (with metabolic activation) | Without metabolic activation: Clastogenic and cytotoxic at doses of 250 & 500 mcg/mL. With metabolic activation: Not clastogenic or cytotoxic. |
Chromosome Aberration (in vivo) | Mouse micronucleus test Strain: Füllinsdorf Moro Albino | Oral Dose (mg/kg) 500 1000 2000 | Post-dose 24 hrs 24 hrs 24 & 48 hrs | The frequency of micronucleated polychromatic erythrocytes was not statistically significantly increased at any of the sampling times. No signs of toxicity in bone marrow cells. |
Reproduction and Teratology Studies:
| Title | Species/ Strain | No./Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
| Mouse Fertility Study | Mouse / BDF1 | 24 | 0 190 380 760 | Males: 28 days before, through confirmation of fertility Females: 14 days before, through mating & until day 6 of gestation Oral (gavage) Recovery: following cessation of treatment, high-dose females that had unsuccessfully mated were re-mated with control or high- dose males. | Parental mice: No drug-related deaths. High Dose: ↓body weight gain & food intake, emaciation, slight ↓ spontaneous motor activity; ↓mating index (due to disturbed estrous cycle) & female fertility index; ↓testes & epididymes weights, degeneration & decrease of spermatocytes & spermatids in testes, ↑ degenerative spermatogenic cells in epididymes in males; no live fetuses, ↑resorptions (early deaths). Mid Dose: ↓live fetuses, ↑resorptions (early deaths). Fetus: Slight ↓female fetal body weights, slight ↑fetuses with external anomalies. Recovery: Adverse effects reversed. No adverse effects on reproductive performance, fetal viability, or body weight; no fetal malformations. |
| Mouse Embryo- toxicity & Terato- genicity Study | Mouse / BDF1 | ca. 20 mated females | 0 190 395 791 | Day 6 - 15 of gestation (1st day of gestation = day 0) Oral (gavage) | Dams: No drug-related deaths. All treated groups: Dose-dependent ↓body weight gain & food intake; dose-dependent ↓live fetuses and ↑early resorption rate. High Dose: No live fetuses. High & Mid Doses: Most had complete resorptions. Mid Dose: Only one dam with live fetuses. Low Dose: Slight ↑late resorptions. Fetus: Mid Dose: Oligodactyly. Mid and Low Dose: ↓fetal body weight. Low Dose: Cleft palate, anophthalmia, microphthalmia, oligodactyly, polydactyly, syndactyly, kinky tail; dilated cerebral ventricles. |
| Title | Species/ Strain | No./Sex / Dose | Dose (mg/kg / day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
| Mouse Embryo- toxicity & Teratogenicity Study (Supplement to Study Ref. 2302) | Mouse/ BDF1 | ca. 20 mated females | 0 25 50 100 | Day 6 - 15 of gestation (1st day of gestation = day 0) Oral (gavage) | Dams: All groups: No drug-related deaths. High Dose: Slight ↓body weight gain and food intake. Fetus: No treatment-related effects. |
| Mouse Embryo- toxicity & Teratogenicity Study (Supplementary Segment II - F1 pup evaluation) | Mouse/ BDF1 | ca. 20 mated females | 0 50 100 200 | Day 6 - 15 of gestation (1st day of gestation = day 0) Oral (gavage) | Dams: No drug-related deaths. High Dose: Slight ↓body weight gain and food intake; slightly prolonged gestation period. Pups: High Dose: ↓Live neonates, ↓viability index from day 0 to day 4 after birth, slight ↓body weight gain, ↑number of pups with skeletal abnormalities (domed head, kinky tail), retardation of ossification, slight ↑ambulation in open field test. High & Mid Doses: Deaths with domed head and hydrocephaly; swollen spleen at necropsy with extramedullary hematopoiesis. |
| Monkey Preliminary Embryo- toxicity & Terato- genicity Study | Monkey / Cynomolgus (Macaca fascicularis) | 2 pregnant females | 90 180 | Day 20 - 50 of gestation Oral (gavage) | Dams: No deaths in any group. High Dose: Abortion (1 between days 40 - 50 of gestation). High and Low Doses: Embryonic death (1 in each group, high dose on day 40 of gestation, low dose on day 50 of gestation); ↓food intake in dams with embryonic death and abortion. Fetus: High and Low Doses: No placental or external anomalies in dead embryos or live fetuses. Low Dose: One normal male fetus; no abnormalities in body weight, or visceral or skeletal findings. |
| Title | Species/ Strain | No./Sex/ Dose | Dose (mg/kg/ day) | Duration / Route of Administration | Target Organs / Systems of Toxicity |
Monkey Embryo- toxicity & Terato- genicity Study | Monkey / Cynomolgus (Macaca fascicularis) | 5 pregnant females | 0 22.5 45 90 | Day 20 - 50 of gestation Oral (gavage) | Dams No maternal deaths or adverse effects. High Dose: Abortion (1 between days 30 - 40 of gestation). Low Dose: Embryonic death (1 on day 30 of gestation). Fetus: No treatment-related changes observed in the examinations of live fetuses. |
Mouse Peri- and Post-natal Study (Segment III) | Mouse/ BDF1 | ca. 20 mated females (F0 generation) | 0 100 200 400 | From day 15 of gestation, through lactation to day 20 post-partum (First day of gestation = gestation day 0) (First day of lactation = lactation day 0) Oral (gavage) | Dams: No treatment-related deaths or adverse effects. Pups (F1): No treatment-related findings. |
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrXELODA® (capecitabine) Tablets 150 mg and 500 mg, Control No. 247293, Product Monograph, Hoffmann-La Roche limited, Canada, Inc. (April 19, 2021).