


Product Monograph - Inqovi
RECENT MAJOR LABEL CHANGES
| 7 Warnings and Precautions, Monitoring and Laboratory Tests | 03/2022 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 7
4.5 Missed Dose ............................................................................................................. 7
5 OVERDOSAGE ............................................................................................................ 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 8
7 WARNINGS AND PRECAUTIONS ................................................................................. 8
7.1 Special Populations ................................................................................................ 11
7.1.1 Pregnant Women ............................................................................................. 11
7.1.2 Breast-feeding .................................................................................................. 11
7.1.3 Pediatrics .......................................................................................................... 12
7.1.4 Geriatrics .......................................................................................................... 12
7.1.5 Patients with Renal Impairment ...................................................................... 12
8 ADVERSE REACTIONS............................................................................................... 12
8.1 Adverse Reaction Overview ................................................................................... 12
8.2 Clinical Trial Adverse Reactions ............................................................................. 13
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 16
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................................. 16
8.5 Post-Market Adverse Reactions ............................................................................. 17
9 DRUG INTERACTIONS .............................................................................................. 17
9.4 Drug-Drug Interactions .......................................................................................... 17
9.5 Drug-Food Interactions .......................................................................................... 18
9.6 Drug-Herb Interactions .......................................................................................... 18
9.7 Drug-Laboratory Test Interactions......................................................................... 18
10 CLINICAL PHARMACOLOGY ...................................................................................... 18
10.1 Mechanism of Action ....................................................................................... 18
10.2 Pharmacodynamics .......................................................................................... 18
10.3 Pharmacokinetics ............................................................................................. 19
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 23
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 23
PART II: SCIENTIFIC INFORMATION ..................................................................................... 24
13 PHARMACEUTICAL INFORMATION .......................................................................... 24
14 CLINICAL TRIALS ...................................................................................................... 25
14.1 Clinical Trials by Indication .............................................................................. 25
Adult Patients with Myelodysplastic Syndromes (MDS) ................................................. 25
15 MICROBIOLOGY ...................................................................................................... 28
16 NON-CLINICAL TOXICOLOGY .................................................................................... 29
PATIENT MEDICATION INFORMATION ................................................................................ 31
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
INQOVI® (decitabine and cedazuridine) is indicated for:
- The treatment of adult patients with myelodysplastic syndromes (MDS) including previously treated and untreated, de novo and secondary MDS with the following French-American-British subtypes (refractory anemia, refractory anemia with ringed sideroblasts, refractory anemia with excess blasts, and chronic myelomonocytic leukemia [CMML]) and intermediate-1, intermediate-2, and high-risk International Prognostic Scoring System (IPSS) groups.
1.1 Pediatrics
Pediatrics (< 18 years of age): MDS is rare in children. Inqovi is not indicated in the pediatric population, as the safety and efficacy of Inqovi has not been studied in patients less than 18 years of age.
1.2 Geriatrics
Geriatrics (> 65 years of age): Of the 208 patients treated with Inqovi, 75% were age 65 years and over, while 36% were age 75 years and over. No overall difference in effectiveness and safety was noted between patients age 65 years and older and younger subjects.
2 CONTRAINDICATIONS
Inqovi is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Inqovi must be prescribed under the supervision of a qualified physician experienced in the use of chemotherapeutic agents.
Important Administration Information
- Do NOT substitute Inqovi for an intravenous decitabine product within a cycle.
- Consider premedication with standard antiemetic therapy prior to each dose to minimize nausea and vomiting (See 8 ADVERSE REACTIONS).
- Obtain complete blood cell counts 1-4 days prior to initiating Inqovi, before each subsequent cycle and as clinically indicated to monitor response and toxicity.
- Obtain liver chemistries and serum creatinine prior to initiation of treatment and repeat if liver/renal toxicities are suspected.
- Delay treatment at the discretion of the treating physician if patients experience hematological or non-hematological adverse reactions. Modify dosage in the presence of hematological and non-hematological toxicities. These adjustments can only occur after cycle 2. (See 4 DOSAGE AND ADMINISTRATION, Recommended Dose and Dosage Adjustment).
- Agents that increase gastric pH should not be taken within 4 hours of Inqovi administration (See 9 DRUG INTERACTIONS).
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
The recommended dose of Inqovi is 1 tablet containing (35 mg of decitabine and 100 mg of cedazuridine) orally once daily on Days 1 through 5 of each 28-day cycle until disease progression or unacceptable toxicity. A complete or partial response may take longer than 4 cycles. Continue treatment until disease progression or unacceptable toxicity. Repeat cycles every 28-days. Do not modify the recommended dose for the first 2 cycles. Delay or reduce the dose per cycle following hematologic and non-hematologic toxicities.
Dosage Adjustment
Hematologic Adverse Reactions
Refer to Table 1 for dose delay and dose resumption criteria for hematologic toxicities (See 7 WARNINGS AND PRECAUTIONS; 8 ADVERSE REACTIONS).
Table 1: Dose delay and resumption criteria for hematological toxicities in the absence of active disease
| Parameter | Delay Criteria | Resumption Criteria |
|---|---|---|
| ANC | < 1.0 x 10⁹/L | ≥ 1.0 x 10⁹/L |
| Platelets | < 50 x 109/L | ≥ 50 x 109/L |
In the absence of active disease
- If hematological recovery occurs (ANC at least 1.0 x 10⁹/L and platelets at least 50 x 109/L) within 2 weeks of the last Inqovi treatment cycle, continue Inqovi at the same dosage.
If hematological recovery does not occur (ANC at least 1.0 x 10⁹/L and platelets at least 50 x 109/L) within 2 weeks of the last Inqovi treatment cycle
- Delay Inqovi for up to 2 additional weeks AND
- Resume at a reduced dosage by administering Inqovi on Days 1 through 4 only. Consider further dosage reductions in the order listed in Table 2 if myelosuppression persists after a dosage reduction.
- Maintain or increase dosage in subsequent cycles as clinically indicated.
Table 2: Recommended Inqovi Dosage Reductions for Myelosuppression
| Dose Reduction | Dosage |
|---|---|
| First | 1 tablet orally once daily on Days 1 through 4 |
| Second | 1 tablet orally once daily on Days 1 through 3 |
| Third | 1 tablet orally once daily on Days 1, 3 and 5 |
Manage persistent severe neutropenia and febrile neutropenia with supportive treatment (See 7 WARNINGS AND PRECAUTIONS, Hematologic
Non-Hematologic Adverse Reactions
Delay subsequent Inqovi cycle for the following non-hematologic adverse reactions and resume at the same or reduced dosage upon resolution:
- Serum creatinine 2 mg/dL or greater
- Serum bilirubin 2 times upper limit of normal (ULN) or greater
- Alanine aminotransferase (ALT) or aspartate aminotransferase (AST) 2 times ULN or greater
- Active or uncontrolled infection
Renal Impairment: No adjustment of starting dosage is recommended when administering Inqovi in patients with mild or moderate renal impairment (creatinine clearance [CLcr] ≥ 30 mL/min). Frequent monitoring for adverse reactions is recommended in patients with moderate renal impairment (CLcr: 30-59 mL/min) due to the increased risks of certain adverse reactions.
Recommended dosage has not been established in patients with severe renal impairment (CLcr: 15 to 29 mL/min) or end stage renal disease (CLcr <15 mL/min) (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions
Hepatic Impairment: No adjustment of starting dosage is recommended when administering Inqovi in patients with mild hepatic impairment (total bilirubin > 1 to ≤ 1.5 × ULN). The recommended dosage of Inqovi has not been established in patients with moderate (total bilirubin > 1.5 to 3 x ULN) or severe hepatic impairment (total bilirubin > 3 × ULN) (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions
4.4 Administration
Instruct patients of the following:
- Take one Inqovi tablet with water on an empty stomach, at approximately the same time each day.
- Swallow Inqovi tablet whole and do not chew, crush, or cut tablet prior to swallowing.
- Do not eat for 2 hours before and 2 hours after taking Inqovi (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics).
- Take one tablet a day for 5 days in each cycle.
Inqovi is a cytotoxic drug. Follow applicable handling and disposal procedures (See 11 STORAGE, STABILITY AND DISPOSAL).
4.5 Missed Dose
Missed dose
- If the patient misses a dose of Inqovi within 12 hours of the usual time it is taken, instruct patients to take the missed dose as soon as possible and then continue with the next scheduled dose at the usual time.
- If the patient misses a dose of Inqovi by more than 12 hours, the patient should wait and take the missed dose the following day at the usual time and then extend the dosing period by one day for every missed dose to complete 5 days of treatment for each cycle.
Vomited dose
If the patient vomits following Inqovi administration, advise not to take an additional dose but to continue with the next scheduled dose. Consider pre-medicating with standard antiemetic therapy.
5 OVERDOSAGE
There is no known antidote for overdosage with Inqovi. Overdosage could cause increased myelosuppression, and neutropenia-related infections such as pneumonia and sepsis. For patients who experience overdose, monitor closely and provide appropriate standard supportive treatment.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3: Dosage Forms, Strengths, Composition and Packaging
Inqovi tablets are biconvex, oval-shaped film-coated, red tablet, plain-faced on one side and debossed with “H35” on the other side.
Inqovi is supplied in a blister pack of five tablets with one blister card in a carton.
7 WARNINGS AND PRECAUTIONS
See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Inqovi administration should only be prescribed under the supervision of healthcare professionals experienced with cancer chemotherapeutic drugs.
Inqovi is a cytotoxic drug. Procedures for proper handling and disposal of antineoplastic drugs should be applied (See 11 STORAGE, STABILITY AND DISPOSAL).
Carcinogenesis and Mutagenesis
Decitabine and cedazuridine are mutagenic. Decitabine was mutagenic in in vitro and in vivo studies. Cedazuridine was mutagenic in a reverse bacterial mutation assay (Ames assay) and was genotoxic in a chromosome aberration assay in human lymphocytes (See 16 NON-CLINICAL TOXICOLOGY).
Carcinogenicity studies have not been conducted with decitabine and cedazuridine.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 35 mg decitabine and 100 mg cedazuridine. | Colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate. The film coating material contains iron oxide red, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. |
Driving and Operating Machinery
Patients should be advised that they may experience fatigue and dizziness due to anemia. Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Hematologic
Hemorrhage
Serious bleeding-related treatment-emergent adverse events (TEAEs) have been reported with Inqovi due to severe thrombocytopenia. Gastrointestinal hemorrhage was reported in 6.7% of patients with Grade ≥ 3 in 2.4%. Intracranial hemorrhage was reported in 1.9% of patients with Grade ≥ 3 in 1.4%. Monitor patients receiving Inqovi closely for signs and symptoms of serious bleeding-related adverse reactions.
Myelosuppression
Fatal and serious myelosuppression can occur with Inqovi.
Based on laboratory values, new or worsening thrombocytopenia occurred in 82% of patients with Grade 3-4 occurring in 76%. Neutropenia occurred in 73% of patients, with Grade 3-4 occurring in 71%. Anemia occurred in 71% of patients, with Grade 3-4 occurring in 55% (See 8 ADVERSE REACTIONS, Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data).
Myelosuppression (thrombocytopenia, neutropenia, anemia, and febrile neutropenia) is the most common cause of dose reductions or dose delays. Dose reduction/dose delays due to myelosuppression (thrombocytopenia, neutropenia, anemia, and febrile neutropenia) occurred in 36% of the patients. Febrile neutropenia occurred in 33% of patients, with Grade 3-4 occurring in 32%. Permanent discontinuation due to myelosuppression (febrile neutropenia) occurred in 1% of patients (See 8 ADVERSE REACTIONS).
Fatal and serious infectious complications can occur with Inqovi. Fatal pneumonia occurred in 1% of patients. Pneumonia occurred in 21% of patients, with Grade 3-4 occurring in 15%. Sepsis occurred in 14% of patients, with Grade 3-4 occurring in 11%. Fatal sepsis occurred in 1% of patients, and fatal septic shock in 1% (See 8 ADVERSE REACTIONS).
Obtain complete blood cell counts 1-4 days prior to initiating Inqovi, before each subsequent cycle, and as clinically indicated to monitor response and toxicity. Manage toxicity using dose delay and dose reduction. Administer growth factors, and anti-infective therapies for treatment or prophylaxis as needed (See 4 DOSAGE AND ADMINISTRATION).
Immune
Hypersensitivity
Serious anaphylactic reactions have been reported with decitabine. Hypersensitivity reactions have been reported with intravenous decitabine and Inqovi. Rash is reported in early cycles of Inqovi and diminishes with later cycles. Discontinue Inqovi for serious hypersensitivity adverse reactions. Initiate supportive treatment promptly.
Infections and Infestations
Serious infection-related adverse reactions such as cellulitis, sepsis, and pneumonia were reported in patients receiving Inqovi. Fungal infections and bacteremia appeared as early events, as did febrile neutropenia. Monitor patients for signs and symptoms of infection and administer anti-infectives as appropriate (See 7 WARNINGS AND PRECAUTIONS, Hematologic
8 ADVERSE REACTIONS).
Monitoring and Laboratory Tests
- Obtain complete blood cell counts 1-4 days prior to initiating Inqovi, before each subsequent cycle, and as clinically indicated to monitor response and toxicity.
- Obtain liver chemistries and serum creatinine prior to initiation of treatment and repeat if liver/renal toxicities are suspected.
- Verify the pregnancy status in females of reproductive potential prior to initiating Inqovi.
Reproductive Health: Female and Male Potential
- Fertility
Decitabine decreased sperm counts in mice when administered at half of the decitabine recommended human dose. Because of the possibility of infertility as a consequence of the decitabine component in Inqovi therapy, advise men to seek advice on conservation of sperm prior to any Inqovi treatment and female patients of childbearing potential to seek consultation regarding oocyte cryopreservation prior to initiation of treatment (See 16 NON-CLINICAL TOXICOLOGY).
- Teratogenic Risk
Verify the pregnancy status in females of reproductive potential prior to initiating Inqovi. Advise women of childbearing potential to avoid becoming pregnant and counsel to use effective contraception while receiving Inqovi and for 6 months following last dose. Based on findings from human and animal data and its mechanism of action, decitabine can cause fetal harm. (See 10 CLINICAL PHARMACOLOGY, Mechanism of Action; 7 WARNINGS AND PRECAUTIONS, Special Populations; 16 NON-CLINICAL TOXICOLOGY).
Advise men not to father a child while receiving treatment with Inqovi, and for 3 months following the last dose.
Advise men with female partners of childbearing potential to use effective contraception during this time
Respiratory
Interstitial lung disease (ILD) (including pulmonary infiltrates, organising pneumonia and pulmonary fibrosis) without signs of infectious etiology was reported in patients receiving intravenous decitabine. Assess patients with acute onset or unexplained worsening of pulmonary symptoms to exclude ILD. If ILD is confirmed, initiate appropriate treatment (See 8 ADVERSE REACTIONS).
7.1 Special Populations
7.1.1 Pregnant Women
Inqovi has not been studied in pregnant women. Inqovi can cause fetal harm when administered to a pregnant woman. A single published case report of decitabine pregnancy exposure in a 39-year-old woman with a hematologic malignancy described multiple structural abnormalities after 6 cycles of therapy in the 18th week of gestation. These abnormalities included holoprosencephaly, absence of nasal bone, mid-facial deformity, cleft lip and palate, polydactyly and rocker-bottom feet. The pregnancy was terminated. Intravenous decitabine administration to pregnant mice and rats during organogenesis at a dose approximately 7% of the recommended human dose caused increased embryo-fetal mortality, alterations in growth and structural abnormalities (See 16 NON-CLINICAL TOXICOLOGY).
Inqovi should not be used in pregnant women. Advise patient of the potential risk to the fetus.
7.1.2 Breast-feeding
It is not known whether cedazuridine, decitabine or their metabolites are excreted in breast milk. Their effects on the breastfed child and milk production are not known. Because many drugs are excreted in human milk, and because of the potential for serious adverse reactions from Inqovi in breastfed infants, advise women to avoid breastfeeding during treatment with Inqovi and for at least 2 weeks after the last dose.
7.1.3 Pediatrics
Inqovi is not indicated in the pediatric population, as the safety and efficacy of Inqovi has not been studied in patients less than 18 years of age.
7.1.4 Geriatrics
No overall difference in effectiveness and safety was noted between patients age 65 years and older and younger subjects.
7.1.5 Patients with Renal Impairment
Inqovi has not been studied in patients with severe renal impairment. Decitabine is mainly excreted in the urine as inactive metabolites and degradation products. Cedazuridine is primarily renally eliminated, with 81% of cedazuridine-related material recovered in the urine after an IV cedazuridine dose. Higher Grade ≥3 TEAEs have been reported in moderate renal impairment. Monitor patients with renal dysfunction closely. Inqovi has not been studied in patients with severe renal impairment (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics, Special Populations and Conditions
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety of Inqovi in adult patients (N=208) was evaluated in a pooled safety population that included MDS and chronic myelomonocytic leukemia (CMML) patients from one Phase 3 study (ASTX727-02, N=130) and one Phase 2 study (ASTX727-01-B, N=78).
Patients were randomized to receive Inqovi (35 mg of decitabine and 100 mg of cedazuridine) orally once daily on Days 1 through 5 in Cycle 1, and decitabine 20 mg/m2 intravenously on Days 1 through 5 in Cycle 2, or the reverse sequence, and then Inqovi orally once daily on Days 1 through 5 of each 28-day cycle in Cycles 3 and beyond.
Among the patients who received Inqovi, 61% of patients were exposed for 6 months or longer and 24% were exposed to Inqovi for greater than 1 year.
The most common treatment-emergent adverse events (TEAEs) (≥ 20%) were fatigue, constipation, hemorrhage, myalgia, mucositis, arthralgia, nausea, dyspnea, diarrhea, rash, dizziness, febrile neutropenia, edema, headache, cough, decreased appetite, upper respiratory tract infection, pneumonia, and transaminase increased. The most common Grade 3 or 4 laboratory abnormalities (≥ 50%) were leukocytes decreased, platelet count decreased, neutrophil count decreased, and hemoglobin decreased.
The incidence of grade ≥ 3 AEs and SAEs were generally consistent across cycles or tended to decrease in later cycles.
Serious TEAEs occurred in 68% of patients who received Inqovi. Serious TEAEs occurring in >5% of patients included febrile neutropenia (30%), pneumonia (14%) and sepsis (13%). Deaths due to TEAEs occurred in 6% of patients, most often from sepsis (1%), septic shock (1%), pneumonia (1%), respiratory failure (1%), and one case each of cerebral hemorrhage and sudden death.
Permanent discontinuation due to a TEAE occurred in 5% of patients who received Inqovi. The most frequent TEAEs resulting in permanent discontinuation were febrile neutropenia (1%) and pneumonia (1%).
Dose delays due to a TEAE occurred in 41% of patients who received Inqovi. The most common TEAEs that led to dose delays were neutropenia (18%), febrile neutropenia (8%), thrombocytopenia (6%), anemia (5%), and leukopenia (5%). The median duration of dose delays was 9 days (range 1 to 75 days).
Dose reductions due to a TEAE occurred in 19% of patients who received Inqovi. TEAEs requiring dosage reductions occurring in > 2 % of patients who received Inqovi included neutropenia (12%), anemia (3%), and thrombocytopenia (3%). The median number of dose reduced cycles in patients was 2 (range 1 to 10 cycles).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Table 4 lists the treatment emergent adverse events in the pooled safety population observed in ≥ 10% (All Grades) or Grades 3 and 4 of patients who received Inqovi.
Table 4. Treatment Emergent Adverse Events Reported in ≥ 10% in Patients Who Received Inqovi in Pooled Safety Population
| TEAEs* | Inqovi Cycle 1 N=107 | Intravenous Decitabine Cycle 1 N=106 | Inqovi† All Cycles N=208 | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | |||||||||||
| Blood & lymphatic system disorders | ||||||||||||||||
| Thrombocytopenia | 51 | 42 | 41 | 34 | 62 | 54 | ||||||||||
| Neutropenia | 38 | 36 | 37 | 31 | 57 | 54 | ||||||||||
| Anemia1 | 31 | 25 | 33 | 28 | 48 | 42 | ||||||||||
| Febrile neutropenia | 10 | 10 | 13 | 13 | 33 | 32 | ||||||||||
| General disorders and administration site conditions | ||||||||||||||||
| TEAEs* | Inqovi Cycle 1 N=107 | Intravenous Decitabine Cycle 1 N=106 | Inqovi† All Cycles N=208 | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | ||||||||||||
| Fatigue2 | 29 | 2 | 25 | 0 | 55 | 5 | |||||||||||
| Hemorrhage3 | 24 | 2 | 17 | 0 | 43 | 3 | |||||||||||
| Edema4 | 10 | 0 | 11 | 0 | 30 | 0.5 | |||||||||||
| Pyrexia | 7 | 0 | 7 | 0 | 19 | 1 | |||||||||||
| Gastrointestinal disorders | |||||||||||||||||
| Constipation5 | 20 | 0 | 23 | 0 | 44 | 0 | |||||||||||
| Mucositis6 | 18 | 1 | 24 | 2 | 41 | 4 | |||||||||||
| Nausea | 25 | 0 | 16 | 0 | 40 | 0.5 | |||||||||||
| Diarrhea7 | 16 | 0 | 11 | 0 | 37 | 1 | |||||||||||
| Transaminase increased8 | 12 | 1 | 3 | 0 | 21 | 3 | |||||||||||
| Abdominal pain9 | 9 | 0 | 7 | 0 | 19 | 1 | |||||||||||
| Vomiting | 5 | 0 | 5 | 0 | 15 | 0 | |||||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||||||||
| Myalgia10 | 9 | 2 | 16 | 1 | 42 | 3 | |||||||||||
| Arthralgia11 | 9 | 1 | 13 | 1 | 40 | 3 | |||||||||||
| Respiratory, thoracic, and mediastinal disorders | |||||||||||||||||
| Dyspnea12 | 17 | 3 | 9 | 3 | 38 | 6 | |||||||||||
| Cough13 | 7 | 0 | 8 | 0 | 28 | 0 | |||||||||||
| Skin and subcutaneous tissue disorders | |||||||||||||||||
| Rash14 | 12 | 1 | 11 | 1 | 33 | 0.5 | |||||||||||
| Nervous system disorders | |||||||||||||||||
| Dizziness15 | 16 | 1 | 11 | 0 | 33 | 2 | |||||||||||
| Headache16 | 22 | 0 | 13 | 0 | 30 | 0 | |||||||||||
| Neuropathy17 | 4 | 0 | 8 | 0 | 13 | 0 | |||||||||||
| Infections and infestations | |||||||||||||||||
| Upper respiratory tract infection18 | 6 | 0 | 3 | 0 | 23 | 1 | |||||||||||
| Pneumonia19 | 7 | 7 | 7 | 5 | 21 | 15 | |||||||||||
| Sepsis20 | 6 | 6 | 2 | 1 | 14 | 11 | |||||||||||
| Cellulitis21 | 4 | 1 | 3 | 2 | 12 | 5 | |||||||||||
| Metabolism and nutritional disorders | |||||||||||||||||
| Decreased appetite | 10 | 1 | 6 | 0 | 24 | 2 | |||||||||||
| Investigations | |||||||||||||||||
| TEAEs* | Inqovi Cycle 1 N=107 | Intravenous Decitabine Cycle 1 N=106 | Inqovi† All Cycles N=208 | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | ||||||||||||
| Renal impairment22 | 9 | 0 | 8 | 1 | 18 | 0 | |||||||||||
| Weight decreased | 5 | 0 | 3 | 0 | 10 | 1 | |||||||||||
| Injury, poisoning, and procedural complications | |||||||||||||||||
| Fall | 4 | 0 | 1 | 0 | 12 | 1 | |||||||||||
| Psychiatric disorders | |||||||||||||||||
| Insomnia | 6 | 0 | 2 | 0 | 12 | 0.5 | |||||||||||
| Vascular disorders | |||||||||||||||||
| Hypotension23 | 4 | 0 | 6 | 1 | 11 | 2 | |||||||||||
| Cardiac Disorders | |||||||||||||||||
| Arrhythmia24 | 3 | 0 | 2 | 0 | 11 | 1 | |||||||||||
†Includes treatment-emergent adverse events that occurred during all cycles, including during treatment with 1 cycle of intravenous decitabine.
*Based on MedDRA version 22.0
Graded using National Cancer Institute Common Terminology Criteria for Adverse Events NCI (CTCAE v 4.0)
Includes multiple adverse event terms:
1 anemia: Includes anemia and hemoglobin decreased
2 fatigue: Includes fatigue, asthenia, and lethargy
3 hemorrhage: Includes contusion, epistaxis, petechiae, hematuria, conjunctival hemorrhage, mouth hemorrhage, purpura, angina bullosa hemorrhagica, gingival bleeding, hematoma, hemoptysis, eye contusion, hemorrhagic diathesis, increased tendency to bruise, vaginal hemorrhage, abdominal wall hematoma, blood blister, bone contusion, catheter site bruise, ecchymosis, genital hemorrhage, intra-abdominal hematoma, oral mucosa hematoma, periorbital hemorrhage, procedural hemorrhage, pulmonary alveolar hemorrhage, retinal hemorrhage, scleral hemorrhage, thrombotic thrombocytopenic purpura, tongue hemorrhage, and vessel puncture site hemorrhage
4 edema: Includes edema peripheral, peripheral swelling, swelling face, fluid overload, localized edema, face edema, edema, eye swelling, eyelid edema, fluid retention, periorbital swelling, scrotal edema, scrotal swelling, and swelling
5 constipation: Includes constipation and feces hard
6 mucositis: Includes oropharyngeal pain, stomatitis, mouth ulceration, proctalgia, oral pain, gingivitis, oral disorder, gingival pain, colitis, glossodynia, mouth swelling, pharyngitis, proctitis, duodenitis, enteritis, gingival discomfort, gingival swelling, lip disorder, lip ulceration, mucosal ulceration, nasal ulcer, noninfective gingivitis, oral mucosal blistering, oral mucosal erythema, pharyngeal erythema, pharyngeal ulceration, tongue ulceration, and vulvitis
7 diarrhea: Includes diarrhea and feces soft
8 transaminase increased: Includes alanine aminotransferase increased, aspartate aminotransferase increased, blood alkaline phosphatase increased, gamma-glutamyltransferase increased, liver function test increased, and transaminases increased
9 abdominal pain: Includes abdominal pain, abdominal pain upper, abdominal pain lower, epigastric discomfort, and abdominal discomfort
10 myalgia: Includes myalgia, pain in extremity, muscle spasms, pain, musculoskeletal pain, non-cardiac chest pain, muscular weakness, musculoskeletal chest pain, flank pain, musculoskeletal stiffness, muscle strain, and musculoskeletal discomfort
11 arthralgia: Includes arthralgia, back pain, neck pain, joint stiffness, pain in jaw, joint swelling, bursitis, joint range of motion decreased, and joint injury
12 dyspnea: Includes dyspnea, dyspnea exertional, hypoxia, wheezing, chronic obstructive pulmonary disease, and tachypnoea
13 cough: Includes cough and productive cough
14 rash: Includes maculo-papular rash, rash, erythema, skin lesion, folliculitis, dermatitis, dermatitis acneiform, eczema, erythema multiforme, rash erythematous, seborrheic keratosis, skin ulcer, dermatitis allergic, dermatitis contact, eczema nummular, genital erythema, rash papular, rash pruritic, rash pustular, seborrheic dermatitis, skin exfoliation, skin irritation, stasis dermatitis, and ulcerative keratitis
15 dizziness: Includes dizziness, vertigo, postural dizziness, and positional vertigo
16 headache: Includes headache, sinus pain, and sinus headache
17 neuropathy: Includes hypoesthesia, paresthesia, neuropathy peripheral, gait disturbance, peripheral sensory neuropathy, ataxia, balance disorder, brachial plexopathy, carpal tunnel syndrome, and radicular pain
18 upper respiratory infection: Includes upper respiratory tract infection, nasopharyngitis, sinusitis, and viral upper respiratory tract infection
19 pneumonia: Includes pneumonia, pneumonitis, atypical pneumonia, and lung infection
20 sepsis: Includes sepsis, bacteremia, septic shock, endocarditis, pseudomonal bacteremia, and staphylococcal bacteremia
21 cellulitis: Includes cellulitis, catheter site cellulitis, and infected bite
22 renal impairment: Includes blood creatinine increased, acute kidney injury, blood urea increased, blood creatine increased, and renal failure
23 hypotension: Includes hypotension, blood pressure decreased, and cardiogenic shock
24 arrhythmia: Includes sinus tachycardia, atrial fibrillation, bradycardia, tachycardia, atrial flutter, sinus bradycardia, and conduction disorder
8.3 Less Common Clinical Trial Adverse Reactions
Clinically Relevant Adverse Reactions in ≤10% of patients who received Inqovi:
Sweet’s syndrome: Acute febrile neutrophilic dermatosis (1%)
Tumor lysis syndrome (0.5%)
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Table 5: Select Laboratory Abnormalities (>20%): Worsening from Baseline in Patients Who Received Inqovi in Pooled Safety Population
| Lab Abnormality* | Inqovi Cycle 1 | Intravenous Decitabine Cycle 1 | Inqovi All Cycles† | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | All Grades (%) | Grades 3-4 (%) | |||||||||||
| Hematology | ||||||||||||||||
| Leukocytes decreased | 79 | 65 | 77 | 59 | 87 | 81 | ||||||||||
| Platelet count decreased | 79 | 65 | 77 | 67 | 82 | 76 | ||||||||||
| Neutrophil count decreased | 70 | 65 | 62 | 59 | 73 | 71 | ||||||||||
| Hemoglobin decreased | 58 | 41 | 59 | 36 | 71 | 55 | ||||||||||
| Chemistry | ||||||||||||||||
| Glucose increased | 19 | 0 | 11 | 0 | 54 | 7 | ||||||||||
| Albumin decreased | 22 | 1 | 20 | 0 | 45 | 2 | ||||||||||
| Alkaline phosphatase increased | 22 | 1 | 12 | 0 | 42 | 0.5 | ||||||||||
| Glucose decreased | 14 | 0 | 17 | 0 | 40 | 1 | ||||||||||
| Alanine aminotransferase increased | 13 | 1 | 7 | 0 | 37 | 2 | ||||||||||
| Sodium decreased | 9 | 2 | 8 | 0 | 30 | 4 | ||||||||||
| Calcium decreased | 16 | 0 | 12 | 0 | 30 | 2 | ||||||||||
| Aspartate aminotransferase increased | 6 | 1 | 2 | 0 | 30 | 2 | ||||||||||
| Creatinine increased | 7 | 0 | 8 | 0 | 29 | 0.5 | ||||||||||
* Includes any lab abnormalities that worsened by one or more grades. Grade 3-4 includes any lab abnormalities that worsened to Grade 3 or Grade 4.
† The denominator used to calculate the rate varied from 103 to 107 for Inqovi Cycle 1, from 102 to 106 for Intravenous Decitabine Cycle and from 203 to 208 for Inqovi All Cycles based on the number of patients with a baseline value and at least one post-treatment value.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of decitabine administered intravenously. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: differentiation syndrome
Cardiac Disorders: cardiomyopathy
Immune System Disorders: anaphylactic reaction and enterocolitis with fatal outcome.
Respiratory, Thoracic and Mediastinal Disorders: interstitial lung disease (including pulmonary infiltrates, organising pneumonia and pulmonary fibrosis).
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
Drug-drug interaction studies were not conducted with decitabine or cedazuridine.
Drugs Metabolized by Cytidine Deaminase: Cedazuridine is an inhibitor of the cytidine deaminase (CDA) enzyme. Concomitant administration of Inqovi with drugs metabolized by CDA (i.e., cytarabine, gemcitabine, azacytidine, zalcitabine, zidovudine, telbivudine, didanosine, stavudine, lamivudine, abacavir, emtricitabine, apricitabine, tenofovir, adefovir, idoxuridine, entecavir, trifluridine, vidarabine) may result in increased systemic exposure with potential for increased toxicity of these drugs. Avoid co-administration of Inqovi with drugs metabolized by CDA (See 10 CLINICAL PHARMACOLOGY).
Gastric pH Modifying Enzymes: Cedazuridine is converted to its epimer prior to absorption and its bioavailability may be affected by gastric PH. Based on a population pharmacokinetic analysis, no effect on cedazuridine or decitabine PK was shown with gastric pH modifying drugs as long as they are not administered within 4 hours of Inqovi administration (See 4 DOSAGE AND ADMINISTRATION).
CYP Enzymes: Decitabine is not a substrate for P450 and did not inhibit or induce cytochrome P450 enzymes in vitro. Cedazuridine did not induce or inhibit CYP1A, CYP3A, CYP2B6 or CYP2C9 and did not inhibit CYP1A, CYP3A, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP2E1 enzymes; therefore, CYP450-mediated drug-drug interactions are unlikely with Inqovi.
Transporter Systems: Decitabine is a weak inhibitor of P-glycoprotein (P-gp), and cedazuridine is neither a substrate nor an inhibitor of transporters including P-gp, MDR1, BCRP, MATE and OAT, therefore, Inqovi is not expected to affect P-gp mediated transport of co-administered medicinal products.
9.5 Drug-Food Interactions
Inqovi should not be taken with food. Based on limited data, taking Inqovi with a meal could reduce overall decitabine exposure. (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics, Effect of Food
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Decitabine is a nucleoside metabolic inhibitor. It is believed to exert its antineoplastic effects after phosphorylation and direct incorporation into DNA and inhibition of DNA methyltransferase, causing hypomethylation of DNA and cellular differentiation and/or apoptosis. Decitabine inhibits DNA methylation in vitro, which is achieved at concentrations that do not cause major suppression of DNA synthesis. Decitabine-induced hypomethylation in neoplastic cells may restore normal function to genes that are critical for the control of cellular differentiation and proliferation. In rapidly dividing cells, the cytotoxicity of decitabine may also be attributed to the formation of covalent adducts between DNA methyltransferase and decitabine incorporated into DNA. Non-proliferating cells are relatively insensitive to decitabine.
Cytidine deaminase (CDA) is an enzyme that is responsible for the degradation of cytidine nucleosides, including the cytidine analog decitabine. High levels of CDA in the gastrointestinal tract and liver rapidly degrade these nucleosides and prohibit or limit their oral bioavailability. Cedazuridine inhibits CDA. Oral administration of cedazuridine with decitabine increases the systemic exposure of decitabine via inhibition of first pass metabolism of decitabine in the gut and liver by CDA.
10.2 Pharmacodynamics
Decitabine induced hypomethylation both in vitro and in vivo. The mean of maximal reduction from baseline of long interspersed nucleotide elements-1 (LINE-1) demethylation was observed at Day 8 in patients administered the recommended 5 consecutive daily doses of Inqovi with less than complete recovery of LINE-1 methylation to baseline at the end of the treatment cycle.
According to a safety-exposure analysis of patients enrolled in the Phase 2 ASTX727-01 and Phase 3 ASTX727-02 studies, increases in decitabine exposure are associated with increased risks of neutropenia and thrombocytopenia.
In Vitro Antitumor Effects
In vitro, decitabine produced antiproliferative and differentiating effects in a panel of leukemic cell lines from murine and human origin, with IC50 values generally below 1µM. Similarly, decitabine decreased the proliferation of many solid tumor cell lines with IC50 values from the nM to the µM range. The differentiation effects were usually observed at concentrations that did not show clear cytotoxic effects. Also, in models of normal hematopoietic cell differentiation, decitabine reduced the growth and induced differentiation characteristic of normal hematopoietic cells without inducing cytotoxicity at concentrations of 10, 50 and 100 nM.
In Vivo Effects in Tumor Models
Decitabine demonstrated dose-dependent antitumor activity in several mouse leukemia models as well as in a rat myeloid leukemia model, with a clear effect on survival at well-tolerated doses.
Decitabine displayed a synergistic interaction with histone deacetylase (HDAC) inhibitors, a class of agents that interfere with the deacetylation of histones and alter gene expression. However, antagonistic or conflicting results were obtained with drugs that block the cell cycle (hydroxyurea) or interfere with nucleoside synthetic pathways and DNA synthesis such as cytarabine. The latter interactions reflect the requirement for decitabine incorporation into DNA in cells progressing through the S-phase of the cell cycle.
Cardiac Electrophysiology
A dedicated study to evaluate the QT prolongation potential of Inqovi has not been conducted.
10.3 Pharmacokinetics
Inqovi, given as a fixed dose combination tablet of decitabine 35 mg and cedazuridine 100 mg, achieved 5-day cumulative decitabine area under the curve (AUC) exposures equivalent to IV infusion of decitabine at 20 mg/m2. Decitabine 5-day total cycle AUC0-24hr was 856 ng•hr/mL for Inqovi and 865 ng•hr/mL for IV decitabine. The ratio of the geometric least square means of the 5-day total decitabine AUC0-24hr between Inqovi and IV decitabine was 99% (90% confidence interval [CI] 93%; 106%) (Table 6).
Table 6: 5-Day Total decitabine AUC0-24/hr: Intravenous decitabine vs Inqovi
5-day AUC0-24 (ng.hr/mL) (N= 123) | IV Decitabine LSM (n=123) | Inqovi Tablet Geo LSM (n=123) | Ratio (%) Geo LSM (90% CI) | Intrasubject Variability (CV%) | |||
| 865 | 856 | 99 (93-106) | 32 | ||||
CI=confidence interval; CV=coefficient of variation; Geo: Geometric; LSM=Least Squares Means
The pharmacokinetics (PK) of decitabine and cedazuridine with Inqovi was studied in patients with MDS and CMML. Following administration of Inqovi, decitabine exposure with Inqovi on Day 1 was 40% less compared to that after the IV decitabine. Steady-state exposures for both cedazuridine and decitabine were reached on Day 2 of dosing with Inqovi. Inqovi achieved decitabine area under the curve (AUC) exposures equivalent to those achieved with IV infusion of decitabine at 20 mg/m2 with the recommended dosage of Inqovi for 5 consecutive days. On Day 2 and Day 5 of once daily dosing with Inqovi, decitabine mean (%CV) AUC0-24hr were 189 (55%) and 178 (53%) ng•hr/mL, respectively, and Cmax was 145 (55%) and 140 (63%) ng/mL, respectively. Cedazuridine mean AUC0-24hr exposure at steady state (Day 2) was 3290 (45%) ng•hr/mL and Cmax was 349 (49%) ng/mL (Table 7).
Table 7: Pharmacokinetics of Inqovi* vs IV decitabine*
| Parameters | IV decitabine | Inqovi | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Decitabine | Decitabine | Cedazuridine | ||||||||||||||||
| Day 1 | Day 2 | Day 1 | Day 2 | Day 5 | Day 1 | Day 2 | ||||||||||||
AUC0-24 ng•hr/mL | 173 (41%) | 169 (42%) | 103 (55%) | 189 (55%) | 178 (53%) | 2950 (49%) | 3290 (45%) | |||||||||||
| Accumulation ratio based on AUC0-24hr | - | - | 0.9 (67%) | 1.7 (42%) | - | - | 1.1 (63%) | |||||||||||
Cmax ng/mL | 184 (48%) | 180 (49%) | 83 (66%) | 145 (55%) | 140 (63%) | 321 (54%) | 349 (49%) | |||||||||||
Tmax** Hours | 1.0 (0.2-1.3) | 1.0 (0.3 -1.6) |
(0.5 - 3.0) |
(0.5 - 2.0) |
(0.3 - 3.0) | 3 (1.6 - 8) | 3 (1 - 8) | |||||||||||
VL/F L | 315 (75%) | 93.5 (79%) | 585 (55%) | 369 (59%) | 417 (54%) | 280 (51%) | 296 (51%) | |||||||||||
T1/2*** Hours | 1.0 (47%) | 1.0 (45%) | 1.2 (23%) | 1.4 (25%) | 1.5 (27%) | 6 (18%) | 7 (19%) | |||||||||||
CL/F L/hours | 226 (46%) | 232 (46%) | 342 (55%) | 185 (56%) | 197 (53%) | 31 (46%) | 30 (46%) | |||||||||||
Cmax= maximum plasma concentration; AUC0-24hr=area under the plasma concentration-time curve from time zero to 24 hours; CV=coefficient of variation; SD=standard deviation; Tmax= Time to maximum concentration; V/F=apparent volume of distribution; CL/F=apparent clearance
* Mean (%CV)
**Median (range)
***Mean SD
In a Phase 1 study, oral coadministration of decitabine (20 mg to 40 mg fixed dose once daily) did not affect the systemic exposure of cedazuridine, whereas cedazuridine (40 mg to 100 mg once daily) increased decitabine exposure (0.6 to 1.1 times the recommended dose) when orally co-administered as compared with oral decitabine alone. Co-administration of oral cedazuridine 100 mg and decitabine 30 mg or 40 mg provided 82% and 129% of decitabine AUC, respectively as compared with IV decitabine (20 mg/m2).
Absorption
After oral administration of Inqovi, the median Tmax was 3 hours (range: 1 to 8) for cedazuridine at steady state (Day 2) and 1 hour (range: 0.3 to 3) for decitabine. When co-administered with cedazuridine, decitabine oral relative bioavailability is enhanced to achieve systemic AUC exposures seen with IV decitabine. In 14C-ADME study, approximately 47.5% (range: 23.2% to 58.8%) of oral cedazuridine dose was absorbed and bioavailability was 20.7% (range: 12.7% to 25.6%).
Effect of Food
In a crossover food effect study in 16 patients, administration of Inqovi with a high-fat, high-calorie meal reduced the overall decitabine exposure (AUC0-8hr) and Cmax significantly. Cedazuridine time to maximum concentration (Tmax) was slightly delayed but its systemic exposure was not affected by the meal.
Distribution:
Decitabine
Decitabine is approximately 5% bound to human plasma proteins in vitro. The geometric mean (CV%) of apparent volume of distribution at steady state is 417 L (54%).
Cedazuridine
Cedazuridine is approximately 35% bound to human plasma proteins in vitro. The geometric mean (CV%) of apparent volume of distribution for cedazuridine is 296 L (51%).
Metabolism:
Decitabine
Decitabine is mainly metabolized via deamination by cytidine deaminases.
Cedazuridine
The primary metabolic pathway for cedazuridine is conversion to its epimer.
Elimination:
Decitabine
Following a single oral dose of Inqovi, the mean (CV%) terminal elimination half-life (T1/2) of decitabine was 1.2 (23%) hours. The apparent clearance was 342 L/hr at Day 1 and 197 L/hr at steady state.
Cedazuridine
Following a single oral dose of Inqovi, the mean (CV%) terminal elimination half-life (T1/2) of cedazuridine was 6.3 (18%) hours. The apparent clearance was 30.6 L/hr at Day 1 and 30.3 L/hr at steady state.
Excretion:
Decitabine
The major elimination pathway for decitabine is metabolic, by cytidine deaminase and also physico-chemical degradation at physiological conditions.
Cedazuridine
Following a single oral dose of 100 mg radiolabeled cedazuridine, 45.7% (17.1% as cedazuridine unchanged and 17.5% as cedazuridine-epimer) of the administered dose was recovered in urine and 51% (mostly unabsorbed drug) was recovered in the feces.
The predominant elimination pathway of cedazuridine is renal, as parent drug and its epimer. Following IV administration of 14C-cedazuridine, 80.9% of the total radioactivity was recovered in the urine and 0.6% in the feces. Following a single oral dose of 100 mg radiolabeled cedazuridine, 45.7% (17.1% as cedazuridine unchanged) of the administered dose was recovered in urine and 51.2% (mostly unabsorbed drug, 27.3% unchanged) was recovered in the feces.
Special Populations and Conditions
- Pediatrics: Inqovi is not indicated in the pediatric population.
- Geriatrics: A population pharmacokinetic (PK) analysis indicated that the PK of Inqovi are age-dependent. The 5-day cumulative AUC for decitabine was 1.4-fold greater and the AUC0-24hr for cedazuridine was 1.2-fold greater in patients aged above 75 years after oral Inqovi administration.
- Sex: A population PK analysis indicated that the pharmacokinetics of cedazuridine and decitabine were affected by gender. Cedazuridine AUC0-24hr and decitabine 5-day cumulative AUCs were 1.2-fold and 1.6-fold greater in female patients following oral Inqovi administration.
- Ethnic Origin: Most of the patients studied were Caucasian (>90%). The effects of ethnicity on the pharmacokinetics of Inqovi are unknown.
- Hepatic Insufficiency: A population PK analysis indicated that mild hepatic impairment (total bilirubin > ULN to ≤1.5 × ULN) did not have a clinically meaningful effect on the pharmacokinetics of decitabine or cedazuridine after dosing with Inqovi. The effects of moderate and severe hepatic impairment (1.5 × ULN) on the pharmacokinetics of decitabine and cedazuridine are unknown.
- Renal Insufficiency: Based on a population PK analysis, mild or moderate renal impairment (CLcr ≥ 30 mL/min) increased cedazuridne AUC0-24hr by 1.2-fold and 1.4-fold, whereas decitabine 5-day cumulative AUCs were increased by 1.4-fold and 1.8-fold respectively. Increases in decitabine exposure in patients with moderate renal impairment were associated with increased toxicity. The effects of severe renal impairment (CLcr <30 mL/min) or end-stage renal disease on the pharmacokinetics of decitabine and cedazuridine are unknown.
- Body Weight: Based on a population PK analysis, decitabine and cedazuridine exposures were affected by body weight. Following oral Inqovi administration, decitabine 5-day cumulative exposures were increased by 1.3-fold in patients with lower baseline body weight (<70 kg) and decreased by 24.1% in patients with higher baseline body weight (>93 kg). Cedazuridine AUC0-24hr was decreased by 21.3% in patients with higher baseline body weight (>93 kg).
11 STORAGE, STABILITY AND DISPOSAL
Store Inqovi tablets in original packaging at room temperature (15 to 30°C).
12 SPECIAL HANDLING INSTRUCTIONS
Inqovi is a cytotoxic drug. Any unused medicinal product or waste material should be disposed according to local requirements.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Decitabine
Chemical name: 4-amino-1-[(2R,4S,5R)-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]-1,3,5-triazin-2(1H)-one
Molecular formula and molecular mass: C8H12N4O4
228.21 daltons
Structural formula:
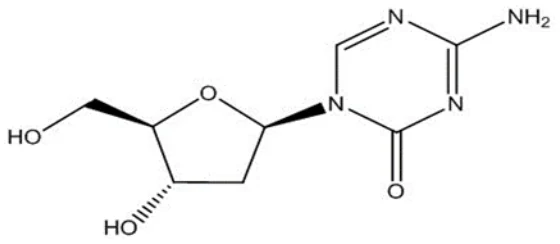
Physicochemical properties: Decitabine is a white to off-white solid. Decitabine drug substance is sparingly soluble in water with a solubility of 8-12 mg/mL.
Proper/Common name: Cedazuridine
Chemical name: (4R)-1-[(2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]-4-hydroxy-1,3-diazinan-2-one
Molecular formula and molecular mass: C9H14F2N2O5
268.21 daltons
Structural formula:
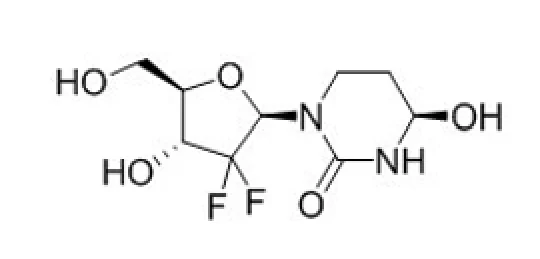
Physicochemical properties:
Cedazuridine is a white to off-white solid. Cedazuridine is sparingly soluble in water with a solubility of 47.2 mg/mL.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Adult Patients with Myelodysplastic Syndromes (MDS)
Inqovi was evaluated in a Phase 3 (ASTX727-02) and a Phase 2 (ASTX727-01-B) study. Both were open-label, randomized, 2-cycle, 2-sequence crossover studies with intravenous (IV) decitabine (20 mg/m2 once daily) and Inqovi oral formulation, followed by a single-arm Inqovi oral treatment. The primary end point was to demonstrate mean total 5-day decitabine AUC0-24hr exposures with Inqovi versus IV decitabine were equivalent. The secondary endpoints were to demonstrate overall response rate, duration of response and rate of transfusion independence (no transfusions for at least a 56-day consecutive period) in transfusion dependent patients at baseline.
The studies were conducted in patients with MDS (International Prognostic Scoring System intermediate [IPSS] Intermediate-1, Intermediate-2, or high-risk), including CMML who were candidates for treatment with a hypomethylating (HMA) agent. Other eligibility criteria included ECOG performance status of 0–2. Patients with uncontrolled cardiac disease or uncontrolled congestive heart failure; creatinine values of >1.5 X ULN; total bilirubin of >1.5 X ULN, AST and ALT > 2.5 X ULN were excluded from these studies. Patients if received one prior cycle of decitabine or azacitidine were also included. No body weight or body surface area limitations were imposed by the eligibility criteria in these studies.
Patients were 1:1 randomized to receive Inqovi (35 mg decitabine and 100 mg cedazuridine) in Cycle 1 and IV decitabine (20 mg/m2) in Cycle 2 or the reverse sequence. Both Inqovi and IV decitabine were dosed once daily for 5 days in 28-day cycles. Starting with Cycle 3, all patients received Inqovi until disease progression, death, or unacceptable toxicity.
Phase 3 and Phase 2 study designs and patient demographics are presented in Table 8 below:
Table 8. Summary of Patient Demographics for Myelodysplastic Syndromes (MDS).
| Study # | Trial design | Dosagea and route of administration | Study subjects (n=number) | Median age (range) | Gender |
|---|---|---|---|---|---|
| ASTX727-02 | Phase 3, open-label, randomized, crossover | Inqovi tablet (35 mg decitabine/100 mg cedazuridine) PO Cycles 1 and 2 (2-way crossover): Inqovi once daily for 5 days, 1 cycle IV decitabine 20 mg/m2 once daily for 5 days, 1 cycle | 133 | 71 (44, 88) | 65% Male 35% Female |
| Study # | Trial design | Dosagea and route of administration | Study subjects (n=number) | Median age (range) | Gender |
|---|---|---|---|---|---|
Cycles ≥3: Inqovi once daily for 5 days in a 28-day treatment cycle | |||||
| ASTX727-01-B | Phase 2, open-label, randomized, crossover study | 35 mg decitabine/100 mg cedazuridine PO Dose confirmation: Cycles 1 and 2 (2-way crossover): Decitabine/cedazuridine once daily for 5 days (administered concomitantly as separate capsules), 1 cycle IV decitabine 20 mg/m2 once daily for 5 days, 1 cycle Cycles ≥3: Decitabine/cedazuridine fixed dose combination once daily for 5 days in each 28-day cycle | 80 total 50 30 | 71 (32, 90) | 76% Male 24% Female |
a All studies: 28-day treatment cycles unless otherwise specified.
Demographics and baseline disease characteristics are shown in Table 9.
Table 9. Demographics and Baseline Disease Characteristics Phase 3 and Phase 2
| Characteristic | Phase 3 Inqovi All Cycles (N=133) | Phase 2 Decitabine 35 mg, Cedazuridine 100 mg capsule/tablet All Cycles (N=80) | ||||
|---|---|---|---|---|---|---|
| Age (years) | ||||||
| Median (min, max) | 71 (44, 88) | 71 (32, 90) | ||||
| Gender (%) | ||||||
| Male | 65 | 76 | ||||
| Female | 35 | 24 | ||||
| Race (%) | ||||||
| Characteristic | Phase 3 Inqovi All Cycles (N=133) | Phase 2 Decitabine 35 mg, Cedazuridine 100 mg capsule/tablet All Cycles (N=80) | ||||
|---|---|---|---|---|---|---|
| White | 91 | 93 | ||||
| Black or African American | 3 | 3 | ||||
| Asian | 2 | 1 | ||||
| Other or Not Reported | 4 | 4 | ||||
| ECOG Performance Score - (%) | ||||||
| 0 | 41 | 44 | ||||
| 1 | 59 | 48 | ||||
| 2 | 0 | 9 | ||||
| Disease Category / IPSS - (%) | ||||||
| Low Risk | 8* | N/A | ||||
| INT-1 | 44 | 44 | ||||
| INT-2 | 20 | 24 | ||||
| High Risk | 16 | 11 | ||||
| CMML | 12 | 21 | ||||
| Prior HMA Therapya - (%) | ||||||
| Prior Azacitidine | 5 | 4 | ||||
| Prior Decitabine | 3 | 4 | ||||
| Transfusion Dependenceb - (%) | ||||||
| RBC Transfusion Dependence | 39 | 48 | ||||
| Platelet Transfusion Dependence | 8 | 15 | ||||
a One cycle only, per the Inclusion Criteria
b Defined as documentation of ≥ 2 units of transfusion within 56 days of the first day of study treatment.
CMML=chronic myelomonocytic leukemia; ECOG= Eastern Cooperative Oncology Group; HMA= hypomethylating agent; INT=Intermediate; IPSS=International Prognostic Scoring System; N/A=Not Applicable; RBC=red blood cell
* Phase 3 study was not stratified by IPSS risk group. Low risk MDS was eligible in the study by their FAB classification.
Efficacy was established based upon complete response (CR) and the rate of conversion from transfusion dependence to transfusion independence. (See Tables 10 and 11)
The primary outcome measure of the Phase 3 study was 5-day cumulative decitabine AUC between Inqovi and IV decitabine. Inqovi achieved AUC0-24hr exposures equivalent to IV infusion of decitabine at 20 mg/m2. The ratio of the geometric mean of the 5-day total decitabine AUC0-24hr between Inqovi and IV decitabine was 99% (90% confidence interval [CI] 93%; 106%) (See 10 CLINICAL PHARMACOLOGY, Pharmacokinetics).
The median follow-up in the Phase 3 study was 12.6 months (range, 9.3 to 20.5). The median treatment duration was 8.2 months (range 0.2 to 19.7). Twenty-seven (20%) of the 133 patients went on to stem cell transplantation following Inqovi treatment.
Table 10: Efficacy Results in Patients with MDS or CMML from Study ASTX727-02 (Phase 3)
| Efficacy Endpoints | Inqovi (N=133) |
| Complete Response (%) [95% CI]a | 21 [15, 29.0] |
| Median Duration of CR - months [range]b | 7.5 [1.6, 17.5] |
| Median Time to CR - months [range] | 4.3 [2.1, 15.2] |
a 2 of the 11 patients with low-risk MDS (18%) achieved CR
b From start of CR until relapse or death
Among the 57 patients who were dependent on red blood cell (RBC) and/or platelet transfusions at baseline, 30 (53%) became independent of RBC and platelet transfusions during any 56-day post-baseline period. Of the 76 patients who were independent of both RBC and platelet transfusions at baseline, 48 (63%) remained transfusion-independent during any 56-day post-baseline period.
In the Phase 2 study the median follow-up was 24 months (range, 12 to 28.8 months) and median treatment duration was 6.6 months (range <0.1 to 28). Twelve (15%) of the 80 patients went on to stem cell transplant following Inqovi treatment.
Table 11: Efficacy Results in Patients with MDS or CMML from Study ASTX727-01-B (Phase 2)
| Efficacy Endpoint | Decitabine 35 mg, Cedazuridine 100 mg capsule/tablet N=80 |
| Complete Response (%) [95% CI] | 18 [10, 28] |
| Median Duration of CR - months [range]a | 8.7 [1.1, 18.2] |
| Median Time to CR - months [range] | 4.8 [1.7, 10.0] |
a From start of CR until relapse or death
Among the 41 patients who were dependent on RBC and/or platelet transfusions at baseline, 20 (49%) became independent of RBC and platelet transfusions during any consecutive 56-day post-baseline period. Of the 39 patients who were independent of both RBC and platelet transfusions at baseline, 25 (64%) remained transfusion-independent during any consecutive 56-day post-baseline period.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Decitabine and cedazuridine were evaluated in mice, rats, and monkeys following administration of oral decitabine and cedazuridine, or both, and additional in vitro and in vivo genotoxicity studies were conducted with cedazuridine.
Carcinogenicity: Carcinogenicity studies were not conducted with decitabine and cedazuridine.
Genotoxicity: Decitabine was genotoxic. Decitabine increased mutation frequency in L5178Y mouse lymphoma cells, and mutations were produced in an Escherichia coli lac-I transgene in colonic DNA of decitabine-treated mice. Decitabine caused chromosomal rearrangements in larvae of fruit flies.
Cedazuridine was genotoxic in the Ames test and in a chromosome aberration assay in human lymphocytes.
Reproductive and Developmental Toxicology: In utero exposure to decitabine causes temporal related defects in the rat and/or mouse, which include growth suppression, exencephaly, defective skull bones, rib/sternabrae defects, phocomelia, digit defects, micrognathia, gastroschisis, and micromelia. Decitabine inhibits proliferation and increases apoptosis of neural progenitor cells of the fetal CNS and induces palatal cleft in the developing murine fetus. Studies in mice have also shown that decitabine administration during osteoblastogenesis (Day 10 of gestation) induces bone loss in offspring.
In mice exposed to single intraperitoneal (IP) decitabine injections (0, 0.9 and 3.0 mg/m2, approximately 2% and 7% of the recommended daily clinical dose, respectively) over gestation Days 8, 9, 10 or 11, reduced fetal survival was observed after treatment at 3 mg/m2 and decreased fetal weight was observed at both dose levels. The 3 mg/m2 dose elicited characteristic fetal defects for each treatment day, including supernumerary ribs (both dose levels), fused vertebrae and ribs, cleft palate, vertebral defects, hind-limb defects and digital defects of fore- and hind-limbs.
Rats were given a single IP injection of 2.4, 3.6 or 6 mg/m2 decitabine (approximately 5, 8, or 13% of the recommended daily clinical dose, respectively) on gestation Days 9-12. No live fetuses were seen at any dose when decitabine was injected on gestation Day 9. A significant decrease in fetal survival and reduced fetal weight was seen when decitabine was given on gestation Day 10.at doses greater than 3.6 mg/m2 Increased incidences of vertebral and rib anomalies were seen at all dose levels, and induction of exophthalmia, exencephaly, and cleft palate were observed at 6.0 mg/m2. Increased incidence of foredigit defects was seen in fetuses at doses greater than 3.6 mg/m2. Reduced size and ossification of long bones of the fore-limb and hind-limb were noted at 6.0 mg/m2.
The effect of decitabine on postnatal development and reproductive capacity was evaluated in mice administered a single 3 mg/m2 IP injection (approximately 7% the recommended daily clinical dose) on Day 10 of gestation. Body weights of males and females exposed in utero to decitabine were significantly reduced relative to controls at all postnatal time points. Untreated females mated to males exposed in utero showed decreased fertility at 3 and 5 months of age (36% and 0% pregnancy rate, respectively). Follow up studies indicated that treatment of pregnant mice with decitabine on gestation Day 10 was associated with a reduced pregnancy rate resulting from effects on sperm production in the F1-generation.
In male mice given IP injections of 0.15, 0.3 or 0.45 mg/m2 decitabine (approximately 0.3% to 1% the recommended clinical dose) 3 times a week for 7 weeks, testes weights were reduced, abnormal histology was observed and significant decreases in sperm number were found at doses ≥ 0.3 mg/m2. In females mated to males dosed with ≥ 0.3 mg/m2 decitabine, pregnancy rate was reduced, and preimplantation loss was significantly increased.
No reproductive or developmental toxicity studies were conducted with cedazuridine.