


Product Monograph - Eribulin Mesylate Injection (DR Reddy's Laboratories)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | All Non-medicinal Ingredients |
|---|---|---|
| Intravenous | Solution for injection: 0.5 mg/mL | dehydrated alcohol, hydrochloric acid, sodium hydroxide and water for injection. |
INDICATIONS AND CLINICAL USE
Eribulin Mesylate Injection is indicated for the treatment of patients with metastatic breast cancer who have previously received at least two chemotherapeutic regimens for the treatment of metastatic disease. Prior therapy should have included an anthracycline and a taxane administered in either the adjuvant or metastatic setting.
Eribulin Mesylate Injection is indicated for the treatment of adult patients with an unresectable advanced or metastatic liposarcoma subtype of soft tissue sarcoma. Prior therapy should have included an anthracycline-containing regimen, unless not clinically appropriate.
Geriatrics (> 65 years of age):
No dose adjustments are recommended based on the age of the patient (see WARNINGS AND PRECAUTIONS, Geriatrics (>65 years of age)).
Pediatrics (< 18 years of age):
The safety and effectiveness of eribulin mesylate in pediatric patients have not been established.
CONTRAINDICATIONS
Eribulin Mesylate Injection is contraindicated in patients with a history of hypersensitivity to eribulin mesylate or halichondrin B or its chemical derivatives.
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
|---|
Eribulin Mesylate Injection should be administered under the supervision of a physician experienced in the use of anti-cancer agents. |
|---|
Carcinogenesis and Mutagenesis
Carcinogenicity studies were not conducted with eribulin mesylate.
Eribulin mesylate was positive in mammalian genotoxicity studies (see TOXICOLOGY, Genotoxicity).
Cardiovascular
Eribulin mesylate is associated with QT/QTc interval prolongation (see WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests; DRUG INTERACTIONS; ACTION AND CLINICAL PHARMACOLOGY, Electrocardiography). Many drugs that cause QT/QTc prolongation are suspected to increase the risk of torsade de pointes. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Use of Eribulin Mesylate Injection in patients with congenital long QT/QTc syndrome should be avoided. The concomitant use of eribulin mesylate with another QT/QTc-prolonging drug should be avoided to the extent possible (see DRUG INTERACTIONS).
The safety of eribulin mesylate has not been established in patients with significant cardiovascular impairment (history of congestive heart failure New York Heart Association > Grade 2, unstable angina or myocardial infarction within the previous 6 months, or serious cardiac arrhythmia).
Hematologic
Myelosuppression is dose dependent and primarily manifested as neutropenia.
Febrile neutropenia occurred in 5% of patients receiving eribulin mesylate. Fatal outcome has been observed due to complications with neutropenia.
Patients should have Absolute Neutrophil Count (ANC) values ≥1,500 cells/mm3 and platelets 100,000/mm3 at the initiation of treatment with Eribulin Mesylate Injection. Frequent monitoring of complete blood counts should be performed on all patients receiving Eribulin Mesylate Injection. Patients should only be retreated with Eribulin Mesylate Injection when ANC is ≥1,000 cells/mm3, platelets are ≥75,000/mm3, and any other toxicity of a previous cycle has recovered to Grade ≤2 (except anemia) (see DOSAGE AND ADMINISTRATION).
Patients experiencing febrile neutropenia, severe neutropenia, or thrombocytopenia may require a subsequent reduction of the dose of Eribulin Mesylate Injection.
Patients with alanine aminotransferase (ALT) or aspartate aminotransferase (AST) >3 × the upper limit of normal (ULN) or bilirubin >1.5 × ULN experienced a higher incidence of Grade 4 neutropenia and febrile neutropenia. Reduction of the starting dose for patients with ALT or AST >3 x ULN or bilirubin >1.5 x ULN should be considered. These patients should be monitored closely for toxicity.
Neurologic
Grade 3 peripheral neuropathy occurred in 8% (40/503) of patients, and Grade 4 in 0.4% (2/503) of patients in a pivotal study. Peripheral neuropathy was the most common toxicity leading to discontinuation of eribulin mesylate (5% of patients; 24/503). Neuropathy lasting more than one year occurred in 5% (26/503) of patients. Twenty-two percent (109/503) of patients developed a new or worsening neuropathy that had not recovered by the end of their follow-up period (median follow-up duration = 269 days, range 25–662 days).
Monitor patients closely for signs of peripheral neuropathy. Dosage in patients experiencing peripheral neuropathy should be adjusted according to the recommendations in Table 5 (see DOSAGE AND ADMINISTRATION).
Eribulin Mesylate Injection may aggravate existing neuropathy and should be used with caution in patients with pre-existing neuropathy.
Special Populations
Pregnant Women:
Eribulin mesylate is a microtubule inhibitor, therefore, it is expected to cause fetal harm when administered to pregnant women. Embryo-fetal toxicity and teratogenicity occurred in pregnant rats that received eribulin mesylate at approximately half of the recommended human dose based on body surface area (see TOXICOLOGY). There are no adequate and well-controlled studies with eribulin mesylate in pregnant women. Women should be advised not to become pregnant when taking Eribulin Mesylate Injection, and should use effective contraception during and for at least 3 months after stopping treatment. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
Nursing Women:
It is not known whether eribulin mesylate is excreted into human milk. Because many drugs are excreted into human milk and because of the potential for serious adverse reactions to eribulin mesylate in nursing infants, breast feeding must be avoided.
Pediatrics (< 18 years of age):
The safety and effectiveness of eribulin mesylate in pediatric patients have not been established.
Geriatrics (> 65 years of age):
Among the 827 patients who received the recommended dose of eribulin mesylate in the Phase 2/3 breast cancer studies, 121 patients (15%) were >65 - 75 years of age and 17 patients (2%) were >75 years of age. The safety profile of eribulin mesylate in elderly patients (>65 years of age) was similar to that of patients ≤65 years of age. No dose adjustments are recommended based on the age of the patient.
Hepatic Impairment:
Patients with mild or moderate hepatic impairment should receive a reduced dose. The recommended dose for patients with mild hepatic impairment (Child-Pugh A) is 1.1 mg/m2. The recommended dose for patients with moderate hepatic impairment (Child-Pugh B) is 0.7 mg/m2. Eribulin mesylate was not studied in patients with severe hepatic impairment (Child-Pugh C); therefore, the use of Eribulin Mesylate Injection is not recommended in these patients (see DOSAGE AND ADMINISTRATION and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Renal Impairment:
A study evaluated the pharmacokinetics of eribulin in patients with moderate (creatinine clearance (CrCl): 30 to 50 mL/min) or severe (CrCl: 15 to <30 mL/min) renal impairment. Compared to patients with normal renal function (CrCl: > 80 mL/min), patients with moderate or severe renal impairment have 1.49-fold higher eribulin dose-normalized exposures. For patients with moderate or severe renal impairment (CrCl: 15 to 50 mL/min), a reduction of the dose to 1.1 mg/m2 is recommended. Caution and close monitoring of adverse reactions, particularly myelosuppression, is advised for patients with renal impairment. Eribulin mesylate has not been studied in patients with End Stage Renal Disease (ESRD) (see DOSAGE AND ADMINISTRATION, Dosage Adjustment in Special Populations and ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions).
Male Patients:
Male patients with breast cancer have not been investigated in the pivotal clinical study. The effects of eribulin mesylate on human fertility are unknown. Testicular toxicity has been observed in rats and dogs (see TOXICOLOGY). Male patients should seek advice on conservation of sperm prior to treatment because of the possibility of irreversible infertility due to therapy with Eribulin Mesylate Injection.
Monitoring and Laboratory Tests
Complete blood count (CBC) evaluation and liver function tests should be performed prior to each dose. The frequency of CBC monitoring should be increased in patients who develop Grade 3 or 4 cytopenias.
Electrolyte Monitoring:
Eribulin mesylate has been associated with an increased incidence of hypokalemia. Eribulin mesylate has also been associated with QT/QTc interval prolongation. Hypokalemia, hypocalcemia, and hypomagnesemia should be corrected prior to initiation of Eribulin Mesylate Injection. Serum potassium, calcium, and magnesium should be monitored periodically during treatment.
ECG Monitoring:
ECG monitoring is recommended in patients with risk factors for torsade de pointes, such as patients with cardiac disease (e.g., congestive heart failure, bradyarrhythmias), and patients on concomitant medications that prolong the QT interval, especially Class IA or III antiarrhythmics, (see WARNINGS AND PRECAUTIONS, Cardiovascular; DRUG INTERACTIONS; ACTION
AND CLINICAL PHARMACOLOGY, Electrocardiography).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
In Phase 2/3 monotherapy clinical trials of metastatic breast cancer and soft tissue sarcoma, eribulin mesylate has been administered to 1,963 patients with multiple tumor types, including 467 patients exposed to eribulin mesylate for 6 months or longer. The majority of the 1,963 patients were women (92%) with a median age of 55 years (range: 17 to 85 years). The racial and ethnic distribution was Caucasian (72%), Black (4%), Asian (9%), and other (3%).
The most common treatment-emergent adverse events (≥25%) reported in patients receiving eribulin mesylate in the metastatic breast cancer and soft tissue sarcoma populations combined were neutropenia, alopecia, peripheral neuropathy, asthenia/fatigue, nausea, and leukopenia.
The most common serious treatment-emergent adverse events (≥1%) reported in patients receiving eribulin mesylate were febrile neutropenia (2.8%), neutropenia (2.2%), and pyrexia (1.1%).
The most common treatment-emergent adverse event resulting in discontinuation of eribulin mesylate was peripheral neuropathy (2.6%).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
METASTATIC BREAST CANCER
In the pivotal randomized, controlled EMBRACE study (Study 305), 762 metastatic breast cancer patients were randomized (2:1) to receive either eribulin mesylate (1.4 mg/m2 on Days 1 and 8 of a 21-day cycle) or single agent treatment chosen by their physician (control group). Of the randomized patients, 750 were treated. A total of 503 patients received eribulin mesylate and 247 patients in the control group received Treatment of Physician’s Choice (TPC). In the control group, 97% of patients received chemotherapy (anthracyclines 10%, capecitabine 18%, gemcitabine 19%, taxanes 15%, vinorelbine 25%, other chemotherapies 10%) and 3% received hormonal therapy. The median duration of exposure was 118 days for patients receiving eribulin mesylate and 63 days for patients receiving control therapy.
Table 1 reports the most common non-hematologic treatment-emergent adverse events for eribulin mesylate and TPC occurring in at least 10% of patients in the EMBRACE Study. Development of severe peripheral neuropathy occurred in 8% of patients (Table 1). The most common adverse reactions leading to a clinical intervention were neutropenia, nausea, constipation, pyrexia, peripheral neuropathy, arthralgia/myalgia, anemia, back pain, headache and leukopenia.
Adverse reactions leading to discontinuation (eribulin mesylate = 13%, Treatment of Physician’s Choice = 15%) or dose reductions (eribulin mesylate = 17%, Treatment of Physician’s Choice = 16%) were comparable between the treatment groups.
Table 1: Non-hematologic Treatment-Emergent Adverse Events with an Incidence of at Least 10% of Patients with Metastatic Breast Cancer (Safety Population) in the EMBRACE Study (Study 305)
| MedDRA SOC and Preferred Terma | Eribulin Mesylate n=503 (%) | Treatment of Physician’s Choice n=247 (%) | ||||
|---|---|---|---|---|---|---|
| Total | Grade 3 | Grade ≥ 4 | Total | Grade 3 | Grade ≥ 4 | |
| Any Event | 99 | 36 | 33 | 93 | 34 | 20 |
| Gastrointestinal disorders | ||||||
| Nausea | 35 | 1 | 0 | 28 | 3 | 0 |
| Constipation | 25 | 1 | 0 | 21 | 1 | 0 |
| Diarrhea | 18 | 0 | 0 | 18 | 0 | 0 |
| Vomiting | 18 | 1 | <1 | 18 | 1 | 0 |
| General disorders and administrative site conditions | ||||||
| Asthenia / Fatigueb | 54 | 9 | 1 | 40 | 11 | 1 |
| Pyrexia | 21 | <1 | 0 | 13 | <1 | 0 |
| Mucosal inflammation | 9 | 1 | 0 | 10 | 2 | 0 |
| Investigations | ||||||
| Weight decreased | 21 | 1 | NA | 14 | <1 | NA |
| Metabolism and nutrition disorders | ||||||
| Anorexia | 20 | 1 | 0 | 13 | 1 | 0 |
| Musculoskeletal and connective tissue disorders | ||||||
| Arthralgia / Myalgia | 22 | <1 | 0 | 12 | 1 | 0 |
| Back pain | 16 | 1 | <1 | 7 | 1 | <1 |
| Bone pain | 12 | 2 | <1 | 9 | 2 | 0 |
| MedDRA SOC and Preferred Terma | Eribulin Mesylate n=503 (%) | Treatment of Physician’s Choice n=247 (%) | ||||
|---|---|---|---|---|---|---|
| Total | Grade 3 | Grade ≥ 4 | Total | Grade 3 | Grade ≥ 4 | |
| Pain in extremity | 11 | 1 | 0 | 10 | 1 | 0 |
| Nervous system disorders | ||||||
| Peripheral neuropathyc | 35 | 8 | <1 | 16 | 2 | 0 |
| Headache | 19 | <1 | 0 | 12 | 0 | <1 |
| Respiratory, thoracic, and mediastinal disorders | ||||||
| Dyspnead | 16 | 4 | 1 | 13 | 2 | 2 |
| Cough | 14 | 0 | NA | 9 | 0 | NA |
| Skin and subcutaneous tissue disorders | ||||||
| Alopeciae | 45 | NA | NA | 10 | NA | NA |
| Palmar-plantar erythrodysesthesia syndrome | 1 | <1 | 0 | 14 | 4 | 0 |
Abbreviations: CTCAE, NCI Common Terminology Criteria for Adverse Events (version 3.0); MedDRA, Medical Dictionary for Regulatory Activities; NA, not applicable (the CTCAE system does not have these grades for the event);
SOC, system organ class.
a Patients reporting >1 adverse event within a preferred term were counted only once for that preferred term. If an adverse event had >1 CTC grade, the highest CTC grade was used.
b Asthenia / Fatigue: Eribulin mesylate = Grade 4: 1%; Grade 5: 0%; TPC = Grade 4: <1%; Grade 5: <1%.
c This term includes the preferred terms neuropathy peripheral, neuropathy, peripheral motor neuropathy, polyneuropathy, peripheral sensory neuropathy, and paraesthesia.
d Dyspnea: Eribulin mesylate = Grade 4: 0%; Grade 5: 1%; TPC = Grade 4: 1%; Grade 5: 1%.
e Alopecia: Eribulin mesylate = Grade 1: 27%, Grade 2: 18%; TPC = Grade 1: 5%, Grade 2: 4%.
Abnormal Hematologic and Clinical Chemistry Findings
Hematologic adverse reactions from the EMBRACE Study are reported in Table 2. Hematologic toxicities resulted in discontinuation in <1% of patients receiving eribulin mesylate. Febrile neutropenia occurred in 5% of patients receiving eribulin mesylate.
Table 2: Hematologic Adverse Reactions Among Patients with Metastatic Breast Cancer (Safety Population) in the EMBRACE Study (Study 305)
Eribulin Mesylate (n=503) | Treatment of Physician’s Choice (n=247) | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Hematology Parameters | Any Grade % | Grade 3 % | Grade 4 % | Any Grade % | Grade 3 % | Grade 4 % | |||||||||
| Leukopenia | 88 | 31 | 5 | 64 | 12 | 2 | |||||||||
| Neutropenia | 82 | 29 | 29 | 54 | 14 | 9 | |||||||||
| Anemia | 78 | 2 | <1 | 73 | 4 | 0 | |||||||||
| Lymphopenia | 72 | 13 | 2 | 71 | 9 | 2 | |||||||||
| Thrombocytopenia | 20 | 1 | <1 | 29 | 1 | 2 | |||||||||
The neutropenia observed was generally reversible and not cumulative; the mean time to nadir within a cycle was approximately 13 days and the mean time to recovery from severe neutropenia (<500 cells/mm3) to neutropenia ≤ Grade 2 (≥1000 cells/mm3) was approximately 8 days.
The frequent laboratory abnormalities from the EMBRACE Study are reported in Table 3.
Table 3: Laboratory Abnormalities Among Patients with Metastatic Breast Cancer (Safety Population) in the EMBRACE Study (Study 305)
Eribulin Mesylate (n=503) | Treatment of Physician’s Choice (n=247) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Laboratory Abnormalities | Any Grade | Grade 3 % | Grade 4 % | Any Grade | Grade 3 % | Grade 4 % | ||||||||
| Aspartate Aminotransferase | 73 | 5 | <1 | 65 | 5 | 0 | ||||||||
| Alanine Aminotransferase | 61 | 3 | 0 | 50 | 2 | 0 | ||||||||
| Alkaline Phosphatase | 58 | 5 | 0 | 65 | 3 | 0 | ||||||||
| Albumin | 40 | 1 | 0 | 40 | 1 | 0 | ||||||||
| Hypokalemia | 38 | 4 | 1 | 15 | 2 | 1 | ||||||||
| Hypocalcemia | 35 | 1 | 2 | 25 | 1 | 3 | ||||||||
| Hypomagnesemia | 34 | 2 | 0 | 28 | 0 | 1 | ||||||||
| Hyponatremia | 32 | 3 | 3 | 25 | 5 | 2 | ||||||||
| Hypophosphatemia | 23 | 6 | 1 | 14 | 2 | 0 | ||||||||
| Hypercalcemia | 19 | <1 | 2 | 12 | <1 | 1 | ||||||||
| Hyperkalemia | 18 | <1 | 1 | 19 | 2 | 1 | ||||||||
| Hypermagnesemia | 17 | 4 | <1 | 13 | 2 | 0 | ||||||||
| Total Bilirubin | 15 | 1 | 0 | 21 | 2 | 0 | ||||||||
| Creatinine | 14 | 1 | 1 | 13 | 1 | 0 | ||||||||
The safety profile of eribulin mesylate in the other Phase 2 and Phase 3 studies was consistent with that observed in the randomized, active-controlled EMBRACE Study (Study 305).
Less Common Clinical Trial Treatment-Emergent Adverse Events (>3% to <10%)
Blood and Lymphatic System Disorders: Febrile neutropenia
Ear and Labyrinth Disorders: Vertigo
Eye Disorders: Lacrimation increased
Cardiac Disorders: Tachycardia
Gastrointestinal Disorders: Abdominal distension, abdominal pain, abdominal pain upper, dyspepsia, dry mouth, stomatitis
General Disorders and Administration Site Conditions: Edema peripheral, pain
Infections and Infestations: Nasopharyngitis, rhinitis, urinary tract infection, upper respiratory tract infection
Investigations: Alanine aminotransferase increased, aspartate aminotransferase increased, weight increased
Metabolism and Nutrition Disorders: Decreased appetite, hyperglycemia, hypokalemia, hypomagnesemia
Musculoskeletal and Connective Tissue Disorders: Muscle spasms, muscular weakness, musculoskeletal chest pain, musculoskeletal pain
Nervous System Disorders: Dizziness, dysgeusia, hypoesthesia, lethargy
Psychiatric Disorders: Anxiety, depression, insomnia
Respiratory, Thoracic, and Mediastinal Disorders: Pharyngolaryngeal pain
Skin and Subcutaneous Tissue Disorder: Pruritus, rash
Vascular Disorders: Hypertension
SOFT TISSUE SARCOMA
In the pivotal open-label randomized Phase 3 study (Study 309) in patients with soft tissue sarcoma (liposarcoma and leiomyosarcoma), the very common treatment-emergent adverse events (≥10%) reported in patients receiving eribulin mesylate are listed in Table 4:
Table 4: Treatment-Emergent Adverse Events with an Incidence of at least 10% in Patients with Soft Tissue Sarcoma (Safety Population) in Study 309
| System Organ Class/Preferred Term | Eribulin Mesylate Study 309 N=226 | Dacarbazine Study 309 N=224 | ||
|---|---|---|---|---|
| All Grades | Grades 3-4 | All Grades | Grades 3-4 | |
| Blood and Lymphatic Disorders | ||||
| Neutropenia | 43.8% | 35.4% | 23.7% | 15.6% |
| Anemia | 29.6% | 7.1% | 30.8% | 12.0% |
| Leukopenia | 15.9% | 10.2% | 10.3% | 3.5% |
| Nervous System Disorders | ||||
| Peripheral Neuropathya | 33.1% | 3.5% | 7.5% | 0.4% |
| Headache | 18.1% | 0 | 9.4% | 0 |
| General Disorders and Administration Site Conditions | ||||
| Asthenia / Fatigue | 64.6% | 3.1% | 61.2% | 1.3% |
| Pyrexia | 27.9% | 0.9% | 13.8% | 0.4% |
| Peripheral oedema | 11.9% | 0 | 7.6% | 0.4% |
| GI Disorders | ||||
| Constipation | 31.4% | 0.9% | 25.9% | 0.4% |
| Diarrhea | 16.8% | 0.4% | 16.1% | 0.8% |
| Nausea | 40.3% | 0.9% | 47.3% | 0.4% |
| Vomiting | 19.0% | 0.9% | 22.3% | 0.4% |
| Stomatitis | 13.7% | 0.9% | 4.9% | 0.4% |
| Abdominal painb | 28.3% | 2.7% | 21.8% | 4.0% |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Arthralgia / Myalgia | 18.6% | 0 | 13.4% | 0 |
| Back pain | 15.5% | 1.8% | 13.8% | 1.3% |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 19.0% | 0.4% | 19.2% | 0.9% |
| Hypokalaemia | 10.2% | 2.7% | 4.0% | 1.7% |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Coughc | 18.6% | 0 | 13.4% | 0 |
| Dyspnead | 16.8% | 0 | 18.3% | 0.4% |
| Skin and Subcutaneous Tissue Disorders | ||||
| Alopecia | 35.0% | N/Ae | 2.7% | N/Ae |
| Infections and Infestations | ||||
| Urinary Tract Infectionf | 11.5% | 2.6% | 6.3% | 0.4 |
a Includes the preferred terms peripheral motor neuropathy, peripheral sensorimotor neuropathy, peripheral sensory neuropathy, polyneuropathy and neuropathy peripheral.
b Includes the preferred terms abdominal pain, abdominal pain upper and abdominal pain lower.
c Includes the preferred terms cough and productive cough.
d Includes the preferred terms dyspnea and exertional dyspnea.
e Not applicable grading system does not specify > grade 2 for alopecia.
f Includes the preferred terms urinary tract infection and cystitis.
Less Common Clinical Trial Treatment-Emergent Adverse Events (≥3% to <10%) reported in Study 309
Blood and Lymphatic System Disorders: Thrombocytopenia
Eye Disorders: Lacrimation increased
Gastrointestinal Disorders: Abdominal distension, dry mouth, dyspepsia, gastroesophageal reflux disease.
General Disorders and Administration Site Conditions: Chills
Infections and Infestations: Upper respiratory tract infection, nasopharyngitis, pneumonia. Investigations: Alanine aminotransferase increased, aspartate aminotransaminase increased, electrocardiogram QT interval prolonged, blood lactate dehydrogenase increased, alkaline phosphatase increased, weight decreased.
Metabolism and Nutrition Disorders: Hyperglycemia, hypoalbuminemia, hypocalcemia, hypomagnesemia.
Musculoskeletal and Connective Tissue Disorders: Muscle spasms, muscular weakness, musculoskeletal chest pain, musculoskeletal pain, pain in extremity.
Nervous System Disorders: Dizziness, dysgeusia, somnolence.
Psychiatric Disorders: Anxiety, insomnia.
Renal and Urinary Disorders: Dysuria.
Respiratory, Thoracic and Mediastinal Disorders: Dysphonia, oropharyngeal pain, rhinorrhea.
Skin and Subcutaneous Disorders: Rash, pruritis
Vascular Disorders: Hypertension, hypotension.
Patients with soft tissue sarcoma who received eribulin mesylate in Study 309 reported a higher frequency of the following treatment-emergent hematologic and laboratory abnormalities: markedly low leukocytes, neutrophils, calcium, potassium and phosphorus levels and markedly high glucose, calcium, bilirubin and aspartate aminotransferase compared to those receiving dacarbazine.
Other serious adverse reactions in the 1,963 patients treated with eribulin mesylate not included above, and for which there is a possibility of a causal relationship to eribulin mesylate, include sudden death, pneumonia, sepsis (including neutropenic sepsis in some cases fatal), dehydration, renal failure, pulmonary embolism, and deep vein thrombosis.
Post-Market Adverse Drug Reactions
The following adverse drug reactions have been identified during post-approval of eribulin mesylate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and Lymphatic System Disorders: Disseminated intravascular coagulation (DIC)
Cardiac Disorders: Atrial fibrillation
Immune System Disorders: Drug hypersensitivity
Hepatobiliary Disorders: Hepatotoxicity
Gastrointestinal Disorders: Pancreatitis
Respiratory, Thoracic and Mediastinal Disorders: Interstitial lung disease
Skin and Subcutaneous tissue disorders: Stevens-Johnson syndrome, Toxic epidermal necrolysis
DRUG INTERACTIONS
Other QT/QTc Prolonging Drugs
The concomitant use of Eribulin Mesylate Injection with another QT / QTc-prolonging drug should be avoided to the extent possible. Drugs that have been associated with QT / QTc interval prolongation and / or torsade de pointes include, but are not limited to, the examples in the following list (Chemical / pharmacological classes are listed if some class members have been implicated in QT / QTc prolongation and / or torsade de pointes): Class IA antiarrhythmics, class III antiarrhythmics, class 1C antiarrhythmics; antipsychotics, antidepressants, opioids, macrolide antibiotics and analogues, quinolone antibiotics, antimalarials, azole antifungals, domperidone, 5-hydroxytryptamine (5-HT)3 receptor antagonists, tyrosine kinase inhibitors, histone deacetylase inhibitors, beta-2 adrenoceptor agonists.
Caution should be observed if Eribulin Mesylate Injection is used with drugs that can disrupt electrolyte levels, including, but not limited to, the following: loop, thiazide, and related diuretics; laxatives and enemas; amphotericin B; high dose corticosteroids.
Current information sources should be consulted for approved drugs that prolong the QT/QTc interval or cause electrolyte disturbances.
Drug-Drug Interactions
Effects of CYP3A4 inhibitors and inducers on Eribulin Mesylate
A pharmacokinetic (PK) study demonstrated that eribulin exposure (area under the curve and maximal concentration) was similar when eribulin mesylate was administered in combination with ketoconazole, a potent inhibitor of cytochrome P450 3A4 (CYP3A4), compared to administration of eribulin mesylate alone. A population PK analysis showed no effect of CYP3A4 inhibitors or inducers on eribulin exposure. Therefore, no drug-drug interactions are expected with CYP3A4 inhibitors or inducers.
Effects of transport protein inhibitors on Eribulin Mesylate
Non-clinical studies indicated that eribulin is a P-gp substrate (see DETAILED PHARMACOLOGY, Pharmacokinetics). A PK study demonstrated that eribulin exposure was similar when administered in combination with ketoconazole, an inhibitor of P-gp, compared to administration of eribulin alone. Eribulin is weakly metabolized and is mainly eliminated, unchanged, in feces and to a lower extent in urine. The contribution of P-gp to the biliary and renal excretion of eribulin is unknown. The transport proteins involved in the excretion of eribulin have not been identified but inhibition of transport proteins could in theory give rise to increased exposure to eribulin. Caution should be exercised when Eribulin Mesylate Injection is administered with inhibitors of transport proteins.
Effects of Eribulin Mesylate on Other Drugs
Eribulin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2D6, CYP2E1 or CYP3A4 or induce CYP1A2, CYP2C9, CYP2C19, or CYP3A4 enzymes at relevant clinical concentrations and is not expected to alter the plasma concentrations of other drugs that are substrates of these enzymes.
Drug-Lifestyle Interactions
No studies on the effects of eribulin mesylate on the ability to drive or use machines have been performed. Eribulin Mesylate Injection may cause side effects such as tiredness (fatigue) and dizziness, which may lead to a minor or moderate influence on the ability to drive or use machines. Patients should be advised not to drive and/or use machinery if they feel tired or dizzy.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
General Dosing Information
The recommended dose of Eribulin Mesylate Injection is 1.4 mg/m2 administered intravenously (IV) over 2 to 5 minutes on Days 1 and 8 of a 21-day cycle.
Patients should have Absolute Neutrophil Count (ANC) values ≥1,500 cells/mm3 and platelets 100,000/mm3 at the initiation of treatment with Eribulin Mesylate Injection.
Premedication with steroids and / or antihistamines to prevent hypersensitivity reactions is not required with the use of Eribulin Mesylate Injection. No special tubing is required for the IV administration of Eribulin Mesylate Injection.
Dosage Adjustment During Treatment
Assess for peripheral neuropathy and obtain complete blood cell counts prior to each dose.
Recommended dose delays
Do not administer Eribulin Mesylate Injection on Day 1 or Day 8 for any of the following:
|
|---|
The Day 8 dose may be delayed for a maximum of 1 week
|
|---|
Recommended dose reductions
If a dose has been delayed for toxicity and toxicities have recovered to Grade 2 severity or less, resume Eribulin Mesylate Injection at a reduced dose as set out in Table 5.
Do not re-escalate Eribulin Mesylate Injection dose after it has been reduced.
Table 5: Dose Adjustment Recommendations
| Event Description | Recommended Eribulin Mesylate Injection Dose | ||
|---|---|---|---|
| Permanently reduce the 1.4 mg/m2 Eribulin Mesylate Injection dose for any of the following: | 1.1 mg/m2 | ||
| ANC <500 cells/mm3 lasting >7 days | |||
| ANC <1,000 cells/mm3 with fever or infection | |||
| Platelets <25,000/mm3 | |||
| Platelets <50,000/mm3 requiring transfusion | |||
| Non-hematologic Grade 3 or 4 toxicities | |||
| Omission or delay of Day 8 Eribulin Mesylate Injection dose in previous cycle for toxicity | |||
| Occurrence of any event requiring permanent dose reduction while receiving 1.1 mg/m2 | 0.7 mg/m2 | ||
| Occurrence of any event requiring permanent dose reduction while receiving 0.7 mg/m2 | Discontinue Eribulin Mesylate Injection | ||
ANC= absolute neutrophil count.
Toxicities graded in accordance with National Cancer Institute (NCI) Common Terminology Criteria for Adverse Reactions (CTCAE) version 3.0.
Re-treatment criteria: Patients should only be re-treated with Eribulin Mesylate Injection when absolute neutrophil count (ANC) is ≥1,000 cells/mm3, platelets are ≥75,000/mm3, and any other toxicity of a previous cycle has recovered to Grade ≤2 (except anemia).
Dosage Adjustment in Special Populations
Patients with Hepatic Impairment
The recommended dose for patients with mild hepatic impairment (Child-Pugh A) is 1.1 mg/m2 administered IV on Days 1 and 8 of a 21-day cycle. The recommended dose for patients with moderate hepatic impairment (Child-Pugh B) is 0.7 mg/m2 administered IV on Days 1 and 8 of a 21-day cycle. Eribulin mesylate was not studied in patients with severe hepatic impairment (Child-Pugh C); therefore, the use of Eribulin Mesylate Injection is not recommended in these patients.
Patients with Renal Impairment
The recommended dose for patients with moderate or severe renal impairment (CrCl: 15 to 50 mL/min) is 1.1 mg/m2 administered intravenously over 2 to 5 minutes on Days 1 and 8 of a 21-day cycle. Eribulin mesylate was not studied in patients with End Stage Renal Disease (ESRD); therefore the use of Eribulin Mesylate Injection is not recommended in these patients.
Administration
Eribulin Mesylate Injection is a sterile, ready-to-use, clear, colorless aqueous solution for IV administration. Each vial contains 1 mg of eribulin mesylate as a 0.5 mg/mL solution in ethanol:water (5:95).
Eribulin Mesylate Injection solution should be aseptically withdrawn from the vial into a syringe and administered IV without dilution. Alternatively, Eribulin Mesylate Injection may be diluted in up to 100 mL 0.9% sodium chloride. Eribulin Mesylate Injection must not be mixed with other medicinal products.
Eribulin Mesylate Injection should not be diluted or administered through an intravenous line containing solutions with dextrose.
Eribulin Mesylate Injection is administered intravenously over 2 to 5 minutes.
No special tubing is required for the IV administration of Eribulin Mesylate Injection.
Good peripheral venous access or a patent central line should be ensured before administration. There is no evidence that eribulin mesylate is a vesicant or an irritant. In the event of extravasation, treatment should be symptomatic.
Parenteral solution should be inspected visually for clarity, particulate matter, precipitation, discoloration, leakage etc. prior to administration. Only clear solution without particles, precipitate or discoloration or leakage should be used. Unused portion should be discarded.
OVERDOSAGE
One case of overdose of eribulin mesylate has been reported. The patient inadvertently received 8.6 mg of eribulin mesylate (approximately 4 times the planned dose) and subsequently developed a hypersensitivity reaction (Grade 3) on Day 3 and neutropenia (Grade 3) on Day 7. Both adverse reactions resolved with supportive care.
There is no known antidote for eribulin mesylate overdose. In the event of an overdose, the patient should be closely monitored. Management of overdose should include supportive medical interventions to treat the presenting clinical manifestations.
For management of a suspected drug overdose, contact your regional poison control centre.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Eribulin is a microtubule dynamics inhibitor belonging to the halichondrin class of antineoplastic agents. Eribulin inhibits the growth phase of microtubule dynamics without affecting the shortening phase and sequesters tubulin into nonproductive aggregates. Eribulin exerts its anticancer effects via a tubulin-based antimitotic mechanism leading to G2/M cell-cycle block, disruption of mitotic spindles, and, ultimately, apoptotic cell death after prolonged and irreversible mitotic blockage.
In addition, eribulin treatment of human breast cancer cells caused changes in morphology and gene expression as well as decreased migration and invasiveness in vitro. In mouse xenograft models of human breast cancer, eribulin treatment was associated with increased vascular perfusion and permeability in the tumor cores, resulting in reduced tumor hypoxia, and changes in the expression of genes in tumor specimens associated with a change in phenotype.
Pharmacodynamics
Eribulin has in vivo antitumor activity in multiple human tumor xenografts in athymic mice, including breast cancer and soft tissue sarcomas.
Electrocardiography
The effect of eribulin mesylate on the electrocardiographic QT interval was assessed in an open-labelled, uncontrolled, multicentre, single-arm study in 26 patients with solid tumors who received treatment with 1.4 mg/m2 on Day 1 and Day 8 of a 21-day cycle. No effect on the QTc interval was observed on Day 1. On day 8 of treatment, QTc interval prolongation was evident. The largest mean increase from baseline was 10.5 msec (90% CI 4.9 to 16.2). The exposure to eribulin mesylate was similar on Day 1 and Day 8; therefore, differences in plasma concentration could not account for the delayed increase in the QTc interval.
Pharmacokinetics
The pharmacokinetics of eribulin is linear over the dose range of 0.25 mg/m2 to 4.0 mg/m2. Following 1.4 mg/m2 dose administration, the mean maximum plasma concentration (Cmax) ranged from 186 to 519 ng/mL and the mean exposure (AUC) ranged from 600 to 971 ng·hr/mL.
Distribution:
The pharmacokinetics of eribulin is characterized by a rapid distribution phase followed by a prolonged elimination phase, with a mean terminal half-life of approximately 40 hours. It has a large volume of distribution (43 to 114 L/m2) and low clearance (1.16 to 2.42 L/hr/m2). Eribulin exposure after multiple dosing is comparable to that following a single dose. No significant accumulation of eribulin is observed on weekly administration.
The plasma protein binding of eribulin is low. At 100 to 1,000 ng/mL eribulin, the protein binding of eribulin ranges from 49% to 65% in human plasma.
Metabolism:
Cytochrome P450 3A4 (CYP3A4) negligibly metabolizes eribulin in vitro. Eribulin inhibits CYP3A4 activity in human liver microsomes, but it is unlikely that eribulin will substantially increase the plasma levels of CYP3A4 substrates. Eribulin shows no induction potential for CYP1A, CYP2C9, CYP2C19, and CYP3A in primary human hepatocytes. No significant inhibition of CYP1A2, CYP2C9, CYP2C19, CYP2D6, or CYP2E1 was detected with eribulin concentrations up to 5 mcM in pooled human liver microsomes. No significant inhibition of CYP3A4 was detected with eribulin concentrations up to 1 mcM (730 ng/mL) in pooled liver microsomes. Therefore, it is unlikely that eribulin will affect plasma levels of drugs that are substrates of CYP enzymes.
Unchanged eribulin was the major circulating species in plasma following administration of 14C-eribulin to patients. Metabolite concentrations represented <0.6% of parent compound, confirming that there are no major human metabolites of eribulin.
Excretion:
Eribulin is eliminated primarily in feces unchanged. After administration of 14C-eribulin to patients, approximately 82% of the dose was eliminated in feces and 9% in urine, indicating that renal clearance is not a significant route of eribulin elimination. Unchanged eribulin accounted for approximately 88% and 91% of the radioactive materials recovered in feces and urine respectively. Eribulin is a substrate of the drug efflux transporter P-gp in vitro.
Special Populations and Conditions
Effects of Age, Gender, and Race
Based on a population pharmacokinetic analysis, gender, race, and age do not have a significant effect on the pharmacokinetics of eribulin.
Effects of Hepatic Impairments
A Phase 1 study evaluated the pharmacokinetics of eribulin in patients with mild (Child-Pugh A, n=7) and moderate (Child-Pugh B, n=4) hepatic impairment. Compared to patients with normal hepatic function (n=6), exposure to eribulin increased 1.75-fold and 2.79-fold in patients with mild and moderate hepatic impairment, respectively. Administration of eribulin mesylate at a dose of 1.1 mg/m2 and 0.7 mg/m2 to patients with mild and moderate hepatic impairment respectively resulted in similar exposure to eribulin as a dose of 1.4 mg/m2 to patients with normal hepatic function. Dose reduction to 1.1 mg/m2 is recommended for patients with mild (Child-Pugh A) and to 0.7 mg/m2 for patients with moderate hepatic impairment (Child-Pugh B). Eribulin mesylate was not studied in patients with severe hepatic impairment (Child-Pugh C).
Effects of Renal Impairments
The pharmacokinetics of eribulin were evaluated in a Phase 1 study in patients with normal renal function (CrCl: > 80 mL/min), moderate (CrCl: 30 to 50 mL/min) or severe (CrCl: 15 to <30 mL/min) renal impairment. Creatinine clearance estimates were calculated using the Cockcroft-Gault formula. Increase in dose-normalized Cmax was 1.31-fold (90% CI: 0.84-2.05) for moderate renal impairment and 2.02-fold (90% CI: 1.27-3.21) for severe renal impairment compared to normal renal function. Moderate and severe renal impairment increased mean dose-normalized AUC(0-inf) 1.49-fold (90% CI: 0.9-2.45) compared to normal renal function. Severity of renal impairment had no incremental effect on eribulin exposure. Eribulin mesylate has not been studied in patients with End Stage Renal Disease (ESRD). The recommended dose for patients with moderate or severe renal impairment (CrCl: 15 to 50 mL/min) is 1.1 mg/m2 administered intravenously over 2 to 5 minutes on Days 1 and 8 of a 21-day cycle.
STORAGE AND STABILITY
Store the vials in their original cartons. Store up to 25°C with excursions permitted to 30°C. Do not freeze.
Once withdrawn from the vial into a syringe, Eribulin Mesylate Injection (0.5 mg/mL) may be stored for up to 6 hours at ambient temperature and lighting or up to 24 hours under refrigeration. Diluted solutions of Eribulin Mesylate Injection (0.005 to 0.2 mg/mL in normal saline) may be stored for up to 48 hours refrigerated or for up to 24 hours at ambient temperature and lighting. Any unused portions of the vial should be discarded.
Diluted solutions of Eribulin Mesylate Injection (0.005 to 0.2 mg/mL in normal saline) are compatible with IV bags for up to 48 hours, refrigerated or for up to 24 hours at ambient temperature and lighting.
SPECIAL HANDLING INSTRUCTIONS
Procedures for proper handling and disposal of anticancer drugs should be followed. There is no general agreement that all of the procedures recommended in the guidelines are necessary or appropriate (ASHP guidelines 2006, OSHA Manual (Section VI, Chapter 2) 1999, Polovich et al. 2005, and NIOSH Alert 2004).
DOSAGE FORMS, COMPOSITION AND PACKAGING
Eribulin Mesylate Injection is a sterile, clear, colorless solution supplied in Type I, clear glass, single use vial, with 13mm teflon coated grey chlorobutyl rubber stopper and a light blue flip-off aluminum seal. The vial stopper is not made with natural rubber latex. It is available as one vial per carton. The drug product contains 1 mg eribulin mesylate per vial in 2 mL of solution. The eribulin mesylate solution concentration is 0.5 mg/mL.
Inactive ingredients: dehydrated alcohol USP (5% v/v), hydrochloric acid (for pH adjustment), sodium hydroxide (for pH adjustment), water for injection USP (95% v/v). Preservative free.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: eribulin mesylate
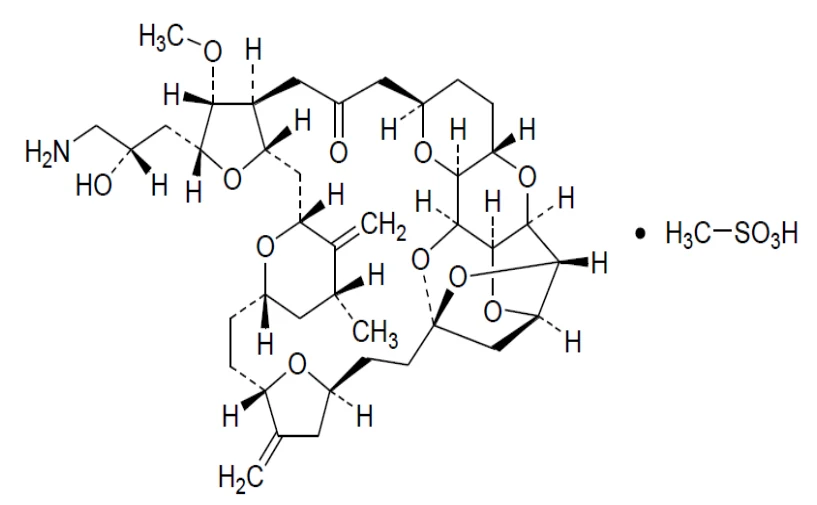
Chemical name: 11,15:18,21:24,28-Triepoxy-7,9-ethano-12,15-methano-9H,15H- furo[3,2-i]furo[2',3':5,6]pyrano[4,3-b][1,4] dioxacyclopentacosin-5(4H)-one, 2-[(2S)-3- amino-2-hydroxypropyl]hexacosahydro-3-methoxy-26-methyl-20,27-bis(methylene)-,(2R,3R,3aS,7R,8aS,9S,10aR, 11S,12R,13aR,13bS,15S,18S,21S,24S,26R,28R,29aS)-,methanesulfonate (salt)
Molecular formula and molecular mass:
Molecular formula: C40H59NO11 · CH4SO3
Molecular weight: 826.01 g / mol (729.90 for free base)
Structural formula:
Physicochemical properties: White to off-white solid and freely soluble in water and ethanol. In buffer solution of pH range from pH 1.2 to pH 8.0, eribulin mesylate was freely soluble.
CLINICAL TRIALS
METASTATIC BREAST CANCER
In an open-label, randomized, multicenter, multinational study of 762 patients with metastatic breast cancer (EMBRACE Study - Table 6), the efficacy and safety of eribulin mesylate were assessed in patients previously treated with a minimum of 2 and a maximum of 5 prior chemotherapy regimens (at least 2 for locally recurrent or metastatic disease), including an anthracycline and a taxane (unless contraindicated). Patients received a median of 4 prior chemotherapy regimens. Patients must have progressed within 6 months of their last chemotherapeutic regimen. Patients with pre-existing peripheral neuropathy Grade ≤2 were enrolled. Patients were randomized 2:1 to receive eribulin mesylate (1.4 mg/m2 on Days 1 and 8 in a 21-day cycle administered IV over 2 to 5 minutes) or Treatment of Physician’s Choice, defined as any single-agent chemotherapy, hormonal treatment, or biologic therapy approved for the treatment of cancer; or palliative treatment or radiotherapy, administered according to local practice, if applicable. The Treatment of Physician’s Choice arm consisted of chemotherapy for 97% of patients or hormonal therapy for 3% of patients. Patients were treated with a median of 5 cycles (range, 1 to 23 cycles) of eribulin mesylate therapy. The median relative dose intensity for eribulin mesylate was 91%.
Patient characteristics were well balanced across treatment arms. Select baseline patient and disease characteristics are summarized in Table 6.
Sixty-four percent of patients were enrolled from North America/Western Europe/Australia, 25% from Eastern Europe/Russia, and 11% from Latin America/South Africa.
Table 6: Patient and Baseline Disease Characteristics (ITT Population) (EMBRACE Study)
| Patient Characteristic | Eribulin Mesylate (n=508) | Treatment of Physician’s Choice (n=254) |
|---|---|---|
| Age (years) | ||
| Median (range) | 55 (28-85) | 56 (27-81) |
| Age (years) distribution, n (%) | ||
| <40 | 34 (7) | 17 (7) |
| >40 to <65 | 380 (75) | 180 (71) |
| >65 to <75 | 86 (17) | 51 (20) |
| >75 | 8 (2) | 6 (2) |
| Race, n (%) | ||
| 20 (4) | 14 (6) | |
| White | 470 (93) | 233 (92) |
| Asian/Pacific Islander | 3 (1) | 2 (1) |
| Other | 15 (3) | 5 (2) |
| ECOG performance status, n (%) | ||
| 0 | 217 (43) | 103 (41) |
| 1 | 244 (48) | 126 (50) |
| 2 | 39 (8) | 22 (9) |
| Patient Characteristic | Eribulin Mesylate (n=508) | Treatment of Physician’s Choice (n=254) |
|---|---|---|
| Not reported | 8 (2) | 3 (1) |
| Estrogen receptor status, n (%) | ||
| Positive | 336 (66) | 171 (67) |
| Negative | 143 (28) | 72 (28) |
| Unknown | 29 (6) | 11 (4) |
| Progesterone receptor status, n (%) | ||
| Positive | 254 (50) | 123 (48) |
| Negative | 197 (39) | 102 (40) |
| Unknown | 57 (11) | 29 (11) |
| HER2 receptor status, n (%) | ||
| Positive | 83 (16) | 40 (16) |
| Negative | 373 (73) | 192 (76) |
| Unknown | 52 (10) | 22 (9) |
| ER–, PR–, HER2–, n (%) | 93 (18) | 51 (20) |
| Number of prior chemotherapy regimens, n (%) | ||
| 1 Regimen | 1 (<1) | 0 (0) |
| 2 Regimens | 65 (13) | 31 (12) |
| 3 Regimens | 176 (35) | 83 (33) |
| 4 Regimens | 166 (33) | 79 (31) |
| 5 Regimens | 85 (28) | 51 (20) |
| >6 Regimens | 13 (3) | 9 (4) |
| Sites of involvement | ||
| Liver | 296 (59) | 159 (63) |
| Lung | 197 (39) | 95 (37) |
| Bone | 306 (60) | 158 (62) |
| Number of sites of metastases | ||
| <2 sites of metastases | 257 (51) | 117 (46) |
| >2 sites of metastases | 249 (49) | 137 (54) |
Abbreviations: ECOG, Eastern Cooperative Oncology Group, ER, estrogen receptor, HER2, human epidermal growth factor receptor 2, PR, progesterone receptor
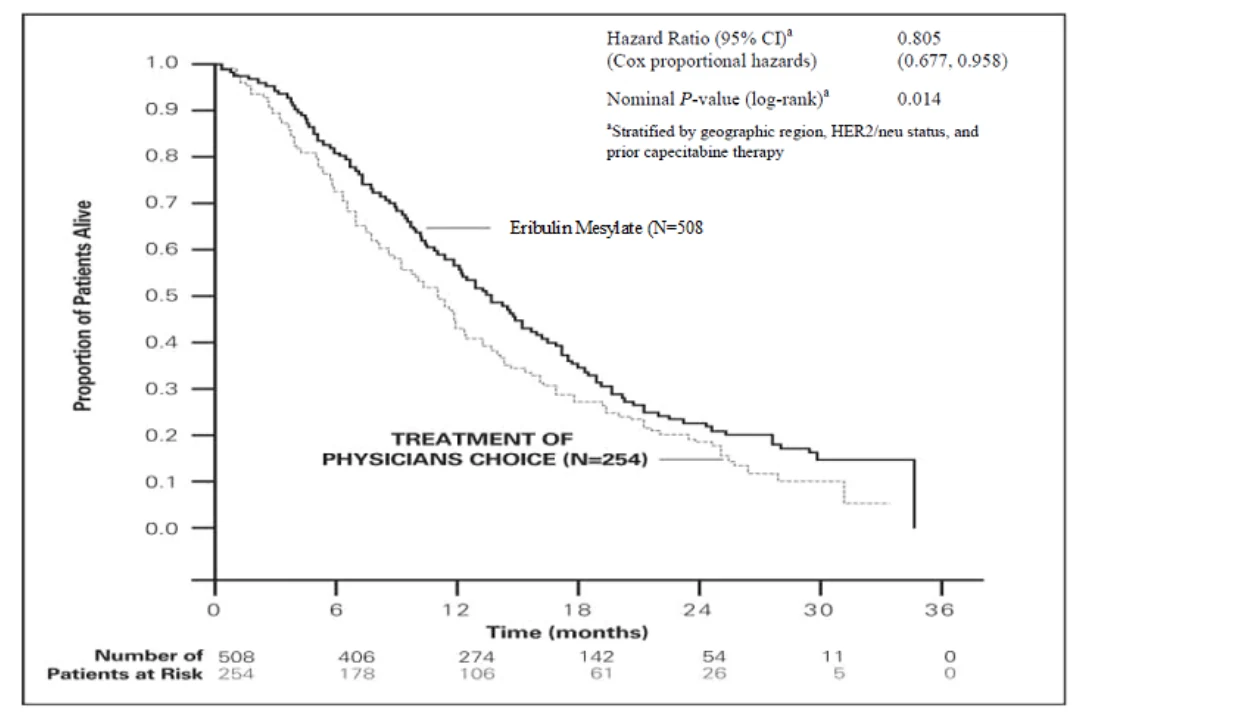
The primary endpoint of the study was overall survival. A statistically significant improvement in overall survival (OS) was observed in patients randomized to eribulin mesylate compared to Treatment of Physician’s Choice (Table 7). An improvement of 2.5 months median survival (hazard ratio (HR) 0.809, 95% CI: 0.660, 0.991, p=0.041) was demonstrated. The 1-year survival rates were 54% (95% CI: 0.492, 0.586) in patients randomized to eribulin mesylate and 44% (95% CI: 0.371, 0.502) in the Treatment of Physician’s Choice group. An updated survival analysis, conducted when 77% of events had been observed (Figure 1), was consistent with the primary analysis with an improvement in median overall survival of 2.6 months (HR 0.805, 95% CI: 0.677, 0.958, nominal p=0.014) observed in patients randomized to eribulin mesylate compared to Treatment of Physician’s Choice. In patients randomized to eribulin mesylate, the objective response rate by the RECIST criteria was 11% (95% CI: 8.6%, 14.3%) and the median response duration was 4.2 months (95% CI: 3.8, 5.0 months).
Table 7: Comparison of Overall Survival: Eribulin Mesylate vs Treatment of Physician’s Choice—ITT Analysis (EMBRACE Study)
| Efficacy Parameter | Eribulin Mesylate (n=508) | Treatment of Physician’s Choice (n=254) |
|---|---|---|
| Overall Survival | ||
| Number of deaths | 274 | 148 |
| Median, months (95% CI) | 13.1 months (11.8, 14.3) | 10.6 months (9.3, 12.5) |
| Hazard Ratio (95% CI)a | 0.809b (0.660, 0.991) | |
| P valuec | 0.041 | |
| Updated survival analysis | ||
| Number of deaths | 386 | 203 |
| Median, months (95% CI) | 13.2 (12.1, 14.4) | 10.6 (9.2, 12.0) |
| Hazard Ratio (95% CI)a | 0.805 (0.677, 0.958) | |
| P valuec | 0.014 | |
Abbreviations: CI, confidence interval; HER2, human epidermal growth factor receptor 2; ITT, intent to treat.
a Based on a Cox proportional hazards model stratified by geographic region, HER2 status, and prior capecitabine therapy.
b For the hazard ratio, a value less than 1.00 favors treatment with eribulin mesylate.
c Based on a log-rank test stratified by geographic region, HER2 status, and prior capecitabine therapy.
Figure 1: Updated Overall Survival Analysis—ITT Analysis (EMBRACE Study)
LIPOSARCOMA
Patients in the pivotal open-label randomized Phase 3 study (Study 309) had locally recurrent or metastatic soft tissue sarcoma of 1 of 2 histology subtypes – leiomyosarcoma or liposarcoma. Patients had received at least two prior chemotherapy regimens, one of which must have been an anthracycline (unless contraindicated).
Patients must have progressed within 6 months of their last chemotherapeutic regimen. A total of 452 patients were randomized 1:1 to receive eribulin mesylate 1.4 mg/m2 administered intravenously on Days 1 and 8 of a 21-day cycle or dacarbazine 850 mg/m2, 1000 mg/m2 or 1200 mg/m2 administered intravenously, every 21 days (dose determined by the investigator prior to randomization). Dacarbazine is not market authorized for treatment of soft tissue sarcoma. The median age was 56 years (range: 24 to 83); 67% were female and 33% were male; the majority (66%) of patients had leiomyosarcoma while only 34% had liposarcoma.
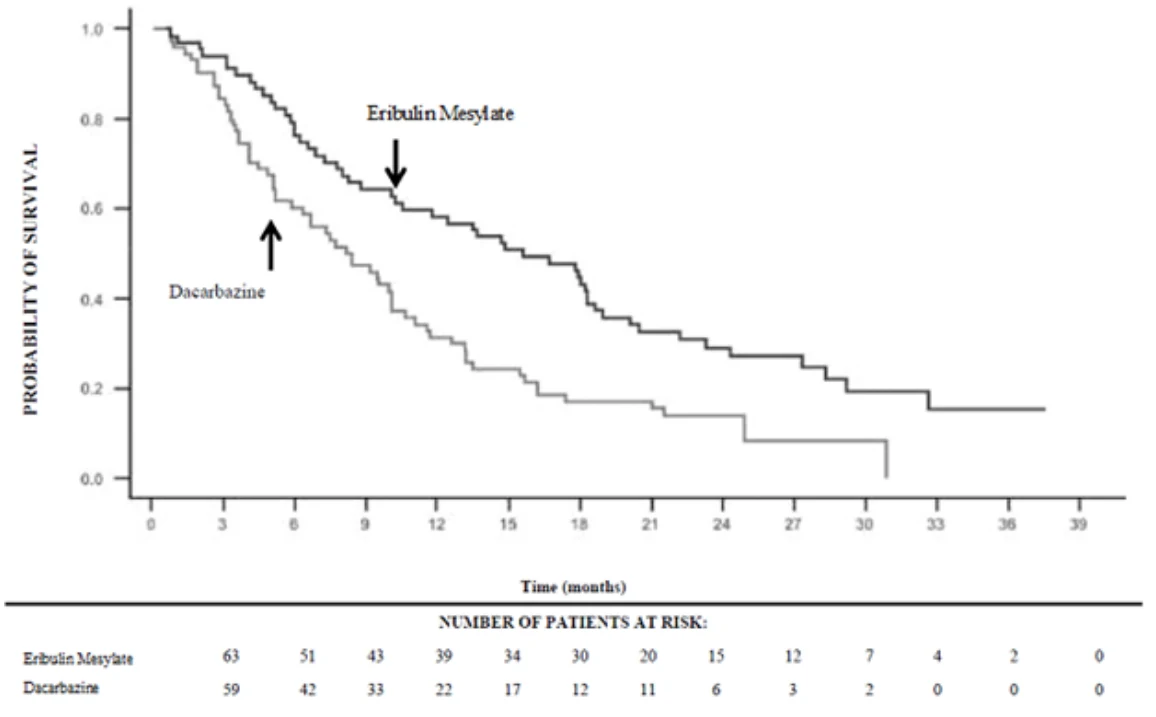
The primary efficacy endpoint was overall survival (OS) and main secondary endpoint was progression free survival (PFS). A statistically significant improvement (p=0.0169) of 2 months in median OS was observed in patients randomized to the eribulin mesylate arm compared to the dacarbazine arm (13.5 months for eribulin mesylate vs. 11.5 months for dacarbazine), with a HR of 0.768 (95% CI 0.618, 0.954) (see Figure 2). Based on preplanned exploratory subgroup analyses, the benefit of eribulin mesylate was limited to patients with liposarcoma (median OS 15.6 months for eribulin mesylate vs. 8.4 months for dacarbazine) with a HR of 0.51 (95% CI 0.346, 0.753, p=0.0006); there was no evidence of benefit in patients with leiomyosarcoma (see Table 8).
Table 8: Comparative Efficacy Results for Patients Treated with Eribulin Mesylate in Study 309
| Study 309 Liposarcoma Subgroup | Study 309 Leiomyosarcoma Subgroup | Study 309 ITT Population | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Eribulin Mesylate (n=71) | Dacarbazine (n=72) | Eribulin Mesylate (n=157) | Dacarbazine (n=152) | Eribulin Mesylate (n=228) | Dacarbazine (n=224) | ||||||||||||
| Overall survival | |||||||||||||||||
| Number of Events | 52 | 63 | 124 | 118 | 176 | 181 | |||||||||||
| Median months | 15.6 | 8.4 | 12.7 | 13.0 | 13.5 | 11.5 | |||||||||||
Hazard Ratio (95% CI) | 0.511 (0.346, 0.753) | 0.927 (0.714, 1.203) | 0.768 (0.618, 0.954) | ||||||||||||||
| Nominal p-value | 0.0006 | 0.5730 | 0.0169 | ||||||||||||||
| Progression-free survival | |||||||||||||||||
| Number of Events | 57 | 59 | 140 | 129 | 197 | 188 | |||||||||||
| Median months | 2.9 | 1.7 | 2.2 | 2.6 | 2.6 | 2.6 | |||||||||||
Hazard Ratio (95% CI) | 0.521 (0.346, 0.784) | 1.072 (0.835, 1.375) | 0.877 (0.710, 1.085) | ||||||||||||||
| Nominal p-value | 0.0015 | 0.5848 | 0.2287 | ||||||||||||||
Figure 2: Overall Survival in the Liposarcoma Subgroup (Study 309)
DETAILED PHARMACOLOGY
Animal
Pharmacodynamics
Results of in vitro studies demonstrate that addition of eribulin mesylate inhibits cell growth with sub- to low-nmol/L half-maximal inhibitory concentration (IC50) values in a wide range of established human cancer cell lines, including breast, colon, prostate, ovarian, small cell lung, and non-small cell lung cancers, as well as histiocytic lymphoma, promyelocytic leukemia, pharyngeal squamous cell (head and neck cancer) carcinoma, melanoma, and adult and pediatric soft tissue sarcomas. Eribulin mesylate exerts its anticancer effects via a tubulin-based antimitotic mechanism, leading to G2/M (Gap 2/mitosis stages of cell cycle) cell cycle blocks, disruption of mitotic spindles, and ultimately apoptotic cell death after prolonged mitotic blockage. Eribulin mesylate leads to inhibition of microtubule growth and formation of non- productive tubulin aggregates, but without effects on microtubule shortening.
Eribulin mesylate retained undiminished in vitro activity against a cancer cell line that was taxane-resistant due to β-tubulin mutations. Eribulin mesylate is a substrate for the P-gp drug efflux pump, and showed reduced in vitro potency against a human cancer cell line expressing P-gp.
Electrophysiological Systems
Intravenous infusion over 1 hour of eribulin mesylate at 0.04 mg/kg (0.8 mg/m2) in dogs resulted in transiently decreased systolic, diastolic and mean arterial pressure and heart rate, and increased RR interval but no effects on other ECG parameters were observed for up to 8 hours post-dose. The estimated maximal plasma concentrations achieved in the cardiovascular safety pharmacology studies were approximately 6% of the clinical Cmax.
Evaluation of potential cardiac effects in vitro were conducted at concentrations far exceeding (>300 times) the clinical Cmax concentrations. In vitro, eribulin at concentrations up to
30 mcmol/L did not inhibit hERG activity in stably transfected HEK293 cells and had no effects on the cardiac action potential parameters in isolated dog Purkinje fibers.
Central Nervous System and Respiratory Systems
Administration of eribulin mesylate by a slow bolus intravenous injection at 0.1 or 0.25 mg/kg produced no notable effects on the central nervous or respiratory systems in male rats.
Pharmacokinetics
Eribulin is eliminated primarily by biliary excretion. The transport protein involved in the excretion is presently unknown. Preclinical studies indicate that eribulin is transported by P-gp. However, it is unknown whether P-gp is contributing to the biliary excretion of eribulin.
TOXICOLOGY
Repeated-dose Toxicity
Intravenous repeated-dose toxicity studies were conducted in F344 rats and beagle dogs. In these studies, eribulin mesylate was administered three times with 4-day (Q4D×3) or 7-day (Q7D×3) intervals. In the 6-month chronic toxicity studies in rats and dogs, the dosing schedule of Q7D×3 followed by a 14-day recovery period was repeated in six cycles. In these studies, eribulin mesylate was administered to rats by slow bolus injection and to dogs as a 1-hour intravenous infusion. The dose-limiting toxicity precluded administration on a repeated basis of doses exceeding the clinical recommended dose (1.4 mg/m2 of eribulin mesylate administered IV over 2 to 5 minutes). At the doses that could be administered, plasma concentrations in animals were lower than the clinical exposure.
The antiproliferative activity of eribulin mesylate was associated with bone marrow, lymphoid and testicular toxicity in all of the Q4D×3 and Q7D×3 repeated-dose toxicity studies in both rats and dogs. In dogs, emesis, diarrhea as well as necrosis and hyperplasia in the crypts/glands of the small and large intestine occurred at lethal doses (0.075 mg/kg [1.5 mg/m2] Q4Dx2). Bone marrow toxicity and/or gastro-intestinal toxicity appeared to be the dose-limiting toxicity of eribulin mesylate. Bone marrow toxicity included a decreased number of hematopoietic cells, resulting in reduced peripheral blood cell counts and histologically visible bone marrow hypocellularity. These bone marrow alterations were often accompanied by compensatory extramedullary hematopoiesis in the spleen. The lowest doses at which bone marrow toxicity appeared in the repeated-dose toxicity studies were 0.05 mg/kg (0.30 mg/m2) in rats and
0.03 mg/kg (0.60 mg/m2) in dogs. Lymphoid toxicity, represented by a decreased circulating lymphocyte count and/or atrophy of the lymphoid organs was noted at doses of ≥0.60 mg/m2 (≥0.10 mg/kg in rats and ≥0.03 mg/kg in dogs) in the Q7D×3 and Q4D×3 studies. Bone marrow and lymphoid toxicity were reversible, with recovery underway or completed within 26 days post-dosing during the post-dosing observation period in the Q4D×3 and Q7D×3 toxicity studies, in both rats and dogs. Testicular toxicity included the macroscopic findings of soft and/or small testes and decreased testicular weight. Histological observations in the testes included hypocellularity or degeneration of the seminiferous tubules. These changes were associated with secondary epididymal hypospermia/aspermia. Testicular toxicity occurred at ≥0.05 mg/kg (0.30 mg/m2) in rats and 0.045 mg/kg (0.90 mg/m2) in dogs. In the rat, testicular degeneration noted at necropsy was generally more severe 14 to 26 days after the last dose than 3 days post dose. This may be related to the failure of the damaged cells to divide and suggests that the testicular damage may be irreversible. It may also be a reflection of insufficient recovery time since the duration of the spermatogenic cycle in rats is 48-52 days.
Degeneration of myocytes and neurofiber degeneration of the sciatic nerve were also observed in rats at doses of ≥0.20 mg/kg (1.20 mg/m2) in the Q4D×3 and Q7D×3 studies, respectively. These effects may appear as neuropathy and/or myalgia in humans. Although degeneration of myocytes disappeared by Day 35 (26 days post dose), fiber degeneration of sciatic nerve was still present on Day 29 (14 days post dose). There was one male rat at the high dose (0.15 mg/kg [0.90 mg/m2]) in the chronic toxicity study with neurofiber degeneration. Six month studies (Q7Dx3 IV administration followed by 14 non-dosing days for 6 cycles) did not identify any unexpected toxicity at the dose administered (up to 0.90 mg/m2 in rats and dogs). Focal and multifocal necrosis in the liver of male rats in the chronic rat study were attributed to bacterial infections and considered secondary to the effects of eribulin on bone marrow.
Genotoxicity
Eribulin mesylate was non-mutagenic in the Ames test, both with and without exogenous metabolizing system (S9). Eribulin mesylate was weakly positive in the mouse lymphoma tk assay in both activated and non-activated cultures. In the in vivo rat micronucleus assay, eribulin mesylate showed some evidence of genotoxic activity, forming substantially larger micronuclei than those seen with cyclophosphamide. The generally large-sized micronuclei induced by eribulin mesylate were consistent with interference or disruption of chromosome segregation rather than to a clastogenic action resulting in chromosome breakage.
Reproductive and Developmental Toxicity
The effects of eribulin mesylate on pregnancy and embryo-fetal development were evaluated by intermittent administration during the mid-organogenesis period in rats. The dose of 0.10 mg/kg (0.60 mg/m2) and higher exhibited embryo-fetal lethality with reduced fetal body weight. The dose of 0.15 mg/kg (0.90 mg/m2) induced external and/or soft tissue anomalies (absence of lower jaw, tongue, stomach and spleen) and early delivery.
Other Toxicity Studies
In vitro myelotoxicity studies were performed in bone marrow cells (CFU-GM) of mouse, dog and human using Hipple’s soft agar assay. Bone marrow cells were incubated with eribulin mesylate at concentrations of 0, 0.01, 0.1, 1, 10 and 100 nmol/L. The inhibition of CFU-GM colony formation was measured, and the concentrations that caused inhibition of colony formation were calculated by a regression analysis where possible. The mean IC90 were 63.1, 19.8, and 21.85 nmol/L in mice, dogs, and human, respectively.
Similar in vitro HALO (hemotoxicity assays via luminescence output) studies were performed with bone marrow multipotential stem cells (CFC-GEMM) of mouse, dog and human. Bone marrow cells were incubated with eribulin mesylate and comparators (paclitaxel and vinblastine) at concentrations of 0.1 to 1000 nmol/L. The murine CFC-GEMM cells appeared to be less sensitive to the antiproliferative effects of eribulin mesylate, whereas human and canine cells appeared to be equally sensitive. The IC50 values of eribulin mesylate were 148, 11.4 and 15.9 nmol/L in mice, dogs and human, respectively. Species sensitivity to eribulin mesylate- caused toxicity can be ranked as follows: dog ≥ human > mouse.
REFERENCES
- 1. American Society of Health-System Pharmacists. ASHP guidelines on handling hazardous drugs. Am J Health-Syst Pharm. 2006;63:1172-1193.
- 2. Cortes J, O'Shaughnessy J, Loesch D, Blum JL, Vahdat LT, Petrakova K, Chollet P, Manikas A, Diéras V, Delozier T, Vladimirov V, Cardoso F, Koh H, Bougnoux P, Dutcus CE, Seegobin S, Mir D, Meneses N, Wanders J, Twelves C. Eribulin monotherapy versus treatment of physician's choice in patients with metastatic breast cancer (EMBRACE): a phase 3 open-label randomised study. Lancet. 2011 Mar 12;377(9769):914-23.
- 3. Cortes J, Vahdat L, Blum JL, Twelves C, Campone M, Roché H, Bachelot T, Awada A, Paridaens R, Goncalves A, Shuster DE, Wanders J, Fang F, Gurnani R, Richmond E, Cole PE, Ashworth S, Allison MA. Phase II study of the halichondrin B analog eribulin mesylate in patients with locally advanced or metastatic breast cancer previously treated with an anthracycline, a taxane, and capecitabine. J Clin Oncol. 2010 Sep 1;28(25):3922-8.
- 4. Funahashi Y, Okamoto K, Adachi Y, Semba T, Uesugi M, Ozawa Y, et al. Eribulin mesilate reduces tumor microenvironment abnormality by vascular remodeling in preclinical human breast cancer models. Cancer Sci. 2014;105(10):1334-42.
- 5. Jordan MA, Kamath K, Manna T, Okouneva T, Miller HP, Davis C, et al. The primary antimitotic mechanism of action of the synthetic halichondrin E7389 is suppression of microtubule growth. Mol Cancer Ther. 2005;4(7):1086-95.
- 6. Kamath K, Jordan MA. Suppression of microtubule dynamics by epothilone B is associated with mitotic arrest. Cancer Res. 2003;63:6026-31.
- 7. Kuznetsov G, Towle MJ, Cheng H, Kawamura T, TenDyke K, Liu D, et al. Induction of morphological and biochemical apoptosis following prolonged mitotic blockage by halichondrin B macrocyclic ketone analog E7389. Cancer Res. 2004;64(16):5760-5766.
- 8. OSHA Technical Manual, TED 1-0.15A, Section VI: Chapter 2. Controlling Occupational Exposure to Hazardous Drugs. OSHA, 1999. http://www.osha.gov/dts/osta/otm/otm_vi/otm_vi_2.html
- 9. Panda D, Jordan MA, Chu KC, Wilson L. Differential effects of vinblastine on polymerization and dynamics of opposite microtubule ends. J Biol Chem. 1996;47:29807-12.
- 10. Polovich M, White JM, Kelleher LO. (eds.) 2005. Chemotherapy and biotherapy guidelines and recommendations for practice (2nd ed.) Pittsburgh, PA: Oncology Nursing Society.
- 11. Preventing Occupational Exposures to Antineoplastic and Other Hazardous Drugs in Health Care Settings. NIOSH Alert 2004;165.
- 12. Schöffski P, Chawla S, Maki RG, Italiano A, Gelderblom H, Choy E, et al. Eribulin versus dacarbazine in previously treated patients with advanced liposarcoma or leiomyosarcoma: a randomised, open-label, multicentre, phase 3 trial. Lancet 2016; 387: 1629–37.
- 13. Smith JA, Wilson L, Azarenko O, Zhu X, Lewis BM, Littlefield BA, et al. Eribulin binds at microtubule ends to a single site on tubulin to suppress dynamic instability. Biochemistry. 2010;49(6):1331-1337.
- 14. Tan-Chiu E, Wright J, Tan AR, Dacosta NA, Chuang E, Smith J, O'Shaughnessy J, Shuster DE, Meneses NL, Chandrawansa K, Fang F, Cole PE, Ashworth S, Blum JL. Phase II study of eribulin mesylate, a halichondrin B analog, in patients with metastatic breast cancer previously treated with an anthracycline and a taxane. J Clin Oncol. 2009 Jun 20;27(18):2954-61.
- 15. Towle MJ, Salvato KA, Budrow J, Wels BF, Kuznetsov G, Aalfs KK, et al. In vitro and in vivo anticancer activities of synthetic macrocyclic ketone analogues of halichondrin B. Cancer Res. 2001;61(3):1013-1021.
- 16. Towle MJ, Salvato KA, Wels BF, Aalfs KK, Zheng W, Seletsky BM, et al. Eribulin induces irreversible mitotic blockade: implications of cell-based pharmacodynamics for in vivo efficacy under intermittent dosing conditions. Cancer Res. 2011;71(2):496-505.
- 17. Yoshida T, Ozawa Y, Kimura T, Sato Y, Kuznetsov G, Xu S, et al. Eribulin mesilate suppresses experimental metastasis of breast cancer cells by reversing phenotype from epithelial- mesenchymal transition (EMT) to mesenchymal-epithelial transition (MET) states. Br J Cancer. 2014;110(6):1497-505.
- 18. PrHALAVEN® (eribulin mesylate) Solution for Injection 0.5 mg/mL, submission control number 197739, Product Monograph, Eisai Limited. AUG 04, 2017