


Product Monograph - Inderal Injectable Liq 1mg/mL
INDICATIONS
INDERAL (propranolol hydrochloride) is indicated in the following conditions:
- 1.
Hypertension
INDERAL (propranolol hydrochloride) is indicated in the treatment of hypertension. It is usually used in combination with other drugs, particularly a thiazide diuretic. INDERAL can, however, in certain patients, be used alone or as an initial agent in those patients in whom, in the judgement of the physician, treatment should be started with a beta-blocker rather than a diuretic. The combination of INDERAL with thiazide-like diuretics and/or peripheral vasodilators has been shown to be compatible and generally more effective than
INDERAL alone. Experience with most commonly used antihypertensive agents has not suggested evidence of incompatibility.
INDERAL by itself is not recommended for the emergency treatment of hypertensive crises.
It is however sometimes used as an adjunct to counteract the unwanted effect (tachycardia)
of the primary agents used in these situations.
- 2.
Angina Pectoris
INDERAL is indicated for the prophylaxis of angina pectoris.
- 3. Cardiac Arrhythmias
- a)
Supraventricular arrhythmias
(i) Paroxysmal atrial tachycardias, particularly those arrhythmias induced by catecholamines or digitalis or associated with Wolff-Parkinson-White syndrome (see
W-P-W under "Warnings").
(ii) Persistent sinus tachycardia which is non-compensatory and impairs the well-being of the patient.
(iii) Tachycardias and arrhythmias due to thyrotoxicosis when causing distress or increased hazard and when immediate effect is necessary as adjunctive, short-term
(2-4 weeks) therapy. May be used with, but not in place of, specific therapy (see
Thyrotoxicosis under "Warnings").
(iv) Persistent atrial extrasystoles which impair the well-being of the patient and do not respond to conventional measures.
(v) Atrial flutter and fibrillation when ventricular rate cannot be controlled by digitalis alone, or when digitalis is contraindicated.
(b) Ventricular tachycardia
Ventricular arrhythmias do not respond to INDERAL as predictably as do the supraventricular arrhythmias.
(i) With the exception of ventricular tachycardia induced by catecholamines or digitalis,
INDERAL is not the drug of first choice. In critical situations when cardioversion techniques or other drugs are not indicated or are not effective, INDERAL may be considered. If after consideration of the risks involved, INDERAL is used, it should be given intravenously in low dosage and very slowly. (See Intravenous under
"Dosage and Administration").
(ii) Persistent premature ventricular extrasystoles which do not respond to conventional measures and impair the well-being of the patient.
- c)
Tachyarrhythmias of digitalis intoxication
If digitalis-induced tachyarrhythmias persist following discontinuance of digitalis and correction of electrolyte abnormalities, they are usually reversible with oral INDERAL.
Severe bradycardia may occur, (see "Symptoms and Treatment of Overdosage").
Intravenous INDERAL is reserved for life-threatening arrhythmias. Temporary maintenance with oral therapy may be indicated. (See "Dosage and Administration").
- d)
Resistant tachyarrhythmias due to excessive catecholamine action during anesthesia.
Tachyarrhythmias due to excessive catecholamine action during anesthesia may sometimes arise because of release of endogenous catecholamines or administration of catecholamines.
When usual measures fail in such arrhythmias, INDERAL may be given intravenously to abolish them. All general inhalation anesthetics produce some degree of myocardial depression. Therefore when INDERAL is used to treat arrhythmias during anesthesia, it should be used with extreme caution and constant ECG and central venous pressure monitoring. In patients during anesthesia with agents that require catecholamine release for maintenance of adequate cardiac function, beta blockage will impair the desired inotropic effect. Therefore INDERAL should be titrated carefully when administered for arrhythmias occurring during anesthesia.
- 4.
Post-Myocardial Infarction
INDERAL is indicated for the reduction of cardiovascular mortality in patients who have survived the acute phase of a myocardial infarction and who are clinically stable. In the study which showed this benefit, treatment with INDERAL began between 5 and 21 days after the acute phase. Data are not available as to whether benefit would ensue if the therapy is initiated later.
- 5.
Migraine
INDERAL is indicated for the prophylaxis of migraine headache. It is not indicated for the treatment of acute migraine attacks.
- 6.
Essential Tremor
INDERAL is indicated in the management of essential tremor.
- 7.
Hypertrophic Subaortic Stenosis
INDERAL is useful in the management of hypertrophic subaortic stenosis, especially for treatment of exertional or other stress-induced angina, palpitations, and syncope. INDERAL also improves exercise performance. The effectiveness of INDERAL in this disease appears to be due to a reduction of the elevated outflow pressure gradient which is exacerbated by beta-adrenergic receptor stimulation. Clinical improvement may be temporary.
- 8.
Pheochromocytoma
After primary treatment with an alpha-adrenergic blocking agent has been instituted,
INDERAL may be useful as adjunctive therapy if the control of tachycardia becomes necessary before or during surgery.
It is hazardous to use INDERAL unless alpha-adrenergic blocking drugs are already in use, since this would predispose to serious blood pressure rise. Blocking only the peripheral dilator (beta) action of epinephrine leaves its constrictor (alpha) action unopposed. In the event of hemorrhage or shock, producing both beta and alpha blockage is contraindicated since the combination prevents the increase in heart rate and peripheral vasoconstriction needed to maintain blood pressure.
In inoperable or metastatic pheochromocytoma, INDERAL may be useful as an adjunct to the management of symptoms due to excessive beta-adrenergic receptor stimulation.
INDERAL-LA CAPSULES
INDERAL-LA (propranolol hydrochloride) extended release capsules are indicated for maintenance therapy in the treatment of hypertension and prophylaxis of angina pectoris.
As for INDERAL, the combination of INDERAL-LA with thiazide-like diuretics and/or peripheral vasodilators has been shown to be compatible and generally more effective than INDERAL-LA alone. Experience with most commonly used antihypertensive agents has not suggested evidence of incompatibility.
Treatment must always be initiated and individual titration of dosage carried out using the conventional tablets. The long-acting formulation may be used for maintenance provided the dosage requirement is suitable.
INDERAL-LA is not indicated for the emergency treatment of hypertensive crises.
CONTRAINDICATIONS
INDERAL (propranolol hydrochloride) and INDERAL-LA are contraindicated in:
(1) bronchospasm, including bronchial asthma;
(2) allergic rhinitis during the pollen season;
(3) sinus bradycardia and greater than first degree block;
(4) cardiogenic shock;
(5) right ventricular failure secondary to pulmonary hypertension;
(6) congestive heart failure (see WARNINGS) unless the failure is secondary to a tachyarrhythmia treatable with INDERAL.
WARNINGS
Cardiac Failure: Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure; therefore, inhibition by means of beta-adrenergic blockade is a potential hazard as it may further depress myocardial contractility and precipitate cardiac failure. INDERAL
(propranolol hydrochloride) and INDERAL-LA act selectively without completely abolishing the inotropic action of digitalis on the heart muscle (i.e. that of supporting the strength of myocardial contractions). In patients already receiving digitalis, the positive inotropic action of digitalis may be reduced by INDERAL'S negative inotropic effect. The effects of INDERAL and digitalis are additive in depressing AV conduction.
In Patients Without a History of Cardiac Failure, continued depression of the myocardium over a period of time can, in some patients, lead to cardiac failure. In rare instances, this has been observed during INDERAL therapy. Therefore, at the first sign or symptom of impending cardiac failure, patients should be fully digitalized and/or given a diuretic, and the response observed closely; a) if cardiac failure continues, despite adequate digitalization and diuretic therapy, INDERAL or
INDERAL-LA should be withdrawn immediately; b) if tachyarrhythmia is being controlled, patients should be maintained on combined therapy and closely followed until threat of cardiac failure is over.
Abrupt Cessation of INDERAL and INDERAL-LA Therapy in Angina Pectoris. Severe exacerbation of angina and the occurrence of myocardial infarction have been reported in some patients with angina pectoris following abrupt discontinuation of INDERAL therapy. Therefore, when discontinuation of INDERAL or INDERAL-LA is planned in patients with angina pectoris, the dosage should be gradually reduced over a period of about two weeks and the patient should be carefully observed. For patients receiving propranolol hydrochloride tablets, the same frequency of administration should be maintained. For patients on INDERAL-LA, discontinuation can be achieved by substituting INDERAL-LA 60, 80, 120 and 160 mg by the equivalent dosage of conventional propranolol hydrochloride tablets spread throughout the day, and then gradually reducing the dose. In situations of greater urgency, INDERAL or INDERAL-LA dosage should be reduced stepwise in four days, under close observation. If angina markedly worsens, or acute coronary insufficiency develops, it is recommended that treatment with conventional Propranolol hydrochloride tablets be reinstituted promptly, at least temporarily. In addition, patients with angina pectoris should be warned against abrupt discontinuation of INDERAL or INDERAL-LA.
Oculomucocutaneous Syndrome. Various skin rashes and conjunctival xerosis have been reported in patients treated with beta blockers, including INDERAL. A severe oculomucocutaneous syndrome, whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the long-term use of one beta-adrenergic blocking agent. This syndrome has not been observed with INDERAL; however, physicians should be alert to the possibility of such reactions and discontinue treatment if they occur.
In Patients with Thyrotoxicosis possible deleterious effects from long-term use of INDERAL have not yet been adequately appraised. Special consideration should be given to INDERAL'S potential for aggravating congestive heart failure. INDERAL and INDERAL-LA may mask the clinical signs of developing or continuing hyperthyroidism or its complications, and give a false impression of improvement. Therefore, abrupt withdrawal of INDERAL or INDERAL-LA may be followed by an exacerbation of symptoms of hyperthyroidism, including thyroid storm. This may be another instance where INDERAL or INDERAL-LA should be withdrawn slowly by reducing dosage.
INDERAL does not distort thyroid function tests.
In Patients with Wolff-Parkinson-White Syndrome, INDERAL or INDERAL-LA should be used with caution since several cases have been reported in which, after INDERAL treatment, the tachycardia was replaced by a severe bradycardia requiring a demand pacemaker. In one patient, this occurred after an initial dose of 5 mg of propranolol hydrochloride.
In Patients Undergoing Elective or Emergency Surgery. The management of patients with angina, being treated with beta-blockers and undergoing elective or emergency surgery, is controversial because beta adrenergic receptor blockade impairs the ability of the heart to respond to beta adrenergically mediated reflex stimuli, but abrupt discontinuation of therapy with INDERAL may be followed by severe complications (see Abrupt Cessation of Therapy Warning). Some patients receiving beta adrenergic blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported.
For these reasons, in patients with angina undergoing elective surgery, INDERAL or INDERAL-LA should be withdrawn gradually following the recommendation given under Abrupt Cessation of
Therapy. According to available evidence, all clinical and physiologic effects of betablockade are no longer present 48 hours after cessation of medication.
In emergency surgery, since INDERAL is a competitive inhibitor of beta adrenergic receptor agonists, its effects may be reversed, if necessary, by sufficient doses of such agonists as isoproterenol or dobutamine.
Anesthesia with agents which maintain cardiac contractility by virtue of their effect on catecholamine release (e.g. ether) should be avoided in patients on INDERAL or INDERAL-LA therapy.
In Patients Prone to nonallergic Bronchospasm (e.g., Chronic Bronchitis, Emphysema,
Bronchiectasis), INDERAL and INDERAL-LA should be administered with caution since they may block the bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta-adrenergic receptors.
In Patients with Diabetes and in those Subject to Hypoglycemia, INDERAL and INDERAL-LA, because of their beta-adrenergic blocking activity, may block premonitory signs and symptoms
(pulse rate and pressure changes) of acute hypoglycemia. This is especially important to keep in mind in patients with labile diabetes. Hypoglycemic attacks may be accompanied by a precipitous elevation of blood pressure. Acute increases in blood pressure have occurred after insulin-induced hypoglycemia in subjects on propranolol.
Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions, have been associated with the administration of propranolol (see ADVERSE REACTIONS”).
Skin Reactions: Cutaneous reactions, including Stevens-Johnson Syndrome, toxic epidermal necrolysis, exfoliative dermatitis, erythema multiforme, and urticaria, have been reported with use of propranolol (see “ADVERSE REACTIONS”).
Use in Pregnancy. The safe use of INDERAL and INDERAL-LA in pregnancy has not been established. Use of any drug in pregnancy or in women of childbearing potential requires that the possible risk to mother and/or fetus be weighed against the expected therapeutic benefit. Perinatal complications, such as small placenta and intrauterine growth retardation, have been reported in a few cases where the mother took INDERAL during pregnancy. Some infants born to mothers treated with INDERAL were reported to have hypoglycemia and/or bradycardia. Use in Children. While experience with INDERAL in children under 12 is limited, the indications for which INDERAL or INDERAL-LA is recommended occur infrequently in childhood. Although reports fail to indicate that children respond in a manner different from the adult, physicians are advised to undertake treatment with caution.
PRECAUTIONS:
There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers.
In these patients, the reaction may be more severe due to pharmacological effects of beta-blockers and problems with fluid changes. Epinephrine should be administered with caution since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other, these doses can be associated with excessive alpha adrenergic stimulation with consequent hypertension, reflex bradycardia and heart-block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids, and the use of beta agonists including parenteral salbutamol or isoproterenol to overcome bronchospasm, and norepinephrine to overcome hypotension.
Some slowing of the heart due to unopposed vagal activity is usual in patients receiving INDERAL
(propranolol hydrochloride), or INDERAL-LA; however occasionally severe bradycardia occurs and may lead to vertigo, syncopal attacks or orthostatic hypotension. Patients, especially those with limited cardiac reserve should be monitored for signs of excessive bradycardia. Should the patient become symptomatic, the dose of INDERAL should be decreased or, if necessary, the drug should be discontinued. If it is essential to correct the bradycardia, intravenous atropine or isoproterenol should be considered.
It has been reported that administration of INDERAL to control cardiac arrhythmias in acute myocardial infarction has caused marked reduction in cardiac output. Therefore, the doses of
INDERAL should be kept to the minimum in patients with severe myocardial infarction. Caution should be exercised when administering INDERAL in such situations, especially when a large portion of the myocardium has been damaged due to coronary occlusion, since adequate sympathetic drive should be preserved to maintain ventricular function. Prior administration of other anti-arrhythmic cardiac depressant drugs, such as procainamide or quinidine may potentiate the cardiac-depressant activity of INDERAL. Prior digitalization may be indicated and atropine should be at hand to control bradycardia.
The combination of INDERAL, or INDERAL-LA, with a thiazide-like diuretic and/or peripheral vasodilator produces a greater fall in blood pressure than either drug alone. This occurs regardless of which drug is administered first. The same degree of blood pressure control can be achieved by lower than usual dosages of each drug. Therefore, when using such combined therapy, careful monitoring of the dosage is required until the patient is stabilized.
Patients receiving catecholamine depleting drugs such as reserpine or guanethidine should be closely observed if INDERAL or INDERAL-LA is administered concomitantly. The added catecholamine blocking action of this drug may produce an excessive reduction of the resting sympathetic nervous activity.
In patients on long-term treatment with INDERAL or INDERAL-LA, laboratory determinations should be made at regular intervals. The drug should be used with caution in patients with impaired renal and hepatic functions.
ADVERSE REACTIONS:
The most serious adverse reactions encountered with INDERAL or INDERAL-LA (propranolol hydrochloride) are congestive heart failure and bronchospasm (see Contraindications, Warnings and
Precautions).
Gastrointestinal disturbances (anorexia, nausea, vomiting, diarrhea, abdominal pain) are the most common adverse effects reported. Other less frequently reported adverse reactions are: (in descending order) cold extremities and exacerbation of Raynaud's phenomenon; congestive heart failure; sleep disturbances including vivid dreams; dizziness, fatigue and bronchospasm. The following adverse reactions have also been reported with the use of propranolol.
Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions, Stevens-Johnson
Syndrome, toxic epidermal necrolysis, exfoliative dermatitis, erythema multiforme and urticaria.
Reported adverse effects, according to organ systems are recorded below.
Cardiovascular
Congestive heart failure (see Warnings); secondary effects of decreased cardiac output which could include; syncope, vertigo, lightheadedness, decreased renal perfusion and rarely, postural hypotension; intensification of A.V. block and hypotension; severe bradycardia; claudications and cold extremities, Raynaud's phenomenon; dyspnoea; palpitations; precordial pain.
Central Nervous System
Dizziness, lethargy, weakness, drowsiness, headache, insomnia, fatigue, anorexia, anxiety, mental depression, poor concentration, reversible amnesia and catatonia, vivid dreams with or without insomnia, hallucinations, paresthesia, incoordination.
Gastrointestinal
Nausea, vomiting, epigastric distress, anorexia, bloating, mild diarrhea, constipation.
Respiratory
Bronchospasm; laryngospasm and respiratory distress. (See Contraindications and Warnings).
Dermatologic
A few cases of erythematous rashes and increase of facial acneiform lesions have been reported;
urticaria; exfoliative psoriasiform eruption, Stevens-Johnson Syndrome, toxic epidermal necrolysis, exfoliative dermatitis and erythema multiforme.
Others
Reduction or loss of libido; reversible alopecia and rarely: diminution and loss of hearing; tinnitus;
visual disturbances; diminished vision; conjunctivitis; thrombocytopenic purpura; pharyngitis and agranulocytosis, fever combined with aching and sore throat; flushing of the face.
Allergic
Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions. Clinical Laboratory Test Findings
Elevated blood urea levels in patients with severe heart disease, elevated serum transaminase, alkaline phosphatase, and lactate dehydrogenase have been reported.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Several reports in the published literature describe cases in which INDERAL (propranolol hydrochloride) was used as a suicide agent. In most cases, other agents, e.g. alcohol have also been involved. One patient who died was thought to have ingested 3600 mg of propranolol hydrochloride. Survival of patients taking higher single doses has, however, also been reported.
The common signs to be expected in overdosage are bradycardia, hypotension, bronchospasm, or acute cardiac failure. If overdosage occurs, in all cases therapy with INDERAL, or INDERAL-LA, should be discontinued and the patient observed closely. In addition the following therapeutic measures are suggested:
Bradycardia: Administer atropine incrementally in 0.6 mg doses. If there is no response to vagal blockade, administer isoproterenol cautiously.
Cardiac Failure: Digitalization and Diuretics.
Hypotension: Vasopressors, e.g., levarterenol or epinephrine. (There is evidence that epinephrine is the drug of choice).
Bronchospasm: Administer isoproterenol and aminophylline.
DOSAGE AND ADMINISTRATION
INDERAL-LA EXTENDED-RELEASE CAPSULES
INDERAL-LA Extended-Release Capsules are intended for maintenance therapy in those patients requiring doses within the range of 60 to 320 mg per day. Initiation of treatment and individual titration of dosage should be carried out using the conventional tablets. INDERAL-LA may be preferred for maintenance because of the convenience of once-daily dosage. Patients with angina or hypertension on a maintenance regimen within the range of 60 to 320 mg per day regular tablets taken in divided doses may be changed to the appropriate number of INDERAL-LA capsules taken once daily in the morning or evening.
However, INDERAL-LA should not be considered a simple mg-for-mg substitute for conventional propranolol hydrochloride tablets and blood levels achieved are lower than those of two to four times daily dosing with the same dose. When changing to INDERAL-LA from conventional propranolol hydrochloride tablets, a possible need for retitration upwards should be considered, especially to maintain effectiveness at the end of the dosing interval. In most clinical settings, however, such as hypertension or angina where there is little correlation between plasma levels and clinical effect, INDERAL-LA has been shown to be therapeutically equivalent to the same mg dose of conventional propranolol hydrochloride tablets as assessed by 24-hour effects on blood pressure, and on 24-hour exercise responses of heart rate, systolic pressure, and rate pressure product.
INDERAL-LA can provide effective beta blockade for 24-hour periods.
When propranolol is combined with another antihypertensive agent which is already being administered, therapy should be initiated with conventional propranolol hydrochloride tablets following usual dosage recommendations. Once adequate blood pressure control has been obtained,
INDERAL-LA capsules may be used for maintenance provided the dosage requirement is suitable.
In the treatment of hypertension, if required, further reduction of blood pressure may be attained by the addition of diuretic and/or peripheral vasodilator. Addition of another antihypertensive agent should, however, be gradual, beginning with 50% of the usual recommended starting dose, to avoid excessive reduction of blood pressure.
INDERAL INJECTION 1 MG/ML
Intravenous administration is reserved for life-threatening arrhythmias, or those occurring under anesthesia. The usual dose is from 1 to 3 mg, administered under careful monitoring, e.g., electrocardiograph, and central venous pressure recording. The rate of administration should not exceed 1 mg (1 ml) per minute to avoid extreme lowering of blood pressure and cardiac arrest.
Sufficient time should be allowed for the drug to reach the site of action especially when a slow circulation is present. If necessary, a second dose may be given after two minutes. Thereafter, additional drug should not be given in less than four hours. Additional INDERAL should not be given once the desired alteration in rate and/or rhythm is achieved. Changeover to oral therapy should be made as soon as possible.
The intravenous product contains no preservatives. Discard the unused portion after the second dose.
CHEMISTRY
(±) Propranolol Hydrochloride.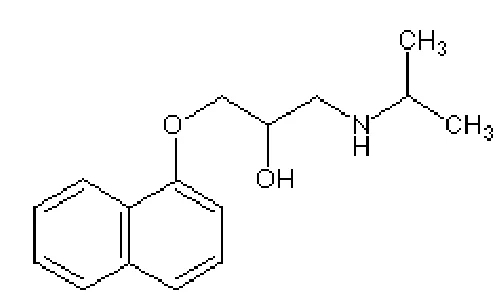
•HCl
MOLECULAR FORMULA: C16H23NO2•HCl
MOLECULAR WEIGHT: 295.81
CHEMICAL NAME: (±) 1-(isopropylamino)-3-(1-naphthyloxy)-2-propanol hydrochloride
DESCRIPTION:
Propranolol hydrochloride is a stable, colorless, crystalline solid with a melting point of 163-164
Co. It is readily soluble in water and ethanol and insoluble in nonpolar solvents.
AVAILABILITY
INDERAL-LA Extended-Release Capsules
60 mg - Each white/light-blue capsule, identified by 3 narrow bands, 1 wide band, and
“INDERAL LA 60", contains 60 mg propranolol hydrochloride. In bottles of 100.
80 mg - Each light-blue capsule, identified by 3 narrow bands, 1 wide band, and "INDERAL
LA 80", contains 80 mg propranolol hydrochloride. In bottles of 100.
120 mg - Each light-blue/dark blue capsule, identified by 3 narrow bands, 1 wide band and
"INDERAL LA 120", contains 120 mg propranolol hydrochloride. In bottles of 100.
160 mg - Each dark-blue capsule, identified by 3 narrow bands, 1 wide band, and "INDERAL
LA 160" contains 160 mg propranolol hydrochloride. In bottles of 100 and 500.
Non-Medicinal Ingredients:
Each 80 mg, 120 mg, 160 mg extended-release capsule contains: Ethylcellulose,
Hydroxypropylmethylcellulose, Microcrystalline Cellulose.
Each 60 mg extended-release capsule contains: Ethylcellulose, Hydroxymethylcellulose,
Microcrystalline Cellulose.
Empty Capsules:
INDERAL-LA 60 mg/INDERAL-LA 80 mg/INDERAL-LA 120 mg: Each capsule contains:
FD&C Blue 1, FD&C Red 3, Gelatin, Silicon Dioxide, Sodium Lauryl Sulphate,
Titanium Dioxide.
- INDERAL-LA 160 mg: Each capsule contains: Gelatin, FD&C Blue 1, Titanium Dioxide.
INDERAL Injection
1 mg/ml - Each mL contains 1 mg of propranolol hydrochloride in aqueous solution. The pH is adjusted with citric acid. Supplied as: 1 mL vials - boxes of 10
10 mL vials - boxes of 5.
PHARMACOLOGY
Propranolol hydrochloride is a non-selective competitive antagonist of endogenous and exogenous sympathomimetic amines at beta-adrenergic receptors (Beta1, and Beta2). Chemically it is a racemic mixture of equal amounts of levo and dextro isomers. The levo isomer is responsible for most of the beta receptor blocking activity.
Cardiovascular Effects
Intravenous administration of propranolol to cats and dogs produced a fall in heart rate by blocking endogenous sympathetic activity to the heart. In anesthetized dogs, propranolol produced dose-related decrease in heart rate, cardiac contractile force, and small depressions in blood pressure, and cardiac output. These effects have also been demonstrated in man. A reduction in myocardial oxygen consumption and increased right atrial pressure were observed in healthy humans.
Human and animal studies with propranolol have demonstrated competitive and reversible blockage of the increased heart rate and increased force of contraction produced by isoproterenol, epinephrine, norepinephrine and stellate ganglion stimulation. Propranolol reduced the pressor response to norepinephrine, potentiated that of epinephrine, but did not affect the response to phenylephrine.
Epstein and associates studied 16 human subjects under conditions of maximal and submaximal exercise. Propranolol 0.15 mg/kg intravenously, was sufficient to reduce by tenfold the sensitivity of heart rate to isoproterenol.
Blockade of beta-adrenergic receptors in the peripheral vasculature has little if any effect on circulation or blood pressure. When administered intra-arterially, propranolol causes a brief vasodilation unrelated to beta-adrenergic receptor blockade.
Amounts of propranolol which completely abolished the increase in heart rate produced by stimulation of the right stellate ganglion in anesthetized cats did not affect the bradycardia produced by vagal stimulation.
Propranolol causes no observable response when it interacts with beta-receptors in the absence of a primary antagonist such as epinephrine or isoproterenol indicating a lack of intrinsic sympathomimetic activity.
Lucchesi et al. demonstrated in dogs that propranolol was effective in reversing or preventing several types of experimentally-induced cardiac arrhythmias.
In animal experiments, at concentrations much higher than those necessary for a complete beta-adrenergic blockade, propranolol exerts a local anesthetic effect. This has also been termed a
"membrane stabilizing" or "quinidine-like" effect. This property of propranolol has been demonstrated in vitro with human myocardium only at a minimum concentration of 10 mg/l which is about 100 times greater than that required for inhibition of exercise tachycardia or suppression of ectopic beats. This is, therefore, not thought to be an important property and there are not in vivo methods for demonstrating this effect in man.
Plasma renin levels are reduced by propranolol.
Respiratory Effects
Propranolol increases airway resistance by reducing the sympathetic tone at the bronchi. This effect is small in most normal individuals where it can only be demonstrated by measuring forced expiry volume (FEV1). In asthmatics and patients with other bronchospastic diseases however, this effect is marked and potentially dangerous.
Injection of propranolol reduced FEV1 with dyspnea, cough and dizziness in 2 of 11 patients with chronic obstructive lung disease. When given the drug orally (40 mg q.i.d.) 5 of these 11 patients reported dyspnoea. Propranolol has been reported to potentiate bronchospasm induced by histamine, acetylcholine, methylcholine or allergen and this potentiation is greater is asthmatics than in non-asthmatic subjects.
Central Nervous System Effects
Propranolol readily crosses the blood/brain barrier. In some animal experiments it has been shown to display central muscle relaxant, sedative and anticonvulsant properties. To date, none of these effects can be directly attributed to blockade of beta-adrenergic receptors in the Central Nervous
System. One publication, suggests that propranolol's CNS activity may be attributable to a glycol metabolite.
Metabolic Activity
Propranolol may produce hypoglycemia but this effect appears to be rare and its mechanism is not clear. Propranolol also impairs the sympathetically mediated rebound response to hypoglycemic symptoms (see Warnings).
Propranolol inhibits the rise in plasma free fatty acids induced by sympathomimetic amines. It also inhibits the lipolytic action of catecholamines in isolated adipose tissues of several animal species.
TOXICOLOGY
Acute Toxicity (LD50)
Dose mg/kg Dose mg/kg
I.V. Oral
Mice 30-50 500-800
Rats 25-30 1000-1500
Rabbits 7.5-10.0 approx. 600
Subacute Toxicity
Four-week subacute toxicity studies were performed in rats (doses of 3.0 and 15 mg/kg intraperiotoneally), on dogs (doses of 1.5 and 7.5 mg/kg intravenously) and three-month oral toxicity studies were conducted on rats, mice and dogs. No drug-induced histopathologic changes were observed in any of the animals.
Chronic Toxicity
Rats
A toxicity study of 18 months' duration was conducted in four groups of rats (one control and three experimental) each consisting of 25 males and 25 females. All animals received medication by tube directly into the stomach for the first six months, and thereafter received the drug in the diet.
A number of animals who received the highest dose (150 mg/kg) developed bronchospasm soon after receiving the drug. A variety of pathologic lesions were observed in both the control and experimental groups. Dilatation of both ventricles was noted in a number of high-dose experiment.
Spontaneous myocarditis consisting of minor lymphocytic infiltration was observed in both groups.
Testicular atrophy and reduction or absence of corpora lutea was seen in both the control and experimental groups.
Dogs
A one-year toxicity test was carried out in 32 dogs in both sexes, divided into four groups (control, and propranolol 60, 20 and 5 mg/kg). A patchy edema and a slight increase in the size of the lymphoid follicles of the mucosa in the fundus of the stomach were seen and were attributed to mild irritation caused by prolonged dosing with high doses of propranolol.
Tumorigenic Tests
The carcinogenic potential of propranolol was investigated in mice and rats by chronic administration of the compound in the diet for 78 weeks at varying concentrations to provide dosage levels of 10, 50 and 150 mg/kg/day. Control groups of mice and rats were fed the same diet without compound. After 78 weeks of administration, the mice were then kept alive for an additional two months, and the rats for six months. At the termination of the experiment, gross and microscopic pathologic investigations revealed that in mice the incidence of benign and malignant neoplasms was similar in control and all treated groups. Thus, no compound-related, tumorigenic effect was observed at any dose level. Similarly, no tumorigenic effect was found in the rat. The tumour incidence was lower in female rats treated with 150 mg/kg/day propranolol than in any of the other groups. This was attributed to the markedly decreased bodyweight gains in this group.
REPRODUCTIVE STUDIES
To determine the effects of propranolol in rats on fertility, pregnancy, the developing fetus, and newborns up to the time of weaning, various dose levels of the drug were administered either by gastric intubation or in the feed. The drug was also fed to rabbits in their diet. In some studies in rats a non-dose related increase in resorption sites and neonatal deaths were observed. No teratogenic effects were noted in either species. Furthermore, the compound had no adverse effect on fertility, pregnancy, parturition, or lactation.
BIBLIOGRAPHY
- 1.
Shand, D.G.: Pharmacokinetics of Propranolol: A Review, Postgraduate Med. J. 52 (Suppl.
4): 22, 1976.
- 2.
Johnsson, G. and Regardh, C.G.: Clinical Pharmacokinetics of Beta-Adrenoreceptor
Blocking Drugs. Clin. Pharmacokin. 1:233-263, 1976.
- 3.
Walle, T., Conradi, E.C., Walle, U.K., Fagan, T.C., and Gaffney, T.E.: Propranolol
Glucuronide Cumulation During Long-Term Propranolol Therapy: A Proposed Mechanism for Propranolol. Clin. Pharm. Ther. 26:686-695, 1979.
- 4.
Black, J.W., Duncan, W.A.M., and Shanks, R.G.: Comparison of Some Properties of
Pronethalol and Propranolol. Br. J. Pharmacol & Chemother. 25:577, 1965.
- 5.
Shankds, R.G.: The Effect of Propranolol on the Cardiovascular Responses to Isoprenaline,
Adrenaline and Noradrenaline in the Anesthetized Dog. Br. J. Pharmacol. & Chemother. 26:322, 1966.
- 6.
Marshall, R.J., Barnes, W.E., and Beane, J.E. et al.: Blockage by Propranolol of the
Hemodynamic and Metabolic Responses to Infused Catecholamines. (Abstr.) Fed. Proc. 24:713 (Mar.-Apr.) Part I, 1965.
- 7.
Troyer, W.G., Wallace, A.G., and Lesage, M.A. et al.: Electrophysiologic Effects of
Adrenergic Stimulation and Blockade. (Abstr.) Fed, Proc. 24:713 (Mar.-Apr.) Part I, 1965.
- 8.
Shanks, R.G.: The Peripheral Vascular Effects of Propranolol and Related Compounds.
Br. J. Pharmacol. & Chemother. 29:204-217, 1967.
- 9.
Epstein, S.E., Robinson, B.F., Kahler, R.C., and Braunwald, E.: Effects of Beta-
Adrenergic Blockade on the Cardiac Response to Maximal and Sub-maximal Exercise in Man. J. Clin. Invest. 44:-1745-1753, 1965.
- 10.
Barrett, A.M. and Cullum, V.A.: The Biological Properties of the Optical Isomers of
Propranolol and Their Effects on Cardiac Arrhythmias. Br. J. Pharm. 34:43-55, 1968.
- 11.
Lucchesi, B.R., Whitsitt, L.S. and Brown, N.L.: Propranolol in Experimentally Induced
Cardiac Arrhythmias. Can. J. Physiol. and Pharmacol. 44:543, 1966.
- 12.
Conolly, M.E., Kersting, F., and Dollery, C.T.: The Clinical Pharmacology of Beta-
Adrenoceptor-Blocking Drugs. Prog. Cardio-vasc. Dis. Vol. XIX, No. 3, 1976.
- 13.
McDevitt, D.G.: The Assessment of Beta-Adrenoceptor Blocking Drugs in Man. Br. J.
Clin. Pharmac. 4:413-425, 1977.
- 14.
Beumer, H.M.: Adverse Effects of Beta-Adrenoreceptor Blocking Drugs on Respiration.
Cardiovascular Drugs. Vol. 2: Beta-Adrenoceptor Blocking Drugs. G.S. Avery, Ed., ADIS Press, Sydney, 1977.
- 15. Gayrard, P. Orehek, J. and Charpin, J.: Le test au propranolol: nouveau test de provocation de l'asthme. Etude comparative. Revue Tuberculose (Paris) 35:511-522, 1971.
- 16.
Tivenius, L. and Nyberg, G.: Effect of Alprenolol and Propranolol on ventilatory function.
A Comparative Study in Patients With Chronic Obstructive Lung Disease. Pharmacologia Clinica 2:51, 1969.
- 17.
Nickerson, M. and Collier, B.: Propranolol and Related Drugs. The Pharmacological
Basis of Therapeutics, 5th Edition, L.S. Goodman and A. Gilman, Eds., MacMillan Publishing Co., Inc. N.Y. 1975.
- 18.
Greenblatt, D.J. and Shader, R.I.: On the Psychopharmacology of Beta-Adrenergic
Blockade. Curr. Ther. Res. 14:615-625, 1972.
- 19.
Saelens, D.A., Walle, T., Privitera, P.J. et al.: Central Nervous System Effects and
Metabolic Disposition of a Glycol Metabolite of Propranolol. J. Pharmacol. Exp. Ther. 188:86-92, 1974.
- 20.
Gibson, D.G.: Pharmacodynamic Properties of Beta-Adrenoreceptor Blocking Drugs in
Man. Cardiovascular Drugs, Vol. 2: Beta-Adrenoceptor Blocking Drugs. G.S. Avery, Ed. ADIS Press, 1977, Sydney.
- 21.
Dollery, C.T., Patterson, J.W., and Conolly, M.E.: Clinical Pharmacology of Beta-
Receptor-Blocking Drugs. Clin. Pharm. Ther. 10:765, 1969.
- 22.
Meyler's Side Effects of Drugs. Vol. 8, 443 Excerpta Medica, Amsterdam-Oxford American
Elsevier Publishing Co. Inc., New York, 1975.
- 23. Hajdu, A. and Vlielander, L.C.: Research Report. Ayerst Laboratories, 1965.
- 24. Ayerst Research Reports 1976, 1977.
- 25.
Winkler, G.F. and Young, R.R.: Efficacy of Chronic Propranolol Therapy in Action
Tremors of the Familial, Senile or Essential Varieties. N. Eng. J. Med. 290:984-988, 1974.
- 26. Murray, T.J.: Essential Tremor. Can. Med. Assoc. J., 124: 1559-1565, 1981.
- 27.
Dvornik, D et al: Relationship between Plasma Propranolol Concentrations and Dose of
Long-Acting Propranolol (Inderal-LA) Current Therapeutic Research, Vol. 34, No. 4, P. 599, Oct. 1983.