


Product Monograph - Inderal-LA
RECENT MAJOR LABEL CHANGES
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics .......................................................................................................... 4
1.2 Geriatrics........................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION................................................................................. 5
4.1 Dosing Considerations ....................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment..................................................... 5
4.4 Administration................................................................................................... 6
4.5 Missed Dose ...................................................................................................... 6
5 OVERDOSAGE ............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 7
7 WARNINGS AND PRECAUTIONS .................................................................................. 8
7.1 Special Populations .......................................................................................... 12
7.1.1 Pregnant Women ....................................................................................... 12
7.1.2 Breast-feeding............................................................................................ 12
7.1.3 Pediatrics ................................................................................................... 12
7.1.4 Geriatrics ................................................................................................... 12
8 ADVERSE REACTIONS ................................................................................................ 12
8.1 Adverse Reaction Overview.............................................................................. 12
8.2 Clinical Trial Adverse Reactions ........................................................................ 14
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................ 14
8.3 Less Common Clinical Trial Adverse Reactions .................................................. 14
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics .......................... 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................... 14
8.5 Post-Market Adverse Reactions........................................................................ 14
9 DRUG INTERACTIONS................................................................................................ 14
9.1 Serious Drug Interactions ................................................................................. 14
9.2 Drug Interactions Overview.............................................................................. 15
9.3 Drug-Behavioural Interactions.......................................................................... 15
9.4 Drug-Drug Interactions .................................................................................... 15
9.5 Drug-Food Interactions .................................................................................... 17
9.6 Drug-Herb Interactions .................................................................................... 17
9.7 Drug-Laboratory Test Interactions .................................................................... 17
10 CLINICAL PHARMACOLOGY ....................................................................................... 17
10.1 Mechanism of Action.................................................................................. 17
10.2 Pharmacodynamics .................................................................................... 18
10.3 Pharmacokinetics ....................................................................................... 18
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 19
PART II: SCIENTIFIC INFORMATION ...................................................................................... 20
13 PHARMACEUTICAL INFORMATION............................................................................ 20
14 CLINICAL TRIALS........................................................................................................ 20
14.1 Trial Design and Study Demographics ......................................................... 20
14.2 Study Results ............................................................................................. 20
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 21
PATIENT MEDICATION INFORMATION ................................................................................. 23
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
INDERAL-LA (propranolol hydrochloride extended-release capsules, USP) is indicated for:
- maintenance therapy in the treatment of hypertension
- prophylaxis of angina pectoris.
As with conventional propranolol hydrochloride tablets, INDERAL-LA capsules are compatible with thiazide-like diuretics and/or peripheral vasodilators. Combinations of INDERAL-LA with thiazide-like diuretics and/or peripheral vasodilators have been shown to be generally more effective than INDERAL-LA alone.
Initial treatment and individual titration of dosage must always be carried out with conventional propranolol hydrochloride tablets. The long-acting formulation may then be used for maintenance therapy, provided the dosage requirement is suitable.
INDERAL-LA is not indicated for the emergency treatment of hypertensive crises.
1.1 Pediatrics
Pediatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use. (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations).
1.2 Geriatrics
Geriatrics: No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2 CONTRAINDICATIONS
INDERAL-LA (propranolol hydrochloride) is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
INDERAL-LA is also contraindicated in:
- Patients with a history of or current reports of bronchial asthma or bronchospasm;
- Allergic rhinitis during the pollen season;
- Sinus bradycardia and greater than first degree block;
- Cardiogenic shock;
- Right ventricular failure secondary to pulmonary hypertension;
- Congestive heart failure (see 7 WARNINGS AND PRECAUTIONS), unless the failure is secondary to a tachyarrhythmia treatable with propranolol hydrochloride;
- Patients prone to hypoglycaemia, i.e. after prolonged fasting or patients with impaired capacity to counter-regulate a possible hypoglycaemic event (see 7 WARNINGS AND PRECAUTIONS).
- As with other beta-blockers, INDERAL-LA must not be used in patients with any of the following: bradycardia, hypotension, metabolic acidosis, severe peripheral arterial circulatory disturbance, sick sinus syndrome, untreated phaeochromocytoma, uncontrolled heart failure, Prinzmetal’s angina.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
INDERAL-LA capsules should not be substituted for conventional propranolol hydrochloride tablets on a simple mg-for-mg basis, as blood levels achieved with INDERAL-LA are lower than blood levels achieved with conventional tablets using the same dose two to four times daily. When switching from conventional tablets to INDERAL-LA, it may be necessary to titrate upwards, especially to maintain effectiveness at the end of the dosing interval (see 10 CLINICAL PHARMACOLOGY).
In most clinical settings involving hypertension or angina, there is little correlation between plasma levels and clinical effect and INDERAL-LA has been shown to be therapeutically equivalent to the same mg dose of conventional propranolol hydrochloride tablets, as assessed by 24-hour effects on blood pressure and on 24-hour responses of heart rate, systolic blood pressure and rate pressure product during exercise.
Combinations of INDERAL-LA with Other Antihypertensive Agents: When propranolol hydrochloride is added to another antihypertensive agent, which is already being administered, therapy should be initiated with conventional propranolol hydrochloride tablets, following the usual dosing recommendations. Once adequate blood pressure control has been obtained, INDERAL-LA capsules can be used for maintenance, provided the dose requirement is suitable.
If additional blood pressure control is necessary in the treatment of hypertension, a diuretic and/or peripheral vasodilator can be added to the treatment regimen. Addition of another antihypertensive agent should, however, be gradual, beginning with 50% of the usual recommended starting dose, to avoid excessive reduction in blood pressure.
4.2 Recommended Dose and Dosage Adjustment
INDERAL-LA (Propranolol Hydrochloride) Extended-Release Capsules are intended for maintenance therapy in those patients requiring doses within the range of 60 to 320 mg per day. Initiation of treatment and individual titration of dosage should be carried out using conventional propranolol hydrochloride tablets. INDERAL-LA may be preferred for maintenance therapy because of the convenience of once-daily dosage. INDERAL-LA can provide effective beta blockade over 24 hours.
Patients with angina or hypertension, who have been maintained on a regimen of 60 to 320 mg per day of conventional propranolol hydrochloride tablets, in divided daily doses, may be switched to the appropriate number of INDERAL-LA capsules, taken once daily in the morning or evening.
Elderly Patients: The optimum dose should be individually determined according to clinical response (see 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations).
Patients with Impaired Renal or Liver Function: INDERAL-LA should be administered with caution to patients with impaired renal or hepatic function, including decompensated cirrhosis, since the half-life may be increased, necessitating lower doses (see 7 WARNINGS AND PRECAUTIONS).
Health Canada has not authorized an indication for pediatric use.
4.4 Administration
INDERAL-LA capsules should be swallowed whole and should not be chewed.
4.5 Missed Dose
If a dose of INDERAL-LA is missed, then it should be taken as soon as the patient remembers unless it is almost time for the next dose, in which case the patient should not take the missed dose. Patients should not take 2 doses at the same time to make up for a missed dose.
5 OVERDOSAGE
Overdosage Overview:
Several reports in the published literature describe cases in which propranolol hydrochloride was used as a suicide agent. In most cases, other agents, such as alcohol, were also involved. One patient who died was thought to have ingested 3600 mg of propranolol hydrochloride. Patients taking higher single doses have reportedly survived.
Symptoms: The common signs expected in overdosage include bradycardia, hypotension, bronchospasm and acute cardiac failure.
Treatment: If overdosage occurs, discontinue INDERAL-LA and observe the patient closely. The following specific therapeutic measures are suggested.
Bradycardia: Administer atropine incrementally in 0.6 mg doses. If there is no response to vagal blockade, administer isoproterenol cautiously.
Cardiac Failure: Digitalization and diuretics
Hypotension: Vasopressors (e.g.: epinephrine or levarterenol). There is evidence that epinephrine is the drug of choice.
Bronchospasm: Administer isoproterenol and aminophylline
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging
60 mg capsules: Each white/light blue capsule, identified by 3 narrow white bands, and imprinted with “INDERAL LA 60” contains 60 mg propranolol hydrochloride. Bottles of 100 capsules.
80 mg capsules: Each light blue capsule, identified by 3 narrow white bands, and imprinted with “INDERAL LA 80” contains 80 mg propranolol hydrochloride. Bottles of 100 capsules.
120 mg capsules: Each light blue/dark blue capsule, identified by 3 narrow white bands, and imprinted with “INDERAL LA 120” contains 120 mg propranolol hydrochloride. Bottles of 100 capsules.
160 mg capsules: Each dark-blue capsule, identified by 3 narrow white bands and imprinted with “INDERAL LA 160” contains 160 mg propranolol hydrochloride. Bottles of 100.
| For management of a suspected drug overdose, contact your regional poison control centre. |
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Extended-release capsules / 60 mg, 80 mg, 120 mg, 160 mg | Capsule: Ethylcellulose, hydroxypropylmethylcellulose, microcrystalline cellulose. Shell: FD&C Blue 1, FD&C Red 3, FD&C Red 28, gelatin, titanium dioxide. |
Empty Capsules:
Each capsule contains:
INDERAL-LA 60 mg: FD&C Blue 1, FD&C Red 28, gelatin, titanium dioxide, white and blue ink.
INDERAL-LA 80 mg: FD&C Blue 1, FD&C Red 3, gelatin, titanium dioxide, white ink.
INDERAL-LA 120 mg: FD&C Blue 1, FD&C Red 3, gelatin, titanium dioxide, white ink.
INDERAL-LA 160 mg: FD&C Blue 1, gelatin, titanium dioxide, white ink
7 WARNINGS AND PRECAUTIONS
General
INDERAL-LA is intended for the maintenance therapy of hypertension and for prophylaxis of angina pectoris. It is not indicated for initial or emergency treatment of these conditions. It should be substituted for conventional propranolol hydrochloride tablets only when the dose requirement is suitable (see 4 DOSAGE AND ADMINISTRATION).
The combination of INDERAL-LA with a thiazide-like diuretic and/or peripheral vasodilator produces a greater fall in blood pressure than either drug alone. The same degree of blood pressure control can be achieved by lower than usual dosages of each drug. Therefore, when using such combined therapy, careful monitoring of the dosage is required until the patient is stabilized (see 9 DRUG INTERACTIONS).
Cardiovascular
Cardiac Failure: Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure; therefore, inhibition by means of beta-adrenergic blockade is a potential hazard, as it may further depress myocardial contractility and precipitate cardiac failure.
INDERAL-LA acts selectively without completely abolishing the inotropic action of digitalis on the heart muscle (i.e. that of supporting the strength of myocardial contractions). In patients already receiving digitalis, the positive inotropic action of digitalis may be reduced by propranolol hydrochloride`s negative inotropic effect. Due to its negative effect on conduction time, caution must be exercised if it is given to patients with first degree heart block. The effects of the drug and digitalis are additive in depressing AV conduction. Caution must be exercised in patients whose cardiac reserve is poor.
In Patients Without a History of Cardiac Failure, continued depression of the myocardium over a period of time can, in some patients, lead to cardiac failure. In rare instances, this has been observed during propranolol hydrochloride therapy. Therefore, at the first sign or symptom of impending cardiac failure, patients should be fully digitalized and/or given a diuretic, and the response observed closely: a) if cardiac failure continues, despite adequate digitalization and diuretic therapy, INDERAL-LA should be withdrawn immediately; b) if tachyarrhythmia is being controlled, patients should be maintained on combined therapy and closely followed until the threat of cardiac failure is over.
Peripheral Arterial Circulatory Disturbances: Although contraindicated in severe peripheral arterial circulatory disturbances (see 2 CONTRAINDICATIONS), INDERAL-LA, as with other beta-blockers, may also aggravate less severe peripheral arterial circulatory disturbances.
Wolff- Parkinson-White Syndrome: INDERAL-LA should be used with caution since several cases have been reported in which, after propranolol hydrochloride treatment, the tachycardia was replaced by a severe bradycardia requiring a demand pacemaker. In one patient, this occurred after an initial dose of 5 mg of propranolol hydrochloride.
Cardiac Arrhythmias: It has been reported that administration of propranolol hydrochloride tablets to control cardiac arrhythmias in acute myocardial infarction has caused a marked reduction in cardiac output. Caution should be exercised when administering propranolol hydrochloride tablets in such situations, especially when a large portion of the myocardium has been damaged due to coronary occlusion, since adequate sympathetic drive should be preserved to maintain ventricular function.
Abrupt Cessation of INDERAL-LA Therapy in Angina Pectoris or Ischaemic Heart Disease: Severe exacerbation of angina and the occurrence of myocardial infarction have been reported in some patients with angina pectoris following abrupt discontinuation of propranolol hydrochloride therapy. Therefore, when discontinuation of INDERAL-LA is planned in patients with angina pectoris or ischaemic heart disease, the dosage should be gradually reduced over a period of at least two weeks and the patient should be carefully monitored.
Discontinuation of INDERAL-LA can be achieved by substituting INDERAL-LA 60, 80, 120 and 160 mg by the equivalent dose of conventional propranolol hydrochloride tablets spread throughout the day, and then gradually reducing the dose. In situations of greater urgency, propranolol hydrochloride tablets or INDERAL-LA dosage should be reduced stepwise in four days, under close observation. If angina markedly worsens, or acute coronary insufficiency develops, it is recommended that treatment with conventional propranolol hydrochloride tablets be reinstituted promptly, at least temporarily. In addition, patients with angina pectoris or ischaemic heart disease should be warned against abrupt discontinuation of propranolol hydrochloride.
Central Nervous System
Dizziness and/or fatigue may occasionally occur with beta-blocker administration and this should be taken into account.
Endocrine and Metabolism
Thyrotoxicosis, Hyperthyroidism: Possible deleterious effects from long-term use of INDERAL-LA have not yet been adequately appraised in patients with thyrotoxicosis. Special consideration should be given to the potential of propranolol hydrochloride to aggravate congestive heart failure.
INDERAL-LA may mask the clinical signs of developing or continuing hyperthyroidism or its complications, and give a false impression of improvement. Therefore, abrupt withdrawal of INDERAL-LA may be followed by an exacerbation of symptoms of hyperthyroidism, including thyroid storm. This may be another instance where INDERAL-LA should be withdrawn slowly by reducing the dosage. Propranolol hydrochloride does not distort thyroid function tests.
Patients with Diabetes and in those Subject to Hypoglycemia: INDERAL-LA, because of its beta-adrenergic blocking activity, may block premonitory signs and symptoms (pulse rate and pressure changes) of acute hypoglycaemia. This is especially important in patients with labile diabetes. Hypoglycemic attacks may be accompanied by a precipitous elevation of blood pressure. Acute increases in blood pressure have occurred after insulin-induced hypoglycaemia in patients on propranolol hydrochloride.
Hepatic
INDERAL-LA should be administered with caution to patients with impaired hepatic function, including decompensated cirrhosis, since the half-life may be increased in these patients.
In patients with portal hypertension, liver function may deteriorate and hepatic encephalopathy may develop. There have been reports suggesting that treatment with propranolol may increase the risk of hepatic developing encephalopathy.
Hypersensitivity, Allergic Reactions
Anaphylactic/anaphylactoid reactions have been associated with the administration of propranolol hydrochloride (see 8 ADVERSE REACTIONS).
There may be increased difficulty in treating an allergic type reaction in patients on beta-blockers. In these patients, the reaction may be more severe due to the pharmacological effects of beta-blockers and problems with fluid changes. Epinephrine should be administered with caution, since it may not have its usual effects in the treatment of anaphylaxis. On the one hand, larger doses of epinephrine may be needed to overcome the bronchospasm, while on the other, these doses can be associated with excessive alpha adrenergic stimulation with consequent hypertension, reflex bradycardia and heart block and possible potentiation of bronchospasm. Alternatives to the use of large doses of epinephrine include vigorous supportive care such as fluids, and the use of beta agonists, including parenteral salbutamol or isoproterenol to overcome bronchospasm, and norepinephrine to overcome hypotension.
Some slowing of the heart due to unopposed vagal activity is usual in patients receiving propranolol hydrochloride; however occasionally severe bradycardia occurs and may lead to vertigo, syncopal attacks or orthostatic hypotension. Patients, especially those with limited cardiac reserve should be monitored for signs of excessive bradycardia. Should the patient become symptomatic, the dose should be decreased or, if necessary, the drug should be discontinued. If it is essential to correct the bradycardia, intravenous atropine or isoproterenol should be considered.
Monitoring and Laboratory Tests
Liver and renal function tests should be performed at regular intervals during long-term treatment with INDERAL-LA.
Ophthalmologic
Oculomucocutaneous Syndrome: Various skin rashes and conjunctival xerosis have been reported in patients treated with beta-blockers, including propranolol hydrochloride. A severe oculomucocutaneous syndrome, whose signs include conjunctivitis sicca and psoriasiform rashes, otitis, and sclerosing serositis has occurred with the long-term use of one beta-adrenergic blocking agent. This syndrome has not been observed with propranolol hydrochloride; however, physicians should be alert to the possibility of such reactions and discontinue treatment if they occur.
Peri-Operative Considerations
In patients undergoing elective or emergency surgery: The management of angina patients taking beta-blockers and requiring elective or emergency surgery is controversial because the beta-adrenergic receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli.
However, the abrupt discontinuation of propranolol hydrochloride may be followed by severe complications (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Abrupt Cessation of INDERAL-LA Therapy in Angina Pectoris or Ischaemic Heart Disease). Some patients receiving beta adrenergic blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported.
For these reasons, INDERAL-LA should be withdrawn gradually from patients scheduled for elective surgery, following the recommendations provided in 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Abrupt Cessation of Therapy. According to available evidence, all clinical and physiologic effects of beta blockade are no longer present 48 hours after cessation of medication.
In patients undergoing emergency surgery, the competitive inhibition of beta-adrenergic receptor agonists, by propranolol hydrochloride, may be reversed, if necessary, using sufficient doses of such agonists as isoproterenol or dobutamine.
Anesthesia with agents which maintain cardiac contractility by virtue of their effect on catecholamine release (e.g. ether) should be avoided in patients on propranolol hydrochloride therapy.
Renal
INDERAL-LA should be administered with caution to patients with impaired renal function since the half-life may be increased in these patients.
Respiratory
Patients Prone to Non-allergic Bronchospasm (e.g., chronic bronchitis, emphysema, bronchiectasis): INDERAL-LA capsules should be administered with caution since they may block the bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta-adrenergic receptors. Bronchospasm can usually be reversed by beta-2-agonist bronchodilators such as salbutamol. Large doses of the beta-2-agonist bronchodilators may be required to overcome the beta-blockade produced by INDERAL-LA and the dose should be titrated according to the clinical response; both intravenous and inhalational administration should be considered. The use of intravenous aminophylline and/or the use of ipratropium (given by nebuliser), may also be considered. Glucagon (1 to 2 mg given intravenously) has also been reported to produce a bronchodilator effect in asthmatic patients. Oxygen or artificial ventilation may be required in severe cases
Skin
Cutaneous reactions, including Stevens-Johnson Syndrome, toxic epidermal, necrolysis, exfoliative dermatitis, erythema multiforme, and urticaria, have been reported with use of propranolol (see 8 ADVERSE REACTIONS).
7.1 Special Populations
7.1.1 Pregnant Women
Propranolol can cause fetal harm when administered to a pregnant woman. The safe use of INDERAL-LA in pregnancy has not been established. Use of any drug in pregnancy or in women of childbearing potential requires that the possible risk to mother and/or fetus be weighed against the expected therapeutic benefit. Post-marketing case reports, including perinatal complications such as small placentas, intra-uterine growth retardation and congenital abnormalities have been reported in neonates when the mother took propranolol during pregnancy. Some infants born to mothers treated with propranolol were reported to have hypoglycaemia, bradycardia and/or respiratory depression. Adequate facilities for monitoring such infants at birth should be available.
INDERAL-LA should be used in pregnancy only if the potential benefit justifies the potential risk to the fetus.
7.1.2 Breast-feeding
Propranolol is excreted in human milk. Breast feeding is therefore not recommended when INDERAL-LA is administered to nursing women.
7.1.3 Pediatrics
INDERAL-LA is not recommended for use in children. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
There is no information available for elderly patients. Therefore, the optimum dose should be individually determined according to clinical response.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most serious adverse reactions encountered with propranolol hydrochloride are congestive heart failure and bronchospasm (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
The most common adverse effects are gastrointestinal disturbances (anorexia, nausea, vomiting, diarrhea, abdominal pain).
The following adverse reactions have also been reported: hypersensitivity reactions, including anaphylactic/anaphylactoid reactions, Stevens-Johnson Syndrome, toxic epidermal necrolysis, exfoliative dermatitis, erythema multiforme and urticaria.
Reported adverse effects, by organ system, are provided below.
Allergic: Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions.
Blood: Thrombocytopenia
Cardiovascular: Congestive heart failure (see 7 WARNINGS AND PRECAUTIONS); heart failure deterioration; precipitation of heart block; secondary effects of decreased cardiac output (which could include: syncope, vertigo, light-headedness, decreased renal perfusion and rarely, postural hypotension); intensification of AV block and hypotension; severe bradycardia; claudication and cold extremities, Raynaud’s phenomenon; dyspnoea; palpitations; precordial pain.
Central Nervous System: Dizziness, lethargy, weakness, drowsiness, headache, insomnia, fatigue and/or lassitude, anorexia, anxiety, mental depression, poor concentration, reversible amnesia and catatonia, vivid dreams with or without insomnia, nightmares, hallucinations, psychoses, mood changes, confusion, paresthesia, incoordination., somnambulism.
Dermatologic: A few cases of erythematous rashes and increase of facial acneiform lesions have been reported; urticaria; exfoliative psoriasiform eruption; Stevens-Johnson Syndrome; toxic epidermal necrolysis, exfoliative dermatitis and erythema multiforme.
Endocrine: Hypoglycaemia in elderly patients, patients on haemodialysis, patients on concomitant antidiabetic therapy, patients with prolonged fasting and patients with chronic liver disease (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
Gastrointestinal: Nausea, vomiting, epigastric distress, anorexia, bloating, mild diarrhoea, constipation.
Nervous System: Isolated reports of myasthenia gravis-like syndrome or exacerbation of myasthenia gravis.
Others: Reduction or loss of libido; reversible alopecia and rarely: diminution and loss of hearing; tinnitus; visual disturbances; diminished vision; conjunctivitis; dry eyes, thrombocytopenic purpura; pharyngitis; agranulocytosis; fever combined with aching and sore throat; flushing of the face.
Respiratory: Bronchospasm (may occur in patients with bronchial asthma or a history of asthmatic complaints, sometimes with fatal outcome); laryngospasm and respiratory distress (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The clinical data on which the original indication was authorized are not available.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
At the time of authorization, no clinical trials in the pediatric population have been conducted.
8.3 Less Common Clinical Trial Adverse Reactions
See 8.1 Adverse Reaction Overview.
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
At the time of authorization, no clinical trials in the pediatric population have been conducted.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Clinical Laboratory Test Findings: Elevated blood urea levels in patients with severe heart disease, elevated serum transaminase, alkaline phosphatase and lactate dehydrogenase have been reported. An increase in ANA (antinuclear antibodies) has been observed, however the clinical relevance of this is not clear.
8.5 Post-Market Adverse Reactions
See 8.1 Adverse Reaction Overview.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
Verapamil, Diltiazem: Beta-blockers combined with calcium channel blockers with negative inotropic effects (such as verapamil and diltiazem) can lead to an exaggeration of these effects, particularly in patients with impaired ventricular function and/or SA or AV conduction abnormalities. This may result in severe hypotension, bradycardia and cardiac failure. Neither the beta-blocker nor the calcium channel blocker should be administered within 48 hours of discontinuing the other.
9.2 Drug Interactions Overview
Please see 9.4 Drug-Drug Interactions.
9.3 Drug-Behavioural Interactions
Alcohol: Concomitant use of alcohol may increase the plasma levels of propranolol.
9.4 Drug-Drug Interactions
The drugs listed in this section are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Anti-arrhythmic drugs
- Class I anti-arrhythmic drugs (e.g. disopyramide) and amiodarone may have a potentiating effect on atrial-conduction time and induce negative inotropic effects.
- Other cardiac-depressant anti-arrhythmic drugs: prior administration of other antiarrhythmic drugs, such as procainamide and quinidine may potentiate the cardiac-depressant activity of propranolol hydrochloride. Prior digitalization may be indicated and atropine should be at hand to control bradycardia.
Thiazide-like diuretics and peripheral vasodilators: The combination of INDERAL-LA with a thiazide-like diuretic and/or a peripheral vasodilator produces a greater fall in blood pressure than either drug alone. This occurs regardless of which drug is administered first (see 7 WARNINGS AND PRECAUTIONS, General).
Reserpine or guanethidine: Patients receiving catecholamine depleting drugs should be closely observed if administered concomitantly with INDERAL-LA. The added catecholamine blocking action of these drugs may produce an excessive reduction in the resting sympathetic nervous activity.
Rizatriptan: The simultaneous administration of rizatriptan and propranolol can increase the rizatriptan AUC and Cmax by approximately 70-80%. The increased rizatriptan exposure is presumed to be caused by inhibition of first-pass metabolism of rizatriptan through inhibition of monoamine oxidase-A. If both drugs are to be used, a rizatriptan dose of 5 mg has been recommended.
Digitalis glycosides: In association with beta-blockers, digitalis glycosides may increase atrioventricular conduction time.
Nifedipine: concomitant therapy with dihydropyridine calcium channel blockers (such as nifedipine) may increase the risk of hypotension and cardiac failure may occur in patients with latent cardiac insufficiency.
Fingolimod: Concomitant use of fingolimod with beta blockers may potentiate bradycardic effects and is not recommended. Where such coadministration is considered necessary, appropriate monitoring at treatment initiation, i.e. at least overnight monitoring, is recommended.
Epinephrine: Concomitant use of sympathomimetic agents, such as epinephrine, may counteract the effects of beta-blockers. Caution must be exercised when administering epinephrine parenterally to patients taking beta-blockers as, in rare cases, vasoconstriction, hypertension and bradycardia may result.
Lidocaine: administration of INDERAL-LA during an infusion of lidocaine may increase the plasma concentration of lidocaine by approximately 30%. Patients already receiving INDERAL-LA tend to have higher lidocaine levels than controls. The combination should be avoided.
Cimetidine: Concomitant use of cimetidine will increase plasma levels of propranolol.
Clonidine: Beta-blockers may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. If clonidine is co-administered with a beta-blocker, the beta-blocker should be withdrawn several days before stopping clonidine administration. If replacing clonidine with beta-blocker therapy, the introduction of the beta-blocker should be delayed for several days after clonidine has been discontinued.
Ergotamine, Dihydroergotamine (and related compounds); Caution must be exercised if ergotamine, dihydroergotamine or related compounds are given in combination with INDERAL-LA, since vasospastic reactions have been reported in a few patients.
Ibuprofen, Indomethacin: Concomitant use of prostaglandin synthetase inhibiting drugs (e.g. ibuprofen and indomethacin) may decrease the hypotensive effects of INDERAL-LA.
Chlorpromazine: The concomitant use of INDERAL-LA and chlorpromazine may result in an increase in plasma levels of both drugs. This may lead to an enhanced antipsychotic effect of chlorpromazine and an increased antihypertensive effect of INDERAL-LA.
Anaesthetic agents: Use of beta-blockers with anaesthetic agents may result in attenuation of the reflex tachycardia and increase the risk of hypotension. Anaesthetic agents causing myocardial depression should be avoided and caution should be exercised when using any anaesthetic agents with INDERAL-LA. If anaesthesia is required, the anaesthetist should be informed that the patient has been taking INDERAL-LA and the choice of anaesthetic should be one with as little negative inotropic activity as possible.
Other medications: Pharmacokinetic studies have shown that several drugs may interact with propranolol due to effects on enzyme systems in the liver, which metabolizes propranolol and the following agents: quinidine, propafenone, rifampicin, theophylline, warfarin, thioridazine and dihydropyridine calcium channel blockers, such as nifedipine, nisoldipine, nicardipine, isradipine, and lacidipine. Owing to the fact that blood concentrations of either agent may be affected, dosage adjustments may be needed according to clinical judgement. (See also the section above on Nifedipine).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Propranolol hydrochloride does not interfere with thyroid function tests. Interactions with other laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Propranolol hydrochloride is a non-selective beta-adrenergic receptor blocking drug. It has no other autonomic nervous system activity. Propranolol is a competitive antagonist which specifically competes with beta-adrenergic receptor stimulating agents for available receptor sites. When access to beta-adrenergic receptor sites is blocked by propranolol, the chronotropic, inotropic and vasodilator responses to beta-adrenergic stimulation are decreased proportionately.
Beta-adrenergic blockade is useful in some clinical conditions in which sympathetic activity is excessive or inappropriate, and therefore detrimental to the patient. Sympathetic stimulation is, however, vital in some situations (e.g., in patients with AV block or with a severely damaged heart) and should be preserved. The basic objective of beta-adrenergic blockade is to decrease adverse sympathetic stimulation, but not to the degree that impairs necessary sympathetic support. Beta-blockade may result in bronchial constriction by interfering with endogenously or exogenously induced bronchodilation (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
The mechanism of the antihypertensive effects of propranolol has not been established. Among the factors that may be involved are: (1) decreased cardiac output, (2) inhibition of renin release by the kidneys and (3) diminution of tonic sympathetic nerve outflow from vasomotor centers in the brain. It has been suggested, but not established, that propranolol may achieve a better antihypertensive effect in patients with normal or elevated plasma renin activity (PRA) than those with low PRA.
Propranolol may reduce the oxygen requirement of the heart at any level of effort by blocking catecholamine-induced increases in the heart rate, systolic blood pressure and the velocity and extent of myocardial contraction. On the other hand, propranolol may increase oxygen requirements by increasing left ventricular fiber length, end-diastolic pressure and systolic ejection period. When the net effect is beneficial in angina patients, it manifests itself during exercise or stress by delaying the onset of pain and reducing the incidence and severity of angina attacks.
Propranolol exerts antiarrhythmic effects in concentrations producing beta-adrenergic blockade, which appears to be its principal antiarrhythmic mechanism of action. Beta-adrenergic blockade is of unique importance in the management of arrhythmias caused by increased levels of circulating catecholamines or enhanced sensitivity of the heart to catecholamines (arrhythmias associated with pheochromocytoma, thyrotoxicosis, exercise).
The mechanisms of the anti-migraine anti-tremor effects of propranolol have not been established. The anti-migraine effect may be due to inhibition of vasodilation or arteriolar spasms over the cortex. Beta-adrenergic receptors have been demonstrated in the pial vessels of the brain. The anti-tremor effects may be exerted through both peripheral and central sites of action. The mechanism by which propranolol reduces the incidence of cardiovascular mortality in post-myocardial infarct patients is unknown.
10.2 Pharmacodynamics
Metabolic Activity
Propranolol may produce hypoglycemia, but this effect appears to be rare and its mechanism is not clear. Propranolol also impairs the sympathetically mediated rebound response to hypoglycemic symptoms (see 7 WARNINGS AND PRECAUTIONS.)
Propranolol inhibits the rise in plasma free fatty acids induced by sympathomimetic amines. It also inhibits the lipolytic action of catecholamines in isolated adipose tissues of several animal species.
Respiratory Effects
Propranolol increases airway resistance by reducing the sympathetic tone at the bronchi. This effect is small in most normal individuals, where it can only be demonstrated by measuring forced expiry volume (FEV1). In asthmatics and patients with other bronchospastic diseases, however, this effect is marked and potentially dangerous.
Injection of propranolol reduced FEV1 with dyspnea, cough and dizziness in 2 of 11 patients with chronic obstructive lung disease. When propranolol was given orally (40 mg q.i.d.), 5 of these 11 patients reported dyspnoea. Propranolol has been reported to potentiate bronchospasm induced by histamine, acetylcholine, methylcholine or allergens. This potentiation is greater in asthmatics than in non-asthmatic individuals.
Other Clinical Pharmacological Effects
Epstein and associates studied 16 human subjects under conditions of maximal and submaximal exercise. Propranolol 0.15 mg/kg intravenously, was sufficient to reduce by tenfold the sensitivity of heart rate to isoproterenol.
Blockade of beta-adrenergic receptors in the peripheral vasculature has little, if any, effect on circulation or blood pressure. When administered intra-arterially, propranolol causes a brief vasodilation unrelated to beta-adrenergic receptor blockade.
10.3 Pharmacokinetics
INDERAL-LA is a special formulation of propranolol hydrochloride consisting of capsules filled with spheroids of the active drug that have a sustained-release coating.
Absorption: Propranolol from INDERAL-LA capsules is almost completely absorbed from the gastrointestinal tract. A large part of the absorbed drug is lost from the systemic circulation due to first-pass metabolism in the liver. The first-pass metabolism is saturable.
Distribution: Peak blood levels following the administration of INDERAL-LA capsules occur at about 6 hours and the apparent plasma half-life has been reported to be between 10 and 12 hours (i.e., 2 to 3 times that of conventional tablets).
Steady state plasma concentrations of propranolol from INDERAL-LA are proportional to the dose over the range of 60 to 160 mg/day, although there is considerable inter-subject variation.
In healthy volunteers, steady state was achieved 2 or 3 days after administration of INDERAL-LA.
Metabolism: When measured at steady state over a 24-hour period, the areas under the propranolol plasma concentration-time curve (AUCs) for INDERAL-LA capsules are approximately 60 to 65% of the AUCs for a comparable divided daily dose of conventional tablets. The lower AUCs for INDERAL-LA capsules are due to more extensive hepatic metabolism of propranolol due to the slower absorption. Over a 24-hour period, blood levels are fairly constant for about 12 hours, then decline exponentially.
Special Populations and Conditions
The half-life of INDERAL-LA may be increased in patients with impaired renal or hepatic function (see 7 WARNINGS AND PRECAUTIONS).
11 STORAGE, STABILITY AND DISPOSAL
Store at 15o – 30oC.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: (±) Propranolol hydrochloride
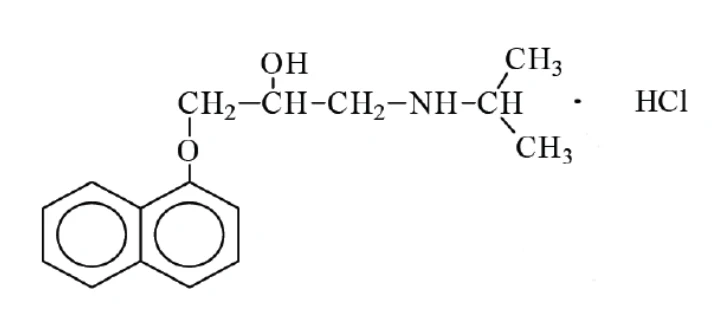
Chemical name: (±) 1-(isopropylamino)-3-(1-naphthyloxy)-2-propanol hydrochloride
Molecular formula: C16H21NO2.HCl
Molecular mass: 295.81
Structural formula:
Physicochemical properties: Propranolol hydrochloride is a stable, colourless, crystalline solid with a melting point of 163 -164oC. It is readily soluble in water and ethanol and insoluble in nonpolar solvents.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The information on the trial design and study demographics on which the original indication was authorized is not available.
14.2 Study Results
The data on which the original indication was authorized are not available.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity (LD50)
| Species | Dose mg/kg I.V. | Dose mg/kg Oral |
| Mice | 30-50 | 500-800 |
| Rats | 25-30 | 1000-1500 |
| Rabbits | 7.5-10.0 | Approx. 600 |
Subacute Toxicity
Four-week subacute toxicity studies were performed in rats (doses of 3.0 and 15 mg/kg intraperitoneally), on dogs (doses of 1.5 and 7.5 mg/kg intravenously) and three-month oral toxicity studies were conducted on rats, mice and dogs. No drug-induced histopathologic changes were observed in any of the animals.
Chronic Toxicity
Rats:
An 18-month toxicity study was conducted in 4 groups of rats (1 control and 3 experimental groups), each consisting of 25 males and 25 females. All animals received medication by tube directly into the stomach for the first 6 months and thereafter, in their diet.
A number of animals receiving the highest dose (150 mg/kg) developed bronchospasm soon after receiving the drug. A variety of pathologic lesions were observed in both the control and experimental groups. Dilatation of both ventricles was noted in a number of animals receiving the high-dose. Spontaneous myocarditis consisting of minor lymphocytic infiltration was observed in both groups. Testicular atrophy and reduction or absence of corpora lutea were observed in both the control and experimental groups.
Dogs:
A 1-year toxicity test was conducted in 32 dogs of both sexes. They were divided into 4 groups: controls and propranolol 60, 20 and 5 mg/kg). A patchy edema and a slight increase in the size of the lymphoid follicles of the mucosa in the fundus of the stomach were seen and were attributed to mild irritation caused by prolonged dosing with high doses of propranolol.
Carcinogenicity:
The carcinogenic potential of propranolol was investigated in mice and rats by chronic administration of the compound in the diet for 78 weeks at varying concentrations to provide dosage levels of 10, 50 and 150 mg/kg/day. Control groups of mice and rats were fed the same diet without the drug. After 78 weeks of dosing, the mice were kept alive for an additional 2 months and the rats for an additional 6 months.
At the termination of the experiment, gross and microscopic pathologic investigations revealed that in mice, the incidence of benign and malignant neoplasms was similar in the control and all treated groups. Therefore, no drug-related tumorigenic effect was observed at any dose level. Similarly, no tumorigenic effect was observed in the rat. The incidence of tumours was lower in the female rats treated with 150 mg/kg/day of propranolol than in any other group. This was attributed to the markedly decreased bodyweight gains in this group.
Reproductive and Developmental Toxicology:
The effects of propranolol on fertility, pregnancy, the developing fetus and newborns at the time of weaning were studied in rats using various dose levels, administered either by gastric intubation or in the feed. The drug was also fed to rabbits in their diet.
In some studies in rats, a non-dose related increase in resorption sites and neonatal deaths were observed. No teratogenic effects were noted in either species. Propranolol had no adverse effect on fertility, pregnancy, parturition or lactation.